


Product Monograph - Kisunla
1. Indications
KISUNLA is indicated for the treatment of adults with a clinical diagnosis of mild cognitive impairment or mild dementia due to Alzheimer's disease, who are apolipoprotein E ε4 (ApoE ε4) heterozygotes or non-carriers, and who have confirmed amyloid pathology.
Important instructions to ensure proper patient selection for treatment with KISUNLA are provided in sections 3. Serious Warnings and Precautions Box; 4.1. Dosing Considerations ; and 7. Warnings and Precautions.
A Canadian Patient Registration Program has been developed to support appropriate patient selection. Healthcare professionals should register all patients prior to or upon treatment initiation. This Registration program can be accessed at kisunlapatient.ca
Educational materials regarding monitoring and management of amyloid related imaging abnormalities (ARIA) have been developed for healthcare professionals who prescribe KISUNLA. They can be accessed at kisunlapatient.ca
1.1. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥65 years of age): Of the 3727 subjects exposed to KISUNLA in clinical trials, 2535 subjects were 65 years or older, including 1374 who were 75 years or older (see 10.3. Pharmacokinetics).
2. Contraindications
KISUNLA is contraindicated in patients with one or more of the following
- homozygous for the ApoE ε4 allele,
pre-treatment imaging findings of intracerebral hemorrhage or suggestive of cerebral amyloid angiopathy (CAA), including
- superficial siderosis,
- more than 4 microhemorrhages
- vasogenic edema
- severe white matter disease,
- uncontrolled bleeding disorders,
- taking anticoagulant medication,
- severe concomitant medical conditions that are not stable and adequately controlled,
- a contraindication to Magnetic Resonance Imaging (MRI) or without access to MRI for monitoring purposes, or
- known serious hypersensitivity to donanemab or to any ingredient in the formulation, including any non-medicinal ingredient. Reactions have included anaphylaxis. For a complete listing, see 6. Dosage Forms, Strengths, Composition, and Packaging.
3. Serious Warnings and Precautions Box
Amyloid Related Imaging Abnormalities (ARIA): KISUNLA increases the risk of ARIA with edema or effusions (ARIA-E) and ARIA with hemorrhages or hemosiderin deposits (ARIA-H). Enhanced clinical vigilance for ARIA is recommended, especially during the first 24 weeks of treatment with KISUNLA. ARIA occurs more frequently early in treatment and is usually asymptomatic, although serious and even fatal ARIA events have occurred in patients treated with KISUNLA (see 4. Dosage and Administration; 7. Warnings and Precautions).
ARIA can cause focal neurologic deficits that can mimic ischemic stroke symptoms. Treating healthcare professionals should conduct differential diagnosis before giving thrombolytic therapy in a patient being treated with KISUNLA. Fatal intracerebral hemorrhage has occurred in patients treated with KISUNLA in the setting of focal neurologic symptoms of ARIA and the use of a thrombolytic agent (see 7. Warnings and Precautions).
Apolipoprotein E ε4 (ApoE ε4) carriers (homozygotes greater than heterozygotes) have a higher frequency of ARIA-E and ARIA-H compared to non-carriers. KISUNLA is contraindicated in patients who are ApoE ε4 homozygotes (see 2. Contraindications, 7. Warnings and Precautions).
4. Dosage and Administration
4.1. Dosing Considerations
- KISUNLA should be initiated by a physician experienced in the diagnosis and treatment of Alzheimer's disease with timely access to Magnetic Resonance Imaging (MRI) (see Monitoring and Dosing Interruption or Discontinuation for Amyloid Related Imaging Abnormalities, below).
- Due to the potential for hypersensitivity or infusion-related reactions, the infusion of KISUNLA should be initiated and supervised by a healthcare professional. Administer KISUNLA under medical supervision in an appropriate clinical setting equipped with resuscitative equipment and rescue medications (see 4.4. Administration).
Patient Selection:
- The presence of amyloid beta (Aβ) pathology must be confirmed using approved methods such as amyloid Positron Emission Tomography (PET) scan or cerebrospinal fluid (CSF) analysis or equivalent validated methods prior to initiating treatment with KISUNLA.
- Testing for ApoE ε4 carrier status must be performed prior to initiation of treatment with KISUNLA to inform on treatment eligibility and the risk of developing ARIA (see 1. Indications; 3. Serious Warnings and Precautions Box; 8.2. Clinical Trial Adverse Reactions).
- KISUNLA should not be initiated in asymptomatic persons with findings suggesting only the presence of amyloid beta pathology or patients with moderate or severe Alzheimer's disease.
- Obtain baseline brain magnetic resonance imaging (MRI) within 6 months prior to initiating treatment to exclude patients with pre-existing conditions that would preclude the use of KISUNLA (see 2. Contraindications, 4.2. Recommended Dose and Dosage Adjustment).
4.2. Recommended Dose and Dosage Adjustment
KISUNLA must be diluted (see Table 4) and is administered as an intravenous infusion over approximately 30 minutes every four weeks (at least 21 days apart) with the recommended dosage and dosing schedule described in Table 1.
Table 1 – Recommended Dosage and Dosing Schedule
Intravenous Infusion (every 4 weeks) | KISUNLA Dosage (administered over approximately 30 minutes) |
|---|---|
| Infusion 1 (Week 0) | 350 mg |
| Infusion 2 (Week 4) | 700 mg |
| Infusion 3 (Week 8) | 1,050 mg |
| Infusion 4 (Week 12) and beyond, to a maximum of 18 months | 1,400 mg |
Treatment Discontinuation for Amyloid Clearance or Disease Progression
In KISUNLA Study 1 (TRAILBLAZER-ALZ 2) and Study 2 (TRAILBLAZER-ALZ 6), treatment was discontinued when an amyloid clearance threshold was achieved. (see 14.1. Clinical Trials by Indication). Discontinue treatment with KISUNLA once amyloid plaque clearance is achieved; there are no data on the safety or efficacy of continued KISUNLA dosing after amyloid clearance. In clinical trials, up to 60% of patients discontinued treatment prior to 18 months due to meeting amyloid clearance thresholds.
Treatment should be continued for up to 18 months, if monitoring of amyloid plaque clearance with a validated method is not possible. The maximum duration of KISUNLA treatment is 18 months.
If the patient progresses to moderate Alzheimer’s disease before the end of the 18 months maximum, treatment should be discontinued.
Monitoring and Dosing Interruption or Discontinuation for Amyloid Related Imaging Abnormalities
KISUNLA can cause amyloid-related imaging abnormalities -edema (ARIA-E) and -hemosiderin deposition (ARIA-H) (see 3. Serious Warnings and Precautions Box; 7. Warnings and Precautions, Amyloid-related imaging abnormalities (ARIA).
Monitoring for ARIA
Obtain baseline brain magnetic resonance imaging (MRI) within 6 months prior to initiating treatment.
Perform an MRI prior to the second dose (Week 4), prior to the fourth dose (Week 12), prior to the seventh dose (Week 24), and when clinically indicated due to suspected ARIA. An additional MRI at Week 52 (prior to the fourteenth dose) in patients with ARIA risk factors such as ApoE ε4 heterozygotes, and/or patients with previous ARIA events earlier in treatment, should be performed, and when clinically indicated due to suspected ARIA.
Most serious ARIA events occurred within 12 weeks of initiation of treatment and an additional MRI prior to the third dose (Week 8) may aid in earlier detection of ARIA (see 7. Warnings and Precautions, Amyloid-related imaging abnormalities (ARIA).
Radiographic Findings
The radiographic severity of ARIA associated with KISUNLA was classified by the criteria shown in Table 2.
Table 2 – ARIA MRI Classification Criteria
| ARIA Type | Radiographic Severity | |||||
|---|---|---|---|---|---|---|
| Mild | Moderate | Severe | ||||
| ARIA-E | FLAIR hyperintensity confined to sulcus and/or cortex/subcortex white matter in one location <5 cm. | FLAIR hyperintensity 5 to 10 cm in single greatest dimension, or more than 1 site of involvement, each measuring <10 cm. | FLAIR hyperintensity >10 cm with associated gyral swelling and sulcal effacement. One or more separate/independent sites of involvement may be noted. | |||
| ARIA-H microhemorrhage | ≤4 new incident microhemorrhages | 5-9 new incident microhemorrhages | ≥10 new incident microhemorrhages | |||
| ARIA-H superficial siderosis | 1 new or increased focal area of superficial siderosis | 2 new or increased focal areas of superficial siderosis | >2 new or increased focal areas of superficial siderosis | |||
Recommendations for Dosing Interruptions or Discontinuations in Patients with ARIA
The recommendations for dosing interruptions for patients with ARIA-E or ARIA-H are provided in Table 3.
Table 3 – Dosing Recommendations for Patients with ARIA-E or ARIA-H
| Clinical Symptom | ARIA-E or ARIA-H Severity on MRIa | |||||||
|---|---|---|---|---|---|---|---|---|
| Mild | Moderate | Severe | ||||||
| Asymptomatic | Consider suspending dosing | Suspend dosingb | Discontinue dosing | |||||
| Symptomaticc | Suspend dosingb | Discontinue dosing | ||||||
a See Table 2 for ARIA MRI radiographic severity classification criteria
b Suspend until MRI demonstrates radiographic resolution (ARIA-E) or stabilisation (ARIA-H) and symptoms, if present, resolve; consider a follow-up MRI to assess for resolution (ARIA-E) or stabilisation (ARIA-H) 2 to 4 months after initial identification. Resumption of dosing or permanent discontinuation after ARIA-E resolution and ARIA-H stabilization should be guided by clinical judgment including re-evaluation of risk factors. Supportive treatment, including corticosteroids may be considered in case of ARIA-E.
c Reported symptoms associated with ARIA include headache, confusion, nausea, vomiting, unsteadiness, dizziness, tremor, visual changes, speech disturbances, worsening cognitive function, alteration of consciousness and seizures.
Use clinical judgement in considering whether to resume dosing in patients with recurrent ARIAs. In the event of radiographically or symptomatic severe ARIA treatment with KISUNLA should be permanently discontinued. KISUNLA should also be permanently discontinued after clinically serious ARIA-E, serious ARIA-H, or intracerebral hemorrhage >1 cm (see 7. Warnings and Precautions).
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use (see 1.1. Pediatrics).
4.3. Reconstitution
Preparation and Administration of KISUNLA for Intravenous Infusion
- KISUNLA solution for intravenous infusion must be diluted, prepared and infused by a healthcare professional.
Dilution of KISUNLA to Prepare Solution for Infusion
- Prior to administration, KISUNLA must be diluted with 0.9% Sodium Chloride Injection, USP (see Table 4).
- Use aseptic technique when preparing the KISUNLA diluted solution for intravenous infusion.
- Allow KISUNLA to equilibrate to room temperature before preparation.
- Gently invert the KISUNLA diluted solution to mix completely. Do not shake. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. KISUNLA solution is clear to opalescent, colorless to slightly yellow to slightly brown. Do not use if particulate matter or discolorations are present.
- Withdraw required volume of KISUNLA and mix with 0.9% Sodium Chloride Injection, to the recommended total volume for a final concentration of 4 mg/mL to 10 mg/mL (see Table 4). Use only 0.9% Sodium Chloride Injection for dilution.
- Each vial is for one time use only. Discard any unused portion left in the vial.
Table 4 – Preparation of KISUNLA
| KISUNLA Dose (mg) | KISUNLA Volume (mL) | Volume of 0.9% Sodium Chloride Injection Diluent (mL) | Final Volume of Diluted Solution to be Infused (mL) | Final Concentration of Diluted Solution (mg / mL)a |
| 350 mg | 20 mL | 15 mL to 67.5 mL | 35 mL to 87.5 mL | 350 mg/87.5 mL (4 mg/mL) to 350 mg/35 mL (10 mg/mL) |
| 700 mg | 40 mLb | 30 mL to 135 mL | 70 mL to 175 mL | 700 mg/175 mL (4 mg/mL) to 700 mg/70 mL (10 mg/mL) |
| 1,050 mg | 60 mLc | 45 mL to 202.5 mL | 105 mL to 262.5 mL | 1,050 mg/262.5 mL (4 mg/mL) to 1,050 mg/105 mL (10 mg/mL) |
| 1,400 mg | 80 mLd | 60 mL to 270 mL | 140 mL to 350 mL | 1,400 mg/350 mL (4 mg/mL) to 1,400 mg/140 mL (10 mg/mL) |
a final concentration of 4 mg/mL to 10 mg/mL
b 2 vials of KISUNLA
c 3 vials of KISUNLA
d 4 vials of KISUNLA
4.4. Administration
Administration of KISUNLA for Infusion
- Administer KISUNLA under medical supervision in an appropriate clinical setting equipped with resuscitative equipment and rescue medications (see 7. Warnings and Precautions). In the case of infusion-related reaction, infusion rate may be reduced or the infusion may be discontinued, and appropriate therapy administered as clinically indicated. Slowing the infusion or prophylactic treatment with antihistamines, or corticosteroids prior to future infusions may be considered if treatment with KISUNLA is continued. Promptly discontinue the infusion upon the first observation of any signs or symptoms consistent with a hypersensitivity-type reaction (see 7. Warnings and Precautions).
- KISUNLA must not be infused with any other medicinal products.
- Administer the entire diluted solution intravenously over approximately 30 minutes. KISUNLA must not be administered as an IV push or bolus injection.
- Flush the line only with 0.9% Sodium Chloride Injection at the end of the infusion per access specific line maintenance protocol.
- Observe the patient post-infusion for a minimum of 30 minutes to evaluate for infusion reactions and hypersensitivity reactions (see 7. Warnings and Precautions).
4.5. Missed Dose
If an infusion is missed, the missed dose should be administered at the next possible occasion. Then, resume the recommended dosing regimen every 4 weeks from the date of administration of the missed dose.
5. Overdose
Single doses up to 40 mg/kg (approximately 2800 mg in a 70 kg person) have been administered. ARIA-E occurred in two out of four patients administered this dose. In case of an overdose, it is recommended that the patient be monitored for signs or symptoms of adverse reactions and appropriate symptomatic treatment be instituted immediately.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, healthcare professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 5 – Dosage Forms, Strengths, Composition and Packaging
KISUNLA for Intravenous Infusion
KISUNLA solution for intravenous infusion after dilution is available as 20 mL solution in a type I glass vial. KISUNLA is preservative-free; therefore, each vial is for single use only.
The stopper is not made with dry natural rubber latex.
KISUNLA 350 mg/20 mL is available in cartons containing 1 vial.
7. Warnings and Precautions
General
Consider the benefit of KISUNLA for the treatment of Alzheimer's disease and potential risk of serious adverse events associated with ARIA when deciding to initiate treatment with KISUNLA (see 3. Serious Warnings and Precautions Box, 8.2. Clinical Trial Adverse Reactions).
The safety and efficacy of continuing treatment in patients that progress to moderate Alzheimer’s disease have not been established. Treatment with KISUNLA should be discontinued before the end of the 18 month maximum treatment period if patients progress to moderate AD.
The safety and efficacy of KISUNLA have not been established in preclinical Alzheimer's disease, patients with more advanced stages of Alzheimer's disease, atypical Alzheimer's disease syndromes (without memory-predominant Alzheimer's disease), autosomal dominant Alzheimer's disease, adults with Down syndrome, and non-Alzheimer neurodegenerative dementia.
| Route of Administration | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
| Intravenous infusion | Solution for intravenous infusion after dilution 17.5 mg/mL 350 mg/20 mL | anhydrous citric acid, polysorbate 80, sodium citrate, sucrose, and water for injection |
Patient Counselling:
- A Canadian Patient Registration Program has been developed to support appropriate patient selection. Healthcare professionals should register all patients prior to or at the time of treatment initiation. This Registration program can be accessed here. kisunlapatient.ca
- Prescribers should be familiar with the educational material prepared for the detection and management of ARIA. Educational materials have been developed for healthcare professionals who prescribe KISUNLA regarding management of amyloid related imaging abnormalities (ARIA) which can be accessed at: kisunlapatient.ca
- As noted in Patient Selection section in 4.1 Dosing Considerations, patients must undergo genetic testing for the ApoE ε4 allele to determine eligibility for KISUNLA. Prior to testing, the healthcare professional should discuss with their patient the implications of genetic testing results.
- Prior to initiating treatment with KISUNLA, patients and their families/caregivers should be fully informed of the risks of treatment with KISUNLA, including the incidence of ARIA, the risk of ARIA and examinations needed for risk management, and actions to be taken in the event of ARIA. Instruct the patient and their family/caregiver to seek medical attention immediately if any abnormality is noted. Ensure the patient and caregiver are aware of how to access important educational materials at: kisunlapatient.ca. The patient should be instructed to carry their Patient Alert Card at all times, and inform any treating healthcare professional of their use of KISUNLA.
Driving and Operating Machinery
Events of dizziness and confusion have been reported in patients treated with KISUNLA. While taking KISUNLA, patients should be cautioned not to drive, operate dangerous machinery or engage in activities that require alertness or physical coordination if they are experiencing any of these events.
Immune
In clinical studies, 88.1% of KISUNLA treated patients developed anti-drug antibodies (ADA) and all of the patients with ADA had neutralising antibodies (see 10.4. Immunogenicity). All patients reporting infusion-related reactions had ADA. Higher ADA titer was associated with increased incidence of infusion-related reactions/immediate hypersensitivity events.
Monitoring and Laboratory Tests
See Monitoring and Dosing Interruption or Discontinuation for Amyloid Related Imaging Abnormalities.
Neurologic
Amyloid-related imaging abnormalities (ARIA)
ARIA events, including serious and fatal events, were observed in KISUNLA clinical trials. Monoclonal antibodies directed against aggregated forms of beta amyloid, including KISUNLA, can cause ARIA, characterized as ARIA with edema (ARIA-E), which can be observed on MRI as brain edema or sulcal effusions, and ARIA with hemosiderin deposition (ARIA-H), which includes microhemorrhage and superficial siderosis. ARIA-H can occur spontaneously in patients with Alzheimer’s disease. ARIA-H generally occurs in association with an occurrence of ARIA-E. ARIA-H of any cause and ARIA-E can occur together or in isolation. ARIA is usually asymptomatic, although serious and life-threatening events, including seizure and status epilepticus, can occur. When present, reported symptoms associated with ARIA include headache, confusion, nausea, vomiting, unsteadiness, dizziness, tremor, visual changes, speech disturbances, worsening cognitive function, and alteration of consciousness. Focal neurologic deficits may also occur. Symptoms associated with ARIA usually resolve over time but may persist even after ARIA resolution on imaging (see 8.2. Clinical Trial Adverse Reactions).
In the event of radiographically or symptomatic severe ARIA, treatment with KISUNLA should be permanently discontinued. KISUNLA should also be permanently discontinued after clinically serious ARIA-E, serious ARIA-H, or intracerebral hemorrhage >1 cm.
KISUNLA is contraindicated in patients with pre-treatment MRI showing ARIA-E, more than 4 microhemorrhages, superficial siderosis, severe white matter disease or intracerebral hemorrhage greater than 1 cm (see 2. Contraindications).
ApoE ε4 Carrier Status and Risk Factors for ARIA
Testing for ApoE ε4 status must be conducted prior to initiating treatment with KISUNLA. Approximately 15% of Alzheimer’s disease patients are ApoE ε4 homozygotes. Patients who were homozygotes and were treated with KISUNLA in clinical trials had a higher incidence of ARIA, including symptomatic, serious, severe radiographic, and recurrent ARIA, compared to heterozygotes and noncarriers. KISUNLA is contraindicated in patients who are ApoE ε4 homozygotes (see 2. Contraindications). ARIA risk is also elevated in ApoE ε4 heterozygotes; patients should be informed of this elevated risk (see 8.2. Clinical Trial Adverse Reactions).
Concomitant Antithrombotic Medication
Baseline use of antithrombotic medicinal products (aspirin, other antiplatelets, or anticoagulants) was allowed in clinical trials with donanemab. Patients who received KISUNLA and an antithrombotic medication (aspirin, other antiplatelets, or anticoagulants) in clinical trials did not have an increased frequency of ARIA-H or intracerebral hemorrhage. However, the majority of exposures to antithrombotic medications were to aspirin (81%). The number of events and the limited exposure to non-aspirin antithrombotic medications limit definitive conclusions about the risk of ARIA or intracerebral hemorrhage in patients taking antithrombotic medications.
Because ARIA-H and intracerebral hemorrhages greater than 1 cm in diameter have been observed in patients taking KISUNLA, additional caution should be exercised when considering the administration of antithrombotics or a thrombolytic agent (e.g., tissue plasminogen activator) to a patient already being treated with KISUNLA.
Fatal intracerebral hemorrhages have occurred in patients treated with KISUNLA in the setting of focal neurologic symptoms of ARIA and the use of a thrombolytic agent. Because ARIA-E can cause focal neurologic deficits that can mimic an ischemic stroke, treating clinicians should consider whether such symptoms could be due to ARIA-E before giving thrombolytic therapy to a patient being treated with KISUNLA (see 3. Serious Warnings and Precautions Box). Use of thrombolytic agents should be avoided except for immediately life-threatening indications with no alternative management (e.g., pulmonary embolism with haemodynamic compromise) when the benefits could outweigh the risks.
KISUNLA is contraindicated in patients taking anticoagulants (see 2. Contraindications).
There is limited experience with the use of KISUNLA with dual antiplatelet therapy.
Other Risk Factors for ARIA and intracerebral hemorrhage
A higher frequency of ARIA has been observed in patients with pre-treatment cerebral microhemorrhage and/or superficial siderosis. KISUNLA treatment is contraindicated in patients with baseline superficial siderosis and patients with > 4 microhemorrhages at baseline (see 2. Contraindications).
The presence of an ApoE ε4 allele is associated with CAA, which has an increased risk for intracerebral hemorrhage. KISUNLA is contraindicated in patients homozygous for the ApoE ε4 allele (see 2. Contraindications).
Monitoring and Dose Management Guidelines
Recommendations for dosing in patients with ARIA depend on clinical symptoms and radiographic severity (see Table 2 and Table 3 in section 4.1).
Baseline brain MRI and periodic monitoring with MRI are recommended (4.1 Monitoring and Dosing Interruption for Amyloid Related Imaging Abnormalities).
Enhanced clinical vigilance for ARIA is recommended during the first 24 weeks of treatment with KISUNLA (see 4.2. Recommended Dose and Dosage Adjustment for instructions on ARIA monitoring). However, ARIA events can occur at any time and monitoring should continue throughout treatment. If a patient experiences symptoms suggestive of ARIA, clinical evaluation should be performed, including additional MRI testing.
If ARIA is observed on MRI, careful clinical evaluation should be performed prior to continuing treatment. If required, administer supportive therapy, which may include corticosteroids.
There is limited experience in patients who continued dosing through ARIA-E. There are limited data for continued dosing patients who experienced recurrent episodes of ARIA-E. Use clinical judgment in considering whether to continue dosing in patients with recurrent ARIA.
Sensitivity/Resistance
Hypersensitivity Reactions
KISUNLA can cause infusion reactions and hypersensitivity reactions, some of which may be serious and life threatening. The majority of infusion reactions and hypersensitivity reactions have occurred within the first 4 doses of KISUNLA, although they can occur at any time. Infusion reactions typically occur during infusion or within 30 minutes post-infusion. In some patients, infusion reactions and hypersensitivity reactions were reported more than 24 hours after the KISUNLA infusion (see 8.2. Clinical Trial Adverse Reactions).
Signs and symptoms of infusion-related reactions may include erythema, chills, nausea, vomiting, sweating, headache, chest tightness, dyspnea and changes in blood pressure.
Promptly discontinue the infusion upon the first observation of any signs or symptoms consistent with a serious hypersensitivity reaction and initiate appropriate therapy. Slowing the infusion or prophylactic treatment with antihistamines, or corticosteroids prior to future infusions may be considered if treatment with KISUNLA is continued (see 4.4. Administration, 8.2. Clinical Trial Adverse Reactions).
Reproductive Health
- Fertility
There are no data on the effect of KISUNLA on human fertility. No animal studies have been performed to test KISUNLA for potential fertility impairment.
7.1. Special Populations
7.1.1. Pregnancy
There are no data on KISUNLA use in pregnant women. No animal studies have been conducted to assess the potential reproductive or developmental toxicity of KISUNLA. Use of KISUNLA is not recommended during pregnancy.
Pregnancy status of females of child-bearing potential should be verified prior to initiating treatment with KISUNLA. Women of childbearing potential should use effective contraception during treatment and for 3 months after the last dose of KISUNLA.
Human IgG is known to cross the placenta. Therefore, donanemab has the potential to be transmitted from the mother to the developing fetus. The effects of KISUNLA on the developing fetus are unknown.
7.1.2. Breastfeeding
It is unknown if donanemab is excreted in human milk. Human IgG is known to be excreted in breast milk. A risk to the newborn/infant cannot be excluded. A decision must be made whether to discontinue breastfeeding or to discontinue KISUNLA therapy taking into account the benefit of breastfeeding for the child and the benefit of therapy for the woman.
There are no data on the presence of donanemab in human milk, the effects of the drug on the breastfed infant, or its effects on milk production. Lactation studies have not been conducted in animals.
7.1.3. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
No dose adjustment is necessary in patients ≥ 65 years (see 10.3. Pharmacokinetics).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Amyloid Related Imaging Abnormalities (see 7. Warnings and Precautions, Amyloid-related imaging abnormalities (ARIA)
- Infusion-Related Reactions and Anaphylaxis (see 7. Warnings and Precautions, Hypersensitivity Reactions)
The safety of KISUNLA has been evaluated in 3727 patients with Alzheimer’s disease who received at least one dose of KISUNLA intravenously. In the combined placebo-controlled and open-label studies, 1912 patients received KISUNLA once monthly for at least 6 months, 1057 patients for at least 12 months, and 432 patients for at least 18 months, with Dosing Regimen 1. For the recommended dosing regimen (Dosing Regimen 2), 212 patients were exposed to KISUNLA up to 18 months. For the indicated population excluding ApoE ε4 homozygotes, 710 patients were exposed to Dosing Regimen 1 in Study 1 and 191 were exposed to Dosing Regimen 2 in Study 2. For description of Regimen 1 and Regimen 2, please see 8.2. Clinical Trial Adverse Reactions.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Study 1 and Study 2 Overviews
In Study 1 (TRAILBLAZER-ALZ 2), safety was assessed in patients who received KISUNLA Dosing Regimen 1* (n = 853) compared to those who received placebo (n = 874). Of these, 710 participants who received KISUNLA concerned the indicated population (ApoE ε4 heterozygotes and non-carriers). The mean duration of exposure to KISUNLA in Study 1 was 12 months including all populations.
In Study 2 (TRAILBLAZER-ALZ 6), the effect of different dosing regimens of KISUNLA on ARIA was assessed, including in patients who received KISUNLA Dosing Regimen 2** (n=212), which is the recommended dosage and described below. Of these, 191 participants who received KISUNLA Dosing Regimen 2 concerned the indicated population (ApoE ε4 heterozygotes and non-carriers). The mean duration of exposure to KISUNLA in Study 2 was 11 months including all populations.
* Dosing Regimen 1 consisted of 3 Q4W infusions of 700 mg KISUNLA followed by Q4W dosing of 1400 mg thereafter.
** Dosing Regimen 2 is the recommended regimen with doses of 350 mg, 700 mg, and 1050 mg for the first 3 months, followed by 1400 mg Q4W thereafter.
Study 1
In the indicated population, there were 26.5% of KISUNLA-treated patients and 21.1% of patients receiving placebo that discontinued from the trial. There were 13% of patients treated with KISUNLA compared to 4% of patients on placebo that discontinued study treatment because of an adverse event. The most common adverse reaction leading to discontinuation of KISUNLA was infusion-related reaction (4% of patients treated with KISUNLA compared to no patients on placebo).
Serious adverse events occurred in 17.9% of KISUNLA and 15.2% of placebo patients. The most relevant serious adverse reactions were: Serious ARIA-E (1.3%), serious ARIA-H (0.3%), and serious hypersensitivity, including infusion-related reactions (0.4%). Anaphylaxis was reported in 0.4% of patients (see 4.4. Administration). There were 1.8% of KISUNLA and 1.1% of placebo patients that died, including 3 KISUNLA patients with fatal outcomes following ARIA during the placebo-controlled period.
Study 2
In the indicated population, there were 19.3% of Kisunla treated patients in Dosing Regimen 1 and 19.4% in Dosing Regimen 2 that discontinued the trial. There were 7.5% of patients treated with KISUNLA in Dosing Regimen 1 compared to 6.8% of patients in Dosing Regimen 2 that discontinued study treatment because of an adverse reaction. The most common adverse reaction leading to discontinuation of KISUNLA was Infusion-related reaction (1.6% in Dosing Regimen 1 and 2.6% in Dosing Regimen 2).
Serious adverse events occurred in 24.7% of KISUNLA treated with Dosing Regimen 1 and 24.6% of patients treated with Dosing Regimen 2. The most relevant serious adverse reactions were serious ARIA-E (0 in Dosing Regimen 1 and 0.5% in Dosing Regimen 2) and serious hypersensitivity, including infusion-related reactions (1.1% in Dosing Regimen 1 and 2.1% in Dosing Regimen 2).
Anaphylaxis was reported in 1.1% of patients treated with Dosing Regimen 1 and 0.5% of patients treated with Dosing Regimen 2 (see 4.4. Administration). There were 0.5% of KISUNLA patients treated with Dosing Regimen 1 and 0.5% of those treated with Dosing Regimen 2 that died; the Dosing Regimen 2 patient died subsequent to macrohemorrhage.
Table 6 shows adverse events in Study 1 and Study 2 that were reported in at least 5% of patients treated with KISUNLA in Study 1 and at least 1% more frequently than in patients on placebo in Study 1.
Table 6: – Treatment Emergent Adverse Events in Study 1 and Study 2 Reported in at Least 5% of Indicated Patients Treated With KISUNLA in Study 1 and at Least 1% Higher Than Placebo in the Placebo-Controlled Trial (Study 1)
| Study 1 | Study 2 | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Placebo (n=728) | Dosing Regimen 1 (n=710) | Dosing Regimen 1 (n=186) | Dosing Regimen 2 (n=191) | |||||||
| ARIA-E a | 1.6% | 20.6% | 20.4% | 14.7% | ||||||
| ARIA-H a | 6.9% | 17.0% | 18.3% | 17.8% | ||||||
| Fall | 12.5% | 14.9% | 13.4% | 20.4% | ||||||
| Headache | 10.0% | 14.6% | 24.7% | 20.4% | ||||||
| IRR | 0.4% | 8.3% | 15.1% | 18.8% | ||||||
| Arthralgia | 5.5% | 6.5% | 6.5% | 8.4% | ||||||
| Superficial siderosis a | 0.8% | 5.6% | 7.5% | 4.7% | ||||||
a Includes events reported as TEAEs only
Amyloid-Related Imaging Abnormalities (ARIA) by MRI/TEAE:
Table 7: ARIA characteristics in the indicated population in Study 1 and Study 2:
| Study 1 | Study 2 | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo (n=728) | KISUNLA Dosing Regimen 1* (n=710) | KISUNLA Dosing regimen 1* (n=186) | KISUNLA Dosing Regimen 2* (n=191) | ||||||||||||
| Any ARIA | 13.5% | 33.0% | 31.2% | 28.8% | |||||||||||
| Any fatal ARIA | 0 | 0.4% | 0% | 0% | |||||||||||
| Any ARIA SAE | 0 | 1.4% | 0 | 0.5% | |||||||||||
| Any symptomatic ARIA | 0.3% | 6.1% | 5.4% | 3.7% | |||||||||||
| ARIA-E | 1.8% | 20.6% | 20.4% | 14.7% | |||||||||||
| ARIA-E SAE | 0 | 1.3% | 0 | 0.5% | |||||||||||
| Isolated ARIA-Ea | 1.1% | 5.1% | 5.9% | 3.1% | |||||||||||
| Symptomatic ARIA-E | 0 | 5.6% | 4.8% | 3.1% | |||||||||||
| ARIA-H | 12.2% | 27.6% | 25.3% | 25.1% | |||||||||||
| ARIA-H SAE | 0 | 0.3% | 0 | 0 | |||||||||||
| Isolated ARIA-Ha | 11.1% | 12.3% | 9.7% | 14.1% | |||||||||||
| Symptomatic ARIA-H | 0.3% | 1.1% | 0.5% | 0.5% | |||||||||||
| ARIA-H microhemorrhagea | 10.6% | 22.7% | 19.4% | 22.5% | |||||||||||
| ARIA-H superficial siderosisa | 2.1% | 13.2% | 12.9% | 8.4% | |||||||||||
| Intracerebral hemorrhage (ICH) >1 cm | 0.3% | 0.4% | 0.5% | 1.0% | |||||||||||
a By MRI
* Study 1 used Dosing Regimen 1, which delivers the same amount of total KISUNLA as Dosing Regimen 2 but with a different schedule. Dosing Regimen 1 is not recommended for use.
Study 1:
Of 12 (1.6%) placebo and 144 (20.3%) Kisunla Dosing Regimen 1 patients with ARIA-E events in Study 1, 66.7% of placebo and 92.7% of Kisunla patients had ARIA-E resolution, with all placebo and 89.6% of Kisunla patients having resolution within 20 weeks of detection by central MRI.
In Study 1, the median time to resolution of ARIA-E was approximately 8.3 weeks. Radiographic resolution was not always associated with resolution of symptoms in patients that were symptomatic.
Of the KISUNLA-treated patients with ARIA-E, 24.3% (35/144) experienced multiple episodes of ARIA-E. Subsequent events were increased in severity for 28.6% (10/35).
Of the KISUNLA-treated patients with ARIA-H, 35.9% (70/195) of participants experienced multiple episodes of ARIA-H.
Study 2:
Study 2 compared KISUNLA Dosing Regimen 1 and KISUNLA Dosing Regimen 2. Dosing Regimen 2, the recommended regimen, showed a lower incidence of ARIA-E, symptomatic ARIA-E, and superficial siderosis compared to Dosing Regimen 1. However, there was no meaningful difference between dosing regimens for ARIA-H, ARIA SAEs, ARIA-H microhemorrhages, or macrohemorrhage.
Of 28 (14.7%) Kisunla Dosing Regimen 2 patients with ARIA-E events in Study 2, 92.9% had resolution of ARIA-E, with 89.3% having resolution within 20 weeks of detection by central MRI.
In Study 2 Dosing Regimen 2, the median time to resolution of ARIA-E was approximately 8.4 weeks. Radiographic resolution was not always associated with resolution of symptoms in patients that were symptomatic.
Of the KISUNLA Dosing Regimen 2 patients with ARIA-E, 14.3% (4/28) experienced multiple episodes of ARIA-E.
Of the KISUNLA Dosing Regimen 2 patients with ARIA-H, 27.1% (13/48) experienced multiple episodes of ARIA-H.
ApoE ε4 Carrier Status and Risk Factors for ARIA
Study 1:
Patients in Study 1 who were ApoE ε4 heterozygotes had a higher incidence of ARIA (37.6%) than noncarriers (24.7%). KISUNLA is contraindicated in patients who are homozygous for the ApoE ε4 allele (see 2. Contraindications).
There were more ARIA-E events in ApoE ε4 heterozygotes (23.2%) than non-carriers (15.7%) among KISUNLA-treated patients in Study 1.
There were more ARIA-H events in ApoE ε4 heterozygotes (32.5%) than non-carriers (18.8%) among KISUNLA-treated patients. Based on MRI, there were more ApoE ε4 heterozygotes with ARIA-H microhemorrhages (26.8%) and/or superficial siderosis (16.6%) than non-carriers (15.3% and 7.5%, respectively) among KISUNLA-treated patients in Study 1.
Study 2:
Patients in Study 2 treated with Dosing Regimen 2, who were ApoE ε4 heterozygotes had a higher incidence of ARIA (31.3%) than noncarriers (25.3%). KISUNLA is contraindicated in patients who are homozygous for the ApoE ε4 allele (see 2. Contraindications).
There were more ARIA-E events in ApoE ε4 heterozygotes (15.7%) than non-carriers (13.3%) among patients in Study 2 treated with Dosing Regimen 2.
There were more ARIA-H events in ApoE ε4 heterozygotes (28.7%) than non-carriers (20.0%) among patients in Study 2 treated with Dosing Regimen 2. Based on MRI, there were more ApoE ε4 heterozygotes with ARIA-H microhemorrhages (25.2%) and/or superficial siderosis (9.6%) than non-carriers (18.7% and 6.7%, respectively) among KISUNLA dosing Regimen 2-treated patients in Study 2.
Radiographic Findings
See Table 2, 4.1. Dosing Considerations , for severity rating scale used in clinical trials.
In Study 1, the maximum radiographic severity for ARIA-E in the KISUNLA (Dosing Regimen 1) arm for the 144 ApoE ε4 heterozygote and non-carrier patients was mild in 30.6% (44/144) of patients, moderate in 62.5% (90/144) of patients, and severe in 6.9% (10/144) of patients. The maximum radiographic severity of ARIA-H in the 195 heterozygote and non-carrier patients treated with KISUNLA in Study 1 who had ARIA-H events was mild in 52.3% (102/195) of patients, moderate in 20.0% (39/195) of patients, and severe in 27.7% (54/195) of patients.
In Study 2, the maximum radiographic severity of ARIA-E in the 28 heterozygote and non-carrier patients treated with Dosing Regimen 2 who had ARIA-E events was mild in 39.3% (11/28), moderate in 60.7% (17/28) and severe in 0% (0/28). In study 2, the maximum radiographic severity of ARIA-H in the Dosing Regimen 2 arm for the 48 ApoE ε4 heterozygote and non-carrier patients who had ARIA-H events was mild in 72.9% (35/48) of patients, moderate in 12.5% (6/48) patients and severe in 14.6% (7/48) patients.
Infusion-Related Reactions:
In Study 1, in the indicated population, infusion reactions were observed in 8.3% of patients treated with KISUNLA using Dosing Regimen 1 compared to 0.4% on placebo. Anaphylactic reaction was reported in 0.4% of KISUNLA-treated patients. Serious infusion reactions or hypersensitivity occurred in 0.4% of patients treated with KISUNLA compared to 0.1% on placebo.
In Study 2, in the indicated population treated with the recommended dosing regimen (Dosing Regimen 2), infusion-related reactions were reported as a treatment emergent adverse event in 18.8% (36/191). Anaphylactic reaction was reported in 0.5%, and serious infusion reactions or hypersensitivity occurred in 2.1% of patients treated with KISUNLA with Dosing Regimen 2.
Most infusion-related reactions associated with KISUNLA occurred during the infusion or within 30 minutes after completion of the infusion, however some have occurred hours after an infusion. Signs and symptoms of infusion-related reactions include chills, erythema, nausea/vomiting, flushing, difficulty breathing/dyspnea, sweating, elevated blood pressure, headache, chest pain, and low blood pressure.
Rechallenge led to subsequent IRR/hypersensitivity events in 46.9% of patients, with severity and type of symptoms usually similar to that of the patient’s previous IRR/hypersensitivity events. Prophylactic medicines prior to subsequent infusions did not prevent IRR recurrence.
8.3. Less Common Clinical Trial Adverse Reactions
The following adverse reactions occurred in less than 5% of patients treated with KISUNLA and more frequently than in patients receiving placebo:
Gastrointestinal Disorders: vomiting, nausea
Injury, poisoning and procedural complications: anaphylaxis
9. Drug Interactions
No formal drug interaction studies have been performed with KISUNLA. No pharmacokinetic drug interactions are expected based on the characteristics of KISUNLA.
KISUNLA is contraindicated in patients taking anticoagulant medications (see 2. Contraindications).
Use caution in administering thrombolytics in patients taking KISUNLA (see 3. Serious Warnings and Precautions Box; 7. Warnings and Precautions).
9.4. Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Donanemab is a humanized immunoglobulin gamma 1 (IgG1) monoclonal antibody directed against insoluble N-truncated pyroglutamate amyloid beta, which is a component (0.6%) of dense, established amyloid beta plaque that are found in Alzheimer’s Disease. Donanemab reduces amyloid beta plaques, as evaluated in TRAILBLAZER-ALZ 2 (see Study 1 10.2. Pharmacodynamics).
10.2. Pharmacodynamics
Effect of donanemab on Amyloid Beta Pathology
The effect of donanemab on amyloid beta plaque levels in the brain in the combined population was evaluated using amyloid PET imaging (18F-florbetapir tracer). The PET signal was quantified using the Standard Uptake Value Ratio (SUVR) method to estimate brain levels of amyloid beta plaque in composites of brain areas expected to be widely affected by Alzheimer’s disease pathology (precuneus, frontal, anterior cingulate, posterior cingulate, parietal and temporal cortices), compared to a brain region expected to be spared of such pathology (cerebellum). Amyloid PET was also expressed on the Centiloid scale.
In Study 1, donanemab reduced amyloid beta plaque levels in the brain, starting at Week 24 and continuing through Week 76 (p<0.0001), compared to placebo (see Table 8).
In Study 2 (TRAILBLAZER-ALZ 6), donanemab reduced amyloid beta plaque levels in the brain, starting at Week 24 and continuing through Week 76 (p<0.0001). Amyloid clearance in the alternative dosing groups did not significantly differ from the standard dosing group.
Using data from patients who completed active treatment based on amyloid imaging, modeled amyloid levels began to increase with a mean rate of 2.8 Centiloids/year.
Effect of donanemab on Tau Pathophysiology
A reduction in plasma P-tau217 was observed with KISUNLA compared to placebo in Study 1 (see Table 8).
Table 8 – Biomarker Results of Donanemab in Study 1
| Biomarker Endpoint at Week 76 | Donanemab | Placebo |
|---|---|---|
| Amyloid Beta PET SUVR | N = 712 | N = 754 |
| Mean baseline | 1.53 | 1.52 |
Change from baseline (%) Difference from placebo | -0.47 (-30.9%) -0.47, p<0.0001 | -0.00 |
| Amyloid Beta PET Centiloid | N = 765 | N = 812 |
| Mean baseline | 104.0 | 101.8 |
Change from baseline (%) Difference from placebo | -87.0 (-83.7%) -86.4, p<0.0001 | -0.7 |
| Plasma P-tau217 (log10 transformed) | N = 758 | N = 786 |
| Mean baseline | 0.67 | 0.66 |
Change from baseline (% of original value) Difference from placebo | -0.19 (-35.0%) -0.22, p<0.0001 | 0.03 |
Exposure-Response Relationships
Model based exposure-response analyses for Study 1 demonstrated that exposures to donanemab were associated with a reduction in clinical decline on iADRS and CDR-SB.
10.3. Pharmacokinetics
The pharmacokinetics (PK) of donanemab were characterized using a population PK analysis with concentration data collected from 2131 patients with Alzheimer’s disease who received donanemab in single or multiple doses. Accumulation of <1.3-fold occured with every-4-week dosing; steady-state exposures were achieved after a single dose. In single doses from 10 to 40 mg/kg (~2 times the approved recommended dosage of 1400 mg for 70 kg of body weight), and multiple 10 and 20 mg/kg doses, exposures (Cmax and AUC) increased proportionally.
Similar steady-state exposures, specifically for Cmax,ss, Ctrough,ss, and Cav,ss, were achieved between Dosing Regimens 1 and 2 (see 14. Clinical Trials).
Table 9 – Summary of Donanemab Population Pharmacokinetic Parameters at steady state
| Exposure metric | Cmax,ss [µg/mL] | t½ (days) | AUCτ,ss [µg*h/mL] | CL,ss [L/h] | V,ss [L] |
| Mean estimate | 358 | 12.1 | 43,700 | 0.027 | 8.44 |
Absorption
Donanemab is for intravenous administration only.
Distribution
The central volume of distribution is 3.43 L with 18.3% inter-individual variability. Peripheral volume of distribution is 5.01 L, with 93.3% inter-individual variability.
Metabolism
Donanemab is a monoclonal antibody and is expected to be degraded into small peptides and amino acids via catabolic pathways in the same manner as an endogenous IgG.
Elimination
Following intravenous dosing, donanemab undergoes biphasic elimination. The mean terminal half-life of donanemab is approximately 12.1 days. Donanemab clearance is 0.027 L/h.
Special populations and conditions
Pediatrics
The pharmacokinetics of donanemab in pediatric patients has not been evaluated.
Geriatrics
Population pharmacokinetic analysis showed that age had no effect on the pharmacokinetics of donanemab.
Sex
Population pharmacokinetic analysis showed that sex did not have a significant effect on the pharmacokinetics of donanemab.
Pregnancy and breastfeeding
Studies characterizing the pharmacokinetics of donanemab in pregnant and breast-feeding patients have not been performed.
Ethnic origin
Population pharmacokinetic analysis showed that race had no effect on the pharmacokinetics of donanemab.
Hepatic Insufficiency
Hepatic impairment did not affect the PK of donanemab based on population PK analysis. No dose adjustment is necessary in patients with hepatic impairments. Donanemab is degraded by proteolytic enzymes and is not expected to undergo renal elimination or metabolism by hepatic enzymes.
Renal Insufficiency
Renal impairment did not affect the PK of donanemab based on population PK analysis. No dose adjustment is necessary in patients with renal impairments.
Obesity
While body weight was found to influence both clearance and volume of distribution, the resulting changes in donanemab exposure were not clinically meaningful.
10.4. Immunogenicity
The observed incidence of anti-drug antibodies (ADA) is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of ADA in the studies described below with the incidence of ADAs in other studies, or to other products.
In up to 18 months of treatment in Study 1, a total of 693/793 (87.4%) patients receiving donanemab once monthly developed anti-donanemab antibodies and all of the patients with ADA had neutralizing antibodies.
In up to 18 months of treatment in Study 2, a total of 181/202 (89.6%) patients receiving donanemab once monthly developed anti-donanemab antibodies and all of the patients with ADA had neutralizing antibodies.
All donanemab-treated patients who reported infusion-related reactions had ADA. Higher ADA titer was associated with increased incidence of infusion-related reactions/immediate hypersensitivity events (see 7. Warnings and Precautions).
Anti-Drug Antibody Effects on Pharmacokinetics and Pharmacodynamics
The presence of ADA increased donanemab clearance. Among patients treated with donanemab in the placebo-controlled studies who developed ADA, mean donanemab serum trough concentrations were lower compared to patients who had not developed ADA. No clinically meaningful effect of ADA was observed on amyloid plaque reduction or clinical efficacy outcomes.
- 11. Storage, Stability, and Disposal
Unopened Vial
- Store refrigerated at 2°C to 8°C.
- Keep the vial in the outer carton to protect from light.
- Do not freeze or shake.
- If refrigeration is not available, may be stored at room temperature (20°C to 25°C) for up to 3 days.
Diluted Solution
- After dilution, immediate use is recommended. If the KISUNLA diluted solution is not administered immediately, store refrigerated at 2°C to 8°C for up to 72 hours or at room temperature (20°C to 25°C) for up to 12 hours.
- Do not freeze the KISUNLA diluted solution.
- Storage times include the duration of infusion.
- Discard any unused portion left in the vial.
12. Special Handling Instructions
KISUNLA is sterile and preservative-free. Discard any unused portion.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): donanemab
Chemical name: Immunoglobulin G1, anti-(human pyroglutamyl Aβ (3-x) peptide) (human clone LY3002813 γ1-chain), disulfide with human clone LY3002813 κ-chain, dimer.
Molecular formula and molecular mass: C6452H10012N1708O2016S42 (disulfide linked) Approximately 145 kDa (non-glycosylated).
Structural formula: Donanemab is a humanized immunoglobulin gamma 1 (IgG1) monoclonal antibody composed of two identical immunoglobulin kappa light chains and two identical immunoglobulin gamma heavy chains.
Physicochemical properties: Donanemab is clear to opalescent, colorless to yellow to brown solution with a pH of 5.5 – 6.5.
Product Characteristics:
Donanemab is produced in Chinese Hamster Ovary (CHO) cells by recombinant DNA technology. Donanemab drug substance manufacture begins with the thawing of the working cell bank, that is scaled-up prior to seeding a production bioreactor. The culture is harvested, clarified, and purified via a downstream purification process. Donanemab drug product is formulated, sterile filtered and filled into vials prior to final packaging.
14. Clinical Trials
14.1. Clinical Trials by Indication
14.1.1. Alzheimer's Disease
Trial Design and Study Demographics
The efficacy of KISUNLA for the treatment of subjects with early symptomatic Alzheimer’s disease was established by TRAILBLAZER-ALZ 2 (Study 1), which assessed a dosing regimen of 700 mg every 4 weeks for the first 3 doses, and 1,400 mg every 4 weeks thereafter (Dosing Regimen 1). TRAILBLAZER-ALZ 6 (Study 2) was conducted to assess different titration regimens, including doses every 4 weeks with 350 mg the first infusion, 700 mg the second infusion, 1,050 mg the third infusion, and 1,400 mg every 4 weeks thereafter (Dosing Regimen 2), which demonstrated consistent donanemab exposure, pharmacodynamic effects on amyloid plaque reduction, and a reduced incidence of amyloid related imaging abnormalities (ARIA)-related events compared to Dosing Regimen 1 (see 4.1. Dosing Considerations, 7. Warnings and Precautions, 8. Adverse Reactions, and 10. Clinical Pharmacology).
Table 10 – Summary of Subject Demographics for Clinical Trials in Alzheimer's Disease
| Study # | Study design | Dosage, route of administration and duration | Study subjects (N) | Mean age (min, max) | Sex n (%) |
TRAIL BLAZER-ALZ 2 (Study 1) | Multicentre, randomized, parallel-group, double-blind, placebo-controlled, Phase 3 study in subjects with early symptomatic Alzheimer’s disease (AD) | Donanemab: 700 mg intravenous (IV) every 4 weeks (Q4W) for the first 3 doses and then 1400 mg IV Q4W Placebo: placebo IV Q4W Duration: Up to 76 weeks | 860 876 | 73 year (59, 86) | Male 740 (43%) Female 996 (57%) |
TRAIL BLAZER-ALZ 6 (Study 2) | Multicentre, randomized, parallel-group, double-blind, Phase 3b study in subjects with early symptomatic Alzheimer’s disease (AD) | Dosing Regimen 1: Donanemab 700 mg intravenous (IV) every 4 weeks (Q4W) for the first 3 doses and then 1400 mg IV Q4W Dosing Regimen 2: Donanemab 350 mg, 700 mg, 1,050 mg intravenous (IV) every 4 weeks (Q4W) for the first 3 doses and then 1400 mg IV Q4W Duration: Up to 76 weeks | 208 212 | 74 years (59, 85) | Male 173 (41%) Female 247 (59%) |
TRAILBLAZER-ALZ 2 (Study 1)
The efficacy and safety of KISUNLA was evaluated in a double-blind, placebo-controlled, parallel-group study in subjects with early symptomatic Alzheimer’s disease (subjects with confirmed presence of amyloid pathology and mild cognitive impairment or mild dementia stage of disease). There were two primary analysis populations based on brain tau deposition assessed by PET imaging with flortaucipir: 1) low/medium tau level population, and 2) overall population (low/medium plus high tau level population).
In Study 1, 1736 subjects were randomized 1:1 to receive 700 mg of KISUNLA every 4 weeks (Q4W) for the first 3 doses and then 1400 mg Q4W (N = 860), or placebo (N = 876) for a total of up to 72 weeks. Completion of active treatment was guided by amyloid PET levels measured at Week 24, Week 52, and Week 76. If the amyloid plaque level was <11 Centiloids on a single PET scan or between 11 to <25 Centiloids on 2 consecutive PET scans (consistent with a negative visual read of an amyloid PET scan), the subject was switched to placebo.
Additionally, dose adjustments were allowed for treatment-emergent ARIA or symptoms that then showed ARIA-Edema (E) or ARIA-Hemorrhage (H) on MRI. Subjects were enrolled with or without concomitant therapies (cholinesterase inhibitors and the N-methyl-D-aspartate antagonist memantine) for Alzheimer’s disease.
Subjects were enrolled with progressive change in memory function for at least 6 months and a Mini–Mental State Examination (MMSE) score of 20 to 28 (inclusive). At baseline, mean age was 73 years, ranging from 59 to 86 years. The majority of subjects were female (57%) and White (92%). Of the total number of subjects randomized, 68% had low/medium tau level and 32% had high tau level; 71% were ApoE ε4 carriers (including 54% heterozygotes and 17% homozygotes) and 29% were ApoE ε4 non-carriers.
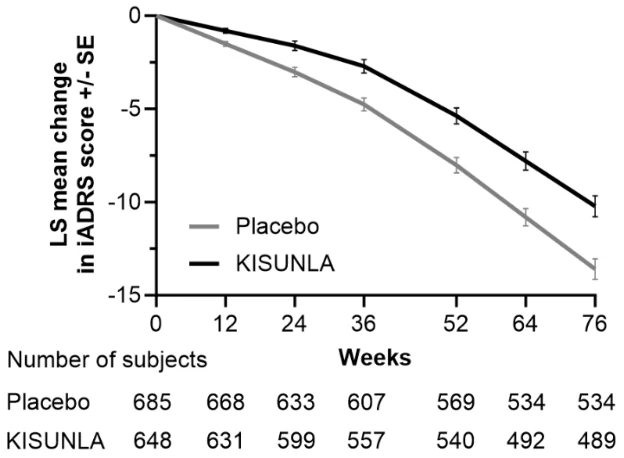
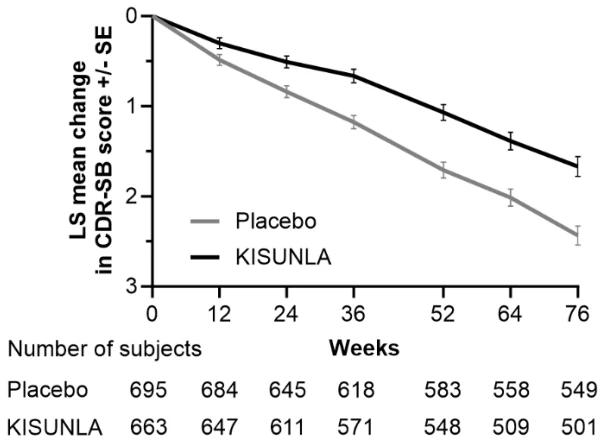
The primary efficacy endpoint was the change in the integrated Alzheimer’s Disease Rating Scale (iADRS) score from baseline to 76 weeks. Key secondary efficacy endpoints included the change from baseline in the Clinical Dementia Rating Scale – Sum of Boxes (CDR-SB), the Alzheimer’s Disease Assessment Scale-Cognitive subscale (ADAS-Cog13), and the Alzheimer’s Disease Cooperative Study – instrumental Activities of Daily Living (ADCS-iADL) scale.
The iADRS is an integrated assessment of cognition and daily function comprised of items from the ADAS-Cog13 and ADCS-iADL scales, respectively. The iADRS total score ranges from 0 to 144, with lower scores reflecting worse cognitive and functional performance. The CDR-SB is a global measure comprised of subscales that index the performance of 3 domains of cognition (i.e., memory, orientation, and judgement and problem-solving) and 3 domains of function (i.e., community affairs, home and hobbies, and personal care). Dementia severity scores are assigned for each of 6 domains from 0 (none), 0.5 (questionable), 1 (mild), 2 (moderate), and 3 (severe). The score for each of the 6 domains are summed to provide a value ranging from 0 (normal) to 18 (severe dementia). The ADAS-Cog13 is a composite measure of multiple cognitive domains comprising a global cognitive measure. It assesses cognition, with specific measures of memory, language, praxis, delayed recall, and attention. ADAS-Cog13 scores range from 0 to 85, with higher scores indicating greater overall cognition deficit. The ADCS-iADL scale assesses the competence of patients with Alzheimer’s Disease in basic and instrumental activities of daily living. The ADCS-iADL scores range from 0 to 59, with lower scores indicating greater impairment in function.
Study Results
The key efficacy results evaluating KISUNLA at Week 76 in subjects with early symptomatic Alzheimer’s disease are presented in Table 11.
The proportion of subjects who discontinued treatment with donanemab based on amyloid PET levels at Week 24, Week 52, and Week 76 were 17%, 47%, and 69%, respectively.
Table 11 – Results of Key Efficacy Endpoints at Week 76 in Subjects with Early Symptomatic Alzheimer's Disease from TRAILBLAZER-ALZ 2
| Low/Medium tauc populationd | Overall tauc populationd | Indicated population | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
KISUNLA (N=588) | Placebo (N=594) | KISUNLA (N=860) | Placebo (N=876) | KISUNLA (N=717) | Placebo (N=594) | ||||||||||||||||
Primary Efficacy Endpoint iADRSa | |||||||||||||||||||||
| LS Mean at baseline | 105.92 | 105.95 | 104.55 | 103.82 | 104.66 | 103.83 | |||||||||||||||
| LS Mean change from baseline | -6.02 | -9.27 | -10.19 | -13.11 | -10.21 | -13.59 | |||||||||||||||
LS Mean change difference (95% CI) | 3.25* (1.88, 4.62) | 2.92* (1.51, 4.33) | 3.38 (1.83, 4.92) | ||||||||||||||||||
Key Secondary Efficacy Endpoints CDR-SBb | |||||||||||||||||||||
| LS Mean at baseline | 3.72 | 3.64 | 3.92 | 3.89 | 3.96 | 3.94 | |||||||||||||||
| LS Mean change from baseline | 1.20 | 1.88 | 1.72 | 2.42 | 1.67 | 2.43 | |||||||||||||||
LS Mean change difference (95% CI) | -0.67* (-0.95, -0.40) | -0.70* (-0.95, -0.45) | -0.77 (-1.04, -0.49) | ||||||||||||||||||
| ADAS-Cog13a | |||||||||||||||||||||
| LS Mean at baseline | 27.41 | 27.60 | 28.53 | 29.16 | 28.43 | 29.00 | |||||||||||||||
| LS Mean change from baseline | 3.17 | 4.69 | 5.46 | 6.79 | 5.37 | 7.06 | |||||||||||||||
LS Mean change difference (95% CI) | -1.52* (-2.25, -0.79) | -1.33* (-2.09, -0.57) | -1.69 (-2.52, -0.86) | ||||||||||||||||||
| ADAS-iADLa | |||||||||||||||||||||
| LS Mean at baseline | 48.20 | 48.56 | 47.96 | 47.98 | 48.02 | 47.84 | |||||||||||||||
| LS Mean change from baseline | -2.76 | -4.59 | -4.42 | -6.13 | -4.55 | -6.31 | |||||||||||||||
LS Mean change difference (95% CI) | 1.83* (0.91, 2.75) | 1.70* (0.84, 2.57) | 1.76 (0.81, 2.72) | ||||||||||||||||||
Abbreviations: ADAS-Cog13 = Alzheimer’s Disease Assessment Scale – 13-item Cognitive Subscale; ADCS-ADL = Alzheimer’s Disease Cooperative Study – instrumental Activities of Daily Living subscale; CDR-SB = Clinical Dementia Rating Scale – Sum of Boxes; iADRS = integrated Alzheimer’s Disease Rating Scale; LS = least squares.
a Assessed using natural cubic spline with 2 degrees of freedom (NCS2) to capture the nonlinear progression of Alzheimer’s disease symptoms over the 76-week trial.
b Assessed using mixed model for repeated measures (MMRM) to capture the nonlinear progression of Alzheimer’s disease symptoms over the 76-week trial.
c Low/medium tau: SUVr ≤1.46 and a topographic deposition pattern consistent with advanced AD (AD++) or 1.10 ≤ SUVr ≤ 1.46 and a topographic deposition pattern consistent with moderate AD (AD+); high tau: SUVr >1.46 and a topographic deposition pattern consistent with either moderate (AD+) or advanced AD (AD++).
d Population includes subjects independent of ApoE ε4 genotype.
* Statistically significant versus placebo based on the pre-defined Bretz’s graphical approach testing hierarchy, with overall two-sided significance levels of 0.04 for the low/medium tau population and 0.01 for the overall tau population.
Figure 1 – iADRS and CDR-SB Change from Baseline in Indicated Population through 76 Weeks in TRAILBLAZER-ALZ 2a
TRAILBLAZER-ALZ 6 (Study 2)
Study 2 was a randomized, double-blind study investigating the effect of different KISUNLA dosing regimens on ARIA-E, change from baseline in amyloid, and pharmacokinetics in adults with Alzheimer’s disease (subjects with confirmed amyloid pathology and mild cognitive impairment or mild dementia stage of disease). Inclusion and exclusion criteria were consistent with Study 1 except that tau PET was not an inclusion criterion. Subjects were randomized to receive Dosing Regimen 1 (N=208) or one of three alternative regimens, including Dosing Regimen 2 (N=212), in a 1:1:1:1 ratio (see 4.2. Recommended Dose and Dosage Adjustment). The treatment period was up to 76 weeks, and treatment stopping criteria based on amyloid PET were the same as Study 1.
Of the 212 subjects receiving Dosing Regimen 2, the mean age was 74 years. The majority of subjects were female (59%) and White (91%). Overall, 64% of these subjects were ApoE ε4 carriers (including 10% homozygotes and 54% heterozygotes) and 36% were ApoE ε4 non-carriers.
The primary endpoint of the study was the proportion of subjects with any occurrence of ARIA-E at 24 weeks. The results showed that subjects receiving Dosing Regimen 2 had less incidence of ARIA-E by Week 76 (15.6%) compared with subjects receiving Dosing Regimen 1 (24.2%) (see 8.2. Clinical Trial Adverse Reactions) but demonstrated consistent donanemab pharmacokinetics and pharmacodynamic effects on amyloid plaque reduction (see 10.2. Pharmacodynamics and 10.3. Pharmacokinetics).
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General Toxicology: Repeat-dose toxicity studies on donanemab were limited to a 6-week study conducted in healthy cynomolgus monkeys to assess for off-target effects. Animals were 2 to 4 years of age with all males on study consisting of (sexually) immature animals. Females were also considered sexually immature as verified by the presence of the follicular phase in the uterus with no corpora lutea in the ovaries. Animals were administered donanemab by intravenous injection at doses of 0 (vehicle control), 1, 10, and 100 mg/kg body weight once weekly. No donanemab-related adverse effects were observed in this study. Exposures at the no-observed-adverse-effect level (NOAEL) of 100 mg/kg were 7.2-fold the human exposure at a dose of 1400 mg Q4W (based on Cmax,ss).
Carcinogenicity: Carcinogenicity studies have not been conducted with donanemab.
Genotoxicity: Genotoxicity studies have not been conducted with donanemab.
Reproductive and Developmental Toxicology: No studies in animals have been conducted to assess the effects of donanemab on male or female fertility, reproduction, or development.