


Product Monograph - Lamisil
RECENT MAJOR LABEL CHANGES
None at the time of authorization
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
TABLE OF CONTENTS ................................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION .......................................................................4
1 INDICATIONS ................................................................................................................4
1.1 Pediatrics ............................................................................................................4
1.2 Geriatrics.............................................................................................................5
2 CONTRAINDICATIONS ...................................................................................................5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ..............................................................5
4 DOSAGE AND ADMINISTRATION...................................................................................5
4.1 Dosing Considerations .........................................................................................5
4.2 Recommended Dose and Dosage Adjustment.......................................................5
4.4 Administration.....................................................................................................7
4.5 Missed Dose ........................................................................................................7
5 OVERDOSAGE ...............................................................................................................8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ...................................8
7 WARNINGS AND PRECAUTIONS ....................................................................................9
7.1 Special Populations ............................................................................................ 12
7.1.1 Pregnant Women .........................................................................................12
7.1.2 Breast-feeding..............................................................................................12
7.1.3 Pediatrics .....................................................................................................12
7.1.4 Geriatrics .....................................................................................................13
8 ADVERSE REACTIONS .................................................................................................. 13
8.2 Clinical Trial Adverse Reactions .......................................................................... 13
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 14
8.5 Post-Market Adverse Reactions.......................................................................... 15
9 DRUG INTERACTIONS.................................................................................................. 16
9.2 Drug Interactions Overview................................................................................ 16
9.4 Drug-Drug Interactions ...................................................................................... 16
9.5 Drug-Food Interactions ...................................................................................... 22
9.6 Drug-Herb Interactions ...................................................................................... 23
10 CLINICAL PHARMACOLOGY ......................................................................................... 23
10.1 Mechanism of Action.................................................................................... 23
10.2 Pharmacodynamics ...................................................................................... 23
10.3 Pharmacokinetics ......................................................................................... 23
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 25
12 SPECIAL HANDLING INSTRUCTIONS............................................................................. 25
PART II: SCIENTIFIC INFORMATION ........................................................................................ 26
13 PHARMACEUTICAL INFORMATION.............................................................................. 26
14 CLINICAL TRIALS.......................................................................................................... 27
14.1 Clinical Trials by Indication............................................................................ 27
Onychomycosis ........................................................................................................... 27
Tinea corporis/Tinea cruris .......................................................................................... 28
Tinea Pedis.................................................................................................................. 33
Cutaneous Candidiasis................................................................................................. 39
Tinea Versicolor .......................................................................................................... 40
15 MICROBIOLOGY .......................................................................................................... 41
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 43
PATIENT MEDICATION INFORMATION ................................................................................... 51
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
LAMISIL® (terbinafine hydrochloride) is indicated for:
- the treatment of fungal infections of the skin and nails caused by dermatophytes such as Trichophyton (e.g. T. rubrum, T. mentagrophytes, T. verrucosum, T. violaceum), Microsporum canis, Epidermophyton floccosum and yeasts of the genus Candida (eg. C. albicans), as well as Malassezia furfur.
LAMISIL tablets:
the treatment of onychomycosis (fungal infection of the nail) caused by dermatophyte fungi.
- Prior to initiating treatment with LAMISIL® tablets, appropriate nail or skin specimens should be obtained for laboratory testing (KOH preparation, fungal culture, or nail biopsy) in order to confirm the diagnosis of onychomycosis or dermatomycosis.
- may be considered for the treatment of severe tineal skin infections (tinea corporis, tinea cruris and tinea pedis) which have been unresponsive to topical treatment.
Note: LAMISIL tablets are not effective in pityriasis versicolor (also known as Tinea versicolor).
LAMISIL cream and spray:
Cream
- the treatment of fungal infections of the skin caused by dermatophytes such as trichophyton, as well as yeast infections of the skin, principally those caused by the genus Candida (e.g. Candida albicans).
- the treatment of pityriasis (tinea) versicolor due to Malassezia furfur.
Spray
- the treatment of fungal infections of the skin caused by dermatophytes such as trichophyton.
- the treatment of pityriasis (tinea) versicolor due to Malassezia furfur.
Note: LAMISIL cream and spray are not effective in onychomycosis.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. (See 7.1.4 Geriatrics)
2 CONTRAINDICATIONS
- LAMISIL tablets and LAMISIL cream and spray are contraindicated in patients with a known hypersensitivity to terbinafine or to any of the excipients of LAMISIL or component of the container. See 6 DOSAGE FORMS, STRENGTHS, and COMPOSITION AND PACKAGING.
- Lamisil tablets are contraindicated for patients with chronic or active hepatic disease. See 7 WARNINGS AND PRECAUTIONS, 8 ADVERSE REACTIONS.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
- HEPATIC: LAMISIL tablets are contraindicated in patients with pre-existing chronic or active hepatic disease. Serious and life-threatening hepatic adverse reactions (including hepatic failure leading to death and liver transplant) have been reported in patients with or without pre-existing chronic or active hepatic disease receiving LAMISIL tablets for the treatment of onychomycosis and dermatomycosis.
- Baseline liver function test should be recommended before initiating treatment with LAMISIL tablets. LAMISIL tablets and should be discontinued if biochemical or clinical evidence of liver injury develops. See 7 WARNINGS AND PRECAUTIONS, Hepatic.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Special Populations
- Liver Impairment: LAMISIL tablets are contraindicated for patients with chronic or active hepatic disease. See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS.
- Renal Impairment: The use of LAMISIL tablets has not been adequately studied in patients with renal impairment and is therefore not recommended in this population.
4.2 Recommended Dose and Dosage Adjustment
LAMISIL tablets:
- Adults: 250 mg once daily. See 4.1 Dosing Considerations.
- The duration of treatment varies according to the indication and the severity of infection:
Table 1
| Indication | Duration of Treatment |
| Onychomycosis (of fingers and toes)* | 6 weeks to 3 months |
Skin Infections** Tinea pedis (interdigital & plantar/moccasin type) | 2-6 weeks |
| Tinea corporis, cruris | 2-4 weeks |
* In patients with fingernail infections or toenail infections other than the big toe, or in younger patients, treatment periods of less than 3 months may be adequate. In patients with infections of the big toenail, treatment for 3 months is usually sufficient, although some patients may require treatment for 6 months or longer. Poor nail outgrowth during the first weeks of treatment may enable identification of those patients in whom longer therapy is required. In onychomycosis the optimal clinical effect is seen some months after mycological cure and cessation of treatment. This is related to the period required for outgrowth of healthy nail tissue.
** Complete resolution of the signs and symptoms may not occur until several weeks after mycolological cure.
LAMISIL cream:
- LAMISIL cream can be applied once or twice daily depending on the indication.
The duration and frequency of treatment varies with the indication and is dependent on the severity of the infection:
Table 2
| Indication | Duration of Treatment |
Tinea pedis Tinea corporis/cruris Cutaneous Candidiasis Pityriasis versicolor | 1 week, once a day 1 week, once a day 1 to 2 weeks once or twice a day * 2 weeks, once or twice a day |
* Two weeks of treatment with LAMISIL cream produced slightly improved efficacy over treatment for one week. The difference in outcome may not be clinically significant.
- Many patients treated with shorter durations of therapy (1-2 weeks) continue to improve during the 2-4 weeks after therapy has been completed. As a consequence, patients should not be considered therapeutic failures until they have been observed for a period of 2-4 weeks after cessation of treatment.
- Relief of clinical symptoms usually occurs within a few days. Irregular use or premature discontinuation of treatment increases the risk of recurrence. If there are no signs of improvement after two weeks the diagnosis should be verified.
- LAMISIL spray:
- LAMISIL spray is applied once or twice daily, depending on the indication.
The duration of treatment varies with the indication and is dependent on the severity of the infection:
Table 3
| Indication | Duration of Treatment |
Tinea pedis Tinea corporis/cruris Pityriasis versicolor | 1 week, once a day 1 week, once a day 1 week, twice a day |
- Relief of clinical symptoms usually occurs within a few days. Irregular use or premature discontinuation of treatment increases the risk of recurrence. If there are no signs of improvement after two weeks the diagnosis should be verified.
4.4 Administration
Tablets: The scored tablets are taken orally with water. They should preferably be taken at the same time each day and can be taken on an empty stomach or after a meal.
Cream: The affected areas should be cleansed and dried thoroughly before application of LAMISIL. The cream should be applied to the affected skin and surrounding area in a thin layer and rubbed in lightly. In the case of intertriginous infections (submammary, interdigital, intergluteal, inguinal) the area to which the cream has been applied may be covered with a gauze strip, especially at night.
Spray: The affected areas should be cleansed and dried thoroughly before application of LAMISIL. A sufficient amount of spray should be applied to wet the treatment area(s) thoroughly, and to cover the affected skin and surrounding area. See 7 WARNINGS AND PRECAUTIONS.
4.5 Missed Dose
If a dose of LAMISIL tablets is missed, the patient should be advised to take it as soon as he/she remembers. However, if it is almost time of the next dose (up to 4 hours), the patient should skip the missed dose and go back to the regular dosing schedule. The patient should not double dose.
5 OVERDOSAGE
LAMISIL Tablets
A few cases of overdosage with Lamisil tablets (up to 5 g) have been reported giving rise to headache, nausea, epigastric pain and dizziness. The recommended treatment of overdosage consists of eliminating the drug, primarily by the administration of activated charcoal and giving, symptomatic supportive therapy, if needed.
LAMISIL cream and spray
No case of overdosage has been reported. The low systemic absorption of LAMISIL cream and spray renders overdosage extremely unlikely. Accidental ingestion of one 30 g tube of LAMISIL cream or one 30 mL bottle of LAMISIL spray, which contain 300 mg terbinafine, is comparable to one LAMISIL tablets. However, should, larger amounts of LAMISIL cream and spray be inadvertently ingested, adverse effects similar to those observed with an overdosage of LAMISIL tablets are to be expected (e.g. headache, nausea, epigastric pain and dizziness). The alcohol content of the spray (28.8% v/v) has to be taken into account.
For management of a suspected drug overdose, contact your regional poison control centre
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 4 – Dosage Forms, Strengths, Composition and Packaging.
LAMISIL 250 mg tablets are whitish to yellow tinged white, circular, biconvex, with bevelled edges tablet, scored on one side and embossed "LAMISIL 250". Available in bottles of 100 and 500 tablets and blister packs of 28 tablets (14 tablets per blister).
LAMISIL cream 1 % is white, smooth or almost smooth, glossy cream with a weak characteristic odor. Available in 15 or 30 gram tubes.
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| oral | Tablet 250 mg | cellulose microcrystalline granulate; hypromellose; magnesium stearate; silica, colloidal anhydrous; sodium starch glycollate. |
| topical | Cream, 1 % w/w (10 mg/g) | benzyl alcohol; cetyl alcohol; cetyl palmitate; isopropyl myristate; polysorbate 60; purified water; sodium hydroxide; sorbitan monostearate; stearyl alcohol. |
| topical | Spray, 1 % w/w (10 mg/g) | ceto-macrogol 1000; ethanol (28.8% v/v); propylene glycol; water. |
LAMISIL spray 1 % is Colourless to faintly yellow clear liquid. Available in 30 mL bottles.
7 WARNINGS AND PRECAUTIONS
LAMISIL Tablets
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Carcinogenesis and Mutagenesis
An increase in liver tumors was observed in male rats at the highest dose level (69 mg/kg) during a life-time (123 weeks) carcinogenicity study. The changes included increased enzyme activity, peroxisome proliferation and altered triglyceride metabolism. The changes have been shown to be species specific since they were not seen in mice or monkeys.
Driving and Operating Machinery
Effects on ability to drive and use machines:
No studies on the effects of LAMISIL tablets treatment on the ability to drive and use machines have been performed. Patients who experience dizziness as an undesirable effect should avoid driving vehicles or using machines.
Endocrine and Metabolism
In vitro and in vivo studies have shown that terbinafine inhibits the CYP2D6 metabolism. Therefore, patients receiving concomitant treatment with drugs predominantly metabolized by this enzyme, e.g. certain members of the following drug classes, tricyclic antidepressants (TCAs), β-blockers, selective serotonine reuptake inhibitors (SSRIs), antiarrhythmics class 1A, 1B and 1C and monoamine oxidase inhibitors (MAO-Is) Type B, should be followed up, if the co-administered drug has a narrow therapeutic window. See 9 DRUG INTERACTIONS.
Hematologic
Very rare cases of blood dyscrasias (neutropenia, agranulocytosis, thrombocytopenia, pancytopenia) have been reported in patients treated with LAMISIL tablets. Etiology of any blood dyscrasias that occur in patients treated with LAMISIL tablets should be evaluated and consideration should be given for a possible change in medication regimen, including discontinuation of treatment with LAMISIL tablets.
Hepatic/Biliary/Pancreatic
LAMISIL tablets are contraindicated for patients with chronic or active hepatic disease. Before prescribing LAMISIL tablets, a baseline liver function test should be performed to assess any pre-existing liver disease since hepatotoxicity may occur in patients with and without pre-existing liver disease. Periodic monitoring (after 4-6 weeks of treatment) of liver function tests is recommended. LAMISIL tablets should be immediately discontinued in case of elevation of liver function tests. Patients prescribed LAMISIL tablets should be warned to report immediately to their physician any symptoms of persistent nausea, decreased appetite, fatigue, vomiting, right upper abdominal pain or jaundice, dark urine or pale feces. Patients with these symptoms should be advised to discontinue taking oral terbinafine, and the patient’s hepatic function should be immediately evaluated. See 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests; 8 ADVERSE REACTIONS.
Immune
Transient decreases in absolute lymphocyte counts (ALC) have been observed in controlled clinical trials. The clinical significance of this observation is unknown. However, in patients with known or suspected immunodeficiency, physicians should consider monitoring complete blood counts in individuals using LAMISIL therapy for greater than six weeks.
Lupus erythematosus:
During post-marketing experience, precipitation and exacerbation of cutaneous and systemic lupus erythematosus have been reported infrequently in patients taking LAMISIL. LAMISIL therapy should be discontinued in patients with clinical signs and symptoms suggestive of lupus erythematosus.
Monitoring and Laboratory Tests
Measurement of serum transaminases (ALT and AST) is advised for all patients before taking LAMISIL tablets.
Neurologic
Sensory disturbances:
Disturbances of visual, auditory and tactile senses have been reported. See 8 ADVERSE REACTIONS. If visual or hearing disturbances occur, LAMISIL tablets should be discontinued.
Taste Disturbance Including Loss of Taste:
Taste disturbance, including taste loss, has been reported with the use of LAMISIL tablets. It can be severe enough to result in decreased food intake, weight loss, and depressive symptoms. Taste disturbance usually resolves within several weeks after discontinuation of treatment.
Isolated cases of prolonged taste disturbances have also been reported. If symptoms of a taste disturbance occur, LAMISIL tablets should be discontinued.
Smell Disturbance Including Loss of Smell:
Smell disturbance, including loss of smell, has been reported with the use of LAMISIL tablets. Smell disturbance may resolve after discontinuation of treatment, but may be prolonged
(greater than one year), or may be permanent. If symptoms of a smell disturbance occur, LAMISIL tablets should be discontinued.
Ophthalmologic
Changes in the ocular lens and retina have been reported following the use of LAMISIL tablets in controlled trials. The changes noted were non-specific and the significance of these changes is unknown.
Psychiatric
Anxiety and depressive symptoms:
Anxiety and depressive symptoms have occurred during postmarketing use of terbinafine secondary to taste disturbances, as well as independent of taste disturbances. If depressive symptoms occur, LAMISIL tablets should be discontinued.
Renal
The pharmacokinetics of LAMISIL have been investigated in patients with renal impairment (creatinine clearance ≤ 50 mL/ min); based on this study the use of LAMISIL in renally impaired patients is not recommended. See 10.3 Pharmacokinetics.
Reproductive Health: Female and Male Potential
Please see 7.1.1. Special Population
Women of child-bearing potential: Some cases of menstrual irregularities have been reported in patients taking LAMISIL tablets concomitantly with oral contraceptives, although the incidence of these disorders remains within the background incidence of patients taking oral contraceptives alone.
There are no data to suggest special recommendations for women of child-bearing potential.
- Fertility: No effect of terbinafine on fertility has been seen in animal studies (see section 16 NON-CLINICAL TOXICOLOGY) and there are no data to suggest an effect on fertility in humans.
Skin
LAMISIL tablets
Serious skin reactions (e.g. Stevens-Johnson syndrome, toxic epidermal necrolysis, drug rash with eosinophilia and systemic symptoms) have been very rarely reported in patients taking LAMISIL tablets. If progressive skin rash occurs, treatment with LAMISIL tablets should be discontinued.
Terbinafine should be used with caution in patients with pre-existing psoriasis or lupus erythematosus as precipitation and exacerbation of psoriasis and cutaneous and systemic lupus erythematosus have been reported in a postmarketing setting.
LAMISIL cream and spray
LAMISIL cream and spray are for external use only. LAMISIL cream and spray formulations may be irritating to the eyes. Contact with the eyes should be avoided. LAMISIL spray should not be used on the face.
In the case of accidental ocular contact, the eyes should be rinsed thoroughly with running water and patients should consult a physician if any symptoms persist. In case of accidental inhalation, patients should be advised to consult a physician if any symptoms develop and persist.
LAMISIL spray should be used with caution in patients with lesions where alcohol could be irritating.
Local skin reactions:
LAMISIL Cream contains cetyl alcohol and stearyl alcohol which may cause local skin reactions (e.g contact dermatitis).
LAMISIL Spray contains propylene glycol which may cause skin irritation.
7.1 Special Populations
7.1.1 Pregnant Women
Animal fetal toxicity studies did not reveal any teratogenic or embryofetotoxic potential of terbinafine. However, there is only very limited documented clinical experience with LAMISIL (terbinafine) in pregnant women; therefore, unless the potential benefits outweigh any potential risks, LAMISIL tablets or LAMISIL cream should not be used during pregnancy.
7.1.2 Breast-feeding
Terbinafine is excreted in breast milk; therefore mothers receiving LAMISIL tablets should not breast feed. However, with LAMISIL cream and spray treatment, the small amounts absorbed through the skin are unlikely to affect the infant. Nursing mothers should NOT apply LAMISIL cream and spray to the breast. In addition, infants must not come into contact with any treated skin area, including the breasts.
7.1.3 Pediatrics
The safety and efficacy of LAMISIL have not been established in pediatric patients.
LAMISIL should be kept out of the reach of children.
7.1.4 Geriatrics
Plasma concentrations and drug half-life appear to be slightly higher in elderly patients than in the general population. In addition, the incidence of all adverse events in a Post Marketing Surveillance study appeared to be slightly higher in the elderly at normal adult doses; however, the overall rate of adverse events possibly or probably related to terbinafine did not appear to be different compared to the general population. When prescribing LAMISIL tablets for patients in this age group, the possibility of pre-existing impairment of liver or kidney function should be considered (see 10.3 Pharmacokinetics).
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Frequency estimate: very common ≥ 10%, common ≥ 1% to < 10%, uncommon ≥ 0.1% to < 1%, rare ≥ 0.01% to < 0.1%, very rare <0.01% (includes isolated reports).
LAMISIL tablets
Serious and life-threatening hepatic adverse reactions, including fatal outcome or requiring liver transplant, have been reported in patients receiving LAMISIL tablets.
In clinical trials submitted for purposes of marketing approval in Canada adverse events occurred in 10.4% of patients receiving the recommended oral dose. Of these, 5% were mild to moderate gastrointestinal events (abdominal distension, decreased appetite, dyspepsia, nausea, mild abdominal pain, diarrhea), 3% were rash, urticaria and the remainder were for musculoskeletal reactions (arthralgia, myalgia) and miscellaneous non-specific events such as malaise or tiredness.
The following table of adverse events illustrates some of these results:
TABLE 5 Clinical Trial Adverse events
| Organ System Adverse Event | LAMISIL 250 mg (n = 998) | |
|---|---|---|
| Number | (%) | |
| SKIN (overall) | 27 | 2.7% |
| Erythema or rash | 9 | 0.9 |
| Urticaria | 5 | 0.5 |
| Eczema | 1 | 0.1 |
8.3 Less Common Clinical Trial Adverse Reactions
Adverse events not frequently observed (< 1%) include the following:
Uncommon: Paresthesia and hypoesthesia
Rare: Idiosyncratic and symptomatic hepatobiliary reactions (2/3 primarily cholestatic in nature and the remainder involving hepatocytic damage or both) have been reported in association with LAMISIL treatment, including very rare cases of serious hepatic failure (some leading to liver transplant or death). Unspecific prodromal symptoms (nausea, anorexia, fatigue, general malaise) have been reported. Liver enzyme increases have been noted in asymptomatic patients as well as in patients with more specific symptoms of hepatic dysfunction (jaundice, upper abdominal right quadrant pain, pruritus, pale stools, dark urine). Hepatic failure, hepatitis, jaundice, cholestasis, hepatic enzyme increased. See 7 WARNINGS AND PRECAUTIONS.
| Pruritis | 4 | 0.4 |
| Other | 8 |
|
| GI (overall) | 52 | 5.2 |
| Diarrhea and/or cramps | 10 | 1.0 |
| Nausea and/or vomiting | 11 | 1.1 |
| Fullness | 5 | 0.5 |
| Sickness | 1 | 0.1 |
| G.I. irritation, dyspepsia, gastritis | 22 | 2.2 |
| Other | 3 | 0.3 |
| CNS (overall) | 12 | 1.2 |
| Headache | 9 | 0.9 |
| Concentration | 2 | 0.2 |
| Other | 1 | 0.1 |
| OTHER (overall) | 11 | 1.1 |
| Tiredness, fatigue | 3 | 0.3 |
| Pain (back, knee, legs, feet, kidney) | 1 | 0.1 |
| Change of taste or dry mouth | 1 | 0.1 |
| Other | 6 | 0.6 |
| LABORATORY ADVERSE CHANGES (overall) | 2 | 0.2 |
| Hypoglycemia | 1 | 0.1 |
| Elevated Liver enzymes | 1 | 0.1 |
| TOTAL | 104 | 10.4 |
The frequency of reported apparent hepatic dysfunctions has varied. An analysis of 7 key placebo-controlled trials (262 placebo vs 1624 LAMISIL patients) suggested increases of 1.4% vs 3.4% in liver function test indicators (APase, SGPT (AST), SGOT (ALT), g-GT, bilirubin >2x above upper normal). In a European post-marketing study in 25 884 patients, asymptomatic liver enzyme increases were reported in 0.17% of patients treated. The reporting frequency for symptomatic liver disorder possibly related to LAMISIL was 1:13 000. The relative risk of acute liver injury in this group was considered to be 4.2 times the background incidence.
In the less controlled circumstances of spontaneous worldwide reporting, the development of clinically significant signs and symptoms of hepatobiliary dysfunction for which no other cause was apparent, and in which LAMISIL was considered the possible causative agent, was calculated to be approximately 1:37 000 treated patients. The reporting frequency overall for hepatobiliary events including elevations in liver enzymes was 1:15 000. Very rare cases of liver failure, some fatal, have been associated with LAMISIL treatment and the incidence rate is about 1:1 000 000 exposed patients.
LAMISIL cream and spray:
Local symptoms such as pruritus, skin lesion, skin disorder, skin exfoliation, application site pain, application site irritation, pigmentation disorder, skin burning sensation, erythema, scab, dry skin, dermatitis contact, eczema may occur at the site of application; however, treatment rarely has to be discontinued for this reason. These minor symptoms must be distinguished from allergic reactions (e.g. bullous eruptions, hives, widespread rash and/or redness, urticaria, angioedema, or positive rechallenge) which are rare but require discontinuation of the drug. In clinical trials, adverse reactions were recorded in 33 of the 1757 (1.8%) patients who received LAMISIL cream, and in 39 of the 898 (4.3%) patients who received LAMISIL spray.
8.5 Post-Market Adverse Reactions
LAMISIL tablets
The following adverse drug reactions have been identified based on post-marketing spontaneous reports with LAMISIL tablets and are organized by system organ classes. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency.
- Blood and lymphatic system disorders: neutropenia, agranulocytosis, thrombocytopenia, anemia, pancytopenia, thrombocytopenic purpura (TPP). The mechanism of TPP induction and the role of LAMISIL have not been elucidated.
- Hepatobiliary disorders: Cases of hepatic failure some leading to liver transplant or death and, idiosyncratic and symptomatic hepatic injury. Cases of hepatitis, cholestasis, and increased hepatic enzymes have been seen with the use of LAMISIL Tablets.
Immune system disorders: anaphylactic reaction including anaphylactic shock, respiratory compromised symptoms such as dyspnea, angioedema, serum sickness-like
- reaction, skin reactions (see Skin section), precipitation or exacerbation of cutaneous or systemic lupus erythematosus
- Psychiatric disorders: anxiety and depressive symptoms secondary to taste disturbances. Anxiety and depressive symptoms independent of taste disturbance have also been reported with use of LAMISIL Tablets.
- Eye disorders: visual impairment, vision blurred, visual acuity reduced.
- Ear and labyrinth disorders: hypoacusis, impaired hearing, tinnitus.
- Vascular disorders: vasculitis.
- Nervous system disorders: dizziness, anosmia including permanent anosmia, hyposmia. Dysgeusia including ageusia (hypogeusia, including ageusia, which usually recover within several weeks after discontinuation of the drug. Isolated cases of prolonged hypogeusia have been reported)
- Gastrointestinal disorders: pancreatitis.
- Musculoskeletal and connective tissue disorders: rhabdomyolysis, arthritis.
- General disorders and administration site conditions: influenza-like illness, pyrexia.
- Investigations: blood creatine phosphokinase increased, weight decreased (secondary to dysgeusia)
- Skin and subcutaneous tissue disorders: Stevens Johnson syndrome, Toxic Epidermal Necrolysis, erythema multiforme, acute generalized exanthematous pustulosis, toxic skin eruption, dermatitis exfoliative, dermatitis bullous, psoriasiform eruptions or exacerbation of psoriasis, photosensitivity reactions (e.g. photodermatosis, photosensitivity allergic reaction and polymorphic light eruption) and alopecia.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Tablets: Many categories of drugs are known to inhibit or induce drug metabolism by cytochrome P450 (CYP) enzymes located in the liver and intestine. Co-administration of such drugs may impact metabolic elimination of drugs, and in some cases, bioavailability may be either increased or decreased and accordingly, possibly necessitate dosage adjustments (see 10.3 Pharmacokinetics).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Effects of other medicinal products on terbinafine:
The following medicinal products may increase the effect or plasma concentration of terbinafine.
Table 6-A Established or Potential Drug-Drug Interactions
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Cimetidine | CT | Decreased the clearance of terbinafine by 33% | |
| Fluconazole | CT | Increased the Cmax and AUC of terbinafine by 52% and 69%, respectively, in a randomized, open-label, single-dose, three-period crossover study (7 day washout) in healthy male adult subjects (n = 18), treated with 750 mg terbinafine, 100 mg fluconazole and 750 mg terbinafine plus 100 mg fluconazole. The interaction likely involves inhibition of CYP2C9 and CYP3A4 enzymes | |
| Theophylline | CT | Increased the Cmax and AUC of terbinafine by 25% each, and decreased the oral clearance of terbinafine by 24% in a randomized, open-label, single-dose, three-period crossover study, in healthy male and female adult subjects (n = 18) treated orally with 250 mg terbinafine, 375 mg theophylline, and 250 mg terbinafine plus 375 mg theophylline | |
| Ketoconazole | T | May increase the systemic exposure to terbinafine, based on predicted inhibition of CYP2C9 and CYP3A4 (no studies were performed) | |
| Amiodarone | T | May increase the systemic exposure to terbinafine, based on predicted inhibition of CYP2C9 and CYP3A4 (no studies |
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| were performed). | |||
| Cotrimoxazole (trimethoprim sulfamethoxazole) | CT | Did not alter the pharmacokinetics of terbinafine, in a randomized, open-label, single-dose, three-period crossover study (7 day washout) in healthy male and female adult subjects (n = 18), treated with 750 mg terbinafine, 160 mg trimethoprim plus 800 mg sulfamethoxazole, and 750 mg terbinafine plus 160 mg trimethoprim plus 800 mg sulfamethoxazole. | |
| Zidovudine | CT | Did not alter the pharmacokinetics of terbinafine, in a randomized, open-label, single-dose, three-period crossover study (7 day washout) in healthy male and female adult subjects (n = 18), treated with 750 mg terbinafine, 200 mg zidovudine, and 750 mg terbinafine plus 200 mg zidovudine. | |
| Rifampicin | CT | May decrease the effect or plasma concentration of terbinafine (increased the clearance of terbinafine by 100 %) | |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Effect of terbinafine on other medicinal products:
Table 6-B Established or Potential Drug-Drug Interactions
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Drugs that are metabolized via the cytochrome P450 system (e.g. terfenadine, triazolam, tolbutamide or oral contraceptives) | C, CT | According to the results from studies undertaken in vitro and in healthy volunteers, terbinafine shows negligible potential for inhibiting or enhancing the clearance except with exception of those drugs that are metabolized via the cytochrome P450 system metabolized through CYP2D6 (see below). Some cases of menstrual irregularities have been reported in patients taking LAMISIL tablets concomitantly with oral contraceptives, although the incidence of these disorders remains within the background incidence of patients taking oral contraceptives alone. | |
| Compounds predominantly metabolized by CYP2D6 (e.g. certain members of the following drug classes: tricyclic antidepressants (TCAs), beta-blockers, selective serotonine reuptake inhibitors (SSRIs), antiarrhythmics (including class 1A, 1B and 1C) and monoamine oxidase inhibitors (MAO-Is) Type B) | T, CT | In vitro and in vivo studies have shown that terbinafine inhibits the CYP2D6-mediated metabolism. This finding may be of clinical relevance for compounds predominantly metabolized by CYP2D6, e.g. certain members of the following drug classes: tricyclic antidepressants (TCAs), beta-blockers, selective serotonine reuptake inhibitors (SSRIs), antiarrhythmics (including class 1A, 1B and 1C) and monoamine |
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| oxidase inhibitors (MAO-Is) Type B, particularly if they also have a narrow therapeutic window (see 7 WARNINGS AND PRECAUTIONS). Case reports indicating interactions of LAMISIL with tricyclic antidepressants e.g nortriptyline and imipramine) have been reported in a post-marketing setting. | |||
| Antipyrine or digoxin | CT | Terbinafine does not interfere with the clearance of antipyrine or digoxin. | |
| Desipramine | CT | Terbinafine decreased the clearance of desipramine by 82%. | |
| Dextromethorphan/dextrorphan | CT | Terbinafine increased the dextromethorphan/dextrorphan metabolic ratio in urine by 16- to 97-fold on average, in healthy subjects, converting some extensive CYP2D6 metabolizers to poor metabolizer status after treatment with 250 mg terbinafine once daily for 14 days. The effect of terbinafine on the dextromethorphan/dextrorphan metabolic ratio in urine was shown to be reversible, though the interaction potential may last for several weeks after termination of a LAMISIL treatment cycle. | |
| Ciclosporin | CT | Terbinafine increased the | |
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| clearance of ciclosporin by 15%. | |||
| Fluconazole | CT | Terbinafine did not alter the pharmacokinetics of fluconazole in a randomized, open-label, single-dose, three-period crossover study (7 day washout) in healthy male adult subjects, treated with 750 mg terbinafine, 100 mg fluconazole and 750 mg terbinafine plus 100 mg fluconazole. | |
| Cotrimoxazole (trimethoprim sulfamethoxazole) | CT | Terbinafine did not alter the pharmacokinetics of cotrimoxazole (trimethoprim and sulfamethoxazole), in a randomized, open-label, single-dose, three-period crossover study (7 day washout) in healthy male and female adult subjects (n = 18), treated with 750 mg terbinafine, 160 mg trimethoprim plus 800 mg sulfamethoxazole, and 750 mg terbinafine plus 160 mg trimethoprim plus 800 mg sulfamethoxazole. | |
| Zidovudine | CT | Terbinafine reduced zidovudine Cmax by 25%, increased AUC by 15%, reduced oral clearance by 15% and did not alter zidovudine plasma elimination half-life, in a randomized, open-label, single-dose, three-period crossover study (7 day washout) in healthy male and female adult subjects (n = 18), treated with 750 mg terbinafine, 200 mg zidovudine, and 750 mg terbinafine plus 200 mg | |
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| zidovudine. | |||
| Theophylline | CT | Single dose terbinafine did not significantly alter the pharmacokinetics of theophylline in a randomized, open-label, single-dose, three-period crossover study, in healthy male and female adult subjects (n = 18) treated orally with 250 mg terbinafine, 375 mg theophylline, and 250 mg terbinafine plus 375 mg theophylline. Multiple dose terbinafine increased the AUC and half-life of theophylline by 16% and 24%, respectively, and decreased the oral clearance of theophylline by 14%, in a randomized, open-label, two-period crossover study in healthy male and female adult subjects (n = 12) treated orally with a single dose of 5 mg/kg theophylline alone (mean 345 mg, range 307 to 397 mg) and 2 hours after the last of 4 daily doses of 250 mg terbinafine. | |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
LAMISIL cream and spray:
No drug interactions are known to date.
9.5 Drug-Food Interactions
- Caffeine: Terbinafine decreased the clearance of caffeine administered intravenously by 19%.
9.6 Drug-Herb Interactions
- St John’s wort may considerably decrease the plasma concentration and exposure of terbinafine, however the extent of decrease in exposure is not known.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
LAMISIL (terbinafine) is an allylamine which has a broad spectrum of antifungal activity. At low concentrations LAMISIL is fungicidal against dermatophytes, molds and certain dimorphic fungi. Its activity against yeasts is fungicidal or fungistatic, depending on the species.
The mechanism of action of terbinafine involves specific inhibition of fungal ergosterol biosynthesis at the point of squalene epoxidation, leading to a deficiency of an essential component of the fungal cell membranes (i.e. ergosterol) and to intracellular accumulation of the precursor squalene. The latter effect appears to be responsible for the primary fungicidal activity, its consequent disruption of cell membranes and cell wall synthesis having been noted in ultrastructural studies of terbinafine treated fungi. This mechanism distinguishes terbinafine from the azole antimycotics, which affect a later step in ergosterol biosynthesis by inhibiting 14 %-demethylase, a cytochrome P 450 enzyme upon which terbinafine has no effect. In contrast to many azoles, terbinafine does not bind to cytochromes P 450 in mammalian steroidogenic tissues.
10.2 Pharmacodynamics
Terbinafine interferes specifically with fungal sterol biosynthesis at an early step. This leads to a deficiency in ergosterol and to an intracellular accumulation of squalene, resulting in fungal cell death. Terbinafine acts by inhibition of squalene epoxidase in the fungal cell membrane. The enzyme squalene epoxidase is not linked to the cytochrome P450 system.
When given orally, terbinafine accumulates rapidly in skin, hair and nails at levels associated with fungicidal activity.
10.3 Pharmacokinetics
LAMISIL tablets:
Absorption: Following oral administration, terbinafine is well absorbed (>70%) and the absolute bioavailability of terbinafine from LAMISIL tablets as a result of first-pass metabolism is approximately 50 %. A single 250 mg dose of LAMISIL tablets resulted in mean peak plasma concentration of 1.3 μg/ml within 1.5 hours after administration. At steady-state (70% steady state is achieved in approximately 28 days), in comparison to a single dose, peak concentration of terbinafine was on average 25% higher and plasma AUC increased by a factor of 2.3. From the increase in plasma AUC an effective half-life of ~30 hours can be calculated. The bioavailability of terbinafine is moderately affected by food (increase in the AUC of less than 20%), but not sufficiently to require dosing adjustments.
Distribution: LAMISIL binds strongly to plasma proteins (99%) and is lipophilic. LAMISIL is widely distributed in the body including adipose tissue. It rapidly diffuses through the dermis and accumulates in lipophilic stratum corneum. It is also secreted in sebum, thus achieving high concentrations in hair follicles, hair and sebum-rich skin. There is evidence that LAMISIL is distributed in the nail plate within the first few weeks of commencing therapy.
Metabolism: LAMISIL tablets is excreted mainly in urine (80%) and in feces (20%). Following absorption terbinafine is metabolized rapidly and extensively by the liver. At least seven cytochrome isoenzymes are involved in its metabolism with major contributions from CYP 2C9, CYP 1A2, CYP 3A4, CYP 2C8 and CYP 2C19. Biotransformation results in metabolites with no antifungal activity which are excreted predominantly through the urine. No clinically relevant age-dependent changes in steady-state plasma concentrations of terbinafine have been observed.
Elimination: Multiple dose administration followed by extended blood sampling revealed a triphasic elimination with a terminal half-life of approximately 16.5 days.
The pharmacokinetics of orally administered terbinafine in plasma can best be described by a 2-compartment model. More than 80% of the dose is absorbed, clearance of the drug is high, it is extensively metabolized in the liver, and it is extensively distributed in the tissues. The peak plasma concentration is proportional to the dose, and the time to peak is ~ 2 hours, independent of the dose.
Mean concentrations of terbinafine (in µg/g) measured in the stratum corneum, dermis/epidermis, hair, sweat, and sebum during and after 12 days of 250 mg LAMISIL per day in 10 healthy volunteers were as follows before (day 0), during (days 2, 6, 12) and after treatment (days 13 and 16).
TABLE 7
| Day | 0 | 2 | 6 | 12 | 13 | 16 |
| Stratum corneum | 0.11 | 0.86 | 2.84 | 9.05 | 5.08 | 3.06 |
| Derm / epiderm | 0 | 0.05 | 0.23 | 0.35 | 0.11 | 0.14 |
| Sebum | 0 | 38.2 | 43.1 | 39.7 | 45.1 | 18.8 |
| Hair | 0.02 | 0.24 | 1.30 | 2.60 | 2.11 | 1.35 |
| Sweat | 0 | 0 | 0 | 0 | 0 | 0 |
The pattern of tissue distribution suggests a rapid diffusion of drug through the dermis/lower epidermis into the stratum corneum, where maximal concentrations were achieved at day 12, and the t1/2 was 3-4 days (this implies that the concentrations of terbinafine would remain above the MIC for most dermatophytes for 3 weeks). Another route of terbinafine distribution likely to be important for the treatment of dermatomycosis would be secretion into sebum, in which drug levels were high and persisted for several days after cessation of treatment.
In a study evaluating the efficacy of terbinafine in the treatment of onychomycosis, plasma levels were measured monthly in 9 patients, half of whom received 250 mg terbinafine q.d. in the evening and the other half 125 mg b.i.d. A pharmacokinetic steady state was attained at or before 4 weeks, the first analysis time point available. The steady-state plasma concentrations were 0.22 - 0.56 and 0.15 - 0.35 µg/ml for the b.i.d. and q.d. doses, respectively, and did not increase over time.
LAMISIL cream and spray:
Less than 5% of the dose is absorbed after topical application to humans; systemic exposure is thus very slight. Pharmacokinetic studies in humans revealed that absorption of terbinafine cream or spray through skin is less than 5%. In a single dose study of 14C-terbinafine, urinary excretion accounted for ~ 90% of the absorbed dose, and the highest concentration appeared in the urine 2 and 3 days after terbinafine application.
Special Populations and Conditions
- Hepatic Insufficiency: Following a single 250 mg dose in 12 hepatically impaired cirrhotic (alcoholic) patients, total clearance of terbinafine was reduced by about 40%.
- Renal Insufficiency: In a sample of 12 renally impaired patients (median creatinine clearance of 17.6 mL/min), LAMISIL clearance following a single 250 mg dose was halved resulting in the doubling or more of peak plasma concentrations or AUC. Patients at the highest and lowest ends of the renal impairment spectrum were not represented. There was no direct correlation between creatinine clearance and terbinafine clearance in renally impaired patients, the metabolism of the drug having been impaired in these patients due to competition between metabolite and parent drug.
11 STORAGE, STABILITY AND DISPOSAL
Tablets: Store at temperature between 15 and 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
Protect tablets from light.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: INN, BAN, USAN: terbinafine
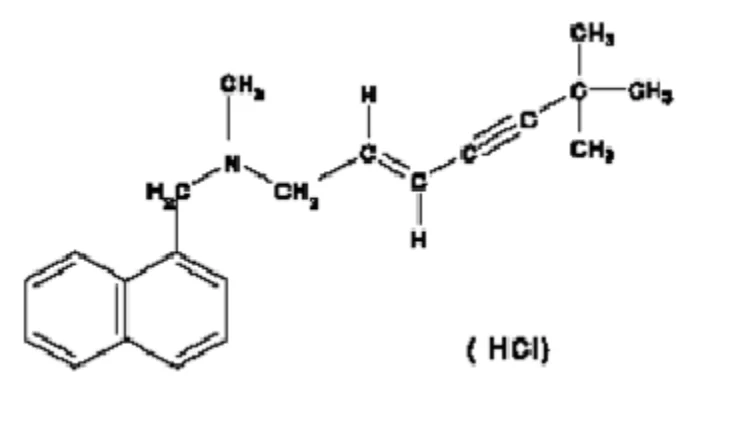
Chemical name: (E)-N-(6,6-dimethyl-2-hepten-4-inyl)-N-methyl-1-naphthaline- methanamine (-hydrochloride)
Molecular formula and molecular mass:
Terbinafine base: 291.40
Terbinafine Hydrochloride: C21H26NCl/327.90
Structural formula:
Physicochemical properties:
- White to off-white finely crystalline powder
- Melting Point: ~ 205°C.
- pKa (I) value: 7.10
- pH of a solution (0.5%) in methanol/water 4:6 (V/V): ~ 4.7. at 25°C.
- Solubility: 0.63% (W/V) in water and >2% (W/V) in chloroform
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Onychomycosis
LAMISIL tablets†
Two studies evaluated the efficacy of oral terbinafine in the treatment of toe or fingernail onychomycosis.
TABLE 8 Summary of patient demographics for oral terbinafine clinical trials in onychomycosis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender | Race |
| SF1501 | Terbinafine tablets, oral 125 mg b.i.d up to 48 wk (toenail) or 24 wk (fingernail) | 51 enrolled 43 evaluable | 45 (18-74) | Male = 34 Female = 9 | Not reporte d | |
| Terbinafine tablets, 2x125 mg o.d. up to 48 wk (toenail) or 24 wk (fingernail) | 52 enrolled 48 evaluable | 45 (18-74) | Male = 34 Female = 14 | Not reporte d | ||
| SF00423 | Randomized, double- blind, multicenter, parallel group, griseofulvin-comparative | Terbinafine capsules: Oral, 250 mg bid for 3-6 months | 47 enrolled 29 evaluable | 44.6 (21-76 yr) | Male = 24 | Caucasi an 100% |
Griseofulvin capsules: Oral 250 mg bid for up to 6 months (standard treatment period is up to 12 months) | 34 enrolled 22 evaluable | 43.5 (20-61 yr) | Male = 15 | Caucasi an 100% |
Study Results:
TABLE 9 Results of study SF1501 in onychomycosis
| Primary Endpoints | b.i.d. Number (%) patients | o.d. Number (%) patients | ||||
| Mycological cure (negative KOH and culture) – all infections | Toenails | |||||
| 25/31 (81%) | 28/35 (80%) | |||||
| Fingernails | ||||||
| 10/10 (100%) | 10/11 (91%) | |||||
| Effective treatment (negative mycology plus continuous or limited nail growth) at end of treatment at week 24 - all infections | Toenails | |||||
| 24/32 (75%) | 26/37 (70%) | |||||
| Fingernails | ||||||
| 10/11 (91%) | 10/11 (91%) | |||||
There were no significant differences between b.i.d and o.d. treatment regimens with respect to mycological cure rates or rates of effective treatment. Mycological cure at end of treatment was 95 % for fingernails and 80% for toenails. At follow-up visit 3-12 months later, over 81% of toenail onychomycosis were cured without relapse.
TABLE 10 Results of study SFO0423 in onychomycosis
| Primary Endpoints | Terbinafine Number (%) patients | Comparator Number (%) patients | |||||
| Effective treatment (negative mycology plus continuous or limited nail growth) at end of treatment at week 24* | Toenail | ||||||
| 11/20 (55%) | 5/12 (42%) | ||||||
| Fingernail | |||||||
| 7/9 (78%) | 8/10 (80%) | ||||||
| Mycological cure (negative culture and KOH) at week 24 | Toenail | ||||||
| 12/20 (60%) | 5/12 (42%) | ||||||
| Fingernail | |||||||
| 7/9 (78%) | 7/10 (70%) | ||||||
*The combined clinical/mycological endpoint was not specified in the protocol
Effective treatment in the LAMISIL treated group was 78% fingernail and 55% toenail with treatment durations of 3-6 months. Griseofulvin was 80% and 42% effective for fingernails and toenails respectively. Thus, short duration therapy (3-6 months) using 500 mg per day of LAMISIL appears effective in many patients with onychomycosis due to dermatophyte infections.
Tinea corporis/Tinea cruris
LAMISIL tablets
Study demographics and trial design:
TABLE 11 Summary of patient demographics for oral terbinafine clinical trials in tinea corporis/cruris
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age across studies (Range) | Gende r | Race: Percen t Caucas ian | |||
|---|---|---|---|---|---|---|---|---|---|
Placebo-controlle d: SFO041B 5-OR SFO041C | Randomize d, single or multicenter , parallel group, double-blind, placebo controlled | Terbinafine oral, capsules, 125 mg bid for 4 wk; 2 wk follow-up | Entered 79 Evaluable 62 | 34 - 40 years (18-74) | Male = 50 Female 11 | 71-100% | |||
| Matching placebo | Entered 77 Evaluable 62 | 37-42 (18-70) | Male = 49 Female = 13 | ||||||
Griseoful vin-controlle d: 11-OR SFO044 | Terbinafine oral capsules, 125 mg and placebo bid for up to 6 wk; 2-6 wk follow-up | Entered 189 Evaluable 174 | 37-38 (17-69) | Male = 105 Female = 69 | 85-99% | ||||
| Griseofulvin oral capsules 2x250 mg bid for up to 6 wk; 2-6 wk follow-up | Entered 192 Evaluable 170 | 31-34 (17-85) | Male = 107 Female = 63 | ||||||
Ketocona zole controlle d: SF3006 SF0047 | Terbinafine oral capsules, 125 mg and placebo bid for up to 6 wk; 4-8 wk follow-up | Entered 73 Evaluable 65 | 34-48 (18-80) | Male = 40 Female = 25 | 60-92% | ||||
| Ketoconazole oral capsules 200 mg od (placebo od) for up to 6 wk; 2-6 wk follow-up | Entered = 71 Evaluable = 62 | 31-43 (16-70) | Male = 40 Female = 22 | ||||||
Study results:
TABLE 12 Combined results of placebo-controlled studies SF 0041 B, 5-OR, SF 0041C in tinea corporis/cruris1
| Primary Endpoints | Terbinafine Number (%) | Placebo Number (%) | |
| Mycological cure (negative culture and KOH) at follow-up | 7-30 (100 - 64%) | 0-4 (0-36%) | |
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up | 8-30 (62-91%) | 0-4 (0-23%) | |
| 5-OR: mycological cure results (combined culture and KOH results) were not provided and too few patients returned at follow-up for meaningful assessments. However, at end of treatment, terbinafine was significantly better than placebo in terms of mycological cures and negative KOH results (Negative KOH of 73% vs 17% for active and placebo, p = 0.043; Negative cultures of 73% vs 0% for active and placebo, p = -.007). | |||
| SF 0041B: too few placebo patients returned at follow-up for meaningful assessments; however, at end of therapy the proportion of patients with mycological cures was greater in the terbinafine group compared with placebo; effective treatment was noted in 75% and 23% of active and placebo groups | |||
1 Range of values represents the highest and lowest values noted across the studies represented
The efficacy of a up to 6 weeks of treatment with terbinafine was consistently positive across 3 placebo-controlled trials both in rates of mycological cures and in the combination of mycological and clinical endpoints. In the placebo-controlled trials, placebo patients often did not return at the post-treatment follow-up to provide meaningful results at that visit. However, results at the end of treatment speak to the high degree of efficacy of terbinafine using clinical and/or mycological endpoints. Results of 4 studies with active comparators show terbinafine to be at least as good as, if not better than, systemically administered griseofulvin and ketoconazole.
TABLE 13 Results of griseofulvin-controlled studies 11-OR and SF 0044 in tinea corporis/cruris1
| Primary Endpoints | Terbinafine Number (%) | Comparator Number (%) |
|---|---|---|
| Mycological cure (negative culture and KOH) at follow-up | 111 - 40 (93-100%) | 101- 36 (94 – 95%) |
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up | 119 – 37 (94 – 77%) | 108 – 36 (86-82%) |
1 Range of values represents the highest and lowest values noted across the studies represented
TABLE 14 Results of ketoconazole-controlled studies SF 3006 and SF 0047 in tinea corporis/cruris1
| Primary Endpoints | Terbinafine Number (%) | Comparator Number (%) |
|---|---|---|
| Mycological cure (negative culture and KOH) at follow-up | 28-36 (100 – 97%) | 23 – 31 (92-86) |
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up | 28 – 35 (100 – 95%) | 23 – 29 (92 – 78 %) |
1 Range of values represents the highest and lowest values noted across the studies represented
LAMISIL cream
Study demographics and trial design:
TABLE 15 Summary of patient demographics for terbinafine cream clinical trials in tinea corporis/cruris
| Study # | Trial design | Dosage, route of administrati on and duration | Study subjects (n=number) | Mean age across studies (Range) | Gender | Race: Percent Caucasian | ||
|---|---|---|---|---|---|---|---|---|
Placebo-controlled: SF 2002 SF 2004 | Randomized, multicenter, parallel group, double-blind, placebo controlled | Terbinafine 1% cream once daily for 1 wk; 3 wk follow-up Cream vehicle | Entered 78 Evaluable 66 | 31-39 (5-89)1 | Male 271 Female 91 | Caucasian 51-67% | ||
Entered 82 Evaluable 73 | 36-40 (6-70) 1 | Male 311 Female 71 | ||||||
1 Range and distribution by sex provided only for SF 2002.
Study results:
TABLE 16 Combined results of placebo-controlled studies SF 2002 and SF2004, terbinafine cream 1%, in tinea corporis/cruris, 2 wk post-treatment
| Primary Endpoints | Terbinafine Number (%) | Placebo Number (%) |
|---|---|---|
| Mycological cure (negative culture and KOH) at follow-up* | 30-27 (88-93%) | 5 in each study (31% in each study) |
| Primary Endpoints | Terbinafine Number (%) | Placebo Number (%) |
|---|---|---|
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up† | 26-29 (81-87%) | 4-5 (11-14%) |
*Study 2002, p value for mycological cure not provided; p <0.007 for KOH and culture results individually. For study 2004 p <0.001 for mycological cure
† p <0.001 for both studies
Two double-blind, placebo controlled studies evaluated whether one week of LAMISIL 1% cream was sufficient to treat Tinea corporis/cruris. At the three week follow-up LAMISIL was effective in 81% -87% of patients, clearly demonstrating the efficacy of daily short duration (one week) treatment.
LAMISIL spray
Study demographics and trial design:
TABLE 17 Summary of patient demographics for terbinafine 1% spray clinical trials in tinea corporis/cruris
| Study # | Trial design | Dosage, route of administratio n and duration | Study subjects (n=number ) | Mean age across studies (Range) | Gender | Race: Percent Caucasian | |||
|---|---|---|---|---|---|---|---|---|---|
| SFF 303 | Randomized, double-blind, vehicle controlled (2:1 terbinafine: vehicle), parallel group, multicenter | Terbinafine 1% spray once daily for 7 days; 7 wk follow-up | Entered 102 ITT 72 | 42 (17-84) | Male 56 Female 16 | 89% | |||
| Terbinafine solution vehicle as above | Entered 49 ITT 37 | 45 (18-71) | Male 28 Female 9 | 86% | |||||
| SFF 105 | Randomized, double-blind, vehicle controlled, parallel group, | Terbinafine 1% spray once daily for 7 days; 3 wk follow-up | Entered 32 ITT 26 | 41 (9-82) | Male 17 Female 9 | 81% | |||
| Study # | Trial design | Dosage, route of administratio n and duration | Study subjects (n=number ) | Mean age across studies (Range) | Gender | Race: Percent Caucasian | ||
|---|---|---|---|---|---|---|---|---|
| multicenter | Terbinafine solution vehicle as above | Entered 34 ITT 26 | 43 (6-71) | Male 18 Female 8 | 77% | |||
| SFF 108 | Randomized, double-blind, vehicle controlled, parallel group, multicenter | Terbinafine 1% spray once daily for 7 days; 3 wk follow-up | Entered 36 ITT 35 | 32 (5-76) | Male 26 Female 9 | 71% | ||
| Terbinafine solution vehicle as above | Entered 36 ITT 35 | 37 (8-81) | Male 23 Female 12 | 71% | ||||
Study results:
LAMISIL 1% spray was significantly more effective than placebo when applied once daily for one week in patients with Tinea corporis/cruris.
TABLE 18 Number (%) subjects with effective treatment (ET) or with both negative microscopy and culture (NM) at study end-point
| Study No. | Treatment | Results | ||||
| ET | NM | |||||
| SFF 303 | LAMISIL Placebo | 71% 11% p<0.001 | 85% 28% p<0.001 | |||
| SFF 105 | LAMISIL Placebo | 65% 8% p<0.001 | 69% 23% p=0.004 | |||
LAMISIL Placebo | 65% 20% p<0.001 | 76% 29% p<0.001 | ||||
Tinea Pedis
LAMISIL tablets
Study demographics and trial design:
TABLE 19 Summary of patient demographics for clinical trials in tinea pedis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender | Race | |||
|---|---|---|---|---|---|---|---|---|---|
| 39-40OR | Randomized, double-blind, multicenter, placebo-controlled | Terbinafine tablets (or matching placebo) 125 mg bid for 6 weeks; 2 week follow-up | Terbinafine Enrolled 26 Evaluable 23 | 37 years (20-64) | Male = 15 Female =8 | 92% Caucasia n | |||
Placebo Enrolled 24 Evaluable 18 | 40 years (20-68) | Male = 13 Female=5 | |||||||
| SF 0508 | Randomized, double-blind, multicenter, placebo-controlled | Terbinafine tablets (or matching placebo) 125x2 mg od for 2 weeks; 6 week follow-up | Terbinafine Enrolled 18 Evaluable 14 | 39 years (19-72) | Male = 20 Female =6 | 79% Caucasia n | |||
Placebo Enrolled 19 Evaluable 14 | 45 years (20-82) | Male =23 Female = 4 | |||||||
| SF 0025 | Randomized, double-blind, multicenter, griseofulvin controlled | Terbinafine capsules, 125 mg bid for 6 wk; 2 wk follow-up | Enrolled 39 Evaluable 33 | 38 years (18-79) | Male = 17 Female = 16 | 95% Caucasia n | |||
| Griseofulvin capsules 250 mg bid for 6 wk; 2 wk follow-up | Enrolled 37 Evaluable 33 | 35 years (14-59) | Male = 18 Female = 15 | ||||||
| 20-OR | Randomized, double-blind, multicenter, griseofulvin controlled | Terbinafine capsules, 125 mg bid for 6 wk; 2 wk follow-up | Enrolled 18 Evaluable 16 | 38 years (22-63) | Male = 11 Female = 5 | 82% Caucasia n | |||
| Griseofulvin capsules 250 mg bid for 6 wk; 2 wk follow-up | Enrolled 18 Evaluable 12 | 36 years (20-49) | Male = 9 Female = 3 | ||||||
Study results:
TABLE 20 Results of placebo controlled studies 39-40OR, SFO508 in tinea pedis
| Primary Endpoints | Terbinafine Number (%) | Placebo Number (%) |
| Mycological cure (negative culture and microscopy) at follow-up | ||
| Study 39-40OR* | 17/22 (77%) | 0/6 (0%) |
| Study SF0508† | 12/14 (86)% | 1/14(7%) |
| Effective treatment (negative mycology and minimal signs and symptoms) at follow-up | ||
| Study 39-40OR* | 15/23 (65%) | 0/18 (0%) |
| Study SF0508† | 10/14 (71%) | 0/14 (0%) |
* Too few placebo patients at follow-up to determine
† P <0.001, Fisher Exact test, one-sided
Placebo-controlled trials demonstrated a consistent treatment effect 2-6 weeks after cessation of treatment, whether assessed solely by mycological results, or when assessed by combined mycological and clinical parameters. Both 6-week and 2-week, o.d., and b.i.d. regimens were effective. In study 39-40OR, too few placebo patients returned at the follow-up visit to allow meaningful statistical analysis of results. Mycological cures and effective treatment rates at end of the 6 week treatment period, however, were significantly greater in the terbinafine treatment group than in the placebo group.
TABLE 21 Results of study griseofulvin-controlled studies SF 0025 and 20-OR in tinea pedis
| Primary Endpoints | Terbinafine Number (%) | Comparator Number (%) |
|---|---|---|
| Mycological cure (negative culture and microscopy) at follow-up | ||
| SF 0025* | 32/33 (97%) | 28/31 (90%) |
| 20-OR* | 16/16 (100%) | 6/11 (55%) |
| Effective treatment (negative mycology and minimal signs and symptoms) at follow-up | ||
| SF 0025† | 32/33 (97%) | 26/33 (79%) |
| 20-OR† | 14/16 (88%) | 5/11 (45%) |
* Statistical significance not reported
† p = 0.054 Fishers Exact test
Two weeks after the end of 6 week courses of treatment, two small studies showed terbinafine to be better than griseofulvin in terms of mycological or combined mycological and clinical parameters.
†LAMISIL 125 mg tablets are not currently available on the Canadian market.
LAMISIL cream
Study demographics and trial design:
TABLE 22 Summary of patient demographics for terbinafine 1% cream clinical trials in tinea pedis
| Study # | Trial design | Dosage, route of administratio n and duration | Study subjects (n=numb er) | Mean age across studies (Range) | Gender | Race: Percent Caucasian | ||
|---|---|---|---|---|---|---|---|---|
Placebo-controlled: 81 T, 4 wk SF0505, 2 wk SF0020, 4 wk | Randomized single or multicenter, parallel group, double-blind, placebo controlled | Terbinafine 1% cream once daily for 2-4 wk | Entered 90 Evaluable 70 | 36-37 yr (12-72) | Male 38 Female 32 | Race not quantified; majority were Mestizo | ||
| Cream vehicle | Entered 87 Evaluable 70 | 38-41 yr (10-86) | Male 39 Female 31 | |||||
Clotrimazo le-controlled: SF018 | Randomized , single or multicenter, parallel group, double-blind, clotrimazole -crean controlled | Terbinafine 1% cream once daily for 4 wk; 2 wk follow-up | Entered 164 Evaluable 133 | 40 yr (18-76) | Male 100 Female 33 | Caucasian 79% | ||
| Clotrimazole 1% cream once daily for 4 wk; 2 wk follow-up | Entered 168 Evaluable 134 | 40 yr (15-88) | Male 94 Female 39 | |||||
Ketoconaz ole controlled ITUK 85 | Randomized , single or multicenter, parallel group, ketoconazol e-cream controlled | Terbinafine 1% cream once daily for 4 wk; 2 wk follow-up | Entered 89 Evaluable 72 | 38 (17-61) | Male 72 Female 0 | Caucasian 96% | ||
| Ketoconazole 2% cream once daily for 4 wk; 2 wk follow-up | Entered 89 Evaluable 73 | 37 (17-63) | Male 73 Female 0 | |||||
Study results:
TABLE 23 Combined results of placebo-controlled studies terbinafine 1% cream studies in tinea pedis 1
| Primary Endpoints | Terbinafine Number (%) | Placebo Number (%) | Significance |
| Mycological cure (negative culture and KOH) at follow-up | 10-24 (67-95) | 1-13 (13-60%) | Not specified for 81 T P <0.03 for others |
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up | 9-23 (60-80%) | 1-12 (7-33%) | Not specified for 81 T P <0.006 for others |
1 Range of values represents the highest and lowest values noted across the studies represented.
TABLE 24 Combined results of active-controlled studies terbinafine 1% cream studies in tinea pedis
| Primary Endpoints | Terbinafine Number (%) | Active control Number (%) | ||
| Mycological cure (negative culture and KOH) at follow-up: | ||||
| Vs clotrimazole cream | 116 (91%) | 98 (78%) | ||
| Vs ketoconazole cream | 68 (100%) | 66 (96%) | ||
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up: | ||||
| Vs clotrimazole cream | 98 (75%) | 79 (61) | ||
| Vs ketoconazole | 61 (86%) | 58 (81%) | ||
| Effective treatment at follow-up is estimated from relapse data (0 relapse for terbinafine; 2 relapses for ketoconazole) | ||||
LAMISIL spray
Study demographics and trial design:
TABLE 25 Summary of patient demographics for terbinafine 1% spray clinical trials in tinea pedis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number ) | Mean age across studies (Range) | Gender | Race: Percent Caucasi an | |||
|---|---|---|---|---|---|---|---|---|---|
| SFF 301 | Multicenter, double-blind, vehicle-controlled, 2:1 randomization (terbinafine:vehi cle) | Terbinafine 1% spray once daily for 7 days; 7 wk follow-up | Entered 115 ITT 105 | 41 (18-81) | Male 51 Female 20 | 96% | |||
| Terbinafine solution vehicle as above | Entered 57 ITT 51 | 42 (18-75) | Male 35 Female 4 | 95% | |||||
| SFF 351 | Multicenter, double-blind, vehicle-controlled, 2:1 randomization (terbinafine:vehi cle) | Terbinafine 1% spray twice daily for 7 days; 7 wk follow-up | Entered 104 ITT 81 | 41 (12-83) | Male 47 Female 11 | 60% | |||
| Terbinafine solution vehicle as above | Entered 49 ITT 38 | 43 (25-72) | Male 18 Female 10 | 82% | |||||
| Study 309 | Terbinafine 1% spray twice daily for 7 days; vehicle 3 wk; 4 wk follow-up | Entered 348 ITT 311 | 47 (13-84) | Male 150 Female 67 | 98% | ||||
| Clotrimazole XXX twice daily for 4 wk; 4 wk follow-up | Entered 351 ITT 323 | 45 (12-85) | Male 147 Female 65 | 97% | |||||
Study Results:
Whether applied once or twice daily for one week or once daily for two weeks, LAMISIL 1% spray was significantly more effective than placebo in the treatment of Tinea pedis but was comparable to cotrimazole.
TABLE 26 Number (%) subjects with effective treatment (ET) or with both negative microscopy and culture (NM) at end of study
| Study No. | Treatment | Treatment regimen | Results |
| ET | NM | |||
| SFF 351 | LAMISIL Placebo | 1 week, b.i.d. | 66% 4% p<0.001 | 88% 14% p<0.001 |
| SFF 301 | LAMISIL Placebo | 1 week o.d. | 76% 21% p<0.001 | 85% 23% p<0.001 |
| SFF 309 | LAMISIL Cotrimazole | 1 week, b.i.d. | 83% 82% p=0.649 | 92% 91% p=0.411 |
Cutaneous Candidiasis
LAMISIL cream
Study demographics and trial design:
TABLE 27 Summary of patient demographics for terbinafine 1% cream clinical trials in cutaneous candidiasis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age across studies (Range) | Gender | Race: Percent Caucasian | ||
|---|---|---|---|---|---|---|---|---|
SF 1003 SF 1004 | Randomized , double-blind, single-center, vehicle controlled | Terbinafine 1% cream, once daily for 1 wk; 3 wk follow-up | Entered 69 Evaluable 63 | 35-40 (6 to 78) | Male 31 Female 32 | Black or Mestiza and Caucasian | ||
| Terbinafine 1% cream vehicle , once daily for 1 wk; 3 wk follow-up | Entered 67 Evaluable 63 | 34-37 (13-81) | Male 44 Female 19 | |||||
Study results:
TABLE 28 Combined results of vehicle-controlled studies terbinafine 1% cream studies in cutaneous candidiasis
| Primary Endpoints | Terbinafine Number (%) | Placebo Number (%) | Significance |
| Mycological cure (negative culture and KOH) at follow-up | 22-25 (86-73%) | 9-11 (28-61%) | NS |
| Effective treatment (mycological cure and no to minimal signs or symptoms) at follow-up | 22-23 (71-72%) | 1-7 (3-23%) | P <0.001 in both studies |
p-values and results for effective treatment at follow-up are based on ITT population
The efficacy of one week of once-daily treatment with terbinafine 1% cream in cutaneous candidiasis is shown by the significantly greater rate of combined mycological and clinical outcomes, even 3 weeks post-treatment. While mycological cures were not significantly different between treatment groups post-treatment, they were significantly different at the end of treatment. Even though mycological cure appeared to decrease post-treatment, the rates of clinical cure (negative mycology and minimal signs and/or symptoms) increased. In study SF1003, complete clinical cure was noted for 3 terbinafine patients at end of treatment and 15 at Week 4. In study SF1004 for the terbinafine group, there was 1 complete cure at end of treatment but 17 at Week 4. No such increase in complete cures was noted in the vehicle group.
Tinea Versicolor
LAMISIL spray
Study demographics and trial design:
TABLE 29 Summary of patient demographics for terbinafine 1% spray clinical trials in tinea versicolor
| Study # | Trial design | Dosage, route of administratio n and duration | Study subjects (n=number ) | Mean age across studies (Range) | Gender | Race: Percent Caucasi an | ||
|---|---|---|---|---|---|---|---|---|
| SFF 305 | Randomized, multicenter, double-blind, vehicle-controlled (2:1 terbinafine:ve hicle) | Terbinafine 1% spray twice daily for 7 days; 7 wk follow-up | Entered 79 ITT 76 | 34 (16-68) | Male 39 Female 37 | 89% | ||
| Terbinafine solution vehicle twice daily for 7 days; 7 wk follow-up | Entered 36 ITT 34 | 32 (15-72) | Male 20 Female 14 | 91% | ||||
| Study # | Trial design | Dosage, route of administratio n and duration | Study subjects (n=number ) | Mean age across studies (Range) | Gender | Race: Percent Caucasi an | |||
|---|---|---|---|---|---|---|---|---|---|
| SFF 353 | Randomized, multicenter, double-blind, vehicle-controlled (2:1 terbinafine:ve hicle) | Terbinafine 1% spray twice daily for 7 days; 7 wk follow-up | Entered 109 ITT 97 | 34 (14-67) | Male 47 Female 50 | 84% | |||
| Terbinafine solution vehicle twice daily for 7 days; 7 wk follow-up | Entered 49 ITT 47 | 34 (14-59) | Male 26 Female 21 | 81% | |||||
Study Results:
When compared to placebo treatment, a one week twice daily application of LAMISIL 1% solution spray was significantly more effective in the treatment of Pityriasis versicolor. Treatment was effective in 70% of LAMISIL treated patients compared to 32% patients who used placebo (p<0.001). At the end of the study there was also a significant difference between the numbers of patients with negative microscopy, who had received LAMISIL treatment (79%) compared to the placebo treated (44%) [p<0.001].
TABLE 30 Number (%) subjects with effective treatment (ET – primary variable1) or negative microscopy (NM) at end of study
| Study | Treatment | Number of patients (%) | |||
| ET | NM | ||||
| SFF 305 | LAMISIL Placebo | 52 (70%) 11(32%) p<0.001 | 58 (79%) 15 (44%) p<0.001 | ||
| SFF 353 | LAMISIL Placebo | 75 (77%) 13 (28%) p<0.001 | 76 (78%) 14 (30%) p<0.001 | ||
1Effective treatment is defined as negative microscopy and a total sign/symptom score of 0 or 1.
15 MICROBIOLOGY
In vitro
The minimum inhibitory concentrations (MICs) of terbinafine were determined by serial dilution tests against yeasts, molds, dermatophytes, the mycelial form of Candida albicans, Pityrosporum spp., and Sporothrix schenkil. The spectrum and MIC values obtained for the various species and strains of fungi at different research laboratories (summarized as a range of activity in the following table) demonstrate that terbinafine possesses a high activity against dermatophytes, aspergilli, and dimorphous or dermatiaceous fungi. The susceptibility of blastospores of various species and strains of yeasts to terbinafine is much lower with MIC's ranging from 0.1 to > 128 μg/ml. The efficacy of terbinafine against 2 clinically important yeasts was confirmed by an evaluation of the susceptibility of 78 clinical isolates of Candida albicans and 20 of Candida parapsilosis. Blastophores of the Candida parapsilosis were more sensitive than those of Candida albicans, but the mycelial growth form of the Candida albicans (considered the pathogenic form) was the most sensitive form (MIC 50 = 0.195 µg/mL).
TABLE 31 Summary of results published on in vitro activities of terbinafine against pathogenic and opportunistic fungi
| Fungus | MIC range (µg/mL) |
I. Dermatophytic Fungi Trichophyton mentagrophytes rubrum rubrum verrucosum Epidermophyton floccosum Microsporum canis Microsporum gypseum Microsporum persicolor | 0.001-0.01 0.001- 0.01 0.001- 0.006 0.001-<0.06 0.005-0.01 0.005-0.01 0.002-0.003 |
II. Filamentous Fungi Aspergillus spp. Aspergillus flavus Aspergillus fumigatus Aspergillus niger Aspergillus terreus Pseudallescheria boydii Mucor, Rhizopus spp. Acremonium spp. Curcularia fallax Fusarium spp. Hendersonula toruloidea Lasiodiplodia theobromae Paecilomycea spp. Scopulariopsis brevicaulis Scytalidium hyalinum | 0.005-5.0 0.01-0.5 0.02-5.0 0.005-0.5 0.05-5.0 32.00->64.0 64.0->128.00 1.0-4.0 0.25-0.5 32.0->64.0 1.0-4.0 0.25-0.5 8.0-64.0 0.5-8.8 1.0-4.0 |
III. Dimorphic Fungi Blastomyces dermatitidis Histoplasma capsulatum Sporothrix schenckii | □ 0.05-0.39 □ 0.05-0.2 □ 0.05-2.0 |
IV. Pathogenic Yeasts Candida albicans (yeast form) Candida albicans (mycelial form) Candida parapsilosis Candida tropicalis Candida pseudotropicalis Candida krusei Candida guilliermondii Candida glabrata (T.glabrata) Cryptococcus neoformans Pityrosporum spp. | 6.25->128.0 0.098-0.78 0.1-3.13 10.0-128.0 0.5-50.0 50.0->100.0 6.25-100.0 >100.0->128.0 0.25-2.0 0.2-0.8 |
V. Dematiacese Phaechyphomycosis complex* Chromoblastomycosis complex** | <0.06- 0.5 □ 0.06-2.0 |
* = Exophiala jeanselmei, Wangiella dermatitidies, Cladosporium bantianum
** = Fonseceas pedrosoi, Phialophora spp.
Terbinafine was primarily fungicidal against T. mantagrophytes, M. canis, A. fumigatus, Sc. brevicaulis, S. schenkii, and C. parapsilosis, and fungistatic against C. albicans.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
- Acute Toxicity:
TABLE 32 ACUTE TOXICITY
| Species | Sex | Route | LD50 |
| Mouse | M,F | Oral | >4 g/kg |
M,F M,F | i.v. 1% solution orally | 393 mg/kg > 250 mg/kg | |
| Rat | M,F | Oral | >4 g/kg |
| M,F | i.v. | 213 mg/kg | |
M,F M,F | 1% cream orally 1% solution orally | 25 mg/kg (no mortalities) >200 mg/kg | |
| Rabbits | M,F | Topical (suspension) | >1.5 g/kg |
- Long Term Toxicity:
TABLE 33 LONG-TERM TOXICITY
| SPECIES | LENGTH OF ADMIN. | ROUTE | DOSES (mg/kg) | RESULTS |
| RAT | 26 weeks | oral | 0, 30, 100, & 300 | ↑ in liver weights in the mid & high dose groups; ↑ in kidney and heart weights in high dose group; ↑adrenal weight all dose groups. In all animals allowed a recovery period organ weights showed signs of reversibility. At all doses males showed ↑ incidence & severity of spontaneous nephropathy. At mid & high doses, livers of female rats showed enlargement of centrilobular hepatocytes. Histological evidence of recovery in liver but not in kidney on cessation of treatment. |
| 52 weeks | oral | M: 6.9, 20, 68 F: 9.3, 28, 95 | Reversible ↑ in kidney weight in mid and high-dose males and liver weight in high dose females. No histopathological organ or tissue changes or evidence of drug-related tumorigenesis. No proliferation of smooth endoplasmic reticulum or peroxisomes. No-toxic-effect level in males 68 mg/kg; in females 95 mg/kg. | |
| Pre and Post pubertal RATS | 55 days | oral | 0, 25, 75, 250 | In 15 day old rats treated until 70 days of age, the mid and high doses were toxic as shown by death of some animals at these dose levels. Reduction in mean body weight gain was also seen in these dose groups. |
| Juvenile RATS | 55 days | oral | 0, 10, 25, 45, 100 | Well tolerated in rats treated from 15 to 70 days of age. 1 death in low dose group. Slight increase in liver weights of high dose females. |
| DOGS | 26 weeks | oral | 0, 20, 60, 200 | Initial hypersalivation in mid and high dose groups; sporadic emesis in high dose group. Haematological parameters remained unchanged throughout experiment. At end of treatment livers of 3 of 4 high dose dogs contained lamellated intracytoplasmic inclusions. The no-toxic-effect level was 60 mg/kg. |
| 52 weeks | oral | 0, 10, 25, 100 | Mid and high dose groups showed sporadic emesis and slightly inhibited body weight gain. High dose groups showed sporadic hypersalivation and reduced food intake. Females of all dose groups showed slightly lower triglyceride values. | |
| RABBITS | 4 weeks | topical (2%cream) | 10, 20, 40 | Moderate reactions (erythema) at the application site. |
| 4 weeks | topical (1% solution) | 0, 5, 15, 30 | Skin site showed erythema, edema and papules in all groups including placebo controls. | |
| 26 weeks | topical (1% & 2%cream) | 10, 20, 40 | Slight erythema and edema in all groups including placebo controls. |
TABLE 34 Carcinogenicity:
| SPECIES | DURATION | ROUTE | DOSES (mg/kg) | RESULTS |
| MICE | 100 weeks | oral | M: 14, 40, 130 F: 16, 60, 156 | There was a slight inhibition of body weight gain in the mid- and high-dose females. Macroscopic and microscopic examinations revealed no neoplastic or other findings which were attributable to treatment with terbinafine. |
| RATS | 123 weeks | oral | M: 6.9, 20, 69 F: 9.6, 28, 97 | Ophthalmoscopy revealed an ↑ in incidence of cataracts in males at high doses. No treatment related cataract changes occurred after 52 weeks, and such eye changes are known to occur spontaneously in old rats. ↑ incidence of enlarged swollen livers and liver nodules in the high dose animals, particularly males. Slight ↑ incidence of hepatocellular tumours in the high dose males. Females of the high dose group showed a slightly greater incidence and extent of hepatocellular necrosis, suggesting the high dose was at the threshold of a toxic response. |
Mutagenicity
In vitro and in vivo mutagenicity testing revealed no specific mutagenic or genotoxic properties of terbinafine. In vitro tests of cell transformation to malignancy were negative.
Genotoxicity: Additional studies
The following additional chronic toxicity and genotoxicity studies were performed to investigate the findings of the life -time rat study and their relevance to man.
4-week oral toxicity study in rats with special emphasis on hepatic alterations
TABLE 35 4-Week oral toxicity study in rats with special emphasis on hepatic alterations
| SPECIES | DURATION |
| ROUTE | |
| DOSES (mg/kg) | |
| RAT | 4 weeks |
| oral | |
| M: 100, 465; F: 108, 530 | |
| RESULTS | |
| FEED INTAKE & BODY WEIGHT GAIN | Only at the high dose level were significant decreases in food intake and body weight gain recorded. |
| CLINICAL CHEMISTRY | At the high-dose level reduced serum glucose (both sexes) and serum triglyceride levels (both sexes) and increased SGPT, SAP (females), and BUN (males) were seen. Significantly lower corticosterone plasma levels were found in high-dose animals and higher testosterone and estradiol plasma levels in low-dose males and females respectively. |
| LIVER MEASUREMENTS | Increased cytochrome P-450 content (high dose males) cytochrome b5 contents (high dose males and females), cytochrome b5 reductase activity (high dose males), 7-ethoxy-coumarin-O-deethylase activity (per mg cytochrome P-450; in low- and high-dose females), and peroxisomal palmitoyl-CoA epoxidase activity (low dose females and high dose males and females). Determination of liver compartments indicated a slight reduction of water content (high dose males), an unchanged protein content, and an increased lipid moiety (low dose males and high-dose males and females). |
| POSTMORTEM FINDINGS | Increased absolute and relative liver, and relative kidney weights (high dose males and females), mild hepatic centrilobular hypertrophy (high-dose only), increase in peroxisome numbers, and abnormal peroxisome shape (high-dose males). Slight increase in hepatic peroxisome size and number (high dose males and females). In high-dose group, numerous abnormal peroxisomes were found in both sexes, as well as a slight proliferation of the SER. |
Effects of 13-week treatment on selected toxicological variables in rats
TABLE 36 EFFECTS OF A 13-WEEK TREATMENT ON SELECTED TOXICOLOGICAL VARIABLES IN RATS
| SPECIES | DURATION | ROUTE | DOSES (mg/kg) | RESULTS |
| RATS | 13 weeks | oral | M: 72 F: 102 | Slight decrease in serum triglycerides (significant in males only), slight increase in albumin (females); these changes were observed in test weeks 5 and 8 only. Relative liver weights were increased as was palmitoyl-CoA epoxidase activity. There was no evidence of hepatic peroxisomal morphological abnormalities; however peroxisome numbers were increased in both sexes. |
4-week oral toxicity study in mice
TABLE 37 4-WEEK ORAL TOXICITY STUDY IN MICE
| SPECIES | DURATION | ROUTE | DOSES (mg/kg) | RESULTS |
| MICE | 4 weeks | oral | M: 103, 510 F: 107, 512 | Slightly impaired liver function in males only. Slight induction of the cytochrome P-450 and b5 systems was seen (biologically relevant only at the high-dose level and more marked in males than females), as well as ethoxycoumarin-O-deethylase activity. The peroxisomal marker palmitoyl-CoA-epoxidase was slightly increased at all dose levels (in both sexes); no changes in the size or number of perosixomes were seen. There seemed to be a link between the degree of induction of some major hepatic enzyme systems and the moderate hepatic centrilobular hypertrophy observed histologically (and more generally the liver weight increases). Endocrinological examinations revealed higher basal corticosterone levels in a number of low and high-dose animals. |
Preliminary toxicity study in monkeys
TABLE 38 PRELIMINARY TOXICITY STUDY IN MONKEYS
| SPECIES | DURATION | ROUTE | DOSES (mg/kg) | RESULTS |
| MONKEYS | 28 days | by gavage | 500 | Emesis and hypersalivation were observed on several occasions. The female showed consistent weight loss during the first 3 weeks and slight recovery thereafter. Liver weights were increased in both the treated animals, but there were no histopathological changes. No treatment-related changes in the peroxisome population or general cellular ultrastructure were seen. Increased activity of hepatic palmitoyl CoA-epoxidase indicated increased peroxisomal fatty oxidation. Cytosolic epoxide hydrolase activity was below detectable limit. |
32-week oral toxicity in monkeys
TABLE 39 WEEK ORAL TOXICITY STUDY IN MONKEYS
| SPECIES | DURATION | ROUTE | DOSE (mg/kg) | RESULTS |
| MONKEY | 32 weeks | Oral | 0, 150, 300 | Eye lesions were seen after 26 weeks of treatment. Ophthalmoscopy revealed white spots on the retina in mid and high dose animals. No similar changes were seen at earlier examination. No morphological changes were seen in any layer of the retina. After withdrawal of terbinafine, the changes described recover fully (after a 13 week recovery period). |
TABLE 40 Reproductive and Developmental Toxicology:
| SPECIES | DURATION | ROUTE OF ADMIN. | DOSES (mg/kg) | RESULTS |
| RATS | Fertility & Reproduction Study M: 63 days prior to mating F: 14 days prior to mating to weaning | oral | 10, 50, 250 | In the high dose group a lower pregnancy rate, mean number of implants and living pups per dam were observed as well as a high pre- and perinatal offspring mortality. Physical and functional development of the offspring was also retarded. The fertility and general reproductive performance of the offspring were normal at all dose levels tested. |
Embryotoxicity study Days 6 to 15 postcoitum | oral | 30, 100, 300 | Inseminated female rats treated with terbinafine tolerated doses up to 100 mg/kg well. Lower body weight gain was seen at 300 mg/kg. No embryolethal or teratogenic effects were seen. | |
Peri & post-natal study Day 15 postcoitum to day 21 postpartum | oral | 30, 100, 300 | Inseminated female rats treated with terbinafine tolerated all doses well. No clinical signs or relevant reproductive changes in any group. | |
Embryotoxicity study Day 6 to 15 postcoitum | subcutaneous | 10, 30, 100 | In the high dose group dams gained less body weight and had skin irritation at the injection site. A tendency to lower body weight gains was also noted in the mid-dose group. No adverse effects observed on pregnancy or embryonic or fetal development in any group. | |
| RABBITS | Embryotoxicity study Day 6 to 18 postcoitum | oral | 30, 100, 300 | Inseminated female rabbits treated with terbinafine tolerated doses up to 100 mg/kg well. In the high-dose group weight loss was observed in some dams, 2 of which had to be euthanized due to poor health. No relevant reproductive alterations were seen at any dose level. |
Test for tumour-initiating activity in the rat liver foci bioassay
After partial hepatectomy, rats were treated with a single oral dose of 1 g/kg terbinafine (controls were treated with N-nitrosomorpholine [NNM]) followed by an 8-week treatment with phenobarbital (for promotion of growth of putative preneoplastic foci). A significant increase in foci/cm was seen only in NNM-treated animals in comparison with the respective control groups. No differences were observed between control animals (treated only with phenobarbital) and those treated with terbinafine plus phenobarbital. It was concluded that terbinafine did not have tumour-initiating potential even in combination with a tumour promoting agent.
Autoradiographic determination of the induction of DNA repair/synthesis and cell replication in rat hepatocyte primary cultures after in vivo treatment
No evidence was found for any induction of either DNA repair or DNA replication in the hepatocytes from terbinafine treated rats, and the frequency of replicating nuclei were in the control range.
Mutagenicity test using Salmonella typhimurium
Liver fractions from male rats treated for 13 weeks with 69 mg/kg/day of terbinafine and non-treated control rats were used to evaluate terbinafine for genetic activity. There was no evidence that repeated treatment of rats with terbinafine induces enzymes capable of producing mutagenic intermediates of terbinafine.