


Product Monograph - Lansoprazole (Sanis Health)
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................... 2
TABLE OF CONTENTS ................................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
1 INDICATIONS ....................................................................................................................... 4
1.1 Pediatrics .............................................................................................................................. 4
1.2 Geriatrics............................................................................................................................... 4
2 CONTRAINDICATIONS .......................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ......................................................................................... 5
4.1 Dosing Considerations .......................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................................... 5
4.4 Administration ...................................................................................................................... 6
4.5 Missed Dose .......................................................................................................................... 8
5 OVERDOSAGE ...................................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................................... 8
7 WARNINGS AND PRECAUTIONS ......................................................................................... 10
7.1 Special Populations ............................................................................................................. 14
7.1.1 Pregnant Women ............................................................................................................. 14
7.1.2 Breast-feeding .................................................................................................................. 14
7.1.3 Pediatrics ......................................................................................................................... 15
7.1.4 Geriatrics .......................................................................................................................... 15
8 ADVERSE REACTIONS......................................................................................................... 15
8.1 Adverse Reaction Overview ................................................................................................ 15
8.2 Clinical Trial Adverse Reactions ........................................................................................... 15
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .................................................................... 21
8.3 Less Common Clinical Trial Adverse Reactions .................................................................... 22
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .......................................................................................................................................... 23
8.5 Post-Market Adverse Reactions .......................................................................................... 24
9 DRUG INTERACTIONS ........................................................................................................ 25
9.2 Drug Interactions Overview ................................................................................................ 25
9.4 Drug-Drug Interactions ....................................................................................................... 26
9.5 Drug-Food Interactions ....................................................................................................... 30
9.6 Drug-Herb Interactions ....................................................................................................... 30
9.7 Drug-Laboratory Test Interactions ...................................................................................... 30
10 CLINICAL PHARMACOLOGY ................................................................................................ 30
10.1 Mechanism of Action ........................................................................................................ 30
10.2 Pharmacodynamics ........................................................................................................... 30
10.3 Pharmacokinetics .............................................................................................................. 33
11 STORAGE, STABILITY AND DISPOSAL.................................................................................. 37
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................... 37
PART II: SCIENTIFIC INFORMATION ......................................................................................... 38
13 PHARMACEUTICAL INFORMATION .................................................................................... 38
14 CLINICAL TRIALS ................................................................................................................ 39
14.1 Clinical Trials by Indication ................................................................................................ 39
14.1.1 Symptomatic Gastroesophageal Reflux Disease (GERD) ................................................ 39
14.1.2 Reflux Esophagitis .......................................................................................................... 44
14.1.3 Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome ............. 48
14.3 Comparative Bioavailability Studies .................................................................................. 51
15 MICROBIOLOGY ................................................................................................................. 55
16 NON-CLINICAL TOXICOLOGY .............................................................................................. 55
17 SUPPORTING PRODUCT MONOGRAPHS ............................................................................ 66
PATIENT MEDICATION INFORMATION .................................................................................... 67
PATIENT MEDICATION INFORMATION .................................................................................... 74
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
LANSOPRAZOLE (lansoprazole delayed-release capsules) and LANSOPRAZOLE FDT (lansoprazole fast-disintegrating, delayed-release tablets) are indicated in the treatment of conditions where a reduction of gastric acid secretion is required, such as:
- Reflux esophagitis including patients with Barrett's esophagus, and patients poorly responsive to an adequate course of therapy with histamine H2-receptor antagonists
- Symptomatic Gastroesophageal Reflux Disease (GERD); treatment of heartburn and other symptoms associated with GERD
- Pathological hypersecretory conditions including Zollinger-Ellison Syndrome (4.2 Recommended Dose and Dosage Adjustment)
1.1 Pediatrics
Pediatrics (6 to 17 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of lansoprazole in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 7.1.3 Pediatrics).
LANSOPRAZOLE and LANSOPRAZOLE FDT is indicated for treatment of erosive and non-erosive GERD in children, aged 6 to 17 years. The clinical trial treatment period did not extend beyond 12 weeks.
1.2 Geriatrics
Geriatrics (>65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. The daily dose should not exceed 30 mg (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
- Lansoprazole is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Co-administration with rilpivirine is contraindicated. See 9.4 Drug-Drug Interactions.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Patients should use the lowest dose and shortest duration of proton pump inhibitor (PPI) therapy appropriate to the condition being treated.
- Withdrawal of long-term PPI therapy can lead to aggravation of acid related symptoms and may result in rebound acid hypersecretion.
4.2 Recommended Dose and Dosage Adjustment
Reflux Esophagitis or Poorly Responsive Reflux Esophagitis Including Patients with Barrett’s Esophagus
- The recommended adult oral dose is 30 mg once daily before breakfast for 4 to 8 weeks (see 1 INDICATIONS).
Maintenance Treatment of Healed Reflux Esophagitis
- For the long-term management of patients with healed reflux esophagitis, 15 mg lansoprazole given once daily before breakfast has been found to be effective in controlled clinical trials of 12 months (see 14 CLINICAL TRIALS).
- The recommended adult oral dose of LANSOPRAZOLE or LANSOPRAZOLE FDT for maintenance treatment of patients with healed reflux esophagitis is 15 mg once daily before breakfast (see 1 INDICATIONS).
Treatment and Maintenance of Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome
- The dosage of LANSOPRAZOLE or LANSOPRAZOLE FDT in patients with pathologic hypersecretory conditions varies with the individual patient. Doses should be adjusted to individual patient needs and should continue for as long as clinically indicated.
- The recommended adult oral starting dose is 60 mg once a day. Dosages up to > 180 mg per day have been administered. Daily dosages of greater than 120 mg should be administered in divided doses.
- Some patients with Zollinger-Ellison Syndrome have been treated continuously with lansoprazole for more than 12 years (see 14 CLINICAL TRIALS, Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome).
Gastroesophageal Reflux Disease (GERD)
- Short-Term Treatment of Symptomatic GERD: The recommended adult oral dose for the treatment of heartburn and other symptoms associated with GERD is 15 mg once daily before breakfast for up to 8 weeks.
- If significant symptom relief is not obtained within 4 to 8 weeks, further investigation is recommended.
Pediatric GERD (erosive and non-erosive esophagitis)
- In clinical studies, lansoprazole was not administered beyond 12 weeks in 6 to 11 year olds. It is not known if lansoprazole is safe and effective if used longer than the recommended duration. Do not exceed the recommended dose and duration of use in children as outlined below.
- Children (6 to 11 years): The recommended pediatric oral dose is 15 mg (≤ 30 kg) and 30 mg (>30 kg) once daily for up to 12 weeks.
- Children (12 to 17 years): The same approved regimen for adults can be used.
Patients with Hepatic Impairment
- The daily dose of LANSOPRAZOLE or LANSOPRAZOLE FDT should not exceed 30 mg (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Patients with Renal Impairment
- No dosage modification of LANSOPRAZOLE or LANSOPRAZOLE FDT is necessary (see 7 WARNINGS AND PRECAUTIONS, Renal).
Elderly Patients
- The daily dose should not exceed 30 mg (see 7.1.4 Geriatrics).
4.4 Administration
LANSOPRAZOLE and LANSOPRAZOLE FDT should be taken daily before breakfast. Where the product may be used twice daily, it should be taken prior to breakfast and another meal. LANSOPRAZOLE capsules and LANSOPRAZOLE FDT SHOULD NOT BE CRUSHED, CHEWED, BROKEN OR CUT.
LANSOPRAZOLE capsules should be swallowed whole with sufficient water before meal.
LANSOPRAZOLE FDT Tablets - Oral:
LANSOPRAZOLE FDT tablets are available in 15 mg and 30 mg strengths. LANSOPRAZOLE FDT should not be broken, cut or chewed. Place the tablet on the tongue and allow it to disintegrate with or without water until the particles can be swallowed. The tablet typically disintegrates in less than 1 minute. LANSOPRAZOLE FDT tablets are not designed to be swallowed intact or chewed.
Do not chew the granules.
Alternatively, for children or other patients who have difficulty swallowing tablets, LANSOPRAZOLE FDT can also be delivered in two different ways.
LANSOPRAZOLE FDT — Oral Syringe:
For administration via oral syringe, LANSOPRAZOLE FDT can be administered as follows:
- Place a 15 mg tablet in an oral syringe and draw up approximately 4 mL of water, or place a 30 mg tablet in an oral syringe and draw up approximately 10 mL of water.
- Shake gently to allow for a quick dispersal.
- After the tablet has dispersed, administer the contents within 15 minutes.
- Refill the syringe with approximately 2 mL (5 mL for the 30 mg tablet) of water, shake gently, and administer any remaining contents.
LANSOPRAZOLE FDT — Nasogastric Tube Administration ( ≥ 10 French):
For administration via a nasogastric tube, LANSOPRAZOLE FDT can be administered as follows:
- Place a 15 mg tablet in a syringe and draw up 5 mL of water, or place a 30 mg tablet in a syringe and draw up 10 mL of water.
- Shake gently to allow for a quick dispersal.
- After the tablet has dispersed, inject through the nasogastric tube into the stomach within 15 minutes.
- Refill the syringe with approximately 5 mL of water, shake gently, and flush the nasogastric tube.
4.5 Missed Dose
If a dose of this medication is missed, patients should be instructed to take it as soon as possible. However, if the next scheduled dose is due, the patient should not take the missed dose, and should be instructed to take the next dose on time. Patients should be instructed not to take two doses at one time to make up for a missed dose.
5 OVERDOSAGE
As in all cases where overdosing is suspected, treatment should be supportive and symptomatic. Any unabsorbed material should be removed from the gastrointestinal tract, and the patient should be carefully monitored. Lansoprazole is not removed from the circulation by hemodialysis. In one reported case of overdose, the patient consumed 600 mg of lansoprazole with no adverse reaction.
Oral doses up to 5000 mg/kg in rats (approximately 1300 times the recommended human dose based on body surface area) and mice (about 675.7 times the recommended human dose based on body surface area) did not produce deaths or any clinical signs.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1. Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Capsule (delayed-release) 15 mg and 30 mg | Corn starch, D&C red #28, FD&C blue #1, FD&C red #40, FD&C yellow #6 (15 mg capsules only), gelatin, hydroxypropyl cellulose, iron oxide black (30 mg capsules only), magnesium carbonate, methacrylic acid copolymer, polyethylene glycol 6000, polysorbate 80, silicon dioxide, sucrose, sugar spheres, talc, titanium dioxide, white imprinting ink (butyl alcohol, dehydrated alcohol, isopropyl alcohol, povidone, propylene glycol, shellac, sodium hydroxide and titanium dioxide). |
| Oral, nasogastric | Tablet (fast-disintegrating, delayed-release) 15 mg and 30 mg | Aspartame*, citric acid monohydrate, crospovidone, hydroxypropyl cellulose, iron oxide red, iron oxide yellow, magnesium carbonate, magnesium stearate, mannitol, |
methacrylic acid-ethylacrylate copolymer, microcrystalline cellulose, polyethylene glycol, polysorbate, sodium bicarbonate, sodium hydroxide, sodium lauryl sulphate, sodium starch glycolate, strawberry flavour, sugar spheres, talc, triethyl citrate. * Phenylketonurics: Contains Phenylalanine which is a component of aspartame (3.37 mg per 15 mg tablet and 6.74 mg per 30 mg tablet) | ||
LANSOPRAZOLE
LANSOPRAZOLE (lansoprazole delayed-release capsules) is supplied in delayed-release capsules for oral administration. The delayed-release capsules contain the active ingredient, lansoprazole, in the form of enteric-coated granules and are available in two dosage strengths: 15 mg and 30 mg of lansoprazole per capsule.
LANSOPRAZOLE (lansoprazole delayed-release capsules) is available as follows:
15 mg: Pink and green capsule filled with white to off white pellets, imprinted axially with 'MYLAN' over 'LR 15' on both cap and body in white ink. The capsules are available in bottles of 30’s and 100’s.
30 mg: Pink and black capsules filled with white to off white pellets, imprinted axially with 'MYLAN' over 'LR 30' on both cap and body in white ink. The capsules are available in bottles of 30’s, 100’s, and 500’s.
LANSOPRAZOLE FDT
LANSOPRAZOLE FDT (lansoprazole fast-disintegrating, delayed-release tablets) contain the active ingredient, lansoprazole in the form of enteric-coated microgranules. The tablets are available in 15 mg and 30 mg dosage strengths.
LANSOPRAZOLE FDT (lansoprazole fast-disintegrating, delayed-release tablets) is available as follows:
15 mg: White to yellowish white round, flat faced bevelled edged tablet engraved with ‘LP1’ on one side and ‘M’ on the other side with orange to dark brown speckles. The tablets are available in bottles of 30’s, 100’s and cartons of 30’s.
30 mg: White to yellowish white round, flat faced bevelled edged tablet engraved with ‘LP2’ on one side and ‘M’ on the other side with orange to dark brown speckles. The tablets are available in bottles of 30’s, 100’s and cartons of 30’s.
7 WARNINGS AND PRECAUTIONS
General
Gastric Malignancy: Symptomatic response to therapy with lansoprazole delayed-release capsules or lansoprazole delayed-release tablets does not preclude the presence of gastric malignancy.
Clostridium Difficile-Associated Diarrhea: Decreased gastric acidity due to any means, including proton pump inhibitors (PPIs), increases gastric counts of bacteria normally present in the gastrointestinal tract. Treatment with PPIs can lead to an increased risk of gastrointestinal infections such as Salmonella, Campylobacter and Clostridium difficile.
An increased risk for Clostridium difficile infection (CDI) and Clostridium difficile-associated diarrhea (CDAD) has been observed in association with PPI use in several observational studies. CDI/CDAD should be considered in the differential diagnosis for diarrhea that does not improve. Additional risk factors for CDI and CDAD include recent hospitalization, the use of antibiotics, old age and the presence of co-morbidities.
Patients should be prescribed PPIs at the lowest dose and for the shortest duration required for the condition being treated and be reassessed to ascertain whether continued PPI therapy remains beneficial.
Concomitant Use with Methotrexate: Literature suggests that concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite, possibly leading to methotrexate toxicities. A temporary withdrawal of the PPI may be considered in some patients receiving treatments with high dose methotrexate (see 9.4 Drug-Drug Interactions).
Carcinogenesis and Mutagenesis
Analysis of gastric biopsy specimens from patients after short-term treatment of PPIs have not detected ECL cell effects similar to those seen in animal studies. Longer term studies in humans revealed a slight increase in the mean ECL-cell density, although there was no microscopic evidence of cell hyperplasia. Similar results were seen in the maintenance treatment studies, where patients received up to 15 months of lansoprazole therapy. Serum gastrin values increased significantly from their baseline values but reached a plateau after 2 months of therapy. By 1 month post-treatment, fasting serum gastrin values returned to lansoprazole therapy baseline. Moreover, results from gastric biopsies from short-term, long-term and maintenance treatment studies indicate that there are no clinically meaningful effects on gastric mucosa morphology among lansoprazole-treated patients.
Dexlansoprazole has shown genotoxic and carcinogenic potential in experimental animals. For further details, see 16 NON-CLINICAL TOXICOLOGY.
Drug Interactions with Antiretroviral Drugs
PPIs have been reported to interact with some antiretroviral drugs. The clinical importance and the mechanisms behind these interactions are not always known. A change in gastric pH may change the absorption of the antiretroviral drug. Other possible mechanisms are via CYP2C19 (see 9.4 Drug-Drug Interactions).
Rilpivirine: Co-administration is contraindicated due to significant decrease in rilpivirine exposure and loss of therapeutic effect (see 2 CONTRAINDICATIONS).
Atazanavir and Nelfinavir: Co-administration with atazanavir or nelfinavir is not recommended due to decreased atazanavir or nelfinavir exposure (see the REYATAZ® and VIRACEPT® Product Monographs).
If the combination of LANSOPRAZOLE or LANSOPRAZOLE FDT with atazanavir is judged unavoidable, close clinical monitoring is recommended in combination with the use of 400 mg atazanavir/100 mg ritonavir dose; the dose of LANSOPRAZOLE or LANSOPRAZOLE FDT should not exceed an equivalent dose of omeprazole of 20 mg daily (see REYATAZ® Product Monograph).
Saquinavir: If LANSOPRAZOLE or LANSOPRAZOLE FDT is co-administered with saquinavir/ritonavir, caution and monitoring for potential saquinavir toxicities, including gastrointestinal symptoms, increased triglycerides, deep vein thrombosis and QT prolongation, are recommended. Dose reduction of saquinavir should be considered from the safety perspective for individual patients (see INVIRASE® Product Monograph).
Endocrine and Metabolism
Hypomagnesemia: Hypomagnesemia, symptomatic and asymptomatic, has been reported rarely in patients treated with PPIs for at least three months, in most cases after a year of therapy. Serious adverse events include tetany, arrhythmias, and seizures. Hypomagnesemia may lead to hypocalcemia and/or hypokalemia (see 8.5 Post-Market Adverse Reactions). In most patients, treatment of hypomagnesemia (and hypomagnesemia associated hypocalcemia and/or hypokalemia) required magnesium replacement and discontinuation of the PPI.
For patients expected to be on prolonged treatment or who take PPIs with medications such as digoxin or drugs that may cause hypomagnesemia (e.g., diuretics), health care professionals may consider monitoring magnesium levels prior to initiation of PPI treatment and periodically (see 8
ADVERSE REACTIONS).
The chronic use of PPIs may lead to hypomagnesemia.
Cyanocobalamin (Vitamin B12) Deficiency: The prolonged use of PPIs may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of cyanocobalamin (Vitamin B12) deficiency.
Gastrointestinal
Long-term use of lansoprazole delayed-release capsules or lansoprazole delayed-release tablets is associated with an increased risk of fundic gland polyps, especially beyond one year (see 8.5 Post-Market Adverse Reactions). Most fundic gland polyps are asymptomatic. Use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Genitourinary
In the 24-month toxicology study in rats, after 18 months of treatment, Leydig cell hyperplasia increased above the concurrent and historical control level at dosages of 15 mg/kg/day or higher.
Testicular interstitial cell adenoma also occurred in 1 of 30 rats treated with 50 mg/kg/day (13 times the recommended human dose based on body surface area) in a 1-year toxicity study.
These changes are associated with endocrine alterations which have not been, to date, observed in humans. For further details, see 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity.
Hepatic/Biliary/Pancreatic
Use in Patients with Hepatic Impairment: It is recommended that the initial dosing regimen need not be altered for patients with mild or moderate liver disease, but for patients with moderate impairment, doses higher than 30 mg per day should not be administered unless there are compelling clinical indications. Dose reduction in patients with severe hepatic disease should be considered.
Immune
Severe Cutaneous Adverse Reactions: Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), acute generalized exanthematous pustulosis (AGEP) and erythema multiforme have been reported in association with the use of PPIs. Discontinue lansoprazole at the first signs or symptoms of SCARs or other signs of hypersensitivity and consider further evaluation. At the time of prescription, patients should be informed of the signs and symptoms, and advised to monitor closely for skin reactions. See 8.5 Post-Market Adverse Reactions.
Subacute cutaneous lupus erythematosus: Subacute cutaneous lupus erythematosus (SCLE) has been reported with the use of PPIs. If lesions occur, especially in sun-exposed areas of the skin, and if accompanied by arthralgia, the patient should seek medical help promptly and the health care professional should consider stopping LANSOPRAZOLE or LANSOPRAZOLE FDT. The occurrence of SCLE with previous PPI treatment may increase the risk of SCLE with other PPIs (see 8.5 Post-Market Adverse Reactions).
Monitoring and Laboratory Tests
During treatment with antisecretory drugs, Chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA levels may interfere with investigations for neuroendocrine tumours. To avoid this interference, LANSOPRAZOLE or LANSOPRAZOLE FDT treatment should be stopped 14 days before CgA measurements (see 9.7 Drug-Laboratory Test Interactions).
Musculoskeletal
Bone Fracture: Several published observational studies suggest that PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. The risk of fracture was increased in patients who received high-dose, defined as multiple daily doses, and long-term PPI therapy (a year or longer). Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated. Patients at risk for osteoporosis-related fractures should be managed according to established treatment guidelines (see 4 DOSAGE AND ADMINISTRATION and 8 ADVERSE REACTIONS).
Ophthalmologic
Retinal atrophy: In animal studies, retinal atrophy was observed in rats dosed orally for 2 years with lansoprazole at doses of 15 mg/kg/day and above. These changes in rats are believed to be associated with the effects of taurine imbalance and phototoxicity in a susceptible animal model.
Clinical data available from long-term lansoprazole delayed-release capsules studies are not suggestive of any drug-induced eye toxicity in humans. In humans, there are presently no concerns for ocular safety with short-term lansoprazole treatment and the risks associated with long-term use for nearly 5 years appear to be negligible.
The finding of drug-induced retinal atrophy in the albino rat is considered to be species-specific with little relevance for humans. For further details, see 16 NON-CLINICAL TOXICOLOGY.
Renal
No dosage adjustment of LANSOPRAZOLE or LANSOPRAZOLE FDT is necessary in patients with renal impairment. See 4.2 Recommended Dose and Dosage Adjustment and 10 CLINICAL PHARMACOLOGY.
Skin
See 7 WARNINGS AND PRECAUTIONS - Immune
Use in Women
Over 4000 women were treated with lansoprazole delayed-release capsules. The incidence rates of adverse events are also similar to those seen in males.
7.1 Special Populations
7.1.1 Pregnant Women
Reproductive studies conducted in pregnant rats at oral doses up to 150 mg/kg/day (40 times the recommended human dose based on body surface area), and in rabbits at oral doses up to
30 mg/kg/day (16 times the recommended human dose based on body surface area), revealed no lansoprazole-related impairment of fertility, fetal malformations or developmental toxicity to fetuses or suckling neonates. Lansoprazole is not considered to be teratogenic.
Maternal toxicity and a significant increase in fetal mortality were observed in the rabbit study at doses above 10 mg/kg/day. In rats, maternal toxicity and a slight reduction in litter survival and weights were noted at doses above 100 mg/kg/day. See Reproductive and Developmental Toxicology.
There are no adequate or well-controlled studies in pregnant women. Therefore, LANSOPRAZOLE or LANSOPRAZOLE FDT should be used with caution during pregnancy, only if the potential benefit justifies the potential risk to the fetus.
7.1.2 Breast-feeding
Lansoprazole or its metabolites are excreted in the milk of rats. It is unknown whether lansoprazole is excreted in human milk. Precaution should be exercised because many drugs can be excreted in human milk. Lansoprazole should not be given to nursing mothers unless its use is considered essential. In this case nursing should be avoided.
7.1.3 Pediatrics
Safety and effectiveness have been established in pediatric patients 1 to 17 years of age for short-term treatment of up to 12 weeks of symptomatic GERD and erosive esophagitis. Use of lansoprazole in this population is supported by evidence of adequate and well controlled studies of lansoprazole in adults with additional clinical, pharmacokinetic, pharmacodynamic, and safety studies performed in pediatric patients. The adverse events (AEs) profile in pediatric patients is similar to that of adults. There were no adverse events reported in U.S. clinical studies that were not previously observed in adults. Dose safety and effectiveness have not been established in patients < 1 year.
Developmental toxicity studies revealed that exposure to lansoprazole in juvenile rats starting at postnatal Days 7, 14, and 21 (approximately equivalent to neonatal, 1, and 2 year old human, respectively) resulted in development of heart valve thickening (see Juvenile Toxicity). However, the development of heart valve thickening has not been reported in pediatric clinical trials or in post-market reports.
7.1.4 Geriatrics
Benefits of use of PPIs should be weighed against the increased risk of fractures as patients in this category (> 71 years of age) may already be at high risk for osteoporosis-related fractures. If the use of PPIs is required, they should be managed carefully according to established treatment guidelines (see 4 DOSAGE AND ADMINISTRATION and 8 ADVERSE REACTIONS).
The incidence rates of adverse events and laboratory test abnormalities are also similar to those seen in other age groups. The initial dosing regimen need not be altered for elderly patients, but subsequent doses higher than 30 mg per day should not be administered unless additional gastric acid suppression is necessary.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common adverse drug reactions (occurring in at least 1% of subjects) reported in adult patients treated with lansoprazole delayed-release capsules in placebo and positive-controlled trials were headache, diarrhea, abdominal pain, nausea, and dizziness. The adverse reaction profile observed in adolescent patients (12 to 17 years of age) was similar to that of adults.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Lansoprazole Delayed-Release Capsules:
The following adverse events were reported to have a possible or probable relationship to drug as described by the treating physician in 1% or more of lansoprazole delayed-release capsules-treated patients who participated in short-term placebo- and positive-controlled trials (Table 2 and Table 3, respectively). Numbers in parentheses indicate the percentage of the adverse events reported.
Table 2. Incidence of Possibly or Probably Treatment-Related Adverse Events in Short-Term, Placebo-Controlled Studies in Takeda* Safety Database
| Body System/Adverse Event† | Lansoprazole Delayed-Release Capsules‡ (N = 817) N (%) | Placebo (N = 254) N (%) | ||
|---|---|---|---|---|
| Body as a Whole | ||||
| Headache | 63 (7.7) | 31 (12.2) | ||
| Abdominal Pain | 19 (2.3) | 3 (1.2) | ||
| Digestive System | ||||
| Diarrhea | 29 (3.5) | 6 (2.4) | ||
| Nausea | 9 (1.1) | 5 (2.0) | ||
| Vomiting | 7 (0.9) | 3 (1.2) | ||
| Liver Function Tests Abnormal | 2 (0.2) | 3 (1.2) | ||
| Nervous System | ||||
| Dizziness | 8 (1.0) | 2 (0.8) | ||
* Takeda Pharmaceuticals America Inc. † Events reported by at least 1% of patients on either treatment are included ‡ Doses 15, 30 and 60 mg once daily for 4 to 8 weeks | ||||
In the Takeda Safety Database, all short-term, Phase II/III studies, one or more treatment-emergent adverse events were reported by 715/1359 (52.6%) lansoprazole delayed-release capsules-treated patients; of those considered to be possibly or probably treatment-related adverse events, one or more were reported by 276/1359 (20.3%) lansoprazole delayed-release capsules-treated patients. In all short-term, Phase II/III studies, one or more treatment-emergent adverse events were reported by 150/254 (59.1%) placebo-treated patients; of those considered to be possibly or probably treatment-related adverse events, one or more were reported by 56/254 (22.0%).
The most frequent adverse events reported in the European short-term studies were diarrhea (3.3%), laboratory test abnormal (2.3%), headache (1.5%), constipation (1.2%), asthenia (1.1%), dizziness (1.1%), and abdominal pain (1.0%). The most frequent adverse events reported in the Asian short-term studies were unspecified laboratory test abnormalities (7.3%), eosinophilia (1.0%), and increased SGPT (1.0%).
Table 3. Incidence of Possibly or Probably Treatment-Related Adverse Events in Short-Term, Positive-Controlled Studies in Takeda Safety Database
| Body System/Adverse Event* | Lansoprazole Delayed-Release Capsules† | Ranitidine (N = 393) | ||||
|---|---|---|---|---|---|---|
(N = 647) N (%) | N (%) | |||||
| Body as a Whole | ||||||
| Headache | 26 (4.0) | 14 (3.6) | ||||
| Abdominal Pain | 8 (1.2) | 3 (0.8) | ||||
| Digestive System | ||||||
| Diarrhea | 27 (4.2) | 8 (2.0) | ||||
| Nausea | 7 (1.1) | 4 (1.0) | ||||
| Nervous System | ||||||
| Dizziness | 8 (1.2) | 3 (0.8) | ||||
| Skin and Appendages | ||||||
| Rash | 7 (1.1) | 1 (0.3) | ||||
* Events reported by at least 1% of patients on either treatment are included † Doses 15, 30 and 60 mg once daily for 4 to 8 weeks | ||||||
Gastroesophageal Reflux Disease (GERD) Studies
All adverse events reported from U.S. placebo-controlled studies that were considered to be possibly/probably treatment-related with an incidence of at least 5% in any treatment group are displayed by COSTART body system and term and by treatment group in Table 4.
Table 4. Adverse Events Possibly/Probably Related to Treatment, Reported by ≥ 5% of Patients in the U.S. Placebo-Controlled Non-Erosive GERD Studies
| Body System/COSTART Term | Lansoprazole Delayed-Release Capsules* N = 249 % (n) | Placebo N = 71 % (n) | |||
|---|---|---|---|---|---|
| Total Patients | |||||
| Any Event | 28.5 (71) † | 16.9 (12) | |||
| Body as a Whole | |||||
| Headache | 7.6 (19) | 7.0 (5) | |||
| Abdominal Pain | 6.0 (15) | 1.4 (1) | |||
| Digestive System | |||||
| Diarrhea | 5.2 (13) | 2.8 (2) | |||
† Statistically significantly different versus placebo at p = 0.05 level * Doses 15 and 30 mg once daily for 8 weeks | |||||
The most commonly reported (incidence ≥ 5% in any treatment group) treatment-emergent adverse events for lansoprazole delayed-release capsules patients were headache (14.9%), pharyngitis (9.6%), abdominal pain (8.8%), diarrhea (7.6%) and rhinitis (6.4%) and for placebo patients were headache (9.9%) and pharyngitis (9.9%). There were no clinically or statistically significant differences between lansoprazole delayed-release capsules and placebo when evaluated for treatment-emergent adverse events.
All adverse events reported from U.S. positive-controlled studies that were considered to be possibly/probably treatment-related with an incidence of at least 5% in either treatment are displayed by body system, COSTART term, and treatment in Table 5.
Table 5. Most Frequently* Reported Possibly/Probably Treatment-Related Adverse Events by Treatment in the Positive-Controlled Non-Erosive GERD Studies
| Body System/COSTART Term | Lansoprazole Delayed-Release Capsules† 15 and 30 mg once daily (N = 572) % (n) | Ranitidine 150 mg twice daily (N = 283) % (n) | |||
|---|---|---|---|---|---|
| Total Patients | |||||
| Any Event | 16 (91) | 17 (49) | |||
| Body as a Whole | |||||
| Abdominal Pain | 5 (29)‡ | 2 (5) | |||
| Digestive System | |||||
| Diarrhea | 4 (23) | 6 (18) | |||
* Reported by ≥ 5% of patients in any treatment † Doses 15 and 30 mg once daily for 8 weeks ‡ Statistically significantly different versus ranitidine at p = 0.05 level | |||||
The most frequently reported (≥ 5% of patients in any treatment) treatment-emergent adverse events for lansoprazole delayed-release capsules-treated patients were abdominal pain (9%), diarrhea (7%), and headache (6%) and for ranitidine-treated patients were diarrhea (9%), abdominal pain (7%), and headache (7%). There were no clinically or statistically significant differences between lansoprazole delayed-release capsules- and ranitidine-treated patients in the percentage of patients reporting specific treatment-emergent adverse events.
Treatment-emergent adverse events with an incidence of at least 2% in any treatment group of the maintenance treatment studies occurring from the start of maintenance treatment to the first recurrence of disease are displayed by body system and COSTART term, and by treatment group in Table 6.
There were no frequently reported (≥ 2.0%, incidence) severe adverse events in the treatment-emergent or the possibly/probably treatment-related event categories with onset at any point from the start of maintenance treatment to the time of first recurrence of disease.
Table 6. Treatment-Emergent Adverse Events Reported by ≥ 2% of the Placebo and Lansoprazole Delayed-Release Capsules Patients to the Time of First Recurrence of Disease* in the Maintenance Treatment Studies
| Lansoprazole Delayed-Release Capsules | Placebo | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| Mean Exposure (Days) | Cumulative N = 386 (267.5) | Cumulative N = 236 (105.4) | |||||||
| Body System/COSTART Term | % (n) | % (n) | |||||||
| Total Patients | |||||||||
| Any Event | 70.5 (272) | 39.4 (93) | |||||||
| Body as a Whole | |||||||||
| Abdominal Pain | 5.2 (20) | 3.0 (7) | |||||||
| Accidental Injury | 5.4 (21) | 2.1 (5) | |||||||
| Back Pain | 3.1 (12) | 4.2 (10) | |||||||
| Chest Pain | 2.3 (9) | 0.8 (2) | |||||||
| Flu Syndrome | 7.3 (28) | 3.8 (9) | |||||||
| Headache | 11.4 (44) | 6.4 (15) | |||||||
| Infection | 2.1 (8) | 1.3 (3) | |||||||
| Pain | 2.6 (10) | 0.8 (2) | |||||||
| Digestive System | |||||||||
| Diarrhea | 9.8 (38) | 5.5 (13) | |||||||
| Gastrointestinal Anomaly (polyp) | 4.4 (17) | 0.8 (2) | |||||||
| Nausea | 2.8 (11) | 1.3 (3) | |||||||
| Tooth Disorder | 2.1 (8) | 0.4 (1) | |||||||
| Vomiting | 3.4 (13) | 0.4 (1) | |||||||
| Musculoskeletal System | |||||||||
| Arthralgia | 4.4 (17) | 1.3 (3) | |||||||
| Myalgia | 2.1 (8) | 1.3 (3) | |||||||
| Nervous System | |||||||||
| Dizziness | 2.8 (11) | 0.4 (1) | |||||||
| Respiratory System | |||||||||
| Bronchitis | 3.1 (12) | 1.3 (3) | |||||||
| Cough Increased | 2.3 (9) | 0 | |||||||
| Pharyngitis | 17.1 (66) | 9.3 (22) | |||||||
| Rhinitis | 5.7 (22) | 1.3 (3) | |||||||
| Sinusitis | 6.5 (25) | 2.5 (6) | |||||||
| Skin and Appendages | |||||||||
| Rash | 4.7 (18) | 3.0 (7) | |||||||
| Urogenital System | |||||||||
| Urinary Tract Infection | 4.1 (16) | 2.5 (6) | |||||||
* Until time of first recurrence, withdrawal or end of maintenance treatment
The adverse events reported by at least 2% of patients in any treatment group are displayed by COSTART body system and term and by treatment group for controlled long-term European Studies in Table 7.
Table 7. Treatment-Emergent Adverse Events Reported by ≥ 2% of Patients Treated with Histamine H2-Receptor Antagonists or Lansoprazole in Long-Term, Phase II/III Histamine H2-Receptor Antagonist Controlled European Studies
| Body System/COSTART Term | Lansoprazole Delayed-Release Capsules (N = 263) % (n) | Histamine H2-Receptor Antagonists (N = 161) % (n) | ||||
|---|---|---|---|---|---|---|
| Total Patients | ||||||
| Any Event | 49.8 (131) | 46.6 (75) | ||||
| Body as a Whole | ||||||
| Abdominal Pain | 3.0 (8) | 3.7 (6) | ||||
| Back Pain | 2.3 (6) | 0.6 (1) | ||||
| Accidental Injury | 1.5 (4) | 2.5 (4) | ||||
| Infection | 1.1 (3) | 3.1 (5) | ||||
| Cardiovascular System | ||||||
| Hypertension | 1.9 (5) | 2.5 (4) | ||||
| Digestive System | ||||||
| Diarrhea | 9.1 (24) | 4.3 (7) | ||||
| Gastritis | 5.3 (14) | 1.2 (2) | ||||
| Constipation | 2.7 (7) | 2.5 (4) | ||||
| Vomiting | 1.9 (5) | 3.1 (5) | ||||
| Dyspepsia | 1.1 (3) | 3.1 (5) | ||||
| Musculoskeletal System | ||||||
| Arthralgia | 1.9 (5) | 2.5 (4) | ||||
| Nervous System | ||||||
| Dizziness | 1.9 (5) | 2.5 (4) | ||||
| Respiratory System | ||||||
| Respiratory Disorder | 2.3 (6) | 3.1 (5) | ||||
| Cough Increased | 1.1 (3) | 2.5 (4) | ||||
The adverse events reported by at least 1% of patients receiving lead-in open-label lansoprazole delayed-release capsules treatment in long-term European Studies are diarrhea (5.7%), esophagitis (2.5%), abdominal pain (2.1%), gastritis (2.1%), flatulence (1.3%), headache (1.1%), constipation (1.0%), and nausea (1.0%). The incidence of adverse events reported in the lead-in open-label period of the European studies was similar to that seen in controlled studies; however, the overall incidence was lower for the lead-in open-label studies than for the Histamine H2-Receptor Antagonist controlled studies (27.5% versus 49.8%, respectively).
Lansoprazole Delayed-Release Tablets: Adverse events from two bioequivalency studies performed in healthy volunteers are listed in Table 8.
The incidence of adverse events between the test 15 mg lansoprazole delayed-release tablets and the reference 15 mg lansoprazole delayed-release capsules (8% and 3%, respectively) was similar and are summarized in Table 8.
The incidence of adverse events between the test 30 mg lansoprazole delayed-release tablets and the reference 30 mg lansoprazole delayed-release capsules (0% and 2%, respectively) was similar and are summarized in Table 8.
Table 8. Summary of Adverse Events by Regimen, Number of Subjects, COSTART Term, Percentage, and Incidence
| Body System/COSTART term | 15 mg Lansoprazole delayed-release tablets (N = 60) % (n) | 15 mg Lansoprazole delayed-release capsules (N = 60) % (n) |
|---|---|---|
| Total Patients | ||
| Any Event | 8 (5) | 3 (2) |
| Body as a Whole | ||
| Headache | 7 (4) | 3 (2) |
| Digestive System | ||
| Nausea | 3 (2) | 2 (1) |
| Respiratory System | ||
| Epistaxis | 2 (1) | -- |
| Body System/COSTART term | 30 mg Lansoprazole delayed-release tablets (N = 60) % (n) | 30 mg Lansoprazole delayed-release capsules (N = 60) % (n) |
|---|---|---|
| Total Patients | ||
| Any Event | 0 (0) | 2 (1) |
| Hemic and Lymphatic System | ||
| Hyperlipemia | N/A | 2 (1) |
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
The adverse event profile in pediatric patients resembled that of adults taking lansoprazole. The most frequently reported (2 or more patients) treatment-related adverse events in patients 1 to
11 years of age (N = 66) were constipation (5%) and headache (3%). There were no adverse events reported in this U.S. clinical study that were not previously observed in adults.
The most frequently reported (at least 3%) treatment-related adverse events in patients 12 to 17 years of age (N = 87) were headache (7%), abdominal pain (5%), nausea (3%) and dizziness (3%). Treatment-related dizziness, reported as occurring in <1% of adult patients, was reported in this study by 3 adolescent patients with non-erosive GERD, who had dizziness concurrently with other events (such as migraine, dyspnea, and vomiting).
In another study, an 8½-year-old female experienced moderate hot flashes and arterial hypertension after receiving lansoprazole 17.7 mg/m2 for 5 days. However, blood pressure values were not recorded. The investigator considered the event possibly related to study drug. Study drug was discontinued and the symptoms resolved. This child experienced the same side effects at a later date when treated with ranitidine.
8.3 Less Common Clinical Trial Adverse Reactions
Additional adverse experiences occurring in < 1% of patients or subjects in domestic and/or international trials, or occurring since lansoprazole was marketed, are shown below within each body system. Other adverse reactions have been observed during post-marketing surveillance; see (8.5 Post-Market Adverse Reactions).
Body as a Whole: abdomen enlarged, allergic reaction, asthenia, candidiasis, carcinoma, chest pain (not otherwise specified), chills, edema, fever, flu syndrome, general pain, halitosis, infection (not otherwise specified), malaise, neck pain, neck rigidity, pelvic pain;
Cardiovascular System: angina, arrhythmia, bradycardia, cerebrovascular accident/cerebral infarction, hypertension/hypotension, migraine, myocardial infarction, palpitations, shock (circulatory failure), syncope, tachycardia, vasodilation;
Digestive System: abnormal stools, anorexia, bezoar, carcinoid, cardiospasm, cholelithiasis, colitis, constipation, dry mouth, dyspepsia, dysphagia, enteritis, eructation, esophageal stenosis, esophageal ulcer, esophagitis, fecal discoloration, flatulence, gastric nodules/fundic gland polyps, gastroenteritis, gastrointestinal disorder, gastrointestinal hemorrhage, glossitis, gum hemorrhage, hematemesis, increased appetite, increased salivation, melena, mouth ulceration, oral monoliasis, rectal disorder, rectal hemorrhage, stomatitis, tenesmus, thirst, tongue disorder, ulcerative colitis, ulcerative stomatitis;
Endocrine System: diabetes mellitus, goiter, hypothyroidism;
Hemic and Lymphatic
System*: anemia, hemolysis, lymphadenopathy;
Metabolism and
Nutritional Disorders: dehydration, gout, hyperglycemia/hypoglycemia, peripheral edema, weight gain/loss;
Musculoskeletal
System: arthralgia, arthritis, bone disorder, joint disorder, leg cramps, musculoskeletal pain, myalgia, myasthenia, synovitis;
Nervous System: abnormal dreams, agitation, amnesia, anxiety, apathy, confusion, convulsion, depersonalization, depression, diplopia, dizziness, emotional lability, hallucinations, hemiplegia, hostility aggravated, hyperkinesia, hypertonia, hypesthesia, insomnia, libido decreased, libido increased, nervousness, neurosis, paresthesia, sleep disorder, somnolence, thinking abnormality, tremor, vertigo;
Respiratory System: asthma, bronchitis, cough increased, dyspnea, epistaxis, hemoptysis, hiccup, laryngeal neoplasia, pleural disorder, pneumonia, stridor, upper respiratory inflammation/infection;
Skin and Appendages: acne, alopecia, contact dermatitis, dry skin, fixed eruption, hair disorder, maculopapular rash, nail disorder, pruritus, rash, skin carcinoma, skin disorder, sweating, urticaria;
Special Senses: abnormal vision, blurred vision, conjunctivitis, deafness, dry eyes, ear disorder, eye pain, ophthalmologic disorders, otitis media, parosmia, photophobia, retinal degeneration, taste loss, taste perversion, tinnitus, visual field defect;
Urogenital System: abnormal menses, breast enlargement, breast tenderness, dysmenorrhea, dysuria, gynecomastia, impotence, kidney calculus, kidney pain, leukorrhea, menorrhagia, menstrual disorder, penis disorder, polyuria, testis disorder, urethral pain, urinary frequency, urination impaired, urinary urgency, vaginitis.
* The majority of hematologic cases received were foreign-sourced and their relationship to lansoprazole was unclear.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
In addition, the following changes in laboratory parameters were reported as adverse events. Abnormal liver function tests, increased SGOT (AST), increased SGPT (ALT), increased creatinine, increased alkaline phosphatase, increased gamma globulins, increased GGTP, increased/decreased/abnormal white blood cells (WBC), abnormal AG ratio, abnormal red blood cells (RBC), bilirubinemia, eosinophilia, hyperlipemia, increased/decreased electrolytes, increased/decreased cholesterol, increased glucocorticoids, increased lactate dehydrogenase (LDH), increased/decreased/abnormal platelets, and increased gastrin levels. Urine abnormalities such as albuminuria, glycosuria, and hematuria were also reported. Additional isolated laboratory abnormalities were reported.
In the placebo controlled studies, when SGOT (AST) and SGPT (ALT) were evaluated, 0.4% (4/978) and 0.4% (11/2677) patients, who received placebo and lansoprazole, respectively, had enzyme elevations > 3 x upper limit of normal range at the final treatment visit. None of these lansoprazole delayed-release capsule-treated patients reported jaundice at any time during the study.
8.5 Post-Market Adverse Reactions
These events were reported during post-marketing surveillance. Estimates of frequency cannot be made since such events are reported voluntarily from a population of unknown size. Due to the uncontrolled nature of spontaneous reports, a clear causal relationship to lansoprazole cannot be established.
| Body as a Whole: | hypersensitivity reactions, including anaphylaxis |
|---|---|
| Digestive System: | colitis, fundic gland polyps (FGPs)†, hepatotoxicity, microscopic colitis, pancreatitis, vomiting; |
| Eye Disorders: | Amblyopia, blurred vision |
Hemic and Lymphatic System: | agranulocytosis, aplastic anemia, hemolytic anemia, leukopenia, neutropenia, pancytopenia, thrombocytopenia, and thrombotic thrombocytopenic purpura; |
| Immune System Disorders: | Subacute cutaneous lupus erythematosus (SCLE)†, erythema multiforme, Stevens-Johnson Syndrome (SJS), toxic epidermal necrolysis (TEN) (some fatal), DRESS syndrome (Drug Reaction with Eosinophilia and Systemic Symptoms (some fatal), Acute generalized exanthematous pustulosis (AGEP); |
| Metabolism and Nutritional Disorders: | hyponatremia, hypomagnesemia, hypocalcemia* and hypokalemia*; |
| Musculoskeletal System: | myositis, osteoporosis and osteoporosis-related fractures; |
| Skin and Subcutaneous Tissue Disorders**: | Rash, pruritus, severe dermatologic reactions including cutaneous lupus erythematosus |
| Special Senses: | speech disorder; |
| Urogenital System: | tubulointerstitial nephritis (TIN) (with possible progression to renal failure), urinary retention. |
* may be related to the occurrence of hypomagnesemia
† For further information, see 7 WARNINGS AND PRECAUTIONS.
** Refer also to Immune System Disorders
In an estimated exposure of 240 million patients worldwide (in both postmarketing surveillance and the clinical trials), the most commonly reported ophthalmic adverse events are amblyopia (13) and vision blurred (67) according to the MedDRA terminology. All the 13 cases of amblyopia had the reported term/verbatim "blurred or smeary vision". Only 2 of these 13 reports were considered serious, and both are foreign-sourced reports with very little information provided. Among the 67 reports with the “vision blurred”, 10 were considered serious and might be related to optic neuritis/neuropathy, whether or not believed related to the drug. In 2 of these 10 cases, 1 of the examining ophthalmologists proposed a diagnosis of anterior ischemic optic neuropathy (AION). Eight out of the 10 cases were foreign-sourced. Only 2 US-sourced serious cases involved the report of blurred vision. Both were consumer reports without any detailed information. No physician assessed any causality in either case.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Lansoprazole is metabolized through the cytochrome P450 system, specifically through CYP3A and CYP2C19. Studies have shown that lansoprazole does not have clinically significant interactions with other drugs metabolized by the cytochrome P450 system such as warfarin, antipyrine, indomethacin, acetylsalicylic acid, ibuprofen, phenytoin, prednisone, diazepam, clarithromycin, propranolol, amoxicillin or terfenadine in healthy subjects. These compounds are metabolized through various cytochrome P450 isozymes including CYP1A2, CYP2C9, CYP2C19, CYP2D6, and CYP3A.
Drugs that Inhibit or Induce CYP2C19: Inhibitors of CYP2C19 such as fluvoxamine would likely increase the systemic exposure to lansoprazole. Inducers of CYP2C19 may decrease the systemic exposure to lansoprazole.
Drugs with pH Dependent Absorption Pharmacokinetics: Lansoprazole causes a profound and long lasting inhibition of gastric acid secretion; therefore, lansoprazole may interfere with the absorption of drugs where gastric pH is an important determinant of bioavailability (e.g., ketoconazole, ampicillin esters, iron salts, digoxin).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 9. Established or Potential Drug-Drug Interactions with LANSOPRAZOLE or LANSOPRAZOLE FDT
Concomitant Drug Name | Source of Evidence | Effect | Clinical Comment | |||
Concomitant Drug Name | Source of Evidence | Effect | Clinical Comment | |||
Concomitant Drug Name | Source of Evidence | Effect | Clinical Comment | |||
Concomitant Drug Name | Source of Evidence | Effect | Clinical Comment | |||
| Antiretroviral Drugs | C | ↓ rilpivirine, atazanavir, nelfinavir ↑saquinavir | See 7 WARNINGS AND PRECAUTIONS, Drug Interactions with Antiretroviral Drugs. Rilpivirine Co-administration is contraindicated due to significant decreases in rilpivirine exposure and loss of therapeutic effect (see 2 CONTRAINDICATIONS). Atazanavir Co-administration of LANSOPRAZOLE or LANSOPRAZOLE FDT with atazanavir is not recommended. Concomitant administration of omeprazole (20 or 40 mg once daily) substantially reduced plasma Cmax and AUC of atazanavir in healthy volunteers administered atazanavir or atazanavir/ritonavir. (see REYATAZ® Product Monograph). Nelfinavir Co-administration of LANSOPRAZOLE or LANSOPRAZOLE FDT with nelfinavir is not recommended. Concomitant administration of omeprazole (40 mg daily) with nelfinavir (1250 mg twice daily) markedly reduced the AUC and Cmax for nelfinavir (by 36% and 37%, | |||
respectively) and its active metabolite M8 (by 92% and 89%, respectively) (see VIRACEPT® Product Monograph). Saquinavir Co-administration of saquinavir requires caution and monitoring, along with potential dose reduction of saquinavir, due to increased saquinavir exposure and thus the risk of saquinavir-related toxicities (see the INVIRASE® Product Monograph). Concomitant administration of omeprazole (40 mg daily) with saquinavir/ritonavir (1000/100 mg twice daily) increased saquinavir AUC by 82% and Cmax by 75%. | ||||||
| Clopidogrel | CT | No clinically important effect | Concomitant administration of lansoprazole and clopidogrel in healthy subjects had no clinically important effect on exposure to the active metabolite of clopidogrel or clopidogrel-induced platelet inhibition. No dose adjustment of clopidogrel is necessary when administered with an approved dose of lansoprazole. | |||
| CYP450 | ||||||
| Methotrexate | C, CT | No clinically important effect | Case reports, published population pharmacokinetic studies, and retrospective analyses suggest that concomitant administration of PPIs and methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate, possibly leading to methotrexate toxicities. However, no formal drug interaction studies of high dose methotrexate with PPIs have been conducted. | |||
| In an open-label, single-arm, eight day, pharmacokinetic study of 28 adult rheumatoid arthritis patients (who required the chronic use of 7.5 to 15 mg of methotrexate given weekly), administration of 7 days of naproxen 500 mg twice daily and lansoprazole delayed-release capsules 30 mg daily had no effect on the pharmacokinetics of methotrexate and 7-hydroxymethotrexate. While this study was not designed to assess the safety of this combination of drugs, no major adverse reactions were noted. However, this study was conducted with low doses of methotrexate. A drug interaction study with high doses of methotrexate has not been conducted. (See 7 WARNINGS AND PRECAUTIONS, General, Concomitant Use with Methotrexate) | ||||||
| Sucralfate | CT | Lansoprazole: AUC ↓, Cmax ↓ | Proton pump inhibitors should be taken at least 30 minutes prior to sucralfate. In clinical trials, antacids were administered with lansoprazole and there was no evidence of a change in the efficacy of lansoprazole (see 10.3 Pharmacokinetics, Absorption, Absorption with Antacids). | |||
| Tacrolimus | C | Increased whole blood levels | Concomitant administration of lansoprazole and tacrolimus may increase whole blood levels of tacrolimus, especially in transplant patients who are intermediate or poor metabolizers of CYP2C19. | |||
Theophylline (CYP1A2, CYP3A) | CT | 10% increase in theophylline clearance | Minor increase of theophylline clearance is unlikely to be of clinical concern. Individual patients may require adjustment of their theophylline dosage when LANSOPRAZOLE or LANSOPRAZOLE FDT is started or stopped to ensure clinically effective | |||
blood levels. Patient monitoring should be taken in coadministration of lansoprazole with theophylline. | ||||||
| Warfarin | C, CT | ↑ INR and PT | In a study of healthy subjects, neither the pharmacokinetics of warfarin enantiomers nor prothrombin time (PT) were affected following co- administration of single or multiple 60 mg doses of lansoprazole and warfarin; however, there have been reports of increased international normalized ratio (INR) and PT in patients receiving PPIs, including lansoprazole, and warfarin concomitantly. Increases in INR and PT may lead to abnormal bleeding and even death. Patients treated with PPIs and warfarin concomitantly may need to be monitored for increases in INR and PT. | |||
| Legend: C = Case Study; CT = Clinical Trial | ||||||
Concomitant Antacid Use
Simultaneous administration of lansoprazole with aluminum and magnesium hydroxide or magaldrate results in lower peak plasma levels, but does not significantly reduce bioavailability. Antacids may be used concomitantly if required. If sucralfate is to be given concomitantly, LANSOPRAZOLE or LANSOPRAZOLE FDT should be administered at least 30 minutes prior to sucralfate (see 10.3 Pharmacokinetics, Absorption, Absorption with Antacids). In clinical trials, antacids were administered concomitantly with lansoprazole delayed-release capsules; this did not interfere with its effect.
9.5 Drug-Food Interactions
Food reduces the peak concentration and the extent of absorption by about 50% to 70%. Therefore, it is recommended that lansoprazole delayed-release capsules be administered in the morning prior to breakfast. See 10.3 Pharmacokinetics.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
During treatment with antisecretory drugs, Chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA level may interfere with investigations for neuroendocrine tumours. To avoid this interference, LANSOPRAZOLE or LANSOPRAZOLE FDT treatment should be stopped 14 days before CgA measurements to allow CgA levels that might be spuriously elevated following PPI treatment to return to reference range (7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Lansoprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that do not exhibit anticholinergic or histamine H2 antagonist properties, but that suppress gastric acid secretion by specific inhibition of the (H+, K+)-ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the parietal cell, lansoprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production. This effect is dose-related and leads to inhibition of both basal and stimulated gastric acid secretion irrespective of the stimulus. The inhibition of gastric acid secretion persists for up to 36 hours after a single dose. Thus, the plasma elimination half-life of lansoprazole does not reflect its duration of suppression of gastric acid secretion.
10.2 Pharmacodynamics
In healthy subjects, single and multiple doses of lansoprazole delayed-release capsules (15 mg to 60 mg) have been shown to decrease significantly basal gastric acid output and to increase significantly mean gastric pH and percent of time at pH >3 and 4. These doses have also been shown to reduce significantly meal-stimulated gastric acid output and gastric secretion volume. Single or multiple doses of lansoprazole delayed-release capsules (10 mg to 60 mg) reduced pentagastrin-stimulated acid output. In addition, lansoprazole delayed-release capsules have been demonstrated to reduce significantly basal and pentagastrin-stimulated gastric acid secretion among Duodenal Ulcer and hypersecretory patients, and basal gastric acid secretion among patients with Gastric Ulcer disease.
A dose-response effect was analyzed by considering the results from clinical pharmacology studies that evaluated more than one dose of lansoprazole delayed-release capsules. The results indicated that, in general, as the dose was increased from 7.5 mg to 30 mg, there was a decrease in mean gastric acid secretion and an increase in the average time spent at higher pH values (pH >4).
The results of pharmacodynamic studies with lansoprazole delayed-release capsules in normal subjects suggest that doses of 7.5 mg to 10 mg are substantially less effective in inhibiting gastric acid secretion than doses of 15 mg or greater. In view of these results, the doses of lansoprazole delayed-release capsules evaluated in the principal clinical trials ranged from 15 mg to 60 mg daily.
Pharmacodynamic Properties
Antisecretory Activity: After oral administration, lansoprazole was shown to significantly decrease the basal acid output, and significantly increase the mean gastric pH and percent of time the gastric pH was >3 and >4. Lansoprazole also significantly reduced meal-stimulated gastric acid output and secretion volume. Lansoprazole also significantly reduced pentagastrin-stimulated acid output. In patients with hyper secretion of acid, lansoprazole significantly reduced basal and pentagastrin-stimulated gastric acid secretion. Lansoprazole inhibited the normal increases in secretion volume, acidity and acid output induced by insulin.
In a crossover study comparing lansoprazole 15 and 30 mg to omeprazole 20 mg for 5 days, the following effects of lansoprazole on intragastric pH were noted (Table 10).
Table 10. Mean Antisecretory Effects of Lansoprazole After Multiple Daily Dosing
| Parameter | Baseline Value | Lansoprazole 15 mg | Lansoprazole 30 mg | Omeprazole 20 mg |
| Mean 24-hour pH | 2.05 | 4.03† | 4.91* | 4.16+ |
| Mean Nighttime pH | 1.91 | 3.01† | 3.80* | 3.04+ |
| % Time Gastric pH > 3 | 18 | 59† | 72* | 61+ |
| % Time Gastric pH > 4 | 12 | 49† | 66* | 51+ |
Note: An intragastric pH of > 4 reflects a reduction in gastric acid by 99%. * (p < 0.05) versus baseline, lansoprazole 15 mg and omeprazole 20 mg. † (p < 0.05) versus baseline only. | ||||
After the initial dose in this study, increased gastric pH was seen within 1 to 2 hours with lansoprazole 30 mg, 2 to 3 hours with lansoprazole 15 mg, and 3 to 4 hours with omeprazole 20 mg. After multiple daily dosing, increased gastric pH was seen within the first hour postdosing with lansoprazole 30 mg and within 1 to 2 hours postdosing with lansoprazole 15 mg and omeprazole 20 mg.
Higher levels of acid suppression have been predicted to potentiate the activity of antibiotics in eradicating H. pylori. The percentage of time gastric pH was elevated above 5 and 6 was evaluated in a crossover study of lansoprazole delayed-release capsules given once daily, twice daily and three times daily (Table 11).
Table 11. Mean Antisecretory Effects After 5 Days of Twice Daily and Three Times Daily Dosing of Lansoprazole Delayed-Release Capsules
| Parameter | 30 mg once daily | 15 mg twice daily | 30 mg twice daily | 30 mg three times daily |
| % Time Gastric pH > 5 | 43 | 47 | 59+ | 77* |
| % Time Gastric pH > 6 | 20 | 23 | 28 | 45* |
+ (p < 0.05) versus Lansoprazole Delayed-Release Capsules 30 mg once daily * (p < 0.05) versus Lansoprazole Delayed-Release Capsules 30 mg once daily, 15 mg twice daily and 30 mg twice daily | ||||
The inhibition of gastric acid secretion as measured by intragastric pH returns gradually to normal over 2 to 4 days after multiple doses. There was no indication of rebound gastric acidity.
Other Gastric and Esophageal Effects: Lansoprazole did not significantly affect mucosal blood flow in the fundus of the stomach. Due to the normal, physiologic effect caused by the inhibition of gastric acid secretion, a decrease of 17% in blood flow in the antrum, pylorus and duodenal bulb was seen. Lansoprazole did not significantly affect gastric emptying of liquids, but significantly slowed the gastric emptying of digestible solids. Esophageal motility and lower esophageal sphincter tone were not modified by lansoprazole therapy. Lansoprazole increased serum pepsinogen levels and decreased pepsin activity under basal conditions and in response to meal stimulation or insulin injection. In patients with gastric ulcer, increases in gastric pH were associated with increases in nitrate-reducing bacteria and elevation of nitrite concentration in gastric juice; however no significant increase in nitrosamine concentrations were observed.
Enterochromaffin-like (ECL) Cell Effects/Carcinoid Formation: Lansoprazole produced dose-related gastric enterochromaffin-like (ECL) cell hyperplasia and ECL cell carcinoids in both male and female rats (see 16 NON-CLINICAL TOXICOLOGY). Hypergastrinemia secondary to prolonged and sustained hypochlorhydria, such as that induced by high doses of ranitidine, omeprazole, and surgery, has been postulated to be the mechanism by which ECL cell hyperplasia and gastric carcinoid tumors develop.
Gastric biopsy specimens from the body of the stomach from over 300 patients treated continuously with lansoprazole for 8 to 120 weeks have not shown evidence of ECL effects similar to those seen in rats. Longer term data are needed to rule out the possibility of an increased risk for the development of gastric carcinoid tumors in patients receiving long-term therapy with lansoprazole.
Serum Gastrin Effects: Fasting serum gastrin levels increased modestly during the first 2 to 4 weeks of therapy with 15 to 60 mg of lansoprazole. This increase was dose-dependent. Median serum gastrin values in over 2100 patients treated with lansoprazole 15 to 60 mg remained within normal range and generally increased 1.5- to 2-fold. Gastrin values returned to pretreatment levels within 4 weeks after discontinuation of therapy.
Endocrine Effects: Human studies for up to 1 year have not detected any clinically significant effects on the endocrine system. Hormones studied included testosterone, luteinizing hormone (LH), follicle stimulating hormone (FSH), sex hormone binding globulin (SHBG), dehydroepiandrosterone sulphate (DHEA-S), prolactin, cortisol, estradiol, insulin, aldosterone, parathormone, glucagon, thyroid stimulating hormone (TSH), triiodothyronine (T3), thyroxine (T4), and somatotropic hormone (STH). Lansoprazole oral doses of 15 to 60 mg for up to 1 year had no clinically significant effect on sexual function. In addition, lansoprazole in oral doses of 15 to 60 mg for 2 to 8 weeks had no clinically significant effect on thyroid function.
Other Effects: No systemic effects of lansoprazole on the central nervous system, lymphoid, hematopoietic, renal, hepatic, cardiovascular or respiratory systems have been found in humans. Lansoprazole in oral doses of 15 to 60 mg for 2 to 8 weeks had no clinically significant effect on thyroid function. No lansoprazole delayed-release capsules-related visual adverse events were noted in over 7000 patients treated in Phase I to Phase III clinical trials worldwide. No visual toxicity was observed among 63 patients who had extensive baseline eye evaluations, were treated with up to 180 mg/day of lansoprazole and were observed for up to 68 months.
10.3 Pharmacokinetics
Table 12. Summary of Lansoprazole delayed-release capsules Pharmacokinetic Parameters in Healthy Subjects Pooled Across Phase I Studies
Cmax* (ng/mL) | Tmax (h) | T½ (h) | AUC* (ng•h/mL) | CL** L/h | Vd*** L | |
|---|---|---|---|---|---|---|
| Mean (%CV) | 824 (50.81) N = 515 | 1.68 (47.71) N = 345 | 1.53 (65.92) N = 285 | 2133 (84.28) N = 513 | 31 ± 8 | 29 ± 4 |
* Normalized to a 30 mg dose
± N = Number of dosages associated with a parameter
** Total Body CL/F
*** Vd/F
Table 13. Mean ± SD Pharmacokinetic Parameters of Lansoprazole in Children (aged 1 to 11 yrs) (Study no. M97-808)
Cmax (ng/mL) | Tmax (h) | t½ (h)‡ | AUC0-∞ (ng•h/mL) | |
|---|---|---|---|---|
| 15 mg * mean | 790.9 ± 435.4 | 1.5 ± 0.7 | 0.68 ± 0.21 | 1707 ± 1689 |
| 30 mg * mean | 898.5 ± 437.7 | 1.7 ± 0.7 | 0.71 ± 0.22 | 1883 ± 1159 |
* Subjects with a body weight of ≤ 30 kg were administered a 15 mg dose; subjects with a body weight of > 30 kg were administered a 30 mg dose.
‡ Harmonic mean ± Pseudo Standard Deviation.
Table 14. Mean ± SD Pharmacokinetic Parameters of Lansoprazole in Adolescents (aged 12 to 17 yrs) (Study no. M97-640)
Cmax (ng/mL) | Tmax (h) | t½ (h)‡ | AUC0-∞ (ng•h/mL) | |
|---|---|---|---|---|
| 15 mg mean | 414.8 ± 215.5 | 1.6 ± 0.7 | 0.84 ± 0.26 | 1017 ± 1737 |
| 30 mg mean | 1005 ± 604.9 | 1.7 ± 0.7 | 0.95 ± 0.31 | 2490 ± 2522 |
‡ Harmonic mean ± Pseudo Standard Deviation.
Lansoprazole delayed-release capsules and lansoprazole delayed-release tablets contain an enteric-coated granule formulation of lansoprazole to ensure that absorption of lansoprazole begins only after the granules leave the stomach (lansoprazole is acid-labile). Peak plasma concentrations of lansoprazole (Cmax) and the area under the plasma concentration curve (AUC) of lansoprazole are approximately proportional in doses from 15 mg to 60 mg after single-oral administration. Lansoprazole pharmacokinetics are unaltered by multiple dosing and the drug does not accumulate.
Lansoprazole delayed-release capsules are highly bioavailable when administered orally. In a definitive absolute bioavailability study, the absolute bioavailability was shown to be 86% for a 15 mg capsule and 80% for a 30 mg capsule. First pass effect is apparently minimal.
Absorption
The absorption of lansoprazole is rapid, with mean peak plasma levels of lansoprazole occurring at approximately 1.7 hours. Peak plasma concentrations of lansoprazole (Cmax) and the area under the plasma concentration curve (AUC) are approximately proportional to dose throughout the range that has been studied (up to 60 mg).
Absorption with Food: Food reduces the peak concentration and the extent of absorption by about 50% to 70%. Moreover, the results of a pharmacokinetic study that compared the bioavailability of lansoprazole following a.m. dosing (fasting) versus p.m. dosing (3 hours after a meal) indicated that both Cmax and AUC values were increased by approximately 2-fold or more with a.m. dosing. Therefore, it is recommended that lansoprazole delayed-release capsules or lansoprazole delayed-release tablets be administered in the morning prior to breakfast.
Absorption with Antacids: Simultaneous administration of lansoprazole delayed-release capsules with aluminum and magnesium hydroxide or magaldrate resulted in lower peak serum levels, but did not significantly reduce the bioavailability of lansoprazole.
In a single-dose crossover study when 30 mg of lansoprazole was administered concomitantly with 1 gram of sucralfate in healthy volunteers, absorption of lansoprazole was delayed and its bioavailability was reduced. The value of lansoprazole AUC was reduced by 17% and that for Cmax was reduced by 21%.
In a similar study when 30 mg of lansoprazole was administered concomitantly with 2 grams of sucralfate, lansoprazole AUC and Cmax were reduced by 32% and 55%, respectively. When lansoprazole dosing occurred 30 minutes prior to sucralfate administration, Cmax was reduced by only 28% and there was no statistically significant difference in lansoprazole AUC. Therefore, lansoprazole may be given concomitantly with antacids but should be administered at least 30 minutes prior to sucralfate.
Distribution:
The apparent volume of distribution of lansoprazole is approximately 15.7 (± 1.9) L, distributing mainly in extracellular fluid. Lansoprazole is 97% bound to plasma proteins. The mean total body clearance (CL) of lansoprazole was calculated at 31 ± 8 L/h, and the volume of distribution (Vss) was calculated to be 29 (± 4) L.
Metabolism:
Lansoprazole is extensively metabolized in the liver. Two metabolites have been identified in measurable quantities in plasma; the hydroxylated sulfinyl and the sulfone derivatives of lansoprazole. These metabolites have very little or no antisecretory activity. Lansoprazole is thought to be transformed into 2 active species that inhibit acid secretion by blocking the proton pump (H+,K+)-ATPase enzyme system at the secretory surface of the gastric parietal cell. The 2 active species are not present in the systemic circulation. The plasma elimination half-life of lansoprazole is less than 2 hours while the acid inhibitory effect lasts more than 24 hours. Therefore, the plasma elimination half-life of lansoprazole does not reflect its duration of suppression of gastric acid secretion.
Elimination:
Following single dose oral administration of lansoprazole, virtually no unchanged lansoprazole was excreted in the urine. After a 30 mg single oral dose of 14C-lansoprazole, approximately one third of the dose was excreted in the urine and approximately two-thirds were recovered in the feces. This implies a significant biliary excretion of the metabolites of lansoprazole.
Special Populations and Conditions
Pediatrics (1 to 17 years of age): The pharmacokinetics of lansoprazole were studied in pediatric patients with Gastroesophageal Reflux Disease (GERD) aged 1 to 11 years, with lansoprazole doses of 15 mg once daily for subjects weighing ≤ 30 kg and 30 mg once daily for subjects weighing >30 kg. The pharmacokinetics were also studied in adolescents aged 12 to 17 years with GERD following 15 mg or 30 mg once daily of lansoprazole.
Pharmacokinetic parameters for lansoprazole following 15 or 30 mg once daily doses of lansoprazole to children aged 1 to 11 years and adolescents aged 12 to 17 years, as well as those observed from healthy adult subjects, are summarized in Table 12, Table 13 and Table 14.
In general, the pharmacokinetics of lansoprazole in children and adolescents (aged 1 to 17 years) with GERD were similar to those observed in healthy adult subjects.
Children 1 to 11 years old weighing ≤ 30 kg received a 15 mg dose and children weighing >30 kg received a 30 mg dose. When normalized for body weight, the mean lansoprazole dose was similar for the two dosing groups (0.82 mg/kg for 15 mg dose group and 0.74 mg/kg for 30 mg dose group). The Cmax and AUC values were therefore similar for both the 15 mg and 30 mg dose groups.
In adolescent subjects aged 12 to 17 years, a nearly proportional increase in plasma exposure was observed between 15 mg and 30 mg once daily dosing groups. Plasma exposure of lansoprazole was not affected by body weight or age; and nearly dose-proportional increases in plasma exposure were observed between the two dose groups in the study. The results of the study in adolescents demonstrated that the pharmacokinetics of lansoprazole in this group is similar to that previously reported in healthy adult subjects.
- Geriatrics: The results from the studies that evaluated the pharmacokinetics of lansoprazole following oral administration in an older population revealed that in comparison with younger subjects, older subjects exhibited significantly larger AUCs and longer t½s. Lansoprazole did not accumulate in the older subjects upon multiple dosing since the longest mean t½ in the studies was 2.9 hours, and lansoprazole is dosed once daily. Cmax in the elderly was comparable to that found in adult subjects.
- Sex: In a study comparing 12 male and 6 female subjects, no gender differences were found in pharmacokinetics or intragastric pH results (see 7 WARNINGS AND PRECAUTIONS, Use in Women).
- Ethnic Origin: The pooled pharmacokinetic parameters of oral administered lansoprazole from twelve U.S. Phase I studies (N=513) were compared to the mean pharmacokinetic parameters from two Asian studies (N=20). The mean AUCs of lansoprazole in Asian subjects are approximately twice that seen in pooled U.S. data, however, the inter-individual variability is high. The Cmax values are comparable.
Hepatic Insufficiency: As would be expected with a drug that is primarily metabolized by the liver, in patients with mild (Child-Pugh Class A) or moderate (Child-Pugh Class B) chronic hepatic disease, the plasma half-life of the drug after oral administration increased to 5.2 hours compared to the 1.5 hours half-life in healthy subjects. An
- increase in AUC of 3.4-fold was observed in patients with hepatic impairment versus healthy subjects (7096 versus 2645 ng•h/mL) which was due to slower elimination of lansoprazole; however, Cmax was not significantly affected. Dose reduction in patients with severe hepatic disease should be considered.
Renal Insufficiency: In patients with mild (Clcr 40 to 80 mL/min), moderate (Clcr 20 to 40 mL/min) and severe (Clcr < 20 mL/min) chronic renal impairment, the disposition of lansoprazole after oral administration was very similar to that of healthy volunteers.
The impact of dialysis on lansoprazole was evaluated from a pharmacokinetic standpoint, and there were no significant differences in AUC, Cmax or t½ between dialysis day and dialysis-free day. Dialysate contained no measurable lansoprazole or metabolite. Lansoprazole is not significantly dialysed.
11 STORAGE, STABILITY AND DISPOSAL
LANSOPRAZOLE (lansoprazole delayed-release capsules)
LANSOPRAZOLE should be stored in a tight container protected from light and moisture. Store between 15°C and 25°C.
LANSOPRAZOLE FDT (lansoprazole fast-disintegrating, delayed-release tablets)
LANSOPRAZOLE FDT should be stored in a tight container protected from moisture. Store between 15°C and 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Lansoprazole
Chemical name: 2-[[[3-methyl-4-(2,2,2-trifluoro-ethoxy)-2-pyridinyl] methyl] sulfinyl]-1H-benzimidazole
Molecular formula: C16H14F3N3O2S
Molecular mass: 369.36 g/mol
Structural formula:
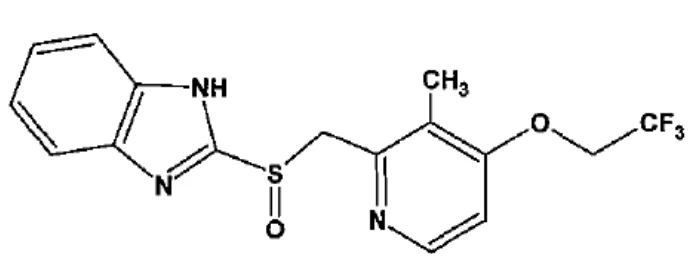
Physicochemical properties:
Lansoprazole is a white to brownish-white, crystalline powder which melts with decomposition at approximately 166°C. Lansoprazole is freely soluble in dimethylformamide; soluble in methanol; sparingly soluble in ethanol; slightly soluble in ethyl acetate, dichloromethane and acetonitrile; and practically insoluble in water.
PKa: 9.745
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
14.1.1 Symptomatic Gastroesophageal Reflux Disease (GERD)
Table 15. Summary of patient demographics for clinical trials in Symptomatic Gastroesophageal Reflux Disease (GERD)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| M95-300 | multicenter, double-blind, placebo-controlled | Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, Oral Placebo 8 weeks | 185‡ | 44.4 years (18 – 77 years) | 85 M (45.9%), 100 F (54.1%) |
| M96-519 | multicenter, double-blind, ranitidine- and placebo-controlled | Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, Oral Ranitidine 150 mg b.i.d. Placebo 8 weeks | 402‡ | 44.7 years (18 – 84 years) | 168 M (41.8%), 234 F (58.2%) |
| M96-521 | multicenter, double-blind, ranitidine- and placebo-controlled | Lansoprazole Delayed Release Capsules: 15 mg QD 30 mg QD, Oral Ranitidine 150 mg b.i.d. 8 weeks | 428‡ | 45.1 years (18 – 86 years) | 174 M (40.7%), 254 F (59.3%) |
| M97-808 | multicenter, uncontrolled, open-label | * Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, Oral 8 to 12 weeks | 66 | 7.0 years (1 to 12 years) | 40 M (60.6%), 26 F (39.4%) |
| M97-640 | Phase I, multicenter, randomized, double-blind trial | Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, Oral Lansoprazole: 15 mg QD, 30 mg QD | 63 | 14.2 years (12 to 17 years) | 32 M (50.8%), 31 F (49.2%) |
| 5 days | |||||
* An initial dose of either Lansoprazole Delayed Release Capsules 15 mg once daily if ≤30 kg or Lansoprazole Delayed Release Capsules 30 mg once daily if >30 kg administered for 8 to 12 weeks. Dosage increased (up to 30 mg twice daily) in 24 patients after two weeks of treatment if they remained symptomatic.
‡ M95-300 had 185 patients that were enrolled with 148 evaluable patients; M96-519 had 453 patients that were enrolled with 402 evaluable patients; M96-521 has 472 patients that were enrolled with 428 evaluable patients.
In a U.S., multicenter, double-blind, placebo-controlled study of 214 patients with frequent GERD symptoms, but no esophageal erosions by endoscopy, significantly greater relief of heartburn associated with GERD was observed with the administration of lansoprazole delayed-release capsules 15 mg once daily up to 8 weeks than with placebo. No significant additional benefit from lansoprazole delayed-release capsules 30 mg once daily was observed.
The intent-to-treat analyses demonstrated significant reduction in frequency and severity of day and night heartburn. After a single dose, 45% and 39% of patients treated with lansoprazole delayed-release capsules 15 mg and lansoprazole delayed-release capsules 30 mg, respectively, reported no day heartburn compared to 19% of patients receiving placebo. Likewise, 61% and 51% of patients treated with lansoprazole delayed-release capsules 15 mg and lansoprazole delayed-release capsules 30 mg, respectively, reported no night heartburn compared to 31% of patients receiving placebo. Data for frequency and severity for the 8-week treatment period were as summarized in Figure 1 and Figure 2 and Table 16.
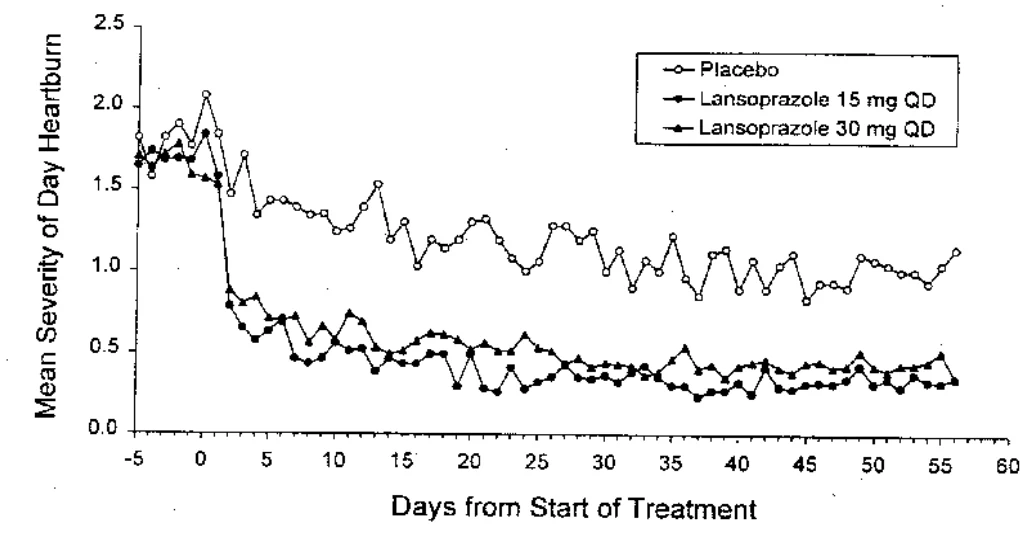
Figure 1. Mean Severity of Day Heartburn by Study Day for Evaluable Non-Erosive GERD Patients (3 = Severe, 2 = Moderate, 1 = Mild, 0 = None). Study M95-300
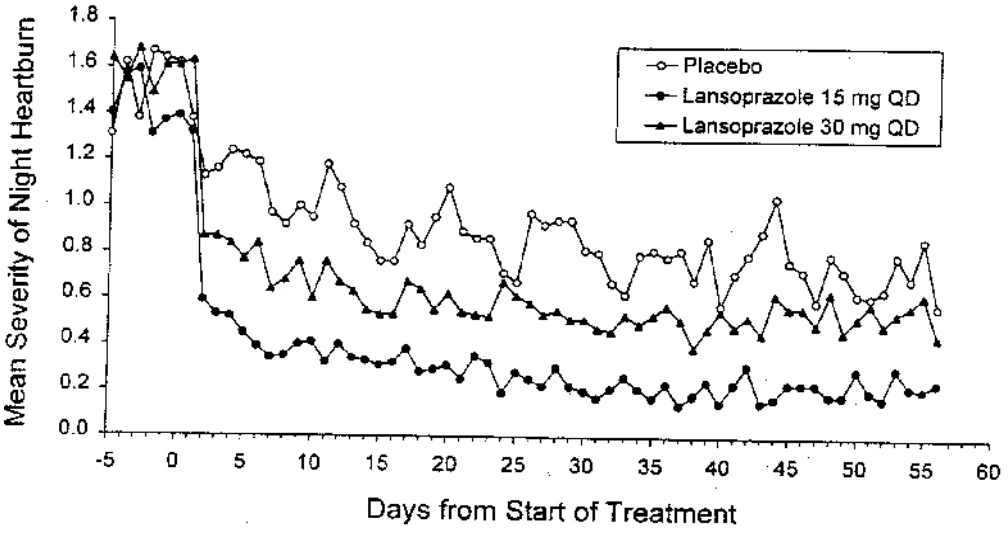
Figure 2. Mean Severity of Night Heartburn by Study Day for Evaluable Non-Erosive GERD Patients (3 = Severe, 2 = Moderate, 1 = Mild, 0 = None). Study M95-300
Table 16. Frequency of Heartburn at Week 1, Week 4, and Week 8 in Non-Erosive GERD Patients (Intent-to-Treat)
| Variable | Placebo (n = 43) | Lansoprazole Delayed Release Capsules 15 mg (n = 80) | Lansoprazole Delayed Release Capsules 30 mg (n = 86) |
| % of Days without heartburn (Median) | |||
| Week 1 | 0 | 71* | 46* |
| Week 4 | 11 | 81* | 76* |
| Week 8 | 13 | 84* | 82* |
| % of Nights without heartburn (Median) | |||
| Week 1 | 17 | 86* | 57* |
| Week 4 | 25 | 89* | 73* |
| Week 8 | 36 | 92* | 80* |
| * (p < 0.01) versus placebo. | |||
In two U.S., multicenter, double-blind, ranitidine-controlled‡ studies of 925 total patients with frequent GERD symptoms, but no esophageal erosions by endoscopy, lansoprazole delayed-release capsules 15 mg was superior to ranitidine 150 mg (twice daily) in decreasing the frequency and severity of day and night heartburn associated with GERD for the 8 week treatment period. No significant additional benefit from lansoprazole delayed-release capsules 30 mg once daily was observed.
‡ In Canada, ranitidine is not indicated for the treatment of symptomatic GERD.
Pediatrics
Children 1 to 11 years of age
In an uncontrolled, open-label, U.S. multicenter study, 66 children (1 to 11 years of age) with GERD (58% had non-erosive GERD and 42% had erosive esophagitis, assessed by endoscopy) were assigned, based on body weight, to receive an initial dose of either lansoprazole delayed-release capsules 15 mg once daily if ≤ 30 kg or lansoprazole delayed-release capsules 30 mg once daily if >30 kg administered for 8 to 12 weeks. The lansoprazole delayed-release capsules dose was increased (up to 30 mg twice daily) in 24 of 66 pediatric patients after 2 or more weeks of treatment if they remained symptomatic. Some children benefited from a dosage increase (up to 60 mg daily) based on efficacy results.
After 8 to 12 weeks of lansoprazole delayed-release capsules treatment, the intent-to-treat analysis demonstrated an approximate 50 % reduction in frequency and severity of GERD symptoms.
Twenty-one of 27 erosive esophagitis patients were healed at 8 weeks and 100% of patients were healed at 12 weeks based on endoscopy (Table 17).
Table 17. Improvement in Overall GERD Symptoms (1 to 11 years)
| GERD | Final Visit* % (n/N) |
| Symptomatic GERD | |
| Improvement in Overall GERD Symptoms† | 76% (47/62‡) |
| Erosive Esophagitis | |
| Improvement in Overall GERD Symptoms† | 81% (22/27) |
| Healing Rate | 100% (27/27) |
* At Week 8 or Week 12 † Symptoms assessed by patients diary kept by caregiver ‡ No data were available for 4 patients | |
Median fasting serum gastrin levels increased 89% from 51 pg/mL at baseline to 97 pg/mL [interquartile range (25th to 75th percentile) of 71 to 130 pg/mL] at the final visit.
In this study, 15 mg and 30 mg doses of lansoprazole delayed-release capsules were safe and well tolerated in this pediatric population (1 to 11 years of age). Dose increases (up to 60 mg daily when required) were not associated with any increase in adverse events or with any apparent trend in adverse events. No clinically significant changes in laboratory values, vital signs values, or physical examination results were observed among these children over an 8- to 12-week period. The elevations seen in serum gastrin levels were consistent with those observed in adult studies. There were no clinically significant changes or trends observed based on gastric biopsy findings including the nonantral endocrine cell population, as measured by Grimelius-positive cell counts and modified Solcia classification for the duration of this study.
Children 12 to 17 years of age
In a Phase I, multicenter, randomized, double-blind trial, the pharmacokinetic profile of lansoprazole in adolescents 12 to 17 years of age was compared to that previously observed in healthy adults, and also the safety and pharmacodynamic profile of lansoprazole in adolescents with symptomatic GERD was evaluated. The study consisted of a 7-day Pretreatment Period and a 5-day Treatment Period. The adolescents were randomized in an equal ratio to lansoprazole 15 mg once daily or lansoprazole 30 mg once daily for 5 days administered prior to breakfast or the first meal of the day.
The results of this study demonstrated that the pharmacokinetics of lansoprazole are similar between the adolescents in this study and those previously observed in healthy adult subjects. Both peak plasma concentration (Cmax) and area under the plasma concentration curve (AUC0-24) of lansoprazole increased proportionately with dose from 15 to 30 mg for oral administration once daily for 5 days. A significant increase in average 24-hour intragastric pH after five days of lansoprazole 15 or 30 mg administration was observed for adolescents in this study, as was consistently observed in healthy adult subjects. The same was true for the percentage of time intragastric pH was above 3 and 4. In addition, the lansoprazole 30 mg once daily regimen significantly increased the percentage of time the intragastric pH was above 5.
Subjects in both the lansoprazole delayed-release capsules 15 mg once daily and lansoprazole delayed-release capsules 30 mg once daily groups demonstrated improvement in symptoms of reflux disease despite receiving a short course of therapy. Additionally, 69% of the lansoprazole delayed-release capsules 15 mg once daily subjects and 74% of the lansoprazole delayed-release capsules 30 mg once daily subjects reported that their reflux symptoms were reduced during the short period of treatment with lansoprazole delayed-release capsules.
14.1.2 Reflux Esophagitis
Table 18. Summary of patient demographics for clinical trials in Reflux Esophagitis
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| M87-092 | multicenter, double-blind, placebo-controlled | Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, 60 mg QD, Oral Placebo 8 weeks | 269 | 45.0 years (21 to 75 years) | 181 M (67.3%), 88 F (32.7%) |
| M88-269 | multicenter, double-blind | Lansoprazole Delayed Release Capsules: 30 mg QD, Oral Ranitidine 150 mg b.i.d, Oral 8 weeks | 242 | 43.9 years (18 to 80 years) | 151 M (62.4%), 91 F (37.6%) |
| M89-349 | multicenter, double-blind, active-controlled | Lansoprazole Delayed Release Capsules: 30 mg QD, Oral Ranitidine 150 mg b.i.d, Oral 12 weeks | 151 | 52.4 years (22 – 79 years) | 106 M (70.2%), 45 F (29.8%) |
| M88-271 | multicenter, double-blind, controlled trials | Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, Oral Placebo 12 months | 170 | 44.8 years (19 – 80 years) | 92 M (54.1%), 78 F (45.9%) |
| M89-350 | multicenter, double-blind, controlled trials | Lansoprazole Delayed Release Capsules: 15 mg | 146 | 54.4 years (24 – 83 years) | 107 M (73.3%), 39 F |
QD, 30 mg QD, Oral Placebo 12 months | (26.7%) | ||||
| D75P506 | multicenter, double-blind, comparative prospectively randomized trial | Lansoprazole Delayed Release Capsules: 15 mg QD, 30 mg QD, Oral Ranitidine, Oral 300 mg b.i.d 12 months | 221* | 57.0 years (20 to 79 years) | 180 M (67.7%), 86 F (32.3%) |
Swarbrick et al. (1996) | multicenter, double-blind, randomised trial | Lansoprazole Delayed Release Capsules: 30 mg QD, Oral Ranitidine 300 mg b.i.d, Oral 12 months | 158 | 68.0 years (18 – 85 years) | 83 M (52.5%), 75 F (47.5%) |
* 266 patients were enrolled; 221 patients were evaluable.
In a U.S. multicenter, double-blind, placebo-controlled study of 269 patients entering with an endoscopic diagnosis of esophagitis with mucosal grading of 2 or more and grades 3 and 4 signifying erosive disease, the percentages of patients with healing are presented in Table 19.
Table 19. Reflux Esophagitis Healing Rates
| Week | Lansoprazole Delayed Release Capsules 15 mg once daily (N = 69) | Lansoprazole Delayed Release Capsules 30 mg once daily (N = 65) | Lansoprazole Delayed Release Capsules 60 mg once daily (N = 72) | Placebo (N = 63) |
| 4 | 67.6%* | 81.3%† | 80.6%† | 32.8% |
| 6 | 87.7%* | 95.4%* | 94.3%* | 52.5% |
| 8 | 90.9%* | 95.4%* | 94.4%* | 52.5% |
* (p ≤ 0.001) versus placebo. † (p ≤ 0.05) versus Lansoprazole Delayed Release Capsules 15 mg. | ||||
In this study, all lansoprazole delayed-release capsules groups reported significantly greater relief of heartburn and less day and night abdominal pain along with fewer days of antacid use and fewer antacid tablets taken per day than the placebo group.
Although all doses were effective, the earlier healing in the higher two doses suggest 30 mg once daily as the recommended dose.
Lansoprazole delayed-release capsules were also compared in a U.S. multicenter, double-blind study to a low dose of ranitidine in 242 patients with erosive reflux esophagitis. Lansoprazole delayed-release capsules at a dose of 30 mg were significantly more effective than ranitidine 150 mg twice daily as shown in Table 20.
Table 20. Reflux Esophagitis Healing Rates
| Week | Lansoprazole Delayed Release Capsules 30 mg once daily (N = 115) | Ranitidine 150 mg twice daily (N = 127) |
| 2 | 66.7%* | 38.7% |
| 4 | 82.5%* | 52.0% |
| 6 | 93.0%* | 67.8% |
| 8 | 92.1%* | 69.9% |
| * (p ≤ 0.001) versus ranitidine. | ||
In addition, patients treated with lansoprazole delayed-release capsules reported less day and nighttime heartburn and took less antacid tablets for fewer days than patients taking ranitidine 150 mg twice daily.
In the two trials described and in several smaller studies involving patients with moderate to severe erosive esophagitis, lansoprazole delayed-release capsules produced healing rates similar to those shown above.
In a U.S. multicenter, double-blind, active-controlled study, 30 mg of lansoprazole delayed-release capsules were compared with ranitidine 150 mg twice daily in 151 patients with erosive reflux esophagitis that was poorly responsive to a minimum of 12 weeks of treatment with at least one H2-receptor antagonist given at the dose indicated for symptom relief or greater, namely cimetidine 800 mg/day, ranitidine 300 mg/day, famotidine 40 mg/day or nizatidine 300 mg/day. Lansoprazole delayed-release capsules 30 mg were more effective than ranitidine 150 mg twice daily in healing reflux esophagitis and the percentage of patients with healing are presented in Table 21.
This study does not constitute a comparison of the effectiveness of histamine H2-receptor antagonists with lansoprazole delayed-release capsules as all patients had demonstrated unresponsiveness to the histamine H2-receptor antagonist mode of treatment. It does indicate, however, that lansoprazole delayed-release capsules may be useful in patients failing on a histamine H2-receptor antagonist.
Table 21. Reflux Esophagitis Healing Rates in Patients Poorly Responsive to Histamine H2-Receptor Antagonist Therapy
| Week | Lansoprazole Delayed Release Capsules 30 mg once daily (N = 100) | Ranitidine 150 mg twice daily (N = 51) |
| 4 | 74.7%* | 42.6% |
| 8 | 83.7%* | 32.0% |
| * (p ≤ 0.001) versus ranitidine. | ||
Long-Term Maintenance Treatment of Reflux Esophagitis
U.S. Studies
Two independent, double-blind, multicenter, controlled trials were conducted in patients with endoscopically confirmed healed esophagitis. Patients remained in remission significantly longer and the number of recurrences of reflux esophagitis was significantly less in patients treated with lansoprazole delayed-release capsules than in patients treated with placebo over a 12-month period (Table 22).
Table 22. Endoscopic Remission Rates (U.S. Study)
| Trial | Drug | No. of Patients | % in Endoscopic Remission 0 to 3 months | % in Endoscopic Remission 0 to 6 months | % in Endoscopic Remission 0 to 12 months |
| 1 | Lansoprazole Delayed Release Capsules 15 mg once daily | 59 | 83%* | 81%* | 79%* |
| Lansoprazole Delayed Release Capsules 30 mg once daily | 56 | 93%* | 93%* | 90%* | |
| Placebo | 55 | 31% | 27% | 24% | |
| 2 | Lansoprazole Delayed Release Capsules 15 mg once daily | 50 | 74%* | 72%* | 67%* |
| Lansoprazole Delayed Release Capsules 30 mg once daily | 49 | 75%* | 72%* | 55%* | |
| Placebo | 47 | 16% | 13% | 13% | |
% = Life Table estimate *(p ≤ 0.001) versus placebo | |||||
Regardless of initial grade of reflux esophagitis, lansoprazole delayed-release capsules 15 mg and 30 mg were similarly effective in maintaining remission.
European Studies
The first study, a double-blind, multicenter, comparative prospectively randomized trial was conducted in patients with endoscopically confirmed healed esophagitis. Patients remained in remission significantly longer and the number of recurrences of reflux esophagitis was significantly less in patients treated with lansoprazole delayed-release capsules than in patients treated with ranitidine over a 12-month period (Table 23).
Table 23. Endoscopic Remission Rates (European Studies)
| Drug | No. of Patients | % in Endoscopic Remission 0 to 6 months | % in Endoscopic Remission 0 to 12 months |
| Lansoprazole Delayed Release Capsules 15 mg once daily | 80 | 81.1%* | 66.1%* |
| Lansoprazole Delayed Release Capsules 30 mg once daily | 71 | 85.6%* | 77.4%* |
| Ranitidine 300 mg twice daily | 70 | 38.1% | 29.8% |
% = Life Table estimate *(p ≤ 0.001) versus placebo | |||
The second study, a double-blind, multicenter, randomised trial was conducted in patients with symptomatic and endoscopically confirmed esophageal stricture resulting from reflux esophagitis. A higher proportion of patients in the ranitidine group required re-dilatation during the 12-month period compared to the lansoprazole delayed-release capsules group, but this difference was not statistically significant (Table 24).
Table 24. Proportion of Patients Requiring Re-Dilatation (European Study)
| Time | Proportion of Patients Requiring Re-Dilatation | |
| Lansoprazole Delayed Release Capsules 30 mg once daily | Ranitidine 300 mg twice daily | |
| Month 6 | 31.4% (22/70) | 40.8% (29/71) |
| Month 12 | 34.3% (24/70) | 46.5% (33/71) |
14.1.3 Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome
Table 25. Summary of patient demographics for clinical trials in Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome
| Study # | Study design | Dosage*, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| M88-139 | single center, open-label, non-randomized, | Lansoprazole Delayed Release Capsules: 15 mg | 21 | 49 years (27-68 years) | 10 M (47.6%), 11 F |
short-term dose determination phase and long-term treatment phase | every other day to 180 mg per day, Oral Up to 5.0 years | (52.4%) | |||
| M89-405 | single center, open-label, short-term dose determination phase and long-term treatment phase | Lansoprazole Delayed Release Capsules: 15 mg every other day to 180 mg per day, Oral Up to 12.8 years | 75 | 52 years (22-88 years) | 50 M (66.7%), 25 F (33.3%) |
| M90-436 | single center, open-label, non-randomized, short-term dose determination phase and long-term treatment phase | Lansoprazole Delayed Release Capsules: 15 mg every other day to 180 mg per day, Oral Up to 8.04 years | 9 | 53 years (35-76 years) | 8 M (88.9%), 1 F (11.1%) |
* Initial doses were titrated to the individual patients need, and adjustments were necessary with time in some patients
In three open studies of 105 patients with pathological hypersecretory conditions, such as Zollinger-Ellison Syndrome (ZES) with or without multiple endocrine adenomas, lansoprazole delayed-release capsules significantly inhibited gastric acid secretion and controlled associated symptoms of diarrhea, anorexia and pain. Doses ranging from 15 mg every other day to 180 mg per day maintained basal acid secretion below 10 mEq/hr in patients without prior gastric surgery, and below 5 mEq/hr in patients with prior gastric surgery.
The majority of patients studied were treated with lansoprazole delayed-release capsules between 1 to 6 years (Table 26). Initial doses were titrated to the individual patients need, and adjustments were necessary with time in some patients (see 4.2 Recommended Dose and Dosage Adjustment). Lansoprazole delayed-release capsules were well tolerated at these high dose levels for prolonged periods (greater than 4 years in some patients). In most ZES patients, serum gastrin levels were not modified by lansoprazole delayed-release capsules. However, in some patients serum gastrin increased to levels greater than those present prior to initiation of lansoprazole delayed-release capsules therapy.
Consistent with its control of acid secretion, lansoprazole delayed-release capsules were also effective in controlling the associated symptoms experienced due to increased gastric acid secretion. In addition to symptom control, lansoprazole delayed-release capsules were effective in healing duodenal ulcers and/or gastric ulcers and erosive reflux esophagitis.
Table 26. Summary of the Major Results from the Principal Zollinger-Ellison Syndrome (ZES) Studies
| Study 1 | Study 2 | Study 3 | |||||||||||||||
| (N = 21) | (N = 75) | (N = 9) | |||||||||||||||
| No. of Patients Entering Maintenance Phase | 20 | 72 | 8 | ||||||||||||||
| Age (yr) | |||||||||||||||||
| Mean | 49 | 52 | 53 | ||||||||||||||
| Range | 27-68 | 22-88 | 35-76 | ||||||||||||||
| Gender (No. of Patients) | |||||||||||||||||
| Male | 10 | 50 | 8 | ||||||||||||||
| Female | 11 | 25 | 1 | ||||||||||||||
| Baseline BAO (mEq/h) | |||||||||||||||||
| Mean | 38.7 | 23.8 | 31.8 | ||||||||||||||
| Range | 9.9-143.9 | 5.5-96.5 | 13.4-64.5 | ||||||||||||||
| Duration of Follow-up (yr) | |||||||||||||||||
| Mean | 3.3 | 5.5 | 5.2 | ||||||||||||||
| Range | 0.5-5.0 | 0.005-12.8 | 0.02-8.04 | ||||||||||||||
| Cumulative No. of Patients with Follow-up: | |||||||||||||||||
| > 1 year | 17 | 61 | 8 | ||||||||||||||
| > 3 years | 14 | 46 | 7 | ||||||||||||||
| > 6 years | 0 | 32 | 4 | ||||||||||||||
| No. of Patients with a Final Maintenance Visit | 20 | 67 | 8 | ||||||||||||||
| Lansoprazole Delayed-Release Capsules Dose/24h at Final Maintenance Visit | |||||||||||||||||
| Median | 52.5 | 82.5 | 22.5 | ||||||||||||||
| Range | 30-120 | 0-450 | 15-180 | ||||||||||||||
| BAO at a Final Maintenance Visit (mEq/h) | |||||||||||||||||
| Mean | 1.2 | 2.2 | 1.29 | ||||||||||||||
| Range | 0.0-7.1 | 0.0-24.1 | 0.0-4.8 | ||||||||||||||
| % (No. Patients with BAO < 10 mEq/h) at Final | 100 (20) | 97 (65) | 100 (8) | ||||||||||||||
| Maintenance Visit | |||||||||||||||||
| % of Patients with Dose Change from End of Titration to Final Maintenance Visit | |||||||||||||||||
| Increase | 5 | NV* | 12.5 | ||||||||||||||
| Decrease | 40 | NV* | 50 | ||||||||||||||
| No Change | 15 | NV* | 37.5 | ||||||||||||||
| Both Increased and Decreased | 40 | NV* | NV* | ||||||||||||||
NV* = No data available
14.3 Comparative Bioavailability Studies
LANSOPRAZOLE
Two comparative bioequivalence studies were conducted on LANSOPRAZOLE (Lansoprazole Delayed-Release Capsules) against PREVACID® as follows:
- A blinded randomized, single oral dose, two-way crossover bioequivalence study to compare Lansoprazole 30 mg Delayed Release Capsules (Sanis Health Inc., Toronto, Canada.) with PREVACID® (Lansoprazole) Delayed-Release Capsules 30 mg (Distributed by: Abbott Laboratories Limited, Quebec, [Canada]) in 57 healthy Asian adult male study participants under fed conditions.
- A blinded randomized, single oral dose, two-way crossover bioequivalence study to compare Lansoprazole 30 mg Delayed Release Capsules (Sanis Health Inc., Toronto, Canada.) with PREVACID® (Lansoprazole) Delayed-Release Capsules 30 mg (Distributed by: Abbott Laboratories Limited, Quebec, [Canada]) in 44 healthy Asian adult male (41) and female (3) study participants under fasting conditions.
The comparative bioavailability data for these studies are summarized in the tables below:
Summary Table of the Comparative Bioavailability Data [single dose Fed studies]
Lansoprazole (1 x 30 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
Lansoprazole (1 x 30 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | LANSOPRAZOLE 30 mg Delayed Release Capsules* | PREVACID® 30 mg Delayed-Release Capsules† | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
| Parameter | LANSOPRAZOLE 30 mg Delayed Release Capsules* | PREVACID® 30 mg Delayed-Release Capsules† | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
AUCT (ng.h/ml) | 698.886 1284.080 (132.58) | 702.272 1585.219 (148.15) | 100 | 85 to 116 |
AUCI (ng.h/ml) | 773.176 1425.554 (130.20) | 768.429 1758.965 (150.79) | 100 | 86 to 117 |
Cmax (ng/ml) | 185.268 285.774 (107.05) | 175.397 283.954 (108.62) | 106 | 92 to 121 |
Tmax§ (h) | 5.000 (1.500 – 7.000) | 4.500 (2.000 – 7.000) | ||
T½€ (h) | 2.28 (96.30) | 2.37 (92.49) | ||
* LANSOPRAZOLE (Sanis Health Inc., Toronto, Canada)
† PREVACID® (manufactured by TAP Pharmaceuticals Inc, and distributed by Abbott Laboratories Limited) was purchased in Canada
§ Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV%) only
Summary Table of the Comparative Bioavailability Data [single dose Fasted studies]
Lansoprazole 1 x 30 mg Lansoprazole From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
Lansoprazole 1 x 30 mg Lansoprazole From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | LANSOPRAZOLE 30 mg Delayed Release Capsules* | PREVACID® 30 mg Delayed-Release Capsules† | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
| Parameter | LANSOPRAZOLE 30 mg Delayed Release Capsules* | PREVACID® 30 mg Delayed-Release Capsules† | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
AUCT (ng.h/ml) | 5071.998 6541.119 (71.27) | 4652.978 5942.220 (72.88) | 109 | 103 to 116 |
AUCI (ng.h/ml) | 5116.036 6757.937 (78.03) | 4805.317 6290.100 (78.42) | 107 | 102 to 113 |
Cmax (ng/ml) | 1217.129 1282.867 (29.73) | 1095.907 1158.862 (33.05) | 111 | 102 to 120 |
| Tmax§ | 2.000 | 2.000 | ||
| (h) | (1.000 – 4.500) | (1.000 – 4.000) | ||
T½€ (h) | 2.97 (73.78) | 2.97 (74.87) | ||
* LANSOPRAZOLE (Sanis Health Inc., Toronto, Canada)
† PREVACID® (manufactured by TAP Pharmaceuticals Inc, and distributed by Abbott Laboratories Limited) was purchased in Canada
§ Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV%) only
LANSOPRAZOLE FDT
Two comparative bioequivalence studies were conducted on LANSOPRAZOLE FDT (Lansoprazole Fast-Disintegrating, Delayed-Release Tablets) against PREVACID® FasTab as follows:
- A single-dose, randomized, balanced, double-blind, two-treatment, two-sequence, two-period, two-way crossover bioequivalence study of 1 x 30 mg LANSOPRAZOLE FDT Tablets of Sanis Health Inc. with that of 1 x 30 mg PrPREVACID® FasTab Lansoprazole Fast-Disintegrating, Delayed-Release Tablets of Abbott Laboratories, Canada in 33 healthy, adult, Asian male, human volunteers under fasting conditions.
- A single-dose, randomized, balanced, double-blind, two-treatment, two-sequence, two-period, two-way crossover bioequivalence study of 1 x 30 mg LANSOPRAZOLE FDT Tablets of Sanis Health Inc. with that of 1x 30 mg PrPREVACID® FasTab Lansoprazole Fast-Disintegrating, Delayed-Release Tablets 30 mg of Abbott Laboratories, Canada in 35 healthy, adult, Asian male, human volunteers under fed conditions.
The summary of results for Lansoprazole is presented in the following tables:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA [single dose Fasted studies]
Lansoprazole (1x30 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference † | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/mL) | 5943.0 7369.6 (65.02) | 5653.3 7354.1 (70.40) | 105.1 | 94.63-116.78 |
AUCI (ng.h/mL) | 6084.2 7641.9 (67.96) | 5795.5 7655.6 (73.29) | 105.0 | 94.52-116.60 |
Cmax (ng/mL) | 1565.38 1660.23 (33.46) | 1421.76 1542.40 (37.25) | 110.1 | 96.70-125.36 |
Tmax§ (h) | 2.00 (1.00-4.50) | 2.00 (1.00-5.00) | ||
T½€ (h) | 2.81 (61.10) | 2.93 (63.13) | ||
* LANSOPRAZOLE FDT, 30 mg fast disintegrating, delayed release tablets manufactured for Sanis Health Inc..
† PREVACID® FasTab, 30 mg delayed release tablets (Abbott Laboratories Canada) were purchased in Canada.
§ Expressed as the median (range) only.
€ Expressed as the arithmetic mean (CV%) only.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA [single dose Fed studies]
Lansoprazole (1x30 mg) From measured data Geometric Least squares Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference † | % Ratio of Geometric Means ׀ | 90% Confidence Interval |
AUCT (ng.h/mL) | 3858.9 4813.6 (60.66) | 3823.8 4472.9 (58.55) | 100.9 | 87.67-116.18 |
AUCI (ng.h/mL) | 4042.7 5081.4 (63.52) | 4098.0 4830.4 (60.16) | 98.6 | 85.80-113.42 |
Cmax (ng/mL) | 611.81 701.28 (43.63) | 566.81 622.01 (42.27) | 107.9 | 92.25-126.30 |
Tmax§ (h) | 4.50 (2.00-7.00) | 5.00 (2.50-8.00) | ||
T½€ (h) | 3.42 (46.04) | 3.91 (55.14) | ||
* LANSOPRAZOLE FDT, 30 mg fast disintegrating, delayed release tablets manufactured for Sanis Health Inc.
† PREVACID® FasTab, 30 mg delayed release tablets (Abbott Laboratories Canada) were purchased in Canada.
׀ Based on least-squares mean estimates.
§ Expressed as the median (range) only.
€ Expressed as the arithmetic mean (CV%) only.
15 MICROBIOLOGY
No microbiological information is required for this drug product
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
Mouse and Rat: In an acute toxicity study, lansoprazole administered via the oral, subcutaneous and intraperitoneal routes was studied in groups of 5M, 5F Wistar rats and 5M, 5F ICR mice. Lansoprazole was suspended in 5% gum arabic adjusted to pH 7 for administration by all 3 routes. The LD50 by the oral route in both rats and mice was greater than 5000 mg/kg, the highest dose tested. There were no deaths in either study. The only clinical sign noted was dark brown urine in mice.
By the subcutaneous route, the LD50 was again greater than 5000 mg/kg, the highest dose tested. Again, there were no deaths in either species. Scratching at the injection site and abdominal stretching were observed in mice. There were no clinical signs in rats. Drug remnants were seen at the injection sites in both species.
Finally, when lansoprazole was administered via the intraperitoneal route, there were no deaths in mice at 5000 mg, but several rats of both sexes died within 2 days after dosing. Surviving rats were normal by the second day after dosing. The LD50 in rats was approximately 5000 mg. Abdominal stretching, decreases in activity, respiratory depression, and hypotonia of abdominal muscles were seen in rats and mice. Dark purple urine was also seen in mice. At autopsy, drug remnants were seen in the peritoneal cavity in animals of both species. Discoloration of the liver was also seen in rats that died at 5000 mg. These studies demonstrated that lansoprazole has a very low degree of toxicity when given as a single dose by either the oral, subcutaneous, or intraperitoneal routes.
In an acute toxicity study of several metabolites, a contaminant, and partially degraded lansoprazole (40°C and 75% relative humidity for 6 months) were determined in ICR mice. The compounds and the routes tested were pyridyl-oxide derivative (oral), sulfonyl derivative or metabolite VII (oral and intraperitoneal), thio derivative or metabolite I (oral and intraperitoneal), 5-hydroxy derivative or metabolite VI (intraperitoneal), and partially degraded lansoprazole (oral). There were no deaths, and the LD50 values in all cases were therefore greater than 5 g/kg, the limit dose. With oral administration, clinical signs were seen only with partially degraded lansoprazole. These included decreased activity, respiratory depression, hypo-irritability (decreased responsiveness), ataxia, and flattened posture (prostration). With intraperitoneal administration, decreased activity, hypo-irritability, and respiratory depression were seen with metabolites VI and VII. In addition, with metabolite VII, chromaturia (dark purple urine) and soft feces or diarrhea were seen. These findings are all similar to the results of previous acute toxicity studies with lansoprazole. Therefore, none of the tested compounds were more toxic than lansoprazole itself.
Dog: In a single-dose study, 2 male beagle dogs per group (fasted for 18 hours) were given lansoprazole orally by gavage at doses of 500, 1000, and 2000 mg/kg. The drug was suspended in 5% gum arabic, pH 7. The dogs were observed for 15 days after dosing and subjected to necropsy. Organ weights and histopathologic assessments of selected organs were obtained. There were no deaths, no treatment-related clinical signs, no effects on body weight or food consumption, no effects on weights of major organs, and no treatment-related gross or histopathologic changes. Therefore, a single dose of 2000 mg/kg was non-toxic. Higher dosing was not justified for humane reasons.
Long-Term Toxicity
Mouse: In a 3-month study, lansoprazole was given by oral gavage to groups of 10 male and 10 female CD-1 mice at dosages of 0, 15, 50, and 150 mg/kg/day. The vehicle was 5% gum arabic. Clinical signs, body weight, and food consumption were monitored. At the end of the study, blood was collected for hematology and biochemistry measurements. All animals were necropsied. Histologic evaluations were conducted on high-dosage and control animals, and stomachs were evaluated histologically in all animals.
There were no treatment-related deaths and no effects on clinical signs, body weight, food consumption, hematology, or serum chemistry variables. There were no treatment-related gross pathologic changes. Stomach weights were increased, and hyperplasia/hypertrophy of the glandular stomach was seen histologically at 50 and 150 mg/kg/day. These changes were secondary to the pharmacologic activity of the compound.
In a 13-week study, lansoprazole was given by oral gavage to groups of 10 male and 10 female CD-1 mice at dosages of 0, 150, 300, 600, 1200, and 2400 mg/kg/day. The drug was suspended in 5% gum arabic, pH 7. There were 3 possibly drug-related deaths at 2400 mg/kg/day. The only clinical sign observed was purple urine seen in all drug-treated groups. There were slight decreases (approximately 10 to 13% relative to controls) in hematocrit, hemoglobin, and erythrocyte counts in all drug-treated groups. Neutrophils were slightly decreased in drug-treated females. Total serum protein was decreased at 300 mg/kg/day or more. Stomach weights were increased in all drug-treated groups. Liver weights were increased at 300 mg/kg/day or more. Testis weights were decreased at 1200 and 2400 mg/kg/day. At necropsy, the glandular stomach appeared thickened, and erosions of the mucosa were evident at all dosages. The testes appeared small at 1200 and 2400 mg/kg/day. Histologically, hyperplasia and vacuolation were seen in the gastric fundic mucosa in all drug-treated groups. A mild, chronic gastritis was seen at 300 mg/kg/day or more. Hepatocellular hypertrophy and vacuolation were seen at 150 mg/kg/day or more, and a brown pigment was seen in the liver mainly at 2400 mg/kg/day. Seminiferous tubular atrophy and aspermatogenesis were seen with increased incidence at 1200 and 2400 mg/kg/day. Reduced amount of sperm was seen in the epididymides at 1200 mg/kg/day or more. A no-toxic-effect dosage was not determined in this study. The maximum therapeutic dose was judged to be in the range of 300 to 600 mg/kg/day.
Rat: In a 3-month study, lansoprazole was administered by gavage to groups of 15 Sprague-Dawley rats/sex at dosages of 0, 5, 15, 50, and 150 mg/kg/day, 7 days per week. The drug was suspended in 5% gum arabic, pH 7.
There were no deaths and no behavioural signs of toxicity. Body weight was decreased in males at 150 mg/kg/day. There was no effect on food consumption. Hemoglobin and mean cell hemoglobin were decreased in females at 50 mg/kg/day or more, and in males at 150 mg/kg/day. Hematocrit was also decreased in males and females, and mean erythrocyte volume was decreased in males at 150 mg/kg/ day. Total leukocyte counts were increased in females at 50 mg/kg/day or more. Serum total protein and globulin were decreased and A/G ratio increased in males at 150 mg/kg/day. There were no gross lesions noted at necropsy. Stomach weight was increased at 15 mg/kg/day or more. Liver weights were increased in females at 15 mg/kg/day or more. Thyroid and uterus weights were increased at 150 mg/kg/day. Thymus weights were decreased at 50 mg/kg/day or more. Histologically, thymic atrophy was observed at 15 mg/kg/day or more. In the stomach, increased chief cell hypertrophy, eosinophilia and single cell necrosis, eosinophilic material in gastric glands, and increased squamous cell hyperplasia and hyperkeratosis at the junction of the glandular and non-glandular mucosa were observed at 50 mg/kg/day or more.
Toxicity was demonstrated by decreased body weight in males, hematologic changes, decreases in serum protein, thymic atrophy, and chief cell necrosis. Hematologic changes and chief cell necrosis occurred at 50 mg/kg/day or more. Thymic atrophy was observed at 15 mg/kg/day or more. Therefore, the no-toxic-effect dosage was 5 mg/kg/day.
In a 4-week study, lansoprazole was administered orally by gavage to 10 Wistar rats/sex/group at dosages of 0, 15, 50, and 150 mg/kg/day (7 days/week). The drug was suspended in 5% gum arabic for administration.
There were no deaths and no behavioural signs of toxicity. Body weight gain was suppressed in males by 7% at 50 mg/kg/day and by 15% at 150 mg/kg/day. Food consumption was decreased in both sexes at 150 mg/kg/day and in males at 50 mg/kg/day. Hepatic drug-metabolizing enzymes, aminopyrine-N-demethylase and aniline hydroxylase activities, were increased at 150 mg/kg/day. Thymic atrophy was noted at necropsy at 150 mg/kg/day. Thymic weights were decreased 21 to 27% at 50 mg/kg/day and 48 to 49% at 150 mg/kg/day. Liver weights were increased at 50 and 150 mg/kg/day. Adrenal weights were increased in females at 150 mg/kg/day. Histologically, centrilobular hepatocellular hypertrophy was seen in the liver at 150 mg/kg/day. An increase in smooth endoplasmic reticulum in the liver was seen by electron microscopy. In the stomach, vacuolation of parietal cells and apical eosinophilia of chief cells were seen histologically, while dilation of parietal cell tubulovesicles was seen by electron microscopy at 150 mg/kg/day.
Toxicity was demonstrated by decreases in body weight gain and food consumption, and thymic atrophy at 50 mg/kg/day or more. The no-toxic-effect dosage was 15 mg/kg/day.
In a 13-week study, lansoprazole was administered to Wistar rats (10/sex/group) at dosages of 0, 5, 15, and 50 mg/kg/day, 7 days/week. The drug was suspended in 5% gum arabic adjusted to pH 7.
There were no deaths and no behavioral signs of toxicity. Body weight was decreased 5 to 6% in both sexes by the end of the study at 50 mg/kg/day. There were no treatment-related effects on hematology, serum chemistry, or urinalysis variables. Measurements of plasma T3, T4, and TSH in the high-dosage and control animals revealed no differences between the 2 groups. Statistically significant elevations in serum gastrin, determined 20 hours post-dosing at the end of the study, were obtained in females at 15 mg/kg/day or more and in males at 50 mg/kg/day. At necropsy, the stomach glandular mucosa was observed to be thickened in both sexes at 50 mg/kg/day and in females at 15 mg/kg/day. Stomach weights were increased at all dosages.
Thymus and submaxillary weights were decreased at 50 mg/kg/day. Histologically, centrilobular hepatocellular hypertrophy was seen in the liver at 50 mg/kg/day. In the stomach, increased argyrophil cell density, hypertrophy of parietal cells, and sporadic necrosis of chief cells were seen at 50 mg/kg/day. Chief cell eosinophilia, hypertrophy, and hyperplasia were seen at all dosages. Dilation of tubulovesicles in parietal cells and small, dense granules in chief cells were seen by electron microscopy at 50 mg/kg/day.
Toxicity was demonstrated by decreased body and thymus weights and chief cell necrosis at 50 mg/kg/day. The no-toxic-effect dosage was 15 mg/kg/day.
In a 13-week study, male Wistar rats were given daily dosages of 50 mg/kg/day lansoprazole orally by gavage, and were then allowed to recover without treatment for periods of 4, 13, or 26 weeks. A control group was given vehicle (5% gum arabic, pH 7). There were 10 rats for each of the necropsy intervals (13 weeks treatment, 4 weeks recovery, 13 weeks recovery, and 26 weeks recovery).
The changes observed at the end of 13 weeks of treatment were similar to those seen at 50 mg/kg/day in the previous 13-week study. In this study, gastrin-secreting cells (G cells) were determined in the stomach pylorus by immunohistochemical staining. The volume density of G cells was found to be increased after 13 weeks of treatment. All of the changes were found to be reversible after 4 weeks recovery without treatment except stomach weight, changes in chief cells, and the increase in argyrophil cells. The increase in argyrophil cells was reversible after 13 weeks of recovery. Necrosis, eosinophilia, hypertrophy, and hyperplasia of chief cells showed partial reversal after 4 and 13 weeks recovery and complete reversal after 26 weeks, recovery. Stomach weight in the treated group was comparable to controls after 26 weeks of recovery.
In a 6-month study, lansoprazole was given to Sprague-Dawley rats (12/sex/group) at dosages of 0, 2, 10, and 50 mg/kg/day, 7 days/week. The drug was suspended in 5% gum arabic, pH 7, and administered orally by gavage.
There were no treatment-related deaths, no behavioral signs of toxicity, no effects on body weight or food consumption, and no treatment-related changes in serum chemistry or urinalysis variables. There was a transient decrease in hematocrit, mean erythrocyte cell volume, and mean erythrocyte cell hemoglobin at 50 mg/kg/ day after 3 months of treatment. This was not seen at the end of the study. Stomach weight was increased in females at all dosages and in males at 10 mg/kg/ day or more. Thymus weights were decreased at 50 mg/kg/day. Histologically, thymic atrophy was seen at 10 mg/kg/day or more. In the stomach, increased hypertrophy, eosinophilia, and single cell necrosis of chief cells and an increase in argyrophil cells were seen at 10 mg/kg/day or more. At 50 mg/kg/day, dilation of gastric glands and increased severity of inflammatory cell accumulation, squamous cell hyperplasia, and hyperkeratosis at the junction of the glandular and nonglandular mucosa were seen.
Toxicity was demonstrated by the hematologic changes at 50 mg/kg/day, thymic atrophy at 10 mg/kg/day or more, and chief cell necrosis at 10 mg/kg/day or more. The no-toxic-effect dosage was 2 mg/kg/day.
In a 1-year study, lansoprazole was administered by oral gavage to Sprague-Dawley rats (30/sex/group) at dosages of 0, 1.5, 5, 15, and 50 mg/kg/day, 7 days per week. The vehicle was 5% gum arabic adjusted to pH 7.
There were no treatment-related deaths and no behavioral signs of toxicity. Body weight gain was decreased in males at 50 mg/kg/day, but there was no effect on food consumption. Hematocrit and hemoglobin were decreased at 50 mg/kg/day. There were no treatment-induced changes in serum chemistry or urinalysis variables. Stomach weight was increased at 5 mg/kg/day or higher. Liver weight was increased in females, while thymus weight was decreased in males at 50 mg/kg/day. Histologic evidence of thymic atrophy was also seen at 50 mg/kg/day. In the stomach, hypertrophy, eosinophilia and necrosis of chief cells was seen at 5 mg/kg/ day or more. Dilated gastric glands and increased incidence of argyrophil cells were seen at 15 mg/kg/day or more. Increased severity of inflammatory cells, squamous hyperplasia, and hyperkeratosis at the junction of the glandular and nonglandular mucosa was seen at 50 mg/kg/day. In the testis at 50 mg/kg/day, an increased incidence of Leydig (interstitial) cell hyperplasia was observed, and a single, benign Leydig cell tumor was found.
Toxicity was characterized by decreased body weight gain in males, decreases in hematocrit and hemoglobin, thymic atrophy, and Leydig cell hyperplasia at 50 mg/kg/day and by chief cell necrosis at 5 mg/kg/day or more. The no-toxic-effect dosage was 1.5 mg/kg/day.
Dog: In a 6-month study, lansoprazole was given to 4 beagle dogs/sex/group in hard gelatin capsules at dosages of 0, 2, 10, and 50 mg/kg/day 7 days per week.
There were no deaths or behavioral signs of toxicity. There were no treatment-related effects on body weight, food consumption, urinalysis, or ophthalmologic, electrocardiographic, or serum chemistry variables. One dog in the high-dosage group had a few atrioventricular (A-V) nodal escape beats; however, this sometimes occurs spontaneously in dogs and was not considered treatment related either by the sponsor or a consulting veterinary cardiologist. There were transient (present at 3 months but not at 6 months) decreases in hematocrit, hemoglobin, and erythrocyte counts in males at 2 and 10 mg/kg/day. Hematocrit, hemoglobin, mean cell hemoglobin, and mean erythrocyte volume were persistently decreased at both 3 and 6 months at 50 mg/kg/day in males. Total leukocyte count was increased in females at 50 mg/kg/day. There were no treatment-related findings at necropsy. Thymus weight was decreased in males at 50 mg/kg/day. Histologically, increased vacuolation of parietal cells in the gastric mucosa was seen at 10 mg/ kg/day or more.
Toxicity was characterized by hematologic changes and by decreased thymus weights at 50 mg/kg/day. The no-toxic effect dosage was 10 mg/kg/day.
In a 12-month study, Beagle dogs were given lansoprazole in hard gelatin capsules at dosages of 0, 1.5, 5, 15, and 50 mg/kg/day, 7 days per week. There were 4 dogs/sex/group. There were 2 deaths, 1 male each at 15 and 50 mg/kg/day.
In surviving dogs, there were no behavioral signs of toxicity, no effects on body weight or food consumption, no treatment-related ophthalmoscopic findings, and no effects on serum chemistry or urinalysis variables. There were no electrocardiogram (ECG) abnormalities in any of the dogs in the study. Total leukocyte counts were increased at 15 and 50 mg/kg/day; the increase at 15 mg/kg/day was transient (present at 3 months but not at later intervals) and in males only. Prostate weight was decreased at 5 mg/kg/day or more. Histologically, increased parietal cell vacuolization was seen at all dosages.
The cause of death or moribundity could not be determined for the 2 dogs that died. There were no indications from the other dogs in the study of any toxicity that could account for these deaths. Nevertheless, a conservative approach suggests that these 2 deaths be considered the result of toxicity due to drug treatment. Therefore, the no-toxic-effect dosage for this study was 5 mg/kg/day.
Carcinogenicity: Safety concerns of long-term treatment relate to hypergastrinemia, possible enterochromaffin-like (ECL) effect and carcinoid formation. ECL cell hyperplasia and gastric carcinoid tumours were observed in four animal studies.
In two 24-month carcinogenicity studies, Sprague-Dawley rats were treated orally with doses of 5 to 150 mg/kg/day about 1 to 40 times the exposure on a body surface (mg/m2) basis of a 50 kg person of average height (1.46 m2 body surface area) given the recommended human dose of 30 mg/day (22.2 mg/m2). Lansoprazole produced dose-related gastric enterochromaffin-like (ECL) cell hyperplasia and ECL cell carcinoids in both male and female rats. It also increased the incidence of intestinal metaplasia of the gastric epithelium in both sexes. In male rats lansoprazole produced a dose related increase of testicular interstitial cell adenomas. The incidence of these adenomas in rats receiving doses of 15 to 150 mg/kg/day (4 to 40 times the recommended human dose based on body surface area) exceeded the low background incidence (range = 1.4 to 10%) for this strain of rats. Testicular interstitial cell adenoma also occurred in 1 of 30 rats treated with 50 mg/kg/day (13 times the recommended human dose based on body surface area) in a 1-year toxicity study. Testicular Leydig cell hyperplasia and tumors were also observed. The Leydig cell changes were shown through mechanistic studies to be rat-specific and not biologically relevant to humans.
In a 24-month carcinogenicity study, CD-1 mice were treated orally with doses of 15 to 600 mg/kg/day, 2 to 80 times the recommended human dose based on body surface area. Lansoprazole produced a dose-related increased incidence of gastric ECL cell hyperplasia. Lansoprazole also induced a low, non-dose-related incidence of carcinoid tumours in the gastric mucosa in several dose groups (1 female mouse in the 15 mg/kg/day group, 1 male mouse in the 150 mg/kg/day group, and 2 males and 1 female in the 300 mg/kg/day group). It also produced an increased incidence of liver tumours (hepatocellular adenoma plus carcinoma). The tumour incidences in male mice treated with 300 and 600 mg/kg/day (40 to 80 times the recommended human dose based on body surface area) and female mice treated with 150 to 600 mg/kg/day (20 to 80 times the recommended human dose based on body surface area) exceeded the ranges of background incidences in historical controls for this strain of mice. Lansoprazole treatment produced adenoma of rete testis in male mice receiving 75 to 600 mg/kg/day (10 to 80 times the recommended human dose based on body surface area).
No carcinogenic effect occurred in P53 knockout mice, which are known to be susceptible to carcinogenesis by genotoxic agents.
Analysis of gastric biopsy specimens from patients after short-term treatment of proton pump inhibitors have not detected ECL cell effects similar to those seen in animal studies. Longer term studies in humans revealed a slight increase in the mean ECL-cell density, although there was no microscopic evidence of cell hyperplasia. Similar results were seen in the maintenance treatment studies, where patients received up to 15 months of lansoprazole therapy. Serum gastrin values increased significantly from their baseline values but reached a plateau after 2 months of therapy. By 1 month post-treatment, fasting serum gastrin values returned to lansoprazole therapy baseline. Moreover, results from gastric biopsies from short-term, long-term and maintenance treatment studies indicate that there are no clinically meaningful effects on gastric mucosa morphology among lansoprazole-treated patients.
In a 2-year study, lansoprazole was administered by oral gavage to Sprague-Dawley rats (60 males and 60 females per group) at dosages of 0, 1.5, 5, 15, and 50 mg/kg/day 5 days per week. Drug was suspended in 5% gum arabic (adjusted to pH 7.0 to 7.4).
Survival rates were 27 to 33% in males and 30 to 45% in females. The median survival time was 650 days in males and 683 days in females. Body weight gain was decreased at 50 mg/kg/day in both sexes and at all dosages in females. At the end of the study, body weight gains for high-dose males and females were both decreased 20% compared to controls. There were no other clinical signs of toxicity.
The incidence of interstitial (Leydig) cell hyperplasia was increased above concurrent and historical control levels at dosages of 15 and 50 mg/kg/day. The incidence of Leydig cell tumors was increased above concurrent control levels at 15 mg/kg/day and was at the high end of the historical control range at 50 mg/kg/day. The increases in incidence of Leydig cell hyperplasia and tumors were statistically significant at 15 and 50 mg/kg/day when compared to concurrent controls. Histologically, the Leydig cell tumors appeared similar to those that occur spontaneously in Sprague-Dawley rats and in aging Fischer 344 rats.
There were numerous changes in the gastric mucosa indicative of the pharmacologic effect of lansoprazole that were similar to those seen in previous toxicity studies. This included necrosis of chief cells which was seen at 5 mg/kg/day or more. A small increase in incidence of intestinal metaplasia was seen in both sexes at 50 mg/kg/day. Detailed examination of the intestinal metaplasia foci revealed the presence of Paneth cells, indicating complete type intestinal metaplasia in virtually every case. A single, carcinoid tumor was seen in the gastric fundic mucosa in a female at 50 mg/kg/day.
The decreases in body weight gain, necrosis of chief cells, and increased incidence of Leydig cell hyperplasia and tumors demonstrated that a MTD was administered.
The results suggest that oral administration of lansoprazole at dosages of 15 and 50 mg/kg/day for 2 years leads to higher levels of interstitial (Leydig) cell hyperplasia and tumors than found in control rats. There was no evidence for any other tumorigenic response due to drug administration.
Genotoxicity: Lansoprazole was positive in the Ames assay for bacterial mutagenicity and in the chromosomal aberration studies in human lymphocytes, but it was negative in three in vivo studies for genotoxicity. Lansoprazole was not genotoxic in the ex vivo rat hepatocyte unscheduled DNA synthesis (UDS) test, the in vivo mouse micronucleus test, or the rat bone marrow cell chromosomal aberration test. Also, a mammalian cell mutagenesis assay was negative.
In vitro cytogenetics studies showed increased levels of aberrations consisting mainly of chromatid breaks which occurred only at cytotoxic concentrations. These cytotoxic concentrations were at least 50 to 60 times expected clinical blood levels of parent drug. Therefore, such concentrations will not be used in humans.
Reproductive and Developmental Toxicology: Six separate studies covering all phases of the reproductive process have been conducted. Treatment with lansoprazole caused a dose related reduction of implantations, viable fetuses and live births, and caused delayed parturition at 150 mg/kg/day.
However, lansoprazole at oral doses up to 150 mg/kg/day (40 times the recommended dose based on body surface area) was found to have no effect on fertility and reproductive performance of male and female rats.
In 2 teratology studies, lansoprazole at dosages up to 300 mg/kg/day (approximately 600 times the human dose) was administered to rats on Days 6 to 17 of pregnancy. At higher dosages (150 to 300 mg/kg/day), only decreased fetal body weights were observed. Also at higher dosages, reduced ossification of vertebrae was indicative of fetal toxicity.
In rabbits, doses of lansoprazole up to 30 mg/kg/day (approximately 60 times the human dose) were administered on Days 6 to 18 of pregnancy. A treatment-related effect on fetal mortality at 30 mg/kg/day was noted, but there were no treatment related external, skeletal, or visceral abnormalities.
Reproductive studies in pregnant rats and rabbits revealed no lansoprazole-related impairment of fertility, fetal malformations or developmental toxicity to fetuses or suckling neonates. Lansoprazole is not considered to be teratogenic.
A pre- and postnatal developmental toxicity study was conducted to assess bone development, in which lansoprazole was orally administered to female rats at doses up to 100 mg/kg/day from gestation day (GD) 6 through GD 20 after birth. A reduction in body weight gain and decreased food consumption were reported during gestation and/or lactation periods at the highest dose. At necropsy on postnatal day (PND) 21, low absolute femur weight and decreases in femur and crown-rump lengths, and a decrease in growth plate thickness in the femur were reported although no histopathological findings indicating abnormal bone development were observed.
These changes were considered to be secondary to overall growth suppression and not direct effects on bone development (see Juvenile Toxicity section for additional information).
Special Toxicology: In two 24-month toxicology studies in albino rats, drug-related retinal changes were seen at dosages of 15 mg/kg/day or higher in females and 50 mg/kg/day or higher in males. These retinal changes were similar to the spontaneous age-related and/or light induced retinal changes normally seen in rats. However, at the higher dosages, higher incidence of diffuse atrophy involving central as well as peripheral retina and a higher incidence of bilateral retinal atrophy occurred.
Retinal atrophy was only observed in albino rats treated continuously for 2 years. These changes in rats are believed to be associated with the effects of taurine imbalance and phototoxicity in a susceptible animal model. This lesion was not seen in other species including mice dogs and monkeys.
Juvenile Toxicity: Two studies were conducted to evaluate the toxicity and toxicokinetics of lansoprazole in preadolescent rats and dogs. Selected dosages for the 2 species were identical to those used in adult animals in 4-week (Wistar strain) and 13-week (Sprague Dawley strain) studies in rats and in a 13-week study in dogs. Dosing of rats continued between weaning throughout adolescence (i.e., reproductive maturity). This age-range simulated the children age group of 2- to 12 year-olds. In dogs, dosing started 2 weeks after birth and continued for 4 weeks prior to weaning, followed by 7 weeks post-weaning for a total of 13 weeks. Evaluation of the stomach was emphasized, since part of the rationale for these studies was to evaluate the threshold for toxicity in target organ(s), particularly the stomach in younger premature animals and compare it to that of adult animals.
These studies also aimed at verifying any additional effects on developmental milestones due to dosing at these young ages.
The toxicity profile in preadolescent animals was not different from adult animals, and the no observable effect level (NOEL) doses were comparable between the 2 age groups. In the pediatric population the mean total initial lansoprazole dose is 0.87 mg/kg. Accordingly, the safety margin based on the NOEL of 5 mg/kg/day in 2 species was approximately 1- to 1.5-fold, based on plasma levels for lansoprazole only (excluding its metabolites); was approximately 1- to 3.5-fold based on surface area and was about 5.7-fold relative to this clinical dose.
In a juvenile rat study, adverse effects on bone growth and development, heart valves, and male reproductive tissue were observed at lansoprazole doses higher than the maximum recommended equivalent human dose.
An eight-week oral toxicity study with a four-week recovery phase was conducted in juvenile rats with lansoprazole administered from postnatal Day 7 (age equivalent to neonatal humans) through 62 (age equivalent to approximately 14 years in humans) at doses of 40 to 500 mg/kg/day (about 1.2 to 12 times the daily pediatric dose of 15 mg in children age one to 11 years weighing 30 kg or less, based on AUC).
Changes in male reproductive tissue (testes and epididymis) occurred at a dose of 250 mg/kg/day (approximately 6 times the daily dose of 15 mg in pediatric patients based on AUC, age one to 11 years weighing 30 kg or less). Heart valve thickening occurred at a lansoprazole dose of 500 mg/kg/day (approximately 12 times the daily dose of 15 mg in pediatric patients based on AUC, age one to 11 years weighing 30 kg or less). Heart valve thickening was not observed at the next lower dose (250 mg/kg/day) and below. The findings trended towards reversibility after a four-week drug-free recovery period.
No effects on heart valves were observed in a 13-week intravenous toxicity study of lansoprazole in adolescent rats (approximately 12 years human age equivalence) at systemic exposures similar to those achieved in the eight-week oral toxicity study in juvenile (neonatal) rats.
In the eight-week oral toxicity study of lansoprazole, doses equal to or greater than 100 mg/kg/day produced delayed growth, with impairment of weight gain observed as early as postnatal Day 10 (age equivalent to neonatal humans). At the end of treatment, the signs of impaired growth at 100 mg/kg/day and higher included reductions in body weight (14% to 44% compared to controls), absolute weight of multiple organs, femur weight, femur length and crown-rump length. Femoral growth plate thickness was reduced only in males and only at the 500 mg/kg/day dose. The effects related to delayed growth persisted through the end of the 4-week recovery period. Longer term data were not collected.
In a follow-up developmental sensitivity toxicity study, juvenile rats (12 rats per treatment group) were orally administered 250 and/or 500 mg/kg/day lansoprazole for four or eight weeks starting on postnatal Day (PND) 7 (age equivalent to neonatal humans), PND 14 (age equivalent to approximately one year in humans), or PND 21 (age equivalent to approximately two years in humans).
Signs of toxicity (lower mean body weight gain and/or heart valve thickening) were observed in all dose groups of juvenile rats. Incidences of heart valve thickening were 2/12, 5/12 and 0/12, respectively, in juvenile rats in those groups dosed starting at ages 7, 14, and 21 day with 500 mg/kg/day lansoprazole for 4 weeks. Heart valve thickening in animals in those groups dosed with 500 mg/kg/day lansoprazole for eight weeks starting at PND 7, 14, and 21 were 2/12, 7/12, and 1/12, respectively.
Due to the high incidence of mortality (9 of 24 males were found dead and 15 of 24 males were euthanized between PND 18 and PND 21) in the 500 mg/kg/day dose group starting at PND 14, the 500 mg/kg/day dose groups were terminated and replaced with 250 mg/kg/day dose groups. Incidences of heart valve thickening in juvenile rats dosed with 250 mg/kg/day (approximately four times the expected lansoprazole exposure based on AUC in pediatric patients 1 to 11 years of age) starting at PND 14 were two (2/12) and one (1/12) in the four week and eight week dose groups, respectively. Incidences of the heart valve thickening were observed in almost all dose groups. Juvenile rats younger than PND 21 (age equivalent to approximately two years in humans) were more sensitive to the development of heart valve thickening.
The relevance of these findings to pediatric patients less than 12 years of age is unknown. The findings in this study are not relevant for patients 12 years of age and above.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PREVACID® Capsules, 15 mg and 30 mg and PREVACID® FasTab Tablets, 15 mg and 30 mg, submission control number: 267149, Product Monograph, Takeda Pharmaceuticals America, Inc. (MAR 16, 2023).