


Product Monograph - Lasix Oral Solution
1 INDICATIONS
LASIX ORAL SOLUTION® (furosemide) is indicated for:
- The treatment of edema associated with congestive heart failure, cirrhosis of the liver and renal disease including, nephrotic syndrome, as well as other edematous states amenable to diuretic therapy.
- The control of mild to moderate hypertension, used alone, or in combination with other antihypertensive agents in more severe cases.
Hypertensive patients who cannot be adequately controlled with thiazides will probably also not be adequately controllable with LASIX ORAL SOLUTION alone.
1.1 Pediatrics
When administered to children, LASIX ORAL SOLUTION therapy should be instituted in the hospital, in carefully selected patients, under close observation with frequent monitoring of serum electrolytes (see 4 DOSAGE AND ADMINISTRATION).
The available pediatric data does not allow for a recommendation of a specific age range in this population.
1.2 Geriatrics
Geriatrics (> 65 years of age)
Use in the geriatric population is associated with differences in safety. Dose selection for the elderly patients should be cautious, usually starting at the low end of dosage range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and the concomitant disease or other drug therapy. (see 7 WARNINGS AND PRECAUTIONS).
2 CONTRAINDICATIONS
LASIX ORAL SOLUTION (furosemide) is contraindicated in:
- Patients who are hypersensitive to furosemide, sulfonamide-derived drugs or to any ingredient in the formulation or component of the container. For a complete listing, see 4 DOSAGE AND ADMINISTRATION of the product monograph. Patients allergic to sulfonamides (e.g. sulfonamide antibiotics or sulfonylureas) may show cross-sensitivity to furosemide.
- Patients with complete renal shutdown. If increasing azotemia and oliguria occur during treatment of severe progressive renal disease, the drug should be discontinued.
- Patients with hepatic coma and pre-coma or in states of electrolyte depletion until the basic condition is improved or corrected. Therapy with LASIX ORAL SOLUTION should not be initiated in these patients (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
- Patients with severe dehydration, hypotension, hyponatremia, hypokalemia, or hypovolemia (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS).
- Jaundiced newborn infants or infants suffering from diseases (e.g. Rh incompatibility, familial non-hemolytic jaundice, etc.) as furosemide may be capable of displacing bilirubin from albumin at least "in vitro". It can lead to hyperbilirubinemia and possibly kernicterus.
- Women that are breast-feeding (see 7 WARNINGS AND PRECAUTIONS).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
LASIX ORAL SOLUTION is a potent diuretic which, if given in excessive amounts, can lead to profound diuresis with water and electrolyte depletion. Therefore, careful medical supervision is required and dose and dosage schedule have to be adjusted to the individual patient's needs (see 4 Dosage and Administration). The use of LASIX ORAL SOLUTION has been associated with exacerbation or activation of systemic lupus erythematosus. |
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Careful observations for changes in blood pressure must be made when LASIX ORAL SOLUTION is used with other antihypertensive drugs, especially during initial therapy. The dosage of other agents must be reduced by at least 50% as soon as LASIX ORAL SOLUTION is added to the regimen to prevent excessive drop in blood pressure. As the blood pressure falls under the potentiating effect of LASIX ORAL SOLUTION, a further reduction in dosage or even discontinuation of other antihypertensive drugs may be necessary.
4.2 Recommended Dose and Dosage Adjustment
Adults
Edema
The usual initial dose of LASIX ORAL SOLUTION is 4 mL to 8 mL of 10 mg/mL. Ordinarily, a prompt diuresis ensues and the starting dose can then be maintained or even reduced. If a satisfactory diuresis has not occurred within 6 hours, succeeding doses should be increased by increments of 2 mL to 4 mL of 10 mg/mL if necessary.
Maximum daily dose: 20 mL of 10 mg/mL. Once the effective single dose has been determined, it may be repeated 1 to 3 times a day.
The mobilization of edema may be most efficiently and safely accomplished by utilizing an intermittent dosage schedule in which LASIX ORAL SOLUTION is given for 2 to 4 consecutive days each week. With doses exceeding 12 mL/day of 10 mg/mL, careful clinical and laboratory observations are particularly advisable.
Hypertension
A dosage schedule of 2 mL to 4 mL of 10 mg/mL twice daily is recommended. Individualized therapy is of great importance. It is further recommended, if 4 mL twice daily of 10 mg/mL does not lead to a clinically satisfactory response, other antihypertensive agents should be added, rather than increase the dose of LASIX ORAL SOLUTION.
Pediatrics
LASIX ORAL SOLUTION therapy should be instituted in the hospital, in carefully selected patients, under close observation with frequent monitoring of serum electrolytes.
Orally, the initial dose should be in the range of 0.5 to 1.0 mg/kg body weight.
The total daily dose (given in divided doses of 6 to 12 hours apart) should not exceed 2 mg/kg orally. In the newborn and in premature babies, the daily dose should not exceed 1 mg/kg.
An intermittent dosage schedule should be adopted as soon as possible using the minimum effective dose at the longest possible intervals. Particular caution with regard to potassium levels is always desirable when LASIX ORAL SOLUTION is used in infants and children.
4.5 Missed dose
In case of a missed dose, patients may not notice any symptoms of the condition for which they are being treated for. However, please advise your patients to take the missed dose as soon as possible. And if it is almost time for their next dose, skip the missed dose and take the dose which is due as per the regular dosing schedule. Do not double dose.
5 OVERDOSAGE
Symptoms
Dehydration, electrolyte depletion and hypotension may be caused by overdosage or accidental ingestion. In cirrhotic patients, overdosage might precipitate hepatic coma.
The clinical picture in acute or chronic overdose depends primarily on the extent and consequences of electrolyte and fluid loss, e.g. hypovolemia, dehydration, hemoconcentration, cardiac arrhythmias (including A-V block and ventricular fibrillation). Symptoms of these disturbances include severe hypotension (progressing to shock), acute renal failure, thrombosis, delirious states, flaccid paralysis, apathy and confusion.
Treatment
The drug should be discontinued and appropriate corrective treatment applied: replacement of excessive fluid and electrolyte losses; serum electrolytes, carbon dioxide level and blood pressure should be determined frequently. Adequate drainage must be assured in patients with urinary bladder outlet obstruction (such as prostatic hypertrophy).
No specific antidote to furosemide is known. If ingestion has only just taken place, attempts may be made to limit further systemic absorption of the active ingredient by measures designed to reduce absorption (e.g. activated charcoal).
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Solution 10 mg/mL | Alcohol, butylated hydroxyanisol, butylated hydroxytoluene, glycerine, methylparaben, natural orange flavour, polysorbate 80, potassium sorbate, purified water, sodium hydroxide and sorbitol. |
LASIX ORAL SOLUTION
Clear, slightly yellowish liquid, with an orange odour, containing 10 mg/mL furosemide.
Available in bottles of 120 mL.
7 WARNINGS AND PRECAUTIONS
General
All patients receiving LASIX ORAL SOLUTION therapy should be observed for signs and symptoms of fluid or electrolyte imbalance, hyponatremia, hypochloremic alkalosis, hypovolemia, hypomagnesemia, or hypocalcemia: dryness of the mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pain or cramps, muscular fatigue, hypotension, oliguria, tachycardia, arrhythmia, or gastro-intestinal disturbances such as nausea and vomiting, increases in blood glucose and alteration in glucose tolerance tests.
During long-term therapy, a high-potassium diet is recommended. Potassium supplements may be required especially when high doses are used for prolonged periods. Some electrolyte disturbances (e.g. hypokalemia, hypomagnesemia) may increase the toxicity of certain other drugs (e.g. digitalis preparations and drugs inducing QT interval prolongation syndrome).
Particular caution with potassium levels is necessary when the patient is on digitalis glycosides, potassium-depleting steroids, or in the case of infants and children. Potassium supplementation, diminution in dose, or discontinuation of LASIX ORAL SOLUTION therapy may be required.
Since rigid sodium restriction is conducive to both hyponatremia and hypokalemia, strict restriction in sodium intake is not advisable in patients receiving LASIX ORAL SOLUTION therapy.
Urinary outflow must be secured. Patients with urinary outflow require careful monitoring-especially during the initial stages of treatment (see ADVERSE REACTIONS-Post-Market Adverse Drug Reactions-Renal and urinary disorders).
The possibility exists of exacerbation or activation of systemic lupus erythematosus. Therapy with LASIX ORAL SOLUTION should be administered cautiously in patients with a history of lupus.
Concomitant use with risperidone
There is an increased risk of mortality in patients with dementia (see 9 DRUG INTERACTIONS Patients with dementia should be carefully monitored, especially their hydration status, as dehydration is an overall risk factor for mortality (see 2 CONTRAINDICATIONS).
Driving and Operating Machinery
LASIX ORAL SOLUTION may lower the state of patient alertness and/or reactivity, particularly at the start of treatment as a result of a reduction in blood pressure and of other adverse reactions (see 8 ADVERSE REACTIONS).
Ear/Nose/Throat
Cases of tinnitus and reversible deafness have been reported. There have also been some reports of cases, the majority in children undergoing renal transplantation, in which permanent deafness has occurred. In these latter cases, the onset of deafness was usually insidious and gradually progressive up to 6 months after furosemide therapy. Hearing impairment is more likely to occur in patients with hypoproteinemia or severely reduced renal function or in patients who are also receiving drugs known to be ototoxic. Since this may lead to irreversible damage, these drugs must only be used with furosemide if there are compelling medical reasons.
Endocrine and Metabolism
Increases in blood glucose and alterations in glucose tolerance tests with abnormalities of the fasting and two-hour postprandial blood sugar levels have been observed. Rare cases of precipitation of diabetes mellitus have been reported.
Asymptomatic hyperuricemia can occur and a gout attack may rarely be precipitated.
Hepatic/Biliary/Pancreatic
It may be advisable to hospitalize patients with hepatic cirrhosis and ascites prior to initiating therapy. Sudden alterations of fluid and electrolyte balance in patients with cirrhosis may precipitate hepatic coma, therefore, strict observation is necessary during the period of diuresis.
Supplemental potassium chloride and, if required, an aldosterone antagonist, are helpful in preventing hypokalemia and metabolic alkalosis (see 2 CONTRAINDICATIONS).
Particularly careful monitoring is necessary in patients with Hepatorenal syndrome.
Monitoring and Laboratory Tests
Frequent serum electrolyte, creatinine and CO2 content determinations should be performed during the first few months of therapy and periodically thereafter. It is essential to replace electrolyte losses and to maintain fluid balance so as to avoid any risk of electrolyte depletion (hyponatremia, hypochloremia, hypokalemia, hypomagnesemia or hypocalcemia), hypovolemia, or hypotension.
Checks on urine and blood glucose should be made at regular intervals especially in diabetics and in those suspected of latent diabetes when receiving LASIX ORAL SOLUTION. Increases in blood glucose and alterations in glucose tolerance tests with abnormalities of the fasting and two-hour postprandial blood sugar levels have been observed.
Frequent BUN determinations during the first few months of therapy and periodically thereafter, as well as regular observations for possible occurrence of blood dyscrasias, liver damage or idiosyncratic reactions are advisable.
Particularly careful monitoring is necessary in:
- Premature infants. Renal function must be monitored and renal ultrasonography performed
Patients with:
- Hypoproteinemia. Cautious dose titration is require
- Hypotension
- A particular risk from a pronounced fall in blood pressure (e.g. patients with significant stenoses of the coronary arteries or of the blood vessels supplying the brain). Hepatorenal syndrome
- latent and manifest Diabetes mellitus
- Gout
Peri-Operative Considerations
Sulfonamide diuretics have been reported to decrease arterial responsiveness to pressor amines and to enhance the effect of tubocurarine. Great caution should be exercised in administering curare or its derivatives to patients undergoing therapy with LASIX ORAL SOLUTION and it is advisable to discontinue LASIX ORAL SOLUTION for one week prior to any elective surgery.
7.1 Special Populations
7.1.1. Pregnant Women
The teratogenic and embryotoxic potential of furosemide in humans is unknown. The drug should not be used in pregnant women or in women of childbearing potential unless in the opinion of the attending physician the benefits to the patient outweigh the possible risk to the fetus.
Reproductive and teratological studies have been performed in mice, rats, rabbits, cats, dogs and monkeys. With the exception of mice and rabbits, no abnormalities attributed to furosemide were detected. Furosemide caused unexplained maternal deaths and abortions in the rabbit at a daily dose of 50 mg/kg (approximately three times the maximum recommended human daily dose of 1000 mg orally) when administered between days 12 to 17 of gestation. In another study in rabbits, a dose of 25 mg/kg caused maternal deaths and abortions. In a third study, none of the pregnant rabbits survived a dose of 100 mg/kg. Data from the above studies indicate fetal lethality which can precede maternal deaths.
The results of a mouse study and one of the three rabbit studies also showed an increased incidence of distention of the renal pelvis and, in some cases, of the ureters in fetuses derived from treated dams as compared to the incidence of fetuses from the control group.
Treatment during pregnancy requires monitoring of fetal growth.
7.1.2 Breast-feeding
It should be noted that diuretics may partially inhibit lactation and that LASIX ORAL SOLUTION passes into the breast milk. Women must not breast-feed if they are treated with furosemide (see 2 CONTRAINDICATIONS).
7.1.3 Pediatrics
LASIX ORAL SOLUTION may lower serum calcium levels, and rare cases of tetany have been reported. Accordingly, periodic serum calcium levels should be obtained.
In premature infants LASIX ORAL SOLUTION may precipitate nephrocalcinosis/nephrolithiasis. When administered to premature infants with respiratory distress syndrome in the first few weeks of life, diuretic treatment with LASIX ORAL SOLUTION may accentuate the risk of a patent ductus arteriosus (see 7 WARNINGS AND PRECAUTIONS- Monitoring and Laboratory Tests).
Caution is required in neonates because of prolonged half-life of furosemide.
7.1.4 Geriatrics
Geriatrics (> 65 years of age)
Excessive diuresis induced by LASIX ORAL SOLUTION may result in dehydration and reduction of blood volume, with circulatory collapse and with the possibility of vascular thrombosis and embolism particularly in elderly patients. LASIX ORAL SOLUTION may cause electrolyte depletion.
Furosemide binding to albumin may be reduced in elderly patients.
The drug is known to be substantially excreted unchanged by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal functions, care should be taken in dose selection and may be useful to monitor renal function.
In general dose selection for the elderly patients should be cautious, usually starting at the low end of dosage range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and the concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse reaction overview
Serious adverse reactions with unknown frequency are thrombosis, nephrocalcinosis/nephrolithiasis in premature infants, renal failure, Stevens-Johnson syndrome, toxic epidermal necrolysis, acute generalized exanthematous pustulosis and Drug Rash with Eosinophilia and Systemic Symptoms. The most commonly reported adverse reactions (≥ 10%) are electrolyte disturbances (including symptomatic), dehydration, hypovolaemia, (especially in elderly patients), increased blood creatinine and triglyceride levels, and hypotension, including orthostatic hypotension (see 7 WARNINGS AND PRECAUTIONS, General).”
8.2 Clinical Trial Adverse Reactions
This information is not available for this drug product.
8.5 Post-Market Adverse Reactions
Adverse reactions are categorized below by body system.
Blood and lymphatic system disorders
Anemia, eosinophilia, leukopenia and thrombocytopenia (with purpura) have occurred, as well as agranulocytosis, aplastic anemia and hemolytic anemia.
Ear and Labyrinth disorders
Cases of tinnitus and sometimes irreversible deafness have been reported. There have also been some reports of cases, the majority in children undergoing renal transplantation, in which permanent deafness has occurred. In these latter cases, the onset of deafness is usually insidious and gradually progressive up to 6 months after furosemide therapy. Hearing disorder is more likely to occur in patients with hypoproteinemia or severely reduced renal function who are also receiving drugs known to be ototoxic.
Vertigo has been reported.
Eye disorders
Xanthopsia and blurred vision have been reported.
Gastrointestinal disorders
Acute pancreatitis, oral and gastric burning, diarrhea, nausea, vomiting and constipation have been reported. Rare occurrence of sweet taste has been reported.
Hepatobiliary disorders
Jaundice (intrahepatic cholestatic jaundice) and cholestasis have been reported.
Immune system disorders
Hypersensitivity reactions to furosemide also include photosensitivity, paresthesia and fever.
Systemic hypersensitivity reactions include vasculitis and necrotizing angiitis.
Severe anaphylactic or anaphylactoid reactions (e.g. with shock) occur rarely.
Exacerbation or activation of systemic lupus erythematosus.
Investigations
Increase in liver transaminases has been reported.
Transient elevations of BUN have been observed, especially in patients with renal insufficiency.
As with other diuretics, there may be an increase in serum creatinine, uric acid (this may lead to gout attack in predisposed patients), blood urea, cholesterol and triglyceride levels during furosemide treatment.
Metabolism and nutrition disorders
Electrolyte depletion has occurred during therapy with LASIX ORAL SOLUTION, especially in patients receiving higher doses with a restricted salt intake. Electrolyte depletion (hyponatremia, hypochloremia, hypokalemia, hypocalcemia and hypomagnesemia) manifests itself by adverse reactions attributed to various body systems: weakness, dizziness, drowsiness, polyuria, polydipsia, orthostatic hypotension, lethargy, sweating, bladder spasms, anorexia, vomiting, mental confusion, meteorism, thirst, headache, muscle cramp, muscle weakness, tetany and disorder of cardiac rhythm (see 7 WARNINGS AND PRECAUTIONS ).
The development of electrolyte disturbances (including symptomatic) is influenced by factors such as underlying diseases (e.g. liver cirrhosis, cardiac failure), concomitant medication and nutrition.
Cases of Pseudo-Bartter syndrome (hypochloremia, hypokalemia, alkalosis, normal to low blood pressures, and elevated plasma renin and aldosterone) have been reported in the context of misuse and/or long-term use of furosemide.
Treatment with LASIX ORAL SOLUTION has occasionally caused some deterioration of metabolic control in cases of manifest diabetes, or has made latent diabetes manifest.
Metabolic alkalosis may develop in the form of a gradually increasing electrolyte deficit or, e.g. where higher furosemide doses are administered to patients with normal renal function, acute severe electrolyte losses.
Pre-existing metabolic alkalosis (e.g. in decompensated cirrhosis of the liver) may be aggravated.
In extreme cases, hypovolemia may lead to dehydration, circulatory collapse, hemoconcentration and thrombophilia. Thrombophlebitis and emboli have been reported.
Musculoskeletal and connective tissue disorders:
Cases of rhabdomyolysis have been reported, often in the context of severe hypokalemia.
Nervous system disorders
At the commencement of treatment, excessive diuresis may give rise, especially in elderly patients, to a feeling of pressure in the head, dizziness, headache fainting or loss of consciousness.
Paresthesia has been reported.
Hepatic encephalopathy in patients with hepatocellular insufficiency has been reported.
Renal and urinary disorders
Symptoms of obstructed micturition (e.g. in hydronephrosis, prostatic hypertrophy, ureterostenosis) may become manifest or may be aggravated during medication with diuretics.
Interstitial nephritis has been reported.
Increased production of urine may provoke or aggravate complaints in patients with an obstruction of urinary outflow. Thus, acute retention of urine with possible secondary complications may occur. Increases in urine sodium and chloride have also been reported.
There have been some reported cases of renal failure.
In premature infants LASIX ORAL SOLUTION may precipitate nephrocalcinosis/nephrolithiasis.
Skin and subcutaneous tissue disorders
Various forms of dermatitis (e.g. dermatitis bullous), including urticaria, erythema multiforme, pemphigoid, Stevens-Johnson syndrome, toxic epidermal necrolysis, exfoliative dermatitis, pruritus, epidermolysis bullosa, AGEP (acute generalized exanthematous pustolosis), lichenoid reactions and DRESS (Drug Rash with Eosinophilia and Systemic Symptoms) have occurred.
Dermatologic reactions to furosemide also include purpura and rash.
Vascular disorders
Too vigorous diuresis may induce orthostatic hypotension or acute hypotensive episodes, which may cause signs and symptoms such as impairment of concentration and reactions, lightheadedness or orthostatic intolerance. There have been some reported cases of thrombosis.
When administered to premature infants with respiratory distress syndrome in the first few weeks of life, diuretic treatment with LASIX ORAL SOLUTION may accentuate the risk of a patent ductus arteriosus.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Sulfonamide diuretics have been reported to decrease arterial responsiveness to pressor amines and to enhance the effect of tubocurarine or curare-type muscle relaxants (see 7 WARNINGS AND PRECAUTIONS – Peri-Operative Considerations).
In case of concomitant abuse of laxatives, the risk of an increased potassium loss should be considered.
Glucocorticoids, carbenoxolone and licorice may also increase potassium loss.
Administration of LASIX ORAL SOLUTION to diabetic patients may result in possible decrease of diabetic control. Dosage adjustment of the anti-diabetic agent may be needed.
Hearing impairment is more likely to occur in patients who are also receiving drugs known to be ototoxic (e.g. aminoglycosides antibiotics, ethacrynic acid and cisplatin) (see 7 WARNINGS AND PRECAUTIONS ).
In edematous hypertensive patients being treated with antihypertensive agents, care should be taken to reduce the dose of these drugs when LASIX ORAL SOLUTION is administered, since LASIX ORAL SOLUTION potentiates their hypotensive effect.
Non-steroidal anti-inflammatory drugs (NSAIDS, e.g. indomethacin, Acetylsalicylic acid, diclofenac, ibuprofen and naproxen.) may attenuate the effect of LASIX ORAL SOLUTION and may cause renal failure in case of pre-existing hypovolemia.
9.4 Drug-Drug Interactions
Table 2 - Established or Potential Drug-Drug Interactions
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| Anticonvulsants | |||
Carbamazepine Phenobarbital Phenytoin | T | ↓ furosemide diuretic effect | Anticonvulsant drugs (phenytoin, carbamazepine, phenobarbital), which, like furosemide, undergo significant renal tubular secretion, may also attenuate the effect of furosemide. |
| Antidiabetics | |||
| Insulin, Metformin, Glipizide | T | ↓ antidiabetic drug effect | The effects of antidiabetic drugs may be reduced. |
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| Antihypertensive Agents | |||
ACE inhibitors Enalapril, Ramipril, Lisinopril | CT | ↓ blood pressure and renal function | Especially in combination with ACE inhibitors, a marked hypotension may be seen sometimes progressing to shock. The concomitant administration of LASIX ORAL SOLUTION with ACE-inhibitors may lead to deterioration in renal function and, in isolated cases, to acute renal failure. Consideration must be given to interrupting the administration of furosemide temporarily or at least reducing the dose of furosemide for three days before starting treatment with, or increasing the dose of, an ACE inhibitor. |
Angiotensin II receptor antagonists Irbesartan, valsartan, losartan | CT | ↓ blood pressure and renal function | Especially in combination with angiotensin II receptor antagonists, a marked hypotension may be seen sometimes progressing to shock. The concomitant administration of LASIX ORAL SOLUTION with angiotensin II receptor antagonists may lead to deterioration in renal function and, in isolated cases, to acute renal failure. Consideration must be given to interrupting the administration of furosemide temporarily or at least reducing the dose of furosemide for three days before starting treatment with, or increasing the dose of, an angiotensin II receptor antagonist. |
| Cephalosporins | |||
| Cefazolin, cefadroxil | T | ↓ renal function | Impairment of renal function may develop in patients receiving concurrent treatment with furosemide and high doses of certain cephalosporins. |
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| Chloral Hydrate | C | — | In isolated cases intravenous administration of furosemide within 24 hours of taking chloral hydrate may lead to flushing, sweating attacks, restlessness, nausea, increase in blood pressure and tachycardia. Use of furosemide concomitantly with chloral hydrate is therefore not recommended. |
| Chlorothiazides | |||
| Hydro-chlorothiazide | T | — | The concurrent use of LASIX ORAL SOLUTION with hydrochlorothiazide has been reported to decrease hypercalciuria and to dissolve some calculi. |
| Cisplatin | T | ↑ nephrotoxicity ↑ ototoxicity | Nephrotoxicity of cisplatin may be enhanced if furosemide is not given in low doses and with positive fluid balance when used to achieve forced diuresis during cisplatin treatment. There is also a risk of ototoxic effects if cisplatin and furosemide are given concomitantly. |
| Cyclosporine | CT | — | Concomitant use of cyclosporine A and furosemide is associated with increased risk of gouty arthritis secondary to furosemide-induced hyperurecemia and cyclosporine impairment of renal urate excretion. |
| Digitalis Glycosides | T | ↓ potassium plasma concentration | Some electrolyte disturbances (e.g. hypokalemia, hypomagnesemia) may increase the toxicity of certain other drugs (e.g. digitalis preparations and drugs inducing QT interval prolongation syndrome). Particular caution with potassium levels is necessary when the patient is on digitalis glycosides. Potassium supplementation, diminution in dose, or discontinuation of LASIX ORAL SOLUTION therapy may be |
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| required (see 7 WARNINGS AND PRECAUTIONS). | |||
| Direct Renin Inhibitor | |||
| Aliskiren | C / CT / T | ↓ Plasma con-centration of furosemide given orally | Aliskiren reduces plasma concentration of furosemide given orally. In patients treated with both aliskiren and oral furosemide, it is recommended to monitor for reduced diuretic effect and adjust the dose accordingly |
| Levothyroxine | C | ↑ then ↓ thyroid hormones | High doses of furosemide may inhibit binding of thyroid hormones to carrier proteins and thereby lead to an initial transient increase in free thyroid hormones, followed by an overall decrease in total thyroid hormone levels. Thyroid hormone levels should be monitored. |
| Lithium | T | ↑ lithium plasma concentration | Renal clearance of lithium is decreased in patients receiving LASIX ORAL SOLUTION, resulting in increased risk of cardiotoxic and neurotoxic effects of lithium. Therefore, it is recommended that lithium levels be carefully monitored in patients receiving this combination. |
| Methotrexate | T | ↓ furosemide diuretic effect | Methotrexate, which like furosemide, undergoes significant renal tubular secretion, may also attenuate the effect of furosemide. |
| Nephrotoxic Drugs | |||
Nephrotoxic Drugs Cisplatin, cyclosporin, Indomethacin | T | ↑ nephrotoxicity | The harmful effects of nephrotoxic drugs on the kidney may be increased. |
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) | |||
| Indomethacin | CT | ↓ furosemide diuretic effect | Clinical studies have shown that the administration of indomethacin can reduce the natriuretic and anti-hypertensive effect of LASIX ORAL SOLUTION in some patients. This response has been attributed to inhibition of prostaglandin synthesis by indomethacin. Therefore, when indomethacin is added to the treatment of a patient receiving LASIX ORAL SOLUTION, or LASIX ORAL SOLUTION is added to the treatment of a patient receiving indomethacin, the patient should be closely observed to determine if the desired effect of LASIX ORAL SOLUTION is obtained. Indomethacin blocks the LASIX ORAL SOLUTION-induced increase in plasma-renin activity. This fact should be kept in mind when evaluating plasma-renin activity in hypertensive patients. |
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| Potassium-depleting Steroids | |||
| Prednisone | T | ↓ potassium plasma concentration | Some electrolyte disturbances (e.g. hypokalemia, hypomagnesemia) may increase the toxicity of certain other drugs (e.g. digitalis preparations and drugs inducing QT interval prolongation syndrome). Particular caution with potassium levels is necessary when the patient is on potassium-depleting steroids. Potassium supplementation, diminution in dose, or discontinuation of LASIX ORAL SOLUTION therapy may be required (see 7 WARNINGS AND PRECAUTIONS). |
| Probenecid | T | ↓ furosemide diuretic effect | Probenecid, which like furosemide, undergoes significant renal tubular secretion, may also attenuate the effect of furosemide. |
| Radiocontrast Agents | CT | ↑ radiocontrast nephropathy | Patients who were at high risk for radiocontrast nephropathy treated with furosemide experienced a higher incidence of deterioration in renal function after receiving radiocontrast compared to high-risk patients who received only intravenous hydration prior to receiving radiocontrast. |
| Proper Name | Source of Evidence | Effect | Clinical Comments |
|---|---|---|---|
| Risperidone | CT | — | A higher incidence of mortality was observed in elderly patients with dementia treated with furosemide plus risperidone (7.3%; mean age 89 years, range 75-97 years) when compared to elderly patients with dementia treated with risperidone alone (3.1%; mean age 84 years, range 70-96 years) or furosemide alone (4.1%; mean age 80 years, range 67-90 years). Caution should be exercised and the risks and benefits of the combination or co-treatment with furosemide or with other potent diuretics should be considered prior to the decision to use. See 7 WARNING AND PRECAUTIONS |
| Salicylates | |||
| Acetylsalicylic acid | T | ↑ salicylate toxicity | Patients receiving high doses of salicylates in conjunction with LASIX ORAL SOLUTION may experience salicylate toxicity at lower doses because of competition for renal excretory sites. |
| Sucralfate | T | ↓ furosemide absorption | Concurrent administration of LASIX ORAL SOLUTION and sucralfate should be avoided, as sucralfate reduces the absorption of furosemide from the intestine and hence weakens its effect. |
| Theophylline | T | ↑ theophylline effect | The effects of theophylline may be increased. |
Legend: C= Case Study; CT= Clinical Trial; T= Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Animal experiments using stop-flow and micropuncture techniques have demonstrated that LASIX ORAL SOLUTION inhibits sodium reabsorption in the ascending limb of Henle's loop as well as in both proximal and distal tubules. The action of LASIX ORAL SOLUTION on the distal tubule is independent of any inhibitory effect on carbonic anhydrase or aldosterone.
LASIX ORAL SOLUTION may promote diuresis in cases which have previously proved resistant to other diuretics.
10.2 Pharmacodynamics
A continuous infusion of furosemide is more effective than repetitive bolus injections. Moreover, above a certain bolus dose of the drug there is no significant increase in effect.
The effect of furosemide is reduced if there is lowered tubular secretion or intra-tubular albumin binding of the drug.
10.3 Pharmacokinetics
Absorption
In humans, LASIX ORAL SOLUTION is rapidly absorbed from the gastro-intestinal tract. The diuretic effect of furosemide is apparent within one hour following oral administration and the peak effect occurs in the first or second hour. The duration of action is 4-6 hours but may continue up to 8 hours. Following intravenous administration of the drug, the diuresis occurs within 30 minutes and the duration of action is about 2 hours.
Distribution
In plasma, Furosemide is extensively bound to proteins mainly to albumin. The unbound fraction in plasma averages 2 - 4% at therapeutic concentrations. The apparent volume of distribution ranges between 0.1 to 0.2 L/kg in adults.
Metabolism:
A small fraction is metabolized by cleavage of the side chain.
Elimination
Urinary excretion is accomplished both by glomerular filtration and proximal tubular secretion, together this accounts for roughly only 2/3 of the ingested dose, the remainder being excreted in the feces. The following table summarizes the elimination kinetics of furosemide.
Table 3 - Summary of furosemide’s elimination kinetics
| Subjects | Route of Administration | Dose (mg) | Rate of Administration | Biliary Excretion | Max. Serum Concentration | t½ (hr) |
|---|---|---|---|---|---|---|
| Normal | Oral | 40 | — | 10-15% | < 1µg /mL | 4.0 |
| Normal | I.V. | 40 | Bolus | 10-15% | 2.5 µg/mL | 4.5 |
| Renal insufficiency | I.V. | 1000 | 25 mg/min. | 60% | 53 µg /mL | 13.5 |
| Renal insufficiency | I.V. | 1000 | 4 mg/min. | — | 29 µg /mL | — |
Special Populations and Conditions
Pediatrics
Depending on the maturity of the kidney, the elimination of furosemide may be slowed down. The metabolism of the drug is also reduced if the infant’s glucuronisation capacity is impaired.
The terminal half-life is below 12 hours in infants with a post-conceptional age of more than 33 weeks.
In infants of 2 months and older, the terminal clearance is the same as in adults.
- Geriatrics The elimination of furosemide is slowed down due to reduced renal function in the elderly.
Pregnancy and Breast Feeding
Furosemide crosses the placental barrier and transfers to the fetus slowly. It is found in the fetus or newborn in the same concentrations as in the mother (see 7 WARNINGS AND PRECAUTIONS, Pregnant Women).
Furosemide passes into the breast milk and may inhibit lactation (see 7 WARNINGS AND PRECAUTIONS, Breast-feeding).
- Hepatic Insufficiency In liver failure, the half-life of furosemide is increased by 30% to 90% mainly due to a larger volume of distribution. Additionally, in this patient group there is a wide variation in all pharmacokinetic parameters.
Renal Insufficiency [In renal failure, the elimination furosemide is slowed down and the half-life prolonged; the terminal half-life may be up to 24 hours in patients with severe renal failure. In nephrotic syndrome the reduced plasma protein concentration leads to a higher concentration of unbound (free) furosemide. On the other hand, efficacy of furosemide is reduced in these patients due to binding to intratubular albumin and lowered tubular secretion.
Furosemide is poorly dialyzable in patients undergoing hemodialysis, peritoneal dialysis and CAPD.
11 STORAGE, STABILITY AND DISPOSAL
Temperature
Oral solution: Store between 15° and 30°C.
Protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions applicable to this drug.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: furosemide
Chemical name: 4-chloro-N-furfuryl-5-sulfamoyl-anthranilic acid
Molecular formula and molecular mass: C12H11ClN2O5S (330.8)
Structural formula:
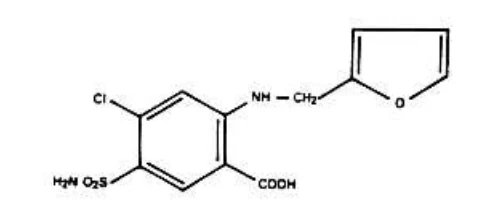
Physicochemical properties: White to slightly yellow, crystalline powder. Practically insoluble in water; freely soluble in acetone, in dimethylformamide, and in solutions of alkali hydroxides; soluble in methanol; sparingly soluble in alcohol; slightly soluble in ether; very slightly soluble in chloroform, melting at about 210°C (with decomposition).
14 CLINICAL TRIALS
The clinical data on which the original data was initially authorized is not available.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
The acute toxicity of furosemide has been determined in four animal species:
Table 4 - ACUTE TOXICITY (LD50) OF FUROSEMIDE (Approximate doses in mg/kg)
| SPECIES | ORAL | INTRAVENOUS |
|---|---|---|
| Mice | 1000 | 300 |
| Adult Rats | 4600 | 700 |
| Newborn Rats | 400 | - |
| Rabbits | 700 | 400 |
| Dogs | 2000 | over 400 |
The acute toxicity was characterized by signs of vasomotor collapse, sometimes accompanied by slight convulsions. Surviving animals often became dehydrated and depleted of electrolytes. In the newborn rats, intragastric injection of the drug caused hyperactivity and anorexia.
Chronic toxicity studies with furosemide were done in rats, dogs and monkeys.
- 1.
Rats: A one-year study was performed on one hundred albino rats at dosages of 0, 50, 100, 200 and 400 mg/kg/day orally. Seventy-six rats survived for one year. Ten rats from the two highest dose groups died within the first 10 days of therapy. Histological examination of those animals dying early revealed striking basophilic degeneration of the myocardial fibres with infiltration and necrotic foci consistent with severe electrolyte imbalance.
In the kidney, the most consistent pathological changes seen were degenerative changes in the tubular epithelium manifested by swollen cells with increased density of the cytoplasm. Occasionally, focal necrosis of the epithelium and decreased cell size were evident, plus accumulation of some calcified material. These changes were considered consistent with the nephropathy of potassium deficiency.
- 2. Dogs: In a six-month study, eighteen out of twenty beagle dogs survived oral daily doses of 0, 10, 30, 100 and 350 mg/kg. The most consistent pathological findings were renal lesions consisting of calcifications and scarring of the renal parenchyma at all doses above 10 mg/kg. The renal capsule above these lesions sometimes showed strikingly enlarged lymph vessels with thickened walls.
- 3. Rhesus Monkeys: In a 12-month study, daily oral doses of furosemide of 27 mg/kg and 60 mg/kg brought about pathological findings that consisted of dilated convoluted tubules with casts in 3 out of 20 animals given 27 mg/kg and in 6 out of 9 animals given 60 mg/kg. These lesions were considered drug related.
Carcinogenicity
Furosemide in the approximate amount of 200 mg/kg body weight daily was administered to female mice and rats over a 2-year period with their diet. An increased incidence of mammary adenocarcinoma was noted in the mice, but not in the rats. These tumors occurred with a positive trend, and the incidence in the high dose group was increased compared to the control, in addition, the high-dose rate was about five fold over the historical rate. These tumors are considered to be associated with furosemide administration. This dose is considerably greater than the therapeutic dose administered in human patients.
In a carcinogenicity study, rats were administered furosemide in daily doses of 15 and 30 mg/kg body weight. Male rats in the 15 mg/kg-dose category, but not in the 30 mg/kg-dose category, showed a marginal increase in uncommon tumours.
Mutagenicity: In in-vitro tests on bacteria and mammalian cells, both positive and negative results have been obtained. Induction of gene and chromosome mutations, however, has been observed only where furosemide reached cytotoxic concentrations.
Reproductive and Developmental Toxicology:
Reproductive and teratological studies have been performed in mice, rats, rabbits, cats, dogs and monkeys. With the exception of mice and rabbits, no abnormalities attributed to furosemide were detected. Furosemide caused unexplained maternal deaths and abortions in the rabbit at a daily dose of 50 mg/kg (approximately three times the maximum recommended human daily dose of 1000 mg orally) when administered between days 12 to 17 of gestation. In another study in rabbits, a dose of 25 mg/kg caused maternal deaths and abortions. In a third study, none of the pregnant rabbits survived a dose of 100 mg/kg. Data from the above studies indicate fetal lethality which can precede maternal deaths.
The results of a mouse study and one of the three rabbit studies also showed an increased incidence of distention of the renal pelvis and, in some cases, of the ureters in fetuses derived from treated dams as compared to the incidence of fetuses from the control group.
DETAILED PHARMACOLOGY
Renal Pharmacology
In dogs, furosemide demonstrated diuretic properties. Diuresis and sodium excretion were induced by doses of 0.125 mg/kg administered intravenously or 0.5 mg administered orally.
Maximum water and sodium excretion is obtained by oral and intravenous doses of 12.5 and 25 mg/kg respectively. Increased potassium excretion can only be demonstrated with doses exceeding 1 mg/kg. The onset of action is rapid after intravenous and oral administration and the duration of activity is approximately 2 and 4 hours respectively.
Furosemide produces an immediate diuresis after intravenous administration and is effective unilaterally after injection into a renal artery. Its action, therefore, is directly on the kidney. The diuretic response is prompt and relatively brief. At the peak of diuretic response 30-40% of filtered sodium load may be excreted, along with some potassium and with chloride as the major anion. Furosemide augments the potassium output as a result of increased distal potassium secretion. Its diuretic action is independent of changes in acid-base balance. Under conditions of acidosis or alkalosis the diuretic produces chloruresis without augmentation of bicarbonate excretion. It does not inhibit carbonic anhydrase.
On the basis of changes in free-water production furosemide inhibits sodium reabsorption in the ascending limb of the loop of Henle . However, proximal sites of action are also involved, as determined by micropuncture. Partial distal inhibition of sodium reabsorption is also possible. It also decreases the urinary excretion of uric acid and prolonged administration may lead to hyperuricemia. Since urate is transported in the proximal tubule, the effect of the drug on uric acid excretion further suggests a proximal tubule site of action.
Administration of furosemide may induce extracellular metabolic alkalosis, primarily by virtue of the disproportionate loss of chloride, but also, in part, as a result of the variable depletion of potassium.
17 SUPPORTING PRODUCT MONOGRAPHS
LASIX ORAL SOLUTION® (Oral Solution 10 mg/mL), Submission Control No: 211339, Product Monograph, sanofi-aventis Canada Inc. (February 21, 2018)