


Product Monograph - Lioresal Tab 10mg
CLINICAL PHARMACOLOGY
Mechanism of action (MOA)
The precise mechanisms of action of LIORESAL (baclofen) are not fully known. It inhibits both monosynaptic and polysynaptic reflexes at the spinal level, probably by hyperpolarization of afferent terminals, although actions at supraspinal sites may also occur and contribute to its clinical effect. Although LIORESAL is an analog of the putative inhibitory neurotransmitter gamma-aminobutyric acid (GABA), there is no conclusive evidence that actions on GABA systems are involved in the production of its clinical effects.
Peak plasma concentrations of LIORESAL are achieved within 2 hours and the plasma half-life is 2-4 hours.
Special populations
Geriatrics (aged 65 years or above)
Following a single oral dose, elderly patients have a slower rate of absorption and elimination, a slightly prolonged elimination half-life, but a similar systemic exposure of baclofen compared to young adults.
Hepatic impairment
No pharmacokinetic data is available in patients with hepatic impairment after administration of LIORESAL. However, as liver does not play a significant role in the disposition of baclofen, it is unlikely that baclofen pharmacokinetics would be altered to a clinically significant level in patients with hepatic impairment.
Renal impairment
No controlled clinical pharmacokinetic study is available in patients with renal impairment after administration of LIORESAL. Baclofen is predominantly eliminated unchanged in urine. Sparse plasma concentration data collected in female patients under chronic hemodialysis or compensated renal failure indicate significantly decreased clearance and increased half-life of baclofen in these patients. Severe neurological outcomes have been reported in patients with renal impairment after oral administration, thus LIORESAL should be given with special care and caution in these patients (see WARNINGS, Renal Impairment).
INDICATIONS
LIORESAL (baclofen) is useful for the alleviation of signs and symptoms of spasticity resulting from multiple sclerosis.
LIORESAL may also be of some value in patients with spinal cord injuries and other spinal cord diseases.
CONTRAINDICATIONS
Hypersensitivity to LIORESAL (baclofen) or to any of the excipients.
WARNINGS
SERIOUS WARNINGS AND PRECAUTIONS
Life-threatening Respiratory Depression
Concomitant use of LIORESAL with opioids may result in respiratory depression, profound sedation, syncope, and death.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
Abrupt Drug Withdrawal:
Following abrupt withdrawal of LIORESAL (baclofen), delirium, visual and auditory hallucinations, convulsion (status epilepticus), dyskinesia, confusional state, psychotic disorder, mania or paranoia, anxiety with tachycardia and sweating, insomnia, rhabdomyolysis and worsening of spasticity have occurred. Therefore, except for serious adverse reactions, the dose should be reduced slowly when the drug is discontinued (over a period of approximately 1-2 weeks).
For the intrathecal formulation of LIORESAL, it has been reported that clinical characteristics of withdrawal may resemble autonomic dysreflexia, malignant hyperthermia, neuroleptic-malignant syndrome, or other conditions associated with a hypermetabolic state or widespread rhabdomyolysis.
Neonatal Withdrawal:
Drug withdrawal reactions including, irritability, high-pitched crying, tremor, hypertonicity, excessive sucking, disordered sleep, hyperthermia, mottling, and postnatal convulsions have been reported in neonates after intrauterine exposure to oral LIORESAL. Neonates with risk of intrauterine exposure to LIORESAL should be carefully monitored for the development of signs consistent with withdrawal. If clinical manifestations of withdrawal develop, non-pharmacologic measures should be considered (for instance, minimizing sensory or environmental stimulation, maintaining temperature stability, increasing the frequency of feeds). Initiation of pharmacotherapy may be considered in neonates with moderate to severe signs of withdrawal to prevent further complications (See WARNINGS, Pregnancy and Lactation).
Neurologic
Respiratory Depression
Baclofen has been associated with central nervous system (CNS) depression including sedation, somnolence, loss of consciousness as well as serious cases of respiratory depression. Patients with compromised respiratory function, respiratory or neurological disease, renal impairment and the elderly are at higher risk of experiencing these severe adverse effects. Concomitant use of CNS depressants with baclofen is also a contributing factor.
Concomitant Use With Opioids
Concomitant use of opioids with LIORESAL potentiates the risk of respiratory depression, profound sedation, syncope, and death.
Patients who require concurrent treatment with opioids or other CNS depressants should be observed carefully for signs and symptoms of CNS depression, and the dose of baclofen or opioid should be reduced accordingly.
Driving and Operating Machinery
LIORESAL may be associated with adverse effects such as dizziness, sedation, somnolence and visual impairment (see ADVERSE REACTIONS) which may impair the patient’s reaction. Patients experiencing these adverse reactions should be advised to refrain from driving or using machines. Patients should also be cautioned that the central nervous system effects of LIORESAL may be additive to those of alcohol and other CNS depressants.
Renal impairment:
After oral LIORESAL dosing, severe neurological outcomes and symptoms of overdose including clinical manifestations of toxic encephalopathy (e.g. confusion, hallucination, somnolence, depressed level of consciousness and coma) have been reported in patients with renal impairment. Patients with renal impairment should be closely monitored for prompt diagnosis of early signs and/or symptoms of toxicity (e.g. somnolence, lethargy) (see SYMPTOMS AND TREATMENT OF OVERDOSAGE). Caution should be exercised while administering LIORESAL in patients with renal impairment because baclofen is primarily excreted unchanged through the kidneys. In patients dependent on dialysis, a particularly low dose of LIORESAL should be selected i.e. approximately 5 mg daily. Unscheduled hemodialysis may be considered a treatment option in cases of severe baclofen toxicity as hemodialysis has been reported to effectively remove baclofen from the body, alleviate clinical symptoms of overdose and shorten the recovery time in these patients.
End Stage Renal Failure: LIORESAL should be administered to end stage renal failure patients only if the expected benefits are considered acceptable, given potential risks.
Concomitant medications that may impact renal function: Particular caution is required when combining LIORESAL to drugs or medicinal products that can significantly impact renal function. Renal function shall be closely monitored and LIORESAL daily dosage adjusted accordingly to prevent baclofen toxicity (see PRECAUTIONS, Drug interactions).
Stroke:
LIORESAL has not significantly benefited patients with stroke. These patients have also shown poor tolerability to the drug.
Pregnancy and Lactation:
Safe use of LIORESAL during pregnancy or lactation has not been established. Baclofen crosses the placental barrier and passes into breast milk. High doses are associated with an increased incidence of abdominal hernias in the fetuses of rats and of ossification defects in those of rats and rabbits. Therefore, the drug should be administered to pregnant patients, or women of child-bearing potential only when, in the judgment of the physician, the potential benefits outweigh the possible hazards.
Infants exposed to LIORESAL through maternal oral dosing during pregnancy are at risk of experiencing baclofen withdrawal at birth; identification of this condition may be confounded due to delayed appearance of withdrawal symptoms in this population.
Epilepsy:
Extreme caution should be exercised in patients with epilepsy or a history of convulsive disorders. In such patients, the clinical state and electroencephalogram should be monitored at regular intervals during therapy, as deterioration in seizure control and EEG has been reported occasionally in patients taking LIORESAL.
Psychiatric and Nervous System Disorders:
Patients suffering from psychiatric disorders such as psychosis, schizophrenia, or confusional states should be treated cautiously with LIORESAL and kept under close surveillance, since exacerbation of these conditions may occur with LIORESAL treatment.
Suicide and suicide-related events have been reported in patients treated with baclofen. In some cases, the patients had additional risk factors associated with an increased risk of suicide including history of suicidal behaviour, depression, alcohol/substance abuse and/or concomitant use of medications known to increase risk of suicide. Close supervision of patients should accompany therapy with LIORESAL. Patients (and caregivers of patients) should be alerted about the need to monitor for clinical worsening, suicidal behaviour or thoughts or unusual changes in behaviour and to seek medical advice immediately if these symptoms present (see ADVERSE REACTIONS).
Cases of misuse, abuse and dependence have been reported with baclofen. Caution should be exercised in patients with a history of substance abuse and the patients should be monitored for symptoms of baclofen misuse, abuse or dependence e.g. dose escalation, drug-seeking behavior, development of tolerance.
PRECAUTIONS
Use in Children:
Safe use of LIORESAL (baclofen) in children under age 12 has not been established and it is, therefore, not recommended for use in children.
Posture and balance:
LIORESAL should be used with caution where spasticity is utilized to sustain upright posture and balance in locomotion, or whenever spasticity is utilized to obtain increased function (see DOSAGE and ADMINISTRATION).
Hepatic Impairment:
No studies have been performed in patients with hepatic impairment receiving LIORESAL therapy. As baclofen does not undergo predominant hepatic metabolism, its pharmacokinetics is unlikely to be altered to a clinically significant level in patients with hepatic impairment.
However, patients with severe hepatic impairment should be treated with caution, as they are in general more sensitive to therapeutic effects/adverse effects of drugs.
In rare instances, elevated SGOT, alkaline phosphatase and glucose levels in the serum have been recorded when using oral baclofen.
Others:
Caution should also be used in treating the following populations: patients with peptic ulceration (or a history of); elderly patients with cerebrovascular disorders; and patients with respiratory impairment. Regarding patients with renal failure, see WARNINGS, Impaired Renal function.
Since unwanted effects are more likely to occur, a cautious dosage schedule should be adopted in elderly and patients with spasticity of cerebral origin (see DOSAGE and ADMINISTRATION).
Urinary disorders:
LIORESAL should be used with caution in patients with underlying bladder sphincter hypertonia, since acute retention of urine may occur.
Laboratory tests:
The following laboratory tests have been found to be abnormal in a few patients receiving LIORESAL: aspartate aminotransferase, blood alkaline phosphatase and blood sugar (all elevated). Therefore, in patients with liver diseases or diabetes mellitus, appropriate laboratory tests should be performed periodically in order to ensure that no drug-induced changes in these underlying diseases have occurred.
Drug Interactions:
Anesthetics
Anesthetic agents may potentiate the CNS effects of baclofen.
Antidepressants
The concomitant administration of baclofen and tricyclic antidepressants may potentiate the pharmacological effects of baclofen, resulting in pronounced muscular hypotonia. In addition, concomitant use of tricyclic antidepressants can cause sedation, drowsiness and potentiate the effects of LIORESAL resulting in pronounced muscular hypotonia.
Lithium
Concomitant use of oral LIORESAL and lithium resulted in aggravated hyperkinetic symptoms. Caution should be exercised when LIORESAL is used concomitantly with lithium.
MAO inhibitors
The concurrent use of MAO inhibitors and LIORESAL may result in increased CNS-depressant effects; therefore, caution is advised and the dosage of one or both agents should be adjusted accordingly.
Antihypertensives
Since combined treatment with LIORESAL and antihypertensives is likely to increase the fall in blood pressure, the dosage of antihypertensive medication should be adjusted accordingly.
Levodopa/Dopa Decarboxylase (DDC) inhibitor (carbidopa)
In patients with Parkinson's disease receiving treatment with baclofen and levodopa (alone or in combination with a DDC inhibitor, carbidopa), there have been several reports of mental confusion, hallucinations, headache, nausea and agitation. Worsening of the symptoms of Parkinsonism has also been reported. Hence, caution should be exercised during concomitant administration of LIORESAL and levodopa/carbidopa.
Antidiabetic agents
Isolated cases of increased blood glucose concentrations have been reported with LIORESAL; dosage adjustments of antidiabetic agents (oral and insulin) may therefore be necessary with combined LIORESAL treatment.
Neuromuscular blocking agents
Caution should be exercised when administering LIORESAL and magnesium sulfate (or other neuromuscular blocking agents), since a synergistic effect may theoretically occur.
Agents reducing renal function
Drugs or medicinal products that can significantly impact renal function (ex: memantine, NSAIDS) may reduce baclofen excretion leading to toxic effects (see WARNINGS, Impaired Renal Function).
Drugs causing Central Nervous System (CNS) depression
Increased sedation may occur when LIORESAL is taken concomitantly with other drugs causing CNS depression, including other muscle relaxants (such as tizanidine), synthetic opiates, hypnotics, anxiolytics or alcohol (see WARNINGS, Driving and Operating Machinery). The risk of respiratory depression is also increased. In addition, hypotension has been reported with concomitant use of morphine and intrathecal baclofen. Careful monitoring of respiratory and cardiovascular functions is essential, especially in patients with cardiopulmonary disease and respiratory muscle weakness.
Lactation
LIORESAL is excreted in human milk. As a general rule, nursing should not be undertaken while a patient is on a drug.
Infertility
There are no data available on the effect of baclofen on fertility in humans. Baclofen did not impair male or female fertility at non-maternally toxic doses in rats (see TERATOLOGY AND REPRODUCTION STUDIES).
ADVERSE REACTIONS
Adverse effects most frequently occur at the start of treatment (e.g. sedation, somnolence), particularly if the dosage is increased too rapidly, if large doses are administered, and in the elderly patient. However, these effects are often transient and can be alleviated or eliminated by decreasing the dosage; they are seldom severe enough to warrant withdrawal of the medication.
Should persistent nausea occur following a reduction in dosage, it is recommended that LIORESAL be ingested with food or a milk beverage.
Lowering of the convulsion threshold and convulsions may occur, particularly in epileptic patients.
In elderly patients or those patients with cerebrovascular disorder or a history of psychiatric illness, more serious adverse reactions may occur, such as hallucinations and confusion.
Muscular hypotonia of a degree sufficient to make walking or movement difficult may occur, but is usually relieved by readjusting the dosage. For this purpose, the overall dose of LIORESAL may be reduced, or the daytime dose reduced and the evening dose increased.
Certain patients have shown increased muscle spasticity as a paradoxical reaction to the medication.
Some of the CNS and genitourinary symptoms reported may be related to the underlying disease rather than to drug therapy.
Adverse reactions listed below are ranked using the following convention: very common (≥1/10); common (≥1/100, <1/10); uncommon (≥1/1,000, <1/100); rare (≥1/10,000, <1/1,000) very rare (<1/10,000), not known (cannot be estimated from the available data).
The most common adverse reactions associated with LIORESAL (baclofen) are transient somnolence, sedation, dizziness, weakness and fatigue. Other adverse reactions reported were:
Nervous system disorders:
Common: Headache, insomnia, muscular weakness, tremor, ataxia, respiratory depression, euphoric mood, depression, confusional state, hallucinations, nightmare, myalgia, nystagmus, and dry mouth.
Rare: Excitement, paresthesia, tinnitus, slurred speech, coordination disorder, rigidity, dystonia, dysarthria, epileptic seizures, lowered convulsion threshold, and dysgeusia.
Not known: Completed suicide, suicide attempt, suicide ideation, drug misuse, drug abuse, drug dependence (see WARNINGS, Psychiatric and nervous system disorders).
Eye disorders:
Common: Accommodation disorders, visual impairment.
Rare: Blurred vision, strabismus, miosis, mydriasis, diplopia.
Cardiac disorders:
Common: Cardiac output decreased.
Rare: dyspnea, palpitation, chest pain, syncope.
Not known: Bradycardia.
Vascular disorders:
Common: Hypotension.
Gastrointestinal disorders:
Very common: Nausea.
Common: Constipation, gastrointestinal disorders, retching, vomiting, diarrhea.
Rare: Anorexia, abdominal pain, and positive test for occult blood in stool.
Hepatobiliary disorders:
Rare: Hepatic function abnormal.
Skin and subcutaneous tissue disorders:
Common: Instances of rash, hyperhidrosis, pruritus.
Not known: Urticaria.
Renal and urinary disorders:
Common: Pollakiuria, enuresis, dysuria.
Rare: Nocturia, hematuria, urinary retention.
Reproductive system and breast disorders:
Rare: Erectile dysfunction, inability to ejaculate.
General disorders and administration site conditions:
Common: Fatigue, ankle edema.
Very rare: Hypothermia.
Not known: Drug withdrawal syndrome*.
Investigation:
Not known: Blood glucose increased.
Other:
Weight gain, nasal congestion.
*Drug withdrawal syndrome including, irritability, high-pitched crying, tremor, hypertonicity, excessive sucking, disordered sleep, hyperthermia, mottling, and postnatal convulsions has also been reported after intra-uterine exposure to oral LIORESAL
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Signs and Symptoms:
Symptoms of overdosage are predominantly those of central nervous system depression and include somnolence, depressed level of consciousness, respiratory depression, coma, seizures, confusion, hallucination, agitation, abnormal electroencephalogram (burst suppression pattern and triphasic waves), accomodation disorder, impaired pupillary refexes, muscular hypotonia, myoclonus, hyporeflexia or areflexia, hypotension or hypertension, bradycardia, tachycardia or cardiac arrhythmia, hypothermia, peripheral vasodilatation, nausea, vomiting, diarrhea, increased salivation, elevated LDH, AST, alkaline phosphatase, blood glucose values, sleep apnea and rhabdomyolysis.
The signs and symptoms may be further aggravated by co-administration of a variety of other agents including alcohol, diazepam, and tricyclic antidepressants.
Treatment:
There is no specific antidote. Supportive measures and symptomatic treatment should be given for complications such as hypotension, hypertension, convulsions, gastrointestinal disturbances, and respiratory or cardiovascular depression.
| For management of a suspected drug overdose, contact your regional Poison Control Centre |
After ingestion of a potentially toxic amount, activated charcoal should be considered, especially during the early period after ingestion. Gastric decontamination (e.g. gastric lavage) should be considered in individual cases, especially in the early period (60 minutes) after ingestion of a potentially life-threatening overdose. Comatose or convulsing patients should be intubated prior to the initiation of gastric decontamination. A high urinary output should be maintained since LIORESAL (baclofen) is excreted mainly by the kidneys. For this purpose, generous quantities of fluid should be administered, possibly together with a diuretic. Hemodialysis (sometimes unscheduled) is indicated in severe poisoning associated with renal failure (see WARNINGS, Impaired Renal Function). In the event of convulsions, administer diazepam i.v. with caution.
DOSAGE AND ADMINISTRATION
The determination of optimal dosage of LIORESAL (baclofen) requires individual titration. Start therapy at a low dosage and increase gradually until optimum effect is achieved (usually between 40-80 mg daily).
Treatment should be started with a dosage of 15 mg daily, preferably in divided doses.
The following dosage titration schedule is suggested:
5 mg t.i.d. for 3 days
10 mg t.i.d. for 3 days
15 mg t.i.d. for 3 days
20 mg t.i.d. for 3 days
Thereafter additional increases may be necessary but the total daily dose should not exceed a maximum of 80 mg daily (20 mg q.i.d.).
The lowest dose compatible with an optimal response is recommended. If benefits are not evident after a reasonable trial period, patients should be slowly withdrawn from the drug (See WARNINGS).
Discontinuation of the treatment should always be gradual by successively reducing the dosage over a period of approximately 1 to 2 weeks, except in overdose-related emergencies, or where serious adverse effects have occurred (see WARNINGS).
Special populations
Renal impairment:
Because LIORESAL is primarily excreted unchanged through the kidneys, it should be given with caution in patients with renal insufficiency, and generally with a reduced dose. In patients dependent on dialysis, a particularly low dose of LIORESAL should be selected i.e. approximately 5 mg daily (see WARNINGS, Impaired Renal Function).
LIORESAL should only be administered to end stage renal failure patients when benefit outweighs risk. These patients should be closely monitored for prompt diagnosis of early signs and/or symptoms of toxicity (see WARNINGS, Renal Impairment).
Since unwanted effects are more likely to occur in elderly patients or in patients with spastic states of cerebral origin, it is recommended that a very cautious dosage schedule be adopted in such cases and that the patient should be kept under appropriate surveillance. Patients should be monitored for signs of overdose, central nervous system depression and toxic encephalopathy such as drowsiness, impairment of consciousness, coma, respiratory depression, hallucinations, agitation, and convulsions (see SYMPTOMS AND TREATMENT OF OVERDOSAGE).
Hepatic impairment:
No studies have been performed in patients with hepatic impairment under LIORESAL therapy. Liver does not play significant role in the metabolism of baclofen after oral administration of LIORESAL (see CLINICAL PHARMACOLOGY). However, LIORESAL has the potential of elevating liver enzymes. LIORESAL should be prescribed with caution in patients with hepatic impairment, although no dosage adjustment is needed (see PRECAUTIONS, Hepatic Impairment).
Geriatrics (aged 65 years or above):
Since unwanted effects are more likely to occur in elderly patients, it is recommended that a cautious dosage schedule be adopted in such cases and that the patient be kept under appropriate surveillance.
Patients with spastic states of cerebral origin:
Since unwanted effects are more likely to occur in patients with spastic states of cerebral origin, it is recommended that a cautious dosage schedule be adopted in such cases and that the patient be kept under appropriate surveillance.
AVAILABILITY
LIORESAL 10mg tablet: White to off-white, oval, flat-faced, bevel-edged tablets. Engraved GEIGY on one side and bisected with KJ on the other side.
LIORESAL D.S. 20mg tablet: White to off-white, capsule-shaped tablets. Engraved GEIGY on one side and bisected with GW on the other side.
Available in bottles of 100 tablets.
LIORESAL must be kept out of the reach and sight of children.
CHEMISTRY AND PHARMACOLOGY
LIORESAL (baclofen) is 4-amino-3-(p-chlorophenyl) butyric acid and has the following structural formula:
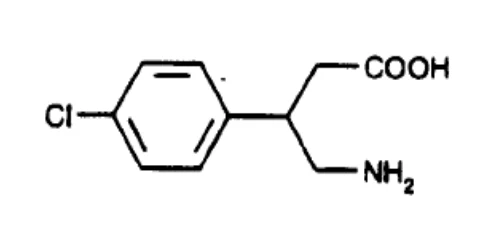
Baclofen is a white to off-white, odorless or practically odorless crystalline powder, with a molecular weight of 213.67. It is slightly soluble in water, very slightly soluble in methanol, and insoluble in chloroform.
Baclofen exerted a pronounced muscle-relaxant effect in the non-anesthetized mouse, rabbit, cat, and dog. Doses of up to 10 mg/kg p.o. did not affect coordination in mice. Intravenous doses of 1 or 2 mg/kg decreased polysynaptic (flexor) spinal reflexes in anesthetized rabbits or cats respectively by 50%. A similar reduction was found in decerebrated or spinal cats. The monosynaptic (extensor) spinal reflex was reduced 50% by a dose of 0.5 mg/kg i.v. in spinalized, decerebrate, or anesthetized cats. Baclofen had no direct effect on the alpha-motor nerve fibres, neuromuscular transmission, or contraction of extrafusal muscle fibres in anesthetized cats. An intravenous dose of 0.8 mg/kg diminished the tonic activity of gamma motoneurons in decerebrate cats by 50%. Baclofen diminished or abolished decerebrate rigidity in cats in doses of 1-3 mg/kg. It had no effect on the de-efferented muscle spindle or the slowly-adapting pulmonary stretch receptors in anesthetized cats.
Baclofen had anticonvulsive effects against thiosemicarbazide and pentetrazole-induced convulsions in mice but had no effect against electroshock or strychnine-induced convulsions.
An intravenous dose of 3-6 mg/kg exerted a hypnotic effect in the unanesthetized dog.
Large doses impaired respiration in mice, rabbits, and dogs. Doses of 1 mg/kg i.v. produced a fall in the blood pressure of anesthetized rabbits or cats, but 3 mg/kg i.v. had no effect on the blood pressure, heart rate, ECG, or respiration of unanesthetized dogs.
In man a single oral dose of 10 mg of baclofen is rapidly and almost completely absorbed whereas absorption of 20 mg and 40 mg doses is less complete. Animal studies indicate rapid distribution throughout the body except to the CNS where concentrations are lower than average. The decay in CNS concentration is, however, slower than the decay from other tissues.
About 85% of a single oral dose is excreted unchanged in the urine. The remaining 15% is mainly deaminated to β-(p-chlorophenyl)- γ-hydroxybutyric acid within 24 hours. LIORESAL is about 30% bound to serum proteins.
TOXICOLOGY
Acute Toxicity:
| Species | Route | LD50 (mg/kg) |
| Mouse | i.v. | 26 + 6 |
| Mouse | p.o. | 75 + 22 |
| Rat | i.v. | 112 + 14 |
| Rat | p.o. | 150 + 18 |
| Rat | s.c. | 137 + 17 |
The toxic symptoms in mice and rats included ataxia, clonic-tonic convulsions and respiratory paralysis.
| Species | Sex M F | No. of Groups | No. of Animals per Group | Dose mg/kg/day | Route | Dura-tion of Study | Toxic Effects |
| Rat | 20 20 | 4 | 5M 5F | 0,5,10; 20-80 (weekly increases of 10 mg/kg/day) | p.o. | 30 D | Slight adrenal enlargement |
| Rat | 10 10 | 5 | 2M 2F | Baclofen + diazepam: 0 + 0, 4 + 2, 20 + 10, 0 + 10, 20 + 0 | p.o. | 30 D | None |
| Dog | 8 8 | 4 | 2M 2F | 0,1,2, 4-8 (doubled in last week) | p.o. | 30 D | Emesis at all dose levels, anorexia, salivation, ataxia, sedation, weight loss |
| Species | Sex M F | No. of Groups | No. of Animals per Group | Dose mg/kg/day | Route | Dura-tion of Study | Toxic Effects |
| Rat | 80 80 | 4 | 20M 20F | 0,5, 20-160, 40-500 | p.o. | 1 Y | Weight loss, mild alopecia, urinary incontinence at intermediate and high doses. Elevated mean neutrophil/ lymphocyte ratios and SGPT at intermediate and high doses. |
| Rat | 280 28 0 | 1 3 | Control: 100M 100F Test: 60M 60F | 0,5, 25-50, 50-100 | p.o. | 1 Y | Reduced weight gain. Dose-related urinary frequency. Dose-related increase in incidence of ovarian cysts. |
| Dog | 12 12 | 4 | 3M 3F | 0, 2-4, 3-8, 4-12 | p.o. | 1 Y | Transient emesis, sedation, convulsions and cardiovascular collapse (single animal), possible slight adrenal enlargement, hind limb weakness or paralysis. |
TERATOLOGY AND REPRODUCTION STUDIES
Reproductive toxicity
Oral baclofen showed no significant adverse effects on fertility or postnatal development at non-maternally toxic dose levels in rats (approximately 2.1-times the maximum oral mg/kg dose in adults). At maternally toxic dose levels (8.3-times the maximum oral mg/kg dose in adults), baclofen increased the the incidence of omphalocoeles (ventral hernias) in rats, an effect not seen in mice or rabbits. Delayed fetal growth (ossification of bones) in the fetuses of rats and rabbits was also observed at maternotoxic doses.
Rat: Doses of 4.4-5 and 17.7-21.3 mg/kg/day were administered orally to two groups of female rats during pre-mating, mating, gestation, and lactation. The only significant effect was a reduction in litter size and survivability of offspring (possibly due to agalactia) in the high-dose group. In another rat study, doses of 5 and 10 mg/kg/day were administered by gavage during the last trimester of pregnancy and throughout the lactation period. Five of 31 dams in the high-dose group showed severe weight loss from days 15-21 of gestation as well as agalactia and the entire litter of each of these dams died by day 2 post-partum. In a third study, baclofen doses of 30 mg/kg/day produced symptoms of ataxia and drowsiness in dams and the death of 4 of 24 dams dosed from gestation Days 1 to 12. At this high dose level, there was a slight increase in the resorption rate; however, the number and size of the fetuses remained normal and no malformations were reported.
Rat and Mouse: Doses of 5 and 20 mg/kg/day were administered by gavage to two groups of pregnant rats on days 6-15 of gestation. The only significant finding was the presence of abdominal hernias in 4/160 fetuses in the high-dose group. In a second similar study, 1/229 control fetuses and 6/293 fetuses from dams receiving 20 mg/kg/day had abdominal hernias. Comparable lesions did not occur in a similar mouse study.
The average number of stillbirths or viable newborns did not differ significantly between control and medicated groups. The average weight of neonates from the high-dose group was significantly reduced.
Rabbit: Doses of 1, 5, and 10 mg/kg/day were administered by gavage to groups of rabbits from the 6th to 18th day of gestation. There was an increased incidence of unossified phalangeal nuclei of forelimbs and hind-limbs in the fetuses from the high-dose group. In another study, a slight increase in resorption rates and the number of rabbits that were non-gravid was observed in rabbits receiving 10 and 15 mg/kg/day of oral baclofen.
Mutagenicity and Carcinogenicity
Baclofen was negative for mutagenic and genotoxic potential in tests in bacteria, mammalian cells, yeast, and Chinese hamsters.
A 2-year rat study (oral administration of baclofen) found no evidence of carcinogenesis. An apparently dose related increase in the incidence of ovarian cysts and of enlarged and/or haemorrhagic adrenals at the maximum dose used (50 to 100 mg/kg) were observed in female rats treated with baclofen for two years. The clinical relevance of these findings is not known.
SELECTED BIBLIOGRAPHY
- 1. Faigle JW, and Keberle H: The chemistry and kinetics of LIORESAL. Postgrad. Med. J. (1972); (October Suppl.):9-13.
- 2. Pinto O de S, Polikar M, and Debono G: Results of international clinical trials with LIORESAL. Postgrad. Med. J. (1972); (October Suppl.): 18-23.
- 3. Pierau FK, and Zimmerman P: Action of a GABA-derivative on postsynaptic potentials and membrane properties of cats' spinal motoneurones. Brain Research (1973); 54: 376-380.
- 4. Fehr HU, and Bein HJ: Sites of action of a new muscle relaxant (baclofen, LIORESAL, CIBA 34 647-Ba). J. Int. Med. Res. (1974); 2: 36-47.
- 5. Lapierre YD, Elie R, and Tetreault L: The antispastic effects of Ba 34647 (B-4-p-chlorophenyl-Y-aminobutyric acid). A GABA derivative. Curr. Ther. Res. (1974); 16(10): 1059-1068.
- 6. Benecke R, and Meyer-Lohmann J: Effects of an antispastic drug [B-(4-chlorophenyl)-Y-amino- butyric acid] on Renshaw cell activity. Neuropharmacology (1974); 13: 1067-1075.
- 7. Brogden RN, Speight TM, and Avery GS: Baclofen: A preliminary report of its pharmacological properties and therapeutic efficacy in spasticity. Drugs (1974); 8: 1-14.
- 8. Knutsson E, Lindblom U, and Martensson A: Plasma and cerebrospinal fluid levels of baclofen (LIORESAL ) at optimal therapeutic responses in spastic paresis. J. Neurol. Sci. (1974); 23: 473-484.
- 9. From A, and Heltberg A: A double-blind trial with baclofen (LIORESAL) and diazepam in spasticity due to multiple sclerosis. Acta Neurol. Scandinav. (1975); 51: 158-166.
- 10. Abiog RO, Reyes OL, and Tan JC: Baclofen and diazepam in spinal spasticity: Assessment of therapeutic efficacy-. Arch.phys.Med. (1981): 62 (10); 504.
- 11. Hattab JR: Review of European clinical trials with baclofen. Spasticity Disordered Motor Control Internat. Symp., Scottsdale, Ariz. (1979). Ed. by RG Feldman, RR Young, WP Koella. Miami, Fla., Symposia Specialists, 1980, pp. 71-85.