


Product Monograph - Lipidil Ez
Recent Major Label Changes
| None at time of the most recent authorization |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics .................................................................................................................. 4
1.2. Geriatrics .................................................................................................................. 4
- 2. Contraindications ............................................................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 5
4.1. Dosing Considerations .............................................................................................. 5
4.2. Recommended Dose and Dosage Adjustment ......................................................... 5
4.4. Administration .......................................................................................................... 6
4.5. Missed Dose ............................................................................................................. 6
- 5. Overdose ......................................................................................................................... 6
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 6
- 7.
Warnings and Precautions ............................................................................................... 7
General ................................................................................................................................. 7
Carcinogenesis and Genotoxicity .......................................................................................... 7
Hematologic ......................................................................................................................... 8
Hepatic/Biliary/Pancreatic .................................................................................................... 8
Monitoring and Laboratory Tests ......................................................................................... 8
Musculoskeletal .................................................................................................................... 8
Renal ..................................................................................................................................... 9
Reproductive Health ............................................................................................................. 9
7.1. Special Populations .................................................................................................. 9
7.1.1. Pregnancy ........................................................................................................ 9
7.1.2. Breastfeeding ................................................................................................ 10
7.1.3. Pediatrics ....................................................................................................... 10
7.1.4. Geriatrics ....................................................................................................... 10
- 8.
Adverse Reactions ......................................................................................................... 10
8.1. Adverse Reaction Overview .................................................................................... 10
8.2. Clinical Trial Adverse Reactions .............................................................................. 10
8.3. Less Common Clinical Trial Adverse Reactions ....................................................... 14
8.5. Post-Market Adverse Reactions ............................................................................. 14
- 9.
Drug Interactions ........................................................................................................... 15
9.2. Drug Interactions Overview .................................................................................... 15
9.3. Drug-Behaviour Interactions .................................................................................. 15
9.4. Drug-Drug Interactions ........................................................................................... 15
9.5. Drug-Food Interactions........................................................................................... 19
9.6. Drug-Herb Interactions ........................................................................................... 19
9.7. Drug-Laboratory Test Interactions ......................................................................... 19
- 10.
Clinical Pharmacology ................................................................................................... 19
10.1. Mechanism of Action .............................................................................................. 19
10.2. Pharmacodynamics ................................................................................................ 19
10.3. Pharmacokinetics ................................................................................................... 21
- 11. Storage, Stability, and Disposal ...................................................................................... 22
Part 2: Scientific Information ................................................................................................ 23
- 13. Pharmaceutical Information .......................................................................................... 23
- 14.
Clinical Trials .................................................................................................................. 23
14.1. Clinical Trials by Indication ..................................................................................... 23
14.2. Comparative Bioavailability Studies ....................................................................... 27
- 16. Non-Clinical Toxicology .................................................................................................. 30
Patient Medication Information ........................................................................................... 34
Part 1: Healthcare Professional Information
1. Indications
LIPIDIL EZ (fenofibrate) is indicated as an adjunct to diet, at least equivalent to the Adults Treatment Panel III (ATP III) and Therapeutic Lifestyle Changes (TLC diet), and other therapeutic measures when the response to diet and other measures has been inadequate for:
- Treatment of patients, including patients with type 2 diabetes (non-insulin dependent), with dyslipoproteinemia (hypercholesterolemia, Fredrickson classification Types IIa and IIb mixed hyperlipidemia), to regulate lipid levels by reducing serum triglycerides and LDL cholesterol levels and increasing HDL cholesterol.
- Treatment of adult patients with very high serum triglyceride levels, Fredrickson classification Type IV and Type V hyperlipidemia, who are at a high risk of sequelae and complications (i.e., pancreatitis) from their hyperlipidemia.
LIPIDIL EZ, administered in combination with ezetimibe, is indicated for the reduction of elevated total-C, LDL-C, Apo B, and non HDL-C in patients with mixed hyperlipidemia.
LIPIDIL EZ alone may not be adequate therapy in some patients with familial combined hyperlipidemia with Type IIb and Type IV hyperlipoproteinemia.
LIPIDIL EZ is not indicated for the treatment of Type I hyperlipoproteinemia.
1.1. Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of LIPIDIL EZ in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 7.1.3 Pediatrics.
1.2. Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies suggests that use in the geriatric population is not associated with significant differences in safety or efficacy.
2. Contraindications
LIPIDIL EZ is contraindicated for:
- Patients who are hypersensitive to fenofibrate or to any ingredients in the formulation of components of the container including peanut or arachis oil or soya lecithin or related products. For complete listing, see the 6 Dosage Forms, Strengths, Composition, and Packaging.
- Patients with hepatic insufficiency (including primary biliary cirrhosis and unexplained persistent liver function abnormality).
- Patients with pre-existing gallbladder disease (see 7 Hepatic/Biliary/Pancreatic).
- Patients with severe renal dysfunction (creatinine clearance < 30ml/min).
- Patients with chronic or acute pancreatitis.
- Pregnant and breast-feeding women.
- Patients with known photoallergy or phototoxic reaction during treatment with fibrates or ketoprofen.
- Co-administration with HMG-CoA reductase inhibitors (statins) in patients with pre-disposing factors for myopathy.
4. Dosage and Administration
4.1. Dosing Considerations
- Patients should be placed on a standard cholesterol-lowering diet (at least equivalent to the Adult Treatment Panel III (ATP III TLC diet)) before receiving LIPIDIL EZ (fenofibrate), and should continue on this diet during treatment with LIPIDIL EZ. If appropriate, a program of weight control and physical exercise should be implemented.
- Prior to initiating therapy with LIPIDIL EZ, secondary causes for elevations in plasma lipid levels should be excluded. A lipid profile should also be performed.
- If a significant serum lipid response is not obtained in three months, LIPIDIL EZ should be discontinued.
4.2. Recommended Dose and Dosage Adjustment
- The usual recommended dose for LIPIDIL EZ in adults, is one 145 mg tablet daily, taken any time with or without food. Tablets should be swallowed whole with a glass of water. In the elderly, the initial dose should be limited to 48 mg per day. The dose should be individualized according to patient response and should be adjusted if necessary following repeat lipid determinations.
- The maximum recommended daily dose of LIPIDIL EZ is 145 mg.
- In patients having impaired renal function, treatment with LIPIDIL EZ should be initiated at a dose of 48 mg per day and increased only after evaluation of the effects on renal function and lipid levels at this dose.
- LIPIDIL EZ can be taken in combination with ezetimibe 10 mg once daily orally with or without food, preferably at the same time each day.
- Initial Therapy: Before instituting fenofibrate therapy, laboratory tests should be conducted to ensure that lipid levels are consistently abnormal. Attempts should be made to control serum lipids with appropriate diet, exercise and weight loss in obese patients. Secondary causes of hypercholesterolemia, such as uncontrolled type 2 diabetes mellitus, hypothyroidism, nephrotic syndrome, dysproteinemia, obstructive liver disease, pharmacological treatment and excessive alcohol intake should be adequately treated before fenofibrate therapy is initiated. In patients at high risk, consideration should be given to the control of other risk factors such as smoking, use of preparations containing estrogen and inadequately controlled hypertension.
- Long-term therapy: Because long-term administration of fenofibrate is recommended, the potential risks and benefits should be carefully weighed. Adequate pretreatment laboratory studies should be performed to ensure that patients have elevated serum cholesterol and/or triglycerides or low HDL-cholesterol levels.
Response to therapy should be monitored by determination of serum lipid values (e.g. total
- cholesterol, LDL-C, triglycerides). If a significant serum lipid response is not obtained in three months, LIPIDIL EZ should be discontinued.
- LIPIDIL EZ is not recommended for use in patients with hepatic impairment due to the lack of data.
- LIPIDIL EZ should not be used in patients with severe renal dysfunction including patients on dialysis.
4.4. Administration
Tablets can be taken any time with or without food and should be swallowed whole (not crushed or chewed) with a glass of water.
4.5. Missed Dose
If a dose is missed, the next dose should be taken at the usual time. A double dose should not be taken to make up for a forgotten dose.
5. Overdose
While there has been no reported case of overdosage, symptomatic and supportive measures should be taken. Fenofibrate is not dialysable because the main metabolite (fenofibric acid) is highly bound to plasma proteins.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Oral | Film-coated tablet 48 mg | colloidal silicon dioxide, crospovidone, docusate sodium, D&C Yellow #10 Aluminum Lake, FD&C yellow #6/sunset yellow FCF Aluminum Lake, FD&C Blue #2/Indigo carmine FCF Aluminum Lake, hypromellose, lactose monohydrate, soybean lecithin, magnesium stearate, microcrystalline cellulose, polyvinyl alcohol, sodium lauryl sulfate, sucrose, talc, titanium dioxide, xanthan gum. |
| Film-coated tablet 145 mg | colloidal silicon dioxide, crospovidone, docusate sodium, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyvinyl alcohol, sodium lauryl sulfate, soybean lecithin, sucrose, talc, titanium dioxide, | |
Availability
LIPIDIL EZ (fenofibrate) film-coated tablets are formulated for oral administration containing fenofibrate and are available in two strengths: 48 mg and 145 mg.
Composition
LIPIDIL EZ 48 mg tablets are supplied as yellow, oval, film-coated tablets (NanoCrystal® formulation) and are embossed with “FI” on one side. The tablets are available in blister packs of 30 tablets.
LIPIDIL EZ 145 mg tablets are supplied as white, oval, film-coated tablets (NanoCrystal® formulation) and are embossed with the Fournier logo on one side and 145 on the other. The tablets are available in blister packs of 30 tablets.
7. Warnings and Precautions
General
Fenofibrate and HMG-CoA Reductase Inhibitors (Statins)
The concomitant administration of LIPIDIL EZ (fenofibrate) and statins should be avoided unless the benefit for further alteration in lipid levels is likely to outweigh the increased risk of this combination.
The combined use of fibric acid derivatives and HMG-CoA reductase inhibitors has been associated, in the absence of a marked pharmacokinetic action, in numerous case reports, with rhabdomyolysis, severe myositis, markedly elevated creatine kinase (CK) levels and myoglobinuria, leading to a high proportion of cases to acute renal failure.
This combination therapy must not be used in patients with predisposing factors for myopathy (pre-existing myopathy, age >70 years, renal impairment, hepatic impairment, severe infection, surgery and trauma, frailty, hypothyroidism or electrolyte imbalance, personal or family history of hereditary muscular disorders, previous history of muscle toxicity with another HMG-CoA reductase inhibitor, concomitant use of a fibrate, niacin or ezetimibe, alcohol abuse, excessive physical exercise, diabetes with hepatic fatty change situations where an increase in plasma levels of active ingredient may occur).
For information on a specific HMG-CoA reductase inhibitor, consult a respective Product Monograph.
Concomitant administration with ezetimibe: When LIPIDIL EZ (fenofibrate) is to be administered with ezetimibe, the ezetimibe Product Monograph should be consulted. The co-administration of ezetimibe with fibrates other than fenofibrate has not been studied. Therefore, co-administration of ezetimibe and fibrates other than fenofibrate is not recommended (see 9.4 Drug-Drug Interactions, and Product Monograph for ezetimibe).
Carcinogenesis and Genotoxicity
In long-term animal toxicity and carcinogenicity studies, fenofibrate has been shown to be tumorigenic for the in benign Leydig cell tumors. Pancreatic acinar cell tumors were increased in male rats at 9 and 40 times the human dose. However, mice and female rats were unaffected at similar doses. Florid hepato-cellular liver in male rats at 12 times the human dose. At this dose level in male rats there was also an increase peroxisome proliferation has been observed following fenofibrate administration to
| xanthan gum. |
rats (see 16 Non-Clinical Toxicology, Carcinogenicity). Such changes have not been found in the human liver after up to 3.5 years of fenofibrate administration.
Hematologic
Mild hemoglobin, haematocrit and white blood cell decreases have been observed occasionally in patients following initiation of fenofibrate therapy. However, these levels stabilize during long-term administration. Periodic blood counts are recommended during the first 12 months of fenofibrate administration.
Hepatic/Biliary/Pancreatic
Fenofibrate may increase cholesterol excretion into the bile, and may lead to cholelithiasis.
If cholelithiasis is suspected in a patient receiving ezetimibe and LIPIDIL EZ, gallbladder studies are indicated and alternative lipid-lowering therapy should be considered (see 8 Adverse Reactions).
Pancreatitis: In common with some other fibrates, pancreatitis has been reported in patients taking fenofibrate. This occurrence may represent a failure of efficacy in patients with severe hypertriglyceridemia, a direct drug effect, or a secondary phenomenon mediated through biliary tract stone or sludge formation with obstruction of the common bile duct. In patients with severe hypertriglyceridemia, cases of acute pancreatitis have been reported.
Cholelithiasis: Fenofibrate may increase cholesterol excretion into the bile, and may lead to cholelithiasis. If cholelithiasis is suspected, gallbladder studies are indicated. LIPIDIL EZ therapy should be discontinued if gallstones are found.
Monitoring and Laboratory Tests
Abnormal liver function tests have occasionally been observed during fenofibrate administration, including elevations of transaminases, and decreases or, rarely, increases in alkaline phosphatase. From 5 placebo-controlled trials of 2 to 6 months’ duration, increases up to >3 times the upper limit of normal occurred in 2.9% (14/477) of patients taking fenofibrate versus 0.5% (2/386) of those treated with placebo. In the DAIS study (3 years duration), increases up to 3 times the upper limit of normal occurred in 1.9% (4/207) of patients taking fenofibrate versus 0% of those treated with placebo (0/211). Follow-up measurements, performed either at the end of treatment or during continued treatment, showed that transaminase values generally returned to normal limits. Therefore, regular periodic liver function tests (AST, ALT and GGT) in addition to other baseline tests are recommended every 3 months for the first 12 months and at least yearly thereafter. LIPIDIL EZ should be discontinued if abnormalities persist and / or AST and ALT levels increase to more than 3 times the upper limit of normal.
Concomitant administration with ezetimibe: When ezetimibe is initiated in a patient already taking LIPIDIL EZ, liver function tests should be considered at initiation of ezetimibe therapy and then as indicated. When ezetimibe is initiated at the same time as LIPIDIL EZ, liver function tests should be performed at initiation of therapy according to the above recommendations (see 8 Adverse Reactions).
Musculoskeletal
The use of fibrates alone, including LIPIDIL EZ, may occasionally be associated with myositis, myopathy or rhabdomyolysis, usually in patients with impaired renal function and in cases of hypoalbuminemia. Patients receiving LIPIDIL EZ should be advised to promptly report diffuse myalgias/muscle pain, muscle cramps, tenderness, or weakness, particularly if accompanied by malaise or fever. They should have prompt medical evaluation for myopathy, including serum creatine phosphokinase level determination. If markedly elevated CK levels (5 times the upper limit of normal), myopathy and or myositis is suspected or diagnosed, LIPIDIL EZ therapy should be stopped.
Patients with pre-disposing factors for myopathy may be at an increased risk of developing rhabdomyolysis (see 7 General, Fenofibrate and HMG-CoA Reductase Inhibitors (Statins)). For these patients, the putative benefits and risks of fenofibrate therapy should be carefully weighed.
The risk of muscle toxicity may be increased if the drug is administered with another fibrate or an HMG-CoA reductase inhibitor, especially in case of pre-existing muscular disease (see 7 General, Fenofibrate and HMG-CoA Reductase Inhibitors (Statins)). Consequently, the co-administration of fenofibrate with a HMG-CoA reductase inhibitor or another fibrate should be reserved to patients with severe combined dyslipidemia and high cardiovascular risk without any history of muscular disease or other pre-disposing factors for myopathy (see 7 General, Fenofibrate and HMG-CoA Reductase Inhibitors (Statins)) and with a close monitoring of potential muscle toxicity.
Post marketing reports of adverse events have included rare cases of myopathy/rhabdomyolysis occurring in patients taking ezetimibe. Myopathy/ rhabdomyolysis should be considered in patients presenting with muscle pain during treatment with ezetimibe and LIPIDIL EZ, and consideration given to discontinuation of the drugs. Most cases of myopathy/rhabdomyolysis resolved when drugs were discontinued.
Renal
In patients with hypoalbuminemia, e.g., nephrotic syndrome, and in patients with renal insufficiency, the dosage of fenofibrate must be reduced and renal function should be monitored regularly (see 7 Skeletal Muscle, 4 Dosage and Administration, and 10 Clinical Pharmacology).
Treatment should be interrupted in case of an increase in creatinine level > 50% upper limit of normal. It is recommended that creatinine measurement may be considered during the first three months after initiation of treatment.
Reproductive Health
Standard tests for teratology, fertility and peri- and post-natal effects in animals have shown a relative absence of risk; however, embryo-toxicity has occurred in animals at maternally toxic doses (see 16 Non-Clinical Toxicology).
7.1. Special Populations
7.1.1. Pregnancy
Safety in pregnant women has not been established. Fenofibrate has been shown to be embryocidal in rats when given in doses 7 to 10 times the maximum recommended human dose (MRHD) and in rabbits when given in doses 9 times the MRHD (on the basis of mg/m2 surface area). There are no adequate and well-controlled studies in pregnant women. Fenofibrate should not be used during pregnancy (see 16 Non-Clinical Toxicology).
7.1.2. Breastfeeding
It is unknown whether fenofibrate and/or its metabolites are excreted in human milk. A risk to the suckling child cannot be excluded. Therefore LIPIDIL EZ should not be used during breast-feeding (see 16 Non-Clinical Toxicology).
7.1.3. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada to establish the safety and efficacy of fenofibrate in children and adolescents younger than 18 years. Therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (>65 years of age): Fenofibrate is excreted by the kidney. Therefore, the risk of adverse reactions to LIPIDIL EZ may be greater in the elderly patients with impaired renal function. Since elderly patients are more likely to have a decreased renal function, dose should be carefully selected (see 4 Dosage and Administration).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The most frequently reported adverse events include: gastrointestinal (epigastric distress, flatulence, abdominal pain, nausea, diarrhea, constipation), dermatologic (erythema, pruritus, urticaria), musculoskeletal (muscle pain and weakness, arthralgia), central nervous system (headache, dizziness, insomnia), miscellaneous (decreased libido, hair loss, weight loss).
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
In five placebo-controlled clinical trials, conducted in the U.S. and Europe, a total of 477 patients on fenofibrate and 386 patients on placebo were evaluated for adverse effects during 2 to 6 months of treatment.
Adverse events led to the withdrawal of treatment in 5.5% of patients (26/477) treated with fenofibrate, the most common symptoms being abnormal elevation in transaminases, skin reactions and digestive disorders. Of the placebo-treated patients, 2.6% (10/386) were discontinued due to adverse effects.
Adverse events, regardless of their causality, reported in more than 1% of patients are shown in Table 2.
Table 2 – Number (%) of Patients Reporting Adverse Events
Fenofibrate n = 477 | Placebo n = 386 | |
Fenofibrate n = 477 | Placebo n = 386 | |
| Body as a whole | 68 (14.3%) | 51 (13.2%) |
| Abdominal pain | 12 (2.5%) | 8 (2.1%) |
| Asthenia | 14 (2.9%) | 7 (1.8%) |
| Headache | 15 (3.1%) | 11 (2.8%) |
| Cardiovascular system | 15 (3.1%) | 13 (3.4%) |
| Digestive system | 63 (13.2%) | 47 (12.2%) |
| Diarrhea | 10 (2.1%) | 13 (3.4%) |
| Nausea | 12 (2.5%) | 7 (1.8%) |
| Constipation | 6 (1.3%) | 3 (0.8%) |
| Dyspepsia | 5 (1.0%) | 6 (1.6%) |
| Flatulence | 10 (2.1%) | 10 (2.6%) |
| Endocrine system | 1 (0.2%) | 1 (0.3%) |
| Haemic & lymphatic system | 3 (0.6%) | 1 (0.3%) |
| Metabolic & nutritional disorders | 18 (3.8%) | 14 (3.6%) |
| ALT increase | 12 (2.5%) | 4 (1.0%) |
| AST increase | 8 (1.7%) | 1 (0.3%) |
| ALT/AST increase | 9 (4.9%) | 0 |
| CPK increase | 1 (0.2%) | 5 (1.3%) |
| Creatinine increase | 8 (1.7%) | 1 (0.3%) |
| Musculo-skeletal system | 31 (6.5%) | 21 (5.4%) |
| Arthralgia | 11 (2.3%) | 11 (2.8%) |
| Myalgia | 3 (0.6%) | 4 (1.0%) |
| Nervous system | 31 (6.5%) | 11 (2.8%) |
| Dizziness | 5 (1.0%) | 4 (1.0%) |
| Respiratory system | 34 (7.1%) | 25 (6.5%) |
| Rhinitis | 10 (2.1%) | 4 (1.0%) |
| Skin and appendages | 24 (5.0%) | 12 (3.1%) |
| Rash | 11 (2.3%) | 3 (0.8%) |
| Pruritus | 10 (2.1%) | 3 (0.8%) |
| Special senses | 14 (2.9%) | 10 (2.6%) |
| Urogenital system | 14 (2.9%) | 9 (2.3%) |
Safety was monitored for 3 years during the placebo-controlled DAIS study (see 14 Clinical Trials) for both adverse events and laboratory anomalies. Fenofibrate was used safely in type 2 diabetic patients, as the overall incidence and severity of adverse events were comparable in fenofibrate and placebo groups. Table 3 below summarizes the incidence of adverse events, by body system, observed in both treatment groups.
Table 3 – DAIS study: Incidence of adverse events (AEs) by system, experienced by type 2 diabetic patients during treatment with fenofibrate or placebo (ITT population)
| Body System | Fenofibrate n = 207 | Placebo n = 211 | ||||||||||
| Total # pts. with at least 1 AE | AEs | Patients | Aes | Patients | ||||||||
Total AEs: 1710 | 201 (97.1%) | Total AEs: 1759 | 202 (95.7%) | |||||||||
| Body as a whole | 371 (21.7%) | 136 (65.7%) | 362 (20.6%) | 146 (69.2%) | ||||||||
| Cardiovascular | 183 (10.7%) | 84 (40.6%) | 220 (12.5%) | 96 (45.5%) | ||||||||
| Digestive | 196 (11.5%) | 86 (41.6%) | 194 (11.0%) | 87 (41.2%) | ||||||||
| Endocrine | 11 (0.6%) | 10 (4.8%) | 19 (1.1%) | 11 (5.2%) | ||||||||
| Haemic/lymphatic | 31 (1.8%) | 19 (9.2%) | 23 (1.3%) | 15 (7.1%) | ||||||||
| Metabolic/nutritional | 50 (2.9%) | 32 (15.5%) | 70 (4.9%) | 41 (19.4%) | ||||||||
| Musculo-skeletal | 155 (9.1%) | 84 (40.6%) | 180 (10.2%) | 84 (39.8%) | ||||||||
| CNS | 103 (6.0%) | 59 (28.5%) | 98 (5.6%) | 58 (27.5%) | ||||||||
| Respiratory | 301 (17.6%) | 108 (52.2%) | 279 (15.9%) | 105 (49.8%) | ||||||||
| Skin/appendage | 107 (6.3%) | 58 (28.0%) | 107 (6.1%) | 48 (22.8%) | ||||||||
| Special senses | 73 (4.3%) | 44 (21.3%) | 90 (5.1%) | 50 (23.7%) | ||||||||
| Urogenital | 118 (6.9%) | 55 (26.6%) | 103 (5.9%) | 46 (21.8%) | ||||||||
| Other | 11 (0.6%) | 9 (4.4%) | 14 (0.8%) | 11 (5.2%) | ||||||||
In two open, non-controlled clinical studies conducted in Canada and Germany, a total of 375 patients on fenofibrate, microcoated formulation, were evaluated for adverse events. Listed in Table 4 are the adverse events possibly or probably related to fenofibrate, microcoated formulation and reported by more than 0.5% of the patients.
Table 4 – Number (%) of Patients Reporting Adverse Events Possibly or Probably Related to Fenofibrate
Canadian and German multicenter studies (12-week treatment) | |
| Adverse Events | Microcoated Fenofibrate n = 375 |
| Digestive system | |
| Gastrointestinal disorder | 4 (1.1%) |
| Nausea | 3 (0.8%) |
| Flatulence | 2 (0.5%) |
| Diarrhea | 2 (0.5%) |
| Liver function tests abnormal | 2 (0.5%) |
| Dyspepsia | 2 (0.5%) |
| Gastritis | 2 (0.5%) |
| Constipation | 2 (0.5%) |
| Body as a whole | |
| Abdominal pain | 4 (1.1%) |
| Headache | 2 (0.5%) |
| Asthenia | 2 (0.5%) |
| Lab test abnormal | 2 (0.5%) |
| Metabolic and Nutritional Disorders | |
| ALT increased (> 3 x UNL) | 3 (0.8%) |
| AST increased (> 3 x UNL) | 4 (1.1%) |
| Creatine kinase increased (> 5 x UNL) | 2 (0.5%) |
| Nervous system | |
| Dizziness | 2 (0.5%) |
| Libido decreased | 2 (0.5%) |
Some epidemiological studies and case reports support paradoxical HDL-C lowering with fenofibrate.
Other adverse events include commonly reported cases of vomiting and increase in levels of blood homocysteine*. Uncommonly reported cases of pancreatitis and venous thromboembolism (pulmonary embolism and deep vein thrombosis). Rarely reported cases of alopecia, sexual asthenia, rhabdomyolysis, myositis and muscular cramps. Episodes of hepatitis have been reported. When symptoms indicative of hepatitis occur (e.g. jaundice, pruritus), and diagnosis is confirmed by laboratory testing, fenofibrate therapy should be discontinued (see 7 Monitoring and Laboratory Tests).
Photosensitivity reactions, development of gallstones and cutaneous hypersensitivity with erythema and vesiculation or nodulation on parts of the skin exposed to sunlight or artificial UV light in individual cases (even after many months of uncomplicated use) have also been reported.
* The average increase in blood homocysteine level in patients treated with fenofibrate was 6.5 μmol/L, and was reversible on discontinuation of fenofibrate treatment. The increased risk of venous thrombotic events may be related to the increased homocysteine level. The clinical significance of this is not clear.
Combination with ezetimibe:
When LIPIDIL EZ (fenofibrate) is to be administered with ezetimibe, the ezetimibe Product Monograph should also be consulted.
In a clinical study involving 625 patients treated for up to 12 weeks and 576 patients treated for up to 1 year, co-administration of fenofibrate and ezetimibe was well tolerated. This study was not designed to compare treatment groups for infrequent events. Incidence rates (95% CI) for clinically important elevations (>3 ULN, consecutive) in serum transaminases were 4.5% (1.9, 8.8) and 2.7% (1.2, 5.4) for fenofibrate monotherapy and ezetimibe co-administered with fenofibrate, respectively, adjusted for treatment exposure. Corresponding incidence rates for cholecystectomy were 0.6% (0.0, 3.1) and 1.7% (0.6, 0.4) for fenofibrate monotherapy and ezetimibe co-administered with fenofibrate, respectively (see 9.4 Drug-Drug Interactions). There were no CPK elevations > 10X ULN in either treatment group in this study. No cases of myopathy, rhabdomyolysis, or pancreatitis were reported in this 12 weeks study.
8.3. Less Common Clinical Trial Adverse Reactions
See Table 4.
8.5. Post-Market Adverse Reactions
In addition to those events reported during clinical trials, the following side effects have been reported spontaneously during post-marketing use:
Respiratory, thoracic and mediastinal disorders: Interstitial lung disease.
Hepatobiliary Disorders: jaundice, complications of cholelithiasis (e.g., cholecystitis, cholangitis, biliary colic, etc.)
Skin and Subcutaneous Tissue Disorders: severe cutaneous reactions (e.g erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis)
Nervous system disorders: Fatigue
9. Drug Interactions
9.2. Drug Interactions Overview
Fenofibrate is highly protein bound (>99%), mainly to albumin. Consideration should be given to the potential for displacement drug interactions with other highly protein-bound drugs.
9.3. Drug-Behaviour Interactions
The interaction of LIPIDIL EZ with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4. Drug-Drug Interactions
No drug-drug interaction studies with fenofibrate and statins have been conducted in patients.
Pharmacokinetic interaction studies conducted with drugs in healthy subjects may not detect the possibility of a potential drug interaction in some patients due to differences in underlying disease and use of concomitant medications (see 7 General, Fenofibrate and HMG-CoA Reductase Inhibitors (Statins)).
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 5 – Established or Potential Drug-Drug Interactions
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
| Atorvastatin | CT | Concomitant administration of fenofibrate (equivalent to 145 mg LIPIDIL EZ) with atorvastatin (20 mg) once daily for 10 days resulted in a 14% decrease in the mean atorvastatin AUC value (range: from a 67% decrease to a 44% increase) in 22 healthy males. There was a no change in the atorvastatin mean Cmax value (range: from a 60% decrease to a 136% increase). No significant pharmacokinetic interaction was observed in the mean fenofibric acid | Although atorvastatin co-administration had no effect on the pharmacokinetics of fenofibrate and fenofibrate co-administration had only little effect on the pharmacokinetics of atorvastatin, combination therapy should be used with caution and patients monitored closely for signs of muscle toxicity. |
| AUC (2.3% decrease, range: from a 39% decrease to a 40 % increase) or in the mean Cmax (3.8% decrease, range: from a 29% decrease to a 42% increase) when fenofibrate was co-administered with multiple doses of atorvastatin. | |||
| Bile Acid Sequestrants | CT, C | The absorption of fibrates is impaired by cholestyramine. | When a fibrate is used concurrently with cholestyramine or any other resin, an interval of at least 2 hours should be maintained between the administration of the two drugs. |
| Estrogens | P | Estrogens may lead to a rise in lipid levels. | Prescribing fibrates in patients taking estrogens or estrogen-containing contraceptives must be considered clinically on an individual basis. |
| Ezetimibe | CT | In a pharmacokinetic study, concomitant fenofibrate administration increased total ezetimibe concentrations approximately 1.5-fold. The safety and effectiveness of fenofibrate co-administered with ezetimibe have been evaluated in a clinical study (see 7 General, Fenofibrate and HMG-CoA Reductase Inhibitors (Statins), Hepatic/Biliary/Pancreatic, Monitoring and Laboratory Tests, and Musculoskeletal, 8 Adverse Reactions, and 14 Clinical Trials). Co-administration of ezetimibe with other fibrates has not | If ezetimibe and fenofibrate are co-administered, monitor patients for signs and symptoms of cholelithiasis, particularly during initiation of therapy and during upward dose titration. If cholelithiasis is suspected, initiate gallbladder studies and consider alternative lipid-lowering therapy. |
| been studied (see ezetimibe Product Monograph). | |||
| Oral Anticoagulants | C | Fenofibrate enhances oral anticoagulant effect and may increase risk of bleeding. | Caution should be exercised when oral anticoagulants are given in conjunction with LIPIDIL EZ. The dosage of oral anticoagulant should be reduced to maintain the prothrombin time at the desired level to prevent bleeding complications. Careful monitoring of prothrombin time is therefore recommended until it has been definitely determined that the prothrombin level has been stabilized. |
| Pravastatin | CT | Concomitant administration in 23 healthy adults of fenofibrate (equivalent to 145 mg LIPIDIL EZ) with pravastatin, 40 mg once daily for 10 days, has been shown to increase the mean Cmax and AUC values for pravastatin by 36% (range: from a 69% decrease to a 321% increase) and 28% (range: from a 54% decrease to a 128% increase), respectively. Co-administration of fenofibrate with pravastatin also increased the mean Cmax and AUC of the major metabolite, 3-alpha-hydroxy-iso-pravastatin by 55% (range: from a 32% decrease to a 314% increase) and 39% (range: from a 24% | Fenofibrate co-administration had modest effect on the pharmacokinetics of pravastatin and combination therapy should be used with caution and patients monitored closely for signs of muscle toxicity. |
| decrease to a 261% increase), respectively. | |||
| Rosiglitazone | C | Some epidemiologic studies and case reports suggest that markedly decreased HDL-C in some patients involve the interaction of rosiglitazone with fenofibrate or bezafibrate. Laboratory findings in some published case reports demonstrated that, in some cases, it is the combination of rosiglitazone and fenofibrate, and neither agent alone, that lowers HDL-C. | It is recommended to monitor HDL-cholesterol if rosiglitazone is added to the other and stopping of either therapy if HDL-cholesterol is too low. |
| Rosuvastatin | CT | Co-administration of fenofibrate (67 mg three times daily) and rosuvastatin (10 mg once daily) for seven days did not lead to a clinically significant change in the plasma concentrations of either drug. | Although co-administration of rosuvastatin and fenofibrate did not lead to a significant change in plasma concentrations of either drug, combination therapy should be used with caution and patients monitored closely for signs of muscle toxicity. |
| Simvastatin | CT | The mean AUC of simvastatin acid, decreased by 42% (range: from a 77% decrease to a 50% increase). No change in the mean simvastatin acid Cmax (range: from a 67% decrease to a 92% increase). The mean fenofibric acid Cmin plasma levels increased by 14% (range: from a 7% decrease to a 48% increase). | Although co-administration of fenofibrate and simvastatin had only little effect on the pharmacokinetics of either drug, combination therapy should be used with caution and patients monitored closely for signs of muscle toxicity. |
| Cyclosporine | C | Severe myositis and rhabdomyolysis have occurred when | Therefore, the benefits and risks of using fenofibrate concomitantly with these |
cyclosporine was administered in combination therapy with a fibrate. Some severe cases of reversible renal function impairment have been reported during concomitant administration of fenofibrate and cyclosporine. | drugs should be carefully considered. The renal function of these patients must therefore be closely monitored and treatment with fenofibrate stopped in the case of severe alteration of laboratory parameters. | ||
Legend: C = Case Study; CT = Clinical Trial; P = Potential
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
- 10. Clinical Pharmacology
10.1. Mechanism of Action
LIPIDIL EZ (fenofibrate) lowers elevated serum lipids by decreasing the low-density lipoprotein (LDL) fraction rich in cholesterol and the very low-density lipoprotein (VLDL) fraction rich in triglycerides. In addition, fenofibrate increases the high-density lipoprotein (HDL) cholesterol fraction.
Fenofibrate appears to have a greater depressant effect on the VLDL than on the low-density lipoproteins (LDL). Therapeutic doses of fenofibrate produce elevations of HDL cholesterol, a reduction in the content of the low-density lipoprotein cholesterol, and a substantial reduction in the triglyceride content of VLDL.
10.2. Pharmacodynamics
Fenofibrate is a fibric acid derivative whose lipid modifying effects reported in humans are mediated by the activation of a specific nuclear receptor called peroxisome proliferator activated receptor alpha (PPARα), which produces:
- a reduction in apo C-III, and therefore a reduction in the level of dense atherogenic LDL particles;
- a stimulation of mitochondrial beta-oxidation, and therefore a reduction in triglyceride secretion;
- a rise in lipoprotein lipase production, and therefore an acceleration of triglyceride rich lipoprotein breakdown;
- a rise in apo A-I and apo A-II production.
Animal Pharmacology
The antilipidemic activity of fenofibrate was investigated in normal and hyperlipidemic rats. Fenofibrate significantly lowers total lipids, LDL and VLDL cholesterol, and triglyceride levels. At the same time it has been found to variably increase HDL cholesterol concentrations. Its effect is more pronounced in hyperlipidemic rats and those fed high fat diets than in normal rats and those fed standard diets. Studies comparing fenofibrate with clofibrate have found that fenofibrate is a potent cholesterol-lowering drug.
The pronounced hypolipidemic effect in hyperlipidemic animals suggests that fenofibrate reduces cholesterol by enhancing the rate of cholesterol elimination. In normocholesterolemic rats, the main effect of fenofibrate is an inhibition of cholesterol biosynthesis.
Fenofibrate has no anti-inflammatory, cardiovascular, respiratory, CNS, autonomic nervous system, or other basal metabolism activities.
Clinical Pharmacology
Uricosuric action
Fenofibrate decreased the plasma uric acid levels in normal as well as hyperuricemic subjects. In a study involving 10 healthy male volunteers, single doses of 300 mg of fenofibrate, non-micronized formulation, were compared to benzbromarone. A uricosuric action was observed with both drugs. During a 14-day study in hyperlipidemic patients, a 28 % decrease in plasma uric acid concentration was observed less than four days after the onset of treatment with 300 mg/day of fenofibrate, non-micronized formulation. This effect remained constant until the end of the study. An additional study conducted in healthy volunteers confirmed the rapid onset of the fenofibrate-induced hypouricemic effect and demonstrated the increased capability of the kidneys under these conditions to eliminate uric acid without damage to the proximal tubules.
Effect on lithogenic index
By virtue of structural similarity to other fibrates, fenofibrate might be suspected of increasing the risk of gallstones as a result of increased cholesterol excretion via the bile.
The biliary lithogenic index in fenofibrate-treated patients was evaluated. In most studies, the lithogenic index was shown to be increased but the effect of fenofibrate was not marked and the degree of significance varied from one study to another. The relative proportions of bile lipids were also affected by fenofibrate treatment.
It is not known how fenofibrate treatment modifies the lipid composition of the bile.
Human liver biopsies
Two specific studies have been conducted in hyperlipidemic patients to evaluate the potential hepatocellular toxicity of fenofibrate. Examination of biopsies from liver samples of 38 patients including 28 receiving fenofibrate, non-micronized formulation, over a mean period of approximately 2 years did not show any difference between treated and untreated patients. Peroxisomes were relatively rare, and macroscopic light and electron-microscopic observations revealed no sign of treatment-associated cellular abnormality. A similar study, taking biopsies from 10 patients who had, on average, received fenofibrate, non-micronized formulation, for 9 months, and comparing these with tissue from 13 hyperlipidemic patients who had only received dietary treatment did not show any morphological difference between the two groups or any significant difference in the number or in the size of peroxisomes.
Concomitant administration with ezetimibe: Administration of fenofibrate with ezetimibe is effective in improving serum total-C, LDL-C, Apo-B, TG, HDL-C, and non-HDL-C in patients with mixed hyperlipidemia.
Clinical studies have demonstrated that elevated levels of total-C, low density lipoprotein cholesterol (LDL-C) and apolipoprotein B (Apo B; the major protein constituent of LDL), promote atherosclerosis in humans. In addition, decreased levels of high density lipoprotein cholesterol (HDL-C) are associated with the development of atherosclerosis. Epidemiologic studies have established that cardiovascular morbidity and mortality vary directly with the level of total-C and LDL-C and inversely with the level of HDL-C. Like LDL, cholesterol-enriched triglyceride-rich lipoproteins, including very low density lipoproteins (VLDL), intermediate density lipoproteins (IDL), and remnants, can also promote atherosclerosis. The effects of fenofibrate given with ezetimibe on cardiovascular morbidity and mortality have not been established.
10.3. Pharmacokinetics
Absorption
Absorption of a micronized fenofibrate formulation (LIPIDIL Micro 200 mg capsules) is low and variable when administered under fasting conditions and increases when given with food. Fenofibrate, given in a micro-coated formulation (LIPIDIL SUPRA 160 mg tablets), requires lower doses (160 mg) to achieve equivalent plasma levels to the micronized (200 mg) formulation. Nanocrystallization of fenofibrate allows for further reduction in the dose (LIPIDIL EZ 145 mg tablets), and LIPIDIL EZ may be taken without regard to meals, because of optimized product absorption.
Distribution
Fenofibric acid is extensively bound (> 99 %) to plasma albumin. This binding is not saturable.
Metabolism
After oral administration, fenofibrate is rapidly hydrolysed to fenofibric acid, the active metabolite.
Elimination
In man, fenofibric acid is eliminated as the glucuronic acid conjugate and is mainly excreted through the kidney. In man, the elimination half-life of fenofibric acid is about 20 to 24 hours, a value that is not modified after multiple dosing.
In healthy elderly patients (77 to 87 years of age), the terminal half-life is prolonged, but no dose adjustment is required due to unchanged clearance.
Special populations and conditions
- Pediatrics: Safety and effectiveness have not been established in pediatric patients.
- Sex: No gender-related differences in pharmacokinetics and metabolism have been observed.
- Hepatic Insufficiency: No pharmacokinetic studies have been conducted in patients having hepatic insufficiency.
Renal Insufficiency: In patients with severe renal impairment the rate of clearance of fenofibric acid is greatly reduced, and the compound accumulates during chronic dosage.
In patients having moderate renal impairment (creatinine clearance of 30 to 60 mL per min.), the oral clearance and oral volume of distribution of fenofibric acid are increased compared to healthy adults (2.1 L/h and 95 L versus 1.1 L/H and 30 L, respectively). Therefore, the dosage of LIPIDIL EZ should be minimized to 48 mg in patients who have moderate renal impairment.
If no low dose is available, then fenofibrate is not recommended.
In patients with severe renal impairment (creatinine clearance < 30ml/min), fenofibrate is contraindicated.
- Storage, Stability, and Disposal
Store at 15 to 30°C. Protect from light and moisture.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): fenofibrate
Chemical name: 2-(4-(4-chlorobenzoyl) phenoxy)-2-methyl-propanoic acid 1-methylethyl ester.
Molecular formula and molecular mass: C20 H21 O4 Cl 360.83
Structural formula: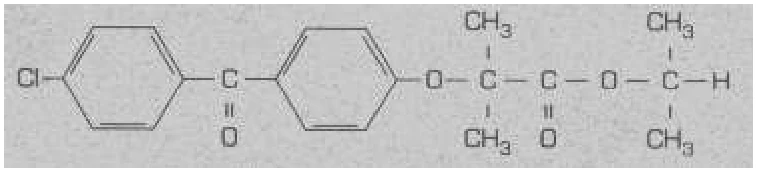
Physicochemical properties: Description: Fenofibrate is a crystalline, whitish powder.
Melting point: 79 to 82°C.
Solubilities: Fenofibrate is practically insoluble in water, slightly soluble in ethanol, freely soluble in acetone and chloroform.
14. Clinical Trials
14.1. Clinical Trials by Indication
Study design and study population
The activity of fenofibrate has been evaluated in more than 150 clinical trials performed in the U.S., Canada and Europe. The majority of these were conducted with fenofibrate, micronized formulation (LIPIDIL Micro), at a daily dose of 200 mg.
Specific clinical studies were performed with fenofibrate, micronized formulation (LIPIDIL Micro).
The first clinical trial followed a double-blind, parallel group versus placebo design. One hundred and eighty-nine patients (Type IIa; 120 and Type IIb; 69) were randomized in three groups: placebo, 200 mg micronized fenofibrate and 3 x 100 mg non-micronized fenofibrate. The ages of the patients ranged from 18 to 75 years. The intent-to-treat analysis indicated an efficacy level after 3 months (as assessed by the number of patients who experienced a cholesterol reduction > 15%) which was significantly greater in the micronized fenofibrate group (71.9%) than in the placebo group (14.8%). Micronized fenofibrate treatment was significantly more active than placebo in reducing total cholesterol (-18%), LDL-cholesterol (-22%), triglycerides (-19%) and apolipoprotein B (-24%).
The second clinical trial evaluated the effectiveness of micronized fenofibrate on lipid parameters. Of 131 eligible patients, 94 (31 Type IIa, 23 Type IIb and 40 Type IV) were evaluated for efficacy. Of those with Type IIa and Type IIb, 45.1% and 69.6%, respectively, were classified as good responders for total cholesterol. Of patients with Type IIb and IV, 71.4% and 77.7%, respectively, were considered good responders for triglycerides. After 3 months of treatment, the mean value of total cholesterol was lowered in patients with Type IIa from 311.4 mg/dl to 258.3 mg/dl with a mean decrease of 17 %. In patients with Type IIb, the mean value of total cholesterol was lowered from 328.0 mg/dl to 266.5 mg/dl, with a mean decrease of 18.6 %. The mean value of triglycerides was lowered in patients with Type IIb from 254.8 mg/dl to 165.7 mg/dl with a mean decrease of 34.4 %. In patients with Type IV, the mean value of triglycerides was lowered from 383.8 mg/dl to 231.1 mg/dl with a mean decrease of 37.9 %.
A placebo-controlled, double-blind study was also performed in 418 patients with type 2 diabetes: The Diabetes Atherosclerosis Intervention Study (DAIS). The patients were randomized to either micronized fenofibrate 200 mg once daily or to placebo for an average of 38 months. The main objectives were to determine the safety of 200 mg fenofibrate, micronized formulation, in a population of type 2 diabetic patients and to measure angiographic responses by quantitative coronary angiography (QCA). Male (73%) and female patients were included in the study. They presented with adequate glycemic control, total cholesterol/high density lipoprotein cholesterol ratio ≥4, and either low-density lipoprotein cholesterol (LDL-C) from 3.5 to 4.5 mmol/l with triglycerides (TG) ≤ 5.2 mmol/l, or TG from 1.7 to 5.2 mmol/l with LDL C ≤ 4.5 mmol/l. An adequate QCA with previous CABG or PTCA or at least one coronary segment with a minimal detectable stenosis was also required.
Study results
The primary efficacy parameter was the mean segment parameter, averaged per patient, to test a null hypothesis of no difference between fenofibrate- and placebo-treated patients. Additional secondary angiographic efficacy parameters were also analyzed.
The angiographic results showed that the primary endpoint (mean segment diameter per patient) did not reach statistical significance and the change from baseline was not clinically meaningful (see following Table 6). The change in mean segment diameter was minimal in both groups over the treatment period, with no statistical difference between groups.
Table 6 – DAIS study: Mean coronary angiogram values (± S.D.) averaged per patient and per segment at baseline and at the end of study (ITT population)
| Fenofibrate | Placebo | p-value* | |||||
| Per patient analysis | N=207 | N=211 | |||||
| |||||||
| Baseline | 2.70 (0.45) | 2.67 (0.45) | 0.494 | ||||
| Final | 2.62 (0.49) | 2.56 (0.50) | 0.173 | ||||
| |||||||
| Baseline | 2.14 (0.44) | 2.10 (0.44) | 0.457 | ||||
| Final | 2.05 (0.46) | 1.98 (0.48) | 0.028 | ||||
| |||||||
| Baseline | 21.8 (7.8) | 21.8 (7.4) | 0.958 | ||||
| Final | 24.1 (9.8) | 25.7 (10.8) | 0.02 | ||||
| Fenofibrate | Placebo | p-value* | |
| Per segment analysis | N=1884 | N=1993 | |
| |||
| Baseline | 2.76 (0.84) | 2.72 (0.83) | 0.145 |
| Final | 2.68 (0.87) | 2.62 (0.87) | 0.037 |
| |||
| Baseline | 2.20 (0.82) | 2.16 (0.81) | 0.077 |
| Final | 2.11 (0.84) | 2.03 (0.83) | 0.541 |
| |||
| Baseline | 21.0 (13.1) | 21.4 (12.8) | 0.309 |
| Final | 23.0 (15.9) | 24.9 (17.2) | 0.059 |
*p-values for Student’s t test and for covariance analysis to compare treatment groups, respectively, at baseline and at the end of the study (last available value on treatment). Statistical significance was established at 0.025.
The changes in lipid levels were also monitored in the type 2 diabetic patients included in the DAIS study. The major lipid values at baseline and at the end of the study are shown in the following Table 7 for both the fenofibrate- and placebo-treated groups.
Table 7 – DAIS study: Mean major lipid values (±S.D.) at baseline and at the end of the study (ITT population)
| Fenofibrate | Placebo | p-value* | |
| |||
| Baseline | 5.56 (0.80) | 5.58 (0.72) | 0.751 |
| Final | 4.93 (0.83) | 5.42 (0.79) | < 0.001 |
| |||
| Baseline | 2.56 (1.23) | 2.52 (1.22) | 0.706 |
| Final | 1.65 (0.90) | 2.16 (1.20) | < 0.001 |
| |||
| Baseline | 1.00 (0.19) | 1.04 (0.21) | 0.045 |
| End of study | 1.06 (0.26) | 1.06 (0.24) | 0.045 |
| |||
| Baseline | 3.36 (0.71) | 3.39 (0.72) | 0.532 |
| Final | 3.12 (0.69) | 3.38 (0.73) | 0.042 |
| TC / HDL-C | |||
| Baseline | 5.63 (1.08) | 5.51 (1.10) | 0.115 |
| Final | 4.87 (1.27) | 5.35 (1.25) | < 0.001 |
| Apo AI (g/L) | |||
| Baseline | 1.24 (0.18) | 1.26 (0.277) | 0.277 |
| Final | 1.33 (0.22) | 1.29 (0.20) | 0.02 |
*p-values for Student’s t test and for covariance analysis to compare treatment groups at baseline and at the end of the study (last available value on treatment)
Co-administration with Ezetimibe
In a multicenter double-blind, placebo-controlled, clinical study in patients with mixed hyperlipidemia, 625 patients were treated for up to 12 weeks and 576 for up to 1 year. Patients with an LDL-C ≥ 3.4mmol/L [130 mg/dL] and ≤ 5.7 mmol/L [220 mg/dL] (for non-diabetics) or ≥ 2.6 mmol/L [100 mg/dL] and ≤ 4.7 mmol/L [180 mg/dL] (for diabetics), and with TG ≥ 2.3 mmol/L [200 mg/dL] and≤ 5.7 mmol/L [500 mg/dL] were randomized to receive placebo, ezetimibe alone, 160 mg fenofibrate alone, or ezetimibe and 160 mg fenofibrate. In general, the groups were balanced with regard to body weight, sex, age, race and baseline lipids; at entry into the study the mean LDL-C was 4.2 mmol/L [161 mg/dL] while the mean age was 54 years and 56% were male.
Ezetimibe co-administration with fenofibrate significantly lowered total-C, LDL-C, Apo B, and non-HDL-C compared to fenofibrate or ezetimibe administration alone. The percent decrease in TG and percent increase in HDL-C for ezetimibe co-administered with fenofibrate were comparable to those for fenofibrate administered alone (see Table 8 below).
Table 8 – Response to ezetimibe and fenofibrate initiated concurrently in patients with mixed hyperlipidemia (Meana % change from untreated baselineb at 12 weeks)
Treatment (Daily Dose) | N | Total-C | LDL-C | Apo B | TGa | HDL-C | Non- HDL-C |
| Placebo | 63 | 0 | 0 | -1 | -9 | 3 | 0 |
| Ezetimibe | 185 | -12 | -13 | -11 | -11 | 4 | -15 |
| Fenofibrate 160 mg | 188 | -11 | -6 | -15 | -43 | 19 | -16 |
| Ezetimibe + Fenofibrate 160 mg | 183 | -22 | -20 | -26 | -44 | 19 | -30 |
aFor triglycerides, median % change from baseline
bBaseline- on no lipid-lowering drug
Improvements in lipid endpoints after 1 year of treatment were consistent with the 12-week data displayed above.
14.2. Comparative Bioavailability Studies
In a single-dose three-way randomized crossover bioavailability study in 72 healthy male and female volunteers, under low fat fed conditions, one 145 mg LIPIDIL EZ or three 48 mg LIPIDIL EZ tablets were compared to one 200 mg micronized capsule (LIPIDIL Micro 200 mg). Each subject received a single oral dose of each formulation with a low fat breakfast (30% fat, approx. 400 Kcal), with a two-week interval between doses.
Table 9 – Summary Table of the Comparative Bioavailability Data:
A Single Dose Study (LIPIDIL EZ 145 mg tablet vs. LIPIDIL Micro 200 mg capsule)
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test: LIPIDIL EZ 145 mg | Reference: LIPIDIL Micro 200 mg | % Ratio of geometric means | 90% Confidence Interval |
AUCT (μg.h/mL) | 148.47 153.5 (27%) | 170.49 174.2 (25%) | 87.1% | 85.2-89.0% |
AUCI (μg.h/mL) | 151.69 157.4 (28%) | 176.03 180.4 (27%) | 86.2% | 84.3-88.1% |
CMAX (μg/mL) | 8.646 8.80 (19%) | 8.582 8.87 (26%) | 100.8% | 96.8-104.9% |
TMAX* (h) | 3.5 (35%) | 4.4 (38%) | ||
T½* (h) | 20.7 (24%) | 22.0 (34%) | ||
* Expressed as the arithmetic mean (CV %) only.
Table 10 – Summary Table of the Comparative Bioavailability Data:
A Single Dose Study (LIPIDIL EZ 3 x 48 mg tablet vs. LIPIDIL Micro 200 mg capsule)
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test: LIPIDIL EZ 3 x 48 mg | Reference: LIPIDIL Micro 200 mg | % Ratio of geometric means | 90% Confidence Interval |
| Parameter | Test: LIPIDIL EZ 3 x 48 mg | Reference: LIPIDIL Micro 200 mg | % Ratio of geometric means | 90% Confidence Interval |
| AUCT | 148.29 | 170.49 | 87.0% | 85.1-88.9% |
| (μg.h/mL) | 153.3 (27%) | 174.2 (25%) | ||
AUCI (μg.h/mL) | 151.34 157.0 (29%) | 176.03 180.4 (27%) | 86.0% | 84.3-88.1% |
CMAX (μg/mL) | 8.399 8.54 (19%) | 8.582 8.87 (26%) | 97.9% | 94.0-101.9% |
TMAX* (h) | 3.6 (35%) | 4.4 (38%) | ||
T½* (h) | 20.1 (23%) | 22.0 (34%) | ||
* Expressed as the arithmetic mean (CV %) only.
These data demonstrate that comparable bioavailability was achieved between LIPIDIL EZ, 145 mg or 3x48 mg tablets, and LIPIDIL Micro 200 mg capsules.
In a single-dose two-way randomized crossover bioavailability study in 40 healthy male volunteers, under low fat fed conditions, one 145 mg LIPIDIL EZ tablet was compared to one 160 mg LIPIDIL Supra tablet. Each subject received a single oral dose of each formulation with a low fat breakfast (30% fat, approx. 400 Kcal), with a two-week interval between doses.
Table 11 – Summary Table of the Comparative Bioavailability Data:
A Single Dose Study (LIPIDIL EZ 145 mg tablet vs. LIPIDIL Supra 160 mg tablet)
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test: LIPIDIL EZ 145 mg tablet | Reference: LIPIDIL Supra 160 mg tablet | % Ratio of geometric means | 90% Confidence Interval |
| Parameter | Test: LIPIDIL EZ 145 mg tablet | Reference: LIPIDIL Supra 160 mg tablet | % Ratio of geometric means | 90% Confidence Interval |
AUCT (μg.h/mL) | 103.52 107.99 (29%) | 103.93 108.96 (29%) | 99.6% | 96.2-103.1% |
AUCI (μg.h/mL) | 105.00 109.53 (29%) | 105.80 110.86 (29%) | 99.2% | 96.0-102.6% |
CMAX (μg/mL) | 8.02 8.14 (17%) | 6.73 6.91 (23%) | 119.2% | 111.5-127.4% |
| TMAX* | 2.88 (42%) | 3.72 (31%) | ||
| (h) | ||||
T½* (h) | 17.15 (20%) | 18.74 (20%) | ||
* Expressed as the arithmetic mean (CV %) only.
These data demonstrate that comparable bioavailability was achieved between, 145 mg LIPIDIL EZ tablets and LIPIDIL SUPRA 160 mg tablets.
A study to examine the effect of food on the absorption of nanocrystallized fenofibrate was performed as a single-dose three-way randomized cross-over bioavailability study in 45 healthy male and female volunteers. Each subject received a single dose of 145 mg LIPIDIL EZ with either a high fat breakfast [50% fat, approx. 1000 Kcal, High Fat Fed (HFF)], a low fat breakfast [30% fat, approx. 400 Kcal; Low Fat Fed (LFF)] or no breakfast (fasted state), with a two-week interval between study arms.
Table 12 – Summary Table of the Comparative Bioavailability Data:
A Single Dose Study (LIPIDIL EZ 145 mg tablets (High Fat Fed vs. Fasted Conditions)
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test: 145 mg high fat fed | Reference: 145 mg fasted | % Ratio of geometric means | 90% Confidence Interval |
AUCT (μg.h/mL) | 123.0 127.9 (27.7%) | 116.5 121.6 (28.1%) | 105.4% | 102.0-109.0% |
AUCI (μg.h/mL) | 124.8 129.9 (28.0%) | 118.5 123.8 (28.8%) | 105.2% | 101.8-108.8% |
CMAX (μg/mL) | 7.82 7.96 (18.5) | 7.77 7.94 (20.1%) | 100.7% | 96.3-105.4% |
TMAX* (h) | 4.27 (45.5%) | 2.33 (31.4%) | ||
T½* (h) | 17.8 (23.3%) | 18.9 (24.9%) | ||
* Expressed as the arithmetic mean (CV %) only.
Table 13 – Summary Table of the Comparative Bioavailability Data:
A Single Dose Study (LIPIDIL EZ 145 mg tablets (Low Fat Fed vs. Fasted Conditions)
Analyte: Fenofibric Acid From measured and log transformed data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test: 145 mg low fat fed | Reference: 145 mg fasted | % Ratio of geometric means | 90% Confidence Interval |
AUCT (μg.h/mL) | 118.1 123.2 (28.4%) | 116.5 121.6 (28.1%) | 101.3% | 98.1-104.7% |
AUCI (μg.h/mL) | 119.8 125.1 (28.7%) | 118.5 123.8 (28.8%) | 101.2% | 97.8-104.6% |
CMAX (μg/mL) | 7.84 7.96 (17.9%) | 7.77 7.94 (20.1%) | 100.9% | 96.4-105.5% |
TMAX* (h) | 3.56 (33.1%) | 2.33 (31.4%) | ||
T½* (h) | 18.7 (19.5%) | 18.9 (24.9%) | ||
* Expressed as the arithmetic mean (CV %) only.
These data demonstrate that LIPIDIL EZ can be administered with or without food, as there was no effect of food on the bioavailability of the nanocrystallized fenofibrate tablets when compared to the bioavailability under the fasted state.
16. Non-Clinical Toxicology
All toxicology studies were performed using fenofibrate, non-micronized formulation.
General toxicology
Acute toxicity
Results from studies in mice, rats, hamsters and dogs indicate a low toxicity for fenofibrate with the highest administered doses (3200 to 24000 mg/kg), resulting in no deaths over the 7-day observation period. Autopsy findings were negative.
Chronic toxicity studies
Rats with normal or high cholesterol diet were treated for 7 days by gavage with fenofibrate at 0, 3, 10, 30, 100 and 300 mg/kg/day or clofibrate at 20, 60, 200 and 600 mg/kg/day. AST levels were raised in treated rats but ALT levels remained within the normal range for rats on normal diet and were only slightly elevated in rats on the high cholesterol diet. Dose-related hepatomegaly and proliferation of peroxisomes occurred, at doses above 30 mg/kg/day. In a second but similar study of drug metabolising enzymes, rats were treated daily by gavage for 7 days with fenofibrate at 0 or 100 mg/kg or clofibrate 200 mg/kg. The absence of significant change in the parameters measured suggests that the mechanisms resulting in hepatomegaly caused by both fibrates had little effect on cell organelles involved in drug metabolism and protein synthesis. In a third study in rats, oral doses of fenofibrate (0 to 1000 mg/kg) were given for 3 months. Depression of blood lipids was seen at all dose levels. AST and ALT values were increased at 500 and 1000 mg/kg. Hepatomegaly was a consistent finding at all dose-levels reaching a maximum of 78 % increase in weight compared to controls but appeared to regress rapidly. There were no other significant findings in the histological examination.
In a three-month oral nonclinical study in the rat species with fenofibric acid, the active metabolite of fenofibrate, toxicity for the skeletal muscles (particularly those rich in type I -slow oxidative- myofibres) and cardiac degeneration, anemia and decreased body weight were seen at exposure levels ≥50- fold the human exposure for the skeletal toxicity and >15 fold for the cardiomyotoxicity. Reversible ulcers and erosions in the gastro-intestinal tract occurred in dogs treated during 3 months at exposures approximately 7-fold the clinical AUC.
A 7-month study in dogs with 50 and 100 mg/kg/day and a 24-month study with 25 mg/kg/day were carried out. None of the dogs died but there was substantial weight loss associated with cholelithiasis and some interstitial nephritis. No important changes were observed in the biological parameters. Livers were apparently normal.
Fenofibrate (0, 12, 50 or 500 mg/kg/day) or clofibrate (200 mg/kg/day) was administered in the food of Rhesus monkeys for 12 months. No fenofibrate-related effect with regard to toxicity was noted in any of the test groups during the study. No evidence of compound-related histomorphologic alterations was present in the animals sacrificed. The Rhesus monkey resembles man where biopsy studies show no signs of peroxisome proliferation during up to 2 years of fenofibrate treatment.
Genotoxicity
Gene mutations: In vitro tests for mutagenicity with either fenofibrate or fenofibric acid in the presence or absence of activating rat or human microsomal enzyme preparations, have all given negative results. Thus, fenofibric acid was without effect on gene mutation frequency in bacteria (Ames), yeast and mouse lymphoma cells in culture.
In a second mouse lymphoma cell comparative study, there was no response to clofibric acid while some increased response to fenofibric acid at the highest concentration used was discounted due to poor relative growth. Similar activity was seen with gemfibrozil at toxic concentrations in the absence of metabolic activation. In conclusion, all three fibrates were found to be non-mutagenic on the protocol criteria, both in the absence and presence of metabolic activation.
Chromosome aberrations: Some trace of increased but not significant incidence of aberrations was seen in an in vitro mouse lymphoma cell multiple end point assay.
Chromosome aberrations as such were not seen in a more recent comparative in vitro study with CHO cells when testing clofibric acid and gemfibrozil as well as fenofibric acid. However, clofibric acid did have a marginal effect in increasing sister chromatid exchange frequency.
The absence of excision repair in human originated HeLa cells incubated with a wide range of concentrations of fenofibric acid with or without S9 reaffirmed the essentially non-genotoxic nature of the product.
Direct effects on DNA: The ability to bind covalently to target organ DNA is a property common to chemical substances which act by direct initiation of the carcinogenic process at the nuclear level. This type of genotoxic activity can be studied in vivo by DNA assay in rodents treated with the radiolabeled drug.
Although binding of fenofibric and clofibric acids to proteins was readily observed, no binding to DNA was demonstrated after oral administration of C14-labeled fenofibric or clofibric acid. The data therefore exclude somatic mutations as responsible for the known hepatocarcinogenic activity of these fibrates in rodents.
In a second in vivo test the effects of fenofibric acid were compared with those of clofibric acid and gemfibrozil on DNA synthesis in mouse testicular tissue, as measured by the incorpor¬ation of 3H thymidine. Any response is representative of changes in DNA synthesis in any testicular cells such as germ, Sertoli, Leydig or interstitial cells undergoing scheduled or unscheduled synthesis.
Both fenofibric acid and gemfibrozil caused modest increases in thymidine incorporation above control values. Clofibrate caused some inhibition of the incorporation of thymidine into DNA at the two lowest doses with a small increase at the highest. No positive control substance was used but it would be assumed that, for example, genotoxic alkylating agents might cause a decrease in incorporation due to an inhibition of DNA synthesis. Such inhibition or cell cycle delay is well known for such agents.
The increase in DNA synthesis as observed in mouse testicular tissue with fenofibric acid and gemfibrozil is difficult to evaluate in the absence of a positive control or historical data for this recently developed test, nevertheless such an effect might be anticipated of such agents which are known to cause peroxisome proliferation and which produce increased cell turnover. The occurrence of increased cell turnover would be in keeping with a non-genotoxic but promoting mode of such compounds in mice.
In a rat primary hepatocyte unscheduled DNA synthesis (UDS) assay in vitro, gemfibrozil, clofibric acid and fenofibric acid showed a negative response. None caused nuclear labeling significantly different from the control and no dose-related trends were evident.
Cell growth or malignant transformation in vitro: fenofibric acid was without effect on growth or malignant transformation of cultured mammalian cell lines.
Carcinogenicity
Five rodent studies have shown that target organs for tumorigenic effects of fenofibrate are liver, pancreas and testes.
Mice showed increased liver weight with intrahepatic cholestasis and some degenerative changes but not liver tumors with 50 mg/kg/day for 22 months.
Dose-related increases in liver and kidney weight were seen in mice treated with 10 to 200 mg/kg/day of fenofibrate for 80 weeks.
When given at a dose of 200 mg/kg/day, both fenofibrate and clofibrate produced gross hepatomegaly associated with cholestasis and occasional cholangitis and periportal fibrosis. Neoplastic lesions were confined to the liver with significant increases in hepatocellular carcinoma at the high dose of fenofibrate in both sexes. Hepatocellular adenomas were also increased in males. In clofibrate-treated mice there was an excess of hepatic adenomas in females but not in males.
Both fenofibrate and clofibrate were found to be associated with an increased incidence of hepatocellular hypertrophy, lobular dysplasia and Kupffer cell pigmentation in another long-term toxicity study (93 weeks) on mice. In both sexes the incidence of total hepatic neoplasms and carcinomas was significantly increased by the high dose of fenofibrate (200 mg/kg). At the intermediate dose (60 mg/kg) the combined tumor incidence was almost significant in males but not in females, while incidence of carcinomas was not significantly increased in males and absent in females. Also, clofibrate (400 mg/kg) significantly increased the total tumor incidence but not carcinomas in males; females were unaffected.
Rats, which received fenofibrate (0, 10, 45 or 200 mg/kg/day) or clofibrate (200 mg/kg/day) mixed with their diet for a 2-year period showed no significant differences in mortality over the study period. Significant increases in incidences of hepatocellular carcinoma were found in the high dose fenofibrate group of animals of both sexes, in mid-dose fenofibrate males, and in clofibrate treated males. Mid-dose fenofibrate males and clofibrate-treated males and females also showed significantly increased incidence of hepatocellular adenomas. Well-differentiated pancreatic acinar cell carcinomas and adenomas were increased in a dose-related manner in the fenofibrate treated males, and higher incidences were also evident in the clofibrate males.
The chronic toxicity and carcinogenicity of fenofibrate was further studied in rats (0, 10 and 60 mg/kg/day) in order to compare treatment-related responses with those produced by clofibrate (400 mg/kg/day) and gemfibrozil (250 mg/kg/day) during 117 weeks of treatments. The absolute and relative weights of the liver were increased in all treatment groups except with 10 mg/kg fenofibrate. Although comparatively low, an incidence of hepatocellular carcinoma was observed in gemfibrozil-treated rats, and neoplastic nodules were also found in the livers of 50 % of the males, which survived up to the termination of the study. Fewer neoplastic nodules were seen in the clofibrate-treated rats but these animals had a high incidence of hepatocellular carcinoma at termination. A significantly increased incidence of pancreatic acinar cell adenoma was seen in the 60 mg/kg fenofibrate males, while this increase in females was not significant. A significant increase in acinar adenoma and a slight increase in acinar carcinoma occurred with clofibrate (400 mg/kg) and some adenomas were seen in gemfibrozil-treated rats. There was some excess of benign interstitial cell tumors of the testes in all treatment groups except the group that received 10 mg/kg of fenofibrate.
Reproductive and developmental toxicology
There was no evidence of any increase in malformation frequency in mice, rabbits and rats after administration of fenofibrate compared to that seen in controls. Examination of offspring from fenofibrate-treated dams and those having received clofibrate did not disclose any significant abnormalities when compared to offspring from the controls.
With the highest dose levels at which the mothers were adversely affected, there was evidence of embryotoxicity in rats and rabbits.