


Product Monograph - M-Rizatriptan ODT
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
|---|---|---|
| Oral | orally disintegrating tablet 5 mg, 10 mg | Mannitol, Calcium Silicate, Crospovidone, Aspartame, Colloidal Silicon Dioxide, Sodium Stearyl Fumarate, and Peppermint Flavor. Peppermint flavor includes maltodextrin and cornstarch. |
INDICATIONS AND CLINICAL USE
Adults
M-RIZATRIPTAN ODT (rizatriptan benzoate) is indicated for:
- acute treatment of migraine attacks with or without aura in adults
M-RIZATRIPTAN ODT is not intended for the prophylactic therapy of migraine or for use in the management of hemiplegic, ophthalmoplegic or basilar migraine (see CONTRAINDICATIONS). Safety and effectiveness of rizatriptan benzoate have not been established for cluster headache, which is present in an older, predominantly male population.
Pediatrics (<18 years of age)
The safety and efficacy of rizatriptan benzoate have not been established in patients under 18 years of age and its use in this age group is not recommended (see WARNINGS AND PRECAUTIONS, Special Populations and Conditions).
Geriatrics (>65 years of age)
The safety and effectiveness of rizatriptan benzoate have not been adequately studied in individuals over 65 years of age. Its use in this age group is, therefore, not recommended (see WARNINGS AND PRECAUTIONS).
CONTRAINDICATIONS
M-RIZATRIPTAN ODT is contraindicated in patients with history, symptoms, or signs of ischemic cardiac, cerebrovascular or peripheral vascular syndromes, valvular heart disease or cardiac arrhythmias (especially tachycardias). In addition, patients with other significant underlying cardiovascular diseases (e.g., atherosclerotic disease, congenital heart disease)
should not receive M-RIZATRIPTAN ODT. Ischemic cardiac syndromes include, but are not restricted to, angina pectoris of any type (e.g., stable angina of effort and vasospastic forms of angina such as the Prinzmetal’s variant), all forms of myocardial infarction, and silent myocardial ischemia.
Cerebrovascular syndromes include, but are not limited to, strokes of any type as well as transient ischemic attacks (TIAs). Peripheral vascular disease includes, but is not limited to, ischemic bowel disease, or Raynaud’s syndrome (see WARNINGS AND PRECAUTIONS).
Because M-RIZATRIPTAN ODT may increase blood pressure, it is contraindicated in patients with uncontrolled or severe hypertension (see WARNINGS AND PRECAUTIONS).
M-RIZATRIPTAN ODT is contraindicated within 24 hours of treatment with another 5-HT1 agonist, or an ergotamine-containing or ergot-type medication like dihydroergotamine or methysergide.
M-RIZATRIPTAN ODT is contraindicated in patients with hemiplegic, ophthalmoplegic or basilar migraine.
Concurrent administration of MAO inhibitors or use of rizatriptan within 2 weeks of discontinuation of MAO inhibitor therapy is contraindicated (see DRUG INTERACTIONS).
Because there is no data available, M-RIZATRIPTAN ODT is contraindicated in patients with severe hepatic impairment.
M-RIZATRIPTAN ODT is contraindicated in patients who are hypersensitive to rizatriptan or any component of the formulation.
WARNINGS AND PRECAUTIONS
General
M-RIZATRIPTAN ODT should only be used where a clear diagnosis of migraine has been established.
For a given attack, if a patient has no response to the first dose of rizatriptan, the diagnosis of migraine should be reconsidered before administration of a second dose.
Psychomotor Effect
Dizziness, somnolence and asthenia/fatigue were experienced by some patients in clinical trials with rizatriptan benzoate (see ADVERSE REACTIONS). Patients should be advised to avoid driving a car or operating hazardous machinery until they are reasonably certain that M-RIZATRIPTAN ODT does not adversely affect them.
Cardiovascular
Risk of Myocardial Ischemia and/or Infarction and Other Adverse Cardiac Events. Rizatriptan benzoate has been associated with transient chest and/or neck pain and tightness which may resemble angina pectoris. Following the use of other 5-HT1 agonists, in rare cases these symptoms have been identified as being the likely result of coronary vasospasm or myocardial ischemia. Rare cases of serious coronary events or arrhythmia have occurred following use of other 5-HT1 agonists and may therefore also occur with rizatriptan benzoate. Because of the potential of this class of compounds (5-HT1B/1D agonists) to cause coronary vasospasm, M-RIZATRIPTAN ODT should not be given to patients with documented ischemic or vasospastic coronary artery disease (see CONTRAINDICATIONS). It is strongly recommended that M-RIZATRIPTAN ODT not be given to patients in whom unrecognized coronary artery disease (CAD) is predicted by the presence of risk factors (e.g., hypertension, hypercholesterolemia, smoker, obesity, diabetes, strong family history of CAD, female with surgical or physiological menopause, or male over 40 years of age) unless a cardiovascular evaluation provides satisfactory clinical evidence that the patient is reasonably free of coronary artery and ischemic myocardial disease or other significant underlying cardiovascular disease. The sensitivity of cardiac diagnostic procedures to detect cardiovascular disease or predisposition to coronary artery vasospasm is unknown. If, during the cardiovascular evaluation, the patient’s medical history, electrocardiographic or other investigations reveal findings indicative of, or consistent with, coronary artery vasospasm or myocardial ischemia, M-RIZATRIPTAN ODT should not be administered (see CONTRAINDICATIONS).
For patients with risk factors predictive of CAD, who are considered to have a satisfactory cardiovascular evaluation, the first dose of rizatriptan should be administered in the setting of a physician’s office or similar medically staffed and equipped facility. Because cardiac ischemia can occur in the absence of clinical symptoms, consideration should be given to obtaining on the first occasion of use an electrocardiogram (ECG) during the interval immediately following M-RIZATRIPTAN ODT, in these patients with risk factors. However, an absence of drug-induced cardiovascular effects on the occasion of the initial dose does not preclude the possibility of such effects occurring with subsequent administrations.
Intermittent long-term users of M-RIZATRIPTAN ODT who have or acquire risk factors predictive of CAD, as described above, should receive periodic interval cardiovascular evaluation as they continue to use M-RIZATRIPTAN ODT.
If symptoms consistent with angina occur after the use of M-RIZATRIPTAN ODT, ECG evaluation should be carried out to look for ischemic changes.
The systematic approach described above is intended to reduce the likelihood that patients with unrecognized cardiovascular disease will be inadvertently exposed to M-RIZATRIPTAN ODT.
Discomfort in the chest, neck, throat and jaw (including pain, pressure, heaviness and tightness) has been reported after administration of rizatriptan. Because drugs in this class may cause coronary artery vasospasm, patients who experience signs or symptoms suggestive of angina following dosing should be evaluated for the presence of CAD or a predisposition to
Prinzmetal’s variant angina before receiving additional doses of medication and should be monitored electrocardiographically if dosing is resumed and similar symptoms recur. Similarly, patients who experience other symptoms or signs suggestive of decreased arterial flow, such as ischemic bowel syndrome or Raynaud’s syndrome following M-RIZATRIPTAN ODT administration should be evaluated for atherosclerosis or predisposition to vasospasm (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Cardiac Events and Fatalities Associated with 5-HT1 Agonists
M-RIZATRIPTAN ODT may cause coronary artery vasospasm. Serious adverse cardiac events, including acute myocardial infarction, life-threatening disturbances of cardiac rhythm, and death have been reported within a few hours following the administration of 5-HT1 agonists. Considering the extent of use of 5-HT1 agonists in patients with migraine, the incidence of these events is extremely low.
Premarketing Experience with Rizatriptan Benzoate
Among the approximately 4200 patients who were treated with at least a single oral dose of either 5 or 10 mg rizatriptan in premarketing clinical trials of rizatriptan benzoate, electrocardiac adverse experiences were observed in 33 patients. One patient was reported to have chest pain with possible ischemic ECG changes following a single dose of 10 mg.
Post marketing Experience with Rizatriptan Benzoate
Serious cardiovascular events have been reported in association with the use of rizatriptan benzoate. The uncontrolled nature of post marketing surveillance, however, makes it impossible to determine definitively the proportion of reported cases that were actually caused by rizatriptan benzoate or to reliably assess causation in individual cases.
Cerebrovascular Events and Fatalities Associated with 5-HT1 Agonists
Cerebral hemorrhage, subarachnoid hemorrhage, stroke, and other cerebrovascular events have been reported in patients treated with 5-HT1 agonists; and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the agonist having been administered in the incorrect belief that the symptoms experienced were a consequence of migraine, when they were not. Before treating migraine headaches with M-RIZATRIPTAN ODT in patients not previously diagnosed as migraineurs, and in migraineurs who present with atypical symptoms, care should be taken to exclude other potentially serious neurological conditions. If a patient does not respond to the first dose, the opportunity should be taken to review the diagnosis before a second dose is given. It should be noted that patients with migraine may be at increased risk of certain cerebrovascular events (e.g., stroke, hemorrhage, transient ischemic attack).
Special Cardiovascular Pharmacology Studies with Another 5-HT1 Agonist
In subjects (n=10) with suspected coronary artery disease undergoing angiography, a 5-HT1 agonist at a subcutaneous dose of 1.5 mg produced an 8% increase in aortic blood pressure, an 18% increase in pulmonary artery blood pressure, and an 8% increase in systemic vascular resistance. In addition, mild chest pain or tightness was reported by four subjects. Clinically significant increases in blood pressure were experienced by three of the subjects (two of whom also had chest pain/discomfort). Diagnostic angiogram results revealed that 9 subjects had normal coronary arteries and one had insignificant coronary artery disease.
In an additional study with this same drug, migraine patients (n=35) free of cardiovascular disease were subjected to assessments of myocardial perfusion by positron emission tomography while receiving a subcutaneous 1.5 mg dose in the absence of a migraine attack. Reduced coronary vasodilatory reserve (~10%), increased coronary resistance (~20%), and decreased hyperemic myocardial blood flow (~10%) were noted. The relevance of these findings to the use of the recommended oral dose of this 5-HT1 agonist is not known.
Similar studies have not been done with rizatriptan benzoate. However, owing to the common pharmacodynamic actions of 5-HT1 agonists, the possibility of cardiovascular effects of the nature described above should be considered for any agent of this pharmacological class.
Other Vasospasm-Related Events
5-HT1 agonists may cause vasospastic reactions other than coronary artery vasospasm. Extensive post-market experience has shown the use of another 5-HT1 agonist to be associated with rare occurrences of peripheral vascular ischemia and colonic ischemia with abdominal pain and bloody diarrhea.
Increase in Blood Pressure
Significant elevation in blood pressure, including hypertensive crisis, has been reported on rare occasions in patients receiving 5-HT1 agonists with and without a history of hypertension. In healthy young male and female subjects who received maximal doses of rizatriptan benzoate (10 mg every 2 hours for 3 doses), slight increases in blood pressure (approximately 2-3 mmHg) were observed. Rizatriptan is contraindicated in patients with uncontrolled or severe hypertension (see CONTRAINDICATIONS). In patients with controlled hypertension, rizatriptan benzoate should be administered with caution, as transient increases in blood pressure and peripheral vascular resistance have been observed in a small portion of patients.
Endocrine and Metabolism
Phenylketonurics
Phenylketonuric patients should be informed that M-RIZATRIPTAN ODT contains aspartame, a source of phenylalanine. Each 5 mg orally disintegrating tablet contains the equivalent of 0.56 mg phenylalanine, and each 10 mg orally disintegrating tablet contains the equivalent of 1.12 mg phenylalanine.
Hepatic/Biliary/Pancreatic
Rizatriptan should be used with caution in patients with moderate hepatic insufficiency due to an increase in plasma concentrations of approximately 30% (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions and DOSAGE AND ADMINISTRATION). Since there is no data in patients with severe hepatic impairment, rizatriptan is contraindicated in this population (see CONTRAINDICATIONS and DOSAGE AND ADMINISTRATION).
Immune
Rare hypersensitivity (anaphylaxis/anaphylactoid) reactions may occur in patients receiving 5-HT1 agonists such as rizatriptan benzoate. Such reactions can be life threatening or fatal. In general, hypersensitivity reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens. Owing to the possibility of cross-reactive hypersensitivity reactions, M-RIZATRIPTAN ODT should not be used in patients having a history of hypersensitivity to chemically-related 5-HT1 receptor agonists.
Neurologic
Care should be taken to exclude other potentially serious neurologic conditions before treating headache in patients not previously diagnosed with migraine or who experience a headache that is atypical for them. There have been rare reports where patients received 5-HT1 agonists for severe headache that were subsequently shown to have been secondary to an evolving neurological lesion. For newly diagnosed patients or patients presenting with atypical symptoms, the diagnosis of migraine should be reconsidered if no response is seen after the first dose of M-RIZATRIPTAN ODT.
Seizures
Caution should be observed if M-RIZATRIPTAN ODT is to be used in patients with a history of epilepsy or structural brain lesions which lower the convulsion threshold. There have been very rare reports of seizures following administration of rizatriptan benzoate in patients with or without risk factors or previous history of seizures (see ADVERSE REACTIONS, Post-Marketing Adverse Reactions, Nervous System).
Ophthalmologic
Binding to Melanin-Containing Tissues
The propensity for rizatriptan to bind melanin has not been investigated. Based on its chemical properties, rizatriptan may bind to melanin and accumulate in melanin-rich tissue (e.g., eye) over time. This raises the possibility that rizatriptan could cause toxicity in these tissues after extended use. There were, however, no adverse ophthalmologic changes related to treatment with rizatriptan in the one-year dog toxicity study. Although no systematic monitoring of ophthalmologic function was undertaken in clinical trials, and no specific recommendations for ophthalmologic monitoring are offered, prescribers should be aware of the possibility of long-term ophthalmologic effects.
Renal
Rizatriptan should be used with caution in dialysis patients due to a decrease in the clearance of rizatriptan, resulting in approximately 44% increase in plasma concentrations (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions and DOSAGE AND ADMINISTRATION).
Selective Serotonin Reuptake Inhibitors/Serotonin Norepinephrine Reuptake Inhibitors and Serotonin Syndrome
Cases of life-threatening serotonin syndrome have been reported during combined use of selective serotonin reuptake inhibitors (SSRIs)/serotonin norepinephrine reuptake inhibitors
(SNRIs) and triptans. If concomitant treatment with M-RIZATRIPTAN ODT and SSRIs (e.g., sertraline, escitalopram oxalate, and fluoxetine) or SNRIs (e.g., venlafaxine, duloxetine) is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. Serotonin syndrome symptoms may include mental status changes (e.g., agitation, hallucinations, coma), autonomic instability (e.g., tachycardia, labile blood pressure, hyperthermia), neuromuscular aberrations (e.g., hyperreflexia, incoordination) and/or gastrointestinal symptoms (e.g., nausea, vomiting, diarrhea) (see DRUG INTERACTIONS).
Medication Overuse Headache: Overuse of acute migraine treatments has been associated with the exacerbation of headache (medication overuse headache) in susceptible patients. Medication overuse headache may present as migraine-like daily headaches or as a marked increase in frequency of migraine attacks. Detoxification of patients, including withdrawal of the overused drugs, and treatment of withdrawal symptoms (which often includes a transient worsening of headache) may be necessary.
Special Populations and Conditions
Pregnant Women: In a reproduction study in rats, birth weights and pre- and post-weaning weight gain were reduced in the offspring of females treated prior to and during mating and throughout gestation and lactation. These effects occurred in the absence of any apparent maternal toxicity (maternal plasma drug exposures were 22 and 337 times, respectively, the exposure in humans receiving the maximum recommended daily dose (MRDD) of 20 mg). The developmental no-effect dose was equivalent to 2.25 times human exposure at the MRDD.
In embryofetal development studies, no teratogenic effects were observed when pregnant rats and rabbits were administered doses at the equivalent of 337 times and 168 times, respectively, the human MRDD, during organogenesis. However, fetal weights were decreased in conjunction with decreased maternal weight gain at these same doses. The developmental no-effect dose in both rats and rabbits was 22 times the human MRDD. Toxicokinetic studies demonstrated placental transfer of drug in both species.
There are no adequate and well-controlled studies in pregnant women; therefore, rizatriptan should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Impairment of Fertility
In a fertility study in rats, altered estrus cyclicity and delays in time to mating were observed in females treated orally with an equivalent of 337 times the maximum recommended daily dose (MRDD) of 20 mg in humans. The no-effect dose was 22 times the MRDD. There was no impairment of fertility or reproductive performance in male rats treated with up to 825 times the MRDD.
Nursing Women: It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when M-RIZATRIPTAN ODT is administered to women who are breast-feeding. Rizatriptan is extensively excreted in rat milk, at a level of 5-fold or greater than maternal plasma levels.
Pediatrics (<18 years of age): The safety and efficacy of rizatriptan benzoate have not been established in patients under 18 years of age and its use in this age group is not recommended (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Geriatrics (>65 years of age): The safety and effectiveness of rizatriptan benzoate has not been adequately studied in individuals over 65 years of age. The risk of adverse reactions to this drug may be greater in elderly patients, as they are more likely to have decreased hepatic function, be at higher risk for CAD, and experience blood pressure increases that may be more pronounced. Clinical studies with rizatriptan benzoate did not include a substantial number of patients over 65 years of age (n=17). Its use in this age group is, therefore, not recommended.
Special Disease Conditions:
M-RIZATRIPTAN ODT should be administered with caution to patients with diseases that may alter the absorption, metabolism, or excretion of drugs (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Monitoring and Laboratory Tests
No specific laboratory tests are recommended for monitoring patients prior to and/or after treatment with M-RIZATRIPTAN ODT.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Serious cardiac events, including some that have been fatal, have occurred following use of 5-HT1 agonists. These events are extremely rare and most have been reported in patients with risk factors predictive of CAD. Events reported have included coronary artery vasospasm, transient myocardial ischemia, myocardial infarction, ventricular tachycardia, and ventricular fibrillation (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Experience in Controlled Clinical Trials with Rizatriptan Benzoate
Typical 5-HT1 Agonist Adverse Reactions
As with other 5-HT1 agonists, rizatriptan benzoate has been associated with sensations of heaviness, pressure, tightness or pain which may be intense. These may occur in any part of the body including the chest, throat, neck, jaw and upper limb.
Acute Safety
Adverse experiences to rizatriptan were assessed in controlled clinical trials that included over 3700 adult patients who received single or multiple doses of rizatriptan benzoate tablets. The most common adverse events during treatment with rizatriptan benzoate were asthenia/fatigue, somnolence, pain/pressure sensation and dizziness. These events appeared to be dose-related. In long-term extension studies where patients were allowed to treat multiple attacks for up to 1 year, 4% (59 out of 1525 patients) withdrew because of adverse experiences.
Table 1 and Table 2 list the adverse events regardless of drug relationship (incidence ≥ 1% and greater than placebo) after a single dose of rizatriptan benzoate tablets and wafers, respectively. Most of the adverse events appear to be dose-related. The events cited reflect experience gained under closely monitored conditions of clinical trials in a highly selected patient population. In actual clinical practice or in other clinical trials, these frequency estimates may not apply, as the conditions of use, reporting behavior, and the kinds of patients treated may differ.
Table 1
Incidence (≥1% and Greater than Placebo) of Adverse Experiences in Adults After a Single Dose of Rizatriptan benzoate tablets or Placebo (Prior to Subsequent Dose) in Phase III Controlled Clinical Trials†
| % of Patients | ||||||||
|---|---|---|---|---|---|---|---|---|
| Placebo | Rizatriptan benzoate tablets 5 mg | Rizatriptan benzoate tablets 10 mg | ||||||
| Number of Patients | 627 | 977 | 1167 | |||||
Symptoms of Potentially Cardiac Origin Upper Limb Sensations* Chest Sensations* Neck/Throat/Jaw Sensations* Palpitations Body as a Whole Asthenia/Fatigue Abdominal Pain Digestive System Nausea Dry Mouth Vomiting Nervous System Dizziness Somnolence | 1.3 1.0 0.6 0.2 2.1 1.0 3.5 1.3 2.1 4.5 3.5 | 1.7 1.6 1.4 0.9 4.2 1.7 4.1 2.6 1.6 4.2 4.2 | 1.8 3.1 2.5 1.0 6.9 2.2 5.7 3.0 2.3 8.9 8.4 | |||||
| % of Patients | ||||||||
|---|---|---|---|---|---|---|---|---|
| Placebo | Rizatriptan benzoate tablets 5 mg | Rizatriptan benzoate tablets 10 mg | ||||||
| Number of Patients | 627 | 977 | 1167 | |||||
Headache Paresthesia Tremor Insomnia Skin and Skin Appendage Flushing | 0.8 1.0 1.0 0.3 1.0 | 1.8 1.5 1.3 1.0 0.6 | 2.1 2.9 0.3 0.3 1.1 | |||||
* The term “sensations” encompasses adverse events described as pain, discomfort, pressure, heaviness, constriction, tightness, heat/burning sensation, paresthesia, numbness, tingling, weakness and strange sensations.
† Data from Studies 022, 025, 029 and 030.
Table 2
Incidence (≥1% and Greater than Placebo) of Adverse Experiences in Adults After a Single Dose of Rizatriptan benzoate wafers or Placebo (Prior to Subsequent Dose) in Phase III Controlled Clinical Trials†
| % of Patients | |||||||
|---|---|---|---|---|---|---|---|
| Placebo | Rizatriptan Benzoate wafers | ||||||
| 5 mg | 10 mg | ||||||
| Number of Patients | 283 | 282 | 302 | ||||
Symptoms of Potentially Cardiac Origin Chest Sensations* Neck/throat/Jaw Sensations* Tachycardia Upper Limb Sensations* Palpitations Body as a Whole Asthenia/Fatigue Digestive System Dry Mouth Nausea Dyspepsia Acid Regurgitation Salivation Increase Musculoskeletal System | 0.4 0.4 1.1 0.4 0.4 0.4 2.1 5.7 0.7 0 0 | 1.4 1.4 1.4 0.7 0.4 2.1 6.4 6.4 1.1 1.1 0 | 1.7 2.0 0.3 2.0 1.0 3.6 6.0 7.0 2.0 0.7 1.3 | ||||
| % of Patients | |||||||
|---|---|---|---|---|---|---|---|
| Placebo | Rizatriptan Benzoate wafers | ||||||
| 5 mg | 10 mg | ||||||
| Number of Patients | 283 | 282 | 302 | ||||
Regional Heaviness Nervous System Dizziness Somnolence Headache Insomnia Paresthesia Hypoesthesia Mental Acuity Decreased Tremor Nervousness Respiratory System Pharyngeal Discomfort Skin and Skin Appendage Sweating Special Senses Taste Perversion Blurred Vision | 0 3.9 2.8 0.7 0 0.4 0 0 0.7 0.4 0 0.7 1.1 0 | 0 6.4 4.3 1.8 1.4 1.4 1.4 1.1 1.1 1.1 1.1 1.1 1.4 0.4 | 1.0 8.6 5.3 2.0 0.7 3.0 0.7 0.3 0 0.7 0.7 1.0 2.3 1.3 | ||||
* The term “sensations” encompasses adverse events described as pain, discomfort, pressure, heaviness, constriction, tightness, heat/burning sensation, paresthesia, numbness, tingling, weakness and strange sensations.
† Data from Studies 039 and 049.
Rizatriptan benzoate was generally well-tolerated. Adverse experiences were typically mild in intensity and were transient. The frequencies of adverse experiences in clinical trials did not increase when up to three doses were taken within 24 hours. The incidences of adverse experiences were not affected by age, gender or use of prophylactic medications. There was insufficient data to assess the impact of race on the incidence of adverse events.
Long-Term Safety
In long-term extension studies, a total of 1854 patients treated 16,150 migraine attacks with rizatriptan benzoate 5 mg tablets and 24,043 attacks with rizatriptan benzoate 10 mg tablets over a period of up to 1 year. In general, the types of clinical adverse experiences observed in the extension studies were similar to those observed in the acute studies. However, the incidences of most clinical adverse events were approximately 3-fold higher in extension, as expected, based on increased observation time. The most common adverse events per attack (defined as occurring at an incidence of at least 1%) for rizatriptan benzoate 5 mg and 10 mg, respectively, were as follows: nausea (3%, 4%), dizziness (2%, 2%), somnolence (2%, 4%), asthenia/fatigue (2%, 2%), headache (1%, 2%), vomiting (1%, <1%), chest pain (<1%, 1%) and paresthesia (<1%, 2%). Due to the lack of placebo controls in the extension studies, the role of rizatriptan benzoate in causation cannot be reliably determined.
Other Events Observed in Association with the Administration of Rizatriptan Benzoate
In the section that follows, the frequencies of less commonly reported adverse clinical events are presented. Because the reports include events observed in open studies, the role of rizatriptan benzoate in their causation cannot be reliably determined. Furthermore, variability associated with adverse event reporting, the terminology used to describe adverse events, etc. limit the value of the quantitative frequency estimates provided. Event frequencies are calculated as the number of patients who used rizatriptan benzoate 5 mg and 10 mg tablets in Phase II and III studies (n=3716) and reported an event divided by the total number of patients exposed to rizatriptan benzoate. All reported events are included, except those already listed in the previous table, those too general to be informative, and those not reasonably associated with the use of the drug. Events are further classified within body system categories and enumerated in order of decreasing frequency using the following definitions: frequent adverse events are those defined as those occurring in at least 1/100 patients; infrequent adverse experiences are those occurring in 1/100 to 1/1000 patients; and rare adverse experiences are those occurring in fewer than 1/1000 patients.
Body as a Whole
Frequent were warm sensations, chest pain and chills/cold sensations. Infrequent were heat sensitivity, facial edema, hangover effect, abdominal distention, edema/swelling and malaise. Rare were fever, orthostatic effects, and syncope.
Cardiovascular
Frequent was palpitation. Infrequent were tachycardia, cold extremities, hypertension, arrhythmia, and bradycardia. Rare were angina pectoris and blood pressure increased.
Digestive
Frequent was diarrhea. Infrequent were dyspepsia, thirst, acid regurgitation, dysphagia, constipation, flatulence, and tongue edema. Rare were anorexia, appetite increase, gastritis, paralysis (tongue), eructation and glossodynia.
Metabolic
Infrequent was dehydration.
Musculoskeletal
Infrequent were muscle weakness, stiffness, myalgia, muscle cramp, musculoskeletal pain, and arthralgia.
Neurological/Psychiatric
Frequent were hypoesthesia and mental acuity decreased. Infrequent were nervousness, vertigo, insomnia, anxiety, depression, euphoria, disorientation, ataxia, dysarthria, confusion, dream abnormality, gait abnormality, irritability, memory impairment, agitation, hyperesthesia, sleep disorder, speech disorder, migraine and spasm. Rare were dysesthesia, depersonalization, akinesia/bradykinesia, apprehension, hyperkinesia, hypersomnia, and hyporeflexia.
Respiratory
Frequent were dyspnea and pharyngeal discomfort. Infrequent were pharyngitis, irritation (nasal), congestion (nasal), dry throat, upper respiratory infection, yawning, respiratory congestion, dry nose, epistaxis, and sinus disorder. Rare were cough, hiccups, hoarseness, rhinorrhea, sneezing, tachypnea, and pharyngeal edema.
Special Senses
Frequent was taste perversion. Infrequent were blurred vision, tinnitus, dry eyes, burning eye, eye pain, eye irritation, ear pain, and tearing. Rare were hyperacusis, smell perversion, photophobia, photopsia, itching eye, and eye swelling.
Skin and Skin Appendage
Infrequent were sweating, pruritus, rash, and urticaria. Rare were erythema, acne, and photosensitivity.
Urogenital System
Frequent was hot flashes. Infrequent were urinary frequency, polyuria, and menstruation disorder. Rare was dysuria.
The adverse experience profile seen with rizatriptan benzoate wafers was similar to that seen with rizatriptan benzoate tablets.
SPECIAL POPULATIONS
Pediatric Patients (6 to 17 years of Age)
The safety of rizatriptan benzoate wafers was evaluated in pediatric patients (6 to 17 years of age) in a placebo-controlled clinical trial, in which 462 patients treated a single migraine attack with rizatriptan.
Table 3 lists the adverse events for pediatric patients regardless of drug relationship (incidence ≥1% and greater than placebo) after a single dose of rizatriptan benzoate wafers.
Table 3
Incidence (≥1% and Greater than Placebo) of Adverse Experiences in Pediatric Patients 6 to 17 years of Age After a Single Dose of Rizatriptan Benzoate wafers or Placebo in Phase III Controlled Clinical Trials †
| % of Patients | |||||
|---|---|---|---|---|---|
| Placebo | Rizatriptan Benzoate wafers* | ||||
| Number of Patients | 515 | 462 | |||
| Gastrointestinal Disorders | |||||
| % of Patients | |||||||
|---|---|---|---|---|---|---|---|
| Placebo | Rizatriptan Benzoate wafers* | ||||||
| Nausea | 2.1 | 2.6 | |||||
| General Disorders and Administration Site Conditions | |||||||
| Asthenia | 0 | 1.1 | |||||
| Fatigue | 1.7 | 2.4 | |||||
| Nervous System Disorders | |||||||
| Somnolence | 2.5 | 2.8 | |||||
* Rizatriptan Benzoate wafers group refers to 5 or 10-mg dose.
† Data from Clinical Trial 082.
Other Events Observed in Association with the Administration of Rizatriptan Benzoate wafers in Pediatric Patients
Safety was evaluated in a 52-week, single-arm, open label trial for rizatriptan benzoate wafers, in which 606 pediatric patients 12 to 17 years of age (432 treated for at least 12 months) were allowed to treat up to eight attacks per month. The safety profile from this open label study was consistent with that observed in the controlled clinical trial (see Table 3). In this study, 151 patients (25%) took two 10-mg doses of rizatriptan benzoate wafers within a 24-hour period. Drug-related adverse experiences were reported for 3 of these patients and included abdominal discomfort, fatigue, and dyspnea. These were deemed by the investigators to be mild in intensity.
Post-Market Adverse Drug Reactions
The following additional adverse reactions have been reported very rarely and most have been reported in patients with risk factors predictive of CAD: Myocardial ischemia or infarction, cerebrovascular accident.
The following adverse reactions have also been reported:
Hypersensitivity: Hypersensitivity reaction, anaphylaxis/anaphylactoid reaction, angioedema (e.g., facial edema, tongue swelling, pharyngeal edema), wheezing, urticaria, rash, toxic epidermal necrolysis.
Nervous System: serotonin syndrome.
Seizures: There have been very rare reports of seizures following administration of rizatriptan benzoate in patients with or without risk factors or previous history of seizures (see WARNINGS AND PRECAUTIONS).
Musculoskeletal: facial pain.
Special Senses: Dysgeusia.
Vascular disorders: Peripheral vascular ischemia.
Gastrointestinal Disorders: Ischemic colitis.
Drug Abuse and Dependence:
Although the abuse potential of rizatriptan benzoate has not been specifically assessed, no abuse of, tolerance to, withdrawal from, or drug-seeking behavior was observed in patients who received rizatriptan benzoate in clinical trials or their extensions. The 5-HT1B/1D agonists, as a class, have not been associated with drug abuse.
DRUG INTERACTIONS
Drug-Drug Interactions
Ergot-Containing Drugs
Ergot-containing drugs have been reported to cause prolonged vasospastic reactions. Because there is a theoretical basis that these effects may be additive, use of ergotamine-containing or ergot-type medications (like dihydroergotamine or methysergide) and rizatriptan within 24 hours is contraindicated (see CONTRAINDICATIONS).
Monoamine Oxidase Inhibitors
Rizatriptan is principally metabolized via monoamine oxidase, ‘A’ subtype (MAO-A). In a drug interaction study, when rizatriptan benzoate tablets 10 mg was administered to subjects (n=12) receiving concomitant therapy with the selective, reversible MAO-A inhibitor, moclobemide 150 mg t.i.d., there were mean increases in rizatriptan AUC and Cmax of 119% and 41%, respectively; and the AUC of the active N-monodesmethyl metabolite of rizatriptan was increased more than 400%. The interaction would be expected to be greater with irreversible MAO inhibitors. Drug interaction studies were not conducted with selective MAO-B inhibitors. The specificity of MAO-B inhibitors diminishes with higher doses and varies among patients. Therefore, co- administration of rizatriptan in patients taking MAO-A or MAO-B inhibitors is contraindicated (see CONTRAINDICATIONS).
Nadolol/Metoprolol
In a drug interactions study, effects of multiple doses of nadolol 80 mg or metoprolol 100 mg every 12 hours on the pharmacokinetics of a single dose of 10 mg rizatriptan were evaluated in healthy subjects (n=12). No pharmacokinetic interactions were observed.
Oral Contraceptives
In a study of concurrent administration of an oral contraceptive during 6 days of administration of rizatriptan benzoate (10-30 mg/day) in healthy female volunteers (n=18), rizatriptan did not affect plasma concentrations of ethinyl estradiol or norethindrone.
Other 5-HT1 Agonists
The administration of rizatriptan with other 5-HT1 agonists has not been evaluated in migraine patients. Because their vasospastic effects may be additive, co-administration of rizatriptan and other 5-HT1 agonists within 24 hours of each other is contraindicated (see CONTRAINDICATIONS).
Propranolol
M-RIZATRIPTAN ODT should be used with caution in patients receiving propranolol, since the pharmacokinetic behavior of rizatriptan during co-administration with propranolol may be unpredictable. In a study of concurrent administration of propranolol 240 mg/day and a single dose of rizatriptan 10 mg in healthy adult subjects (n=11), mean plasma AUC and Cmax for rizatriptan were increased by 70% and 75%, respectively, during propranolol administration. In one subject, a 4-fold increase in AUC and 5-fold increase in Cmax was observed. This subject was not distinguishable from the others based on demographic characteristics. The AUC of the active N-monodesmethyl metabolite of rizatriptan was not affected by propranolol (See DOSAGE AND ADMINISTRATION).
Selective Serotonin Reuptake Inhibitors / Serotonin Norepinephrine Reuptake Inhibitors and Serotonin Syndrome
Cases of life-threatening serotonin syndrome have been reported in post-marketing experience during combined use of selective serotonin reuptake inhibitors (SSRIs) or serotonin norepinephrine reuptake inhibitors (SNRIs) and triptans (See WARNINGS AND PRECAUTIONS).
In a pharmacokinetic study with paroxetine and rizatriptan, paroxetine had no influence on the plasma levels of rizatriptan.
Drug-Food Interactions
Interactions with food have not been studied. Food has no significant effect on the bioavailability of rizatriptan but delays the time to reach peak concentration by an hour. In clinical trials, rizatriptan benzoate was administered without regard to food.
Drug-Herb Interactions
Interactions with herbal products have not been studied.
Drug-Laboratory Interactions
Rizatriptan benzoate is not known to interfere with commonly employed clinical laboratory tests.
Drug-Lifestyle Interactions
Lifestyle interactions have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
M-RIZATRIPTAN ODT is recommended only for the acute treatment of migraine attacks. Rizatriptan benzoate orally disintegrating tablets should not be used prophylactically.
Controlled trials have not established the effectiveness of a second dose if the initial dose is ineffective.
The safety of treating, on average, more than four headaches in a 30-day period has not been established.
Recommended Dose and Dosage Adjustment
ADULTS
M-RIZATRIPTAN ODT
The recommended single adult dose is 5 mg. The maximum recommended single dose is 10 mg.
There is evidence that the 10 mg dose may provide a greater effect than the 5 mg dose (see ACTION AND CLINICAL PHARMACOLOGY, Clinical Studies). The choice of dose should therefore be made on an individual basis, weighing the possible benefit of the 10 mg dose with the potential risk for increased adverse events.
For M-RIZATRIPTAN ODT, administration with liquid is not necessary. The orally disintegrating tablet is packaged in a blister package. Patients should be instructed not to remove the tablet from the blister package until just prior to dosing. The blister pack should then be peeled open with dry hands and the orally disintegrating tablet placed on the tongue, where it will dissolve and be swallowed with the saliva.
Redosing
Doses should be separated by at least 2 hours; no more than a total of 20 mg (Tablets) should be taken in any 24-hour period.
Patients receiving propranolol
A single 5 mg dose of M-RIZATRIPTAN ODT should be used. In no instances should the total daily dose exceed 10 mg per day, given in two doses, separated by at least two hours (see DRUG INTERACTIONS).
Renal Impairment
In hemodialysis patients with severe renal impairment (creatinine clearance <2 mL/min/1.73 m2), the AUC of rizatriptan was approximately 44% greater than in patients with normal renal function (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions). Consequently, if treatment is deemed advisable in these patients, the 5 mg M-RIZATRIPTAN ODT should be administered. No more than a total of 10 mg should be taken in any 24-hour period. Repeated dosing in renally impaired patients has not been evaluated.
Hepatic Impairment
Rizatriptan benzoate orally disintegrating tablet is contraindicated in patients with severe hepatic impairment (Child-Pugh grade C) due to the absence of safety data. Plasma concentrations of rizatriptan were approximately 30% greater in patients with moderate hepatic insufficiency (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions). Consequently, if treatment is deemed advisable in the presence of moderate hepatic impairment, the 5 mg M-RIZATRIPTAN ODT should be administered. No more than a total of 10 mg should be taken in any 24-hour period. Repeated dosing in hepatically impaired patients has not been evaluated.
Patients with Hypertension
M-RIZATRIPTAN ODT should not be used in patients with uncontrolled or severe hypertension. In patients with mild to moderate controlled hypertension, patients should be treated cautiously at the lowest effective dose.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
|---|
No overdoses of rizatriptan benzoate were reported during clinical trials in adults.
Rizatriptan 40 mg (administered as either a single dose or as two doses with a 2-hour interdose interval) was generally well tolerated in over 300 adult patients; dizziness and somnolence were the most common drug-related adverse effects.
In a clinical pharmacology study in which 12 adult subjects received rizatriptan, at total cumulative doses of 80 mg (given within four hours), two subjects experienced syncope and/or bradycardia. One subject, a female aged 29 years, developed vomiting, bradycardia, and dizziness beginning three hours after receiving a total of 80 mg rizatriptan (administered over two hours); a third degree AV block, responsive to atropine, was observed an hour after the onset of the other symptoms. The second subject, a 25-year-old male, experienced transient dizziness, syncope, incontinence, and a 5-second systolic pause (on ECG monitor) immediately after a painful venipuncture. The venipuncture occurred two hours after the subject had received a total of 80 mg rizatriptan (administered over four hours).
In addition, based on the pharmacology of rizatriptan, hypertension or other more serious cardiovascular symptoms could occur after overdosage. Gastrointestinal decontamination (i.e., gastric lavage followed by activated charcoal) should be considered in patients suspected of an overdose with rizatriptan benzoate. The elimination half-life of rizatriptan is 2 to 3 hours (see ACTION AND CLINICAL PHARMACOLOGY). Clinical and electrocardiographic monitoring should be continued for at least 12 hours, even if clinical symptoms are not observed.
There is no specific antidote to rizatriptan. In cases of severe intoxication, intensive care procedures are recommended, including establishing and maintaining a patent airway, ensuring adequate oxygenation and ventilation, and monitoring and support of the cardiovascular system.
The effects of hemo- or peritoneal dialysis on serum concentrations of rizatriptan are unknown.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Rizatriptan benzoate is a selective 5-hydroxytryptamine1B/1D (5-HT1B/1D) receptor agonist. Rizatriptan binds with high affinity to human cloned 5-HT1B and 5-HT1D receptors. It has weak affinity for other 5-HT1 receptor subtypes (5-HT1A, 5-HT1E, 5-HT1F) and the 5-HT7 receptor, but has no significant activity at 5-HT2, 5-HT3, alpha- and beta-adrenergic, dopaminergic, histaminergic, muscarinic or benzodiazepine receptors.
Current theories on the etiology of migraine headache suggest that symptoms are due to local cranial vasodilatation and/or to the release of vasoactive and pro-inflammatory peptides from sensory nerve endings in an activated trigeminal system. The therapeutic activity of rizatriptan in migraine can most likely be attributed to agonist effects at 5-HT1B/1D receptors on the extracerebral, intracranial blood vessels that become dilated during a migraine attack and on nerve terminals in the trigeminal system. Activation of these receptors results in cranial vessel constriction, inhibition of neuropeptide release and reduced transmission in trigeminal pain pathways.
Pharmacokinetics
Absorption: Rizatriptan is completely absorbed following oral administration. The mean oral absolute bioavailability of the rizatriptan tablet is about 45%, and mean peak plasma concentrations (Cmax) are reached in approximately 1-1.5 hours (Tmax). The presence of a migraine headache did not appear to affect the absorption or pharmacokinetics of rizatriptan. Food has no significant effect on the bioavailability of rizatriptan but delays the time to reach peak concentration by an hour. In clinical trials, rizatriptan benzoate was administered without regard to food. The plasma half-life of rizatriptan in males and females averages 2-3 hours.
When rizatriptan benzoate 10 mg was administered every 2 hours for three doses on four consecutive days, the plasma concentrations of rizatriptan within each day were approximately 3-fold greater than those seen with a single 10 mg dose and no plasma accumulation of the drug occurred from day to day.
The bioavailability and Cmax of rizatriptan were similar following administration of rizatriptan benzoate tablets and rizatriptan benzoate wafers, but the rate of absorption is somewhat slower with rizatriptan benzoate wafers. In a pharmacokinetic study in adults, median Tmax was 0.67 hours for the 10-mg tablet and 1.33 hours for the 10-mg rizatriptan benzoate wafers. AUC of rizatriptan is approximately 30% higher in females than in males.
Distribution: The mean volume of distribution is approximately 140 liters in male subjects and 110 liters in female subjects. Rizatriptan is minimally bound (14%) to plasma proteins.
Metabolism: The primary route of rizatriptan metabolism is via oxidative deamination by monoamine oxidase-A (MAO-A) to the indole acetic acid metabolite, which is not active at the 5-HT1B/1D receptor. N-monodesmethyl-rizatriptan, a metabolite with activity similar to that of parent compound at the 5-HT1B/1D receptor, is formed to a minor degree. Plasma concentrations of N-monodesmethyl-rizatriptan are approximately 14% of those of parent compound, and it is eliminated at a similar rate. Other minor metabolites, the N-oxide, the 6-hydroxy compound, and the sulfate conjugate of the 6-hydroxy metabolite are not active at the 5-HT1B/1D receptor.
Rizatriptan is not an inhibitor of the activities of human liver cytochrome P450 isoforms 3A4/5, 1A2, 2C9, 2C19, or 2E1; rizatriptan is a competitive inhibitor (Ki=1400 nM) of cytochrome P450 2D6, but only at high, clinically irrelevant concentrations
Excretion: The total radioactivity of the administered dose recovered over 120 hours in urine and feces was 82% and 12%, respectively, following a single 10 mg oral administration of 14C-rizatriptan. Following oral administration of 14C-rizatriptan, rizatriptan accounted for about 17% of circulating plasma radioactivity. Approximately 14% of an oral dose is excreted in urine as unchanged rizatriptan while 51% is excreted as indole acetic acid metabolite, indicating substantial first pass metabolism.
Table 4
Pharmacokinetic Parameters of a Single Dose of Rizatriptan in Females (n=12)
| Arithmetic Mean (±SD) | |||||||||
|---|---|---|---|---|---|---|---|---|---|
Rizatriptan Benzoate wafer 5 mg | Rizatriptan Benzoate wafer 10 mg | ||||||||
| AUC (0-∞) (ng•hr/mL)a | 33.2 ± 9.8 | 75.9 ± 24.7 | |||||||
| Cmax (ng/mL)a | 11.1 ± 4.7 | 20.3 ± 7.9 | |||||||
| Tmax (hr) | 1.6 ± 0.8* | 2.5 ± 1.4* | |||||||
| t½ (hr)b | 1.6 | 1.7 | |||||||
Plasma Clearance (mL/min)c | 1121.2 ± 241.6 | 1099.3 ± 251.7 | |||||||
a Potency-normalized
b Harmonic mean
c Plasma clearance of 1-mg stable, heavy-labeled I.V. dose of rizatriptan given concomitantly with oral dose
* P <0.05 compared to tablet formulation
Special Populations and Conditions
Pediatrics: The mean AUC0-∞ and Cmax of rizatriptan benzoate tablets (10 mg orally) were about 12% and 19% higher in adolescents (n=12) as compared to historical data in adults, respectively.
A pharmacokinetics study of rizatriptan was conducted in pediatric migraineurs 6 to 17 years of age. Exposures following single dose administration of 5 mg rizatriptan benzoate wafer to pediatric patients weighing 20-39 kg (44-87 lb) or 10 mg rizatriptan benzoate wafer to pediatric patients weighing ≥ 40 kg (88 lb) were similar to those observed following single dose administration of 10 mg rizatriptan benzoate wafer to adults.
The safety and efficacy of rizatriptan benzoate have not been established in patients under 18 years of age and its use in this age group is not recommended (see WARNINGS AND PRECAUTIONS, Special Populations and Conditions).
In an earlier randomized placebo-controlled trial with 291 adolescents migraineurs (dosed without regard to body weight), aged 12-17 years, the efficacy of rizatriptan benzoate tablets (5 mg) was not different from that of placebo.
The efficacy of rizatriptan benzoate wafers in pediatric patients (12 to 17 years of age) was evaluated in an additional multicenter, randomized, double-blind, placebo-controlled, parallel group study (n=570). Using a weight-based dosing strategy, patients 20 kg to <40 kg received 5 mg rizatriptan and patients ≥40 kg received 10 mg rizatriptan. In this study, a difference of 9 % between active treatment and placebo was observed for the primary efficacy endpoint of pain freedom (reduction from moderate or severe pain to no pain) 2 hours after treatment (31 % under rizatriptan vs. 22 % for placebo (p=0.025)). No significant difference for the secondary endpoint of pain relief (reduction from moderate or severe pain to mild or no pain) was found. Non- responsiveness to acetaminophen and NSAIDs was not prospectively established in the population.
Geriatrics: Rizatriptan pharmacokinetics in healthy elderly non-migraineur volunteers (age 65- 77 years) were similar to those in younger non-migraineur volunteers (age 18-45 years).
Gender: The mean AUC0-∞ and Cmax of rizatriptan (10 mg orally) were about 30% and 11% higher in females as compared to males, respectively, while Tmax occurred at approximately the same time.
Race: Pharmacokinetic data revealed no significant differences between African American and Caucasian subjects. The effect of race on the pharmacokinetics of rizatriptan has not been systematically evaluated.
Hepatic Insufficiency: Following oral administration in patients with hepatic impairment caused by mild to moderate alcoholic cirrhosis of the liver, plasma concentrations of rizatriptan were similar in patients with mild hepatic insufficiency compared to a control group of healthy subjects; plasma concentrations of rizatriptan were approximately 30% greater in patients with moderate hepatic insufficiency (see WARNINGS AND PRECAUTIONS). Since there is no data in patients with severe hepatic impairment (Child-Pugh grade C), rizatriptan is contraindicated in this population (see CONTRAINDICATIONS).
Renal Insufficiency: In patients with renal impairment (creatinine clearance 10-60 mL/min/1.73 m2), the AUC0-∞ of rizatriptan was not significantly different from that in healthy subjects. In hemodialysis patients (creatinine clearance <2 mL/min/1.73 m2), however, the AUC for rizatriptan was approximately 44% greater than that in patients with normal renal function (see WARNINGS AND PRECAUTIONS).
STORAGE AND STABILITY
Store the orally disintegrating tablets at room temperature (15°C – 30°C) and protect from moisture.
SPECIAL HANDLING INSTRUCTIONS
The patient should be instructed not to remove the tablets from the blisters until the patient is ready to consume the orally disintegrating tablets inside.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each orally disintegrating tablets contains either 5 mg or 10 mg of rizatriptan (corresponding to 7.265 mg or 14.53 mg of the benzoate salt, respectively) and the following non-medicinal ingredients: mannitol, calcium silicate, crospovidone, aspartame, Colloidal silicon dioxide, sodium stearyl fumarate, and peppermint flavor includes maltodextrin and cornstarch.
M-RIZATRIPTAN ODT 5 mg tablets are white, round, flat faced beveled edge, sweet peppermint flavoured orally disintegrating tablets debossed with “HP” on one side and “238” on other side. Available in blister packages of 6 tablets.
M-RIZATRIPTAN ODT 10 mg tablets are white, round, flat faced beveled edge, sweet peppermint flavoured orally disintegrating tablets debossed with “HP” on one side and “239” on other side. Available in blister packages of 6 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | rizatriptan benzoate |
|---|---|
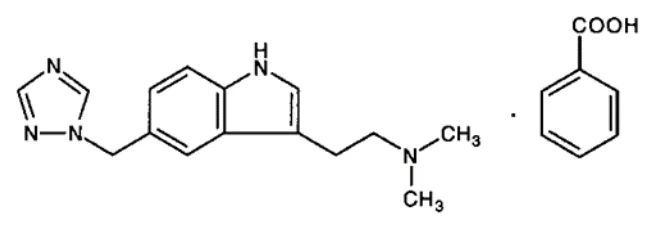
| Chemical name: | N,N-dimethyl-5-(1H-1,2,4-triazol-1-ylmethyl)-1H-indole-3- ethanamine monobenzoate |
| Molecular formula: | C22H25N5O2 (Rizatriptan Benzoate) C15H19N5 (Rizatriptan) |
| Molecular mass: | The molecular weight of rizatriptan benzoate is 391.5 g/ mol |
Structural formula:
| Physicochemical properties: | Rizatriptan benzoate is a white or almost white powder or crystals. Rizatriptan benzoate is soluble in water; sparingly soluble in Ethanol (96 percent), slightly soluble in Methylene chloride. |
|---|
CLINICAL TRIALS
A randomized, two-period, two-treatment, two-sequence, crossover, single dose, evaluation of the relative oral bioavailability of M-RIZATRIPTAN ODT 10 mg with that of MAXALT SMELT® 10 mg (Merck Sharp & Dohme BV, The Netherlands) was conducted in 28 healthy adult human subjects under fasting conditions.
Rizatriptan (1 x 10 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference€ | % Ratio of Geometric Means | 90% Confidence Interval |
AUCt (ng*h/ml) | 109.17 111.84 (22.00) | 115.01 118.68 (24.06) | 94.91 | 91.32 – 98.65 |
AUCinf (ng*h/ml) | 110.52 113.19 (21.79) | 116.251 119.91 (23.89) | 95.07 | 91.53 – 98.75 |
Cmax (ng/ml) | 27.26 28.11 (25.51) | 29.98 31.94 (37.49) | 90.91 | 83.54 – 98.93 |
Tmax ± (h) | 1.33 (0.53 – 3.00) | 1.25 (0.50 – 3.00 ) | ||
T½ § (h) | 2.20 (19.49) | 2.31 (13.25) | ||
* Test Product: M-RIZATRIPTAN ODT 10 mg (Mantra Pharma Inc.)
€ Reference Product: Maxalt Smelt ® 10 mg (Merck Sharp & Dohme BV., The Netherlands)
± Expressed as the median (range)
§ Expressed as arithmetic mean (%CV) only
Study results in adults
Rizatriptan Benzoate wafers
The efficacy of rizatriptan benzoate wafer in the acute treatment of migraine attacks in adults was established in two multicenter, randomized, placebo-controlled trials that were similar in design to the trials of rizatriptan benzoate tablets. In one study (n=311), by 2 hours postdosing, headache response rates in patients treated with rizatriptan benzoate wafer were approximately 66% for rizatriptan 5 mg and 10 mg, compared to 47% in the placebo group. In a larger study (n=547), by 2 hours postdosing, headache response rates were 59% in patients treated with rizatriptan benzoate wafer 5 mg, and 74% after 10 mg, compared to 28% in the placebo group. Headache response was statistically significant as early as 30 minutes following dosing with the 10 mg rizatriptan benzoate wafer. The 10 mg dose was superior to 5 mg at 2 hours. Rizatriptan benzoate wafer also relieved the functional disability, nausea, photophobia, and phonophobia which accompanied the migraine episodes.
DETAILED PHARMACOLOGY
Nonclinical Pharmacodynamics
In Vitro
Rizatriptan has been shown to be a selective agonist at human 5-HT1B (IC50 11 nM) and 5-HT1D (IC50 41nM) receptors with 20-40 fold reduced activity at 5-HT1A receptors using radioligand binding and functional pharmacological bioassays.
Rizatriptan has no significant activity at 5-HT2 or 5-HT3 receptor subtypes or at alpha- and beta- adrenergic receptors, dopaminergic, histaminergic, muscarinic or benzodiazepine receptors.
Rizatriptan contracted human isolated cerebral (middle meningeal) arteries (EC50 0.09 micromolar) yet was significantly less potent in contracting human isolated coronary arteries (EC50 1.0 micromolar) with a 5.6 fold lower maximum response.
Rizatriptan’s primary metabolite, indole acetic acid derivative, was devoid of activity at human 5-HT receptors. The minor metabolite, monodesmethyl rizatriptan retained activity at human 5-HT1B (IC50 19 nM) and 5-HT1D (IC50 9 nM) receptors. The 6-hydroxytryptamine metabolite of rizatriptan that is found only at low levels in humans had an affinity of IC50 600 nM at α2a and of IC50 140 nM at α2c adrenergic receptors.
In vivo
Rizatriptan caused dose-dependent vasoconstriction within the carotid artery vascular bed in anesthetized dogs (ED50 54 μg/kg I.V.; plasma concentration 16 ng/mL) with selectivity for the craniovasculature since effects were not seen in the coronary artery until high (>137 ng/mL) plasma concentrations were reached. In ferrets rizatriptan caused vasoconstriction in the carotid artery (ED50 20 μg/kg I.V.) with no evidence for tachyphylaxis to 3 sequential doses of 15 μg/kg I.V.
Rizatriptan produced a dose-dependent inhibition of dural plasma protein extravasation, dural vasodilatation, and central trigeminal pain signal transmission evoked by electrical stimulation of the trigeminal ganglion or dura mater in anesthetized rats.
Rizatriptan (1.0 mg/kg P.O.; plasma level 317 ng/mL) was free of cardiovascular effects in conscious dogs but at higher doses (5 mg/kg P.O. plasma level 1642 ng/mL) produced increases in blood pressure (~40 mmHg) and heart rate (~80 beats/min) and behavioural activation that were sustained for at least 120 minutes.
Rizatriptan caused a 12% increase in mean arterial blood pressure (mmHg) and a 16% decrease in heart rate (beats/min) with lengthening of the P-R interval (90-103 msec) in anesthetized dogs. QT intervals were unchanged.
Rizatriptan prevented the increases in blood pressure evoked in pithed rats and guinea pigs by stimulation of vascular pre-ganglionic sympathetic nerves.
Rizatriptan caused increases in urine flow (0.46 to 0.83 mL/min), sodium (56-110 microEq/min) and potassium (28-40 microEq/min) excretion in conscious dogs. Average glomerular filtration and effective renal plasma flow rates were unchanged.
Rizatriptan caused behavioural activation and mydriasis at doses >2 mg/kg P.O.
Rizatriptan, in conscious rhesus monkeys, caused behavioral activation and emesis at plasma levels of 260 ng/mL. Rizatriptan (7 mg/kg S.C.) caused mild hypothermia and emesis in squirrel monkeys at high plasma levels of 1546 ng/mL.
Animal Pharmacokinetics
The absorption of oral solutions of rizatriptan in rats and dogs was rapid and high. The time to reach the maximum plasma concentration was 71 minutes in rats and 26 minutes in dogs. The absorption, as measured by the relative urinary excretion of total radioactivity (drug and metabolites) after oral and intravenous doses, was 78% in rats and essentially complete in dogs. The oral bioavailability, as estimated by comparison of plasma AUC0-∞ of rizatriptan after oral and intravenous doses, was 64% in rats and 47% in dogs. The apparent discrepancy in the absorption and bioavailability of rizatriptan is consistent with moderate first-pass metabolism of the drug.
The pharmacokinetics of rizatriptan were generally similar in rats and dogs. Plasma concentrations of rizatriptan declined biexponentially with terminal half-lives of 65 minutes in rats and 72 minutes in dogs. The plasma clearance was rapid in rats (71 mL/min/kg) and dogs (46 mL/min/kg). The steady state volumes of distribution were 4.3 L/kg in rats and 3.2 L/kg in dogs. The systemic exposure of rizatriptan increased slightly greater than proportionally with increases in oral doses in rats (3 and 10 mg/kg) and dogs (1, 2 and 5 mg/kg).
Radioactivity was distributed widely throughout the body after a single 3 mg/kg oral or intravenous dose of 14C-rizatriptan in rats. In general, the pattern of distribution was similar after both routes of administration. Tissues with significant percentages of dose were the liver, kidney, small intestine and stomach, while the brain contained only a trace amount of radioactivity. At 24 hours, tissue concentrations of rizatriptan equivalents had declined to trace levels except in organs involved in elimination (i.e., liver, kidney and the G.I. tract). Over a 24-hour period, the recoveries of radioactivity in the G.I. contents and excreta were 85% and 96% of I.V. and oral doses, respectively.
Toxicokinetic studies demonstrated high placental transfer of rizatriptan in pregnant rats and rabbits and high milk transfer in lactating rats (see TOXICOLOGY, Reproduction).
Rizatriptan was poorly bound to plasma proteins of mouse, rat, rabbit, dog and human and the binding was independent of concentration in the range 50-5000 ng/mL. The unbound fraction was 81% in mouse, 82% in rat, 73% in rabbit, 88% in dog and 86% in human.
The pathways of rizatriptan metabolism in laboratory animals (rat, mouse, rabbit, dog) are similar to those in humans, and consist of oxidative deamination, aromatic hydroxylation followed by sulfation, N-oxidation and N-demethylation.
In general, there were no major differences in the qualitative metabolism of rizatriptan in rodents and humans with respect to dosing frequency (single or multiple oral doses), the size of the dose (therapeutically relevant or toxicological doses) or sex. The extent of metabolism, however, was species dependent. Rizatriptan and its metabolites were eliminated primarily via renal excretion, although biliary excretion also played a role in rats. Rizatriptan underwent more extensive metabolism in dogs and humans when compared to two rodent species, less than 15% of oral doses being excreted in urine as the unchanged drug. The indole acetic acid derivative of rizatriptan was the most prominent metabolite in all species studied although the N-oxide analog also was a significant metabolite in rats and dogs.
In rats, both urinary and biliary routes contributed to the elimination of rizatriptan and its metabolites, while in dogs and human, renal excretion was the primary route of elimination. Accordingly, the excretion of an intravenous dose of rizatriptan in rats was 58% in urine and 23% in feces, while that of the oral dose was balanced evenly between urine (45%) and feces (42%). Approximately one-half (I.V.) and one-third (p.o.) of the urinary radioactivity represented rizatriptan while the remainder was divided among several metabolites. In dogs, 75% of oral and intravenous doses was excreted in urine and 12-13% in feces. The majority of urinary radioactivity after either route of administration represented metabolites while the unchanged drug accounted for approximately 7% (p.o.) and 21% (I.V.) of the radioactivity.
Human Pharmacodynamics
In healthy young male and female subjects who received maximal doses of rizatriptan benzoate (10 mg every 2 hours for three doses), slight increases in blood pressure (approximately 2-3 mmHg) were observed. These small, transient increases in blood pressure were not clinically significant. During long-term monitoring of migraine patients in controlled studies, no consistent effects on blood pressure or heart rate were observed.
In a study in healthy male subjects, rizatriptan benzoate 10 mg produced slight, transient peripheral vasoconstriction (measured as a 5.1 mmHg increase in toe-arm systolic blood pressure gradient). In contrast, intravenous ergotamine (0.25 mg) produced a 14.6 mmHg increase in toe-arm systolic blood pressure gradient. When ergotamine and rizatriptan were given together, the increase in toe-arm systolic blood pressure gradient was similar to that when ergotamine was given alone.
No change in the ECG parameters measured was observed when two 10-mg doses of rizatriptan benzoate, separated by 2 hours, were studied in 157 migraine patients (age range 18 to 72 years) during a migraine attack.
TOXICOLOGY
Acute Toxicity
The approximate oral LD50 of rizatriptan was 700 mg/kg and 2227 mg/kg in mice and rats, respectively. The approximate intravenous LD50 values were 89 and 141 mg/kg in mice and rats, respectively.
Chronic Toxicity
The toxicity potential of rizatriptan was evaluated in a series of repeat dose oral toxicity studies up to one year in dogs and rats and up to 14 weeks in mice. There were no adverse findings that would preclude administration of rizatriptan benzoate at the recommended therapeutic dosages to humans.
Carcinogenesis
The carcinogenic potential of rizatriptan was evaluated in a 106-week study in rats and a 100- week study in mice at oral doses of up to 125 mg/kg/day (625-fold the human dose of 10 mg or 0.2 mg/kg). These doses produced exposure margins (AUC ratios) of up to 600- and 400-fold in rats and mice, respectively, over the human systemic exposure at a therapeutic dose of 10 mg (0.2 mg/kg). For both rats and mice, no evidence of carcinogenicity was seen with increasing doses of rizatriptan.
Mutagenesis
Rizatriptan, with and without metabolic activation, was neither genotoxic, mutagenic, nor clastogenic in all in vitro and in vivo genetic toxicity studies, including: microbial mutagenesis, in vitro chromosome aberration assays, in vitro V-79 mammalian cell mutagenesis assays, an in vitro alkaline elution/rat hepatocyte assay, and an in vivo chromosome aberration assay in mouse bone marrow.
Reproduction
No adverse effects on fertility or reproductive performance, and no fetal toxicity or malformations were observed in female and male rats (except slightly decreased body weight at the high dose) given oral doses of rizatriptan up to 100 and 250 mg/kg/day, respectively (500- and 1250-fold the human dose of 10 mg or 0.2 mg/kg). In addition, no adverse effects on reproductive parameters were detected during early or late gestation, or during the lactation period. These doses provided exposure margins more than 900-fold over the human systemic exposure, based on the AUC ratio derived from rat maternal drug levels compared to humans treated with 10 mg (0.2 mg/kg). High placental transfer occurred, as evidenced by rat fetal plasma levels of 20 to 40% of the maternal plasma levels. High milk transfer occurred, and resulted in rat milk levels that were 5-fold, or greater, the maternal plasma levels. Although high maternal, fetal and neonatal exposure to rizatriptan occurred in these studies, no adverse treatment-related effects were observed on F1 survival, development, behavior, reproductive performance, or testicular histology, nor were there any effects seen in the F2 offspring.
No adverse effects on development, and no fetal toxicity or malformations were observed in pregnant rabbits (except slightly decreased body weight at the high dose) given oral doses of rizatriptan up to 50 mg/kg/day (250-fold the human dose of 10 mg or 0.2 mg/kg). These doses produced high maternal drug levels, resulting in a 475-fold exposure margin, based on the AUC ratio derived from rabbit maternal drug levels compared to humans treated with 10 mg (0.2 mg/kg). High placental transfer occurred with rabbit fetal tissue reaching 42 to 49% of the maternal plasma levels.
Development
There were no adverse effects on fetal development in rats or rabbits exposed to large multiples of the human therapeutic dose of rizatriptan during early and late gestation. High placental transfer of rizatriptan was documented by fetal plasma and tissue levels.
REFERENCES
- 1. Goldberg MR, Lowry RC, Musson DG, Birk KL, Fisher A, DePuy ME, Shadle CR. Lack of pharmacokinetic and pharmacodynamic interaction between rizatriptan and paroxetine. J Clin Pharmacol 1999;39:192-9.
- 2. Ho TW, Pearlman E, Lewis D, Hamalainen M, Connor K, Michelson D, Zhang Y, Assaid C, Mozley LH, Strickler N, Bachman R, Mahoney E, Lines C and Hewitt DJ. Efficacy and tolerability of rizatriptan in pediatric migraineurs: Results from a randomized, double-blind, placebo-controlled trial using a novel adaptive enrichment design.
- 3. Longmore J, Boulanger CM, Desta B, Hill RG, Schofield WN, Taylor AA. 5-HT1D receptor agonists and human coronary artery reactivity in vitro: crossover comparisons of 5-HT and sumatriptan with rizatriptan and L-741,519. Br J Clin Pharmacol 1996;42:431-41.
- 4. Longmore J, Razzaque Z, Shaw D, Davenport AP, Maguire J, Pickard JD, Schofield WN, Hill RG. Comparison of the vasoconstrictor effects of rizatriptan and sumatriptan in human isolated cranial arteries: immunohistological demonstration of the involvement of 5-HT1B- receptors. Br J Clin Pharmacol 1998;46:577–582.
- 5. Visser HW, Terwindt GM, Reines SA, Jiang K, Lines CR, Ferrari MD. Rizatriptan vs. sumatriptan in the acute treatment of migraine. Arch of Neurol 1996;53:1132-7.
- 6. Product Monograph for Maxalt RPD® (Rizatriptan benzoate wafers) 5mg and 10mg, submission control No. 182185, date of revision: April 9, 2015