


Product Monograph - Magnesium Sulfate Injection, USP
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, 1.1 Pediatrics | 05/2025 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Renal, Aluminum toxicity | 05/2025 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics | 05/2025 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................................ 2
TABLE OF CONTENTS .......................................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................................. 4
1 INDICATIONS ......................................................................................................................... 4
1.1 Pediatrics ............................................................................................................................... 4
1.2 Geriatrics ............................................................................................................................... 4
2 CONTRAINDICATIONS ............................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ............................................................................................ 4
4.1 Dosing Considerations ........................................................................................................... 4
4.2 Recommended Dose and Dosage Adjustment ...................................................................... 5
4.3 Reconstitution ....................................................................................................................... 6
5 OVERDOSAGE ........................................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .............................................. 6
7 WARNINGS AND PRECAUTIONS .............................................................................................. 7
7.1 Special Population ................................................................................................................. 8
7.1.1 Pregnant Women .................................................................................................................. 8
7.1.2 Breast-feeding ....................................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................................... 9
7.1.4 Geriatrics ............................................................................................................................... 9
8 ADVERSE REACTIONS ............................................................................................................. 9
8.1 Adverse Reaction Overview .................................................................................................. 9
9 DRUG INTERACTIONS ............................................................................................................. 9
9.4 Drug-Drug Interactions .......................................................................................................... 9
9.5 Drug-Food Interactions ....................................................................................................... 10
9.6 Drug-Herb Interactions ........................................................................................................ 10
9.7 Drug-Laboratory Test Interactions ...................................................................................... 10
10 CLINICAL PHARMACOLOGY .................................................................................................. 10
10.1 Mechanism of Action ........................................................................................................... 10
10.3 Pharmacokinetics ................................................................................................................ 10
11 STORAGE, STABILITY AND DISPOSAL ..................................................................................... 10
12 SPECIAL HANDLING INSTRUCTIONS ...................................................................................... 11
PART II: SCIENTIFIC INFORMATION ................................................................................................... 12
13 PHARMACEUTICAL INFORMATION ....................................................................................... 12
14 CLINICAL TRIALS ................................................................................................................... 12
15 MICROBIOLOGY ................................................................................................................... 12
16 NON-CLINICAL TOXICOLOGY ................................................................................................. 12
PATIENT MEDICATION INFORMATION .............................................................................................. 13
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Magnesium Sulfate Injection, USP may be of therapeutic value in the following conditions:
- as an anticonvulsant, for preeclampsia and eclampsia of pregnancy;
- as an electrolyte replenisher for hypomagnesemia and magnesium deficiency to maintain normal neuromuscular irritability.
1.1 Pediatrics
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use. (See 4.2 Recommended Dose and Dosage Adjustment, Route of administration, Intramuscular; 4.2 Recommended Dose and Dosage Adjustment, Considerations for special population, Pediatrics; 4.3 Reconstitution, Deep Intramuscular Solutions, Pediatrics); 7 WARNINGS AND PRECAUTIONS, Renal, Aluminum toxicity; 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics: Health Canada has not authorized an indication for geriatric use. (See 4.2 Recommended Dose and Dosage Adjustment, Considerations for special populations, Geriatrics; 7 WARNINGS AND PRECAUTIONS, Renal and 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Magnesium Sulfate Injection, USP should not be administered parenterally in patients with:
- heart block
- myocardial damage
- hypersensitivity to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Renal
Parenteral use in the presence of renal insufficiency may lead to magnesium intoxication. In patients with severe renal impairment, dosage should not exceed 20 g in 48 hours. Serum magnesium should be monitored in such patients. (See 7 WARNINGS AND PRECAUTIONS, Renal, Aluminum toxicity).
4.2 Recommended Dose and Dosage Adjustment
Usual Dose Range
1 to 40 g daily.
Route of administration:
- Intramuscular
Adults and older children for severe hypomagnesemia 1 to 5 g (2 to 10 mL of 50% solution) daily in divided doses; administration is repeated daily until serum levels have returned to normal. If deficiency is not severe, 1 g (2 mL of 50% solution) can be given once or twice daily. Serum magnesium levels should serve as a guide to continued dosage.
- Intravenous
Must be diluted before IV use. 1 to 4 g Magnesium Sulfate Injection, USP may be given intravenously in 10% to 20% solution, but only with great caution; the rate should not exceed 1.5 mL of 10% solution or equivalent per minute until relaxation is obtained.
Intravenous use in eclampsia should be reserved for immediate control of life-threatening convulsions. See 7 WARNINGS AND PRECAUTIONS.
- Intravenous Infusion
Must be diluted before IV use. 4 g in 250 mL of 5% Dextrose Injection, USP at a rate not exceeding 3 mL per minute.
Recommended dose per indication:
- Electrolyte Replenisher
Intramuscular 1 to 2 g in 50% solution four times a day until serum magnesium is within normal limits.
- For Pre-eclampsia or Eclampsia
Initially 1 to 2 g in 25% or 50% solution is given intramuscularly. Subsequently, 1 g is given every 30 minutes until relief is obtained. The blood pressure should be monitored after each injection.
Magnesium sulfate should be used for treatment of preeclampsia and eclampsia of pregnancy only if clearly needed and for the shortest time required. See 7 WARNINGS AND PRECAUTIONS.
Parenteral drug products should be visually inspected for particulate matter and discolouration prior to administration whenever solution and container permit.
Considerations for special populations:
- Pediatrics
Health Canada has not authorized an indication for pediatric use.
Usual pediatric dose: Intramuscular 20 to 40 mg/kg of body weight in a 20% solution repeated up to four times a day. Do not exceed 8 g daily.
- Geriatrics
Geriatric patients often require reduced dosage because of impaired renal function. In patients with severe impairment, dosage should not exceed 20 g in 48 hours. Serum magnesium should be monitored in such patients.
4.3 Reconstitution
Parenteral Products:
Intravenous Solutions:
- Must be diluted to a concentration of 20% or less prior to administration.
- Diluents commonly used: 5% Dextrose Injection, USP and 0.9% Sodium Chloride Injection, USP.
Deep Intramuscular Solutions:
- Adult: Undiluted (50%) solution is appropriate in adults.
- Pediatrics: Solution should be diluted to a 20% or less concentration prior such injection in children.
5 OVERDOSAGE
Hypermagnesemia is manifested by muscle weakness, hypotension, ECG changes, sedation, and confusion. As plasma concentrations of magnesium begin to exceed 4 mEq/L, the deep-tendon reflexes are decreased and may be absent at levels approaching 10 mEq/L. At 12 to 15 mEq/L, respiratory paralysis is a potential hazard; the respiratory effects can be antagonized to some extent by the intravenous administration of calcium salts. In cases of severe renal impairment, symptomatic hypermagnesemia may be an indication for dialysis. Although man usually tolerates high concentrations of magnesium in plasma, there are occasional instances when cardiac consequences may be seen in the form of complete heart block at concentrations well below 10 mEq/L.
Before the parenteral administration of each dose, the respiratory rate should be at least 16 per minute and urinary function should be adequate. In the event of overdosage, assisted ventilation must be provided until calcium can be given intravenously. Peritoneal dialysis or hemodialysis may be required in cases of extreme hypermagnesemia.
When Magnesium Sulfate Injection, USP is administered parenterally in doses that are sufficient to induce hypermagnesemia, the drug has a depressant effect on the central nervous system and, via the peripheral neuromuscular junction, on muscle.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Intravenous, Intramuscular | Solution, 500 mg/mL | Sulfuric Acid, NF Sodium Hydroxide, NF Water for Injection, USP |
Description
Magnesium Sulfate Injection, USP is a sterile, concentrated solution (50%) of magnesium sulfate in Water for Injection.
Each mL contains 500 mg magnesium sulfate heptahydrate (49.3 mg Mg++ and 194.7 mg SO42-). pH adjusted with sulfuric acid or sodium hydroxide if necessary.
The solution contains no bacteriostatic agent or other preservatives.
Magnesium Sulfate Injection, USP contains no more than 300 mcg/L of aluminum (see 7 WARNINGS AND PRECAUTIONS, Renal).
| Packaging type | Magnesium per mL | Sulfate per mL | Volume |
|---|---|---|---|
Glass vial The stopper used for the glass vials is not made with natural rubber latex. | 49.3 mg | 194.7 mg | 10 mL in a 20 mL vial |
Pharmacy Bulk Package (Glass vial) – Not for Direct Infusion The stopper used for the glass vials is not made with natural rubber latex. | 49.3 mg | 194.7 mg | 50 mL |
7 WARNINGS AND PRECAUTIONS
General
Administer with caution if flushing and sweating occurs. (See 8.1 Adverse Reaction Overview.)
When barbiturates, narcotics or other hypnotics (or systemic anesthetics) are to be given in conjunction with magnesium, their dosage should be adjusted with caution because of additive CNS depressant effects of magnesium. A preparation of calcium salt should be readily available for intravenous injection to counteract potential serious signs of magnesium intoxication. (See 9.4 Drug-Drug Interactions).
The principal hazard in parenteral magnesium therapy is the production of abnormally high levels of magnesium in the plasma. The most immediate danger to life is respiratory depression. A preparation of calcium, such as the gluconate or gluceptate, should be at hand for intravenous administration as an antidote. (See 5 OVERDOSAGE).
Monitoring and Laboratory Tests
Magnesium Sulfate Injection, USP should not be given unless hypomagnesemia has been confirmed and the serum concentration of magnesium is monitored. The normal serum level is 1.5 to 2.4 mEq/L.
Renal
Since magnesium is excreted almost entirely by the kidneys, it should be given very cautiously in the presence of serious impairment of renal function.
Aluminum toxicity: This product contains aluminum that may be toxic.
Aluminum may reach toxic levels with prolonged parenteral administration if kidney function is impaired. Neonates and infants, especially premature (preterm) neonates and preterm infants, are particularly at risk because their kidneys are immature, and they require large amounts of calcium and phosphate solutions which contain aluminum.
Patients with impaired or immature kidney function, including neonates and infants (preterm or term), who receive parenteral levels of aluminum at greater than 4 to 5 mcg per kg per day accumulate aluminum at levels associated with central nervous system and bone toxicity. Tissue loading may occur at even lower rates of administration of TPN products and of the lock-flush solutions used in their administration, and from lower daily amounts of aluminum.
Exposure to aluminum from Magnesium Sulfate Injection, USP at the recommended dosage is not more than 0.024 mcg/kg per dose of 40 mg/kg bodyweight. (see 4 DOSAGE AND ADMINISTRATION).
When prescribing Magnesium Sulfate Injection, USP for use in parenteral nutrition solutions containing other small volume parenteral products and/or pharmacy bulk packages, limit the total daily patient exposure to aluminum in the admixture to no more than 4 to 5 mcg/kg/day (see 7 WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
This product contains no more than 300 mcg/L of aluminum.
Reproductive Health: Female and Male Potential
- Fertility
No studies have been conducted to determine if Magnesium Sulfate Injection, USP has an effect on fertility.
- Teratogenic Risk
Continuous administration of magnesium sulfate (intravenous or intramuscular) beyond 5 to 7 days to pregnant women can lead to hypocalcemia and bone abnormalities in the developing fetus. These bone abnormalities include skeletal demineralization and osteopenia. In addition, cases of neonatal fracture have been reported. The shortest duration of treatment that can lead to fetal harm is not known. Magnesium sulfate should be used for treatment of preeclampsia and eclampsia of pregnancy only if clearly needed and for the shortest time required.
- Non-teratogenic Risk
Magnesium Sulfate Injection, USP can cause fetal harm when administered to a pregnant woman. When Magnesium Sulfate Injection, USP is administered to a toxemic mother, the newborn is usually not compromised. When Magnesium Sulfate Injection, USP is administered intravenously by a continuous infusion for longer than 24 hours before delivery, the possibility of the baby showing signs of neuromuscular or respiratory depression of the newborn should be considered, since fetal toxicity can occur. A baby with hypermagnesemia may require resuscitation and assisted ventilation. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus.
7.1 Special Population
7.1.1 Pregnant Women
Magnesium sulfate should be used for treatment of preeclampsia and eclampsia of pregnancy only if clearly needed and for the shortest time required.
Intravenous use in eclampsia should be reserved for immediate control of life-threatening convulsions.
Magnesium sulfate can cause fetal abnormalities when administered beyond 5-7 days to pregnant women. There are retrospective epidemiological studies and case reports documenting fetal abnormalities such as hypocalcemia, skeletal demineralization, osteopenia and other skeletal abnormalities with continuous maternal administration of magnesium sulfate for more than 5 to 7 days.
7.1.2 Breast-feeding
Since magnesium is distributed into milk during parenteral magnesium sulfate administration, caution should be exercised when Magnesium Sulfate Injection, USP is administered to a nursing women.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use.
Magnesium Sulfate Injection, USP contains aluminum that mat be associated with central nervous system and bone toxicity. The safety and efficacy of Magnesium Sulfate Injection, USP (for the approved indications) have not been established in pediatric patients younger than 18 years old.
7.1.4 Geriatrics
Geriatric patients often require reduce dosage because of impaired renal function. (See 7 WARNINGS AND PRECAUTIONS, Renal and 4.2 Recommended Dose and Dosage Adjustment, Considerations for special populations, Geriatrics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Principal adverse reactions are related to the high plasma levels of magnesium and include flushing, sweating, hypotension, circulatory collapse, and cardiac and central nervous system depression. Respiratory depression is the most life-threatening effect. Hypocalcemia with signs of tetany secondary to magnesium sulfate therapy for eclampsia has been reported.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
When barbiturates, narcotics, hypnotics (or systemic anesthetics), or other central nervous system depressants are to be given in conjunction with magnesium, their dosage should be adjusted with caution because of the additive central nervous system depressant effects of magnesium.
Central nervous system depression and peripheral transmission defects produced by magnesium may be antagonized by calcium.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
Magnesium is the second most plentiful cation of the intracellular fluids. It is essential for the activity of many enzyme systems and plays an important role with regard to neurochemical transmission and muscular excitability. Deficiencies are accompanied by a variety of structural and functional disturbances.
10.1 Mechanism of Action
Some of the effects of magnesium on the nervous system are similar to those of calcium. An increased concentration of magnesium in the extracellular fluid causes depression of the central nervous system (CNS). Magnesium has a direct depressant effect on skeletal muscle.
Abnormally low concentrations of magnesium in the extracellular fluid result in increased acetylcholine release and increased muscle excitability that can produce tetany.
Magnesium slows the rate of SA nodal impulse formation. Higher concentrations of magnesium (greater than 15 mEq/L) produce cardiac arrest in diastole.
Excess magnesium causes vasodilation by both a direct action on blood vessels and ganglionic blockade.
10.3 Pharmacokinetics
Elimination
Magnesium is excreted principally by the kidney by glomerular filtration.
11 STORAGE, STABILITY AND DISPOSAL
Store vials at 15 °C to 30 °C.
Use only if solution is clear, and seal intact.
Unused portion of container should be discarded.
Incompatibilities
Magnesium sulfate in solution may result in a precipitate formation when mixed with solutions containing:
Alcohol (in high concentrations), Heavy metals, Alkali carbonates and bicarbonates, Hydrocortisone sodium succinate, Alkali hydroxides Phosphates, Arsenates, Polymyxin B sulfate, Barium Procaine hydrochloride, Calcium, Salicylates, Clindamycin phosphate, Strontium, Tartrates.
The potential incompatibility will often be influenced by the changes in the concentration of reactants and the pH of the solutions.
12 SPECIAL HANDLING INSTRUCTIONS
This information is not available for this drug product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
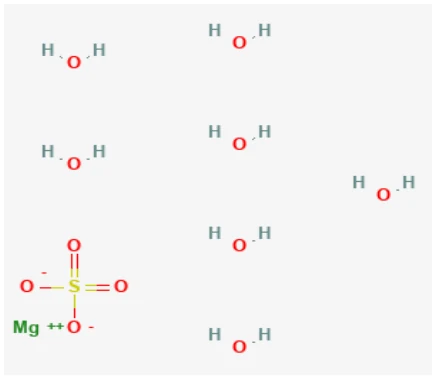
Drug Substance:
| Proper name: | Magnesium sulfate heptahydrate |
|---|---|
| Chemical name: | Magnesium sulfate heptahydrate |
| Molecular formula: | MgSO4•7H2O |
| Molecular mass: | 246.4746 g/mol |
| Structural formula: | |
| Physicochemical properties: | Freely soluble in water, very soluble in boiling water, practically insoluble in ethanol (96 per cent). |
| Product characteristics: | White or almost white, crystalline powder or brilliant, colourless crystals. |
14 CLINICAL TRIALS
The clinical trial data on which the original indication was authorized is not available.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Information not available.
 |