


Product Monograph - Maxidol Liquid Gels
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS | 10/2025 |
|---|---|
| 8 ADVERSE REACTIONS, 8.5 Post-Market Adverse Reactions | 10/2025 |
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 07/2025 |
| 7 WARNINGS AND PRECAUTIONS | 07/2025 |
| 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.1 Pregnant Women | 07/2025 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ....................................................................................... 2
TABLE OF CONTENTS ......................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ................................................................. 4
1 INDICATIONS .................................................................................................................. 4
1.1 Pediatrics ............................................................................................................................ 4
1.2 Geriatrics ............................................................................................................................ 4
2 CONTRAINDICATIONS ..................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................................. 5
4 DOSAGE AND ADMINISTRATION ..................................................................................... 5
4.1 Dosing Considerations .................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................... 5
4.4 Administration .................................................................................................................... 6
4.5 Missed Dose ........................................................................................................................ 6
5 OVERDOSAGE ................................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ...................................... 6
7 WARNINGS AND PRECAUTIONS ...................................................................................... 6
7.1 Special Populations ............................................................................................................. 8
7.1.1 Pregnant Women .......................................................................................................... 8
7.1.2 Breast-feeding ............................................................................................................... 9
7.1.3 Pediatrics ....................................................................................................................... 9
7.1.4 Geriatrics ....................................................................................................................... 9
8 ADVERSE REACTIONS ................................................................................................ 10
8.1 Adverse Reaction Overview ......................................................................................... 10
8.2 Clinical Trial Adverse Reactions.................................................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions ........................................................... 11
8.5 Post-Market Adverse Reactions ................................................................................... 12
9 DRUG INTERACTIONS .................................................................................................... 14
9.2 Drug Interactions Overview .............................................................................................. 14
9.4 Drug-Drug Interactions ..................................................................................................... 14
9.5 Drug-Food Interactions..................................................................................................... 17
9.6 Drug-Herb Interactions ..................................................................................................... 17
9.7 Drug-Laboratory Test Interactions ................................................................................... 17
10 CLINICAL PHARMACOLOGY ......................................................................................... 17
10.1 Mechanism of Action ...................................................................................................... 17
10.2 Pharmacodynamics ........................................................................................................ 17
10.3 Pharmacokinetics ........................................................................................................... 17
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 18
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................. 18
PART II: SCIENTIFIC INFORMATION .................................................................................. 19
13 PHARMACEUTICAL INFORMATION .............................................................................. 19
14 CLINICAL TRIALS .......................................................................................................... 20
14.1 Trial Design and Study Demographics ............................................................................ 20
14.2 Study Results .................................................................................................................. 21
14.3 Comparative Bioavailability Studies ............................................................................... 23
15 MICROBIOLOGY .......................................................................................................... 23
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 23
PATIENT MEDICATION INFORMATION ............................................................................. 28
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
MAXIDOL® Liquid Gels (naproxen sodium) is indicated for the reduction of fever and treatment of pain:
- MAXIDOL® Liquid Gels relieves muscular ache
- MAXIDOL® Liquid Gels relieves backache
- MAXIDOL® Liquid Gels relieves headache
- MAXIDOL® Liquid Gels relieves migraine pain
- MAXIDOL® Liquid Gels relieves the pain of menstrual cramps (dysmenorrhoea)
1.1 Pediatrics
Pediatrics (<12 years of age): Children under 12 should not take this drug, unless directed by a doctor. The safety in pediatric use has not been established
1.2 Geriatrics
Patients older than 65 years and frail or debilitated patients are more susceptible to a variety of adverse reactions from NSAIDs. The incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. Most reports of fatal GI events are in this population. Older patients are also at risk of lower esophageal injury including ulceration and bleeding.
2 CONTRAINDICATIONS
Naproxen sodium is contraindicated in patients:
- who have previously exhibited allergy to naproxen sodium
- with known hypersensitivity to the active substance naproxen (including naproxen sodium) or any of the excipients in the capsule. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph
- with a history of asthma, urticaria, or allergic-type reactions after taking acetylsalicylic acid (ASA) or other NSAIDs (i.e. complete or partial syndrome of ASA-intolerance - rhinosinusitis, urticaria/angioedema, nasal polyps, asthma). Fatal anaphylactoid reactions have occurred in such individuals. Individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse reaction.
- with active peptic ulcers, a history of recurrent ulceration, or active gastrointestinal bleeding
- with inflammatory bowel disease.
- with severe liver impairment or active liver disease
- with severe renal impairment (creatinine clearance <30 mL/min or 0.5 mL/sec) or deteriorating renal disease (individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs and must be monitored)
- in women in their third trimester of pregnancy because of risk of premature closure of the ductus arteriosus and prolonged parturition.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- Caution should be exercised in prescribing MAXIDOL® during the first and second trimesters of pregnancy. Use of NSAIDS at approximately 20 weeks of gestation or later may cause oligohydramnios, and renal dysfunction including renal failure (see WARNINGS AND PRECAUTIONS). MAXIDOL® is CONTRAINDICATED for use during the third trimester because of risk of premature closure of the ductus arteriosus and uterine inertia (prolonged parturition) (see CONTRAINDICATIONS).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- In self-medication, MAXIDOL® Liquid Gels should only be used for a short term treatment period of up to five days for pain and 3 days for fever. Otherwise a doctor should be consulted.
- Each dose should be swallowed with a full glass of water and can be taken fasting or with meals and/or antacids. Absorption may be slightly delayed with meals.
- If symptoms change, a doctor should be consulted.
- The recommended dosage should be adhered to unless directed by a doctor.
- MAXIDOL® Liquid Gels is as safe on the stomach as Tylenol Extra Strength 500 mg and Advil 200mg if the maximum daily dose and the recommended length of use for each product is not exceeded.
- MAXIDOL® Liquid Gels provides non-prescription pain relief that lasts up to 12 hours with 1 pill.
4.2 Recommended Dose and Dosage Adjustment
- Adults (12-65 years): 1 capsule every 8 - 12 hours. For individuals over 65 years, 1 capsule every 12 hours. Do not take more than 2 capsules in a 24-hour period. Drink a full glass of water with each dose.
- Under 12 years: Children under 12 should not take this drug. The safety in pediatric use has not been established.
4.4 Administration
See Section 4.2 Recommended Dose and Dosage Adjustment
4.5 Missed Dose
If you miss taking your dose on time, do not worry; take your dose when you remember. Do not exceed more than two doses in 24 hours.
5 OVERDOSAGE
Significant overdose can be characterized by drowsiness, heartburn, indigestion, nausea and vomiting. A few patients have experienced convulsions but it is not clear if these were naproxen related. Some cases with acute, reversible renal failure have been described. It is not known what dose of the drug would be life-threatening.
Should a patient ingest a large quantity of naproxen sodium the stomach may be emptied and usual supportive measures like administration of activated charcoal employed. Hemodialysis does not decrease the plasma concentration of naproxen because of the high degree of its protein binding. There is no specific antidote.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 - Dosage Forms, Strengths, Composition and Packaging
One capsule of MAXIDOL® Liquid Gels contains naproxen sodium 220 mg, of which 20 mg is sodium. The excipients consist of FD&C Blue No. 1, gelatin, glycerin, lactic acid, mannitol, pharmaceutical ink, polyethylene glycol, povidone, propylene glycol, sorbitan, sorbitol, water. Packaging consists of:
- Opaque HDPE bottles containing 30 capsules packed into an outer carton.
7 WARNINGS AND PRECAUTIONS
General
Patients who are taking any other analgesic or anti-inflammatory drugs (including naproxen or naproxen sodium), steroids, diuretics or drugs that influence hemostasis.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Capsule, 220mg | FD&C Blue No. 1, gelatin, glycerin, lactic acid, mannitol, pharmaceutical ink, polyethylene glycol, povidone, propylene glycol, sorbitan, sorbitol, water |
Cardiovascular
Patients with severe cardiac impairment and a history of hypertension.
Naproxen may attenuate acetylsalicylic acid’s antiplatelet effect. Patients should talk to their doctor if they are on an acetylsalicylic acid regimen and plan to take naproxen sodium (see Drug-Drug Interactions).
Cases of Kounis syndrome have been reported in patients treated with naproxen. Kounis syndrome has been defined as cardiovascular symptoms secondary to an allergic or hypersensitive reaction associated with constriction of coronary arteries and potentially leading to myocardial infarction.
Gastrointestinal
Patients with a medical history of gastrointestinal disease including peptic ulceration. Pain of gastrointestinal origin is not an indication for naproxen sodium.
Hematologic
Patients with coagulation disturbances. Numerous studies have shown that concomitant use of NSAIDs and anti-coagulants increases the risk of bleeding. Concurrent therapy of MAXIDOL® Liquid Gels with warfarin requires close monitoring of the international normalized ratio (INR). Even with therapeutic INR monitoring, increased bleeding may occur.
Immune
Hypersensitivity reactions, including anaphylactic (anaphylactoid) reactions may occur both in patients with and without a history of hypersensitivity on exposure to aspirin, other non-steroidal anti-inflammatory drugs or naproxen-containing products.
Cases of Kounis syndrome have been reported in patients treated with naproxen. Kounis syndrome has been defined as cardiovascular symptoms secondary to an allergic or hypersensitive reaction associated with constriction of coronary arteries and potentially leading to myocardial infarction.
Monitoring and Laboratory Tests
Naproxen sodium causes transient, dose-dependent modestly increased bleeding times. However, these values often do not exceed the upper limit of the reference range. Naproxen sodium may theoretically interfere with the urinary analyses of 17-ketogenic steroids and 5-hydroxy indoleacetic acid (5 HIAA).
Pregnancy If MAXIDOL® Liquid Gels is administered in the middle (approximately 20 weeks) to the end of the second trimester, it is recommended that pregnant women on MAXIDOL® Liquid Gels be closely monitored for amniotic fluid volume since MAXIDOL® Liquid Gels may result in reduction of amniotic fluid volume and even oligohydramnios (see Special Populations). MAXIDOL® Liquid Gels is CONTRAINDICATED for use in the third trimester of pregnancy.
Neurologic
Some patients may experience drowsiness, dizziness, blurred vision vertigo, tinnitus, hearing loss, insomnia or depression with the use of NSAIDs such as MAXIDOL® Liquid Gels. If patients experience such adverse reactions, they should exercise caution in carrying out activities that require alertness, like driving or using machinery.
Reproductive Health: Female and Male Potential
Fertility
- Naproxen, as with any drug known to inhibit cyclooxygenase/prostaglandin synthesis, may impair fertility and is not recommended in women attempting to conceive. In women who have difficulty conceiving or who are undergoing investigation of infertility, withdrawal of naproxen should be considered.
Respiratory
Patients with a medical history of asthma, rhinitis or nasal polyps.
Skin
Patients with a medical history of urticaria and angioedema.
7.1 Special Populations
7.1.1 Pregnant Women
Caution should be exercised in prescribing MAXIDOL® Liquid Gels during the first and second trimesters of pregnancy. As with other drugs of this type, naproxen sodium produces delay in parturition in animals and also affects the human fetal cardiovascular system (closure of the ductus arteriosus). Therefore, naproxen sodium should not be used unless clearly needed and when directed to do so by a doctor. The use of naproxen sodium in the first and second trimesters of pregnancy requires cautious balancing of the possible benefits and risks to the mother and fetus, especially during the first trimester.
Inhibition of prostaglandin synthesis may adversely affect pregnancy and/or the embryo/fetal development. Data from epidemiological studies suggest an increased risk of miscarriage and of cardiac malformation after use of a prostaglandin synthesis inhibitor in early pregnancy. In animals, administration of a prostaglandin synthesis inhibitor has been shown to result in increased pre- and post-implantation loss and embryo-fetal lethality. In addition, increased incidences of various malformations, including cardiovascular, have been reported in animals given a prostaglandin synthesis inhibitor during the organogenetic period.
Oligohydramnios/Neonatal Renal Impairment:
Use of NSAIDs, including MAXIDOL® Liquid Gels, at approximately 20 weeks gestation or later in pregnancy may cause fetal renal dysfunction leading to oligohydramnios and, in some more severe cases, neonatal respiratory, musculoskeletal and renal problems (see TOXICOLOGY). Published studies and post-marketing reports describe maternal NSAID use at approximately 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment, or failure. NSAIDs were shown to cause significant reduction in fetal urine production prior to reduction of amniotic fluid volume. There have also been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible, even after treatment discontinuation.
These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. Oligohydramnios is often, but not always, reversible with treatment discontinuation. Complications of prolonged oligohydramnios may, for example, include limb contractures and delayed lung maturation. In some post-marketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required. If, after careful consideration of alternative treatment options for pain management, NSAID treatment is necessary anywhere from the middle (onset approximately 20 weeks) to the end of the second trimester of pregnancy, it is recommended that the use be limited to the lowest effective dose and shortest duration possible. Consider ultrasound monitoring of fetal well-being, including of amniotic fluid volume assessment if MAXIDOL® Liquid Gels treatment extends beyond 48 hours. It is recommended that NSAIDs treatment be discontinued if oligohydramnios occurs, followed by appropriate medical follow up.
Inform pregnant women not to use MAXIDOL® Liquid Gels and other NSAIDs from the third trimester of pregnancy because of the risk of the premature closing of the fetal ductus arteriosus (see Contraindications). If treatment with MAXIDOL® Liquid Gels is needed for a pregnant woman anywhere from the middle (onset approximately 20 weeks gestation) to the end of the second trimester of pregnancy, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours.
7.1.2 Breast-feeding
Naproxen has been found in the milk of lactating mothers. The use of naproxen sodium should therefore be avoided in women who are breast feeding unless clearly needed and directed to do so by a doctor.
7.1.3 Pediatrics
Children under 12 should not take this drug, unless directed by a doctor. The safety in pediatric use has not been established.
7.1.4 Geriatrics
Patients older than 65 years and frail or debilitated patients are more susceptible to a variety of adverse reactions from NSAIDs. The incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. Most reports of fatal GI events are in this population. Older patients are also at risk of lower esophageal injury including ulceration and bleeding.
Persons on a Low Sodium Diet:
One capsule contains 20 mg sodium, which is classified as low in sodium. A variety of Health Canada guidelines suggest that a diet low in sodium should be restricted to 2 g per day while the Sodium Collaborative Research group suggests that a low-sodium diet should be restricted to ≤ 1.2 g (50 mmol) per day.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety profile of naproxen sodium was analysed through a meta-analysis of the clinical trials which were performed in the course of the naproxen sodium clinical development program. Naproxen sodium was studied in single (Sd, 220mg or 440mg pooled data), multiple (MD, 440mg/day and 880mg/day) or PRN (up to 880mg/day), involving 4623 subjects treated with naproxen sodium and 2659 subjects with placebo. The occurrence of clinical trial adverse events did not differ between naproxen sodium and placebo, with gastrointestinal (nausea 4.4%, dyspepsia 1.9%, vomiting 1.8%) and nervous system (headache 4.9%, somnolence 2.4%, dizziness 2%) adverse events most commonly reported. An evaluation of gastrointestinal adverse events showed no difference between naproxen sodium and placebo. There was no serious gastrointestinal adverse event (bleeding or perforation) or any case of anaphylaxis
In post-market adverse reactions observed for OTC naproxen sodium and/or prescription dosages (higher dose and/or longer duration), the most commonly (≥ 1% - < 10%) observed adverse events are gastrointestinal in nature or associated with the nervous system. The most common adverse drug reactions for OTC naproxen sodium are dizziness, headache, light-headedness, dyspepsia, nausea, heartburn, and abdominal pain. The adverse drug reactions seen during short term use of naproxen sodium are normally mild and disappear after discontinuing the drug. In short term use of naproxen sodium occurrence of GI ulcers/bleeding/perforation are rare events. The adverse events are related to NSAIDs as a class; there is no adverse event that is specific for naproxen alone.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use. The safety profile of naproxen sodium was analysed through a meta-analysis of the clinical trials which were performed in the course of the naproxen sodium clinical development program. The meta-analysis included a total of 46 studies, which satisfied the criteria of being randomized, placebo controlled, double-blind and used naproxen sodium in single (SD, 220 mg or 440 mg pooled data), multiple (MD, 440 mg/day and 880 mg/day) or PRN (up to 880 mg/day) doses. In total 4623 subjects were treated with naproxen sodium while 2659 took placebo. Fifty-two percent of subjects participated in SD trials, 20 % in MD trials all lasting for 7 days and the remaining 28% in PRN trials. They were predominantly Caucasian, slightly more women with a mean age between the 20s and 30s with exception of 422 patients from the arthritis studies with a mean age in the low 60s. The occurrence of all adverse events did not differ between naproxen sodium and placebo, in the SD, MD or PRN trials. Moderate and severe events tended to occur less frequently in the subjects treated with naproxen sodium MD compared to placebo, presumably due to concomitant treatment of naturally occurring headache. The data in Table 2 shows the frequencies of adverse events that are > 1% from the meta-analysis. A thorough evaluation of gastrointestinal adverse events showed no difference between naproxen sodium and placebo. There was no serious gastrointestinal adverse event (bleeding or perforation) or any case of anaphylaxis.
Table 2 - Adverse events that occurred with naproxen sodium (low dose short duration) with a frequency >1% in clinical trials
Naproxen sodium n = 4623 (%) | Placebo n = 2659 (%) | |
Gastrointestinal Dyspepsia Nausea Vomiting | 1.9% 4.4% 1.8% | 1.8% 4.8% 2.4% |
Nervous system Dizziness Headache Somnolence | 2.0% 4.9% 2.4% | 2.1% 6.8% 1.5% |
8.3 Less Common Clinical Trial Adverse Reactions
Gastrointestinal (<1%): Constipation, diarrhea
Other (<1%): Allergic reaction, Edema, Rash/pruritus
8.5 Post-Market Adverse Reactions
Table 3 - The following post-marketing adverse drug reactions have been observed for OTC naproxen sodium and/or solely for prescription dosages (higher dose and/or longer duration) of naproxen/naproxen sodium.
Immune system disorders
Very rare
< 0.01% and isolated reports
Not Known (cannot be estimated from available data)
Anaphylaxis/anaphylactoid reactions
Kounis syndrome (See Section 7 WARNINGS AND PRECAUTIONS)
Blood and the lymphatic system disorders
Very rare
< 0.01% and isolated reports
hematopoietic disturbances (leukopenia, thrombocytopenia, agranulocytosis, aplastic anemia, eosinophilia, hemolytic anemia)
Psychiatric disorders
Very rare
< 0.01% and isolated reports
psychiatric disorders
Nervous system disorders
Common
≥ 1% - < 10%
dizziness, headache, lightheadedness
Uncommon
≥ 0.1 % - < 1 %
drowsiness, insomnia, somnolence
Very rare
< 0.01% and isolated reports
aseptic meningitis, cognitive dysfunction, convulsions
Eye disorders
Very rare
< 0.01% and isolated reports
visual disturbance, corneal opacity, papillitis, retrobulbar optic neuritis, papilledema
Ear & labyrinth disorders
Uncommon
≥ 0.1 % - < 1 %
vertigo
Very rare
< 0.01% and isolated reports
hearing impairment, tinnitus
Cardiac disorders
Very rare
< 0.01% and isolated reports
congestive heart failure, hypertension, pulmonary edema
Vascular disorders
Very rare
< 0.01% and isolated reports
vasculitis
Respiratory, Thoracic and
Very rare
dyspnea, asthma, eosinophilic pneumonitis
Mediastinal disorders
< 0.01% and isolated reports
Gastrointestinal disorders
Common
≥ 1% - < 10%
dyspepsia, nausea, heartburn, abdominal pain
Uncommon
≥ 0.1 % - < 1 %
diarrhea, constipation, vomiting
Rare
≥ 0.01% - < 0.1%
peptic ulcers without or with bleeding or perforation, gastrointestinal bleeding, hematemesis, melena
Very rare
< 0.01% and isolated reports
pancreatitis, colitis, aphthous ulcers, stomatitis, esophagitis, intestinal ulcerations
Hepatobiliary disorders
Very rare
< 0.01% and isolated reports
Hepatitis, icterus
Skin & subcutaneous tissue disorders
Uncommon
≥ 0.1 % - < 1 %
exanthema (rash), pruritus, urticaria
Rare
≥ 0.01% - < 0.1%
angioneurotic edema
Very rare
< 0.01% and isolated reports
alopecia (usually reversible), photosensitivity, porphyria, exudative erythema multiforme, epidermal necrolysis, erythema nodosum, fixed drug eruption, lichen planus, pustular reaction, skin rashes, Systemic Lupus Erythematosus, Stevens-Johnson syndrome, photosensitivity reactions including porphyria cutanea tarda (“pseudoporphyria”) or epidermolysis bullosa
Renal & urinary disorders
Rare
≥ 0.01% - < 0.1%
renal impairment
Very rare
< 0.01% and isolated reports
interstitial nephritis, renal papillary necrosis, nephrotic syndrome, renal failure, renal disease
Pregnancy
Very rare
< 0.01% and isolated reports
Induction of labour
Congenital
Very rare
< 0.01% and isolated reports
Closure of ductus arteriosus, orofacial clefts as an isolated report
Reproductive system and breast disorders
Very rare
< 0.01% and isolated reports
female infertility
General disorders
Rare
≥ 0.01% - < 0.1%
peripheral edema, particular in patients with hypertension or kidney failure, pyrexia
Investigations
Very rare
< 0.01% and isolated reports
raised serum creatinine, abnormal liver function test
Severe allergic ADRs are very rare events, which are more likely to occur in subjects who have experienced allergic reactions previously. In short term use of naproxen sodium occurrence of GI ulcers/bleeding/perforation are rare events.
The adverse drug reactions seen during short term use of naproxen sodium are normally mild and disappear after discontinuing the drug. The most common ADRs for OTC naproxen sodium and/or solely for prescription doses (higher dose and or longer duration) are dizziness, headache, light-headedness, dyspepsia, nausea, heartburn, and abdominal pain. Uncommonly drowsiness, insomnia, and skin rashes are encountered. Peripheral edemas are rare events. Other ADRs are very rare and/or observed through isolated reports only. The adverse events are common to all NSAIDs as a class; there is no adverse event that is specific for naproxen alone.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
During short term use of naproxen sodium, interactions with the following medications could be of clinical significance.
9.4 Drug-Drug Interactions
The drugs listed in Table 4 are based on either drug interaction case reports or studies
Table 4 - Established or Potential Drug-Drug Interactions
| Proper Name | Effect | Clinical comment |
|---|---|---|
| Proper Name | Effect | Clinical comment |
| Cyclosporine | cyclosporin concentrations may increase, which could induce nephrotoxicity | These patients should be monitored adequately. |
| Lithium | in some patients lithium concentrations may increase, which could induce nausea, polydipsia, polyuria, tremor, confusion | These patients should be monitored adequately |
| Methotrexate | if weekly methotrexate intake exceeds 15 mg, methotrexate concentrations may increase which could induce blood dyscrasia, nephrotoxicity, mucosal ulcerations | These patients should be monitored adequately |
| NSAIDS | adds to the risk of gastro-intestinal bleeding | Should be avoided; however, effects may be minimised by using the lowest effective dose for the shortest duration necessary. |
| Low dose ASA (81mg to 325mg daily, for cardiovascular protection e.g. ASPIRIN® 81mg) | Can add to the risk of gastro-intestinal bleeding and may attenuate the irreversible platelet inhibition induced by acetylsalicylic acid | These patients should be monitored adequately |
| Anticoagulants | adds to the risk of gastro-intestinal bleeding | These patients should be monitored adequately |
| Glucocorticoids | adds to the risk of gastro-intestinal bleeding | These patients should be monitored adequately |
| Diuretics, antihypertensive drugs including ACE Inhibitors, β blockers | the diuretic and antihypertensive efficacy, particular in patients with pre-existing nephropathy, may be reduced | These patients should be monitored adequately. Concomitant use with diuretics may increase risk of congestive heart failure. |
Low-dose ASPIRIN:
In a recent (2005) American case-control study, labelled, short term use of OTC naproxen or OTC ibuprofen was not associated with GI risk nor was there any detectable interaction with ASA at this dose level; furthermore there was no difference between OTC naproxen or OTC ibuprofen. An increased risk could be attributed with concomitant use of ASA and high dose NSAIDs; however, the numbers of exposed cases were small.
Another recent (2006) American retrospective database study found an odds ratio of 2.07 (1.23 – 3.49) for GI complications with concomitant use of low dose ASA and OTC-dose naproxen; for comparison, this ratio was 3.36 (2.36 – 4.80) in subjects taking OTC-dose ibuprofen and low dose ASA; the corresponding ratio for naproxen as mono-therapy was 1.54 (1.04-2.28) which is not significantly different from the combined therapy. The corresponding ratio for ibuprofen as mono-therapy was 1.38 (1.07-1.78) which is significantly lower than the combined therapy of ibuprofen and low dose ASA therapy.
Due to the nature of the study, information regarding the duration of naproxen and ibuprofen intake could not be collected. The findings are consistent with previous study results indicating increased GI risk in patients taking OTC-NSAIDS for longer terms or prescription NSAIDs while on low dose ASA.
Labelled, short term use of OTC naproxen together with low dose ASA was not associated with a detectable GI-risk; longer term use (mainly >10 days) of NSAIDs in OTC doses and concomitant ASA can increase the relative risk a little, adding however only very little absolute risk.
Naproxen may attenuate the irreversible platelet inhibition induced by acetylsalicylic acid. Clinical pharmacodynamic data suggest that concurrent (same day) naproxen sodium usage for more than one day consecutively inhibits the effect of low-dose acetylsalicylic acid on platelet activity and this inhibition may persist for up to several days after stopping naproxen sodium therapy. The clinical relevance of this interaction is not known. Treatment with naproxen sodium in patients with increased cardiovascular risk may limit the cardiovascular protection of acetylsalicylic acid.
During short term use of naproxen sodium interactions of clinical significance do not seem to be relevant for the following medications: antacids, antidiabetics, hydantoines, probenecid, zidovudine.
9.5 Drug-Food Interactions
The absorption is delayed with a meal. Peak naproxen levels were reached at 1.4 hours on an empty stomach and at 3.7 hours with a meal.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established
9.7 Drug-Laboratory Test Interactions
Naproxen sodium causes transient, dose-dependent modestly increased bleeding times. However, these values often do not exceed the upper limit of the reference range. Naproxen sodium may theoretically interfere with the urinary analyses of 17-ketogenic steroids and 5-hydroxy indoleacetic acid (5 HIAA).
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Naproxen like all other nonsteroidal anti-inflammatory drugs (NSAIDs) is an analgesic, antipyretic and anti-inflammatory medication. MAXIDOL® Liquid Gels works at both the site of pain and centrally. The principle mechanism of action relies on the inhibition of prostaglandin synthesis. Prostaglandins are naturally occurring fatty acids derivates that are widely distributed in the tissues, and are involved in the production of pain, fever and inflammation. NSAIDs inhibit prostaglandin synthesis through inhibition of the cyclo-oxygenase enzymes. The anti-inflammatory and analgesic activity of these drugs is based on the concept that prostaglandins sensitize the tissues to pain- and inflammation-producing mediators and the antipyretic activity is assumed to be due to inhibition of prostaglandin synthesis in the hypothalamus induced by infectious states such as the common cold.
10.2 Pharmacodynamics
In low dose, that is ≤ 660 mg naproxen sodium daily, the analgesic and anti-pyretic activities prevail, while higher doses mostly are necessary for a full anti-inflammatory activity response. Significant naproxen plasma levels and onset of pain relief can be obtained within 20 minutes of intake.
10.3 Pharmacokinetics
Table 5 - Summary of Naproxen sodium’s Pharmacokinetic Parameters in healthy subjects
| Single dose | Cmax | Tmax | t½ (h) | AUC0-∞ | CL | Vd |
| 220 mg | 35 | 18 | 546 | 0.4 | 10.0 | 35 |
| 440 mg | 66 | 18 | 1021 | 0.4 | 10.6 | 66 |
| 2 x 220 mg | 53 | 18.6 | 852 | 0.5 | 14.1 | 53 |
Absorption:
Naproxen sodium promptly dissolves in the gastric juice to sodium and fine particles of naproxen. Naproxen is rapidly and completely absorbed from the gastrointestinal tract. The peak plasma level (Cmax) of 53-66 g/ml is reached approximately 1-1½ hours after intake of 440mg naproxen sodium. For MAXIDOL® Liquid Gels, food delays naproxen absorption. The kinetics is dose linear up to 550 mg naproxen sodium twice daily. Plasma concentrations of un-bound circulating naproxen, the active component, of about 10 ng/ml exert analgesic action and correspond to a total naproxen plasma concentration of 15 μg/ml.
Distribution:
The volume of distribution of naproxen is small, about 0.1 l/kg. Steady-state concentrations are obtained in two days, and no significant accumulation has been observed. More than 99% of the circulating naproxen is albumin-bound.
Metabolism:
Naproxen is either metabolised (cytochrome P450) to 6-0-desmethyl naproxen (6-DMN) and conjugated to glucuronides or left un-metabolised. Naproxen does not induce metabolizing enzymes.
Elimination:
Naproxen and its metabolites are primarily excreted via the kidneys (>95%). The elimination half-life of naproxen is about 14 hours. The rate of excretion has been found to coincide closely with the rate of drug disappearance from plasma.
Special Populations and Conditions
- Geriatrics: There is no evidence of differential metabolism or excretion in the elderly.
- Sex: There is no evidence of differential metabolism or excretion between genders.
- Hepatic Insufficiency: In case of severe hepatic insufficiency circulating albumin is decreased giving rise to increased fractions of free and unbound naproxen.
- Renal Insufficiency: In case of severe renal insufficiency protein binding is lower giving rise to increased fractions of free and unbound naproxen. In patients with severely reduced glomerular filtration, the rate of urinary excretion may be reduced. Naproxen, in contrast to its non-active metabolite 6-DMN, is not cleared from the body during haemodialysis.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15 -25°C.
12 SPECIAL HANDLING INSTRUCTIONS
No special requirements
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name:
Naproxen sodium
Chemical name:
2-Napthaleneacetic acid, 6-methoxy –α -methyl-, sodium salt, (-)
Molecular formula and molecular mass:
C14H13NaO3, 252.24
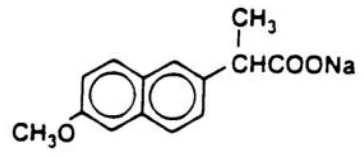
Structural formula:
Physicochemical properties:
Naproxen sodium is a white to creamy white, crystalline solid, freely soluble in water with a melting point of about 255°C with decomposition.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The published trials regarding the efficacy of naproxen sodium consist of 4 studies; three dental extraction trials and 1 trial evaluating the efficacy for short term treatment of knee osteoarthritis.
Table 6 - Summary of patient demographics for Published clinical trials
| Study Ref. Indication | Trial design & Indication | Duration | Dose (mg) Naproxen sodium & Comparator | Study subjects (n) | Mean age (Range) | Sex |
Kiersch 1993 | DB, R, PC, SD Extraction of 1-2 molars | 12 hours | Naproxen sodium 220 mg, Advil 200 mg Placebo | 203 healthy subjects | 25 (7) | 90/113 |
Fricke 1993 | DB, R, PC, SD Extraction of 3-4 molars | 12 hours | Naproxen sodium 440 mg, Advil 400 mg Placebo | 201 healthy subjects | 24 (7) | 77/124 |
| Kiersch 1994 | DB, R, PC, SD Extraction of 3-4 molars | 12 hours | Naproxen sodium 440 mg, Tylenol Extra Strength 1000 mg, Placebo | 226 healthy subjects | 24 (5) | 102/124 |
Schiff 2004 | DB, R, PC, MD Pain and stiffness of knee osteoarthritis | 7 days | Naproxen sodium 440 mg daily (220 mg morning & evening) Advil 1200 mg daily (400 mg TID) placebo | 198 patients, ≥ 65 years knee osteoarthritis | 72 (5) | 75/123 |
The dental study population consisted of young, healthy subjects that required extraction of 1 - 4 molars. The knee osteoarthritis (OA) patients were in good general health, of both sexes and any race and had a mean age of 72 years. The diagnosis was verified by standard radiographic criteria applicable for OA stage I-III. All patients had episodic flare ups of OA with at least moderate pain.
14.2 Study Results
Table 7 - Overview of Published Clinical Trial Results
| Study | Endpoints | Associated Values and statistical significance for Naproxen sodium (N), Comparator (C) and Placebo (P) | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study | Endpoints | Associated Values and statistical significance for Naproxen sodium (N), Comparator (C) and Placebo (P) | ||||||||||||||||||
| Naproxen Sodium | Comparator | Placebo | N vs C | N vs P | C vs P | |||||||||||||||
| Naproxen Sodium | Comparator | Placebo | N vs C | N vs P | C vs P | |||||||||||||||
Kiersch 1993 | Pain relief up to 12 hours TOTPAR1 Onset of pain relief (median) Time to re-medication (median) Re-medication % |
9.4 h 51% | 17.8 2 h 8.0 h 63 % | 6.0 > 12 h 2 h 90 % | NS NS NS NS | < 0.001 < 0.001 < 0.001 < 0.001 | < 0.001 < 0.001 < 0.001 < 0.001 | |||||||||||||
Fricke 1993 | Pain relief up to 12 hours TOTPAR1 Onset of pain relief (median) Time to re-medication (median) Re-medication % | 19.6 0.7 h 7 h 64 % | 15.8 0.7 h 6 h 78% | 3.5 > 12 h 1.1 h 95% | NS NS NS (=0.056) | < 0.001 < 0.001 < 0.001 < 0.001 | < 0.001 < 0.001 < 0.001 < 0.001 | |||||||||||||
Kiersch 1994 | Pain relief up to 12 hours TOTPAR1 Onset of pain relief (median) Time to re-medication (median) Re-medication % | 19.1 2 h 9.9 h 56 % | 8.3 2 h 3.1 h 90 % | 5.7 > 12 h 2.0 h 90 % | < 0.001 NS < 0.001 < 0.001 | < 0.001 < 0.001 < 0.001 < 0.001 | NS < 0.001 NS NS | |||||||||||||
Schiff 2004 | Symptom improvement on day 7: | |||||||||||||||||||
| 0.8 | 0.8 | 0.5 | NS | < 0.05 | NS | ||||||||||||||
| 0.9 | 0.9 | 0.6 | NS | < 0.05 | NS | ||||||||||||||
| 1.2 | 1.0 | 0.7 | NS | (=0.064) | NS | ||||||||||||||
| 0.9 | 0.9 | 0.4 | NS | < 0.05 | NS | ||||||||||||||
| 1.0 | 1.0 | 0.4 | NS | < 0.01 | < 0.01 | ||||||||||||||
| 1.0 | 0.8 | 0.5 | NS | < 0.05 | NS | ||||||||||||||
| 2.3 s | 1.9 s | 1.0 s | NS | < 0.05 | NS | ||||||||||||||
s = second(s)
h = hour(s)
1 Total pain relief (TOTPAR) is an integrated (summary) pain score where pain relief is assessed hourly and represented on a 5-point scale and summed over a period of time (i.e.12 hours). The 5-point scale consists of a zero-score representing no pain relief, 1= a little, 2=some, 3 = a lot and 4=complete pain relief
The dental pain model, i.e. tooth extraction model, is accepted as the model of choice to establish analgesic efficacy and the results can be extrapolated to other pain states relevant for OTC medication. The studies demonstrate that naproxen sodium provides fast and effective pain relief.
For the short-term treatment of pain or stiffness of rheumatic or non-serious arthritic conditions naproxen sodium provides clear relief of such states. Naproxen sodium is clinically proven to relieve arthritis pain. In the comparison naproxen sodium /placebo and Advil®/placebo, naproxen sodium was superior with respect to alleviating pain experienced at night and stiffness after rest.
In dysmenorrhea naproxen sodium compared to placebo demonstrated a significant superiority with respect to total pain relief over 12 hours.
The MAXIDOL® Liquid Gels safety data is derived from clinical trials and post-marketing experience. MAXIDOL® Liquid Gels is as safe on the stomach as Tylenol Extra Strength 500 mg and Advil 200mg if the maximum daily dose and recommended length of use for each product is not exceeded. In the clinical trials the safety profile was comparable to that of Advil, Tylenol Extra Strength and placebo; the most common reactions were GI upset and dizziness, occurring in a small percentage of subjects, with no difference between placebo and active treatments. Serious adverse reactions, like gastrointestinal bleeding or anaphylactic shock, were very rare events (< 0.01%) and occurred in the same degree in MAXIDOL® Liquid Gels and Advil as well as Tylenol Extra Strength treated subjects.
Overall, MAXIDOL® Liquid Gels is an effective analgesic suitable for the treatment of common ailments relevant for self-medication.
14.3 Comparative Bioavailability Studies
A single dose, 2-way comparative bioavailability study of 2 x 220mg naproxen sodium tablets and 2 x 220mg MAXIDOL® Liquid Gels in 26 healthy male and female volunteers was conducted under fasted conditions. A summary of the comparative bioavailability data is presented below
Naproxen (2 x 220mg naproxen sodium)a From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | MAXIDOL® Liquid Gels (Capsules) 220 mg | Naproxen sodium (Tablets) 220mg† | % Ratio of Geometric Means | Confidence Intervala |
AUCT † (ng.hr/mL) | 789789.9 800415.7 (16.7) | 778610.6 795708.5 (21.4) | 101.4 | 97.9 – 105.1 |
AUCI (ng.hr/mL) | 838635.9 851570.5 (18.0) | 835610.5 854934.0 (22.1) | 100.4 | 97.9 – 103.0 |
Cmax (ng/mL) | 52342.3 53378.26 (19.5) | 57339.3 57818.3 (12.6) | 91.3 | 86.3 – 96.5 |
Tmax€ (h) | 1.62, (72.8) | 1.10 (55.0) | Not applicable | Not applicable |
T½€ (h) | 18.60 (14.0) | 18.55 (17.9) | Not applicable | Not applicable |
* MAXIDOL® Liquid Gels 220mg, liquid filled soft gelatin capsules
† Naproxen sodium Tablets 220mg
€ Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
The oral LD50 of the drug is 543 mg/kg in rats, 1234 mg/kg in mice, 4110 mg/kg in hamsters and greater than 1000 mg/kg in dogs. No carcinogenic or embryotoxic properties were detected and since the launch of naproxen in the beginning of the 1970's no experience or information has been obtained that could indicate such properties.
Subacute and Chronic Oral Studies
In subacute and chronic oral studies with naproxen in a variety of species, the principle pathologic effect was gastrointestinal irritation and ulceration. The lesions seen were predominantly in the small intestine and ranged from hyperaemia to perforation and peritonitis. Similar results have been reported with other non-steroidal anti-inflammatory agents such as ibuprofen, phenylbutazone, ASA, indomethacin and mefenamic acid.
Nephropathy was seen occasionally in acute and subacute studies in rats, mice and rabbits at high-dose levels of naproxen, but not in rhesus monkeys, miniature pigs or dogs. In the affected species the pathologic changes occurred in the cortex and papilla. Some rats examined 14 days after single oral doses of 230 mg/kg or more of naproxen evidenced necrotic areas of cortical and papillary tissue. Tubular dilation (ectasia) occurred in rabbits dosed orally for 14 days with 200mg/kg/day or more of naproxen. An examination of unfixed renal tissue from rabbits so-treated was conducted and revealed the presence of diffraction patterns similar to that of crystalline naproxen. This suggests that the ectasia observed was a physical response to deposition of excreted naproxen within the tubules.
In mice given oral doses of 120 mg/kg/day or more of naproxen for 6 months, the kidneys were characterized by a low but non-dosage-related incidence of cortical sclerosis and papillary tip necrosis. Chronic administration of high doses of naproxen to mice appears to be associated with exacerbation of spontaneous murine nephropathy.
Rhesus monkeys were administered daily doses of 7, 20, or 60 mg/kg and the monkeys received these daily doses for the next six months. No evidence of drug-related pathology was seen in this study. In a 1-year study in rhesus monkeys at daily doses of 100, 140, 180 mg/kg renal lesions consistent with those described for analgesic nephropathy were observed. The severity of the lesions was generally dose related.
A similar catalogue of renal responses has been reported in the laboratory animals treated with a variety of non-steroidal anti-inflammatory agents.
A wide range of susceptibility to gastrointestinal lesions from administration of naproxen was evident in the various species tested. For example, 30mg/kg/day was tolerated well by rats for 90 days, but the same dose was ulcerogenic when administered for 6 months. Rhesus monkeys and miniature swine exhibited no significant pathology when dosed with naproxen at 45 mg/kg/day for 30 days. This dose of naproxen was also tolerated by miniature swine without obvious evidence of adverse effects when administered daily for 1 year. In rhesus monkeys doses as high as 120 mg/kg/day (60 mg/kg b.i.d.) for 6 months produced no clinical or histopathological evidence of gastrointestinal irritation although occult blood in the feces occurred more frequently in these animals compared to controls. Daily administration of naproxen to rhesus monkeys for one year was associated with mild gastric irritation in a few animals receiving 100, 140 or 180 mg/kg. In rabbits the maximum tolerated repeated oral dose is 80 to 100 mg/kg/day. Mice survived oral daily doses of 240 mg/kg/day for 6 months. In dogs, on the other hand, 5.0 mg/kg/day approaches the maximum tolerated dose. This peculiar canine susceptibility to gastrointestinal effects of non-steroidal anti-inflammatory agents has also been shown with indomethacin and ibuprofen.
In dogs’ naproxen exhibits a considerably longer plasma half-life than it does in rats, guinea pigs; miniature swine, monkeys, and man. The same observation has been made with ibuprofen in dogs compared to rats and man. In addition, in the species listed, only the dog excretes significant amounts of administered naproxen in the feces (50%). In the rat, guinea pigs, miniature swine, monkey and man, 86-90% of the administered drug is excreted in the urine. The suggested enteroheptic circulation of naproxen in the dog (as judged by fecal excretion) most likely is a major factor in the susceptibility of the dog to gastrointestinal irritation by this compound.
In subacute and chronic toxicity studies, other pathological changes were often seen which were considered to be clearly secondary to the effects of naproxen on the gastrointestinal tract. These consisted of peritoneal inflammation and adhesions, mesenteric lymphadenopathy, decreased haemoglobin and hematocrit levels, leucocytosis, evidence of stimulated hematopoeisis and elevated plasma glutamic oxaloacetic transaminase.
As noted above, gastrointestinal pathology in laboratory animals is a finding common to non-steroidal anti-inflammatory agents.
Ophthalmic examinations were made in the two year rat study and the one year monkey study. No eye changes considered to be drug related were noted except for the observation of pale irides in the rats. This was secondary to anemia as a result of gastrointestinal blood loss and did not represent a toxic effect of naproxen on the eye.
Plasma levels of naproxen were measured in monkeys dosed for one year with 100, 140 or 180 mg/kg/day naproxen. Plasma levels after 1 week of dosing were not significantly different form those after 12 months of dosing. As judged by these results there was no evidence of tachyphylaxis or accumulation over the 1 year dosing period.
Moderate weight loss of the male secondary sex glands occurred in some studies in naproxen-treated rats and dogs. Histopathologically the affected glands in some instances exhibited atrophic and/or hypoplastic changes characterized by decreased secretory material. A possible estrogenic action of naproxen as a causative factor seems highly unlikely since in standard bioassay procedures the drug exhibited no estrogenic activity.
Daily doses of naproxen as high as 30 mg/kg administered for 60 days before mating had no effect on fertility and reproductive performance of male rats. These results reflect the physiological integrity of the entire male reproductive apparatus after administration of naproxen throughout the spermatogenic cycle.
Teratology
In embryotoxicity studies no skeletal or visceral anomalies or pathologic changes were induced in the fetuses of pregnant rats and rabbits treated during organogenesis with daily oral doses of naproxen up to 20 mg/kg nor in mice similarly treated with 30 or 50 mg/kg. In these studies there were also no significant differences from controls in the number of live fetuses, resorptions, fetal weights or ano-genital distances. In another mouse study no malformations were observed with administration of 60 or 120 mg/kg of naproxen although there was a slight reduction in numbers of live fetuses in both dose groups and in fetal body weight in the high dose group.
Reproductive Studies
Daily oral administration of 15, 30 or 60 mg/kg of naproxen to female rabbits from 2 weeks before mating until day 20 of pregnancy did not affect fertility, gestation, or the numbers of live fetuses.
In a peri- and post-natal study in rats, oral doses of naproxen up to 20 mg/kg administered daily during the last part of pregnancy through weaning did not result in adverse effects in viability of pups, lactation index, sex ratio or weight gain of offspring. However, there was a slight increase in gestation length at the 10 and 20 mg/kg dose levels; and, at the 10 mg/kg dose level, there was a significant increase in stillbirths.
The mechanism of this phenomenon in the rats is not entirely clear at present. It is possible that difficulties in delivery in naproxen-treated rats reflect a general underlying maternal debility induced by increased susceptibility of the pregnant animals to gastrointestinal ulceration and subsequent peritonitis. Such an observation has been reported with ibuprofen. Pregnant animals were reported to be 9 times more susceptible to the ulcerogenic effects of that compound than were non-pregnant animals. Similarly, with naproxen, gastrointestinal lesions in non-pregnant paired drug-treated controls were found to occur less frequently and were less extensive than those in pregnant rates treated daily from day 15 of pregnancy through term.
More recent evidence, however, suggests that inhibition of prostaglandin synthesis by non-steroidal anti-inflammatory compounds may be related to decreased uterine contractility. Thus, the onset of labour in a rat model system can be delayed with naproxen administration without causing maternal or fetal deaths in excess of that seen in controls. Since it has been shown that naproxen inhibits prostaglandin synthesis in vitro, it has been suggested that the effects of naproxen on uterine contractility are mediated through that mechanism.
Maternal and fetal deaths seen in naproxen-treated rats were, therefore, apparently related to dystocia rather than to a direct toxic effect of the compound. Naproxen is not unique in this regard since comparable results were obtained in the rat with other commonly used non-steroidal anti-inflammatory agents (ASA, indomethacin, mefenamic acid and phenylbutazone). Similar results have been suggested in reports of other animal studies with ibuprofen.
In a fertility and reproduction study in mice, the dams were dosed daily with 12, 36 or 108 mg/kg from 14 days prior to mating through weaning. At the highest dose level, there was an increase in maternal deaths which was reflected in decreased 21 day survival and lactation indices. There were no other changes in the parameters examined. In a similar study in rats, daily doses were 2, 10 or 20 mg/kg from 14 days before mating through weaning. Other than decreased survival to weaning which appeared due to poor maternal care in pups born to high dose dams, there were no differences between control and treated groups. One mid and one high dose dam died during labour due to delayed parturition.
The toxicity of naproxen in juvenile animals was compared to that in adult animals. The results of single oral dose LD50 studies in weanling rats and mice, run simultaneously with studies in adult animals, revealed no significant differences in the values obtained with mature and immature animals of both species.
An additional study with juvenile mice consisted of two parts. Weaning animals were treated daily for one month wit a pediatric formulation of naproxen. At the end of the treatment period a portion of the animals were examined for pathologic changes. The remaining animals were allowed to reach maturity and breed.
The usual gastroenteropathy characteristic for non-steroidal anti-inflammatory agents was observed in some high dose (135 mg/kg) mice. Naproxen administration for the first post-weaning month of life did not compromise in any way the later fertility or reproductive capacity of mice so treated.
Mutagenicity
Mutagenicity tests were performed with naproxen using 5 strains of bacteria and one of yeast. The test was carried out with and without mammalian microsomal activation. Naproxen was also tested in the mouse lymphoma assay. Naproxen was not mutagenic.
Carcinogenicity
To evaluate the carcinogenic potential of naproxen, the compound was administered in the feed to rats for up to 2 years. Naproxen did not reveal any carcinogenic potential in rats.