


Product Monograph - Metoclopramide Hydrochloride Injection Hs
ACTION AND CLINICAL PHARMACOLOGY:
Metoclopramide is a benzamide derivative structurally related to procainamide and sulpiride. It has a dopamine antagonist activity with selective affinity for D2 (nonadenylate cyclase linked)
receptors. The behavioral, motor and neuroendocrine effects of metoclopramide have been suggested to be due to its antidopaminergic activity.
Metoclopramide has antiemetic properties which are believed to result from its action on the chemoreceptor trigger zone. A peripheral mechanism of action may also be involved.
Metoclopramide raises resting pressure in the lower esophageal sphincter and the gastric fundus, and gives rise to an increase in the amplitude of peristaltic movements in the esophagus, gastric antrum and small intestine. As a consequence, esophageal clearance is hastened, gastric emptying accelerated and transit time through the small bowel shortened. These effects are blocked by atropine and opioids but not by vagotomy.
Metoclopramide elevates serum prolactin and causes transient increases in circulating aldosterone levels. These effects are thought to be due to blockade of dopamine receptors at the pituitary and adrenocortical cellular level.
Following intravenous administration, peak plasma levels occur within minutes. The terminal halflife is approximately 3 hours but this is prolonged in patients with impaired renal function and may reach 14 hours or more. About 20% of the drug is eliminated unchanged in the urine, and 30 – 40% is eliminated as the sulfate conjugate. Metoclopramide is 15 – 20% bound to the plasma proteins.
In some patients, metoclopramide may produce drowsiness, sedation, glactorrhea, menstrual disorders and extrapyramidal reactions. Extrapyramidal symptoms are more frequent at higher than recommended doses, but may occur with therapeutic doses, particularly in children and in patients with impaired renal or hepatic function. Tardive dyskinesia has been reported following discontinuation of longterm treatment with Metoclopramide.
INDICATIONS AND CLINICAL USE:
Metoclopramide Hydrochloride Injection is indicated in the prophylaxis of vomiting induced by cancer chemotherapeutic regimens that include cisplatin as a component.
Metoclopramide Hydrochloride Injection has been found useful as an adjunct to facilitate small bowel intubation.
CONTRAINDICATIONS:
Metoclopramide Hydrochloride Injection is contraindicated whenever stimulation of the gastrointestinal motility may be dangerous, i.e. in the presence of gastrointestinal hemorrhage, perforation or mechanical obstruction. Metoclopramide Hydrochloride Injection should not be used in patients with known sensitivity or intolerance to the drug. Metoclopramide should not be used in epileptics or patients receiving other drugs which are likely to cause extrapyramidal reactions, since the frequency and severity of seizures or extrapyramidal reactions may be increased.
WARNINGS:
Tardive dyskinesia has been reported to occur during long-term treatment (over 12 weeks)
and following discontinuation of long-term treatment with metoclopramide.
The risk of developing tardive dyskinesia increases with the duration of treatment and the total cumulative dose. The elderly, especially elderly women are at increased risk of developing this condition.
Metoclopramide elevates prolactin levels; the elevation persists during the chronic administration. Tissue culture experiments demonstrate that about one third of human breast cancers are prolactindependent in vitro, a factor of potential importance if the prescription of metoclopramide is contemplated in a patient with previously detected breast cancer. Even though disturbances such as amenorrhea, galactorrhea, impotence and gynecomastia have been reported with prolactinelevating drugs, the clinical significance of elevated serum prolactin levels is unknown for the most patients. After chronic administration of prolactin stimulating neuroleptic drugs, an increase in mammary neoplasms has been detected in rodents. However, neither epidemiological studies nor clinical studies conducted to date, have shown an association between chronic administration of these drugs and mammary tumorigenesis. The available evidence is considered to be too limited to be conclusive at this time.
Tardive Dyskinesia:
Tardive dyskinesia may develop in patients treated with metoclopramide. Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is not possible to predict which patients are likely to develop the syndrome.
Both risk of developing the syndrome and the likelihood that it will become irreversible are believed to increase with the duration of treatment and the total cumulative dose.
Less commonly, the syndrome can develop after relatively brief treatment periods at low doses;
in these cases, symptoms appear more likely to be reversible. Prolonged treatment (greater than
12 weeks) with metoclopramide should be avoided unless therapeutic benefit is thought to outweigh the risks to the patient developing tardive dyskinesia.
There is no known treatment for established cases of tardive dyskinesia although the syndrome may remit, partially or completely, within several weeks to months after metoclopramide has been withdrawn.
Metoclopramide itself, however, may suppress (or partially suppress) the signs of tardive dyskinesia, thereby masking the underlying disease process. The effect of this symptomatic suppression upon the long term course of the syndrome is unknown.
Other Extrapyramidial Symptoms (EPS):
Acute Dystonic Reactions
Acute dystonic reactions occur in approximately 1 in 500 patients treated with the usual adult dosages of 30-40 mg/day of metoclopramide. These usually are seen during the first 24-48 hours of treatment with metoclopramide, occur more frequently in pediatric patients and adult patients less than 30 years of age and are even more frequent at the highter doses used in prophylazis of vomiting due to cancer chemotherapy. These symptoms may include involuntary movements of limbs and facial grimacing, torticollis, oculogyric crisis, rhythemic protrusion of tongue, bulbar type of speech, trismus, or dystonic reactions resembling tetanus. Rarely, dystonic reactions may present as stridor and dyspnea, possibly due to laryngospasm. If these symptoms should occur, immediate treatment by health care professionals should be initiated to treat this condition.
Parkinsonian-like Symptoms
Parkinsoniam-like symptoms, including bradykinesia, tremor, cogwheel rigidity, or mask-like facies, have occurred more commonly within the first 6 months after beginning treatment with metoclopramide, but occasionally after longer periods. These symptoms generally subside within 2-3 months following discontinuance of metoclopramide. Patients with preexisting
Parkinson’s disease should be given metoclopramide cautiously, if at all, since such patients may experience exacerbation of parkinsonian symptoms when taking metoclopramide.
Neuroleptic Malignant syndrome (NMS):
There have been rare reports of an uncommon but potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) associated with metoclopramide.
Clinical manifestations of NMS include hyperthermia, muscle rigidity, altered consciousness, and evidence of autonomic instability (irregular pulse of blood pressure, tachycardia, diaphoresis and cardiac arrhythmias). When these symptoms occur, treatment with metoclopramide and other drugs not essential to concurrent therapy should be discontinued immediately. Intensive symptomatic treatment and medical monitoring should be initiated.
Depression:
Mental depression has occurred in patients with and without prior history of depression.
Symptoms have ranged from mild to severe and have included suicidal ideation and suicide.
Metoclopramide should be given to patients with a prior history of depression only if th expected benefits outweigh the potential risks.
Use in Pregnancy:
The safe use of metoclopramide in pregnancy has not been established. Therefore, metoclopramide should not be used in pregnant women unless in the opinion of the physician, the expected benefits outweigh the potential risks to the fetus.
Use in Children:
The daily dose should not exceed 0.5 mg/kg, since with higher doses, extrapyramidal symptoms frequently occur.
PRECAUTIONS:
General:
The recommended dosage of metoclopramide should usually not be exceeded since a further increase in dosage will not produce a corresponding increase in clinical response.
Patients with Special Diseases and Conditions:
Metoclopramide Hydrochloride Injection should not be used in patients with extrapyramidal symptoms or epilepsy unless the expected benefits outweigh the risks of increased frequency and severity of extrapyramidal reactions or seizures.
In patients with pheochromocytoma, I.V. metoclopramide may cause a hypertensive crisis.
Administer phentolamine by slow I.V. injection to control this effect.
Dosage may need to be reduced in patients with impaired hepatic or renal function (see
DOSAGE AND ADMINISTRATION).
Drug Interactions:
Metoclopramide may reduce the absorption of drugs such as digoxin from the stomach, and accelerate the absorption of drugs such as acetaminophen, ethanol, levodopa and tetrayclines from the small bowel.
Anticholinergic drugs antagonize the effects of metoclopramide on gastrointestinal motility.
Metoclopramide should not be used in conjunction with neuroleptic or ganglioplegic drugs as potentiation of effects may occur. The sedative effects of metoclopramide may be potentiated by narcotics, sedatives, anxiolytics, and hypnotics.
Caution should be exercised when metoclopramide is administered in combination with MAO inhibitor. In an animal study, pretreatment with a MAO inhibitor increased the toxicity of intravenous metoclopramide (see TOXICOLOGY).
In patients with pheochromocytoma, I.V. metoclopramide may cause a hypertensive crisis.
Administer phentolamine by slow I.V. injection to control this effect.
ADVERSE REACTIONS:
Drowsiness, fatigue and lassitude occur in approximately 10% of patients at the normal recommended dosage. Less frequent adverse reactions, occurring in approximately 5% of patients are headache, dizziness, insomnia and bowel disturbances. Menstrual disorders and galactorrhea have also been reported.
The more serious adverse reactions associated with the use of metoclopramide are Parkinsonism and/or other extrapyramidal reactions. These consist often of a feeling of restlessness, facial spasms, involuntary movements, and in some cases, muscular twitching, torticollis, trismus, opisthotonos and oculogyric crisis. Dystonic reactions resembling tetanus have been reported.
Extrapyramidal side effects appear to occur more frequently at higher than the normal recommended dosage.
In general, the incidence of adverse reactions correlates with the dose and duration of metoclopramide administration. Tardive dyskinesia, which in some cases appears to be irreversible, has been reported during long-term treatment (over 12 weeks) and following discontinuation of long-term metoclopramide therapy. Therefore, prolonged treatment with metoclopramide should be avoided. Tardive dyskinesia is characterized most frequently by involuntary movements of the tongue, face, mouth or jaw, and sometimes by involuntary movements of the trunk and/or extremities.
SYMPTOMS AND TREATMENT OF OVERDOSAGE:
For management of suspected drug overdose, contact your regional Poison Control Centre.
The most frequently reported adverse reactions to overdosage are the extrapyramidal reactions described in the preceding section. Management of overdosage consists of close observation and supportive therapy. Extrapyramidal reactions have been effectively controlled by antiparkinson and antihistamine /anticholinergic drugs such as diphenhydramine hydrochloride.
Hemodialysis removes relatively little metoclopramide, probably because of the small amount of the drug in blood relative to tissues. Similarly, continuous ambulatory peritoneal dialysis does not remove significant amounts of drug. It is unlikely that dosage would need to be adjusted to compensate for loss through dialysis. Dialysis is not likely to be an effective method of drug removal in overdose situations.
Methemoglobinemia has occurred in premature and full-term neonates who were given overdoses of metoclopramide (1 - 4 mg/kg/day orally, intramuscularly or intravenously for 1 – 3 or more days). Methemoglobinemia has not been reported in neonates treated with
0.5mg/kg/day in divided doses. Methemoglobinemia can be reversed by the intravenous administration of methylene blue.
DOSAGE AND ADMINISTRATION:
NOTE: EXCEPT FOR THE PROPHYLAXIS OF CISPLATIN-INDUCED VOMITING,
THE TOTAL DAILY DOSAGE MUST NOT EXCEED 0.5 mg/kg BODY WEIGHT.
For the Prophylaxis of Cisplatin-Induced Vomiting:
Adults: For the patients treated with cisplatin in doses up to and including 100 mg/m²,
Metoclopramide Hydrochloride Injection may be administered by infusion after dilution (See
INTRAVENOUS INFUSION) in single doses of 1 mg/kg of body weight. For patients treated with cisplatin in doses greater than 100 mg/m², the single recommended dose may be increased to 2 mg/kg body weight administered by infusion.
Infuse slowly over a 15 minute period and repeat the dose every 2 hours for two doses, then every 3 hours for three doses. (When the 2 mg/kg dose is used, the last dose may be omitted).
For Small Bowel Intubations:
Adults: 10 mg by I.V. route (slowly) preferably at the time when the tip of the tube reaches the pyloric region.
Children: Single dose of 100 mcg/kg I.V. slowly.
Use in Patients with Renal or Hepatic Impairment:
Since metoclopramide is excreted principally through the kidneys, in those patients whose creatinine clearance is below 40 mL/min., therapy should be initiated at approximately one-half the recommended dosage. Depending upon clinical efficacy and safety considerations, the dosage may be increased or decreased as appropriate.
See SYMPTOMS AND TREATMENT OF OVERDOSAGE section for information regarding dialysis.
Metoclopramide undergoes minimal hepatic metabolism, except for simple conjugation. Its safe use has been described in patients with advanced liver disease whose renal function was normal.
PHARMACEUTICAL INFORMATION
DRUG SUBSTANCE:
Proper Name: Metoclopramide hydrochloride
Chemical Name: Benzamide, 4-amino-5chloro-N-[2-(diethylamino)ethyl]-2- methoxy-, monohydrochloride, monohydrate.
Structural Formula:
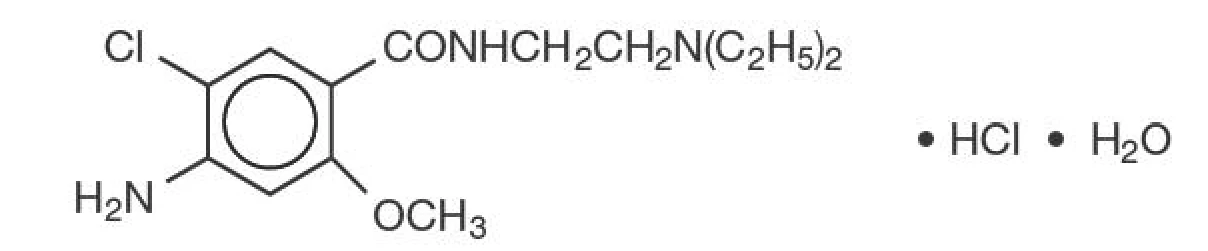
Molecular Weight: 354.3
DESCRIPTION:
Metoclopramide hydrochloride is a white or almost white, odourless crystalline powder. It is soluble in water (1 in 0.7), alcohol (1 in 3) and chloroform (1 in 55) and practically indoluble in ether. A 10% solution in water has a pH of 4.5 to 6.5. The melting point is about 185⁰C.
COMPOSTION:
Metoclopramide Hydrochloride Injection is a sterile solution in single dose glass vials. Each mL of the Injection contains metoclopramide hydrochloride 5 mg, with sodium chloride 8.5 mg in
Water for Injection; sodium hydroxide or hydrochloric acid may be added as pH adjuster.
STABILITY AND STORAGE RECOMMENDATIONS:
Metoclopramide Hydrochloride Injection should be stored at 15ºC 25ºC, protected from light.
INTRAVENOUS INFUSION:
The 10 mL single dose vial containing 50 mg (5 mg/mL) of metoclopramide hydrochloride and the 30 mL single dose vial containing 150 mg (5 mg/mL) of metoclopramide hydrochloride is intended for intravenous infusion after dilution. Dilute the calculated amount of Metoclopramide
Hydrochloride Injection 5 mg/mL with one of the following intravenous solutions:
Dextrose Injection 5%
Sodium Chloride Injection 0.9%
Dextrose 4% in Sodium Chloride 0.18% Injection
Ringer:s Injection
Compound Sodium Lactate Injection B.P. (Hartmann:s Solution)
Dilutions of Metoclopramide Hydrochloride injection prepared in PVC infusion bags, may be stored up to 24 hours at room temperature. Unused portions should be discarded after this time, in order to avoid the risk of microbial contamination.
Warning: As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discolouration and leakage prior to administration, whenever solution and container permit. Solutions showing haziness, particulate matter, precipitate, discolouration or leakage should not be used.
AVAILABILITY:
Metoclopramide Hydrochloride Injection is a sterile solution in single dose glass vials. Each mL of the Injection contains metoclopramide hydrochloride 5 mg (equivalent to metoclopramide 4.4:
mg), with sodium chloride 8.5 mg in Water for Injection; sodium hydroxide or hydrochloric acid may be added as pH adjuster. Metoclopramide Hydrochloride Injection 5 mg/mL is supplied in 2 mL, 5 mL, 10 mL and 30 mL single dose vials.
PHARMACOLOGY:
Metoclopramide is a dopamine antagonist which appears to block preferentially the D-2
(nonadenylate cyclase linked) receptors.
In the rat, metoclopramide antagonizes apomorphine-induced stereotypy, causes catalepsy, elevates prolactin, aldosterone and plasma renin levels, and enhances dopamine turnover in mesolimbic and striatal structures.
Metoclopramide antagonizes in vitro the dopamine-induced inhibition of potassium-evoked
3Hacetylcholine release in striatal structures. In the rat, parenteral administration of metoclopramide decreases striatal acetylcholine levels. The extrapyramidal side effects caused by metoclopramide and other neuroleptics are believed to be a consequence of this action.
Oral administration of metoclopramide to rats for 39 days induced behavioural supersensitivity to apomorphine and enhanced specific binding of 3H-spiroperidol to striatal membranes. These effects are induced by other neuroleptic drugs, and are associated with a potential to elicit tardive dyskinesia in man.
In experimental animals, metoclopramide enhances gastrointestinal motility, increasing both resting muscle tension and the amplitude of peristaltic movements.
Metoclopramide is virtually inactive as an antagonist at the D-1 (adenylate cyclase linked)
dopamine receptors, and is without potency in displacing radiolabelled ligands in receptor models designed to evaluate antipsychotic potential.
In the rat, intraventricular administration of metoclopramide and spiroperidol produce comparable dose-dependent depression of responding in electrical self-stimulation procedures.
When administered by the intraperitoneal route, the potency of metoclopramide, but not that of spiroperidol, is decreased by a factor of 30.
TOXICOLOGY:
Acute Toxicity
Acute toxicity by the oral route is low in most animal species, though metoclopramide is markedly more toxic when given intravenously. (see table).
TABLE
Acute toxicity of metoclopramide in various animal species.
| Species | Route of administration | LD 50 mg/kg |
| Mouse | Intravenous | 63 |
| Mouse | Intramuscular | 306 |
| Rat | Intramuscular | 325 |
| Rat | Subcutaneous | 540 |
| Rat | Intraperitoneal | 112 |
| Rat | Oral | 401 to 740 |
| Weanling rat | Oral | 560 |
| Rabbit | Intravenous | 22 |
| Rabbit Oral | Oral | 870 |
| Dog | Intravenous | 40 |
Subacute toxicity
Dogs receiving up to 80 mg/kg metoclopramide for 5 days a week over 16 weeks showed marked behavioural changes only at higher doses, characterized by fine tremors, subdued behavior, anorexia and miosis. These signs disappeared during the weekend withdrawal of the drug.
In studies in rabbits and dogs, animals showed signs of fine tremors, hypoactivity, miosis, panting and bizarre positions following intravenous or intramuscular doses of up to 20 mg/kg metoclopramide for 4 to 5 weeks. These signs appeared and disappeared more rapidly with intravenous than with intramuscular administration, but there were no other signs of drug-related effects and no hematological, biochemical or histopathological changes.
Chronic Toxicity
There were no abnormal hematological, biochemical or histopathological changes in rats receiving daily oral doses of up to 40 mg/kg or 100 mg/kg metoclopramide for 77 weeks or 3 to
6 months respectively. A similar regimen of 300 mg/kg slowed growth and weight gain in some animals, while 600 mg/kg resulted in the death of the majority of animals within the dosage period.
Dogs receiving up to 40 mg/kg daily for 5 days a week showed behavioural changes like those observed in the sub-acute studies, to which tolerance did not develop over 54 weeks. There were no significant alterations in liver, renal or cardiovascular functions, and no hematological, biochemical or histopathological abnormalities.
Teratology and Reproduction Studies
There were no abnormalities or drug-related effects on fetal size and weight, in the offspring of mice, rats and rabbits treated with up to 20 mg/kg metoclopramide daily by the oral, subcutaneous or intravenous routes and at various stages of gestation. Young born to treated animals grew normally, and autopsy at 6 to 10 weeks revealed no abnormalities.
Interaction with Nialamide
Nialamide, a MAO inhibitor, did not potentiate the acute lethality of metoclopramide in rats.
These findings contrast with earlier tests showing the phenelzine, another MAO inhibitor, potentiates the acute lethality of metoclopramide in rabbits.
REFERENCES:
- 1. Johnson A.G. The action of metoclopramide on the Canine stomach, duodenum and gall bladder. British Journal of Surgery 1969; 56:696.
- 2. Gordon, C.J. et al. Metoclopramide versus metoclopramide and lorazepam – superiority of combined therapy in the control of cisplatin – induced emesis. Cancer 1989; 63: 578-582.
- 3. Guelrud M. Effect of intravenous metoclopramide on the incompetent lower esophageal sphincter. The American Journal of Gastroenterology 1974; 61(2): 119-124.
- 4. Gaze H., Rolles C., Signer E., et al. Premedication for jejunal biopsy in children using intravenous diazepam and metoclopramide. Archives of Disease in Childhood 1974; 49: 322-324.
- 5. Pearson M.C., Edwards D., Tate A., et al. Comparison of the effects of oral and intravenous metoclopramide on the small bowel. Postgraduate Medical Journal 1973; 49(4): 47-50.
- 6.
Nakra B.R.S., Bond A.J., Lader M.H. Comparative psychotropic effects of
metoclopramide and prochlorperazine in normal subjects. Journal of Clinical Pharmacology May 1975; 15(5-6): 449-454.
- 7.
Tarsy, D., Parkes, J.D. and Marsden, C.D. Metoclopramide in parkinsonism. Lancet
1975; I(7918): 1244-1245.
- 8.
Robinson O.P.W. Metoclopramide - side effects and safety. Postgraduate Medical Journal
1973; 49 (Suppl. 4): 77-80.
- 9. Casteels Van Daele M., Jaeken J., Vander Schueren P., et al. Dystonic reactions in children caused by metoclopramide. Archives of Disease in Childhood 1970; 45: 130-133.
- 10.
Gralla R.J., Itri L.M., Pisko S.E., et al. Antiemetic efficacy of high dose metoclopramide:
Randomized trials with placebo and prochlorperazine in patients with chemotherapy-induced nausea and vomiting. The New England Journal of Medicine 1981; 305(16): 905-909.
- 11.
Laszlo J., Lucas V.S. Emesis as a critical problem in Chemotherapy. The New England
Journal of Medicine Oct 15, 1981; 305(16): 948-949.
- 12. Bateman D.N., Kahn C., Davies D.S. The pharmacokinetics of metoclopramide in man with observations in the dog. British Journal of Clinical Pharmacology 1980; 9: 371-377.
- 13. Bateman D.N., Gokal R., Dodd T.R.P., et al. The pharmacokinetics of single doses of metoclopramide in renal failure. European Journal of Clinical Pharmacology 1981; 19: 437-441.
- 14. Healy D.L., Burger H.G. Sustained elevation of serum prolactin by metoclopramide: A clinical model of idiopathic hyperprolactinemia. Journal of Clinical Endocrinology and Metabolism 1978; 46(5): 709-714.
- 15. Hahn R.A., Wardell J.R. Antagonism of the renal vasodilator activity of dopamine by metoclopramide. Naunyn Schmiedeberg's Archives of Pharmacology 1980;314:177-182.
- 16. Carey R.M., Thorner M.O., Ortt E.M. Dopaminergic inhibition of metoclopramide-induced aldosterone secretion in man. Journal of Clinical Investigation 1980; 66:10-18.
- 17. Brown R.D., Wisgerhof M., Jiang N.S., et al. Effect of metoclopramide on the secretion and metabolism of aldosterone in man. Journal of Clinical Endocrinology and Metabolism 1981; 52(5): 1014-1018.
- 18. Kebabian J.W., Calne D.B. Multiple receptors for dopamine. Nature 1979; 277: 93-96.
- 19. Rotrosen J., Stanley M., Lautin A., et al. Discrimination of functionally heterogenous receptor subpopulations: Antipsychotic and antidopaminergic properties of metoclopramide. Psychopharmacology Bulletin 1981; 17(1): 110-113.
- 20. Lautin A., Wazer D., Stanley M., et al. Chronic treatment with metoclopramide induces behavioral supersensitivity to apomorphine and enhances specific binding of 3H-spiroperidol to rat striata. Life Sciences 1980; 27(4): 305-316.
- 21. Herberg L.J., Wishat T.B. Selective permeation of the blood-brain barrier as a cause of the anomalous properites of 'atypical' neuroleptics. Pharmacology Biochemistry & Bahavior 1980; 12: 871-873.
- 22.
Grimes J.D., Hassan M.N., Preston D.N. Adverse neurologic effects of metoclopramide.
CMA Journal 1982; 126: 23-25.
- 23. Homesley D., Gainey J.M., Jobson V.W., et al. Metoclopramide an antiemetic in chemotherapy. (Letter to the editor) The New England Journal of Medicine 1982;307(4):250.
- 24. Strum S.B., McDermed J.E., Opfell R.W., et al. Intravenous metoclopramide - an effective antiemetic in cancer chemotherapy. JAMA 1982; 247:2683-2686.
- 25. Gralla R.J., Tyson L.B., Clark R.A., et al. Antiemetic trials with high dose metoclopramide: Superiority over THC, and preservation of efficacy in subsequent chemotherapy courses. Proceedings of American Society of Clinical Oncology 1982; 1:58.
- 26. Pinder R.M., Brogden R.N., Sawyer P.R., et al. Metoclopramide: A review of its pharmacological properties and clinical use. Drugs 1976; 12: 81-131.
- 27.
Summary Basis of Approval for NDA’s 17-854 and 17-862 for metoclopramide. US
Freedom of Information documents.
- 28. Dolphin, A., Jenner, P., Marsden, C.D. et al. Pharmacological evidence for cerebral dopamine receptor blockade by metoclopramide in rodents. 1975. Psychopharmacologia (Berl.) 41: 133.