


Product Monograph - Mint-Famotidine
ACTION AND CLINICAL PHARMACOLOGY
Famotidine is a competitive inhibitor of histamine H2 receptors. The primary clinically important pharmacologic activity of famotidine is inhibition of gastric juice secretion. Famotidine reduces the acid and pepsin content, as well as the volume, of basal, nocturnal, and stimulated gastric secretion.
Comparative Bioavailability Studies
A double-blind, randomized, two-treatment, single-dose, crossover oral bioequivalence study of MINT-FAMOTIDINE 40 mg tablets (Mint Pharmaceuticals Inc.) and PrTEVA-FAMOTIDINE 40 mg tablets (Teva Canada Limited) was conducted in healthy, adult subjects under fasting condition. A summary of the comparative bioavailability data from the 30 subjects included in the statistical analysis is presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Famotidine (1 x 40 mg famotidine) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 723.42 746.47 (23.73) | 756.54 775.48 (21.70) | 95.6 | 91.5 – 99.9 |
AUCI (ng·h/mL) | 744.65 767.16 (23.20) | 775.41 794.66 (21.66) | 96.0 | 92.0 – 100.2 |
Cmax (ng/mL) | 112.15 115.82 (25.54) | 119.11 123.07 (26.23) | 94.2 | 88.3 – 100.4 |
Tmax3 (h) | 2.25 (1.00- 5.00) | 2.13 (0.67- 5.00) | ||
T1/24 (h) | 5.02 (19.52) | 4.66 (15.55) | ||
1 MINT-FAMOTIDINE (famotidine) tablets, 40 mg (Mint Pharmaceuticals Inc.).
2 PrTEVA-FAMOTIDINE (famotidine) tablets, 40 mg (Teva Canada Limited).
3 Expressed the median (range) only.
4 Expressed as the arithmetic mean (CV%) only.
INDICATIONS AND CLINICAL USE
MINT-FAMOTIDINE is indicated in the treatment of the following conditions where a controlled reduction of gastric secretion is required:
- 1. Treatment of acute duodenal ulcer;
- 2. Prophylactic use in duodenal ulcer;
- 3. Treatment of acute benign gastric ulcer;
- 4. Treatment of pathological hypersecretory conditions (e.g., Zollinger-Ellison Syndrome)
- 5. Treatment of gastroesophageal reflux disease (GERD);
- 6. Maintenance of remission of patients with GERD.
CONTRAINDICATIONS
Hypersensitivity to any component of this medication. Cross sensitivity in this class of compounds has been observed. Therefore, MINT-FAMOTIDINE (famotidine) should not be administered to patients with a history of hypersensitivity to other H2-receptor antagonists.
PRECAUTIONS
Patients with Moderate or Severe Renal Insufficiency:
Since CNS adverse effects have been reported in patients with moderate and severe renal insufficiency, longer intervals between doses or lower doses may need to be used in patients with moderate (creatinine clearance 30-50 mL/min) or severe (creatinine clearance < 30 mL/min) renal insufficiency to adjust for the longer elimination half-life of famotidine (see HUMAN PHARMACOLOGY, Pharmacokinetics and DOSAGE AND ADMINISTRATION).
Drug Interactions:
Studies with famotidine in man, in animal models, and in vitro have shown no significant interference with the disposition of compounds metabolized by the hepatic microsomal enzymes, e.g., cytochrome P450 system. Compounds tested in man have included warfarin, theophylline, phenytoin, diazepam, aminopyrine and antipyrine. Indocyanine green as an index of hepatic blood flow and/or hepatic drug extraction has been tested and no significant effects have been found. In addition, studies with famotidine have shown no augmentation of expected blood alcohol levels resulting from alcohol ingestion.
Use in Gastric Ulcer:
Gastric malignancy should be excluded prior to initiation of therapy of gastric ulcer with MINT-FAMOTIDINE. Symptomatic response of gastric ulcer to therapy with MINT- FAMOTIDINE does not preclude the presence of gastric malignancy.
Use in Pregnancy:
Reproductive studies have been performed in rats and rabbits at oral doses of up to 2000 and 500 mg/kg/day, respectively (approximately 2500 and 625 times the maximum recommended human dose, respectively), and have revealed no evidence of impaired fertility or harm to the fetus due to famotidine. There are, however, no adequate or well- controlled studies in pregnant women.
Since the safe use of famotidine in pregnant women has not been established, the benefits of treatment with MINT- FAMOTIDINE should be weighed against potential risks.
Nursing Mothers:
Famotidine is detectable in human milk. Nursing mothers should either stop this drug or should stop nursing.
Pediatric Use:
Safety and effectiveness in children have not been established.
Use in Elderly Patients:
No dosage adjustment is required based on age (see HUMAN PHARMACOLOGY, Pharmacokinetics). This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. Dosage adjustment in the case of moderate or severe renal impairment is necessary (see PRECAUTIONS, Patients with Moderate or Severe Renal Insufficiency and DOSAGE AND ADMINISTRATION, Dosage Adjustment for Patients with Moderate or Severe Renal Insufficiency).
Driving and Operating Machinery:
MINT-FAMOTIDINE may cause certain side effects such as dizziness, confusion, or hallucinations and, therefore, patients should know how they react to famotidine before they operate an automobile or machinery or engage in activities requiring mental alertness and coordination (see ADVERSE REACTIONS).
ADVERSE REACTIONS
Famotidine is usually well tolerated; most adverse reactions have been mild and transient. The adverse reactions listed below have been reported during clinical trials in 2333 patients. In those controlled clinical trials in which famotidine was compared to placebo, the overall incidence of adverse experiences in the group which received famotidine 40 mg at bedtime, was similar to the placebo group. No antiandrogenic or other adverse hormonal effects have been observed.
The following adverse reactions have been reported at a rate greater than 1% in patients on therapy with famotidine in controlled clinical trials, and may be causally related to the drug: headache (4.6%), dizziness (1.2%), constipation (1.2%) and diarrhea (1.6%).
Other reactions have been reported in clinical trials but occurred under circumstances where a causal relationship could not be established. However, in these reported events, most of which are uncommon, that possibility cannot be excluded. Therefore, these observations are listed to serve as alerting information to physicians.
| Gastrointestinal | 8.0% |
|---|---|
| Nausea | 1.6% |
| Vomiting | 0.9% |
| Anorexia | 0.5% |
| Abdominal discomfort | 0.3% |
| Dry mouth | 0.2% |
| Nervous System/Psychiatric | 7.3% |
| Insomnia | 0.6% |
| Somnolence | 0.4% |
| Anxiety | 0.3% |
| Paresthesia | 0.3% |
| Depression | 0.2% |
| Libido decreased | 0.1% |
| Respiratory | 4.4% |
| Bronchospasm | < 0.1% |
| Body as a whole | 3.0% |
| Fatigue Asthenia Fever | 0.6% 0.3% 0.2% |
| Musculoskeletal | 1.7% |
| Musculoskeletal pain including muscle cramps | 0.1% |
| Arthralgia | 0.1% |
| Skin | 1.7% |
|---|---|
| Pruritus | 0.4% |
| Rash | 0.3% |
| Alopecia | 0.2% |
| Flushing | 0.2% |
| Acne | 0.1% |
| Dry skin | 0.1% |
| Cardiovascular | 1.0% |
| Palpitations | 0.2% |
| Special Senses | 0.9% |
| Taste disorder | 0.1% |
| Tinnitus | 0.1% |
| Orbital edema | <0.1% |
| Urogenital | 0.9% |
The following additional adverse reactions have been reported since the drug was marketed: urticaria, alopecia, liver enzyme abnormalities, hepatitis, cholestatic jaundice, anaphylaxis, angioedema, agitation, confusion, hallucinations, thrombocytopenia, leukopenia, neutropenia, and agranulocytosis. Interstitial pneumonia and Stevens Johnson syndrome/toxic epidermal necrolysis has been reported very rarely. In patients with impaired renal function, the following have been reported very rarely: convulsions, prolonged QT interval. As with other H2-receptor antagonists, cases of bradycardia, A-V block and other arrhythmias have been reported rarely in patients treated with famotidine.
The following adverse reactions have been reported, however, a causal relationship to therapy with famotidine has not been established: grand mal seizures, pancytopenia, rare cases of impotence.
Gynecomastia has been reported rarely. In most cases that were followed up, it was reversible after discontinuing treatment.
Laboratory Abnormalities:
Laboratory parameters may be affected during treatment with famotidine, but the changes are usually not considered serious. Among the laboratory changes that were reported during clinical trials were increases in AST, ALT, BUN, and serum creatinine. These changes were rarely of clinical significance.
Only three patients had to be discontinued from therapy because of laboratory adverse experiences, however laboratory abnormalities were present at baseline.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
The adverse reactions in overdose cases are similar to the adverse reactions encountered in normal clinical experience (see ADVERSE REACTIONS). Doses of up to 800 mg/day have been employed in patients with pathological hypersecretory conditions with no serious adverse effects. In the event of overdosage, treatment should be symptomatic and supportive. Unabsorbed material should be removed from the gastrointestinal tract, the patient should be monitored, and supportive therapy should be employed.
The oral LD50 of famotidine in male and female rats and mice was > 5000 mg/kg.
DOSAGE AND ADMINISTRATION
DUODENAL ULCER:
Acute Therapy:
The recommended adult oral dosage of MINT-FAMOTIDINE (famotidine) for acute duodenal ulcer is 40 mg once a day at bedtime. Treatment should be given for 4 to 8 weeks, but the duration of treatment may be shortened if healing can be documented. Healing occurs within 4 weeks in most cases of duodenal ulcer.
Maintenance Therapy:
For the prevention of recurrence of duodenal ulcer, it is recommended that therapy with MINT-
For management of a suspected drug overdose, contact your regional poison control centre.
FAMOTIDINE be continued with a dose of 20 mg once a day at bedtime, for a duration of up to 6 to 12 months depending on the severity of the condition.
BENIGN GASTRIC ULCER:
Acute Therapy:
The recommended adult oral dosage for acute benign gastric ulcer is 40 mg once a day at bedtime. Treatment should be given for 4 to 8 weeks, but the duration of treatment may be shortened if healing can be documented.
PATHOLOGICAL HYPERSECRETORY CONDITIONS (SUCH AS ZOLLINGER-ELLISON SYNDROME):
The dosage of famotidine in patients with pathological hypersecretory conditions varies with the individual patient. The recommended adult oral starting dose for pathological hypersecretory conditions is 20 mg every six hours. In some patients, a higher starting dose may be required. Doses should be adjusted to individual patient needs and should continue as long as clinically indicated. Doses up to 800 mg/day have been administered to some patients with severe Zollinger-Ellison syndrome.
GASTROESOPHAGEAL REFLUX DISEASE:
The recommended dosage for the symptomatic relief of gastroesophageal reflux disease is 20 mg of famotidine twice a day.
For the treatment of esophageal erosion or ulceration associated with gastroesophageal reflux disease, the recommended dosage is 40 mg of famotidine twice a day.
For the maintenance of remission of patients with GERD, the recommended dosage is 20 mg of famotidine twice a day.
Concomitant Use with Antacids:
Antacids may be given concomitantly if needed.
Dosage Adjustment for Patients with Moderate or Severe Renal Insufficiency
In patients with moderate (creatinine clearance 30-50 mL/min) or severe (creatinine clearance <
30 mL/min) renal insufficiency, the elimination half-life of famotidine is increased. For patients with severe renal insufficiency, it may exceed 20 hours, reaching approximately 24 hours in anuric patients. Since CNS adverse reactions have been reported in patients with moderate and severe renal insufficiency, to avoid excess accumulation of the drug in patients with moderate or severe renal insufficiency, the dose of famotidine may be reduced to half the dose or the dosing interval may be prolonged to 36-48 hours as indicated by the patient’s clinical response.
PHARMACEUTICAL INFORMATION
DRUG SUBSTANCE:
Proper Name: Famotidine
Chemical Name: N'-(aminosulfonyl)-3-[[[2-[(diaminomethylene)amino]-4- thiazolyl]methyl]thio]Propanimidamide.
Structural Formula:
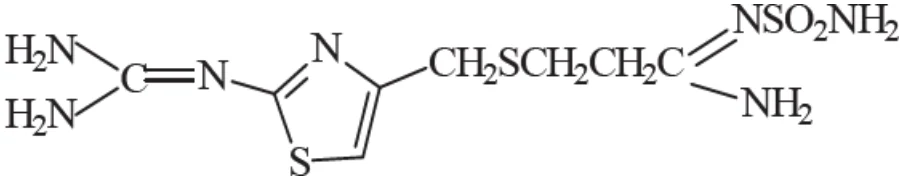
Description:
Famotidine is a white to pale yellowish white crystalline powder. Freely soluble in dimethyl formamide, glacial acetic acid, slightly soluble in methanol, very slightly soluble in water, practically insoluble in acetone, in alcohol, in chloroform, in ether and in ethyl acetate.
Molecular Formula: C8H15N7O2S3
Molecular Weight: 337.45 g/mol
COMPOSITION
MINT-FAMOTIDINE tablets: Active ingredient: famotidine. Non-medicinal ingredients: hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, pre-gelatinized starch, sodium starch glycolate (Type-A), and film coating: Opadry White.
Composition of Opadry white: hypromellose, polyethylene glycol / macrogol, talc, titanium dioxide, triacetin.
STABILITY AND STORAGE RECOMMENDATIONS:
MINT-FAMOTIDINE tablets: Store between 15°C - 30°C in well-closed, light-resistant containers.
AVAILABILITY OF DOSAGE FORMS
MINT-FAMOTIDINE (famotidine) tablets are available as:
20 mg - Round, white to off-white film coated tablets, debossed with “V” on one side and “15” on other side.
Supplied: Bottles of 30, 100, and 1000 tablets.
40 mg - Round, white to off-white film coated tablets, debossed with “V” on one side and “45” on other side.
Supplied: Bottles of 30, 100, and 500 tablets
INFORMATION FOR THE PATIENT
PrMINT-FAMOTIDINE
Full prescribing information is available to the physician and pharmacist.
MINT-FAMOTIDINE (20 mg and 40 mg tablets) is available only on prescription from your physician. Famotidine belongs to a class of medicines known as histamine H2-receptor antagonists. It reduces the amount of acid produced by the stomach. For this reason it is used in the treatment of certain ulcers of the stomach or duodenum, and other conditions, for example the treatment of gastroesophageal reflux disease or Zollinger- Ellison syndrome, in which the stomach produces too much acid.
Remember—This medicine is prescribed for the particular condition that you have.
Do not give this medicine to other people, nor use it for any other condition. Do not use outdated medicine.
Keep out of the reach and sight of children.
Read the following information carefully. If you need any explanations, or further information, ask your physician or pharmacist.
Before Taking this Medicine: This medicine may not be suitable for some patients. So, tell your physician if you think any of the following applies to you:
- Do not take MINT-FAMOTIDINE if you are allergic to any of its ingredients or to other H2-receptor antagonists.
- You are pregnant or intend to become pregnant.
- You are breast-feeding or intend to breast-feed.
- You have confirmed kidney or liver ailment.
- Your physician also needs to know if you are taking any other medication (example, a prescription or over the counter drugs).
Proper Use of this Medicine:
- Take this medicine exactly as directed by your physician. For the treatment of ulcers, it is often recommended as a single dose at bedtime; but some conditions may require different dosing. In any case, follow the instructions provided by your physician and your pharmacist.
- If necessary, your physician may also recommend an antacid.
- If you miss the usual time for a tablet, take it as soon as possible. But, if it is too close to the time of your next dose, take only the prescribed dose at the appointed time. Do not take a double dose.
- The safety of famotidine in children has not been established.
- Carefully follow any dietary measures that your physician has recommended. Certain foods and drinks and certain medicines, such as acetylsalicylic acid, may irritate the stomach and worsen your condition.
Take this medicine for the full duration of treatment, even if you begin to feel better.
The pain usually subsides before complete healing is obtained. Do not alter the dosage or stop taking the medicine without consulting your physician.
MINT-FAMOTIDINE does not usually interfere with other medicines that you may
be taking. It is important, however, to tell your physician about all the drugs that you are taking, including those obtained without a prescription.
- Store at 15°C to 30°C in a tightly closed container. Protect from light.
Can I drive or operate machinery while using MINT-FAMOTIDINE?
There have been side effects such as dizziness reported with famotidine that may affect your ability to drive or operate machinery. Individual responses to famotidine may vary. Determine your response to famotidine before driving or operating machinery. (See SIDE EFFECTS OF THIS MEDICINE - AND WHAT YOU SHOULD DO).
Overdose:
If you think you, or a person you are caring for, have taken too much MINT-
FAMOTIDINE, contact a healthcare professional, hospital emergency department, or regional poison control centre immediately, even if there are no symptoms.
Side Effects of this Medicine - and What you Should Do:
Along with its intended action, any medication may cause unwanted effects. Most people do not have any problem when taking this medicine.
Check with your physician as soon as possible if any of the following side effects occur: headache, dizziness, diarrhea, constipation and liver problems with symptoms such as abdominal pain, vomiting, fatigue (or tiredness) and jaundice (yellowing of the eyes and skin).
Other side effects reported less frequently are dry mouth, nausea and/or vomiting, stomach discomfort, loss of appetite, tiredness, rash, itching, hair loss, jaundice, painful joints, muscle cramps, and mental disturbances that stopped when the medicine was discontinued. Patients with kidney problems have experienced seizures very rarely.
A few people may be allergic to some medicines. If any of the following side effects occur after taking MINT-FAMOTIDINE, stop taking this medicine and contact your doctor immediately: swelling of the face, lips, tongue and/or throat (with difficulty in breathing or swallowing); hives; or severe skin reactions (very rare reports with this class of medicines).
Other effects not listed above may also occur in some patients. If you notice any other unusual symptoms, check with your physician.
Ingredients: Active Ingredient: Each tablet of MINT-FAMOTIDINE contains famotidine. It comes in two strengths: 20 mg and 40 mg.
Nonmedicinal ingredients: hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, pregelatinized starch, sodium starch glycolate (Type-A) and film coating: Opadry White.
Composition of Opadry white: hypromellose, polyethylene glycol / macrogol, talc, titanium dioxide, triacetin.
If you want more information about MINT-FAMOTIDINE:
- Talk to your healthcare professional
- Find the full product monograph that is prepared for healthcare professionals and includes this Patient Medication Information by visiting the Health Canada website (https://www.canada.ca/en/health-canada/services/drugs-health-products/drug- products/drug-product-database.html); the manufacturer’s website www.mintpharmaceuticals.com, or by contacting MINT Pharmaceuticals Inc. by: Phone: 1-877-398-9696
Mint Pharmaceuticals Inc.
6575 Davand Drive
Mississauga, Ontario
Canada
L5T 2M3
Last Revised: May 23, 2023
Reporting Side Effects
You can report any suspected side effects associated with the use of health products to Health Canada by:
- Visiting the Web page on Adverse Reaction Reporting (https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect- canada/adverse-reaction-reporting.html) for information on how to report online, by mail or by fax; or
- Calling toll-free at 1-866-234-2345.
NOTE: Contact your health professional if you need information about how to manage your side effects. The Canada Vigilance Program does not provide medical advice.
PHARMACOLOGY
- I. Human Pharmacology:
In both normal volunteers and hypersecretors, famotidine inhibited basal nocturnal and daytime gastric secretion, as well as secretion stimulated by a variety of stimuli, such as pentagastrin and food.
After oral administration, the onset of the antisecretory effect occurred within one hour; the maximum effect was dose-dependent, occurring within one to three hours. Duration of inhibition of secretion was 10 to 12 hours. After intravenous administration, the maximum effect was achieved within 30 minutes. Single intravenous doses of 10 and 20 mg inhibited basal nocturnal secretion for a period of 10-12 hours. The 20 mg dose was associated with the longest duration of action in most subjects. Single oral doses of 20 and 40 mg inhibited basal nocturnal acid secretion in all subjects; mean gastric acid secretion was inhibited by 86% and 94%, respectively, for a period of at least 10 hours. Similar doses given in the morning suppressed food-stimulated acid secretion in all subjects, with mean suppression of 76% and 84%, respectively, 3 to 5 hours after drug, and of 25% and 30%, respectively, 8 to 10 hours after drug; however, in some subjects who received the 20 mg dose, the antisecretory effect was dissipated earlier, within 6 to 8 hours. There was no cumulative effect with repeated doses. The basal nocturnal intragastric pH was raised by evening doses of 20 and 40 mg of famotidine to mean values of 5.0 and 6.4, respectively. When famotidine was given in the morning, the basal daytime interdigestive pH at 3 and 8 hours after 20 or 40 mg of famotidine was raised to about 5.0.
Fasting and postprandial serum gastrin levels may be slightly elevated during periods of drug antisecretory effect, and with chronic therapy an increase in gastric bacterial flora may occur. Gastric emptying and exocrine pancreatic function are not affected by famotidine.
The presence of gastroesophageal reflux disease appears to correlate best with the percentage of time over 24 hours during which the esophagus is exposed to acid. In gastroesophageal reflux disease patients, 20 mg twice a day and 40 mg twice a day of famotidine reduced intraesophageal acid exposure into the normal range as measured by 24 hour intraesophageal pH monitoring. In clinical studies of gastroesophageal reflux disease patients with endoscopically verified erosive or ulcerative esophagitis, 40 mg twice a day was more effective than 20 mg twice a day in healing esophageal lesions.
Both dosage regimens were superior to placebo.
In patients treated for six months with famotidine, relapse of esophageal erosion or ulceration was significantly less than in patients treated with placebo. Famotidine was also shown to be superior to placebo in preventing symptomatic deterioration.
Other Effects:
Systemic pharmacologic effects of famotidine in the CNS, respiratory or endocrine systems have not been found to date. Serum prolactin levels do not rise after intravenous bolus doses of 20 mg of famotidine and no antiandrogenic effects have been detected.
Pharmacokinetics:
Famotidine is incompletely absorbed. The mean bioavailability of oral doses is 40-45%. Bioavailability may be slightly increased by food, or slightly decreased by antacids; however, these effects are of no clinical consequence. Famotidine undergoes minimal first-pass metabolism. After oral doses, peak plasma levels occur in 1 to 3 hours. Plasma levels after multiple doses are similar to those after single doses. Fifteen to 20% of famotidine in plasma is protein bound. Famotidine has an elimination half-life of 2.5 to 3.5 hours. Famotidine is eliminated by renal (65 to 70%) and metabolic (30 to 35%) routes. Renal clearance is 250 to 450 mL/min., indicating some tubular excretion.
Twenty-five to 30% of an oral dose and 65 to 70% of an intravenous dose are recovered in the urine as unchanged compound. The only metabolite identified in man is the S- oxide. There is a close relationship between creatinine clearance values and the elimination half -life of famotidine. In patients with severe renal insufficiency, i.e., creatinine clearance less than 30 mL/min., elimination half-life of famotidine may exceed 20 hours and adjustment of dosing intervals in moderate and severe renal insufficiency may be necessary (see PRECAUTIONS, DOSAGE AND ADMINISTRATION). In elderly patients, there are no clinically significant age-related changes in the pharmacokinetics of famotidine. However, in elderly patients with decreased renal function, the clearance of the drug may be decreased (see PRECAUTIONS, Use in Elderly Patients).
- II. Animal Pharmacology:
Famotidine inhibits gastric secretion evoked by histamine and other secretagogues. In dogs, the ED50 was 0.03 mg/kg after oral or intravenous administration of famotidine. An oral dose of 2.1 mg/kg in dogs inhibited gastric secretion for at least 24 hours. An oral dose of 3 mg/kg one hour prior to feeding inhibited the acid response in dogs during a 4-hour post feeding period by an average of 96%.
Mechanism of Action:
Famotidine is a specific, competitive, H2 receptor antagonist. There was no effect in vitro on responses mediated by H1-histamine, beta1-adrenergic, or cholinergic
receptors. Famotidine was inactive in radioligand binding to dopaminergic,
neuroleptic, serotonergic, adrenergic, cholinergic, and purinergic sites. Famotidine was also inactive in an androgen receptor assay.
The interaction between famotidine and H2 receptors is tissue-dependent. In guinea pig lungs and rabbit gastric glands the effects of famotidine were surmountable and readily reversible on washout, indicating classic competitive inhibition at the H2 receptor sites. However, in guinea pig atria, famotidine acted as a non-competitive H2 antagonist, and recovery after washout of famotidine was retarded.
Absorption and Distribution:
The absorption, distribution, metabolism and excretion of famotidine was studied in two animal species. Absorption was 28% in the rat and 43% in the dog. The plasma half-life in dogs was 2.5 hours, which was unchanged after repeated doses, indicating no tendency for the drug to accumulate. In rats, the highest levels of radioactivity after an oral dose of famotidine were found in the gastrointestinal tract, kidneys, liver, submandibular glands, arteries, epiphyseal membrane, fascia, and uvea. The distribution pattern was not affected on repeated dosing. Famotidine did not effectively cross the blood-brain or placental barrier of rats. It was present in rat milk.
Metabolism and Excretion:
The only metabolite of famotidine in rat and dog urine was the sulfoxide derivative, which was present in minor amounts. Urinary and fecal excretion of radioactivity in rats accounted for 28% and 70% respectively, of an oral dose, compared to 83% and 17% respectively, of an intravenous dose. About 2.4% of the dose in rats was excreted in the bile. Dogs excreted 45% of an oral dose in the urine, compared to 100% of an intravenous dose.
Effects on Liver Microsomal Drug-Metabolizing Enzymes:
Famotidine did not affect pentobarbital or hexobarbital sleeping times and it did not affect ascorbic acid excretion, suggesting that famotidine does not induce drug- metabolizing enzymes. Famotidine caused none of the changes induced by cimetidine on the pharmacokinetics of diazepam, warfarin, and propranolol. Famotidine produced only minimal suppression of aminopyrine and diazepam N-demethylase activity in vitro, and showed little affinity for testosterone hydroxylases of mouse liver in vitro.
Gastrointestinal Effects Other than Antisecretory:
Famotidine prevented gastric erosions induced in rats by cold restraint, water immersion, pyloric ligation, or drugs such as acetylsalicylic acid, histamine or prednisolone; also duodenal ulcers caused by cysteamine and mepirizole. It also significantly accelerated the healing of the gastric lesions induced by acetic acid and the duodenal ulcers produced by mepirizole.
The antiulcer effect of famotidine plus magnesium and aluminum hydroxides was greater than the sum of the effects of these drugs used separately.
Famotidine inhibited the gastric lesions and hemorrhage resulting from blood removal and histamine injection in anesthetized rats.
In normal rats, famotidine had no effect on the concentration of gastric mucosal histamine, but it did reduce the levels of cAMP, particularly in response to histamine stimulation.
In anaesthetized cats, famotidine had no effect on the intragastric electropotential when tested at intragastric doses more than ten-fold greater than those required to block gastric secretion maximally.
Cardiorenal Effects:
The cardiorenal effects of famotidine were studied in dogs and rats. Ten mg/kg of famotidine administered orally were without effect on the blood pressure of spontaneously hypertensive rats. In anesthetized dogs, intravenous administration of 1.0 and 4.0 mg/kg of famotidine was without effect on cardiovascular parameters relating to the autonomic nervous system, blood pressure, heart rate, or respiratory function. In conscious dogs, an oral dose of 10 mg/kg was without diuretic effect.
Central Nervous System Effects:
The effects of famotidine on the central nervous system were studied in squirrel monkeys, mice and cats. In monkeys, famotidine had a bidirectional effect on lever pressing (avoidance response) causing an increase at the low dose (1.0 mg/kg p.o.) and a small decrease at 9 mg/kg. In mice, following intraperitoneal administration of 6 to 150 mg/kg no overt behavioural signs or symptoms of central nervous system activity were observed. In mice, famotidine was not active as an antagonist of the CNS actions of TRH, neurotensin, substance P, or amphetamine. Famotidine was free of major or minor tranquilizing, anticonvulsant, anticholinergic, ganglionic blocking or dopaminergic activity. In cats, famotidine did not affect the EEG or arousal response, but did prolong the duration of hippocampal after discharge. Only 4% of the plasma concentration of the drug was detected in the cerebrospinal fluid.
TOXICOLOGY
Acute Toxicity:
| Species | Sex | Route | LD50(mg/kg) |
|---|---|---|---|
| Mouse | M | p.o.* | 4,684 |
| F | p.o.* | 3,233 | |
| Mouse | M | i.v. (4%) | 254 |
| F | i.v. (4%) | 358 | |
| Rat | M | p.o.* | 4,907 |
| F | p.o.* | 4,049 | |
| Rat | M | i.p. | 987 |
| F | i.p. | 814 |
* In solution (acidic, 50-55˚C deionized water)
Subacute and Chronic Toxicity:
Famotidine is well tolerated by both rats and dogs at doses of 2 g/kg twice a day orally in subacute studies and at doses up to 1000 or 2000 mg/kg/day for one year in these species. Eosinophilic cytoplasmic granularity of gastric chief cells was seen at a higher incidence in rats given 200 mg/kg/day or more of the compound compared to controls. This is considered as a secondary effect due to the exaggerated pharmacologic activity of the compound and at these extremely high dosage levels and is considered of no toxicologic significance. In a 106-week study in rats designed to study the carcinogenic potential of the compound, this gastric change did not progress to hyperplasia or neoplasia. Similarly, mice (given the compound for 92 weeks) showed no evidence of a neoplastic potential.
Based on the results from studies performed using pharmacologically-related compounds, this change was fully reversible.
Intravenous administration of famotidine was well tolerated by rats for 13 weeks at dosage levels of up to 20 mg/kg/day and by dogs, except for occasional emesis, at dosage levels of up to 10 mg/kg/day for 5 to 26 weeks.
Reproduction Studies:
In studies with rats given oral doses of up to 2000 mg/kg/day or intravenous doses of up to 200 mg/kg/day (approximately 2500 and 250 times the maximum recommended human dose, respectively), fertility and reproductive performance were not affected
Famotidine given orally to pregnant rats up to 2000 mg/kg/day or intravenously at dosage levels up to 200 mg/kg/day, from days 7 to 17 of pregnancy did not reveal any evidence of embryolethality or teratogenicity.
Oral administration of famotidine to pregnant rabbits from days 6 to 18 of pregnancy at dosage levels up to 500 mg/kg/day revealed no evidence of embryolethality or teratogenicity.
Mutagenicity:
Famotidine was tested in a reverse-mutation test (Ames test) using Salmonella typhimurium and Escherichia coli with and without metabolic activation. No mutagenic potential was seen. These same studies were performed with famotidine/sodium, nitrite reaction mixture and C-nitroso derivatives of famotidine and they were also negative. Famotidine and C-nitroso derivatives of famotidine were tested in the rec-assay using Bacillus subtilis H17 and M45 and the tests were negative for DNA-damaging capacity of the compounds. In in vivo studies in mice, a micronucleus test and a chromosomal aberration test, no evidence of a mutagenic effect was seen.
Carcinogenicity:
A 92-week oral carcinogenicity study was conducted in mice at doses of 20, 200 and 2000 mg/kg/day. No evidence of a carcinogenic potential was seen. A 106-week oral carcinogenicity study in rats given doses of 20, 200 and 2000 mg/kg/day did not reveal any carcinogenic potential for famotidine.
Special Studies:
The effects of famotidine on the thyroid of rats were evaluated after five weeks of oral administration at doses up to 2000 mg/kg/day. No evidence of treatment-related alterations of serum thyroid hormone levels, thyroid weight or the microscopic appearance were seen after administration of famotidine.
In immunogenicity studies, no effect on the production of IgE antibodies was seen in the sera of mice which were injected, once intraperitoneally, with famotidine alone (up to 2 mg/8 mL/kg) or coupled with either mouse serum albumin or ovalbumin. The sera were used to measure passive cutaneous anaphylaxis in rats which were then challenged with solutions of antigens similar to those antigens used for the initial dose in mice. Similarly, no evidence of an anaphylactic reaction was seen in guinea pigs challenged intravenously with famotidine after initiating doses (three times, subcutaneously, at six-day intervals) of up to 10 mg/mL.
REFERENCES
- 1. Dammann HG, Walter TA, Muller P, Simon B. The role of H2-antagonists in Zollinger-Ellison-Syndrome. Ital J Gastroenterol 1984;16:167-169.
- 2. Dicenta C, Pierzchala PA, Rhymer AR, Jaffe ME, Outline of clinical studies with a new H2-antagonist: famotidine. Ital J Gastroenterol 1984;16:181-182.
- 3. Hayakawa A, Che K, Miyoshi A, Harasawa S, Miwa T, Makabatake T. Properties of famotidine in relation to safety. Ital J Gastroenterol 1984;16:174-176.
- 4. Howard JM, Collen MJ, Cherner JA, McArthur KE, Maton PN, Gardner JD, Jensen RT. Famotidine: an effective, potent H2 antagonist for the therapy of Zollinger- Ellison Syndrome (ZES). Gastroenterology (in Soc. Proc.) 1984;86:1117.
- 5. Howard JM, Chremos AN, Collen MJ, McArthur KE, Cherner JA, Maton PN, Ciarleglio CA, Cornelius MJ, Gardner JD, Jensen RT. Famotidine, a new, potent, long-acting histamine H2-receptor antagonist: comparison with cimetidine and ranitidine in the treatment of Zollinger-Ellison syndrome. Gastroenterology 1985;88:1026-1033.
- 6. Hucker HB, Hutt JE, Chremos AN, Rotmensch H. Disposition and metabolism of famotidine, a potent H2-receptor blocker, in man. Fed Proc Fed Am Soc Exp Biol (in Soc. Proc.) 1984;43:655.
- 7. McCallum RW, Kuljian B, Chremos AN, Tupy-Visich MA, Huber PB. Prolonged gastric antisecretory effect of a novel H2- receptor inhibitor, MK-208. Gastroenterology (in Soc. Proc.) 1983;84:1245.
- 8. Miyoshi A, Muto V, Mori H, Miwa T, Nakazawa S, Ohe K, Hayakawa A. Famotidine : Summary of overall safety from Japanese clinical studies. Ital J Gastroenterol 198;16(2):177-178.
- 9. Muller P, Dammann HG, Schmidt-Gayk H, Lichtwald K, Staiger C, Simon B. Famotidine (MK-208): Duration of action, 24-hour intragastric acidity, antipyrine kinetics and basal hormone levels in man. Gastroenterology (in Soc. Proc.) 1984;86:1190.
- 10. Ohe K, Miyoshi A, Yachi A, Yabana T, Saton K, Sakita T, Fukutomi H, Mutoh H, Sugata F, Fujita Y, Matsuo Y, Mori H, Miwa T, Miwa M, Kubota Y, Watanabe Y, Nakazawa S, Segawa K, Tsukamoto S, Moriga M, Kishi S. Clinical pharmacology of famotidine-effect of famotidine on gastric secretion. Ital J Gastroenterol 1984;16:169- 171.
- 11. Ryan JR, Vargas R, Mantell G, Chremos AN, McMahon FG, Regel G. The effect of dose size, frequency and timing of famotidine (MK-208) on nocturnal and meal- stimulated gastric secretion. Clin Pharmacol Ther (in SOC. Proc.) 1984;35:271.
- 12. Ryan R. Clinical pharmacology of famotidine: Summary of data from the United States. Ital J Gastroenterol 1984;16:171 -174.
- 13. Shiratori K, Watanabe S, Maruyama M, Kurokawa K, Takeuchi T. Effect of famotidine on gastric secretion, and on 24-hour intragastric pH in duodenal ulcer patients. Gastroenterology (in Soc. Proc.) 1984;86:1250.
- 14. Smith JL, Gamal MA, Chremos AN, Graham DY. Effect of an H2-receptor antagonist, MK-208, on gastric parietal and nonparietal secretion. Gastroenterology (in Soc. Proc.) 1983;84:1314.
- 15. Smith JL Gamal MA, Chremos AN, Graham DY. Famotidine a new H2-receptor antagonist effect on parietal nonparietal and pepsin secretion in man. Dig Dis Sci 1985;30:308-312.
- 16. A two-way comparative bioavailability study of famotidine 40 mg tablets in normal volunteers. Completed November 1990.
- 17. A two-way comparative bioavailability study of famotidine 20 mg tablets in normal volunteers. Completed October 1991.
- 18. Product Monograph for PEPCID® by Merck Canada Inc., date of revision April 27, 2011, control# 145448.
- 19. Product Monograph for TEVA-FAMOTIDINE by Teva Canada Limited, date of revision July 20, 2021, control# 249422.
Last Revised: June 7, 2023