


Product Monograph - Mitomycin for Injection (Eugia Pharma)
ACTION AND CLINICAL PHARMACOLOGY
Mitomycin was first investigated as an antibiotic in Japan. It was then found to be active as an antineoplastic agent. It selectively inhibits the synthesis of deoxyribonucleic acid (DNA). The exact point of mitomycin attachment to DNA remains unknown. There is a correlation between the guanine and cytosine content of DNA and the degree of mitomycin-induced cross-linking. At high concentrations of the drug, cellular RNA and protein synthesis are also suppressed.
In humans, mitomycin is rapidly cleared from the plasma after intravenous administration with a biphasic plasma elimination curve. Time required to reduce the serum concentration by 50% after a 30 mg bolus injection is 17 minutes. After injection of 30 mg, 20 mg or 10 mg intravenously, the maximal serum concentrations were 2.4 µg / mL, 1.7 µg / mL and 0.52 µg / mL, respectively.
In general, the smaller the dose, the more rapidly blood levels of mitomycin decreased. Clearance is affected primarily by metabolism in the liver, but metabolism occurs in other tissues as well.
Approximately 10% of a dose of mitomycin is excreted unchanged in the urine. Since metabolic pathways are saturated at relatively low doses, the percent of a dose excreted in urine increases with increasing doses. In children, excretion of intravenously administered mitomycin is similar.
Mitomycin is not appreciably absorbed from the urinary bladder, following intravesical administration. Serial plasma samples from 55 patients treated with doses of 20 mg to 40 mg of mitomycin by intravesical instillation were assayed. There was no mitomycin detectable (assay limit 10 to 100 ng / mL) in any plasma samples collected during and 30 minutes post-therapy at any dose.
INDICATIONS AND CLINICAL USE
Mitomycin for Injection is indicated in the palliative treatment as an adjunct to surgery, radiation or chemotherapy for adenocarcinoma of the stomach and colon.
Mitomycin for Injection as a single agent is indicated as topical therapy for superficial (no invasion beyond the lamina propria) transitional cell carcinoma of the urinary bladder. Efficacy has been demonstrated both in patients who have had no prior intravesical chemotherapy and in those who have failed such therapy with Thiotepa or other antineoplastic agents.
CONTRAINDICATIONS
Mitomycin for Injection is contraindicated in patients who have demonstrated a hypersensitivity to it in the past.
Mitomycin for Injection is contraindicated in patients with thrombocytopenia, leukopenia, coagulation disorder, or an increased bleeding tendency due to other causes.
Mitomycin for Injection is contraindicated for intravesical administration in patients who have demonstrated a hypersensitive or idiosyncratic reaction to it in the past.
WARNINGS
It is recommended that Mitomycin for Injection be administered under the supervision of a qualified physician experienced in the use of cancer chemotherapeutic agents. Since facilities for necessary laboratory studies must be available, hospitalization of patients is recommended.
Mitomycin for Injection should not be administered to any patient with a white blood cell count below 4000 mm3 and a platelet count below 150 000 mm3, or to those with potentially serious infections.
Bone marrow depression, notably thrombocytopenia and leukopenia, is the most severe toxicity (see ADVERSE REACTIONS). Thrombocytopenia may contribute to hemorrhage and leukopenia to overwhelming infection in an already compromised, poor risk patient and may result in death.
Mitomycin for Injection is cytotoxic. In the treatment of each patient, the physician must weigh carefully the possibility of achieving therapeutic benefit versus the risk of toxicity. Studies have shown that mitomycin is carcinogenic in animals.
Use in Obstetrics
Safe use of mitomycin in pregnant women has not been established. Mitomycin has known teratogenic properties in animals, therefore, the benefits derived from the use of Mitomycin for Injection in pregnancy must be weighed against the hazards involved.
Nursing Women
It is not known if mitomycin is excreted in human milk. It is recommended that women receiving mitomycin not breast feed because of the potential for serious adverse reactions from mitomycin in nursing infants.
PRECAUTIONS
Mitomycin for Injection should be administered, preferably, to patients who are hospitalized and who can be observed carefully and frequently during and after therapy.
It should be used with extreme caution in patients with significant impairment of renal function.
Since mitomycin has a high incidence of bone marrow depression, particularly thrombocytopenia and leukopenia, the following studies should be obtained frequently during therapy and for at least seven weeks following therapy: platelet count, prothrombin time, bleeding time, white blood count and differential. The persistence of thrombocytopenia below 150 000 mm3, or a significant prolongation of prothrombin time or bleeding time, or a white blood cell count below 4000 mm3 is an indication for the termination of therapy.
Hemolytic Uremic Syndrome (HUS), a serious complication of chemotherapy, consisting primarily of microangiopathic hemolytic anemia, thrombocytopenia and irreversible renal failure has been reported in patients receiving mitomycin. The syndrome may occur at any time during systemic therapy with mitomycin as a single agent or in combination with other cytotoxic drugs; however, most cases occur at doses 60 mg of mitomycin. Blood product transfusion may exacerbate the symptoms associated with this syndrome. The incidence of the syndrome has not been defined. (See ADVERSE REACTIONS)
Patients should be advised of the potential toxicity of this drug, particularly bone marrow depression. A low incidence of septicemic deaths, as a result of leukopenia attributable to the drug, have been reported. Patients receiving Mitomycin for Injection should be observed for evidence of renal toxicity. Mitomycin for Injection should not be given to patients with a serum creatinine greater than 1.7 mg percent.
Mitomycin-associated pulmonary toxicity has been reported. Cases have been reported with both single-agent therapy and combination chemotherapy. Dyspnea and nonproductive cough are the usual presenting symptoms. Radiographic evidence of interstitial infiltrates may or may not be present. If other etiologies have been eliminated, a diagnosis of mitomycin-related pulmonary toxicity may be made.
Signs and symptoms of pneumonitis associated with mitomycin may be reversed if appropriate therapy is instituted early and mitomycin is discontinued. Corticosteroids have been reported by several authors to expedite symptomatic relief.
Acute shortness of breath and severe bronchospasm have been reported following the administration of vinca alkaloids in patients who had previously or simultaneously received mitomycin. The onset of this acute respiratory distress occurred within minutes to hours after the vinca alkaloid injection. The total number of doses for each drug has varied considerably. Bronchodilators, steroids and / or oxygen have produced symptomatic relief.
A few cases of adult respiratory distress syndrome have been reported in patients receiving mitomycin, in combination with other chemotherapy, and maintained at FiO2 concentrations greater than 50% perioperatively. Therefore, caution should be exercised using only enough oxygen to provide adequate arterial saturation, since oxygen itself is toxic to the lungs. Careful attention should be paid to fluid balance and overhydration should be avoided.
ADVERSE REACTIONS
Bone Marrow Toxicity
The most serious and most common toxicity of mitomycin is thrombocytopenia and leukopenia, which occur anytime within eight weeks after onset of therapy. In a recent study, at a dose of 20 mg / m2 every six to eight weeks, by itself or in combination with 5-fluorouracil, leukopenia occurred in 74 of 94 patients, with 10 being in the life-threatening category; and thrombocytopenia occurred in 68 of 94 patients, with 18 being in the life-threatening category.
In a previous study, at doses of 0.5 mg / kg / day for five days and repeating once monthly, or 0.25 mg / kg every two weeks, leukopenia and/or thrombocytopenia occurred in 605 of 937 patients. The return to normal counts after cessation of therapy was within 10 weeks. Mitomycin produces cumulative myelosuppression.
Integument and Mucous Membrane Toxicity
This has occurred in approximately 4% of patients treated with mitomycin. Cellulitis at the injection site has been reported and is occasionally severe. Stomatitis and alopecia also occur frequently. Rashes are rarely reported.
The most important dermatological problem with this drug, however, is the necrosis and consequent sloughing of tissue, which results if the drug is extravasated during injection.
Extravasation may occur with or without an accompanying stinging or burning sensation and even if there is adequate blood return when the injection needle is aspirated. There have been reports of delayed erythema and / or ulceration occurring either at or distant from the injection site, weeks to months after mitomycin, even when no obvious evidence of extravasation was observed during administration. Skin grafting has been required in some of the cases.
Pulmonary Toxicity
Refer to section on pulmonary toxicity under PRECAUTIONS.
Renal Toxicity
A small number of patients demonstrated a significant rise in BUN from a baseline pre-therapy. There appeared to be no correlation between total dose administered or duration of therapy and renal toxicity. Seventy-five percent of the patients with a definite renal toxicity had evidence of metastatic disease. The data, to date, are inconclusive as far as a direct relationship of mitomycin to renal toxicity.
Hemolytic Uremic Syndrome (HUS)
A serious and often fatal syndrome consisting of microangiopathic hemolytic anemia, thrombocytopenia, renal failure, and hypertension, has been reported in patients receiving mitomycin. Most of these patients received long-term therapy (6 to 12 months) with mitomycin in combination with fluorouracil and doxorubicin; however, some patients received mitomycin in combination with other drugs or were treated for less than six months. Exacerbation of the symptoms associated with HUS has been reported in some patients receiving blood product transfusions. The incidence of the syndrome has not been defined. A high mortality rate (52%) has been associated with this syndrome (See PRECAUTIONS).
Acute Side Effects
Fever, hemolytic anemia, anorexia, stomatitis, hypoglycemia, mucositis, and diarrhea have occurred.
Other Undesirable Side Effects
Headache, blurring of vision, confusion, drowsiness, syncope, fatigue, weakness, edema, thrombophlebitis, hematemesis, nausea, vomiting, weight loss, ataxia, and pain. It is difficult to determine whether these side effects are dose-related or due to the primary or metastatic disease process.
Genitourinary Irritation
Genitourinary irritation following intravesical administration indicated dysuria, cystitis, nocturia and increased frequency of micturition, hematuria, and other symptoms of local irritation. Approximately 25% of the patients treated experienced irritative symptoms, but not all were unequivocally drug-related and may have been symptoms of the disease. Reports of bladder fibrosis/contraction, which in rare cases have required cystectomy, have been received postmarketing.
Dermatitis
Dermatitis occurred in approximately 10% of the patients treated. It was commonly manifested as palmar rash with desquamation, generally appearing on the extremities and less often on the trunk and also as genital rash. Topical steroids have been employed, but their therapeutic value has not been determined.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
No specific antidote for mitomycin is known. Management of overdosage would include general supportive measures to sustain the patient through any period of toxicity that might occur.
DOSAGE AND ADMINISTRATION
Mitomycin for Injection should be given with care to avoid extravasation of the compound into the tissue. If extravasation occurs, cellulitis, ulceration and slough may result.
To reconstitute a vial of Mitomycin for Injection, add Sterile Water for Injection as listed in the Reconstitution Table below:
Reconstitution Table
| Vial Size | Diluent Added to Vial (mL) | Approximate Available Volume (mL) | Approximate Concentration (mg / mL) |
|---|---|---|---|
| 20 mg | 40 | 39.0 | 0.5 |
Shake well until dissolved. If the product does not dissolve immediately, shake under warm tap water for approximately two minutes until a solution is obtained. All steps of dilution and administration must be conducted using non-PVC materials and containers.
Intravenous Use
After full hematological recovery from any previous chemotherapy, either of the following Dosage Schedules may be used at 6 to 8 week intervals. Because of cumulative myelosuppression, patients should be re-evaluated after each course of Mitomycin for Injection and the dose reduced if the patient has experienced any toxicities (see Guide to Dosage Adjustment).
Doses greater than 20 mg / m2 do not demonstrate increased effectiveness and are more toxic than lower doses.
- (1) 20 mg / m2 intravenously as a single dose via a functioning intravenous catheter.
- (2) 2 mg / m2 / day intravenously for 5 days. After a drug free interval of 2 days, 2 mg / m2 / day for 5 days, thus making the total initial dose of 20 mg / m2 given over 10 days.
Intravesical Use
A dose of 20 to 40 mg intravesically once per week for 8 weeks. Patients are advised to abstain from liquids for 12 hours prior to therapy. The patient is catheterized, the bladder is drained and Mitomycin for Injection is instilled. The solution should be retained for 2 hours. If desired, the patient may rotate positions every 15 minutes, for maximum area-contact.
The following schedule is suggested as a Guide to Dosage Adjustment:
Guide to Dosage Adjustment
Nadir After Prior Dose Leukocytes Platelets | Percentage of Prior Dose to be Given | ||||
|---|---|---|---|---|---|
| > 4000 | >100 000 | 100% | |||
| 3000 - 3999 | 75 000 – 99 999 | 100% | |||
| 2000 - 2999 | 25 000 – 74 999 | 70% | |||
| <2000 | <25000 | 50% | |||
No repeat dosage should be given until leukocyte count has returned to 3000 and platelet count to 75 000.
When Mitomycin for Injection is used in combination with other myelosuppressive agents, the doses should be adjusted accordingly. If the disease continues to progress after two courses of mitomycin, the drug should be stopped since chances of response are minimal.
PHARMACEUTICAL INFORMATION
Drug Substance
| Common Name: | mitomycin |
|---|---|
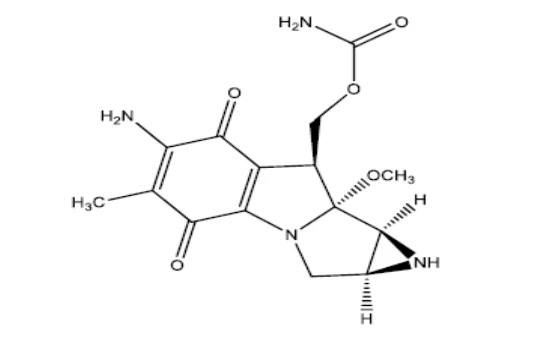
| Chemical Name: | [(1aS,8S,8aR,8bS)-6-Amino-8a-methoxy-5-methyl-4,7-dioxo-1,1a,2,4,7,8,8a,8 b-octahydroazirino[2’,3’:3,4]pyrrolo[1,2-a]-indol-8-yl]methyl carbamate (Mitomycin C). |
| Structural Formula: | |
| Molecular Formula: | C15H18N4O5 |
| Molecular Weight: | 334.3 g / mol |
| Description: | Mitomycin is blue-violet crystals or crystalline powder. It has a melting point of 360°C and is slightly soluble in water, freely soluble in dimethylacetamide, sparingly soluble in methanol, slightly soluble in acetone. |
Composition
Each vial contains mitomycin 20 mg and mannitol 40 mg.
Stability and Storage Recommendations
Store at controlled room temperature (15° - 30°C) protected from light.
Reconstituted Solutions
Solutions for Reconstitution: Sterile Water for Injection
Reconstitution Table
| Vial Size | Diluent Added to Vial (mL) | Approximate Available Volume (mL) | Approximate Concentration (mg/mL) |
|---|---|---|---|
| 20 mg | 40 | 39.0 | 0.5 |
 |
Shake well until dissolved. If the product does not dissolve immediately, shake under warm tap water for approximately two minutes until a solution is obtained. All steps of dilution and administration must be conducted using non-PVC materials and containers.
Reconstituted with Sterile Water for Injection to a concentration of 0.5 mg / mL, Mitomycin for Injection is stable for 72 hours refrigerated or 6 hours at controlled room temperature (15° - 30°C), protected from light.
Parenteral Products
Reconstituted solutions may be further diluted with one of the following diluents to a concentration of 20 to 40 µg / mL:
| IV Fluid | Storage condition | Stability |
|---|---|---|
| 0.9% Sodium Chloride Injection | 15° - 30°C | 3 hours |
| 2° - 8°C | 18 hours | |
| Sodium Lactate Injection | 15° - 30°C | 3 hours |
| 2° - 8°C | 6 hours |
The combination of mitomycin (5 mg to 15 mg) and heparin (1000 units to 10 000 units) in 30 mL of 0.9% Sodium Chloride Injection is stable for 12 hours at room temperature.
The reconstituted and diluted solutions should be inspected for discolouration, haziness, particulate matter and leakage prior to administration. Discard unused portion.
Handling and Disposal
- 1. Preparation of Mitomycin for Injection should be done in a vertical laminar flow hood (Biological Safety Cabinet - Class II).
- 2. Personnel preparing mitomycin should wear PVC gloves, safety glasses, disposal gowns and masks.
- 3. All needles, syringes, vials and other materials, which have come in contact with mitomycin should be segregated and incinerated at 1000°C or more. Sealed containers may explode. Intact vials should be returned to the manufacturer for destruction. Proper precautions should be taken in packaging these materials for transport.
Personnel regularly involved in the preparation and handling of Mitomycin for Injection should have bi-annual blood examinations.
AVAILABILITY OF DOSAGE FORMS
Mitomycin for Injection is supplied as a sterile lyophilized powder, preservative-free with mannitol in single use vials containing 20 mg of mitomycin, packaged individually and it is essentially free from visible particles. The vial stopper is not made with natural rubber latex.
PHARMACOLOGY
Mitomycin disappears rapidly from the plasma and there is no evidence of specific tissue localization.
After intravenous injection in dogs, mitomycin appeared in the urine within 5 to 6 minutes. Eighteen to twenty-nine percent is recovered within one hour. Simultaneous creatinine clearance studies indicate that excretion is primarily by glomerular filtration.
In children given intravenous doses, the urinary recovery was 5 to 20% within one hour and was essentially complete in two hours.
TOXICOLOGY
Acute Toxicity
| Species | Route | Number of Successive Daily Doses | LD50 (mg / kg / day) |
|---|---|---|---|
| Mice | Intraperitoneal | 1 | 8.5 |
| Mice | Intraperitoneal | 5 | 2.3 |
| Mice | Intravenous | 1 | 7.83 |
| Rats | Intraperitoneal | 1 | 2.5 |
| Rats | Intraperitoneal | 5 | 1.0 |
| Rats | Intravenous | 1 | 3.41 |
| Dogs | Intravenous | 1 | 1.25 |
| Dogs | Intravenous | 10 | 0.125 |
Repeated Dose Toxicity in Monkeys
No pharmacotoxic signs were observed following intravenous injections of 0.2 or 0.4 mg / kg / day given for 10 consecutive days.
At higher dosage levels (up to 3.2 mg / kg) dose-related pharmacologic signs included moderate to marked anorexia, soft stools, diarrhea, decreased activity, depression, and weight loss. An increase in BUN was noted and on autopsy, damage to renal tubules and the hematopoietic tissue was found.
The toxicity of mitomycin in the four species studied is fairly uniform. Moreover, the constancy of the total dose required to produce lethal effects has been suggested in the toxicity studies. The LD50 as a single intravenous dose was about the same as the total dose in a ten-day schedule.
Clinical signs of intoxication in animals were intestinal and hematopoietic disturbances, hyperthermia non-related to agranulocytosis, tissue hemorrhages, and necrotizing nephrosis. Therefore, diarrhea and neutropenia may offer suitable warnings of impending severe intoxication in humans.
REFERENCES
Ashizawa T, Okabe M. Gomi K, Hirata T. Reduced bone marrow toxicity of KW-2149, a mitomycin C derivative, in mice. Anti-Cancer Drugs 1993; 4:181-188.
Balson PJ, Roberts DF, Chromosome disorders. In: Davies DM (Ed) Textbook of Adverse Drug Reactions, Oxford University Press, Toronto 1977:54-63.
Barbhaiya RH, Papp EA, Van Harken DR, Smyth RD. Pharmacokinetics of mitomycin C in dogs: application of a high-performance liquid chromatographic assay. J Pharm Sci 1984; 73(9):
1220-1223.
Buroker T, Kim PN, Groppe C, et al. 5 FU infusion with mitomycin-C vs. 5 FU infusion with methyl-CCNU in the treatment of advanced upper gastrointestinal cancer. Cancer 1979; 44(4):1215-1221.
Buroker TR, Kim PN Baker LH et al. Mitomycin-C alone and in combination with infused
5-fluorouracil in the treatment of disseminated gastrointestinal carcinomas. Med Pediatr Oncol 1978; 4:35-42.
Buzdar AU, Legha SS, Luna MA, et al. Pulmonary toxicity of mitomycin. Cancer 1980; 45(2): 236-244.
Chaube S, Murphy ML. The teratogenic effects of the recent drugs active in cancer chemotherapy. Adv Teratol 1968; 3:181-237.
Colsky J. Clinical studies of mitomycin C in patients with metastatic cancer. Proc Am Assoc Cancer Res 1964; 5(44):12.
Early K, Elias EG, Mittelman A, Albert D, Murphy GP. Mitomycin C in the treatment of metastatic transitional cell carcinoma of urinary bladder. Cancer 1973; 31(5):1150-1153.
Fantel AG, Barber CV Tumbic R. The role of oxygenation in the embryotoxicity of three bioreducible agents. Teratology 1992; 45(5):510.
Franklin R, Steiger Z, Vaishampayan G, et al. Combined modality therapy for esophageal squamous cell carcinoma. Cancer 1983; 51(6):1062-1071.
Fujita H. Comparative studies on the blood level, tissue distribution, excretion and inactivation of anticancer drugs. Jap J Clin Oncol 1871; 12(1):151-162.
Ginsberg SJ, Comis RL. The pulmonary toxicity of antineoplastic agents. Semin Oncol 1982; 9(1):34-51.
Hattori T, Inokuchi K, Taguchi T, Abe O. Postoperative adjuvant chemotherapy for gastric cancer, the second report. Analysis of data on 2873 patients followed for five years. Jpn J Surg
1986; 16(3):175-180.
Henry NM, Koontz WW, Barton B, et al. Intravesical thiotepa versus mitomycin C in patients with TA, T1 and TIS transitional cell carcinoma of the bladder: a phase III prospective randomized study. J Urol 1988; 140(6):1390-1393.
Isaka S, Okano T, Shimazaki J, et al. Prophylaxis of superficial bladder cancer with instillation of adriamycin or mitomycin C. Cancer Chemother Pharmacol 1987; 20 (Suppl.):S77-S80.
Jolivet J, Giroux L, Laurin S, et al. Microangiopathic hemolytic anemia, renal failure, and noncardiogenic pulmonary edema: a chemotherapy-induced syndrome. Cancer Treat Rep 1983; 67(5):429-434.
Kris MG, Pablo D, Gralla RJ, et al. Dyspnea following vinblastine or vindesine administration in patients receiving mitomycin plus vinca alkaloid combination therapy. Cancer Treat Rep 1984; 68(7-8):1029-1031.
Liu K, Mittelman A, Sproul EE, Elias EG. Renal toxicity in man treated with mitomycin C. Cancer 1971; 28(5):1314-1320.
Luedke D, McLaughlin TT, Daughaday C, et al. Mitomycin C and vindesine associated pulmonary toxicity with variable clinical expression. Cancer 1985; 55(3):542-545.
Martino S, Baker LH, Pollard RJ, et al. Pulmonary toxicity of mitomycin. In: Carter SK and Crooke ST (Ed's) Mitomycin C - Current Status and New Developments, Academic Press, New York. 1979;231-242.
Metzger U, Laffer U, Aeberhard P, et al. Randomized multicenter trial of adjuvant intraportal chemotherapy for colorectal cancer SAKK 40/81. Acta Chir Scand 1990; 156(6-7): 467-474.
Milliken ST, Tattersall MHN, Woods RL, et al. Metastatic adenocarcinoma of unknown primary site. A randomized study of two combination chemotherapy regimens. Eur J Cancer Clin Oncol 1987; 23(11):1645-1648.
Mishina T, Oda K, Murata S, et al. Mitomycin C bladder instillation therapy for bladder tumors. J Urol 1975; 114:217-219.
Nakajima T, Fukami A, Ohashi I, Kajitani T. Long-term follow-up study of gastric cancer patients treated with surgery and adjuvant chemotherapy with mitomycin C. 1978; 16(5):209-216.
Neild VS, Sanderson KV, Riddle PR. Dermatitis due to mitomycin bladder instillations. JR Soc Med 1984; 77:610-611.
Philips FS, Schwartz HS, Sternberg SS. Pharmacology of mitomycin C, toxicity and pathologic effects. Cancer Res 1960; 20:1354-1361.
Pogwizd SM, Lerner SA. Mechanisms of action of antimicrobial agents. In: O'Leary W (Ed) Practical Handbook of Microbiology. CRC Press, Inc., Boca Raton, Florida. 1989:603-620.
Rao SX, Ramaswamy G, Levin M, McCravey JW. Fatal acute respiratory failure after vinblastine- mitomycin therapy in lung carcinoma. Arch Intern Med 1985;145:1905-1907.
Tsushima T, Matsumura Y, Ozaki Y, et al. Prophylactic intravesical instillation therapy with adriamycin and mitomycin C in patients with superficial bladder cancer. Cancer Chemother Pharmacol 1987; 20(Suppl.):S72-S76.
Wood HA, Ellerhorst-Ryan JM. Delayed adverse skin reactions associated with mitomycin-C administration. Oncol Nurs Forum 1984; 11(4):14-18.
Zincke H, Benson RC, Hilton JF, Taylor WF. Intravesical thiotepa and mitomycin C treatment immediately after transurethral resection and later for superficial (stages Ta and Tis) bladder cancer: a prospective, randomized, stratified study with crossover design. J Urol 1985;
134(6):1110-1114.
Acronyms in Cancer Chemotherapy, Fifth Edition, 1990. Evans WK, Van der Vliet W, Eli Lilly Canada Inc. 1990:160-161.
AHFS Drug Information 1994. American Society of Hospital Pharmacists Inc. Bethesda, MD, USA. 1994:668-670.
Drug Facts and Comparisons, 1993 Edition. Facts and Comparisons, St. Louis Miss, USA. 1993:2578-2579.
Physicians Desk Reference 47th Edition, 1993. Medical Economics Data, Montvale NJ, USA. 1993:749-751.
USPDI Drug Information for the Health Care Professional Volume 1, 13th Edition, 1993. United States Pharmacopeial Convention Inc., Taunton Mass, USA. 1993; 1950-1953.
Mitomycin for Injection USP Product Monograph, Teva Canada limited, Canada. Control No.:202039, Date of Preparation: June 30, 2017.
PrMITOMYCIN FOR INJECTION USP (Sterile Lyophilized Powder, 20 mg mitomycin per vial) Control #: 216814, Product Monograph, Accord Healthcare Inc., (July 16, 2018).
Reporting Side Effects You can report any suspected side effects associated with the use of health products to Health Canada by:
|
|---|
| NOTE: Contact your healthcare professional if you need information about how to manage your side effects. The Canada Vigilance Program does not provide medical advice. |
If you want more information about Mitomycin for Injection:
- Talk to your healthcare professional
- Find the full product monograph that is prepared for healthcare professionals and includes this Patient Medication Information by visiting the Health Canada website (https://www.canada.ca/en/health-canada/services/drugs-health-products/drug-products/drug-product-database.html); or by calling the sponsor http://www.eugiapharma.com at 1-855-648-6681.
Eugia Pharma Inc.
3700 Steeles Avenue West, Suite # 402
Woodbridge, Ontario, L4L 8K8
CANADA
Date of Revision: MAY 22, 2025