


Product Monograph - Mylan-Ranitidine
INDICATIONS AND CLINICAL USE
MYLAN-RANITIDINE (ranitidine hydrochloride) tablets are indicated for the treatment of duodenal ulcer, benign gastric ulcer, reflux esophagitis, post-operative peptic ulcer, Zollinger-Ellison Syndrome, and other conditions where reduction of gastric secretion and acid output is desirable. These include the following:
- the treatment of nonsteroidal anti-inflammatory drug (NSAID)-induced lesions, both ulcers and erosions, and their gastrointestinal (GI) symptoms and the prevention of their recurrence;
- the prophylaxis of GI hemorrhage from stress ulceration in seriously ill patients;
- the prophylaxis of recurrent hemorrhage from bleeding ulcers;
- the prevention of Acid Aspiration Syndrome from general anaesthesia in patients considered to be at risk for this, including obstetrical patients in labour, and obese patients.
In addition, MYLAN-RANITIDINE is indicated for the prophylaxis and maintenance treatment of duodenal or benign gastric ulcer in patients with a history of recurrent ulceration.
CONTRAINDICATIONS
MYLAN-RANITIDINE (ranitidine hydrochloride) is contraindicated for patients known to have hypersensitivity to ranitidine or to any ingredient in the formulation. For a complete listing, see COMPOSITION.
WARNINGS
Gastric Ulcer
Treatment with a histamine H2-antagonist may mask symptoms associated with carcinoma of the stomach and, therefore, may delay diagnosis of that condition. Accordingly, where gastric ulcer is suspected the possibility of malignancy should be excluded before therapy with MYLAN-RANITIDINE (ranitidine hydrochloride) is instituted.
Cyanocobalamin (Vitamin B12) Deficiency
The prolonged use of H2-receptor antagonists, may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of cyanocobalamin (vitamin B12) deficiency.
Concomitant NSAID Use
Regular supervision of patients who are taking non-steroidal anti-inflammatory drugs concomitantly with MYLAN-RANITIDINE is recommended especially in the elderly and in those with a history of peptic ulcer. Baseline endoscopy and histological evaluation is necessary to rule out gastric carcinoma.
Use in Patients with a History of Acute Porphyria
Rare clinical reports suggest that ranitidine may precipitate acute porphyric attacks. Therefore, ranitidine should be avoided in patients with a history of acute porphyria.
Fertility
There are no data on the effects of ranitidine hydrochloride on human fertility. There were no effects on male and female fertility in animal studies (see TOXICOLOGY).
Use in Pregnancy and Nursing Mothers
The safety of ranitidine hydrochloride in the treatment of conditions where a controlled reduction of gastric secretion is required during pregnancy has not been established. Reproduction studies performed in rats and rabbits have revealed no evidence of ranitidine hydrochloride induced impaired fertility or harm to the fetus. Ranitidine crosses the placenta. Nevertheless, if the administration of MYLAN-RANITIDINE is considered to be necessary, its use requires that the potential benefits be weighed against possible hazards to the patient and to the fetus.
Ranitidine hydrochloride is secreted in breast milk in lactating mothers but the clinical significance of this has not been fully evaluated. Like other drugs, MYLAN-RANITIDINE should only be used during nursing if considered essential.
Children
Experience with ranitidine hydrochloride in children is limited. It has, however, been used successfully in children aged 8 to 18 years in oral doses up to 150 mg twice daily.
PRECAUTIONS
General
Use in Impaired Renal Function
Ranitidine hydrochloride is excreted via the kidneys and, in the presence of renal impairment, plasma levels of ranitidine hydrochloride are increased and elimination prolonged. Accordingly, it is recommended in such patients, to decrease the dosage of MYLAN-RANITIDINE by one half. Accumulation of MYLAN-RANITIDINE with resulting elevated plasma concentrations will occur in patients with renal impairment (creatinine clearance less than 50 ml/min); a recommended daily dose of oral ranitidine in such patients should be 150 mg.
Interaction with Other Drugs
Ranitidine has the potential to affect the absorption, metabolism or renal excretion of other drugs. The altered pharmacokinetics may necessitate dosage adjustment of the affected drug or discontinuation of treatment.
Interactions occur by several mechanisms including:
- 1) Inhibition of cytochrome P450-linked mixed function oxygenase system:
Ranitidine at usual therapeutic doses does not potentiate the actions of drugs which are inactivated by this enzyme system such as diazepam, lidocaine, phenytoin, propranolol and theophylline.
There have been reports of altered prothrombin time with coumarin anticoagulants (e.g. warfarin). Due to the narrow therapeutic index, close monitoring of increased or decreased prothrombin time is recommended during concurrent treatment with ranitidine.
- 2) Competition for renal tubular secretion:
Since ranitidine is partially eliminated by the cationic system, it may affect the clearance of other drugs eliminated by this route. High doses of ranitidine (e.g., such as those used in the treatment of Zollinger-Ellison syndrome) may reduce the excretion of procainamide and N-acetylprocainamide resulting in increased plasma levels of these drugs.
- 3) Alteration of gastric pH:
The bioavailability of certain drugs may be affected. This can result in either an increase in absorption (e.g. triazolam, midazolam) or a decrease in absorption (e.g. ketoconazole, atazanavir, delaviridine, gefitnib).
Sporadic cases of drug interactions have been reported in elderly patients involving both hypoglycaemic drugs and theophylline. The significance of these reports cannot be determined at present, as controlled clinical trials with theophylline and ranitidine hydrochloride have not shown interaction.
If high doses (two grams) of sucralfate are co-administered with MYLAN-RANITIDINE, the absorption of ranitidine hydrochloride may be reduced. This effect is not seen if sucralfate is taken at least two hours after ranitidine hydrochloride administration.
Special Populations
In patients such as the elderly, persons with chronic lung disease, diabetes or the immunocompromised, there may be an increased risk of developing community acquired pneumonia. A large epidemiological study showed an increased risk of developing community acquired pneumonia in current users of H2 receptor antagonists versus those who had stopped treatment, with an observed adjusted relative risk increase of 1.63 (95% CI, 1.07-2.48).
Use in the Elderly
Since malignancy is more common in the elderly, particular consideration must be given to this before therapy with MYLAN-RANITIDINE is instituted. Elderly patients receiving non-steroidal anti-inflammatory drugs concomitantly with MYLAN-RANITIDINE should be closely supervised.
As with all medication in the elderly, when prescribing MYLAN-RANITIDINE, consideration should be given to the patient's concurrent drug therapy. Sporadic cases of drug interaction have been reported in elderly patients involving both hypoglycaemic drugs and theophylline. The significance of these reports cannot be determined at present, as controlled clinical trials with theophylline and ranitidine hydrochloride have not shown interaction. Elderly patients may be at increased risk for confusional states and depression.
ADVERSE REACTIONS
The following adverse reactions have been reported as events in clinical trials or in the routine management of patients treated with ranitidine hydrochloride. A cause and effect relationship to ranitidine hydrochloride is not always established.
Central Nervous System
Headache, sometimes severe; malaise; dizziness; somnolence; insomnia; vertigo; and reversible blurred vision suggestive of a change in accommodation. Isolated cases of reversible mental confusion, agitation, depression, hallucinations have been reported, predominantly in severely ill elderly patients. In addition, reversible involuntary movement disorders have been reported rarely.
Cardiovascular
Isolated reports of tachycardia, bradycardia, premature ventricular beats, AV block have been noted. Asystole has been reported in very few individuals with and without predisposing conditions following IV administration and has not been reported following oral administration of ranitidine hydrochloride. (See PRECAUTIONS, DOSAGE AND ADMINISTRATION).
Gastrointestinal
Constipation, diarrhea, nausea/vomiting and abdominal discomfort/pain.
Hepatic
With oral administration, there have been occasional reports of hepatitis, hepatocellular or hepatocanalicular or mixed, with or without jaundice. In such circumstances, ranitidine should be discontinued immediately. These are usually reversible, but in exceedingly rare circumstances, death has occurred.
Renal
Very rare cases of acute interstitial nephritis have been reported.
Musculoskeletal
Rare reports of arthralgia and myalgia.
Haematologic
Blood count changes (leukopenia, thrombocytopenia) have occurred in a few patients. These are usually reversible. Rare cases of agranulocytosis or pancytopenia, sometimes with marrow hypoplasia or aplasia have been reported.
Endocrine
No clinically significant interference with endocrine or gonadal function has been reported. There have been a few reports of breast symptoms and breast conditions (such as gynaecomastia and galactorrhoea).
Dermatologic
Rash, including cases suggestive of mild erythema multiforme. Rare cases of vasculitis and alopecia have been reported.
Other
Rare cases of hypersensitivity reactions (including chest pain, bronchospasm, fever, rash, eosinophilia, anaphylaxis, urticaria, angioneurotic edema, hypotension) and small increases in serum creatinine have occasionally occurred after a single dose. Acute pancreatitis and reversible impotence has been reported rarely.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
There is no experience to date with deliberate overdosage. The usual measures to remove unabsorbed drug from the gastrointestinal tract (including activated charcoal or syrup of ipecac), clinical monitoring and supportive therapy should be employed.
| For management of a suspected drug overdose, contact your regional Poison Control |
| Centre immediately. |
DOSAGE AND ADMINISTRATION
Duodenal ulcer or benign gastric ulcer
300 mg once daily at bedtime or 150 mg twice daily taken in the morning and before retiring. It is not necessary to time the dose in relation to meals. In most cases of duodenal ulcer and benign gastric ulcer, healing will occur in four weeks. In the small number of patients whose ulcers may not have fully healed, these are likely to respond to a further four week course of therapy. In the treatment of duodenal ulcers, 300 mg twice daily for 4 weeks may be of benefit when more rapid healing is desired.
Maintenance therapy
Duodenal ulcers, benign gastric ulcers: Patients who have responded to short-term therapy, particularly those with a history of recurrent ulcer, may benefit from chronic maintenance therapy at a reduced oral dosage of 150 mg once daily at bedtime.
In the management of duodenal ulcers, smoking is associated with a higher rate of ulcer relapse (up to 9.2 times higher in one trial), and such patients should be advised to stop smoking. In those patients who fail to comply with such advice, 300 mg nightly provides additional therapeutic benefit over the 150 mg once daily dosage regimen.
Reflux esophagitis
Acute treatment
300 mg once daily at bedtime, or alternatively 150 mg twice daily, taken in the morning and before retiring for up to eight weeks. In patients with moderate to severe esophagitis, the dosage of ranitidine may be increased to 150 mg four times daily for up to 12 weeks.
Long-term Management
For the long-term management of reflux esophagitis, the recommended adult oral dose is 150 mg twice daily.
Post-operative peptic ulcer
150 mg twice daily, taken in the morning and before retiring.
Pathological hypersecretory conditions (Zollinger-Ellison Syndrome)
150 mg three times daily may be administered initially. In some patients, it may be necessary to administer MYLAN-RANITIDINE 150 mg doses more frequently. Doses should be adjusted to individual patient needs. Doses up to six grams per day have been well tolerated.
Treatment of NSAID-induced lesions (both ulcers and erosions) and their gastrointestinal symptoms and prevention of their recurrence
In ulcers following non-steroidal anti-inflammatory drug therapy or associated with continued non-steroidal anti-inflammatory drugs, 150 mg twice daily for 8-12 weeks may be necessary. For the prevention of non-steroidal anti-inflammatory drug associated ulcer recurrence, 150 mg twice daily may be given concomitantly with non-steroidal anti-inflammatory drug therapy.
Prophylaxis of acid aspiration syndrome (AAS)
150 mg the evening prior to anaesthesia induction is recommended, however, 150 mg two hours before anaesthesia induction is also effective. For the prevention of AAS in pre-partum patients who elect for anaesthesia, 150 mg every six hours may be employed, but if general anaesthesia is warranted, a non-particulate oral antacid (for example, sodium citrate) could supplement MYLAN-RANITIDINE therapy. In an emergency situation, the use of alkalis, antacids, and meticulous anaesthetic technique is still necessary as MYLAN-RANITIDINE does not affect the pH and volume of the existing gastric content.
Prophylaxis of hemorrhage from stress ulceration in seriously ill patients or prophylaxis of recurrent hemorrhage in patients bleeding from peptic ulceration who are currently managed by intravenous ranitidine.
An oral dose of 150 mg twice daily may be substituted for the injection once oral feeding commences.
Dosage for the Elderly
For all conditions listed above, the drug dosage for the elderly who are seriously ill should start at the lowest recommended dose and be adjusted as necessary with close supervision.
Patients over 50 years of age (see ACTIONS AND CLINICAL PHARMACOLOGY, Patients over 50 years of age).
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: ranitidine hydrochloride
Chemical Name: N-[2-[[[5-[(Dimethylamino)methyl]-2-furanyl]methyl]thio]ethyl]-N'-methyl-2-nitro-1,1-ethenediamine, hydrochloride.
Molecular Formula: C13H22N4O3S•HCl
Molecular Mass: 350.87 g/mol (as hydrochloride salt)
Structural Formula:
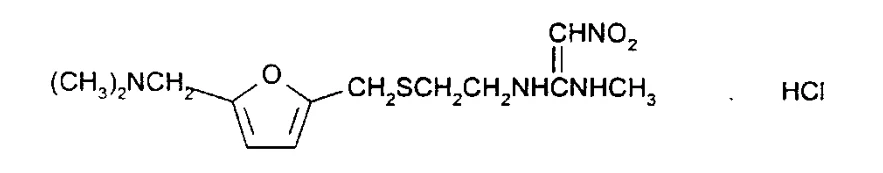
Description: Ranitidine hydrochloride is a white to pale yellow, crystalline, practically odourless powder. It is very soluble in water, moderately soluble in alcohol and sparingly soluble in chloroform. It melts at about 140°C, with decomposition. Ranitidine hydrochloride is sensitive to light and moisture.
STORAGE AND STABILITY
MYLAN-RANITIDINE tablets should be stored in a dry place between 15°C and 30°C. Protect from light.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Availability
Mylan-Ranitidine 150 mg tablets are supplied in cartons containing 3 blister strips of 10 tablets, in cartons containing 3 blister strips of 20 tablets and in HDPE bottles of 60’s, 100’s and 500’s.
Mylan-Ranitidine 300 mg tablets are supplied in cartons containing 3 blister strips of 10 tablets and in HDPE bottles of 100’s and 500’s.
Composition
Mylan-Ranitidine 150 mg Tablets
Mylan-Ranitidine 150 mg tablets are white to off-white, round, biconvex, film-coated, tablets, with "G" on one side and "150" on the other.
Each tablet contains 168 mg of ranitidine hydrochloride and the following non-medicinal ingredients: microcrystalline cellulose and magnesium stearate. The film-coating suspension contains the following excipients: hydroxypropyl methylcellulose, polydextrose, polyethylene glycol, titanium dioxide and triethyl citrate.
Mylan-Ranitidine 300 mg Tablets
Mylan-Ranitidine 300 mg tablets are white to off-white, capsule shaped, film-coated, tablets, with "G" on one side and "300" on the other.
Each tablet contains 336 mg of ranitidine hydrochloride and the following non-medicinal ingredients: croscarmellose sodium, magnesium stearate and microcrystalline cellulose. The coating contains: hydroxypropyl methylcellulose, polydextrose, polyethylene glycol, titanium dioxide and triethyl citrate.
PHARMACOLOGY
Animal Pharmacology
Ranitidine is a potent competitive reversible, selective antagonist of histamine at H2-receptors in vitro and in vivo. Thus, ranitidine antagonised the actions of histamine at H2-receptors in the rat isolated uterus and in the guinea pig isolated atrium. Ranitidine is not an anticholinergic agent. On a molar basis, ranitidine is 4 to 5 times more active than cimetidine with a pA2 value of 7.2. In concentrations 1,000 times greater than those required to block H2-receptors, it failed to block either H1-receptors or muscarinic receptors in the guinea pig isolated ileum. The beta-adrenoceptor responses of the rat uterus and guinea pig atrium to isoprenaline were also unaffected by ranitidine.
Blockade of histamine H2-receptors in the stomach in vivo is the pharmacological action of ranitidine with greatest immediate clinical relevance. Ranitidine inhibits gastric secretion induced by various secretagogues in both the rat and dog.
In the conscious dog with a Heidenhain pouch, ranitidine given orally or intravenously antagonised gastric acid secretion induced by histamine, pentagastrin and bethanechol. Ranitidine was 5 to 10 times more active than cimetidine. However, both ranitidine and cimetidine had similar time curves of action. Ranitidine also inhibited the gastric secretory response to food in the conscious fistulated dog.
Ranitidine inhibited acid secretion in the perfused stomach of the anaesthetised rat, and acetylsalicylic acid-induced gastric lesion formation in the conscious rat, both in the presence and absence of excess hydrochloric acid. Measurements of the ratio of mucosal blood flow to acid secretion show that the inhibitory action of ranitidine upon gastric acid secretion cannot be attributed to changes in blood flow.
There were no behavioural effects in the mouse and rat after oral administration of 800 mg/kg ranitidine. Cats and dogs dosed with ranitidine 80 mg/kg orally, exhibited no behavioural effects indicative of an action on the central nervous system, although at this high dose level in the dog there was an indication of peripheral vasodilation and skin irritation due to released histamine. Ranitidine, when coadministered with the following CNS modulating preparations; codeine, hexobarbitone, ethyl alcohol, chlordiazepoxide, chlorpromazine, imipramine, α-methyldopa, reserpine, apomorphine or pentylenetetrazol, did not alter the pharmacological effects of either preparation.
At a dose level 45 times the antisecretory ED50, intravenous infusion of ranitidine had no effect on the heart rate, blood pressure or electrocardiogram of the anaesthetised dog. The respiratory system was unaffected by ranitidine after oral doses in the mouse, rat, rabbit, cat and dog and after intravenous doses in the dog.
In the conscious dog, ranitidine had no appreciable effect on blood pressure or heart rate when administered orally at 10 mg/kg. There were short-lived falls in diastolic blood pressure after an intravenous dose of 10 mg/kg, 370 times the antisecretory dose level. There was no evidence of arrhythmia nor of any electrocardiographic abnormality.
Long-term toxicity studies have shown that ranitidine does not possess antiandrogenic activity nor does it displace dihydrotestosterone from the androgen binding sites.
Metoclopramide, atropine and acetylsalicylic acid in the rat produced no change in the antisecretory activity of ranitidine.
The effect of ranitidine on anti-inflammatory drugs was varied. There was no effect on the anti-inflammatory action of prednisolone, but the anti-inflammatory action of indomethacin was enhanced. Administration of ranitidine reduced the frequency of acetylsalicylic acid- and indomethacin-induced gastric erosions. The antinociceptive action of acetylsalicylic acid was reduced after ranitidine treatment.
Ranitidine, unlike cimetidine, does not inhibit the hepatic mixed function oxygenase system. Spectral interaction studies have shown that whilst cimetidine binds strongly to cytochrome P450, ranitidine has only weak affinity for this enzyme. Cimetidine is known to impair the metabolism of pentobarbitone and warfarin. In doses of up to 166 mg/kg in the rat, ranitidine had no effect on the pentobarbitone sleeping time or the pharmacokinetics and pharmacodynamics of warfarin.
Metabolism, Distribution and Excretion
The metabolism of ranitidine hydrochloride has been studied in four species of laboratory animal (mouse, rat, rabbit and dog) using radio-labelled drug. The drug was rapidly absorbed after oral administration. In the mouse, rat and rabbit between 30% and 60% of the administered radioactivity was excreted in the urine, the remainder being recovered in the feces.
In the mouse 47% was excreted in the urine within 24 hours. In the rat, N-demethylation of ranitidine was the major route of metabolism. 30% of the administered dose was excreted in the urine as unchanged drug, up to 14% as desmethylranitidine, 3-6% as the N-oxide and 4% as the S-oxide. In rat bile the major radioactive components were ranitidine and an unidentified metabolite known as "Fast-Running Metabolite" (FRM) which is thought to be a charge transfer complex of ranitidine with bile pigments.
In the rabbit, sulphoxidation of ranitidine was the major route of metabolism, 18% of the administered dose being excreted in the urine as unmetabolised ranitidine, 8% as S-oxide, 2-4% as the N-oxide, and 2-4% as desmethylranitidine.
In the dog up to 70% of the administered dose was excreted in the first 24 hours. About 40% of the drug was excreted in the urine as unchanged ranitidine and up to 30% as the N-oxide, N-oxidation being the main route of metabolism of ranitidine in the dog. The N-oxide was also the major radioactive component present in dog bile together with small amounts of unchanged ranitidine and FRM.
In the rat, rabbit and dog, less than 10.1% of ranitidine in plasma is protein bound. Within one to seven days of administration of radio-labelled drug in the rat and dog over 99% of the radioactivity was cleared from the body. In common with many drugs, radioactivity persisted in the uveal tract of these two species, the half-life in the dog uveal tract being of the order of 6 months. Ranitidine and its S-oxide have greater affinity for melanin than the desmethyl metabolite; the N-oxide is bound only to a small extent.
The placental transfer of radioactive ranitidine and its metabolites has been studied in the pregnant rat and rabbit. Whole body autoradiography of rat and rabbit fetuses showed that small amounts of radioactivity were present in the uveal tract of the fetal eye in both species, in the gall bladder and intestine of the rabbit fetus and in the bladder of the rat fetus. Radioactivity was also detected in the salivary and mammary glands of the maternal rat and at very low concentration, in the milk.
Human Pharmacokinetics
Serum concentrations necessary to inhibit 50% of stimulated gastric acid secretion are estimated to be 36 to 94 ng/mL. Following a single oral dose of 150 mg, serum concentrations of ranitidine are in this range for up to 12 hours. There is a relationship between plasma concentrations of ranitidine and suppression of gastric acid production but wide interindividual variability exists.
Ranitidine is 50% absorbed after oral administration compared to an IV injection with mean peak levels of 440 to 545 ng/mL occurring two to three hours after a 150 mg dose. The elimination half-life is 2 to 3 hours.
The major route of elimination is renal. After oral administration of 150 mg 3-H ranitidine, 96% of the dose was recovered, 26% in the feces and 70% in urine of which 35% was unchanged parent drug. Less than 3% of the dose is excreted in bile. Renal clearance is approximately 500 mL/min, which exceeds glomerular filtration indicating net renal tubular secretion.
Ranitidine is absorbed very rapidly after an intramuscular injection. Mean peak levels of 576 ng/mL occur within 15 minutes or less following a 50 mg intramuscular dose. Absorption from intramuscular sites is virtually complete, with a bioavailability of 90% to 100% compared with intravenous administration.
The principal route of excretion is the urine, with approximately 30% of the orally-administered dose collected in the urine as unchanged drug in 24 hours. Renal clearance is about 530 mL/min, indicating active tubular excretion, with a total clearance of 760 mL/min. The volume of distribution ranges from 96 to 142 L.
Studies in patients with hepatic dysfunction (compensated cirrhosis) indicate that there are minor, but clinically insignificant alterations in ranitidine half-life, distribution, clearance and bioavailability.
Serum protein binding averages 15%.
The gastric antisecretory activity of ranitidine metabolites has been examined. In man, both the principal metabolite in the urine, the N-oxide (4% of the dose) and the S-oxide (1%) possess weak H2-receptor blocking activity but desmethylranitidine (1%) is only 4 times less potent than ranitidine in the rat and half as potent as ranitidine in the dog.
CLINICAL TRIALS
In 6 clinical trials examining the healing of duodenal ulcers in 1,500 patients, a dose of 300 mg daily for 4 weeks was found to have an 83% healing rate; however, increasing the dose to 300 mg twice daily gave significantly better results (92% healed at 4 weeks; p<0.001).
Comparative Bioavailability Studies
Mylan Pharmaceuticals ULC markets Pr MYLAN-RANITIDINE using two alternate formulations, which have been shown to be bioequivalent with Pr ZANTAC®. Therefore, data from two comparative bioavailability studies is presented below.
A double-blind, single oral dose, two-way crossover bioequivalence study of Pr MYLAN-RANITIDINE 150 mg (Mylan Pharmaceuticals ULC) and Pr ZANTAC® (ranitidine) 150 mg (GlaxoSmithKline Inc.) was performed.
A summary of the results is presented in the following table.
Ranitidine (1 x 150 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 2416 2510 (24.9) | 2566 2652 (23.2) | 94 | 90-100 |
AUCI (ng•h/mL) | 2490 2582 (24.6) | 2644 2725 (22.8) | 94 | 90-100 |
Cmax (ng/mL) | 513 547 (36.5) | 556 594 (39.0) | 92 | 84-103 |
Tmax§ (h) | 2.54 (0.706) | 2.63 (0.980) | ||
T½§ (h) | 2.59 (0.340) | 2.58 (0.362) | ||
* Pr Mylan-Ranitidine 150 mg tablets, manufactured by Mylan Pharmaceuticals ULC.
† Pr Zantac® 150 mg tablets, manufactured by GlaxoSmithKline Inc. (purchased in Canada).
§ Expressed as the arithmetic mean (CV%) only.
A double-blind, balanced, randomized, single oral dose, two–treatment, two-sequence, two-period, crossover bioequivalence study of Pr MYLAN-RANITIDINE 150 mg (Mylan Pharmaceuticals ULC) and Pr ZANTAC® (ranitidine) 150 mg (GlaxoSmithKline Inc.) was performed in healthy, adult male subjects (n=26) under fasting conditions.
A summary of the results is presented in the following table.
Ranitidine (1 x 150 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•hr/mL) | 3090.4 3182.8 (24) | 3172.4 3268.1 (25) | 97.4 | 93.3 – 100.8 |
AUCI (ng•hr/mL) | 3175.5 3182.8 (24) | 3255.2 3350.0 (24) | 97.5 | 93.6 – 101.6 |
Cmax (ng/mL) | 571.4 609.8 (36) | 592.8 615.9 (28) | 96.4 | 90.1 – 103.2 |
| Tmax§ (h) | 3.00 (32) | 2.95 (33) | ||
| T½§ (h) | 2.86 (15) | 2.92 (13) | ||
* Pr Mylan-Ranitidine 150 mg tablets, manufactured by Mylan Pharmaceuticals ULC.
† Pr Zantac® 150 mg tablets, manufactured by GlaxoSmithKline Inc. (purchased in Canada).
§ Expressed as the arithmetic mean (CV%) only.
A double-blind, single oral dose, three-way crossover bioequivalence study of Pr MYLAN-RANITIDINE 300 mg (Form 1) (Mylan Pharmaceuticals ULC) and Pr ZANTAC® (ranitidine) 300 mg (GlaxoSmithKline Inc.) was performed.
A summary of the results is presented in the following table.
Ranitidine (1 x 300 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 4574 4739 (22.6) | 4559 4647 (18.6) | 100.3 | 90-111 |
AUCI (ng•h/mL) | 4632 4798 (22.5) | 4622 4709 (18.3) | 100.2 | 90-111 |
Cmax (ng/mL) | 967.8 1016 (27.9) | 989.4 1010 (20.1) | 97.8 | 84-114 |
Tmax§ (h) | 2.714 (40.7) | 2.699 (28.0) | ||
T½§ (h) | 2.681 (15.5) | 2.605 (17.7) | ||
* Pr Mylan-Ranitidine 300 mg tablets, manufactured by Mylan Pharmaceuticals ULC.
† Pr Zantac® 300 mg tablets, manufactured by GlaxoSmithKline Inc. (purchased in Canada).
§ Expressed as the arithmetic mean (CV%) only.
A double-blind, balanced, randomized, single oral dose, two–treatment, two-sequence, two-period, crossover bioequivalence study of Pr MYLAN-RANITIDINE 300 mg (Mylan Pharmaceuticals ULC) and Pr ZANTAC® (ranitidine) 300 mg (GlaxoSmithKline Inc.) was performed in healthy, adult male subjects (n=26) under fasting conditions.
A summary of the results is presented in the following table.
Ranitidine (1 x 300 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•hr/mL) | 6718.0 6926.5 (22) | 7068.8 7175.7 (18) | 95.0 | 87.0-103.8 |
AUCI (ng•hr/mL) | 6825.3 7035.9 (22) | 7175.21 7179.9 (18) | 95.1 | 87.1-103.9 |
Cmax (ng/mL) | 1442.4 1527 (32) | 1448.1 1515 (31) | 99.6 | 89.9-110.8 |
| Tmax§ (h) | 2.73 (26) | 2.91 (29) | ||
| T½§ (h) | 3.52 (34) | 3.28 (18) | ||
* Pr Mylan-Ranitidine 300 mg tablets, manufactured by Mylan Pharmaceuticals ULC.
† Pr Zantac® 300 mg tablets, manufactured by GlaxoSmithKline Inc. (purchased in Canada).
§ Expressed as the arithmetic mean (CV%) only.
TOXICOLOGY
Toxicology, Impairment of Fertility, Carcinogenesis, and Mutagenesis
Ranitidine hydrochloride has been subjected to exhaustive toxicological testing which has demonstrated the lack of any specific target organ or any special risk associated with its clinical use.
Non-clinical data revealed no special hazard for humans based on conventional studies of safety pharmacology, repeated-dose toxicity, genotoxicity, carcinogenic potential and toxicity to reproduction and development.
Acute Toxicity Studies
In mice and rats, the intravenous LD50 is of the order of 75 mg/kg, whereas orally, even doses of 1,000 mg/kg are not lethal. In dogs, the oral minimum lethal dose is 450 mg/kg/day. High single doses of ranitidine (up to 80 mg/kg orally) show only minimal and reversible signs of toxicity, some of which are related to transitory histamine releases.
Long-Term Toxicity Studies
In the long-term toxicity and carcinogenicity studies, very high doses of ranitidine were given daily to mice (up to 2000 mg/kg/day) throughout their normal life-span, and to dogs (up to 450 mg/kg/day) for periods of up to one year.
These doses produced massive plasma ranitidine concentrations far in excess of those found in human patients receiving ranitidine at the recommended therapeutic dose. For example, in the dogs, peak plasma concentrations were in excess of 115 μg/mL and in mice basal plasma levels were in the range of 4-9 μg/mL. In man, after oral administration of 150 mg ranitidine, the mean peak plasma concentration (Cmax) was between 360 and 650 ng/mL.
In the rat, doses as high as 2,000 mg/kg/day were well tolerated, the only morphological change seen was the increased incidence of accumulations of foamy alveolar macrophages in the lungs. The accumulations of these cells is a natural phenomena in aging rats and chronic administration of a wide variety of drugs has been known to contribute to this process. Therefore, it is unlikely that the pharmacologic concentrations of ranitidine administered to these rats contributed to this natural process.
In the six-week and six-month oral studies in the dog (100 mg/kg/day) loose feces were occasionally detected, while in the six-month study loose stools were accompanied on eight occasions by mucus-like material and sometimes by blood, mostly from one dog. Loose feces, salivation and vomiting were observed in the 54-week dog study.
In isolated cases, dogs passed red-stained feces which occasionally tested positive for occult blood. When the dose level was increased from 100 mg/kg/day to 225 - 450 mg/kg/day, no further red-stained feces were seen, suggesting that any relationship to ranitidine is unlikely. Post-mortem examination of the dogs revealed no ranitidine-induced changes in the alimentary tract.
One dog had marginally raised levels of plasma alanine aminotransferase and alkaline phosphatase during the six-week study. This same dog also showed some necrotic foci in the liver. Small lesions of focal necrosis and fibrosis were also seen in one piece of liver from one female dog treated with 100 mg/kg for six months. No other differences were detected by light and electron microscopic examination of the treated and control livers. Since the focal lesions were seen in only one dog and were restricted to one piece of liver, it suggests that they were not caused by ranitidine.
Muscular tremors, an inability to stand, and rapid respiration were seen on occasion in dogs treated with 225 mg/kg/day in the 54-week study. The prevalence of these observations was increased when the dose was increased to a toxic level of 450 mg/kg/day. One dog died: no specific pathological changes or reason for the death was discovered.
Changes in the colour or granularity of the tapetum lucidum of the eye were detected in three dogs receiving the highest dose of ranitidine (450 mg/kg/day) during the 54-week study. In one dog this change was considered to be related to treatment. The change, a pallor of the tapetum, was reversible. No changes were seen with light or electron microscopic examination of the eye. The changes in the tapetum are of no clinical significance in humans since (i) humans do not have a tapetum lucidum and (ii) the changes were only seen at toxic pharmacological concentrations of ranitidine.
The mean serum glutamic pyruvic transaminase values for dogs treated at 450 mg/kg/day were significantly greater, albeit marginally, than the control values. These enzyme increases were not accompanied by any histological changes.
Reproduction Studies (Impairment of Fertility)
Reproduction studies were carried out in the rat and rabbit.
Rats were exposed to ranitidine before and during mating, throughout pregnancy, lactation and during the weaning period. No effects on the reproductive process were seen and there was no evidence of an anti-androgenic effect.
A total of 2,297 fetuses from rats treated with ranitidine were examined. There was no evidence that ranitidine is a rat teratogen. Cleft palates occurred in fetuses from both treatment groups, however, there were significantly more in the control rat population.
A total of 944 fetuses from rabbits treated with ranitidine were examined; no drug-related adverse events or abnormalities in the fetuses were observed.
Rabbits receiving a bolus intravenous injection of ranitidine (10 mg/kg) once daily on gestation days 7-16 exhibited a reduction in weight gain. Their fetuses weighed significantly less than fetuses of untreated controls. In addition, 12.4% of ranitidine-exposed fetuses had cleft palates. Reanalysis of this and a companion study performed to assess reproducibility demonstrated a lack of data reproducibility. Therefore, the effects observed in the first trial are aberrant, and should not form the basis for maternal or fetal toxicity.
In the subsequent study, no evidence of maternal or fetal toxicity was observed in rabbits dosed with 100 mg/kg ranitidine orally during days 2-29 of pregnancy. The peak plasma levels of ranitidine after a 100 mg/kg oral dose are similar to those obtained one minute after a 10 mg/kg dose administered intravenously (20-25 μg/mL). Therefore, no teratogenic effects of ranitidine have been demonstrated at doses of 10 mg/kg (IV) and 100 mg/kg (Tablets) in rabbits.
Carcinogenicity Studies
There is no evidence that ranitidine is a carcinogen. Long term toxicity and carcinogenicity studies have involved the treatment of 600 mice and 636 rats at doses up to 2,000 mg/kg for two years and 129 weeks respectively and 42 dogs at doses up to 450 mg/kg/day for periods up to one year. These dose levels are far in excess of those to be used therapeutically in man. None of these animals had any intestinal metaplasia. There was no evidence of a tumourigenic effect of ranitidine in any other tissue.
Mutagenesis
Ranitidine is not mutagenic at doses as great as 30 mg/plate in the Ames Assay utilizing Salmonella typhimurium (TA 1538, TA 98, TA 100 and TA 1537) or in doses of 9 mg/plate utilizing Escherichia coli (WP2 and WP2 uvrA) with or without activation.
Ranitidine at concentrations of 20-30 mg/plate had a weak direct mutagenic action in S. typhimurium TA 1535 and at 9 mg/plate in E. coli WP67. Ranitidine was not mutagenic at a concentration of 2 mg/mL in E. coli or S. typhimurium in the more sensitive Oral Solution microtitre fluctuation assay method. This weak direct mutagenic effect is of no clinical significance; the magnitudes of ranitidine concentration used in these assays are thousands of times greater than that attained therapeutically in human plasma.
The principal metabolites of ranitidine in man were not significantly mutagenic. This conclusion is supported by the following experiment. A test solution obtained by interacting ranitidine (10 mM) and sodium nitrite (40 mM) was mutagenic in S. typhimurium (TA 1535) but not in S. typhimurium (TA 1537) or in E. coli (WP67 or WP2 uvrA). This positive result is attributable to the presence of a nitrosonitrolic acid derivative AH 23729, which was mutagenic. When the sodium nitrite concentration was reduced to 15 mM or less, the solution was not mutagenic in any of the test microorganisms. The formation of AH 23729 requires concentrations of nitrous acid far in excess of those encountered in any probable physiological conditions. The other nitrosation products were not mutagenic in any of the microorganisms tested. There is no reason, therefore, for supposing that ranitidine is likely to be mutagenic in animals or man as a consequence of nitrosation in the stomach.
There is no evidence from long term toxicology, carcinogenicity and mutagenicity studies in animals to suggest that ranitidine is likely to have any deleterious effects in man when administered at therapeutic dose levels.
Selected Bibliography
- 1. Ashton MG, Holdsworth CD, Ryan FP, Moore M. Healing of gastric ulcers after one, two, and three months of ranitidine. Br Med J (Clin Res Ed) 1982; 284(6314):467-468.
- 2. Bell JA, Dallas FA, Jenner WN, Martin LE. The metabolism of ranitidine in animals and man [proceedings]. Biochem Soc Trans 1980; 8(1):93.
- 3. Bories P, Michel H, Duclos B, Beraud JJ, Mirouze J. Use of ranitidine, without mental confusion, in patients with renal failure. Lancet 1980; 2(8197):755.
- 4. Boyd EJ, Wilson JA, Wormsley KG. Review of ulcer treatment: role of ranitidine. J Clin Gastroenterol 1983; 5 Suppl 1:133-141.
- 5. Breen KJ, Bury R, Desmond PV, Mashford ML, Morphett B, Westwood B et al. Effects of cimetidine and ranitidine on hepatic drug metabolism. Clin Pharmacol Ther 1982; 31(3):297-300.
- 6. Brogden RN, Carmine AA, Heel RC, Speight TM, Avery GS. Ranitidine: a review of its pharmacology and therapeutic use in peptic ulcer disease and other allied diseases. Drugs 1982; 24(4):267-303.
- 7. Critchlow JF. Comparative efficacy of parenteral histamine (H2)-antagonists in acid suppression for the prevention of stress ulceration. Am J Med 1987; 83(6A):23-28.
- 8. Dammann HG, Muller P, Simon B. Parenteral ranitidine: onset and duration of action. Br J Anaesth 1982; 54(11):1235-1236.
- 9. Danilewitz M, Tim LO, Hirschowitz B. Ranitidine suppression of gastric hypersecretion resistant to cimetidine. N Engl J Med 1982; 306(1):20-22.
- 10. Domschke W, Lux G, Domschke S. Furan H2-antagonist ranitidine inhibits pentagastrin-stimulated gastric secretion stronger than cimetidine. Gastroenterology 1980; 79(6):1267-1271.
- 11. Durrant JM, Strunin L. Comparative trial of the effect of ranitidine and cimetidine on gastric secretion in fasting patients at induction of anaesthesia. Can Anaesth Soc J 1982; 29(5):446-451.
- 12. Ehsanullah RSB, Page MC, Tildesley G, Wood JR. A placebo-controlled study of ranitidine in healing NSAID-associated gastric and duodenal ulcers. British Society for Rheumatology, Seventh Annual General Meeting, London, 26-28 September 1990.
- 13. Freston JW. H2-receptor antagonists and duodenal ulcer recurrence: analysis of efficacy and commentary on safety, costs, and patient selection. Am J Gastroenterol 1987; 82(12):1242-1249.
- 14. Gaginella TS, Bauman JH. Ranitidine hydrochloride. Drug Intell Clin Pharm 1983; 17(12):873-885.
- 15. Goudsouzian NG, Young ET. The efficacy of ranitidine in children. Acta Anaesthesiol Scand 1987; 31(5):387-390.
- 16. Halparin L, Ruedy J. Inhibition of pentagastrin-stimulated gastric acid secretion by ranitidine hydrochloride and cimetidine. Current Therapeutic Research 1980; 28(2):154-162.
- 17. Harris PW, Morison DH, Dunn GL, Fargas-Babjak AM, Moudgil GC, Smedstad KG et al. Intramuscular cimetidine and ranitidine as prophylaxis against gastric aspiration syndrome--a randomized double-blind study. Can Anaesth Soc J 1984; 31(6):599-603.
- 18. Jensen RT, Collen MJ, Pandol SJ, Allende HD, Raufman JP, Bissonnette BM et al. Cimetidine-induced impotence and breast changes in patients with gastric hypersecretory states. N Engl J Med 1983; 308(15):883-887.
- 19. Knodell RG, Holtzman JL, Crankshaw DL, Steele NM, Stanley LN. Drug metabolism by rat and human hepatic microsomes in response to interaction with H2-receptor antagonists. Gastroenterology 1982; 82(1):84-88.
- 20. Konturek SJ, Obtulowicz W, Kwiecien N, Sito E, Mikos E, Oleksy J. Comparison of ranitidine and cimetidine in the inhibition of histamine, sham-feeding, and meal-induced gastric secretion in duodenal ulcer patients. Gut 1980; 21(3):181-186.
- 21. Lancaster-Smith MJ, Jaderberg ME, Jackson DA. Ranitidine in the treatment of non-steroidal anti-inflammatory drug associated gastric and duodenal ulcers. Gut 1991; 32(3):252-255.
- 22. Lebert PA, Mahon WA, MacLeod SM, Soldin SJ, Fenje P, Vandenberghe HM. Ranitidine kinetics and dynamics. II. Intravenous dose studies and comparison with cimetidine. Clin Pharmacol Ther 1981; 30(4):545-550.
- 23. Leeder JS, Tesoro AM, Bertho-Gebara CE, MacLeod SM. Comparative bioavailability of ranitidine tablets and suspension. Canadian Journal of Hospital Pharmacy 1984; 37(3):92-94, 106.
- 24. Maile CJ, Francis RN. Pre-operative ranitidine. Effect of a single intravenous dose on pH and volume of gastric aspirate. Anaesthesia 1983; 38(4):324-326.
- 25. Misiewicz JJ, Sewing K, editors. Proceedings of the First International Symposium on Ranitidine. Scand J Gastroenterol 1981; 16(Suppl. 69): 1-131.
- 26. Misiewicz JJ, Wormsley KG, editors. The clinical use of ranitidine : proceedings of the Second International Symposium on Ranitidine held at the Barbican Centre, London, UK, October 1981. 2nd International Symposium on Ranitidine; 1981; London, England. Oxford [Oxfordshire]: Medicine Publishing Foundation; 1982.
- 27. Nelis GF, Van de Meene JG. Comparative effect of cimetidine and ranitidine on prolactin secretion. Postgrad Med J 1980; 56(657):478-480.
- 28. Page M, Lacey L. Ranitidine syrup in the treatment of duodenal ulcer. American Journal of Gastroenterology. 1987; 82(9),977.
- 29. Pasquali R, Corinaldesi R, Miglioli M, Melchionda N, Capelli M, Barbara L. Effect of prolonged administration of ranitidine on pituitary and thyroid hormones, and their response to specific hypothalamic-releasing factors. Clin Endocrinol (Oxf) 1981; 15(5):457-462.
- 30. Peden NR, Robertson AJ, Boyd EJ, Brown RA, Gibbs JH, Potts RC et al. Mitogen stimulation of peripheral blood lymphocytes of duodenal ulcer patients during treatment with cimetidine or ranitidine. Gut 1982; 23(5):398-403.
- 31. Riley AJ, Salmon PR, editors. Ranitidine : proceedings of an international symposium held in the context of the Seventh World Congress of Gastroenterology, Stockholm, 17th June 1982. 3rd International Symposium on Ranitidine and 7th World Congress of Gastroenterology; 1982; Stockholm, Sweden. Amsterdam: Excerpta Medica; 1982.
- 32. Roberts CJ. Clinical pharmacokinetics of ranitidine. Clin Pharmacokinet 1984; 9(3):211-221.
- 33. Scarpignato C, Bertaccini G, Zimbaro G, Vitulo F. Ranitidine delays gastric emptying of solids in man. Br J Clin Pharmacol 1982; 13(2):252-253.
- 34. Wolfe MM. Considerations for selection of parenteral histamine (H2)-receptor antagonists. Am J Med 1987; 83(6A):82-88.
- 35. Yeomans ND, Hanson RG, Smallwood RA, Mihaly GW, Louis WJ. Effect of chronic ranitidine treatment on secretion of intrinsic factor. Br Med J (Clin Res Ed) 1982; 285(6337):264.
- 36. Pr ZANTAC®, GlaxoSmithKline Inc., Product Monograph dated: January 15, 2015, Control No.: 179097.