


Product Monograph - Mylan-Topotecan Hydrochloride for Injection
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Intravenous (i.v) infusion | lyophilized powder Topotecan 4 mg per vial, incorporated as the hydrochloride for the reconstitution | mannitol and tartaric acid |
INDICATIONS AND CLINICAL USE
Adults
Mylan-Topotecan Hydrochloride for Injection is indicated for the treatment of:
- metastatic carcinoma of the ovary after failure of initial or subsequent therapy.
- sensitive small cell lung cancer after failure of first line chemotherapy (defined as recurrence at least 60 days after first line chemotherapy).
Pediatrics
Safety and effectiveness in pediatric patients have not been established, therefore is not recommended for use in this population.
CONTRAINDICATIONS
Mylan-Topotecan Hydrochloride for Injection is contraindicated:
- in patients who have a history of hypersensitivity reactions (anaphylactoid reactions) to topotecan or to any of its excipients.
- in patients who are pregnant or breast-feeding.
- in patients who already have severe bone marrow depression prior to starting first course, as evidenced by baseline absolute neutrophils < 1.5x10⁹/L and/or a platelet count of < 100 x 109/L.
in patients with severe renal impairment (creatinine clearance of < 20 mL/min or
< 0.33 mL/sec).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
Mylan-Topotecan Hydrochloride for Injection should be prescribed by a qualified health care professional who is experienced in the use of antineoplastic therapy agents.
The following is a clinically significant adverse event:
- Bone marrow suppression, primarily neutropenia (see WARNINGS AND PRECAUTIONS, Hematologic);
- Potentially fatal neutropenic colitis (see WARNINGS AND PRECAUTIONS, Gastrointestinal);
- Potentially fatal interstitial lung disease (see WARNINGS AND PRECAUTIONS, Respiratory).
General
Mylan-Topotecan Hydrochloride for Injection should be administered under the supervision of a physician experienced in the use of cancer chemotherapeutic agents. Bone marrow suppression, primarily neutropenia, is the dose limiting toxicity. Therapy with Mylan-Topotecan Hydrochloride for Injection should not be given to patients with baseline absolute neutrophil counts of 1.5x10⁹/L or less. In order to monitor the occurrence of bone marrow suppression, frequent peripheral blood cell counts should be performed on all patients receiving Mylan-Topotecan Hydrochloride for Injection (see DOSAGE AND ADMINISTRATION).
Inadvertent extravasation with topotecan hydrochloride has been associated only with mild local reactions such as erythema (and bruising).
Caution should be observed when driving or operating machinery if fatigue or asthenia persist.
Selection of Patients In Small Cell Lung Cancer
Clinical studies were conducted in patients with sensitive and refractory small cell lung cancer; a reduced chance for benefit in the refractory patients was noted with response rates ranging from 11-31% for patients with sensitive disease and 2.1 to 7.3% for patients with refractory disease. As the risk for toxicity is similar, the overall benefit/risk is reduced.
The benefit to patients versus the risk of toxicity must be carefully weighed.
Carcinogenesis and Mutagenesis
The carcinogenic potential of topotecan hydrochloride has not been studied. (See Special Populations, Pregnant Women.)
Topotecan hydrochloride has been shown to be genotoxic to mammalian cells (mouse lymphoma cells and human lymphocytes) in vitro, and mouse bone marrow cells in vivo, but is not mutagenic in bacterial cells (Salmonella typhimurium and Escherichia coli).
Gastrointestinal
Topotecan-induced neutropenia can cause neutropenic colitis (caecitis or typhlitis). Fatalities due to neutropenic colitis have been reported in clinical trials with topotecan. In patients presenting with fever, neutropenia, and a compatible pattern of abdominal pain, the possibility of neutropenic colitis should be considered.
Gastrointestinal perforations (including life-threatening and fatal cases) have been reported with topotecan-treated patients. Monitor patients with symptoms of severe stomach pain, nausea, vomiting and bloody stool for a possibility of GI perforation. Discontinue Mylan-Topotecan Hydrochloride for Injection in patients who experience a GI perforation.
Hematologic
Bone marrow suppression (primarily neutropenia) is the dose-limiting toxicity of topotecan. Neutropenia is not cumulative over time. Myelosuppression leading to sepsis and fatalities due to sepsis have been reported in patients treated with topotecan [2% fatalities across all SCLC studies (n = 426 subjects), which includes 3% fatalities in one Phase III SCLC study (n = 107 subjects, Table 4)] (see ADVERSE REACTIONS).
Mylan-Topotecan Hydrochloride for Injection should not be administered to patients with baseline absolute neutrophil counts of less than 1.5x10⁹/L. To monitor the occurrence of myelotoxicity, it is recommended that frequent peripheral blood cell counts be performed on all patients receiving Mylan-Topotecan Hydrochloride for Injection. Patients should not be retreated with subsequent courses of Mylan-Topotecan Hydrochloride for Injection until neutrophils recover to a level > 1x10⁹/L, platelets recover to a level > 100x109/L and hemoglobin recovers to 90 g/L, using transfusion if necessary.
Neutropenia
Grade 4 neutropenia (< 0.5x10⁹/L) occurred in 78% of patients and in 39% of all courses, with a median duration of 7 days. The nadir neutrophil count occurred at a median of 12 days. Therapy-related sepsis or febrile neutropenia occurred in 23% of patients and sepsis was fatal in 1.3%.
Topotecan-induced neutropenia can cause neutropenic colitis (see WARNINGS AND PRECAUTIONS, Gastrointestinal).
In the case of severe neutropenia (< 0.5x10⁹/L for 7 days or more) during a course of Mylan-Topotecan Hydrochloride for Injection, a reduction in dose of 0.25 mg/m2 for subsequent courses of therapy is recommended (see DOSAGE AND ADMINISTRATION).
Thrombocytopenia
Grade 4 thrombocytopenia (< 25x109/L) occurred in 27% of patients and in 9% of courses, with a median duration of 5 days and platelet nadir at a median of 15 days. Platelet transfusions were given to 15% of patients in 4% of courses.
Anemia
Severe anemia (grade 3/4, < 80 g/L) occurred in 37% of patients and in 14% of courses. Median nadir was at day 15. Transfusions were needed in 52% of patients in 22% of courses.
Monitoring of Bone Marrow Function
Mylan-Topotecan Hydrochloride for Injection should only be administered in patients with adequate bone marrow reserves including baseline absolute neutrophil counts of at least 1.5x10⁹/L and platelet count at least 100x109/L. Frequent monitoring of blood counts should be instituted during treatment with Mylan-Topotecan Hydrochloride for Injection (see DOSAGE AND ADMINISTRATION).
Respiratory
Topotecan has been associated with reports of interstitial lung disease (ILD), some of which have been fatal (see ADVERSE REACTIONS). Underlying risk factors include history of ILD, pulmonary fibrosis, lung cancer, thoracic exposure to radiation and use of pneumotoxic drugs and/or colony stimulating factors. Patients should be monitored for pulmonary symptoms indicative of ILD (e.g. cough, fever, dyspnoea and/or hypoxia), and topotecan should be discontinued if a new diagnosis of ILD is confirmed.
Special Populations
Pregnant Women:
Mylan-Topotecan Hydrochloride for Injection may cause fetal harm when administered to a pregnant woman. Topotecan was shown to cause embryonic and fetal lethality when given to rats (0.59 mg/m2) and rabbits (1.25 mg/m2) at doses less than the human clinical intravenous dose (1.5 mg/m2). At maternally toxic doses (0.59 mg/m2), topotecan caused malformations, primarily of the eye, brain, skull, and vertebrae. This drug is contraindicated during pregnancy. Women of childbearing potential should be advised to avoid becoming pregnant during therapy with Mylan-Topotecan Hydrochloride for Injection and to inform the treating physician immediately should this occur.
Nursing Women:
Mylan-Topotecan Hydrochloride for Injection is contraindicated during breast-feeding (see CONTRAINDICATIONS).
Pediatrics:
Safety and effectiveness of topotecan in pediatric patients have not been established, and therefore is not indicated for use in this population.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Data in the following section are based on the combined experience of 453 patients with metastatic ovarian carcinoma, and 426 patients with small cell lung cancer, treated with topotecan hydrochloride. Table 1 lists the principal hematologic toxicities and Table 2 lists non-hematologic toxicities occurring in at least 15% of patients.
Table 1 Summary of Hematologic Adverse Events in Patients Receiving Topotecan
Hydrochloride
| Patients n=879 | Courses n=4124 | |
| Hematologic Adverse Events | % Incidence | % Incidence |
| Neutropenia < 1.5x10⁹/L < 0.5x10⁹/L | 97 78 | 81 39 |
| Leukopenia < 3x10⁹/L < 1x10⁹/L | 97 32 | 80 11 |
Thrombocytopenia < 75x109/L < 25x109/L | 69 27 | 42 9 |
| Anemia < 100 g/L < 80 g/L | 89 37 | 71 14 |
| Sepsis or fever/infection with grade 4 neutropenia | 23 | 7 |
| Platelet transfusions | 15 | 4 |
| RBC transfusions | 52 | 22 |
Table 2 Summary of Non-hematologic Adverse Events in Patients Receiving Topotecan
Hydrochloride
| Non-hematologic Adverse Events | All Grades % Incidence | Grade 3 % Incidence | Grade 4 % Incidence | |||
| n=879 Patients | n=4124 Courses | n=879 Patients | n=4124 Courses | n=879 Patients | n=4124 Courses | |
| Gastrointestinal | ||||||
| Nausea | 64 | 42 | 7 | 2 | 1 | <1 |
| Vomiting | 45 | 22 | 4 | 1 | 1 | <1 |
| Diarrhea | 32 | 14 | 3 | 1 | 1 | <1 |
| Constipation | 29 | 15 | 2 | 1 | 1 | <1 |
| Abdominal Pain | 22 | 10 | 2 | 1 | 2 | <1 |
| Stomatitis | 18 | 8 | 1 | <1 | <1 | <1 |
| Anorexia | 19 | 9 | 2 | 1 | <1 | <1 |
| Body as a Whole | ||||||
| Fatigue | 29 | 22 | 5 | 2 | 0 | 0 |
| Fever | 28 | 11 | 1 | <1 | <1 | <1 |
| Pain* | 23 | 11 | 2 | 1 | 1 | <1 |
| Asthenia | 25 | 13 | 4 | 1 | 2 | <1 |
| Skin/Appendages | ||||||
| Alopecia | 49 | 54 | N/A | N/A | N/A | N/A |
| Rash** | 16 | 6 | 1 | <1 | 0 | 0 |
| Respiratory System | ||||||
| Dyspnea | 22 | 11 | 5 | 2 | 3 | 1 |
| Coughing | 15 | 7 | 1 | <1 | 0 | 0 |
| CNS/ Peripheral Nervous System | ||||||
| Headache | 18 | 7 | 1 | <1 | <1 | 0 |
*Pain includes body pain, back pain and skeletal pain.
**Rash also includes pruritus, rash erythematous, urticaria, dermatitis, bullous eruption and rash maculo-papular.
Hematologic (See WARNINGS AND PRECAUTIONS)
Gastrointestinal
The prophylactic use of anti-emetics was not routine in patients treated with topotecan hydrochloride. Gastrointestinal effects were usually mild at the recommended dose level. The incidence of nausea was 64% (8% Grade 3/4) and vomiting occurred in 45% (6% Grade 3/4) of patients (see Table 2).
Thirty-two percent of patients had diarrhea (4% Grade 3/4), 29% constipation (2% Grade 3/4) and 22% had abdominal pain (4% Grade 3/4). Grade 3/4 abdominal pain was 6% in ovarian cancer patients and 2% in small cell lung cancer patients.
After i.v. administration of topotecan hydrochloride, drug-related diarrhea (Grade1/2) was 10% in patients greater than 65 years of age (see DOSAGE AND ADMINSTRATION).
Skin / Appendages
Total alopecia (Grade 2) occurred in 31% of patients.
Central and Peripheral Nervous System
Headache (18%) was the most frequently reported neurologic toxicity. Paresthesia occurred in 7% of patients, but was generally Grade 1.
Liver/Biliary
Grade 1 transient elevations in hepatic enzymes (8%); Grade 3/4 elevated Bilirubin occurred in < 2% of patients.
Respiratory
The incidence of Grade 3/4 dyspnea was 3.8% in ovarian cancer patients and 12.2% in small cell lung cancer patients. Table 3 shows the Grade 3/4 hematologic and major non-hematologic adverse events in the topotecan/paclitaxel comparator trial. Table 4 shows the Grade 3/4 hematologic and major non-hematologic adverse events in the topotecan/CAV comparator trial in small cell lung cancer.
Note: All grading scales are based on National Cancer Institute criteria.
Table 3 Comparative Toxicity Profiles for Ovarian Cancer Patients Randomized to
Receive Topotecan Hydrochloride or Paclitaxel
| Adverse Event | Topotecan hydrochloride | Paclitaxel | ||
| Patients n=112 % | Courses n=597 % | Patients n=114 % | Courses n=589 % | |
| Hematologic Grade 3/4 | ||||
| Grade 4 neutropenia (<0.5x10⁹/L) | 80.2 | 35.8 | 21.4 | 8.6 |
| Grade 3/4 Anemia (Hgb <80 g/L) | 41.4 | 16.1 | 6.3 | 1.9 |
| Grade 4 Thrombocytopenia (<25x109/L) | 27.0 | 10.0 | 2.7 | 0.5 |
| Fever/Grade 4 neutropenia | 23.2 | 6.0 | 4.0 | 1.0 |
| Adverse Event | Topotecan hydrochloride | Paclitaxel | ||
| Patients n=112 % | Courses n=597 % | Patients n=114 % | Courses n=589 % | |
| Documented Sepsis | 4.5 | 0.8 | 1.8 | 0.3 |
| Death related to Sepsis | 1.8 | N/A | 0 | N/A |
| Non-hematologic Grade ¾ | ||||
| Gastrointestinal | ||||
| Abdominal pain | 5.4 | 1.3 | 3.5 | 0.9 |
| Constipation | 5.4 | 1.0 | 0.0 | 0.0 |
| Diarrhea | 6.3 | 1.9 | 0.9 | 0.2 |
| Intestinal Obstruction | 4.5 | 1.0 | 4.4 | 0.8 |
| Nausea | 9.8 | 2.7 | 1.8 | 0.3 |
| Stomatitis | 0.9 | 0.2 | 0.9 | 0.2 |
| Vomiting | 9.9 | 1.9 | 2.7 | 0.5 |
| Constitutional | ||||
| Anorexia | 3.6 | 0.8 | 0.0 | 0.0 |
| Dyspnea | 6.3 | 1.8 | 5.4 | 1.2 |
| Fatigue | 7.1 | 1.8 | 6.1 | 2.2 |
| Malaise | 1.8 | 0.5 | 1.8 | 0.3 |
| Neuromuscular | ||||
| Arthralgia | 0.9 | 0.2 | 2.6 | 0.5 |
| Asthenia | 5.4 | 1.6 | 2.6 | 1.0 |
| Headache | 0.9 | 0.2 | 1.8 | 0.8 |
| Myalgia | 0.0 | 0.0 | 2.6 | 1.5 |
| Pain* | 4.5 | 1.0 | 7.0 | 2.2 |
| Chest Pain | 1.8 | 0.3 | 0.9 | 0.3 |
| Skin and Appendages | ||||
| Rash** | 0 | 0 | 0.9 | 0.2 |
| Liver/Biliary | ||||
| Increased Hepatic Enzymes+ | 0.9 | 0.2 | 0.9 | 0.2 |
*Pain includes body pain, skeletal pain, and back pain
**Rash also includes pruritus, rash erythematous, urticaria, dermatitis, bullous eruption, and rash maculo-papular. +Increased hepatic enzymes includes Increased SGOT/AST, Increased SGPT/ALT and Increased Hepatic Enzymes
Table 4 Comparative Toxicity Profiles for Small Cell Lung Cancer Patients
Randomized to Receive topotecan hydrochloride or CAV
| Adverse Event | Topotecan hydrochloride | CAV | ||
| Patients n=107 % | Courses n=446 % | Patients n=104 % | Courses n=359 % | |
| Hematologic Grade 3/4 | ||||
| Grade 4 neutropenia (<0.5x10⁹/L) | 70 | 38 | 72 | 51 |
| Grade 3/4 Anemia (Hgb <80 g/L) | 42 | 18 | 20 | 7 |
| Grade 4 Thrombocytopenia (<25x109/L) | 29 | 10 | 5 | 1 |
| Fever/Grade 4 neutropenia | 28 | 9 | 26 | 13 |
| Documented Sepsis | 5 | 1 | 5 | 1 |
| Death related to Sepsis | 3 | N/A | 1 | N/A |
| Non-hematologic Grade ¾ | ||||
| Gastrointestinal | ||||
| Abdominal pain | 6 | 1 | 4 | 2 |
| Adverse Event | Topotecan hydrochloride | CAV | ||
| Patients n=107 % | Courses n=446 % | Patients n=104 % | Courses n=359 % | |
| Constipation | 1 | <1 | 0 | 0 |
| Diarrhea | 1 | <1 | 0 | 0 |
| Nausea | 8 | 2 | 6 | 2 |
| Stomatitis | 2 | <1 | 1 | <1 |
| Vomiting | 3 | <1 | 3 | 1 |
| Constitutional | ||||
| Anorexia | 3 | 1 | 4 | 2 |
| Dyspnea | 9 | 5 | 14 | 7 |
| Fatigue | 6 | 4 | 10 | 3 |
| Neuromuscular | ||||
| Asthenia | 9 | 4 | 7 | 2 |
| Headache | 0 | 0 | 2 | <1 |
| Pain* | 5 | 2 | 7 | 4 |
| Respiratory System | ||||
| Pneumonia | 8 | 2 | 6 | 2 |
| Coughing | 2 | 1 | 0.0 | 0 |
| Skin and Appendages | ||||
| Rash** | 1 | <1 | 1 | <1 |
| Liver/Biliary | ||||
| Increased Hepatic Enzymes+ | 1 | <1 | 0 | 0 |
*Pain includes body pain, skeletal pain, and back pain
** Rash also includes pruritus, rash erythematous, urticaria, dermatitis, bullous eruption, and rash maculo-papular. +Increased hepatic enzymes includes Increased SGOT/AST, Increased SGPT/ALT and Increased Hepatic Enzymes
Premedications were not routinely used in patients randomized to topotecan hydrochloride, while patients receiving CAV received routine pretreatment with corticosteroids, diphenhydramine, and histamine receptor type 2 blockers.
Postmarket Adverse Drug Reactions
Reports of adverse events in patients taking topotecan hydrochloride after market introduction include the following:
Body as a Whole: allergic manifestations, angioedema, anaphylactoid reactions, extravasation*, pancytopenia
Gastrointestinal: abdominal pain**, gastrointestinal perforation, mucosal inflammation Hematologic: severe bleeding (in association with thrombocytopenia) Respiratory, Thoracic
and Mediastinal Disorders: interstitial lung disease
Skin / Appendages: severe dermatitis, severe pruritus
*Reactions associated with extravasation have been mild and have not generally required specific therapy.
**Neutropenic colitis, including fatal neutropenic colitis, has been reported to occur as a complication of topotecan-induced neutropenia (see WARNINGS and PRECAUTIONS).
DRUG INTERACTIONS
There are no adequate data to define a safe and effective regimen for topotecan hydrochloride in combination with other cytotoxic agents. Preliminary studies combining topotecan hydrochloride with platinum-containing agents (e.g. cisplatin or carboplatin) suggest a sequence dependent interaction whereby greater myelosuppression is seen when the platinum containing agent is given on day 1 compared to day 5 of the topotecan hydrochloride dosing. If topotecan is administered in combination with other cytotoxic agents, dose reduction may be necessary.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Initial Dose
Prior to administration of the first course of Mylan-Topotecan Hydrochloride for Injection, patients must have:
- a baseline absolute neutrophil count of ≥ 1.5x10⁹/L
- a platelet count of ≥ 100x109/L
- a hemoglobin level of ≥ 90 g/L
Recommended Dose and Dosage Adjustment
Initial Dose
The recommended dose of Mylan-Topotecan Hydrochloride for Injection is 1.5 mg/m2 by intravenous infusion over 30 minutes daily for 5 consecutive days, starting on day one of a 21-day course. Because median time to response in three ovarian cancer clinical trials was 9 to 12 weeks and median time to response in four small cell lung cancer trials was 5 to 7 weeks, a minimum of 4 courses of Mylan-Topotecan Hydrochloride for Injection is recommended.
Subsequent doses
Topotecan should not be re-administered unless the absolute neutrophil count is more than or equal to 1x10⁹/L, the platelet count is more than or equal to 100x109/L, and the hemoglobin level is more than or equal to 90 g/L (after transfusion if necessary).
Standard oncology practice for the management of neutropenia is either to administer topotecan with other medications (e.g. G-CSF) or to dose reduce to maintain neutrophil counts.
If dose reduction is chosen for patients who experience severe neutropenia (absolute neutrophil count less than or equal to 0.5x10⁹/L) for 7 days or more, or severe neutropenia associated with fever or infection, or who have had treatment delayed due to neutropenia, the dose should be reduced by 0.25 mg/m2/day to 1.25 mg/m2/day (or subsequently down to 1.0 mg/m2/day if necessary).
Doses should be similarly reduced if the platelet count falls below 25x109/L.
Routine pre-medication for the prevention of non-hematological adverse events is not required with Mylan-Topotecan Hydrochloride for Injection.
Hepatic Impairment: No dosage adjustment is required for treating patients with hepatic impairment (plasma bilirubin > 1.5 to < 10 mg/dL or (SI units) > 25.7 to < 171 μmol/L).
Renally impaired patients: No dosage adjustment is required for patients with mild renal impairment (CrCl 40 to 60 mL/min or 0.67 to 1 mL/sec). Dosage adjustment to 0.75 mg/m2/day is recommended for patients with moderate renal impairment (CrCl 20 to 39 mL/min or 0.33 to 0.65 mL/sec). Advice on dosing of topotecan for patients with moderate renal impairment (creatinine clearance of 20 to 39 mL/min) is based on studies involving patients with advanced cancer. Treatment with Mylan-Topotecan Hydrochloride for Injection in patients with severe renal impairment (CrCl < 20 mL/min or 0.33 mL/sec) is not recommended (see CONTRAINDICATIONS).
Neutropenia
In the case of severe neutopenia (<0.5x10⁹/L for 7 days or more) during a course of Mylan-Topotecan Hydrochloride for Injection, a reduction in dose of 0.25 mg/m2 for subsequent courses of therapy is recommended. (see WARNINGS AND PRECAUTIONS, Neutropenia)
Use in Children: Insufficient data are available in pediatric patients to provide a dosage recommendation (see PRECAUTIONS AND WARNINGS).
Use in the Elderly: No dosage adjustment appears to be needed in the elderly, other than adjustments related to renal function.
After i.v. administration of topotecan hydrochloride drug-related diarrhea (Grade 1/2) was 10% in patients greater than 65 years of age (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, Gastrointestinal). Patients over the age of 65 should be closely monitored for diarrhea and treated accordingly.
Dosage in Combination with Cytotoxic Agents: Dose adjustment may be necessary if topotecan is administered in combination with other cytotoxic agents (see DRUG INTERACTIONS).
Administration
Mylan-Topotecan Hydrochloride for Injection is a cytotoxic anticancer drug. As with other potentially toxic compounds, Mylan-Topotecan Hydrochloride for Injection solution should be prepared under a vertical laminar flow hood while wearing gloves and protective clothing. If Mylan-Topotecan Hydrochloride for Injection solution contacts the skin; wash the skin immediately and thoroughly with soap and water. If Mylan-Topotecan Hydrochloride for Injection contacts mucous membranes, flush thoroughly with water.
Preparation for Intravenous Administration: Each Mylan-Topotecan Hydrochloride for Injection 4 mg vial is reconstituted with 4 mL Sterile Water for Injection, giving a final concentration of 1 mg/mL.
Then the appropriate volume of the reconstituted solution is further diluted to an infusion concentration of 20 - 500 μg/mL in 50 to 100 mL of either 0.9% Sodium Chloride Intravenous Infusion or 5% Dextrose Intravenous Infusion prior to administration.
Since the vials contain no preservative, it is recommended that the product be used immediately after reconstitution. If not used immediately the reconstituted product should be stored in a refrigerator, for up to 24 hours.
As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity and particulate matter, discoloration and leakage prior to administration, whenever solution and container permit.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
There is no known antidote for overdosage with topotecan hydrochloride. Further management should be as clinically indicated. Overdoses (from 1.1 fold up to 10 fold of the prescribed dose) have been reported in patients being treated with intravenous topotecan hydrochloride. The primary complication of overdosage is bone marrow suppression. The observed signs and symptoms for overdose are consistent with the known adverse reactions associated with topotecan hydrochloride (see ADVERSE REACTIONS). In addition, elevated hepatic enzymes, mucositis, fatal hemorrhagic necrotising colitis, hypotension and tachycardia have been reported following overdose. In a phase I study, one patient was incorrectly dosed at 35 mg/m2 during course 9 of therapy and experienced hematologic toxicity associated with this increased dose. The LD10 Rate in mice receiving single intravenous infusions of topotecan hydrochloride was 74.85 mg/m2 (CI 95%: 47.22 to 97.41).
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Topotecan Hydrochloride inhibits topoisomerase-I, an enzyme that functions in DNA replication to relieve the torsional strain introduced ahead of the moving replication fork. Topotecan inhibits topoisomerase-I by stabilizing the covalent complex of enzyme and strand-cleaved DNA, which is an intermediate of the catalytic mechanism, thereby inducing breaks in the protein-associated DNA single-strands, resulting in cell death.
Pharmacodynamics
The dose-limiting toxicity for topotecan is leukopenia. The relationship between decreased white blood count and either topotecan or total topotecan AUC can be described by a Sigmoid Emax Model.
Pharmacokinetics
Following intravenous administration of topotecan at doses of 0.5 to 1.5 mg/m2 as a 30-minute infusion daily for 5 days, topotecan demonstrated a clearance of 1030 mL/min with a plasma half-life of 2 to 3 hours.
Comparison of pharmacokinetic parameters did not suggest any change in pharmacokinetics over the dosing period. Area under the curve increased approximately in proportion to the increase in dose.
Distribution: Topotecan has a volume of distribution of 130 L. Binding of topotecan to plasma proteins is about 35%. Topotecan is evenly distributed between blood cells and plasma.
Metabolism: Topotecan undergoes pH dependent hydrolysis, with the equilibrium favoring the ring-opened hydroxy-acid form at physiologic pH.
Excretion: The renal clearance of topotecan could not be measured in humans due to the effect of urine pH on interconversion, although measurement of total topotecan (the lactone ring and the ring-opened hydroxy acid) in urine suggests that a variable fraction of the dose (generally 20 to 60%) is excreted in urine. Topotecan has also been measured in human bile samples indicating that topotecan is excreted by both biliary and urinary routes in humans.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of topotecan were studied in 12 pediatric patients treated with topotecan at doses between 2.0 and 7.5 mg/m2 as a 24-hour continuous infusion. Mean plasma clearance was 28.3 L/h/m2 with a range of 18.1 to 44.2 L/h/m2.
These values are similar to plasma clearance values seen in adults (approx. 36 L/h/m2) who received 24-hour topotecan infusions.
Geriatrics: Topotecan pharmacokinetics has not been specifically investigated in elderly patients. However, a population pharmacokinetic analysis in female patients did not identify age as a significant factor. Renal clearance is likely to be a more important determinant of topotecan clearance than age in this patient population.
Gender: The overall mean topotecan plasma clearance in male patients was approximately 24% higher than in female patients, largely reflecting difference in body size.
Race: The effect of race on topotecan pharmacokinetics has not been determined.
Hepatic Insufficiency: Based on clinical data and total topotecan pharmacokinetics, no dosage adjustment is required in patients with hepatic impairment (serum bilirubin < 10 mg/dL or 171 μmol/L). Plasma clearance in patients with hepatic impairment decreased to about 67% when compared with a control group of patients. Topotecan half-life was increased by about 30%, but no change in volume of distribution was observed. Total topotecan clearance in patients with hepatic impairment only decreased by about 10% compared with the control group of patients.
Renal Insufficiency: Plasma clearance of topotecan in patients with mild renal impairment (creatinine clearance [CrCl] of 40 to 60 mL/min or 0.67 to 1 mL/sec) decreased to about 67% compared with control patients. Volume of distribution was slightly decreased and thus half-life only increased by 14%.
In patients with moderate renal impairment (CrCl of 20 to 39 mL/min or 0.33 to 0.65 mL/sec), topotecan plasma clearance was reduced to 34% of the value in control patients. Volume of distribution also decreased by about 25%, which resulted in an increase in mean half-life from 1.9 hours to 4.9 hours. Total topotecan clearance also decreased by 57% in patients with moderate renal impairment and by 17% in patients with mild renal impairment. Based on clinical data and on total topotecan pharmacokinetics, no dosage adjustment is required for patients with mild renal impairment (CrCl 40 to 60 mL/min or 0.67 to 1 mL/sec). Dosage adjustment to 0.75 mg/m2/day is recommended for patients with moderate renal impairment. Mylan-Topotecan Hydrochloride for Injection is not recommended for patients with a creatinine clearance of < 20 mL/min (0.33 mL/min).
STORAGE AND STABILITY
Unopened vials of Mylan-Topotecan Hydrochloride for Injection are stable until the date indicated on the package when stored between 15° to 30°C (59° to 86°F) and protected from light in the original package.
Reconstituted Solutions
Vials which have been reconstituted with Water for Injection are stable for up to 24 hours when refrigerated at 5ºC (41ºF) or stored at 30ºC (86ºF).
However, since the vials contain no preservative, it is recommended that the product should be used immediately after reconstitution. If not used immediately, the reconstituted solution should be stored in a refrigerator and discarded after 24 hours.
Diluted solutions
Reconstituted vials of Mylan-Topotecan Hydrochloride for Injection diluted for infusion are stable for up to 24 hours at approximately 20 to 25ºC (68 to 77ºF) and ambient lighting conditions. If not used immediately, the diluted solution should be stored in a refrigerator in line with good pharmaceutical practice.
SPECIAL HANDLING INSTRUCTIONS
Handling and Disposal: Procedures for proper handling and disposal of anticancer drugs should be used. Several guidelines on this subject have been published.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Topotecan Hydrochloride for injection is supplied as a sterile lyophilized, buffered, light yellow to greenish powder available in single-dose vials. Each vial contains topotecan hydrochloride
equivalent to 4 mg of topotecan as free base. The reconstituted solution ranges in color from yellow to yellow-green and is intended for administration by intravenous infusion.
Inactive ingredients consist of mannitol and tartaric acid. Hydrochloric acid and sodium hydroxide may be used to adjust to a pH of 3. The solution pH ranges from 2.5 to 3.5.
Mylan-Topotecan Hydrochloride for Injection is supplied in a 4 mg (free base) single-dose vial, in a package of 5 vials.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
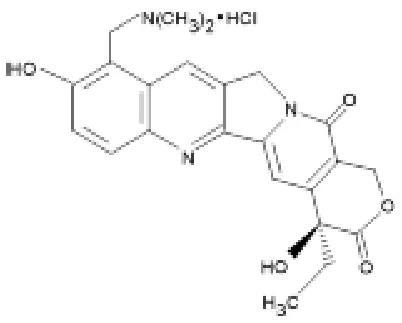
Proper name: Topotecan hydrochloride
Chemical name: (S)-10-[(dimethylamino)methyl]-4-ethyl-4,9-dihydroxy-1Hpyrano[
3',4':6,7]indolizino[1,2-b]quinoline-3,14-(4H,12H)-dione monohydrochloride.
Molecular formula and molecular mass: C23H23N3O5•HCl, 457.9.
Structural formula:
Physicochemical properties:
Description: Topotecan hydrochloride is a yellow to yellow orange powder. It is soluble in water and melts with decomposition at 213º to 218ºC.
CLINICAL TRIALS
Ovarian Cancer
Study Demographics and Trial Design
Topotecan hydrochloride was studied in four clinical trials of 453 patients with metastatic ovarian carcinoma.
Patients in these four studies received an initial dose of 1.5 mg/m2 given by intravenous infusion over 30 minutes for the first five consecutive days of a 21-day course.
In a randomized Phase III study, topotecan hydrochloride was compared with paclitaxel in patients with recurrent ovarian cancer who had failed initial treatment with a platinum containing regimen. This study treated 112 patients with topotecan hydrochloride (1.5 mg/m2/day for the first 5 consecutive days of a 21-day course) and 114 patients with paclitaxel (175 mg/m2 over 3 hours on day one of a 21-day course).
Response rates, response duration (measured from the time of documented response), time to progression, time to response and survival for the comparative study are provided in Table 5.
Study results
Patients receiving topotecan hydrochloride achieved a higher response rate (21% vs 14%, p=0.196) than those receiving paclitaxel; a longer duration of response (median of 26 vs 22 weeks, Hazard-ratio = 0.778, p=0.476); a longer time to progression (median of 19 vs 15 weeks, Hazard-ratio=0.764, p=0.0718); and a longer estimated median survival (63 vs 53 weeks, Hazard-ratio=0.986, p=0.9315).
However, the median time to response was longer with topotecan hydrochloride compared to paclitaxel: median of 8 vs 6 weeks (Hazard-ratio=0.615, p=0.1465). Consequently there is a risk of underestimating the expected efficacy of topotecan hydrochloride if patients are withdrawn from treatment prematurely (see DOSAGE AND ADMINISTRATION).
Table 5 Comparative Efficacy Parameters of Topotecan Hydrochloride vs. Paclitaxel in
Ovarian Cancer
| Parameter | Topotecan Hydrochloride (n=112) | Paclitaxel (n=114) |
| Complete Response Rate (%) Partial Response Rate (%) Overall Response Rate (%) 95% CI | 4.5 16.1 20.5 (13.1,28.0) | 2.6 11.4 14.0 (7.7,20.4) |
| (p-value) | (0.196) | |
Response Duration (weeks) Median 95% CI | 26* (22.1,32.9) | 22* (16.0,34.6) |
| Hazard-ratio (p-value) | 0.778(0.476) | |
| Time to Progression (weeks) Median | 19 (12.1,23.6) | 15 (11.9,18.3) |
| 95% CI | ||
| Hazard-ratio (p-value) | 0.764(0.0718) | |
Time to Response (weeks) Median Range | 8.0* 3.1 to 19.0 | 6.0* 2.4 to 12.3 |
| Hazard-ratio (p-value) | 0.615(0.1465) | |
Survival (weeks) Median Range | 63 0.7 to 122.1 | 53 0.6 to 129.9 |
| Hazard-ratio (p-value) | 0.97(0.87) | |
* topotecan (n=23) paclitaxel (n=16)
Hazard-ratio (p-value)
Hazard-ratio (p-value)
Patients who failed on the initial arm of this study were allowed to switch to the alternate treatment. Eight of 61 (13.1%) patients who received topotecan hydrochloride after paclitaxel responded. Five of 49 (10.2%) patients who received paclitaxel after topotecan hydrochloride responded.
Topotecan hydrochloride was active in ovarian cancer patients who had developed resistance to platinum-containing therapy, defined as tumour progression while on, or tumour relapse within 6 months after completion of, a platinum-containing regimen. One complete and seven partial responses were seen in 60 patients, for a response rate of 13%. In the same study, there were no complete responders and only four partial responders on the paclitaxel arm, for a response rate of 7%.
Topotecan hydrochloride remained active in patients who did not respond to or eventually failed paclitaxel, as shown by the responders in this trial and the trial in platinum and paclitaxel failures (see below).
The safety profile for paclitaxel in this study was consistent with the product’s monograph; the safety profile for topotecan hydrochloride in this study was consistent with that observed in all 453 patients from the four ovarian clinical trials (see ADVERSE REACTIONS).
The three additional studies were open-label and non-comparative in design. The first study enrolled 111 patients with recurrent ovarian cancer who had failed one prior platinum-containing regimen. The response rate was 14% (95% CI: =7.9 - 20.9%). The median duration of response was 16 weeks (range: 4.6 to 41.9 weeks). The time to progression was 11 weeks (range: 0.7 to 72.1 weeks). The median survival was 52 weeks (range: 1.4 to 72.3 weeks).
A second open study enrolled 139 patients with recurrent ovarian cancer who had failed one (62 patients) or two (77 patients) prior regimens containing platinum and paclitaxel. The response rates in this study for evaluable patients were 12.9% and 16.9%, respectively. Median response duration was 18.1 weeks. Median time to progression was 12 weeks (range: 0.6 - 52.7 weeks). Median survival was 51.3 weeks for patients failing first-line therapy.
The third open study enrolled 30 patients with recurrent ovarian cancer who had failed one or two prior platinum-containing regimens. The response rate was 13% (95% CI: =3.8 - 30.7%). The median duration of response was 28 weeks (range: 16 - 59 weeks).
Small Cell Lung Cancer
Study Demographics and Trial Design
Topotecan hydrochloride was studied in 426 patients with recurrent or progressive small cell lung cancer in one randomized Phase III, comparative study and in three non-randomized, Phase II studies.
In a randomized, Phase III, comparative trial, 107 patients were treated with topotecan hydrochloride (1.5 mg/m2/day x 5 days starting on day one of a 21-day course) and 104 patients were treated with CAV (1000 mg/m2 cyclophosphamide, 45 mg/m2 doxorubicin, 2 mg vincristine administered sequentially on day one of a 21 day course). All patients were considered sensitive to first-line chemotherapy (responders who then subsequently progressed ≥ 60 days after completion of first-line therapy). A total of 77% of patients treated with topotecan hydrochloride and 79% of patients treated with CAV received platinum/etoposide with or without other agents as first-line chemotherapy.
Response rates, response duration, time to progression, and survival are shown in Table 6.
Table 6 Efficacy of Topotecan Hydrochloride vs CAV (cyclophosphamide-doxorubicinvin-cristine) in Small Cell Lung Cancer Patients Sensitive to First-Line Chemotherapy
| Parameter | Topotecan Hydrochloride (n= 107) | CAV (n=104) |
| Complete Response Rate Partial Response Rate Overall Response Rate 95% Confidence Interval* | 0.0% 24.3% 24.3% 16.17 to 32.43% | 1.0% 17.3% 18.3% 10.84 to 25.7% |
| (p-value) | (0.285) | |
Response Duration (weeks) Median 95% CI | n=26 14.4 13.1 to 18.0 | n=19 15.3 13.1 to 23.1 |
Hazard-ratio (topotecan hydrochloride vs CAV) (p-value) | 1.42 (0.30) | |
Time to Progression (weeks) Median 95% Confidence Interval | 13.3 11.4 to 16.4 | 12.3 11.0 to 14.1 |
Hazard-ratio (topotecan hydrochloride vs CAV) (p-value) | 0.92 (0.55) | |
Survival (weeks) Median Range95% Confidence Interval | 25.0 20.6 to 29.6 | 24.7 21.7 to 30.3 |
| Hazard-ratio (topotecan hydrochloride vs CAV) | 1.04 (0.80) | |
(p-value)
The calculation for duration of response was based on the interval between first response and time to progression. * 95% confidence interval for the difference in the rate of response (6.0%) was -6.0 to 18%
The time to response was similar in both arms: topotecan hydrochloride median of 6 weeks (range 2.4 to 15.7) versus CAV median of 6 weeks (range 5.1 to 18.1).
Palliation of disease-related symptoms was greater in patients who received topotecan hydrochloride than in patients who received CAV. These clinically important improvements occurred at a higher rate in 8 of 9 symptoms in patients treated with topotecan hydrochloride. Symptom improvement was statistically significant in 5 of 9 symptoms. These data are presented in Table 7.
Patients treated with topotecan hydrochloride also experienced a longer time to worsening in 7 of 9 disease-related symptoms (shortness of breath, anorexia, interference with daily activity, cough, insomnia, hoarseness and fatigue). Time to worsening of chest pain and hemoptysis were similar for both treatment groups. Statistically significant differences in the length of time to worsening of shortness of breath (p=0.046) and anorexia (p=0.003) were noted, with the topotecan hydrochloride group worsening at a slower rate.
Table 7 Percentage of Patients with Symptom Improvement+: Topotecan Hydrochloride versus CAV in Patients with Small Cell Lung Cancer
| Symptom | Topotecan Hydrochloride (n=107) | CAV (n=104) | Pearson chi-square p-value | ||
| n++ | (%) | n++ | (%) | ||
| Shortness of Breath | 68 | (27.9) | 61 | ( 6.6) | 0.002 |
| Interference with Daily Activity | 67 | (26.9) | 63 | (11.1) | 0.023 |
| Fatigue | 70 | (22.9) | 65 | ( 9.2) | 0.032 |
| Hoarseness | 40 | (32.5) | 38 | (13.2) | 0.043 |
| Cough | 69 | (24.6) | 61 | (14.8) | 0.160 |
| Insomnia | 57 | (33.3) | 53 | (18.9) | 0.085 |
| Anorexia | 56 | (32.1) | 57 | (15.8) | 0.042 |
| Chest Pain | 44 | (25.0) | 41 | (17.1) | 0.371 |
| Hemoptysis | 15 | (26.7) | 12 | (33.3) | 0.706 |
+ defined as improvement sustained over at least 2 courses compared to baseline
++ Number of patients with baseline and at least one post-baseline assessment.
Topotecan hydrochloride (1.5 mg/m2 /day x 5 days starting on day one of a 21-day course) was also studied in three open-label, non-comparative trials in 319 patients with recurrent or progressive small cell lung cancer after treatment with first-line chemotherapy. In all three studies, patients were stratified as either sensitive (responders who then subsequently progressed ≥ 90 days after completion of first-line therapy) or refractory (no response to first-line chemotherapy or who responded to first-line therapy and then progressed within 90 days of completing first-line therapy).
In one study, the median response rate was 15.4% for sensitive (n=52) and 2.1% for refractory patients (n=47). Median time to response was 6.1 weeks (sensitive) and 5.4 weeks (refractory).
The median duration of response was 23.1 weeks (sensitive) and 24.9 weeks (refractory). Median time to progression was 13.1 weeks (sensitive) and 9.6 weeks (refractory). Median survival time was 28.3 weeks (sensitive) and 21.4 weeks (refractory). Disease-related symptoms resolved or improved versus baseline in 20% of patients (n=65), remained unchanged in 60%, or worsened in 20%.
In an EORTC (European Organization for Research and Treatment of Cancer) Study, the median response rate was 31.1% for sensitive (n=45) and 7.3% for refractory patients (n=55). Median time to response was 7 weeks for sensitive and 5.6 weeks for refractory patients. The median duration of response was 20.7 weeks (sensitive) and 30.7 weeks (refractory). Median time to progression was 17.7 weeks (sensitive) and 8.3 weeks (refractory). Median survival was 35.6 weeks (sensitive) and 20.9 weeks (refractory).
In a third study, the median response rate was 11.3% for sensitive (n=71) and 2.1% for refractory patients (n=48). Median time to response was 5.6 weeks (sensitive) and 5.7 weeks (refractory). The median duration of response was 21.9 weeks (sensitive) and 22.0 weeks (refractory). Median time to progression was 10.3 weeks (sensitive) and 6.4 weeks (refractory). Median survival time was 26.4 weeks (sensitive) and 15.9 weeks (refractory).
DETAILED PHARMACOLOGY
Pharmacokinetics
Metabolism
Topotecan undergoes pH dependent hydrolysis, with the equilibrium favoring the ring opened hydroxy-acid form at physiologic pH. The metabolism of topotecan in humans has not been extensively studied. However in rats and dogs, approximately 4% and 17% of the dose, respectively, was excreted as N-desmethyl derivatives of topotecan and its ring opened hydroxy-acid form. In vitro studies in rat, dog and human liver microsomes indicate that the rate of metabolism of topotecan to the N-demethylated metabolite in human microsomes is between that in rat and dog liver microsomes.
No other metabolite of topotecan has been identified. A major route of clearance of topotecan was by hydrolysis of the lactone ring to form the ring-opened hydroxy acid.
Drug Interactions
When given in combination with cisplatin (cisplatin day 1, topotecan days 1 to 5), the clearance of topotecan was reduced on day 5 compared to day 1 (19.1 L/h/m2 compared to 21.3 L/h/m2) (see DRUG INTERACTIONS).
In vitro, topotecan did not inhibit human P450 enzymes CYP1A2, CYP2A6, CYP2C8/9, CYP2C19, CYP2D6, CYP2E, CYP3A, or CYP4A nor did it inhibit the human cytosolic enzymes dihydropyrimidine or xanthine oxidase. Following 14 days of intravenous dosing in rats at doses up to 1.36 mg/m2 topotecan free base, no inductive effect was observed on P450 enzymes 1A, 2B, 3A and 4A.
MICROBIOLOGY
Not applicable.
TOXICOLOGY
The toxicity of topotecan in animals has been predictive of the toxicity observed thus far in patients, where neutropenia (the most common dose-limiting toxicity) was often associated with thrombocytopenia and anemia.
Carcinogenicity
Carcinogenicity studies are not generally performed with antineoplastic agents and have not been performed for topotecan.
Mutagenicity
Topotecan was not mutagenic in bacterial mutagenicity tests using Salmonella typhimurium and Escherichia coli. Topotecan was genotoxic in mammalian cells (mouse lymphoma cells and human lymphocytes) in vitro and in mouse bone marrow cells in vivo. Similar findings have been observed for another topoisomerase I inhibitor, CPT-11.
REFERENCES
- 1.
AMA Council Report. Guidelines for handling parenteral antineoplastics. Journal of the
American Medical Association 1985; 253(11):1590-1592.
- 2. American Society of Hospital Pharmacists Technical Assistance Bulletin on Handling Cytotoxic and Hazardous Drugs. American Journal of Hospital Pharmacy 1990; 47(5):1033-1049.
- 3.
Ardizzoni A, Hansen H, Dombernowsky P, Gamucci T, Kaplan S, Postmus P et al. Topotecan, A
New Active Drug in the Second-Line Treatment of Small-Cell Lung Cancer: A Phase Ii Study in Patients with Refractory and Sensitive Disease. J Clin Oncol 1997; 15(5):2090-2096.
- 4.
Blaney SM, Balis FM, Cole DE, Craig C, Reid JM, Ames MM et al. Pediatric Phase I Trial and
Pharmacokinetic Study of Topotecan Administered As A 24- Hour Continuous Infusion. Cancer Res 1993; 53(5):1032-1036.
- 5. Clinical Oncological Society of Australia. Guidelines and recommendations for safe handling of antineoplastic agents. The Medical journal of Australia 1983; 1(9):426-428.
- 6.
Creemers GJ, Bolis G, Gore M, Scarfone G, Lacave AJ, Guastalla JP et al. Topotecan, An Active
Drug in the Second-Line Treatment of Epithelial Ovarian Cancer: Results of A Large European Phase Ii Study. J Clin Oncol 1996; 14(12):3056-3061.
- 7. Goodwin JE, Shin DD - Neutropenia. E-medicine.com. 2005
- 8.
Jones RB, Frank R, Mass T. Safe handling of chemotherapeutic agents: a report from The Mount
Sinai Medical Center. CA: a cancer journal for clinicians 1983; 33(5):258-263.
- 9. Miller AA, Hargis JB, Lilenbaum RC, Fields SZ, Rosner GL, Schilsky RL. Phase I study of topotecan and cisplatin in patients with advanced solid tumors: A cancer and leukemia group B study. J Clin Oncol 1994; 12(12):2743-2750.
- 10. National Study Commission on Cytotoxic Exposure-recommendations for handling cytotoxic agents.
- 11.
O’Reilly S, Rowinsky EK, Slichenmyer W, Donehower RC, Forastiere AA, Ettinger DS et al.
Phase I and Pharmacologic Study of Topotecan in Patients with Impaired Renal Function. J Clin Oncol 1996; 14(12):3062-3073.
- 12.
OSHA. Work-Practice guidelines for personnel dealing with cytotoxic antineoplastic drugs.
American Journal of Hospital Pharmacy 1986; 43(5):1193- 1204.
- 13. Recommendations for the Safe Handling of Parenteral Antineoplastic Drugs. Superintendent.
- 14.
Rowinsky EK, Kaufmann SH, Baker SD, Grochow LB, Chen T-L, Peereboom D et al.
Sequences of topotecan and cisplatin: Phase I, pharmacologic, and in vitro studies to examine sequence dependence. J Clin Oncol 1996; 14(12):3074-3084.
- 15.
Rowinsky EK, Grochow LB, Sartorius SE, Bowling MK, Kaufmann SH, Peereboom D et al.
Phase I and Pharmacologic Study of High Doses of the Topoisomerase I Inhibitor Topotecan with Granulocyte Colony-Stimulating Factor in Patients with Solid Tumors. J Clin Oncol 1996; 14(4):1224-1235.
- 16. Talcott JA, Siegel RD, Finberg G, Goldman L. Risk Assessment in Cancer patients with Fever and Neutropenia: A Prospective Two-Center Validation of a Predication Rule. J Clin Oncol. 1992; 10(2): 316-322.
- 17.
PrHYCAMTIN® Product Monograph. Novartis Pharmaceuticals Canada Inc., Control No.
207443, August 29, 2017.
IMPORTANT: PLEASE READ