


Product Monograph - NB-Alendronate-Fc
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ................................................................................................ 2
TABLE OF CONTENTS .................................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION .......................................................................... 4
1 INDICATIONS ......................................................................................................................... 4
1.1 Pediatrics ........................................................................................................................ 4
1.2 Geriatrics ........................................................................................................................ 4
2 CONTRAINDICATIONS ........................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ........................................................................................... 5
4.1 Dosing Considerations .................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................ 5
4.4 Administration ................................................................................................................ 5
4.5 Missed Dose .................................................................................................................... 6
5 OVERDOSAGE ....................................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................................ 6
7 WARNINGS AND PRECAUTIONS............................................................................................. 7
7.1 Special Populations ....................................................................................................... 10
7.1.1 Pregnant Women .......................................................................................................... 10
7.1.2 Breast-feeding .............................................................................................................. 10
7.1.3 Pediatrics ...................................................................................................................... 11
7.1.4 Geriatrics ...................................................................................................................... 11
8 ADVERSE REACTIONS .......................................................................................................... 11
8.1 Adverse Reaction Overview .......................................................................................... 11
8.2 Clinical Trial Adverse Reactions ..................................................................................... 11
8.3 Less Common Clinical Trial Adverse Reactions .............................................................. 14
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data............................................................................................................................... 14
8.5 Post-Market Adverse Reactions .................................................................................... 15
9 DRUG INTERACTIONS .......................................................................................................... 15
9.2 Drug Interactions Overview .......................................................................................... 15
9.3 Drug-Behavioural Interactions ..................................................................................... 16
9.5 Drug-Food Interactions ................................................................................................. 17
9.6 Drug-Herb Interactions ................................................................................................. 17
9.7 Drug-Laboratory Test Interactions ................................................................................ 17
10 CLINICAL PHARMACOLOGY ................................................................................................. 17
10.1 Mechanism of Action .................................................................................................... 17
10.2 Pharmacodynamics ....................................................................................................... 17
10.3 Pharmacokinetics.......................................................................................................... 19
11 STORAGE, STABILITY AND DISPOSAL ................................................................................... 21
PART II: SCIENTIFIC INFORMATION ........................................................................................... 22
13 PHARMACEUTICAL INFORMATION ...................................................................................... 22
14 CLINICAL TRIALS .................................................................................................................. 23
14.1 Clinical Trials by Indication ........................................................................................... 23
14.2 Comparative Bioavailability Studies .............................................................................. 34
15 MICROBIOLOGY .................................................................................................................. 34
16 NON-CLINICAL TOXICOLOGY ................................................................................................ 35
17 SUPPORTING PRODUCT MONOGRAPHS .............................................................................. 36
PATIENT MEDICATION INFORMATION ...................................................................................... 37
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
NB-ALENDRONATE-FC (alendronate sodium tablets) is indicated for:
The treatment of osteoporosis in postmenopausal women.
- For the treatment of osteoporosis in postmenopausal women, alendronate sodium increases bone mass and prevents fractures, including those of the hip and spine (vertebral compression fractures).
The treatment of osteoporosis in men.
- For the treatment of osteoporosis in men, alendronate sodium increases bone mass and reduces the incidence of fractures.
Important limitations of use: The optimal duration of use has not been determined. Patients should have the need for continued therapy re-evaluated on a periodic basis (see 4 DOSAGE AND ADMINISTRATION).
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): In clinical studies, there was no age-related difference in the efficacy or safety profiles of alendronate sodium (see 14 CLINICAL TRIALS).
2 CONTRAINDICATIONS
NB-ALENDRONATE-FC is contraindicated in patients with
- hypersensitivities to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- abnormalities of the esophagus which delay esophageal emptying such as stricture or achalasia.
- the inability to stand or sit upright for at least 30 minutes.
- hypocalcemia (see 7 WARNINGS AND PRECAUTIONS).
- renal insufficiency with creatinine clearance <0.58 mL/s (<35 mL/min) (see 4 DOSAGE AND ADMINISTRATION; and 10.3 Pharmacokinetics, Renal Insufficiency)
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Patients should receive supplemental calcium and vitamin D if dietary intake is inadequate. See 7 WARNINGS AND PRECAUTIONS.
- The optimal duration of bisphosphonate treatment for osteoporosis has not been established. The need for continued treatment should be re-evaluated periodically based on the benefits and potential risks of NB-ALENDRONATE-FC on an individual patient basis.
- Although no specific studies have been conducted on the effects of switching patients on another therapy for osteoporosis to alendronate sodium, there are no known or theoretical safety concerns related to alendronate sodium in patients who previously received any other antiosteoporotic therapy.
4.2 Recommended Dose and Dosage Adjustment
Treatment of Osteoporosis in Postmenopausal Women and in Men
The recommended dosage is one 70 mg tablet once weekly.
Dosage Adjustment
Geriatrics (≥ 65 years of age): No dosage adjustment is necessary for the elderly (see 1 INDICATION, 1.2 Geriatrics).
Pediatrics (< 18 years of age): Health Canada has not authorized an indication for pediatric use (see 1 INDICATION, 1.1 Pediatrics).
Renal Impairment: No dosage adjustment is required for patients with mild-to-moderate renal insufficiency (creatinine clearance 0.58 to 1 mL/s [35 to 60 mL/min]). NB-ALENDRONATE-FC is contraindicated for patients with more severe renal insufficiency (creatinine clearance < 0.58 mL/s [< 35 mL/min]) (see 2 CONTRAINDICATIONS).
4.4 Administration
NB-ALENDRONATE-FC must be taken at least one-half hour before the first food, beverage, or medication of the day with plain water only. Other beverages (including mineral water), food, and some medications are known to reduce the absorption of NB-ALENDRONATE-FC (see 9 DRUG INTERACTIONS).
Waiting less than 30 minutes will lessen the effect of NB-ALENDRONATE-FC by decreasing its absorption into the body.
NB-ALENDRONATE-FC should only be taken upon arising for the day. To facilitate delivery to the stomach and thus reduce the potential for esophageal irritation, a NB-ALENDRONATE-FC tablet should be swallowed with a full glass of water (200–250 mL). Patients should not lie down for at least 30 minutes and until after their first food of the day. NB-ALENDRONATE-FC should not be taken at bedtime or before arising for the day. Failure to follow these instructions may increase the risk of esophageal adverse experiences (see 7 WARNINGS AND PRECAUTIONS).
NB-ALENDRONATE-FC tablets should not be chewed, sucked, cut, or crushed (see 7 WARNINGS AND PRECAUTIONS).
4.5 Missed Dose
Patients should be instructed that if they miss a dose of NB-ALENDRONATE-FC 70 mg once weekly, they should take one dose on the morning after they remember. They should not take two doses on the same day but should return to taking one dose once a week, as originally scheduled on their chosen day.
5 OVERDOSAGE
No specific information is available on the treatment of overdosage with NB-ALENDRONATE-FC. Hypocalcemia, hypophosphatemia, and upper gastrointestinal adverse events, such as upset stomach, heartburn, esophagitis, gastritis, or ulcer, may result from oral overdosage. Milk or antacids should be given to bind alendronate. Due to the risk of esophageal irritation, vomiting should not be induced and the patient should remain fully upright.
Dialysis would not be beneficial.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control center or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Tablet / 70 mg / Each tablet contains 91.37 mg of alendronate sodium, which is the molar equivalent to 70 mg of free acid | Hypromellose, Magnesium Stearate, Mannitol, Microcrystalline Cellulose, Sodium Starch Glycolate, and Starch. |
NB-ALENDRONATE-FC
70 mg: Each white, oval-shaped, biconvex coated tablet with "P" logo debossed on one side and "70" on the other side. Available in HDPE bottles of 100 tablets and blisters of 4 tablets.
7 WARNINGS AND PRECAUTIONS
General
To facilitate delivery to the stomach and thus reduce the potential for esophageal irritation, patients should be instructed to swallow each tablet of NB-ALENDRONATE-FC with a full glass of water. Patients should be instructed not to lie down for at least 30 minutes and until after their first food of the day. Patients should not chew or suck on the tablet because of a potential for oropharyngeal ulceration. Patients should be specifically instructed not to take NB-ALENDRONATE-FC at bedtime or before arising for the day. Patients should be informed that failure to follow these instructions may increase their risk of esophageal problems. Patients should be instructed that if they develop symptoms of esophageal disease (such as difficulty or pain upon swallowing, retrosternal pain or new or worsening heartburn) they should stop taking NB-ALENDRONATE-FC immediately and consult their physician (see 4.4 Administration).
Causes of osteoporosis other than estrogen deficiency, aging and glucocorticoid use should be considered.
Endocrine and Metabolism
Hypocalcemia must be corrected before initiating therapy with NB-ALENDRONATE-FC (see 2 CONTRAINDICATIONS). Other disorders affecting mineral metabolism (such as Vitamin D deficiency) should be treated. In patients with these conditions, serum calcium and symptoms of hypocalcemia should be monitored during therapy with NB-ALENDRONATE-FC. Symptomatic hypocalcemia has been reported rarely, both in patients with predisposing conditions and patients without known predisposing conditions.
Patients should be advised to report to their physicians any symptoms of hypocalcemia, such as paresthesias or muscle spasms. Physicians should carefully evaluate patients who develop hypocalcemia during therapy with NB-ALENDRONATE-FC for predisposing conditions.
Due to the positive effects of alendronate sodium in increasing bone mineral, small, asymptomatic decreases in serum calcium and phosphate may occur, in whom the pre-treatment rate of bone turnover may be greatly elevated, and in patients receiving glucocorticoids, in whom calcium absorption may be decreased.
Ensuring adequate calcium and Vitamin D intake is especially important in patients receiving glucocorticoids.
Gastrointestinal
NB-ALENDRONATE-FC, like other bisphosphonates, may cause local irritation of the upper gastrointestinal mucosa.
Esophageal adverse experiences, such as esophagitis, esophageal ulcers and esophageal erosions, rarely followed by esophageal stricture or perforation, have been reported in patients receiving treatment with alendronate sodium. In some cases these have been severe and required hospitalization. Physicians should therefore be alert to any signs or symptoms signaling a possible esophageal reaction and patients should be instructed to discontinue NB-ALENDRONATE-FC immediately and seek medical attention if they develop dysphagia, odynophagia, retrosternal pain or new or worsening heartburn (see 8.2 Clinical Trial Adverse Reactions; 8.5 Post-Market Adverse Reactions.
The risk of severe esophageal adverse experiences appears to be greater in patients who lie down after taking alendronate sodium and/or who fail to swallow it with the recommended amount of water, and/or who continue to take alendronate sodium after developing symptoms suggestive of esophageal irritation. Therefore, it is very important that the full dosing instructions are provided to, and understood by, the patient (see 4 DOSAGE AND ADMINISTRATION).
Because of possible irritant effects of alendronate sodium on the upper gastrointestinal mucosa and a potential for worsening of the underlying disease, caution should be used when NB-ALENDRONATE-FC is given to patients with active upper gastrointestinal problems, such as dysphagia, esophageal diseases (including known Barrett’s esophagus), gastritis, duodenitis, or ulcers.
While no increased risk was observed in extensive clinical trials, there have been rare (post- marketing) reports of gastric and duodenal ulcers, some severe and with complications.
Musculoskeletal
Atypical fractures: Low-energy fractures of the subtrochanteric and proximal femoral shaft and other bones have been reported in some long-term (time to onset in the majority of reports ranged from 18 months to 10 years) alendronate-treated patients. Some were stress fractures (some of which were reported as insufficiency fractures) occurring in the absence of apparent trauma or induced by mild external force. Some patients experienced prodromal pain in the affected area, often associated with imaging features of stress fracture, weeks to months before a complete fracture occurred. Approximately one third of the reported femur fractures were bilateral; therefore, the contralateral femur should be examined in patients who have sustained a femoral shaft stress fracture. Poor healing of these fractures was also reported.
Patients with suspected stress fractures should be evaluated, including evaluation for causes and risk factors of stress fractures (e.g., vitamin D deficiency, malabsorption, glucocorticoid use, lower extremity arthritis or fracture, previous stress fracture, extreme or increased exercise, diabetes mellitus, chronic alcohol abuse), and receive appropriate orthopedic care. Interruption of alendronate therapy in patients with stress fractures should be considered based on individual benefit/risk assessment (see 8.5 Post-Market Adverse Reactions).
Musculoskeletal Pain: In post-marketing experience, severe and occasionally incapacitating bone, joint, and/or muscle pain has been reported in patients taking bisphosphonates that are approved for the prevention and treatment of osteoporosis. However, such reports have been infrequent. This category of drugs includes NB-ALENDRONATE-FC. Most of the patients were postmenopausal women. The time to onset of symptoms varied from one day to several months after starting the drug. Most patients had relief of symptoms after stopping the medication. A subset had recurrence of symptoms when rechallenged with the same drug or another bisphosphonate (see 8.5 Post-Market Adverse Reactions).
In placebo-controlled clinical studies of alendronate sodium, the percentages of patients with these symptoms were similar in the alendronate sodium and placebo groups.
Osteonecrosis:
Osteonecrosis of the jaw (ONJ) has been reported in patients receiving treatment regimens including bisphosphonates. The majority of reports occurred following tooth extractions with delayed healing and involved cancer patients treated with intravenous bisphosphonates. Many of these patients were also receiving chemotherapy and corticosteroids. However, some cases have also occurred in patients receiving oral bisphosphonate treatment for postmenopausal osteoporosis and other diagnoses. The majority of reported cases have been associated with dental procedures such as tooth extraction. Many had signs of local infection, including osteomyelitis (see 8.5 Post-Market Adverse Reactions).
A dental examination with appropriate preventive dentistry should be considered prior to treatment with bisphosphonates in patients with concomitant risk factors. Known risk factors for osteonecrosis of the jaw include a diagnosis of cancer, concomitant therapies (e.g., chemotherapy, radiotherapy, corticosteroids, angiogenesis inhibitors, immunosuppressive drugs), poor oral hygiene, co-morbid disorders (e.g., periodontal and/or other pre-existing dental disease, anemia, coagulopathy, infection, diabetes mellitus), smoking, and heavy alcohol use.
Patients who develop osteonecrosis of the jaw should receive appropriate antibiotic therapy and/or oral surgery and discontinuation of bisphosphonate therapy should be considered based on individual benefit/risk assessment. Dental surgery may exacerbate the condition. For patients requiring dental procedures (e.g., tooth extraction, dental implants), there are no definitive data available to establish whether discontinuation of bisphosphonate treatment reduces the risk of ONJ.
Cases of osteonecrosis of the external auditory canal (cholesteatoma) have been reported in patients treated with alendronate sodium.
Clinical judgment of the treating physician and/or oral surgeon should guide the management plan, including bisphosphonate treatment, of each patient based on individual benefit/risk assessment.
The following should be considered when evaluating a patient’s risk of developing ONJ:
- Potency of the medicinal product that inhibits bone resorption (higher risk for highly potent compounds).
- Route of administration (higher risk for parenteral administration).
- Cumulative dose of bone resorption therapy.
- Co-morbid conditions (e.g., anemia, coagulopathies) and smoking.
- Periodontal disease, poorly fitting dentures, history of dental disease.
Ophthalmologic
Ocular disturbances including conjunctivitis, uveitis, episcleritis and scleritis have been reported with alendronate therapy. Patients with ocular events other than uncomplicated conjunctivitis should be referred to an ophthalmologist for evaluation. If ocular inflammatory symptoms are observed, treatment may need to be discontinued (see 8.5 Post-Market Adverse Reactions).
Renal
NB-ALENDRONATE-FC is contraindicated for patients with severe renal insufficiency (creatinine clearance < 0.58 mL/s [< 35 mL/min]) (see 2 CONTRAINDICATIONS).
Reproductive Health: Female and Male Potential
Fertility
The effect of alendronate sodium on human fertility has not been evaluated. Animal study data is included in Section 16 NON-CLINICAL TOXICOLOGY
7.1 Special Populations
7.1.1 Pregnant Women
NB-ALENDRONATE-FC should not be used by pregnant women. Alendronate sodium has not been studied in pregnant women.
7.1.2 Breast-feeding
NB-ALENDRONATE-FC should not be used during breast-feeding. It is unknown whether alendronate/metabolites are excreted in human milk. A risk to the newborns/infants cannot be excluded.
7.1.3 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
In clinical studies, there was no age-related difference in the efficacy or safety profiles of alendronate sodium (see 14 CLINICAL TRIALS).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common drug-related adverse reactions include gastrointestinal disorders (abdominal pain, dyspepsia, constipation, diarrhea, flatulence, esophageal ulcer, dysphagia, acid regurgitation, melena, nausea and abdominal distention), musculoskeletal (bone, muscle or joint) pain and headache.
It is important to follow the recommended dosing instructions. See 7 WARNINGS AND PRECAUTIONS, Gastrointestinal; and 4.4 Administration.
Osteonecrosis of the Jaw and atypical bone fractures have been observed under post marketing setting. See 7 WARNINGS AND PRECAUTIONS, Musculoskeletal.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Treatment of Osteoporosis
Postmenopausal Women:
In two, three-year, placebo-controlled, double-blind, multicenter studies (United States and Multinational) of virtually identical design, with a total of 994 postmenopausal women, the overall safety profiles of alendronate sodium 10 mg/day and placebo were similar.
Discontinuation of therapy due to any clinical adverse experience occurred in 4.1% of 196 patients treated with alendronate sodium 10 mg/day and 6.0% of 397 patients treated with placebo.
Adverse experiences considered by the investigators as possibly, probably, or definitely drug- related in ≥ 1% of patients treated with either alendronate sodium 10 mg/day or placebo are presented in the following table.
Table 2 - Drug-Related* Adverse Experiences Reported in ≥ 1% of Patients Treated for Osteoporosis
Alendronate Sodium 10 mg/day n = 196 (%) | Placebo n = 397 (%) | |
|---|---|---|
Gastrointestinal abdominal pain nausea dyspepsia constipation diarrhea flatulence acid regurgitation esophageal ulcer vomiting dysphagia abdominal distention gastritis | 6.6 3.6 3.6 3.1 3.1 2.6 2.0 1.5 1.0 1.0 1.0 0.5 | 4.8 4.0 3.5 1.8 1.8 0.5 4.3 0.0 1.5 0.0 0.8 1.3 |
Musculoskeletal musculoskeletal (bone, muscle or joint) pain muscle cramp | 4.1 0.0 | 2.5 1.0 |
Nervous System/Psychiatric headache dizziness | 2.6 0.0 | 1.5 1.0 |
| Special Senses | 0.5 | 1.0 |
* Considered possibly, probably, or definitely drug-related as assessed by the investigators.
One patient treated with alendronate sodium (10 mg/day), who had a history of peptic ulcer disease and gastrectomy and who was taking concomitant acetylsalicylic acid (ASA) developed an anastomotic ulcer with mild hemorrhage, which was considered drug-related. ASA and alendronate sodium were discontinued and the patient recovered.
In the two-year extension (treatment years 4 and 5) of the above studies, the overall safety profile of alendronate sodium 10 mg/day was similar to that observed during the three-year placebo- controlled period. Additionally, the proportion of patients who discontinued alendronate sodium 10 mg/day due to any clinical adverse experience was similar to that during the first three years of the study.
In the Fracture Intervention Trial, discontinuation of therapy due to any clinical adverse experience occurred in 9.1% of 3,236 patients treated with alendronate sodium 5 mg/day for two years and 10 mg/day for either one or two additional years and 10.1% of 3,223 patients treated with placebo.
Discontinuations due to upper gastrointestinal adverse experiences were: alendronate sodium, 3.2%; placebo, 2.7%. The overall adverse experience profile was similar to that seen in other studies with alendronate sodium 5 or 10 mg/day.
In a one-year, double-blind multicenter study, the overall safety and tolerability profiles of alendronate sodium 70 mg once weekly and alendronate sodium 10 mg daily were similar. The adverse experiences considered by the investigators as possibly, probably, or definitely drug-related in ≥ 1% of patients in either treatment group are presented in the following table:
Table 3 - Drug-Related* Adverse Experiences Reported in ≥ 1% of Patients Treated for Osteoporosis
Alendronate sodium 70 mg once weekly n = 519 (%) | Alendronate sodium 10 mg/day n = 370 (%) | |
|---|---|---|
Gastrointestinal abdominal pain dyspepsia acid regurgitation nausea abdominal distention constipation flatulence gastritis gastric ulcer | 3.7 2.7 1.9 1.9 1.0 0.8 0.4 0.2 0.0 | 3.0 2.2 2.4 2.4 1.4 1.6 1.6 1.1 1.1 |
Musculoskeletal musculoskeletal (bone, muscle or joint) pain muscle cramp | 2.9 0.2 | 3.2 1.1 |
* Considered possibly, probably, or definitely drug-related as assessed by the investigators.
Men:
In two placebo-controlled, double-blind, multicenter studies in men (a two-year study of alendronate sodium 10 mg/day [n = 146] and a one-year study of alendronate sodium 70 mg once weekly [n = 109]), the safety profile of alendronate sodium was generally similar to that seen in postmenopausal women. The rates of discontinuation of therapy due to any clinical adverse experience were 2.7% for alendronate sodium 10 mg/day vs. 10.5% for placebo, and 6.4% for alendronate sodium 70 mg once weekly vs. 8.6% for placebo.
Other Studies in Men and Women:
In a ten-week endoscopy study in men and women (n = 277; mean age: 55) no difference was seen in upper gastrointestinal tract lesions between alendronate sodium 70 mg once weekly and placebo.
In an additional one-year study in men and women (n = 335; mean age: 50) the overall safety and tolerability profiles of alendronate sodium 70 mg once weekly were similar to that of placebo and no difference was seen between men and women.
Concomitant Use with Estrogen/Hormone Replacement Therapy:
In two studies (of one- and two-years’ duration) of postmenopausal osteoporotic women (total: n = 853), the safety and tolerability profile of combined treatment with alendronate sodium 10 mg once daily and estrogen ± progestin (n = 354) was consistent with those of the individual treatments.
8.3 Less Common Clinical Trial Adverse Reactions
Skin: rash and erythema
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
In double-blind, multicenter, controlled studies, asymptomatic, mild, and transient decreases in serum calcium and phosphate were observed in approximately 18 and 10%, respectively, of patients taking alendronate sodium versus approximately 12 and 3% of those taking placebo. However, the incidences of decreases in serum calcium to < 8.0 mg/dL (2.0 mM) and serum phosphate to ≤ 2.0 mg P1/dL (0.65 mM) were similar in both treatment groups.
In a small, open-label study, at higher doses (80 mg/day) some patients had elevated transaminases. However, this was not observed at 40 mg/day. No clinically significant toxicity was associated with these laboratory abnormalities.
Rare cases of leukemia have been reported following therapy with other bisphosphonates. Any causal relationship to either the treatment or to the patients’ underlying disease has not been established.
1 P: Elemental phosphorus
8.5 Post-Market Adverse Reactions
The following adverse reactions have been reported in post-marketing use of alendronate sodium:
Body as a Whole: Hypersensitivity reactions including urticaria and angioedema; transient symptoms of myalgia, malaise, asthenia and fever have been reported with alendronate sodium typically in association with initiation of treatment; symptomatic hypocalcemia both in association with predisposing conditions and in patients without known predisposing conditions; peripheral edema.
Dental: Localized osteonecrosis of the jaw (ONJ) generally associated with local infection (including osteomyelitis) and/or tooth extraction with delayed healing (see 7 WARNINGS AND PRECAUTIONS).
Gastrointestinal: Esophagitis, esophageal erosions, esophageal ulcers, esophageal stricture or perforation, and oropharyngeal ulceration; gastric or duodenal ulcers, some severe and with complications (see 7 WARNINGS AND PRECAUTIONS; and 4 DOSAGE AND ADMINISTRATION).
Musculoskeletal: Bone, joint, and/or muscle pain, occasionally severe and/or incapacitating; joint swelling; low-energy fractures of the femoral shaft and other bones (see 7 WARNINGS AND PRECAUTIONS).
Nervous System: Dizziness, vertigo, dysgeusia
Skin: Rash (occasionally with photosensitivity), pruritus, alopecia; severe skin reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis
Special Senses: Uveitis, scleritis or episcleritis; osteonecrosis of the external auditory canal (cholesteatoma)
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Specific interaction studies were not performed. Animal studies have demonstrated that alendronate sodium is highly concentrated in bone and is retained only minimally in soft tissue. No metabolites have been detected. Although alendronate is bound approximately 78% to plasma protein in humans, its plasma concentration is so low after oral dosing that only a small fraction of plasma-binding sites is occupied, resulting in a minimal potential for interference with the binding of other drugs. Alendronate is not excreted through the acidic or basic transport systems of the kidney in rats, and thus it is not anticipated to interfere with the excretion of other drugs by those systems in humans. In summary, alendronate sodium is not expected to interact with other drugs based on effects on protein binding, renal excretion, or metabolism of other drugs.
9.3 Drug-Behavioural Interactions
No studies on the effects on the ability to drive and use machines have been performed. However, certain adverse reactions that have been reported with alendronate sodium (e.g., dizziness, vertigo, visual disturbances, and severe bone, muscle or joint pain) may affect some patients’ ability to drive or operate machinery. Individual responses to NB-ALENDRONATE-FC may vary.
Table 4 - Interaction with Alendronate Sodium
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Calcium supplements, Antacids, other Multivalent Cations and other Oral Medications | Interfere with absorption of alendronate | Wait at least one-half hour after taking NB-ALENDRONATE-FC before taking any other oral medication. | |
| Ranitidine | CT | Was shown to double the bioavailability of oral alendronate | The clinical significance of this increased bioavailability and whether similar increases will occur in patients given oral H2 antagonists is unknown |
Hormone Replacement Therapy (HRT [estrogen ± progestin]) | CT | Greater increases in bone mass, together with greater decreases in bone turnover, than seen with either treatment alone. | The safety and tolerability profile of the combination was consistent with those of the individual treatments (see 8.2 ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, Concomitant Use with Estrogen/Hormone Replacement Therapy). The studies were too small to detect antifracture efficacy, and no significant differences in fracture incidence among the treatment groups were found. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Alendronate sodium was used in osteoporosis studies in men, postmenopausal women, and glucocorticoid users, with a wide range of commonly prescribed drugs without evidence of clinical adverse interactions.
In clinical studies, the incidence of upper gastrointestinal adverse events was increased in patients receiving daily therapy with dosages of alendronate sodium greater than 10 mg and acetylsalicylic acid-containing products. This was not observed in a study with alendronate sodium 70 mg once weekly.
Alendronate sodium may be administered to patients taking nonsteroidal anti-inflammatory drugs (NSAIDs). In a three-year, controlled, clinical study (n=2,027) during which a majority of patients received concomitant NSAIDs, the incidence of upper gastrointestinal adverse events was similar in patients taking alendronate sodium 5 or 10 mg/day compared to those taking placebo.
However, since NSAID use is associated with gastrointestinal irritation, caution should be used during concomitant use with alendronate sodium.
9.5 Drug-Food Interactions
Food and beverages other than plain water may markedly reduce the absorption and effectiveness of alendronate. NB-ALENDRONATE-FC must be taken at least one-half hour before the first food, beverage, or medication of the day with plain water only (see 4 DOSAGE AND ADMINISTRATION, 4.4 Administration).
9.6 Drug-Herb Interactions
Herbal products may interfere with the absorption of alendronate. NB-ALENDRONATE-FC must be taken at least one-half hour before any herbal products. See 4 DOSAGE AND ADMINISTRATION, 4.4 Administration)
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Alendronate sodium is a bisphosphonate that acts as a potent, specific inhibitor of osteoclast-mediated bone resorption. Bisphosphonates are synthetic analogs of pyrophosphate that bind to the hydroxyapatite found in bone.
10.2 Pharmacodynamics
Alendronate is a bisphosphonate that binds to bone hydroxyapatite and specifically inhibits the activity of osteoclasts, the bone-resorbing cells. Alendronate reduces bone resorption with no direct effect on bone formation, although the latter process is ultimately reduced because bone resorption and formation are coupled during bone turnover.
Osteoporosis in Postmenopausal Women
Osteoporosis is characterized by low bone mass that leads to an increased risk of fracture. The diagnosis can be confirmed by the finding of low bone mass, evidence of fracture on x -ray, a history of osteoporotic fracture, or height loss or kyphosis, indicative of vertebral fracture.
Osteoporosis occurs in both males and females but is most common among women following the menopause, when bone turnover increases and the rate of bone resorption exceeds that of bone formation. These changes result in progressive bone loss and lead to osteoporosis in a significant proportion of women over age 50. Fractures, usually of the spine, hip, and wrist, are the common consequences. From age 50 to age 90, the risk of hip fracture in white women increases 50-fold and the risk of vertebral fracture 15- to 30-fold. It is estimated that approximately 40% of 50-year-old women will sustain one or more osteoporosis-related fractures of the spine, hip, or wrist during their remaining lifetimes. Hip fractures, in particular, are associated with substantial morbidity, disability, and mortality.
Daily oral doses of alendronate (5, 20, and 40 mg for six weeks) in postmenopausal women produced biochemical changes indicative of dose-dependent inhibition of bone resorption, including decreases in urinary calcium and urinary markers of bone collagen degradation (such as deoxypyridinoline and cross-linked N-telopeptides of type I collagen). These biochemical changes tended to return toward baseline values as early as 3 weeks following the discontinuation of therapy with alendronate and did not differ from placebo after 7 months.
Long-term treatment of osteoporosis with alendronate sodium 10 mg/day (for up to five years) reduced urinary excretion of markers of bone resorption, deoxypyridinoline and cross-linked N-telopeptides of type I collagen, by approximately 50% and 70%, respectively, to reach levels similar to those seen in healthy premenopausal women. Similar decreases were seen in patients in osteoporosis prevention studies who received alendronate sodium 5 mg/day. The decrease in the rate of bone resorption indicated by these markers was evident as early as one month and at three to six months reached a plateau that was maintained for the entire duration of treatment with alendronate sodium. In osteoporosis treatment studies, alendronate sodium 10 mg/day decreased the markers of bone formation, osteocalcin and bone specific alkaline phosphatase by approximately 50%, and total serum alkaline phosphatase, by approximately 25 to 30%, to reach a plateau after 6 to 12 months. Similar reductions in the rate of bone turnover were observed in postmenopausal women during a one-year study with alendronate sodium 70 mg once weekly for the treatment of osteoporosis. These data indicate that the rate of bone turnover reached a new steady-state, despite the progressive increase in the total amount of alendronate deposited within bone.
As a result of inhibition of bone resorption, asymptomatic reductions in serum calcium and phosphate concentrations were also observed following treatment with alendronate sodium. In the long- term studies, reductions from baseline in serum calcium (approximately 2%) and phosphate (approximately 4 to 6%) were evident the first month after the initiation of alendronate sodium 10 mg. No further decreases in serum calcium were observed for the five-year duration of treatment, however, serum phosphate returned toward pre-study levels during years three through five. Similar reductions were observed with alendronate sodium 5 mg/day. In a one-year study with alendronate sodium 70 mg once weekly, similar reductions were observed at 6 and 12 months. The reduction in serum phosphate may reflect not only the positive bone mineral balance due to alendronate sodium but also a decrease in renal phosphate reabsorption.
Osteoporosis in Men
Even though osteoporosis is less prevalent in men than in postmenopausal women, a significant proportion of osteoporotic fractures occur in men. The prevalence of vertebral deformities appears to be similar in men and women. Treatment of men with osteoporosis with alendronate sodium 10 mg/day for two years reduced urinary excretion of cross-linked N- telopeptides of type I collagen by approximately 60% and bone-specific alkaline phosphatase by approximately 40%. Similar reductions were observed in a one-year study in men with osteoporosis receiving alendronate sodium 70 mg once weekly.
10.3 Pharmacokinetics
Table 5 - Summary of alendronate sodium Pharmacokinetic Parameters in the Normal Population
| Mean | 90% Confidence Interval | ||||||
|---|---|---|---|---|---|---|---|
| Absolute bioavailability of 5 mg tablet, taken 2 hours before first meal of the day | 0.63% (females) | (0.48, 0.83) | |||||
| Absolute bioavailability of 10 mg tablet, taken 2 hours before first meal of the day | 0.78% (females) | (0.61, 1.04) | |||||
| 0.59% (males) | (0.43, 0.81) | ||||||
| Absolute bioavailability of 40 mg tablet, taken 2 hours before first meal of the day | 0.60% (females) | (0.46, 0.78) | |||||
| Absolute bioavailability of 70 mg tablet, taken 2 hours before first meal of the day | 0.57% (females) | (0.44, 0.73) | |||||
| Renal Clearance mL/s (mL/min) (n = 6) | 1.18 (71) | (1.07, 1.3) (64, 78) | |||||
Absorption
Relative to an intravenous (IV) reference dose, the mean oral bioavailability of alendronate in women was 0.64% for doses ranging from 5 to 70 mg when administered after an overnight fast and two hours before a standardized breakfast. Oral bioavailability of the 10 mg tablet in men was 0.59%.
A study examining the effect of timing of a meal on the bioavailability of alendronate was performed in 49 postmenopausal women. Bioavailability was decreased (by approximately 40%) when 10 mg alendronate was administered either 0.5 or 1 hour before a standardized breakfast, when compared to dosing 2 hours before eating. In studies of treatment and prevention of osteoporosis, alendronate was effective when administered at least 30 minutes before breakfast.
Bioavailability was negligible whether alendronate was administered with or up to two hours after a standardized breakfast. Concomitant administration of alendronate with coffee or orange juice reduced bioavailability by approximately 60%.
In healthy subjects, oral prednisone (20 mg three times daily for five days) did not produce a clinically meaningful change in the oral bioavailability of alendronate (a mean increase ranging from 20 to 44%).
Distribution
Preclinical studies (in male rats) show that alendronate transiently distributes to soft tissues following 1 mg/kg IV administration but is then rapidly redistributed to bone or excreted in the urine. The mean steady-state volume of distribution, exclusive of bone, is at least 28 L in humans.
Concentrations of drug in plasma following therapeutic oral doses are too low (less than 5 ng/mL) for analytical detection. Protein binding in human plasma is approximately 78%.
Metabolism
There is no evidence that alendronate is metabolized in animals or humans.
Elimination
Following a single IV dose of [14C] alendronate, approximately 50% of the radioactivity was excreted in the urine within 72 hours and little or no radioactivity was recovered in the feces.
Following a single 10 mg IV dose, the renal clearance of alendronate was 71 mL/min and systemic clearance did not exceed 200 mL/min. Plasma concentrations fell by more than 95% within 6 hours following IV administration. The terminal half-life in humans is estimated to exceed 10 years, probably reflecting release of alendronate from the skeleton. Based on the above, it is estimated that after 10 years of oral treatment with alendronate sodium (10 mg daily) the amount of alendronate released daily from the skeleton is approximately 25% of that absorbed from the gastrointestinal tract.
Special Populations and Conditions
- Pediatrics: The oral bioavailability in children (4 to 16 years of age) with osteogenesis imperfecta(OI) was similar to that observed in adults; however, NB-ALENDRONATE-FC is not indicated for use in children (see 7.1.3 Pediatrics).
- Geriatrics: Bioavailability and disposition (urinary excretion) were similar in elderly (≥ 65 years of age) and younger patients. No dosage adjustment is necessary (see 4 DOSAGE AND ADMINISTRATION).
- Sex: Bioavailability and the fraction of an IV dose excreted in urine were similar in men and women.
- Ethnic Origin: Pharmacokinetic differences due to race have not been studied.
- Hepatic Insufficiency: As there is evidence that alendronate is not metabolized or excreted in the bile, no studies were conducted in patients with hepatic insufficiency. No dosage adjustment is necessary.
Renal Insufficiency: Preclinical studies show that, in rats with kidney failure, increasing amounts of drug are present in plasma, kidney, spleen, and tibia. In healthy controls, drug that is not deposited in bone is rapidly excreted in the urine. No evidence of saturation of bone uptake was found after 3 weeks dosing with cumulative IV doses of 35 mg/kg in young male rats. Although no clinical information is available, it is likely that, as in animals, elimination of alendronate via the kidney will be reduced in patients with impaired renal function. Therefore, somewhat greater accumulation of alendronate in bone might be expected in patients with impaired renal function.
No dosage adjustment is necessary for patients with mild-to-moderate renal insufficiency (creatinine clearance 0.58 to 1 mL/s [35 to 60 mL/min]). NB-ALENDRONATE-FC is contraindicated for patients with more severe renal insufficiency (creatinine clearance < 0.58 mL/s [< 35 mL/min]). See 2 CONTRAINDICATIONS.
11 STORAGE, STABILITY AND DISPOSAL
Store NB-ALENDRONATE-FC tablets between 15°C and 30°C.
Keep out of reach and sight of children.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Alendronate sodium
Chemical name: (4-amino-l-hydroxybutylidene) bisphosphonic acid monosodium salt trihydrate.
Molecular formular: C4H12NNaO7P2.● 3H2O
Molecular mass: 325.13 g/mol
Structural formula:
OH P P O OH ONa OH OH O H2NCH2CH2CH2C . 3H2O
Physicochemical properties:
Description: Alendronate sodium is a white, crystalline, nonhygroscopic powder.
Solubility: It is soluble in water, very slightly soluble in alcohol, and practically insoluble in chloroform.
pH: The pH in a 1% aqueous solution is between 4.0 and 5.0.
pKa: The pKa is: pK1 = 2.72±0.05; pK2 = 8.73±0.05; pK3 = 10.5±0.1; pK4 = 11.6±0.1.
Melting Point: Melting point is 275°C.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Treatment of osteoporosis in postmenopausal women
Table 6 - Summary of patient demographics for clinical trials (treatment of osteoporosis in postmenopausal women)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| PN035 | Double -blind, randomized, placebo-controlled, parallel group multicenter extension study | PBO FOS 5mg FOS 10mg FOS 20/5mg ORAL 3 years | 478 | 45-82 | Women |
| PN037 | Double -blind, randomized, placebo-controlled, parallel group multicenter extension study | PBO FOS 5mg FOS 10mg FOS 20/5mg ORAL 3 years | 516 | 44 to 84 | Women |
| PN041 | Double-blind, randomized, parallel-group study | PB0 FOS 10mg FOS 20mg sCT ORAL 2 years | 286 | 48-76 | Women |
| PN118 | Randomized, Double-blind, multicenter study | FOS 10mg FOS 35mg (twice a week) FOS 70mg (once a week) ORAL 1 year | 1,258 | 42-95 | Women |
| PN026 | Double-blind, randomized, placebo controlled- parallel group, multicenter study | PBO FOS 5mg FOS 10mg FOS 20mg/PBO FOS 40mg/PBO FOS 40mg/2.5mg ORAL 2 (+1*year) | 188 | 42-75 | Women |
| PN054 | Double-blind, randomized, placebo controlled, parallel-group study | PBO FOS 1mg FOS 2.5mg FOS 5mg ORAL 2 years | 359 | 59-85 | Women |
| FIT 1 | Randomized, placebo-controlled | PBO FOS 10mg ORAL 3 years | 2,027 | 55-81 | Women |
| FIT 2 | Randomized, placebo-controlled | PBO FOS 10mg ORAL 4 years | 4,432 | 55-80 | Women |
| PN072 | Double-blind, randomized, placebo-controlled, multicenter study | FOS 10mg + conjugated estrogens (0.625 mg) OR conjugated estrogens (0.625 mg) OR PBO OR FOS 10mg ORAL 2 years | 425 | 42-82 | Women |
| PN097 | Triple-blind, randomized, placebo-controlled, parallel-group, multicenter study | FOS 10 mg/day + HRT (estrogen + progestin) OR PBO/HRT ORAL 1 year | 428 | 40-84 | Women |
PBO = Placebo; FOS = alendronate (mg/day); sCT = Intranasal salmon calcitonin 100 IU/day; FOS 20/PB0, FOS 40/PBP = alendronate 20 or 40 mg for 1 year followed by placebo for 1 year; FOS 40/2.5 = alendronate 40mg for 3 months followed by 2.5 for 21 months; FOS 20/5 = alendronate 20 mg for 2 years followed by 5 mg for 1 year
*Following 2 years of treatment, patients were followed for a further year off treatment
Effect on Bone Mineral Density
The efficacy of alendronate sodium 10 mg once daily in postmenopausal women, 44 to 84 years of age, with osteoporosis (lumbar spine bone mineral density [BMD] of at least 2 standard deviations below the premenopausal mean) was demonstrated in four double-blind, placebo-controlled clinical studies of two or three years duration. These included two large three-year, multicenter studies of virtually identical design, one performed in the United States (U.S.) and the other in 15 different countries (Multinational), which enrolled 478 and 516 patients, respectively. The following graph shows the mean increases in BMD of the lumbar spine, femoral neck, and trochanter in patients receiving alendronate sodium 10 mg/day relative to placebo-treated patients at three years for each of these studies.
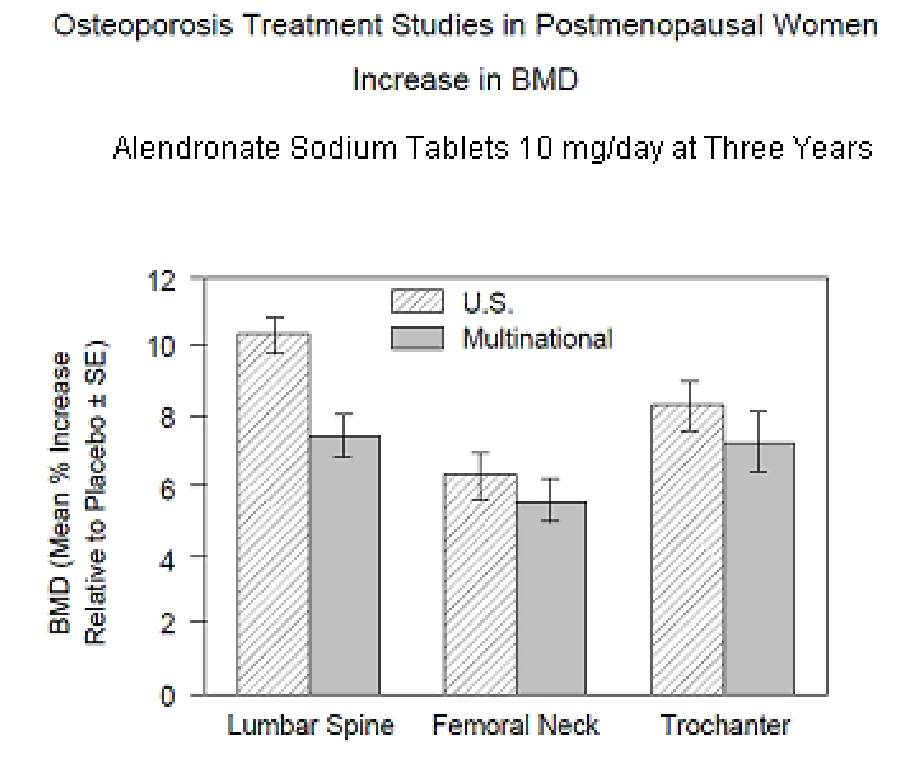
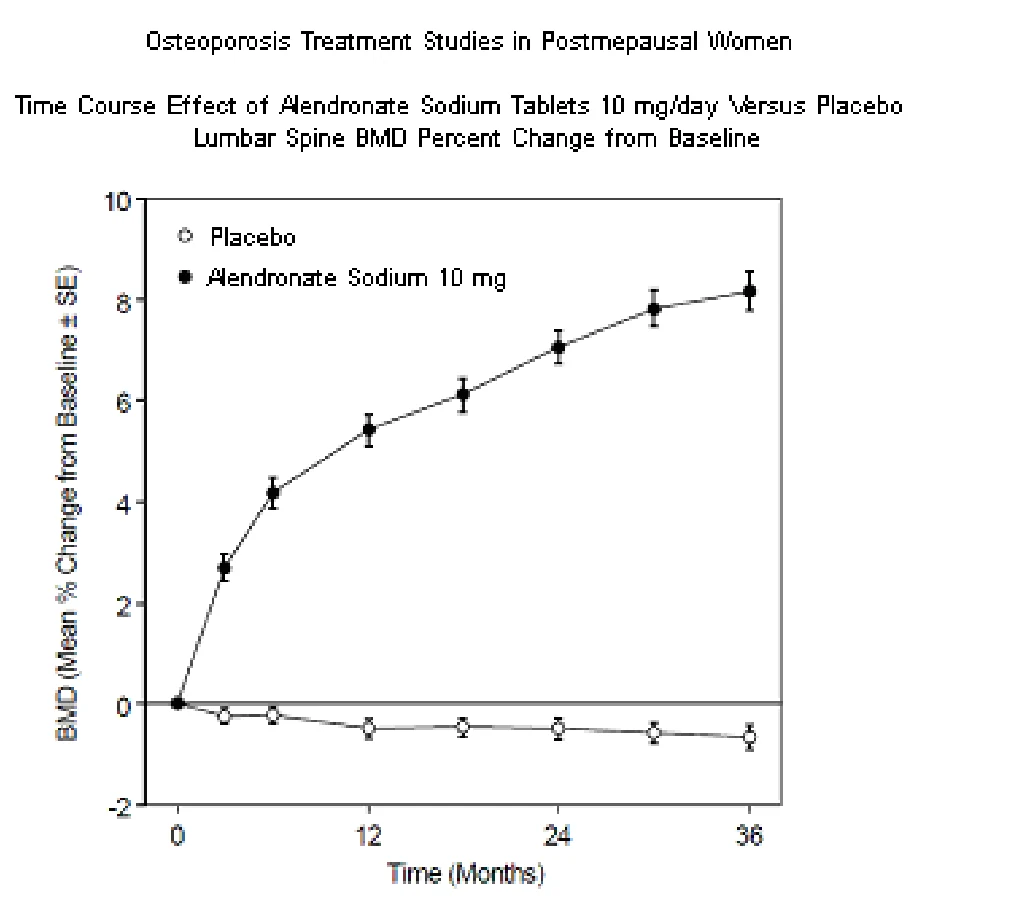
In the combined studies, after three years, BMD of the lumbar spine, femoral neck and trochanter in placebo-treated patients decreased significantly by between 0.65 and 1.16%. Highly significant increases, relative both to baseline and placebo, were seen at each measurement site in each study in patients who received alendronate sodium 10 mg/day. Total body BMD also increased significantly in both studies, suggesting that the increases in bone mass of the spine and hip did not occur at the expense of other skeletal sites. Increases in BMD were evident as early as three months and continued throughout the entire three years of treatment (see following figure for lumbar spine results). In the two-year extension of these studies, treatment with alendronate sodium 10 mg/day resulted in continued increases in BMD at the lumbar spine and trochanter (absolute additional increases between years three and five: lumbar spine, 0.94%; trochanter, 0.88%).
BMD at the femoral neck, forearm and total body were maintained. Thus, alendronate sodium reverses the progression of osteoporosis. Alendronate sodium was similarly effective regardless of age, race, baseline rate of bone turnover, renal function and use with a wide range of common medications.
In a separate study, alendronate sodium 10 mg/day for two years induced highly significant increases in BMD of the spine, femoral neck, trochanter, and total body relative to either intranasal salmon calcitonin 100 IU/day or placebo.
The therapeutic equivalence of alendronate sodium 70 mg once weekly (n = 519) and alendronate sodium 10 mg daily (n = 370) was demonstrated in a one-year, double-blind, multicenter study of postmenopausal women with osteoporosis. The mean increases from baseline in lumbar spine BMD at one year were 5.1% (4.8, 5.4%; 95% CI) in the 70 mg once-weekly group and 5.4% (5.0, 5.8%; 95% CI) in the 10 mg daily group. The two treatment groups were also similar with regard to BMD increases at other skeletal sites. In trials with alendronate sodium changes in BMD of this magnitude were associated with a decrease in fracture incidence (see below).
Effects of Withdrawal
In patients with postmenopausal osteoporosis treated with alendronate sodium 10 mg/day for one or two years the effects of treatment withdrawal were assessed. Following discontinuation, bone turnover gradually returned toward pretreatment levels, and BMD no longer increased although accelerated bone loss was not observed. These data indicate that treatment with alendronate sodium must be continuous to produce progressive increases in bone mass.
Effect on Fracture Incidence
To assess the effects of alendronate sodium on vertebral fracture incidence, the U.S. and Multinational studies were combined in an analysis that compared placebo to the pooled dosage groups of alendronate sodium (5 or 10 mg for three years or 20 mg for two years followed by 5 mg for one year).
There was a statistically significant 48% reduction in the proportion of patients treated with alendronate sodium experiencing one or more vertebral fractures relative to those treated with placebo (3.2% vs 6.2%). An even greater reduction in the total number of vertebral fractures (4.2 vs. 11.3 per 100 patients) was also observed. Furthermore, of patients who sustained any vertebral fracture, those treated with alendronate sodium experienced less height loss (5.9 mm vs. 23.3 mm) due to a reduction in both the number and severity of fractures.
Additionally, analysis of the data pooled across doses of ≥ 2.5 mg from five placebo-controlled studies of two or three years’ duration including the U.S. and Multinational studies (alendronate sodium n = 1,012, placebo: n = 590) revealed a significant 29% reduction in non-vertebral fracture incidence (alendronate sodium, 9.0% vs placebo, 12.6%). Like the effect on vertebral fracture incidence, these results of alendronate treatment are consistent with the observed increases in bone mass.
The Fracture Intervention Trial (FIT) consisted of two studies in postmenopausal women: the Three-Year Study of patients who had at least one baseline vertebral (compression) fracture and the Four-Year Study of patients with low bone mass but without a baseline vertebral fracture.
Fracture Intervention Trial: Three-Year Study (patients with at least one baseline vertebral fracture)
This randomized, double-blind, placebo-controlled 2,027-patient study (alendronate sodium, n = 1,022; placebo, n = 1,005) demonstrated that treatment with alendronate sodium resulted in statistically significant and clinically meaningful reductions in fracture incidence at three years as shown in the following table.
Table 7 - Effect of alendronate sodium on Fracture Incidence in the Three-Year Study of FIT (Patients with Vertebral Fracture at Baseline)
| Patients with: | % of Patients | Reduction (%) in Fracture Incidence | ||||||
|---|---|---|---|---|---|---|---|---|
| Alendronate Sodium (n = 1,022) | Placebo (n = 1,005) | |||||||
| Vertebral fractures (diagnosed by X-ray)† | ||||||||
≥ 1 new vertebral fracture ≥ 2 new vertebral fractures | 7.9 | 15.0 | 47*** | |||||
| 0.5 | 4.9 | 90*** | ||||||
| Painful (clinical) fractures | ||||||||
≥ 1 painful vertebral fracture Any painful fracture Hip fracture Wrist (forearm) fracture | 2.3 | 5.0 | 54** | |||||
| 13.8 | 18.1 | 26** | ||||||
| 1.1 | 2.2 | 51* | ||||||
| 2.2 | 4.1 | 48* | ||||||
†Number evaluable for vertebral fracture: alendronate sodium, n = 984; placebo, n = 966
* p < 0.05
** p < 0.01
*** p < 0.001
Furthermore, in this population of patients with baseline vertebral fracture, treatment with alendronate sodium significantly reduced the incidence of hospitalizations (25.0% vs. 30.7%).
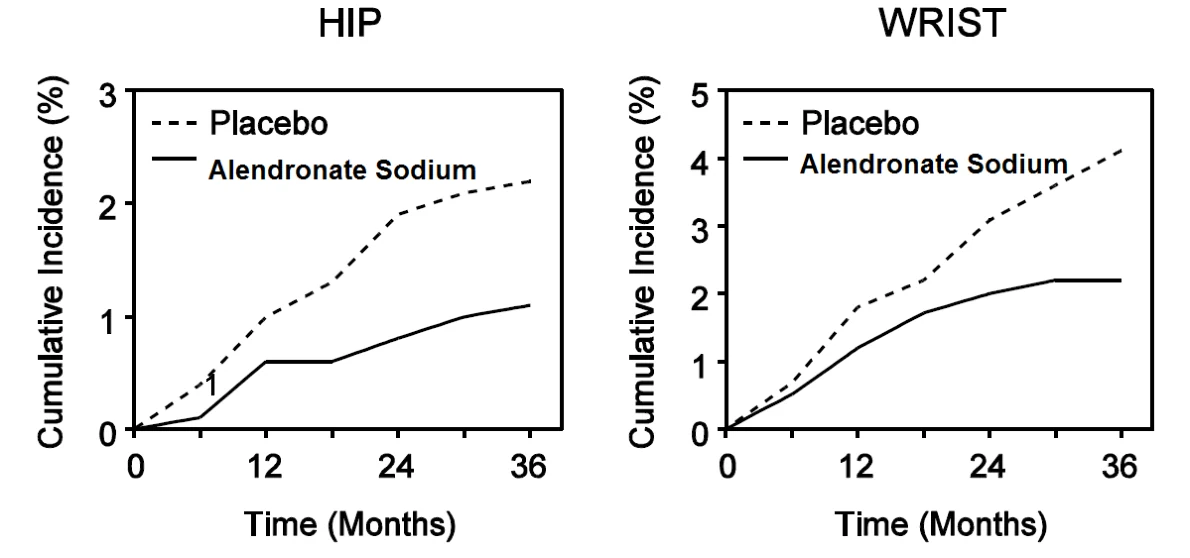
The following two figures display the cumulative incidence of hip and wrist fractures in the Three-Year Study of FIT. In both figures, the cumulative incidence of these types of fracture is lower with alendronate sodium compared with placebo at all time points. Alendronate sodium reduced the incidence of hip fracture by 51% and wrist fracture by 48%. Proportionately similar reductions of hip and wrist fractures were seen in pooled earlier osteoporosis treatment studies.
Cumulative Incidence of Hip and Wrist Fractures in the Three-Year Study of FIT (Patients with Vertebral Fracture at Baseline)
Fracture Intervention Trial: Four-Year Study (patients with low bone mass but without a baseline vertebral fracture)
This randomized, double-blind, placebo-controlled, 4,432-patient study (alendronate sodium, n = 2,214; placebo, n = 2,218) further demonstrated the reduction in fracture incidence due to alendronate sodium. The intent of the study was to recruit women with osteoporosis, i.e. with a baseline femoral neck BMD at least two standard deviations below the mean for young adult women. However, due to subsequent revisions to the normative values for femoral neck BMD, 31% of patients were found not to meet this entry criterion and thus this study included both osteoporotic and non-osteoporotic women. The results are shown in the following table for the patients with osteoporosis.
Table 8 - Effect of alendronate sodium on Fracture Incidence in Osteoporotic† Patients in the Four-Year Study of FIT (Patients without Vertebral Fracture at Baseline)
| Patients with: | % of Patients | Reduction (%) in Fracture Incidence | |
|---|---|---|---|
| Alendronate Sodium (n = 1,545) | Placebo (n = 1,521) | ||
| ≥ 1 painful fracture | 12.9 | 16.2 | 22** |
| ≥ 1 vertebral fracture†† | 2.5 | 4.8 | 48*** |
| ≥ 1 painful vertebral fracture | 1.0 | 1.6 | 41††† |
| Hip fracture | 1.0 | 1.4 | 29††† |
| Wrist (forearm) fracture | 3.9 | 3.8 | none |
† Baseline femoral neck BMD at least 2 SD below the mean for young adult women
†† Number evaluable for vertebral fracture: alendronate sodium, n = 1,426; placebo, n = 1,428
††† Not significant
** p = 0.01
*** p < 0.001
In all patients (including those without osteoporosis), the reductions in fracture incidence were: ≥ 1 painful fracture, 14% (p = 0.072); ≥ 1 vertebral fracture, 44% (p = 0.001); > 1 painful vertebral fracture, 34% (p = 0.178), and hip fracture, 21% (p = 0.44). The incidence of wrist fracture in all patients was alendronate sodium, 3.7%; placebo, 3.2% (not significant).
Combined FIT Studies
The reductions in fracture incidence for the combined Three- and Four-Year Studies of FIT are shown in the following table.
Table 9 - Effect of Alendronate Sodium on Fracture Incidence in the Combined (Three- and Four-Year) Studies of FIT
| Patients with: | Reduction (%) in Fracture Incidence Alendronate Sodium vs. Placebo | |
Osteoporotic Patients† (n = 5,093) | All Patients (n = 6,459) | |
Vertebral fractures (diagnosed by X-ray)†† > 1 vertebral fracture > 2 vertebral fractures | 48*** | 46*** |
| 88*** | 84*** | |
Painful (clinical) fractures Any painful fracture Painful vertebral fracture Hip fracture Wrist (forearm) fracture††† | ||
| 24*** | 18** | |
| 50*** | 47*** | |
| 40* | 36‡‡ | |
| 18‡ | 6‡ | |
† Includes all patients in the Three-Year Study plus osteoporotic patients (baseline femoral neck BMD at least 2 SD below the mean for young adult women) in the Four-Year Study
†† Number evaluable for vertebral fractures: osteoporotic patients, n = 4,804; all patients, n = 6,084
††† Significant reduction in wrist fracture incidence was observed in the Three-Year Study (patients with baseline vertebral fracture) but not in the Four-Year Study (patients without baseline vertebral fracture)
‡ Not significant
‡‡ p = 0.059
* p<0.05
**p<0.01
***p<0.001
Consistency of Fracture Results
The reductions in the incidence of vertebral fractures (alendronate sodium vs. placebo) in the Three- and Four-Year Studies of FIT were consistent with that in the combined U.S. and Multinational (U.S./Mult) treatment studies (see above), in which 80% of the women did not have a vertebral fracture at baseline. During these studies, treatment with alendronate sodium reduced the proportion of women experiencing at least one new vertebral fracture by approximately 50% (Three-Year FIT: 47% reduction, p < 0.001; Four-Year FIT: 44% reduction, p = 0.001; U.S./Mult: 48% reduction, p = 0.034). In addition, alendronate sodium reduced the proportion of women experiencing multiple (two or more) new vertebral fractures by approximately 90% in the U.S./Mult. and Three-Year FIT Studies (p < 0.001). Thus, alendronate sodium reduces the incidence of vertebral fractures whether or not patients have experienced a previous vertebral fracture.
Overall, these results demonstrate the consistent efficacy of alendronate sodium to reduce the incidence of fractures, including those of the spine and hip, which are the sites of osteoporotic fracture associated with the greatest morbidity.
Bone Histology
Bone histology in 270 postmenopausal patients with osteoporosis treated with alendronate sodium at doses ranging from 1 to 20 mg/day for one, two or three years revealed normal mineralization and structure, as well as the expected decrease in bone turnover relative to placebo. These data, together with the normal bone histology and increased bone strength observed in rats and baboons exposed to long-term alendronate treatment, indicate that bone formed during therapy with alendronate sodium is of normal quality.
Treatment of osteoporosis in men
Table 10 - Summary of Patient Demographics for Clinical Trials (treatment of osteoporosis in men)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| PN096 | Double-blind randomized placebo-controlled, multicenter, multinational study | PBO FOS 10mg Calcium (500 mg) and Vitamin D (400 IU) supplement daily ORAL 2 years | 241 | 31-87 | Men |
| PN165 | Double-blind, placebo-controlled, multicenter study | PBO FOS 70mg (once weekly) ORAL 1 year | 167 | 38-91 | Men |
PBO = Placebo; FOS = alendronate (mg/day)
The efficacy of alendronate sodium in men with osteoporosis was demonstrated in two clinical studies.
A two-year, double-blind, placebo-controlled, multicenter study of alendronate sodium 10 mg once daily enrolled a total of 241 men between the ages of 31 and 87 (mean, 63). At two years, the mean increases relative to placebo in BMD in men receiving alendronate sodium 10 mg/day were: lumbar spine, 5.3%; femoral neck, 2.6%; trochanter, 3.1%; and total body, 1.6% (all p ≤ 0.001).
Consistent with much larger studies in postmenopausal women, in these men, alendronate sodium 10 mg/day reduced the incidence of new vertebral fracture (assessed by quantitative radiography) relative to placebo (0.8% vs. 7.1%, respectively; p = 0.017) and, correspondingly, also reduced height loss (-0.6 vs. -2.4 mm; respectively; p = 0.022).
A one-year, double-blind, placebo-controlled, multicenter study of alendronate sodium 70 mg once weekly enrolled a total of 167 men between the ages of 38 and 91 (mean, 66). At one year, the mean increases in BMD relative to placebo were significant at the following sites: lumbar spine, 2.8% (p ≤ 0.001); femoral neck, 1.9% (p = 0.007); trochanter, 2.0% (p ≤ 0.001); and total body, 1.2% (p = 0.018). These increases in BMD were similar to those seen at one year in the 10 mg once-daily study. The trial was not powered to detect a clinical difference in fracture incidence between the alendronate and placebo groups. However, other studies with daily or weekly alendronate administrations have consistently demonstrated a relationship between increases in BMD (a surrogate marker) and decreases in fracture rate (clinical endpoint).
Therefore, it can be assumed that this relationship is also true in men given a weekly administration of alendronate.
In both studies alendronate sodium was effective regardless of age, gonadal function or baseline BMD (femoral neck and lumbar spine).
14.2 Comparative Bioavailability Studies
A single center, blind, randomized, two-period, 2 sequence, crossover, single dose , oral bioequivalence study of NB-ALENDRONATE 70 mg Tablet ( NB Pharma Inc.) with FOSAMAX®, 70 mg tablet (Merck Frosst Canada & Co.)was performed in healthy adult male volunteers under fasting conditions. Bioavailability data estimated from the amount of drug excreted in urine from the 75 subjects who were included in the statistical analysis are presented below:
Summary Table of Comparative Bioavailability Data
Alendronate
(1 x 70 mg)
Geometric Mean
Arithmetic Mean (CV %)
Parameter
Test1
Reference2
% Ratio of geometric means
90% Confidence Interval
Ae0-t4
(mcg)
165.12
212.81(64.82)
185.56
238.28 (66.78)
88.98
82.36 - 97.03
Rmax5
(mcg/h)
51.84
70.71 (68.76)
59.94
82.96 (71.86)
86.49
79.53 - 95.02
Tmax
(h)3
1.11
(50.49)
1.12
(54.14)
1 NB-ALENDRONATE (alendronate sodium Talets), tablets, 70 mg (NB Pharma Inc.)
2FOSAMAX® (alendronate sodium) tablets, 70 mg (Merck Frosst Canada & Co.)
3 Expressed as the arithmetic mean (CV%) only
4 Ae: Total amount of drug excreted in urine
5 Rmax: Maximum rate of urinary excretion
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
The oral LD50 values of alendronate in female rats and mice were 552 mg/kg (3,256 mg/m2) and 966 mg/kg (2,898 mg/m2) (equivalent to human oral doses* of 27,600 and 48,300 mg), respectively. In males, these values were slightly higher, 626 and 1,280 mg/kg, respectively. There was no lethality in dogs at oral doses up to 200 mg/kg (4,000 mg/m2) (equivalent to a human oral dose* of 10,000 mg).
Chronic Toxicity
Alendronate-related changes in the repeated dose-toxicity studies of up to one year in rats and three years in dogs consisted of retention of primary spongiosa of bone in areas of endochondral bone formation, sustained reduction of alkaline phosphatase activities, and transient reduction in serum calcium and phosphate concentrations. These are related to the desired pharmacologic activity of alendronate. The species most sensitive to nephrotoxicity (dogs) required a dose* equivalent to at least 100 mg in humans to manifest nephrotoxicity.
Rats also showed evidence of this effect at higher doses. Gastrointestinal toxicity was seen in rodents only. This appears to be due to a direct effect on the mucosa and occurred only at doses greater than 2.5 mg/kg/day.
Carcinogenicity: No evidence of carcinogenic effect was observed in a 105-week study in rats receiving oral doses up to 3.75 mg/kg/day and in a 92-week study in mice receiving oral doses up to 10 mg/kg/day.
Harderian gland (a retroorbital gland not present in humans) adenomas were increased in high-dose female mice (p = 0.003) in a 92-week carcinogenicity study at doses of alendronate of 1, 3 and 10 mg/kg/day (males) or 1, 2 and 5 mg/kg/day (females). These doses are equivalent to 0.5 to 4 times the 10 mg human dose based on surface area, mg/m2.
Parafollicular cell (thyroid) adenomas were increased in high-dose male rats (p = 0.003) in a 2- year carcinogenicity study at doses of 1 and 3.75 mg/kg body weight. These doses are equivalent to 1 and 3 times the 10 mg human dose based on surface area.
Genotoxicity: Alendronate was not genotoxic in the in vitro microbial mutagenesis assay with and without metabolic activation. Similarly, no evidence of mutagenicity was observed in an in vitro mammalian cell mutagenesis assay, an in vitro alkaline elution assay in rat hepatocytes, and an in vivo chromosomal aberration assay in mice at IV doses up to 25 mg/kg/day (75 mg/m2). In an in vitro chromosomal aberration assay in Chinese hamster ovary cells, however, alendronate was weakly positive at concentrations ≥ 5 mM in the presence of cytotoxicity. This is of no relevance to safety in humans since similar concentrations are not achievable in vivo at therapeutic doses. Furthermore, clear negative results in four of five genotoxicity studies, including the most relevant studies for human carcinogenic potential (the in vivo chromosomal aberration assay and the microbial mutagenesis assay), and negative carcinogenicity studies in rats and mice lead to the conclusion that there is no evidence of genotoxic or carcinogenic risks from alendronate in humans.
Reproductive and Developmental Toxicology: Alendronate had no effect on fertility or reproductive performance (male or female) in rats at oral doses up to 5 mg/kg/day. The only drug-related effect seen in these studies was difficulty in parturition in rats, which is directly related to pharmacologically mediated hypocalcemia. This effect can be prevented in rats by calcium supplementation. Furthermore, a clear no-effect level of 1.25 mg/kg/day was established.
In developmental toxicity studies, there were no adverse effects at doses up to 25 mg/kg/day in rats and 35 mg/kg/day in rabbits.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. FOSAMAX® (tablet, 70 mg), submission control 273860, Product Monograph, Organon Canada Inc. (August 3, 2023).