


Product Monograph - NB-Amlodipine
1 INDICATIONS
NB-Amlodipine (amlodipine besylate tablets) is indicated for:
- Hypertension
NB-Amlodipine is indicated in the treatment of mild to moderate essential hypertension.
Combination of amlodipine besylate with a diuretic, a beta-blocking agent, or an angiotensin converting enzyme inhibitor has been found to be compatible and showed additive antihypertensive effect.
- Chronic Stable Angina
NB-Amlodipine is indicated for the management of chronic stable angina (effort-associated angina) in patients who remain symptomatic despite adequate doses of beta-blockers and/or organic nitrates or who cannot tolerate those agents.
NB-Amlodipine may be tried in combination with beta-blockers in chronic stable angina in patients with normal ventricular function. When such concomitant therapy is introduced, care must be taken to monitor blood pressure closely since hypotension can occur from the combined effects of the drugs.
1.1 Pediatrics
Pediatrics (6-17 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of amlodipine besylate in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 4.2 Recommended Dose and Dosage Adjustment, 7.1.3 Pediatrics, 10.2 Pharmacodynamics).
The use of NB-Amlodipine in children less than 6 years of age is not recommended (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics (>65 years of age): Evidence from clinical studies suggests that use in the geriatric population is associated with differences in safety and exposure (see 7.1.4 Geriatrics, 10.3 Pharmacokinetics, 4.2 Recommended Dose and Dosage Adjustment).
2 CONTRAINDICATIONS
NB-Amlodipine is contraindicated in patients:
- who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- who are hypersensitive to other dihydropyridines. Amlodipine besylate is a dihydropyridine calcium channel blocker.
- who are breast-feeding (see 7.1.2 Breast-feeding).
- with severe hypotension (less than 90 mmHg systolic).
- with shock including cardiogenic shock.
- with obstruction of the outflow tract of the left ventricle (e.g. high grade aortic stenosis).
- with haemodynamically unstable heart failure after acute myocardial infarction.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Dosage should be individualized depending on patient's tolerance and responsiveness.
4.2 Recommended Dose and Dosage Adjustment
- For both hypertension and angina, the recommended initial dose of NB-Amlodipine is 5 mg once daily. If necessary, dose can be increased after 1-2 weeks to a maximum dose of 10 mg once daily.
- Use in the Elderly or in Patients with Impaired Renal Function: The recommended initial dose in patients over 65 years of age or patients with impaired renal function is 5 mg once daily. If required, increasing in the dose should be done gradually and with caution (see 7.1.4 Geriatrics).
- Use in Patients with Impaired Hepatic Function: Dosage requirements have not been established in patients with impaired hepatic function. When NB-Amlodipine is used in these patients, the dosage should be carefully and gradually adjusted depending on patients tolerance and response. A lower starting dose of 2.5 mg once daily should be considered (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
- Use in Pediatric Patients (6 – 17 years of age): The effective antihypertensive oral dose in pediatric patients ages 6-17 years is 2.5 mg to 5 mg once daily. Doses in excess of 5 mg daily have not been studied; dose should be determined based upon the medical need of the patients (see 7.1.3 Pediatrics, 10.2 Pharmacodynamics).
4.4 Administration
NB-Amlodipine can be administered once daily, at any time of the day, with or without food.
4.5 Missed Dose
The patient should be advised that if they miss a dose, it should be taken immediately unless it has been more than 12 hours since the missed dose. In such an event, the patient should wait for the next scheduled dose and continue on the regular schedule. A double dose should not be taken to make up for a missed dose.
5 OVERDOSAGE
Symptoms: Overdosage can cause excessive peripheral vasodilation with marked and probably prolonged hypotension and possibly a reflex tachycardia. In humans, experience with overdosage of amlodipine besylate is limited. In healthy volunteers, the use of charcoal up to 2 hours after administration of amlodipine 10 mg has been shown to reduce the absorption rate of amlodipine. A patient who took 70 mg of amlodipine with benzodiazepine developed shock which was refractory to treatment and died. In a 19 month old child who ingested 30 mg of amlodipine (about 2 mg/kg) there was no evidence of hypotension but tachycardia (180 bpm) was observed. Ipecac was administered 3.5 hrs after ingestion and on subsequent observation (overnight) no sequelae were noted.
Treatment: Clinically significant hypotension due to overdosage requires active cardiovascular support including frequent monitoring of cardiac and respiratory function, elevation of extremities, and attention to circulating fluid volume and urine output. A vasoconstrictor (such as norepinephrine) may be helpful in restoring vascular tone and blood pressure, provided that there is no contraindication to its use. As amlodipine besylate is highly protein bound, hemodialysis is not likely to be of benefit. Intravenous calcium gluconate may be beneficial in reversing the effects of calcium channel blockade. Clearance of amlodipine is prolonged in elderly patients and in patients with impaired liver function.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING Table 1 – Dosage Forms, Strengths, Composition and Packaging
Route of
Administration
Dosage Form / Strength /
Composition Non-medicinal Ingredients
Oral Tablet 2.5 mg, 5 mg and
10 mg
Calcium hydrogen phosphate anhydrous, magnesium stearate, microcrystalline cellulose, and sodium starch glycolate
NB-Amlodipine is available as white or almost white, octagonal tablets containing amlodipine besylate equivalent to 5 mg and 10 mg amlodipine per tablet. The respective tablet strengths are debossed on one tablet face as "AML 5" and "AML 10". The 5 mg and 10 mg tablets are scored.
NB-Amlodipine is also available as white or almost white, oblong, beveled tablets containing amlodipine besylate equivalent to 2.5 mg amlodipine per tablet. The respective tablet strength is coded on one tablet face as “2,5”.
NB-Amlodipine 2.5 mg is marketed in white plastic (high density polyethylene) bottles of 100 and 500 tablets.
NB-Amlodipine 5 mg and 10 mg are marketed in white plastic (high density polyethylene) bottles of 100 and 500 tablets. Approved in bottles of 1000 tablets.
7 WARNINGS AND PRECAUTIONS
General
Beta-blocker withdrawal: NB-Amlodipine gives no protection against the dangers of abrupt beta-blocker withdrawal and such withdrawal should be done by the gradual reduction of the dose of beta-blocker.
Concomitant Use with Strong Inhibitors of CYP 3A4: Use of NB-Amlodipine with drugs that result in strong inhibition of CYP 3A4, such as ketoconazole, clarithromycin, ritonavir, may lead to increased plasma levels of amlodipine and associated serious events (see 9.4 Drug-Drug Interactions). Such concomitant use should be avoided.
An observational study demonstrated an increased risk of hospitalization with acute kidney injury when amlodipine was used concomitantly with clarithromycin in elderly patients (>65 years of age) compared to when it was used concomitantly with azithromycin, [odds ratio amlodipine: 1.61 (95% C.I. 1.29-2.02)].
Cardiovascular
Increased Angina and/or Myocardial Infarction: Rarely, patients, particularly those with severe obstructive coronary artery disease, have developed documented increased frequency, duration and/or severity of angina or acute myocardial infarction on starting calcium channel blocker therapy or at the time of dosage increase. The mechanism of this effect has not been elucidated.
Use in Patients with Congestive Heart Failure: Although calcium channel blockers should only be used with caution in patients with heart failure, it has been observed that amlodipine besylate had no overall deleterious effect on survival and cardiovascular morbidity in both short-term and long-term clinical trials in these patients. While a significant proportion of the patients in these studies had a history of ischemic heart disease, angina or hypertension, the studies were not designed to evaluate the treatment of angina or hypertension in patients with concomitant heart failure.
Of note, in an amlodipine long-term, placebo-controlled study in patients with severe heart failure (NYHA class III and IV), the reported incidence of pulmonary edema was higher in the amlodipine treated group than in the placebo group. Calcium channel blockers, including amlodipine, may increase the risk of future cardiovascular events and mortality.
Hypotension: NB-Amlodipine may occasionally precipitate symptomatic hypotension. Careful monitoring of blood pressure is recommended, especially in patients with a history of cerebrovascular insufficiency, and those taking medications known to lower blood pressure.
Peripheral Edema: Mild to moderate peripheral edema was the most common adverse event in the clinical trials (see 8.2 Clinical Trial Adverse Reactions). The incidence of peripheral edema was dose-dependent and ranged in frequency from 3.0 to 10.8% in 5 mg to 10 mg dose range. Care should be taken to differentiate this peripheral edema from the effects of increasing left ventricular dysfunction.
Hepatic/Biliary/Pancreatic
Use in Patients with Impaired Hepatic Function: There are no adequate studies in patients with liver dysfunction and dosage recommendations have not been established. In a small number of patients with mild to moderate hepatic impairment given a single dose of 5 mg, amlodipine half-life has been prolonged (see 10.3 Pharmacokinetics). NB-Amlodipine should, therefore, be administered with caution in these patients and careful monitoring should be performed. A lower starting dose may be required (see 4.2 Recommended Dose and Dosage Adjustment).
Patients with severe hepatic impairment or hepatic failure: Because amlodipine besylate is extensively metabolized by the liver and the plasma elimination half-life (t 1/2) is 56 hours in patients with impaired hepatic function, it should be administered cautiously and at reduced dosages in patients with severely impaired hepatic function (see 4.2 Recommended Dose and Dosage Adjustment). Slow dose titration and careful monitoring are required in patients with severe hepatic impairment.
Reproductive Health: Female and Male Potential
Fertility
Reversible biochemical changes in the head of spermatozoa have been reported in some patients treated by calcium channel blockers. Reversible adverse effects on male rat fertility have also been suggested (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1 Special Populations
7.1.1 Pregnant Women
There is no clinical experience with amlodipine besylate in pregnant women. NB-Amlodipine should be used during pregnancy only if the potential benefit outweighs the potential risk to the mother and fetus.
Although amlodipine was not teratogenic in the rat and rabbit, some dihydropyridine compounds have been found to be teratogenic in animals. In rats, amlodipine has been shown to prolong both the gestation period and the duration of labour. There was no effect on the fertility of rats treated with amlodipine.
7.1.2 Breast-feeding
In human study, the mean maternal daily dose of amlodipine was 6.0 mg and the median plasma and milk concentrations of amlodipine were 15.5 and 11.5 ng/mL, respectively, with a median milk/plasma concentration ratio of 0.85. Since amlodipine safety in newborns has not been established, NB-Amlodipine should not be given to nursing mothers. A decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother (see 2 CONTRAINDICATIONS).
7.1.3 Pediatrics
Pediatrics (6-17 years of age): In pediatric patients aged 6-17 years, safety and efficacy studies beyond 8 weeks of duration, for the treatment of hypertension, have not been conducted. The prescription in this population should be based on a careful risk/benefit assessment of the limited available information. The risk/benefit assessment should be conducted by a qualified health professional.
The use of amlodipine besylate is not recommended in patients less than 6 years of age since safety and efficacy have not been established in that population.
7.1.4 Geriatrics
Geriatrics (>65 years of age): In elderly patients, clearance of amlodipine is decreased with a resulting increase in AUC (see 10.3 Pharmacokinetics). In clinical trials the incidence of adverse reactions in elderly patients was approximately 6% higher than that of younger population (<65 years). Adverse reactions include edema, muscle cramps and dizziness. NB-Amlodipine should be used cautiously in elderly patients. Dosage adjustment is advisable (see 4.2 Recommended Dose and Dosage Adjustment).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most serious adverse reaction associated with the amlodipine besylate is hypotension especially under gross overdose (see 5 OVERDOSAGE). The most commonly reported adverse reactions in placebo controlled trials, that may be associated with amlodipine therapy were oedema (9.4%), headaches (8.0%), fatigue (4.5%), dizziness (3.8%) and nausea (3.4%) (see 8.2 Clinical Trial Adverse Reactions).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use. Amlodipine besylate has been administered to 1,714 patients (805 hypertensive and 909 angina patients) in controlled clinical trials (vs placebo alone and with active comparative agents). Most adverse reactions reported during therapy were of mild to moderate severity.
HYPERTENSION
In the 805 hypertensive patients treated with amlodipine besylate in controlled clinical trials, adverse effects were reported in 29.9% of patients and required discontinuation of therapy due to side effects in 1.9% of patients. The most common adverse reactions in controlled clinical trials were: oedema (8.9%), and headache (8.3%).
The following adverse reactions were reported with an incidence of >0.5% in the controlled clinical trials program (n=805):
Autonomic Nervous System: flushing (3.1%), hyperhidrosis (0.9%), dry mouth (0.7%). Cardiovascular: oedema (8.9%), palpitations (2.0%), tachycardia (0.7%), postural dizziness (0.5%).
Central and Peripheral Nervous System: headaches (8.3%), dizziness (3.0%), paraesthesia (0.5%).
Gastrointestinal: nausea (2.4%), abdominal pain (1.1%), dyspepsia (0.6%), constipation (0.5%). General: fatigue (4.1%), pain (0.5%).
Musculoskeletal: muscle cramps (0.5%).
Psychiatric: somnolence (1.4%).
Skin and Appendages: pruritus (0.7%).
ANGINA
In the controlled clinical trials in 909 angina patients treated with amlodipine besylate, adverse effects were reported in 30.5% of patients and required discontinuation of therapy due to side effects in 0.6% of patients. The most common adverse reactions reported in controlled clinical trials were: oedema (9.9%) and headache (7.8%).
The following adverse reactions occurred at an incidence of >0.5% in the controlled clinical trials program (n=909):
Autonomic Nervous System: flushing (1.9%).
Cardiovascular: oedema (9.9%), palpitations (2.0%), postural dizziness (0.6%). Central and Peripheral Nervous System: headaches (7.8%), dizziness (4.5%), paraesthesia (1.0%), hypoaesthesia (0.9%).
Gastrointestinal: nausea (4.2%), abdominal pain (2.2%), dyspepsia (1.4%), diarrhea (1.1%), flatulence (1.0%), constipation (0.9%).
General: fatigue (4.8%), pain (1.0%), asthenia (1.0%).
Musculoskeletal: muscle cramps (1.0%).
Psychiatric: somnolence (1.2%), insomnia (0.9%), nervousness (0.7%).
Respiratory System: dyspnoea (1.1%).
Skin and Appendages: rash (1.0%), pruritus (0.8%).
Special Senses: visual impairment (1.3%), tinnitus (0.6%).
8.3 Less Common Clinical Trial Adverse Reactions
Amlodipine besylate has been evaluated for safety in about 11,000 patients with hypertension and angina. The following events occurred in <1% but >0.1% of patients in comparative clinical trials (double-blind comparative vs placebo or active agents; n = 2,615) or under conditions of open trials or marketing experience where a causal relationship is uncertain.
Autonomic Nervous System: dry mouth, hyperhidrosis.
Cardiovascular: arrhythmia (including ventricular tachycardia and atrial fibrillation), bradycardia, myocardial infarction, hypotension, peripheral ischemia, syncope, tachycardia, postural dizziness, postural hypotension, vasculitis, chest pain.
Central and Peripheral Nervous System: hypoaesthesia/paraesthesia, neuropathy peripheral, tremor, vertigo.
Gastrointestinal: anorexia, constipation, dysphagia, vomiting, gingival hyperplasia, change in bowel habits, dyspepsia.
General: allergic reaction, asthenia+, back pain, pain, hot flushes, malaise, rigors and weight increased/weight decreased.
Hemopoietic: leukopenia, purpura, thrombocytopenia.
Metabolic and Nutritional: hyperglycaemia, thirst.
Musculoskeletal System: arthralgia, arthrosis, myalgia, muscle cramps. Psychiatric: sexual dysfunction (male+ and female), insomnia, nervousness, depression, abnormal dreams, anxiety, depersonalization, mood altered.
Reproductive system and breast disorders: gynecomastia, erectile dysfunction. Respiratory System: dyspnoea, epistaxis.
Skin and Appendages: pruritus, rash erythematous, rash maculopapular, erythema multiforme. Special Senses: conjunctivitis, diplopia, eye pain, visual impairment, tinnitus. Urinary System: pollakiuria, micturition disorder, nocturia.
+These events occurred in less than 1% in placebo controlled trials, but the incidence of these side effects was between 1% and 2% in all multiple dose studies.
The following events occurred in <0.1% of patients: cardiac failure, skin discoloration*, urticaria*, skin dryness, Stevens-Johnson syndrome, alopecia*, twitching, ataxia, hypertonia*, migraine, apathy, amnesia, gastritis*, pancreatitis*, increased appetite, coughing*, rhinitis*, parosmia, taste perversion*, and xerophthalmia.
*These events were observed in marketing experience as well.
Isolated cases of angioedema have been reported. Angioedema may be accompanied by breathing difficulty.
8.5 Post-Market Adverse Reactions
In postmarketing experience, jaundice and hepatic enzyme elevations (mostly consistent with cholestasis or hepatitis) in some cases severe enough to require hospitalization have been reported in association with use of amlodipine.
Postmarketing reporting has also revealed cases of extrapyramidal disorders induced by amlodipine.
9 DRUG INTERACTIONS
9.1 Serious Drug Interaction
Serious Drug Interactions
Concomitant treatment with strong inhibitors of CYP 3A4 (see 9.4 Drug-Drug
Interactions)
- Concomitant treatment with clarithromycin (see 9.4 Drug-Drug Interactions)
9.2 Drug Interactions Overview
As with all drugs, care should be exercised when treating patients with multiple medications. Dihydropyridine calcium channel blockers undergo biotransformation by the cytochrome P450 system, mainly via CYP 3A4 isoenzyme. Coadministration of amlodipine with other drugs which follow the same route of biotransformation may result in altered bioavailability of amlodipine or these drugs. Dosages of similarly metabolized drugs, particularly those of low therapeutic ratio, and especially in patients with renal and/or hepatic impairment, may require adjustment when starting or stopping concomitantly administered amlodipine to maintain optimum therapeutic blood levels.
9.4 Drug-Drug Interactions
Table 2- Established or Potential Drug-Drug Interactions
Proper name Source of
Evidence Effect Clinical comment
Atorvastatin CT In healthy volunteers, co-
administration of multiple 10 mg doses of amlodipine with 80 mg of atorvastatin resulted in no clinical significant change in the AUC (average of 18% increase) or Cmax or Tmax of atorvastatin.
Close monitoring is required.
Beta-blockers T Blood pressure lowering
effect of beta-blockers may be increased by amlodipine.
When beta-adrenergic receptor blocking drugs are administered concomitantly with amlodipine besylate, Proper name Source of
Evidence Effect Clinical comment patients should be carefully monitored since blood pressure lowering effect of beta-blockers may be augmented by amlodipine's reduction in peripheral vascular resistance.
Clarithromycin CT In elderly patients (>65
years of age), concomitant use of amlodipine with clarithromycin was
associated with increased risk of hospitalization with acute kidney injury.
Avoid concomitant use.
Cyclosporin CT No drug interaction studies
have been conducted with cyclosporin and amlodipine in healthy volunteers or other populations with the exception of renal
transplant patients. A prospective study in
hypertensive renal
transplant patients (N=11) showed on an average of 40% increase in trough cyclosporin levels when concomitantly treated with amlodipine.
Consideration should be given for monitoring cyclosporin levels in renal transplant patients on amlodipine.
Dantrolene T In animals, lethal ventricular
fibrillation and
cardiovascular collapse are observed in association with hyperkalemia after administration of verapamil and intravenous
dantrolene.
Due to risk of
hyperkalemia, it is recommended that the co-administration of calcium channel blockers such as amlodipine be avoided in patients susceptible to malignant hyperthermia and in the management of malignant hyperthermia. Drugs known to be
biotransformed via
P450
T Amlodipine has a low (rate
of first-pass) hepatic clearance and consequent
Proper name Source of
Evidence Effect Clinical comment
(benzodiazepines, flecainide,
imipramine,
propafenone,
theophylline)
high bioavailability, and thus, may be expected to have a low potential for clinically relevant effects associated with elevation of amlodipine plasma levels when used concomitantly with drugs that compete for or inhibit the cytochrome P450 system.
Drugs known to be inducers of the cytochrome P450 system include: phenobarbital, phenytoin, rifampin
T There is no data available
regarding the effect of CYP3A4 inducers on
amlodipine. The
concomitant use of CYP3A4 inducers may give a lower plasma concentration of amlodipine which in turn can result in decreased blood pressure lowering effects.
Amlodipine should be used with caution together with CYP3A4 inducers and dose adjustment may be necessary to maintain efficacy. Hence, monitoring of therapy is required.
Drugs known to be inhibitors of the cytochrome P450 system (diltiazem, azole antifungals, erythromycin,
quinidine,
terfenadine and warfarin)
CT
T
Co-administration of a 180 mg daily dose of diltiazem with 5 mg
amlodipine in elderly hypertensive patients (69 to 87 years of age) resulted in a 57% increase in
amlodipine systemic
exposure. Erythromycin co-administration in healthy volunteers (18 to 43 years of age) increased the systemic exposure of amlodipine by 22%.
These pharmacokinetic changes may be more pronounced in the elderly. Close monitoring and dose adjustment may be required.
Mechanistic Target of Rapamycin
(mTOR)
Inhibitors (sirolimus, temsirolimus, and everolimus)
CT
T
mTOR inhibitors are CYP3A substrates. Amlodipine is a weak CYP3A inhibitor. With concomitant use of mTOR inhibitors, amlodipine may increase exposure of mTOR inhibitors.
Proper name Source of
Evidence Effect Clinical comment
Sildenafil CT A single 100 mg dose of
sildenafil (Viagra) in
subjects with essential hypertension had no effect on AUC or Cmax of
amlodipine. When
sildenafil (100 mg) was co-administered with
amlodipine, 5 mg or 10 mg in hypertensive patients, the mean additional reduction of supine blood pressure was 8 mmHg systolic and 7 mmHg diastolic.
Simvastatin CT Co-administration of
multiple doses of 10 mg of amlodipine
with 80 mg simvastatin resulted in a 77% increase in exposure to simvastatin compared to simvastatin alone.
Limit the dose of
simvastatin in patients on amlodipine to 20 mg daily.
Strong inhibitors of
CYP3A4 (e.g.,
ketoconazole,
itraconazole,
ritonavir,
clarithromycin)
T May significantly increase
the plasma concentrations of amlodipine to a greater extent than diltiazem.
Amlodipine should be used with caution together with CYP3A4 inhibitors and monitoring of therapy is required.
Appropriate dosage adjustment of amlodipine may be necessary when used with CYP3A4 inhibitors.
Patients should be advised to seek medical attention if they experience edema or swelling of the lower extremities; sudden, unexplained weight gain; difficulty breathing; chest pain or tightness; or hypotension as indicated Proper name Source of
Evidence Effect Clinical comment by dizziness, fainting, or orthostasis.
Avoid concomitant administration of amlodipine with strong CYP3A4 inhibitors.
Tacrolimus C There is a risk of increased
tacrolimus blood levels when co-administered with amlodipine.
In order to avoid toxicity of tacrolimus, administration of amlodipine in a patient treated with tacrolimus requires monitoring of tacrolimus blood levels and dose adjustments of tacrolimus when appropriate.
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interaction with Grapefruit Juice: Published data indicate that through inhibition of the cytochrome P450 system, grapefruit juice can increase plasma levels and augment pharmacodynamic effects of some dihydropyridine calcium channel blockers. Co-administration of 240 mL of grapefruit juice with a single oral dose of amlodipine 10 mg in 20 healthy volunteers had no significant effect on the pharmacokinetics of amlodipine. The study did not allow examination of the effect of genetic polymorphism in CYP3A4, the primary enzyme responsible for metabolism of amlodipine; therefore, administration of amlodipine with grapefruit or grapefruit juice is not recommended as bioavailability may be increased in some patients resulting in increased blood pressure lowering effects. Hence, monitoring of therapy is required.
Following oral administration of 10 mg amlodipine to 20 male volunteers, pharmacokinetics of amlodipine, geometric mean Cmax of amlodipine was 6.2 ng/mL when the drug was administered with grapefruit juice and 5.8 ng/mL when administered with water. Mean Tmax of amlodipine was 7.6 hours with grapefruit juice and 7.9 hours with water. Geometric mean AUC0-∞was 315 ng/hr/mL with grapefruit juice and 293 ng/hr/mL with water. Geometric mean bioavailability of amlodipine was 85% when administered with grapefruit juice and 81% when administered with water.
9.6 Drug-Herb Interactions
St-John's Wort is an inducer of CYP3A4. The concomitant use of CYP3A4 inducers may give a lower plasma concentration of amlodipine which in turn can result in decreased blood pressure lowering effects. Amlodipine should be used with caution together with CYP3A4 inducers and dose adjustment may be necessary to maintain efficacy. Hence, monitoring of therapy is required.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Amlodipine besylate is a calcium ion influx inhibitor (calcium entry blocker or calcium ion antagonist). Amlodipine is a member of the dihydropyridine class of calcium antagonists.
The therapeutic effect of this group of drugs is believed to be related to their specific cellular action of selectively inhibiting transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. The contractile processes of these tissues are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Serum calcium concentration is not affected by amlodipine. Within the physiologic pH range, amlodipine is an ionized compound and its kinetic interaction with the calcium channel receptor is characterized by the gradual association and dissociation with the receptor binding site. Experimental data suggest that amlodipine binds to both dihydropyridine and nondihydropyridine binding sites.
A. Hypertension: The mechanism by which amlodipine reduces arterial blood pressure involves direct peripheral arterial vasodilation and reduction in peripheral vascular resistance.
B. Angina: The precise mechanism by which amlodipine relieves angina has not been fully delineated. Amlodipine is a dilator of peripheral arteries and arterioles which reduces the total peripheral resistance and, therefore, reduces the workload of the heart (afterload). The unloading of the heart is thought to decrease ischemia and relieve effort angina by reducing myocardial energy oxygen consumption and oxygen requirements.
10.2 Pharmacodynamics
Hemodynamics: Following administration of recommended doses to patients with hypertension, amlodipine produces vasodilation resulting in a reduction of supine and standing blood pressures. These decreases in blood pressure are not accompanied by any significant change in heart rate or plasma catecholamine levels with chronic dosing. With chronic once daily oral administration (5 mg and 10 mg once daily), antihypertensive effectiveness is maintained throughout the 24 hours dose interval with minimal peak to trough differences in plasma concentration. Since the vasodilation induced by amlodipine is gradual in onset, acute hypotension has rarely been reported after oral administration of amlodipine. In normotensive patients with angina amlodipine has not been associated with any clinically significant reductions in blood pressure or changes in heart rate.
Negative inotropic effects have not been observed when amlodipine was administered at the recommended doses to man, but has been demonstrated in animal models. Hemodynamic measurements of cardiac function at rest and during exercise (or pacing) in angina patients with normal ventricular function have generally demonstrated a small increase in cardiac index without significant influence on dP/dt or on left ventricular end diastolic pressure or volume.
In hypertensive patients with normal renal function, therapeutic doses of amlodipine resulted in a decrease in renal vascular resistance and an increase in glomerular filtration rate and effective renal plasma flow without change in filtration fraction.
Electrophysiologic Effects: Amlodipine does not change sinoatrial nodal function or atrioventricular conduction in intact animals, or man. In patients with chronic stable angina, intravenous administration of 10 mg of amlodipine and a further 10 mg of amlodipine after a 30 min. interval produced peripheral vasodilation and afterload reduction, but did not significantly alter A-H and H-V conduction and sinus node recovery time after pacing. Similar results were obtained in patients receiving amlodipine and concomitant beta-blockers. In clinical studies in which amlodipine was administered in combination with beta-blockers to patients with either hypertension or angina, no adverse effects on electrocardiographic parameters were observed. In clinical trials with angina patients, amlodipine as monotherapy did not alter electrocardiographic intervals.
Effects in Hypertension
Pediatric Patients
Two hundred sixty-eight hypertensive patients aged 6 to 17 years were randomized first to amlodipine besylate 2.5 mg or 5 mg once daily for 4 weeks and then randomized again to the same dose or to placebo for another 4 weeks. Patients receiving 5 mg at the end of 8 weeks had lower blood pressure than those secondarily randomized to placebo. The magnitude of the treatment effect is difficult to interpret, but it is probably less than 5 mmHg systolic on the 5 mg dose. Adverse events were similar to those seen in adults.
Pediatric safety and efficacy studies beyond 8 weeks of duration have not been conducted. In addition, the long-term effect of amlodipine on growth and development, myocardial growth and vascular smooth muscles has not been studied.
10.3 Pharmacokinetics
Absorption: After oral administration of therapeutic doses of amlodipine, absorption occurs gradually with peak plasma concentration reached between 6 and 12 hours. Absolute bioavailability has been estimated to be between 64 and 90%. The bioavailability of amlodipine is not altered by the presence of food.
Distribution: Ex vivo studies have shown that approximately 93% of the circulating drug is bound to plasma proteins in hypertensive patients.
Metabolism: Amlodipine is metabolized through the cytochrome P450 system, mainly via CYP 3A4 isoenzyme. Amlodipine is extensively (about 90%) converted to inactive metabolites (via hepatic metabolism) with 10% of the parent compound and 60% of the metabolites excreted in the urine.
Elimination: Elimination from the plasma is biphasic with a terminal elimination half-life of about 35-50 hours. Steady state plasma levels of amlodipine are reached after 7 to 8 days of consecutive daily dosing.
Special Populations and Conditions
Pediatrics: Two studies were conducted to evaluate the use of amlodipine besylate in a pediatric population.
In one study (pharmacokinetic), sixty-two hypertensive patients aged greater than 6 years received doses of amlodipine besylate between 1.25 mg and 20 mg. Weight-adjusted clearance and volume of distribution were similar to values in adults (see 4.2 Recommended Dose and Dosage Adjustment). The mean absorption rate constant (Ka) in children (0.85 hr-1) is approximately 50% higher than that in healthy adults (0.55 hr-1, range of 0.28–1.09 hr-1).
Gender effect: In a second trial (clinical), a pattern of greater reductions in both systolic and diastolic blood pressure in females than in males was observed. Mean change in systolic blood pressure from baseline to end of study: amlodipine 2.5 mg: males, -6.9 mmHg (n=51); females, -8.9 mmHg (n=32); amlodipine 5.0 mg: males, -6.6 mmHg (n=63); females, -14.0 mmHg (n=23); placebo males, -2.5 mmHg (n=54), females, -3.8 mmHg (n=33).
Renal Insufficiency: The pharmacokinetics of amlodipine are not significantly influenced by renal impairment. Plasma concentrations in the patients with moderate to severe renal failure were higher than in the normal subjects. Accumulation and mean elimination half-life in all patients were within the range of those observed in other pharmacokinetic studies with amlodipine in normal subjects.
Geriatrics: In elderly hypertensive patients (mean age 69 years), there was a decrease in clearance of amlodipine from plasma as compared to young volunteers (mean age 36 years) with a resulting increase in the area under the curve (AUC) of about 60%.
Hepatic Insufficiency: Following single oral administration of 5 mg of amlodipine, patients with chronic mild-moderate hepatic insufficiency showed about 40% increase in AUC of amlodipine as compared to normal volunteers. This was presumably due to a reduction in clearance of amlodipine as the terminal elimination half-life was prolonged from 34 hrs in young normal subjects to 56 hrs in the elderly patients with hepatic insufficiency.
Patients with severe hepatic impairment or hepatic failure: Because amlodipine besylate is extensively metabolized by the liver and the plasma elimination half-life (t 1/2) is 56 hours in patients with impaired hepatic function, it should be administered cautiously and at reduced dosages in patients with severely impaired hepatic function (see 4.2 Recommended Dose and Dosage Adjustment). Slow dose titration and careful monitoring are required in patients with severe hepatic impairment.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15°C-30°C. Protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions for this drug product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: amlodipine besylate
Chemical name: 3-Ethyl 5-methyl (±)-2-[(2-aminoethoxy)methyl]-4-(2-chlorophenyl)-1,4-dihydro-6-methyl-3,5-pyridinedicarboxylate benzenesulphonate
Molecular formula and molecular mass: C20H25ClN2O5.C6H6O3S and 567.1 g/mol
Structural formula:
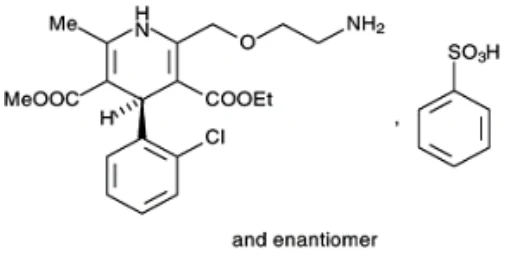
Physicochemical properties: Amlodipine besylate is a white crystalline substance, slightly soluble in water and sparingly soluble in ethanol.
M.p=203°C with decomposition
pKa=9.02 at 23.5 °C
14 CLINICAL TRIALS
The clinical trial data on which the original indication was authorized is not available.
14.2 Comparative Bioavailability Studies
A single dose crossover comparative bioavailability study of NB-Amlodipine (amlodipine besylate) 5 mg tablets and Norvasc TM (amlodipine besylate) 5 mg tablets in 17 healthy male volunteers (18 to 50 years old) was conducted under fasted conditions. Bioavailability data were measured and the results are summarized in the following table.
Amlodipine
(1 x 5 mg)
From Measured Data
Geometric Mean Arithmetic Mean (CV %)
Parameter Amlodipine besylate
5 mg tablets
NorvascTM Pfizer
Canada Inc. 5 mg tablets*
% Ratio of
Geometric
Means
Confidence Interval 90 %
AUC0-72
(pg.h/mL)
80403.0
81136.8 (16.1)
79846.4
80887.9 (20.3)
100.70 95.15 – 106.56
AUCI
(pg.h/mL)
118132.5
119990.2 (22.3)
114835.1
117961.2 (25.2)
102.87 92.74 – 114.11
CMAX
(pg/mL)
2207.9
2239.7 (18.0)
2095.4
2111.0 (14.6)
105.37 99.49 – 111.60
TMAX§
(h)
6.00 (5.00–10.00) 7.03 (5.00–12.00)
T½║
(h)
42.14 (20.0) 40.64 (31.8)
§ Expressed as median (range) only. ║ Expressed as the arithmetic mean (CV %). * Norvasc TM 5 mg tablets manufactured by Pfizer Canada Inc. were purchased in Canada.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Table 3. Single Dose Studies
SPECIES
ROUTE
DOSE
base
mg/kg/
day
ANIMAL
PER
DOSE
LEVEL
DURATION
FINDINGS
Maximum Tolerated Dose (Single)
Table 3. Single Dose Studies
SPECIES
ROUTE
DOSE
base
mg/kg/ day
ANIMAL
PER DOSE LEVEL
DURATION
FINDINGS
Maximum Tolerated Dose (Single)
Dog Oral
(gavage)
4
8
16
2 M Single Dose At all dose levels: Vasodilation and increases in plasma aldosterone levels.
At 4 mg/kg: Compensatory tachycardia.
At 8 mg/kg: In 1 of 2 dogs vomiting, sedation, respiratory distress and diarrhea 48 hr post-dose; normal at day 5.
Compensatory tachycardia. At 16 mg/kg: Moribund with hyperthermia within 24 hours; low blood pressure returned to normal over 2-6 days; transient raise in heart rate.
Histological examination showed congestion, edema and hemorrhage of the right atrial wall in the 2 dogs at 16 mg/kg. The hemorrhage in the right atrial wall corresponds to the right atrial lesions seen in long-term studies with amlodipine and other vasodilators (see long-term toxicity). One of 2 dogs at each dose showed fibrosis of the left ventricle in the subendocardial region and the posterior papillary muscle. The maximum tolerated dose was not determined.
Table 3. Single Dose Studies
SPECIES
ROUTE
DOSE
base
mg/kg/
day
ANIMAL
PER DOSE LEVEL
DURATION
FINDINGS
Maximum Tolerated Dose (Single)
Dog
(Japanese
Study)
Oral 3.5
7
1 M 1 F
Single Dose Mortality: 1 male dog at 7 mg/kg. Decreased spontaneous movement and flushing of palpebral conjunctiva and buccal cavity.
At 7 mg/kg: 1 female vomiting; 1 male hypothermia, lying prone.
Hematology/Clinical Chemistry: Increase in WBC and BUN at 10 and 5 mg/kg (males).
The maximum tolerated dose was not determined.
Table 4. Subacute And Chronic Toxicity Studies
SPECIES
ROUTE
DOSE
base
mg/kg/d
ay
ANIMAL
PER DOSE LEVEL
DURATION
FINDINGS
Mouse Oral
(diet)
0
2.5
5
10
10 M 10 F
2 Months At 10 mg/kg/day: Mice died during week 2 of the study. At 5 mg/kg/day (males and females) and 2.5 mg/kg/day (males): Increase in water consumption.
At 5 mg/kg/day - Pathology: Drug-related increases in heart and liver weights.
SPECIES
ROUTE
DOSE
base
mg/kg/d
ay
ANIMAL
PER
DOSE
LEVEL
DURATION
FINDINGS
Rat
(Japanese
Study)
Oral
(gavage
)
0
4
16
32
64
12 M
12 F
1 Month At 64 mg/kg/day: All rats died within 9 days.
At 32 mg/kg/day: 12/24 rats died; decreased food
consumption, growth
inhibition, ptosis, decreased spontaneous movement. At 16 and 32 mg/kg/day: The pattern of results on heart weights, increased urinary volume, effect on electrolyte balance and the adrenals was similar to that of the 6 month study below; increase in BUN at 16 mg/kg (males) and at 32 mg/kg (males and females).
Rat
(Japanese
Study)
Oral
(gavage
)
0
2
7
21
16 M
16 F
3 Months followed by 1 Month drug withdrawal
21 mg/kg/day: Salivation, growth inhibition, increased BUN, increased urinary volume, effect on electrolyte balance and adrenals was similar to that of the 6 month study below. Also post-mortem dilation of small intestine without
morphological lesions.
At 7 mg/kg/day: Alterations in urinary electrolytes excretion. No drug related effects at the end of 1 month drug
withdrawal phase.
SPECIES
ROUTE
DOSE
base
mg/kg/d
ay
ANIMAL
PER DOSE LEVEL
DURATION
FINDINGS
Rat Oral
(gavage
)
0
2.5
5
10
20 M 20 F
6 Months At all dose levels: Renal effects:
increased urinary volume and/or Na/K/Cl excretion, decreased plasma Na/K and/or Ca/Cl and increased urea; Post-mortem: Increase in heart weights.
At 10 mg/kg/day: Renal effects: increased kidney weight. Histopathology: Thickening of zona glomerulosa at 5 and 10 mg/kg/day.
Rat
(Japanese
Study)
Oral
(gavage
)
1.4
7
18
30 M 30 F
12 Months
(interim
sacrifice
5/sex/group
after
6 months)
Mortality: 3 rats (2 males and 1 female) at 18 mg/kg/day. At 18 mg/kg/day: Salivation, growth inhibition; Renal effects: increase in urinary volume with increased
electrolytes excretion and decreased serum electrolytes; increase in BUN.
At 7 mg/kg/day: Growth inhibition (males); Renal effects: increases of urinary volume and electrolyte
excretion.
Post-mortem: Increases of adrenal weights (at 18 mg/kg), increases of relative heart weight (18 and 7 mg/kg), dilated small intestines without morphological change
(18 mg/kg).
Histopathology - Main Finding: Enlargement of the zona glomerulosa of the adrenals (18 and 7 mg/kg).
SPECIES
ROUTE
DOSE
base
mg/kg/d
ay
ANIMAL
PER DOSE LEVEL
DURATION
FINDINGS
Dog Oral
(gavage
)
0.5 to 4
2 M 2 F
10 Days Supple-
mentary Dose
Escalation
Study
(0.5
mg/kg/day)
At 4 mg/kg: Death of all (4/4) dogs preceded in 3 dogs by low systolic blood pressure, bradycardia, disturbances of heart rhythm and conduction. Clinical signs included pale skin, hypothermia and prostration. Histopathology: Showed foci of myocyte necrosis and
sarcoplasmic vacuolation in the left ventricle, papillary muscle and left and right atria. Congestion and/or edema in several organs (i.e.
gastrointestinal tract/gall bladder wall and surrounding tissues as well as the
connective tissue surrounding both kidneys).
Dog Oral 0
0.25
0.5
1
3 M 3 F
6 Months At all dose levels: Increase in urinary volume and urinary excretion of electrolytes (not dose-related). Reduction in blood pressure and increases in heart rate.
At 1 mg/kg/day - Pathology: Increase in relative heart weights in 4/6 dogs,
inflammatory lesion of the right atrial wall was seen which was considered to be consequence of excessive hemodynamic changes.
SPECIES
ROUTE
DOSE
base
mg/kg/d
ay
ANIMAL
PER
DOSE
LEVEL
DURATION
FINDINGS
Dog Oral 0
0.125
0.25
0.5
4 M
4 F
12 Months At 0.5 mg/kg/day: Reduction in blood pressure and increases in heart rate; increase in urinary volume and urinary excretion of electrolytes (females). At 0.5 mg/kg/day - Pathology: Showed inflammatory lesions of the right atrial wall in 1/8 dogs, similar to that of the 6 month study above, and diffuse gingival hyperplasia.
Table 5. Mutagenicity studies
Study
Test Organism
Dose
Route
Major Findings
Ames Test
(modified)
Quantitative Plate
Assay (QAP) and
Metabolic
Activation (MA)
with Hepatic
Microsomes
Salmonella
typhimurium:
Strains TA
1535, TA 1537,
TA 98 and TA
100
10-0.02
mg/plate
(QAP)
0.2-0.0005
mg/plate
(MA)
In vitro No evidence of mutation frequency.
In vivo
Cytogenetic Tests
mouse bone
marrow
20 mg/kg single
dose
10 mg/kg/day
for
5 days
In vivo
PO
SC
No indication of chromosome breakage or mutagenicity observed.
In vitro
Cytogenetic Tests
with or without
metabolic
activation [rat
liver microsomal
enzymes (S-9)]
human
lymphocytes
Without
metabolic
activation:
0.01 to 1000
mcg/mL of
culture medium
With metabolic
activation:
1.0 to 25
mcg/mL of
culture medium.
In vitro Non-activation: No evidence of induced chromosome breakage observed at levels of 1.0 mcg/mL and below. At levels higher that 1.0 mcg/mL, compound produced mitotic inhibition. Activation: No drug
Study
Test Organism
Dose
Route
Major Findings induced clastogenic activity observed at levels up to 10 mcg/mL. Higher levels produced mitotic inhibition. Quantitative Plate
Assay (QAP) of
Mouse Urine
Salmonella
typhimurium
Strains: TA
1535, TA 1537,
TA 98 and TA
100.
0, 1, 10 and
20 mg/kg
In vivo
PO
No incidence of an excreted mutagen.
L 5178Y/TK +/-
Gene Mutation
Assay with and
without liver S-9
fraction
mouse
lymphoma cells
1.2 - 38 mcg/mL In vitro No evidence of gene mutational activity.
Carcinogenicity
There was no evidence of a carcinogenic effect when amlodipine was administered in the diet for up to 24 months to rats up to 2.5 mg/kg/day. Amlodipine was also administered for up to 24 months of dietary administration to mice at doses up to 2.5 mg/kg/day and no evidence of carcinogenicity was observed.
Table 6. Reproductive and Developmental Toxicology Studies
Species
Route
Dose
base/mg/
kg/day
Animal
per Dose
Level
Duration
Findings
Fertility
Rat (SD)
(Japanes
e Study)
Oral
(gavag
e)
0
1.4
7
18
24 M + 24
F
Males 71 days
prior to and during mating. Females
14 days prior to
and during mating and up to 7 days of gestation.
At 18 mg/kg: Impairment of body weight gain (females). There were no effects of the drug on copulation or pregnancy rates, nor any evidence of embryotoxicity or teratogenicity.
Teratology
Rat
(Charles
River
CD/SD)
Oral
(gavage
)
0
2
5
10
20 F Days 6-15 post
insemination.
Hysterectomies on day 20 of
gestation.
No effects were observed.
Rat (SD)
Japanese
Study
Oral
(gavage
)
0
3
7
18
34 F Days 7-17 post-
insemination. 2/3 of dams sacrificed on day 21 of
gestation. F1
generation
followed.
No effects were observed except in the dams.
At 18 mg/kg:
Reduction in food intake and body weight gain.
Rabbit
(Japanes
e White)
Japanese
Study
Oral 0
3
7
18
18 or 19 F Day 6 to day 18 of
gestation.
At 18 and 7 mg/kg: Decrease in maternal body weight (18 mg/kg) decrease in food consumption (18 and 7 mg/kg). No evidence of drug induced fetotoxicity or teratogenicity.
Peri- and Post-Natal
Rat (SD)
Japanese
Study
Oral
(gavage
)
0
1.4
2.8
7.0
25 F Day 17 of
gestation to day 21 post-partum.
As in the combined Fertility/Perinatal Study above; at the high dose level (7.0 mg/kg/day) adverse effects were observed on parturition and number of viable pups at birth and day 4 post-partum.
Reproductive and Developmental Toxicology
Reproductive studies in rats and mice have shown delayed date of delivery, prolonged duration of labour and decreased pup survival at dosages approximately 8 times greater than the maximum recommended dosage for humans.
Impairment of fertility
There was no effect on the fertility of rats treated orally with amlodipine maleate (males for 64 days and females for 14 days prior to mating) at doses ≤ 10 mg amlodipine/kg/day (about 8 times the maximum recommended human dose of 10 mg/day on a mg/m2 basis, for a 50 kg human).
In another rat study in which male rats were treated with amlodipine besylate for 30 days at a dose comparable with the human dose based on mg/kg decreased plasma follicle-stimulating hormone and testosterone were found as well as decreases in sperm density and in the number of mature spermatids and Sertoli cells.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1.
PrNORVASC® (Tablets, 5 mg and 10 mg, Oral), Submission Control Number 277171, Product
Monograph, BGP Pharma ULC. (August 2, 2023).