


Product Monograph - Niopeg
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis | |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Hematologic |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ....................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ................................................................................ 4
1 INDICATIONS .................................................................................................................................... 4
1.1 Pediatrics (<18 years of age): ......................................................................................................... 4
2 CONTRAINDICATIONS ..................................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .......................................................................... 4
4 DOSAGE AND ADMINISTRATION ................................................................................................... 4
4.1 Dosing Considerations ................................................................................................................... 4
4.2 Recommended Dose and Dosage Adjustment ............................................................................... 4
4.3 Reconstitution ................................................................................................................................. 5
4.4 Administration ................................................................................................................................. 5
4.5 Missed Dose ................................................................................................................................... 5
5 OVERDOSAGE .................................................................................................................................. 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................................... 5
7 WARNINGS AND PRECAUTIONS .................................................................................................... 6
7.1 Special Populations ........................................................................................................................ 9
7.1.1 Pregnant Women ............................................................................................................................ 9
7.1.2 Breast-feeding ................................................................................................................................ 9
7.1.3 Pediatrics ........................................................................................................................................ 9
7.1.4 Geriatrics ........................................................................................................................................ 9
8 ADVERSE REACTIONS .................................................................................................................... 9
8.1 Adverse Reaction Overview .......................................................................................................... 10
8.2 Clinical Trial Adverse Reactions ................................................................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions ........................................................................... 12
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .. 13
8.5 Post-Market Adverse Reactions ................................................................................................... 13
9 DRUG INTERACTIONS ................................................................................................................... 14
9.1 Serious Drug Interactions ............................................................................................................. 14
9.2 Drug Interactions Overview .......................................................................................................... 14
9.3 Drug-Behavioural Interactions ...................................................................................................... 14
9.4 Drug-Drug Interactions ................................................................................................................. 14
9.5 Drug-Food Interactions ................................................................................................................. 14
9.6 Drug-Herb Interactions ................................................................................................................. 14
9.7 Drug-Laboratory Test Interactions ................................................................................................ 14
10 CLINICAL PHARMACOLOGY ........................................................................................................ 15
10.1 Mechanism of Action .................................................................................................................... 15
10.2 Pharmacodynamics ...................................................................................................................... 15
10.3 Pharmacokinetics ......................................................................................................................... 15
11 STORAGE, STABILITY AND DISPOSAL ....................................................................................... 16
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................................... 17
PART II: SCIENTIFIC INFORMATION .................................................................................................... 18
13 PHARMACEUTICAL INFORMATION ............................................................................................. 18
14 CLINICAL TRIALS ........................................................................................................................... 19
14.1 Clinical Trials by Indication ........................................................................................................... 19
15 MICROBIOLOGY ............................................................................................................................. 21
16 NON-CLINICAL TOXICOLOGY....................................................................................................... 21
17 SUPPORTING PRODUCT MONOGRAPHS ................................................................................... 22
PATIENT MEDICATION INFORMATION ................................................................................................ 23
Niopeg (pegfilgrastim) is a biosimilar biologic drug (biosimilar) to Pegfilgrastim®. A biosimilar is a biologic drug that was granted authorization based on a demonstration of similarity to a version previously authorized in Canada, known as the reference biologic drug.
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Indication has been granted on the basis of similarity between Niopeg and the reference biologic drug Pegfilgrastim (pegfilgrastim).
Niopeg (pegfilgrastim) is indicated to decrease the incidence of infection, as manifested by febrile neutropenia, in patients with non-myeloid malignancies receiving myelosuppressive anti-neoplastic drugs.
1.1 Pediatrics (<18 years of age):
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
2 CONTRAINDICATIONS
Niopeg (pegfilgrastim) is contraindicated in patients with known hypersensitivity to E. coli-derived products‚ pegfilgrastim‚ filgrastim, or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing of the components, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Niopeg (pegfilgrastim) should be administered no sooner than 24 hours after the administration of cytotoxic chemotherapy (see 7 WARNINGS AND PRECAUTIONS).
Renal impairment, including end-stage renal disease, appears to have no effect on the pharmacokinetics of pegfilgrastim and no dosage adjustment is required.
4.2 Recommended Dose and Dosage Adjustment
The recommended dosage of Niopeg is a single subcutaneous injection of 6 mg, administered once per cycle of chemotherapy. Niopeg should be administered no sooner than 24 hours after the
Serious Warnings and Precautions
- Splenic rupture, including fatal cases, has been reported following the administration of pegfilgrastim and its parent compound, filgrastim (see 7 WARNINGS AND PRECAUTIONS: General).
- Severe sickle cell crisis have been associated with the use of pegfilgrastim in patients with sickle cell trait or sickle cell disease. Severe sickle cell crises, in some cases resulting in death, have also been associated with filgrastim, the parent compound of pegfilgrastim (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
administration of cytotoxic chemotherapy (see 7 WARNINGS AND PRECAUTIONS).
4.3 Reconstitution
Not applicable. Product does not need to be reconstituted.
4.4 Administration
Niopeg is intended for subcutaneous injection only and should not be given by any other route of administration. Niopeg should not be mixed with any diluents.
Niopeg should not be vigorously shaken.
Niopeg is supplied in prefilled syringes with a BD UltraSafe Plus™ Passive Needle Guard. Following administration of Niopeg from the prefilled syringe, the Needle Guard is automatically activated to cover the needle after the injection is given. The Needle Guard will help prevent stick injuries to anyone who handles the prefilled syringe. The prefilled syringe should be disposed of by placing the entire prefilled syringe with activated Needle Guard into an approved puncture-proof container.
4.5 Missed Dose
If a scheduled dose is missed, Niopeg should not be administered less than 14 days before subsequent administration of cytotoxic chemotherapy.
5 OVERDOSAGE
The maximum tolerated dose of Niopeg (pegfilgrastim) has not been determined in humans. Pegfilgrastim administered at a dose of 300 mcg/kg (n = 12), approximately 3 times the recommended dose, exhibited an adverse event profile similar to that observed at the recommended dose.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognize the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
For management of a suspected drug overdose, contact your regional poison control center.
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Subcutaneous | Sterile Solution for Injection 6 mg (10 mg/mL) | Acetic Acid Polysorbate 20 Sodium hydroxide Sorbitol Water for Injection |
Niopeg (pegfilgrastim) is supplied in 6 mg / 0.6 mL single-use, preservative-free, prefilled syringe (PFS) with a 27-gauge ½ inch needle and a BD UltraSafe Plus™ Passive Needle Guard for manual subcutaneous injection. The prefilled syringe does not bear graduation marks and is designed to deliver the entire contents of the syringe.
The syringe plunger stopper and needle cover are not made with natural rubber latex. Niopeg is provided in a carton containing one PFS and a package insert.
Description
Niopeg (pegfilgrastim) is a biosimilar to Pegfilgrastim. It is a long-acting form of recombinant methionyl human granulocyte-colony stimulating factor (r-metHuG-CSF), referred to as filgrastim. Niopeg is composed of filgrastim with a 20 kDa monomethoxypolyethylene glycol propionaldehyde (mPEG-p) molecule covalently bound to the N-terminal methionine residue. Filgrastim is expressed in Escherichia coli (E. coli) as a 175 amino acid protein with a theoretical average weight of 18,799 Da; Niopeg exhibits molecular weight dispersity with an observed distribution of approximately 37.0 to 42.5 kDa.
7 WARNINGS AND PRECAUTIONS
General
Niopeg (pegfilgrastim) has not been evaluated for PBPC (peripheral blood progenitor cell) mobilization. Therefore, it should not be used in that setting.
Splenic Rupture
Splenic rupture, including fatal cases, has been reported following the administration of pegfilgrastim and its parent compound, filgrastim. Patients receiving Niopeg who report left upper abdominal and/or shoulder tip pain should be evaluated for an enlarged spleen or splenic rupture.
Simultaneous Use with Chemotherapy and Radiation Therapy
The safety and efficacy of Niopeg administered concurrently with cytotoxic chemotherapy have not been established. Because of the potential for an increase in sensitivity of rapidly dividing myeloid cells to cytotoxic chemotherapy‚ Niopeg should not be administered in the period between 14 days before and 24 hours after administration of cytotoxic chemotherapy (see 4 DOSAGE AND ADMINISTRATION).
The safety and efficacy of Niopeg have not been evaluated in patients receiving chemotherapy associated with delayed myelosuppression (e.g., nitrosoureas), mitomycin C, or myelosuppressive doses of anti-metabolites such as 5-fluorouracil (5-FU). Concomitant use of Niopeg with 5-FU or other anti-metabolites has not been evaluated in humans, although pegfilgrastim has been studied and shown to potentiate myelosuppression in animal models (see 16 NON-CLINICAL TOXICOLOGY).
The safety and efficacy of pegfilgrastim have not been evaluated in patients receiving radiation therapy, except for patients with breast or lung cancer.
Carcinogenesis and Mutagenesis
No carcinogenesis or mutagenesis studies were conducted with Niopeg.
Potential Effect on Malignant Cells
Niopeg (pegfilgrastim) and filgrastim are growth factors that primarily stimulate production of neutrophils and neutrophil precursors by binding to the G-CSF receptor. Overall, the possibility that Niopeg can act as a growth factor for any tumour type cannot be excluded. The use of Niopeg in chronic myeloid leukemia (CML) and myelodysplastic syndrome (MDS) has not been studied.
MDS and AML in Breast and Lung Cancer Patients
In the post-marketing observational study setting, findings showed that pegfilgrastim is associated with an increased risk of MDS and AML in breast and lung cancer patients when used in conjunction with chemotherapy and/or radiotherapy. Monitor patients for signs and symptoms of MDS/AML in these settings.
Cardiovascular
Aortitis
Aortitis has been reported in patients receiving pegfilgrastim and may present with generalized signs and symptoms such as fever and increased inflammatory markers. Consider aortitis in patients who develop these signs and symptoms without known etiology.
Capillary Leak Syndrome
Capillary leak syndrome (CLS) has been reported after the administration of pegfilgrastim or filgrastim. CLS can cause circulatory shock and may be fatal, and is characterized by hypotension, hypoalbuminemia, edema, and hemoconcentration. Episodes vary in frequency, severity, and may be life-threatening if treatment is delayed. Patients who develop symptoms of capillary leak syndrome should be closely monitored and receive treatment, which may include a need for intensive care.
Hematologic
Sickle Cell Crises
Severe sickle cell crises have been associated with the use of pegfilgrastim in patients with sickle cell trait or sickle cell disease. Severe sickle cell crises, in some cases resulting in death, have also been associated with filgrastim, the parent compound of pegfilgrastim. Only physicians qualified by specialized training or experience in the treatment of patients with sickle cell trait and sickle cell disease should prescribe Niopeg for such patients, and only after careful consideration of the potential risks and benefits.
Leukocytosis
In clinical studies with pegfilgrastim, white blood cell counts of 100 x 109/L or greater have been reported in less than 1% of patients with cancer receiving myelosuppressive chemotherapy (n = 930), and were not associated with any reported adverse clinical effects (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
In studies of pegfilgrastim administration after chemotherapy‚ most reported side effects were consistent with those usually seen as a result of cytotoxic chemotherapy (see 8 ADVERSE REACTIONS). Because of the potential for patients to receive full doses of chemotherapy on the prescribed schedule‚ patients may be at greater risk of thrombocytopenia‚ anemia‚ and non- hematologic consequences of increased chemotherapy doses (please refer to the prescribing information for specific chemotherapy agents). Regular monitoring of hematocrit value and platelet count is recommended. Furthermore‚ care should be exercised in the administration of Niopeg in conjunction with drugs known to lower platelet count.
Thrombocytopenia
Thrombocytopenia, including serious events, has been reported in patients receiving pegfilgrastim. Platelet count should be monitored regularly as clinically indicated.
Immune
Hypersensitivity/Allergic Reactions
Hypersensitivity including serious allergic reactions and anaphylactic reactions, skin rash, urticaria and erythema/flushing occurring on initial or subsequent treatment have been reported both with pegfilgrastim and filgrastim. In some cases, symptoms have recurred with rechallenge, suggesting a causal relationship. In rare cases, allergic reactions, including anaphylactic reactions, recurred within days after initial anti-allergic treatment was discontinued. If a serious allergic reaction or an anaphylactic reaction occurs, appropriate therapy should be administered and further use of Niopeg should be discontinued. Antibodies to filgrastim or pegfilgrastim have been reported, although no neutralizing antibodies have been reported (see 8 ADVERSE REACTIONS; Immunogenicity). Do not administer filgrastim to patients with a history of hypersensitivity to filgrastim or pegfilgrastim.
Cutaneous Vasculitis
Uncommon (≥1/1,000 to <1/100) events of cutaneous vasculitis have been reported in patients treated with pegfilgrastim sterile solution for injection. The mechanism of vasculitis in patients receiving pegfilgrastim is unknown.
Monitoring and Laboratory Tests
To assess a patient's hematologic status and ability to tolerate myelosuppressive chemotherapy, a complete blood count (CBC) and platelet count should be obtained before chemotherapy is administered. Pegfilgrastim produced ANC (absolute neutrophil count) profiles similar to daily filgrastim, including earlier ANC nadir, shorter duration of severe neutropenia, and accelerated ANC recovery, compared with ANC profiles observed without growth factor support. Regular monitoring of hematocrit value, white blood cell count and platelet count, as clinically indicated, is recommended.
Renal
Glomerulonephritis
Glomerulonephritis has been reported in patients receiving filgrastim and pegfilgrastim. Generally, events of glomerulonephritis resolved after dose reduction or withdrawal of filgrastim and pegfilgrastim. Urinalysis monitoring is recommended.
Respiratory
Acute Respiratory Distress Syndrome
Acute respiratory distress syndrome (ARDS) has been reported following administration of pegfilgrastim and is postulated to be secondary to an influx of neutrophils to sites of inflammation in the lungs. Neutropenic patients receiving Niopeg who develop fever, lung infiltrates, or respiratory distress should be evaluated for the possibility of ARDS. In the event that ARDS occurs, Niopeg should be discontinued and/or withheld until resolution of ARDS, and patients should receive appropriate medical management for this condition.
Sexual Function/Reproduction
No studies evaluating sexual function or reproduction in humans were conducted with Niopeg.
7.1 Special Populations
7.1.1 Pregnant Women
There were no pregnant women exposed to pegfilgrastim in clinical trials. Niopeg should be used during pregnancy only if the potential benefit outweighs the risk to the fetus (see 1 6 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
It is not known whether pegfilgrastim is excreted in human milk. Because many drugs are excreted in human milk‚ Niopeg is not recommended for women who are breast-feeding. Niopeg should only be administered to a nursing woman if the potential benefit outweighs the risk.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of Niopeg in pediatric patients have not been established.
7.1.4 Geriatrics
Geriatrics (>65 years of age): Of the total number of patients with cancer who received pegfilgrastim in clinical studies (n = 930), 139 patients (15%) were 65 years or older and 18 patients (2%) were 75 years or older. No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients; however, due to the small number of elderly subjects, small but clinically relevant differences cannot be excluded.
8 ADVERSE REACTIONS
The adverse drug reaction profiles reported in clinical studies that compared Niopeg (pegfilgrastim) to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
The most frequently reported study drug-related adverse event was bone pain, for which the incidence in patients treated with pegfilgrastim was similar to that in patients treated with filgrastim. Bone pain was generally reported as mild-to-moderate, could be controlled in most patients with non-narcotic analgesia.
See 7 WARNINGS AND PRECAUTIONS regarding Splenic Rupture, ARDS, Hypersensitivity/Allergic Reactions, and Sickle Cell Crises.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying and for approximating rates of drug-related adverse events in real-world use.
Safety data are based on 7 randomized clinical trials involving 932 patients with lymphoma and solid tumours (breast and thoracic) who received pegfilgrastim after non-myeloablative cytotoxic chemotherapy. Common adverse events occurred at similar rates between the treatment arms in both the filgrastim-controlled trials (pegfilgrastim, n = 465; filgrastim, n = 331) and the placebo- controlled trial (pegfilgrastim, n = 467; placebo, n = 461). Most adverse experiences were attributed by the investigator as the sequelae of the underlying malignancy or cytotoxic chemotherapy. In the filgrastim-controlled trials, these adverse experiences occurred at rates between 15% and 72% and included: nausea, fatigue, alopecia, diarrhea, vomiting, constipation, fever, anorexia, skeletal pain, headache, taste perversion, dyspepsia, myalgia, insomnia, abdominal pain, arthralgia, generalized weakness, peripheral edema, dizziness, granulocytopenia, stomatitis, mucositis, and neutropenic fever. A summary of the most frequently reported adverse reactions in these randomized clinical trials can be found in Table 2 and Table 3.
In clinical trials comparing pegfilgrastim to filgrastim, medullary bone pain was reported in 26% of pegfilgrastim-treated patients, which was comparable to the incidence in filgrastim-treated patients. In the study comparing pegfilgrastim to placebo, the incidence of bone pain was 23% vs. 16%, respectively. This bone pain was generally reported to be of mild-to-moderate severity. Approximately 17% (for all bone pain type AEs; 10% for specifically “bone pain”) of all subjects utilized non-narcotic analgesics and less than 6% utilized narcotic analgesics in association with bone pain. No patient withdrew from study due to bone pain.
Across all studies, no life-threatening or fatal adverse events were attributed to pegfilgrastim. There was only one serious adverse event (dyspnea) reported as possibly related to pegfilgrastim in a single patient. No events of pleuritis, pericarditis, or other major systemic reactions to pegfilgrastim were reported.
No clinically significant changes in vital signs were observed. No evidence of interaction of pegfilgrastim with other drugs was observed in the course of clinical trials (see 7 WARNINGS AND PRECAUTIONS).
Table 2: Most Frequently* Reported Adverse Reactions in Randomized Clinical Trials with Filgrastim as Comparator
| Body System and Preferred Term | Pegfilgrastim (n = 465) | Filgrastim (n = 331) |
|---|---|---|
| Application Site | ||
| Injection Site Pain | 16 (3%) | 9 (3%) |
| Body as a whole | ||
| Pain | 8 (2%) | 4 (1%) |
| Chest Pain (Non-Cardiac) | 4 (1%) | 3 (1%) |
| Edema Periorbital | 3 (1%) | 0 (0%) |
| Fever | 3 (1%) | 4 (1%) |
| CNS/PNS | ||
| Headache | 20 (4%) | 12 (4%) |
| Musculo-skeletal | ||
| Skeletal Pain | 96 (21%) | 89 (27%) |
| Myalgia | 32 (7%) | 25 (8%) |
| Arthralgia | 27 (6%) | 19 (6%) |
| Back Pain | 19 (4%) | 26 (8%) |
| Limb Pain | 12 (3%) | 7 (2%) |
| Musculo-Skeletal Pain | 5 (1%) | 4 (1%) |
| Neck Pain | 4 (1%) | 3 (1%) |
* Most frequently reported events were considered to be those events reported in ≥1% of the patients in the pegfilgrastim group.
Table 3: Most Frequently* Reported Adverse Reactions in Randomized Clinical Trials with Placebo Control
| Body System and Preferred Term | Pegfilgrastim (n = 467) | Placebo (n = 461) |
|---|---|---|
| Blood and Lymphatic System Disorders | ||
| Leukocytosis | 5 (1%) | 1 (0%) |
| Gastrointestinal Disorders | ||
| Diarrhea | 9 (2%) | 10 (2%) |
| General Disorders and Administration Site Conditions | ||
| Pyrexia | 8 (2%) | 9 (2%) |
| Fatigue | 3 (1%) | 5 (1%) |
| Infections and Infestations | ||
| Influenza | 6 (1%) | 5 (1%) |
| Musculoskeletal and Connective Tissue Disorders | ||
| Bone Pain | 62 (13%) | 41 (9%) |
| Myalgia | 26 (6%) | 23 (5%) |
| Arthralgia | 32 (7%) | 19 (4%) |
| Polymyalgia | 8 (2%) | 7 (2%) |
| Musculoskeletal Pain | 14 (3%) | 5 (1%) |
| Pain in Limb | 11 (2%) | 5 (1%) |
| Back Pain | 8 (2%) | 4 (1%) |
| Polyarthralgia | 5 (1%) | 0 (0%) |
| Nervous System Disorders | ||
| Headache | 6 (1%) | 2 (0%) |
| Skin and Subcutaneous Tissue Disorders | ||
| Alopecia | 8 (2%) | 9 (2%) |
* Most frequently reported events were considered to be those events reported in ≥ 1% of the patients in the pegfilgrastim group.
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse drug reactions were reported at an incidence of <1% in controlled clinical studies (occurring in more than 1 patient, with higher frequency than filgrastim):
General Disorders and Administration Site Conditions: injection site bruising.
Infections and Infestations: rhinitis.
Nervous System Disorders: hypertonia.
Skin and Subcutaneous Tissue Disorders: periorbital edema.
The following adverse drug reactions were reported at an incidence of <1% in controlled clinical studies (occurring in more than 1 patient, with higher frequency than placebo):
General Disorders and Administration Site Conditions: chest pain, pain.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Spontaneously reversible elevations in lactate dehydrogenase (LDH), alkaline phosphatase, and uric acid of mild-to-moderate severity were observed. Most changes have been attributed to post-cytokine bone marrow expansion as well as to chemotherapy and metastatic disease. The incidences of these changes, presented for pegfilgrastim versus filgrastim and placebo, were: LDH (18% versus 29% and 18%), alkaline phosphatase (11% versus 16% and 12%), and uric acid [10% versus 9% and 13% (1% of uric acid reported cases for filgrastim and pegfilgrastim treatment groups were classified as severe)].
In clinical studies with pegfilgrastim, white blood cell counts of 100 x 109/L or greater have been reported in less than 1% of patients with cancer receiving myelosuppressive chemotherapy (n = 930), and were not associated with any reported adverse clinical effects.
Immunogenicity
As with all therapeutic proteins, there is a potential for immunogenicity. The incidence of antibody development in patients receiving pegfilgrastim has not been adequately determined. While available data suggest that a small proportion of patients developed binding antibodies to filgrastim or pegfilgrastim, the nature and specificity of these antibodies have not been adequately studied. No neutralizing antibodies have been detected using a cell-based bioassay in 46 (9%, n =534) patients who apparently developed binding antibodies. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay, and the observed incidence of antibody positivity in an assay may be influenced by several factors including sample handling, concomitant medications, and underlying disease. Therefore, comparison of the incidence of antibodies to pegfilgrastim with the incidence of antibodies to other products may be misleading.
Cytopenias resulting from an antibody response to exogenous growth factors have been reported on rare occasions in patients treated with other recombinant growth factors. There is a theoretical possibility that an antibody directed against pegfilgrastim may cross-react with endogenous G-CSF, resulting in immune-mediated neutropenia, but this has not been observed in clinical studies.
8.5 Post-Market Adverse Reactions
In addition to the events listed above, reports of adverse reactions have been identified post-market in patients receiving pegfilgrastim, including:
- Splenomegaly (enlarged spleen) and Splenic rupture (see 7 WARNINGS AND PRECAUTIONS, General, Splenic Rupture)
- Aortitis (see 7 WARNINGS AND PRECAUTIONS: Cardiovascular)
- Capillary Leak Syndrome (see 7 WARNINGS AND PRECAUTIONS: Cardiovascular)
- Sickle cell crisis (see 7 WARNINGS AND PRECAUTIONS: Hematologic)
- Myelodysplastic Syndrome (MDS) and Acute Myeloid Leukemia (AML) in Breast and Lung Cancer Patients (see 7 WARNINGS and PRECAUTIONS, Hematologic)
- Allergic reactions (see 7 WARNINGS AND PRECAUTIONS: Immune, Hypersensitivity/Allergic Reactions)
- Cutaneous Vasculitis (see 7 WARNINGS AND PRECAUTIONS: Immune)
- Glomerulonephritis (see 7 WARNINGS AND PRECAUTIONS: Renal)
- Acute respiratory distress syndrome (ARDS) (see 7 WARNINGS AND PRECAUTIONS: Respiratory)
- Injection site reactions (pain, induration, and local erythema)
- Generalized erythema and flushing
- Sweet’s syndrome (acute febrile neutrophilic dermatosis)
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
No serious drug interactions have been identified.
9.2 Drug Interactions Overview
Drug interactions between pegfilgrastim and other drugs have not been studied. Drugs such as lithium that may potentiate the release of neutrophils should be used with caution; such patients should have more frequent monitoring of their neutrophil counts.
9.3 Drug-Behavioural Interactions
No drug-behavioural interactions have been established.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Increased hematopoietic activity of the bone marrow in response to growth factor therapy has been associated with transient positive bone-imaging changes. This should be considered when interpreting bone-imaging results.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Both pegfilgrastim and filgrastim are colony-stimulating factors that act on hematopoietic cells by binding to specific cell surface receptors thereby stimulating proliferation, differentiation, commitment, and end cell functional activation. Studies on cellular proliferation, receptor binding, and neutrophil function demonstrate that filgrastim and pegfilgrastim have the same mechanism of action. Pegfilgrastim has reduced renal clearance and prolonged persistence in vivo as compared to filgrastim.
10.2 Pharmacodynamics
See information in 10.3 below.
10.3 Pharmacokinetics
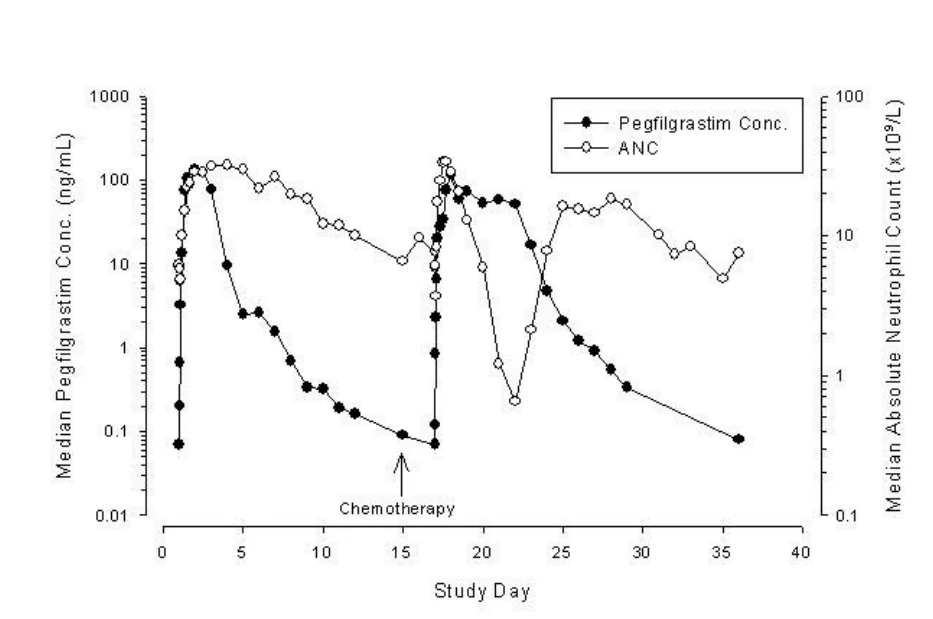
The pharmacokinetics and pharmacodynamics of pegfilgrastim were studied in patients with cancer. The pharmacokinetics of pegfilgrastim were nonlinear in cancer patients and clearance decreased with increases in dose. Neutrophil-mediated clearance is an important component of the clearance of pegfilgrastim, and serum clearance is related to the number of neutrophils (neutrophil-mediated, self-regulating clearance). Consistent with a self-regulating clearance mechanism, the serum concentration of pegfilgrastim declined rapidly at the onset of neutrophil recovery, following myelosuppressive chemotherapy (see Figure 1). In addition to numbers of neutrophils, body weight appeared to be a factor. Patients with higher body weights experienced higher systemic exposure to pegfilgrastim after receiving a dose normalized for body weight. A large variability in the pharmacokinetics of pegfilgrastim was observed in cancer patients. The half-life of pegfilgrastim ranged from 25 to 49 hours after SC injection.
Table 4: Summary of Pharmacokinetic Parameters of Pegfilgrastim in Cancer Patients After SC Administration
| Cmax | t½ | AUC0-∞ | Clearance | |
|---|---|---|---|---|
| Single dose* Median | 78.3-175 ng/mL | 25-49 hr | 5640-15000 ng·hr/mL | 6.68-17.7 mL/hr/kg |
* Doses of 100 mcg/kg and 6 mg
Figure 1. Median NEULASTA (pegfilgrastim) Serum Concentration and Absolute Neutrophil Count Profiles in Patients With Non-Small Cell Lung Cancer (n = 3) After a Single Injection of NEULASTA 100 mcg/kg Administered Before and After Chemotherapy
Special Populations and Conditions
Pediatrics: The pharmacokinetic profile in pediatric populations has not been assessed.
Geriatrics: no differences were observed in the pharmacokinetics of geriatric patients with cancer (≥ 65 years of age) compared to younger patients (< 65 years of age) (see 7 WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
Sex: no gender-related differences were observed in the pharmacokinetics of pegfilgrastim.
Ethnic origin: The effect of race on pharmacokinetics has not been adequately assessed.
Hepatic Insufficiency: The pharmacokinetic profile in patients with hepatic insufficiency has not been assessed.
Renal Insufficiency: Renal impairment, including end-stage renal disease, appears to have no effects on the pharmacokinetics of pegfilgrastim.
11 STORAGE, STABILITY AND DISPOSAL
Niopeg (pegfilgrastim) should be stored in the refrigerator at 2°C to 8°C. Do not store in the freezer. Store in the carton to protect from light.
Accidental exposure to room temperature (up to 25°C) or accidental exposure to freezing temperatures does not adversely affect the stability of the product. If frozen, thaw in refrigerator before administration. Discard Niopeg if frozen more than once.
Niopeg may be allowed to reach room temperature for a maximum of 4 days. Any prefilled syringe left at room temperature for greater than 4 days should be discarded.
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration, whenever solution and container permit. Niopeg should not be administered if discolouration or particulates are observed.
The prefilled syringe should be disposed of by placing the entire prefilled syringe with the Needle Guard into an approved puncture-proof container.
12 SPECIAL HANDLING INSTRUCTIONS
Niopeg (pegfilgrastim) should not be vigorously shaken.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: pegfilgrastim
| Proper name: | pegfilgrastim |
|---|---|
| Chemical name: | recombinant methionyl human granulocyte colony-stimulating factor |
| Molecular formula and molecular mass: | Pegfilgrastim has a total molecular weight of 39,000 daltons. |
| Structural formula: | Pegfilgrastim is composed of filgrastim (recombinant methionyl human G-CSF) with a 20,000 dalton polyethylene glycol (PEG) molecule covalently bound to the N-terminal methionine residue. Filgrastim is a 175 amino acid protein manufactured by recombinant DNA technology. Filgrastim is produced by Escherichia coli (E. coli) bacteria into which the human G-CSF gene has been inserted. Filgrastim has an amino acid sequence that is identical to the natural sequence predicted by human DNA sequence analysis‚ except for the addition of an N-terminal methionine necessary for expression in E. coli. Because filgrastim is produced in E. coli‚ the protein is nonglycosylated and thus differs from G-CSF isolated from a human cell. |
Physicochemical properties: pH 3.8 – 4.3
Product Characteristics
Niopeg (pegfilgrastim) is a sterile, clear, colourless liquid.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Decrease the incidence of infection in patients with non-myeloid malignancies receiving myelosuppressive anti-neoplastic drugs
Trial Design and Study Demographics
Table 5. Summary of patient demographics for clinical trials in specific indication
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n = number) | Mean age (Range) years | Gender |
|---|---|---|---|---|---|
| 980226 | Phase 3, double- blind, randomized, filgrastim controlled | Single SC dose of 100 mcg/kg/day pegfilgrastim or daily SC dose of 5 mcg/kg/day filgrastim, up to 4 cycles | 310 (154 pegfilgrastim, 156 filgrastim) | 50.9 (25-81) pegfilgrastim 51.8 (26-87) filgrastim | 306 female, 4 male |
| 990749 | Phase 3, double- blind, randomized, filgrastim controlled | 6 mg single dose of pegfilgrastim SC or 5 mcg/kg/day filgrastim up to 14 days, up to 4 cycles | 157 (80 pegfilgrastim, 77 filgrastim) | 51.9 (31-75) pegfilgrastim 52.6 (30-74) filgrastim | 156 female, 1 male |
| 20010144 | Phase 3, double- blind, placebo- controlled, randomized | Pegfilgrastim, 6 mg SC, single dose every 3 weeks, up to 12 weeks | 928 (463 pegfilgrastim, 465 placebo) | 51.9 (21-88) pegfilgrastim 52.1 (24-76) placebo | 99% female |
Study Results
Clinical Experience: Response to Pegfilgrastim
Pegfilgrastim administered as a single SC injection, after each cycle of chemotherapy, has been shown to be safe and effective in reducing neutropenia and associated clinical sequelae in a variety of chemotherapy settings.
Pegfilgrastim has been evaluated in three Phase 3, randomized, double-blind, controlled studies. Results from two active controlled studies (n = 467) conducted in patients with breast cancer undergoing up to 4 cycles of chemotherapy with doxorubicin and docetaxel demonstrated non- inferiority of pegfilgrastim to filgrastim. A clinically and statistically similar reduction in the duration of severe neutropenia (absolute neutrophil count [ANC] < 0.5 x 10⁹/L; WHO grade 4) was seen in patients who received a single injection of pegfilgrastim, either 6 mg fixed dose or 100 mcg/kg, compared with patients who received a mean of 11 daily injections (cycle 1) of filgrastim
5 mcg/kg/day.

*

*

*
The mean (std dev) duration of severe neutropenia in cycle 1 in patients who received a single fixed-dose (6 mg) SC injection of pegfilgrastim (n = 68) was 1.8 (1.4) days compared with 1.6 (1.1) days in patients who received daily injections (range: 7-14 injections) of filgrastim (n = 62). The difference in means was 0.18 days (95% CI of -0.23 to 0.61). Durations of severe neutropenia were also comparable between treatment groups in all subsequent cycles. The rate of febrile neutropenia (temperature ≥ 38.2°C with an ANC < 0.5 x 10⁹/L) across all cycles was lower for patients receiving pegfilgrastim (13%) compared to patients receiving filgrastim (20%) (-7% difference; 95% CI of -19% to +5%). A single SC injection of pegfilgrastim per chemotherapy cycle was safe and well tolerated (see 8 ADVERSE REACTIONS).
The third study employed a placebo control and evaluated the effect of pegfilgrastim on the incidence of febrile neutropenia when administered in first and all subsequent cycles of a moderately myelosuppressive chemotherapy regimen, docetaxel administered at 100 mg/m2 Q3W for 4 cycles, which has been reported to be associated with a febrile neutropenia rate of 10% to 20%.
In this study, 928 patients with metastatic or non-metastatic breast cancer were treated with docetaxel. On day 2 of cycle 1, patients were randomized to receive either a single SC dose of 6 mg of pegfilgrastim or placebo. Patients who received pegfilgrastim in cycle 1 were scheduled to receive pegfilgrastim in all subsequent cycles. Patients who received placebo in cycle 1 were scheduled to receive placebo in all subsequent cycles; however, patients who experienced febrile neutropenia would receive open-label pegfilgrastim.
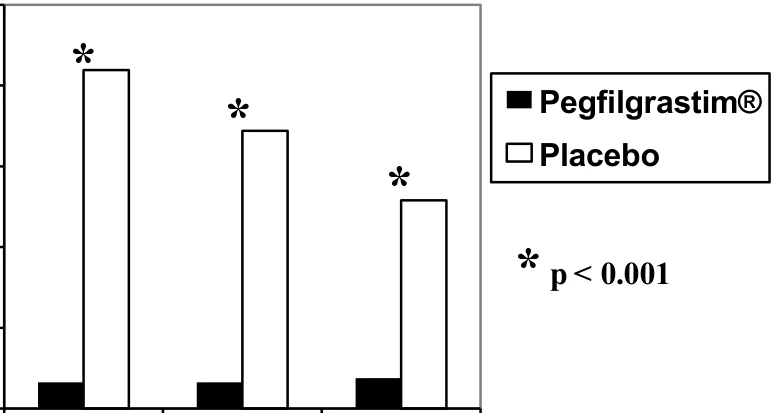
The incidence of febrile neutropenia was statistically significantly lower for patients randomized to receive pegfilgrastim versus placebo (1% versus 17%, p ≤ 0.001). The incidence of hospitalizations and IV anti-infective use associated with a clinical diagnosis of febrile neutropenia was significantly lower in the pegfilgrastim group compared with placebo [1% versus 14%, p ≤ 0.001; and 2% versus 10%, p ≤ 0.001, respectively (see Figure 2)].
Figure 2. Percentage of Subjects With Febrile Neutropenia (FN), Who Were Hospitalized, and Who Received IV Anti-infectives for FN
20
16
12
8 * p < 0.001
4
0
FN Hospitalization IV Anti- infectives
Incidence rate
Data from Phase 2 studies in patients with various malignancies undergoing a variety of chemotherapy regimens further support the safety and efficacy of pegfilgrastim. Dose-finding studies in patients with breast cancer (n = 152), thoracic tumours (n = 92), and non-Hodgkin's lymphoma (NHL) (n = 49) demonstrated that the efficacy of a single injection of pegfilgrastim
100 mcg/kg was similar to daily injections of filgrastim 5 mcg/kg/day, and superior to pegfilgrastim doses of 30 or 60 mcg/kg, at reducing the duration of severe neutropenia and the rate of febrile neutropenia. A randomized phase II study of patients with NHL or Hodgkin's lymphoma (n = 60) further supports the safety and efficacy of pegfilgrastim.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
The preclinical toxicology of pegfilgrastim was studied in Sprague-Dawley® rats and cynomolgus monkeys. A single-dose IV study was conducted in rats. Pegfilgrastim caused no clinical signs or mortality at single IV doses up to 10,000 mcg/kg in rats.
Repeat-dose studies included 2-week SC (every-other-day dosing) and 6-month SC/IV (weekly dosing) studies in rats and a 1-month SC (weekly dosing) study in monkeys. Dosing was intermittent to mimic intended human use of pegfilgrastim. Pegfilgrastim was well tolerated for 6 months at once-weekly doses up to 1000 mcg/kg SC or 300 mcg/kg IV in rats, and for 1 month at once-weekly doses up to 750 mcg/kg SC in cynomolgus monkeys. No effects on body weight, food consumption, or survival were observed. Pegfilgrastim caused an increase in leukocyte counts, primarily segmented neutrophils, but also some increases in band neutrophils, monocytes, and lymphocytes. Pegfilgrastim also modestly decreased erythrocyte counts, hemoglobin and hematocrit levels, decreased serum cholesterol, slightly decreased serum potassium, and increased serum alkaline phosphatase. Splenomegaly was the principal gross pathological finding. Histopathological examination revealed increased neutrophilic granulopoiesis in bone marrow and extramedullary hematopoiesis in spleen, liver, and/or lymph nodes. Leukocytosis in spleen, liver, and lymph nodes, and mild inflammation and mononuclear cell infiltrate at the injection site were additionally observed in monkeys treated with pegfilgrastim. Observed changes tended to reverse upon cessation of treatment. Changes specific to every-other-day dosing in rats (≥ 500 mcg/kg only) included slightly increased serum ALT and/or AST, mild myelofibrosis in bone marrow, and increased osteoblastic/osteoclastic activity in bone. Little or no seroreactivity to pegfilgrastim was evident in rats, whereas a dose- and time-dependent increase in seroreactivity was observed in monkeys; however, pegfilgrastim-induced neutrophil increases were maintained.
Carcinogenicity:
Filgrastim is known to be negative in bacterial mutagenesis assays (Ames assay). Pegfilgrastim did not cause precancerous or cancerous lesions in Sprague-Dawley® rats after once-weekly SC injections of up to 1000 mcg/kg for 6 months. Given the similar biochemical activity to filgrastim, the chemical nature of the PEG moiety, and extensive clinical experience with filgrastim, it is considered unlikely that pegfilgrastim would be carcinogenic when used as directed.
Pegfilgrastim is a growth factor that primarily stimulates production of neutrophils and neutrophil precursors; however, the G-CSF receptor through which pegfilgrastim and filgrastim act has been found on tumour cell lines, including some myeloid, T-lymphoid, lung, head and neck, and bladder tumour cell lines. In vitro proliferation has been observed in response to filgrastim in some of these cell lines, particularly acute myeloid leukemia (AML) cell lines.
Reproductive and Developmental Toxicology:
Pegfilgrastim has been shown to have adverse effects in pregnant rabbits when given every- other-day at doses as low as 50 mcg/kg. Nonclinical data in pregnant rats indicate that very low levels of pegfilgrastim may cross the placenta.
Pegfilgrastim administered SC to pregnant rabbits at doses of 200 and 250 mcg/kg every-other- day during the period of organogenesis was associated with an increased incidence of abortions. Increased postimplantation loss due to early resorptions and decreased numbers of live fetuses were observed at pegfilgrastim doses of 200 to 1000 mcg/kg every other day. Decreased maternal food consumption and/or weight gain and decreased fetal weight were observed at doses of 50 to 1000 mcg/kg every other day. Pegfilgrastim did not cause visceral or skeletal malformations in rabbit fetuses at doses as high as 200 mcg/kg every-other-day and did not cause external malformations in rabbit fetuses at doses as high as 1000 mcg/kg every other day.
Pegfilgrastim was not associated with an increase in external, visceral, or skeletal malformations in fetuses when administered by SC injection to pregnant rats during the period of organogenesis at dose levels up to 1000 mcg/kg every other day. However, an increased incidence of wavy ribs, generally regarded as a reversible pathological finding, was observed in rat fetuses at dose levels of 300 and 1000 mcg/kg every other day. No maternal or neonatal toxicities were observed in female rats administered once-weekly SC injections of pegfilgrastim up to 1000 mcg/kg in a pre- and postnatal developmental study.
Indices of mating or fertility in male and female Sprague-Dawley® rats were not adversely affected by once-weekly SC injections of pegfilgrastim of up to 1000 mcg/kg for 2 to 4 weeks before and during cohabitation.
17 SUPPORTING PRODUCT MONOGRAPHS
Neulasta® (Pegfilgrastim Injection, 6mg (10 mg/mL), Control No. 242732, Product Monograph, Amgen Canada Inc., January 8, 2021.