


Product Monograph - Noroxin
INDICATIONS AND CLINICAL USE
The treatment of upper and lower urinary tract infections, specifically complicated and uncomplicated cystitis, pyelitis and pyelonephritis caused by susceptible strains of the following microorganisms:
Escherichia coli,
Klebsiella pneumoniae,
unspecified Klebsiella spp.,
unspecified Enterobacter spp.,
unspecified Citrobacter spp.,
Proteus mirabilis,
Staphylococcus aureus,
Streptococcus faecalis,
Pseudomonas aeruginosa,
The treatment of adults with gonococcal urethritis, or cervicitis due to penicillinase-producing and non-penicillinase-producing Neisseria gonorrhoeae.
Appropriate culture and susceptibility studies should be carried out prior to initiation of therapy with NOROXIN® (norfloxacin) and if clinically indicated during treatment. Therapy may be initiated before obtaining results of these tests (see
MICROBIOLOGY), however, modification of such treatment may be required once the results become available.
CONTRAINDICATIONS
NOROXIN® (norfloxacin) is contraindicated in patients with known hypersensitivity to norfloxacin, to any component of this product or to other quinolone antibacterial agents.
WARNINGS
The safety of NOROXIN® (norfloxacin) in children is unknown. NOROXIN® should not be given to patients in whom epiphyseal closure has not occurred. In two animal species (dogs and rabbits) in which norfloxacin was administered to young animals, lameness and lesions (i.e., blister formation and eventual erosion) of the articular cartilage of the weight bearing joints were observed. In young dogs this occurred following a single dose several times the recommended human dose. These changes were not observed in dogs 6 months of age or older. Similar changes in animals have been observed with other structurally related drugs.
NOROXIN® should be used with caution in individuals with a history of convulsions or known factors that predispose to seizures. Convulsions have been reported rarely in patients receiving NOROXIN®; however, a causal relationship to NOROXIN® has not been established.
The safety of use of NOROXIN® in the treatment of infections in pregnant women is not established.
PRECAUTIONS
General
NOROXIN® (norfloxacin) should be used with caution in patients with a history of convulsions.
During therapy with NOROXIN®, patients should be reminded to drink sufficient amount of fluids to maintain adequate hydration in order to avoid possible development of crystalluria.
As with other quinolones, tendinitis and/or tendon rupture have been observed rarely in patients taking NOROXIN®, especially when corticosteroids are taken concomitantly. If a patient develops symptoms of tendinitis and/or tendon rupture,
NOROXIN® should be discontinued immediately and the patient advised to seek appropriate medical management.
Rarely, hemolytic reactions have been reported in patients with latent or actual defects in glucose-6-phosphate dehydrogenase activity who take quinolone antibacterial agents, including NOROXIN® (see ADVERSE REACTIONS).
Photosensitivity reactions have been observed in patients exposed to sunlight while receiving quinolone antibiotics. While taking NOROXIN®, excessive exposure to sunlight should be avoided and therapy discontinued if photosensitivity should occur.
Quinolones, including norfloxacin, may exacerbate the signs of myasthenia gravis and lead to life threatening weakness of the respiratory muscles. Caution should be exercised when using quinolones, including NOROXIN®, in patients with myasthenia gravis (see ADVERSE REACTIONS).
Some quinolones have been associated with prolongation of the QT interval on the electrocardiogram and infrequent cases of arrhythmia. During post-marketing surveillance, extremely rare cases of torsades de pointes, have been reported in patients taking norfloxacin. These reports generally involve patients who had other concurrent medical conditions and the relationship to norfloxacin has not been established. Among drugs known to cause prolongation of the QT interval, the risk of arrhythmias may be reduced by avoiding use in the presence of hypokalemia, significant bradycardia, or concurrent treatment with class Ia or class III antiarrhythmic agents.
Use in Obstetrics
The safety of use of NOROXIN® in the treatment of infections in pregnant women is not established; consider its use only if the anticipated benefits to the mother justifies the potential risks to the fetus. Following a single dose of 200 mg norfloxacin concentrations in umbilical cord serum ranged from non detectable levels to 0.5 mg/L and in amniotic fluid from non detectable levels to 0.92 mg/L.
The pharmacokinetics of norfloxacin in pregnant patients have not been investigated.
Reproduction studies have been carried out in the mouse, rat, rabbit and monkey. Norfloxacin did not show any teratogenic effects in these studies. In the monkey, however, an increased incidence of embryonic loss has been observed at a dosage of 10 times the human dose which result in peak plasma levels approximately 2 to 3 times that in humans. In the rabbit, embryonic loss was observed when norfloxacin was given by the oral route but not by the subcutaneous route. The clinical significance of the study results observed in rabbits and monkeys is not known (see TOXICOLOGY).
Nursing Mothers
Norfloxacin was not detected in human milk following a single 200 mg dose.
However, because this dose was low (half the recommended single dose) and as many drugs are secreted in human milk, caution should be exercised if
NOROXIN® is to be administered to a nursing woman.
Elderly
Alterations in dosage are not recommended (see DOSAGE AND
ADMINISTRATION and HUMAN PHARMACOLOGY). When NOROXIN® was administered to 4 females and 2 males, 67 to 74 years old, with normal renal function for their age, [i.e., creatinine clearance of 1.52 mL ± 0.2 mL/s/1.73 m2
(91±14 mL/min/1.73 m2)], the plasma half-life of the drug was only slightly prolonged.
Drug Interactions
Since urinary excretion of norfloxacin is diminished by concomitant administration of probenecid, NOROXIN® should not be administered concomitantly with probenecid.
Elevated plasma levels of theophylline have been reported with concomitant quinolone use. There have been rare reports of theophylline-related adverse reactions in patients on concomitant therapy with NOROXIN® and theophylline.
Therefore, monitoring of theophylline plasma levels should be considered and dosage of theophylline adjusted as required.
Elevated serum levels of cyclosporine have been reported with concomitant use with NOROXIN®. Therefore, cyclosporine serum levels should be monitored and appropriate cyclosporine dosage adjustments made when these drugs are used concomitantly.
NOROXIN® may enhance the effects of the oral anticoagulant warfarin or its derivatives. When these products are administered concomitantly, prothrombin time or other suitable coagulation tests should be closely monitored.
The concomitant administration of quinolones including norfloxacin with glyburide
(a sulfonylurea agent) has, on rare occasions, resulted in severe hypoglycemia.
Therefore, monitoring of blood glucose is recommended when these agents are co-administered.
Multivitamins, products containing iron or zinc, antacids, sucralfate or didanosine
(Videx) should not be administered concomitantly with, or within two hours of, the administration of NOROXIN® because they may interfere with absorption resulting in lower serum and urine levels of norfloxacin.
NOROXIN® has been shown to interfere with the metabolism of caffeine. This may lead to reduced clearance of caffeine and a prolongation of its plasma half-life.
Antagonism has been demonstrated in vitro between NOROXIN® and nitrofurantoin.
Renal Impairment
Since norfloxacin is eliminated primarily by the kidney, NOROXIN® should be used with caution and at a reduced dosage in patients with impaired renal function (see DOSAGE AND ADMINISTRATION). NOROXIN® is not recommended for anuric patients.
There is insufficient data on which to have a dosage recommendation for the treatment of gonorrhea in patients with a creatinine clearance of 0.5 mL/s/1.73 m2 (30 mL/min/1.73 m2) or less.
ADVERSE REACTIONS
NOROXIN® (norfloxacin) is generally well tolerated. In controlled clinical trials involving 1,528 patients, the overall incidence of drug-related adverse reactions was approximately 3%. The following adverse reactions were reported:
Gastrointestinal System Incidence (%)
Nausea 2.0 Dyspepsia 0.3 Flatulence 0.3 Heartburn 0.3 Abdominal pain 0.3 Vomiting 0.2 Diarrhea 0.2 Anorexia 0.1
Nervous System
Headache 1.6 Dizziness/Lightheadedness 1.2 Drowsiness <1.0 Mood alterations <1.0 Anxiety disorders 2 cases Depression 4 cases Disorientation 1 case Dream abnormalities 1 case Euphoria 2 cases Explosive personality disorder 1 case Hallucinations 1 case Irritability 1 case Nervousness 2 cases
Paresthesia <1.0 Visual disturbances <0.1 Epiphora 1 case Insomnia <0.4
Musculoskeletal System
Tendinitis 0.1 Arthralgia 0.1
Hypersensitivity Reactions
Rash 0.4 Erythema 0.2 Urticaria 0.1 Pruritus 0.1
The following additional adverse reactions have been reported since the drug was marketed:
Musculoskeletal System
Tendon rupture
Exacerbation of myasthenia gravis
Elevated creatine kinase (CK)
Body as a Whole/Site Unspecific
Asthenia/fatigue
Hypersensitivity Reactions
Anaphylaxis
Angioedema
Dyspnea
Vasculitis
Urticaria
Arthritis
Myalgia
Interstitial nephritis
Ocular
Conjunctivitis
Eye pain/irritation
Skin
Photosensitivity
Stevens-Johnson syndrome Toxic epidermal necrolysis Exfoliative dermatitis
Erythema multiforme
Pruritus
Gastrointestinal
Constipation
Flatulence
Pseudomembranous colitis Pancreatitis (rare)
Hepatitis, jaundice, including cholestatic jaundice
Nervous System/Psychiatric
Convulsions
Confusion
Paresthesia
Polyneuropathy including Guillain-Barré syndrome Psychic disturbances including psychotic reactions Somnolence
Tremors
Myoclonus
Hematologic
Hemolytic anemia
Thrombocytopenia
Renal Function
Renal Failure
Special Senses
Tinnitus
Dysgeusia
Visual Disturbances
Genitourinary
Vaginal candidiasis
Laboratory
Abnormal adverse reactions observed rarely in clinical trials include leukopenia, eosinophilia, neutropenia, proteinuria and elevation of ALAT (SGPT), ASAT
(SGOT), alkaline phosphatase, bilirubin, increased BUN, serum creatinine, and
LDH, and decreased hematocrit.
On very rare occasions,the following have been reported:
Hypertonia
Dyspnea
Ataxia
Dysarthria
Dysphasia
Hemophthalmia
Nystagmus
Periorbital erythema
Fever
Dry mouth
Transient hearing loss
Others
Although the following adverse reactions were not observed in these clinical trials with NOROXIN®, they have been reported following treatment with other quinolone antibacterial agents:
- hemolytic anemia in patients with latent or actual defects in glucose-6-phosphate dehydrogenase (G6PD) activity
- restlessness
- bullae
- palpitation
- soreness of the gums
- joint stiffness
- swelling of the extremities
- metallic taste
- toxic psychosis (rare)
- perineal burning
- vertigo
- edema
- cholestasis
- metabolic acidosis
- (signs and symptoms of increased intracranial pressure in infants and children which usually disappeared rapidly with no sequelae when treatment was discontinued)
SYMPTOMS AND TREATMENT OF OVERDOSAGE
There has not been any case of overdose with NOROXIN® (norfloxacin) reported to date; consequently, neither the signs nor the symptoms of overdosage have been identified.
In the event of recent acute overdose, the stomach should be emptied by inducing vomiting or by gastric lavage, and the patient carefully observed and given symptomatic and supportive treatment. Adequate hydration should be maintained to avoid the possible development of crystalluria. Norfloxacin is not dialyzable.
DOSAGE AND ADMINISTRATION
Adults:
The recommended dosage of NOROXIN® (norfloxacin) for urinary tract infections is one 400 mg tablet twice a day taken with a glass of water at least one hour before, or two hours after a meal or milk ingestion for 7-10 days.
For women with uncomplicated acute cystitis, the duration of therapy can be reduced to three (3) days.
For adults with gonococcal urethritis or cervicitis, the recommended dosage of
NOROXIN® is two 400 mg tablets (800 mg) given as a single dose.
Elderly:
The recommended dosage of NOROXIN® in elderly patients with normal renal function for their age is the same as given for adults above.
Impaired Renal Function:
NOROXIN® may be used in the treatment of patients with renal insufficiency who do not require hemodialysis.
In patients with a glomerular filtration rate of less than 0.50 mL/s/1.73 m2 (30 mL/min/1.73 m2) but greater than 0.11 mL/s/1.73 m2 (6.6 mL/min/1.73 m2) the recommended dose is one 400 mg tablet once daily (see PRECAUTIONS).
When only the serum creatinine level is available, the following formula (based on sex, weight, and age of the patient) may be used to convert this value into creatinine clearance. The serum creatinine should represent a steady state of renal function.
Males: Weight (kg) x (140 - age)
72 x serum creatinine (mg/100 mL)
Females: 0.85 x above value
To convert to international units multiply result by 0.01667
The administration of NOROXIN® to anuric patients is not recommended.
Children:
The safety and efficacy of NOROXIN® in prepubertal children have not been established. NOROXIN® should not be used in patients in whom epiphyseal closure has not occurred (see WARNINGS).
PHARMACEUTICAL INFORMATION
I. DRUG SUBSTANCE
Proper name: norfloxacin
Chemical name: 1-ethyl-6-fluoro-1,4 dihydro-4-oxo-7-(1- piperazinyl)-3-quinoline carboxylic acid.
Structural formula: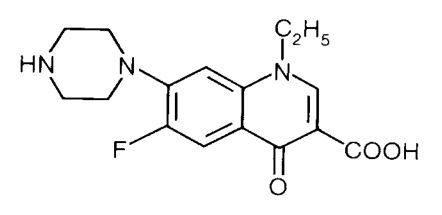
Molecular formula:C16H18FN303
Molecular weight: 319.34
Description: Norfloxacin is an odourless, white to pale yellow crystalline powder with a bitter taste and a melting point of 220-224°C. It is freely soluble in glacial acetic acid; sparingly soluble in dichloromethane; slightly soluble in acetone and chloroform; very slightly soluble in ethanol, methanol, ethyl acetate and benzene; and practically insoluble in water. Solubility in water is minimal between pH 6.0 to 10. Dissociation constants are: pKa1 =
6.3 and pKa2 = 8.8.
II. COMPOSITION
Each tablet contains the following non-medicinal ingredients: carnauba wax, croscarmellose sodium, hydroxypropyl cellulose, hydroxypropyl methylcellulose, magnesium stearate, microcrystalline cellulose, titanium dioxide, and red ferric oxide.
III. STABILITY AND STORAGE RECOMMENDATIONS
Store tablets at 15° - 30°C in tightly closed containers, protected from heat, moisture and direct light.
AVAILABILITY OF DOSAGE FORMS
NOROXIN® (norfloxacin tablets, USP) 400 mg are oval shaped, dark pink, film coated compressed tablets engraved “NOROXIN” on one side and “MSD 705" on the other. Available in bottles of 30 tablets.
INFORMATION FOR THE PATIENT
NOROXIN® Tablets
NOROXIN® is the brandname of Merck Frosst Canada Ltd. for the substance norfloxacin, available only on prescription from your physician. Norfloxacin is one of a group of medicines known as antibacterials. Antibacterials are used to treat infections caused by bacteria or germs; norfloxacin works against a large variety of species of bacteria, killing them or preventing them from developing.
Norfloxacin has been prescribed by your physician to treat an infection of the urogenital tract.
Remember: - This medicine is prescribed for the particular infection you have at this time. Do not give to other people, nor use this for other infections.
Keep all medicines out of the reach of children.
Read the following information carefully. If you need any explanations, or further information, ask your physician or pharmacist.
BEFORE TAKING THIS MEDICINE
This medicine may not be suitable for certain people. So, tell your physician if you think any of the following applies to you:
C You have previously taken norfloxacin or any related medicines, example, ciprofloxacin (Cipro) or nalidixic acid (NegGram), and were allergic, or had reacted badly to it.
C You suffer from kidney disease.
C You have any heart rhythm problems.
C You have ever suffered from convulsions.
C You are pregnant or intend to become pregnant or are breast-feeding or intend to breast-feed.
C Inform your physician if you are taking any of the following medications:
probenecid, nitrofurantoin, theophylline, cyclosporine, blood thinning medicines, glyburide (a sulfonylurea agent), didanosine, multivitamins or products containing iron, zinc, caffeine.
C Also inform your physician if you are taking any other medications
(prescription or non-prescription drugs).
This medicine is not recommended for children before puberty.
PROPER USE OF THIS MEDICINE
C Take this medicine exactly as your physician ordered for the specified number of days. Do not stop even if you feel better. Stopping too soon might bring on your symptoms again.
C It is best to take the tablet one hour before, or two hours after a meal or milk ingestion, with a full glass of water. It is good to drink plenty of liquids
- water or juice - every day, unless your physician has told you otherwise.
NOROXIN® should not be taken within two hours of taking iron, zinc supplements or multivitamins containing them.
C Sucralfate (Sulcrate), antacids (such as Diovol, Maalox or Amphojel), and didanosine (Videx) may interact with this medicine. If you have to take these medications, take them at least two to three hours before or after you take norfloxacin.
C If you forget to take a dose, take the recommended dose next time, as scheduled. Do not double the dose to make up. If you happen to take too many tablets by accident, contact your physician or pharmacist as soon as possible.
C If you develop any new medical problem while using this medicine, or you wish to begin using any other medicine, on prescription or not, check with your physician or pharmacist.
C Store your tablets at 15°-30°C in a tightly-closed container, away from heat and direct light, and out of damp places such as the bathroom or kitchen.
SIDE EFFECTS OF THIS MEDICINE - AND WHAT YOU SHOULD DO
Along with its intended action, any medication, including norfloxacin, may cause side effects. Most people do not have any problem when taking this medicine;
but if you notice any of the following effects, check with your physician or pharmacist as soon as possible:
C Dizziness, headache
C If you experience any of the above effects, or visual problems, avoid driving and any other activity or job that requires alertness, coordination or good vision.
Other possible effects which occur less commonly are: confusion, convulsions
(seizures), swollen or inflamed joints, abdominal or stomach pain with:
indigestion, gas, nausea, vomiting, diarrhea or loss of appetite; heartburn, rash, drowsiness and trouble sleeping.
STOP TAKING NOROXIN® AND CONTACT YOUR DOCTOR IMMEDIATELY IN
ANY OF THE FOLLOWING CASES:
If you develop allergic reactions such as swelling of the face, lips and/or throat
(with difficulty in breathing or swallowing), or hives;
If you develop skin reactions, including severe reaction to sunlight, such as rash, redness or increased sensitivity of skin or eyes to sunlight, swelling or blistering.
Stay out of direct sunlight, wear protective clothing and use a sunblock preparation.
If you develop pain in your tendons (tendinitis, tendon rupture);
If you experience any worsening of your myasthenia gravis symptoms;
If you develop any signs of mental disturbances, including mood changes such as anxiety or depression.
Some people may have other reactions. If you notice any unusual effect, check with your physician or pharmacist.
INGREDIENTS
Active ingredient: Each tablet of NOROXIN® contains 400 mg of norfloxacin.
Non-medicinal ingredients: carnauba wax, croscarmellose sodium, hydroxypropyl cellulose, hydroxypropyl methylcellulose, magnesium stearate, microcrystalline cellulose, titanium dioxide, and red ferric oxide.
MICROBIOLOGY
The in vitro activity of norfloxacin against clinical isolates of gram-positive and gram-negative aerobic bacteria is shown in Table 1. Susceptibility was determined by both agar and broth dilution tests, pH 7.1-7.4, using inoculum sizes ranging from 104 to 105 colony-forming units (cfu) per mL. Norfloxacin lacks useful activity against Actinomyces spp., Fusobacterium spp.,
Bacteroides spp., and Clostridium spp., other than C. perfringens.
The minimal inhibitory concentrations (MICs) of norfloxacin against aerobic bacteria are not significantly affected by culture medium composition or by changes in inoculum size in the range 103 to 10 6 cfu/spot (Table 2). In one study with 37 enterobacteria in Mueller-Hinton agar, increases in MIC values of norfloxacin at 108 cfu/spot were 2- to 4-fold higher than at 106 cfu/spot.
MICs of 4- to 33-fold higher were seen when representative enterobacteria were tested simultaneously in Diagnostic Sensitivity Test (DST) agar at pH 5.5 (MIC range = 0.12 to 32 mg/L), and at pH 7.2 (MIC = 0.015 to 4). This reduction in antibacterial activity suggests a pH effect (Table 2). In pooled human urine agar at pH 6.5 the observed MICs ranged from 0.06 to 16 mg/L. The magnesium content of urine could account for the reduced activity of norfloxacin and other quinolones in pooled human urine agar.
Generally, minimal bactericidal concentrations (MBCs) for norfloxacin are 1 to 4 times the MICs against susceptible bacteria. At these concentrations, norfloxacin is bactericidal, even with bacteria in their stationary phase of growth.
TABLE 1
CUMULATIVE PERCENT OF STRAINS INHIBITED AT THE INDICATED CONCENTRATIONS OF NORFLOXACIN
(mg/L)
Organism No./Strains 0.002 0.004 0.008 0.016 0.03 0.06 0.125 0.25 0.5 1 2 4 8 16 32 64 128
Achromobacter xylosoxidans (30) 3 7 13 37 60 73 Acinetobacter calcoaceticus (122) 1 7 20 38 62 91 96 100 Alcaligenes faecalis (23) 4 9 22 70 91 Citrobacter freundii (27) 26 48 74 93 96 100
Citrobacter spp. (15) 60 80 87 100 Enterobacter cloacae (76) 3 28 50 92 96 97 100 Enterobacter spp. (67) 33 55 87 91 96 97 100 Escherichia coli (417) 0.5 47 77 93 95 97 99 99 100 Klebsiella pneumoniae (50) 6 30 64 84 88 94 98 100 Klebsiella spp. (138) 24 56 77 84 95 99 99 100 Morganella morganii (52) 2 25 79 87 94 100 Neisseria gonorrhoeae (589)* 0.5 2 14 56 82 95 99 99 99 100 Proteus mirabilis (115) 51 63 74 93 100
Proteus vulgaris (58) 10 26 67 93 98 100 Proteus spp., indole + (10) 90 100
Proteus spp. (27) 52 93 100
Providencia rettgeri (111) 10 23 43 66 74 80 85 87 93 100 Providencia stuartii (16) 6 32 63 76 82 88 94 100 Providencia spp. (20) 80 85 95 95 100 Pseudomonas aeruginosa (245) 1 8 36 64 84 92 98 100 Pseudomonas cepacia (17) 6 71 100 Pseudomonas maltophilia (43) 2 9 49 84 95 100 Pseudomonas spp. (112) 10 12 58 81 86 90 96 99 100 Salmonella spp. (11) 55 91 100
Serratia marcescens (87) 6 44 67 79 85 90 93 99 100 Serratia spp. (20) 15 95 100
Shigella spp. (3) 100x
Staphylococcus aureus (111) 1 2 8 42 76 95 99 100 Staphylococcus epidermidis (75) 3 15 41 81 95 97 100 Staphylococcus saprophyticus (15) 13 13 87 100 Streptococcus agalactiae (10) 10 90 100 Streptococcus bovis (15) 20 20 33 53 80 87 100 Streptococcus faecalis (67) 3 52 91 100 Ureaplasma urealyticum (20) 15 50 90 100
* Includes 303 penicillinase-producing strains.
x Only three strains.
TABLE 2
EFFECT OF CULTURE MEDIUM COMPOSITION, pH, AND INOCULUM SIZE
ON ANTIBACTERIAL ACTIVITY OF NORFLOXACIN
MIC (mg/L)
Culture Mediuma pHb Inoculum Size (cfu)c
Organism/Strain TSA NA MH BHI 6 7 8 103 104 105 106
Staphylococcus aureus 2868 0.125 1.0 0.5 2 4 2 1 2 2 2 2 Escherichia coli 4391 0.03 0.06 0.06 0.06 1 0.06 0.06 0.03 0.03 0.03 0.03 Klebsiella pneumoniae 4005 0.06 0.06 0.06 0.06 ND ND ND 0.03 0.06 0.06 0.06 Escherichia coli 4392 0.25 0.25 0.25 0.5 8 0.5 0.25 0.5 0.25 0.25 0.5 Proteus mirabilis 3125 0.125 0.25 0.125 0.25 2 0.5 0.125 0.03 0.125 0.03 0.125 Serratia marcescens 2854 0.25 0.5 0.125 0.25 ND ND ND 0.125 0.125 0.06 0.125 Pseudomonas aeruginosa 2835 1 1 1 2 4 1.0 0.5 1 1 0.5 0.5 a TSA = trypticase soy agar (BBL); NA = nutrient agar (Difco); MH = Mueller Hinton agar (BBL); BHI = brain heart infusion (Difco); 106 cfu, pH 7.3
b Trypticase soy broth, 105 cfu/mL; ND = not done
c TSA (BBL), pH 7.3
Development of Resistance
A progressive increase in MIC of norfloxacin was demonstrated in five bacterial isolates by daily passage in subinhibitory concentrations of drug (Table 3).
Cross-resistance with other quinolone antibacterial agents has also been observed.
TABLE 3
COMPARATIVE NORFLOXACIN MIC OF PARENT AND
DERIVATIVE STRAINS
Norfloxacin MICs (mg/L)x
Organism/Strain Parent Strain R3 R5
Escherichia coli 2891 0.25 0.25 0.5 Klebsiella pneumoniae 4354 0.25 4 8 Proteus vulgaris 2829 0.25 0.5 4 Pseudomonas aeruginosa 2835 0.5 2 8 Staphylococcus aureus 4310 1 4 32 x Broth dilution test, inoculum 106 cfu/mL, trypticase soy broth.
R 3 = parent strain after 3 transfers.
R 5 = parent strain after 5 transfers.
The frequency with which resistant mutants arise varies among genera (Table 4), is greatest for P. aeruginosa and least for E. coli. In concentrations within two dilutions of the MIC, mutants of P. aeruginosa can be isolated rather frequently
(10-4 to 10-6), whereas those of E. coli are relatively uncommon (10-8). Increasing amounts of norfloxacin resulted in lower frequency of mutants (Table 4).
TABLE 4
FREQUENCY OF NORFLOXACIN-RESISTANT MUTANTS AMONG VARIOUS SPECIES OF ENTEROBACTERIACEAE, PSEUDOMONAS AERUGINOSA,
AND STAPHYLOCOCCUS AUREUS
Norfloxacin (mg/L)x
Organism/Strain 0.15 0.45 1.5
Escherichia coli 3773 1.1 x 10⁻⁸ ND ND Klebsiella oxytoca 4007 7.5 x 10⁻⁷ 1.5 x 10⁻⁷ ND Klebsiella pneumoniae 3972 2.2 x 10⁻⁷ 5.1 x 10⁻⁸ ND Enterobacter cloacae 301 2.3 x 10⁻⁸ ND ND Serratia marcescens 1581 4.6 x 10⁻⁷ 2.8 x 10⁻⁷ 1.3 x 10⁻⁹
Citrobacter freundii 2301 5.0 x 10⁻⁸ ND ND Proteus vulgaris J 17 1.2 x 10⁻⁶ ND ND Morganella morganii 2481 1.3 x 10⁻⁷ ND ND
Norfloxacin (mg/L)
Organism/Strain 2 8 24
Pseudomonas aeruginosa
Pseudomonas aeruginosa
Pseudomonas aeruginosa
Pseudomonas aeruginosa
Pseudomonas aeruginosa
Pseudomonas aeruginosa
Staphylococcus aureus
Staphylococcus aureus
Staphylococcus aureus
8.9 x 10⁻⁵
4.6 x 10⁻⁷
1.3 x 10⁻⁶
ND
4.6 x 10⁻⁴
5.4 x 10⁻⁷
ND
ND
4.1 x 10⁻⁹
7.3 x 10⁻⁹
ND ND ND ND ND ND ND ND
ND ND ND ND ND ND --
--
--x Overnight cultures in trypticase soy broth (Oxoid) were plated in 10- and 100-fold dilutions on
CLED agar (Oxoid) containing various concentrations of norfloxacin. ND = not detectable, frequency of resistant mutants < 10-10.
Nalidixic acid-resistant urinary isolates have been reported to demonstrate higher
MICs to norfloxacin than nalidixic acid-susceptible strains. In one study, nalidixic acid-resistant strains of enterobacteria (MIC $128 mg/L) showed an MIC range for norfloxacin of 0.06 - 16 mg/L (Table 5), or 4-16 times that for the nalidixic acid-susceptible strains tested (MIC range of 0.015 - 1.0 mg/L). Thus, induced resistance to nalidixic acid was associated with cross-resistance to norfloxacin.
TABLE 5
NORFLOXACIN MICs AGAINST NALIDIXIC ACID-SUSCEPTIBLE
AND-RESISTANT URINARY ENTEROBACTERIA
Organisms (# of strains tested) MIC Range (mg/L)x
Nalidixic acid-susceptiblea (59)
DST agar (Oxoid) (pH 7.2) 0.015 - 0.12 urine agar (pH 6.5) 0.06 - 1.0 Nalidixic acid-resistantb (44)
DST agar (pH 7.2) 0.06 - 4.0 urine agar (pH 6.5) 0.25 - 16.0
x The inoculum was applied with a multipoint inoculator, at approximately 102 cfu/spot. a MIC # 32 mg/L
b MIC $ 128 mg/L
Nalidixic acid-resistant organisms were inhibited by norfloxacin at a concentration of 16 mg/L or less for approximately 90% of the isolates investigated.
Norfloxacin is active in vitro against Enterobacteriaceae and nonfermentative gram-negative bacilli (Pseudomonas aeruginosa, Acinetobacter spp.) resistant to ampicillin, carbenicillin, trimethoprim and aminoglycosides. Antagonism has been demonstrated in vitro between norfloxacin and nitrofurantoin.
Susceptibility Testing
The standardized disc (1-3) susceptibility test [formerly, Kirby-Bauer] (using the
10 :g NOROXIN® disc of 6-mm diameter) or dilution susceptibility should be used.
Organisms should be tested with NOROXIN® discs, since norfloxacin has been shown by in vitro tests to be active against genera and strains of bacteria known to be or determined to be resistant when nalidixic acid discs are used.
TABLE 6
INTERPRETATION OF SUSCEPTIBILITY CRITERIA OF NORFLOXACIN (FOR MILD OR MODERATE INFECTIONS OF THE URINARY TRACT)
Zone Diameter
(10 :g norfloxacin disc)
(mm)
Approximate MIC Correlation
(:g/mL)
Susceptible
Intermediate
Resistant
$17
13 - 16
#12
#4
$16
These susceptibility criteria apply only to organisms isolated from urine (urinary tract).
There is a lack of clinical data to indicate if these same susceptibility criteria will be appropriate for the treatment of severe urinary tract infections suitable for oral therapy.
Proposed control limits for monitoring susceptibility tests are given in Table 7.
TABLE 7
CONTROL LIMITS FOR MONITORING NORFLOXACIN SUSCEPTIBILITY
TESTS
Organism Zone Diameter
(mm)
MIC (mg/L)
E. coli
ATCC* 25922 28-35 0.03 - 0.12 S. aureus
ATCC* 25923 17 - 28
S. aureus
ATCC* 29213 0.5 - 2.0 S. faecalis
ATCC* 29212 2.0 - 8.0 P. aeruginosa
ATCC* 27853 22 - 29 1.0 - 4.0
* Trademark of American Type Culture Collection
PHARMACOLOGY
Animal Pharmacology
Central Nervous System
Norfloxacin (0.1-1.0 g/kg p.o.) showed no significant influences on behavior or in various pharmacological tests of central nervous system activity in either mice or rats. Similarly, norfloxacin (10 mg/kg I.V.) produced no changes in the central nervous system of rabbits implanted with recording electrodes.
Peripheral Nervous System
Intravenous administration of norfloxacin (10 mg/kg) modestly reduced (30%)
contractions of the cat nictitating membrane elicited by both pre- and post-ganglionic nerve stimulation. Nerve stimulated contractions of the rabbit tibialis muscle, however, were unaffected by similar doses of norfloxacin.
Using in vitro smooth muscle preparations (guinea pig ileum and trachea), norfloxacin (100-300 mg/L) exhibited no anticholinergic, antiserotonergic or antihistaminergic activity. Likewise, norfloxacin did not alter the intrinsic muscle tone of the above preparations. In the isolated rat vas deferens, norfloxacin did alter responses to norepinephrine (slightly enhancing low concentrations and reducing high concentrations) though no alteration in epinephrine responses were observed in the guinea pig ileum and trachea. Norfloxacin (100 mg/L)
slightly reduced the amplitude of spontaneous contractions of the pregnant and nonpregnant rat uterus and rabbit ileum in vitro. However, in vivo norfloxacin (10 mg/kg I.V.) was without significant effect on spontaneous contractions of the stomach, intestine, bladder and uterus of rabbits. Similarly, gastrointestinal motility in mice was unaffected by 1.0 g/kg p.o. of norfloxacin.
Cardiovascular and Respiratory Systems
Norfloxacin (1.0 mg bolus) slightly increased (10 ± 3%) coronary flow and decreased heart rate (7 ± 2%) while modestly depressing contractile force (45 ±
4%) of isolated, perfused guinea pig hearts. In the isolated rabbit ear artery, a similar 1 mg bolus of norfloxacin produced a weak, transient decrease followed by an increase in blood flow. In vivo, norfloxacin administered intravenously increased by about 20% the respiratory rate in urethane anesthetized rabbits (30 mg of norfloxacin/kg) and barbiturate anesthetized dogs (10 mg of norfloxacin/kg). In these animals blood pressure tended to be reduced without significant changes in heart rate. The decrease of blood pressure in rabbits
(approximately 15%) and particularly dogs, was marked by considerable animal variation (3/6 dogs had decreases of 90-100 mmHg). Infusion of norfloxacin
(180 mg/hour I.V.) produced an elevation in the respiratory rate (60% increase)
with a decrease (about 10%) in blood pressure and no change in heart rate in dogs. In urethane anesthetized rats a reduction of about 20% in blood pressure was caused by norfloxacin (200 mg/kg I.V.). This reduction was inhibited by diphenhydramine but unaffected by atropine, propranolol or phentolamine. Oral administration of norfloxacin (1.0 g/kg) did not alter the blood pressure of unanesthetized rats.
Other Systems
Norfloxacin (1.0 g/kg p.o.) did not change blood sugar levels or coagulation time in rats and did not exhibit any antiinflammatory activity in rats. Similarly, norfloxacin (300 mg/kg p.o.) was unable to prevent cold stress-induced ulcers in rats. Subcutaneous administration of norfloxacin (200 mg/kg) significantly reduced by about 90% gastric acid secretion while doses as high as 1.0 g/kg p.o.
failed to alter bile secretion in rats. Norfloxacin (1.0 g/kg p.o.) significantly reduced urinary volume (30% decrease) over 24 hours and reduced urinary Na+ excretion (ca. 25%) and significantly increased urinary K+ excretion (ca. 30%)
over this time period. None of these effects were observed at doses of
100 mg/kg p.o.
Animal Pharmacokinetics
The absorption, distribution, and excretion of norfloxacin has been studied in rats, dogs, monkeys, mice, and rabbits. Absorption is rapid in all species following oral administration, ranging from 10-12% in rats, mice and rabbits to 20-
25% in monkeys and 70% in beagle dogs. Serum levels of norfloxacin measured for 0.5 to 4 hours after oral drug administration to monkeys (25 mg/kg) ranged from 0.3 to 2.35 :g/mL. In rats, dogs, and monkeys, 8%, 39%, and 17% of respective oral doses of norfloxacin was excreted in urine, chiefly as unchanged drug (>75%), but also as various combinations of six metabolites, all with modifications in the piperazine ring.
Human Pharmacology
Pharmacokinetics
In fifteen healthy fasting male volunteers aged 22 to 52 years (mean age: 34.1 ±
9.2 years), the mean peak serum concentrations of norfloxacin was 0.8 ± 0.3
(0.4-1.5) and 1.5 ± 0.6 (0.6-2.7) mg/L occurring within 1-1.5 hours of oral
administration of 200 mg and 400 mg doses, respectively (see Figure 1).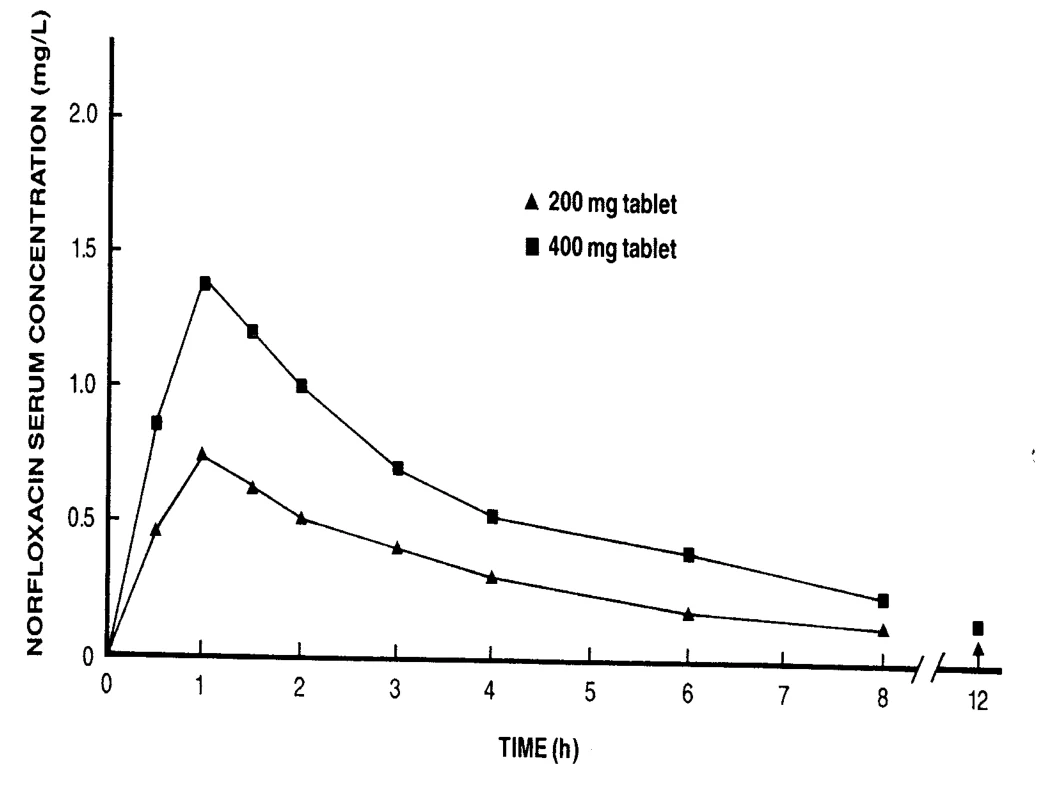
FIGURE 1 Mean norfloxacin serum concentrations after single oral doses The mean elimination half-life of norfloxacin was approximately 3 hours
(2.3 - 4.5). Therefore, as was noted in another group of twenty-six healthy male
(23) and female (3) volunteers aged 19 to 50 years (mean age: 28.6
± 9.1 years), norfloxacin regimens of 400 mg given every 12 hours produced
slight accumulation (see Figure 2).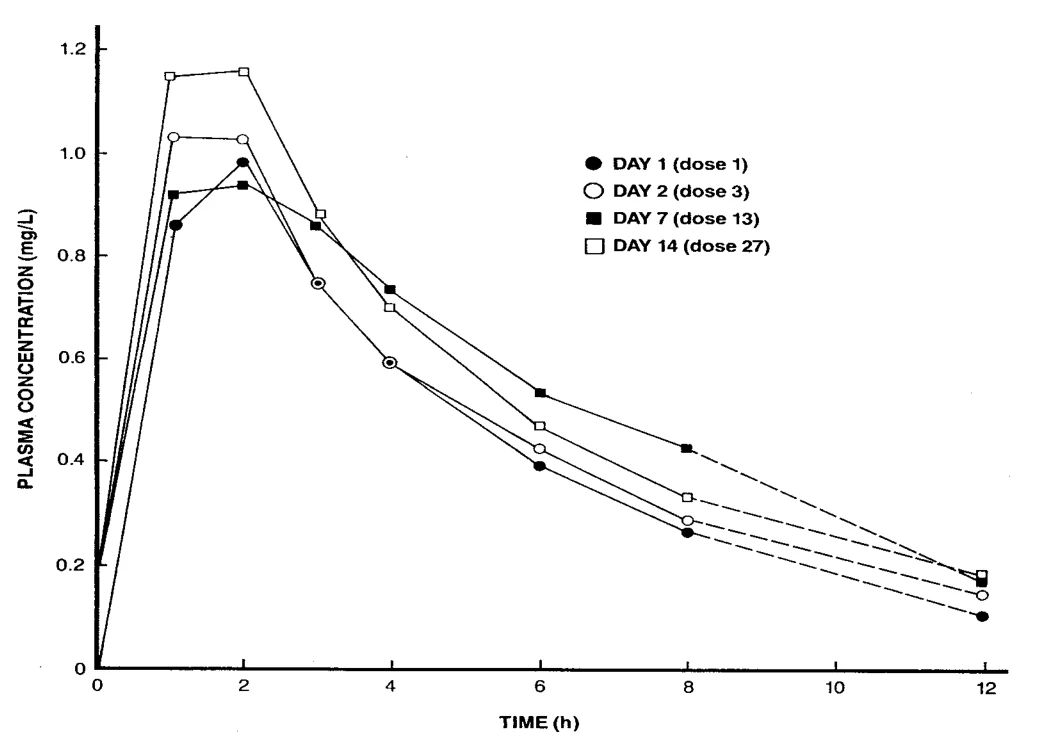
FIGURE 2 Mean norfloxacin plasma concentrations after 400 mg doses given every 12 hours.
Theoretically it could be expected that steady state concentrations of norfloxacin will be attained after 2 days of recommended dosage.
Pharmacokinetic information for healthy normal volunteers is given in Table 9. Excretion and Metabolism:
Following oral administration to fifteen healthy fasting male volunteers, aged 22 to 52 years (mean age: 34.1 ± 9.2 years), 25%-30% of a norfloxacin dose was recovered unchanged in urine within 48 hours (see Table 8).
TABLE 8
MEAN URINARY EXCRETION OF NORFLOXACIN
Hours After Administration
0-1 1-2 2-3 3-4 4-6 6-8 8-12 12-24 24-48 Total
Urine Concentration, :g/mL (±S.D.)
200 mg dose 37.7
(31.3)
139.1
(159.9)
65.7
(88.3)
44.5
(54.8)
19.1
(10.7)
19.2
(9.9)
16.5
(10.5)
7.3 (6.4)
1.0 (1.7)
--
400 mg dose 138.6
(206.0)
392.7
(302.0)
244.6
(300.9)
141.0
(182.9)
57.0
(60.5)
42.2
(26.4)
36.0
(24.1)
13.7 (9.9)
1.5 (2.0)
--
400 mg dose
elderly
100.6
(100.8)
154.1
(85.1)
148.3
(74.0)
67.8
(77.5)
101.8
(59.5)
43.0
(23.1)
30.5
(11.0)
12.8 (7.0)
-- --
Amount Excreted, mg (±S.D.)
200 mg dose 3.2
(2.4)
14.2
(6.6)
8.2
(2.6)
5.0
(2.0)
6.5
(3.7)
3.9
(1.6)
5.0
(3.3)
5.3 (3.2)
0.9 (1.3)
52.2 (18.6)
400 mg dose 7.5
(6.4)
22.6
(9.9)
19.7
(12.9)
12.5
(6.6)
14.2
(6.4)
8.8
(3.4)
10.2
(4.3)
8.3 (4.3)
1.3 (1.8)
105.1 (36.2)
400 mg dose
elderly
9.0
(3.3)
19.0
(9.0)
16.0
(9.0)
6.3
(3.7)
8.7
(5.9)
8.3
(7.1)
8.7
(4.2)
7.1 (3.2)
-- 83.2
(31.6) During the same period of time, an additional 8-10% of the dose is recovered as six metabolites with modifications on the piperazine ring. The two major metabolites are the 3-oxo-piperazinyl derivative and the 7-ethylenediamine derivative. The 3-oxo-piperazinyl predominates and no glucuronide conjugates were detected. Norfloxacin and these metabolites were detected in bile. The concentration of norfloxacin in bile was 5 :g/mL collected 1-2 hours after oral administration of a 200 mg dose to one patient with choledocholithiasis. A similar distribution ratio of the same six metabolites was in both bile and urine. These data suggest that 30-40% of an oral dose of norfloxacin is absorbed. After a single 400 mg dose of NOROXIN® (norfloxacin), mean antimicrobial activities equivalent to 164 (±202), 338 (±220), 632 (±688), and 126 (±123) :g of norfloxacin/g of feces were recovered over 0-12, 12-24, and 24-36, and 36-48 hours, respectively.
Renal excretion of norfloxacin occurs by both glomerular filtration and tubular secretion as evidenced by the high rate of renal clearance 4.58±1.18 mL/s
(range: 2.68 - 7.07) [275±71 mL/min (range: 161 - 424)]. Two to three hours after a single 400 mg dose, mean urinary concentrations of 200 mg/L or more were obtained in the urine. In healthy volunteers, mean urinary concentrations of norfloxacin remain above 30 mg/L for at least 12 hours following a 400 mg dose
(see Table 8).
Factors Influencing the Pharmacokinetics:
Food
Food slightly reduces the absorption of norfloxacin as evidenced by a reduction of approximately 30% in peak serum concentration and of approximately 35% in peak urine concentration.
Age (elderly)
In 4 females and 2 males, 67 to 74 years old with normal renal function for their age i.e., creatinine clearance 1.52±0.23 mL/s/1.73 m2 (91±14 mL/min/1.73 m2), norfloxacin was eliminated more slowly because of their slightly decreased renal function causing a small increase in plasma concentrations of drug (see
Figure 3).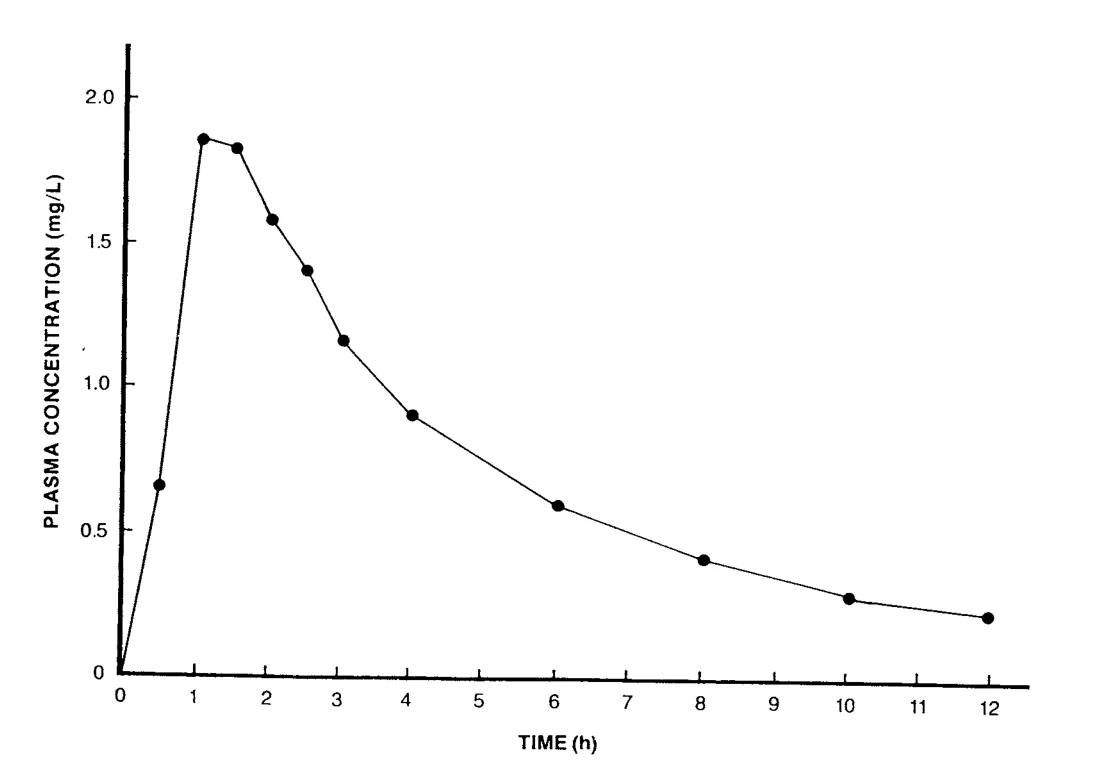
Figure 3. Mean norfloxacin plasma concentrations following a single 400 mg dose given to healthy elderly subjects. Approximately 22% of the norfloxacin dose was recovered unchanged in urine
(see Table 8). The renal clearance of drug was 2.57 mL/s (154 mL/min). The maximum plasma concentration of norfloxacin was approximately 2 mg/L, occurring 1.3 hours after drug administration. The plasma half-life of norfloxacin in these individuals was 4 hours (see Table 9).
Table 9
COMPARISON OF PHARMACOKINETIC PARAMETERS BETWEEN HEALTHY ELDERLY VOLUNTEERS AND HEALTHY YOUNGER VOLUNTEERS FOLLOWING A SINGLE 400 MG ORAL DOSE
Parameter Elderly Volunteers Younger Volunteers
Cmax, mg/L 2.0 (± 0.8) 1.5 (± 0.6) Tmax, h 1.3 (± 0.4) 1.0 (± 0.4) Half-life, hx 3.9 3.2 Total (AUC), mg.h/L 9.8 (±2.8) 6.6 (± 3.3) Renal clearance, mL/min 154 (± 16) 299 (± 95) Renal clearance, mL/s. 2.57(± 0.27) 4.98 (± 1.58) %-Dose Urinary Recovery 22(± 7) 27(± 9)
x Harmonic mean
Impaired renal function
Excretion of norfloxacin in patients with creatinine clearance (Ccr) greater than
0.50 mL/s/1.73 m2 (30 mL/min/1.73 m2), was similar to that of healthy volunteers.
In patients with Ccr less than 0.50 mL/s/1.73 m2 (30 mL/min/1.73 m2) but greater than 0.11 mL/s/1.73 m2 (6.6 mL/min/1.73 m2), less than 10% of an oral dose was excreted in urine. The mean elimination half-life of norfloxacin in serum increased to 6.5 hours in these patients (see Table 10 and Figure 4).
TABLE 10
MEAN PHARMACOKINETIC PARAMETERS FOR NORFLOXACIN FOLLOWING A SINGLE 400 MG ORAL DOSE IN HEALTHY VOLUNTEERS AND IN PATIENTS WITH VARYING
DEGREES OF RENAL INSUFFICIENCY
Parameter
Group Creatinine Clearan
ce
[mL/s/1.73 m2]
(mL/min/1.73 m2)
Cmax (mg/L) Tmax (h)
Half-
Lifex (h)
Total (AUC) (mg.h/L)
Renal Clearanc e
(mL/min)
%-Dose
Urinary Recovery
I [$1.5]
$90
1.51
(±0.56)
1.4
(±0.4)
3.47 6.94
(±2.73)
297.2
(±117.4)
28.2
(±12.8)
II [0.52-1.48]
31-89
1.91 (±0.71) 1.3
(±0.4)
3.38 9.53
(±2.47)
264.5
(±83.2)
35.3
(±9.2)
III [0.17-0.50]
10-30
1.70 (±0.43) 1.8
(±1.1)
6.57 24.01
(±13.49)
17.8
(±4.4)
6.7
(±4.1)
IV [0.11-0.15]
6.6-9
1.70 (±0.92) 1.8
(±1.2)
6.40 16.46
(±14.52)
14.7
(±8.4)
2.4
(±1.1)
x Harmonic mean
Figure 4 Mean norfloxacin serum concentrations following a single 400 mg dose given to healthy volunteers and to patients with varying degrees of renal insufficiency.
Probenecid
The 12-hour urinary excretion of norfloxacin following a 200 mg dose was diminished from 28% of the dose to 14% of the dose by the coadministration of probenecid.
Serum Protein Binding
At a serum concentration of 2.5 mg/L the human serum protein binding is 10-15%. Tissue Concentrations
Concurrent norfloxacin concentrations in serum, tissues and body fluids are given in Table 11.
TABLE 11
NORFLOXACIN CONCENTRATIONS IN HUMAN TISSUES AND BODY FLUIDS
Concentration (±S.D.)
Tissue/Fluid No. of
subjects
Dose of
norfloxacin
(mg)
Sampling time
(h after dose)
Tissue/Fluid
(mg/L or mg/kg)
Serum (:g/mL)
Liver 2 200 mg 2 h 3.40 0.10
1.66 0.52
Gall bladder 2 200 mg 2.5 h <0.2 -
0.48 -
Gall bladder bile 2 200 mg 2 h 0.15 0.10
4.46 0.52
20 400 mg 2 h 10.3 (± 2.7) 1.25 (± 0.3)
Bile in common 2 200 mg 2.5 h 0.41 -bile duct 4.19 -
20 400 mg 2 h 8.8 (± 1.4) 1.25 (± 0.3)
Bile 1 100 mg 4 h 3.16 0.65
6 h 5.68 0.48
3 400 mg 2 h 0.13 - 0.70 0.18 - 1.2
3 h 2.72 - 6.0 0.53 - 1.1 4 h 2.60 - 4.20 0.6 - 0.83 6 h 1.4 - 2.5 0.30 - 0.70
Prostate 15 800 mg+ 3 - 4 h 0.93 (± 0.66) 1.17 (± 0.55)
10 800 mgx 1 - 2 h <0.25 - 4.65 <0.25 - 5.30
Kidneyxx 3 800 mgx 2 h 16.2 4.30
3 h 15.1 4.00 6.5 h 3.9 0.32
+ One 400 mg tablet at time zero the evening before surgery and again 11h later.
x One 400 mg tablet given between 21h and 22h the night before surgery and a second 400 mg tablet one hour before surgery.
xx The serum levels in 2 out of 3 patients were higher than expected and consequently kidney concentrations may also have been higher than expected.
TOXICOLOGY
Acute Toxicology
SPECIES SEX ROUTE
LD50 mg/kg (95% confidence limits)
Mouse
Mouse
Mouse
Mouse
Mouse
Mouse
Mouse
Mouse
Male
Male
Male
Male
Female Female Female Female
p.o.
Subcutaneous Intramuscular Intravenous
p.o.
Subcutaneous Intramuscular Intravenous
>4,000
>1,500
470(405-545) 220(209-232)
>4,000
>1,500
480(429-538) 237(226-248) Rat
Rat
Rat
Rat
Rat
Rat
Rat
Rat
Male
Male
Male
Male
Female Female Female Female
p.o.
Subcutaneous Intramuscular Intravenous
p.o.
Subcutaneous Intramuscular Intravenous
>4,000
>1,500
> 500
270(233-313)
>4,000
>1,500
> 500
245(211-284)
The six metabolites were also tested orally for their acute toxicity in rats and mice. The LD50 values were estimated to be greater than 2,000 mg/kg.
Subacute Toxicity Studies
One month oral toxicity studies were carried out in rats (250, 500 and
1,000 mg/kg/day, 10 males and 10 females per group), dogs (50, 100 and
200 mg/kg/day, one male and one female per group; or 25, 50 and 100 mg/kg, b.i.d., 6 days per week, 3 males and 3 females per group) and monkeys (25, 50,
100 mg/kg, b.i.d., 6 days per week, 2 males per group). In all studies similar size groups served as controls and received sterile distilled water. A slight increase in urinary potassium excretion was seen in female rats dosed at
500 and 1,000 mg/kg/day. There was, however, no concurrent decrease in serum potassium level. A slight enlargement of cecum was observed in 3 of 10 male rats at 1000 mg/kg/day. Liver glucose-6-phosphatase activity was slightly increased at all dose levels in the dog study in which norfloxacin was given at doses of 25, 50 or 100 mg/kg b.i.d.
Chronic Toxicity Studies
Rat
A six-month oral toxicity study in rats at norfloxacin doses of 0, 125, 250 and
500 mg/kg/day (10 rats/sex/group) revealed only minimal effects as evidenced by slight body weight retardation in male rats in the 250 and 500 mg/kg/day groups.
A similar study was carried out in rats (15 rats/sex/group) at norfloxacin doses of
0, 50, 200 and 600 mg/kg/day orally. There was a slight, but not statistically significant, decrease in body weight gain at 600 mg/kg/day in males. In addition, crystalluria consisting of the dihydrate and the magnesium salt of norfloxacin occurred in rats from the 200 and 600 mg/kg/day groups. The crystalluria was most frequent in males given 600 mg/kg/day. A high incidence of cecal enlargement was seen at all dose levels. Gray feces were observed in all treated groups and a very slight but statistically significant decrease in serum proteins were observed in males dosed at 600 mg/kg/day.
Dog
Four chronic oral toxicity studies were performed to evaluate the potential toxicity of norfloxacin in dogs following chronic administration for 20 weeks to 13 months.
The doses used were: 0, 25, 50 and 100/200 mg/kg/day (the dose was increased due to lack of drug-induced effect, 6 days per week, 4 males and 4 females per group); 0, 50, 150 and 300 mg/kg/day (7 days per week, 3 males and 3 females per group); 0, 25, 50 and 100 mg/kg/day, (7 days per week, 1 male and 1 female per group); 0, 50, 100 and 150 mg/kg/day (7 days per week, 4 males and
4 females per group). Crystalluria was evident in one of these studies where dogs were given the drug at 50, 150 and 300 mg/kg/day for 26 weeks. The incidence was dose related. Four dogs, (1 and 3 in the 150 and 300 mg/kg/day dosage groups, respectively), were found dead or were sacrificed due to urinary obstruction from drug crystals. It was postulated that crystalluria in dogs and rats is the result of low solubility of norfloxacin in alkaline urine. This was supported by the observation of a significant decrease in the incidence of crystalluria and the absence of urinary obstruction in dogs in a separate study at 50, 150 and
300 mg/kg/day orally to 3 dogs/sex/group for three months where the urine was acidified by the administration of ammonium chloride. The pH after urine acidification was generally 6.0 or below whereas the urinary pH of dogs where drug crystals were formed was between 6.86 and 8.28.
Other frequently observed changes in the 150 and 300 mg/kg/day groups consisted of a dose-related incidence of emesis, grey or clay-coloured feces (due to unabsorbed drug) and retardation of body weight gain. There were also changes in the haematologic and serum biochemical parameters (leukocytosis, elevated serum urea nitrogen and creatinine) that are compatible with uremia and pyelonephritis secondary to intrarenal or urethral obstruction.
Reproduction Studies
Fertility
The effect of norfloxacin on fertility was assessed in male and female mice.
Norfloxacin was administered orally at dosage levels of 0, 125, 250,
500 mg/kg/day (20 per sex per group) for 61 days before mating and during mating to male mice and for 15 days before mating until the sixth day of pregnancy to female mice. There were no treatment-related effects on the reproductive performances of the adults or differences in growth and characteristics of the fetuses.
Teratology
Mice
In mice oral doses of 0, 125, 250 or 500 mg/kg/day (31 mice/group) given on days 6 to 15 of gestation did not have any adverse effect on the pregnant mother or F1 or F2 fetuses.
Rats
In rats, oral doses of 0, 50, 200 or 800 mg/kg/day (administered b.i.d. to
20 rats/group) given on days 6 to 17 of gestation did not adversely affect the progress or outcome of pregnancy.
Rabbits
In an oral teratology study, rabbits were given 0, 25, 50 or 100 mg/kg/day of norfloxacin orally (12 or 13 rabbits per group) from day 6 to 18 of gestation. In this study, rabbits in the 100 mg/kg/day group showed decreased activity, reduced appetite, diarrhea, and reduced body weight gain. Embryotoxicity (i.e., abortion and fetal resorption) was also observed at this dosage level. An additional study comparing the maternal and fetal toxicity of norfloxacin administered orally at doses of 100 mg/kg/day with that administered subcutaneously at doses of 20 mg/kg/day (which resulted in approximately 5-fold higher maximum plasma drug levels) was carried out. There was no evidence of embryotoxicity in the group that received norfloxacin at a dose of 20 mg/kg/day by the subcutaneous route. This suggested that the embryotoxicity of norfloxacin in rabbits did not correlate with drug levels in blood.
Monkeys
In an oral teratology study in cynomolgus monkeys, norfloxacin was given at doses of 0, 50, 100, 150 or 300/200 mg/kg/day (the dose was reduced because of emesis) in single or divided doses from days 20 to 50 of gestation. There were at least 10 female monkeys in each group. Doses of 200 mg/kg/day and greater were maternotoxic and produced vomiting, reduced appetite, and body weight loss. In the 150 and 300/200 mg/kg/day groups, 3 of 10 and 11 of 16 monkeys lost their embryos. There was no evidence of a teratogenic effect in surviving fetuses. Doses of 100 mg/kg/day did not result in any increase in embryonic losses relative to controls.
Gestation and Postnatal Development
The effect of norfloxacin during gestation and postnatal period was studied in mice at doses of 0, 125, 250 and 500 mg/kg/day (21 mice per group). Female mice were dosed orally from Day 15 of gestation to Day 21 postpartum. No significant difference was observed with newborn of the treated groups as compared to controls.
Mutagenicity
Norfloxacin was negative in a dominant lethal test in mice (300 or 800 mg/kg administered as a single dose), an in vivo chromosome aberration test in rats
(1000 mg/kg/day for 38 days) and hamsters (250 or 500 mg/kg, one dose), and various in vitro genotoxicity studies including an Ames test, chromosomal aberration test, sister chromatid exchange assay, unscheduled DNA synthesis assay and V-79 mammalian cell mutagenesis assay. Norfloxacin was weakly positive in a test for DNA repair (rec assay), however, this was considered to be of questionable biological significance since a more sensitive test for DNA repair
(V-79 mammalian cell mutagenesis assay) was negative.
Carcinogenicity
A 19-month chronic oral toxicity study was done in rats (50 per sex per group).
The rats were autopsied after a 12 to 14 week withdrawal period. Norfloxacin was given in the diet at 0.05 or 0.2% in the feed. The estimated drug intake was
18-35 mg/kg/day for the low dose group and 70-140 mg/kg/day for the high-dose group. No drug related neoplastic changes were reported as compared to control animals. The highest dose was below the maximum tolerated dose
(approximately 600 mg/kg/day).
Special Toxicity Studies
Arthropathy
Three to five month old dogs were treated orally with norfloxacin for seven days at doses of 0, 30, 60, 100, 250 or 500 mg/kg/day or for 99 days at a dose of 0 or
200 mg/kg/day (2 or 3 dogs per group). Similarly, 8-10 week old rabbits were treated orally for seven days at 0, 250 or 300 mg/kg/day or for 21 days at 0, 100 or 150 mg/kg/day (5-11 rabbits/group). Nalidixic acid (30, 60 and 100 mg/kg/day)
and pipemidic acid (30, 60, 100, 200 and 500 mg/kg/day) were used as positive controls. Clinical signs of lameness appeared from the second day in dogs given doses greater than 60 mg/kg/day of norfloxacin and persisted through the duration of the seven day study. Similar signs of lameness were seen in dogs given oral doses greater than 30 mg/kg/day of nalidixic acid and pipemidic acid.
No clinical signs of lameness were seen in rabbits treated with any of these test compounds. In dogs, lameness was associated with joint lesions that were characterized by increased amount of synovial fluid and blister formation and sometimes erosions on the articular cartilage. There was recovery from clinical signs within six to eight weeks after initiation of the study, but lesions remained.
In the rabbits, there was blister formation on the articular cartilage at doses of
250 mg/kg/day or greater for seven days. There were no clinical signs of lameness.
The arthropathogenic effects of norfloxacin were limited to young animals. There was no evidence of lameness or gross changes in the joints of dogs that were 8 to 10 months of age at the start of the study and given oral doses of norfloxacin up to 100 to 150 mg/kg/day for 22 weeks to 13 months.
Antigenicity
Antigenicity of norfloxacin was studied by examining its potential to induce delayed hypersensitivity and anaphylactic reaction in guinea pigs (0.8% and
0.5% respectively) and specific antibodies in rabbits (30 mg/mL - 1 mL,
2 injections). Norfloxacin elicited no delayed hypersensitivity reaction on the skin of guinea pigs. Anaphylactic reaction was not observed in guinea pigs sensitized with norfloxacin alone or a mixture of norfloxacin and Freund's complete adjuvant. Serum from guinea pigs sensitized with norfloxacin failed to induce passive cutaneous anaphylaxis in recipient guinea pigs. Specific antibodies against norfloxacin were not detected in sera of rabbits immunized with norfloxacin conjugated with bovine gammaglobulin and Freund's complete adjuvant.
Retina
No evidence of retinal toxicity was seen in cats given oral doses up to
200 mg/kg/day for two weeks as measured by electroretinogram and histopathology.
Auditory System
Norfloxacin administered to rats at a rate of 500 mg/kg/day orally for six months did not have any adverse effect on the auditory or vestibular function or on the histology of the organ of Corti.
REFERENCES
- 1.
Abiko T, Ishihama A, Ogawa N, Uchida H, Muragama S, Hirai K, Oomori
Y, Abe Y, Irikura T. Phase I. Study on AM-715. Chemotherapy (Tokyo) 1981;29(Suppl. 4):136-45.
- 2.
Barry AL, Jones RN. Cross-resistance among cinoxacin, ciprofloxacin,
DJ-6783, enoxacin, nalidixic acid, norfloxacin, and oxolinic acid after in vitro selection of resistant populations. Antimicrob Agents Chemother 1984;25:775-77.
- 3. Bauernfeind A, Petermuller C. In vitro activity of ciprofloxacin, norfloxacin and nalidixic acid. Eur J Clin Microbiol 1983;2:111-15.
- 4. Bergeron MG, Thabet M, Roy R, Lessard C, Foucault P. Norfloxacin penetration into human renal and prostatic tissues. Antimicrob Agents Chemother 1985;28:349-50.
- 5. Body BA, Fromtling RA, Shadomy S, Shadomy HJ. In vitro antibacterial activity of norfloxacin compared with eight other antimicrobial agents. Eur J Clin Microbiol 1983;2:230-34.
- 6. Bologna M, Vaggi L, Flammini D, Carlucci G, Forchetti CM. Norfloxacin in prostatitis: correlation between HPLC tissue concentrations and clinical results. Drugs Exp Clin Res 1985;11:95-100.
- 7. Boppano VK, Swanson BN. Determination of norfloxacin, a new nalidixic acid analog, in human serum and urine by high-performance liquid chromatography. Antimicrob Agents Chemother 1982;21:808-10.
- 8. Carver PL, Fekety R. The quinolones expanded choices and individual differences. Consultant 1988;28:59-67.
- 9. Corigliano BE, Appleman MD, Heseltine PNR, Leedom JM. Comparative in vitro activities of norfloxacin (MK-0366) and six commonly used antimicrobial agents against 199 urinary isolates showing various degrees of antibiotic resistance. Diagn Microbiol Infect Dis 1984;2:101-6.
- 10. Cullmann W, Stieglitz M, Baars B, Opferkuch W. Comparative evaluation of recently developed quinolone compounds -- with a note on the frequency of resistant mutants. Chemotherapy 1985;31:19-28.
- 11.
Davies BI, Maesen FPV. Drug interactions with quinolones. Rev Inf Dis
1989;II(Supp.5):S1083-90.
- 12. Downs J, Andriole VT, Ryan JL. In vitro activity of MK-0366 against clinical urinary pathogens including gentamicin-resistant Pseudomonas aeruginosa. Antimicrob Agents Chemother 1982;21:670-72. 13. Dubreuil L, Devos J, Romond C, Bryskier A. Susceptibility of obligate anaerobes to ofloxacin, pefloxacin, enoxacin, and norfloxacin. Pathol Biol (Paris) 1985;33:421-25.
- 14. Duckworth GJ, Williams JD. Frequency of appearance of resistant variants to norfloxacin and nalidixic acid. J Antimicrob Chemother 1984;13(Suppl. B):33-8.
- 15. Edwards DJ, Bowles SK, Svensson CK, Rybak MJ. Inhibition of drug metabolism by quinolone antibiotics. Clin Pharmacokinet 1988;15:194-204.
- 16. Ferguson J. Double blind placebo and ciprofloxacin controlled phototest study in the in vivo phototoxic potential of norfloxacin in normal volunteers. Photobiology Unit, Ninewells Hospital Dundee, Scotland. Feb 1990. Report on file, Merck Sharp & Dohme Research Laboratories.
- 17. Fromtling RA, Abruzzo GK, Gadebusch HH. In vitro effect of pH and glucose concentration on the antibacterial activity of norfloxacin in urine. Methods Find Exp Clin Pharmacol 1984;6:737-41.
- 18.
Gadebusch HH, Koupal LR, Celozzi E, Shungu DL, Bland J, Weissberger
J, Pelak B, Fisch E, Chang GK, Huber J. Norfloxacin (MK-0366, AM-715), a new orally-absorbed synthetic compound for the treatment of bacterial infections. Current Chemotherapy and Immunotherapy (Proceedings 12th ICC) 1982;Vol. I, 351-53.
- 19. Gadebusch HH, Shungu DL, Weinberg E, Chung SK. Comparison of the antibacterial activity of norfloxacin (MK-0366, AM-715), a new organic acid, with that of other orally absorbed chemotherapeutic agents. Infection 1982;10:41-4.
- 20.
Gilfillan EC, Pelak BA, Tutlane VK, Weissberger B, Gadebusch HH.
Interaction of norfloxacin with nine other antibacterial agents in vitro. Basic Microbiology Report, Merck Sharp & Dohme Research Laboratories, 27 October 1983.
- 21. Goto S, Ogawa M, Kaneko Y, Muto Y, Kuwahara S. The in vitro and in vivo antibacterial activities and serum levels of AM-715, a new quinolinecarboxylic acid. Chemotherapy (Tokyo) 1981;29(Suppl. 4):12-26.
- 22.
Greenwood D, Osman M, Goodwin J, Cowlishaw WA, Slack R.
Norfloxacin: Activity against urinary tract pathogens and factors influencing the emergence of resistance. J Antimicrob Chemother 1984;13:315-23.
- 23. Haase D, Urias B, Harding G, Ronald A. Comparative in vitro activity of norfloxacin against urinary tract pathogens. Eur J Clin Microbiol 1983;2:235-41.
- 24. Harder SS, Staib AH, Beer C, Papenburg A, Stille W, Shah PM. 4-quinolones inhibit biotransformation of caffeine. Eur J Clin Pharmacol 1988;35:651-59.
- 25. Husson MO, Izard D, Leclerc H. Comparative in vitro antibacterial activity of norfloxacin versus four other quinolone derivatives. Drugs Exp Clin Res 1984;10:315-19.
- 26. Irikura T, Suzuki H, Sugimoto T. Reproduction studies of AM-715 in mice, I. Fertility study, Chemotherapy (Tokyo) 1981;29(Suppl. 4):886-94.
- 27.
Irikura T, Suzuki H, Sugimoto T. Reproduction studies of AM-715, II.
Teratology Study, Chemotherapy (Tokyo) 1981;29(Suppl. 4):895-914.
- 28.
Irikura T, Suzuki H, Sugimoto T. Reproduction studies of AM-715 in
Mice, III. Perinatal and Post-natal study. Chemotherapy 1981;29(Suppl. 4):915-31.
- 29. Ito A, Hirai K, Inoue M, Koga H, Suzue S, Irikura T, Mitsuhashi S. In vitro antibacterial activity of AM-715, a new nalidixic acid analog. Antimicrob Agents Chemother 1980;17:103-8.
- 30.
Ito A, Shindo K, Matsumura E, Maruta I, Murohashi M, Suzuki C,
Fukushima K. Clinical evaluation on AM-715 in the field of internal medicine. Chemotherapy (Tokyo) 1981;29(Suppl.4): 284-92.
- 31. Jones RN, Barry AL. Norfloxacin (MK-0366; AM-715): In vitro activity and cross-resistance with other organic acids including quality control limits for disk diffusion testing. Diagn Microbiol Infect Dis 1983;1:165-72.
- 32.
Kato Y, Saitoh A, Ishikawa K, Uemura H, Odagaki E, Shinohara M.
Studies of AM-715, A new synthetic antibacterial agent. Chemotherapy (Tokyo) 1981;29(Suppl. 4):146-56.
- 33. Khan MY, Gruninger RP, Nelson SM, Klicker RE. Comparative in vitro activity of norfloxacin (MK-0366) and ten other oral antimicrobial agents against urinary bacterial isolates. Antimicrob Agents Chemother 1982;21:848-51.
- 34. King A, Warren C, Shannon K, Phillips I. In vitro antibacterial activity of norfloxacin (MK-0366). Antimicrob Agents Chemother 1982;21:604-7.
- 35.
Kiriyama T, Okada K, Okabe T, Okada Y, Nishibuchi S, Yoshida O. A
Phase II study of AM-715 on acute simple cystitis and complicated urinary tract infection. Chemotherapy (Tokyo) 1981;29(Suppl. 4):531-45. 36. Koga H, Itoh A, Murayama S, Suzue S, Irikura T. Structure-activity relationships of antibacterial 6, 7 - and 7, 8 - Disubstituted 1 - Alkyl - 1,4 -Dihydro - - Oxoquinoline - 3 - carboxylic acids. J Med Chem 1980;23:1358-63.
- 37. Leigh DA, Smith EC, Marriner J. Comparative study using norfloxacin and amoxycillin in the treatment of complicated urinary tract infections in geriatric patients. J Antimicrob Chemother 1984;13(Suppl. B):79-83.
- 38. Martin BK. An open study to determine the pharmacokinetics of a single dose of norfloxacin in the elderly. Nov 1984. Bios Ltd. Surrey, England. Report on file. Merck Sharp & Dohme Research Laboratories.
- 39. Matsuoka K, Eto K, Sakai Y, Yoshizumi O, Miyahara S. Clinical experience of AM-715 on urinary tract infection. Chemotherapy (Tokyo) 1981;29(Suppl. 4):622-30.
- 40.
Naide Y, Fujita T, Okishio N, Asano H, Tamai H, Yanaoka M, Suzuki K,
Nagakubo I, Moriguchi R, Mitsui H, Ogawa T, Ikeda N, Oda T, Hashimoto T, Kawakami T, Aoki S. Clinical and pharmacological evaluation of AM-715 for application to urogenital infections. Chemotherapy (Tokyo) 1981;29(Suppl. 4):475-96.
- 41.
Nakatsu H, Hatachi K, Fujii M, Nihira H, Masu C, Nakano H.
Fundamental and clinical studies of AM-715 in complicated urinary tract infections. Chemotherapy 1981;29(Suppl. 4):578-86.
- 42. National Committee for Clinical Laboratory Standards. Performance standards for antimicrobial disk susceptibility tests - Fourth edition approved standard, M2-A4. National Committee for Clinical Laboratory Standards, Villanova, PA. 1990;10(7).
- 43. National Committee for Clinical Laboratory Standards. Methods for dilution antimicrobial susceptibility tests for bacteria that grow aerobically. Second edition approved standard, M7-A2. National Committee for Clinical Laboratory Standards, Villanova, PA. 1990;10(8).
- 44.
Neu HC. Effects of cations upon the activity of quinolone agents. In:
Shah PM, ed. Quinolone Bulletin: Reports on gyrase inhibitors. M.I. Publications, Frankfurt, 1985.
- 45. Neu HC, Labthavikul P. In vitro activity of norfloxacin, a quinolinecarboxylic acid, compared with that of ß-lactams, aminoglycosides and trimethoprim. Antimicrob Agents Chemother 1982;22:23-7.
- 46.
Newsom SWB. The antimicrobial spectrum of norfloxacin. J Antimicrob
Chemother 1984;13(Suppl. B):25-31.
- 47. Newsom SWB, Mathews J, Amphlett M, Warren RE. Norfloxacin and the antibacterial ( pyridone ß carboxylic acids. J Antimicrob Chemother 1982;10:25-30.
- 48.
Nix DE, Wilton JH, Ronald B, Disterath L, Williams VC, Norman A.
Inhibition of norfloxacin absorption by antacids. Antimicrob Agents Chemother 1990;34(3):432-35.
- 49.
Norfloxacin New Drug Submission, Section 3.1, Volume C,
Microbiological and Pharmacological Studies, Merck Frosst Canada Inc., Kirkland, Quebec, Canada, 20 June 1983.
- 50.
Noyes M, Polk RE. Norfloxacin and absorption of magnesium-aluminum.
Ann Intern Med 1988:168-69.
- 51.
Okayama K, Kanzaki R, Hayakawa M, Adachi M, Imataka K, Kawai M,
Takizuka H, Nakano M, Katsu M, Ogiwara K, Satoh S, Imai T, Kanazawa M, Masuda G, Yajima T, Tanaka G, Hagane K, Koizumi Y, Watanabe S, Yanai N, Aoyagi T, Nakayama S. Basic and clinical studies on AM-715. Chemotherapy (Tokyo) 1981;29(Suppl. 4): 259-83.
- 52. Ozaki T, Uchida H, Irikura T. Studies on the metabolism of AM-715 in humans by high-performance liquid chromatography. Chemotherapy (Tokyo) 1981;29(Suppl. 4):128-35.
- 53.
Parpia SH, Nix DE, Hejmanowski LG, Goldstein HR, Wilton JH, Schentag
JJ. Sucralfate reduces the gastrointestinal absorption of norfloxacin. Antimicrob Agents Chemother 1989;33(1):99-102.
- 54. Polk RE. Drug-drug interactions with ciprofloxacin and other fluoroquinolones. Am J Med 1989;87(Suppl 5A):76S-81S.
- 55.
Prince RA. Fluoroquinolone-drug interactions: an overview. Antimicrob
Newsletter 1989;6(12):93-9.
- 56. Ratcliffe NT, Smith JT. Mechanism of reduced activity of 4-quinolone agents in urine. Fortschritte der Antimikrobiellen und Antineoplasticken Chemotherapie 1984;3:563-69.
- 57. Saito T, Yamada Y, Arai T. Studies on AM-715: Biliary excretion, tissue concentration of the liver and the gallbladder wall, and clinical evaluation in surgical field. Chemotherapy Dec. 1981;29(Suppl. 4):631-38.
- 58.
Sanders CC, Sanders WE Jr, Goering RV, Werner V. Selection of multiple antibiotic resistance by quinolones, ß-lactams, and aminoglycosides with special reference to cross-resistance between unrelated drug classes. Antimicrob Agents Chemother 1984;26:797-801. 59. Sato K, Matsuura Y, Inoue M, Une T, Osada Y, Ogawa H, Mitsuhashi S.
In vitro and in vivo activity of DL-8280, a new oxazine derivative. Antimicrob Agents Chemother 1982;22:548-53.
- 60.
Sawae Y, Okada K. Laboratory and clinical studies on AM-715.
Chemotherapy (Tokyo) 1981;29(Suppl. 4):388-95.
- 61.
Shimada J, Yamaji T, Ueda Y, Uchida H, Kusajima H, Irikura T.
Mechanism of renal excretion of AM-715, a new quinolocarboxylic acid derivative, in rabbits, dogs and humans. Antimicrob Agents Chemother 1983;23:1-7.
- 62.
Shimura H, Yamamoto H, Igimi H, Arima S, Ohkuma R, Kuroda Y, Taira
A, Ozasa K, Sakaguchi N, Imaizumi N, Midorikawa T, Tamura R, Fukamura T, Furusawa T. Fundamental and clinical studies of norfloxacin (AM-715) in biliary tract infection. Chemotherapy 1983;31:351-67.
- 63. Shungu DL, Weinberg E, Gadebusch HH. Tentative interpretive standards for disk diffusion susceptibility testing with norfloxacin (MK-0366, AM-715). Antimicrob Agents Chemother 1983;23:256-60.
- 64. Simon C, Lindner U. In vitro activity of norfloxacin against Mycoplasma hominis and Ureaplasma urealyticum. Eur J Clin Microbiol 1983;2:479-80.
- 65. Speranza V, Fiocca F, Basoli A, Lezoche E. Terapia delle infezioni biliari con norflossacina (Norfloxacin treatment of biliary-tract infections). Istituto di VI Clinica Chirurgica e Terapia Chirurgica, Università degli Studi "La Sapienza", Policlinico "Umberto I" - Roma, G Ital Chemioter 1984;31:149-52.
- 66.
Stein GE. The 4-quinolone antibiotics: past, present and future.
Pharmacotherapy 1988;8:301-14.
- 67.
Stille W, Ostner KH. Nitrofurantoin-nalidixic acid antagonism. Klin
Wochenschr 1966;44:155-56.
- 68.
Takahashi H, Kobayashi Y, Fujimori I. Clinical study on AM-715.
Chemotherapy (Tokyo) 1981;29(Suppl. 4):293-98.
- 69. Thomson DJ, Menkis AH, McKenzie FM. Norfloxacin-cyclosporine interaction. Transplantation 1988;46:312-13.
- 70. Westwood GP, Hooper WL. Letter: antagonism of oxolinic acid by nitrofurantoin. Lancet 1975;1(7904):460.
- 71. Wang C, Sabbaj M, Corrado M, Hoagland V. World-wide clinical experience with norfloxacin efficacy and safety. Scand J Infect Dis 1986;48(Suppl.):81-89.
- 72. Yamamoto Y, Ihara T, Shimura H. Laboratory and clinical investigations of AM-715 in surgical field. Chemotherapy 1981;29(Suppl. 4):663-68.
- 73.
Knupp CA, Barbhaiya RH. A Multiple-Dose Pharmacokinetic Interaction
Study between Didanosine (VIDEX®) and Ciprofloxacin (CIPRO®) in Male Subjects Seropositive for HIV but Asymptomatic. Biopharmaceutics & Drug Disposition 1997;18:65-77.
- 74.
Sieb JP. Fluoroquinolone Antibiotics Block Neuromuscular Transmission.
Neurology 1998;50:804-807.
- 75.
Moore N, Breemeersch C, Noblet C. Renal Failure with Fluoroquinolones.
Thérapie 1996;51:421-423.