


Product Monograph - Norvir (Abbvie, Capsule)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form/Strength | Clinically Relevant Non-medicinal Ingredientsa |
|---|---|---|
| oral | film-coated tablets / 100 mg | sorbitan monolaurate/sorbitan laurate |
a. For a complete listing of non-medicinal ingredients, see DOSAGE FORMS, COMPOSITION AND PACKAGING section.
INDICATIONS AND CLINICAL USE
NORVIR (ritonavir) is indicated in combination with other antiretroviral agents for the treatment of HIV infection when therapy is warranted.
For patients with advanced Human Immunodeficiency Virus (HIV) disease, this indication is based on the results from a study that showed a reduction in both mortality and AIDS-defining clinical events for patients who received NORVIR. Median duration of follow-up in this study was 6 months. The clinical benefit from NORVIR therapy for longer periods of treatment is unknown.
For patients with less advanced disease, this indication is based on changes in surrogate markers in studies evaluating patients who received NORVIR alone or in combination with other antiretroviral agents (see CLINICAL TRIALS).
Geriatrics (≥ 65 years of age)
Clinical studies of NORVIR did not include sufficient numbers of subjects age 65 and over to determine whether they respond differently from younger subjects. In general, appropriate caution should be exercised in the administration and monitoring of NORVIR in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Pediatrics (2 to 16 years of age)
NORVIR concentrations obtained after 350 to 400 mg/m² twice daily in pediatric patients were comparable to those obtained in adults receiving 600 mg (approximately 330 mg/m²) twice daily (see Pharmacokinetics, Special Populations and Conditions, Pediatrics). The safety and effectiveness of NORVIR in pediatric patients below the age of 2 years have not been established.
CONTRAINDICATIONS
When NORVIR (ritonavir) is used as a pharmacokinetic enhancer with other protease inhibitors, see the full prescribing information of that protease inhibitor including contraindication information.
NORVIR is contraindicated in patients with known hypersensitivity [e.g., toxic epidermal necrosis (TEN) or Stevens Johnson syndrome (SJS)] to NORVIR or any of its ingredients (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
Co-administration of NORVIR is contraindicated with the drugs listed in Table 1 (see also DRUG INTERACTIONS, Serious Drug Interactions box) because competition for primarily CYP3A by NORVIR could result in inhibition of the metabolism of these drugs and create the potential for serious and/or life-threatening reactions, such as cardiac arrhythmias, prolonged or increased sedation, and respiratory depression. Voriconazole and St. John’s Wort are exceptions in that co-administration of NORVIR and voriconazole results in a significant reduction in plasma concentrations of voriconazole and possible loss of effect, and co-administration of NORVIR with St. John’s Wort may lead to loss of virologic response and possible resistance to NORVIR.
Table 1. Drugs that are Contraindicated with NORVIR
| Drug Class | Drugs Within Class that are Contraindicated with NORVIR | Clinical Comment |
|---|---|---|
| Alpha1-Adrenoreceptor Antagonist | alfuzosin | Potential for serious reactions, such as hypotension (see DRUG INTERACTIONS, Table 5). |
| Antiarrhythmics | amiodarone, bepridil1, dronedarone, flecainide, propafenone, quinidine | Potential for serious and/or life-threatening reactions, such as cardiac arrhythmias. |
| Antibiotic | fusidic acid | Potential of increased fusidic acid-associated adverse events, such as hepatitis or bone marrow suppression. |
| Anticancer | venetoclax4 | Concomitant use of strong CYP3A inhibitors, such as NORVIR, and venetoclax may increase the risk of tumor lysis syndrome at the dose initiation and during the ramp-up phase. |
| Anticoagulant | rivaroxaban | Potential of increased rivaroxaban plasma concentrations which may lead to risk of increased bleeding. |
| Antifungal | voriconazole | Significant reduction in voriconazole plasma concentrations and possible loss of effect (see DRUG INTERACTIONS, Table 6). |
| Antigout | colchicine | Potential for serious and/or life-threatening reactions in patients with renal and/or hepatic impairment (see DRUG INTERACTIONS, Table 5). |
| Antihistamines | astemizole1, terfenadine1 | Potential for serious and/or life-threatening reactions, such as cardiac arrhythmias. |
| Antipsychotics | lurasidone pimozide | Potential for serious and/or life-threatening reactions. Potential for serious and/or life-threatening reactions, such as cardiac arrhythmias. |
| Ergot Derivatives | dihydroergotamine, ergonovine, ergotamine1, methylergonovine1 | Potential for serious and/or life-threatening reactions, such as acute ergot toxicity characterized by vasospasm and tissue ischemia. |
| GI Motility Agent | cisapride1 | Potential for serious and/or life-threatening reactions, such as cardiac arrhythmias. |
| Herbal Products | St. John’s wort (Hypericum perforatum) | May lead to loss of virologic response and possible resistance to NORVIR or to the class of protease inhibitors. |
| Drug Class | Drugs Within Class that are Contraindicated with NORVIR | Clinical Comment |
|---|---|---|
Lipid-modifying agents HMG-CoA Reductase Inhibitors Microsomal triglyceride transfer protein (MTTP) Inhibitor | lovastatin, simvastatin lomitapide | Potential for serious reactions, such as risk of myopathy including rhabdomyolysis. Potential for serious reactions, such as hepatotoxicity. |
| Long Acting Beta-Adrenoceptor | salmeterol | May result in potential increased risk of cardiovascular adverse events associated with salmeterol. |
| PDE5 Inhibitors | sildenafil2, only when used for the treatment of pulmonary arterial hypertension (PAH) vardenafil, when used for the treatment of erectile dysfunction or PAH | Potential increase in PDE5 inhibitor associated adverse reactions including hypotension, syncope, visual changes and prolonged erection. Potential increase in PDE5 inhibitor associated adverse reactions including hypotension, syncope, visual changes and prolonged erection. |
| Sedative/Hypnotics | orally administered midazolam3, triazolam | Potential for serious and/or life-threatening reactions, such as prolonged or increased sedation or respiratory depression. |
1: Product no longer marketed in Canada. 2: See WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS for co-administration of sildenafil in patients with erectile dysfunction. 3: See DRUG INTERACTIONS, Table 5 for parenterally administered midazolam. Oral formulation of midazolam is not marketed in Canada. 4: See DRUG INTERACTIONS, Table 5 for coadministration of the maintenance dose of venetoclax. | ||
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
|
Drug-Drug Interactions
When NORVIR (ritonavir) is used as a pharmacokinetic enhancer with other protease inhibitors, see the full prescribing information of that protease inhibitor including Warning and Precautions.
NORVIR is an inhibitor of cytochrome P450 3A (CYP3A) both in vitro and in vivo. NORVIR also inhibits CYP2D6 in vitro, but to a lesser extent than CYP3A.
Initiation of NORVIR, a CYP3A inhibitor, in patients receiving medications metabolized by CYP3A or initiation of medications metabolized by CYP3A in patients already receiving NORVIR, may increase plasma concentrations of medications metabolized by CYP3A. Initiation of medications that inhibit or induce CYP3A may increase or decrease concentrations of NORVIR, respectively. These interactions may lead to:
- Clinically significant adverse reactions, potentially leading to severe, life-threatening, or fatal events from greater exposures of concomitant medications.
- Clinically significant adverse reactions from greater exposures of NORVIR.
- Loss of therapeutic effect of NORVIR and possible development of resistance.
See Table 5 for steps to prevent or manage these possible and known significant drug interactions, including dosing recommendations (see DRUG INTERACTIONS). Consider the potential for drug interactions prior to and during NORVIR therapy; review concomitant medications during NORVIR therapy, and monitor for the adverse reactions associated with the concomitant medications (see CONTRAINDICATIONS and DRUG INTERACTIONS).
Allergic Reactions
Allergic reactions including urticaria, skin eruptions, bronchospasm, and angioedema have been reported. Rare cases of anaphylaxis, toxic epidermal necrosis (TEN) and Stevens-Johnson syndrome (SJS) have also been reported. Discontinue treatment if these reactions occur.
Organ Targets for Toxicity
Toxicological studies in laboratory animals identified various organs as targets for toxicity at drug exposures below or approaching those achieved in patients participating in clinical trials with NORVIR. Because no safety margin or a small safety margin has been demonstrated in long-term studies, these organs should be assessed periodically or if clinical signs and symptoms occur during therapy (see NON-CLINICAL TOXICOLOGY).
Carcinogenesis and Mutagenesis
For a brief discussion of pre-clinical carcinogenicity data, see NON-CLINICAL TOXICOLOGY, Mutagenicity and Carcinogenicity. No evidence of mutagenic or clastogenic activity have been reported in a battery of in vitro and in vivo assays.
Cardiovascular
PR Interval Prolongation
NORVIR has been shown to cause asymptomatic prolongation of the PR interval in some patients.
Post-marketing reports of second or third degree atrioventricular block have been reported in patients with underlying structural heart disease and pre-existing conduction system abnormalities, ischemic heart disease, cardiomyopathies, as these patients may be at increased risk of cardiac conduction abnormalities, or in patients receiving drugs known to prolong the PR interval (such as calcium channel blockers, beta-adrenergic blockers, digoxin, verapamil or atazanavir). Co-administration of NORVIR with these drugs should be undertaken with caution, particularly with drugs metabolized by CYP3A4 (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Effects on the Electrocardiogram). Clinical monitoring is recommended (see DRUG INTERACTIONS).
Endocrine and Metabolism
Diabetes Mellitus/Hyperglycemia
Levels of blood glucose may increase during antiretroviral therapy. Such changes may in part be linked to the treatment per se (e.g., protease inhibitors), and in part to disease control and life style. New onset diabetes mellitus, exacerbation of pre-existing diabetes mellitus and hyperglycemia have been reported during post-marketing surveillance in HIV-infected patients receiving protease inhibitor therapy. Some patients required either initiation or dose adjustments of insulin or oral hypoglycemic agents for treatment of these events. In some cases diabetic ketoacidosis has occurred. In those patients who discontinued protease inhibitor therapy, hyperglycemia persisted in some cases. Because these events have been reported voluntarily during clinical practice, estimates of frequency cannot be made and a causal relationship between protease inhibitor therapy and these events has not been established. For monitoring of blood glucose, reference is made to established HIV treatment guidelines. Glucose elevations should be managed as clinically appropriate (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
Lipid Disorders
Levels of blood lipids may increase during antiretroviral therapy. Such changes may in part be linked to the treatment per se (e.g., protease inhibitors), and in part to disease control and life style. (see ADVERSE REACTIONS, Table 4).
Triglycerides and cholesterol testing should be performed prior to initiating NORVIR therapy and at periodic intervals during therapy (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). For monitoring of blood lipids, reference is made to established HIV treatment guidelines. Lipid disorders should be managed as clinically appropriate.
Hematologic
There have been reports of increased bleeding, including spontaneous skin hematomas and hemarthrosis, in patients with hemophilia type A and type B treated with protease inhibitors. In some patients, additional Factor VIII was given. In more than half of the reported cases, treatment with protease inhibitors was continued or re-introduced. There is no proven relationship between protease inhibitors and such bleeding; however, the frequency of bleeding episodes should be closely monitored in patients on NORVIR.
Hepatic/Biliary/Pancreatic
Impaired Hepatic Function
NORVIR is principally metabolized by the liver. Pre-clinical studies have identified the liver as a toxicity target (see NON-CLINICAL TOXICOLOGY). Therefore, appropriate tests should be performed at treatment initiation and at periodic intervals to assess hepatic function.
Caution should be exercised when administering NORVIR to patients with impaired hepatic function.
Hepatic Reactions
Hepatic transaminase elevations exceeding 5 times the upper limit of normal, clinical hepatitis, and jaundice have occurred in patients receiving NORVIR alone or in combination with other antiretroviral drugs (see ADVERSE REACTIONS, Table 4). There may be an increased risk for transaminase elevations in patients with underlying hepatitis B or C. Therefore, caution should be exercised when administering NORVIR to patients with pre-existing liver disease, liver enzyme abnormalities, or hepatitis. Liver enzyme elevations should be monitored as clinically appropriate (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
There have been post-marketing reports of hepatic dysfunction, including some fatalities. These have generally occurred in patients taking multiple concomitant medications and/or with advanced AIDS.
Pancreatitis
Pancreatitis has been observed in patients receiving NORVIR therapy, including those who developed hypertriglyceridemia. In some cases fatalities have been observed. Patients with advanced HIV disease may be at increased risk of elevated triglycerides and pancreatitis.
Pancreatitis should be considered if clinical symptoms (nausea, vomiting, abdominal pain) or abnormalities in laboratory values (such as increased serum lipase or amylase values) suggestive of pancreatitis should occur. Patients who exhibit these signs or symptoms should be evaluated and NORVIR therapy should be discontinued if a diagnosis of pancreatitis is made.
Immune Reconstitution Inflammatory Syndrome
Immune reconstitution inflammatory syndrome has been reported in HIV-infected patients treated with combination antiretroviral therapy, including NORVIR. During the initial phase of treatment, patients responding to antiretroviral therapy may develop an inflammatory response to indolent or residual opportunistic infections (such as Mycobacterium avium infection, cytomegalovirus, Pneumocystis jirovecii pneumonia, or tuberculosis), which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves’ disease, polymyositis, Guillain-Barré syndrome, and autoimmune hepatitis) have also been reported to occur in the setting of immune reconstitution, however, the time to onset is more variable, and can occur many months after initiation of treatment.
Neurologic
Central nervous system (CNS) penetration of NORVIR has not been established.
Sensitivity/Resistance
Resistance
Mutations associated with the HIV viral protease in isolates obtained from 41 patients appeared to occur in a stepwise and ordered fashion.
The clinical relevance of phenotypic and genotypic changes associated with NORVIR therapy has not been established (see MICROBIOLOGY, Resistance).
Cross-Resistance
Serial HIV isolates obtained from six patients during NORVIR therapy showed a decrease in ritonavir susceptibility in vitro to indinavir (8-fold), nelfinavir (12- to 14-fold), and none to amprenavir. One zidovudine (ZDV)-resistant HIV isolate tested in vitro retained full susceptibility to ritonavir (see MICROBIOLOGY, Cross-Resistance to Other Antiretrovirals).
Special Populations
Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Prospective pregnancy data from the Antiretroviral Pregnancy Registry (APR) are not sufficient to adequately assess the risk of birth defects or miscarriage. Based on approximately 6100 live births following exposure to ritonavir-containing regimens (including over 2800 live births exposed in the first trimester and over 3200 live births exposed in the second and third trimesters) in the APR, there was no difference in the rate of overall birth defects for ritonavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The prevalence of birth defects in live births was 2.3% (95% CI: 1.7%-2.9%) following first-trimester exposure to ritonavir-containing regimens and 2.9% (95% CI: 2.3%-3.5%) following second and third trimester exposure to ritonavir-containing regimens. The prevalence of birth defects after any trimester exposure to ritonavir is comparable to the prevalence observed in the general population.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
In rat fertility studies, hepatic toxicity precluded drug exposures equal to those achieved with the proposed human therapeutic dose. No effects on fertility in rats were produced at drug exposures approximately 40% (male) and 60% (female) of that achieved with the proposed human therapeutic dose.
No treatment-related malformations were observed when ritonavir was administered to pregnant rats or rabbits. Developmental toxicity observed in rats (early resorptions, decreased fetal body weight and ossification delays and developmental variations) occurred at a maternally toxic dosage at an exposure equivalent to approximately 30% of that achieved with the proposed therapeutic dose. A slight increase in the incidence of cryptorchidism was also noted in rats at an exposure approximately 22% of that achieved with the proposed therapeutic dose.
Developmental toxicity observed in rabbits (resorptions, decreased litter size and decreased fetal weights) also occurred at a maternally toxic dosage equivalent to 1.8 times the proposed therapeutic dose based on a body surface area conversion factor.
Antiretroviral Pregnancy Registry
To monitor maternal-fetal outcomes of pregnant women exposed to NORVIR, an Antiretroviral Pregnancy Registry has been established. Physicians are encouraged to register patients by calling 1-800-258-4263.
Nursing Women
HIV-infected mothers should not breast-feed their infants to avoid risking postnatal transmission of HIV. Limited published data reports that ritonavir is present in human milk. There is no information on the effects of ritonavir on the breastfed infant or the effects of the drug on milk production. Because of the potential for (1) HIV transmission (in HIV-negative infants), (2) developing viral resistance (in HIV-positive infants) and (3) serious adverse reactions in a breastfed infant, instruct mothers not to breast-feed if they are receiving NORVIR.
Pediatrics (2 to 16 years of age)
The safety and effectiveness of NORVIR in pediatric patients below the age of 2 years have not been established. Although the database in HIV-infected patients age 2 to 16 years is much smaller, the adverse event profile seen during a clinical trial and post-marketing experience was similar to that observed for adult patients.
Geriatrics (≥ 65 years of age)
Clinical studies of NORVIR did not include sufficient numbers of subjects age 65 and over to determine whether they respond differently from younger subjects. In general, appropriate caution should be exercised in the administration and monitoring of NORVIR in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Monitoring and Laboratory Tests
NORVIR has been associated with elevations in cholesterol, triglycerides, SGOT (AST), SGPT (ALT), GGT, CK, and uric acid. Appropriate laboratory testing should be performed prior to initiating NORVIR therapy and at periodic intervals or if any clinical signs or symptoms occur during therapy. For monitoring of liver enzymes, blood lipids, and glucose refer to established HIV treatment guidelines. For comprehensive information concerning laboratory test alterations associated with other antiretroviral agents, physicians should refer to the complete product information for each of these drugs.
ADVERSE REACTIONS
When NORVIR (ritonavir) is used as a pharmacokinetic enhancer with other protease inhibitors, see the full prescribing information of that protease inhibitor including Adverse Reactions.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adult Patients
The safety of NORVIR alone and in combination with nucleoside reverse transcriptase inhibitors was studied in 1270 adult patients.
Table 2 lists treatment-emergent adverse events (at least possibly related and of at least moderate intensity) that occurred in 2% or greater of adult patients receiving NORVIR alone or in combination with nucleoside reverse transcriptase inhibitors in Study M94-247 or Study M94-245 and in combination with saquinavir in Study M94-462. In that study, 141 protease inhibitor-naïve, HIV-infected patients with mean baseline CD4 of 300 cells/microliter were randomized to one of four regimens of NORVIR plus saquinavir, including NORVIR 400 mg twice daily plus saquinavir 400 mg twice daily. Overall, the most frequently reported adverse drug reactions among patients receiving NORVIR alone or in combination with other antiretroviral drugs were gastrointestinal and neurological disturbances including diarrhea, nausea, vomiting, anorexia, abdominal pain (upper and lower), and neurological disturbances (including paresthesia and oral paresthesia), and fatigue/asthenia. Similar adverse event profiles were reported in adult patients receiving NORVIR in other trials.
Table 2. Percentage of Patients with Treatment-Emergent Adverse Events1 of Moderate or Severe Intensity Occurring in ≥ 2% of Adult Patients Receiving NORVIR
Study M94-247 Advanced Patients2 | Study M94-245 Naïve Patients3 | Study M94-462 PI-Naïve Patients4 | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Adverse Events | NORVIR (n = 541) | Placebo (n = 545) | NORVIR + Zidovudine (n = 116) | NORVIR (n = 117) | Zidovudine (n = 119) | NORVIR5 + Saquinavir (n = 141) | |||||||||
| Body as a Whole | |||||||||||||||
| Abdominal Pain | 8.3 | 5.1 | 5.2 | 6.0 | 5.9 | 2.1 | |||||||||
| Asthenia | 15.3 | 6.4 | 28.4 | 10.3 | 11.8 | 16.3 | |||||||||
| Fever | 5.0 | 2.4 | 1.7 | 0.9 | 1.7 | 0.7 | |||||||||
| Headache | 6.5 | 5.7 | 7.8 | 6.0 | 6.7 | 4.3 | |||||||||
| Malaise | 0.7 | 0.2 | 5.2 | 1.7 | 3.4 | 2.8 | |||||||||
| Pain (unspecified) | 2.2 | 1.8 | 0.9 | 1.7 | 0.8 | 4.3 | |||||||||
| Cardiovascular | |||||||||||||||
| Syncope | 0.6 | 0.0 | 0.9 | 1.7 | 0.8 | 2.1 | |||||||||
| Vasodilation | 1.7 | 0.0 | 3.4 | 1.7 | 0.8 | 3.5 | |||||||||
| Digestive | |||||||||||||||
| Anorexia | 7.8 | 4.2 | 8.6 | 1.7 | 4.2 | 4.3 | |||||||||
| Constipation | 0.2 | 0.4 | 3.4 | 0.0 | 0.8 | 1.4 | |||||||||
| Diarrhea | 23.3 | 7.9 | 25.0 | 15.4 | 2.5 | 22.7 | |||||||||
| Dyspepsia | 5.9 | 1.5 | 2.6 | 0.0 | 1.7 | 0.7 | |||||||||
| Fecal Incontinence | 0.0 | 0.0 | 0.0 | 0.0 | 0.0 | 2.8 | |||||||||
| Flatulence | 1.7 | 0.7 | 2.6 | 0.9 | 1.7 | 3.5 | |||||||||
| Liver Function Tests Abnormal | 3.3 | 0.9 | 2.6 | 1.7 | 1.7 | 5.0 | |||||||||
| Local Throat Irritation | 2.8 | 0.4 | 0.9 | 1.7 | 0.8 | 1.4 | |||||||||
| Nausea | 29.8 | 8.4 | 46.6 | 25.6 | 26.1 | 18.4 | |||||||||
| Vomiting | 17.4 | 4.4 | 23.3 | 13.7 | 12.6 | 7.1 | |||||||||
| Metabolic and Nutritional | |||||||||||||||
| Creatinine Phosphokinase (CK) Increase | 0.9 | 0.2 | 4.3 | 3.4 | 3.4 | N/A | |||||||||
| Hyperlipidemia | 5.7 | 0.2 | 2.6 | 1.7 | 0.0 | 3.5 | |||||||||
| Weight Loss | 2.4 | 1.7 | 0.0 | 0.0 | 0.0 | 0.0 | |||||||||
Study M94-247 Advanced Patients2 | Study M94-245 Naïve Patients3 | Study M94-462 PI-Naïve Patients4 |
|---|
| Adverse Events | NORVIR (n = 541) | Placebo (n = 545) | NORVIR + Zidovudine (n = 116) | NORVIR (n = 117) | Zidovudine (n = 119) | NORVIR5 + Saquinavir (n = 141) |
|---|---|---|---|---|---|---|
| Musculoskeletal | ||||||
| Arthralgia | 1.7 | 0.7 | 0.0 | 0.0 | 0.0 | 2.1 |
| Myalgia | 2.4 | 1.1 | 1.7 | 1.7 | 0.8 | 2.1 |
| Nervous | ||||||
| Anxiety | 1.7 | 0.9 | 0.9 | 0.0 | 0.8 | 2.1 |
| Circumoral Paresthesia | 6.7 | 0.4 | 5.2 | 3.4 | 0.0 | 6.4 |
| Confusion | 0.6 | 0.6 | 0.0 | 0.9 | 0.0 | 2.1 |
| Depression | 1.7 | 0.7 | 1.7 | 1.7 | 2.5 | 7.1 |
| Dizziness | 3.9 | 1.1 | 5.2 | 2.6 | 3.4 | 8.5 |
| Insomnia | 2.0 | 1.8 | 3.4 | 2.6 | 0.8 | 2.8 |
| Paresthesia | 3.0 | 0.4 | 5.2 | 2.6 | 0.0 | 2.1 |
| Peripheral Paresthesia | 5.0 | 1.1 | 0.0 | 6.0 | 0.8 | 5.7 |
| Somnolence | 2.4 | 0.2 | 2.6 | 2.6 | 0.0 | 0.0 |
| Thinking Abnormal | 0.9 | 0.4 | 2.6 | 0.0 | 0.8 | 0.7 |
| Respiratory | ||||||
| Pharyngitis | 0.4 | 0.4 | 0.9 | 2.6 | 0.0 | 1.4 |
| Skin and Appendages | ||||||
| Rash | 3.5 | 1.5 | 0.9 | 0.0 | 0.8 | 0.7 |
| Sweating | 1.7 | 1.1 | 3.4 | 2.6 | 1.7 | 2.8 |
| Special Senses | ||||||
| Taste Perversion | 7.0 | 2.2 | 17.2 | 11.1 | 8.4 | 5.0 |
| Urogenital | ||||||
| Nocturia | 0.2 | 0.0 | 0.0 | 0.0 | 0.0 | 2.8 |
Study M94-247 Advanced Patients2 | Study M94-245 Naïve Patients3 | Study M94-462 PI-Naïve Patients4 |
|---|
| Adverse Events | NORVIR (n = 541) | Placebo (n = 545) | NORVIR + Zidovudine (n = 116) | NORVIR (n = 117) | Zidovudine (n = 119) | NORVIR5 + Saquinavir (n = 141) |
|---|---|---|---|---|---|---|
1: Includes those adverse events at least possibly related to study drug or of unknown relationship and excludes concurrent HIV conditions. 2: The median duration of treatment for patients randomized to regimens containing NORVIR in Study M94-247 was 9.4 months. 3: The median duration of treatment for patients randomized to regimens containing NORVIR in Study M94-245 was 9.1 months. 4: The median duration of treatment for patients in Study M94-462 was 48 weeks. 5: The dose of NORVIR when co-administered with saquinavir was reduced to 400 mg twice daily. Definitions: N/A = Not available | ||||||
Other Common Clinical Trial Adverse Drug Reactions
Table 3 includes other treatment-emergent adverse reactions (with possible or probable relationship to study drug) occurring in ≥ 1% of adult patients receiving NORVIR derived from cumulative data from combined Phase 2 to 4 studies.
Table 3. Treatment-Emergent Adverse Reactions (With Possible or Probable Relationship to Study Drug) Occurring in ≥ 1% of Adult Patients Receiving NORVIR in Combined Phase 2 to 4 Studies (N = 1,755)
| Adverse Reactions | n | % |
|---|---|---|
| Eye disorders | ||
| Blurred vision | 113 | 6.4 |
| Gastrointestinal disorders | ||
| Abdominal Pain (upper and lower) | 464 | 26.4 |
| Diarrhea including severe with electrolyte imbalance | 1,192 | 67.9 |
| Dyspepsia | 201 | 11.5 |
| Flatulence | 142 | 8.1 |
| Gastrointestinal hemorrhage | 41 | 2.3 |
| Gastroesophageal reflux disease (GERD) | 19 | 1.1 |
| Nausea | 1,007 | 57.4 |
| Vomiting | 559 | 31.9 |
| Adverse Reactions | n | % |
|---|---|---|
| General disorders and administration site conditions | ||
| Fatigue including asthenia | 811 | 46.2 |
| Hepatobiliary disorders | ||
| Blood bilirubin increased (including jaundice) | 25 | 1.4 |
| Hepatitis (including increased AST, ALT, GGT) | 153 | 8.7 |
| Immune system disorders | ||
| Hypersensivity including urticatria and face edema | 114 | 8.2 |
| Metabolism and nutrition disorders | ||
| Edema and peripheral edema | 110 | 6.3 |
| Gout | 24 | 1.4 |
| Hypercholesterolemia | 52 | 3.0 |
| Hypertriglyceridemia | 158 | 9.0 |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia and back pain | 326 | 18.6 |
| Myopathy/creatine phosphokinase increased | 66 | 3.8 |
| Myalgia | 156 | 8.9 |
| Nervous system disorders | ||
| Dizziness | 274 | 15.6 |
| Dysgeusia | 285 | 16.2 |
| Paresthesia (including oral paresthesia) | 889 | 50.7 |
| Peripheral neuropathy | 178 | 10.1 |
| Syncope | 58 | 3.3 |
| Psychiatric disorders | ||
| Confusion | 52 | 3.0 |
| Disturbance in attention | 44 | 2.5 |
| Renal and urinary disorders | ||
| Increased urination | 74 | 4.2 |
| Respiratory, thoracic and mediastinal disorders | ||
| Coughing | 380 | 21.7 |
| Oropharyngeal Pain | 279 | 15.9 |
Adverse Reactions
| n | % | |
|---|---|---|
| Skin and subcutaneous tissue disorders | ||
| Acne | 67 | 3.8 |
| Pruritus | 214 | 12.2 |
| Rash (includes erythematous and maculopapular) | 475 | 27.1 |
| Vascular disorders | ||
| Flushing, feeling hot | 232 | 13.2 |
| Hypertension | 58 | 3.3 |
| Hypotension including orthostatic hypotension | 30 | 1.7 |
| Peripheral coldness | 21 | 1.2 |
Less Common Clinical Trial Adverse Events (< 2%)
Adverse events occurring in less than 2% of adult patients receiving NORVIR in all Phase 2/Phase 3 studies and considered at least possibly related or of unknown relationship to treatment and of at least moderate intensity are listed below by body system.
| Body as a Whole: | abdomen enlarged, accidental injury, cachexia, chest pain, chills, facial pain, flu syndrome, hormone level altered, hypothermia, kidney pain, neck pain, neck rigidity, pelvic pain, photosensitivity reaction, and substernal chest pain. |
| Cardiovascular System: | cardiovascular disorder, cerebral ischemia, cerebral venous thrombosis, hemorrhage, migraine, myocardial infarct, palpitation, peripheral vascular disorder, phlebitis, postural hypotension, tachycardia, and vasospasm. |
| Digestive System: | abnormal stools, bloody diarrhea, cheilitis, cholangitis, cholestatic jaundice, colitis, dry mouth, dysphagia, eructation, esophageal ulcer, esophagitis, gastritis, gastroenteritis, gastrointestinal disorder, gingivitis, hepatic coma, hepatomegaly, hepatosplenomegaly, ileitis, ileus, liver damage, melena, mouth ulcer, oral moniliasis, pancreatitis, periodontal abscess, pseudomembranous colitis, rectal disorder, rectal hemorrhage, sialadenitis, stomatitis, tenesmus, thirst, tongue edema, and ulcerative colitis. |
| Endocrine System: | adrenal cortex insufficiency and diabetes mellitus. |
| Hemic and Lymphatic System: | acute myeloblastic leukemia, anemia, ecchymosis, leukopenia, lymphadenopathy, lymphocytosis, myeloproliferative disorder, and thrombocytopenia. |
| Metabolism and Nutritional Disorders: | albuminuria, alcohol intolerance, avitaminosis, BUN increased, dehydration, enzymatic abnormality, glycosuria, and xanthomatosis. |
| Musculoskeletal System: | arthritis, arthrosis, bone disorder, bone pain, extraocular palsy, joint disorder, leg cramps, muscle cramps, muscle weakness, myositis, and twitching. |
| Nervous System: | abnormal dreams, abnormal gait, agitation, amnesia, aphasia, ataxia, coma, convulsion, dementia, depersonalization, diplopia, emotional lability, euphoria, grand mal convulsion, hallucinations, hyperesthesia, hyperkinesia, hypesthesia, incoordination, libido decreased, manic reaction, nervousness, neuralgia, neuropathy, paralysis, peripheral neuropathic pain, peripheral sensory neuropathy, personality disorder, sleep disorder, speech disorder, stupor, subdural hematoma, tremor, urinary retention, vertigo, and vestibular disorder. |
| Respiratory System: | asthma, bronchitis, dyspnea, epistaxis, hiccup, hypoventilation, interstitial pneumonia, larynx edema, lung disorder, rhinitis, and sinusitis. |
| Skin and Appendages: | contact dermatitis, dry skin, eczema, erythema multiforme, exfoliative dermatitis, folliculitis, fungal dermatitis, furunculosis, molluscum contagiosum, onychomycosis, psoriasis, pustular rash, seborrhea, skin discoloration, skin disorder, skin hypertrophy, skin melanoma, and vesiculobullous rash. |
| Special Senses: | abnormal electro-oculogram, abnormal electroretinogram, abnormal vision, amblyopia/blurred vision, blepharitis, conjunctivitis, ear pain, eye disorder, eye pain, hearing impairment, increased cerumen, iritis, parosmia, photophobia, taste loss, tinnitus, uveitis, visual field defect, and vitreous disorder. |
| Urogenital System: | acute kidney failure, breast pain, cystitis, dysuria, hematuria, impotence, kidney calculus, kidney failure, kidney function abnormal, kidney pain, menorrhagia, penis disorder, polyuria, pyelonephritis, urethritis, urinary frequency, urinary tract infection, and vaginitis. |
Abnormal Hematologic and Clinical Chemistry Findings
Table 4 shows the percentage of adult patients who developed marked laboratory abnormalities.
Table 4. Percentage of Adult Patients, by Study and Treatment Group, with Chemistry and Hematology Abnormalities Occurring in ≥ 2% of Patients Receiving NORVIR
Study M94-247 Advanced Patients | Study M94-245 Naïve Patients | Study M94-462 PI-Naïve Patients | |||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Variable | Limit | NORVIR (n = 541) | Placebo (n=545) | NORVIR + ZDV (n = 116) | NORVIR (n = 117) | ZDV (n=119) | NORVIR + Saquinavir (n = 141) | ||||||||||||||||
| Chemistry | High | ||||||||||||||||||||||
| Alkaline Phosphatase | > 550 IU/L | 2.3 | 2.2 | - | 0.9 | - | - | ||||||||||||||||
| Cholesterol | > 6.22 mmol/L | 36.5 | 8.0 | 30.7 | 44.8 | 9.3 | 65.2 | ||||||||||||||||
| CK | > 1000 IU/L | 9.1 | 6.3 | 9.6 | 12.1 | 11.0 | 9.9 | ||||||||||||||||
| GGT | > 300 IU/L | 19.6 | 11.3 | 1.8 | 5.2 | 1.7 | 9.2 | ||||||||||||||||
| Glucose | > 13.88 mmol/L | 0.9 | 1.3 | 2.6 | 0.9 | 0.8 | 0.7 | ||||||||||||||||
| SGOT/AST | > 180 IU/L | 6.4 | 7.0 | 5.3 | 9.5 | 2.5 | 7.8 | ||||||||||||||||
| SGPT/ALT | > 215 IU/L | 8.5 | 4.4 | 5.3 | 7.8 | 3.4 | 9.2 | ||||||||||||||||
| Total Bilirubin | > 61.56 micromol/L | 1.3 | 0.2 | - | 0.9 | 0.8 | 2.1 | ||||||||||||||||
| Triglycerides | > 9.04 mmol/L | 33.6 | 9.4 | 9.6 | 17.2 | 3.4 | 23.4 | ||||||||||||||||
| Triglycerides | > 16.95 mmol/L | 12.6 | 0.4 | 1.8 | 2.6 | - | 11.3 | ||||||||||||||||
| Triglycerides Fasting | > 16.95 mmol/L | 9.9 | 0.3 | 1.5 | 1.3 | - | - | ||||||||||||||||
| Uric Acid | > 713.76 micromol/L | 3.8 | 0.2 | - | - | - | 1.4 | ||||||||||||||||
| Chemistry | Low | ||||||||||||||||||||||
| Potassium | < 3.0 mEq/L | 3.0 | 2.0 | - | 1.7 | - | 2.1 | ||||||||||||||||
| Hematology | High | ||||||||||||||||||||||
| Eosinophils | > 1.0 x 10⁹/L | 2.6 | 3.3 | - | 2.6 | 1.7 | 0.7 | ||||||||||||||||
| Neutrophils | > 20 x 109/L | 2.3 | 1.3 | - | - | - | - | ||||||||||||||||
Study M94-247 Advanced Patients | Study M94-245 Naïve Patients | Study M94-462 PI-Naïve Patients |
|---|
| Variable | Limit | NORVIR (n = 541) | Placebo (n=545) | NORVIR + ZDV (n = 116) | NORVIR (n = 117) | ZDV (n=119) | NORVIR + Saquinavir (n = 141) |
|---|---|---|---|---|---|---|---|
| Hematology | Low | ||||||
| Hematocrit | < 30% | 17.3 | 22.0 | 2.6 | - | 0.8 | 0.7 |
| Hemoglobin | < 80 g/L | 3.8 | 3.9 | 0.9 | - | - | - |
| Neutrophils | ≤ 0.5 x 10⁹/L | 6.0 | 8.3 | - | - | - | - |
| Red Blood Cells (RBC) | < 3.0 x 10¹²/L | 18.6 | 24.4 | 1.8 | - | 5.9 | - |
| White Blood Cells (WBC) | < 2.5 x 10⁹/L | 36.9 | 59.4 | - | 0.9 | 6.8 | 3.5 |
Definitions: CK = creatinine; ULN = upper limit of the normal range; N/A = Not Applicable; SGPT/ALT = serum glutamic-pyruvic transaminase/alanine aminotransferase; SGOT/AST = serum glutamic-oxaloacetic transaminase/aspartate aminotransferase; GGT = gamma-glutamyl transpeptidase; ZDV = zidovudine. | |||||||
Post-Market Adverse Drug Reactions
The following adverse events have been reported during post-marketing use of NORVIR. Because these reactions are reported voluntarily from a population of unknown size, it is not possible to reliably estimate their frequency or establish a causal relationship to NORVIR exposure.
| Cardiovascular System: | First-degree AV block, second-degree AV block, third-degree AV block, right bundle branch block have been reported (see WARNINGS AND PRECAUTIONS, Cardiovascular, PR Interval Prolongation). Myocardial infarction has been reported. Cardiac and neurologic events have been reported when NORVIR has been co-administered with disopyramide, mexiletine, nefazodone, fluoxetine, and beta blockers. The possibility of drug interaction cannot be excluded. |
| Endocrine System: | Hyperglycemia has been reported in individuals with and without a known history of diabetes. Cushing's syndrome and adrenal suppression have been reported when NORVIR was co-administered with fluticasone propionate, budesonide or triamcinolone. |
| Hemic and Lymphatic System: | There have been reports of increased bleeding in patients with hemophilia A or B (see WARNINGS AND PRECAUTIONS, Hematologic). |
| Immune System: | Immune Reconstitution Inflammatory Syndrome (see WARNINGS AND PRECAUTIONS, Immune Reconstitution Inflammatory Syndrome) |
| Metabolism and Nutrition Disorders: | Dehydration, usually associated with gastrointestinal symptoms, and sometimes resulting in hypotension, syncope, or renal insufficiency has been reported. Syncope, orthostatic hypotension and renal insufficiency have also been reported without known dehydration. Co-administration of NORVIR with ergotamine or dihydroergotamine has been associated with acute ergot toxicity characterized by vasospasm and ischemia of the extremities and other tissues including the central nervous system. |
| Nervous System Disorders: | There have been post-marketing reports of seizure. Cause and effect relationship has not been established. |
| Reproductive System and Breast Disorders: | Menorrhagia has been reported. |
| Skin and Subcutaneous Tissue Disorders: | Stevens-Johnson syndrome (SJS), and Toxic epidermal necrolysis (TEN). |
Pediatric Patients
The safety and pharmacokinetic profiles of NORVIR in pediatric patients below the age of 2 have not been studied. Although the database in HIV-infected patients age 2 to 16 years is much smaller, the adverse event profile seen during a clinical trial and post-marketing experience was similar to that observed for adult patients.
DRUG INTERACTIONS
Overview
When NORVIR (ritonavir) is used as a pharmacokinetic enhancer with other protease inhibitors, see the full prescribing information of that protease inhibitor including information on drug interactions.
Potential for NORVIR to Affect Other Drugs
Ritonavir is an inhibitor of cytochrome P450 3A (CYP3A) and may increase plasma concentrations of agents that are primarily metabolized by CYP3A. Agents that are extensively metabolized by CYP3A and have high first pass metabolism appear to be the most susceptible to large increases in AUC (> 3-fold) when co-administered with ritonavir. Thus, co-administration of NORVIR with drugs highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening events is contraindicated. Co-administration with other CYP3A substrates may require a dose adjustment or additional monitoring as shown in Table 5.
Ritonavir also inhibits CYP2D6 to a lesser extent. Co-administration of substrates of CYP2D6 with ritonavir could result in increases (up to 2-fold) in the AUC of the other agent, possibly requiring a proportional dosage reduction. Ritonavir also appears to induce CYP3A, CYP1A2, CYP2C9, CYP2C19, and CYP2B6 as well as other enzymes, including glucuronosyl transferase. Therefore, decreased plasma concentrations of the co-administered drugs and potential loss of therapeutic effects may signify the need for dosage alteration of these agents.
Serious Drug Interactions
|
When co-administering NORVIR with any agent having a narrow therapeutic margin, such as anticoagulants, anticonvulsants, and antiarrhythmics, special attention is warranted.
Potential for Other Drugs to Affect NORVIR
Agents which increase CYP3A activity (e.g., phenobarbital, carbamazepine, dexamethasone, phenytoin, rifampin, and rifabutin) would be expected to increase the clearance of NORVIR resulting in decreased ritonavir plasma concentrations. Tobacco use is associated with an 18% decrease in the area under the concentration-time curve (AUC) of ritonavir.
Drug-Drug Interactions
Table 5 lists the established and other potentially significant drug interactions. Alteration in dose or regimen may be recommended based on drug interaction studies or predicted interaction (see also CONTRAINDICATIONS and DRUG INTERACTIONS, Table 6 and Table 7 for magnitude of interaction).
Table 5. Established and Other Potentially Significant Drug Interactions: Alteration in Dose or Regimen Recommended Based on Drug Interaction Studies or Predicted Interaction.
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| HCV-Antiviral Agents | ||
| HCV Combination Drug: | ||
| ombitasvir/paritaprevir/ ritonavir with or without dasabuvir1 | ↑ paritaprevir | Exposures of paritaprevir may be increased when co-administered with NORVIR, therefore, co-administration is not recommended. |
| HCV Protease Inhibitors: | ||
| simeprevir1 | ↑ simeprevir | A pharmacokinetic study demonstrated that concomitant administration of simeprevir 200 mg once daily with NORVIR 100 mg twice daily resulted in an increase in simeprevir concentrations. It is not recommended to co-administer NORVIR with simeprevir. |
| glecaprevir/pibrentasvir | ↑ glecaprevir | Coadministration with ritonavir is not recommended due to an increased risk of ALT elevations associated with increased glecaprevir exposure. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| HIV-Antiretroviral Agents | ||
| HIV Protease Inhibitors: | ||
| fosamprenavir | ↑ amprenavir (↑ AUC, ↑ Cmax, ↑ Cmin) | Refer to the fosamprenavir Product Monograph for details on co-administration of fosamprenavir 700 mg twice daily with NORVIR 100 mg twice daily or fosamprenavir 1400 mg once daily with NORVIR 200 mg once daily. |
| atazanavir | ↑ atazanavir (↑ AUC, ↑ Cmax, ↑ Cmin) | Atazanavir plasma concentrations achieved with atazanavir 300 mg once daily and NORVIR 100 mg once daily are higher than those achieved with atazanavir 400 mg once daily. Refer to the atazanavir Product Monograph for details on co-administration of atazanavir 300 mg once daily, with NORVIR 100 mg once daily. |
| darunavir | ↑ darunavir (↑ AUC, ↑ Cmax, ↑ Cmin) | Refer to the darunavir Product Monograph for details on co-administration of darunavir 600 mg twice daily with NORVIR 100 mg twice daily. |
| indinavir1 | ↑ indinavir (↑ AUC, ↑ Cmax, ↑ Cmin) | Alterations in concentrations are noted when reduced doses of indinavir are co-administered with reduced dose of NORVIR. The safety and efficacy of this combination have not yet been established. The risk of nephrolithiasis may be increased when doses of indinavir equal to or greater than 800 mg twice daily are given with NORVIR. Adequate hydration and monitoring of the patients is warranted. |
| nelfinavir | ↑ M8 (major active metabolite of nelfinavir) | NORVIR increases the concentrations of nelfinavir major active metabolite, M8. This interaction is likely to involve cytochrome P450 inhibition and induction. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| saquinavir | ↑ saquinavir (↑ AUC, ↑ Cmax, ↑ Cmin) | The recommended dosage regimen is saquinavir 1000 mg with NORVIR 100 mg twice daily taken within 2 hours after a meal. Dose adjustment may be needed if other HIV-protease inhibitors are used in combination with saquinavir and NORVIR. Saquinavir and NORVIR should not be given together with rifampin due to risk of severe hepatotoxicity (presenting as increased hepatic transaminases) if the three drugs are given together. In some cases, co-administration of saquinavir and NORVIR has led to severe adverse events, mainly diabetic ketoacidosis and liver disorders, especially in patients with pre-existing liver disease. Refer to the saquinavir Product Monograph for prescribing information. |
| tipranavir | ↑ tipranavir (↑ AUC, ↑ Cmax, ↑ Cmin) | Refer to the tipranavir Product Monograph for details on co-administration of tipranavir 500 mg twice daily with NORVIR 200 mg twice daily. |
| Nucleoside Reverse Transcriptase Inhibitors: | ||
| didanosine | ↓ didanosine | Dosing of didanosine and NORVIR should be separated by 2.5 hours to avoid formulation incompatibility. |
| tenofovir | ↑ tenofovir | Lopinavir/ritonavir has been shown to increase tenofovir concentrations. Higher tenofovir concentrations could potentiate tenofovir-associated adverse events, including renal disorders. Patients receiving NORVIR and tenofovir disoproxil fumarate should be monitored for tenofovir-associated adverse events. Refer to the tenofovir Product Monograph for more information. |
| Non-Nucleoside Reverse Transcriptase Inhibitors: | ||
| delavirdine1 | ↑ ritonavir ↔ delavirdine | When used in combination with delavirdine, a dose reduction of NORVIR should be considered. Based on comparison to historical data, the pharmacokinetics of delavirdine did not appear to be affected by NORVIR. The safety and efficacy of this combination (delavirdine/ NORVIR) have not been established. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| efavirenz | ↑ efavirenz | In healthy volunteers receiving 500 mg NORVIR twice daily with efavirenz 600 mg once daily, the steady state AUC was increased by 21%. An associated increase in the AUC of NORVIR of 17% was observed. |
| Integrase Inhibitor: | ||
| raltegravir | ↓ raltegravir | A pharmacokinetic study showed that co-administration of NORVIR 100 mg twice daily and raltegravir 400 mg single dose resulted in a reduction in raltegravir plasma concentration. |
| CCR5 Antagonist: | ||
| maraviroc | ↑ maraviroc (↑ AUC, ↑ Cmax, ↑ Cmin) | When co-administered with reduced doses of NORVIR plasma levels of maraviroc increases. The dose of maraviroc should be decreased during co-administration with NORVIR. Refer to the maraviroc Product Monograph for details on co-administration of maraviroc 150 mg twice daily with NORVIR. |
| Other Agents | ||
| Alpha1-adrenoreceptor Antagonist: | ||
| alfuzosin | ↑ alfuzosin | Based on results of a drug interaction study with ketoconazole, another potent inhibitor of CYP3A4, a significant increase in alfuzosin exposure is expected in the presence of NORVIR (600 mg twice daily). Therefore, alfuzosin is contraindicated with NORVIR (see CONTRAINDICATIONS). |
| Analgesics, Narcotic: | ||
| fentanyl | ↑ fentanyl | NORVIR inhibits CYP3A4 and as a result is expected to increase the plasma concentrations of fentanyl, tramadol and propoxyphene. Careful monitoring of therapeutic and adverse effects (including respiratory depression) is recommended when NORVIR is co-administered with fentanyl, including extended-release, transdermal or transmucosal preparations. Use tramadol and propoxyphene with caution, dose reduction of these drugs may be needed. |
| tramadol | ↑ tramadol | |
| propoxyphene1 | ↑ propoxyphene | |
| methadone | ↓ methadone | Dosage increase of methadone may be considered. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| Anesthetic: | ||
| meperidine | ↓ meperidine ↑ normeperidine (metabolite) | Dosage increase and long-term use of meperidine with NORVIR are not recommended due to the increased concentrations of the metabolite normeperidine which has both analgesic activity and CNS stimulant activity (e.g., seizures). |
| Antiarrhythmics: | ||
| disopyramide, lidocaine (systemic), mexiletine | ↑ antiarrhythmics | Plasma concentrations of these drugs are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of these drugs may be needed. |
| amiodarone, bepridil1, dronedarone, flecainide, propafenone, quinidine1 | ↑ antiarrhythmics | Co-administration may lead to serious and/or life-threatening reactions, such as cardiac arrhythmias. Therefore, use of these antiarrhythmics with NORVIR is contraindicated (see CONTRAINDICATIONS). |
| Antibacterial: | ||
| fusidic acid | ↑ fusidic acid ↑ ritonavir | Coadministration of protease inhibitors, including NORVIR with fusidic acid is expected to increase fusidic acid, as well as the protease inhibitor concentration in plasma (see CONTRAINDICATIONS). |
| Anticancer agents: | ||
| dasatinib, ibrutinib, nilotinib, vincristine, vinblastine | ↑ anticancer agents | Serum concentrations increase when co-administered with NORVIR resulting in the potential for increased incidence of adverse events. Coadministration of NORVIR with ibrutinib is not recommended due to expected increase in ibrutinib exposure that could potentially result in a risk of tumor lysis syndrome. Coadministration of NORVIR with dasatinib should be avoided due to expected increase in dasatinib exposure. If the co-administration is unavoidable, close monitoring for toxicity and a dasatinib dose reduction should be considered (see SPRYCEL Product Monograph). Coadministration of NORVIR with nilotinib should be avoided due to expected increase in nilotinib exposure. If the co-administration is unavoidable, close monitoring for the QT interval prolongation is recommended (see TASIGNA Product Monograph). |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| venetoclax | ↑ venetoclax | Concomitant use of strong CYP3A inhibitors, such as NORVIR, and venetoclax may increase the risk of tumor lysis syndrome at the dose initiation and during the ramp-up phase (see CONTRAINDICATIONS). For patients who have completed the ramp-up phase and are on a steady daily dose of venetoclax, reduce the venetoclax dose by at least 75% when used with strong CYP3A inhibitors (see VENCLEXTA Product Monograph). |
| Anticoagulants: | ||
| rivaroxaban | ↑ rivaroxaban | A study has shown that co-administration of NORVIR and rivaroxaban resulted in increased exposure of rivaroxaban which may lead to risk of increased bleeding. NORVIR and rivaroxaban should not be used concomitantly (see CONTRAINDICATIONS). |
| warfarin | ↓ R-warfarin ↓ ↑ S-warfarin | Initial frequent monitoring of the INR (International Normalized Ratio) during NORVIR and warfarin co-administration is indicated. |
| Anticonvulsants: | ||
| clonazepam | ↑ clonazepam | Plasma concentrations of clonazepam and ethosuximide are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of these drugs may be needed. Plasma concentrations of divalproex and lamotrigine are expected to decrease by co-administration with NORVIR. Use with caution, dose increase of these drugs may be needed. |
| ethosuximide | ↑ ethosuximide | |
| divalproex | ↓ divalproex | |
| lamotrigine | ↓ lamotrigine | |
| carbamazepine, phenobarbital, phenytoin | ↑ carbamazepine ↓ phenytoin ↓ ritonavir | Plasma concentrations of carbamazepine are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of carbamazepine may be needed. Plasma concentrations of phenytoin are expected to decrease by co-administration with NORVIR. Use with caution, dose increase of phenytoin may be needed. Carbamazepine, phenobarbital, phenytoin, which increase CYP3A activity, would be expected to increase the clearance of NORVIR resulting in decreased ritonavir plasma concentrations. Use with caution, dose adjustment of NORVIR may be needed. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| Antidepressants: | ||
| amitriptyline, clomipramine, fluoxetine, imipramine, maprotiline, nefazodone, nortriptyline, paroxetine, sertraline, trimipramine, venlafaxine | ↑ antidepressants | NORVIR dosed as an antiretroviral agent may inhibit CYP2D6 and result in increased plasma exposure of these drugs. NORVIR dosed as a pharmacokinetic enhancer is not expected to result in any clinically meaningful increases in CYP2D6 substrates. Use with caution, dose reduction of these drugs may be needed. |
| bupropion | ↓ bupropion | Bupropion is primarily metabolized by CYP2B6. Concurrent administration of bupropion with repeated doses of NORVIR decreases bupropion levels. |
| desipramine | ↑ desipramine | A study has shown that co-administration of NORVIR and desipramine resulted in increased exposure of desipramine. Dosage reduction and concentration monitoring of desipramine is recommended. |
| trazodone | ↑ trazodone | Concomitant use of NORVIR and trazodone increases concentrations of trazodone. Adverse events of nausea, dizziness, hypertension and syncope have been observed. If trazodone is used with a CYP3A4 inhibitor, such as NORVIR, the combination should be used with caution and a lower dose of trazodone should be considered. |
| Antiemetics: | ||
| dronabinol | ↑ dronabinol | Plasma concentrations of dronabinol are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of dronabinol may be needed. |
| Antifungal: | ||
| ketoconazole | ↑ ketoconazole | High doses of ketoconazole or itraconazole (> 200 mg/day) are not recommended. |
| itraconazole | ↑ itraconazole | |
| Antigout: | ||
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| colchicine | ↑ colchicine | For patients with renal and/or hepatic impairment:
For patients with normal renal and/or hepatic function:
|
| Anti-infective: | ||
| clarithromycin | ↑ clarithromycin | For patients with renal impairment, the following dosage adjustments should be considered:
No dose adjustment for patients with normal renal function is necessary. |
| Antimycobacterial: | ||
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| rifabutin | ↑ rifabutin and rifabutin metabolite ↓ ritonavir | Dosage reduction of rifabutin by at least three-quarters of the usual dose of 300 mg/day is recommended (e.g. 150 mg every other day or three times a week). Further dosage reduction may be necessary. |
| rifampin | ↓ ritonavir | May lead to loss of virologic response. Alternate antimycobacterial agents, such as rifabutin should be considered (see Antimycobacterial: rifabutin) for dose reduction recommendations. |
| Antiparasitics: | ||
| atovaquone | ↓ atovaquone | Plasma concentrations of atovaquone are expected to decrease by co-administration with NORVIR. Use with caution, dose increase of atovaquone may be needed. Plasma concentrations of quinine are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of quinine may be needed. |
| quinine | ↑ quinine | |
| Anxiolytics/Sedative/Hypnotics: | ||
| midazolam, oral1 | ↑ midazolam | Midazolam is extensively metabolized by CYP3A4. Increases in the concentration of midazolam are expected to be significantly higher with oral than parenteral administration. Co-administration of oral midazolam with NORVIR is contraindicated (see CONTRAINDICATIONS). |
| midazolam, parenteral | ↑ midazolam | Concomitant use of parenteral midazolam with NORVIR may increase plasma concentrations of midazolam. Coadministration should be done in a setting which ensures close clinical monitoring and appropriate medical management in case of respiratory depression and/or prolonged sedation. Dosage reduction for midazolam should be considered, especially if more than a single dose of midazolam is administered. |
| buspirone, clorazepate, diazepam, estazolam1, flurazepam, zolpidem | ↑ Anxiolytics/Sedatives/Hypnotics | Plasma concentrations of these drugs are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of these drugs may be needed. |
| Beta-blockers: | ||
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| metoprolol, timolol | ↑ beta-blockers | Plasma concentrations of these drugs are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of these drugs may be needed. |
| Bronchodilator: | ||
| theophylline | ↓ theophylline | Increased dosage of theophylline may be required; therapeutic monitoring should be considered. |
| Calcium channel blockers: | ||
| diltiazem, nifedipine, verapamil | ↑ calcium channel blockers | Plasma concentrations of these drugs are expected to increase by co-administration with NORVIR. Use with caution, dose reduction of these drugs may be needed. |
| Corticosteroids: | ||
| fluticasone propionate, budesonide, triamcinolone | ↑ fluticasone ↑ budesonide ↑ triamcinolone | Concomitant use of NORVIR and inhaled, injectable, or intranasal fluticasone propionate, budesonide, triamcinolone, or other glucocorticoids that are metabolized by CYP3A4 are not recommended unless the potential benefit of treatment outweighs the risk of systemic corticosteroid side effects, including Cushing’s syndrome and adrenal suppression. Concomitant use of NORVIR and fluticasone propionate, budesonide or triamcinolone can significantly increase fluticasone propionate, budesonide or triamcinolone plasma concentrations and reduce serum cortisol concentrations. Consider alternatives to fluticasone propionate, budesonide or triamcinolone particularly for long-term use. |
| dexamethasone | ↑dexamethasone ↓ ritonavir | Dexamethasone, which increases CYP3A activity, would be expected to increase the clearance of NORVIR resulting in decreased ritonavir plasma concentrations. Plasma concentrations of dexamethasone and prednisone are expected to increase by co-administration with NORVIR. Use with caution, dose adjustment of these drugs may be needed. |
| prednisone | ↑ prednisone | |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| digoxin | ↑ digoxin | A literature report has shown that co-administration of NORVIR (300 mg every 12 hours) and digoxin resulted in significantly increased digoxin levels. Caution should be exercised when co-administrating NORVIR and digoxin, with appropriate monitoring of serum levels. |
| Endothelin receptor antagonist: | ||
| bosentan | ↑ bosentan | Co-administration of bosentan in patients already on NORVIR for at least 10 days: Start at 62.5 mg once daily or every other day based upon individual tolerability. Coadministration of NORVIR in patients on bosentan: Discontinue use of bosentan at least 36 hours prior to initiation of NORVIR. After at least 10 days following the initiation of NORVIR, resume bosentan at 62.5 mg once daily or every other day based upon individual tolerability. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| PDE5 Inhibitors: | ||
| sildenafil, tadalafil, vardenafil | ↑ sildenafil | Particular caution should be used when prescribing PDE5 inhibitors for the treatment of erectile dysfunction in patients receiving NORVIR. Co-administration of NORVIR with these drugs is expected to substantially increase their concentrations and may result in increase in associated adverse events, such as hypotension, syncope, visual changes, and prolonged erection. Use of PDE-5 Inhibitors for Erectile Dysfunction Sildenafil may be used with caution at reduced doses of 25 mg every 48 hours with increased monitoring for adverse events. Tadalafil may be used with caution at reduced doses of 10 mg every 72 hours with increased monitoring for adverse events. Vardenafil should not be used with NORVIR (see CONTRAINDICATIONS). Use of PDE-5 Inhibitors for Pulmonary Arterial Hypertension Coadministration of NORVIR and tadalafil for the treatment of pulmonary arterial hypertension is not recommended. The use of sildenafil or vardenafil is contraindicated with NORVIR (see CONTRAINDICATIONS). |
| Hypolipidemics, HMG- CoA Reductase Inhibitors: | ||
| lovastatin, simvastatin | ↑ lovastatin, simvastatin | The HMG-CoA reductase inhibitors simvastatin and lovastatin are highly dependent on CYP3A for metabolism, thus concomitant use of NORVIR with simvastatin or lovastatin is contraindicated due to an increased risk of myopathy including rhabdomyolysis (see CONTRAINDICATIONS). |
| lomitapide | ↑ lomitapide | Lomitapide is a sensitive substrate for CYP3A4 metabolism. CYP3A4 inhibitors increase the exposure of lomitapide, with strong inhibitors increasing exposure approximately 27-fold. Concomitant use of moderate or strong CYP3A4 inhibitors with lomitapide is contraindicated. |
| atorvastatin, rosuvastatin | ↑ atorvastatin, rosuvastatin | Caution must also be exercised and reduced doses |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| should be considered if NORVIR is used concurrently with atorvastatin, which is metabolized to a lesser extent by CYP3A4. While rosuvastatin elimination is not dependent on CYP3A, an elevation of rosuvastatin exposure has been reported with NORVIR co-administration. Use the lowest doses of atorvastatin or rosuvastatin with careful monitoring for signs and symptoms of myopathy or rhabdomyolysis. If treatment with an HMG-CoA reductase inhibitor is indicated, pravastatin or fluvastatin is recommended. | ||
| Immunosuppressants : | ||
| cyclosporine, everolimus, tacrolimus, rapamycin1 | ↑ immunosuppressants | Therapeutic concentration monitoring is recommended for immunosuppressant agents when co-administered with NORVIR. |
| Neuroleptics/Antipsychotics: | ||
| lurasidone | ↑ lurasidone | Due to CYP3A inhibition by NORVIR, concentrations of lurasidone are expected to increase. Co-administration of lurasidone with NORVIR is contraindicated (see CONTRAINDICATIONS). |
| perphenazine, risperidone, thioridazine1 | ↑ neuroleptics | NORVIR dosed as an antiretroviral agent may inhibit CYP2D6 resulting in increases in the plasma concentration of perphenazine, risperidone, and thioridazine. NORVIR dosed as a pharmacokinetic enhancer is not expected to result in any clinically meaningful increases in CYP2D6 substrates. Use with caution, dose reduction of these drugs may be needed. |
| pimozide | ↑ pimozide | Co-administration of NORVIR with pimozide is contraindicated as it may lead to serious and/or life-threatening reactions, such as cardiac arrhythmias (see CONTRAINDICATIONS). |
| quetiapine | ↑ quetiapine | Caution should be exercised when NORVIR is co-administered with quetiapine. Due to CYP3A inhibition by NORVIR, concentrations of quetiapine are expected to increase, which may lead to quetiapine-related toxicities. Consider alternative antiretroviral therapy to avoid increase in quetiapine exposures. If co-administration is necessary, reduce the dose of quetiapine and monitor for quetiapine-associated adverse reactions. Refer to the quetiapine Product Monograph for recommendations on adverse reaction monitoring. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of NORVIR or Concomitant Drug | Clinical Comment |
|---|---|---|
| Oral Contraceptive or Patch Contraceptive: | ||
| ethinyl estradiol | ↓ ethinyl estradiol | Dosage increase or alternate contraceptive measures should be considered. |
| Stimulants: | ||
| methamphetamine | ↑ methamphetamine | NORVIR dosed as an antiretroviral agent may inhibit CYP2D6 and as a result is expected to increase concentrations of amphetamine and its derivatives. NORVIR dosed as a pharmacokinetic enhancer is not expected to result in any clinically meaningful increases in CYP2D6 substrates. Use with caution, dose reduction of these drugs may be needed. |
1: Products not marketed in Canada. ↑ Indicates increase; ↓ indicates decrease; ↔ indicates no change. | ||
Assessment of Drug Interactions
For details regarding the ritonavir pharmacokinetics refer to section (ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
The effects of co-administration of ritonavir on the AUC, Cmax, and Cmin are summarized in Table 6 and Table 7.
Table 6. Drug Interactions: Pharmacokinetic Parameters for Ritonavir in the Presence of the Co-administered Drug (See Table 5 for Recommended Alterations in Dose or Regimen)
| Co-Administered Drug | Dose of Co-Administered Drug | NORVIR Dosage | n | AUC % (95% CI) | Cmax % (95% CI) | Cmin % (95% CI) |
|---|---|---|---|---|---|---|
| Antidepressants | ||||||
| Fluoxetine | 30 mg every 12 h 8 days | 600 mg single dose | 16 | ↑ 19% (7, 34%) | ↔ | ND |
| Antifungal | ||||||
| Fluconazole | 400 mg Day 1, 200 mg daily 4 days | 200 mg every 6 h 4 days | 8 | ↑ 12% (5, 20%) | ↑ 15% (7, 22%) | ↑ 14% (0, 26%) |
| Ketoconazole | 200 mg daily 7 days | 500 mg every 12 h 10 days | 12 | ↑ 18% (-3, 52%) | ↑ 10% (-11, 36%) | ND |
| Voriconazole | 400 mg every 12 h, 1 day; then 200 mg every 12 h 8 days | 400 mg every 12 h 9 days | 17 | ↔ | ↔ | ND |
| Anti-infective | ||||||
| Clarithromycin | 500 mg every 12 h 4 days | 200 mg every 8 h 4 days | 22 | ↑ 12% (2, 23%) | ↑ 15% (2, 28%) | ↑ 14% (-3, 36%) |
| Antimycobacterial | ||||||
| Rifampin | 600 mg or 300 mg daily 10 days | 500 mg every 12 h 20 days | 7,91 | ↓ 35% (7, 55%) | ↓ 25% (-5, 46%) | ↓ 49% (-14, 91%) |
| HIV-Antiretroviral Agents | ||||||
| Didanosine | 200 mg every 12 h 4 days, about 2.5 h before NORVIR | 600 mg every 12 h 4 days | 12 | ↔ | ↔ | ↔ |
| Zidovudine | 200 mg every 8 h 4 days | 300 mg every 6 h 4 days | 10 | ↔ | ↔ | ↔ |
↑ Indicates increase; ↓ indicates decrease; ↔ indicates no change. 1: Parallel group design; entries are subjects receiving combination and control regimens, respectively. Definitions: h = hour; ND = not detected | ||||||
Table 7. Drug Interactions: Pharmacokinetic Parameters for Co-administered Drug in the Presence of ritonavir (See Table 5 for Recommended Alterations in Dose or Regimen)
| Co-Administered Drug | Dose of Co-Administered Drug | NORVIR Dosage | n | AUC % (95% Cl) | Cmax % (95% Cl) | Cmin % (95% Cl) |
|---|---|---|---|---|---|---|
| Analgesics, Narcotic | ||||||
| Methadone1 | 5 mg single dose | 500 mg every 12h 15 days | 11 | ↓ 36% (16, 52%) | ↓ 38% (28, 46%) | ND |
| Anesthetic | ||||||
| Meperidine | 50 mg oral single dose | 500 mg every 12h 10 days | 8 | ↓ 62% (59, 65%) | ↓ 59% (42, 72%) | ND |
| Normeperidine metabolite | 6 | ↑ 47% (-24, 345%) | ↑ 87% (42, 147%) | ND | ||
| Anticoagulants | ||||||
Warfarin S-Warfarin | 5 mg single dose | 400 mg every 12h 12 days | 12 | ↑ 9% (-17, 44%)2 | ↓ 9% (-16, -2%)2 | ND |
| R-Warfarin | ↓ 33% (-38, -27%)2 | ↔ | ND | |||
| Antidepressant | ||||||
| Trazodone | 50 mg single dose | 200 mg every 12h 10 days | 10 | ↑ 2.4-fold | ↑ 34% | |
| Desipramine | 100 mg single dose | 500 mg every 12h 12 days | 14 | ↑ 145% (103, 211%) | ↑ 22% (12, 35%) | ND |
| 2-OH desipramine metabolite | ↓ 15% (3, 26%) | ↓ 67% (62, 72%) | ND | |||
| Antifungal | ||||||
| Ketoconazole | 200 mg daily 7 days | 500 mg every 12h 10 days | 12 | ↑ 3.4-fold (2.8, 4.3X) | ↑ 55% (40, 72%) | ND |
| Voriconazole | 400 mg every 12h, 1day; then 200 mg every 12h 8 days | 400 mg every 12h 9 days | 17 | ↓ 82% | ↓ 66% | not reported |
| Anti-infective | ||||||
| Clarithromycin | 500 mg every 12h 4 days | 200 mg every 8h 4 days | 22 | ↑ 77% (56, 103%) | ↑ 31% (15, 51%) | ↑ 2.8-fold (2.4, 3.3X) |
| Co-Administered Drug | Dose of Co-Administered Drug | NORVIR Dosage | n | AUC % (95% Cl) | Cmax % (95% Cl) | Cmin % (95% Cl) |
|---|---|---|---|---|---|---|
| 14-OH clarithromycin metabolite | ↓100% | ↓ 99% | ↓ 100% | |||
| Antimicrobial | ||||||
| Sulfamethoxazole3 | 800 mg single dose | 500 mg every 12h 12 days | 15 | ↓ 20% (16, 23%) | ↔ | ND |
| Trimethoprim3 | 160 mg single dose | 500 mg every 12h 12 days | 15 | ↑ 20% (3, 43%) | ↔ | ND |
| Antimycobacterial | ||||||
| Rifabutin | 150 mg daily 16 days | 500 mg every 12h 10 days | 5,118 | ↑ 4-fold (2.8, 6.1X) | ↑ 2.5-fold (1.9, 3.4X) | ↑ 6-fold (3.5, 18.3X) |
25-O-desacetyl rifabutin metabolite | ↑ 38-fold (28, 56X) | ↑ 16-fold (13, 20X) | ↑ 181-fold (ND) | |||
| Bronchodilator | ||||||
| Theophylline | 3 mg/kg every 8h 15 days | 500 mg every 12h 10 days | 13, 118 | ↓ 43% (42, 45%) | ↓ 32% (29, 34%) | ↓ 57% (55, 59%) |
| CCR5 Antagonist | ||||||
| Maraviroc | 100 mg every 12h | 100 mg every 12h | 8 | ↑ 28% | ↑ 161% | not reported |
| Corticosteroid | ||||||
| Fluticasone propionate aqueous nasal spray | 200 mcg daily 7 days | 100 mg every 12h 7 days | 18 | ↑ approx. 350-fold5 | ↑ approx. 25-fold5 | |
| HIV-Antiretroviral Agents | ||||||
| Atazanavir | 300 mg every 24h Days 1 to 20 | 100 mg every 24h Days 11 to 20 | 28 | ↑ 3.4-fold | ↑ 1.9-fold | ↑ 11.9-fold |
| Darunavir | 800 mg single dose | Titrated: 300 to 600 mg every 12h over 6 days | 8 | ↑ 9.2-fold | ↑ 2-fold | not reported |
| Didanosine | 200 mg every 12h 4 days, about 2.5 h before NORVIR | 600 mg every 12h 4 days | 12 | ↓ 13% (0, 23%) | ↓ 16% (5, 26%) | ↔ |
| Co-Administered Drug | Dose of Co-Administered Drug | NORVIR Dosage | n | AUC % (95% Cl) | Cmax % (95% Cl) | Cmin % (95% Cl) |
|---|---|---|---|---|---|---|
Indinavir6 Day 14 | 400 mg every 12h 15 days | 400 mg every 12h 15 days | 10 | ↑ 6% (-14, 29%) | ↓ 51% (40, 61%) | ↑ 4-fold (2.8, 6.8X) |
| Day 15 | ↓ 7% (-22, 28%) | ↓ 62% (52, 70%) | ↑ 4-fold (2.5, 6.5X) | |||
| Saquinavir6 | 400 mg every 12h steady state | 400 mg every 12h steady-state | 7 | ↑ 17-fold (9, 31X) | ↑ 14-fold (7, 28X) | ND |
| Raltegravir | 400 mg single dose | 100 mg every 12 h 16 days | 10 | ↓ 16% (-30, 1%) | ↓ 24% (-45, 4%) | ↓ 1% (-30, 40%) |
| Zidovudine | 200 mg every 8h 4 days | 300 mg every 6h 4 days | 9 | ↓ 25% (15, 34%) | ↓ 27% (4, 45%) | ND |
| Oral Contraceptive or Patch Contraceptive | ||||||
| Ethinyl estradiol | 50 mcg single dose | 500 mg every 12h 16 days | 23 | ↓ 40% (31, 49%) | ↓ 32% (24, 39%) | ND |
| PDE-5 Inhibitors | ||||||
| Sildenafil | 100 mg single dose | 500 mg b.i.d.7 8 days | 28 | ↑ 11-fold | ↑ 4-fold | ND |
| Tadalafil | 20 mg single dose | 200 mg every 12h | ↑ 124% | ↔ | ND | |
| Vardenafil | 5 mg | 600 mg every 12h | ↑ 49-fold | ↑ 13-fold | ND | |
| Sedative/hypnotics | ||||||
| Alprazolam | 1 mg single dose | 500 mg every 12h 10 days | 12 | ↓ 12% (-5, 30%) | ↓ 16% (5, 27%) | ND |
| Co-Administered Drug | Dose of Co-Administered Drug | NORVIR Dosage | n | AUC % (95% Cl) | Cmax % (95% Cl) | Cmin % (95% Cl) |
|---|---|---|---|---|---|---|
1: Effects were assessed on a dose normalized comparison to a methadone 20 mg single dose. 2: 90% CI presented for R- and S-warfarin AUC and Cmax ratios. 3: Sulfamethoxazole and trimethoprim taken as single combination tablet. 4: NORVIR and indinavir were co-administered for 15 days; Day 14 doses were administered after a 15% fat breakfast (757 Kcal) and 9% fat evening snack (236 Kcal), and Day 15 doses were administered after a 15% fat breakfast (757 Kcal) and 32% fat dinner (815 Kcal). Indinavir Cmin was also increased 4-fold. Effects were assessed relative to an indinavir 800 mg every 8h regimen under fasting conditions. 5: This significant increase in plasma fluticasone propionate exposure resulted in a significant decrease (86%) in plasma cortisol AUC. 6: Comparison to a standard saquinavir 600 mg every 8h regimen (n = 114). 7: Subjects in the entire study, a subset of subjects were administered the specified regimen. 8: Parallel group design; entries are subjects receiving combination and control regimens, respectively. ↑ Indicates increase; ↓ indicates decrease; ↔ indicates no change. Definitions: b.i.d. = twice daily; ND = not detected. | ||||||
Drug-Food Interactions
It is recommended that NORVIR be taken with meals, if possible. Refer to ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Absorption and to CLINICAL TRIALS for information on the effect of food on ritonavir pharmacokinetics.
Drug-Herb Interactions
Concomitant use of NORVIR and St. John’s wort (Hypericum perforatum) or products containing St. John’s wort is contraindicated. Co-administration of protease inhibitors, including NORVIR, with St. John’s wort is expected to substantially decrease protease inhibitor concentrations and may result in sub-optimal levels of ritonavir and lead to loss of virologic response and possible resistance to NORVIR or to the class of protease inhibitors (see CONTRAINDICATIONS).
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
General Dosing Guidelines
Patients should be aware that frequently observed adverse events, such as mild to moderate gastrointestinal disturbances and paresthesias, may diminish as therapy is continued. In addition, patients initiating combination regimens with NORVIR (ritonavir) and other antiretroviral agents may improve gastrointestinal tolerance by initiating NORVIR alone and subsequently adding the other antiretroviral agents before completing two weeks of NORVIR monotherapy. The long-term effects of dose escalation on efficacy have not been established.
Dose Modification for NORVIR
Dose reduction of NORVIR is necessary when used with other protease inhibitors: atazanavir, darunavir, fosamprenavir, saquinavir, and tipranavir.
When NORVIR is used as a pharmacokinetic enhancer with other protease inhibitors, see the full prescribing information and clinical study information of that protease inhibitor.
Recommended Dose and Dosage Adjustment
Adult Patients
The recommended dose of NORVIR is 600 mg (six tablets) twice daily orally and should be taken with a meal.
NORVIR tablets should be swallowed whole with water and not chewed, broken or crushed.
Some patients experience nausea upon initiation of 600 mg twice daily dosing. Use of a dose titration schedule may help to reduce treatment-emergent adverse events while maintaining appropriate ritonavir plasma levels. NORVIR should be started at no less than 300 mg twice daily and increased by 100 mg twice daily increments up to 600 mg twice daily. The titration period should not exceed 14 days.
Pediatric Patients (2 to 16 years of age)
NORVIR should be used in combination with other antiretroviral agents.
Missed Dose
If a dose of this medication has been missed, it should be taken as soon as possible. However, if it is almost time for the next dose, skip the missed dose and go back to the regular dosing schedule. Do not double doses.
Administration
NORVIR is administered orally.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
Acute Overdosage
Human Overdose Experience
Human experience of acute overdose with NORVIR (ritonavir) is limited. One patient in clinical trials took NORVIR 1500 mg/day for two days. The patient reported paresthesias which resolved after the dose was decreased.
A post-marketing case of renal failure with eosinophilia has been reported with NORVIR overdose.
Management of Overdosage
Administration of activated charcoal may be used to aid in removal of unabsorbed drug. Treatment of overdose with NORVIR consists of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient. There is no specific antidote for overdose with NORVIR. Since ritonavir is extensively metabolized by the liver and is highly protein-bound, dialysis is unlikely to be beneficial in significant removal of the drug.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
NORVIR is an inhibitor of HIV protease with activity against the Human Immunodeficiency Virus (HIV).
Ritonavir is an orally active peptidomimetic inhibitor of both the HIV-1 and HIV-2 proteases. Inhibition of HIV protease renders the enzyme incapable of processing the gag-pol polyprotein precursor which leads to the production of HIV particles with immature morphology that are unable to initiate new rounds of infection. Ritonavir has selective affinity for the HIV protease and has little inhibitory activity against human aspartyl proteases.
Pharmacodynamics
In vitro data indicate that ritonavir is active against all strains of HIV tested in a variety of transformed and primary human cell lines. The concentration of drug that inhibits 50% and 90% (EC50, EC90) of viral replication is approximately 0.02 and 0.11 microM, respectively. Studies which measured direct cell toxicity of ritonavir on several cell lines showed no direct toxicity at concentrations up to 25 microM, with a resulting in vitro therapeutic index of at least 1000.
Effects on the Electrocardiogram
A Phase 1, multiple-dose, open-label, placebo and active controlled (moxifloxacin 400 mg once daily), randomized crossover study was conducted in healthy volunteers. NORVIR was dosed at 400 mg twice daily and on Day 3, ritonavir concentrations were approximately 1.5 fold higher than that observed with the 600 mg twice daily dose at steady state. At these increased concentrations, the maximum increase in QTcF was 5.5 msec. This increase is not clinically significant. No subject experienced an increase in QTcF of ≥ 60 msec from baseline or a QTcF interval exceeding the potentially clinically relevant threshold of 500 msec. Maximum PR interval was 252 msec and no second or third degree heart block was observed. Exposure-response analysis predicted that the PR effect of ritonavir plateaus around 20 msec, thus ritonavir 600 mg twice daily is unlikely to result in clinically significant PR prolongation (see WARNINGS AND PRECAUTIONS).
Pharmacokinetics
The pharmacokinetics of ritonavir have been studied in healthy volunteers and HIV-infected patients (CD4 ≥ 50 cells/microliter). See Table 8 for ritonavir pharmacokinetic characteristics.
Table 8. Ritonavir Pharmacokinetic Characteristics
| Parameter | n | Values (Mean ± SD) |
|---|---|---|
| Cmax SS1 | 10 | 11.2 ± 3.6 mcg/mL |
| Ctrough SS1 | 10 | 3.7 ± 2.6 mcg/mL |
| Vβ/F2 | 91 | 0.41 ± 0.25 L/kg |
| t½ | 3 to 5 h | |
| CL/F SS1 | 10 | 8.8 ± 3.2 L/h |
| CL/F2 | 91 | 4.6 ± 1.6 L/h |
| CLR | 62 | < 0.1 L/h |
| RBC/Plasma Ratio | 0.14 | |
| Percent Bound3 | 98 to 99% | |
1: SS = steady state; patients taking NORVIR 600 mg every 12h. 2: Single NORVIR 600 mg dose. 3: Primarily bound to human serum albumin and alpha-1 acid glycoprotein over the ritonavir concentration range of 0.01 to 30 mcg/mL. | ||
Absorption
NORVIR tablets are not bioequivalent to NORVIR capsules. Under moderate fat conditions (857 kcal; 31% fat, 13% protein, 56% carbohydrates), when a single 100 mg NORVIR dose was administered as a tablet compared with a capsule, AUC(0-∞) met equivalence criteria but mean Cmax was increased by 26% (92.8% confidence intervals: +15 to +39%).
Effect of Food on Oral Absorption
A food effect is observed for NORVIR tablets. Food decreased the bioavailability of the ritonavir tablets when a single 100 mg dose of NORVIR was administered. Under high fat conditions (907 kcal; 52% fat, 15% protein, 33% carbohydrates), a 23% decrease in mean AUC(0-∞) [90% confidence intervals: -30 to -15%], and a 23% decrease in mean Cmax [90% confidence intervals: -34 to -11%] was observed relative to fasting conditions. Under moderate fat conditions, a 21% decrease in mean AUC(0-∞) [90% confidence intervals: -28 to -13%], and a 22% decrease in mean Cmax [90% confidence intervals: -33 to -9%] was observed relative to fasting conditions.
However, the type of meal administered did not change ritonavir tablet bioavailability when high fat was compared to moderate fat meals.
Distribution
The protein binding of ritonavir in human plasma was noted to be approximately 98 to 99%. Ritonavir binds to both human α-1-acid glycoprotein (AAG) and human serum albumin (HSA) with comparable affinities. Total plasma protein binding is constant over the concentration range of 1 to 100 mcg/mL.
Tissue distribution studies with 14C-labeled ritonavir in rats showed the liver, adrenals, pancreas, kidneys and thyroid to have the highest concentrations of drug. Tissue to plasma ratios of approximately one, measured in rat lymph nodes, suggest that ritonavir distributes into lymphatic tissue. Ritonavir penetrates minimally into the brain.
Metabolism
Nearly all of the plasma radioactivity after a single oral 600 mg dose of 14C-ritonavir oral solution (n = 5) was attributed to unchanged ritonavir. Five ritonavir metabolites have been identified in human urine and feces. The isopropyl thiazole oxidation metabolite (M-2) is the major metabolite and has antiviral activity similar to that of parent drug; however, the concentrations of this metabolite in plasma are low. Studies utilizing human liver microsomes have demonstrated that cytochrome P450 3A (CYP3A) is the major isoform involved in ritonavir metabolism, although CYP2D6 also contributes to the formation of M-2.
Excretion
In a study of five subjects receiving a 600 mg dose of 14C-ritonavir oral solution, 11.3 ± 2.8% of the dose was excreted into the urine, with 3.5 ± 1.8% of the dose excreted as unchanged parent drug. In that study, 86.4 ± 2.9% of the dose was excreted in the feces with 33.8 ± 10.8% of the dose excreted as unchanged parent drug. Upon multiple dosing, ritonavir accumulation is less than predicted from a single dose possibly due to a time and dose-related increase in clearance.
Special Populations and Conditions
Pediatrics
The pharmacokinetic profile of NORVIR in pediatric patients below the age of 2 years has not been established. Steady-state pharmacokinetics were evaluated in 37 HIV-infected patients ages 2 to 14 years receiving doses ranging from 250 mg/m2 twice daily to 400 mg/m2 twice daily. Across dose groups, ritonavir steady-state oral clearance (CL/F/m2) was approximately 1.5 times faster in pediatric patients than in adult subjects. Ritonavir concentrations obtained after 350 to 400 mg/m2 twice daily in pediatric patients were comparable to those obtained in adults receiving 600 mg (approximately 330 mg/m2) twice daily.
Geriatrics
No age-related pharmacokinetic differences have been observed in adult patients (18 to 63 years). Ritonavir pharmacokinetics have not been studied in older patients.
Gender
A study of ritonavir pharmacokinetics in healthy males and females showed no statistically significant differences in the pharmacokinetics of ritonavir.
Race
Pharmacokinetic differences due to race have not been identified.
Weight
Ritonavir pharmacokinetic parameters were not statistically significantly associated with body weight or lean body mass.
Hepatic Insufficiency
In six HIV-infected adult subjects with mild hepatic insufficiency dosed with NORVIR 400 mg twice daily, ritonavir exposures were similar to control subjects dosed with 500 mg twice daily. Results indicate that dose adjustment is not required in patients with mild hepatic impairment.
Adequate pharmacokinetic data are not available for patients with moderate hepatic impairment. Protein binding of ritonavir was not statistically significantly affected by mildly or moderately impaired hepatic function.
Renal Insufficiency
Ritonavir pharmacokinetics have not been studied in patients with renal insufficiency; however, since renal clearance is negligible, a decrease in total body clearance is not expected in patients with renal insufficiency.
Because ritonavir is highly protein bound it is unlikely that it will be significantly removed by dialysis (see OVERDOSAGE).
STORAGE AND STABILITY
Store NORVIR (ritonavir) film-coated tablets between 15 and 30°C. Dispense in original container or USP equivalent container (60 mL or less). For patient use: exposure of the product to high humidity outside the original or USP equivalent tight container (60 mL or less) for longer than 2 weeks is not recommended.
DOSAGE FORMS, COMPOSITION AND PACKAGING
NORVIR (ritonavir) is available as 100 mg film-coated tablets.
NORVIR film-coated tablets are white oval tablets debossed with the Abbott logo and the Abbo-Code “NK” on the same side. NORVIR is available as 100 mg tablets. Each bottle contains 30 tablets.
Listing of Non-Medicinal Ingredients
Each white film-coated oval tablet contains 100 mg of ritonavir with the following non-medicinal ingredients: copovidone, colloidal silicon dioxide/colloidal anhydrous silica, dibasic calcium phosphate anhydrous/calcium hydrogen phosphate anhydrous, sorbitan monolaurate/sorbitan laurate, sodium stearyl fumarate. The film coating ingredients include: colloidal silicon dioxide/colloidal silica anhydrous, hydroxypropyl cellulose, hypromellose, polyethylene glycol 400/macrogol type 400, polyethylene glycol 3350/macrogol type 3350, polysorbate 80, talc and titanium dioxide E171.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | ritonavir | |
| Chemical name: | 10-Hydroxy-2-methyl-5-(1-methylethyl)-1- [2-(1-methylethyl)-4-thiazolyl]-3,6-dioxo-8,11-bis(phenylmethyl)-2,4,7,12-tetraazatridecan-13-oic acid, 5-thiazolylmethyl ester, [5S-(5R*,8R*,10R*,11R*)] | |
| Molecular formula and molecular mass: | C37H48N6O5S2 | 720.95 |
| Structural formula: | 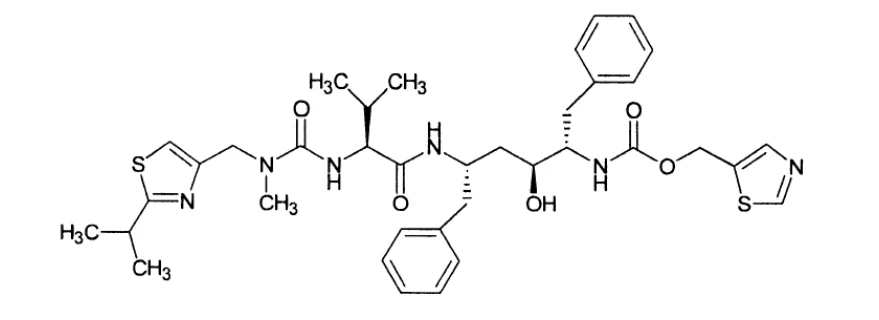 | |
| Physicochemical properties: | Ritonavir is a white to light tan powder. | |
| Solubility: | Ritonavir has a bitter metallic taste. It is freely soluble in methanol and ethanol, soluble in isopropanol and practically insoluble in water. | |
CLINICAL TRIALS
The activity of NORVIR (ritonavir) as monotherapy or in combination with nucleoside reverse transcriptase inhibitors has been evaluated in 1446 patients enrolled in two double-blind, randomized trials. NORVIR therapy in combination with zidovudine and zalcitabine was also evaluated in an open-label, non-comparative study of 32 patients.
Study Demographics and Trial Design
Table 9. Summary of Patient Demographics for Clinical Trials in Specific Indication
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age (Range) | Gender Race (% M/F) (%C/O)1 | Mean Baseline CD4 Cell Count (Range) |
|---|---|---|---|---|---|---|
| Advanced Patients with Prior Antiretroviral Therapy | ||||||
| M94-247 | Double blind, randomized, two-arm, parallel, multicenter international | NORVIR liquid or semi-solid capsules (600 mg b.i.d.) vs. Placebo Oral 6 months double-blind followed by 14 months open-label follow-up | 1090 | 38.9 years (15-72) | 92/8 86/14 | 32 cells/microliter (0-154)2 |
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age (Range) | Gender Race (% M/F) (%C/O)1 | Mean Baseline CD4 Cell Count (Range) |
|---|---|---|---|---|---|---|
| Patients Without Prior Antiretroviral Therapy | ||||||
| M94-245 | Double blind, randomized, three-arm, parallel, multicenter | NORVIR liquid or semi-solid capsules (600 mg b.i.d.) vs. zidovudine capsules (200 mg t.i.d.) vs. NORVIR liquid or semi-solid capsules (600 mg b.i.d.) + zidovudine capsules (200 mg t.i.d.) Oral 8 to 12 months | 356 | 36.0 years (18-69) | 91/9 83/17 | 364 cells/ microliter Range: 139-1054 (200-500)3 |
| Combination Therapy in Anti-retroviral Naïve Patients | ||||||
| M94-208 | Phase II, open-label, multicenter | Triple Therapy Combination: NORVIR (600 mg b.i.d.) + zidovudine (200 mg t.i.d.) + zalcitabine (0.75 mg t.i.d.) Oral 6 months | 32 | 38.1 years (29-52) | 88/12 97/3 | Median: 83 > 100 cells/ microliter (81%)4 |
1: % Male/Female; % Caucasian/Other 2: Approximately 50% of patients had baseline CD4 cell counts ≤ 20 cells/microliter, and only 22% had counts > 50 cells/microliter. 3: Approximately 75% of the patients were evenly distributed between this range 4: The majority (81%) of patients had baseline CD4 values > 100 cells/microliter Definitions: b.i.d. = twice daily; t.i.d. = three times daily. | ||||||
Study Results
Advanced Patients with Prior Antiretroviral Therapy
Study M94-247 was a randomized, double-blind trial conducted in HIV-infected patients with at least nine months of prior antiretroviral therapy and baseline CD4 cells counts ≤ 100 cells/microliter. NORVIR 600 mg twice daily or placebo was added to each patient's baseline antiretroviral therapy regimen, which could have consisted of up to two approved antiretroviral agents. The study accrued 1090 patients, with mean baseline CD4 cell count at study entry of 32 cells/ microliter. Median duration of follow-up was 6 months.
The six month cumulative incidence of clinical disease progression or death was 17% for patients randomized to NORVIR compared to 34% for patients randomized to placebo. This difference in rates was statistically significant.
The six-month cumulative mortality was 5.8% for patients randomized to NORVIR and 10.1% for patients randomized to placebo. This difference in rates was statistically significant.
In addition, analyses of mean CD4 cell count changes from baseline over the first 16 weeks of study for the first 211 patients enrolled (mean baseline CD4 cell count = 29 cells/microliter) showed that NORVIR was associated with larger increases in CD4 cell counts than was placebo. Compared to placebo, NORVIR also produced a greater mean decrease in HIV RNA levels from baseline.
Patients Without Prior Antiretroviral Therapy
In Study M94-245, 356 antiretroviral-naïve HIV-infected patients (mean baseline CD4 = 364 cells/microliter) were randomized to receive either NORVIR 600 mg twice daily, zidovudine 200 mg three times daily, or a combination of these drugs. In analyses of average CD4 cell count changes from baseline over the first 16 weeks of study, both NORVIR monotherapy and combination therapy produced greater mean increases in CD4 cell count than did zidovudine monotherapy. The CD4 cell count increases for NORVIR monotherapy were larger than the increases for combination therapy. Similarly, the mean decreases in HIV RNA level from baseline were larger with NORVIR monotherapy than with combination therapy or zidovudine monotherapy.
Combination Therapy with NORVIR, Zidovudine, and Zalcitabine in Antiretroviral- Naïve Patients
In Study M94-208, an open-label uncontrolled trial, 32 antiretroviral- naïve HIV-infected patients initially received NORVIR 600 mg twice daily monotherapy. Zidovudine 200 mg three times daily and zalcitabine 0.75 mg three times daily were added after 14 days of NORVIR monotherapy. Results of combination therapy for the first 20 weeks of this study show median increases in CD4 cell counts from baseline levels of 83 to 106 cells/microliter over the treatment period. Mean decreases from baseline in HIV RNA particle levels ranged from 1.69 to 1.92 logs.
MICROBIOLOGY
Resistance
HIV-1 isolates with reduced susceptibility to ritonavir have been selected in vitro. The clinical relevance of phenotypic and genotypic changes associated with NORVIR therapy has not been established (see WARNINGS AND PRECAUTIONS and MICROBIOLOGY). Genotypic analysis of these isolates showed mutations in the HIV protease gene at amino acid positions 84 (Ile to Val), 82 (Val to Phe), 71 (Ala to Val), and 46 (Met to Ile). Phenotypic (n = 18) and genotypic (n = 44) changes in HIV isolates from selected patients treated with ritonavir were monitored in Phase 1/2 trials over a period of 3 to 32 weeks. Mutations associated with the HIV viral protease in isolates obtained from 41 patients appeared to occur in a stepwise and ordered fashion; in sequence, these mutations were position 82 (Val to Ala/Phe), 54 (Ile to Val), 71 (Ala to Val/Thr), and 36 (Ile to Leu), followed by combinations of mutations at an additional 5 specific amino acid positions.
Of 18 patients for which both phenotypic and genotypic analysis were performed on free virus isolated from plasma, 12 showed reduced susceptibility to ritonavir in vitro. All 18 patients possessed one or more mutations in the viral protease gene. The 82 mutation appeared to be necessary but not sufficient to confer phenotypic resistance. Phenotypic resistance was defined as a ≥ 5-fold decrease in viral sensitivity in vitro from baseline. The clinical relevance of phenotypic and genotypic changes associated with NORVIR therapy has not been established.
Cross-resistance to Other Antiretrovirals
Among protease inhibitors variable cross-resistance has been recognized. (see WARNINGS AND PRECAUTIONS and MICROBIOLOGY). Serial HIV isolates obtained from six patients during NORVIR therapy showed a decrease in ritonavir susceptibility in vitro but did not demonstrate a concordant decrease in susceptibility to saquinavir in vitro when compared to matched baseline isolates. However, isolates from two of these patients demonstrated decreased susceptibility to indinavir in vitro (8-fold). Isolates from five patients were also tested for cross-resistance to amprenavir and nelfinavir; isolates from two patients had a decrease in susceptibility to nelfinavir (12- to 14-fold), and none to amprenavir. Cross-resistance between ritonavir and reverse transcriptase inhibitors is unlikely because of the different enzyme targets involved. One ZDV-resistant HIV isolate tested in vitro retained full susceptibility to ritonavir.
Cross-resistance between ritonavir and reverse transcriptase inhibitors is unlikely because of the different enzyme targets involved. One ZDV-resistant HIV isolate tested in vitro retained full susceptibility to ritonavir.
Antiviral Activity in vitro
The activity of ritonavir was assessed in vitro in acutely infected lymphoblastoid cell lines and in peripheral blood lymphocytes. The concentration of drug that inhibits 50% (EC50) of viral replication ranged from 3.8 to 153 nM depending upon the HIV-1 isolate and the cells employed. The average EC50 for low passage clinical isolates was 22 nM (n = 13). In MT4 cells, ritonavir demonstrated additive effects against HIV-1 in combination with either zidovudine (ZDV) or didanosine (ddI). Studies which measured cytotoxicity of ritonavir on several cell lines showed that > 20 microM was required to inhibit cellular growth by 50% resulting in an in vitro therapeutic index of at least 1000.
NON-CLINICAL TOXICOLOGY
The toxicology of ritonavir has been assessed in mice, rats, dogs and rabbits in studies ranging in duration from a single dose to six months of oral administration. All phases of the reproductive process have been evaluated for potential adverse effects, and a generally accepted battery of in vitro and in vivo mutagenicity studies has been conducted. The following section summarizes the findings from these studies. The most significant target organs in the toxicity studies have been the liver and retina. Retinal changes secondary to phospholipidosis were limited to rodents only and were considered not to pose any undue risk to humans. Dogs appeared to be less sensitive than the rodent to the hepatotoxic effects of ritonavir. Human clinical studies have not disclosed a high incidence of hepatic complications (see ADVERSE REACTIONS).
Pharmacodynamics
Ritonavir was administered orally to mice or rats at doses of 5 to 50 mg/kg to determine potential effects on various neuropharmacological endpoints. In mice, ritonavir had no meaningful effect on rotarod performance, ethanol-induced sleep time or pentobarbital-induced sleep time. In rats, no effect was observed on spontaneous motor activity or rotarod performance.
Ritonavir produced no pharmacologically significant effects on heart rate or blood pressure when administered orally to unanesthetized rats at doses of 20 or 50 mg/kg. The compound was also infused intravenously in a vehicle consisting of 20% ethanol and 15% propylene glycol in 5% dextrose water to pentobarbital-anesthetized dogs instrumented to measure various cardiovascular parameters.
Mean peak plasma levels of ritonavir were as high as 15.11 mcg/mL. Although the vehicle itself produced hemodynamic changes consistent with cardiac depression, ritonavir produced no consistent additional effects on systemic or pulmonary pressures or resistance, central venous pressure, cardiac output, left ventricular dP/dt or end-diastolic pressure.
Ritonavir had no effect on isolated guinea pig ileum basal tone or on carbachol-induced contractions.
Acute Toxicity
Ritonavir has a low order of acute toxicity in rodents by oral route but is more toxic when given intravenously. The difference is probably due to the fact that the acute toxicity produced by ritonavir is more related to plasma Cmax than AUC values, and Cmax is most likely considerably higher following intravenous injection. When given orally in a vehicle of propylene glycol and ethyl alcohol (95:5, v/v) containing two molar equivalents of p-toluene sulfonic acid monohydrate, the median lethal dose (LD50) generally exceeds the limited dose of 2500 mg/kg for both mice and rats. Toxic signs for both species consisted of decreased activity, ataxia, dyspnea, squinting, prostration, and tremors.
When administered intravenously, the approximately lethal dose (ALD) ranged from 35 to 80 mg/kg for both species. Signs of toxicity included decreased activity, ataxia, dyspnea, exophthalmos, and clonic convulsions.
Sub-chronic Toxicity
Rat
Ritonavir has been studied in rats at study durations for one-month (0, 15, 50 and 150/100 mg/kg/day), 13-weeks (0, 25, 75, and 175/125 mg/kg/day) and six-months (0, 25, 75, and 175/125 mg/kg/day). Consistent findings across all studies included treatment-related clinical signs consisting of decreased activity, emaciation, hunched posture, weakness, and rough hair coat along with some indications of ataxia, lower body weight and food consumption at higher dosages. Target organs of toxicity were liver, eye (retina), kidney and thyroid.
Hepatic changes include multinucleated hepatocytes, single cell necrosis, histiocytic granulomas and chronic paricholangitis. Changes in laboratory parameters consisten with these findings were observed in serum for ALT, AST, GGT, ALP, total bilirubin, and cholesterol.
Retinal changes included observation of pale choroidal vasculature, with hypertrophy and cytoplasmic granularity in the retinal pigment epithelium, with reduced or absent photoreceptor outer segments. Electroretihograms (ERGs) revealed decreases in A- and –wave amplitudes, with primary findings associated with rods. Recovery was not observed following treatment discontinuation.
Mild epithelial hypertrophy in the thyroid gland was associated with increased TSH and lower T4. Kidney changes were consisted of tubular degeneration and were only observed in the six-month study.
The no-toxic effect dosage was considered to be 15 mg/kg/day and corresponded to systemic exposure of 3.6 to 4.7 mcg.h/mL in male rats and 5.3 to 8.9 mcg.h/mL in female rats (approximately 1/25th of the expected human exposure of 150 mcg.h/mL from a dose of 600 mg twice daily).
Dog
Ritonavir has been studied in dogs at study durations for one-month (0, 10, 50 and 200 mg/kg/day), 13-weeks (0, 10, 50, and 200/100 mg/kg/day) and six-months (0, 10, 50 and 125 mg/kg/day). Consistent findings across all studies included treatment-related clinical signs consisting of emesis and abnormal stool/diarrhea; at higher dosages decreased activity, ataxia, weakness, tremor and posture difficulties were observed along with decreased body weight and food intake. Target organs of toxicity were liver and thymus. Due to pronounced clinical adversity and moribundity the high dosage was reduced from 200 to 100 mg/kg/day in the 13-week study.
Hepatic changes included histopathological findings of hydropic degeneration, with pericholangitis, biliary hyperplasia, fibrosis becoming evident as the dose duration increased. Associated changes in serum markers included ALT, ALLP, GGT, and bile acids.
Decreased thymic weight and atrophy were observed at the highest dosages.
The no-toxic effect dosage was dependent on the test formulation used and ranged from 10 to 50 mg/kg/day that corresponded to systemic exposure of 18 to 25 mcg.h/mL (approximately one-seventh of the expected human exposure of 150 mcg.h/mL). However, it is important to note that histopathological changes in liver were only observed in a single female dog at the highest dosage (125 mg/kg/day) at a plasma drug exposure of 482 mcg.h/mL.
Special Studies
Dietary administration of ritonavir was provided to mice and rats for 13-weeks in preparation for two-year carcinogenicity studies in these species. Dosages were 0, 200, 400, 600, and 1000 mg/kg/day for mice and 0 50, 100, 160, and 200 mg/kg/day for male rats and 0, 30, 75, 125, and 175 mg/kg/day for female rats. In both species target organ toxicity was similar to that noted in the 3-month rat study using oral gavage administration, with target organ toxicities in liver, eye (retina), and thyroid (rat only). Systemic plasma exposure (AUC) associated with target organ toxicity was similar to plasma exposures in the 3-month study in rats.
Ritonavir was evaluated for the potential to produce delayed contact hypersensitivity in guinea pigs. The Maximization Method was used in this study and the data generated indicated that ritonavir did not induce delayed contact hypersensitivity in guinea pigs.
Mutagenicity and Carcinogenicity
Carcinogenicity studies with ritonavir have been conducted in mice and rats. In male mice, at dosage levels of 50, 100, or 200 mg/kg/day, there was a dose dependent increase in the incidence of both adenomas and combined adenomas and carcinomas in the liver. Based on the drug exposure (AUC) measurements, the exposure at the high dosage was approximately 0.3-fold for males that of exposure in humans with the recommended therapeutic dose (600 mg twice daily). There were no carcinogenic effects seen in females at the dosages tested. The exposure at the high dosage was approximately 0.6-fold for the females that of the exposure in humans. In rats dosed at levels of 7, 15, or 30 mg/kg/day there were no carcinogenic effects. In this study the exposure at the high dose was approximately 5% that of the exposure in humans with the 600 mg twice daily regimen. Based on the exposures achieved in the animal studies, the significance of the observed effects is not known.
Ritonavir was not found to be mutagenic or clastogenic in a battery of in vitro and in vivo assays including the Ames bacterial reverse mutation assay using S. Typhimurium and E. coli, the mouse lymphoma assay, the mouse micronucleus test and chromosomal aberration assays in human lymphocytes.
Reproduction and Teratology
Fertility and General Reproductive Performance
Rats
Ritonavir was administered orally by gavage to female rats at dosages of 0, 20, 40, and 75 mg/kg/day beginning at 14 days prior to mating with males that were treated at dosages of 0, 20, 40, and 125 mg/kg/day beginning at 28 days prior to mating. The treatment in female rats was continued through mating until gestation Day 9. The group mean plasma AUC values for males near the end of the premating period were 8.2, 19.7 and 61.0 mcg·h/mL, respectively, for the 20, 40, and 125 mg/kg/day treatment groups. The corresponding values for females were 14.6, 33.1 and 90.5 mcg·h/mL, respectively, for the 20, 40 and 75 mg/kg/day treatment groups. There were no treatment-related deaths in the study. Maternal toxicity consisted of adverse clinical signs and decreases in mean body weights and food intake in the mid and high dosage groups.
There were no treatment-related effects on the estrous cycle or male and female reproductive indices. Maternal survival and pregnancy status of the ritonavir-treated groups were also comparable to the controls. No treatment-related effects were seen in the number of corpora lutea, implantation sites, viable and nonviable embryos. There were no increases in the incidence of preimplantation and postimplantation losses. The no-toxic-effect level for systemic toxicity in F0 generation rats was 20 mg/kg/day. However, there were no adverse effects on male or female reproduction or early embryonic development up to the highest dosage (125/75 mg/kg/day) tested.
Developmental Toxicity
Rats
Ritonavir was administered orally to mated female rats at dosages of 0, 15, 35, and 75 mg/kg/day from Gestation Day 6 to 17. Three high dosage rats were euthanized in moribund condition during the study. The group mean plasma AUC values on Gestation Day 16 were 17.3, 34.3 and 45.2 mcg·h/mL at dosages of 15, 35 and 75 mg/kg/day, respectively. Decreased activity, emaciation, dehydration, rough coat and/or matted coat, hunched posture, tremors, and noisy respiration were observed in rats at the high dosage level. Marked decreases in body weights and food consumption were evident in the high dosage group. Reduction in food consumption accompanied by a reduction in body weight gain was also noted for the mid dosage group during Gestation Days 6 to 9. No effects were found in the number of corpora lutes or implantation sites. Developmental toxicity in the high dosage group was characterized by increased postimplantation loss, decreased fetal body weights, and an increased incidence of ossification delays and developmental variations (enlarged fontanelles, cryptorchidism and wavy ribs). Developmental toxicity at the 35 mg/kg/day dosage level was characterized by a slight increase in cryptorchidism. No treatment-related malformations were observed in this study.
Developmental toxicity occurred only at maternally toxic dosages. The no-effect level for maternal and developmental toxicity was 15 mg/kg/day corresponding to a systemic exposure of 17.3 mcg·h/mL.
Rabbits
Ritonavir was administered to mated female rabbits by oral gavage at dosages of 0, 25, 50, and 110 mg/kg/day from Gestation Day 6 to 19. The group mean plasma AUC values on Gestation Day 20 were 1.30 and 28.55 mcg·h/mL at dosages of 25 and 50 mg/kg/day, respectively. Plasma AUC values were not calculated for the 110 mg/kg/day group because plasma samples were obtained from the three surviving rabbits at only two time points. Four deaths in rabbits given 110 mg/kg/day were considered to be possibly drug-related. There was an increased incidence of decreased defecation and soft stool in all drug-treated groups. The observation of no stool was noted in mid and high dosage groups; rales and mucoid stool occurred only at the high dosage. Marked decreases in body weights, body weight gain and food consumption were noted in the high dosage group. Developmental toxicity was evident at the high dosage level with four whole litter resorptions and in surviving litters a significant increase in postimplantation losses, decreased litter size and decreased uterine and fetal weights. There were no drug-related fetal malformations in this study.
The no-observable-effect level was 50 mg/kg/day with respect to maternal and developmental toxicity.
Peri-/Postnatal Toxicity
Rats
Mated female rats were administered ritonavir orally at dosages of 0, 15, 35, or 60 mg/kg/day beginning on Gestation Day (GD) 6. Treatment continued throughout gestation, parturition and lactation; the final dosage was given on Postpartum Day (PD) 20. Plasma drug levels were not determined in this study. No deaths or treatment-related clinical signs were observed among the F0 dams. Dams in the 60 mg/kg/day group gained less weight and consumed less food during GD 6 to 9. Gestation length, litter size at birth, and F1 pup growth and survival were unaffected. No effects on the time of appearance of developmental landmarks or learning as measured by a passive avoidance test were evident. The ontogeny of various reflexes were unaffected. The reproductive competence of the F1 generation was unaffected. Therefore, the no-observed-effect level for developmental toxicity was considered to be 60 mg/kg/day, the highest dosage tested.
REFERENCES
- 1. Bugelski PJ, Kirsh R, Hart TK. HIV protease inhibitors: effects on viral maturation and physiologic function in macrophages. J Leukoc Biol 1994; 56:374-380.
- 2. Caliendo AM, Hirsch MS. Combination therapy for infection due to human immunodeficiency virus type 1. Clin Infect Dis 1994; 18:516-524.
- 3. Cameron DW, Heath-Chiozzi M, Danner S, et al. Randomised placebo-controlled trial of ritonavir in advanced HIV-1 disease. Lancet 1998; 351:543-49.
- 4. Coffin JM. HIV population dynamics in vivo: implications for genetic variation, pathogenesis, and therapy. Sci 1995; 267:483-489.
- 5. Church JA. Clinical aspects of HIV infection. Pediatric Ann. 1993; 22(7):417-427.
- 6. Danner SA, Carr A, Leonard JM, et al. A short-term study of the safety, pharmacokinetics, and efficacy of ritonavir, an inhibitor of HIV-1 protease. N Eng J Med 1995; 333:1528-1533.
- 7. Darke PL, Huff JR. HIV protease as an inhibitor target for the treatment of AIDS. Adv Pharmacol 1994; 25:399-455.
- 8. Hammer SM, Kessler HA, Saag MS. Issues in combination antiretroviral therapy: a review. J Acq Immun Def Synd 1994; 7(Suppl. 2):524-537.
- 9. Ho DD, Neumann AU, Perelson AS, Chen W, Leonard J, Markowitz M. Rapid turnover of plasma virions and CD4 lymphocytes in HIV-1 infection. Nature 1995; 373:123-126.
- 10. Hsu A, Granneman GR, Bertz RJ. Ritonavir. Clinical pharmacokinetics and interactions with other anti-HIV agents. Clin Pharmacokinet 1998 Oct; 35(4):275-91. Review. Erratum in: Clin Pharmacokinet 1998 Dec; 35(6):473.
- 11. Hsu A, Granneman R, Rynkiewicz K, et al. Kinetics of ABT-538, a protease inhibitor, in human after single oral rising doses. Pharm Res 1994; 11(Suppl):S400.
- 12. Kempf DJ, Marsh KC, Denissen JF, et al. ABT-538 is a potent inhibitor of human immunodeficiency virus protease and has a high oral bioavailability. Proc Natl Acad Sci 1995; 92:2484-2488.
- 13. Kohl NE, Emini EA, Schleif WA, et al. Active human immunodeficiency virus protease is required for viral infectivity. Proc Natl Acad Sci USA 1988; 85:4686-4690.
- 14. Markowitz M, Saag M, Powderly WG, et al. A preliminary study of ritonavir, an inhibitor of HIV-1 protease to treat HIV-1 infection. N Eng J Med 1995; 333:1534-1539.
- 15. Mathez D, Bagnarelli P, Gorin I, et al. Reductions in viral load and increases in T lymphocyte numbers in treatment-naïve patients with advanced HIV-1 infection treated with ritonavir, zidovudine and zalcitabine triple therapy. Antiviral Therapy 1997:2(3); 175-83.
- 16. Mellors JW, Kingsley LA, Rinaldo CR, et al. Quantitation of HIV-1 RNA in plasma predicts outcome after seroconversion. Ann Intern Med 1995; 122:573-579.
- 17. Mitsuya H, Yarchoan R, Kageyama S, Broder S. Targeted therapy of human immunodeficiency virus-related disease. FASEB J 1991; 5:2369-2381.
- 18. Roberts NA, Craig JC, Duncan IB. HIV protease inhibitors. Biochem Soc Trans 1992; 20:513-516.
- 19. Tudor-Williams G, St. Clair MH, McKinney RE et al. HIV-1 Sensitivity to zidovudine and clinical outcome in children. Lancet. 1992; 339(8784):15-19.
- 20. Wei X, Ghosh SK, Tayler ME, et al. Viral dynamics in human immunodeficiency virus type 1 infection. Nature 1995; 373:117-122.
- 21. Whitcup SM, Butler KM, Caruso R et al. Retinal toxicity in human immunodeficiency virus-infected children treated with 2,3'-dideoxyinosine. Am J Ophthalmol. 1992; 113(1):1-7.