


Product Monograph - Novo-Levetiracetam
ACTIONS AND CLINICAL PHARMACOLOGY
Mechanism of Action
Levetiracetam is a drug of the pyrrolidine class chemically unrelated to existing antiepileptic drugs (AEDs). As with other drugs in this class, the mechanism of action of levetiracetam in man is not known (see PHARMACOLOGY, Preclinical Studies, for experimental in vitro and in vivo data in animals).
Pharmacokinetics
Summary
Single- and multiple-dose pharmacokinetics of levetiracetam have included healthy volunteers, adult and pediatric patients with epilepsy, elderly subjects, and subjects with renal and hepatic impairment. Results of these studies indicate that levetiracetam is rapidly and almost completely absorbed after oral administration. The pharmacokinetic profile is linear with low intra- and inter-subject variability. There is no modification of the clearance after repeated administration. Food does not affect the extent of absorption of levetiracetam, although the rate is decreased. Levetiracetam is not protein-bound (<10% bound) and its volume of distribution is close to the volume of intracellular and extracellular water. Sixty-six percent (66%) of the dose is renally excreted unchanged. The major metabolic pathway of levetiracetam (24% of the dose) is an enzymatic hydrolysis of the acetamide group. It is not liver cytochrome P450 dependent. The metabolites have no known pharmacodynamic activity and are renally excreted. Plasma half-life of levetiracetam across studies is 6-8 hours. Plasma half-life is increased in subjects with renal impairment, and in the elderly primarily due to impaired renal clearance.
Based on its pharmacokinetic characteristics, levetiracetam is unlikely to produce or to be subject to metabolic interactions.
The pharmacokinetic profile is comparable in healthy volunteers and in patients with epilepsy.
Due to its complete and linear absorption, plasma levels can be predicted from the oral dose of levetiracetam expressed as mg/kg body weight. Therefore, there is no need for plasma level monitoring of levetiracetam.
Human Pharmacology
Pharmacokinetics
The pharmacokinetics of levetiracetam have been characterized in single- and multiple- dose PK studies, with doses up to 5000 mg; these studies included healthy volunteers (N=98), patients with epilepsy (N=58 adult patients and N=24 pediatric patients), elderly subjects (N=16) and subjects with renal and hepatic impairment (N=36 and 16, respectively).
Absorption and Distribution
Levetiracetam is rapidly and almost completely absorbed after oral administration. The oral bioavailability of levetiracetam tablets is 100%. Plasma peak concentrations (Cmax) are achieved at 1.3 hours after dosing. The extent of absorption is independent of both dose and the presence of food, but the latter delays Tmax by 1.5 hours and decreases Cmax by 20%. The pharmacokinetics of levetiracetam are linear over the dose range of 500-5000 mg. Steady-state is achieved after two days of a twice daily administration schedule. Mean peak concentrations (Cmax) are 31 and 43 μg/mL, respectively, following a single 1000 mg dose, and a repeated 1000 mg twice daily dose.
Neither levetiracetam nor its primary metabolite is significantly bound to plasma proteins (<10%). The volume of distribution of levetiracetam is approximately 0.5 to 0.7 L/kg, a value that is close to the total body water volume. No tissue distribution data for humans are available.
Metabolism
Levetiracetam is not extensively metabolized in humans. The major metabolic pathway is the enzymatic hydrolysis of the acetamide group, which produces the pharmacologically inactive carboxylic acid metabolite, ucb L057 (24% of dose). The production of this metabolite is not dependent on any liver cytochrome P450 isoenzymes and is mediated by serine esterase(s) in various tissues, including blood cells. Two minor metabolites were identified as the product of hydroxylation of the 2-oxo-pyrrolidine ring (2% of dose) and opening of the 2-oxo-pyrrolidine ring in position 5 (1% of dose). There is no evidence for enantiomeric interconversion of levetiracetam or its major metabolite.
Elimination
Levetiracetam plasma half-life in adults is 7 ± 1 hours and was unaffected by dose, route of administration or repeated administration. Levetiracetam is eliminated from the systemic circulation by renal excretion as unchanged drug, which represents 66% of administered dose. The total body clearance is 0.96 mL/min/kg and renal clearance is 0.6 mL/min/kg. Approximately 93% of the dose was excreted within 48 hours. The mechanism of excretion is glomerular filtration with subsequent partial tubular reabsorption. The primary metabolite, ucb L057, is excreted by glomerular filtration and active tubular secretion with a renal clearance of 4 mL/min/kg. Levetiracetam elimination is correlated to creatinine clearance and clearance is thus reduced in patients with impaired renal function (See PRECAUTIONS and DOSAGE AND ADMINISTRATION).
Special Populations
Elderly
Pharmacokinetics of levetiracetam were evaluated in 16 elderly patients, ranging in age from 61-88 years, with 11 of the 16 patients aged 75 years of age or over with creatinine clearance ranging from 30 to 74 mL/min. Following oral administration of 500 mg bid for 10 days, total body clearance decreased by 38% and the half- life was increased about 40% (10 to 11 hours) when compared to healthy adults. This is most likely due to the decrease in renal function in these subjects.
Pediatrics (6 to 12 years)
Pharmacokinetics of levetiracetam were evaluated in 24 pediatric patients (age 6-12 years) after a single dose. The apparent clearance of levetiracetam adjusted to body weight was approximately 40% higher than in epileptic adults.
Gender
Levetiracetam Cmax and AUC were 20% higher in women (N=11) compared to men (N=12). However, clearances adjusted for body weight were comparable.
Race
Formal pharmacokinetic studies of the effects of race have not been conducted. Because levetiracetam is primarily renally excreted and there are no known important racial differences in creatinine clearance, significant pharmacokinetic differences due to race are not expected.
Renal Impairment
Single dose pharmacokinetics were performed in 20 subjects with renal impairment (N= 7 mild/CLcr of 50-79 mL/min; N= 8 moderate/CLcr of 30-49 mL/min; N= 5 severe/CLcr<30 mL/min), and N= 11 matching healthy volunteers. Clearance of levetiracetam is correlated with creatinine clearance and levetiracetam pharmacokinetics following repeat administration were well predicted from single dose data. The apparent body clearance of the parent drug levetiracetam is reduced in patients with impaired renal function by approximately 40% in the mild group, 50% in the moderate group, and 60% in the severe renal impairment group. For the primary metabolite ucb L057, the decrease in clearance values from baseline was greater than that seen for the parent drug in all subject groups.
In anuric (end stage renal disease) patients, the apparent body clearance was approximately 30% compared to that of normal subjects. Approximately 50% of the pool of levetiracetam in the body is removed during a standard 4-hour hemodialysis procedure.
Dosage should be reduced in patients with impaired renal function receiving levetiracetam, and supplemental doses should be given to patients after dialysis (see PRECAUTIONS and DOSAGE AND ADMINISTRATION).
Hepatic Impairment
A single-dose pharmacokinetic study was performed in 16 subjects with hepatic impairment (N=5 mild/Child-Pugh Grade A; N=6 moderate/Grade B; N=5 severe/Grade C vs 5 healthy controls). For the mild and moderate subgroups neither mean nor individual pharmacokinetic values were clinically different from those of controls. In patients with severe hepatic impairment, mean apparent body clearance was 50% that of normal subjects, with decreased renal clearance accounting for most of the decrease. Therefore a 50% reduction of the daily maintenance dose is recommended when the creatinine clearance is <70 mL/min (see PRECAUTIONS AND DOSAGE AND ADMINISTRATION).
Clinical Trials
A Bioequivalence Study was conducted to compare the rate and extent of absorption of Levetiracetam from Teva Pharmaceuticals USA and Keppra from UCB Pharma Inc. Belgium for UCB Pharma Inc. USA; administered as a 1 x 750 mg tablet under fasting conditions in 22 healthy, adult subjects. The study design was a randomized, open-label, 2-way crossover, conducted under fasting conditions. Results are summarized in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Levetiracetam (1 x 750 mg tablet) From measured data uncorrected for potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test◊ | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (mcg x hr/mL) | 170.938 173.932 (19.2%) | 171.651 174.275 (17.9%) | 100 | 96 – 103 |
AUCI (mcg x hr/mL) | 182.541 185.604 (19.1%) | 182.404 184.636 (16.2%) | 100 | 96 – 104 |
Cmax (mcg/mL) | 20.934 21.625 (26.4%) | 22.699 23.501 (26.6%) | 92 | 85 – 100 |
Tmax § (hrs) | 1.015 (59.7%) | 0.781 (62.1%) | ||
T½§ (hrs) | 7.245 (17.5%) | 6.959 (12.6%) | ||
◊ Test: Levetiracetam 750 mg Tablets (TEVA Pharmaceutical Industries, Ltd.)
† Reference: KEPPRA® 750 mg Tablets (Manufactured by UCB Pharma Inc. Belgium for UCB Pharma Inc. USA.). Purchased in the USA.
§ Expressed as the arithmetic mean (CV%) only
Clinical Efficacy
The efficacy of Levetiracetam as adjunctive therapy (added to other antiepileptic drugs) in adults was established in three multicenter, randomized, double-blind, placebo-controlled clinical studies in a total of 904 adult patients who had a history of partial onset seizures with or without secondary generalization.
General Methodology
Patient Population
Patients in these three studies had refractory partial onset seizures for a minimum of 1 (or 2) year(s) prior to enrollment. They had previously taken a minimum number of classical AEDs (either one or two), and at the time of the study were taking a stable dose regimen of at least one AED. During the baseline period, it was required that patients experienced a minimum of 12 partial onset seizures over 12 weeks (Study N132) or 4 partial onset seizures during each 4-week period (Study N051) or 2 partial onset seizures per 4-week period (Study N138).
Dosing Schedules
After a prospective baseline period of approximately 12 weeks, patients were randomized to placebo, or levetiracetam at 1000 mg, 2000 mg or 3000 mg/day (depending on the study), given as twice daily doses. In all trials, there was a 2 or 4 week titration period, followed by a 12-14 week maintenance period.
Measure of Efficacy
The primary measure of efficacy was a between group comparison of the percent reduction in weekly partial seizure frequency relative to placebo over the entire randomized treatment period (titration + maintenance). Secondary efficacy parameters include the 50% and 100% responder rate in partial onset seizure frequency over the entire randomized treatment period. Efficacy results are based on the ITT population with the exception of a few patients lacking evaluable seizure frequency data.
The above trial description applies to all three studies below. Thus for each trial, only primary distinguishing information is stated below.
Study N132
Study N132 was a parallel-group study conducted in the United States comparing placebo, levetiracetam 1000 mg/day, and Levetiracetam 3000 mg/day in 95, 98, and 101 randomized patients, respectively. The efficacy for Study N132 is displayed in Table 1.
Table 1: Median Percent Reduction from Baseline in Weekly Frequency of Partial Onset Seizures in Study N132
| AEDs + Placebo | AEDs + Levetiracetam 1000 mg/day | AEDs + Levetiracetam 3000 mg/day | |
| N | 95 | 97 | 101 |
| Median Baseline Seizure Frequency | 1.77 | 2.53 | 2.08 |
| Percent reduction in partial seizure frequency from baseline | 6.9% | 36.9%* | 38.1%* |
*P<0.001 versus placebo.
Study N051
Study N051 was a crossover study conducted in Europe comparing placebo, levetiracetam 1000 mg/day, and levetiracetam 2000 mg/day in 112, 106, and 106 randomized patients, respectively.
The first period of the study (Period A) was designed to be analyzed as a parallel-group study. The efficacy results for Period A are displayed in Table 2.
Table 2: Median Percent Reduction from Baseline in Weekly Frequency of Partial Onset Seizures in Study N051 Period A
| AEDs + Placebo | AEDs + Levetiracetam 1000 mg/day | AEDs + Levetiracetam 2000 mg/day | |
| N | 111 | 106 | 105 |
| Median Baseline Seizure Frequency | 2.46 | 2.82 | 2.59 |
| Percent reduction in partial seizure frequency from baseline | 1.1% | 20.7%* | 24.4%* |
*P<0.001 versus placebo.
Study N138
Study N138 was a parallel-group study conducted in Europe comparing placebo and levetiracetam 3000 mg/day in 105 and 181 randomized patients. respectively. Table 3 displays the efficacy results for Study N138.
Table 3: Median Percent Reduction from Baseline in Weekly Frequency of Partial Onset Seizures in Study N138
| AEDs + Placebo | AEDs + Levetiracetam 3000 mg/day | |
| N | 104 | 180 |
| Median Baseline Seizure Frequency | 1.78 | 1.67 |
| Percent reduction in partial seizure frequency from baseline | 7.3% | 36.8%* |
*P<0.001 versus placebo.
Responder Rates
Each patient is categorized according to their efficacy data: percent reduction from baseline in weekly frequency of partial onset seizures, calculated over the entire randomized treatment period. The percentage of patients who remained on levetiracetam for at least 21 days and achieved ≥50% reduction, or a 100% reduction (seizure free) within each of the three pivotal studies is presented in Table 4.
Table 4: Partial Onset Responder Rate over the Entire Treatment Period by Randomized Dose
| Percent Reduction | AEDs + Placebo | AEDs + Levetiraceam 1000 mg/day | AEDs + Levetiraceam 2000 mg/day | AEDs + Levetiraceam 3000 mg/day |
| Study N132 | ||||
| N | 95 | 97 | - | 101 |
| ≥50% | 7% | 36% | - | 40% |
| Seizure free (100%) | 0% | 3% | - | 6% |
| Study N051 | ||||
| N | 111 | 106 | 105 | - |
| ≥50% | 6% | 21% | 34% | - |
| Seizure free (100%) | 1% | 2% | 3% | - |
| Study N138 | ||||
| N | 104 | - | - | 180 |
| ≥50% | 14% | - | - | 39% |
| Seizure free (100%) | 0% | - | - | 7% |
INDICATIONS AND CLINICAL USE
Novo-Levetiracetam is indicated as adjunctive therapy in the management of patients with epilepsy who are not satisfactorily controlled by conventional therapy.
CONTRAINDICATIONS
This product should not be administered to patients who have previously exhibited hypersensitivity to levetiracetam or any of the inactive ingredients in levetiracetam tablets.
WARNINGS
Central Nervous System Adverse Events
Levetiracetam use is associated with the occurrence of central nervous system (CNS) adverse events; the most significant of these can be classified into the following categories 1) somnolence and fatigue, 2) behavioral/psychiatric symptoms and 3) coordination difficulties.
There was no clear dose response relationship for any of the three categories of CNS adverse events, within the recommended dose range of up to 3000 mg/day. Somnolence/asthenia and coordination difficulties occurred most frequently within the first four weeks of treatment and usually resolved while patients remained on treatment. In the case of behavioral/psychiatric symptoms (including such adverse events as aggression, agitation, anger, anxiety, emotional lability, hostility, irritability), approximately half of the patients reported these events within the first four weeks, with the remaining events occurring throughout the duration of the trials.
See also PRECAUTIONS, Central Nervous System Adverse Events.
Withdrawal of Anti-Epileptic Drugs
As with all antiepileptic drugs, Novo-Levetiracetam should be withdrawn gradually to minimize the potential of increased seizure frequency.
PRECAUTIONS
General
Hematological Abnormalities
Minor but statistically significant decreases compared to placebo were seen in total mean RBC count, mean hemoglobin, and mean hematocrit in levetiracetam-treated patients in controlled trials. For hemoglobin values, the percentage of levetiracetam or placebo treated patients with possibly clinically significant abnormalities were less than 0.5% each. For hematocrit values, a total of 5.1% of levetiracetam treated versus 3.2% of placebo patients had at least one possibly significant decrease in hematocrit (≤ 37% in males and 32% in females).
For white blood cells (WBC), 2.9% of treated versus 2.3% of placebo patients had at least one possibly clinically significant decrease in WBC count (≤ 2.8 x 10⁹/L), while 2.6% of treated vs. 1.7% of placebo patients had at least one possibly significant decrease in neutrophil count (≤1.0 x 10⁹/L). Of the levetiracetam treated patients with a low neutrophil count, all but one rose towards or reached baseline with continued treatment. No patient was discontinued secondary to low neutrophil counts.
Central Nervous System Adverse Events (See WARNINGS)
Levetiracetam use is associated with the occurrence of central nervous system (CNS) adverse events; the most significant of these can be classified into the following categories: 1) somnolence and fatigue, 2) behavioral/psychiatric symptoms and 3) coordination difficulties.
The following CNS adverse events were observed in controlled clinical trials.
Table 5: Total Combined Incidence Rate for each of the Three Categories of CNS Adverse Events in Placebo-Controlled Add-On Clinical Trials.
| Category of CNS Adverse Event | Levetiracetam* + AED Therapy (N=672) | Placebo + AED Therapy (N=351) |
Somnolence and fatigue Somnolence Asthenia | 15% 14% | 10% 10% |
Behavioral/ psychiatric symptoms Nonpsychotic1 Psychotic2 | 14% 1% | 6% 0% |
| Coordination difficulties3 | 3% | 2% |
* Reflects Levetiracetam doses of 1000 mg, 2000 mg, 3000 mg, and 4000 mg per day.
1 “Non-psychotic behavioral/psychiatric symptoms” encompasses the following terms: agitation, antisocial reaction, anxiety, apathy, depersonalization, depression, emotional lability, euphoria, hostility, nervousness, neurosis, personality disorder and suicide attempt.
2 “Psychotic behavioral/psychiatric symptoms” encompasses the following terms: hallucinations, paranoid reaction, psychosis and psychotic depression.
3 “Coordination difficulties” encompasses the following terms: ataxia, abnormal gait, incoordination.
See ADVERSE EVENTS, Table 6 for incidence rate of individual AEs contained within the categories.
Behavioral/psychiatric symptoms (including agitation, emotional lability, hostility, anxiety etc.) have been reported approximately equally in patients with and without a psychiatric history.
There was no clear dose response relationship for any of the three categories of CNS adverse events, within the recommended dose range of up to 3000 mg/day. In a controlled study including a dose of 4000 mg, administered without titration, the incidence rate of somnolence during the first four weeks of treatment for patients receiving the high dose was 42%, compared to 21% for patients receiving 2000 mg/day.
No studies on the effects on the ability to drive and use machines have been performed. Due to possible different individual sensitivity, some patients might experience somnolence or other central nervous system related symptoms, at the beginning of treatment or following a dose increase. Therefore, caution is recommended in those patients when performing skilled tasks, e.g. driving vehicles or operating machinery.
Special Populations
Patients with Renal Impairment
Renal excretion of unchanged drug accounts for approximately 66% of administered levetiracetam dose. Consistent with this, pharmacokinetic studies in renally-impaired patients indicate that apparent clearance is significantly reduced in subjects with renal impairment (see ACTIONS AND CLINICAL PHARMACOLOGY, Special Populations).
In patients with renal impairment Novo-Levetiracetam dosage should be appropriately reduced. Patients with end stage renal disease, i.e. those undergoing dialysis should be given supplemental doses after dialysis (See DOSAGE AND ADMINISTRATION).
Pregnancy and Nursing
There are no adequate and well-controlled studies on the use of levetiracetam in pregnant women. Levetiracetam and/or its metabolites cross the placental barrier in animal species. In reproductive toxicity studies in rats and rabbits, levetiracetam induced developmental toxicity at exposure levels similar to or greater than the human exposure. There was evidence of increased skeletal variations/minor anomalies, retarded growth, embryonic death, and increased pup mortality. In the rat, fetal abnormalities occurred in the absence of overt maternal toxicity. The systemic exposure at the observed no effect level in the rabbit was about 4 to 5 times the human exposure. The potential risk for humans is unknown. Novo-Levetiracetam should not be used during pregnancy unless potential benefits to mother and fetus are considered to outweigh potential risks to both. Discontinuation of antiepileptic treatments may result in disease worsening, which can be harmful to the mother and the fetus.
Pregnancy Registry
To facilitate monitoring of fetal outcomes of pregnant women exposed to levetiracetam, physicians should encourage patients to register, before fetal outcome is known (e.g., ultrasound, results of amniocentesis, etc.), in the North American Antiepileptic Drug Pregnancy Registry by calling (888) 233-2334 (toll free).
Nursing Mothers
Levetiracetam is excreted in breast milk. Therefore, there is a potential for serious adverse reactions from Novo-Levetiracetam in nursing infants. A decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother, and the as-yet uncharacterized risks to the infant.
Use in Pediatric Patients
Safety and efficacy in patients below the age of 18 have not been established.
Use in the Elderly
Renal function can be decreased in the elderly and levetiracetam is known to be substantially excreted by the kidney, the risk of adverse reactions to the drug may be greater in patients with impaired renal function. A pharmacokinetic study in 16 elderly subjects (age 61-88 years) showed a decrease in clearance by about 40% with oral administration of both single dose and 10 days of multiple twice-daily dosing. This decrease is most likely due to the expected decrease in renal function in these elderly subjects. Care should therefore be taken in dose selection for elderly patients, and it may be useful to monitor renal function.
There were insufficient numbers of elderly patients in controlled trials of epilepsy to adequately assess the efficacy or safety of levetiracetam in these patients. Nine of 672 patients treated with levetiracetam were 65 or over.
Drug Interactions
In vitro Studies on Metabolic Interaction Potential
In vitro, levetiracetam and its primary metabolite have been shown not to inhibit the major human liver cytochrome P450 isoforms (CYP3A4, 2A6, 2C8/9/10, 2C19, 2D6, 2E1 and 1A2) glucuronyl transferase (paracetamol UGT i.e. UCT1A6, ethinyl estradiol UGT i.e. UGT1A1 and p-nitrophenol UGT i.e. [p16.2]) and epoxide hydrolase activities. In addition, levetiracetam does not affect the in vitro glucuronidation of valproic acid. In human hepatocytes in culture, levetiracetam did not cause enzyme induction.
Levetiracetam circulates largely unbound (<10% bound) to plasma proteins; therefore clinically significant interactions with other drugs through competition for protein binding sites are unlikely.
Thus in vitro data, in combination with the pharmacokinetic characteristics of the drug, indicate that levetiracetam is unlikely to produce, or be subject to, pharmacokinetic interactions.
Clinical Pharmacokinetic Data
Other Antiepileptic Drugs (AEDs.)
Potential drug interactions between levetiracetam and other AEDs (phenytoin. carbamazepine, valproic acid, phenobarbital, lamotrigine, gabapentin and primidone) were assessed by evaluating the serum concentrations of levetiracetam and these AEDs during placebo-controlled clinical studies. These data suggest that levetiracetam may not significantly influence the plasma concentrations of these other AEDs, and that the other AEDs may not significantly influence the plasma concentrations of levetiracetam.
For two of these AEDs-phenytoin and valproate- formal pharmacokinetic interaction studies with levetiracetam were performed. Levetiracetam was co-administered with either phenytoin or valproate at doses of 3000 mg/day and 1000 mg/day respectively. No clinically significant interactions were observed.
Other Drug Interactions
No data on the influence of antacids on the absorption of levetiracetam is available.
No data on the interaction of levetiracetam with alcohol is available.
Oral Contraceptives
A pharmacokinetic clinical interaction study has been performed in healthy subjects between the oral contraceptive containing 0.03 mg ethinyl estradiol and 0.15 mg levonorgesterol, and the lowest therapeutic dose of levetiracetam (500 mg bid). No clinically significant pharmacokinetic interactions were observed.
However, pharmacokinetic interaction studies using Levetiracetam as adjunctive therapy and covering the recommended dosage range have not been conducted. Therefore, physicians should advise their female patients to be alert to any irregular vaginal bleeding or spotting, and to immediately report to them any occurrences.
Digoxin
Levetiracetam (1000 mg bid) did not influence the pharmacokinetics and pharmacodynamics (ECG) of digoxin given as a 0.25 mg dose every day. Coadministration of digoxin did not influence the pharmacokinetics of levetiracetam.
Warfarin
Levetiracetam (1000 mg bid) did not influence the pharmacokinetics of R and S warfarin (2.5 mg, 5 mg, or 7.5 mg daily). Prothrombin time was not affected by levetiracetam. Coadministration of warfarin did not affect the pharmacokinetics of levetiracetam.
Probenecid
Probenecid, a renal tubular secretion blocking agent, administered at a dose of 500 mg four times a day, did not change the pharmacokinetics of levetiracetam 1000 mg bid). Css
max of the metabolite, ucb L057, was approximately doubled in the presence of probenecid and the renal clearance of the metabolite ucb L057 was decreased by 60%; this alteration is likely related to competitive inhibition of tubular secretion of ucb L057. The effect of levetiracetam on probenecid was not studied.
ADVERSE EVENTS
Commonly Observed
In well-controlled clinical studies, the most frequently reported adverse events associated with the use of levetiracetam in combination with other AEDs, not seen at an equivalent frequency among placebo-treated patients, were somnolence, asthenia, dizziness and infection. Of the most frequently reported adverse events, asthenia, somnolence and dizziness appeared to occur predominantly during the first four weeks of treatment with levetiracetam.
Incidence of AEs in Controlled Clinical Trials
Table 6: Incidence (%) Of Treatment-Emergent Adverse Events In Placebo-Controlled, Add-On Studies By Body System. (Adverse Events Occurred In At Least 1% of Levetiracetam-Treated Patients And Occurred More Frequently Than Placebo-Treated Patients.) (Studies N051, N052, N132 and N138)
| Body System/ Adverse Event | Levetiracetam + AED Therapy (N = 672) | Placebo + AED Therapy (N=351) |
Body as a Whole Asthenia Infection* | 14% 13% | 10% 7% |
Digestive System Tooth Disorders | 2% | 1% |
Hemic and Lymphatic System Ecchymosis | 2% | 1% |
Nervous System Anmesia Anxiety Ataxia Depression Dizziness | 2% 2% 3% 4% 9% | 0% 1% 1% 2% 4% |
| Body System/ Adverse Event | Levetiracetam + AED Therapy (N = 672) | Placebo + AED Therapy (N=351) |
Emotional Lability Hostility Nervousness Personality Disorders Somnolence Thinking Abnormal Vertigo | 2% 2% 4% 1% 15% 2% 3% | 0% 1% 2% 0% 10% 1% 1% |
Respiratory System Pharyngitis Rhinitis Sinusitis | 6% 4% 2% | 4% 3% 1% |
*In levetiracetam-treated patients, the majority of “Infection” events (93%) were coded to reported terms of “common cold” or “infection upper respiratory”.
Other events reported by 1% or more of patients treated with Levetiracetam but as or more frequent in the placebo group were: abdominal pain, accidental injury, amblyopia, anorexia, back pain, bronchitis, chest pain, confusion, constipation, convulsion, cough increased, diarrhea, diplopia, drug level increased, dysmenorrhea, dyspepsia, fever, flu syndrome, fungal infection, gastroenteritis, gingivitis, grand mal convulsion, headache, insomnia, nausea, otitis media, pain, paresthesia, rash, tremor, urinary tract infection, vomiting and weight gain.
Additional Events Observed in Placebo Controlled Trials
Lack of Dose Related Incidence of Adverse Events within Therapeutic Range.
Based on the data from the controlled clinical trials, there was no evidence of dose relationship within the recommended dose range of 1000 to 3000 mg/day.
Discontinuation or Dose Reduction in Well-Controlled Clinical Studies.
In well-controlled clinical studies, 14.3% of patients receiving levetiracetam and 11.7% receiving placebo either discontinued or had a dose reduction as a result of an adverse event. Table 7 lists the most common (>1%) adverse events that resulted in discontinuation or dose reduction.”
Table 7: Adverse Events that Most Commonly resulted in Discontinuation or Dose Reduction in Placebo-Controlled Studies in Patients with Epilepsy
Levetiracetam ® (N=672) | Placebo (N=351) | |
Asthenia Headache Convulsion Dizziness Somnolence Rash | 9 (1.3%) 8 (1.2%) 16 (2.4%) 11(1.6%) 31(4.6%) 0 | 3 (0.9%) 2 (0.6%) 10 (2.8%) 0 6 (1.7%) 5 (1.4%) |
The overall adverse experience profile of levetiracetam was similar between females and males. There are insufficient data to support a statement regarding the distribution of adverse experience reports by age and race.
The following adverse events were seen in well-controlled studies of Levetiracetam for indications in epilepsy other than those approved in this labeling: balance disorder, disturbance in attention, eczema, hyperkinesias, memory impairment, myalgia, nasopharyngitis, pruritus, mood swings, and vision blurred.
Post-Marketing Experience
In post-marketing experience, nervous system and psychiatric disorders have most frequently been reported. In addition to adverse reactions during clinical studies, and listed above, the following adverse reactions have been reported in post-marketing experience. Data are insufficient to support an estimate of their incidence in the population to be treated.
Blood and lymphatic disorders: leukopenia, neutropenia, pancytopenia (with bone marrow suppression identified in some of these cases), thrombocytopenia.
Metabolism and nutrition disorders: weight loss
Hepatic/Biliary/Pancreatic: abnormal liver function test, hepatitis, hepatic failure, pancreatitis (see Hepatic Failure section)
Psychiatric: suicidal behavior (including completed suicide)
Skin: alopecia
Hepatic Failure: Reports of increases in liver function tests in patients taking Levetiracetam, with and without other medications, have been received. Reports of hepatitis and hepatic failure in patients taking Levetiracetam, with and without other medications, have been received.
SYMPTOMS AND TREATMENT OF OVERDOSE
Symptoms
The highest reported levetiracetam overdose is approximately 10 times the therapeutic dose. In the majority of overdose cases, multiple drugs were involved. Somnolence, agitation, aggression, depressed level of consciousness, respiratory depression, and coma were observed with levetiracetam overdoses. The minimal lethal oral dose in rodents is at least 233 times the maximum clinically studied dose.
Treatment
There is no antidote for overdose with levetiracetam, treatment is symptomatic and may include hemodialysis. If indicated, elimination of unabsorbed drug should be attempted by emesis or gastric lavage; usual precautions should be observed to maintain airway. General supportive care of the patient is indicated including monitoring of vital signs and observation of the clinical status of the patient.
Standard hemodialysis procedures result in significant removal of levetiracetam (approximately 50% in 4 hours) and should be considered in cases of overdose. Although hemodialysis has not been performed in the few known cases of overdose, it may be indicated by the patient’s clinical state or in patients with significant renal impairment.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
DOSAGE AND ADMINISTRATION
General
Renal excretion of unchanged drug accounts for approximately 66% of administered levetiracetam dose. Consistent with this, reduced doses are recommended for patients with renal impairment.
Novo-Levetiracetam is given orally with or without food.
Adults
Treatment should be initiated at a dose of 1000 mg/day, given as twice daily dosing (500 mg bid). Depending on clinical response and tolerability, the daily dose may be increased every two weeks by increments of 1000 mg, to a maximum recommended daily dose of 3000 mg.
In clinical trials, daily doses of 1000 mg, 2000 mg, and 3000 mg, given as twice a day dosing, were shown to be effective. Although there was a tendency toward greater response rate with higher dose, a consistent statistically significant increase in response with increased dose has not been shown. There are limited safety data from controlled clinical trials at doses higher than 3000 mg/day (approximately 40 patients), therefore these doses are not recommended.
Patients with Impaired Renal Function
Novo-Levetiracetam dosage should be reduced in patients with impaired renal function (see Table 8 below). Patients with end stage renal disease should receive supplemental doses following dialysis. To use this dosing table, an estimate of the patient’s CLcr in mL/min is needed. CLcr in mL/min may be estimated from serum creatinine (mg/dL) determination using the following formula: 140-age (years)] x weight (kg)
CLcr = -------------------------------------------------- (x 0.85 for female patients)
72 x serum creatinine (mg/dL)
Table 8: Dosing adjustment for patients with impaired renal function
| Group | Creatinine Clearance (mL/min) | Dosage and frequency |
Normal Mild Moderate Severe* End-stage renal disease patients undergoing dialysis (1) | ≥80 50-79 30-49 <30 - | 500 to 1500 mg twice daily 500 to 1000 mg twice daily 250 to 750 mg twice daily 250 to 500 mg twice daily 500 to 1000 mg once daily |
(1) Following dialysis, a 250 to 500 mg supplemental dose is recommended.
* or according to best clinical judgement
Patients with Impaired Hepatic Function
No dose adjustment is needed in patients with mild to moderate hepatic impairment. In patients with severe hepatic impairment, the creatinine clearance may underestimate the renal insufficiency. Therefore a 50% reduction of the daily maintenance dose is recommended when the creatinine clearance is < 70 mL/min.
Elderly Patients
Dose selection and titration should proceed cautiously in elderly patients, as renal function decreases with age.
PHARMACEUTICAL INFORMATION
Drug Substance
U.S.A.N: levetiracetam
Chemical Name: (-)-(S)-α-ethyl-2-oxo-1-pyrrolidine acetamide
Structural Formula:
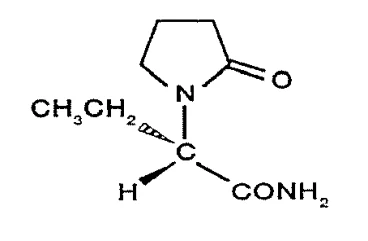
Molecular Formula: C8H14N2O2
Molecular Weight: 170.21
Physical Form: a white to off-white crystalline powder with a faint odor and a bitter taste.
Solubility: It is very soluble in water (104.0 g/100 mL). It is freely soluble in chloroform (65.3 g/100 mL) and in methanol (53.6 g/100 mL), soluble in ethanol (16.5 g/100 mL), sparingly soluble in acetonitrile (5.7 g/100 mL) and practically insoluble in n-hexane.
pKa and pH values: The pKa of levetiracetam is <-2 and cannot be determined with accuracy due to the chemical instability of the protonated form.
The protonation of levetiracetam starts at H0 values between -1 and -2.
Partition co-efficient: Δ log P (log P octanol - log P cyctohexane) was calculated at pH 7.4 using phosphate buffered saline and at pH 1.0 using KCl/HCl. The Δ log P at pH 7.4 is 3.65 and at pH 1.0 is 3.10.
Melting Range: 115-119°C
Composition: Novo-Levetiracetam tablets contain the labeled amount of levetiracetam. Inactive ingredients include croscarmellose sodium, magnesium stearate, povidone, purified water, starch and coloring agents.
The individual tablets contain the following coloring agents:
750 mg tablets: Iron Oxide Yellow
FD&C Yellow #6/Sunset Yellow FCF Aluminum Lake Iron Oxide Red.
Stability and Storage Recommendations
Store between 15-30°C (59-86°F)
AVAILABILITY OF DOSAGE FORMS
Novo-Levetiracetam tablets, 750 mg are orange, oblong-shaped, biconvex film-coated tablets, engraved with 93 on one side, and 7287 on the other side. They are supplied in bottles of 120 tablets and 500 tablets.