


Product Monograph - Nucynta Extended-Release
Recent Major Label Changes
| 2025-11 |
|---|---|
| 2025-11 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications .......................................................................................................................... 4
1.1. Pediatrics ................................................................................................................... 4
1.2. Geriatrics ................................................................................................................... 4
- 2. Contraindications ........................................................................................................ 4
- 3. Serious Warnings and Precautions Box ....................................................................... 5
- 4.
Dosage and Administration ......................................................................................... 6
4.1. Dosing Considerations ............................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment ......................................................... 7
4.2.1 Discontinuing Treatment ......................................................................................... 9
4.4. Administration ...................................................................................................... 9
4.5. Missed Dose ......................................................................................................... 9
- 5. Overdose..................................................................................................................... 9
- 6. Dosage Forms, Strengths, Composition, and Packaging ............................................. 10
- 7.
Warnings and Precautions ......................................................................................... 11
General .......................................................................................................................................... 12
Carcinogenesis and Mutagenesis .................................................................................................. 12
Cardiovascular ............................................................................................................................... 12
Dependence, Tolerance and/or Abuse Liability ............................................................................ 12
Driving and Operating Machinery ................................................................................................. 14
Endocrine and Metabolism ........................................................................................................... 14
Gastrointestinal ............................................................................................................................. 15
Hepatic/Biliary/Pancreatic ............................................................................................................ 15
Immune ......................................................................................................................................... 15
Neurologic ..................................................................................................................................... 15
Perioperative Considerations ....................................................................................................... 17
Renal ............................................................................................................................................. 17
Reproductive Health ...................................................................................................... 18
Respiratory .................................................................................................................................... 18
7.1. Special Populations ................................................................................................................ 19
7.1.1. Pregnancy .................................................................................................................... 19
7.1.2 Breastfeeding ................................................................................................................... 19
7.1.4. Geriatrics ..................................................................................................................... 19
- 8.
Adverse Reactions ..................................................................................................... 20
8.1. Adverse Reaction Overview ..................................................................................... 20
8.2. Clinical Trial Adverse Reactions ............................................................................... 21
8.3. Less Common Clinical Trial Adverse Reactions ........................................................ 22
8.5. Post-Market Adverse Reactions .............................................................................. 23
- 9.
Drug Interactions ...................................................................................................... 24
9.1. Serious Drug Interactions ........................................................................................ 24
9.2. Drug Interactions Overview ..................................................................................... 24
9.3. Drug-Behavioural Interactions ................................................................................. 25
9.4. Drug-Drug Interactions ...................................................................................... 25
9.5. Drug-Food Interactions............................................................................................ 26
9.6. Drug-Herb Interactions ............................................................................................ 26
9.7. Drug-Laboratory Test Interactions .......................................................................... 26
- 10.
Clinical Pharmacology ............................................................................................... 27
10.1. Mechanism of Action ............................................................................................. 27
10.2. Pharmacodynamics ............................................................................................... 27
10.3. Pharmacokinetics .................................................................................................. 28
- 11. Storage, Stability, and Disposal ................................................................................. 30
Part 2: Scientific Information ................................................................................................ 31
- 13. Pharmaceutical Information ........................................................................................... 31
- 14.
Clinical Trials ................................................................................................................... 31
14.1. Clinical Trials by Indication .................................................................................... 31
- 15. Microbiology .................................................................................................................. 35
- 16. Non-Clinical Toxicology ................................................................................................... 35
Patient Medication Information ........................................................................................... 38
Part 1: Healthcare Professional Information
1. Indications
NUCYNTA EXTENDED-RELEASE (tapentadol extended-release tablets) is indicated for the management of pain severe enough to require daily, continuous, long-term opioid treatment, and:
- that is opioid-responsive; and
- for which alternative treatment options are inadequate.
NUCYNTA EXTENDED-RELEASE is not indicated as an as-needed (prn) analgesic.
1.1. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy (see 10.3. Pharmacokinetics, Special populations and conditions, Geriatrics).
2. Contraindications
NUCYNTA EXTENDED-RELEASE is contraindicated in:
- patients who are hypersensitive (e.g., anaphylaxis, angioedema, anaphylactic shock) to tapentadol, to opioids, or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container (see 7. Warnings and Precautions, Immune, Hypersensitivity, and 8.5. Post-Market Adverse Reactions). For a complete listing of ingredients, see the 6.Dosage Forms, Strengths, Composition and Packaging section of the Product Monograph.
- patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction or strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- patients with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis).
- the management of acute pain.
- patients taking monoamine oxidase inhibitors (MAOIs) (or within 14 days of such therapy) (see 9.1. Serious Drug Interactions).
- patients with severe renal or hepatic impairment (creatinine clearance of less than 30 mL/min and/or Child-Pugh Class C).
- patients with mild, intermittent or short-duration pain that can be managed with other pain medications.
- the management of peri-operative pain.
- patients with acute or severe bronchial asthma, chronic obstructive airway disease, or status asthmaticus.
- patients with acute respiratory depression, elevated carbon dioxide levels in the blood, and cor pulmonale.
- patients with acute alcoholism, delirium tremens, and convulsive disorders.
- patients with severe CNS (central nervous system) depression, increased cerebrospinal or intracranial pressure, and head injury.
- women who are breastfeeding, pregnant, or during labour and delivery (see 3. Serious Warnings and Precautions Box and 7.1.1. Pregnancy).
3. Serious Warnings and Precautions Box
Limitations of Use
Because of the risks of addiction, abuse and misuse with opioids, even at recommended doses, and because of the greater risks of overdose and death with extended-release opioid formulations, NUCYNTA EXTENDED-RELEASE should only be used in patients for whom alternative treatment options (e.g., non-opioid analgesics) are ineffective, not tolerated, or would be otherwise inadequate to provide appropriate management of pain (e.g., immediate-release opioids) (see 4.1. Dosing Considerations).
Addiction, Abuse and Misuse
NUCYNTA EXTENDED-RELEASE poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing NUCYNTA EXTENDED-RELEASE, and all patients should be monitored regularly for the development of these behaviours or conditions (see 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Abuse and Misuse). NUCYNTA EXTENDED-RELEASE should be stored securely to avoid theft or misuse.
Life-threatening Respiratory Depression: OVERDOSE
Serious, life-threatening, or fatal respiratory depression may occur with use of NUCYNTA EXTENDED-RELEASE. Infants exposed in-utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of NUCYNTA EXTENDED-RELEASE or following a dose increase.
NUCYNTA EXTENDED-RELEASE must be swallowed whole. Cutting, breaking, crushing, chewing, or dissolving NUCYNTA EXTENDED-RELEASE can cause rapid release and absorption of a potentially fatal dose of tapentadol (see 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Abuse and Misuse). Further, instruct patients of the hazards related to taking opioids including fatal overdose.
Accidental Exposure
Accidental ingestion of even one dose of NUCYNTA EXTENDED-RELEASE, especially by children, can result in a fatal overdose of tapentadol (see 11. Storage, Stability and Disposal for instructions on proper disposal).
Neonatal Opioid Withdrawal Syndrome
Prolonged maternal use of NUCYNTA EXTENDED-RELEASE during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Neonatal Opioid Withdrawal Syndrome (NOWS)).
Interaction with Alcohol
The co-ingestion of alcohol with NUCYNTA EXTENDED-RELEASE should be avoided as it may result in dangerous additive effects, causing serious injury or death (see 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Abuse and Misuse and 9.4. Drug-Drug Interactions).
Risks From Concomitant Use With Benzodiazepines or Other CNS Depressants
Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see 7. Warnings and Precautions, Neurologic, Interactions with Benzodiazepines and Other Central Nervous System (CNS) Depressants) and 9.4. Drug-Drug Interactions).
- Reserve concomitant prescribing of NUCYNTA EXTENDED-RELEASE and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
4. Dosage and Administration
4.1. Dosing Considerations
- All doses of opioids carry an inherent risk of fatal or non-fatal adverse events. This risk is increased with higher doses. For the management of chronic non-cancer, non-palliative pain, it is recommended that 300 mg (90 morphine milligram equivalent) daily of NUCYNTA EXTENDED-RELEASE not be exceeded. Each patient should be assessed for their risk prior to prescribing NUCYNTA EXTENDED-RELEASE, as the likelihood of experiencing serious adverse events can depend upon the type of opioid, duration of treatment, level of pain as well as the patient’s own level of tolerance. In addition, the level of pain should be assessed routinely to confirm the most appropriate dose and the need for further use of NUCYNTA EXTENDED-RELEASE (see 4.2. Recommended Dose and Dosage Adjustment, Adjustment or Reduction of Dosage).
- NUCYNTA EXTENDED-RELEASE should not be used longer than necessary.
- NUCYNTA EXTENDED-RELEASE should only be used in patients for whom alternative treatment options are ineffective or not tolerated (e.g., non-opioid analgesics), or would be otherwise inadequate to provide appropriate management of pain (e.g., immediate-release opioids).
- NUCYNTA EXTENDED-RELEASE tablets must be swallowed whole with sufficient liquid. When exposed to a small volume of water, particles or whole tablets become viscous (gel-like). Cutting, breaking, crushing, chewing or dissolving NUCYNTA EXTENDED-RELEASE tablets can cause rapid release and absorption of a potentially fatal dose of tapentadol (see 3. Serious Warnings and Precautions Box).
- As with many centrally acting analgesic medications, the dosing regimen should be individualized according to the severity of pain being treated, the patient’s medical and analgesic history, and the ability to follow-up and provide oversight of treatment. Owing to the varied response to opioids observed between individuals, it is recommended that all patients be started at the lowest possible dose of opioid therapy and titrated to an adequate level of analgesia, balanced against acceptable adverse events.
- Treatment goals and discontinuation: Before initiating treatment with NUCYNTA EXTENDED-RELEASE, a treatment strategy including treatment duration and treatment goals, and a plan for end of the treatment, should be agreed together with the patient, in accordance with pain management guidelines. During treatment, there should be frequent contact between the physician and the patient to evaluate the need for continued treatment, consider discontinuation and to adjust dosages if needed. In absence of adequate pain control, the possibility of hyperalgesia, tolerance and progression of underlying disease should be considered.
4.2. Recommended Dose and Dosage Adjustment
Adults
Patients Currently Not Taking Opioid Analgesics (Opioid Naïve): The 50 mg NUCYNTA EXTENDED-RELEASE tablets are intended for short-term use in the initial titration phase only.
Patients currently not taking opioid analgesics should begin NUCYNTA EXTENDED-RELEASE therapy with 50 mg twice a day (approximately every 12 hours) and then be individually titrated to an optimal dose within the therapeutic range of 100 mg to 250 mg twice daily.
Patients Currently Taking Opioid Analgesics (Opioid Experienced): Due to the dual mechanism of action of tapentadol (see 10.1 Mechanism of Action ), caution should be exercised when switching from pure mu-opioids to tapentadol.
Generally, the nature of the previous analgesic, its administration and the mean total daily dose should be taken into account in choosing the initial dose. NUCYNTA EXTENDED-RELEASE clinical studies demonstrated comparable pain relief between tapentadol extended-release tablet and oxycodone controlled-release tablet at a dose ratio of 5:1. Published relative potency information may be used to calculate the relative equianalgesic dose of other opioids to oxycodone. Clinical guidelines suggest that a switch to a new drug should be accompanied by a 50% reduction in the calculated dose. Further adjustment to reach the optimal dose is recommended (see Individualization of Dose and Maintenance of Therapy). Patients should receive appropriate follow-up and oversight to ensure adequate analgesia and to minimize side effects.
The recommended NUCYNTA EXTENDED-RELEASE dose is 100 mg to 250 mg twice daily, taken approximately every 12 hours.
Opioid switching / rotation: Conversion ratios for opioids are subject to variations in kinetics governed by genetics and other factors. Therefore, when switching from one opioid to another, reduce the calculated dose by 25-50% to minimize the risk of overdose. Subsequently, up-titrate the dose, as required, to reach the appropriate maintenance dose.
Table 1 – Opioid Conversion Tablea
| Opioids | To convert to oral morphine equivalent | To convert from oral morphine multiply by | Daily 90 mg MEDb |
|---|---|---|---|
| Morphine | 1 | 1 | 90 mg/d |
| Codeine | 0.15 | 6.67 | 600 mg/d |
| Hydromorphone | 5 | 0.2 | 18 mg/d |
| Oxycodone | 1.5 | 0.667 | 60 mg/d |
| Tapentadol | 0.3-0.4 | 2.5-3.33 | 300 mg/d |
| Tramadol | 0.1-0.2 | 6 | *** |
| Methadone | Morphine dose equivalence is not reliably established | ||
*** The maximum recommended daily dose of tramadol is 300 mg - 400 mg depending on the formulation.
- a) Adapted from the 2017 Canadian guideline for opioids for chronic non-cancer pain. McMaster University; 2017
- b) MED: Morphine Equivalent Dose
Individualization of Dose and Maintenance of Therapy: Pain relief and other opioid effects should be frequently assessed. In clinical practice, titration of the total daily dose of NUCYNTA EXTENDED-
RELEASE should be based upon the amount of supplemental opioid utilization, severity of the patient’s pain, and the patient’s ability to tolerate NUCYNTA EXTENDED-RELEASE. Patients should be titrated to a dose providing a meaningful improvement of pain with acceptable tolerability. Experience from clinical studies has shown that a titration regimen in increments of 50 mg NUCYNTA EXTENDED-RELEASE twice daily every 3 days was appropriate to achieve adequate pain control in most patients. Total daily doses greater than 500 mg of NUCYNTA EXTENDED-RELEASE have not been studied and, therefore, are not recommended (see 14. Clinical Trials).
If signs of excessive opioid-related adverse experiences are observed, the dose can be reduced depending on patient status and medical judgment. Adverse events can be treated symptomatically as well. Once adverse events are under control, upward titration can continue to an acceptable level of pain control.
During periods of changing analgesic requirement, including initial titration, frequent contact is recommended between physician and/or health care provider and the patient.
Management of Patients Requiring Rescue Medication: If rescue medications are warranted for episodes of pain in the course of appropriate adjustments of NUCYNTA EXTENDED-RELEASE dose, medications such as acetaminophen, ibuprofen or tramadol may be given. Fentanyl products should not be used as rescue medication in patients taking NUCYNTA EXTENDED-RELEASE. If immediate release tramadol is used as rescue medication, the total daily dose of tramadol should not exceed 400 mg. Selection of rescue medication should be based on individual patient conditions. For patients whose dose has been titrated to the recommended maintenance dose, without attainment of adequate analgesia, the total daily dose may be increased, unless precluded by side effects.
Conversion between NUCYNTA IR and NUCYNTA EXTENDED-RELEASE: Clinical data indicate that patients who have been titrated to a stable daily dose with NUCYNTA IR and have achieved optimal analgesia with acceptable tolerability, can be directly converted to an approximately equivalent total daily dose of NUCYNTA EXTENDED-RELEASE, and vice-versa, if necessary, with equivalent efficacy. As an example, a patient receiving 50 mg of NUCYNTA IR four times per day (total of 200 mg/day) may be converted to 100 mg NUCYNTA EXTENDED-RELEASE twice a day.
Adjustment or Reduction of Dosage: Dependence and tolerance tend to occur with chronic administration of opioids, including NUCYNTA EXTENDED-RELEASE. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. In patients who are appropriately treated with opioid analgesics and who undergo gradual withdrawal for the drug, withdrawal symptoms are usually mild (see 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Withdrawal Symptoms). Tapering should be individualized and carried out under medical supervision.
Following successful relief of severe pain, periodic attempts to reduce the opioid dose should be made. Smaller doses or complete discontinuation may become feasible due to a change in the patient's condition or mental state.
Patients should be informed that reducing and/or discontinuing opioids decreases their tolerance to these drugs. If treatment needs to be re-initiated, the patient must start at the lowest dose and titrate up to avoid overdose.
Patients with Renal Impairment: No dosage adjustment is recommended in patients with mild or moderate renal impairment (see 10.3. Pharmacokinetics, Special populations and conditions, Renal Insufficiency).
NUCYNTA EXTENDED-RELEASE has not been studied in controlled efficacy studies in patients with severe renal impairment. The use in this population is contraindicated.
Patients with Hepatic Impairment: No dosage adjustment is recommended in patients with mild hepatic impairment (see 10.3. Pharmacokinetics, Special populations and conditions, Hepatic Insufficiency).
NUCYNTA EXTENDED-RELEASE should be used with caution in patients with moderate hepatic impairment. Treatment in these patients should be initiated at 50 mg NUCYNTA EXTENDED-RELEASE and not be administered more frequently than once every 24 hours. Further treatment, which may include dose titration, should reflect maintenance of analgesia with acceptable tolerability (see 10.3. Pharmacokinetics, Special populations and conditions, Hepatic Insufficiency).
NUCYNTA EXTENDED-RELEASE has not been studied in patients with severe hepatic impairment and use in this population is contraindicated.
Pediatrics (< 18 years of age)
Health Canada has not authorized an indication for pediatric use.
Geriatrics (≥ 65 years of age)
In general, recommended dosing for elderly patients with normal renal and hepatic function is the same as for younger adult patients with normal renal and hepatic function. Because elderly patients are more sensitive to opioid effects and more likely to have decreased renal and hepatic function, consideration should be given to starting elderly patients within the lower range of recommended doses (see 7.1.4. Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
4.2.1 Discontinuing Treatment
Patients on prolonged therapy with any tapentadol formulation may be withdrawn gradually from the drug if it is no longer required for pain control. Mild to moderate withdrawal symptoms could occur after abrupt discontinuation of treatment with tapentadol. Clinical experience suggests that withdrawal symptoms may be relieved by reinstitution of opioid therapy followed by a gradual, tapered dose reduction of the medication combined with symptomatic support (see 7. Warnings and Precautions, Withdrawal Symptoms and 8. Adverse Reactions).
4.4. Administration
NUCYNTA EXTENDED-RELEASE tablets must be swallowed whole with sufficient liquid. NUCYNTA EXTENDED-RELEASE tablets must not be cut, broken, crushed, chewed, or dissolved (see 3. Serious Warnings and Precautions box, 4.1. Dosing Considerations).
NUCYNTA EXTENDED-RELEASE tablets can be taken with or without food (see 10.3 Pharmacokinetics, Absorption, Food Effect).
4.5. Missed Dose
Patients should be advised not to take extra tablets or a double dose to make up for a missed dose. NUCYNTA EXTENDED-RELEASE should be taken once approximately every 12 hours.
5. Overdose
Signs and Symptoms
Experience with NUCYNTA EXTENDED-RELEASE overdose is very limited. Preclinical data suggest that symptoms similar to those of other centrally-acting analgesics with mu-opioid receptor agonist activity are to be expected upon intoxication with tapentadol. In principle, the clinical manifestations of opioid overdose are miosis, vomiting, cardiovascular collapse, consciousness disorders up to coma, convulsions, skeletal muscle flaccidity, cold and clammy skin, bradycardia, toxic leukoencephalopathy, delayed post-hypoxic leukoencephalopathy, hypotension, pneumonia aspiration, respiratory depression up to respiratory arrest, and death.
Management of Overdosage
Management of overdosage should be focused on treating symptoms of mu-opioid receptor agonism. Primary attention should be given to re-establishment of a patent airway and institution of assisted or controlled ventilation when overdosage of NUCYNTA EXTENDED-RELEASE is suspected.
Pure opioid antagonists, such as naloxone, are specific antidotes to respiratory depression resulting from opioid overdose. Respiratory depression following an overdose may outlast the duration of action of the opioid antagonist. Administration of an opioid antagonist is not a substitute for continuous monitoring of airway, breathing, and circulation following an opioid overdose. If the response to opioid antagonists is suboptimal or only brief in nature, an additional antagonist should be administered as directed by the manufacturer of the antagonist product. Overdosage with naloxone has been associated with seizure.
Gastrointestinal decontamination may be considered in order to eliminate unabsorbed drug. Gastrointestinal decontamination with activated charcoal or by gastric lavage may be considered within 2 hours after intake. Before attempting gastrointestinal decontamination, care should be taken to secure the airway.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 2 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non Medicinal Ingredients | |||
| Route of Administration | Dosage Form / Strength / Composition | Non Medicinal Ingredients | |||
| Extended-release tablet 50 mg (as 58.24 mg of tapentadol hydrochloride) | Ammonium hydroxide, black iron oxide, butyl alcohol, butylated hydroxytoluene, hypromellose, isopropyl alcohol, polyethylene glycol, polyethylene oxide, polyvinyl alcohol, propylene glycol, shellac glaze, talc, titanium dioxide, vitamin E. | ||||
| oral | Extended-release tablet 150 mg (as 174.72 mg of tapentadol hydrochloride) | Ammonium hydroxide, black iron oxide, butyl alcohol, butylated hydroxytoluene, FD&C blue #2 aluminum lake, hypromellose, isopropyl alcohol, polyethylene glycol, polyethylene oxide, polyvinyl alcohol, propylene glycol, shellac glaze, talc, titanium dioxide, vitamin E, yellow iron oxide. | |||
| Extended-release tablet 100 mg (as 116.48 mg of tapentadol hydrochloride) | Ammonium hydroxide, black iron oxide, butyl alcohol, butylated hydroxytoluene, FD&C blue #2 aluminum lake, hypromellose, isopropyl alcohol, polyethylene glycol, polyethylene oxide, polyvinyl alcohol, propylene glycol, shellac glaze, talc, titanium dioxide, vitamin E. | ||||
| Extended-release tablet 200 mg (as 232.96 mg of tapentadol hydrochloride) | Ammonium hydroxide, black iron oxide, butyl alcohol, butylated hydroxytoluene, FD&C blue #2 aluminum lake, hypromellose, isopropyl alcohol, polyethylene glycol, polyethylene oxide, polyvinyl alcohol, propylene glycol, shellac glaze, talc, titanium dioxide, vitamin E. | ||||
| Extended-release tablet 250 mg (as 291.2 mg of tapentadol hydrochloride) | Ammonium hydroxide, butyl alcohol, butylated hydroxytoluene, FD&C blue #2 aluminum lake, hypromellose, isopropyl alcohol, polyethylene glycol, polyethylene oxide, polyvinyl alcohol, propylene glycol, shellac glaze, talc, titanium dioxide, vitamin E. | ||||
Description
NUCYNTA EXTENDED-RELEASE tablets are composed of a hydrophilic matrix system with demonstrated extended-release properties obtained through the use of the specific melt extrusion manufacturing process and the polymer polyethylene oxide.
NUCYNTA EXTENDED-RELEASE tablets contain tapentadol (as tapentadol hydrochloride) as the medicinal ingredient and are available in 50 mg, 100 mg, 150 mg, 200 mg tapentadol dose strengths as follows:
50 mg tablet: A white oblong-shaped tablet with a black print “OMJ 50” on one side.
100 mg tablet: A light blue oblong-shaped tablet with a black print “OMJ 100” on one side.
150 mg tablet: A blue green oblong-shaped tablet with a black print “OMJ 150” on one side.
200 mg tablet: A blue oblong-shaped tablet with a depression in the middle running lengthwise on each side and a black print “OMJ 200” on one side.
250 mg tablet: A dark blue oblong-shaped tablet with a depression in the middle running lengthwise on each side and a white print “OMJ 250” on one side.
Packaging
NUCYNTA EXTENDED-RELEASE tablets is supplied as bottles of 60 tablets with dessicant.
7. Warnings and Precautions
See 3. Serious Warnings and Precautions Box.
General
NUCYNTA EXTENDED-RELEASE tablets must be swallowed whole with sufficient liquid. NUCYNTA EXTENDED-RELEASE tablets must never be cut, broken, chewed, divided, dissolved or crushed. Taking broken or divided NUCYNTA EXTENDED-RELEASE could lead to the uncontrolled release and rapid absorption of a potentially fatal dose of tapentadol.
Patients who have received NUCYNTA EXTENDED-RELEASE should be closely monitored, especially for signs of respiratory depression, until a stable maintenance dose is reached. As with many centrally acting analgesic medications, with both central and peripheral adverse effects, the dosing regimen should be individualized according to the severity of pain being treated, the previous treatment experience, and the ability to monitor the patient. Patients should be cautioned not to consume alcohol while taking NUCYNTA EXTENDED-RELEASE as it may increase the chance of experiencing serious adverse events, including death.
Risk of Overdosage: Serious potential consequences of overdosage with NUCYNTA EXTENDED-RELEASE are central nervous system depression, respiratory depression, and death. In treating an overdose, primary attention should be given to maintaining adequate ventilation along with general supportive treatment (see 5. Overdose).
Do not prescribe NUCYNTA EXTENDED-RELEASE for patients who are suicidal or addiction prone.
NUCYNTA EXTENDED-RELEASE should not be taken in doses higher than those recommended by the physician. The judicious prescribing of tapentadol is essential to the safe use of this drug.
Carcinogenesis and Mutagenesis
See 16. Non-Clinical Toxicology section.
Cardiovascular
Hypotension: Tapendatol administration may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by a reduced blood volume, or concurrent administration of drugs such as phenothiazines and other tranquilizers, sedatives/hypnotics, tricyclic antidepressants or general anesthetics (see 9.4 Drug-Drug Interactions). These patients should be monitored for signs of hypotension after initiating or titrating the dose of NUCYNTA EXTENDED-RELEASE. The use of NUCYNTA EXTENDED-RELEASE in patients with circulatory shock should be avoided as it may cause vasodilation that can further reduce cardiac output and blood pressure.
Dependence, Tolerance and/or Abuse Liability
As with other opioids, tolerance, dependence and opioid use disorder (OUD) may develop upon repeated administration of NUCYNTA EXTENDED-RELEASE. A higher dose and longer duration of opioid treatment can increase the risk of developing OUD.
Dependence and tolerance reflect the neuroadaptation of the opioid receptors to chronic exposure to an opioid, and are separate and distinct from abuse and OUD. Tolerance and dependence are not by themselves evidence of OUD or abuse.
The risk of developing OUD is increased in patients with a personal or a family history (parents or siblings) of substance use disorders (including alcohol use disorder), in current tobacco users or in patients with a personal history of other mental health disorders (e.g., major depression and anxiety).
Before initiating treatment with NUCYNTA EXTENDED-RELEASE and during the treatment, treatment goals and a discontinuation plan should be agreed with the patient (see 4.1. Dosing Considerations). Before and during treatment, the patient should also be informed about the risks and signs of OUD. If these signs occur, patients should be advised to contact their healthcare professional.
Patients will require monitoring for signs of drug-seeking behaviour (e.g., too early requests for refills). This includes the review of concomitant opioids and psycho-active drugs (like benzodiazepines). For patients with signs and symptoms of OUD, consultation with an addiction specialist should be considered.
NUCYNTA EXTENDED-RELEASE should not be used in opioid-dependent patients since it cannot suppress morphine withdrawal symptoms, even though it is an opioid agonist.
Abuse and Misuse:
Like all opioids, NUCYNTA EXTENDED-RELEASE is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, NUCYNTA EXTENDED-RELEASE should be prescribed and handled with caution.
Patients should be assessed for their clinical risks for opioid abuse or OUD prior to being prescribed opioids. All patients receiving opioids should be routinely monitored for signs of misuse and abuse.
Opioids, such as NUCYNTA EXTENDED-RELEASE should be used with particular care in patients with a history of alcohol and illicit/prescription drug abuse. However, concerns about abuse, OUD, and diversion should not prevent the proper management of pain.
NUCYNTA EXTENDED-RELEASE is intended for oral use only. NUCYNTA EXTENDED-RELEASE should be swallowed whole, cutting, breaking, crushing, chewing, snorting, or injecting the dissolved product can result in the uncontrolled delivery of the opioid and pose a significant risk to the patient, including overdose and death. With parenteral abuse, the tablet excipients can be expected to result in local tissue necrosis, infection, pulmonary granulomas, and an increased risk of endocarditis and valvular heart injury.
Withdrawal Symptoms:
The opioid withdrawal syndrome may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, rhinorrhea, sneezing, tremors or shivering, abdominal cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness, yawning, lacrimation, perspiration, myalgia, and mydriasis. Other symptoms also may develop, including irritability, backache, joint pain, insomnia, vomiting, increased blood pressure, respiratory rate or heart rate.
Generally, tolerance and/or withdrawal are more likely to occur the longer a patient is on continuous opioid therapy. Patients should be cautioned about the possibility of experiencing withdrawal symptoms and counselled accordingly.
Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer required for pain control. Clinical experience suggests that withdrawal symptoms may be relieved by reinstitution of opioid therapy followed by a gradual, tapered dose reduction of the medication combined with symptomatic support.
Neonatal Opioid Withdrawal Syndrome (NOWS):
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Use of NUCYNTA EXTENDED-RELEASE is contraindicated in pregnant women (see 2. Contraindications).
Interactions with Alcohol and Drugs of Abuse: Due to its mu-opioid agonist activity, NUCYNTA EXTENDED-RELEASE may be expected to have additive effects when used in conjunction with alcohol, opioids, or illicit drugs that cause central nervous system depression, respiratory depression, hypotension, and profound sedation, coma, or death. If such combined therapy is necessary, a dose reduction of one or both agents should be considered. Use of NUCYNTA EXTENDED-RELEASE with alcoholic beverages or prescription or non-prescription products containing alcohol should be avoided (see 9.4. Drug-Drug Interactions, Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants).
Use in Drug and Alcohol Addiction: NUCYNTA EXTENDED-RELEASE is an opioid with no approved use in the management of addictive disorders. Its proper usage in individuals with drug or alcohol dependence, either active or in remission is for the management of chronic pain requiring continuous treatment with an opioid analgesic. Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to NUCYNTA EXTENDED-RELEASE; extreme caution and awareness is warranted to mitigate the risk.
Driving and Operating Machinery
Patients should be cautioned that NUCYNTA EXTENDED-RELEASE may impair the mental and/or physical abilities required for the performance of potentially hazardous tasks such as driving a car or operating machinery. This is to be expected especially at the beginning of treatment, at any change of dosage, as well as in combination with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol (see 9.4. Drug-Drug Interactions, Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants).
Endocrine and Metabolism
Adrenal Insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency.
Gastrointestinal
Tapentadol and other morphine-like opioids have been shown to decrease bowel motility. Tapentadol may obscure the diagnosis or clinical course of patients with acute abdominal conditions (see 2. Contraindications).
Hepatic/Biliary/Pancreatic
Hepatic Impairment: A study of tapentadol in subjects with hepatic impairment showed higher serum concentrations than in those with normal hepatic function. NUCYNTA EXTENDED-RELEASE should be used with caution in patients with moderate hepatic impairment (see 4.2. Recommended Dose and Dosage Adjustment, Patients with Hepatic Impairment and 10.3. Pharmacokinetics, Special populations and conditions, Hepatic Insufficiency). NUCYNTA EXTENDED-RELEASE has not been studied in patients with severe hepatic impairment and, therefore, use in this population is contraindicated (see 2. Contraindications, 4.2. Recommended Dose and Dosage Adjustment, Patients with Hepatic Impairment, and 10.3. Pharmacokinetics, Special populations and conditions, Hepatic Insufficiency).
Use in Pancreatic/Biliary Tract Disease: Drugs with mu-opioid receptor agonist activity may cause spasm of the sphincter of Oddi. NUCYNTA EXTENDED-RELEASE should be used with caution in patients with biliary tract disease, including acute pancreatitis.
Immune
Hypersensitivity: There have been spontaneous post-marketing reports of hypersensitivity (e.g., anaphylaxis, angioedema, anaphylactic shock) in some patients during tapentadol treatment. Reported symptoms included skin redness, blisters, rash, hives, swollen face, throat tightness, dyspnea, and wheezing. Tapentadol treatment should be discontinued if such symptoms occur. Patients with hypersensitivity to tapentadol, or any other ingredient of the formulation or component of the container, should not take tapentadol (see 2. Contraindications and 8.5. Post-Market Adverse Reactions). Caution should also be exercised in patients who have had serious allergic reactions to other medications. For a complete listing of ingredients, see 6. Dosage forms, Strengths, Composition and Packaging.
Neurologic
Head Injury and Increased Intracranial Pressure: NUCYNTA EXTENDED-RELEASE should be used with caution in patients with increased intracranial pressure or head injury, since the respiratory depressant effects of opioid receptor agonism include carbon dioxide retention and secondary elevation of cerebrospinal fluid pressure, and such effects may be markedly exaggerated in these patients. Also, pupillary changes (miosis) from tapentadol may obscure the existence, extent or course of intracranial pathology. Clinicians should also maintain a high index of suspicion for adverse drug reactions when evaluating altered mental status in these patients if they are receiving tapentadol (see 2. Contraindications).
Interactions with Benzodiazepines and Other Central Nervous System (CNS) Depressants: Tapentadol should be used with caution and in a reduced dosage during concomitant administration of other opioid analgesics, general anesthetics, phenothiazines and other tranquilizers, sedatives, hypnotics, tricyclic antidepressants, antipsychotics, antihistamines, benzodiazepines, gabapentinoids, baclofen, centrally-active anti-emetics and other CNS depressants including alcohol. Respiratory depression, hypotension and profound sedation, coma or death may result. When such combination therapy is contemplated, a substantial reduction in the dose of one or both agents should be considered and patients should be carefully monitored (see 9.4. Drug-Drug Interactions, Drugs Associated with a Risk of Serotonin Toxicity (also known as Serotonin Syndrome). With patients who are depressed or suicidal, consideration should be given to the use of non-narcotic analgesics. NUCYNTA EXTENDED-RELEASE should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects.
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with opioid analgesics (see 9.4. Drug-Drug Interactions, Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants). If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation.
Advise both patients and caregivers about the risks of respiratory depression and sedation when NUCYNTA EXTENDED-RELEASE is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the benzodiazepine or other CNS depressant have been determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk for overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs (see 9.4. Drug-Drug Interactions, Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants).
NUCYNTA EXTENDED-RELEASE should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects, including death (see 2. Contraindications and 9.4. Drug-Drug Interactions, Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants).
Severe pain antagonizes the subjective and respiratory depressant actions of opioid analgesics. Should pain suddenly subside, these effects may rapidly become manifest.
Opioid induced hyperalgesia: Opioid induced hyperalgesia (OIH) is a paradoxical response to an opioid in which there is an increase in pain perception despite stable or increased opioid exposure. It differs from tolerance, in which higher opioid doses are required to achieve the same analgesic effect or treat recurring pain. Clinically, OIH may be associated with high opioid doses, long term opioid treatment, and intra-operative opioid use. OIH may manifest as an unexplained increase in pain, more diffuse pain than pre-existing, or as pain from ordinary (i.e. non-painful) stimuli (allodynia) in the absence of disease progression. When OIH is suspected, the dose of opioid should be reduced or tapered off, if possible. It is reasonable to consider opioid rotation, or the use of a non-opioid strategy for pain control. There is currently no well-established treatment for OIH.
Seizure Risk: Clinical studies with tapentadol excluded patients with a history of seizure disorder or epilepsy and those with a neurological disorder that may increase the risk of seizures, such as any of the following within one year: mild/moderate traumatic brain injury, stroke, transient ischemic attack, and brain neoplasm, and severe traumatic brain injury within 15 years (consisting of at least one of the following: brain contusion, intracranial hematoma, unconsciousness or post-traumatic amnesia, lasting for more than 24 hours or residual sequelae suggesting transient change in consciousness). During the clinical trials of tapentadol one subject with a past history of seizures developed convulsion.
Spontaneous post-marketing reports of patients receiving tapentadol indicate that seizures have been reported. Although tapentadol has been given with concomitant use of selective serotonin re-uptake inhibitors (SSRIs) or serotonin norepinephrine re-uptake inhibitors (SNRIs) and other medications in clinical trials, precaution should be used when tapentadol is administered concomitantly with other medications that may cause seizures. If seizures occur, tapentadol should be discontinued.
Risk of convulsions may also increase in patients with epilepsy, those with a history of seizures, or in patients with a recognized risk for seizure (such as head trauma, metabolic disorders, alcohol and drug withdrawal, CNS infections).
Serotonin toxicity / Serotonin syndrome: Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported with tapentadol hydrochloride, particularly during combined use with other serotonergic drugs (see 9.4. Drug-Drug Interactions, Drugs Associated with a Risk of Serotonin Toxicity (also known as Serotonin Syndrome).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with NUCYNTA EXTENDED-RELEASE and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4. Drug-Drug Interactions, Drugs Associated with a Risk of Serotonin Toxicity (also known as Serotonin Syndrome). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Perioperative Considerations
NUCYNTA EXTENDED-RELEASE is contraindicated for peri-operative pain relief. In the case of planned chordotomy or other pain-relieving operations, patients should not be treated with NUCYNTA EXTENDED-RELEASE for at least 48 hours before the operation and NUCYNTA EXTENDED-RELEASE should not be used in the immediate post-operative period. If NUCYNTA EXTENDED-RELEASE is to be continued after the patient recovers from the post-operative period, a new dosage should be administered in accordance with the changed need for pain relief. The risk of withdrawal in opioid-tolerant patients should be addressed as clinically indicated (see 7. Warnings and Precautions, Withdrawal Symptoms).
The administration of analgesics in the peri-operative period should be managed by healthcare providers with adequate training and experience (e.g., by an anesthesiologist).
Renal
NUCYNTA EXTENDED-RELEASE has not been studied in controlled efficacy studies in patients with severe renal impairment; therefore, its use in this population is contraindicated (see 2.Contraindications, 4.2. Recommended Dose and Dosage Adjustment, Patients with Renal Impairment, and 10.3. Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Reproductive Health
See sections 2.Contraindications and 7.1.1. Pregnancy
- Fertility
Animal data with tapentadol did not show an alteration of fertility at any dose level (see 16. Non-Clinical Toxicology, Reproductive and developmental toxicology, Impairment of fertility).
- Function
Long-term use of opioids may be associated with decreased sex hormone levels and symptoms such as low libido, erectile dysfunction, or infertility (see 8.5. Post-Market Adverse Reactions).
Respiratory
Respiratory Depression: Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Carbon dioxide (CO2) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids.
Respiratory depression is a potential problem in elderly or debilitated patients as well as in those suffering from conditions accompanied by hypoxia or hypercapnia when even moderate therapeutic doses may dangerously decrease pulmonary ventilation.
NUCYNTA EXTENDED-RELEASE should be administered with extreme caution to patients with conditions accompanied by hypoxia, hypercapnia, or decreased respiratory reserve such as: asthma, chronic obstructive pulmonary disease (COPD), cor pulmonale, severe obesity, sleep apnea syndrome, myxedema, kyphoscoliosis, CNS depression or coma. In these patients, even usual therapeutic doses of opioids may decrease respiratory drive while simultaneously increasing airway resistance to the point of apnea. Alternative non-opioid analgesics should be considered, and NUCYNTA EXTENDED-RELEASE should be employed only under careful medical supervision at the lowest effective dose in such patients (see 2. Contraindications).
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of NUCYNTA EXTENDED-RELEASE, the risk is greatest during the initiation of therapy or following a dose increase. Patients should be closely monitored for respiratory depression when initiating therapy with NUCYNTA EXTENDED-RELEASE and following dose increases.
Severe pain antagonizes the respiratory-depressant effects of opioids. However, should pain suddenly subside, these effects may rapidly become manifest. Patients who are scheduled for regional anesthetic procedures or other interruptions of pain transmission pathways should not receive NUCYNTA EXTENDED-RELEASE within 24 hours of the procedure. Concomitant administration of tapentadol with other opioid analgesics is associated with an increased risk of respiratory failure. Therefore, it is important to reduce the dose of tapentadol when other opioid analgesics are given concomitantly.
To reduce the risk of respiratory depression, proper dosing and titration of NUCYNTA EXTENDED-RELEASE are essential (see 4.2. Recommended Dose and Dosage Adjustment). Overestimating the NUCYNTA EXTENDED-RELEASE dose when converting patients from another opioid product can result in fatal overdose with the first dose. Respiratory depression has also been reported with the use of modified-release opioids even when used as recommended and not misused or abused.
If respiratory depression does occur, it should be treated as an overdose. If naloxone is to be administered, use cautiously because it may precipitate seizures (see 7. Warnings and Precautions, Neurologic, Seizure Risk and 5. Overdose).
Sleep Apnea: Opioids can cause sleep-related breathing disorders such as sleep apnea syndromes (including central sleep apnea [CSA]) and hypoxia (including sleep-related hypoxia). Opioid use increases the risk of CSA in a dose-dependent fashion. Evaluate patients on an ongoing basis for the onset of a new sleep apnea, or a worsening of an existing sleep apnea. In these patients, consider reducing or stopping the opioid treatment if appropriate, using best practices for tapering of opioids (see 4.2. Recommended Dose and Dosage Adjustment, Adjustment or Reduction of Dosage; 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability).
7.1. Special Populations
Special Risk Groups: Tapentadol should be administered with caution to patients with a history of alcohol and drug abuse and in a reduced dosage to debilitated patients, and in patients with severely impaired pulmonary function, Addison’s disease, hypothyroidism, myxedema, toxic psychosis, prostatic hypertrophy or urethral stricture.
7.1.1. Pregnancy
Studies in pregnant women have not been conducted. While animal reproduction studies have revealed no evidence of harm to the fetus, tapentadol crosses the placental barrier and is contraindicated in pregnant women and prior to or during labour and delivery (see 2 Contraindications; 16 Non-Clinical Toxicology).
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening (see 7. Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Neonatal Opioid Withdrawal Syndrome).
Pregnant women using opioids should not discontinue their medication abruptly as this can cause pregnancy complication such as miscarriage or still-birth. Tapering should be slow and under medical supervision to avoid serious adverse events to the fetus.
7.1.2 Breastfeeding
There is no information on the excretion of tapentadol in human milk. Therefore, NUCYNTA EXTENDED-RELEASE is contraindicated during breastfeeding. Life-threatening respiratory depression may occur in the infant if opioids are administered to the mother. Naloxone, a drug that counters the effects of opioids, should be readily available if NUCYNTA EXTENDED-RELEASE is used in this population.
- 7.1.3. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (> 65 years of age): In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy. NUCYNTA EXTENDED-RELEASE dosing for elderly patients with normal renal and hepatic function is the same as for younger adult patients with normal renal and hepatic function. Such patients should be monitored closely, particularly when initiating and titrating NUCYNTA EXTENDED-RELEASE and when this drug is given concomitantly with other opioids or drugs that depress respiration. Of the total number of patients in Phase 2/3 double-blind, multiple-dose clinical studies of NUCYNTA EXTENDED-RELEASE, 28% (1023/3613) were 65 years and over, while 7% (245/3613) were 75 years and over. No overall differences in effectiveness or tolerability were observed between these patients and younger patients (see 10.3. Pharmacokinetics, Special populations and conditions).
8. Adverse Reactions
8.1. Adverse Reaction Overview
Adverse effects of tapentadol are similar to those of other opioid analgesics and represent an extension of pharmacological effects of the drug class. The major hazards of opioids include respiratory and central nervous system depression and to a lesser degree, circulatory depression, respiratory arrest, shock and cardiac arrest.
NUCYNTA EXTENDED-RELEASE was studied in nine multiple-dose, active- or placebo-controlled Phase 2/3 studies. Patients were treated with doses ranging from 21.5 mg to 250 mg of NUCYNTA EXTENDED-RELEASE dosed twice a day. A total of 3613 patients with moderate to severe pain were treated with NUCYNTA EXTENDED-RELEASE, including 227 with exposure for more than 1 year. More than 60% of NUCYNTA EXTENDED-RELEASE treated subjects were opioid naïve (see 4.2. Recommended Dose and Dosage Adjustment, Initiation of Therapy, Patients Currently Not Taking Opioid Analgesics (Opioid Naïve)). The population was 18 to 91 years old (mean age 57.4 years).
Based on data from the double-blind, placebo- and/or active-controlled studies that administered multiple doses of NUCYNTA EXTENDED-RELEASE, 64.4% of NUCYNTA EXTENDED-RELEASE treated patients experienced adverse events. These were predominantly of mild and moderate severity. The most common adverse events (reported by ≥10% in any NUCYNTA EXTENDED-RELEASE dose group) were: nausea, dizziness, constipation and headache.
No deaths were reported during the treatment period or within 30 days after treatment discontinuation in NUCYNTA EXTENDED-RELEASE treated groups. Approximately 2.5% of NUCYNTA EXTENDED-RELEASE treated patients experienced a serious adverse event during the Phase 2/3 multi-dose studies vs. 1.0% on placebo.
Approximately 18% of NUCYNTA EXTENDED-RELEASE treated patients and 6% of patients on placebo with adverse events discontinued from the Phase 2/3 multi-dose studies. The most common reasons for discontinuation due to adverse events in the studies described above (reported by ≥1% in any NUCYNTA EXTENDED-RELEASE dose group) for NUCYNTA EXTENDED-RELEASE and placebo-treated patients were nausea (4.3% vs. 1.3%), dizziness (3.1% vs. 0.7%), vomiting (2.8% vs. 0.5%), somnolence (2.0% vs. 0.2%), constipation (1.4% vs. 0.2%), headache (1.2% vs. 0.3%) and fatigue (1.2% vs. 0.3%), respectively.
Withdrawal symptoms may occur if an opioid analgesic is discontinued abruptly. In all NUCYNTA EXTENDED-RELEASE clinical studies, all treatment was discontinued following patient exposure up to 1 year, without a requirement for a tapering regimen. In all Phase 2/3 NUCYNTA EXTENDED-RELEASE studies, patients taking NUCYNTA EXTENDED-RELEASE who stopped abruptly without initiating alternative opioid therapy were assessed for withdrawal symptoms between 2 to 4 days after discontinuation, and then between 5 to 14 days after discontinuation, using the Clinical Opioid Withdrawal Scale. There were 635 patients in the NUCYNTA EXTENDED-RELEASE group assessed between Day 2 and Day 4 after abrupt cessation of treatment with 11.8% and 2.0% of patients having mild or moderate withdrawal, respectively. Assessments on Day 5 or later were available for 1145 patients treated with NUCYNTA EXTENDED-RELEASE (mild, 5.1%; moderate 0.3%). Withdrawal symptoms may be reduced by further tapering NUCYNTA EXTENDED-RELEASE.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore the frequencies of adverse reactions observed in the clinical trials may not reflect the frequencies observed in clinical practice and should not be compared to the frequencies reported in the clinical trials of another drug.
Double-Blind Studies
Treatment-emergent adverse events (TEAEs) reported in ≥1% of NUCYNTA EXTENDED-RELEASE treated patients with moderate to severe pain from eight double-blind, active and/or placebo-controlled studies are summarized in Table 3, if they occurred at an equivalent or higher rate with NUCYNTA EXTENDED-RELEASE than with placebo. These adverse events were included regardless of any causal relationship to NUCYNTA EXTENDED-RELEASE.
Table 3 – Treatment-Emergent Adverse Events Reported by ≥1% of NUCYNTA EXTENDED-RELEASE Treated Patients in Phase 2/3 Double-Blind (Placebo- and/or Active-Controlled) Multiple-Dose Clinical Studies
| System/Organ Class MedDRA Preferred Term | NUCYNTA EXTENDED-RELEASE (n=2328) % | Placebo (n=1498) % |
|---|---|---|
| Ear and labyrinth disorders | ||
| Vertigo | 2.2 | 0.8 |
| Gastrointestinal disorders | ||
| Nausea | 18.0 | 8.5 |
| Constipation | 9.9 | 5.7 |
| Vomiting | 6.9 | 2.9 |
| Dry mouth | 4.6 | 1.7 |
| General disorders and administration site conditions | ||
| Fatigue | 5.4 | 3.2 |
| Asthenia | 1.8 | 0.7 |
| Chills | 1.1 | 0.2 |
| Infections and infestations | ||
| Bronchitis | 1.1 | 0.9 |
| Influenza | 1.0 | 0.7 |
| Investigations | ||
| Electrocardiogram QT prolonged | 1.0 | 0.3 |
| Metabolism and nutrition disorders | ||
| Decreased appetite | 1.5 | 0.5 |
| Musculoskeletal and connective tissue disorders | ||
| Pain in extremity | 1.5 | 1.3 |
| Myalgia | 1.0 | 0.6 |
| Nervous system disorders | ||
| Dizziness | 11.8 | 5.1 |
| Headache | 11.4 | 11.3 |
| Somnolence | 8.2 | 2.9 |
| Tremor | 1.4 | 0.2 |
| Lethargy | 1.2 | 0.2 |
| Psychiatric disorders | ||
| Insomnia | 3.5 | 1.9 |
| Anxiety | 2.7 | 0.9 |
| Restlessness | 1.0 | 0.2 |
| Respiratory, thoracic and mediastinal disorders | ||
| Pharyngolaryngeal pain | 1.1 | 1.0 |
| Skin and subcutaneous tissue disorders | ||
| Hyperhidrosis | 4.8 | 1.1 |
| Pruritus | 3.9 | 1.3 |
| Rash | 1.0 | 0.8 |
| Vascular disorders | ||
| Hot flush | 1.3 | 0.3 |
8.3. Less Common Clinical Trial Adverse Reactions
The following treatment-emergent adverse events (TEAEs), which have been included regardless of any causal relationship to tapentadol, occurred in less than 1% in NUCYNTA EXTENDED-RELEASE treated patients in the double-blind, placebo- or active-controlled clinical studies and were observed at a higher incidence with NUCYNTA EXTENDED-RELEASE than with placebo:
- Cardiac disorders: tachycardia, bradycardia, extrasystoles
- Ear and labyrinth disorders: tinnitus
- Endocrine disorders: hypothyroidism
- Eye disorders: vision blurred, lacrimation increased, dry eye
- Gastrointestinal disorders: food poisoning, hematochezia, gastric disorder, rectal hemorrhage
- General disorders and administration site conditions: malaise, feeling jittery, drug withdrawal syndrome, feeling cold, chest pain, feeling hot, feeling abnormal, feeling of body temperature change, thirst, sluggishness
- Infections and infestations: gastroenteritis, cystitis, rhinitis, viral infection, localized infection, pneumonia, tooth infection, pharyngitis streptococcal, tooth abscess, infection
- Injury, poisoning and procedural complications: contusion, muscle strain, excoriation
- Investigations: blood pressure increased, gamma glutamyltransferase increased, weight decreased, electrocardiogram abnormal, electrocardiogram T-wave abnormal, blood calcium increased
- Metabolism and nutrition disorders: anorexia, dehydration, hypoglycemia, hypokalemia
- Musculoskeletal and connective tissue disorders: neck pain, bone pain, muscle twitching, osteoarthritis, muscular weakness, musculoskeletal chest pain
- Nervous system disorders: disturbance in attention, migraine, dysgeusia, paraesthesia, hypoesthesia, restless legs syndrome, syncope, balance disorder, sedation, depressed level of consciousness, hypersomnia, memory impairment, mental impairment, tension headache. Seizure occurred in one volunteer with a history of seizure in a Phase 1 study.
- Psychiatric disorders: depression, sleep disorder, depressed mood, nervousness, abnormal dreams, nightmare, agitation, disorientation, hallucination, stress, euphoric mood, libido decreased
- Renal and urinary disorders: dysuria, hematuria
- Reproductive system and breast disorders: erectile dysfunction
- Respiratory, thoracic and mediastinal disorders: dyspnea, rhinorrhea, yawning, wheezing, hiccups
- Skin and subcutaneous tissue disorders: pruritus generalized, erythema, night sweats, piloerection, eczema, urticaria, rash macular
- Vascular disorders: pallor
QTc Interval in Healthy Volunteers: In a thorough QT study in healthy volunteers under stringent study conditions, tapentadol showed no clinically relevant effect on the QTc interval (see 10.2. Pharmacodynamics, Clinical safety pharmacology, Cardiac Electrophysiology).
8.5. Post-Market Adverse Reactions
Adverse events identified during post-marketing experience with tapentadol are included in Table 4. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
In Table 4, based on patient treatment years, the frequencies are provided according to the following convention:
Very common ≥1/10
Common ≥1/100 and <1/10
Uncommon ≥1/1000 and <1/100
Rare ≥1/10,000, <1/1000
Very Rare <1/10,000
Not known (cannot be estimated from the available data)
Table 4 – Adverse Events Identified During Post-Marketing Experience with Tapentadol
Gastrointestinal disorders
Rare
Diarrhea
Immune system disorders
Uncommon
Hypersensitivity (including rare events of angioedema, anaphylaxis and anaphylactic shock)
Psychiatric disorders
Rare
Hallucination
Very rare
Not known
Panic attack
Delirium
Nervous system disorders
Uncommon
Headache
Cardiac disorders
Rare
Palpitations
Androgen deficiency: Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
Hypersensitivity: There have been reports of hypersensitivity (e.g., anaphylaxis, angioedema, anaphylactic shock), including fatalities, in some patients during tapentadol treatment. Reported symptoms included skin redness, blisters, rash, hives, swollen face, throat tightness, dyspnea, and wheezing. Tapentadol treatment should be discontinued if such symptoms occur. Patients with hypersensitivity to tapentadol, or any other ingredient of the formulation or component of the container, should not take NUCYNTA EXTENDED-RELEASE (see 2. Contraindication and 7. Warnings and Precautions, Hypersensitivity). For a complete listing of ingredients, see the 6. Dosage Forms, Strengths, Composition and Packaging section of the Product Monograph.
Serotonin Toxicity (also known as Serotonin syndrome): Cases of serotonin toxicity/serotonin syndrome, a potentially life-threatening condition, has been reported with tapentadol when used concomitantly with other serotonergic agents such as SSRI’s and MAOIs.
Suicidality: Suicidal ideation has been reported during post-market use of tapentadol. A causal relationship between suicidal ideation and tapentadol drug exposure has not been established based on data from clinical trials and post-marketing reports.
9. Drug Interactions
9.1. Serious Drug Interactions
Risks from concomitant use of opioids and benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see 7 Warnings and Precautions, Neurologic, Interactions with CNS Depressants (including benzodiazepines and alcohol))
- Reserve concomitant prescribing of NUCYNTA EXTENDED RELEASE and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate
- Consider dose reduction of CNS depressants in situations of concomitant prescribing
- Follow patients for signs and symptoms of respiratory depression and sedation
- Monoamine oxidase inhibitors (MAOIs) intensify the effects of opioid drugs which can cause anxiety, confusion and decreased respiration. NUCYNTA EXTENDED RELEASE is contraindicated in patients receiving MAOIs or who have used them within the previous 14 days.
9.2. Drug Interactions Overview
Tapentadol is mainly metabolized by glucuronidation, a system with a very high capacity which is not easily saturated even in disease. As therapeutic concentrations of drugs that are subject to glucuronidation are generally well below the concentrations needed for potential inhibition of glucuronidation, the risk of clinically relevant interaction between these drugs is generally low. The following substances have been included in a set of interaction studies without any clinically significant finding: acetaminophen, acetylsalicylic acid, naproxen and probenecid. The pharmacokinetics of tapentadol were not affected when gastric pH or gastrointestinal motility were increased by omeprazole and metoclopramide, respectively.
Plasma protein binding of tapentadol is low (approximately 20%). Therefore, the likelihood of pharmacokinetic drug-drug interactions by displacement from the protein binding site is low.
Drugs Metabolized by Cytochrome P450 Enzymes
In vitro investigations indicate that tapentadol does not inhibit or induce P450 enzymes. Thus, clinically relevant interactions mediated by the cytochrome P450 system are unlikely to occur.
Drugs That Inhibit or Induce Cytochrome P450 Enzymes
The major pathway of tapentadol metabolism is conjugation with glucuronic acid to produce glucuronides, a high capacity metabolic pathway. To a lesser extent, tapentadol is additionally metabolized to N-desmethyl tapentadol (13%) by CYP2C9 and CYP2C19, and to hydroxy tapentadol (2%) by CYP2D6, which are further metabolized by conjugation. Since only a minor amount of tapentadol is metabolized via the oxidative pathway, clinically relevant interactions mediated by the cytochrome P450 system are unlikely to occur.
Alcohol Interaction Study
An in vivo, cross-over study examined the effect of alcohol (240 mL of 40%) on the bioavailability of a single dose of 100 mg and 250 mg of NUCYNTA EXTENDED-RELEASE tablets in 19 healthy, fasted volunteers. After co-administration of a 100 mg NUCYNTA EXTENDED-RELEASE tablet and alcohol, the mean Cmax value increased by 48% compared to control (consumed water instead of alcohol) with a range of 0.99-fold up to 4.38-fold. In addition, the 3 subjects (15%) with the highest Cmax values were at least 2.3 times that of the control mean Cmax value. The mean tapentadol AUClast and AUCinf were increased by 17%; the Tmax and t1/2 were relatively unchanged. After co-administration of a 250 mg NUCYNTA EXTENDED-RELEASE tablet and alcohol, the mean Cmax value increased by 28% compared to control with a range of 0.90-fold up to 2.67-fold. The individual Cmax value for 2 of these subjects (10%) were at least 2.6 times that of the control mean Cmax value. The mean tapentadol AUClast and AUCinf were increased by 16%; the Tmax and t1/2 were relatively unchanged. However, concomitant use of alcohol must be avoided since NUCYNTA EXTENDED-RELEASE is expected to have additive effects when used in conjunction with alcohol (see 7. Warnings and Precautions, Neurologic, Interactions with Benzodiazepines and Other Central Nervous System (CNS) Depressants)
9.3. Drug-Behavioural Interactions
The concomitant use of alcohol should be avoided. Due to its mu-opioid agonist activity, NUCYNTA EXTENDED-RELEASE may be expected to increase the sedative effects of alcohol (see 3. Serious Warnings and Precautions Box).
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 5 – Established or Potential Drug-Drug Interactions
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
CNS Depressants (e.g., benzodiazepines, other opioid agonist analgesics, general anesthetics, phenothiazines, antiemetics, antitussives or substitution treatments, benzodiazepines, other tranquilizers, muscle relaxants (e.g., baclofen), sedatives, hypnotics, barbiturates, gabapentinoids (gabapentin and pregabalin), alcohol) | T | Due to additive pharmacologic effect, the concomitant use with tapentadol may increase the risk of hypotension, respiratory depression, profound sedation, coma, and death. | If such combined therapy is contemplated, a dose reduction of one or both agents should be considered. NUCYNTA EXTENDED-RELEASE should not be consumed with alcohol as it may increase the risk of dangerous side effects. |
Monoamine Oxidase inhibitors (MAOIs) (e.g., linezolid, methylene blue and triptans) | C, T | Due to potential additive effects on norepinephrine levels, the concomitant use of tapentadol and a MAOI may result in adverse cardiovascular events. | NUCYNTA EXTENDED-RELEASE is contraindicated in patients who are receiving MAOIs or who have taken them within the last 14 days (see 2. Contraindications). |
| Anticholinergic Drugs (e.g., oxybutynin, ipratropium bromide, tiotropium, carbamazepine) | T | The use of NUCYNTA EXTENDED-RELEASE with anticholinergic products may increase the risk of urinary retention and/or severe constipation, which may lead to paralytic ileus. | Caution is warranted. |
Serotonergic Agents (e.g., selective serotonin re-uptake inhibitors [SSRIs], serotonin norepinephrine re-uptake inhibitors [SNRIs]), and other serotonergic drugs [tricyclic antidepressants, MAOIs] and drugs that impair metabolism of serotonin) | C, T | Coadministration with NUCYNTA EXTENDED-RELEASE may increase the risk of serotonin syndrome, a potentially life-threatening condition. This can occur within the recommended dose. | Caution is warranted when tapentadol used in concomitantly of serotonergic drugs. See 7. Warnings and Precautions, Neurologic, Serotonin toxicity / Serotonin syndrome) |
Legend: C = Case Study; T = Theoretical
9.5. Drug-Food Interactions
No significant effects on the pharmacokinetics of NUCYNTA EXTENDED-RELEASE were observed with administration of a high fat meal. NUCYNTA EXTENDED-RELEASE can be taken with or without food (see 10.3. Pharmacokinetics, Absorption, Food Effect).
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Tapentadol is a centrally-acting synthetic analgesic. Although its exact mechanism is unknown, analgesic efficacy is thought to be due to mu-opioid agonist activity and the inhibition of norepinephrine reuptake.
Tapentadol hydrochloride, the centrally-active analgesic (anti-nociceptive) agent has an apparent dual-mode of action. Tapentadol is a mu-opioid receptor agonist with a Ki (mean ± SD) of 0.16 ± 0.04 mcM, compared to morphine with a mean Ki of 0.009 ± 0.0035 mcM, for the human mu-opioid receptor. In the GTPγS assay using membranes from cells expressing recombinant human µ-opioid receptors, the potency (mean EC50 ± SD) of tapentadol is 0.67 ± 0.15 mcM, compared to 0.022 ± 0.003 mcM for morphine.
Tapentadol also inhibits, in vitro, the reuptake of norepinephrine via the norepinephrine transporter. Both mechanisms are likely to contribute to the analgesic effects of the compound. In a microdialysis study in the rat, tapentadol elicited a dose-dependent increase of extracellular concentrations of norepinephrine whereas morphine did not increase extracellular concentrations of norepinephrine.
10.2. Pharmacodynamics
Tapentadol is a novel 3-[(1R, 2R)-3-(dimethylamino)-1-ethyl-2-methylpropyl]phenol with a dual mechanism of action, mu-opioid agonist and norepinephrine reuptake inhibitor. It is 18 times less potent than morphine in binding to the human mu-opioid receptor and is 2-3 times less potent in producing analgesia in animal models. Tapentadol has been shown to inhibit norepinephrine reuptake in the brains of rats, resulting in increased norepinephrine concentrations. In preclinical models, the analgesic activity due to the mu-opioid receptor agonist activity of tapentadol can be antagonized by selective mu-opioid antagonists (e.g., naloxone), whereas the norepinephrine reuptake inhibition is sensitive to norepinephrine modulators.
In preclinical models, the analgesic activity due to the mu-opioid receptor agonist activity of tapentadol can be antagonized by selective mu-opioid antagonists (e.g., naloxone), whereas the norepinephrine reuptake inhibition is sensitive to norepinephrine modulators.
Tapentadol-O-glucuronide, the major metabolite in man has no mu-opioid binding affinity and has no effects on norepinephrine – and 5-hydroxy tryptophan uptake mechanisms, up to a concentration of 10 mcM. Furthermore, there are no other metabolites which contribute to the analgesic activity of tapentadol. Tapentadol exerts its analgesic effects without a pharmacologically active metabolite.
Clinical Safety Pharmacology
Cardiac Electrophysiology
Thorough QT Study: In a randomized, double-blind, placebo- and positive-controlled crossover study, healthy subjects (N=61-63) were administered five consecutive doses of immediate-release tapentadol, NUCYNTA IR, 100 mg every 6 hours, NUCYNTA IR 150 mg every 6 hours, placebo and a single dose of moxifloxacin. At the doses studied, which produced mean±SD steady-state Cmax values of 129±42.0 ng/mL for the 100 mg q6h dose and 197±89.1 ng/mL for the 150 mg q6h dose, immediate release tapentadol (NUCYNTA IR) had no relevant effect on the QTc interval, the PR interval, or QRS duration
Evaluation in Phase 2/3 Clinical Trials: In Phase 2/3 multiple-dose clinical studies, mean blood pressure values were similar between tapentadol and placebo for up to 3 months, but the frequencies of cases with clinically significant changes in blood pressure (blood pressure increased or decreased, hypertension or hypotension), were higher in those on tapentadol. In an objective central electrocardiogram (ECG) evaluation of Phase 2/3 clinical studies, tapentadol showed no clinically relevant effect on the QTc interval.
Dependence
Tolerance and/or a withdrawal syndrome are more likely to occur the longer a patient is on continuous opioid therapy. Withdrawal symptoms included: nausea, diarrhea, insomnia, sweating, anxiety, arthralgia, and chills. Withdrawal symptoms may be reduced by tapering.
In a randomized, open-label, parallel group safety study, NUCYNTA EXTENDED-RELEASE maintained stable analgesic scores throughout the 12-month duration of the study with stable average total daily dose, indicating no development of tolerance to the tested dose ranges of 50 to 250 mg twice daily. In another clinical study in patients with neuropathic pain (safety data only), patients were allowed to titrate within 3 weeks to optimal treatment dose followed by randomization to placebo or the same dose of NUCYNTA EXTENDED-RELEASE (100 to 250 mg) fixed for 12 weeks in the maintenance period. Stable analgesia was maintained; there was no evidence for tolerance to NUCYNTA EXTENDED-RELEASE, either over 15 weeks in fixed dosing, or over one year with flexible dosing.
10.3. Pharmacokinetics
Absorption
Mean absolute bioavailability after single-dose administration (fasting) of tapentadol is approximately 32% due to extensive first-pass metabolism. Maximum serum concentrations of tapentadol are observed between 3 and 6 hours after administration of NUCYNTA EXTENDED-RELEASE. Dose proportional increases in serum AUC and Cmax were observed following administration of NUCYNTA EXTENDED-RELEASE as single doses over a range of 50-250 mg.
Steady-state exposure of tapentadol is attained following the third dose (i.e., within 36 hours after the first twice-daily multiple dose administration). Mean serum tapentadol AUC and Cmax values accumulated approximately 1.86- and -1.6 times, respectively, following dosing with 250 mg every 12 hours, relative to single-dose administration. The serum accumulation ratio is primarily determined by the dosing interval and apparent half-life of tapentadol.
Food Effect: The AUC and Cmax increased by 6% and 17%, respectively, when NUCYNTA EXTENDED-RELEASE tablets were administered after a high-fat, high-calorie breakfast. Phase 3 clinical studies were conducted without restrictions to food intake. NUCYNTA EXTENDED-RELEASE may be given with or without food.
Distribution
Tapentadol is widely distributed throughout the body. Following intravenous administration, the volume of distribution (Vz) for tapentadol is 540 ± 98 L. The plasma protein binding is low and amounts to approximately 20%.
Metabolism
In humans, the metabolism of tapentadol is extensive. About 97% of the parent compound is metabolized. Tapentadol is mainly metabolized via Phase 2 pathways, and only a small amount is metabolized by Phase 1 oxidative pathways. The major pathway of tapentadol metabolism is conjugation with glucuronic acid to produce glucuronides. After oral administration, approximately 70% (55% O-glucuronide and 15% sulfate of tapentadol) of the dose is excreted in urine in the conjugated form. A total of 3% of drug was excreted in urine as unchanged drug. Tapentadol is additionally metabolized to N-desmethyl tapentadol (13%) by CYP2C9 and CYP2C19 and to hydroxy tapentadol (2%) by CYP2D6, which are further metabolized by conjugation. Therefore, drug metabolism mediated by the cytochrome P450 system is of less importance than phase 2 conjugation. None of the metabolites contributes to the analgesic activity.
Elimination
Tapentadol and its metabolites are excreted almost exclusively (99%) via the kidneys. The terminal half-life after oral administration is approximately 5.0 hours and the apparent clearance (CL/F) is on average 4449 (±1199) mL/min across all doses of tapentadol extended-release. The total serum clearance of tapentadol after intravenous administration is 1530 ± 177 mL/min.
Special populations and conditions:
- Pediatrics (< 18 years of age): The pharmacokinetic profile of tapentadol in children has not been evaluated. No clinical studies with NUCYNTA EXTENDED-RELEASE have been conducted in children. Health Canada has not authorized an indication for pediatric use.
- Geriatrics (≥ 65 years of age): The mean exposure (AUC) to tapentadol was similar in elderly subjects and young adults, with a 16% lower mean Cmax observed in the elderly subject group compared to young adult subjects. Because elderly patients are more sensitive to opioid effects and more likely to have decreased renal and hepatic function, care should be taken in dose selection as recommended.
- Sex: Sex was not identified as a statistically significant covariate in the Population Pharmacokinetic Analysis of tapentadol.
- Genetic Polymorphism: Tapentadol is primarily eliminated through glucuronidation by several uridine diphosphate glucuronyl transferase isozymes. Although there are no direct data on the impact of genetic variation of single isozymes on the pharmacokinetics of tapentadol or its glucuronide metabolite, such effect is not expected. Due to the small contribution of CYP2C9, CYP 2C19, and CYP2D6 to the metabolism of tapentadol, a contribution of genetic polymorphism of these enzymes to variability in the pharmacokinetics of tapentadol is not expected.
- Ethnic Origin: No statistically significant effect of ethnic origin on any of the pharmacokinetic parameters was identified.
- Hepatic Insufficiency: Administration of tapentadol resulted in higher exposures and serum levels to tapentadol in subjects with impaired hepatic function compared to subjects with normal hepatic function. The ratios of tapentadol pharmacokinetic parameters for the mild and moderate hepatic impairment groups in comparison to the normal hepatic function group were 1.7 and 4.2, respectively, for AUC; 1.4 and 2.5, respectively, for Cmax; and 1.2 and 1.4, respectively, for t1/2. The rate of formation of tapentadol-O-glucuronide was lower in subjects with increased liver impairment (see 2. Contraindications).
Renal Insufficiency: AUC and Cmax of tapentadol were comparable in subjects with varying degrees of renal function (from normal to severely impaired). In contrast, increasing exposure (AUC) to tapentadol-O-glucuronide was observed with increasing degree of renal impairment. In subjects with mild, moderate, and severe renal impairment, the AUC of tapentadol-O-glucuronide was 1.5-,
2.5-, and 5.5-fold higher compared with normal renal function, respectively (see 2. Contraindications).
Mastication Study: A single-center, open-label, single-dose, randomized, 2-way cross-over study was conducted to evaluate the safety, tolerability, and pharmacokinetics following mastication (chewing) of a 100 mg NUCYNTA EXTENDED-RELEASE tablet in 24 healthy male subjects compared to the ingestion of an intact 100 mg tapentadol immediate-release (IR) tablet swallowed whole. The subjects received each single-dose in random order (washout period of 5 to 7 days between both single-dose administrations), under fasted conditions. Serial blood samples were collected from predose to up to 48 hours postdose for the measurement of tapentadol in serum. On a scale regarding difficulty of chewing the NUCYNTA EXTENDED-RELEASE tablet (easy, slightly difficult, moderately difficult, and very difficult), the majority of subjects (18/24; 75%) reported that chewing the tablet for up to 3 minutes was difficult (slightly, moderately, very) and unpleasant. Six of the 24 subjects found the tablet easy to chew. Of the 24 subjects, 20 (83.3%) described the taste of the tablet as “bitter.” However, all subjects except one chewed and swallowed the tablet successfully. The mean tapentadol Cmax (55.8 ng/mL) following ingestion of the masticated 100-mg NUCYNTA EXTENDED-RELEASE tablet was lower relative to the Cmax produced by an intact 100-mg IR tablet swallowed whole (129 ng/mL), whereas there were no significant differences in the mean tapentadol AUC. Compared to the intact IR tablet swallowed whole, extended-release properties of the NUCYNTA EXTENDED-RELEASE tablet were not maintained in 5 subjects (20%), as mastication and subsequent swallowing of the chewed NUCYNTA EXTENDED-RELEASE tablet resulted in the release of tapentadol. In 79% (19/24 subjects), the extended-release properties of the NUCYNTA EXTENDED-RELEASE tablet were maintained. Tapentadol Cmax was approximately 32% higher in 2 subjects who chewed the NUCYNTA EXTENDED-RELEASE tablet, relative to the intact IR tablet swallowed whole. For all other subjects, the Cmax was 13% to 82% lower for the chewed NUCYNTA EXTENDED-RELEASE tablet, relative to the intact IR tablet.
NUCYNTA EXTENDED-RELEASE tablets are to be swallowed whole with sufficient volume of liquid and must not be chewed. Taking chewed NUCYNTA EXTENDED-RELEASE tablets can lead to the rapid release and absorption of a potentially fatal dose of tapentadol (see 7. Warnings and Precautions, Abuse, Addiction and Misuse and 4.4. Administration).
- 11. Storage, Stability, and Disposal
Storage and Stability
NUCYNTA EXTENDED-RELEASE tablets should be stored at 15-30℃.
Keep NUCYNTA EXTENDED-RELEASE out of the sight and reach of children.
NUCYNTA EXTENDED-RELEASE should be kept in a safe place, out of the sight and reach of children before, during and after use. NUCYNTA EXTENDED-RELEASE should not be used in front of children, since they may copy these actions.
Disposal
NUCYNTA EXTENDED-RELEASE should never be disposed of in household trash. Disposal via a pharmacy take-back program is recommended. Unused or expired NUCYNTA EXTENDED-RELEASE should be properly disposed of as soon as it is no longer needed to prevent accidental exposure to others, including children or pets. If temporary storage is required before disposal, a sealed child-proof container, such as a biohazard waste container or a lockable medication box could be obtained from a pharmacy.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: tapentadol hydrochloride
Chemical name: 3-[(1R,2R)-3-(dimethylamino)-1-ethyl-2-methylpropyl]phenol hydrochloride
Molecular formula and molecular mass: The molecular formula is C14H23NO•HCl. The molecular weight of tapentadol HCl is 257.80 g/mol, molecular weight of tapentadol base is 221.34 g/mol.
Structural formula:
Physicochemical properties: Tapentadol hydrochloride is a white to off-white powder. Tapentadol hydrochloride is freely soluble in water, 0.1 N HCl, and simulated intestinal fluid (SIF), soluble in ethanol, sparingly soluble in methanol and slightly soluble in 2-propanol. The melting point ranges from 204 to 210 °C. The n-octanol:water partition coefficient log P value is 2.89. The pKa values are 9.36 and 10.37.
14. Clinical Trials
14.1. Clinical Trials by Indication
Moderate to Severe Chronic Pain
Table 6 – Summary of patient demographics for clinical trials in moderate to severe chronic pain
| Study | Study design | Dosage, route of administration and duration | Study subjects (n) | Age (Range) | Sex |
|---|---|---|---|---|---|
Chronic low back pain PAI-3011 | Randomized, double-blind, parallel-group; placebo and active | 3-week titration to effect then 12 weeks maintenance with controlled dose adjustment NUCYNTA EXTENDED-RELEASE: 100 mg to 250 mg BID Oxycodone CR: 20 mg to 50 mg BID Placebo | n=965 (Randomized n=981) | 49.9 (18 to 89) | M: 406 F: 559 |
Pain from Osteo-arthritis of the knee PAI-3008 | Randomized, double-blind, parallel-group; placebo and active | 3-week titration to effect then 12 weeks maintenance with controlled dose adjustment NUCYNTA EXTENDED-RELEASE: 100 mg to 250 mg BID Oxycodone CR: 20 mg to 50 mg BID placebo | n=1023 (Randomized n= 1030) | 58.3 (40 to 91) | M: 405 F: 618 |
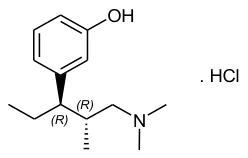
Table 7 – Summary of patient demographics for clinical trials in NUCYNTA IR and NUCYNTA EXTENDED-RELEASE Dose Conversion Study
| Study | Study design | Dosage, route of administration and duration | Study subjects (n) | Age (Range) | Sex |
|---|---|---|---|---|---|
PAI-3019/KF3 9 Chronic low back pain | Randomized, double-blind, 2-period crossover | Titration phase (3-week titration to optimal effect and tolerability): NUCYNTA IR 50 mg, 75 mg, or 100 mg q4-6h. Double-blind phase (two 14-day cross-over periods): NUCYNTA IR 50 mg, 75 mg, or 100 mg q4-6h at dose reached during titration; NUCYNTA EXTENDED-RELEASE 100 mg, 150 mg, 200 mg, or 250 mg BID at the same total daily dose as for IR | n=116 (open–label) n=87 (for safety during double-blind treatment) n=60 (per protocol for non-inferiority) | 53.6 years (21-88 years) | M: 51 F: 65 |
The efficacy and safety of NUCYNTA EXTENDED-RELEASE have been established in two studies in patients with moderate to severe chronic pain. The studies were randomized, double-blind, placebo- and active-controlled studies – one in patients with low back pain (LBP) and one in patients with pain related to osteoarthritis. An additional double-blind crossover study was also conducted to test whether subjects with moderate to severe chronic low back pain titrated to stable efficacy and tolerability could be switched between NUCYNTA IR (50 mg, 75 mg, or 100 mg every 4 to 6 hours) and NUCYNTA EXTENDED-RELEASE (100 mg, 150 mg, 200 mg, or 250 mg twice daily) while maintaining comparable efficacy.
Study PAI-3011 (chronic low back pain)
Study PAI-3011 was a randomized, multi-centre, double-blind, parallel-group study in patients with moderate to severe chronic LBP, comparing controlled dose-adjustment regimens of NUCYNTA EXTENDED-RELEASE (100 to 250 mg b.i.d.) to oxycodone controlled release (CR, 20 to 50 mg b.i.d.), and placebo b.i.d. Efficacy was evaluated in patients 18 years of age or older with chronic low back pain and a baseline pain score of ≥5 on an 11-point numerical rating scale (NRS), ranging from 0 to 10. Patients were randomized in a 1:1:1 ratio to 1 of 3 treatments: NUCYNTA EXTENDED-RELEASE, oxycodone CR, or placebo.
Following a screening and a wash-out period, patients randomized to NUCYNTA EXTENDED-RELEASE and oxycodone CR initiated the titration period with NUCYNTA EXTENDED-RELEASE 50 mg and oxycodone CR 10 mg twice daily respectively for three days. The dose was increased to NUCYNTA EXTENDED-RELEASE 100 mg b.i.d., oxycodone CR 20 b.i.d., or placebo b.i.d. for the next 4 days. Thereafter, increases in dose were allowed in increments of NUCYNTA EXTENDED-RELEASE 50 mg b.i.d., oxycodone CR 10 mg b.i.d., or placebo for the remaining of the three weeks titration period to achieve a stable optimal dose. Subsequent titrations in increments of NUCYNTA EXTENDED-RELEASE 50 mg b.i.d., oxycodone CR 10 mg b.i.d. were allowed over a 3-week titration period to a dose of 100 mg to 250 mg twice daily to achieve an optimal therapeutic dose. A 12-week maintenance period followed the titration period with allowed controlled dose adjustments in increments of NUCYNTA EXTENDED-RELEASE 50 mg b.i.d., oxycodone CR 10 mg b.i.d. every three days.
Efficacy was evaluated by comparing the difference in pain intensity from baseline to the last week of the maintenance period between NUCYNTA EXTENDED-RELEASE and placebo, and the difference in pain intensity from baseline to overall maintenance period between NUCYNTA EXTENDED-RELEASE and placebo. The primary efficacy analyses were performed using the last observation carried forward (LOCF) imputation method for missing values. Sensitivity analyses were performed with various imputation methods (baseline observation carried forward [BOCF], worst observation carried forward [WOCF], placebo mean imputation [PMI], and modified BOCF to evaluate the robustness of the observed treatment effects on the primary efficacy endpoints.
There were 981 patients randomized; 965 patients received study drug. The mean age of the study population was 49.9 (range 18 to 89) years; the mean baseline pain intensity score was 7.6 (SD 1.29). Approximately half of the patients (46.6%) were opioid-naïve (had not taken opioids during the three months prior to the screening visit).
The number of patients completing the study was 50.5% in the placebo group, 54.1% in the NUCYNTA EXTENDED-RELEASE group and 43.3% in the oxycodone CR group. Lack of efficacy was the most common reason for discontinuation among placebo-treated patients (20.7%), whereas adverse events were the most common reason for discontinuation among the active treatment groups (16.7% and 32.3% for NUCYNTA EXTENDED-RELEASE and oxycodone CR, respectively).
Study PAI-3008 (osteoarthritis pain)
Study PAI-3008 was a randomized, multi-centre, double-blind, parallel-group study, comparing controlled dose-adjustment regimens of NUCYNTA EXTENDED-RELEASE (100 to 250 mg b.i.d.) to oxycodone controlled release (CR, 20 to 50 mg b.i.d.), and placebo in patients with moderate to severe chronic pain due to OA of the knee. Efficacy was evaluated in patients 40 years of age or older with pain due to osteoarthritis and a pain score of ≥5 on an 11-point numerical rating scale ranging from 0 to 10. Patients were randomized in a 1:1:1 ratio to 1 of 3 twice-daily treatments: NUCYNTA EXTENDED-RELEASE, oxycodone CR, or placebo.
Following a screening and a wash-out period, patients randomized to NUCYNTA EXTENDED-RELEASE and oxycodone CR initiated the titration period with NUCYNTA EXTENDED-RELEASE 50 mg and oxycodone CR 10 mg twice daily respectively for three days. The dose was increased to NUCYNTA EXTENDED-RELEASE 100 mg b.i.d., oxycodone CR 20 b.i.d., or placebo b.i.d. for the next 4 days. Thereafter, increases in dose were allowed in increments of NUCYNTA EXTENDED-RELEASE 50 mg b.i.d., oxycodone CR 10 mg b.i.d., or placebo for the remaining of the three weeks titration period to achieve a stable optimal dose.
Subsequent titrations in increments of NUCYNTA EXTENDED-RELEASE 50 mg b.i.d., oxycodone CR 10 mg b.i.d. were allowed over a 3-week titration period to a dose of 100 mg to 250 mg twice daily to achieve an optimal therapeutic dose. A 12-week maintenance period followed the titration period with allowed controlled dose adjustments in increments of NUCYNTA EXTENDED-RELEASE 50 mg b.i.d., oxycodone CR 10 mg b.i.d. every three days.
Efficacy was evaluated by comparing the difference in pain intensity from baseline to the last week of the maintenance period between NUCYNTA EXTENDED-RELEASE and placebo, and the difference in pain intensity from baseline to overall maintenance period between NUCYNTA EXTENDED-RELEASE and placebo. The primary efficacy analyses were performed using the last observation carried forward (LOCF) imputation method for missing values.
There were 1030 patients randomized with 1023 patients received study drug. The mean age was 58.3 (range 40 to 91) years; the mean baseline pain intensity score was 7.3 (SD 1.31). Approximately two-thirds of the patients (67.6%) were opioid-naïve (had not taken opioids during the three months prior to the screening visit).
The number of patients completing the study was 61.4% in the placebo group, 57.3% in the NUCYNTA EXTENDED-RELEASE group and 35.4% in the oxycodone CR group. Lack of efficacy was the most common reason for discontinuation among placebo-treated patients (16.7%), whereas adverse events were the most common reason for discontinuation among the active treatment groups (19.2% and 40.0% for NUCYNTA EXTENDED-RELEASE and oxycodone CR, respectively).
Study PAI-3019/KF39 (Nucynta IR and NUCYNTA EXTENDED-RELEASE dose conversion study in low back pain model)
Study PAI-3019/KF39 was a randomized, double-blind, multi-center, 2-period, crossover study to establish the dose equivalence and direct conversion between NUCYNTA IR and NUCYNTA EXTENDED-RELEASE in subjects with moderate to severe Low Back Pain (LBP). Subjects were titrated open label to an optimal dose of NUCYNTA IR (50 mg, 75 mg, or 100 mg every 4 hours or 6 hours, with a maximum total daily dose of 500 mg) for 21 days. This was followed by 2 double-blind fixed dose crossover periods (using the total daily dose given either as NUCYNTA IR or NUCYNTA EXTENDED-RELEASE in the titration phase) each for a 14-day duration. The primary efficacy endpoint, assessed using a non-inferiority test, was the mean average pain intensity score during the last 3 days of each double-blind treatment period, measured twice daily with the 11-point NRS.
A total of 116 subjects were enrolled in the open-label Titration Period, 88 subjects were randomized, 87 subjects were included in the double-blind Safety Analysis Set and 60 subjects were included in the Per-Protocol Analysis Set. For the patients in the open-label Safety Analysis Set, the median age was 53.0 years (range 21 to 88) and the majority of subjects were women (56%), white (77.6%), and under 65 years of age (74.1%). The mean pre-treatment pain intensity, based on the 11-point NRS, at the start of the open-label titration was 7.3. Slightly more than half of the subjects (53.4%) were opioid naïve, they had not taken opioids during the 3 months prior to the screening visit.
Table 8 – Results of studies in Moderate to Severe Chronic Pain (PAI-3011 and PAI-3008)
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control | |||
|---|---|---|---|---|---|
| PAI-3011 (chronic low back pain) | |||||
Change from Baseline to Week 12 of Maintenance | Mean (SD): | -2.9 (2.66) | Mean (SD): | -2.1 (2.33) | |
| LS Mean Change: | -2.9 | LS Mean Change: | -2.1 | ||
| LS Mean Difference versus placebo (SE): | -0.8 (0.19) | ||||
| 95% CI (versus placebo): | [-1.22, -0.47] | ||||
| P-value (versus placebo): | <0.001 | ||||
| PAI-3008 (osteoarthritis) | |||||
Change from Baseline to Week 12 of Maintenance | Mean (SD): | -3.0 (2.39) | Mean (SD): | -2.2 (2.54) | |
| LS Mean Change: | -2.9 | LS Mean Change: | -2.3 | ||
| LS Mean Difference versus placebo (SE): | -0.7 (0.18) | ||||
| 95% CI (versus placebo): | [-1.04, -0.33] | ||||
| P-value (versus placebo): | <0.001 | ||||
Study PAI-3011 (chronic low back pain)
NUCYNTA EXTENDED-RELEASE provided significantly greater analgesia compared to placebo throughout the entire 12-week maintenance period. Results of the primary endpoint using additional imputation methods were consistent with the primary analysis with significant improvement of pain for the NUCYNTA EXTENDED-RELEASE group compared with the placebo group for all imputations methods (BOCF, WOCF, modified BOCF, and PMI).
A significantly higher proportion of NUCYNTA EXTENDED-RELEASE patients had a 30% or 50% reduction in pain score from baseline to the end of Week 12 of the maintenance period compared to placebo (NUCYNTA EXTENDED-RELEASE vs. placebo: 39.7% vs. 27.1% and 27.0% vs. 18.9%, respectively).
Other secondary efficacy points such as, change from baseline to 12-week overall maintenance, BPI, and SF36 are supportive.
Study PAI-3008 (osteoarthritis pain)
NUCYNTA EXTENDED-RELEASE provided significantly greater analgesia compared to placebo throughout the entire 12-week maintenance period.
A significantly higher proportion of NUCYNTA EXTENDED-RELEASE patients had a 50% reduction in pain score from baseline to the end of Week 12 of the maintenance period compared to placebo (NUCYNTA EXTENDED-RELEASE vs. placebo: 32.0% vs. 24.3%).
Other secondary endpoints, such as change from baseline to 12-week overall maintenance, 30% responder data, and WOMAC Health Survey were also supportive of efficacy.
Study PAI-3019/KF39 (Nucynta IR and NUCYNTA EXTENDED-RELEASE dose conversion study in low back pain model)
The total mean pain intensity score decreased from a pre-treatment value of 7.3 to a mean score of 4.2 after 3 weeks of open-label titration (before the start of the double-blind crossover) (n=60, per protocol). The estimated mean average pain intensity score over the last 3 days of treatment from the primary analysis per protocol was 4.0 for the period on NUCYNTA EXTENDED-RELEASE and 3.9 for the period on NUCYNTA IR. The estimated difference in mean primary endpoint values (mean average pain intensity score over the last 3 days of treatment: NUCYNTA EXTENDED-RELEASE to NUCYNTA IR) was 0.1 with a 95% CI of (-0.09, 0.28) which was within the pre-specified margin of non-inferiority (-2, 2). This study demonstrated that patients who have been titrated to a stable daily dose with NUCYNTA IR and have achieved optimal analgesia with acceptable tolerability, can be directly converted to an approximately equivalent total daily dose of NUCYNTA EXTENDED-RELEASE, or vice-versa, if necessary, with equivalent efficacy.
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General Toxicology
Studies were conducted in mice, rats, guinea pigs, rabbits, dogs and monkeys to establish the toxicological profile of tapentadol hydrochloride following administration via different routes. In toxicological studies with tapentadol, the most common systemic effects of tapentadol were related to the mu-opioid receptor agonist and norepinephrine reuptake inhibition pharmacodynamic properties of the compound. Transient, dose-dependent and predominantly CNS-related findings were observed, including impaired respiratory function and convulsions, the latter occurring in the dog at plasma levels (Cmax), which are in the range associated with the maximum recommended human dose (MRHD).
Acute and repeat-dose toxicity studies: In acute toxicity studies in rodents with p.o. and i.v. administration, tapentadol HCl demonstrated a low acute toxicity. LD50 values were clearly above 300 (p.o.) or 40 (i.v.) mg/kg in mice and rats, respectively.
Tapentadol was evaluated in repeat-dose toxicity studies in mice, rats, dogs and monkeys up to a duration of 3, 6 or 12 months or 14 days, respectively. At high doses of tapentadol, transient, dose dependent and predominantly CNS-related findings, e.g., fearfulness, sedation or excited behaviour, recumbency and hunched posture, impaired respiratory function, rarely convulsions, were observed.
In dogs, salivation, vomiting and retching were additionally observed. The CNS- and gastrointestinal symptoms are concordant with the pharmacodynamic effects of MOR agonists. In rats, adaptive changes of the liver were seen. These changes are considered to be related to the xenobiotic overload of hepatocytes due to substantial phase II metabolism and are not regarded as a sign of overt hepatotoxicity. Additionally, there was a lack of relevant tumour formation in the liver in both rodent species (rats and mice) in the 2-year carcinogenicity studies.
In dogs, transient prolongation of the QTc-time was observed in repeat-dose studies. The effects increased with dose and were significant only at the beginning of the studies. No other electrocardiographic findings were observed. Some late toxicity, including convulsions and deaths in rats and dogs occurred in the high dose groups with a delay of several hours following intravenous or oral administration. The cause of these deaths remained unclear, but is regarded as a result of exaggerated pharmacodynamic effects of the compound.
Genotoxicity
Tapentadol did not induce gene mutations in bacteria, but was clastogenic with metabolic activation in a chromosomal aberration test in V79 cells. The test was repeated and was negative in the presence and absence of metabolic activation. The one positive result for tapentadol was not confirmed in vivo in rats, using the two endpoints of chromosomal aberration and unscheduled DNA synthesis, when tested up to the maximum tolerated dose.
Carcinogenicity
Tapentadol was administered to rats (diet) and mice (oral gavage) for two years. In mice, tapentadol HCl was administered by oral gavage at dosages of 50, 100 and 200 mg/kg/day (200 mg/kg/day = maximum tolerated dose in mice) for 2 years. Exposures based on mean plasma Cmax were ~4.9x higher than the maximum recommended human daily dose. Exposure based on dose adjusted for body surface area (based on a 500 mg dose of NUCYNTA EXTENDED-RELEASE to a 50 kg human) was ~1.6x higher in mice than the maximum recommended human daily dose. No increase in tumour incidence was observed at any dose level. In rats, tapentadol HCl was administered in the diet at dosages of 10, 50, 125 and 250 mg/kg/day for two years. Exposure based on dose adjusted for body surface area (based on a 500 mg dose of NUCYNTA EXTENDED-RELEASE to a 50 kg human) was ~4.0x higher in rats than at the maximum recommended human daily dose. Cmax values were not measured in this carcinogenicity study and therefore a direct Cmax exposure multiple cannot be calculated. However, in 3- and 6-month oral gavage toxicity studies, at exposures similar to the AUC exposures in the rat carcinogenicity study, Cmax exposures were on average ~2.5x higher than in humans at the maximum recommended daily dose. No increase in tumour incidence was observed at any dose level.
Reproductive and developmental toxicology:
Impairment of fertility: Tapentadol HCl was administered intravenously to male or female rats at dosages of 3, 6, or 12 mg/kg/day (representing exposures of up to approximately 0.56 times in male rats and 0.50 times in female rats the exposure at the MRHD on an AUC basis, based on extrapolation from toxicokinetic analyses in a separate 4-week intravenous study in rats). Tapentadol did not alter fertility at any dose level. Maternal toxicity and adverse effects on embryonic development, including decreased numbers of implantations, decreased numbers of live conceptuses, and increased pre- and post-implantation losses occurred at dosages ≥6 mg/kg/day.
Developmental studies: Tapentadol HCl was evaluated for teratogenic effects in pregnant rats and rabbits following intravenous and subcutaneous exposure during the period of embryofetal organogenesis. When tapentadol was administered twice daily by the subcutaneous route in rats at dose levels of 10, 20, or 40 mg/kg/day [producing up to 1.36 times the plasma exposure at the maximum recommended human dose (MRHD) of 500 mg/day for NUCYNTA EXTENDED-RELEASE based on an area under the time-curve (AUC) comparison], no teratogenic effects were observed. Evidence of embryofetal toxicity included transient delays in skeletal maturation (i.e., reduced ossification) at the 40 mg/kg/day dose which was associated with significant maternal toxicity. Administration of tapentadol HCl in rabbits at doses of 4, 10, or 24 mg/kg/day by subcutaneous injection [producing up to 2.48 times the plasma exposure at the MRHD based on an AUC comparison] revealed embryofetal toxicity at doses ≥10 mg/kg/day. Findings included reduced fetal viability, skeletal delays and other variations. In addition, there were multiple malformations including gastroschisis/thoracogastroschisis, amelia/phocomelia, and cleft palate at doses ≥10 mg/kg/day and above, and ablepharia, encephalopathy, and spina bifida at the high dose of 24 mg/kg/day. Embryofetal toxicity, including malformations, may be secondary to the significant maternal toxicity observed in the study.
In a study of pre- and postnatal development in rats, oral administration of tapentadol at doses of 20, 50, 150, or 300 mg/kg/day to pregnant and lactating rats during the late gestation and early postnatal period [resulting in up to 2.28 times the plasma exposure at the MRHD on an AUC basis] did not influence physical or reflex development, the outcome of neurobehavioral tests or reproductive parameters. Treatment-related developmental delay was observed, including incomplete ossification, and significant reductions in pup body weights and body weight gains at doses associated with maternal toxicity (150 mg/kg/day and above). At maternal tapentadol doses ≥150 mg/kg/day, a dose-related increase in pup mortality was observed to postnatal Day 4.
Special toxicology:
Dependence and tolerance: Tapentadol is a mu-opioid receptor agonist. The potential to induce drug dependence and the abuse liability of tapentadol was studied in animal models in rats and monkeys. Tapentadol produced physical dependence as shown in an acute (mouse) and a chronic (rat) model. In both cases, however, tapentadol produced fewer withdrawal symptoms than morphine at equi-analgesic doses. In rat models of reward and reinforcement, tapentadol had potency comparable to morphine at equianalgesic doses. Tapentadol produced a conditioned place preference, was intravenously self administered, and generalized to a morphine cue (but not to an amphetamine cue) in a drug discrimination procedure.
Development of tolerance to the analgesic effects of tapentadol was much slower than that of morphine (at equianalgesic doses) in an acute and a chronic pain model in rats.