


Product Monograph - Tridural
RECENT MAJOR LABEL CHANGES
| None | N/A |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics ................................................................................................................. 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 6
4.1 Dosing Considerations ............................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ........................................................ 7
4.4 Administration ........................................................................................................ 8
4.5 Missed Dose ............................................................................................................ 9
5 OVERDOSAGE ............................................................................................................... 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 10
7 WARNINGS AND PRECAUTIONS ................................................................................. 11
7.1 Special Populations................................................................................................ 18
7.1.1 Pregnant Women ............................................................................................ 19
7.1.2 Breast-feeding ................................................................................................. 19
7.1.3 Pediatrics ......................................................................................................... 19
7.1.4 Geriatrics ......................................................................................................... 19
8 ADVERSE REACTIONS ................................................................................................. 20
8.1 Adverse Reaction Overview ................................................................................... 20
8.2 Clinical Trial Adverse Reactions ............................................................................. 20
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 23
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data ............................................................................................................ 24
8.5 Post-Market Adverse Reactions ............................................................................ 25
9 DRUG INTERACTIONS ................................................................................................. 26
9.1 Serious Drug Interactions ...................................................................................... 26
9.2 Drug Interactions Overview ................................................................................... 26
9.3 Drug-Behavioural Interactions ............................................................................... 27
9.4 Drug-Drug Interactions .......................................................................................... 27
9.5 Drug-Food Interactions .......................................................................................... 33
9.6 Drug-Herb Interactions .......................................................................................... 33
9.7 Drug-Laboratory Test Interactions ......................................................................... 33
10 CLINICAL PHARMACOLOGY ........................................................................................ 33
10.1 Mechanism of Action ....................................................................................... 33
10.2 Pharmacodynamics ......................................................................................... 33
10.3 Pharmacokinetics ............................................................................................ 35
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 38
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 39
PART II: SCIENTIFIC INFORMATION ........................................................................................ 40
13 PHARMACEUTICAL INFORMATION ............................................................................. 40
14 CLINICAL TRIALS ......................................................................................................... 41
14.1 Clinical Trials by Indication .............................................................................. 41
15 MICROBIOLOGY ......................................................................................................... 43
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 43
PATIENT MEDICATION INFORMATION ................................................................................... 47
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TRIDURAL (tramadol hydrochloride extended-release tablets) is indicated for the management of moderate to moderately severe pain in adults who require treatment for several days or more.
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (>65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy (see 4.1 Dosing Considerations).
2 CONTRAINDICATIONS
TRIDURAL is contraindicated in patients:
- who are hypersensitive to the active substance tramadol hydrochloride or other opioid analgesics, to any ingredient in the formulation, including any non-medicinal ingredient, or to a component of the container. For a complete listing, see 6 DOSAGE FORMS, COMPOSITION AND PACKAGING.
- in any situation where opioids are contraindicated, including acute intoxication with any of the following: alcohol, hypnotics, centrally acting analgesics, opioids or psychotropic drugs. TRIDURAL may worsen central nervous system and respiratory depression in these patients.
- with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction or strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis).
- with severe renal impairment (creatinine clearance of less than 30 mL/min).
- with severe hepatic impairment (Child-Pugh Class C).
- with mild pain that can be managed with other pain medications.
- with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus.
- with acute respiratory depression, elevated carbon dioxide levels in the blood and cor pulmonale.
- with acute alcoholism, delirium tremens, and convulsive disorders.
- with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury.
- taking monoamine oxidase inhibitors (MAOIs) (or within 14 days of such therapy).
Pediatrics
TRIDURAL is contraindicated in pediatric patients:
- less than 18 years of age who have undergone tonsillectomy and/or adenoidectomy for obstructive sleep apnea syndrome (see 7.1.3 Pediatrics).
- less than 12 years of age.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Limitations of Use
Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, and because of the greater risks of overdose and death with extended-release opioid formulations, TRIDURAL should only be used in patients for whom alternative treatment options are ineffective or not tolerated (e.g., non-opioid analgesics), or would be otherwise inadequate to provide sufficient management of pain (e.g., immediate-release opioids) (see 4.1 Dosing Considerations).
Addiction, Abuse, and Misuse
TRIDURAL poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing TRIDURAL, and all patients should be monitored regularly for the development of these behaviours or conditions (see 7 WARNINGS AND PRECAUTIONS, General, Addiction, Abuse and Misuse). TRIDURAL should be stored securely to avoid theft or misuse.
Life-threatening Respiratory Depression: OVERDOSE
Serious, life-threatening, or fatal respiratory depression may occur with use of TRIDURAL. Infants exposed in-utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of TRIDURAL or following a dose increase.
Administration
TRIDURAL must be swallowed whole; breaking, crushing, chewing, or dissolving TRIDURAL extended-release tablets can cause rapid release and absorption of a potentially fatal dose of tramadol (see 7 WARNINGS AND PRECAUTIONS, General, Addiction, Abuse and Misuse). Further, instruct patients of the hazards related to taking opioids including fatal overdose.
Accidental Exposure
Accidental consumption of even one dose of TRIDURAL, especially by children, can result in a fatal overdose of tramadol (see 11 STORAGE, STABILITY AND DISPOSAL for instructions on proper disposal).
Neonatal Opioid Withdrawal Syndrome
Prolonged maternal use of TRIDURAL during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance, Neonatal Opioid Withdrawal Syndrome).
Interaction with Alcohol
The co-ingestion of alcohol with TRIDURAL may result in increased plasma levels and a potentially fatal overdose of tramadol (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Interactions with Central Nervous System Depressants (Including Benzodiazepines and Alcohol); 9.4 Drug-Drug Interactions).
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants
Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Interactions with Central Nervous System Depressants (Including Benzodiazepines and Alcohol); 9.4 Drug-Drug Interactions).
- Reserve concomitant prescribing of TRIDURAL and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
General
- TRIDURAL should only be used in patients for whom alternative treatment options are ineffective or not tolerated (e.g., non-opioid analgesics), or would be otherwise inadequate to provide sufficient management of pain (e.g., immediate-release opioids).
- All doses of opioids can carry an inherent risk of fatal or non-fatal adverse events. This risk is increased with higher doses. Each patient should be assessed for their risk prior to prescribing TRIDURAL, as the likelihood of experiencing serious adverse events can depend upon the type of opioid, duration of treatment, level of pain as well as the patient’s own level of tolerance. In addition, the level of pain should be assessed routinely to confirm the most appropriate dose and the need for further use of TRIDURAL (see 4.2 Recommended Dose and Dosage Adjustment).
- Due to possible differences in pharmacokinetic properties, TRIDURAL tablets are not interchangeable with other tramadol-containing products.
- Do not co-administer TRIDURAL tablets with other tramadol-containing products.
- TRIDURAL is contraindicated in patients with severe hepatic or renal impairment (see 2 CONTRAINDICATIONS).
- The maximum recommended daily dose of TRIDURAL should not be exceeded.
- TRIDURAL tablets have a continuous release of active ingredient over 24 hours: a repeat dosage within 24 hours is not recommended.
Geriatrics
- In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
Adults: Treatment with TRIDURAL should be initiated at a dose of 100 mg/day. Daily doses should be titrated by 100 mg/day increments every 2 days (i.e., start 200 mg/day on day 3 of therapy) to achieve a balance between adequate pain control and tolerability for the individual patient. For patients requiring the 300 mg daily dose, titration should take at least 4 days (i.e., 300 mg/day on day 5). The daily dose and titration should be individualized for each patient. Therapy should be continued with the lowest effective dose. TRIDURAL should not be administered at a dose exceeding 300 mg per day.
The correct dosage for any individual patient is that which controls the pain for a full 24 hours with no or tolerable side effects.
Consider the benefits and the risks of higher doses as they are associated with an increased risk of adverse events and overdose. The level of pain should be assessed regularly to evaluate the need for further use of TRIDURAL.
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
Geriatrics (>65 years of age): Respiratory depression has occurred in the elderly following administration of large initial doses of opioids to patients who were not opioid-tolerant or when opioids were co-administered with other agents that can depress respiration. TRIDURAL should be initiated at a low dose and slowly titrated to effect (see 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Special Populations, Geriatrics).
TRIDURAL should be administered with greater caution at the lowest effective dose in patients over 75 years, due to the potential for greater frequency of adverse events in this population.
Patients Not Receiving Opioids at the Time of Initiation of Tramadol Hydrochloride Treatment: The usual initial dose of TRIDURAL for patients who have not previously received opioid analgesics is 100 mg q24h.
Patients Currently Receiving Other Tramadol Formulations: Patients currently receiving other oral immediate-release tramadol preparations may be transferred to TRIDURAL tablets at the same or lowest nearest total daily tramadol dosage.
Patients with Hepatic Impairment: TRIDURAL is contraindicated in patients with severe hepatic impairment (see 2 CONTRAINDICATIONS).
The elimination half-life of tramadol and its active metabolite may be prolonged in mild to moderate hepatic disease (see 10.3 Pharmacokinetics, Special Populations, Hepatic Insufficiency). A starting dose of 100 mg daily is recommended, and upward dosage titration should be done with careful monitoring.
Patients with Renal Impairment: TRIDURAL is contraindicated in patients with creatinine clearance less than 30 mL/min (see 2 CONTRAINDICATIONS).
The elimination half-life of tramadol and its active metabolite may be prolonged in mild to moderate renal disease (see 10.3 Pharmacokinetics, Special Populations, Renal Insufficiency). A starting dose of 100 mg daily is recommended, and upward dosage titration should be done with careful monitoring.
Use with Non-Opioid Medications: If rescue medications are warranted for episodes of pain in the course of appropriate adjustments of TRIDURAL dose, acetaminophen or ibuprofen may be given. If immediate release tramadol is used as rescue medication, the total daily dose of tramadol should not exceed 300 mg. Selection of rescue medication should be based on individual patient conditions. Fentanyl products should not be used as rescue medication in patients taking TRIDURAL.
If a non-opioid analgesic is being provided, it may be continued. If the non-opioid analgesic is discontinued, consideration should be given to increasing the opioid dose to compensate for the non-opioid analgesic. TRIDURAL can be safely used concomitantly with usual doses of other non-opioid analgesics.
Dosage Adjustment
Dosage adjustments should be based on the patient's clinical response.
Dose Titration: Dose titration is the key to success with opioid analgesic therapy. Proper optimization of doses scaled to the relief of the individual's pain should aim at administration of the lowest dose which will achieve the overall treatment goal of satisfactory pain relief with acceptable side effects. Studies with tramadol products in adults have shown that starting at the lowest possible dose and titrating upward will result in fewer discontinuations and increased tolerability.
Adjustment or Reduction of Dosage: Physical dependence with or without psychological dependence tends to occur with chronic administration of opioids, including TRIDURAL. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. These symptoms may include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, pain, rigors, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, upper respiratory symptoms, weakness, yawning and rarely, hallucinations.
Other symptoms that have been seen less frequently with tramadol discontinuation include: panic attacks, severe anxiety, and paresthesias.
Following successful relief of moderate to moderately severe pain, periodic attempts to reduce the opioid dose should be made. Smaller doses or complete discontinuation may become feasible due to a change in the patient’s condition or mental state. Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer required for pain control. In patients who are appropriately treated with opioid analgesics and who undergo gradual withdrawal for the drug, these symptoms are usually mild (see 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance). Tapering should be carried out under medical supervision.
Patient should be informed that reducing and/or discontinuing opioids decreases their tolerance to these drugs. If treatment needs to be re-initiated, the patient must start at the lowest dose and titrate up to avoid overdose.
Opioid analgesics may only be partially effective in relieving dysesthetic pain, postherpetic neuralgia, stabbing pains, activity-related pain and some forms of headache. That is not to say that patients with advanced cancer suffering from some of these forms of pain should not be given an adequate trial of opioid analgesics, but it may be necessary to refer such patients at an early time to other forms of pain therapy.
4.4 Administration
TRIDURAL extended-release tablets should be taken once a day at breakfast. The tablets should be swallowed whole with liquid.
TRIDURAL should be swallowed whole; breaking, crushing, chewing, or dissolving TRIDURAL extended-release tablet can cause rapid release and absorption of a potentially fatal dose of tramadol (see 7 WARNINGS AND PRECAUTIONS, General, Addiction, Abuse and Misuse).
TRIDURAL is not indicated for rectal administration.
4.5 Missed Dose
If the patient forgets to take one or more doses, they should skip the missed dose(s) and take their next dose as scheduled and in the normal amount.
5 OVERDOSAGE
Deaths due to overdose have been reported with abuse and misuse of tramadol, by ingesting, inhaling, or injecting the crushed tablets. Review of case reports has indicated that the risk of fatal overdose is further increased when tramadol is abused concurrently with alcohol or other CNS depressants, including other opioids.
Symptoms of Overdose
Acute overdosage with tramadol can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, bradycardia, toxic leukoencephalopathy, delayed post-hypoxic leukoencephalopathy, hypotension, and death. Also, it has been reported that serotonin syndrome can occur in a context of overdose with tramadol. In addition, cases of QT prolongation have been reported during overdose with tramadol.
Treatment of Overdose
A single or multiple overdose with TRIDURAL may be a potentially lethal drug overdose, and consultation with a regional poison control centre is recommended.
In treating an overdose, primary attention should be given to maintaining adequate ventilation along with general supportive treatment. Supportive measures (including oxygen and vasopressors) should be employed in the management of circulatory shock and pulmonary edema accompanying overdose as indicated. Cardiac arrest or arrhythmias may require cardiac massage or defibrillation.
While naloxone will reverse some, but not all, symptoms caused by overdosage with tramadol, the risk of seizures is also increased with naloxone administration. In animals, convulsions following the administration of toxic doses of tramadol could be suppressed with barbiturates or benzodiazepines but were increased with naloxone. Naloxone administration did not change the lethality of an overdose in mice.
Hemodialysis is not expected to be helpful in an overdose because it removes less than 7% of the administered dose in a 4-hour dialysis period.
Emptying of the gastric contents may be useful to remove any unabsorbed drug.
With regard to serotonin syndrome, withdrawal of serotonergic drugs usually brings about a rapid improvement. Treatment depends on the type and severity of the symptoms.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
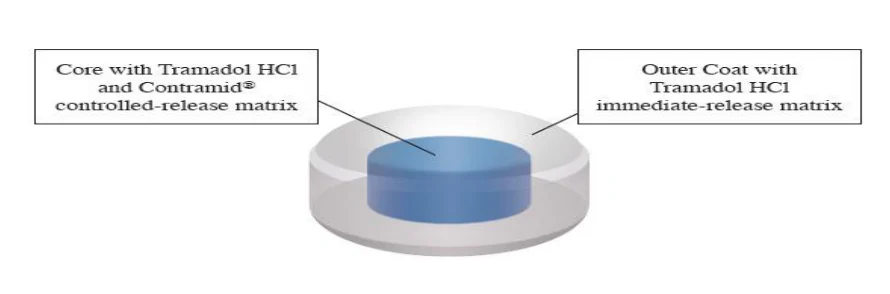
TRIDURAL tablets are comprised of a dual-matrix delivery system with an outer compression coat (containing tramadol hydrochloride) providing immediate release characteristics and a controlled-release core containing tramadol hydrochloride and Contramid®, which provides the controlled-release characteristics (Figure 1).
Figure 1. Tablet Showing the Immediate Release Matrix (lighter outer part) and the Extended Release Matrix (dark inner part)
TRIDURAL (tramadol hydrochloride) extended-release tablets are supplied in a number of packages and dose strengths:
100-mg, white, beveled edge, round biconvex tablets, plain on one side and printed “LP 100” in black ink on the other side.
- Bottle of 4 tablets
- Bottle of 30 tablets
- Bottle of 90 tablets
- Bottle of 100 tablets
- Bottle of 500 tablets
200-mg, white, beveled edge, round biconvex tablets, plain on one side and printed “LP 200” in black ink on the other side.
- Bottle of 4 tablets
- Bottle of 30 tablets
- Bottle of 90 tablets
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Extended-release tablets 100 mg, 200 mg, 300 mg Tramadol, as tramadol hydrochloride | Ammonium hydroxide, colloidal silicon dioxide, Contramid® (modified starch), hydrogenated vegetable oil, iron oxide black, isopropyl alcohol, magnesium stearate, n-butyl alcohol, polyvinyl acetate, povidone, propylene glycol, shellac glaze, sodium lauryl sulfate, xanthan gum |
- Bottle of 100 tablets
- Bottle of 500 tablets
300-mg, white, beveled edge, round biconvex tablets, plain on one side and printed “LP 300” in black ink on the other side.
- Bottle of 30 tablets
- Bottle of 90 tablets
- Bottle of 100 tablets
- Bottle of 500 tablets
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Patients should be instructed not to give TRIDURAL extended-release tablets to anyone other than the patient for whom it was prescribed, as such inappropriate use may have severe medical consequences, including death. TRIDURAL should be stored securely to avoid theft or misuse.
TRIDURAL should only be prescribed by persons knowledgeable in the continuous administration of potent opioids, in the management of patients receiving potent opioids for the treatment of pain, and in the detection and management of respiratory depression, including the use of opioid antagonists.
Patients should be cautioned not to consume alcohol while taking TRIDURAL as it may increase the chance of experiencing serious adverse events, including death.
Hyperalgesia that will not respond to a further dose increase of tramadol hydrochloride can occur at particularly high doses. A tramadol hydrochloride dose reduction or change in opioid may be required.
Addiction, Abuse and Misuse: Like all opioids, TRIDURAL is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, TRIDURAL should be prescribed and handled with caution.
Patients should be assessed for their clinical risks for opioid abuse or addiction prior to being prescribed opioids. All patients receiving opioids should be routinely monitored for signs of misuse and abuse.
Proper assessment of the patient, proper prescribing practices, periodic re-evaluation of therapy, and proper dispensing and storage are appropriate measures that help to limit abuse of opioid drugs.
Opioids, such as TRIDURAL, should be used with particular care in patients with a history of alcohol and illicit/prescription drug abuse. However, concerns about abuse, addiction, and diversion should not prevent the proper management of pain.
In addition, abuse of opioids can occur in the absence of true addiction and is characterized by misuse for non-medical purposes, often in combination with other psychoactive substances.
The development of addiction to opioid analgesics in properly managed patients with pain has been reported to be rare. However, data are not available to establish the true incidence of addiction in chronic pain patients.
TRIDURAL is intended for oral use only. The tablets should be swallowed whole, and not chewed or crushed. Abuse of oral dosage forms can be expected to result in serious adverse events, including death.
These practices will result in the uncontrolled delivery of the opioid and pose a significant risk to the abuser that could result in overdose and death. This risk is increased with concurrent abuse of alcohol and other substances. With parenteral abuse, the tablet excipients can be expected to result in local tissue necrosis, infection, pulmonary granulomas, and increased risk of endocarditis and valvular heart injury.
Risk of Overdosage: Serious potential consequences of overdosage with TRIDURAL are central nervous system depression, respiratory depression and death. In treating an overdose, primary attention should be given to maintaining adequate ventilation along with general supportive treatment (see 5 OVERDOSAGE).
Do not prescribe TRIDURAL for patients who are suicidal or addiction-prone.
TRIDURAL should not be taken in doses higher than those recommended by the physician. The judicious prescribing of tramadol is essential to the safe use of this drug. With patients who are depressed or suicidal, consideration should be given to the use of non-narcotic analgesics. Patients should be cautioned about the concomitant use of tramadol products and alcohol because of potentially serious CNS-additive effects of these agents. Because of its added depressant effects, tramadol should be prescribed with caution for those patients whose medical condition requires the concomitant administration of sedatives, tranquilizers, muscle relaxants, antidepressants, or other CNS-depressant drugs. Patients should be advised of the additive depressant effects of these combinations.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY section.
Cardiovascular
Hypotension: Tramadol hydrochloride administration may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by reduced blood volume, or concurrent administration of drugs such as phenothiazines and other tranquilizers, sedative/hypnotics, tricyclic antidepressants or general anesthetics. These patients should be monitored for signs of hypotension after initiating or titrating the dose of TRIDURAL.
The use of TRIDURAL in patients with circulatory shock should be avoided as it may cause vasodilation that can further reduce cardiac output and blood pressure.
QTc Interval Prolongation: The effect of tramadol on the QT/QTc interval were evaluated in a dedicated randomized, double-blind, 4-way crossover, placebo- and positive-controlled, multiple dose ECG study in healthy subjects (N=62). The study involved administration of tramadol at a supra-therapeutic dose of 100 mg every 6 h on days 1-3 (400 mg/day), with a single 100 mg dose on day 4, or 150 mg every 6 h (600 mg/day) on days 1-3, with a single 150 mg dose on day 4. The maximum placebo-adjusted mean change from baseline in the QTcF interval was 5.5 ms (90% CI 3.2, 7.8) in the 400 mg/day treatment arm and 6.5 ms (90% CI 4.1, 8.8) in the 600 mg/day mg treatment arm, both occurring at the 8h time point (see 10.2 Pharmacodynamics, Cardiac Electrophysiology). Post-marketing experience with the use of tramadol containing products included rare reports of QT prolongation reported with an overdose (see 8.5 Post-Market Adverse Reactions; 9.4 Drug-Drug Interactions; 5 OVERDOSAGE).
Many drugs that cause QTc prolongation are suspected to increase the risk of torsade de pointes. Torsade de pointes is a polymorphic ventricular tachyarrhythmia. Generally, the risk of torsade de pointes increases with the magnitude of QTc prolongation produced by the drug. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
Particular care should be exercised when administering TRIDURAL to patients who are suspected to be at an increased risk of experiencing torsade de pointes during treatment with a QTc-prolonging drug.
Risk factors for torsade de pointes in the general population included, but are not limited to the following:
- female gender;
- age 65 years or older;
- baseline prolongation of the QT/QTc interval;
- presence of pathological genetic variants affecting cardiac ion channels or regulatory proteins, especially congenital long QT syndromes;
- family history of sudden cardiac death at <50 years;
- cardiac disease (e.g., myocardial ischemia or infarction, congestive heart failure, left ventricular hypertrophy, cardiomyopathy, conduction system disease);
- history of arrhythmias (especially ventricular arrhythmias, atrial fibrillation, or recent conversion from atrial fibrillation);
- electrolyte disturbances (e.g., hypokalemia, hypomagnesemia, hypocalcemia);
- bradycardia (<50 beats per minute);
- acute neurological events (e.g., intracranial or subarachnoid haemorrhage, stroke, intracranial trauma);
- nutritional deficits (e.g., eating disorders, extreme diets);
- diabetes mellitus;
- autonomic neuropathy.
When drugs that prolong the QTc interval are prescribed, healthcare professionals should inform their patients of the nature and implications of the ECG changes, underlying diseases and disorders that may be risk factors. Healthcare professionals should also inform their patients of demonstrated and predicted drug-drug interactions, symptoms suggestive of arrhythmia, risk management strategies, and other information relevant to the use of the drug.
Dependence/Tolerance
As with other opioids, tolerance and physical dependence may develop upon repeated administration of TRIDURAL and there is a potential for development of psychological dependence.
The drug has been associated with craving, drug-seeking behaviour and tolerance development. Cases of abuse and dependence on tramadol have been reported. TRIDURAL should not be used in opioid-dependent patients. Tramadol has been shown to reinitiate physical dependence in some patients that have been previously dependent on other opioids. Dependence and abuse, including drug-seeking behaviour and taking illicit actions to obtain the drug, are not limited to those patients with prior history of opioid dependence. In patients with a tendency to abuse drugs or a history of drug dependence, and in patients who are chronically abusing opioids, treatment with TRIDURAL is not recommended.
Physical dependence and tolerance reflect the neuroadaptation of the opiate receptors to chronic exposure to an opiate, and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
Use in Drug and Alcohol Addiction: TRIDURAL is an opioid with no approved use in the management of addictive disorders. Its proper usage in individuals with drug or alcohol dependence, either active or in remission is for the management of pain requiring opioid analgesia. Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to TRIDURAL unless used under extreme caution and awareness.
In Vitro Dissolution Studies of Interaction with Alcohol: Increasing concentrations of ethanol resulted in a decrease in the rate of release of TRIDURAL tablets.
Withdrawal Symptoms: Patients on prolonged therapy should be tapered gradually from the drug if it is no longer required for pain control. Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, pain, rigors, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, upper respiratory symptoms, palpitations, unexplained fever, weakness, yawning and rarely hallucination (see 8.5 Post-Market Adverse Reactions, 4.2 Recommended Dose and Dosage Adjustment).
TRIDURAL should not be used to treat the symptoms of opioid withdrawal in opioid-dependent patients since it cannot suppress morphine withdrawal symptoms, even though it is an opioid agonist.
Neonatal Opioid Withdrawal Syndrome (NOWS): Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn.
Driving and Operating Machinery
TRIDURAL may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery. Patients should be cautioned accordingly. Patients should also be cautioned about the combined effects of tramadol hydrochloride with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol.
Endocrine and Metabolism
Adrenal Insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency.
Hyponatremia: Hyponatremia has been reported very rarely with the use of tramadol, usually in patients with predisposing risk factors, such as elderly patients and/or patients using concomitant medications that may cause hyponatremia (e.g., antidepressants, benzodiazepines, diuretics). In some reports, hyponatremia appeared to be the result of the syndrome of inappropriate antidiuretic hormone secretion (SIADH) and resolved with discontinuation of tramadol and appropriate treatment (e.g., fluid restriction). During TRIDURAL treatment, monitoring for signs and symptoms of hyponatremia is recommended for patients with predisposing risk factors.
Use in Diabetic Patients: TRIDURAL should be used with caution in diabetic patients due to the occurrence of hypoglycemia with tramadol.
Gastrointestinal
Acute Abdominal Conditions: TRIDURAL is contraindicated in patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction or strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type). Tramadol and other morphine-like opioids have been shown to decrease bowel motility. Tramadol may obscure the diagnosis or clinical course of patients with acute abdominal conditions (see 2 CONTRAINDICATIONS).
Hepatic/Biliary/Pancreatic
Metabolism of tramadol and M1 is reduced in patients with advanced cirrhosis of the liver, resulting in both a larger area under the concentration time curve for tramadol and longer tramadol and M1 elimination half-lives (13 hours for tramadol and 19 hours for M1). TRIDURAL is contraindicated in patients with severe hepatic impairment (see 2 CONTRAINDICATIONS; 4.1 Dosing Considerations).
Immune
Anaphylactoid Reactions: Serious and rarely fatal anaphylactoid reactions have been reported in patients receiving therapy with tramadol. When these events do occur, it is often following the first dose. Other reported allergic reactions include pruritus, hives, bronchospasm, angioedema, toxic epidermal necrolysis and Stevens-Johnson syndrome. Patients with a history of anaphylactoid reactions to codeine and other opioids may be at increased risk and therefore should not receive TRIDURAL (see 2 CONTRAINDICATIONS).
Neurologic
Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol): TRIDURAL should be used with caution and in a reduced dosage during concomitant administration of other opioid analgesics, general anesthetics, phenothiazines and other tranquilizers, sedative-hypnotics, tricyclic antidepressants, antipsychotics, antihistamines, benzodiazepines, centrally-active anti-emetics and other CNS depressants. Respiratory depression, hypotension and profound sedation, coma or death may result.
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with opioid analgesics (see 9.4 Drug-Drug Interactions). If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation.
Advise both patients and caregivers about the risks of respiratory depression and sedation when TRIDURAL is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the benzodiazepine or other CNS depressant have been determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk of overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs (see 9.4 Drug-Drug Interactions).
TRIDURAL should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects, including death (see 2 CONTRAINDICATIONS; 8.1 Adverse Reaction Overview, Sedation; 9.4 Drug-Drug Interactions).
Severe pain antagonizes the subjective and respiratory depressant actions of opioid analgesics. Should pain suddenly subside, these effects may rapidly become manifest.
Head Injury: The respiratory depressant effects of tramadol, and the capacity to elevate cerebrospinal fluid pressure, may be greatly increased in the presence of an already elevated intracranial pressure produced by trauma. Also, tramadol may produce confusion, miosis, vomiting and other side effects which obscure the clinical course of patients with head injury. In such patients, tramadol hydrochloride must be used with extreme caution and only if it is judged essential (see 2 CONTRAINDICATIONS).
Opioid Induced Hyperalgesia: Opioid induced hyperalgesia (OIH) is a paradoxical response to an opioid in which there is an increase in pain perception despite stable or increased opioid exposure. It differs from tolerance, in which higher opioid doses are required to achieve the same analgesic effect or treat recurring pain. Clinically, OIH may be associated with high opioid doses, long term opioid treatment, and intra-operative opioid use. OIH may manifest as an unexplained increase in pain, more diffuse pain than pre-existing, or as pain from ordinary (i.e. non-painful) stimuli (allodynia) in the absence of disease progression. When OIH is suspected, the dose of opioid should be reduced or tapered off, if possible. It is reasonable to consider opioid rotation, or the use of a non-opioid strategy for pain control. There is currently no well-established treatment for OIH.
Seizure Risk: Seizures have been reported in patients receiving tramadol hydrochloride within the recommended dosage range. Spontaneous postmarketing reports indicate that seizure risk is increased with doses above the recommended range. Concomitant use of tramadol hydrochloride increases the seizure risk in patients taking:
- selective serotonin reuptake inhibitors (SSRI antidepressants or anorectics),
- serotonin-norepinephrine reuptake inhibitors (SNRIs),
- tricyclic antidepressants (TCAs), and other tricyclic compounds (e.g., cyclobenzaprine, promethazine, etc.) or,
- other opioids.
Administration of tramadol may enhance the seizure risk in patients taking:
- MAOIs (see 2 CONTRAINDICATIONS),
- antipsychotics,
- neuroleptics,
- other drugs that reduce the seizure threshold (such as bupropion, mirtazapine, tetrahydrocannabinol).
Risk of convulsions may also increase in patients with epilepsy, those with a history of seizures, or in patients with a recognized risk for seizure (such as head trauma, metabolic disorders, alcohol and drug withdrawal, CNS infections). In tramadol overdose, naloxone administration may increase the risk of seizures.
Serotonin Toxicity / Serotonin Syndrome: Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported with tramadol hydrochloride, including
TRIDURAL, particularly during combined use with other serotonergic drugs (see 9.4 Drug-Drug Interactions).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with TRIDURAL and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Peri-Operative Considerations
TRIDURAL is not recommended for obstetrical preoperative medication or for post-delivery analgesia in nursing mothers because its safety in infants and newborns has not been studied. (see 7.1.2 Breast-Feeding).
Renal
Impaired renal function results in a decreased rate and extent of excretion of tramadol and its active metabolite, M1. TRIDURAL is contraindicated in severe renal impairment. The total amount of tramadol and M1 removed during a 4-hour dialysis period is less than 7% of the administered dose (see 2 CONTRAINDICATIONS; 4.1 Dosing Considerations).
Reproductive Health: Female and Male Potential
See 7.1.1 Pregnant Women.
Fertility
Animal data with tramadol did not show an alteration of fertility at any dose level (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Function
Long-term use of opioids may be associated with decreased sex hormone levels and symptoms such as low libido, erectile dysfunction, or infertility (see 8.5 Post-Market Adverse Reactions).
- Teratogenic Risk
Animal data with tramadol did not show teratogenicity at any dose level (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Respiratory
Respiratory Depression: Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient’s clinical status. Tramadol should be used with extreme caution in patients with substantially decreased respiratory reserve, pre-existing respiratory depression, hypoxia or hypercapnia (see 2 CONTRAINDICATIONS).
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of TRIDURAL, the risk is greatest during the initiation of therapy or following a dose increase. Patients should be closely monitored for respiratory depression when initiating therapy with TRIDURAL and following dose increases.
Life-threatening respiratory depression is more likely to occur in the elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients.
To reduce the risk of respiratory depression, proper dosing and titration of TRIDURAL are essential. Overestimating the TRIDURAL dose when converting patients from another opioid product can result in fatal overdose with the first dose. In these patients, the use of non-opioid analgesics should be considered, if feasible (see 7.1 Special Populations, Special Risk Groups; 4.2 Recommended Dose and Dosage Adjustment).
Sleep Apnea: Opioids can cause sleep-related breathing disorders such as sleep apnea syndromes (including central sleep apnea [CSA]) and hypoxia (including sleep-related hypoxia). Opioid use increases the risk of CSA in a dose-dependent fashion. Evaluate patients on an ongoing basis for the onset of a new sleep apnea, or a worsening of an existing sleep apnea. In these patients, consider reducing or stopping the opioid treatment if appropriate, using best practices for tapering of opioids (see 4.2 Recommended Dose and Dosage Adjustment; 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance, Withdrawal Symptoms).
Cytochromes P450 (CYP) 2D6 Ultra-Rapid Metabolism: Some individuals may be CYP2D6 ultra-rapid metabolizers. These individuals convert tramadol more rapidly than other people into its more potent opioid metabolite O-desmethyltramadol (M1). This rapid conversion could result in higher than expected opioid-like side effects including life-threatening respiratory depression (see 7.1.2 Breast-Feeding; 9.2 Drug Interaction Overview). The prevalence of this CYP2D6 phenotype varies widely in the population (see 10.3 Pharmacokinetics, Special Populations and Conditions, Ethnic Origin).
Use in Patients with Chronic Pulmonary Disease: Monitor patients with significant chronic obstructive pulmonary disease or cor pulmonale, and patients having a substantially decreased respiratory reserve, hypoxia, hypercapnia, or preexisting respiratory depression for respiratory depression, particularly when initiating therapy and titrating with TRIDURAL, as in these patients, even usual therapeutic doses of TRIDURAL may decrease respiratory drive to the point of apnea. In these patients, use of alternative non-opioid analgesics should be considered, if possible. The use of TRIDURAL is contraindicated in patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus (see 2 CONTRAINDICATIONS).
7.1 Special Populations
Special Risk Groups: Tramadol should be administered with caution to patients with a history of alcohol and drug abuse and in a reduced dosage to debilitated patients, and in patients with severely impaired pulmonary function, Addison’s disease, hypothyroidism, myxedema, toxic psychosis, prostatic hypertrophy or urethral stricture.
7.1.1 Pregnant Women
Studies in pregnant women have not been conducted. TRIDURAL crosses the placental barrier and should not be administered to pregnant women unless in the judgment of the physician, the potential benefits outweigh the potential risks.
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal Opioid Withdrawal Syndrome (NOWS), unlike opioid withdrawal syndrome in adults, can be life-threatening (see 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance, Neonatal Opioid Withdrawal Syndrome).
Neonatal seizures, neonatal withdrawal syndrome, fetal death and stillbirth have been reported with tramadol during post-marketing. The effect of tramadol, if any, on the later growth, development and functional maturation of the child is unknown.
Pregnant women using opioids should not discontinue their medication abruptly as this can cause pregnancy complication such as miscarriage or still-birth. Tapering should be slow and under medical supervision to avoid serious adverse events to the fetus.
7.1.2 Breast-feeding
Since opioids can cross the placental barrier and are excreted in breast milk, TRIDURAL should not be used in nursing women and during labour and delivery unless, in the judgment of the physician, the potential benefits outweigh the risks. Life-threatening respiratory depression can occur in the infant if opioids are administered to the mother. Naloxone, a drug that counters the effects of opioids, should be readily available if TRIDURAL is used in this population.
7.1.3 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. Further, adolescent patients (12 to 18 years old) who are obese or have conditions such as obstructive sleep apnea or severe lung disease may be at increased risk of serious breathing problems; the use of TRIDURAL is not recommended in these pediatrics patients.
7.1.4 Geriatrics
Geriatrics (>65 years of age): In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range and titrate slowly, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see 4.1 Dosing Considerations; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
The elimination half-life of tramadol may be prolonged in patients over 75 years, thereby increasing the potential for adverse events.
TRIDURAL should also be used with caution in elderly patients due to the risk of loss of consciousness and falls.
In clinical trials, TRIDURAL was administered to 1013 patients aged 65 years and older. Of those, 89 patients were 75 years of age and older. Comparable incidence rates of patients experiencing adverse events were observed for patients older than 65 years of age compared with younger patients (< 65 years of age), except constipation for which the incidence was higher in older patients. TRIDURAL should be used with caution in patients older than 75 years of age (see 4.1 Dosing Considerations; 10. 3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse effects of TRIDURAL are similar to those of other opioid analgesics, and represent an extension of pharmacological effects of the drug class. The major hazards of opioids include respiratory and central nervous system depression and to a lesser degree, circulatory depression, respiratory arrest, shock and cardiac arrest.
The most frequently observed adverse effects of TRIDURAL are constipation, nausea, vomiting, dizziness, headache, somnolence and pruritus.
Sedation: Sedation is a common side effect of opioid analgesics, especially in opioid naïve individuals. Sedation may also occur partly because patients often recuperate from prolonged fatigue after the relief of persistent pain. Most patients develop tolerance to the sedative effects of opioids within three to five days and, if the sedation is not severe, will not require any treatment except reassurance. If excessive sedation persists beyond a few days, the dose of the opioid should be reduced and alternate causes investigated. Some of these are: concurrent CNS depressant medication, hepatic or renal dysfunction, brain metastases, hypercalcemia and respiratory failure. If it is necessary to reduce the dose, it can be carefully increased again after three or four days if it is obvious that the pain is not being well controlled. Dizziness and unsteadiness may be caused by postural hypotension, particularly in elderly or debilitated patients, and may be alleviated if the patient lies down.
Nausea and Vomiting: Nausea is a common side effect on initiation of therapy with opioid analgesics and is thought to occur by activation of the chemoreceptor trigger zone, stimulation of the vestibular apparatus and through delayed gastric emptying. The prevalence of nausea declines following continued treatment with opioid analgesics. When instituting therapy with an opioid for chronic pain, the routine prescription of an antiemetic should be considered. In the cancer patient, investigation of nausea should include such causes as constipation, bowel obstruction, uremia, hypercalcemia, hepatomegaly, tumor invasion of celiac plexus and concurrent use of drugs with emetogenic properties. Persistent nausea which does not respond to dosage reduction may be caused by opioid-induced gastric stasis and may be accompanied by other symptoms including anorexia, early satiety, vomiting and abdominal fullness. These symptoms respond to chronic treatment with gastrointestinal prokinetic agents.
Constipation: Practically all patients become constipated while taking opioids on a persistent basis. In some patients, particularly the elderly or bedridden, fecal impaction may result. It is essential to caution the patients in this regard and to institute an appropriate regimen of bowel management at the start of prolonged opioid therapy. Stimulant laxatives, stool softeners, and other appropriate measures should be used as required. As fecal impaction may present as overflow diarrhea, the presence of constipation should be excluded in patients on opioid therapy prior to initiating treatment for diarrhea.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
TRIDURAL was administered to a total of 2707 subjects (2406 patients and 301 healthy volunteers) during clinical studies, including four randomized double-blind studies (treatment ≥ 12 weeks) and two open-label long-term studies (treatment up to 12 months) in patients with moderate to severe pain due to osteoarthritis of the knee. A total of 1901 patients were exposed to TRIDURAL during 12-week studies, 493 for a 6-month period and 243 for a 12-month period. A total of 1013 patients were 65 years and older, including 89 patients 75 years of age and older. A summary of adverse events occurring at an incidence of 1% or more is given in Table 2, which includes all events, whether considered by the clinical investigator to be related to the study drug or not.
Table 2 – Percentage of Patients with Incidence of Adverse Events ≥ 1% from Three 12-week Placebo-Controlled Studies (MDT3-002, MDT3-003 and MDT3-005)
| TRIDURAL | Placebo n = 668 (%) | |||||||||||||
| TRIDURAL | Placebo n = 668 (%) | |||||||||||||
100 mg n = 216 (%) | 200 mg n = 311 (%) | 300 mg n = 530 (%) | Total n = 1095 (%) | |||||||||||
100 mg n = 216 (%) | 200 mg n = 311 (%) | 300 mg n = 530 (%) | Total n = 1095 (%) | |||||||||||
| Any TEAE | 125 (57.9%) | 184 (59.2%) | 302 (57.0%) | 690 (63.0%) | 338 (50.6%) | |||||||||
Ear and labyrinth disorders Vertigo | 3 (1.4%) | 3 (1.0%) | 8 (1.5%) | 27 (2.5%) | 3 (0.4%) | |||||||||
Gastrointestinal disorders Abdominal pain Abdominal pain upper Constipation Diarrhea Dry mouth Dyspepsia Nausea Vomiting | 2 (0.9%) 3 (1.4%) 21 (9.7%) 6 (2.8%) 7 (3.2%) 3 (1.4%) 29 (13.4%) 8 (3.7%) | 5 (1.6%) 4 (1.3%) 38 (12.2%) 1 (0.3%) 17 (5.5%) 6 (1.9%) 50 (16.1%) 19 (6.1%) | 8 (1.5%) 9 (1.7%) 53 (10.0%) 10 (1.9%) 7 (1.3%) 4 (0.8%) 88 (16.6%) 36 (6.8%) | 17 (1.6%) 18 (1.6%) 143 (13.1%) 21 (1.9%) 38 (3.5%) 13 (1.2%) 202 (18.4%) 71 (6.5%) | 7 (1.0%) 4 (0.6%) 27 (4.0%) 20 (3.0%) 8 (1.2%) 7 (1.0%) 39 (5.8%) 6 (0.9%) | |||||||||
General disorders and administration site conditions Fatigue Pain exacerbated Weakness | 6 (2.8%) 6 (2.8%) 3 (1.4%) | 10 (3.2%) 3 (1.0%) 5 (1.6%) | 9 (1.7%) 6 (1.1%) 4 (0.8%) | 29 (2.6%) 18 (1.6%) 12 (1.1%) | 6 (0.9%) 16 (2.4%) 1 (0.1%) | |||||||||
Infections and infestations Influenza Nasopharyngitis Upper respiratory tract infection Urinary tract infection | 2 (0.9%) 4 (1.9%) 3 (1.4%) 2 (0.9%) | 1 (0.3%) 7 (2.3%) 5 (1.6%) 3 (1.0%) | 8 (1.5%) 7 (1.3%) 6 (1.1%) 6 (1.1%) | 11 (1.0%) 20 (1.8%) 16 (1.5%) 12 (1.1%) | 3 (0.4%) 18 (2.7%) 17 (2.5%) 10 (1.5%) | |||||||||
Investigations Weight decreased | 1 (0.5%) | 5 (1.6%) | 11 (2.1%) | 20 (1.8%) | 1 (0.1%) | |||||||||
Metabolism and nutrition disorders Anorexia | 5 (2.3%) | 4 (1.3%) | 11 (2.1%) | 27 (2.5%) | 2 (0.3%) | |||||||||
Musculoskeletal and connective tissue disorders Arthralgia | 2 (0.9%) | 3 (1.0%) | 8 (1.5%) | 15 (1.4%) | 14 (2.1%) | |||||||||
Nervous system disorders Dizziness Headache Somnolence Tremor | 18 (8.3%) 13 (6.0%) 12 (5.6%) 1 (0.5%) | 31 (10.0%) 18 (5.8%) 23 (7.4%) 3 (1.0%) | 59 (11.1%) 26 (4.9%) 26 (4.9%) 6 (1.1%) | 119 (10.9%) 64 (5.8%) 82 (7.5%) 11 (1.0%) | 21 (3.1%) 43 (6.4%) 13 (1.9%) 1 (0.1%) | |||||||||
Psychiatric disorders Anxiety NEC Insomnia | 1 (0.5%) 3 (0.4%) | 6 (1.9%) 9 (2.9%) | 4 (0.8%) 11 (2.1%) | 11 (1.0%) 25 (2.3%) | 1 (0.1%) 8 (1.2%) | |||||||||
Skin and subcutaneous tissue disorders Pruritus Sweating increased | 11 (5.1%) 1 (0.5%) | 16 (5.1%) 10 (3.2%) | 23 (4.3%) 16 (3.0%) | 60 (5.5%) 38 (3.5%) | 7 (1.0%) 6 (0.9%) | |||||||||
Vascular disorders Hot flushes | 1 (0.5%) | 3 (1.0%) | 7 (1.3%) | 12 (1.1%) | 1 (0.1%) | |||||||||
Note: Due to the difference in study design of MDT3-005, only the results of the double-blind phase of the study are presented and the dose specific results include maintenance period data only.
The majority of patients who experienced the most common adverse events (≥1%) reported mild to moderate symptoms. Less than 3% of adverse events were rated as severe. Overall, onset of these adverse events usually occurred within the first two weeks of treatment.
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse effects occur less frequently (<1%) with opioid analgesics and include those reported in TRIDURAL clinical trials, whether related or not to tramadol hydrochloride.
Blood and lymphatic system disorders: anaemia, lymphadenopathy, thrombocytopenia.
Cardiovascular: acute myocardial infarction, angina pectoris, angina unstable, atrial fibrillation, bradycardia, cardiovascular disorder, palpitations, sinus tachycardia, tachycardia.
Ear and labyrinth disorders: cerumen impaction, ear congestion, ear discomfort, ear pain, labyrinthitis, tinnitus.
Endocrine disorders: hypothyroidism.
Eye disorders: cataract, dry eyes, eye pain, eyelid disorder, lacrimation increased, photopsia, scleral haemorrhage, blurred vision, visual disturbance.
Gastrointestinal disorders: abdominal discomfort, abdominal distension, lower abdominal pain, abdominal tenderness, change in bowel habit, constipation aggravated, diverticulitis, dyspepsia aggravated, dysphagia, faecal impaction, feces discoloured, flatulence, food poisoning, gastric irritation, gastritis, gastrointestinal haemorrhage, gastrointestinal irritation, gastro-oesophageal reflux disease, hiccups, lip blister, loose stools, pancreatitis aggravated, rectal haemorrhage, rectal prolapse, retching, small intestinal obstruction, toothache.
General disorders and administration site conditions: asthenia, chest pain, chest tightness, fall, feeling abnormal, feeling cold, inflammation localised, inflammation, influenza like illness, lethargy, malaise, mass, oedema peripheral, pain, rigors, thirst, ataxia, burning sensation, gait abnormal.
Hepatobiliary disorders: biliary tract disorder, cholelithiasis.
Immune system disorders: hypersensitivity, seasonal allergy.
Infections and infestations: abscess limb, bladder infection, bronchitis, ear infection, erysipelas, foot infection fungal, fungal infection, gastroenteritis, gastroenteritis viral, gastrointestinal infection, helicobacter infection, herpes simplex, herpes zoster, laryngitis acute, nail fungal infection, otitis externa, otitis media, otitis media serous, pharyngitis, respiratory tract infection viral, sinusitis, stye, tooth abscess, tooth infection, tracheitis, vaginosis fungal, viral infection, wound infection.
Injury, poisoning and procedural complications: abrasion, arthropod bite, back injury, blister, concussion, eye injury, face injury, hand fracture, head injury, joint sprain, laceration, ligament injury, limb injury, muscle injury, muscle strain, neck injury, postoperative wound complication, soft tissue injury, tendon injury, wrist fracture.
Investigations: alanine aminotransferase decreased, alanine aminotransferase increased, aspartate aminotransferase decreased, aspartate aminotransferase increased, blood amylase increased, blood calcium increased, blood cholesterol increased, blood creatinine increased, blood glucose abnormal, blood glucose increased, blood in stool, blood potassium abnormal, blood pressure increased, blood urea increased, body temperature increased, cardiac murmur, c-reactive protein increased, gamma-glutamyltransferase increased, haematocrit decreased, haematocrit increased, haemoglobin decreased, haemoglobin increased, low density lipoprotein increased, lymphocyte count increased, mammogram abnormal, mean platelet volume decreased, neutrophil count decreased, protein total decreased, red blood cell count decreased, red blood cell count increased, red blood cell sedimentation rate increased, red cell distribution width increased, white blood cell count increased.
Metabolism and nutrition disorders: decreased appetite, dehydration, diabetes mellitus, gout, hypercholesterolemia, hyperglycaemia, hyperlipidemia, hypertriglyceridaemia, hyperuricaemia, hypocalcaemia, hypokalaemia.
Musculoskeletal and connective tissue disorders: back disorder, back pain, bone pain, bone spur, bursitis, ganglion, groin pain, joint crepitation, joint disorder, joint stiffness, joint swelling, muscle cramps, muscle spasms, musculoskeletal discomfort, musculoskeletal stiffness, myalgia, neck pain, neck stiffness, osteoarthritis aggravated, osteopenia, osteoporosis, pain in limb, plantar fasciitis, polyarthralgia, rheumatoid arthritis, temporomandibular joint arthralgia, tendonitis.
Neoplasms benign, malignant and unspecified (including cysts and polyps): benign breast neoplasm, breast cancer invasive, breast cancer, thyroid neoplasm, uterine fibroids.
Nervous system disorders: disturbance in attention, dysarthria, dysgeusia, headache aggravated, hypoaesthesia, mental impairment, migraine, neuralgia, paraesthesia, sedation, sinus headache, sleep apnoea syndrome, syncope.
Psychiatric disorders: abnormal behaviour, agitation, bipolar disorder, confusion, depression, emotional disturbance, euphoric mood, indifference, irritability, libido decreased, nervousness, sleep disorder.
Renal and urinary disorders: calculus renal, difficulty in micturition, dysuria, haematuria, micturition urgency, nocturia, renal impairment, renal pain, urinary frequency, urinary hesitation, urinary incontinence, urinary retention.
Reproductive system and breast disorders: dysmenorrhoea, erectile dysfunction, genital pruritus female, menometrorrhagia, prostatitis, sexual dysfunction, vaginal cyst, vaginal discharge.
Respiratory, thoracic and mediastinal disorders: asthma aggravated, asthma, chest wall pain, cough, crackles lung, dry throat, dyspnoea, epistaxis, nasal congestion, nasal oedema, pharyngolaryngeal pain, productive cough, rhinitis allergic, rhinitis, rhinorrhea, rhonchi, sinus congestion, sinus pain, throat irritation.
Skin and subcutaneous tissue disorders: acne, cold sweat, contusion, dermatitis allergic, dermatitis contact, dermatitis, dermatitis aggravated, dermatosis, dry skin, eczema exacerbated, eczema, erythema, hyperkeratosis, ingrowing nail, night sweat, pallor, piloerection, prurigo, pruritus generalised, rash, rash pruritic, rosacea, skin ulcer, urticaria.
Surgical and medical procedures: cardiac pacemaker replacement, colon polypectomy, endodontic procedure, foot operation, hernia repair, lesion excision, tumour excision.
Vascular disorders: aortic aneurysm, deep venous thrombosis, flushing, haematoma, hot flushes aggravated, hypertension aggravated, hypertension, hypotension, orthostatic hypotension, poor peripheral circulation, vascular insufficiency, wound haemorrhage.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
In clinical trials where clinical abnormalities were recorded (n = 106), the following abnormalities were reported: Sedimentation rate increased (0.7%), glucose abnormalities (0.5%), GGT increased (0.4%).
The following abnormalities occurred in 0.2% of patients: cholesterol abnormalities, LDH increased, uric acid increased, hemoglobin decreased, red cell count decreased.
The following abnormalities occurred in <0.1% of patients: hematocrit decreased, alanine aminotransferase increased, aspartate aminotransferase increased, urea increased, liver function tests abnormal.
The following abnormalities were single occurrences: alanine aminotransferase decreased, aspartate aminotransferase decreased, amylase increased, bilirubin increased, calcium increased, creatinine increased, potassium abnormal, C-Reactive Protein increased, hematocrit increased, hemoglobin increased, low density lipoprotein increased, lymphocyte count decreased, mean platelet volume decreased, neutrophil count decreased, platelet count decreased, protein total decreased, red cell count increased, red cell distribution width increased, white cell count increased.
8.5 Post-Market Adverse Reactions
Adverse events which have been reported with the use of tramadol products include: allergic reactions (including anaphylaxis, angioneurotic edema and urticaria), bradycardia, convulsions, drug dependence, drug withdrawal (including agitation, anxiety, gastrointestinal symptoms, hyperkinesia, insomnia, nervousness, tremors), hyperactivity, hypoactivity, hypotension, loss of consciousness, hyponatremia and respiratory depression. Other adverse events which have been reported with the use of tramadol products and for which a causal association has not been determined include: difficulty concentrating, hepatitis, liver failure, pulmonary edema, Stevens-Johnson syndrome and suicidal tendency.
Cases of hypoglycemia have been reported in patients taking tramadol, mostly in patients with pre-disposing risk factors, including diabetes, elderly and renal insufficiency. Caution should be exercised when prescribing tramadol to diabetic patients. More frequent monitoring of blood glucose levels may be appropriate.
Serotonin syndrome (whose symptoms may include mental status change, hypertonia, hyperreflexia, fever, shivering, tremor, agitation, spontaneous clonus, inducible or ocular clonus, diaphoresis, seizures and coma) has been reported with tramadol when used concomitantly with other serotonergic agents such as SSRIs, SNRIs, MAOIs, tricyclic antidepressants and mirtazapine. Withdrawal of the serotonergic drugs usually brings about rapid improvement and the treatment depends on the type and the severity of symptoms.
Electrocardiogram QT prolonged, ventricular fibrillation, and ventricular tachycardia have been reported during post-market use with tramadol.
Androgen deficiency: Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
Hallucinations: Visual and auditory hallucinations have been reported at therapeutic doses of tramadol, during post-marketing experience, in a higher rate in elderly patients compared to younger patients. This is consistent with potential risk factors of polypharmacy, hepatic and renal impairment, and comorbid conditions being more common among elderly patients.
Withdrawal Symptoms: Withdrawal symptoms may occur if tramadol is discontinued abruptly. These symptoms may include: anxiety, sweating, insomnia, rigors, pain, nausea, tremors, diarrhea, upper respiratory symptoms, piloerection, and rarely hallucinations. Other symptoms that have been seen less frequently with tramadol hydrochloride discontinuation include: panic attacks, severe anxiety, and paresthesias.
Withdrawal symptoms have been studied in 325 patients, 3 and 7 days after discontinuation of treatment with TRIDURAL. The majority of symptoms were mild to moderate in nature. Onset of the post-treatment adverse events occurred more frequently within the first 3 days after treatment was stopped. Less than 1% of patients taking TRIDURAL met the DSM-IV criteria for a diagnosis of opioid withdrawal.
Clinical experience suggests that signs and symptoms of withdrawal may be avoided by tapering medication when discontinuing tramadol therapy.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
- Concomitant use of TRIDURAL with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma and death (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS, Neurologic; 9.2 Drug Interaction Overview).
- Do not use TRIDURAL in patients currently using or within 14 days of using a monoamine oxidase inhibitor (MOAI) (see 2 CONTRAINDICATIONS; 9.4 Drug-Drug Interactions).
- The co-ingestion of alcohol with TRIDURAL may result in increased plasma levels and a potentially fatal overdose of tramadol (see 2 CONTRAINDICATIONS; 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS, General and Neurologic; 9.3 Drug-Behavioural Interactions)
9.2 Drug Interactions Overview
In vitro studies indicate that tramadol is unlikely to inhibit the CYP3A4-mediated metabolism of other drugs when it is administered concomitantly at therapeutic doses. Tramadol does not appear to induce its own metabolism in humans, since observed maximal plasma concentrations after multiple oral doses are higher than expected based on single dose data. Tramadol is a mild inducer of selected drug metabolism pathways measured in animals.
The concomitant use of alcohol should be avoided (see 9.3 Drug-Behavioural Interactions).
Serotonergic Agents: Coadministration of tramadol hydrochloride with a serotonergic agent, such as a Selective Serotonin Re-uptake Inhibitor or a Serotonin Norepinephrine Re-uptake Inhibitor, may increase the risk of serotonin syndrome, a potentially life-threatening condition (see 7 WARNINGS AND PRECAUTIONS, Neurologic). Caution should be used when administering TRIDURAL in patients taking serotonergic drugs and the patient should be monitored for signs of adverse events. Discontinue TRIDURAL if serotonin syndrome is suspected.
Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants (e.g.
other opioids, sedatives/hypnotics, antidepressants, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, phenothiazines, neuroleptics, antihistamines, antiemetics, and alcohol) and beta-blockers, increases the risk of respiratory depression, profound sedation, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients closely for signs of respiratory depression and sedation (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol; 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery). TRIDURAL should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects.
9.3 Drug-Behavioural Interactions
The concomitant use of alcohol should be avoided. The co-ingestion of alcohol with TRIDURAL may result in increased plasma levels and a potentially fatal overdose of tramadol (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e. those identified as contraindicated).
Table 3 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Alcohol, Benzodiazepines and other CNS depressants | C | Respiratory depression, hypotension and profound sedation, coma or death may result. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. | Follow patients closely for signs and symptoms of respiratory depression and sedation. (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants; 7 WARNINGS AND PRECAUTIONS, Neurologic, Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol)) |
| Monoamine Oxidase inhibitors (MAOIs) | C | The concomitant use of tramadol and a MAOI can enhance the risk of seizure and serotonin syndrome. | Tramadol is contraindicated in patients receiving MAOIs or who have used them within the previous 14 days. (see 2 CONTRAINDICATIONS; 7 WARNINGS AND PRECAUTIONS, Neurologic, Seizure Risk) |
| Selective serotonin reuptake inhibitors (SSRI antidepressants or anorectics, e.g. fluoxetine, citalopram) and Serotonin-norepinephrine reuptake inhibitors (SNRIs, e.g. venlafaxine) | C | The concomitant use with tramadol increases the risk of seizure and serotonin syndrome. | Caution is warranted. (see 7 WARNINGS AND PRECAUTIONS, Neurologic) |
| Seizure threshold lowering drugs (e.g. bupropion, mirtazapine, tetrahydrocannabinol), Tricyclic antidepressants (TCAs), and other tricyclic compounds (e.g., cyclobenzaprine, promethazine, etc.) and anti-psychotics | C | The concomitant use with tramadol increases the risk of seizure. | Caution is warranted. (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Seizure Risk) |
| Carbamazepine (CYP3A4 inducer) | C | May significantly reduce tramadol’s analgesic effect. | Because carbamazepine increases tramadol metabolism and because of the seizure risk associated with tramadol, concomitant administration of TRIDURAL and carbamazepine is not recommended. |
| Quinidine | T | Can increase tramadol concentration and reduce M1 concentrations. In vitro drug interaction studies in human liver microsomes indicate that tramadol has no effect on quinidine metabolism. | Tramadol is metabolized to M1 by CYP2D6 and quinidine is a selective inhibitor of that isoenzyme. The clinical consequences of these findings are unknown. Caution is warranted. |
| Inhibitors of CYP2D6 (e.g. fluoxetine, paroxetine and amitryptiline) | C | Concomitant administration of CYP2D6 inhibitors may reduce metabolic clearance of tramadol. This could increase the risk for serious adverse events including seizures, serotonin syndrome, and QTc interval prolongation, potentially resulting in cardiac arrhythmias. (see 10.3 Pharmacokinetics) In vitro drug interaction studies in human liver microsomes indicate that concomitant administration with inhibitors of CYP2D6 could also result in some inhibition of tramadol’s metabolism. | Caution is warranted. |
| Inhibitors of CYP3A4 (e.g. ketoconazole and erythromycin) or inducers of CYP3A4 (e.g. rifampin and St. John’s Wort) | C | May lead to altered tramadol exposure and reduced metabolic clearance. This could increase the risk for serious adverse events including seizures, serotonin syndrome, and QTc interval prolongation, potentially resulting in cardiac arrhythmias. | Caution is warranted. |
| QTc Interval-Prolonging Drugs*† | C | May increase the risk of Torsade de pointes. | The concomitant use of TRIDURAL with QTc interval-prolonging drugs should be avoided and extreme caution is warranted. |
| Drugs that Affect Electrolytes (e.g. loop, thiazide, and related diuretics, laxatives and enemas, amphotericin B , high-dose corticosteroids, proton pump inhibitors) † | C | N/A | The concomitant administration of TRIDURAL with drugs that can decrease electrolyte levels should be avoided to the extent possible and caution is warranted. |
| Cimetidine | T | Concomitant administration of tramadol immediate-release tablets with cimetidine does not result in clinically significant changes in tramadol pharmacokinetics. | No alteration of the TRIDURAL dosage regimen with cimetidine is recommended. |
| Protease Inhibitors (e.g., ritonavir) | C | May increase serum concentration of tramadol, resulting in tramadol toxicity. | Caution is warranted. |
| Digoxin | C | Digoxin toxicity. | Post-marketing surveillance of tramadol has revealed rare reports of digoxin toxicity. |
| Warfarin-Like Compounds | C | Alteration of warfarin effect, including elevation of prothrombin times. | Post-marketing surveillance of tramadol has revealed rare reports of alteration of warfarin effect, including elevation of prothrombin times. While such changes have been generally of limited clinical significance for tramadol, periodic evaluation of prothrombin time should be performed when TRIDURAL tablets and warfarin like compounds are administered concurrently. |
| 5-HT3 Antagonists (e.g. ondansetron, granisetron, dolasetron) | C | Risk of decreasing/weakening effect of tramadol. | Post-marketing surveillance of tramadol has revealed an antagonistic interaction between 5-HT3 antagonists (e.g. ondansetron, granisetron, dolasetron) and tramadol with the risk of decreasing/weakening effect of tramadol. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
* QTc Interval-prolonging Drugs such as: Class IA antiarrhythmics (e.g., quinidine,procainamide, disopyramide); Class III antiarrhythmics (e.g.,amiodarone, sotalol, ibutilide, dronedarone) ; Class IC antiarrhythmics (e.g.,flecainide, propafenone); Antipsychotics (e.g., chlorpromazine, pimozide, haloperidol, droperidol, ziprasidone, risperidone); Antidepressants (e.g., fluoxetine, citalopram, venlafaxine, tricyclic/tetracyclic antidepressants [e.g., amitriptyline, imipramine, maprotiline]); opioids (e.g., methadone); macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, azithromycin, tacrolimus); quinolone antibiotics (e.g., moxifloxacin, levofloxacin, ciprofloxacin); pentamidine; antimalarials (e.g., quinine, chloroquine); azole antifungals (e.g., ketoxonazole, fluconazole, voriconazole); domperidone; 5-hydroxytryptamine (5-HT) 3 recepts antagonists (e.g., ondansetron); tyrosine kinase inhibitors (e.g., sunitinib, nilotinib, ceritinib, vandetanib); arsenic trioxide; histone deacetylase inhibitors (e.g., vorinostat); beta-2 adrenoceptor agonists (e.g., salmeterol, formoterol)
† The above list of potentially interacting drugs is not comprehensive. Current information sources should be consulted for newly approved drugs that prolong the QTc interval or decrease electrolytes, as well as for older drugs for which these effects have recently been established.
9.5 Drug-Food Interactions
Co-administration with food did not significantly change the overall exposure to tramadol; however, peak plasma concentrations increased. In the presence of food, the availability and controlled-release properties of TRIDURAL tablets were maintained with no evidence of dose dumping. TRIDURAL was administered either with breakfast or before breakfast in all clinical trials.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Tramadol hydrochloride is a centrally acting synthetic opioid analgesic. Although its mode of action is not completely understood, from animal tests, at least two complementary mechanisms appear applicable: binding of parent and M1 metabolite to µ-opioid receptors and weak inhibition of reuptake of norepinephrine and serotonin. Opioid activity is due to both low affinity binding of the parent compound and higher affinity binding of the O-demethylated metabolite M1 to μ-opioid receptors. In animal models, M1 is up to 6 times more potent than tramadol in producing analgesia and 200 times more potent in μ-opioid binding. Tramadol-induced analgesia is only partially antagonized by the opiate antagonist naloxone in several animal tests. The relative contribution of both tramadol and M1 to human analgesia is dependent upon the plasma concentrations of each compound (see 10.3 Pharmacokinetics, Absorption).
Tramadol has been shown to inhibit reuptake of norepinephrine and serotonin in vitro, as have some other opioid analgesics. These mechanisms may contribute independently to the overall analgesic profile of TRIDURAL.
Tramadol is a mild inducer of ethoxycoumarin deethylase activity in the mouse and dog.
Apart from analgesia, tramadol administration may produce a constellation of symptoms (including dizziness, somnolence, nausea, constipation, sweating and pruritus) similar to that of opioids. In contrast to morphine, tramadol has not been shown to cause histamine release. At therapeutic doses, tramadol has no effect on heart rate, left-ventricular function or cardiac index. Orthostatic hypotension has been observed.
10.2 Pharmacodynamics
Tramadol hydrochloride, 2-[(dimethylamino) methyl]-1-(3-methoxyphenyl) cyclohexanol HCl, is a centrally acting synthetic analgesic compound. It is thought to produce its analgesic effect through at least two complementary mechanisms of action: agonist activity at the μ-opioid receptor and weak inhibition of neuronal monoamine reuptake. These dual activities are observed in studies conducted in vitro as well as in nonclinical animal models of antinociception. In studies conducted in vitro, tramadol inhibited binding to native rat μ-opioid receptor at approximately the same concentration at which it blocked the reuptake of norepinephrine and serotonin. The K1 values for μ-opioid receptor affinity and monoamine reuptake inhibitory activities are 2.1 and ~ 1 μM respectively. Tramadol affinities for recombinant human opioid receptors (K1 = 17 μM) were slightly weaker than those observed at the rat receptors. Apart from analgesia, tramadol may produce a constellation of symptoms similar to that of an opioid.
Tramadol is an efficacious analgesic in a wide variety of standard analgesic models of acute, tonic, chronic, or neuropathic pain. In some of these studies, specific antagonists were used to probe the mechanism of tramadol’s antinociceptive action. In contrast to the full blockade of morphine antinociception by naloxone, the antinociceptive action of tramadol in most tests is only partially blocked by naloxone. Furthermore, although the antinociception of morphine is unaffected by the alpha2-adrenergic antagonist yohimbine or the serotonergic antagonist ritanserin, each of these antagonists reduces tramadol’s antinociception. These pharmacologic studies suggest the contribution of both opioid and monoamine mechanisms to tramadol antinociception.
In drug interaction studies carried out with tramadol, a substantial increase in toxicity was found after pretreatment with an MAOI, tranylcypromine. The antinociceptive effect of the compound was reduced by concomitant administration of barbiturates and atropine, and was virtually eliminated by tranylcypromine. Physostigmine potentiated the antinociceptive effect of a sub-maximal dose of tramadol. Other potential drug interactions based on enzyme induction or displacement from protein binding were thought to be unlikely with tramadol as no inductive effect on liver enzymes has been found for this agent and the protein binding is too low in induce relevant interference with the binding of other compounds.
Central Nervous System: Tramadol produces respiratory depression by direct action on brain stem respiratory centres. The respiratory depression involves both a reduction in the responsiveness of the brain stem centres to increases in CO2 tension and to electrical stimulation.
Tramadol depresses the cough reflex by direct effect on the cough centre in the medulla. Antitussive effects may occur with doses lower than those usually required for analgesia.
Tramadol causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings). Marked mydriasis rather than miosis may be seen with hypoxia in the setting of tramadol overdose.
Gastrointestinal Tract and Other Smooth Muscle: Tramadol causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in gastric, biliary and pancreatic secretions, spasm of the sphincter of Oddi, and transient elevations in serum amylase.
Endocrine System: Opioids may influence the hypothalamic-pituitary-adrenal or -gonadal axes. Some changes that can be seen include an increase in serum prolactin, and decreases in plasma cortisol and testosterone. Clinical signs and symptoms may be manifest from these hormonal changes.
Immune System: In vitro and animal studies indicate that opioids have a variety of effects on immune functions, depending on the context in which they are used. The clinical significance of these findings is unknown.
Cardiac Electrophysiology: In a randomized, double-blind, 4-way crossover, placebo- and positive-controlled, multiple dose ECG assessment study in healthy subjects (N=62), the following tramadol treatments were tested: A) 100 mg every 6 h on days 1-3 (400 mg/day), with a single 100 mg dose on day 4 and B) 150 mg every 6 h (600 mg/day) on days 1-3, with a single 150 mg dose on day 4. The doses administered in the trial are higher than the maximum daily dose for TRIDURAL which is 300 mg/day. In both treatment arms, the maximum difference from placebo in the mean change from baseline QTcF interval occurred at the 8 h time point: 5.5 ms (90% CI 3.2, 7.8) in the 400 mg/day treatment arm and 6.5 ms (90% CI 4.1, 8.8) in the 600 mg/day mg treatment arm. Both treatment groups were within the 10 ms threshold for QT prolongation (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular; 8.5 Post-Market Adverse Reactions; 9.4 Drug-Drug Interactions, QTc Interval-Prolonging Drugs; 4.2 Recommended Dose and Dosage Adjustment; 5 OVERDOSAGE).
10.3 Pharmacokinetics
In a single-dose study, the dose adjusted bioavailability of the 100 mg, 200 mg and 300 mg tablets were equivalent confirming a linear pharmacokinetic response (in relation to both tramadol and O-desmethyltramadol) over this range of strengths. Dose proportionality of the 100 mg, 200 mg and 300 mg tablets has been demonstrated.
Absorption
Following oral administration of a single dose, tramadol is almost completely absorbed and the absolute bioavailability is approximately 70%. There is no lag time in drug absorption following administration of TRIDURAL. TRIDURAL exhibits a plasma/time concentration profile with a sharp initial slope similar to immediate-release tramadol tablets followed by a sustained release phase. This behavior is due to the two phases of drug release which work together to provide a smooth plasma concentration/time profile (Figure 2).
Figure 2. Mean Tramadol and M1 Plasma Concentrations over the 24-Hour Dosing Interval Following a Single Oral Dose of TRIDURAL 200 mg
The mean peak steady-state plasma concentrations of tramadol and M1 after multiple dose administration of TRIDURAL 200 mg tablets to healthy subjects are attained at about 4.3 h and 7.4 h, respectively (Table 4).
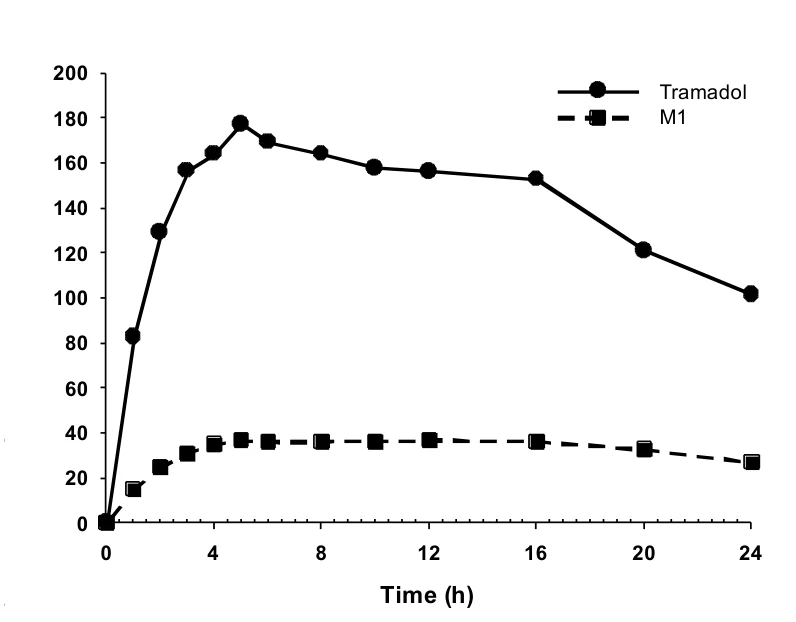
Table 4 – Mean (%CV) Steady-State Pharmacokinetic Parameter Values (n=26)
| Pharmacokinetic Parameter | Tramadol | M1 Metabolite | ||||||
|---|---|---|---|---|---|---|---|---|
| TRIDURAL 200 mg Tablet Once-Daily | TRIDURAL 200 mg Tablet Once-Daily | |||||||
| AUC0-24 (ng∙h/mL) | 5991 (22) | 1361 (27) | ||||||
| Cmax (ng/mL) | 345 (21) | 71 (27) | ||||||
| Cmin (ng/mL) | 157 (31) | 41 (30) | ||||||
| Tmax (hr)* | 4.0 (3.0 – 9.0) | 5.0 (3.0 – 20.0) | ||||||
| Fluctuation (%) | 77 (26) | 53 (29) | ||||||
*Tmax is presented as Median (Range).
Steady-state levels with TRIDURAL were reached within 48 hours (Figure 3). This is clinically meaningful in that it forms the basis for the titration schedule in all clinical studies and the dosing recommendations related to titration (see 4.2 Recommended Dose and Dosage Adjustment).
Figure 3. Mean Tramadol Plasma Concentrations at Steady-State Following Oral Administration of TRIDURAL 200 mg Once Daily
Tramadol was rapidly absorbed after oral administration in the mouse, rat, and dog. In dogs, the mean absolute bioavailability of a single 20 mg/kg oral dose of tramadol (Avicel formulation in gelatin capsules) was 81.8%, with maximum plasma concentrations achieved in about one hour.
Food Effect: Co-administration with food did not significantly change the overall exposure to tramadol; however, peak plasma concentrations increased. TRIDURAL was administered either with breakfast or before breakfast in all efficacy and safety clinical trials.
In Vitro Dissolution Studies of Interaction with Alcohol: Increasing concentrations of ethanol resulted in a decrease in the rate of release of TRIDURAL tablets.
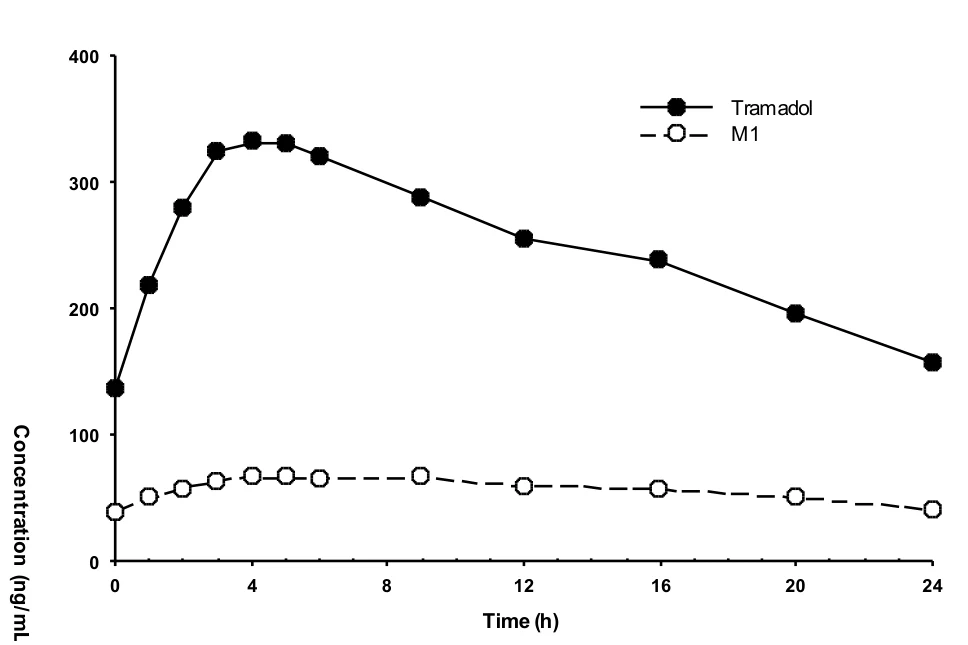
Distribution
The volume of distribution of tramadol is 2.6 and 2.9 L/kg in males and females, respectively, following a 100 mg intravenous dose. The binding of tramadol to human plasma proteins is approximately 20%. Protein binding also appears to be independent of concentration up to 10 mcg/mL. Saturation of plasma protein binding occurs only at concentrations outside the clinically relevant range.
Distribution of radioactivity into tissues was rapid following the intravenous administration of 14C-labelled tramadol to rats, with the highest concentration of radioactivity found in the liver. Radioactivity levels in the brain were comparable to plasma levels for the first 2 hours post-injection, demonstrating that the drug crosses the blood brain barrier. Concentrations in the kidneys, lungs, spleen, and pancreas were also higher than the serum concentration.
Metabolism
Tramadol is extensively metabolized after oral administration. The major metabolic pathways appear to be N- and O-demethylation and glucuronidation or sulfation in the liver. One metabolite (O-desmethyltramadol, denoted M1) is pharmacologically active in animal models. Formation of M1 is dependent on CYP2D6 and as such is subject to inhibition, which may affect the therapeutic response (see 9.4 Drug-Drug Interactions).
The major metabolic pathway was qualitatively similar for all species studied, including mouse, rat, hamster, guinea pig, rabbit, and man, and involved both Phase I (N- and O-demethylation and 4-hydroxylation; eight metabolites) and Phase II (glucuronidation or sulfation; thirteen metabolites) reactions. The primary metabolite mono-O-desmethylation (M1) has antinociceptive activity. In biochemical studies, (±) mono-O-desmethyltramadol and its enantiomers each had greater affinity for opioid receptors and were less potent inhibitors of monoamine uptake than were the corresponding parent compounds.
Elimination
Tramadol is eliminated primarily through metabolism by the liver and the metabolites are eliminated primarily by the kidneys. Approximately 30% of the dose is excreted in the urine as unchanged drug, whereas 60% of the dose is excreted as metabolites. The remainder is excreted either as unidentified or as unextractable metabolites. After single administration of TRIDURAL, the mean terminal plasma elimination half-lives of racemic tramadol and racemic M1 are 6.5 ± 1.5 and 7.5 ± 1.4 hours, respectively.
Excretion was primarily by the renal route in the animal species studied. After oral administration, faecal excretion was approximately 13% in rats and dogs and 80% of 14C-labelled tramadol doses were excreted in the urine within 72 to 216 hours of dosing. Amounts of unchanged tramadol excreted in the urine within 72 to 216 hours of dosing. Amounts of unchanged tramadol excreted in the urine were higher in man (approximately 30% of the dose) than in animals (approximately 1%).
Special Populations and Conditions
Pediatrics (<18 years of age): Pharmacokinetics of TRIDURAL tablets have not been studied in pediatric patients below 18 years of age.
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
- Geriatrics (>65 years of age): Healthy elderly subjects aged 65 to 75 years, administered an immediate-release formulation of tramadol, have plasma concentrations and elimination half-lives comparable to those observed in healthy subjects less than 65 years of age. The elimination half-life of tramadol may be prolonged in patients over 75 years, thereby increasing the potential for adverse events. Adjustment of the daily dose is recommended for patients older than 75 years (see 4.2 Recommended Dose and Dosage Adjustment).
- Sex: Following a 100 mg IV dose of tramadol, plasma clearance was 6.4 mL/min/kg in males and 5.7 mL/min/kg in females. This difference is not likely to be clinically significant; therefore, dosage adjustment based on sex is not recommended.
Ethnic Origin: Some patients are CYP2D6 ultra-rapid metabolizers of tramadol due to a specific genotype. These individuals convert tramadol into its active metabolite, M1, more rapidly and completely than other people leading to higher-than-expected serum M1 levels. The prevalence of this CYP2D6 phenotype varies widely and has been estimated at 0.5 to 1% in Chinese, Japanese and Hispanics, 1 to 10% in Caucasians, 3% in African Americans, and 16 to 28% in North Africans, Ethiopians, and Arabs. Data are not available for other ethnic groups.
In contrast, some patients exhibit the CYP2D6 poor metabolizer phenotype and do not convert tramadol to the active M1 metabolite sufficiently to benefit from the analgesic effect of the drug (see 9.2 Drug Interactions Overview). The prevalence of this CYP2D6 phenotype is about 5-10 percent in Caucasians and 1 percent of Asians.
- Hepatic Insufficiency: TRIDURAL is contraindicated in patients with severe hepatic impairment. The elimination half-life of tramadol and its active metabolite may be prolonged in patients with hepatic impairment. TRIDURAL has not been studied in patients with severe hepatic impairment and, therefore should not be used (see 2 CONTRAINDICATIONS; 4.2 Recommended Dose and Dosage Adjustment; 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
- Renal Insufficiency: Impaired renal function results in a decreased rate and extent of excretion of tramadol and its active metabolite, M1. TRIDURAL has not been studied in patients with severe renal impairment (creatinine clearances of less than 30 mL/min), and therefore should not be used in these patients (see 2 CONTRAINDICATIONS; 4.2 Recommended Dose and Dosage Adjustment; 7 WARNINGS AND PRECAUTIONS, Renal). The total amount of tramadol and M1 removed during a 4-hour dialysis period is less than 7% of the administered dose.
11 STORAGE, STABILITY AND DISPOSAL
Storage and Stability
Store at room temperature (15°-30°C).
TRIDURAL should be kept in a safe place, out of the sight and reach of children before, during and after use. TRIDURAL should not be used in front of children, since they may copy these actions.
Disposal
TRIDURAL should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended. Unused or expired TRIDURAL should be properly disposed of as soon as it is no longer needed to prevent accidental exposure to others, including children or pets. If temporary storage is required before disposal, a sealed child-proof container, such as a biohazard waste container or a lockable medication box could be obtained from a pharmacy.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: tramadol hydrochloride
Chemical name: (±)cis-2-[(dimethylamino) methyl]-1-(3-methoxyphenyl) cyclohexanol hydrochloride
Molecular formula and molecular mass: C16H25NO2•HCl and 299.8
Structural formula:
Physicochemical properties: tramadol hydrochloride is a white crystalline powder that is freely soluble in water and methanol.
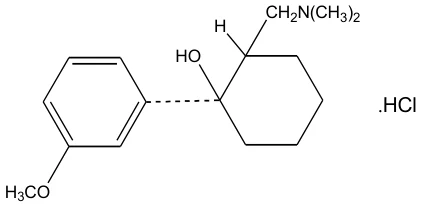
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Moderate to Moderately Severe Pain
Table 5 – Summary of patient demographics for clinical trials in osteoarthritis pain
| Study # | Study Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean age (Years) | Sex |
|---|---|---|---|---|---|
Study MDT3-005 | Randomised, double-blind, placebo-controlled, parallel group, titration to effect - TRIDURAL vs. placebo | TRIDURAL 200-300 mg/day vs. placebo, oral, 12 weeks | 646 randomised | TRIDURAL: 62±9 Placebo: 62±9 | Males: 37% Females: 63% |
| Study MDT3-003 | Randomised, double-blind, placebo-controlled, parallel group, titration to randomized dose | TRIDURAL 100-300 mg/day vs. placebo, oral, 12 weeks | 552 | TRIDURAL: 61±9 Placebo: 61±10 | Males: 38% Females: 62% |
TRIDURAL (tramadol hydrochloride extended-release tablets) efficacy was studied in three 12-week placebo-controlled, randomized, double-blind, studies (MDT3-002, MDT3-003 and MDT3-005) in patients with moderate to severe pain due to osteoarthritis. No rescue medication was permitted in any of the studies.
In one placebo-controlled study (MDT3-005), the key measure of analgesic efficacy was the Pain Intensity on Numerical Rating Scale (PI-NRS) (Table 6). In the other two studies, the three co-primary measures of analgesic efficacy were the Patient Global Rating of Pain, the WOMAC Pain subscale and the WOMAC Physical Function subscale (Table 7).
Table 6 – Results of study MDT3-005 in osteoarthritis pain
| Primary Endpoint | Associated value and statistical significance for TRIDURAL vs baseline | Associated value and statistical significance for placebo vs baseline | |||||
|---|---|---|---|---|---|---|---|
| Primary Endpoint | Associated value and statistical significance for TRIDURAL vs baseline | Associated value and statistical significance for placebo vs baseline | |||||
Pain intensity (11 point numerical rating scale )* | TRIDURAL Score Baseline 7.2 ± 1.6 Last Visit 4.3 ± 2.5 | Placebo Score Baseline 7.2 ± 1.6 Last Visit 4.8 ± 2.4 | |||||
Improvement from baseline: 2.9 ± 2.5 95% CI [2.7; 3.1] | Improvement from baseline: 2.4 ± 2.4 95% CI [2.1; 2.7] | ||||||
Improvement from baseline TRIDURAL vs. Placebo, p = 0.0157 | |||||||
* Pain Intensity Numerical Rating Scale: 11 points (0 = No pain, 10 = Worst possible pain)
Table 7 – Results of study MDT3-003 in osteoarthritis pain
| Primary Endpoint | Patient Rating | Associated value for TRIDURAL | Associated value for Placebo | |||||||||||||||
| 200 mg | 300 mg | |||||||||||||||||
Patient Global Rating of Pain (Categorical scale: not effective, effective or very effective at the end of treatment) | Very effective n and (%) | 32/107 (30%) | 45/105 (43%) | 50/224 (22%) | ||||||||||||||
Effective n and (%) | 44 /107 (41%) | 37/105 (35%) | 85/224 (38%) | |||||||||||||||
Not effective n and (%) | 31/107 (29%) | 23/105 (22%) | 88/224 (40%) | |||||||||||||||
| Statistical significance (P value) for the difference TRIDURAL vs. Placebo | ||||||||||||||||||
| 200 mg | 300 mg | |||||||||||||||||
| p = 0.0017 | p < 0.0001 | |||||||||||||||||
| Associated value for TRIDURAL | Associated value for Placebo | |||||||||||||||||
| 200 mg | 300 mg | |||||||||||||||||
WOMAC Pain subscale1 (5 X 100 mm VAS) | Baseline | 284 ± 82 mm | 314 ± 97 mm | 301 ± 89 mm | ||||||||||||||
| Last Visit | 160 ± 129 mm | 172 ± 138 mm | 202 ± 149 mm | |||||||||||||||
| Improvement from baseline | 123 ± 129 mm (43%) | 143 ± 136 mm (46%) | 100 ± 146 mm (32%) | |||||||||||||||
| Difference active vs. placebo | 11% | 13% | - | |||||||||||||||
| Statistical significance (P value) for the difference TRIDURAL vs. Placebo | ||||||||||||||||||
| 200 mg | 300 mg | |||||||||||||||||
| p = 0.0504 | p = 0.0162 | |||||||||||||||||
| Associated value for TRIDURAL | Associated value for Placebo | |||||||||||||||||
| 200 mg | 300 mg | |||||||||||||||||
WOMAC Physical Function subscale2 (17 X 100 mm VAS) | Baseline | 999 ± 323 mm | 1096 ± 349 mm | 1051 ± 325 mm | ||||||||||||||
| Last Visit3 | 493 mm | 543 mm | 668 mm | |||||||||||||||
| Improvement from baseline3 | 367 mm (45%) | 421 mm (46%) | 267 mm (27%) | |||||||||||||||
| Difference active vs. placebo | 11% | 12% | - | |||||||||||||||
| Statistical significance (P value) for the difference TRIDURAL vs. Placebo | ||||||||||||||||||
| 200 mg | 300 mg | |||||||||||||||||
| p= 0.0450 | p= 0.0211 | |||||||||||||||||
1 WOMAC Pain subscale score: 5 questions, 100 mm VAS each (0 – no pain to 100 mm – extreme pain). Subscale score range (0 to 500 mm).
2 WOMAC Physical Function subscale score: 17 questions, 100 mm VAS each (0 – no difficulty to 100 mm – extreme difficulty). Subscale score range (0 to 1700 mm).
3 Median values presented due to non-normal distribution of the data.
4 Non-parametric ANCOVA.
Study MDT3-002
In study MDT3-002, on the Patient Global Rating of Pain, 73% of patients randomized to TRIDURAL 300 mg rated it as effective or very effective, compared to 59% of patients randomized to Placebo. The difference between TRIDURAL 300 mg and Placebo was statistically significant (p= 0.0008). Due to a high placebo response, the other study parameters did not achieve statistical significance.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Contramid®: Contramid® (hydroxypropyl distarch phosphate), an excipient present in TRIDURAL 100 mg, 200 mg and 300 mg tablets, is responsible for the controlled-release characteristics of the TRIDURAL tablets. TRIDURAL 100 mg, 200 mg and 300 mg tablets have already been approved in the US, in more than 20 European countries and in 7 Latin American countries and are currently commercially available in many of them. Contramid® is also utilized as a food additive and its use is permitted in unlimited proportions. It meets the specifications for food-modified starch as stated in the current editions of the USP-NF 30 and the Food Chemicals Codex, as well as in 21 CFR part 172.892. The safety profile of Contramid® has been established in one acute toxicity study and one Bacterial Reverse Mutation assay (Ames test). These findings confirm the toxicological findings regarding hydroxypropyl distarch phosphate in the literature.
The acute toxicity study performed in rats showed that the oral LD50 of Contramid® was greater than 2000 mg/kg. There were no clinical or gross necropsy findings. This result was consistent with high oral LD50 values determined for distarch phosphate. The LD50 of distarch phosphate in mice, rats, guinea pigs, rabbits and cats was found to be greater than 24, 35, 18, 10 and 9 g/kg respectively. Absence of mutagenic potential of Contramid® at concentrations up to 5000 mcg/plate was shown in the reverse bacterial mutation assay (Ames test). Available data from the literature from several short-term studies show no significant adverse effects in rats fed daily for up to 3 months with a diet containing up to 25% of hydroxypropyl distarch phosphate. Data from long-term studies did not provide any evidence of carcinogenicity of hydroxypropyl distarch phosphate at dietary levels up to 62%, which is equivalent to 37 g per rat per day, and in animals fed three days a week. A diet of up to 62% modified starches had no effects on fertility, litter size or embryonic or pre-weaning mortality, and histological examination of the F3 generation showed no treatment-related anomalies.
Tramadol hydrochloride: The acute toxicity of tramadol hydrochloride has been examined in the mouse, rat, rabbit, guinea pig and dog. Summarized LD50 values are presented in Table 8.
Table 8 – Acute Toxicity Studies Summary
| Species | Oral LD50 Values (mg/kg) | s.c. | i.v. | i.m. | i.p. | rectal |
|---|---|---|---|---|---|---|
| Mouse* | 328-785 | 197-265 | 47-68 | 179-184 | 178-200 | – |
| Rat | 151-572 | 240-293 | 56 | – | – | 540-662 |
| Rabbit | 300-450 | – | 20-40 | 100-150 | – | 160 |
| Guinea pig | 850-897 | 23-250 | – | – | – | – |
| Dog | 100-450 | – | >50 < 100 | >50 < 100 | – | – |
s.c. = subcutaneous; i.v. = intravenous; i.m. = intramuscular; i.p. = intraperitoneal
* Signs of toxicity of tramadol in male mice: sedation in low doses followed by hypermotility, straub tail, slight tremor, exopthalmos, clonic convulsions, cyanosis.
Long-Term Toxicity: Multi-dose toxicity studies were conducted in rat and dog. Table 9 summarizes the results of the two chronic multi-dose studies in the rat and dog.
Table 9 – Multidose Toxicity Studies Summary
| Species/Strain Age/B.W. | No./Sex/ Group/Duration | Route | Dosage Levels (mg/kg) | Lethality | Evaluated Parameters | Results |
|---|---|---|---|---|---|---|
Rat Wistar 18 mo Age: 30-35 days B.W. M: 83 g F: 78 g | 20 M + 20 F /dose 18 mo | Oral | Tramadol 0 7.5 15 30 | 4/20 M, 0/20 F 1/20 M, 0/20 F 2/20 M, 2/20 F 1/20 M, 2/20 F | Mortality, B.W., food and water consumption, clinical signs, haematology, fecal blood, urinalysis, organ weights, histopathology | Except for body weight loss and increased food and water consumption, no treatment dose-related effects were observed. |
Dog Beagle Age: approx 11 mo B.W. M: 10.4-13.6 kg F: 6.6-10.4 kg | 4F + 4M /dose 52-weeks | Oral | Tramadol: 0 10 24 40 | 1/4 M* | Mortality, B.W., food and water consumption, clinical signs, haematology, fecal blood, urinalysis, organ weights, histopathology | No treatment related effects were observed except for slightly reduced weight gain and food intake in the females of all treatment groups. |
B.W. = body weight; M = male; F = female; mo = month
* All animals survived except one mid-dose male was sacrificed, week 37, due to recurring urinary obstruction due to large bladder stone. This was not considered treatment related.
Carcinogenicity
Two carcinogenicity studies were conducted: a 24-month oral mouse study and a 30-month oral rat study. These studies examined approximately 4 times the human therapeutic daily dose. There was no evidence that tramadol is carcinogenic. In mice, chronic administration of tramadol at doses of 0, 7.5, 15, or 30 mg/kg/day did not affect life span or enhance tumour formation. There was a slight but statistically significant increase in the incidence of commonly occurring tumours in aged mice. Rats treated at the same dosage levels for 30 months did not show any evidence of carcinogenic potential.
Genotoxicity
Tramadol hydrochloride did not demonstrate any mutagenic activity in the Ames test, the CHO/HPRT assay, or in the mouse lymphoma assay in the absence of metabolic activation. Weekly mutagenic results were obtained in the presence of metabolic activation in the mouse lymphoma assay, but these were secondary to high levels of induced cytotoxicity. In vivo studies (micronucleus test in the mouse, rat, and hamster) were negative. A bone marrow cytogenics test in hamsters was negative as was a dominant lethal test in mice.
Reproductive and Developmental Toxicology
The potential of tramadol to produce reproductive toxicity was evaluated in a series of six main studies in mice, rats and rabbits. The results of these studies indicated that tramadol had no effect on fertility in male or female rats, even at toxic oral dose levels (up to 50 mg/kg in males and 75 in females). Tramadol did not induce teratogenicity in mice, rats, or rabbits given up to 140, 80, or 300 mg/kg, respectively. Embryo/fetal toxicity, consisting of slight decreases in fetal weight, and/or variations in bone ossification, occurred at tramadol doses 3 to 15 times the maximum human dose or higher, but only in the presence of maternal toxicity. Maternal toxicity generally consisted of decreased body weight gain in conjunction with decreased food consumption.
In peri- and postnatal studies in the rat, maternal toxicity occurred in dams treated with tramadol gavaged doses of 8 mg/kg and higher. Signs of toxicity included decreased body weight gain and reduced food consumption. A rebound in these parameters did occur during lactation, suggesting some adaptation to the effects of the drug, although weight gain of treated dams continued to lag behind those controls throughout the remainder of the study. At doses of 20 mg/kg and higher, clinical signs such as exophthalmia and dilated pupils increased; alopecia increased at doses of 40 mg/kg and greater. Progeny of dams receiving 50 mg/kg or higher had decreased body weights. At doses of 80 mg/kg or higher, decreased pup survival during early lactation was noted.
Special Toxicology
Dependence Liability: The physical dependence liability potential associated with the chronic use of tramadol has been evaluated in a number of animal studies, including investigations in the mouse, rat, and monkey. A slight degree of antinociceptive tolerance to tramadol evolved in the mouse studies, but there was little or no indication of the development of physical dependence. No evidence of dependence was observed in the rat study. However, in dogs addicted to morphine, withdrawal symptoms were relieved by tramadol. In primate studies, which evaluated the physical dependence and reinforcement properties of tramadol, the physical dependence of the drug was deemed to be low.