


Product Monograph - Opsynvi
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions, Cardiovascular | 03/2025 |
|---|---|
| 4 Dosage and Administration | 03/2025 |
| 7 Warnings and Precautions, Cardiovascular, Hepatic and Reproductive Health | 03/2025 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics ................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................... 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.4 Administration .......................................................................................................... 6
4.5 Missed Dose ............................................................................................................ 6
5 OVERDOSAGE ................................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................... 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 7
7.1 Special Populations ............................................................................................... 11
7.1.1 Pregnant Women ............................................................................................... 11
7.1.2 Breast-feeding ................................................................................................... 12
7.1.3 Pediatrics ........................................................................................................... 12
7.1.4 Geriatrics ........................................................................................................... 12
8 ADVERSE REACTIONS ................................................................................................. 13
8.1 Adverse Reaction Overview .................................................................................. 13
8.2 Clinical Trial Adverse Reactions ............................................................................ 13
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 19
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ................................................................................................... 20
8.5 Post-Market Adverse Reactions ............................................................................ 21
9 DRUG INTERACTIONS .................................................................................................. 22
9.1 Serious Drug Interactions ...................................................................................... 22
9.2 Drug Interactions Overview ................................................................................... 22
9.3 Drug-Behavioural Interactions ............................................................................... 23
9.4 Drug-Drug Interactions .......................................................................................... 23
9.5 Drug-Food Interactions .......................................................................................... 28
9.6 Drug-Herb Interactions .......................................................................................... 29
9.7 Drug-Laboratory Test Interactions ......................................................................... 29
10 CLINICAL PHARMACOLOGY ....................................................................................... 29
10.1 Mechanism of Action ......................................................................................... 29
10.2 Pharmacodynamics ........................................................................................... 30
10.3 Pharmacokinetics .............................................................................................. 32
11 STORAGE, STABILITY AND DISPOSAL ...................................................................... 37
12 SPECIAL HANDLING INSTRUCTIONS ......................................................................... 37
PART II: SCIENTIFIC INFORMATION ....................................................................................... 38
13 PHARMACEUTICAL INFORMATION ............................................................................ 38
14 CLINICAL TRIALS ......................................................................................................... 38
14.1 Trial Design and Study Demographics .............................................................. 38
14.2 Study Results ..................................................................................................... 40
14.3 Comparative Bioavailability Studies ................................................................... 49
15 MICROBIOLOGY ............................................................................................................ 49
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 50
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................. 53
PATIENT MEDICATION INFORMATION .................................................................................. 54
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
OPSYNVI® (macitentan and tadalafil), is indicated for:
- the long-term treatment of pulmonary arterial hypertension (PAH, World Health Organization [WHO] Group 1) to reduce morbidity in patients of WHO functional class (FC) II or III whose PAH is idiopathic, heritable or associated with connective tissue disease or congenital heart disease.
- OPSYNVI® should be used in patients who are currently treated concomitantly with stable doses of macitentan 10 mg and tadalafil 40 mg (20 mg x 2) as separate tablets.
1.1 Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of OPSYNVI® in children and adolescents <18 years of age has not been established.
2 CONTRAINDICATIONS
OPSYNVI® is contraindicated in:
- Patients who are hypersensitive to macitentan and/or tadalafil or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Women who are or may become pregnant (see 7.1.1 Pregnant Women).
- Nursing women (see 7.1.2 Breast-feeding).
- Patients who are using any form of organic nitrate (e.g. oral, sublingual, transdermal, by inhalation), either regularly and/or intermittently due to the risk of developing potentially severe hypotension (see 9.4 Drug-Drug Interactions, Nitrates).
- Patients with previous episode of non-arteritic anterior ischaemic optic neuropathy (NAION) (see 7 WARNINGS AND PRECAUTIONS).
- Patients treated with guanylate cyclase stimulators, such as riociguat because coadministration of drugs containing phosphodiesterase type 5 (PDE5) inhibitors, including OPSYNVI®, with guanylate cyclase stimulators could lead to potentially life-threatening episodes of symptomatic hypotension or syncope.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Renal impairment
The administration of OPSYNVI® to patients with severe renal impairment is not recommended because of increased tadalafil exposure (AUC), lack of clinical experience and the lack of ability to influence clearance by dialysis. (see 7 WARNINGS AND PRECAUTIONS, Renal). There is no experience with the use of macitentan in patients undergoing dialysis, and therefore OPSYNVI® is not recommended in this population.
OPSYNVI® is recommended only for patients with mild or moderate renal impairment who tolerate macitentan 10 mg and tadalafil 40 mg once daily.
Patients with moderate renal impairment may have a higher risk of experiencing hypotension and anemia during treatment with OPSYNVI®. Therefore, monitoring of blood pressure and hemoglobin should be considered.
- Hepatic impairment
The administration of OPSYNVI® to patients with moderate hepatic impairment is not recommended. OPSYNVI® must not be initiated in patients with severe hepatic impairment, with or without cirrhosis (Child-Pugh Class C), or clinically significant elevated hepatic aminotransferases greater than 3 times the Upper Limit of Normal (> 3 × ULN).
Liver enzyme tests should be obtained prior to initiation of OPSYNVI®. Subsequently, monthly testing during the first year of treatment is recommended. Testing may then be repeated less frequently during treatment as clinically indicated (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
OPSYNVI® is recommended only for patients with mild hepatic impairment who tolerate stable doses of macitentan 10 mg and tadalafil 40 mg once daily as individual components, following a careful individual benefit/risk evaluation by the prescribing physician (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of OPSYNVI® is one tablet taken once daily.
- Switch from macitentan and tadalafil as individual components to OPSYNVI®
Patients who are currently treated concomitantly with stable doses of macitentan 10 mg and tadalafil 40 mg (20 mg x 2) once daily as individual components may be switched to OPSYNVI®.
- Pediatrics (<18 years of age)
The safety and efficacy of OPSYNVI® have not been established in children and adolescent patients <18 years of age. Health Canada has not authorized an indication for pediatric use.
- Geriatrics (≥65 years of age)
No dose adjustment is required in patients 65 years and older. There is limited clinical experience in patients >75 years of age with macitentan or tadalafil, and therefore OPSYNVI® should be used with caution in this population.
4.4 Administration
- OPSYNVI® should be taken orally once daily with or without food. Tablets are to be swallowed whole.
4.5 Missed Dose
If a dose of OPSYNVI® is missed, the tablet should be taken as soon as the patient remembers. Otherwise, advise the patient to skip the dose and take the next dose at the regular time. The patient should be advised not to take 2 doses on the same day to make up for a missed dose.
5 OVERDOSAGE
There is no human experience of acute overdose with OPSYNVI®. As OPSYNVI® contains macitentan and tadalafil, the risk of overdose associated with each component should be considered.
Treatment
In the event of an overdose with OPSYNVI®, standard supportive measures must be taken as required. Based on the individual component data, dialysis is unlikely to be effective.
Macitentan
Macitentan has been administered as a single dose of up to and including 600 mg to healthy subjects. Adverse events of headache, nausea and vomiting were observed.
Tadalafil
Single doses of up to 500 mg of tadalafil have been given to healthy subjects, and multiple daily doses up to 100 mg/day for 21 days have been given to patients with erectile dysfunction (ED). Adverse reactions were similar to those seen at lower doses. Doses greater than 40 mg have not been studied in patients with pulmonary arterial hypertension.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Description
OPSYNVI® is available as oblong, white to almost-white, film-coated tablets debossed “MT” on one side and “1040” on the other side. Each film-coated tablet contains 10 mg macitentan and 40 mg tadalafil.
OPSYNVI® tablets are supplied as follows:
30 count film-coated tablets in high-density polyethylene bottles
7 WARNINGS AND PRECAUTIONS
General As OPSYNVI® contains macitentan and tadalafil, the Warnings and Precautions associated with each component should be considered.
Cardiovascular
In the double-blind portion of the A DUE study, cardiac failure events were reported within one month of treatment initiation with OPSYNVI® in 4 out of 20 patients aged 65 years or older. All four patients had not been previously treated with PAH-specific medications. Two cases out of four resolved while on treatment, whereas treatment in the other two was discontinued due to other adverse events [a newly established diagnosis of Pulmonary Veno-Occlusive Disease (exclusionary as per study protocol) and anaemia].
Pulmonary Veno-Occlusive Disease
Since there are no clinical data on administration of tadalafil to patients with veno-occlusive disease, administration of OPSYNVI® to such patients in not recommended. Cases of pulmonary edema have been reported with vasodilators (mainly prostacyclins) when used in patients with pulmonary veno-occlusive disease. Consequently, if signs of pulmonary edema occur when OPSYNVI® is administered in patients with PAH, the possibility of pulmonary veno-occlusive disease should be considered.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Film-coated tablet, 10 mg macitentan + 40 mg tadalafil | Tablet core: Hydroxypropyl cellulose, Lactose monohydrate, Low-substituted hydroxypropyl cellulose, Magnesium stearate, Microcrystalline cellulose, Polysorbate 80, Povidone K30, Sodium lauryl sulfate, Sodium starch glycolate Type A Film coat material: Hydroxypropyl methylcellulose, Lactose monohydrate, Talc, Titanium dioxide, Triacetin |
Tadalafil
Physicians should discuss with patients the appropriate action in the event that they experience anginal chest pain requiring nitroglycerin following intake of OPSYNVI®. In such a patient, who has taken OPSYNVI®, where nitrate administration is deemed medically necessary for a life-threatening situation, at least 48 hours should have elapsed after the last dose of OPSYNVI® before nitrate administration is considered. In such circumstances, nitrates should still only be administered under close medical supervision with appropriate hemodynamic monitoring. Therefore, patients who experience anginal chest pain after taking OPSYNVI® should seek immediate medical attention.
As with other PDE5 inhibitors, tadalafil has mild systemic vasodilatory properties that may result in transient decreases in blood pressure. While this effect should not be of consequence in most patients, prior to prescribing OPSYNVI®, physicians should carefully consider whether their patients with underlying cardiovascular disease could be affected adversely by such vasodilatory effects. Patients with severely impaired autonomic control of blood pressure may be particularly sensitive to the actions of vasodilators, including PDE5 inhibitors.
Patients with left ventricular outflow obstruction, (e.g., aortic stenosis and idiopathic hypertrophic subaortic stenosis) can be sensitive to the action of vasodilators, including PDE5 inhibitors.
The following groups of patients with cardiovascular disease were excluded in the tadalafil PAH clinical trials:
- Patients with clinically significant aortic and mitral valve disease
- Patients with pericardial constriction
- Patients with restrictive or congestive cardiomyopathy
- Patients with significant left ventricular dysfunction
- Patients with life-threatening arrhythmias
- Patients with symptomatic coronary artery disease
- Patients with hypotension (< 90/50 mm Hg), or uncontrolled hypertension
Ear/Nose/Throat Tadalafil
Decreased or Sudden Hearing Loss
Physicians should advise patients to seek immediate medical attention in the event of sudden decrease or loss of hearing. These events, which may be accompanied by tinnitus and dizziness, have been reported in temporal association to the intake of PDE5 inhibitors, including tadalafil. It is not possible to determine whether these events are related directly to the use of PDE5 inhibitors or to other factors (see 8 ADVERSE REACTIONS).
Gastrointestinal OPSYNVI® contains lactose monohydrate. Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this medicinal product.
Hematologic
Initiation of OPSYNVI® is not recommended in patients with severe anemia. It is recommended that hemoglobin concentrations are measured prior to initiation of treatment, again after one month, and periodically thereafter as clinically indicated (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 8 ADVERSE REACTIONS). Macitentan
As with other endothelin receptor antagonists (ERAs), treatment with macitentan has been associated with a decrease in hemoglobin concentration. Macitentan related decreases in hemoglobin concentration occurred early, were not progressive, stabilized before 12 weeks of treatment and remained stable during chronic treatment. Cases of anemia requiring transfusion have been reported with macitentan and other ERAs.
Hepatic/Biliary/Pancreatic
OPSYNVI® must not be initiated in patients with severe hepatic impairment, with or without cirrhosis (Child-Pugh Class C), or clinically significant elevated hepatic aminotransferases greater than 3 times the Upper Limit of Normal (> 3 × ULN). OPSYNVI® is not recommended in patients with moderate to severe hepatic impairment (see 4.1 Dosing Considerations, Hepatic Impairment).
The A DUE Phase 3 clinical study for OPSYNVI® excluded patients with known severe hepatic impairment (defined as a Model for End Stage Liver Disease score ≥19).
Liver enzyme tests should be obtained prior to initiation of OPSYNVI®. Subsequently, monthly testing during the first year of treatment is recommended. Testing may then be repeated less frequently during treatment as clinically indicated (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
If unexplained clinically relevant aminotransferase elevations occur, or if elevations are accompanied by an increase in bilirubin >2 x ULN, or by clinical symptoms of liver injury (e.g. jaundice), OPSYNVI® should be discontinued. Re-initiation of OPSYNVI® may be considered following the return of hepatic enzyme levels to within the normal range in patients who have not experienced clinical symptoms of liver injury (see 8 ADVERSE REACTIONS).
Macitentan
Elevations of liver aminotransferases (AST, ALT) have been associated with PAH and with ERAs. In a long-term double blind, placebo-controlled Phase III outcome study of macitentan, the incidence of an increase in ALT of >3 times the upper limit of normal (ULN) was 3.4% in the 10 mg group compared to 1.6% in the placebo group. The incidence of elevated aminotransferases of >8 x ULN was 2.1% in the macitentan 10 mg group compared to 0.4% in the placebo group. Post-market cases of liver injury have been reported with macitentan use (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Liver aminotransferases and 8.5 Post-Market Adverse Reactions, Gastrointestinal Disorders).
Monitoring and Laboratory Tests Hematologic: It is recommended that hemoglobin concentrations are measured prior to initiation of treatment, again after one month, and periodically thereafter as clinically indicated (see 7 WARNINGS AND PRECAUTIONS, Hematologic and 8 ADVERSE REACTIONS).
Hepatic/Biliary/Pancreatic: Liver enzyme tests should be obtained prior to initiation of OPSYNVI® and subsequently at monthly intervals during the first year of treatment. They may then be repeated less frequently during treatment as clinically indicated (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Ophthalmologic Tadalafil
Physicians should advise patients to seek immediate medical attention in the event of a sudden loss of vision in one or both eyes. Such an event may be a sign of non-arteritic anterior ischemic optic neuropathy (NAION), a cause of decreased vision, including permanent loss of vision that has been reported rarely post-marketing in temporal association with the use of all PDE5 inhibitors. An increased risk of acute NAION has been suggested from analyses of observational data in men with ED within 1 to 4 days of episodic PDE5 inhibitor use. Physicians should also discuss with patients the increased risk of NAION in individuals who have already experienced NAION in one eye, including whether such individuals could be adversely affected by use of vasodilators such as PDE5 inhibitors (see 8 ADVERSE REACTIONS).
There is evidence that patients at risk for NAION may have abnormal optic discs (e.g. crowded disc) prior to development of the condition. If physicians are concerned about the overall risk of NAION, they should consider discussing these concerns with an ophthalmologist.
Patients with known hereditary degenerative retinal disorders, including retinitis pigmentosa, were not included in the clinical trials, and use in these patients is not recommended.
Renal The administration of OPSYNVI® to patients with severe renal impairment is not recommended, due to increased tadalafil exposure (AUC), limited clinical experience, and the lack of ability to influence tadalafil clearance by dialysis in patients with severe renal insufficiency. There is no experience with the use of macitentan in patients undergoing dialysis, and therefore OPSYNVI® is not recommended in this population.
Patients with moderate or severe renal impairment may run a higher risk of experiencing hypotension and anemia during treatment with macitentan. Therefore, monitoring of blood pressure and hemoglobin should be considered in patients with moderate renal impairment. (see 4.1 Dosing Considerations, Renal Impairment).
Reproductive Health: Female and Male Potential
Fertility
The effect of OPSYNVI® on human fertility has not been evaluated. As OPSYNVI® contains macitentan and tadalafil, the fertility information associated with each component should be considered.
Macitentan
Based on findings in animals, macitentan may impair fertility in males of reproductive potential. Decreases in sperm cell count have been observed in patients taking ERAs. Macitentan, like other ERAs, may have an adverse effect on spermatogenesis in men. It is not known whether effects on fertility would be reversible. Counsel men about potential effects on fertility.
In repeated-dose toxicity studies, pathologic changes in testes (tubular dilatation, tubular degeneration and/or tubular atrophy and/or hypospermatogenesis) occurred in rats or dogs at >18-fold human exposure (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Tadalafil
Long-term human studies with subjects 45 years or older have shown that tadalafil therapy may decrease sperm concentration in some patients, but the clinical relevance of this to human fertility is unknown (see 10.2 Pharmacodynamics Effects on Sperm Characteristics).
Function
Tadalafil
Priapism has been reported in men treated with PDE5 inhibitors. Patients who experience erections lasting 4 hours or more should be instructed to seek immediate medical assistance. If priapism is not treated immediately, penile tissue damage and permanent loss of potency may result.
OPSYNVI® should be used with caution in patients with anatomical deformation of the penis (such as angulation, cavernosal fibrosis, or Peyronie's disease), or in patients who have conditions which may predispose them to priapism (such as sickle cell anemia, multiple myeloma or leukemia).
7.1 Special Populations
7.1.1 Pregnant Women
There are no data on the use of OPSYNVI® during pregnancy. OPSYNVI® is contraindicated during pregnancy or in patients who may become pregnant due to teratogenicity identified in the animal studies with macitentan (see 2 CONTRAINDICATIONS). As OPSYNVI® contains macitentan and tadalafil, the pregnancy information associated with each component should be considered.
Macitentan
PAH is a contraindication to pregnancy, due to a high mortality risk to both mother and fetus. There are limited data from the use of macitentan in pregnant women. The potential risk for humans is still unknown. In animal studies, macitentan was teratogenic in rabbits and rats, causing cardiovascular and mandibular arch fusion abnormalities at all dose levels tested. Women receiving macitentan must be advised of the risk of harm to the fetus.
Macitentan treatment should only be initiated in women of child-bearing potential when the absence of pregnancy has been verified, appropriate advice on contraception provided, and reliable contraception is practiced. Women should not become pregnant for 1 month after discontinuation of macitentan. Monthly pregnancy tests during treatment with macitentan are recommended to allow the early detection of pregnancy.
Tadalafil
There are no adequate and well controlled studies of tadalafil use in pregnant women. Animal reproduction studies in rats and mice revealed no evidence of fetal harm.
Animal reproduction studies showed no evidence of teratogenicity, embryotoxicity, or fetotoxicity when tadalafil was given to pregnant rats or mice at unbound tadalafil exposures up to 9 times the maximum recommended human dose (MRHD) of 40 mg/day during organogenesis (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1.2 Breast-feeding
OPSYNVI® is contraindicated in nursing women. It is not known whether macitentan or tadalafil, or their metabolites are excreted into human breast milk. In rats, macitentan and its metabolites were excreted into milk during lactation.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of OPSYNVI® in pediatric patients has not been established (see 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Pediatrics). Therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
In a clinical study for OPSYNVI® in PAH (A DUE), 20.4% of patients were ≥65 years of age. Patients enrolled in A DUE study were naïve to PAH therapies or received monotherapies with either ERA or PDE5i, including macitentan and tadalafil. The AEs reported with a frequency >10% in patients ≥65 years of age in A DUE study were edema peripheral (30.0%), anemia
(25.0%), and headache (15.0%). For comparison, the corresponding incidences in the 18-64 years age group were 9.2%, 3.4%, and 17.2%, respectively. In clinical studies for macitentan and tadalafil in PAH, 14% and 28% of subjects were ≥65 years of age. There is also limited clinical experience in patients >75 years of age with macitentan or tadalafil, and therefore OPSYNVI® should be used with caution in geriatric patients (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics (≥65 years of age)).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The overall safety profile of OPSYNVI® is based on the data from the clinical study in PAH patients for OPSYNVI® as well as the individual component safety data. In the OPSYNVI® clinical study in PAH patients, which included treatment-naïve patients, patients on ERA monotherapy or PDE5i monotherapy, the most frequently occurring adverse reactions (≥ 10%) were anemia/hemoglobin decrease, edema/fluid retention and headache.
As OPSYNVI® contains macitentan and tadalafil, the adverse reactions associated with each component may be expected.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Experience from A DUE study [PAH]
The overall safety profile of OPSYNVI® is based on data from a double-blind, randomized, active controlled, Phase 3 clinical study (A DUE), followed by an open-label extension study, in patients with PAH. In the double-blind portion of the study, a total of 107 patients were treated with OPSYNVI® 10 mg/40 mg, 35 patients were treated with 10 mg macitentan monotherapy, and 44 patients were treated with 40 mg tadalafil monotherapy. The duration of exposure to OPSYNVI® during the double-blind portion was 16 weeks. One-hundred eighty-five patients received OPSYNVI® in the double-blind or open-label phase of the study. The median exposure to OPSYNVI® during the combined double-blind/open-label extension was 59.9 weeks and the mean exposure was 63.2 weeks.
The most common adverse reactions (occurring in ≥ 10% of the OPSYNVI® treated patients) from the double-blind study data were edema/fluid retention (20.6%), anemia/hemoglobin decrease (18.7%), and headache (16.8%).
The most common adverse reactions (occurring in ≥ 10% of the OPSYNVI® treated patients) from the combined double-blind/open-label study data included anemia/hemoglobin decrease (22.2%) edema/fluid retention (17.3%), and headache (14.1%).
The majority of adverse drug reactions were mild to moderate in intensity. During the double-blind phase of A DUE, reactions of severe intensity were more frequent in the OPSYNVI® group (14.0%) than in the macitentan (5.7%) and tadalafil (6.8%) groups.
The incidence of treatment discontinuations due to adverse events (AEs) during the double-blind phase was 8.4% (9/107 patients) for OPSYNVI, 4.5% (2/44 patients) for tadalafil and 0% (0/35 patients) for macitentan.
Serious adverse events (SAEs) were reported more frequently in the OPSYNVI® group than in the macitentan monotherapy or tadalafil monotherapy groups. The only System/Organ Class (SOC) with an imbalance in SAEs during the double-blind phase was Cardiac disorders: 6.5% in the OPSYNVI® group versus 2.9% in the macitentan group and 2.3% in the tadalafil group. The imbalance was mainly driven by AEs denoting cardiac failure (ie, cardiac failure, left and right ventricular failure).
Eight cases of hypotension were reported during the double-blind phase of the study. All occurred in the OPSYVNI® group, and all cases were classified as mild to moderate severity.
During the double-blind study, anemia/hemoglobin decrease was reported in 18.7% participants in the OPSYNVI® group compared to 2.9% in the macitentan and 2.3% in tadalafil groups. In the combined double-blind/open label group, 22.2% of participants treated with OPSYNVI® reported anemia/hemoglobin decrease. There was a single case of severe anemia/hemoglobin decrease; all other cases were reported as mild to moderate.
The frequencies of the adverse reactions listed in Table 1 were determined based on double-blind data and combined double-blind/open-label data from A DUE.
| Table 1: Adverse Reactions Occurring in Patients Treated with OPSYNVI® in A DUE | ||||
|---|---|---|---|---|
| A DUE DB | Long-term combined A DUE DB/OLa | |||
| System/Organ Class | OPSYNVI (n=107) (%) | Macitentan monotherapy (n=35) (%) | Tadalafil monotherapy (n=44) (%) | Combined FDC A DUE DB/OL (n=185) (%) |
| Blood and lymphatic system disorders | ||||
| Anemia/Hemoglobin decreaseb | 18.7 | 2.9 | 2.3 | 22.2 |
| Cardiac disorders | ||||
| Cardiac failure eventsc | 5.6 | 0 | 4.6 | 5.9 |
| Palpitations | 3.7 | 2.9 | 4.5 | 5.4 |
| Tachycardia | 1.9 | 0 | 0 | 1.6 |
| Eye disorders | ||||
| Vision blurred | 1.9 | 2.9 | 0 | 1.6 |
| Gastrointestinal disorders | ||||
| Nausea | 5.6 | 0 | 6.8 | 4.3 |
| Dyspepsia | 3.7 | 0 | 6.8 | 2.2 |
| Vomiting | 3.7 | 0 | 4.5 | 4.9 | |||
|---|---|---|---|---|---|---|---|
| Abdominal discomfort | 1.9 | 2.9 | 4.5 | 2.2 | |||
| Abdominal pain | 1.9 | 0 | 4.5 | 2.2 | |||
| Gastroesophageal reflux disease | 0.9 | 2.9 | 2.3 | 2.2 | |||
| General disorders and administration site conditions | |||||||
| Edema/fluid retentiond | 20.6 | 14.3 | 15.9 | 17.3 | |||
| Swelling face | 1.9 | 0 | 2.3 | 1.1 | |||
| Chest pain | 0.9 | 2.9 | 0 | 1.1 | |||
| Immune system disorders | |||||||
| Angioedema | 0.9 | 0 | 0 | 1.1 | |||
| Hypersensitivity | 0.9 | 0 | 0 | 0.5 | |||
| Infections and infestations | |||||||
| Nasopharyngitis | 2.8 | 2.9 | 0 | 3.8 | |||
| Influenza | 1.9 | 2.9 | 0 | 2.7 | |||
| Urinary tract infection | 1.9 | 0 | 0 | 4.9 | |||
| Upper respiratory tract infection | 0.9 | 0 | 0 | 6.5 | |||
| Investigations | |||||||
| Transaminases increased | 0.9 | 0 | 2.3 | 1.1 | |||
| Musculoskeletal and connective tissue disorders | |||||||
| Myalgia | 5.6 | 0 | 4.5 | 5.9 | |||
| Back pain | 4.7 | 2.9 | 9.1 | 5.4 | |||
| Pain in extremity | 2.8 | 0 | 6.8 | 3.8 | |||
| Nervous system disorders | |||||||
| Headache | 16.8 | 17.1 | 13.6 | 14.1 | |||
| Migraine | 0.9 | 0 | 0 | 0.5 | |||
| Syncope | 0.9 | 0 | 4.5 | 1.6 | |||
| Reproductive system and breast disorders | |||||||
| Increased uterine bleedinge | 4.9 | 0 | 0 | 4.9 | |||
| Respiratory, thoracic and mediastinal disorders | |||||||
| Nasal congestion | 3.7 | 0 | 0 | 4.9 | |||
| Epistaxis | 2.8 | 0 | 0 | 2.2 | |||
| Skin and subcutaneous tissue disorders | |||||||
| Rash | 1.9 | 2.9 | 4.5 | 3.2 | |||
| Vascular disorders | |||||||
| Hypotension | 7.5 | 0 | 0 | 6.5 | |||
| Flushingf | 3.7 | 5.7 | 0 | 2.7 | |||
| a Based on a data cut-off date of 31Dec2022, in patients exposed to OPSYNVI® for a median duration of 59.9 months. | |||||||
b Grouped term includes preferred terms (PTs) of anemia, iron deficiency anemia, anemia of chronic disease, hemoglobin decreased, normochromic anemia, pancytopenia, blood loss anemia, and myelofibrosis. c Grouped term includes PTs of cardiac failure, left ventricular failure, right ventricular failure and cardiac failure chronic. | |||||||
| d Grouped term includes PTs of edema peripheral, peripheral swelling, generalized edema, swelling, fluid retention, bone marrow edema, joint swelling, edema, hypervolaemia, and pericardial effusion. | |||||||
| e Grouped term includes PTs of heavy menstrual bleeding, intermenstrual bleeding, polymenorrhagia, and vaginal hemorrhage. Frequency based on exposure in female subjects. | |||||||
f Grouped term includes PTs of flushing, and hot flush. DB = double-blind; FDC = fixed dose combination; OL = open-label |
|---|
Macitentan
Safety data for macitentan were obtained from 1 long-term placebo-controlled clinical study (SERAPHIN) in 742 patients with PAH. Doses of 3 mg and 10 mg macitentan were administered once daily. Safety data for the recommended dose of macitentan 10 mg are presented. The exposure to macitentan in this trial was up to 3.6 years (N=542 for 1 year; N=429 for 2 years and N=98 for more than 3 years). The overall incidence of treatment discontinuations due to adverse events (AEs) was 11% (26/242 patients) for macitentan 10 mg and 12% (31/249 patients) for placebo. The overall incidence of patients with a serious AE was 45% (109/242 patients) for macitentan 10 mg and 55% (137/249 patients) for placebo.
The majority of AEs were mild to moderate in intensity. Table 2 represents treatment-emergent AEs reported by >3% of patients in the macitentan 10 mg group and more frequently than on placebo by >3%.
Table 2: Treatment-emergent Adverse Reactions Reported by >3% of Patients on macitentan and more Frequent than on Placebo by >3%
| System Organ Class / Adverse Events (AEs) | Macitentan 10 mg (n=242) (%) | Placebo (n=249) (%) |
| Blood and Lymphatic System Disorders | ||
| Anemia | 13 | 3 |
| Infections and Infestations | ||
| Nasopharyngitis | 14 | 10 |
| Bronchitis | 12 | 6 |
| Urinary tract infection | 9 | 6 |
| Pharyngitis | 6 | 3 |
| Influenza | 6 | 2 |
| Nervous System Disorders | ||
| Headache | 14 | 9 |
Hypotension has been associated with the use of ERAs. In a long-term double-blind study in patients with PAH, hypotension as an AE was reported for 7.0% and 4.4% of patients on macitentan 10 mg and placebo, respectively. This corresponded to 3.5 events/100 patient-years on macitentan 10 mg compared to 2.7 events/100 patient-years on placebo. Edema/fluid retention has been associated with the use of ERAs and is also a clinical manifestation of right heart failure and underlying PAH disease. In a long-term double-blind study in patients with PAH, the incidence of edema AEs in macitentan 10 mg and placebo treatment groups were 21.9%, and 20.5%, respectively. This corresponded to 11.0 events/100 patient-years on macitentan 10 mg compared to 12.5 events/100 patient-years on placebo.
Open-Label Extension Study
Of the 742 patients who participated in the pivotal SERAPHIN double-blind study, 550 patients entered a long-term open-label extension study (182 patients who continued on macitentan 10 mg and 368 patients who received placebo or macitentan 3 mg and crossed over to macitentan 10 mg).
Long-term follow up of patients treated with macitentan 10 mg in the double-blind / open-label extension studies (N=242) for a median exposure of 4.6 years and a maximum exposure of 11.8 years showed a safety profile that was consistent with that described above for the double-blind, placebo-controlled phase.
Tadalafil
Tadalafil was administered to 402 patients with PAH during clinical trials worldwide. In trials of tadalafil, a total of 266 patients were treated for at least 182 days, and 110 patients were treated for at least 360 days. Adverse events (AEs) were reported with greater incidence in subjects taking tadalafil 40 mg; however, the rate of discontinuation due to AEs other than events related to worsening of PAH was similar in the tadalafil treatment group (3.8%) and in placebo (4.9%).
Table 3: Treatment Emergent Adverse Events Reported by ≥3% of Patients in tadalafil 40 mg group and more Frequent than Placebo
| Event | Placebo (%) (n=82) | Tadalafil 40 mg (%) (n=79) |
| Headache | 15 | 42 |
| Myalgia | 4 | 14 |
| Nasopharyngitis | 7 | 13 |
| Flushing | 2 | 13 |
| Respiratory Tract Infection (Upper and Lower) | 6 | 13 |
| Pain in Extremity | 2 | 11 |
| Diarrhea | 10 | 11 |
| Nausea | 6 | 11 |
| Back Pain | 6 | 10 |
| Dyspepsia | 2 | 10 |
| Nasal Congestion (including sinus congestion) | 1 | 9 |
| Chest Pain | 1 | 6 |
| Dyspnea | 4 | 6 |
| Fatigue | 4 | 6 |
| Vomiting | 1 | 6 |
| Upper Respiratory Tract Infection | 4 | 6 |
| Bronchitis | 0 | 5 |
| Gastroesophageal Reflux Disease | 4 | 5 |
| Edema | 1 | 5 |
| Rash | 3 | 5 |
| Constipation | 1 | 4 |
| Hot Flush | 2 | 4 |
| Insomnia | 2 | 4 |
| Menorrhagia (including increased uterine bleeding)a | 0 | 4 |
| Musculoskeletal Stiffness | 0 | 4 |
| Non-Cardiac Chest Pain | 0 | 4 |
| Urinary Tract Infection | 0 | 4 |
| Abdominal discomfort | 0 | 3 |
| Abdominal pain | 2 | 3 |
| Abdominal pain lower | 1 | 3 |
| Abdominal pain upper | 1 | 3 |
| Sinusitis | 0 | 3 |
| Muscle Spasms | 2 | 3 |
| Vision Blurred | 1 | 3 |
a Clinical non-MedDRA term to include reports of abnormal/excessive menstrual bleeding conditions such as menorrhagia, metrorrhagia or menometrorrhagia.
In the placebo-controlled study, one subject (receiving tadalafil 10 mg) reported changes in colour vision. In the long-term extension study, no patients reported changes in colour vision.
8.3 Less Common Clinical Trial Adverse Reactions
Macitentan1
Blood and Lymphatic System Disorders: anemia, eosinophilia, hemorrhagic, leukopenia, lymphadenitis, polycythemia
Cardiac Disorders: atrial flutter, atrial tachycardia, atrioventricular block first degree, bundle branch block right, pericardial effusion, supraventricular tachycardia
Ear and Labyrinth Disorders: vertigo
Eye Disorders: cataract, conjunctivitis, lacrimation increased, vision blurred
Gastrointestinal Disorders: abdominal pain, colitis, constipation, diverticulum intestinal, food poisoning, gastritis erosive, hemorrhoids, irritable bowel syndrome, periodontitis, toothache
General Disorders and Administration Site Conditions: influenza like-illness, non-cardiac chest pain, sudden death
Hepatobiliary Disorders: cholelithiasis, hyperbilirubinemia
Immune System Disorders: drug hypersensitivity
Infections and Infestations: ear infection, furuncle, gastroenteritis viral, infection parasitic, lower respiratory infection, oral herpes, overgrowth bacterial, strongyloidiasis, tonsillitis, tooth abscess, tracheitis
Injury, Poisoning and Procedural Complications: arthropod sting, contusion, laceration
Investigations: alanine aminotransferase increased, blood creatinine increased, blood urea increased, hematocrit decreased, hemoglobin decreased, platelet count decreased, red blood cell count decreased, weight decreased, white blood cell count decreased
Metabolism and Nutrition Disorders: hyperkalemia, hyponatremia
Musculoskeletal and Connective Tissue Disorders: arthritis, costochondritis, myofascial pain syndrome, muscle spasms, osteoarthritis, osteochondrosis, plantar fasciitis, systemic sclerosis
Neoplasms Benign, Malignant and Unspecified (including cysts and polyps): uterine leiomyoma
Nervous System Disorders: dizziness exertional, migraine, neuralgia, sciatica
Psychiatric Disorders: anxiety, decreased activity
Reproductive System and Breast Disorders: amenorrhea, gynecomastia, menorrhagia, metrorrhagia, ovarian cyst, uterine cervical erosion
Respiratory, Thoracic and Mediastinal Disorders: bronchial hyperreactivity, chronic obstructive pulmonary disease, dysphonia, dyspnoea exertional, hydrothorax, hypoxia, nasal congestion, oropharyngeal pain, productive cough, respiratory failure, rhinitis allergic, rhinorrhea
Skin and Subcutaneous Tissue Disorders: dermatitis allergic, eczema, erythema, photosensitivity reaction, pruritis, swelling face, urticaria
Vascular Disorders: flushing, hematoma, hot flush, orthostatic hypotension, thrombophlebitis, varicose vein
1 Events with frequency <3% occurring in more than 1 patient in the macitentan group, and more frequently than in the placebo group; Less frequent events occurring in at least two subjects in the tadalafil 40 mg treatment group, and greater than placebo.
Tadalafil2
Blood and Lymphatic Disorders: increased International Normalized Ratio
Body as a Whole: chills, herpes zoster, onychomycosis, pain
Digestive: abdominal discomfort, abdominal pain (lower and upper), gastritis, stomach discomfort
Metabolic and Nutrition Disorders: hypercholesterolemia
Musculoskeletal: arthralgia, joint sprain, limb discomfort/pain
Nervous: hypesthesia, paresthesia
Psychiatric Disorders: depression
Ophthalmologic: lacrimation increased, eyelid edema/swelling
Otologic: vertigo
Respiratory: lower respiratory tract infection, pharyngolaryngeal pain, rhinitis
Reproductive System: vaginal hemorrhage
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Hemoglobin: In the double-blind phase of the A DUE study, the mean decrease in hemoglobin from baseline to week 16 in patients treated with OPSYNVI®, macitentan and tadalafil alone was 1.4 g/dL, 0.7 g/dL and 0.1 g/dL, respectively. A decrease in hemoglobin to below 10 g/dL was reported in 11.0% of the OPSYNVI® treated patients compared to 2.9% and 0.0% in macitentan and tadalafil treated patients, respectively. In the combined double-blind/open-label data, the mean decrease in hemoglobin concentration in OPSYNVI® treated patients was 0.95 g/dL up to week 47 (106 patients) and 0.56 g/dL up to week 120 (16 patients). In OPSYNVI® treated patients, the incidence of a hemoglobin decrease below 10 g/dL was 13.8% and the incidence of a decrease below 8 g/dL was 2.3%.
Macitentan
In a double-blind study in patients with PAH, macitentan 10 mg was associated with a mean decrease in hemoglobin versus placebo of 1.0 g/dL. A decrease in hemoglobin concentration to below 10 g/dL was reported in 8.7% of patients treated with macitentan 10 mg and 3.4% of placebo-treated patients. Macitentan-related decreases in hemoglobin concentration occurred early, were not progressive, stabilized before 12 weeks of treatment and remained stable during chronic treatment. Decreases in hemoglobin concentration have occurred following administration of other ERAs (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
2 Events reported in the controlled clinical trial of tadalafil occurring in at least two subjects in the 40 mg treatment group, and greater than placebo. A causal relationship of these events to tadalafil is uncertain.
Liver aminotransferases: The incidence of aminotransferase elevations (ALT/AST) >3 x ULN was 3.4% on macitentan 10 mg and 4.5% on placebo in a double-blind study in patients with PAH. Elevations >5 x ULN occurred in 2.5% of patients on macitentan 10 mg versus 2% of patients on placebo. The incidence of elevated aminotransferases of >8 x ULN was 2.1% on macitentan 10 mg versus 0.4% in the placebo group (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Elevations of liver aminotransferases (ALT, AST) and liver injury have been reported with macitentan use. In most cases, alternative causes could be identified (heart failure, hepatic congestion, autoimmune hepatitis). Endothelin receptor antagonists have been associated with elevations of aminotransferases, hepatotoxicity, and cases of liver failure.
The incidence of elevated aminotransferases in the double-blind (DB) and combined double-blind/open-label (OL) arms of the study of OPSYNVI® in PAH are shown in Table 4.
| Table 4: Incidence of Elevated Aminotransferases in the A DUE Study* | ||
|---|---|---|
OPSYNVI® DB (N=107) | OPSYNVI® DB/OL (N=185) | |
| ≥3 x ULN | 1.0% | 3.4% |
| ≥5 x ULN | 1.0% | 2.2% |
| ≥8 x ULN | 1.0% | 1.1% |
*The A DUE study excluded patients with known severe hepatic impairment (defined as a Model for End Stage Liver Disease score ≥19) and patients with serum aminotransferases (AST and/or ALT) > 1.5 x ULN at screening.
8.5 Post-Market Adverse Reactions
In addition to adverse events identified from clinical studies, the following adverse events were identified during post-marketing experience. Because these events have been reported voluntarily from a population of unknown size, estimates of frequency cannot be made.
Macitentan
Gastrointestinal Disorders: elevations of liver aminotransferases (ALT, AST), liver injury
General Disorders and Administration Site Conditions: edema/fluid retention
Immune System Disorders: hypersensitivity reactions (angioedema, pruritus and rash)
Reproductive system and breast disorders: increased uterine bleeding
Respiratory, Thoracic and Mediastinal Disorders: nasal congestion
Tadalafil
Body as a Whole: hypersensitivity reactions including rash, urticaria, facial edema, Stevens-
Johnson syndrome and exfoliative dermatitis
Cardiovascular and Cerebrovascular: serious cardiovascular events, including myocardial infarction, sudden cardiac death, unstable angina pectoris, ventricular arrhythmia, stroke, transient ischemic attacks, chest pain, palpitations and tachycardia Hypotension (more commonly reported when tadalafil is given to patients who are already taking antihypertensive agents), hypertension and syncope
Gastrointestinal: abdominal pain and gastroesophageal reflux
Nervous System: migraine, transient global amnesia
Otologic: cases of sudden decrease or loss of hearing have been reported post-marketing in temporal association with the use of PDE5 inhibitors, including tadalafil. In many cases, medical follow-up information was limited.
Respiratory System: epistaxis (nosebleed)
Skin and Subcutaneous Tissues: hyperhidrosis (sweating)
Special Senses: blurred vision, nonarteritic anterior ischemic optic neuropathy, retinal vein occlusion, visual field defect
Urogenital: priapism, prolonged erection
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
Based on the known characteristics of macitentan and tadalafil, no pharmacokinetic interaction is expected between these individual components in OPSYNVI®.
Based on the information of the individual component data, in the presence of strong CYP3A4 inhibitors, exposure of OPSYNVI® could be increased. Co-administration of OPSYNVI® with strong CYP3A4 inhibitors (e.g., itraconazole, ketoconazole and ritonavir) is not recommended.
Based on the information of the individual component data, in the presence of strong CYP3A4 inducers, exposure and efficacy of OPSYNVI® could be reduced. Co-administration of OPSYNVI® with strong CYP3A4 inducers (e.g., rifampicin) is not recommended.
As OPSYNVI® contains macitentan and tadalafil, the interactions associated with each component should be considered. Macitentan
The metabolism of macitentan to its active metabolite is catalysed mainly by CYP3A4, with minor contributions from CYP2C8, CYP2C9 and CYP2C19.
At clinically relevant concentrations, macitentan and its active metabolite do not have relevant inhibitory or inducing effects on CYP enzymes.
Macitentan is neither a substrate nor an inhibitor of the multi-drug resistance protein (P-gp, MDR-1). At clinically relevant concentrations, the active metabolite of macitentan is not an
Serious Drug Interactions
|
inhibitor of P-gp. At clinically relevant concentrations, macitentan and its active metabolite are neither substrates nor inhibitors of the organic anion transporting polypeptides OATP1B1 and OATP1B3.
At clinically relevant concentrations, macitentan and its active metabolite are not inhibitors of the uptake transporters OCT1, OCT2, OAT1, OAT, and the drug efflux pumps BCRP, MATE-1, and MATE2-K.
At clinically relevant concentrations, macitentan and its active metabolite do not interact with proteins involved in hepatic bile salt transport, i.e., the bile salt export pump (BSEP) and the sodium-dependent taurocholate co-transporting polypeptide (NTCP).
Tadalafil
Tadalafil is predominantly metabolized by the cytochrome P450 (CYP) 3A4 isoform.
9.3 Drug-Behavioural Interactions
Effects on Ability to Drive and Use Machines
No studies on the effect of OPSYNVI® on the ability to drive and use machines have been performed. However, as OPSYNVI® contains macitentan and tadalafil, the patient should be informed of the individual component data before driving vehicles or operating machinery.
9.4 Drug-Drug Interactions
The drugs listed in Table 5 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Macitentan
Table 5: Established or Potential Drug-Drug Interactions for Macitentan
| Co-administered Drug | Source of Evidence | Effect | Clinical comment |
| Breast cancer resistance protein substrate drugs | Macitentan 10 mg once daily did not affect the pharmacokinetics of oral rosuvastatin 10 mg. | No dose adjustment is warranted. | |
| Cyclosporin A | CT | In healthy volunteers, concomitant treatment with cyclosporine A 100 mg twice daily, a combined CYP3A4 and OATP inhibitor, did not alter the steady-state exposure to macitentan and its active metabolite to a clinically relevant extent. | No dose adjustment is warranted. |
| Hormonal contraceptives | T | Macitentan 10 mg once daily did not affect the pharmacokinetics of an oral contraceptive (norethisterone 1 mg and ethinyl estradiol 35 mcg). | No dose adjustment is warranted. |
| Moderate Dual or Combined CYP3A4 and CYP2C9 Inhibitors (fluconazole) | T | In the presence of fluconazole 400 mg daily, a moderate dual inhibitor of CYP3A4 and CYP2C9, exposure to macitentan may increase approximately 3.8 fold or higher in CYP2C9 poor metabolisers, as assessed in physiologically based pharmacokinetic modelling. However, there were no clinically relevant changes in exposure to the active metabolite of macitentan, and the clinical significance of these findings is not known. The uncertainties of such modelling should be considered. | Caution should be exercised when OPSYNVI® is administered concomitantly with dual inhibitors and moderate dual inhibitors of CYP3A4 and CYP2C9 (e.g., fluconazole, amiodarone). Caution should also be exercised when macitentan is administered concomitantly with both a moderate CYP3A4 inhibitor (e.g., ciprofloxacin, cyclosporine, diltiazem, erythromycin, verapamil) and CYP2C9 inhibitor (e.g., miconazole). |
| Rifampicin | CT | In healthy volunteers, concomitant treatment with rifampicin 600 mg daily, a potent inducer of CYP3A4, reduced the steady-state exposure (AUC) to macitentan by 79% but did not affect the exposure to the active metabolite. Reduced efficacy of macitentan in the presence of a potent inducer of CYP3A4, such as rifampicin, should be considered. | The combination of OPSYNVI® with strong CYP3A4 inducers should be avoided. |
| Riociguat | Macitentan 10 mg once daily did not affect the pharmacokinetics of oral riociguat 1 mg. | As OPSYNVI® contains tadalafil, co-administration of OPSYNVI® with riociguat is contraindicated. | |
| Sildenafil | CT | At steady state in healthy volunteers, the exposure to sildenafil 20 mg three times daily was increased by 15% during concomitant administration of macitentan 10 mg once daily. Sildenafil, a CYP3A4 substrate, did not affect the pharmacokinetics of macitentan, while there was a 15% reduction in the exposure to the active metabolite of macitentan. These changes are not considered clinically relevant. In a placebo-controlled trial in patients with PAH, the efficacy and safety of macitentan 10 mg in combination with sildenafil were demonstrated. | No dose adjustment is warranted. |
Strong CYP3A4 inhibitors (ketoconazole) | CT | In the presence of ketoconazole 400 mg daily, a strong CYP3A4 inhibitor, exposure to macitentan increased approximately 2-fold in healthy volunteers. Exposure to the active metabolite of macitentan was reduced by 26%. The clinical significance of these changes is not known. | Caution should be exercised when OPSYNVI® is administered concomitantly with strong CYP3A4 inhibitors (e.g., itraconazole, ketoconazole, voriconazole, clarithromycin, nefazodone, ritonavir, saquinavir). |
| Warfarin | CT | In healthy volunteers receiving 25 mg warfarin, daily doses of macitentan did not have a clinically relevant effect on the pharmacokinetics of S-warfarin (CYP2C9 substrate) or R-warfarin (CYP3A4 substrate). The pharmacodynamic effect of warfarin on International Normalized Ratio (INR) was not affected by macitentan. The pharmacokinetics of macitentan and its active metabolite were not affected by warfarin. | No dose adjustment is warranted. |
Legend: CT = Clinical Trial; T = Theoretical
Tadalafil
Potential for Pharmacodynamic Interactions with Tadalafil
Alcohol — PDE5 inhibitors, including tadalafil, are vasodilators and may augment the blood-pressure-lowering effect of alcohol.
Tadalafil did not affect alcohol concentrations, and alcohol did not affect tadalafil concentrations. At high doses of alcohol (0.7 g/kg, mean maximum blood concentration 0.08%), the addition of tadalafil 10 or 20 mg did not induce statistically significant mean blood pressure decreases. In some subjects, postural dizziness and orthostatic hypotension were observed. When tadalafil was administered with lower doses of alcohol (0.6 g/kg), hypotension was not observed and dizziness occurred with similar frequency to alcohol alone.
Alpha Blockers — Caution is advised when PDE5 inhibitors are co-administered with alpha blockers. PDE5 inhibitors, including tadalafil, and alpha-adrenergic blocking agents are both vasodilators with blood-pressure-lowering effects. When vasodilators are used in combination, an additive effect on blood pressure may be anticipated. Clinical pharmacology studies have been conducted with coadministration of tadalafil with doxazosin, alfuzosin or tamsulosin (see 10 CLINICAL PHARMACOLOGY).
Antihypertensives — PDE5 inhibitors, including tadalafil, are mild systemic vasodilators. Clinical pharmacology studies were conducted to assess the effect of tadalafil on the potentiation of the blood-pressure-lowering effects of selected antihypertensive medications (amlodipine, angiotensin II receptor blockers, bendrofluazide, enalapril, and metoprolol). Small reductions in blood pressure occurred following coadministration of tadalafil with these agents compared with placebo (see 10 CLINICAL PHARMACOLOGY).
Physicians should discuss with patients the potential for OPSYNVI® to augment the blood pressure lowering effect of alpha blockers and antihypertensive medications (see 10 CLINICAL PHARMACOLOGY).
In some patients, concomitant use of PDE5 inhibitors and alpha blockers can lower blood pressure significantly, which may lead to symptomatic hypotension (e.g., fainting). Consideration should be given to the following:
- Patients should be stable on alpha-blocker therapy prior to initiating treatment with OPSYNVI®. Patients who demonstrate hemodynamic instability on alpha-blocker therapy alone are at increased risk of symptomatic hypotension with concomitant use of PDE5 inhibitors.
- In those patients already taking an optimized dose of PDE5 inhibitor, alpha-blocker therapy should be initiated at the lowest dose. Stepwise increase in alpha-blocker dose may be associated with further lowering of blood pressure when taking a PDE5 inhibitor.
- Safety of combined use of PDE5 inhibitors and alpha blockers may be affected by other variables, including intravascular volume depletion and other antihypertensive drugs.
Combination with Other PDE5 Inhibitors — Tadalafil is also marketed as Cialis for treatment of male erectile dysfunction. The safety and efficacy of combinations of OPSYNVI® with Cialis or other PDE5 inhibitors have not been studied. Therefore, the use of such combinations is not recommended.
Nitrates — Administration of tadalafil to patients who are using any form of organic nitrate, is contraindicated. In clinical pharmacology studies, tadalafil was shown to potentiate the hypotensive effect of nitrates. In a patient who has taken tadalafil, where nitrate administration is deemed medically necessary in a life-threatening situation, at least 48 hours should elapse after the last dose of tadalafil before nitrate administration is considered. In such circumstances, nitrates should still only be administered under close medical supervision with appropriate hemodynamic monitoring (see 2 CONTRAINDICATIONS and 10 CLINICAL PHARMACOLOGY).
Potential for Other Drugs to Affect Tadalafil
Antacids — Simultaneous administration of an antacid (magnesium hydroxide/aluminum hydroxide) and tadalafil (10 mg) reduced the apparent rate of absorption of tadalafil without altering exposure (AUC) to tadalafil.
Cytochrome P450 Inducers — Studies have shown that drugs that induce CYP3A4 can decrease tadalafil exposure. For patients chronically taking potent inducers of CYP3A4, such as rifampicin, the use of tadalafil is not recommended (see 4 DOSAGE AND ADMINISTRATION). Rifampin (600 mg daily), a CYP3A4 inducer, reduced tadalafil 10 mg single-dose exposure (AUC) by 88% and Cmax by 46%, relative to the values for tadalafil 10 mg alone. Bosentan (125 mg twice daily), a substrate of CYP2C9 and CYP3A4 and a moderate inducer of CYP3A4, CYP2C9 and possibly CYP2C19, reduced tadalafil (40 mg once per day) systemic exposure by 42% and Cmax by 27% following multiple-dose co-administration. Although specific interactions have not been studied, other CYP3A4 inducers, such as carbamazepine, phenytoin, and phenobarbital, would likely decrease tadalafil exposure. Cytochrome P450 Inhibitors — Tadalafil is metabolized predominantly by CYP3A4. In patients taking potent inhibitors of CYP3A4 such as ketoconazole, itraconazole or ritonavir, the use of OPSYNVI® is not recommended (see 4 DOSAGE AND ADMINISTRATION). Studies have shown that drugs that inhibit CYP3A4 can increase tadalafil exposure.
Ketoconazole (400 mg daily), a selective and potent inhibitor of CYP3A4, increased tadalafil 20 mg single-dose exposure (AUC) by 312% and Cmax by 22%, relative to the values for tadalafil 20 mg alone. Ketoconazole (200 mg daily) increased tadalafil 10 mg single-dose exposure (AUC) by 107% and Cmax by 15%, relative to the values for tadalafil 10 mg alone (see 4 DOSAGE AND ADMINISTRATION).
Although specific interactions have not been studied, other CYP3A4 inhibitors, such as erythromycin and itraconazole would likely increase tadalafil exposure.
H2 Antagonists (e.g. Nizatidine) — An increase in gastric pH resulting from administration of nizatidine had no significant effect on tadalafil (10 mg) pharmacokinetics.
HIV Protease inhibitor — Ritonavir (500 mg or 600 mg twice daily at steady state), an inhibitor of CYP3A4, CYP2C9, CYP2C19, and CYP2D6, increased tadalafil 20 mg single-dose exposure (AUC) by 32% with a 30% reduction in Cmax, relative to the values for tadalafil 20 mg alone. Ritonavir (200 mg twice daily), increased tadalafil 20 mg single-dose exposure (AUC) by 124% with no change in Cmax, relative to the values for tadalafil 20 mg alone. Although specific interactions have not been studied, other HIV protease inhibitors would likely increase tadalafil exposure (see 4 DOSAGE AND ADMINISTRATION).
Potential for Tadalafil to Affect Other Drugs
Aspirin — Tadalafil (10 mg and 20 mg once per day) did not potentiate the increase in bleeding time caused by aspirin.
Combined Oral Contraceptives — At steady-state, tadalafil (40 mg once per day) increased ethinylestradiol exposure (AUC) by 26% and Cmax by 70% relative to oral contraceptive administered with placebo. There was no statistically significant effect of tadalafil on levonorgestrel.
Cytochrome P450 Substrates — Tadalafil is not expected to cause clinically significant inhibition or induction of the clearance of drugs metabolized by cytochrome P450 (CYP) isoforms.
CYP1A2 (e.g. Theophylline) — Tadalafil (10 mg once per day) had no significant effect on the pharmacokinetics of theophylline. When tadalafil was administered to subjects taking theophylline, a small augmentation (3 beats per minute) of the increase in heart rate associated with theophylline was observed.
CYP2C9 (e.g. Warfarin) — Tadalafil (10 mg and 20 mg once per day) had no significant effect on exposure (AUC) to S-warfarin or R-warfarin, nor did tadalafil affect changes in prothrombin time induced by warfarin.
CYP3A4 (e.g. Midazolam, Lovastatin or Bosentan) — Tadalafil (10 mg and 20 mg once per day) had no significant effect on exposure (AUC) to midazolam or lovastatin. Tadalafil (40 mg once per day) had no clinically significant effect on exposure (AUC and Cmax) of bosentan, a substrate of CYP2C9 and CYP3A4, or its metabolites.
P-glycoprotein (e.g. Digoxin) — Coadministration of tadalafil (40 mg once per day) for 10 days did not have a significant pharmacokinetics of digoxin (0.25 mg/day) in healthy subjects.
9.5 Drug-Food Interactions
When OPSYNVI® was administered to healthy subjects with a high-fat meal, no effect of food on the pharmacokinetics of macitentan was observed and the AUC for tadalafil remained unchanged, while Cmax increased by 45%. This increase in Cmax of tadalafil is not considered clinically significant (see 4 DOSAGE AND ADMINISTRATION).
Grapefruit juice being a weak inhibitor of CYP3A4 gut wall metabolism, may give rise to modest increases in plasma levels of tadalafil.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
OPSYNVI® combines two oral agents with synergistic mechanisms of action to improve pulmonary arterial hypertension: macitentan, an endothelin receptor antagonist, and tadalafil, a PDE5 inhibitor. As OPSYNVI® contains both macitentan and tadalafil, the mechanism of action of each component should be considered.
Macitentan
Endothelin (ET)-1 and its receptors (ETA and ETB) mediate a variety of deleterious effects such as vasoconstriction, fibrosis, proliferation, hypertrophy, and inflammation. In disease conditions such as PAH, the local ET system is upregulated and is involved in vascular hypertrophy and in organ damage.
Macitentan is an orally active, dual ETA and ETB receptor antagonist that prevents the binding of ET-1 to its receptors. Macitentan displays high affinity to and sustained occupancy of the ET receptors in human pulmonary arterial smooth muscle cells and has physicochemical properties favoring penetration into lung tissue. In animal studies, penetration of macitentan in lung tissues was higher in rats with induced pulmonary hypertension compared to normal rats.
In models of pulmonary hypertension, macitentan selectively decreased mean pulmonary arterial pressure without affecting systemic blood pressure, decreased pulmonary arterial hypertrophy and right ventricular remodeling, and significantly increased survival compared to vehicle-treated rats.
Tadalafil
Tadalafil is a potent and selective inhibitor of PDE5, the enzyme responsible for the degradation of cyclic guanosine monophosphate (cGMP). Pulmonary arterial hypertension is associated with impaired release of nitric oxide by the vascular endothelium and consequent reduction of cGMP concentrations within the pulmonary vascular smooth muscle. PDE5 is the predominant phosphodiesterase in the pulmonary vasculature. Inhibition of PDE5 by tadalafil increases the concentrations of cGMP resulting in relaxation of the pulmonary vascular smooth muscle cell and vasodilation of the pulmonary vascular bed.
10.2 Pharmacodynamics
As OPSYNVI® contains macitentan and tadalafil, the pharmacodynamic effects of each component should be considered.
Macitentan
In healthy subjects, macitentan dose-dependently increased plasma ET-1 concentrations at single and multiple doses.
Cardiac Electrophysiology: In a randomized, placebo-controlled four-way crossover study with a positive control in healthy subjects, repeated doses of 10 mg and 30 mg macitentan had no significant effect on the QTc interval.
Tadalafil
Effects on Blood Pressure and Heart Rate
Tadalafil 20 mg administered to healthy male subjects produced no significant difference compared to placebo in supine systolic and diastolic blood pressure (difference in the mean maximal decrease of 1.6/0.8 mm Hg, respectively) and in standing systolic and diastolic blood pressure (difference in the mean maximal decrease of 0.2/4.6 mm Hg, respectively). In addition, there was no significant effect on heart rate.
Nitrates — In clinical pharmacology studies, tadalafil (5 to 20 mg) was shown to potentiate the hypotensive effect of nitrates. Therefore, the use of tadalafil in patients taking any form of nitrates is contraindicated (see 2 CONTRAINDICATIONS).
Antihypertensives —When tadalafil and certain oral antihypertensive medications (amlodipine, enalapril, metoprolol, bendrofluazide, angiotensin II receptor blockers) were assessed in drug interaction studies, tadalafil 10 mg or 20 mg doses did not result in clinically significant augmentation of the antihypertensive effects of those medications (see 9 DRUG INTERACTIONS). Analysis of Phase 3 clinical trial data also showed no difference in adverse events in patients taking tadalafil with or without antihypertensive medications.
Alpha-Blockers — The potential hemodynamic interactions of tadalafil with a non-selective alpha-blocker (doxazosin 4 mg and 8 mg), a selective [1A] alpha-blocker (tamsulosin 0.4 mg) and a selective [1] alpha-blocker (alfuzosin 10 mg) were investigated in randomized, double-blind, crossover design studies. Blood pressure (BP) and heart rate were recorded before dosing and for 24 hours after dosing.
Tadalafil 20 mg augmented the hypotensive effect of 8 mg doxazosin by producing a mean maximal decrease in standing systolic BP (SBP) that was significantly greater than placebo (a mean difference of 9.8 mm Hg). Analysis of BP outliers showed that the number of subjects with a standing SBP of less than 85 mm Hg was greater after doxazosin plus tadalafil (28%) versus doxazosin plus placebo (6%). A further clinical pharmacology study was performed in order to investigate the lower dose of 4 mg doxazosin. The changes produced in that study were comparable to those observed in the earlier study. An additional study carried out with doxazosin (up to 4 mg daily) added to tadalafil (5 mg daily) also showed an augmentation of response, and symptoms associated with a decrease in blood pressure.
In subjects on tamsulosin, tadalafil 10 mg and 20 mg produced mean maximal decreases in standing SBP that were similar to placebo (mean difference of 1.7 and 2.3 mm Hg, respectively). No subject taking tamsulosin had a decrease in standing SBP less than 85 mm Hg. An additional study carried out with tamsulosin (0.4 mg) added to tadalafil (5 mg daily) also showed similar results with only two of the 37 subjects showing significantly low systolic and diastolic blood pressure following the administration of tadalafil and tamsulosin. In subjects receiving alfuzosin, tadalafil 20 mg also produced a maximal decrease in SBP that was not significantly different from that after placebo (mean difference of 4.35 mm Hg). One subject taking alfuzosin had an asymptomatic SBP of less than 85 mm Hg.
No vasodilatory adverse events were observed when tadalafil was administered with tamsulosin or alfuzosin. Dizziness, vertigo and syncope were reported following administration of tadalafil with doxazosin.
Effects on Other Cardiac/Hemodynamic Parameters
In patients with stable coronary artery disease (CAD) and demonstrable ischemia with exercise, tadalafil 10 mg was non-inferior to placebo with respect to effect on time to ischemia. In a separate double-blind, placebo-controlled study to evaluate the effects of tadalafil on myocardial perfusion in patients with CAD, tadalafil 20 mg had no significant effect on myocardial blood flow, both at rest and during pharmacological stress with dobutamine.
Tadalafil at doses up to 500 mg did not significantly change cardiac output and did not significantly impact patients’ hemodynamic response to exercise.
No tadalafil-related changes in electrocardiographic measures, including QTc interval, were observed following administration of tadalafil single doses up to 500 mg and multiple doses of up to 100 mg once-daily for 21 days, to healthy subjects or patients with ED. ECGs were obtained pre- and post-dose, spanning the period from the expected Tmax of tadalafil (2 hours) to the expected Tmax of the primary metabolite (methylcatechol glucuronide, 24 hours).
The effect of a single 100-mg dose of tadalafil (2.5 times the recommended dose) on the QT interval was evaluated at the time of peak tadalafil concentration in a randomized, double-blinded, placebo, and active (intravenous ibutilide) -controlled crossover study in 90 healthy males aged 18 to 53 years. The mean change in QTc (Fridericia QT correction) for tadalafil, relative to placebo, was 3.5 milliseconds (two-sided 90% CI=1.9, 5.1). The mean change in QTc (Individual QT correction) for tadalafil, relative to placebo, was 2.8 milliseconds (two-sided 90% CI=1.2, 4.4). In this study, the mean increase in heart rate associated with a 100-mg dose of tadalafil compared to placebo was 3.1 beats per minute.
In clinical pharmacology studies, tadalafil 10 mg and 20 mg had no clinically significant effect on acetylsalicylic acid-induced prolongation of bleeding time or warfarin-induced changes in prothrombin time (See 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
Effects on Vision
In a study to assess the effects of a single dose of tadalafil 40 mg on vision, no impairment of colour discrimination (blue/green) was detected using the Farnsworth-Munsell 100-hue test. This finding is consistent with the low affinity of tadalafil for PDE6 compared to PDE5 (see 10 CLINICAL PHARMACOLOGY, 10.1 Mechanism of Action). In addition, no effects were observed on visual acuity, electroretinograms, intraocular pressure, or pupillometry. Across all clinical studies with tadalafil 10 mg or 20 mg, reports of changes in colour vision were rare (< 0.1% of patients).
Effects on Sperm Characteristics
Three studies were conducted in men, ages 45-70 years, to assess the potential effect on spermatogenesis of tadalafil 10 mg (one 6-month study) and 20 mg (one 6-month and one 9-month study) administered once daily. In all 3 studies, there were no adverse effects on sperm morphology or sperm motility. There were also no significant changes in mean concentrations of the reproductive hormones, testosterone, luteinizing hormone or follicle-stimulating hormone with either 10 mg or 20 mg of tadalafil compared to placebo. No decrease in sperm concentration was observed in the study of tadalafil 20 mg taken for 6 months. In the study of tadalafil 10 mg for 6 months and the study of tadalafil 20 mg for 9 months, results showed a statistically significant decrease in mean sperm concentration relative to placebo. The clinical relevance of this to human fertility is unknown. In the 9 month study (n=125 [tadalafil 20 mg], n=128 [placebo]), decreases in sperm concentration were in a few patients (but not all) associated with higher ejaculatory frequency, which may have resulted from tadalafil-related improvement in sexual function.
Exposure-Response Relationship
An analysis of tadalafil exposure and 6-minute walk distance in subjects with PAH in the Phase 3 Study, generated a model-predicted increase in 6-minute walk distance from baseline of 35.6 meters (30.5, 39.6 meters) and 38.09 meters (33.52, 43.20 meters) at 16 weeks of 20 mg and 40 mg daily administration, assuming the median (10th and 90th percentiles) steady-state tadalafil exposures.
10.3 Pharmacokinetics
Bioequivalence of macitentan and tadalafil was demonstrated following a single dose of macitentan 10 mg and tadalafil 40 mg as the OPSYNVI® fixed dose combination tablet or concomitantly as a single dose of OPSUMIT® (macitentan) tablet and ADCIRCA® (tadalafil) in healthy subjects under fasting conditions (N=162). As OPSYNVI® contains macitentan and tadalafil, the pharmacokinetic properties of the individual components should be considered.
Macitentan
The pharmacokinetics of macitentan and its active metabolite have mainly been documented in healthy subjects. A cross study comparison shows that the exposures to macitentan and its active metabolite in patients with PAH are similar to those observed in healthy subjects. Trough plasma concentrations of macitentan in PAH patients were not influenced by the severity of the disease.
After repeated administration of doses of ≤30 mg, the pharmacokinetics of macitentan are dose proportional.
Steady-state conditions of macitentan and its active metabolite are achieved after 3 days and 7 days, respectively. Peak plasma concentrations of macitentan were reached 8 hours after administration and the AUC0-24 and Cmax of macitentan were dose-proportional over the tested dose range (1 to 30 mg once daily). As anticipated from the observed t1/2 of 16 hours and 48 hours for macitentan and its active metabolite, respectively, the accumulation of macitentan was minimal (approximately 1.5-fold) whereas that of the active metabolite was about 8.5-fold. Macitentan and its circulating metabolites are highly bound (≥99%) to plasma proteins, mainly albumin, in all species, including man.
Absorption:
Maximum plasma concentrations of macitentan are achieved about 8 hours after administration. Thereafter, plasma concentrations of macitentan and its active metabolite decreased slowly, with an apparent elimination half-life of approximately 16 hours and 48 hours, respectively.
In healthy subjects, the exposure to macitentan and its active metabolite is unchanged in the presence of food and, therefore, macitentan may be taken with or without food.
Distribution:
Macitentan and its active metabolite ACT-132577 are well distributed into tissues as indicated by an apparent volume of distribution (Vss/F) of approximately 50 L and 40 L, respectively. Macitentan and its active metabolite are highly bound to plasma proteins (>99%) primarily to albumin and to a lesser extent to alpha1-acid glycoprotein.
Metabolism:
Macitentan has four primary metabolic pathways. Macitentan primarily undergoes oxidative depropylation of the sulfamide to form a pharmacologically active metabolite. This reaction is dependent on the cytochrome P450 system, mainly CYP3A4 with a minor contribution of CYP2C19. Very small amounts of the active metabolite are also formed by CYP2C8 and CYP2C9. The active metabolite circulates in human plasma and may contribute to the overall pharmacological effect.
Other metabolic pathways yield products without pharmacological activity. For these pathways, CYP2C9 plays a predominant role with minor contributions from CYP2C8, CYP2C19 and CYP3A4.
Elimination:
Macitentan is excreted only after extensive metabolism. The major excretion route is via urine, accounting for about 50% of the dose.
Tadalafil
Over a dose range of 2.5 to 20 mg, tadalafil exposure (AUC) increases proportionally with dose in healthy subjects. Between 20 to 40 mg, an approximate 1.5-fold greater AUC is observed indicating a less than proportional increase in exposure over the entire dose range of 2.5 to 40 mg. During tadalafil 20- and 40-mg once-daily dosing, steady-state plasma concentrations are attained within 5 days, and exposure is approximately 1.3-fold than that after a single dose.
Phosphodiesterases are a diverse family of enzymes having different tissue distributions and functions, but which all ultimately act to hydrolyze cyclic nucleotides, thereby terminating their actions. There are eleven known phosphodiesterase classes, many with subtypes identified by structure and function. PDE5 is a major cGMP-hydrolyzing enzyme in the pulmonary vasculature.
Studies in vitro have shown that tadalafil is a potent inhibitor of PDE5. PDE5 is an enzyme found in pulmonary vascular smooth muscle, visceral smooth muscle, corpus cavernosum, skeletal muscle, platelets, kidney, lung, cerebellum, and pancreas. The effect of tadalafil is more selective on PDE5 than on other phosphodiesterases. Tadalafil is >10,000-fold more selective for PDE5 than for PDE1, PDE2, PDE4, and PDE7 enzymes, which are found in the heart, brain, blood vessels, liver, and other organs. Tadalafil is > 10,000-fold more selective for PDE5 than for PDE3, an enzyme found in the heart and blood vessels. This selectivity for PDE5 over PDE3 is important because PDE3 is an enzyme involved in cardiac contractility. Additionally, tadalafil is approximately 700-fold more potent for PDE5 than for PDE6, an enzyme which is found in the retina and is responsible for phototransduction. Tadalafil is also > 9000-fold more potent for PDE5 than for PDE8 through PDE10. Tadalafil is 14-fold more potent for PDE5 than for PDE11A1 and 40-fold more potent for PDE5 than for PDE11A4, two of the four known forms of PDE11. PDE11 is an enzyme found in human prostate, testes, skeletal muscle and in other tissues. In vitro, tadalafil inhibits human recombinant PDE11A1 and, to a lesser degree, PDE11A4 activities at concentrations within the therapeutic range. The physiological role and clinical consequence of PDE11 inhibition in humans have not been defined.
Absorption:
Tadalafil is readily absorbed after oral administration and the mean maximum observed plasma concentration (Cmax) is achieved at a median time of 4 hours after dosing. Absolute bioavailability of tadalafil following oral dosing has not been determined.
The rate and extent of absorption of tadalafil are not influenced by food, thus tadalafil may be taken with or without food.
Distribution:
The mean apparent volume of distribution is approximately 77 L at steady state, indicating that tadalafil is distributed into tissues. At therapeutic concentrations, 94% of tadalafil in plasma is bound to proteins. Protein binding is not affected by impaired renal function.
Metabolism:
Tadalafil is predominantly metabolised by the cytochrome P450 (CYP) 3A4 isoform. The major circulating metabolite is the methylcatechol glucuronide. This metabolite is at least 13,000-fold less potent than tadalafil for PDE5. Consequently, it is not expected to be clinically active at observed metabolite concentrations.
Elimination:
The mean oral clearance for tadalafil is 3.4 L/h at steady state and the mean terminal half-life is 15 hours in healthy subjects. Tadalafil is excreted predominantly as inactive metabolites, mainly in the faeces (approximately 61% of the dose) and to a lesser extent in the urine (approximately 36% of the dose).
Population pharmacokinetics: In patients with pulmonary hypertension not receiving concomitant bosentan, the average tadalafil exposure at steady-state following 40 mg was 26% higher when compared to those of healthy volunteers. There were no clinically relevant differences in Cmax compared to healthy volunteers. The results suggest a lower clearance in patients with pulmonary hypertension compared to healthy volunteers.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of OPSYNVI® in pediatrics have not been studied. However, data are available for macitentan. Tadalafil has not be evaluated in individuals less than 18 years old.
Health Canada has not authorized an indication for use of OPSYNVI® in pediatric patients.
Macitentan
The pharmacokinetics of macitentan and its metabolite ACT-132577 were assessed in 16 pediatric patients (5 were 6 to 11 years old and 11 were adolescents 12 to 17 years old) with pulmonary arterial hypertension. Pediatric patients in the ≥ 25 kg and < 50 kg body weight subgroup were administered 7.5 mg once daily dose of macitentan (8 patients). A dose of 10 mg once daily of macitentan was administered to pediatric patients with a body weight of ≥ 50 kg (8 patients).
Macitentan exposure, based on Cmax and AUCτ was in a similar range regardless of weight and age. Compared to adult data from 20 patients treated with macitentan 10 mg once daily in Study AC-055-303 (SERAPHIN PK substudy), macitentan exposure appeared to be marginally lower in children as compared to adults while there were no indications of differences in exposure to its metabolite ACT-132577 in children.
Tadalafil
Tadalafil has not been evaluated in individuals less than 18 years old.
Geriatrics: The pharmacokinetics of OPSYNVI® in elderly patients has not been studied.
Macitentan
There is no clinically relevant effect of age, gender or race on the pharmacokinetics of macitentan and its active metabolite.
Tadalafil
The mean AUC value (4881 mcg·h/L for 10 mg dose) in male subjects aged 65 to 78 years was approximately 25% higher than AUC (3896 mcg·h/L) for subjects aged 19 to 45 years, while age had negligible effect on Cmax values. This effect of age is not clinically significant and does not require a dose adjustment (See 7.1.4 Geriatric).
Hepatic Insufficiency: The pharmacokinetics of OPSYNVI® have not been investigated in patients with hepatic impairment. However, data are available for the individual components of OPSYNVI®.
Macitentan
Exposure to macitentan was decreased by 21%, 34% and 6% and for the active metabolite by 20%, 25% and 25% in subjects with mild, moderate or severe hepatic impairment, respectively. This decrease is not considered clinically relevant.
Tadalafil
In a clinical pharmacology study using tadalafil 10 mg, tadalafil exposure (AUC) in subjects with mild and moderate hepatic impairment (Child-Pugh Class A and B) was comparable to exposure in healthy subjects (see 4 DOSAGE AND ADMINISTRATION).
Patients with severe hepatic cirrhosis (Child-Pugh Class C) have not been studied, and therefore dosing of tadalafil in these patients is not recommended.
Renal Insufficiency: The pharmacokinetics of OPSYNVI® have not been investigated in patients with renal impairment. However, data are available for the individual components of OPSYNVI®.
Macitentan
Exposure to macitentan and its active metabolite was increased by 1.3- and 1.6-fold, respectively, in patients with severe renal impairment. This increase is not considered clinically relevant.
Tadalafil
In clinical pharmacology studies using single-dose tadalafil 5 to 20 mg, tadalafil exposure (AUC) approximately doubled in subjects with mild (creatinine clearance 51 to 80 mL/min) or moderate (creatinine clearance 31 to 50 mL/min) renal insufficiency, and in subjects with end-stage renal disease on dialysis. In dialysis patients, Cmax was 41% higher than that observed in healthy subjects. Hemodialysis contributed negligibly to tadalafil elimination. (See 7 WARNINGS AND PRECAUTIONS, Renal and 4 DOSAGE AND ADMINISTRATION).
Other populations: The pharmacokinetics of OPSYNVI® have not been investigated in other populations. However, data are available for the individual components of OPSYNVI®.
Tadalafil use in patients with diabetes
Tadalafil exposure (AUC 3454 mcg·h/L for a 10 mg dose) in patients with diabetes was 19% lower, and the mean maximum plasma concentration (Cmax of 184 mcg/L) was 5% lower than that observed in healthy subjects. This difference in exposure does not require a dose adjustment.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15ºC – 30ºC in the original package.
Keep out of the sight and reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
This information is not available for this drug product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper Name | Macitentan | Tadalafil |
|---|---|---|
| Chemical Name | N-[5-(4-Bromophenyl)-6-[2-[(5-bromo-2-pyrimidinyl)oxy]ethoxy]-4 pyrimidinyl]- N’-propylsulfamide | pyrazino[1’,2’:1,6]pyrido[3,4-b] indole-1,4-dione, 6-(1,3-benzodioxol-5-yl)-2,3,6,7,12,12a- hexahydro-2-methyl-, (6R,12aR) |
| Molecular Formula | C19H20Br2N6O4S | C22H19N3O4 |
| Molecular Mass | 588.27 | 389.41 |
| Structural Formula | ||
| Physiochemical Properties | Macitentan is a crystalline powder that is insoluble in water. In the solid state macitentan is very stable, is not hygroscopic, and is not light sensitive. | Tadalafil is a crystalline solid that is practically insoluble in water and very slightly soluble in ethanol. |
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The efficacy of OPSYNVI® is based on the established efficacy of the individual components. The efficacy associated with the individual component should be considered.
Trial Design and Study Demographics: Macitentan
A multicenter, double-blind, placebo-controlled, parallel-group, event-driven, Phase 3 outcome study (AC-055-302/SERAPHIN) was conducted in 742 patients with symptomatic PAH, who were randomized to three treatment groups (placebo [n=250], 3 mg [n=250] or 10 mg [n=242] of macitentan once daily), to assess the long-term effect on morbidity or mortality. At baseline, the majority of enrolled patients (64%) were treated with a stable dose of specific therapy for PAH, either oral phosphodiesterase inhibitors (61%) and/or inhaled/oral prostanoids (6%). The primary study endpoint was the time to first occurrence of a morbidity or mortality event, up to end of treatment (EOT), defined as death, or atrial septostomy, or lung transplantation, or initiation of intravenous (i.v.) or subcutaneous (s.c.) prostanoids, or other worsening of PAH. Other worsening of PAH was defined as the presence of all of the three following components: a sustained decrease in 6-minute walk distance (6MWD) of at least 15% from baseline; worsening of PAH symptoms (worsening of WHO FC or right heart failure); and need for new treatment for
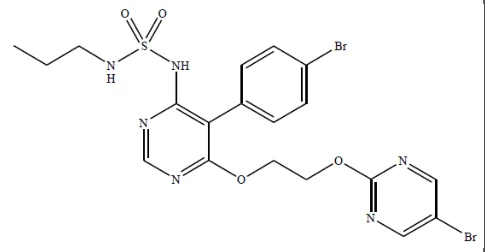 | 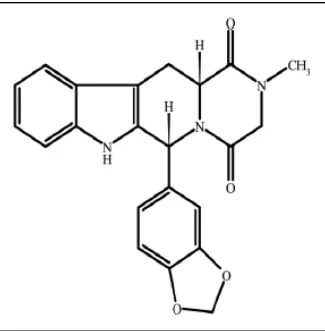 |
PAH. All events were confirmed by an independent adjudication committee, blinded to treatment allocation.
The median treatment duration was 101, 116, and 118 weeks in the placebo, macitentan 3 mg, and 10 mg groups, respectively, up to a maximum of 188 weeks on macitentan. Efficacy was evaluated up to the end of double-blind treatment (EOT). The EOT either coincided with end of study (EOS) for patients who completed the study as scheduled or occurred earlier in case of premature discontinuation of study drug. For those patients who stopped treatment prior to EOS, PAH therapy, including macitentan, may have been initiated. All patients were followed up to EOS for vital status. The ascertainment rate for vital status at the EOS was greater than 95%.
The mean age of all patients was 46 years (range 12–85 years of age) with the majority of subjects being Caucasian (55%) and female (77%). Approximately 52%, 46%, and 2% of patients were in WHO FC II, III, and IV, respectively.
Idiopathic or heritable PAH was the most common etiology in the study population (57%), followed by PAH due to connective tissue disorders (31%), PAH associated with congenital heart disease with shunts (8%), and PAH associated with other etiologies (drugs and toxins [3%] and HIV [1%]).
Trial Design and Study Demographics: Tadalafil
A randomized, double-blind, 16 week placebo-controlled study was conducted in 405 patients with pulmonary arterial hypertension (PAH, defined as a resting mean pulmonary artery pressure (mPAP) ≥ 25 mmHg, pulmonary capillary wedge pressure (PCWP) ≤ 15 mmHg, and pulmonary vascular resistance (PVR) ≥ 3 Wood units via right heart catheterization). Allowed background therapy included bosentan (maintenance dosing up to 125 mg twice daily) and chronic anticoagulation, whereas excluded therapy consisted of a prostacyclin or analogue, L-arginine, phosphodiesterase inhibitor, or other chronic PAH medication.
Subjects were randomly assigned to 1 of 5 treatment groups (tadalafil 2.5, 10, 20, 40 mg, or placebo) in a 1:1:1:1:1 ratio. Subjects were at least 12 years of age and had a diagnosis of PAH that was idiopathic, related to collagen disease, anorexigen use, human immunodeficiency virus (HIV) infection, associated with an atrial-septal defect, or associated with surgical repair of at least 1 year in duration of a congenital systemic to pulmonary shunt (for example, ventricular septal defect, patent ductus arteriosus). Patients with a history of left-sided heart disease, severe renal insufficiency or pulmonary hypertension related to conditions other than specified in the inclusion criteria were not eligible for enrolment.
The mean age of all subjects was 54 years (range 14 - 90 years) with the majority of subjects being Caucasian (80.5%) and female (78.3%). Pulmonary arterial hypertension (PAH) etiologies were predominantly idiopathic PAH (61.0%) and related to collagen vascular disease (23.5%). More than half (53.3%) of the subjects in the study were receiving concomitant bosentan therapy. The majority of subjects had a World Health Organization (WHO) Functional Class III (65.2%) or II (32.1%). The mean baseline 6-minute walk distance (6-MWD) was 343.6 meters. There were no major differences among treatment groups. Of the 405 subjects, 341 completed the study. The most common reason for early discontinuation was adverse events (AEs).
14.2 Study Results
Study Results: Macitentan
Treatment with macitentan 10 mg resulted in a 45% relative risk reduction (hazard ratio [HR] 0.55; 97.5% confidence interval [CI] 0.39–0.76; logrank p < 0.0001) in the occurrence of a primary endpoint event up to EOT compared to placebo. The proportion of patients without an event at 3 years was 63.2% in macitentan 10 mg compared to 47.0% in placebo, corresponding to an absolute risk reduction of 16.2% at 3 years (Figure 1). The beneficial effect of macitentan 10 mg was primarily attributable to a reduction in other PAH worsening events (the concurrent presence of sustained deterioration in 6MWD and worsening of PAH symptoms and need for new PAH treatment). The treatment effect was established early and sustained for a median duration of 2 years.
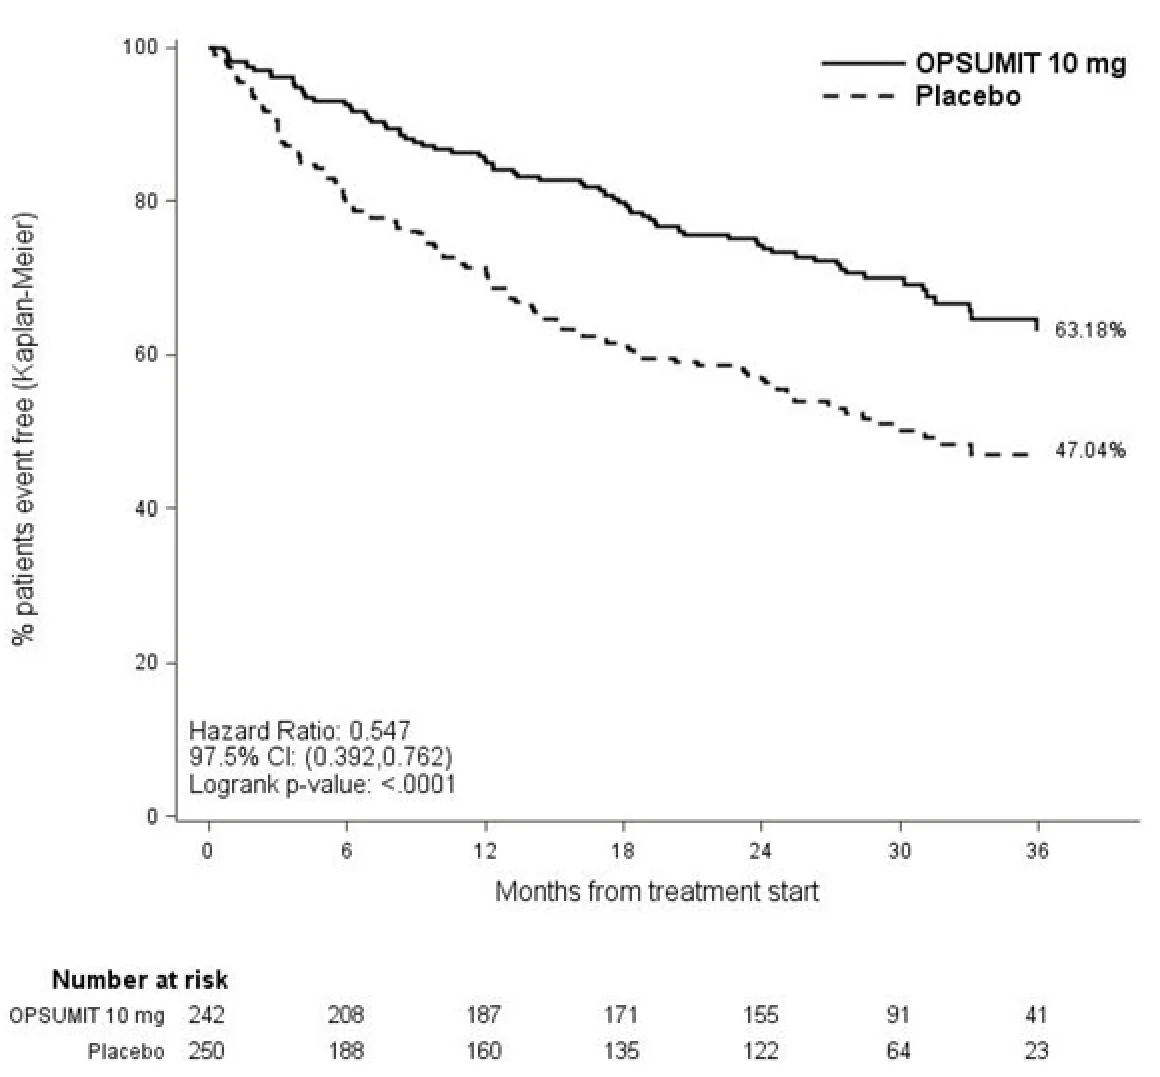
Figure 1: Kaplan-Meier Estimates of Primary Endpoint Events up to EOT in SERAPHIN*
*Note: The treatment response on the primary endpoint was almost entirely attributable to an effect on morbidity.
During treatment 46.4% and 31.4% of the patients in the placebo and macitentan 10 mg dose groups, respectively, experienced a morbidity or mortality primary endpoint event, with worsening of PAH reported as the most common first event in the placebo (37.2%) and macitentan 10 mg (24.4%) treatment groups. Other events reported that contributed to the primary endpoint included death (6.8% placebo, 6.6% macitentan 10 mg,) and i.v./s.c. prostanoid initiation (2.4% placebo, 0.4% macitentan 10 mg).
Consistent efficacy of macitentan 10 mg on the primary endpoint was seen across subgroups of age, sex, ethnic origin, geographical region, etiology, by monotherapy or in combination with another PAH therapy and WHO FC.
Treatment with macitentan 10 mg in monotherapy resulted in a 55% relative risk reduction (HR 0.45, 95% CI 0.28-0.72; logrank p=0.0007) in the occurrence of a primary endpoint event compared to placebo. The proportion of patients without an event at 3 years was 64.4% in macitentan 10 mg compared to 43.5% in placebo, corresponding to an absolute risk reduction of 20.9% (Figure 2).
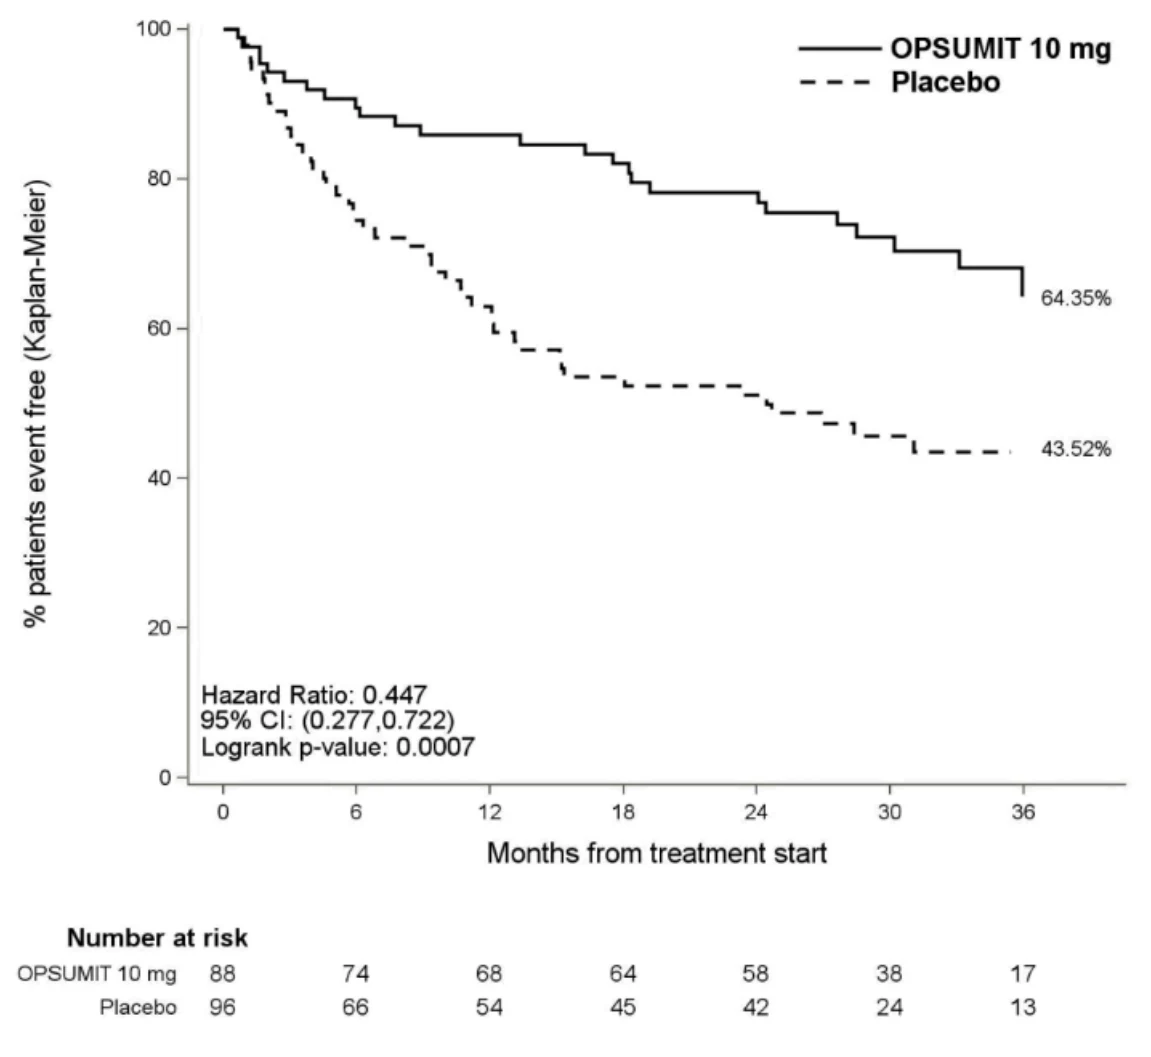
Figure 2: Kaplan-Meier Estimates of Primary Endpoint Events up to EOT; Monotherapy at Baseline in SERAPHIN*
*Note: The treatment response on the primary endpoint was almost entirely attributable to an effect on morbidity.
Treatment with macitentan 10 mg in combination with another PAH therapy resulted in a 38% relative risk reduction (HR 0.62, 95% CI 0.43 0.89; logrank p = 0.0094) in the occurrence of a primary endpoint event. The proportion of patients without an event at 3 years was 62.6% in macitentan 10 mg compared to 48.6% in placebo, corresponding to an absolute risk reduction of 14.0% (Figure 3).
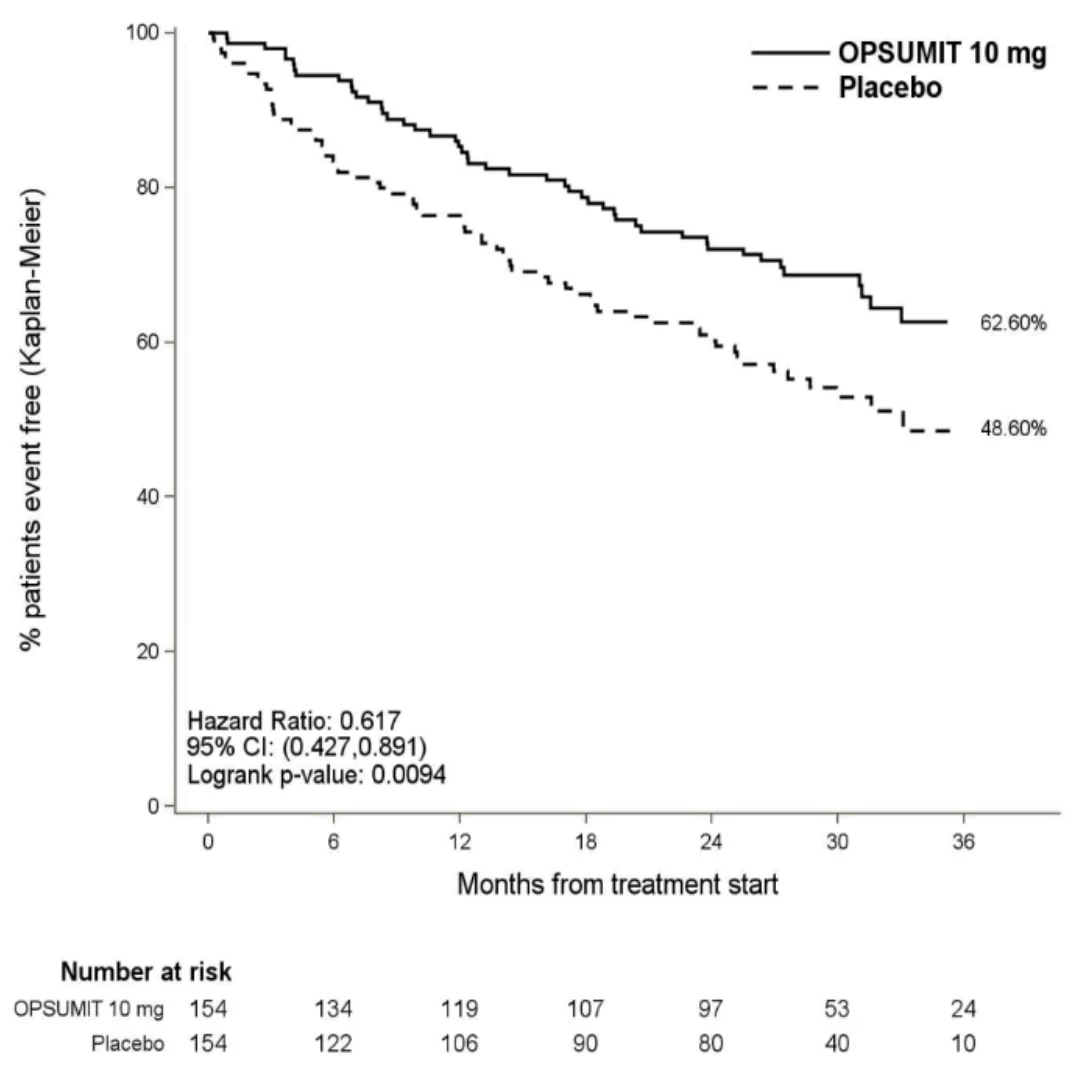
Figure 3: Kaplan-Meier Estimates of Primary Endpoint Events up to EOT; Combination PAH Therapy* at Baseline in SERAPHIN†
*At baseline, patients were treated with a stable dose of either a phosphodiesterase inhibitor or an inhaled/oral prostanoid.
†Note: The treatment effect in the primary endpoint was almost entirely attributable to an effect on morbidity.
Treatment with macitentan 10 mg resulted in a 50% relative risk reduction (HR 0.50, 97.5% CI 0.34-0.75; logrank p<0.0001) in the occurrence of PAH related death or hospitalization for PAH, up to EOT compared to placebo. The proportion of patients without a PAH related death or hospitalization for PAH at 3 years was 70.6% in macitentan 10 mg compared to 55.4% in placebo, corresponding to an absolute risk reduction of 15.2% (Figure 4).
Treatment with macitentan 10 mg resulted in fewer PAH related hospitalizations per year (0.3 and 0.7 with macitentan 10 mg and placebo, respectively) and for all causes (0.5 and
1.0 with macitentan 10 mg and placebo, respectively).
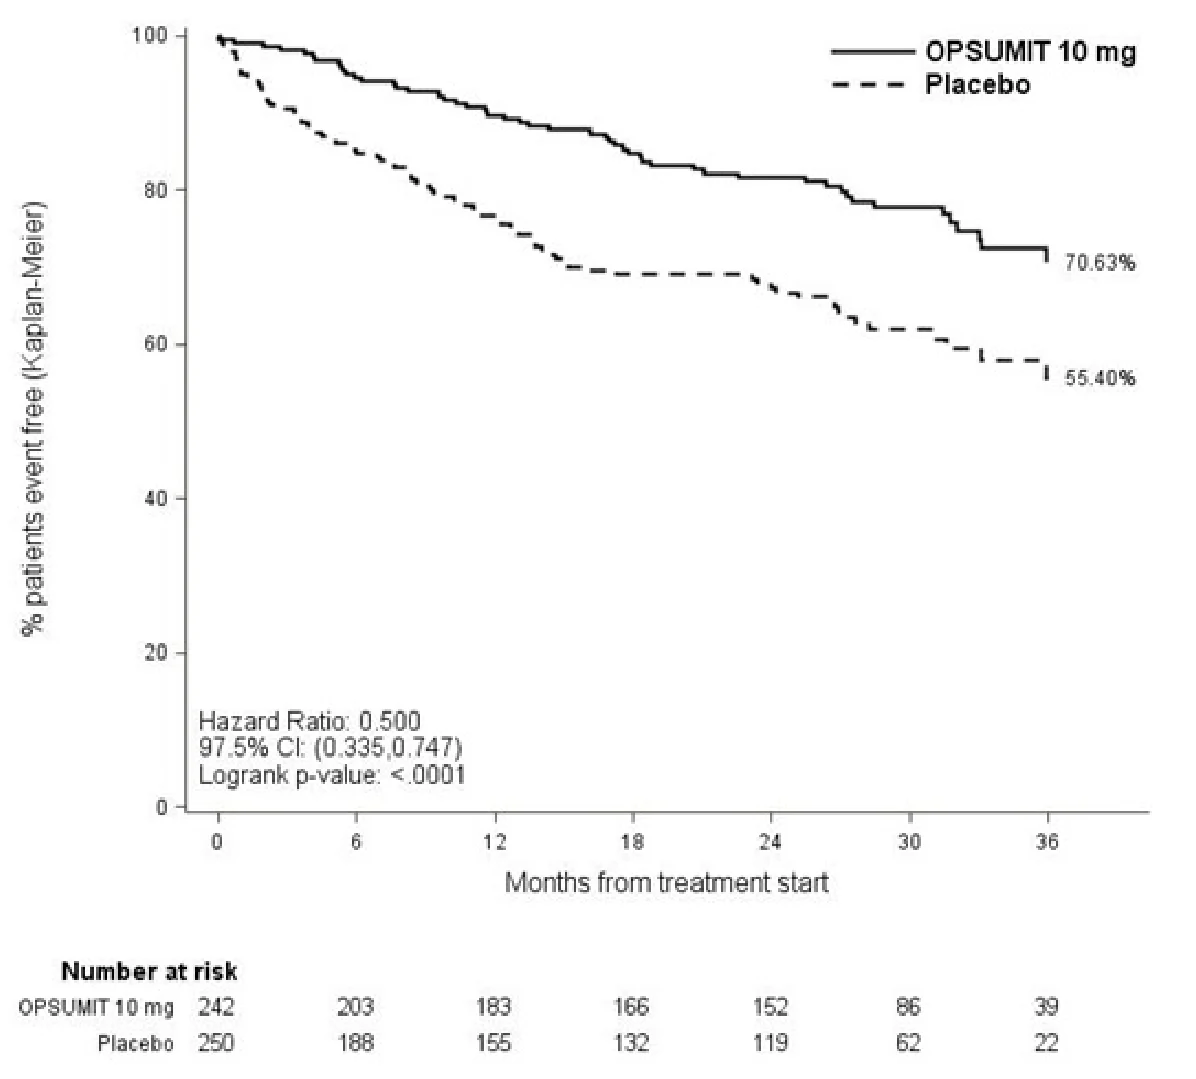
Figure 4: Kaplan-Meier Estimates of Death due to PAH or Hospitalization for PAH up to EOT in SERAPHIN
Treatment with macitentan 10 mg resulted in a 36% relative risk reduction (HR 0.64, 97.5% CI 0.29-1.42; logrank p=0.2037) in the occurrence of death of all causes up to EOT. The proportion of deaths of all causes at 3 years was 10.2% in placebo compared to 6.7% in macitentan 10 mg, corresponding to an absolute risk reduction of 3.5% (Figure 5). The relative risk reduction for death up to EOS was 23% (HR 0.77, 97.5% CI 0.46-1.28; logrank p=0.2509). The proportion of deaths of all causes at 3 years was 19.3% in the placebo group compared to 17.1% in the macitentan 10 mg, corresponding to an absolute risk reduction of 2.2%.
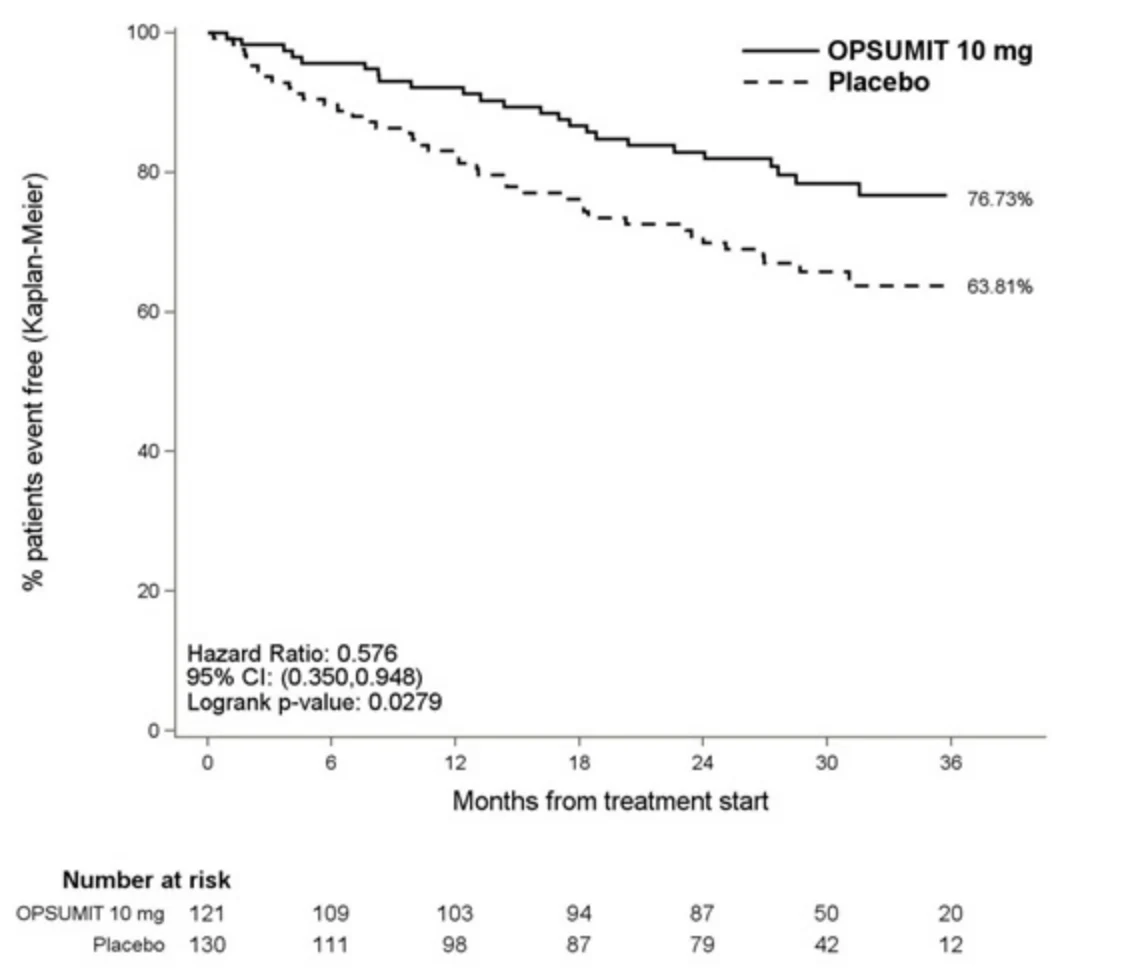
Figure 5: Kaplan-Meier Estimates of Death of all Causes up to EOT in SERAPHIN
Symptomatic and Functional Endpoints
Exercise ability was evaluated as a secondary endpoint. Treatment with macitentan 10 mg at Month 6 resulted in a placebo-corrected mean increase in 6MWD of 22 meters (97.5% CI 3-41; p=0.0078). Evaluation of 6MWD by functional class resulted in a placebo corrected mean increase from baseline to Month 6 in FC III/IV patients of 37 meters (97.5% CI 5- 69; p=0.0088) and in FC I/II of 12 meters (97.5% CI -8-33; p=0.1762). The increase in 6MWD achieved with macitentan was maintained for the duration of the study.
Treatment with macitentan 10 mg led to a 74% higher chance of WHO FC improvement relative to placebo (risk ratio 1.74; 97.5% CI 1.10–2.74; p=0.0063). Treatment with macitentan 10 mg led to an improvement of at least one WHO FC at Month 6 in 22% of patients compared to 13% of patients treated with placebo.
Macitentan 10 mg improved quality of life assessed by the Short-form 36 (SF-36) questionnaire. Improvements compared to placebo were observed in 7 out of 8 domains at 6 months, including physical functioning, role-physical, bodily pain, vitality, social functioning, role emotional, and mental health domains of the SF-36 questionnaire.
Hemodynamic Endpoints
Hemodynamic parameters were assessed in a subset of patients (placebo, N=67, macitentan 10 mg, N=57) after 6 months of treatment. Patients treated with macitentan 10 mg achieved a median reduction of 36.5% (CI 21.7–49.2%) in PVR and an increase of 0.58 L/min/m2 (CI 0.28–0.93 L/min/m2) in cardiac index compared to placebo.
Long-Term Treatment of PAH
In long-term follow-up of patients who were treated with macitentan 10 mg in the double-blind / open-label extension studies (N=242), Kaplan-Meier estimates of survival at 1, 2, 3, 4, 5, 6, 7, 8 and 9 years were 95%, 89%, 84%, 78%, 73%, 66%, 63%, 58% and 53% respectively (Figure 6). The median follow-up time was 5.9 years. These uncontrolled observations do not allow comparison with a group not given macitentan and cannot be used to determine the long term-effect of macitentan on mortality.
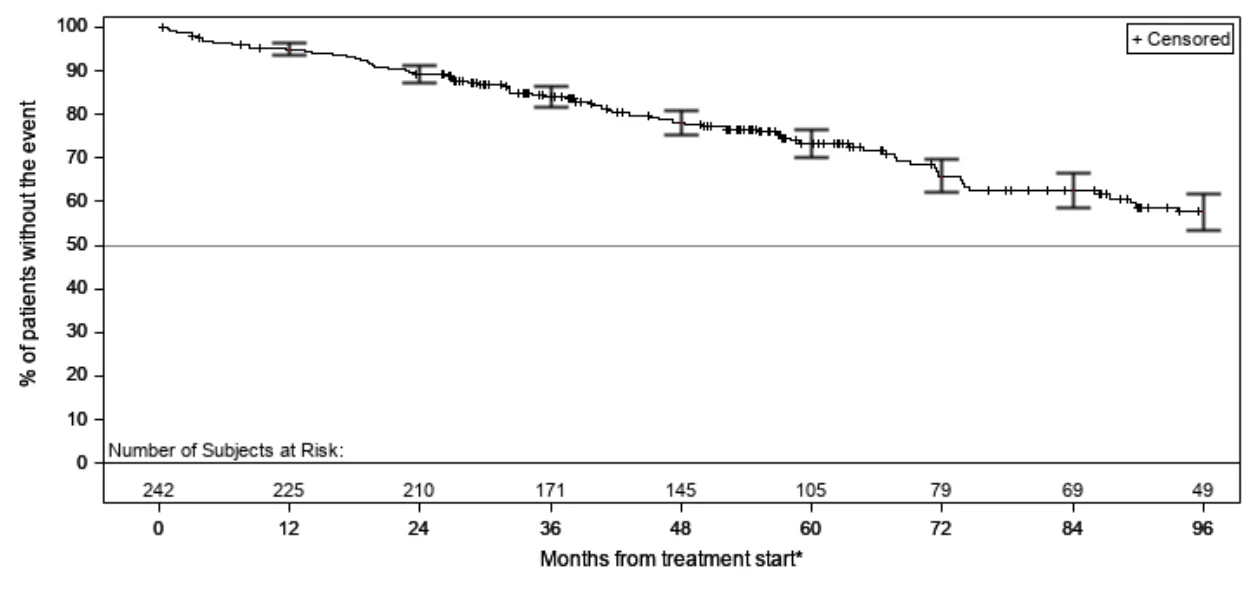
Figure 6: Kaplan-Meier estimates of time to death (all-causes) in long-term follow-up of macitentan treatment
Survival curves are presented up to the time when more than 10% of the subjects are still at risk.
Error bars show Kaplan-Meier estimate ± standard error.
*Treatment start corresponds to the start of double-blind macitentan 10 mg in AC-055-302.
Study Results: Tadalafil
The primary efficacy endpoint was the change from baseline at week 16 in 6-MWD (see Figure 7). In the tadalafil 40 mg treatment group, the placebo-adjusted mean change increase in 6-MWD was 33 meters (95% C.I. 15-50 meters; p=0.0004). The improvement in 6-MWD was apparent at 8 weeks of treatment and then maintained at week 12 and week 16 (p<0.05). Statistical significance in the 6-MWD was demonstrated at week 12 when subjects were asked to delay taking study medication in order to reflect trough drug concentrations.
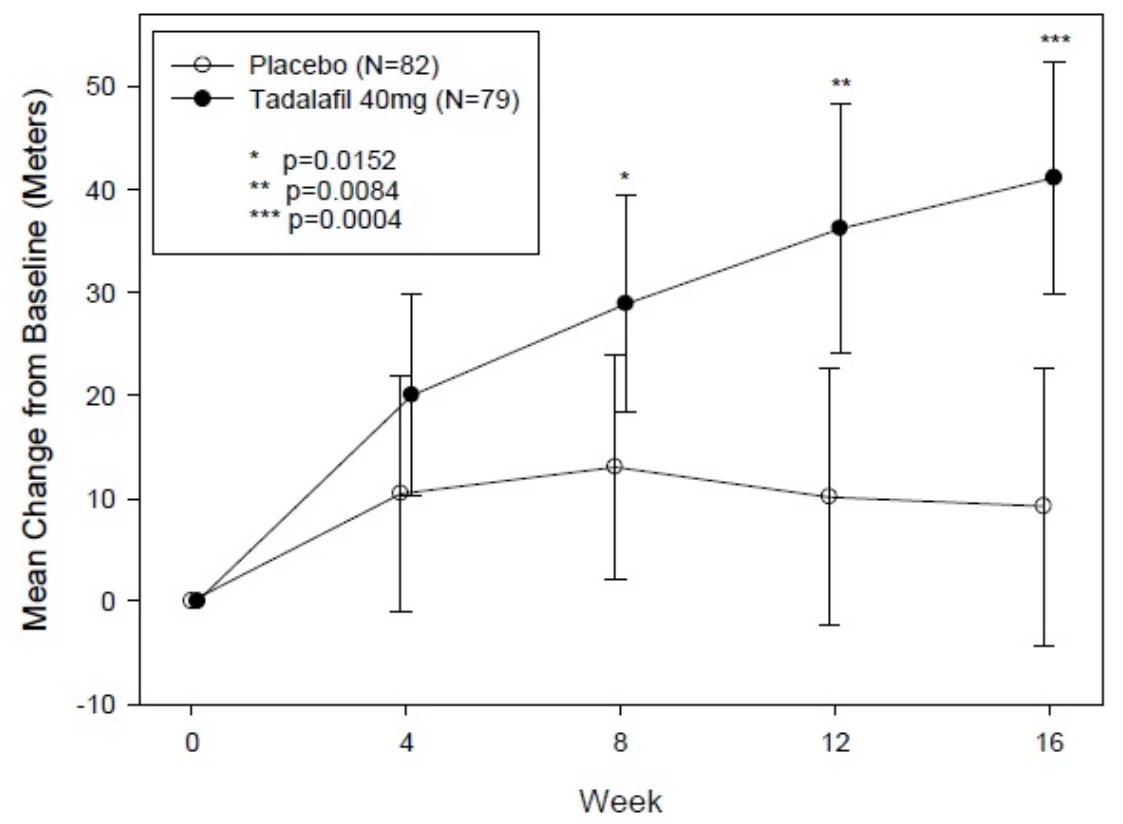
Figure 7: 6-Minute Walk Distance (meters) Mean Change from Baseline, with 95% Confidence Interval
Placebo-adjusted changes in 6-MWD at 16 weeks were evaluated in pre-defined subpopulations (Figure 8) In patients taking only tadalafil 40 mg (i.e., without concomitant bosentan), the placebo-adjusted change in 6-MWD was 44 meters (p<0.01). In patients taking tadalafil 40 mg and concomitant bosentan therapy the placebo adjusted change in 6-MWD was 23 meters (p>0.05).
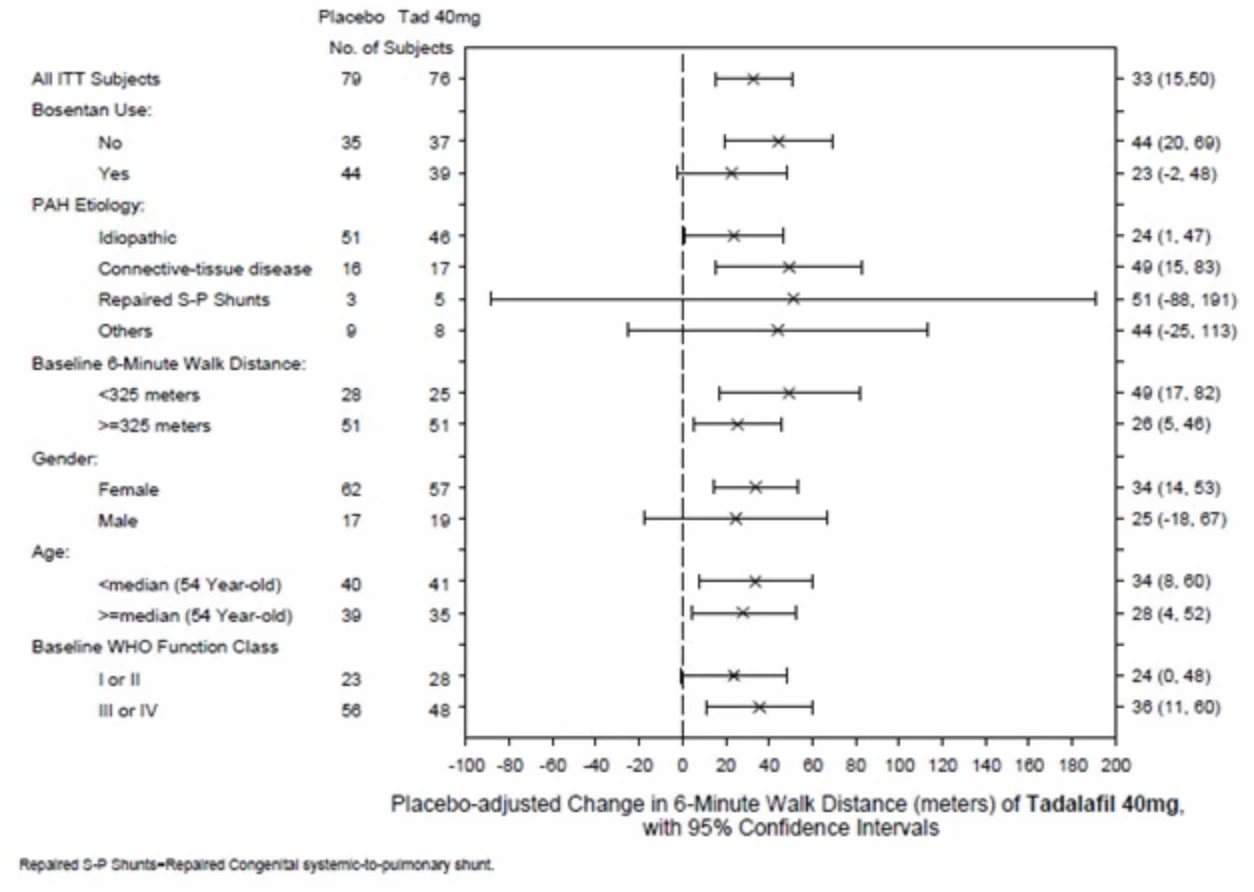
Figure 8: Placebo-adjusted Change in 6-Minute Walk Distance (meters) of Tadalafil 40 mg, with 95% Confidence Intervals
Per the protocol, the secondary endpoints were tested in the order listed in Table 6 with no further inferential testing once a statistically non-significant result was reached. Inferential testing did not process beyond WHO functional Class since this comparison was statistically non-significant. In the tadalafil 40 mg group 23% of subjects improved and 10% worsened their WHO functional class. In the placebo group 21% of subjects improved and 16% worsened their WHO functional class. The probability of having no clinical worsening was 94% with tadalafil 40 mg and 84% with placebo. Based on the number of subjects, this represents a 68% relative risk reduction in the incidence of clinical worsening (95% Confidence Interval 6% to 89%). The changes in the Borg dyspnea scores were small with both placebo and tadalafil 40 mg.
Table 6: Assessment of Secondary Endpoints in Patients with Pulmonary Arterial Hypertension Following a Randomized, Double-Blind, 16-Week Placebo-Controlled Study
Tadalafil 40 mg (n=79) | Placebo (n=82) | |
|---|---|---|
| Change in WHO Functional Class No. (%) | ||
| Improved | 18 (22.8) | 17 (20.7) |
| No Change | 53 (67.1) | 52 (63.4) |
| Worsen | 8 (10.1) | 13 (15.9) |
| Clinical Worseninga | ||
Probability of No Clinical Worsening at Week 16 (95% C.I.) | 0.94 (0.85, 0.98) | 0.84 (0.74, 0.90) |
| Number of patients (%) with Clinical Worsening | 4 (5.1) | 13 (15.9) |
| Change in Bord Dyspneab Score | ||
| Mean (SD) | -0.70 (1.75) | 0.41 (1.89) |
a Clinical worsening was defined as death, lung transplantation, atrial septostomy, hospitalization due to worsening PAH, initiation of new PAH therapy, and worsening WHO functional class.
b A positive change in Borg-Dyspnea score represents a worsening of patient perceived breathlessness during the 6 minute walk.
A statistically significant increase in quality of life, compared to placebo, was demonstrated in the tadalafil 40 mg group in 6 of the 8 SF36 domains: physical functioning, role physical, bodily pain, general health, vitality and social functioning domains of the SF-36 (p<0.01). No improvements were observed in the role emotional and mental health domains of the SF-36. Improvements compared to placebo were observed with tadalafil 40 mg in the EuroQol (EQ-5D) US and UK index scores (p<0.001) comprising mobility, self-care, usual activities, pain/discomfort, anxiety/depression components, and in the visual analogue scale (VAS) (p<0.05).
Long Term Treatment of Pulmonary Arterial Hypertension
357 patients from the placebo-controlled study entered a long-term extension study. Of these, 266 patients have been treated with tadalafil for at least 6 months and 125 for 1 year (median exposure 279 days; range 2 days to 400 days). The interim mortality rate in the extension study was 4.6 per 100 patient years. Additionally, 6 minute walk distance and WHO functional class status appeared to be stable in those treated with tadalafil for 1 year. Without a control group, these data must be interpreted cautiously.
14.3 Comparative Bioavailability Studies
Bioequivalence (as measured by Cmax and AUCτ) between OPSYNVI® (10 mg/40 mg) and a concomitant dose of OPSUMIT® (10 mg macitentan) and ADCIRCA® (2x20 mg tadalafil; by Eli Lilly Canada Inc.) was demonstrated in healthy subjects under fasting conditions.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Non-clinical studies with OPSYNVI® have not been performed due to the long-term clinical experience with the concurrent use of ERAs and PDE5 inhibitors.
Non-clinical pharmacology studies with macitentan and tadalafil in free combination were performed and demonstrated an additive/synergistic antihypertensive effect on systemic hypertension and pulmonary hypertension when compared to monotherapy with the individual active agent in rodent PAH models.
General Toxicology:
Acute Toxicity Studies
Macitentan
Macitentan had a low order of acute toxicity in rodents. No deaths occurred following a single oral dose of 2000 mg/kg in mice and rats.
Tadalafil
Tadalafil demonstrated low acute oral toxicity in both mice and rats, as doses up to 2000 mg/kg did not cause death and produced only minimal clinical observations.
Repeated-dose toxicity studies
Macitentan
No adverse effects were observed in repeated-dose oral toxicity studies in rats or dogs with treatment durations ≤ 26 or 39 weeks at exposures of 2- to 6-fold the human exposure at 10 mg/day.
Prolonged coagulation test times (PT and APTT) leading to hemorrhage and death occurred at a very high dose level (1500 mg/kg/day) in male rats. As exposure at this dose was 137-fold the human exposure, this finding is considered of limited relevance for humans.
Generally mild to moderate decreases in red blood cell parameters (red blood cell count, hemoglobin, hematocrit) that occurred in rats or dogs were reversible.
In dogs, macitentan decreased blood pressure at exposures similar to the therapeutic human exposure. Intimal thickening of coronary arteries, considered secondary to hemodynamic changes, was observed in dogs at 17-fold the human exposure after 4 to 39 weeks of treatment.
Treatment-related coronary intimal thickening of coronary arteries was not observed in dogs at 4-fold (males) to 9-fold (females) human exposure.
Increased incidences of arteritis/peri-arteritis of coronary arteries occurred in dogs at ≥ 17-fold human exposure. Due to the species-specific sensitivity and the safety margin, this finding is considered of limited relevance for humans.
There were no adverse liver findings in long-term studies conducted in B6C3F1 mice, rats, and dogs at exposures of 12- to 116-fold the human exposure. The relevance of increased aminotransferase activities and liver cell necrosis observed in CD-1 mice at ≥ 5 mg/kg/day is not known in view of the inconsistency of these findings across studies.
Liver cell hypertrophy in mice, rats and dogs and associated thyroid follicular cell hypertrophy in rats, represent adaptive changes related to hepatic enzyme induction.
Pathologic changes in testes (tubular dilatation, degeneration and/or atrophy; and/or hypospermatogenesis) occurred in rats or dogs at >18-fold human exposure. Tadalafil
Daily oral administration of tadalafil to mice for 3 months at doses up to 800 mg/kg/day produced no deaths or treatment-related findings. In rats, oral toxicity studies of 1- and 6-months duration, with doses up to 400 mg/kg/day, and a 3 month study with doses up to 800 mg/kg/day, produced no treatment-related deaths or substantive clinical observations. These studies yielded no gross or histopathologic findings that were considered toxicologically important.
In dogs given tadalafil daily for 6 to 12 months at doses of 25 mg/kg/day and above, there were alterations to the seminiferous tubular epithelium that resulted in a decrease in spermatogenesis in some dogs. However, in placebo-controlled studies in men who received tadalafil 10 or 20 mg daily for up to 9 months, there were no treatment-related effects on sperm concentration, sperm count, motility, or morphology. Minimal thymic and hepatic changes were observed in dogs at higher doses.
Carcinogenicity: Macitentan
Carcinogenicity studies of 2 years duration did not reveal any carcinogenic potential at exposures 18-fold and 116-fold the human exposure in rats and mice, respectively.
Tadalafil
Tadalafil was not carcinogenic to rats or mice when administered for 24 months.
Genotoxicity: Macitentan
Macitentan was not genotoxic in a standard battery of in vitro and in vivo assays. Macitentan was not phototoxic in vivo.
Tadalafil
Tadalafil was not mutagenic or genotoxic in in vitro bacterial and mammalian cell assays, and in vitro human lymphocytes and in vivo rat micronucleus assays. Tadalafil induces only mild ocular and dermal irritation.
Reproductive and Developmental Toxicology: Macitentan
Macitentan was teratogenic in rabbits and rats at all dose levels tested. In both species there were cardiovascular abnormalities and mandibular arch fusion abnormalities.
Macitentan was fetotoxic in rabbits at a dose 218-fold the human exposure.
Administration of macitentan to female rats from late pregnancy through lactation caused reduced pup survival and impairment of the reproductive capability of the offspring at maternal exposures 5-fold the human exposure.
Treatment of juvenile rats from postnatal Day 4 to Day 114 led to reduced body weight gain and testicular tubular atrophy at exposures 6-fold the human exposure.
Treatment with macitentan also caused a reduction in the numbers of implantation sites and live embryos. Although at an exposure 3-fold the human exposure, macitentan had no effects on sperm count or motility, the incidence of sperm misshapen or with abnormally curved hook was increased.
Testicular tubular dilatation was not observed in repeated-dose toxicity studies at exposures 8-and 6-fold the human exposure in rats and dogs, respectively.
After 2 years of treatment, tubular atrophy was seen in rats at 4-fold the human exposure. Macitentan did not affect male or female fertility at exposures ranging from 19- to 44-fold the human exposure, respectively, and had no effect on sperm count, motility, and morphology in male rats.
No testicular findings were noted in mice after treatment up to 2 years. In mice treated for 2 years with macitentan, uterine weight was increased and there was an increase in the mean severity and incidence of uterine endometrial cysts at exposures 9-fold and 90-fold the human exposure, respectively.
Tadalafil
There was no evidence of teratogenicity, embryotoxicity or fetotoxicity in rats or mice that received tadalafil up to 1000 mg/kg/day. In a rat pre- and postnatal development study, the no-observed effect dose was 30 mg/kg/day. In the pregnant rat the AUC for calculated free drug at this dose was approximately 18 times the human AUC at a 20 mg dose.
There was no impairment of fertility in male and female rats.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. OPSUMIT® (macitentan film-coated tablet, 10 mg), 257188, Product Monograph, Janssen Inc. (Nov. 28, 2022)
- 2. ADCIRCA® (tadalafil tablets, 20 mg), 197483, Product Monograph, Eli Lilly Canada Inc. (Nov. 22, 2016)