


Product Monograph - Oritiniv
1. Indications
ORITINIV for injection is indicated for:
the treatment of adult patients with acute bacterial skin and skin structure infections (ABSSSI) caused by susceptible isolates of the following Gram-positive microorganisms:
Staphylococcus aureus (including methicillin-susceptible and methicillin-resistant isolates), Streptococcus pyogenes, Streptococcus agalactiae, Streptococcus dysgalactiae, Streptococcus anginosus group (includes S. anginosus, S. intermedius, and S. constellatus), and Enterococcus faecalis (vancomycin susceptible isolates only).
To reduce the development of drug-resistant bacteria and maintain the effectiveness of ORITINIV and other antibacterial drugs, ORITINIV should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.1. Pediatrics
Pediatrics (˂ 18 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of ORITINIV in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (>65 years of age): The pooled Phase 3 ABSSSI clinical trials of ORITINIV did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently compared to younger subjects. Other reported clinical experience has not identified clinically relevant differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out, see 7.1.4 Warning and Precautions, Special population, Geriatrics.
2. Contraindications
- Use of intravenous unfractionated heparin sodium is contraindicated for 120 hours (5 days) after ORITINIV administration because the activated partial thromboplastin time (aPTT) test results may remain falsely elevated for up to 120 hours (5 days) after ORITINIV administration, see 7 Warnings and Precautions and 9 Drug Interactions.
- ORITINIV is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
3. Serious Warnings and Precautions Box
Serious hypersensitivity reactions, including anaphylaxis, have been reported with the use of oritavancin products, see 7 Warnings and Precautions.
4. Dosage and Administration
4.1. Dosing Considerations
There are two oritavancin products that are supplied in two different dose strengths, with differences in formulation, duration of infusion, and preparation (reconstitution, dilution and compatible diluents), see 4.2 Recommended Dose and Dosage Adjustment and 4.3 Reconstitution.
4.2. Recommended Dose and Dosage Adjustment
- For ORITINIV 400 mg/vial, the recommended dosage is 1,200 mg (3 vials) administered as a single dose by intravenous infusion over 3 hours, see 7 Warnings and Precautions.
- For ORITINIV 1200 mg/vial, the recommended dosage is 1,200 mg (1 vial) administered as a single dose by intravenous infusion over 1 hour, see 7 Warnings and Precautions.
Pediatric (<18 years of age)
Health Canada has not authorized an indication for pediatric use. The safety and efficacy of ORITINIV in pediatrics (<18 years) have not yet been established.
Geriatric (>65 years of age)
No dosage adjustment is required for patients ≥65 years of age, see 7.1.4 Warning and Precautions, Special population, Geriatrics.
Renal impairment
No dosage adjustment is needed in patients with mild or moderate renal impairment, see 10.3 Clinical Pharmacology, Pharmacokinetics. The pharmacokinetics of ORITINIV in patients with severe renal impairment have not been evaluated. ORITINIV is not removed from blood by hemodialysis procedures.
Hepatic impairment
No dosage adjustment is required for patients with mild to moderate hepatic impairment (Child-Pugh Class B), see 10.3 Clinical Pharmacology, Pharmacokinetics. The pharmacokinetics of ORITINIV in patients with severe hepatic impairment (Child-Pugh Class C) has not been evaluated.
4.3. Reconstitution
Parenteral Products:
ORITINIV 400 mg/vial
- Three (3) ORITINIV 400 mg vials need to be reconstituted and diluted to prepare a single 1200 mg intravenous dose.
Reconstitution: Aseptic technique should be used to reconstitute three (3) ORITINIV 400 mg vials.
- Add 40 mL of Sterile Water for Injection (SWFI) to reconstitute each vial to provide a 10 mg/mL solution per vial.
- For each vial, swirl the contents gently, to avoid foaming, and ensure that all oritavancin powder is completely dissolved to form a reconstituted solution.
Each vial should be inspected visually for particulate matter after reconstitution. Each
- reconstituted vial should appear to be a clear, colorless to pale yellow solution, free of visible particles.
- Discard any unused portion of reconstituted solution.
Dilution: Use ONLY 5% Dextrose in Sterile Water (D5W) for dilution to prepare the final intravenous solution for infusion. Do NOT use 0.9% Sodium Chloride Injection for dilution, as it is incompatible with ORITINIV 400 mg and may cause precipitation of the drug (see 12 Special Handling Instructions). Since no preservative or bacteriostatic agent is present in ORITINIV 400 mg, aseptic technique must be used in preparing the final intravenous solution, as follows:
- Withdraw and discard 120 mL from a 1000 mL intravenous bag of D5W.
- Withdraw 40 mL from each of the three reconstituted vials of ORITINIV 400 mg, and add to D5W intravenous bag, to bring the bag volume to 1000 mL. This yields a concentration of 1.2 mg/mL.
ORITINIV 1200 mg/vial
- One ORITINIV 1200 mg single-vial needs to be reconstituted and diluted to prepare a single 1200 mg intravenous dose.
Reconstitution: Aseptic technique should be used to reconstitute one (1) ORITINIV 1200 mg vial.
- Add 40 mL of Sterile Water for Injection (SWFI) to reconstitute the vial, to provide a 30 mg/mL solution.
- Swirl the contents gently, to avoid foaming, and ensure that all ORITINIV 1200 mg powder is completely dissolved to form a reconstituted solution.
- The vial should be inspected visually for particulate matter. The reconstituted vial should appear to be clear, colorless to pink solution, free of visible particles.
- Discard any unused portion of reconstituted solution.
Dilution: Use 0.9% Sodium Chloride Injection or D5W for dilution to prepare the final intravenous solution for infusion. Since no preservative or bacteriostatic agent is present in ORITINIV 1200 mg, aseptic technique must be used in preparing the final intravenous solution, as follows:
- Withdraw and discard 40 mL from a 250 mL intravenous bag of 0.9% Sodium Chloride Injection or D5W.
- Withdraw 40 mL of the reconstituted vial of ORITINIV 1200 mg, and add to the intravenous bag of 0.9% Sodium Chloride Injection or D5W, to bring the bag volume to 250 mL. This yields a concentration of 4.8 mg/mL.
Table 1– Reconstitution & Dilution
| Step | Product / Vial size | Volume of Diluent to be Added to Vial / Infusion bag | Approximate Available Volume | Concentration per mL |
| ORITINIV 400 mg / 50 ml | Add 40 mL of Sterile Water for Injection (SWFI)* | 40 mL | 10 mg/mL per vial |
| Withdraw and discard 120 mL from a 1000 mL intravenous bag of D5W. Withdraw and add 40 mL from each of the three reconstituted vials of ORTINIV 400 mg to the intravenous bag of D5W. | 1000 mL | 1.2 mg/mL in intravenous bag | |
| ORITINIV 1200 mg / 50 ml | Add 40 mL of Sterile Water for Injection (SWFI) | 40 mL | 30 mg/ml per vial |
| 2.a Dil | Withdraw and discard 40 mL from a 250 mL intravenous bag of 0.9% Sodium Chloride Injection. Withdraw and add 40 mL of the reconstituted vial of ORITINIV 1200 mg to intravenous bag of 0.9% Sodium Chloride Injection. | 250 mL | 4.8 mg/mL in intravenous bag | |
| 2.b Dil | Withdraw and discard 40 mL from a 250 mL intravenous bag of D5W. Withdraw and add 40 mL of the reconstituted vial of ORITINIV 1200 mg to intravenous bag of D5W. | 250 mL | 4.8 mg/mL in intravenous bag |
Rec: Reconstitution – Dil: Dilution
* This process must be performed on 3 vials of ORITINIV 400 mg to yield the 1200 mg dose.
For storage and use of intravenous solution, see 11 Storage, Stability and Disposal.
4.4. Administration
Intended for intravenous infusion, only after reconstitution and dilution.
4.5. Missed Dose
Not applicable.
5. Overdose
No cases of overdose associated with ORITINIV were reported in clinical trials.
In the event of overdose, medical care should be provided including consulting with a healthcare professional and close observation of the clinical status of the patient, see 10 Clinical Pharmacology.
Oritavancin is not removed from blood by hemodialysis. In the event of overdose, supportive measures should be taken.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6. Dosage Forms, Strengths, Composition and Packaging
Table 2 – Dosage Forms, Strengths, and Composition
Description
ORITINIV 400 mg is available as 3 single-use 50 ml vials per package.
ORITINIV 1200 mg is available as 1 single-use 50 ml vial per package.
7. Warnings and Precautions
Please see 3 Serious Warnings and Precautions Box.
Gastrointestinal
Clostridioides difficile-associated diarrhea (CDAD) has been reported for nearly all systemic antibacterial drugs, including oritavancin, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of C. difficile.
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin-producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antibacterial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial use. Careful medical history is necessary because
| Formulation | Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| ORITINIV 400 mg | Intravenous infusion | powder for solution / 400 mg oritavancin (as oritavancin phosphate) per vial | mannitol and phosphoric acid |
| ORITINIV 1200 mg | Intravenous infusion | powder for solution / 1200 mg oritavancin (as oritavancin phosphate) per vial | hydroxypropyl-β-cyclodextrin (HPβCD), mannitol, and phosphoric acid or sodium hydroxide |
CDAD has been reported to occur more than 2 months after the administration of antibacterial agents.
If CDAD is suspected or confirmed, antibacterial use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial treatment of C. difficile, and surgical evaluation should be instituted as clinically indicated, see 8 Adverse Reactions.
Immune
- Hypersensitivity reactions
Serious hypersensitivity reactions, including anaphylaxis, have been reported with the use of ORITINIV products. If an acute hypersensitivity reaction occurs during ORITINIV infusion, discontinue ORITINIV immediately and institute appropriate supportive care. Before using ORITINIV, inquire carefully about previous hypersensitivity reactions to glycopeptides. Due to the possibility of cross-sensitivity, carefully monitor for signs of hypersensitivity during ORITINIV infusion in patients with a history of glycopeptide allergy. In the Phase 3 ABSSSI clinical trials, the median onset of hypersensitivity reactions in ORITINIV-treated patients was 1.2 days and the median duration of these reactions was 2.4 days.
- Infusion-related reactions
Infusion-related reactions have been reported with the glycopeptide class of antimicrobial agents, including ORITINIV products, with presentations including flushing of the upper body, urticaria, pruritus, and/or rash. Infusion-related reactions characterized by chest pain, back pain, chills, and tremor have also been observed with the use of ORITINIV, including after the administration of more than one dose of ORITINIV during a single course of therapy.
Stopping or slowing the infusion may result in cessation of these reactions, see 8 Adverse Reactions. The safety and effectiveness of more than one dose of ORITINIV during a single course of therapy have not been established (see 4.2 Dosage and Administration, Recommended Dose and Dosage Adjustment).
Monitoring and Laboratory Tests
- Coagulation test interference
Oritavancin has been shown to interfere with certain laboratory coagulation tests, see 9.7 Drug Interactions, Drug-Laboratory Test Interactions.
Oritavancin has been shown to artificially prolong aPTT for up to 120 hours by binding to and preventing action of the phospholipid reagents commonly used in laboratory coagulation tests. Oritavancin has also been shown to elevate D-dimer concentrations up to 72 hours after oritavancin administration, PT and international normalized ratio (INR) for up to 12 hours, and ACT for up to 24 hours following administration of a single 1200 mg dose. This ex vivo effect results from oritavancin binding to and preventing action of the phospholipid reagents which activate coagulation in commonly used laboratory coagulation tests.
For patients who require aPTT monitoring within 120 hours of ORITINIV dosing, a nonphospholipid-dependent coagulation test such as a Factor Xa (chromogenic) assay or an alternative anticoagulant not requiring aPTT monitoring may be considered.
- Concomitant use of warfarin
Oritavancin has been shown to artificially prolong PT and INR for up to 12 hours, making the monitoring of the anticoagulation effect of warfarin unreliable up to 12 hours after an ORITINIV dose (see 7
Warnings and Precautions, Coagulation test interference).
Patients should be monitored for bleeding if concomitantly receiving ORITINIV and warfarin (see 9.7 Drug Interactions, Drug-Laboratory Test Interaction).
Musculoskeletal
- Osteomyelitis
In the Phase 3 ABSSSI clinical trials, more cases of osteomyelitis were reported in the ORITINIV-treated arm than in the vancomycin-treated arm. Monitor patients for signs and symptoms of osteomyelitis. If osteomyelitis is suspected or diagnosed, institute appropriate alternative antibacterial therapy, see 8 Adverse Reactions.
Reproductive Health: Female and Male Potential
Fertility
Animal studies have revealed no evidence of impaired fertility due to oritavancin at the highest concentrations administered; however, there is no data on the effects of oritavancin on human fertility. See 16 Non-Clinical Toxicology.
Teratogenic Risk
Studies in pregnant rats and rabbits do not indicate direct or indirect harmful effects with respect to pregnancy, embryonal/fetal development, parturition, or postnatal development. There was no evidence of transplacental transfer of oritavancin in pregnant rats. The exposure in rats at the no observed adverse event level (NOAEL) was less than the human exposure based on the AUC; therefore, these results should be considered with caution.
Sensitivity/Resistance
- Development of drug-resistant bacteria
Prescribing ORITINIV in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria.
7.1. Special Populations
7.1.1. Pregnancy
There are very limited data from clinical trials on the use of ORITINIV during pregnancy. Additional clinical safety data is required to support the use of ORITINIV in pregnancy. ORITINIV should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Reproduction studies performed in rats and rabbits have revealed no evidence of harm to the fetus due to oritavancin at the highest concentrations administered, 30 mg/kg/day and 15 mg/kg/day, respectively. Those daily doses would be equivalent to a human dose of 300 mg, or 25% of the single clinical dose of 1200 mg. Higher doses were not evaluated in nonclinical developmental and reproductive toxicology studies.
7.1.2. Breastfeeding
There are no data on the use of ORITINIV during lactation in humans. It is unknown whether ORITINIV is excreted in human milk. Precaution should be exercised because many drugs can be excreted in human milk. A risk to the newborn cannot be excluded. Following a single intravenous infusion in lactating rats, radio-labeled [14C]-oritavancin was excreted in milk and absorbed by nursing pups.
7.1.3. Pediatrics
Pediatrics (˂ 18 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of ORITINIV in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (>65 years of age): The pooled Phase 3 ABSSSI clinical trials of ORITINIV did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently compared to younger subjects. Other reported clinical experience has not identified clinically relevant differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. See 8.2 Clinical Trial Adverse Reactions.
8. Adverse Reactions
8.1. Adverse Reaction Overview
The following serious adverse reactions are discussed in greater detail in other sections of the product monograph:
- Clostridium difficile-associated disease (see 7 Warnings and Precautions)
- Hypersensitivity reactions (see 7 Warnings and Precautions)
- Infusion-related reactions (see 7 Warnings and Precautions)
- Coagulation test interference (see 7 Warnings and Precautions)
- Concomitant use of warfarin (see 7 Warnings and Precautions)
- Osteomyelitis (see 7 Warnings and Precautions)
- Development of drug-resistant bacteria (see 7 Warnings and Precautions)
The safety data for ORITINIV was evaluated in pooled form from two double-blind clinical trials in patients with ABSSSI (SOLO I and SOLO II). A total of 976 adult patients were treated with a 1,200 mg intravenous dose of ORITINIV followed by placebo, and 983 patients were treated with vancomycin 1g or 15mg/kg intravenous dose every 12 hours for 7 to 10 days. The median duration of treatment was 8 days in both groups.
The median age of patients treated with ORITINIV was 46 years (range 18 to 89 years); 8.8% of patients treated with ORITINIV were ≥65 years of age. Patients treated with ORITINIV were predominantly male (65.4%), and Caucasian (64.4%); 5.8% were African American, and 28.1% were Asian.
Treatment-emergent adverse events (TEAE) occurred in 55.3% in the ORITINIV group and 56.9% in the vancomycin group. The most commonly reported TEAE in patients who were treated with ORITINIV were nausea (9.9%), headache (7.1%), and vomiting (4.6%) (Table 3, below). Patients aged 65 to 74 years and >75 years who reported a TEAE were 31/69 (44.9%) and 11/17 (64.7%), respectively, compared to 498/890 (56%) for patients <65 years; adverse events were similar in frequency and nature between the treatment groups.
Serious adverse events (SAEs) were reported in 5.8% in the ORITINIV group and 5.9% in the vancomycin group. The most commonly reported SAEs in the ORITINIV group included cellulitis (1.1%), osteomyelitis (0.4%), abscess limb (0.3%), pneumonia (0.3%), skin infection (0.3%) and subcutaneous abscess (0.3%).
A total of 5 deaths (2 in the ORITINIV group and 3 in the vancomycin group) were reported, none of which were considered related to study drug. The incidence of adverse events leading to study drug discontinuation was 3.7% in the ORITINIV group and 4.2% in the vancomycin group. The most frequently reported AEs leading to study drug discontinuation in the ORITINIV group were cellulitis (0.4%) and osteomyelitis (0.3%).
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect the frequencies observed in clinical practice and should not be compared to the frequencies reported in clinical trials of another drug.
Adverse drug reactions that occurred in at least 1% of patients in the pooled adult Phase 3 SOLO Clinical Trials are presented in Table 3, below.
Table 3 - Adverse Drug Reactions Occurring in ≥ 1% of Patients After Receiving a single dose of ORITINIV (1200mg) in the Pooled Adult Phase 3 SOLO Clinical Trials
| Adverse Reactions* | Oritavancin n = 976 (%) | Vancomycin n = 983 (%) |
| Adverse Reactions* | Oritavancin n = 976 (%) | Vancomycin n = 983 (%) |
Blood and lymphatic system disorders Anaemia | 13 (1.3) | 12 (1.2) |
Cardiac disorders Tachycardia | 24 (2.5) | 11 (1.1) |
Gastrointestinal disorders Nausea Vomiting Diarrhea Constipation Dyspepsia Abdominal pain | 97 (9.9) 45 (4.6) 36 (3.7) 33 (3.4) 11 (1.1) 9 (0.9) | 103 (10.5) 46 (4.7) 32 (3.3) 38 (3.9) 10 (1.0) 14 (1.4) |
General disorders and administration site conditions Infusion site extravasation Pyrexia Infusion site phlebitis Infusion site reaction Fatigue Edema peripheral Chills Device occlusion | 33 (3.4) 30 (3.1) 24 (2.5) 19 (1.9) 15 (1.5) 14 (1.4) 13 (1.3) 10 (1.0) | 33 (3.4) 31 (3.2) 15 (1.5) 34 (3.5) 10 (1.0) 19 (1.9) 16 (1.6) 9 (0.9) |
Infections and infestations Cellulitis Abscess limb Subcutaneous Abscess Abscess Infection | 37 (3.8) 27(2.8) 15 (1.5) 11 (1.1) 12 (1.2) | 32 (3.3) 13 (1.3) 11 (1.1) 6 (0.6) 2 (0.2) |
Hepatobiliary disorders Alanine aminotransferase increased Aspartate aminotransferase increased | 27 (2.8) 18 (1.8) | 15 (1.5) 15 (1.5) |
Musculoskeletal and connective tissue disorders Myalgia | 13 (1.3) | 8 (0.8) |
Nervous system disorders Headache Dizziness | 69 (7.1) 26 (2.7) | 66 (6.7) 26 (2.6) |
Psychiatric disorders Insomnia | 21 (2.2) | 25 (2.5) |
Respiratory, thoracic and mediastinal disorders Oropharyngeal Pain Cough Dyspnoea | 12 (1.2) 11 (1.1) 11 (1.1) | 5 (0.5) 14 (1.4) 8 (0.8) |
Skin and subcutaneous tissue disorders Pruritus Pruritus generalised Urticaria | 29 (3.0) 16 (1.6) 11 (1.1) | 73 (7.4) 23(2.3) 21 (2.1) |
Vascular disorders Hypertension | 10 (1.0) | 14 (1.4) |
*MedRA System Organ Class and Preferred Terms.
8.3. Less Common Clinical Trial Adverse Reactions
Adverse reactions, that occurred in less than 1% of patients in the Phase 3 SOLO trials safety pool, are listed below.
- Blood and lymphatic system disorders: eosinophilia, thrombocytopenia
- General disorders and administration site conditions: erythema, induration, infusion site pruritus, infusion site rash
- Immune system disorders: hypersensitivity
- Infections and infestations: osteomyelitis
- Investigations: blood bilirubin increased
- Metabolism and nutrition disorders: hypoglycaemia, hyperuricaemia
- Musculoskeletal and connective tissue disorders: tenosynovitis
- Respiratory, thoracic and mediastinal disorders: bronchospasm, wheezing
- Skin and subcutaneous tissue disorders: angioedema, erythema multiforme, rash, flushing, leukocytoclastic vasculitis
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
In the Phase 3 SOLO clinical trials, the incidence of laboratory abnormalities was balanced between the ORITINIV and vancomycin groups and no clinically meaningful differences in hematology or chemistry values or changes from baseline were observed. Transient elevations in liver enzymes (ALT: alanine aminotransferase; AST: aspartate aminotransferase) were observed in both groups. See Table 3. Of the 24 patients (10 ORITINIV and 14 vancomycin patients) with AST or ALT elevations greater than 5X ULN in the SOLO pool, 17 patients’ (8 ORITINIV and 9 vancomycin patients) AST and ALT values returned to baseline levels. For the remaining 7 patients (2 ORITINIV and 5 vancomycin patients), AST or ALT values were either decreasing and returning to baseline levels or the patients were lost to follow up.
8.5. Post-Market Adverse Reactions
The following serious and/or unexpected adverse reactions, not already listed above, have been reported during post-approval use of ORITINIV: chest pain, back pain, chills, and tremor.
9. Drug Interactions
9.1. Serious Drug Interactions
- Use of intravenous unfractionated heparin sodium is contraindicated for 120 hours (5 days) after ORITINIV administration because the activated partial thromboplastin time (aPTT) test results may remain falsely elevated for up to 120 hours (5 days) after ORITINIV administration. See 7 Warnings and Precautions and 9.7 Drug-Laboratory Test Interactions.
9.2. Drug Interactions Overview
- Inhibitors and inducers of CYP450
A screening drug-drug interaction study was conducted in healthy volunteers (n=16) evaluating the concomitant administration of a single 1,200 mg dose of ORITINIV with probe substrates for several CYP450 enzymes. ORITINIV was found to be a nonspecific, weak inhibitor of (CYP2C9 and CYP2C19) or inducer (CYP3A4 and CYP2D6) of several CYP isoforms.
Caution should be used when administering ORITINIV concomitantly with medicinal products with a narrow therapeutic window that are predominantly metabolized by one of the affected CYP450 enzymes (e.g., warfarin), as co-administration may increase (e.g., for CYP2C9 and CYP2C19 substrates) or decrease (e.g., for CYP2D6 and CYP3A4 substrates) concentrations of the narrow therapeutic range medicinal product. Patients should be closely monitored for signs of toxicity or lack of efficacy if they have been given ORITINIV while on a potentially affected compound (e.g. patients should be monitored for bleeding if concomitantly receiving ORITINIV and warfarin), see Section 7 Warning and Precautions.
9.4. Drug-Drug Interactions
The drugs listed in Table 4 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
A study to assess the drug-drug interaction effect of a single 1200 mg dose of oritavancin on the pharmacokinetics of S-warfarin dose was conducted in 36 healthy subjects. S-warfarin pharmacokinetics were evaluated following a single dose of warfarin 25 mg given alone, or administered at the start, 24, or 72 hours after a single 1200 mg oritavancin dose. The results showed no effect of oritavancin on S-warfarin Cmax or AUC.
Table 4 - Established or Potential Drug-Drug Interactions
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
| Warfarin | CT | Potential risk of bleeding with concomitant use of warfarin. ORITINIV has been shown to artificially prolong prothrombin time (PT) and international normalized ratio (INR) for up to 12 hours, making the monitoring of the anticoagulation effect of warfarin unreliable up to 12 hours after an ORITINIV dose (See 7 Warning and Precautions). | Patients should be monitored for bleeding if concomitantly receiving ORITINIV and warfarin (see 7 Warning and Precautions). |
Legend: CT = Clinical Trial
9.7. Drug-Laboratory Test Interactions
- Prolongation of Certain Laboratory Coagulation Tests
Oritavancin may artificially prolong certain laboratory coagulation tests by binding to and preventing the action of the phospholipid reagents that activate coagulation (Table 5), see 7 Warning and Precautions. For patients who require monitoring of anticoagulation effect within the indicated time after ORITINIV dosing, a non-phospholipid-dependent coagulation test such as a Factor Xa (chromogenic) assay or an alternative anticoagulant not requiring aPTT monitoring may be considered.
Oritavancin does not affect tests that are used for diagnosis of Heparin-Induced Thrombocytopenia (HIT).
Table 5: Coagulation Tests Affected and Unaffected by Oritavancin
| Affected by Oritavancin | Unaffected by Oritavancin |
|---|---|
| Activated partial thromboplastin time (aPTT), up to 120 hours | Chromogenic Factor Xa Assay |
| Activated clotting time (ACT), up to 24 hours | Thrombin Time (TT) |
| D-dimer concentrations, up to 72 hours | |
| Dilute Russell’s viper venom time (DRVVT), up to 72 hours | |
| International normalized ratio (INR), up to 12 hours | |
| Prothrombin time (PT), up to 12 hours | |
| Silica clot time (SCT), up to 18 hours |
- Positive Indirect and Direct Antiglobulin Tests (IAT/DAT)
Positive Indirect and Direct Antiglobulin Tests (IAT/DAT) were noted with administration of ORITINIV products in studies with healthy volunteers and patients with ABSSSI. Positive IAT may interfere with cross-matching before blood transfusion.
10. Clinical Pharmacology
10.1. Mechanism of Action
Oritavancin has three mechanisms of action: (i) inhibition of the transglycosylation (polymerization) step of cell wall biosynthesis by binding to the stem peptide of peptidoglycan precursors; (ii) inhibition of the transpeptidation (crosslinking) step of cell wall biosynthesis by binding to the peptide bridging segments of the cell wall; and (iii) disruption of bacterial membrane integrity, leading to depolarization, permeabilization, and rapid cell death. These multiple mechanisms contribute to the concentration-dependent bactericidal activity of oritavancin. See 15 Microbiology.
10.2. Pharmacodynamics
The antimicrobial activity of oritavancin appears to correlate with the ratio of area under the concentration-time curve to minimal inhibitory concentration (AUC/MIC) based on animal models of infection. The AUC from time zero to 72 hours correlates with antimicrobial activity in both preclinical and clinical studies.
Exposure-response analyses from both preclinical and clinical studies support the treatment of clinically relevant Gram-positive microorganisms (e.g. S. aureus and S. pyogenes) causative of ABSSSI with a single 1,200 mg dose of oritavancin.
In a thorough QTc study of 148 healthy subjects administered oritavancin at a dose of 1600 mg over 3 hours, oritavancin did not prolong the QTc interval to any clinically relevant extent, but had a mild, non-clinically relevant, impact on the PR interval. Other studies did not reveal any significant QTc prolongation effects of oritavancin.
10.3. Pharmacokinetics
The population PK analysis was derived using data from the two Phase 3 ABSSSI clinical trials in 297 patients. The mean pharmacokinetic parameters of ORITINIV 400 mg in patients following a single 1,200 mg dose are presented in Table 6.
Table 6 - Summary of ORITINIV 400 mg Pharmacokinetic Parameters in patients receiving a single 1200 mg dose for ABSSSI (n=297)
| Pharmacokinetic Parameter | Mean | CV% |
|---|---|---|
| Cmax (µg/mL) | 138 | 23.0 |
| AUC0-∞ (µg∙h/mL) | 2800 | 28.6 |
Cmax, Maximum plasma concentration; AUC0--∞, Area under the plasma concentration time curve from time zero to infinity
The mean pharmacokinetic parameters of oritavancin products (ORITINIV 400 mg and ORITINIV 1200 mg) in patients with ABSSSI are presented in Table 7. Due to the difference in formulations between the two strengths, this data demonstrates that the formulation differences do not impact the pharmacokinetics of the drug product.
Table 7 - Mean Pharmacokinetic Parameters following a single 1,200 mg dose of ORITINIV 1200 mg by intravenous infusion over 1 hour (N= 50) and oritavancin 400 mg by intravenous infusion over 3 hours (N=50) in Patients with ABSSSI
| Pharmacokinetic Parameter | ORITINIV 1200 mg (1 hour) | ORITINIV 400 mg (3 hour) | ||||
|---|---|---|---|---|---|---|
| Mean | CV% | Mean | CV% | |||
| Cmax (µg/mL) | 148 | 29.1 | 112 | 30.8 | ||
| AUC0-72 (µg∙h/mL) | 1460 | 35.0 | 1470 | 39.6 | ||
Cmax, Maximum plasma concentration; AUC0-72, Area under the plasma concentration-time curve from time zero to 72 hours
ORITINIV 400 mg and ORITINIV 1200 mg exhibit linear pharmacokinetics at a dose up to 1,200 mg. The mean, population-predicted oritavancin concentration-time profile displays a multi-exponential decline with a long terminal plasma half-life.
Absorption
Not applicable.
Distribution:
Oritavancin is approximately 85% bound to human plasma proteins. Based on population PK analysis, the population mean total volume of distribution is estimated to be approximately 87.6 L, indicating that oritavancin is extensively distributed into the tissues.
Exposures (AUC0-24) of oritavancin in skin blister fluid were 20% of those in plasma after a single 800 mg dose in healthy subjects.
Metabolism:
No metabolites were observed in plasma or bile from oritavancin treated dogs and rats, respectively. Non-clinical studies, including in vitro human liver microsome studies, indicated that oritavancin is not metabolized.
Elimination
No mass balance study has been conducted in humans. In humans, oritavancin is slowly excreted unchanged in feces and urine with less than 1% and 5% of the dose recovered in feces and urine, respectively, after 2 weeks of collection.
Oritavancin has a terminal half-life of approximately 245 hours and a clearance of 0.445 L/h, based on population pharmacokinetic analyses.
Special Populations and Conditions
- Geriatrics Population PK analysis from the single dose Phase 3 ABSSSI studies in patients indicated that age had no clinically relevant effect on the exposure of oritavancin. No dosage adjustment is warranted in these subpopulations.
- Sex Population PK analysis from the single dose Phase 3 ABSSSI studies in patients indicated that gender had no clinically relevant effect on the exposure of oritavancin. No dosage adjustment is warranted in these subpopulations.
- Ethnic Origin Population PK analysis from the single dose Phase 3 ABSSSI studies in patients indicated that race had no clinically relevant effect on the exposure of oritavancin. No dosage adjustment is warranted in these subpopulations.
Hepatic Insufficiency The pharmacokinetics of oritavancin were evaluated in a study of subjects with moderate hepatic impairment (Child-Pugh Class B, n=20) and compared with healthy subjects (n=20) matched for gender, age, and weight. There were no relevant changes in pharmacokinetics of oritavancin in subjects with moderate hepatic impairment.
Dosage adjustment of oritavancin is not needed in patients with mild and moderate hepatic impairment. The pharmacokinetics of oritavancin in patients with severe hepatic impairment has not been studied.
Renal Insufficiency The pharmacokinetics of oritavancin was examined in the Phase 3 ABSSSI trials in patients with normal renal function, CrCL ≥80 mL/min (n=238), mild renal impairment, CrCL 50-79 mL/min (n=48), and moderate renal impairment, CrCL 30-49 mL/min (n=11). Population pharmacokinetic analysis indicated that mild to moderate renal impairment had no clinically relevant effect on the exposure of oritavancin. No dedicated studies in dialysis patients have been conducted.
Dosage adjustment of oritavancin is not needed in patients with mild or moderate renal impairment. The pharmacokinetics of oritavancin in patients with severe renal impairment have not been evaluated.
The solubiliser HPβCD is excreted in urine. Clearance of HPβCD may be reduced in patients with renal impairment. The clinical significance of this finding is unknown.
11. Storage, Stability and Disposal
ORITINIV 400 mg and ORITINIV 1200 mg vials should be stored at 15 to 30°C. For ORITINIV 400 mg, diluted intravenous solution in an infusion bag should be used within 6 hours when stored at room temperature (15 to 30°C), or used within 12 hours when refrigerated at 2 to 8°C. The combined storage time (reconstituted solution in the vial and diluted solution in the bag) and 3 hours infusion time should not exceed 6 hours at room temperature (15 to 30°C) or 12 hours if refrigerated (2 to 8°C).
For ORITINIV 1200 mg, diluted intravenous solution in an infusion bag should be used within 4 hours when stored at room temperature (15 to 30°C), or used within 12 hours when refrigerated at 2 to 8°C. The combined storage time (reconstituted solution in the vial and diluted solution in the bag) and 1 hour infusion time should not exceed 4 hours at room temperature (15 to 30°C) or 12 hours if refrigerated (2 to 8°C).
12. Special Handling Instructions
- Incompatibilities
ORITINIV 400 mg is administered intravenously. ORITINIV 400 mg should only be diluted in D5W. Do NOT use sodium chloride injection for dilution as it is incompatible with ORITINIV 400 mg and may cause precipitation of the drug. Therefore, other intravenous substances, additives or other medications mixed in sodium chloride injection should not be added to ORITINIV 400 mg single-dose vials or infused simultaneously through the same intravenous line or through a common intravenous port.
In addition, drugs formulated at a basic or neutral pH may be incompatible with ORITINIV 400 mg. ORITINIV 400 mg should not be administered simultaneously with commonly used intravenous drugs through a common intravenous port. If the same intravenous line is used for sequential infusion of additional medications, the line should be flushed before and after infusion of ORITINIV 400 mg with D5W.
ORITINIV 1200 mg is administered intravenously. ORITINIV 1200 mg should only be diluted with either D5W or 0.9% Sodium Chloride Injection.
Additionally, drugs formulated at a basic or neutral pH may be incompatible with ORITINIV 1200 mg. ORITINIV 1200 mg should not be administered simultaneously with commonly used intravenous drugs through a common intravenous port. If the same intravenous line is used for sequential infusion of additional medications, the line should be flushed before and after infusion of ORITINIV 1200 mg with 0.9% sodium chloride injection or D5W.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper/common name: Oritavancin phosphate
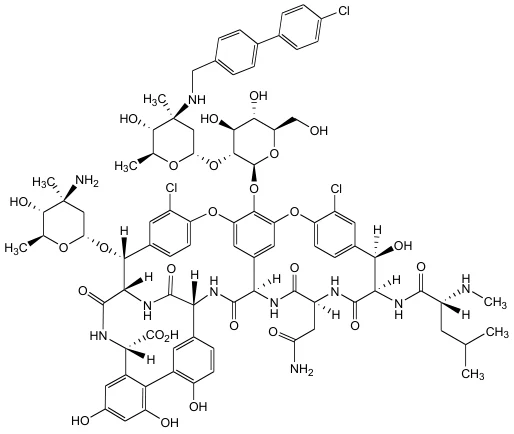
Chemical name: [4”R]-22-O-(3-amino-2,3,6-trideoxy-3-C-methyl-α-L-arabino-hexopyranosyl)-N3’’-[(4’-chloro[1,1’-biphenyl]-4-yl)methyl] vancomycin phosphate [1:2] [salt]
Molecular formula and molecular mass: C86H97N10O26Cl3•2H3PO4 and the molecular weight is 1989.09 g.mol-1. Oritavancin base weight is 1793.12 g·mol−1.
Structural formula:
•2H3PO4
Physicochemical properties:
(a) Physical form (for example [e.g.], polymorphic form, solvate, hydrate):
White to pale pink solid
(b) Solubilities and Dose/Solubility Volume over the physiological pH range (1.2-6.8):
Soluble in water (60.75 mg/mL); solubility is affected by pH and buffer species used; decreasing considerably at neutral/basic pH; solubility in 5% Dextrose/water (D5W) is ≥33.3 to < 100 mg/mL
(c) pKa:
Ionization constants are 3.2, 7.1, 7.4, 8.8, 9.6, 10.3, 12.1 (0.2 mM in 0.166 M NaCl)
Product Characteristics:
ORITINIV (oritavancin) powder for solution, for injection, contains oritavancin diphosphate, a semisynthetic lipoglycopeptide antibacterial drug for intravenous infusion.
ORITINIV 400 mg for injection is supplied as a sterile white to off-white lyophilized powder in a single-dose clear glass vial that contains 400 mg of oritavancin (equivalent to 444 mg oritavancin diphosphate).
Each vial is reconstituted with sterile water for injection and further diluted with 5% dextrose injection
(D5W) for intravenous infusion. Both the reconstituted solution and the diluted solution for infusion should be a clear, colorless to pale yellow solution, free of visible particles, see 4 Dosage and Administration.
ORITINIV 1200 mg for injection is supplied as a sterile white to off-white or pink lyophilized powder in a single-dose clear glass vial that contains 1,200 mg of oritavancin (equivalent to 1331.16 mg oritavancin diphosphate).
The vial is reconstituted with sterile water for injection and further diluted with 0.9% sodium chloride injection or 5% dextrose in sterile water (D5W) for intravenous infusion. Both the reconstituted solution and the diluted solution for infusion should be a clear, colorless to pink solution, free of visible particles, see 4 Dosage and Administration.
14. Clinical Trials
14.1. Clinical Trials by Indication
Table 8 - Summary of Patient Demographics for Clinical Trials in ABSSSI
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| SOLO I (tmc-ori-10-01) | A Multicenter, Double-Blind, Randomized Study to Evaluate the Efficacy and Safety of Single-Dose IV ORITINIV vs IV Vancomycin for the Treatment of Patients with Acute Bacterial Skin and Skin Structure Infections | ORITINIV: 1200 mg single dose, IV infusion, followed by placebo infusions every 12 hours, for 7 to 10 days. Vancomycin: either a 1 g dose or at 15 mg/kg IV infusion, every 12 hours for 7 to 10 days | Patients with ABSSSI ORITINIV: n=475 Vancomycin: n=479 | 45.2 years (18-93 years) | Male: n=602 (63.1%) Female: n=352 (36.9%) |
| SOLO II (tmc-ori-10-02) | A Multicenter, Double-Blind, Randomized Study to Evaluate the Efficacy and Safety of Single-Dose IV ORITINIV vs IV Vancomycin for the Treatment of Patients with Acute Bacterial Skin and Skin Structure Infections | ORITINIV: 1200 mg single dose, IV infusion, followed by placebo infusions every 12 hours, for 7 to 10 days. Vancomycin: either a 1 g dose or 15 mg/kg IV infusion, every 12 hours for 7 to 10 days | Patients with ABSSSI ORITINIV: n=503 Vancomycin: n=502 | 44.7 years (18-92 years) | Male: n=681 (67.8%) Female: n=324 (32.2%) |
aABSSSI=: Acute Bacterial Skin and skin structure infections included traumatic and surgical wound infections (onset within 7 days prior to randomization and no later than 30 days following the trauma or surgical procedure); cellulitis/erysipelas (onset within 7 days prior to randomization); and major cutaneous abscesses. Inclusion also required the presence of signs and symptoms of systemic inflammation and a minimum lesion surface area of 75.0 cm2.
IV = intravenous
A total of 1987 adults with clinically documented ABSSSI suspected or proven to be due to Gram-positive pathogens were randomized into two identically designed, randomized, double-blind, multi-center, multinational, non-inferiority trials (SOLO I and SOLO II) comparing a single 1200 mg intravenous dose of ORITINIV to intravenous vancomycin (1 g or 15 mg/kg every 12 hours) for 7 to 10 days. The primary analysis population (modified intent to treat, mITT) included all randomized patients who received any study drug. Patients could receive concomitant aztreonam or metronidazole for suspected Gram-negative and anaerobic infection, respectively.
Patient demographic and baseline characteristics were balanced between treatment groups. Across the two trials, approximately 64% of patients were Caucasian and 65% were males. The mean age was 45 years and the mean body mass index was 27 kg/m2. Approximately 60% of patients were enrolled from the United States and 27% of patients from Asia. A history of diabetes was present in 14% of patients. The types of ABSSSI across both trials included cellulitis/erysipelas (40%), wound infection (29%), and major cutaneous abscesses (31%). Median infection area at baseline across both trials was 266.6 cm2.
The primary endpoint in both trials was early clinical response (responder), defined as cessation of spread or reduction in size of baseline lesion, absence of fever, and no rescue antibacterial drug at 48 to 72 hours after initiation of therapy. See Table 9.
Key secondary endpoints were the percentage of patients achieving a 20% or greater reduction in lesion area from baseline at 48 to 72 hours after initiation of therapy (see Table 10) and the investigator-assessed clinical cure at post-therapy evaluation at day 14 to 24 (7 to 14 days from end of blinded therapy) (see Table 11). A patient was categorized as a clinical success if the patient experienced a complete or nearly complete resolution of baseline signs and symptoms related to primary ABSSSI site (erythema, induration/edema, purulent drainage, fluctuance, pain, tenderness, local increase in heat/warmth) such that no further treatment with antibacterial drugs was needed.
The primary endpoint and two key secondary endpoints were prespecified for noninferiority testing with a margin of 10% using the modified intention to treat (mITT) population.
Study Results
Table 9 - Clinical Response Rates in ABSSSI Trials using Early Clinical Respondersa, b at 48-72 Hours after Initiation of Therapy
| Study | Oritavancin n /N (%) | Vancomycin n /N (%) | Difference (95% CI)c |
| SOLO I (tmc-ori-10-01) | 391/475 (82.3) | 378/479 (78.9) | 3.4 (-1.6, 8.4) |
| SOLO II (tmc-ori-10-02) | 403/503 (80.1) | 416/502 (82.9) | -2.7 (-7.5, 2.0) |
a Cessation of spread or reduction in size of baseline lesion, absence of fever (<37.7°C) and no rescue antibacterial drug at 48 to 72 hours.
b Patients who died at 48 to 72 hours, after initiation of therapy or who had increase in lesion size at 48 to 72 hours, after initiation of therapy or who used non-study antibacterial therapy during first 72 hours or who had an additional, unplanned, surgical procedure or who had missing measurements during the first 72 hours from initiation of study drug were classified as nonresponders.
c 95% CI based on the Normal approximation to Binomial distribution.
Table 10 - Clinical Response Ratesa in ABSSSI Trials using Reduction in Lesion Area of 20% or Greater at 48-72 Hours after Initiation of Therapy
| Study | Oritavancin n /N (%) | Vancomycin n /N (%) | Difference (95% CI)b |
| SOLO I (tmc-ori-10-01) | 413/475 (86.9) | 397/479 (82.9) | 4.1 (-0.5, 8.6) |
| SOLO II (tmc-ori-10-02) | 432/503 (85.9) | 428/502 (85.3) | 0.6 (-3.7, 5.0) |
a Patients who died at 48 to 72 hours, after initiation of therapy or who had increase in lesion size at 48 to 72 hours, after initiation of therapy or who used non-study antibacterial therapy during first 72 hours or who had an additional, unplanned, surgical procedure or who had missing measurements during the first 72 hours from initiation of study drug were classified as nonresponders.
c 95% CI based on the Normal approximation to Binomial distribution.
Table 11 – Investigator-Assessed Clinical Cure Ratesa in ABSSSI Trials at the Follow-Up Visit (7-14 days after end of therapy)
| Study | Oritavancin n /N (%) | Vancomycin n /N (%) | Difference (95% CI)b |
SOLO I (tmc-ori-10-01) mITT CE | 378/475 (79.6) 362/394 (91.9) | 383/479 (80.0) 370/397 (93.2) | -0.4 (-5.5, 4.7) -1.3 (-5.0,2.3) |
SOLO II (tmc-ori-10-02) mITT CE | 416/503 (82.7) 398/427 (93.2) | 404/502 (80.5) 387/408 (94.9) | 2.2 (-2.6, 7.0) -1.6 (-4.9,1.6) |
a Clinical cure was defined as being achieved if the patient experienced a complete or nearly complete resolution of baseline signs and symptoms as described above.
b 95% CI based on the Normal approximation to Binomial distribution mITT population consisted of all randomized patients who received study drug; CE population consisted of all mITT patients who did not have violations of inclusion and exclusion criteria, completed treatment and had investigator assessment at the Follow-Up Visit.
Outcomes by Baseline Pathogen: Table 12 shows outcomes in patients with an identified baseline pathogen in the microbiological Intent-to-Treat (microITT) population in a pooled analysis of SOLO I and SOLO II. The outcomes shown in the table are clinical response rates at 48 to 72 hours and clinical success rates at follow-up study day 14 to 24.
Table 12 - Outcomes by Baseline Pathogen (microITT)
| Pathogen | At 48-72 hours | Study day 14 to 24 | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Early Clinical Respondera | ≥ 20% reduction in lesion sizeb | Clinical Curec | ||||||||
Oritavancin n/N (%) | Vancomycin n/N (%) | Oritavancin n/N (%) | Vancomycin n/N (%) | Oritavancin n/N (%) | Vancomycin n/N (%) | |||||
| Staphylococcus aureus | 388/470 = 82.6% | 391/468 = 83.5% | 419/470 = 89.1% | 404/468 = 86.3% | 389/470 = 82.8% | 393/468 = 84% | ||||
| Methicillin-susceptible | 222/268 (82.8) | 233/272 (85.7) | 231/268 (86.2) | 232/272 (85.3) | 220/268 (82.1) | 229/272 (84.2) | ||||
| Methicillin-resistant | 166/204 (81.4) | 162/201 (80.6) | 190/204 (93.1) | 175/201 (87.1) | 170/204 (83.3) | 169/201 (84.1) | ||||
| Streptococcus pyogenes | 21/31 (67.7) | 23/32 (71.9) | 24/31 (77.4) | 24/32 (75.0) | 25/31 (80.6) | 23/32 (71.9) | ||||
| Streptococcus agalactiae | 7/8 (87.5) | 12/12 (100.0) | 8/8 (100.0) | 12/12 (100.0) | 7/8 (87.5) | 11/12 (91.7) | ||||
| Streptococcus dysgalactiae | 7/9 (77.8) | 6/6 (100.0) | 6/9 (66.7) | 5/6 (83.3) | 7/9 (77.8) | 3/6 (50.0) | ||||
| Streptococcus anginosus group | 28/33 (84.8) | 40/45 (88.9) | 29/33 (87.9) | 42/45 (93.3) | 25/33 (75.8) | 38/45 (84.4) | ||||
| Enterococcus faecalis | 11/13 (84.6) | 10/12 (83.3) | 10/13(76.9) | 8/12 (66.7) | 8/13 (61.5) | 9/12 (75.0) | ||||
a Early clinical response was defined as a composite of the cessation of spread or reduction in size of baseline lesion, absence of fever and no rescue antibacterial drug at 48-72 hours.
b Patients achieving a 20% or greater reduction in lesion area from baseline at 48-72 hours after initiation of therapy.
c Clinical cure was defined if the patient experienced a complete or nearly complete resolution of baseline signs and symptoms as described above.
15. Microbiology
ORITINIV is a semi synthetic, lipoglycopeptide antibacterial drug. ORITINIV exerts a concentration dependent bactericidal activity in vitro against S. aureus, S. pyogenes, and E. faecalis.
Mechanism of Action
See 10.1 Clinical Pharmacology, Mechanism of Action.
Resistance
In serial passage studies, resistance to oritavancin was observed in isolates of S. aureus and E. faecalis.
Resistance to oritavancin was not observed in clinical studies.
Interaction with Other Antimicrobials
In in vitro studies, oritavancin exhibits synergistic bactericidal activity in combination with gentamicin, moxifloxacin or rifampicin against isolates of methicillin-susceptible S. aureus (MSSA), with gentamicin or linezolid against isolates of heterogenous vancomycin-intermediate S. aureus (hVISA), VISA, and vancomycin-resistant S. aureus (VRSA), and with rifampin against isolates of VRSA. In vitro studies demonstrated no antagonism between oritavancin and gentamicin, moxifloxacin, linezolid or rifampin.
Antibacterial Activity
Oritavancin has been shown to be active against most isolates of the following bacteria, both in vitro and in clinical infections, see 1 Indications.
Gram-positive micro-organisms:
- Staphylococcus aureus
- Streptococcus pyogenes
- Streptococcus agalactiae
- Streptococcus dysgalactiae
- Streptococcus anginosus group (includes S. anginosus, S. intermedius, and S. constellatus)
- Enterococcus faecalis (vancomycin-susceptible isolates only)
The following in vitro data are available, but their clinical significance has not been established.
At least 90% of isolates of the following microorganisms exhibit an in vitro minimum inhibitory concentration (MIC) less than or equal to 0.12 mcg/mL for oritavancin. However, the safety and effectiveness of oritavancin in treating clinical infections due to these bacteria have not been established in adequate and well-controlled clinical trials.
- Enterococcus faecium (vancomycin susceptible isolates only)
Susceptibility Test Methods
When available, the results of in vitro susceptibility test results for antimicrobial drugs used in resident hospitals should be provided to the physician as periodic reports which describe the susceptibility profile of nosocomial and community-acquired pathogens. These reports should aid the physician in selecting the most effective antimicrobial.
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimal inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Oritavancin powder is dissolved and diluted in the presence of 0.002% polysorbate 80 and broth test medium is supplemented with polysorbate 80 to a final concentration of 0.002%. CLSI-approved MIC value interpretive criteria are shown in Table 13.
Table 13: MIC Susceptibility Test Interpretive Criteria for Oritavancina
| Pathogen | Susceptible MIC Value (mcg/mL) | ||
|---|---|---|---|
| S | Ib | Rb | |
| Staphylococcus aureus (including methicillin-resistant isolates) | ≤0.12 | - | - |
| Streptococcus pyogenes, Streptococcus agalactiae, Streptococcus dysgalactiae, Streptococcus anginosus, Streptococcus constellatus, and Streptococcus intermedius | ≤0.25 | - | - |
| Enterococcus faecalis (vancomycin-susceptible isolates only) | ≤0.12 | - | - |
I=intermediate; MIC=minimum inhibitory concentration; R=resistant; S=susceptible.
aAs determined by broth microdilution with 0.002% polysorbate-80 during oritavancin dissolution and dilution and in the final assay.
bThe current absence of resistant isolates precludes defining any results other than “Susceptible”. Isolates yielding test results other than “Susceptible” should be retested, and if the result is confirmed, the isolate should be submitted to a reference laboratory for further testing.
Quality Control
Quality control (QC) limits for MIC susceptibility testing are shown in Table 14.
Table 14: QC Ranges for Oritavancina
| Quality Control Strain | MIC Range (mcg/mL) |
|---|---|
| Staphylococcus aureus ATCC 29213 | 0.016 - 0.12 |
| Streptococcus pneumoniae ATCC 49619 | 0.001 - 0.004 |
| Enterococcus faecalis ATCC 29212 | 0.008 - 0.03 |
ATCC=American Type Culture Collection
aAs determined by broth microdilution with 0.002% polysorbate-80 during oritavancin dissolution and dilution and in the final assay.
16. Non-Clinical Toxicology
Genotoxicity: No mutagenic or clastogenic potential of oritavancin was found in a battery of tests, including an Ames assay, in vitro chromosome aberration assay in Chinese hamster ovary cells, in vitro forward mutation assay in mouse lymphoma cells, and an in vivo mouse micronucleus assay.
Carcinogenicity: No long-term animal studies have been performed to evaluate carcinogenic potential or whether oritavancin affects fertility in males or females.
Reproductive and Developmental Toxicology: When administered intravenously at doses up to 30 mg/kg, oritavancin did not affect the fertility or reproductive performance of male and female rats. Oritavancin did not affect the fertility or reproductive performance of male (exposed to daily doses up to 30 mg/kg for at least 4 weeks) and female rats (exposed to daily doses up to 30 mg/kg for at least 2 weeks prior to mating). Those daily doses would be equivalent to a human dose of 300 mg, or 25% of clinical dose. Higher doses were not evaluated in nonclinical fertility studies.