


Product Monograph - Xydalba
RECENT MAJOR LABEL CHANGES
| 1 Indications | 07/2024 |
|---|---|
| 4 Dosage and Administration | 07/2024 |
| 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic; Renal; 7.1.3 Pediatrics | 07/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
Recent Major label changes ..................................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ............................................................................................................... 4
1.2 Geriatrics ............................................................................................................... 5
2 CONTRAINDICATIONS .................................................................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 5
4.3 Administration ....................................................................................................... 7
4.4 Reconstitution ....................................................................................................... 7
5 OVERDOSAGE ............................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................... 9
7.1 Special Populations .............................................................................................. 12
7.1.1 Pregnant Women ............................................................................................ 12
7.1.2 Breast-feeding ................................................................................................. 12
7.1.3 Pediatrics ......................................................................................................... 12
7.1.4 Geriatrics ......................................................................................................... 13
8 ADVERSE REACTIONS ................................................................................................. 13
8.1 Adverse Reaction Overview ................................................................................. 13
8.2 Clinical Trial Adverse Reactions ........................................................................... 14
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .................................................... 16
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 16
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ............................. 17
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 17
9 DRUG INTERACTIONS ................................................................................................. 18
9.2 Drug Interactions Overview ................................................................................. 18
9.3 Drug-Behavioural Interactions ............................................................................. 18
9.4 Drug-Drug Interactions ........................................................................................ 18
9.5 Drug-Food Interactions ........................................................................................ 18
9.6 Drug-Herb Interactions ........................................................................................ 18
9.7 Drug-Laboratory Test Interactions ....................................................................... 18
10 CLINICAL PHARMACOLOGY ........................................................................................ 19
10.1 Mechanism of Action ........................................................................................... 19
10.2 Pharmacodynamics ............................................................................................. 19
10.3 Pharmacokinetics ................................................................................................ 19
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 24
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 24
PART II: SCIENTIFIC INFORMATION ........................................................................................ 25
13 PHARMACEUTICAL INFORMATION ............................................................................. 25
14 CLINICAL TRIALS ......................................................................................................... 26
14.1 Clinical Trials by Indication .................................................................................. 26
15 MICROBIOLOGY ......................................................................................................... 35
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 38
PATIENT MEDICATION INFORMATION ................................................................................... 40
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
XYDALBA (dalbavancin for injection) is indicated for:
- treatment of adults and pediatric patients aged 3 months and older with acute bacterial skin and skin structure infections (ABSSSI), caused by susceptible isolates of the following gram-positive microorganisms: Staphylococcus aureus (including methicillin-susceptible and methicillin-resistant strains), Streptococcus pyogenes, Streptococcus agalactiae, Streptococcus dysgalactiae, Streptococcus anginosus group (including Streptococcus anginosus, Streptococcus intermedius, Streptococcus constellatus) and Enterococcus faecalis (vancomycin susceptible strains).
XYDALBA is not active against gram-negative bacteria; therefore, combination therapy may be clinically indicated if the ABSSSI is polymicrobial and includes a suspected or documented gram-negative pathogen.
XYDALBA has been studied in the treatment of cellulitis/erysipelas, major cutaneous abscesses, or wound infections. Other types of complicated skin infections (including diabetic foot ulcer, necrotizing fasciitis, or decubitus ulcer) have not been studied.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of XYDALBA and other antibacterial drugs, XYDALBA should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.1 Pediatrics
Pediatrics (≥ 3 months of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of XYDALBA in pediatric patients (3 months of age and older) has been established. Therefore, Health Canada has authorized an indication for pediatric use in patients 3 months of age and older (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.3 Pediatrics).
Pediatrics (< 3 months of age): The safety and efficacy of XYDALBA in patients less than 3 months of age have not been established; therefore, Health Canada has not authorized an indication for pediatric use in patients less than 3 months old.
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies suggests that use in the geriatric population is not associated with significant differences in safety or efficacy. The pharmacokinetics of XYDALBA was not significantly altered with age; therefore, no dosage adjustment is necessary based on age alone (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
2 CONTRAINDICATIONS
XYDALBA (dalbavancin for injection) is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING. No data are available on cross-reactivity between dalbavancin and other glycopeptides, including vancomycin and telavancin.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The safety and efficacy of XYDALBA when administered for more than 1500 mg have not been established.
- In ABSSSI, the types of infections treated were cellulitis/erysipelas, major cutaneous abscesses, and wound infections. Other types of skin infections have not been studied.
- XYDALBA is not active against gram-negative bacteria; therefore, combination therapy may be clinically indicated if the ABSSSI is polymicrobial and includes a suspected or documented gram-negative pathogen.
- See Recommended Dose and Dosage Adjustment for Renal Impairment.
- See Recommended Dose and Dosage Adjustment for Hepatic Impairment.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
Adults
The recommended dosage regimen for XYDALBA in adult patients with ABSSSI is 1500 mg, administered either as a single dose or 1000 mg followed one week later by 500 mg. XYDALBA should be administered over 30 minutes by intravenous infusion.
Pediatrics (≥ 6 years of age to < 18 years of age)
The recommended dosage regimen for XYDALBA in children (≥ 6 years of age) and adolescent patients with ABSSSI is a single dose of 18 mg / kg of body weight (maximum of 1500 mg). XYDALBA should be administered over 30 minutes by intravenous infusion.
Pediatrics (≥ 3 months of age to < 6 years of age)
The recommended dosage regimen for XYDALBA in infant and children patients (aged from 3 months to less than 6 years) with ABSSSI is a single dose of 22.5 mg / kg of body weight (maximum of 1500 mg). XYDALBA should be administered over 30 minutes by intravenous infusion.
Pediatrics (< 3 months of age)
Health Canada has not authorized an indication for pediatric use in patients less than 3 months of age.
Dosage Adjustment
Renal Impairment in Adults
Dose adjustments are not required for patients with mild or moderate renal impairment (creatinine clearance ≥ 30 to 79 mL/min). Dose adjustments are not required for patients receiving regularly scheduled hemodialysis (3 times/week), and XYDALBA may be administered without regard to the timing of hemodialysis.
In patients with renal impairment whose known creatinine clearance is < 30 mL/min and who are not receiving regularly scheduled hemodialysis, the recommended dose for XYDALBA should be reduced to either 1000 mg administered as a single infusion or 750 mg followed one week later by 375 mg (see 7 WARNINGS AND PRECAUTIONS, Renal and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Table 1 – Dosage of XYDALBA in Patients with Renal Impairment
| Estimated CrCl1 | XYDALBA Single Dose Regimen2 | XYDALBA Two-Dose Regimen2 |
|---|---|---|
| > 30 mL/min or on regular hemodialysis | 1500 mg | 1000 mg followed one week later by 500 mg |
| < 30 mL/min and not on regular hemodialysis | 1000 mg | 750 mg followed one week later by 375 mg |
1 As calculated using the Cockcroft-Gault formula.
2 Administer by intravenous infusion over 30 minutes.
Renal Impairment in Pediatrics
Dose adjustments are not required for pediatric patients with mild or moderate renal impairment (creatinine clearance ≥ 30 to 79 mL/min). There is insufficient information to recommend dosage adjustment for pediatric patients with creatinine clearance less than 30 mL/min/1.73m2 as no observed pharmacokinetic data is available. XYDALBA is therefore not recommended for use in pediatric patients with severe renal impairment (see 7 WARNINGS AND PRECAUTIONS, Renal and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Hepatic Impairment in Adults
No dose adjustment of XYDALBA is recommended for patients with mild hepatic impairment (Child-Pugh Class A). Caution should be exercised when prescribing XYDALBA to patients with moderate or severe hepatic impairment (Child-Pugh Class B & C) as no data are available to determine appropriate dosing in these patients (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Hepatic Impairment in Pediatrics
The use of XYDALBA in pediatric patients with hepatic impairment (mild, moderate or severe) has not been evaluated and therefore caution should be exercised when prescribing XYDALBA to these patients (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
4.3 Administration
Intravenous Use
After reconstitution and dilution, XYDALBA is to be administered via intravenous infusion, using a total infusion time of 30 minutes.
Do not co-infuse XYDALBA with other medications or electrolytes. Sodium chloride containing solutions may cause precipitation and should not be used. The compatibility of reconstituted XYDALBA with intravenous medications, additives, or substances other than 5% Dextrose Injection, has not been established.
If a common intravenous line is being used to administer other drugs in addition to XYDALBA, the line should be flushed before and after each XYDALBA infusion with 5% Dextrose Injection.
4.4 Reconstitution
XYDALBA (dalbavancin for injection) must be reconstituted with either Sterile Water for Injection, or 5% Dextrose Injection, and subsequently diluted only with 5% Dextrose Injection, to a final concentration of 1 mg/mL to 5 mg/mL.
Reconstitution: XYDALBA must be reconstituted under aseptic conditions, using 25 mL of either Sterile Water for Injection, or 5% Dextrose Injection, for each 500 mg vial (Table 2). To avoid foaming, alternate between gentle swirling and inversion of the vial until its contents are completely dissolved. Do not shake. The reconstituted vial contains 20 mg/mL dalbavancin as a clear, colorless to yellow solution.
Table 2 – Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL |
|---|---|---|---|
| 48 mL | 25 mL | 25 mL | 20 mg/mL dalbavancin |
Reconstituted vials may be stored either refrigerated at 2 to 8°C, or at controlled room temperature of 20 to 25°C. Do not freeze.
Dilution: Aseptically transfer the required dose of reconstituted dalbavancin solution from the vial(s) to an intravenous bag or bottle containing 5% Dextrose Injection. For pediatric patients the dose of dalbavancin will vary according to the age and weight of the child, up to a maximum of 1500 mg (see 4.2 Recommended Dose and Dosage Adjustment). The diluted solution must have a final dalbavancin concentration of 1 mg/mL to 5 mg/mL. Discard any unused portion of the reconstituted solution.
Once diluted into an intravenous bag or bottle as described above, XYDALBA may be stored either refrigerated at 2 to 8°C or at a controlled room temperature of 20 to 25°C. Do not freeze.
The total time from reconstitution to dilution to administration should not exceed 48 hours.
Like all parenteral drug products, diluted XYDALBA should be inspected visually for particulate matter prior to infusion. If particulate matter is identified, do not use.
5 OVERDOSAGE
Specific information is not available on the treatment of overdose with XYDALBA, as dose- limiting toxicity has not been observed in clinical studies. In Phase 1 studies, healthy volunteers have been administered cumulative doses of up to 4500 mg over a period of up to 8 weeks, with no signs of toxicity or laboratory results of clinical concern.
Treatment of overdose with XYDALBA should consist of observation and general supportive measures. Although no information is available specifically regarding the use of hemodialysis to treat overdose, in a Phase 1 study in patients with renal impairment less than 6% of the recommended dalbavancin dose was removed after 3 hours of hemodialysis (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 – Dosage Forms, Strengths, Composition and Packaging
XYDALBA is supplied in clear glass vials as a sterile, lyophilized, preservative-free, white to off-white to pale yellow powder containing dalbavancin hydrochloride (equivalent to 500 mg of dalbavancin as the free base).
One box contains one single-use 48 mL type I glass vial with an elastomeric stopper and a green flip off seal.
7 WARNINGS AND PRECAUTIONS
General
Infusion-Related Reactions
XYDALBA is administered via intravenous infusion, using a total infusion time of 30 minutes to minimize the risk of infusion-related reactions. Rapid intravenous infusions of XYDALBA can cause reactions that resemble “Red-Man Syndrome”, including flushing of the upper body, urticaria, pruritus and/or rash. Stopping or slowing the infusion may result in cessation of these reactions.
Mixed Infections
In mixed infections in which gram-negative bacteria are suspected, patients should also be treated with an appropriate antibacterial agent(s) against gram-negative bacteria (see 15 MICROBIOLOGY).
Limitations of the Clinical Data
The safety and efficacy of XYDALBA when administered for more than 1500 mg have not been established. In the major trials in acute bacterial skin and skin structure infections (ABSSSI), the types of infections treated were confined to cellulitis/erysipelas, abscesses and wound infections only. There is no experience with XYDALBA in the treatment of severely immunocompromised patients.
Driving and Operating Machinery
No studies on the effects on the ability to drive and use machines have been performed. Dizziness may occur and may have an effect on driving and the use of machines (see 8 ADVERSE
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous (IV) (infusion) | Lyophilized Powder for Solution/ 500 mg dalbavancin (as dalbavancin hydrochloride) per vial | Hydrochloric Acid Lactose Monohydrate Mannitol Sodium Hydroxide |
REACTIONS). Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Gastrointestinal
Clostridium difficile-Associated Disease (CDAD)
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including XYDALBA. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see 8 ADVERSE REACTIONS).
Hepatic/Biliary/Pancreatic
No dose adjustment of XYDALBA is recommended for adult patients with mild hepatic impairment (Child-Pugh Class A). Caution should be exercised when prescribing XYDALBA to adult patients with moderate or severe hepatic impairment (Child-Pugh Class B & C) as no data are available to determine appropriate dosing in these patients (see 4.2 Recommended Dose and Dosage Adjustment).
In Phase 2 and 3 clinical trials in adults, more XYDALBA than comparator-treated subjects with normal baseline transaminase levels had post-baseline alanine aminotransferase (ALT) elevation greater than 3 times the upper limit of normal (ULN). Overall, abnormalities in liver tests (ALT, AST, bilirubin) were reported with similar frequency in the XYDALBA and comparator arms (see 8 ADVERSE REACTIONS).
Caution should be exercised when prescribing XYDALBA to pediatric patients with hepatic impairment (mild, moderate or severe) as no data are available to determine appropriate dosing in these patients (see 4.2 Recommended Dose and Dosage Adjustment).
Immune
Hypersensitivity Reactions
Serious hypersensitivity (anaphylactic/anaphylactoid) and skin reactions have been reported in patients treated with XYDALBA. If an allergic reaction occurs, treatment with XYDALBA should be discontinued and appropriate therapy for the allergic reaction should be instituted. Before using XYDALBA, inquire carefully about previous hypersensitivity reactions to glycopeptides, and due to the possibility of cross-sensitivity, exercise caution in patients with a history of glycopeptide allergy (see 8 ADVERSE REACTIONS).
Renal
Information on the efficacy and safety of XYDALBA in patients with creatinine clearance
< 30 mL/min is limited. Based on simulations, dose adjustment is needed for adult patients with renal impairment whose known creatinine clearance is < 30 mL/min and who are not receiving regular hemodialysis (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
There is insufficient information to recommend dosage adjustment for pediatric patients with creatinine clearance < 30 mL/min/1.73m2 and XYDALBA is therefore not recommended for use in pediatric patients with severe renal impairment (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Reproductive Health: Female and Male Potential
Fertility
Studies in animals have shown reduced fertility (see 16 NON-CLINICAL TOXICOLOGY). The potential risk for humans is unknown.
Sensitivity/Resistance
Development of Drug Resistant Bacteria
Prescribing XYDALBA in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Potential for Microbial Overgrowth
The use of any antibiotics, including XYDALBA, may promote the overgrowth of non-susceptible micro-organisms. If superinfection occurs during therapy, appropriate measures should be taken.
7.1 Special Populations
7.1.1 Pregnant Women
There are no data from the use of XYDALBA in pregnant women. Studies in animals have shown reproductive toxicity (see below and 16 NON-CLINICAL TOXICOLOGY). XYDALBA should not be used during pregnancy unless the benefit to the mother clearly outweighs the risk to the fetus.
No treatment-related malformations or embryo-fetal toxicity were observed in pregnant rats or rabbits at clinically relevant exposures of dalbavancin. Treatment of pregnant rats with dalbavancin at 3.5 times the human dose on an exposure basis during early embryonic development and from implantation to the end of lactation resulted in delayed fetal maturation and increased fetal loss, respectively (see below and 16 NON-CLINICAL TOXICOLOGY).
Animal Data
No evidence of embryo or fetal toxicity was found in the rat or rabbit at a dose of 15 mg/kg/day (1.2 and 0.7 times the human dose on an exposure basis, respectively). Delayed fetal maturation was observed in the rat at a dose of 45 mg/kg/day (3.5 times the human dose on an exposure basis).
In a rat prenatal and postnatal development study, increased embryo lethality and increased offspring deaths during the first week post-partum were observed at a dose of 45 mg/kg/day (3.5 times the human dose on an exposure basis) (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
It is not known whether XYDALBA or its metabolites are excreted in human milk. However, dalbavancin is excreted in the milk of lactating rats and may be excreted in human breast milk. Therefore, caution should be exercised when XYDALBA is administered to a nursing woman.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for XYDALBA and any potential adverse effects on the breastfed child from XYDALBA or from the underlying maternal condition.
7.1.3 Pediatrics
Pediatrics (< 3 months of age): Based on data submitted and reviewed by Health Canada, the safety and efficacy of XYDALBA in pediatric patients less than 3 months of age has not been established; therefore, Health Canada has not authorized an indication for pediatric use in patients less than 3 months of age.
7.1.4 Geriatrics
Of the 2473 patients treated with XYDALBA in Phase 2 and 3 clinical trials, 403 patients (16.3%) were 65 years of age or older. The efficacy and tolerability of XYDALBA were similar to comparator regardless of age. The pharmacokinetics of XYDALBA was not significantly altered with age; therefore, no dosage adjustment is necessary based on age alone.
XYDALBA is substantially excreted by the kidney, and the risk of adverse reactions may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection in this age group.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse reactions were evaluated for 2473 adult patients treated with XYDALBA: 1778 patients were treated with XYDALBA in seven Phase 2/3 trials comparing XYDALBA to comparator antibacterial drugs and 695 patients were treated with XYDALBA in one Phase 3 trial comparing XYDALBA single and two-dose regimens. In pediatric patients, adverse reactions were evaluated in 168 patients treated with XYDALBA (90 patients receiving a single-dose regimen and 78 patients receiving a two-dose regimen) in one Phase 3 trial comparing XYDALBA to comparator antibacterial drugs.
Serious Adverse Reactions and Adverse Reactions Leading to Discontinuation
Serious adverse reactions occurred in 121/2473 (4.9%) of patients treated with any regimen of XYDALBA. In the Phase 2/3 trials comparing XYDALBA to comparator, serious adverse reactions occurred in 109/1778 (6.1%) of patients in the XYDALBA group and 80/1224 (6.5%) of patients in the comparator group. In a Phase 3 trial comparing XYDALBA single and two-dose regimens, serious adverse reactions occurred in 7/349 (2.0%) of patients in the XYDALBA single dose group and 5/346 (1.4%) of patients in the XYDALBA two-dose group.
XYDALBA was discontinued due to an adverse reaction in 64/2473 (2.6%) patients treated with any regimen of XYDALBA. In the Phase 2/3 trials comparing XYDALBA to comparator, XYDALBA was discontinued due to an adverse reaction in 53/1778 (3.0%) of patients in the XYDALBA group and 35/1224 (2.9%) of patients in the comparator group. In a Phase 3 trial comparing XYDALBA single and two-dose regimens, XYDALBA was discontinued due to an adverse reaction in 6/349 (1.7%) of patients in the XYDALBA single dose group and 5/346 (1.4%) of patients in the XYDALBA two-dose group.
Serious adverse reactions occurred in 3/168 (1.8%) of pediatric patients treated with XYDALBA, all in the single-dose arm. There were no adverse reactions leading to XYDALBA discontinuation.
Most Common Adverse Reactions
The most common adverse reactions in adult patients treated with any regimen of XYDALBA were nausea (4.7%), headache (3.8%), and diarrhea (3.4%). The median duration of adverse reactions was 3.0 days in patients treated with XYDALBA. In the Phase 2/3 trials comparing XYDALBA to comparator, the median duration of adverse reactions was 3.0 days for patients in the XYDALBA group and 4.0 days in patients in the comparator group. In a Phase 3 trial comparing XYDALBA single and two-dose regimens, the median duration of adverse reactions was 3.0 days for patients in the XYDALBA single and two-dose group. In pediatric patients the most common adverse reactions were pyrexia (1.2%) and cough (1.2%), both observed in 2 patients enrolled in the two-dose regimen.
Description of Selected Class Adverse Reactions
Ototoxicity has been associated with glycopeptide use (e.g., vancomycin); patients who are receiving concomitant therapy with an ototoxic agent, such as an aminoglycoside, may be at increased risk.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 4 lists adverse reactions occurring in 1% or more of patients treated with XYDALBA in Phase 2/3 clinical trials. A causal relationship between study drug and adverse reactions was not always established.
Table 4 – Treatment Emergent Adverse Events in ≥1% Patients Receiving XYDALBA by Decreasing Frequency: Pooled Data from 8 Phase 2/3 Studies
| XYDALBA Dosage Regimen | ||||
| XYDALBA Dosage Regimen | ||||
1500 mg Single Dosea n = 349 (%) | 1000 mg on Day 1 and 500 mg on Day 8b n = 2124 (%) | XYDALBA Any Dose Any Regimenc n = 2473 (%) | Comparatord n = 1224 (%) | |
1500 mg Single Dosea n = 349 (%) | 1000 mg on Day 1 and 500 mg on Day 8b n = 2124 (%) | XYDALBA Any Dose Any Regimenc n = 2473 (%) | Comparatord n = 1224 (%) | |
| Infection and infestations | ||||
| Urinary tract infection | 2 (0.6) | 36 (1.7) | 38 (1.5) | 16 (1.3) |
| Cellulitis | 1 (0.3) | 28 (1.3) | 29 (1.2) | 18 (1.5) |
| Blood and lymphatic system disorders | ||||
| Anemia | 1 (0.3) | 36 (1.7) | 37 (1.5) | 20 (1.6) |
| Psychiatric disorders | ||||
| Insomnia | 0 (0.0) | 28 (1.3) | 28 (1.1) | 30 (2.5) |
| Nervous system disorders | ||||
| Headache | 6 (1.7) | 87 (4.1) | 93 (3.8) | 59 (4.8) |
| Dizziness | 4 (1.1) | 28 (1.3) | 32 (1.3) | 15 (1.2) |
| Vascular disorders | ||||
| Hypertension | 1 (0.3) | 23 (1.1) | 24 (1.0) | 17 (1.4) |
| Edema peripheral | 0 (0.0) | 21 (1.0) | 21 (0.8) | 16 (1.3) |
| Respiratory, thoracic and mediastinal disorders | ||||
| Dyspnea | 1 (0.3) | 23 (1.1) | 24 (1.0) | 14 (1.1) |
| Gastrointestinal disorders | ||||
| Nausea | 12 (3.4) | 105 (4.9) | 117 (4.7) | 78 (6.4) |
| Diarrhea | 4 (1.1) | 81 (3.8) | 85 (3.4) | 70 (5.7) |
| Vomiting | 6 (1.7) | 53 (2.5) | 59 (2.4) | 37 (3.0) |
| Constipation | 2 (0.6) | 54 (2.5) | 56 (2.3) | 30 (2.5) |
| Abdominal pain | 1 (0.3) | 24 (1.1) | 25 (1.0) | 11 (0.9) |
| Skin and subcutaneous tissue disorders | ||||
| Pruritus | 6 (1.7) | 38 (1.8) | 44 (1.8) | 41 (3.3) |
| Rash | 2 (0.6) | 40 (1.9) | 42 (1.7) | 22 (1.8) |
| Investigations | ||||
| GGT increased | 0 (0.0) | 31 (1.5) | 31 (1.3) | 19 (1.6) |
| Hyperglycemia | 1 (0.3) | 24 (1.1) | 25 (1.0) | 14 (1.1) |
| Blood LDH increased | 0 (0.0) | 21 (1.0) | 21 (0.8) | 14 (1.1) |
| General disorders and administration site conditions | ||||
| Pyrexia | 1 (0.3) | 28 (1.3) | 29 (1.2) | 21 (1.7) |
GGT: Gamma-glutamyl transferase; LDH: Lactate dehydrogenase; TEAE = Treatment-emergent adverse event.
a Based on one study (Study DUR001-303, Trial 3) and should not be directly compared to the pooled data or the comparator.
b Based on 8 Phase 2/3 studies, including the two-dose XYDALBA arm of Study DUR001-303 (Trial 3).
c Pooled XYDALBA columns are based on 8 Phase 2/3 studies including patients treated with either the XYDALBA single- or two-dose regimen.
d Comparators included linezolid, cefazolin, cephalexin and vancomycin. TEAEs in the comparator column should not be directly compared to TEAEs in the XYDALBA columns as 695 subjects in the XYDALBA columns did not include a comparator.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Table 5 lists adverse reactions occurring in 1% or more of pediatric patients treated with XYDALBA in the Phase 3 clinical trial. A causal relationship between study drug and adverse reactions was not always established.
Table 5 – Treatment Emergent Adverse Events in ≥1% (n>1) of Pediatric Patients Receiving XYDALBA – Trial 4
| XYDALBA Dosage Regimen | ||||
Single Dose n = 90 (%) | Two Dose n = 78 (%) | XYDALBA Any Dose Any Regimen n = 168 (%) | Comparatora n = 30 (%) | |
| General disorders and administration site conditions | ||||
| Pyrexia | 0 (0.0) | 2 (2.6) | 2 (1.2) | 0 (0.0) |
| Respiratory, thoracic and mediastinal disorders | ||||
| Cough | 0 (0.0) | 2 (2.6) | 2 (1.2) | 0 (0.0) |
a Comparators included vancomycin, oxacillin and flucloxacillin.
8.3 Less Common Clinical Trial Adverse Reactions
The following selected adverse reactions were reported in XYDALBA treated patients at a rate of less than 1% in these clinical trials:
Blood and lymphatic system disorders: hemorrhagic anemia, leucopenia, neutropenia, thrombocytopenia, petechiae, eosinophilia, thrombocytosis
Gastrointestinal disorders: gastrointestinal hemorrhage, melena, hematochezia
General disorders and administration site conditions: infusion-related reactions
Hepatobiliary disorders: hepatotoxicity
Immune system disorders: anaphylactic/anaphylactoid reaction
Infections and infestations: Clostridium difficile colitis, oral candidiasis, vulvovaginal mycotic infection
Investigations: hepatic transaminases increased, blood alkaline phosphatase increased, international normalized ratio increased
Metabolism and nutrition disorders: hypoglycemia
Respiratory, thoracic and mediastinal disorders: bronchospasm
Skin and subcutaneous tissue disorders: urticaria
Vascular disorders: flushing, phlebitis, wound hemorrhage, spontaneous hematoma
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
The following adverse reactions were reported in XYDALBA treated pediatric patients at a rate of less than 1% (n=1) in the pivotal clinical trial:
Eye disorders: eyelid oedema
Gastrointestinal disorders: constipation, diarrhea, vomiting
General disorders and administration site conditions: infusion site extravasation
Immune system disorders: drug hypersensitivity
Infections and infestations: abscess bacterial, bronchitis, nasopharyngitis, osteomyelitis bacterial, upper respiratory tract infection, varicella
Injury, poisoning and procedural complications: anaemia postoperative, ear injury, fall
Investigations: blood bilirubin increased
Metabolism and nutrition disorders: decreased appetite
Nervous system disorders: dizziness, febrile convulsions
Respiratory, thoracic and mediastinal disorders: epistaxis, nasal congestion, rhinorrhoea
Skin and subcutaneous tissue disorders: acne infantile, dermatitis atopic, pruritus, skin exfoliation
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Alanine Aminotransferase (ALT) Elevations
Among patients with normal baseline ALT levels treated with XYDALBA 17 (0.8%) had post- baseline ALT elevations greater than 3 times the upper limit of normal (ULN) including five subjects with post-baseline ALT values greater than 10 times ULN. Among patients with normal baseline ALT levels treated with non-XYDALBA comparators 2 (0.2%) had post-baseline ALT elevations greater than 3 times the upper limit of normal. Fifteen of the 17 patients treated with XYDALBA and one comparator patient had underlying conditions which could affect liver enzymes, including chronic viral hepatitis, history of alcohol abuse and metabolic syndrome. In addition, one XYDALBA-treated subject in a Phase 1 trial had post-baseline ALT elevations greater than 20 times ULN. ALT elevations were reversible in all subjects with follow-up assessments. No comparator-treated subject with normal baseline transaminases had post- baseline ALT elevation greater than 10 times ULN.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No behavioural, drug, food, herb or laboratory test interactions have been established.
9.3 Drug-Behavioural Interactions
Interactions with individual risks, such as alcohol consumption, sexual activity and smoking have not been established.
9.4 Drug-Drug Interactions
No clinical drug-drug interaction studies have been conducted with XYDALBA. There is minimal potential for drug-drug interactions between XYDALBA and cytochrome P450 (CYP450) substrates, inhibitors, or inducers (see 10.3 Pharmacokinetics, Metabolism).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Drug-laboratory test interactions have not been reported. XYDALBA at therapeutic concentrations does not artificially prolong prothrombin time (PT) or activated partial thromboplastin time (aPTT).
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Dalbavancin is a semisynthetic bactericidal lipoglycopeptide active against susceptible strains of gram-positive bacteria. Its mechanism of action involves interruption of cell wall synthesis by binding to the terminal D-alanyl-D-alanine of the stem peptide in nascent cell wall peptidoglycan, preventing cross-linking (transpeptidation and transglycosylation) of disaccharide subunits resulting in bacterial cell death (see 15 MICROBIOLOGY).
10.2 Pharmacodynamics
The antibacterial activity of dalbavancin appears to best correlate with the ratio of area under the concentration-time curve to minimal inhibitory concentration (AUC/MIC) for Staphylococcus aureus based on animal models of infection. An exposure-response analysis of a single study in patients with complicated skin and skin structure infections supports the two-dose regimen.
Cardiac Electrophysiology: In a randomized, positive- and placebo-controlled, thorough QT/QTc study, 200 healthy subjects received either dalbavancin 1000 mg intravenous (IV), dalbavancin 1500 mg IV, oral moxifloxacin 400 mg, or placebo. Neither dalbavancin 1000 mg nor dalbavancin 1500 mg had any clinically relevant adverse effect on cardiac repolarization.
10.3 Pharmacokinetics
Dalbavancin pharmacokinetic parameters have been characterized in healthy subjects, patients, and specific populations. Pharmacokinetic parameters following administration of single intravenous 1000 mg and 1500 mg doses were as shown in Table 6. The pharmacokinetics of dalbavancin can be described using a three-compartment model.
Table 6– Dalbavacin Pharmacokinetic Parameters in Healthy Subject
Cmax (mg/L) | Terminal t1/2 (h) | AUC0-24h (mg•h/L) | AUC0-Day7 (mg•h/L) | AUC0-∞ (mg•h/L) | CL (L/h) | |
| Single 1000 mg Dose | 287 (13.9)1 | 346 (16.5)2,3 | 3185 (12.8)1 | 11160 (41.1)2 | 23443 (40.9)2 | 0.0513 (46.8)2 |
| Single 1500 mg Dose | 423 (13.2)4 | ND | 4837 (13.7)4 | ND | ND | ND |
All values are presented as mean (% coefficient of variation).
1 Data from 50 healthy subjects.
2 Data from 12 healthy subjects.
3 Based upon population pharmacokinetic analyses of data from patients, the effective half-life is approximately 8.5 days (204 hours).
4 Data from 49 healthy subjects. Abbreviation: ND – not determined.
Absorption: In healthy subjects, dalbavancin AUC0-24h and Cmax both increased proportionally to dose following single intravenous (IV) dalbavancin doses ranging from 140 mg to 1500 mg, indicating linear pharmacokinetics.
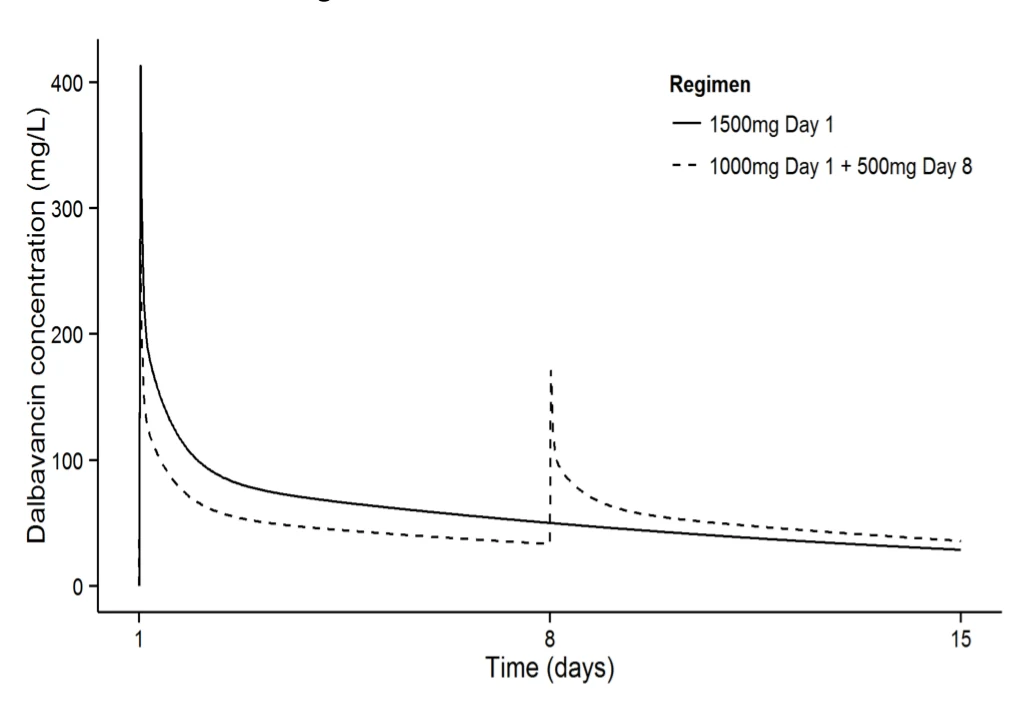
The predicted dalbavancin plasma concentration-time following two-dose regimen of 1000 mg following one week later by 500 mg and for the single dose regimen of 1500 mg are shown in Figure 1.
Figure 1 – Dalbavancin Plasma Concentrations versus time in a typical ABSSSI patient (simulation using population pharmacokinetic model) for both the single and the two-dose regimens.
No apparent accumulation of dalbavancin was observed following multiple IV infusions administered once weekly for up to eight weeks, with 1000 mg on Day 1 followed by up to seven weekly 500 mg doses, in healthy adults with normal renal function.
Distribution: Dalbavancin is reversibly bound to human plasma proteins, primarily to albumin. The plasma protein binding of dalbavancin is 93% and is not altered as a function of drug concentration, renal insufficiency, or hepatic insufficiency. The mean concentrations of dalbavancin achieved in skin blister fluid remain above 30 mg/L up to 7 days (approximately 146 hours) post dose, following 1000 mg IV dalbavancin. The mean ratio of the AUC0-144h in skin blister fluid/AUC0-144h in plasma is 0.60 (range 0.44 to 0.64).
Metabolism: Metabolites have not been observed in significant amounts in human plasma. The metabolites hydroxy-dalbavancin and mannosyl aglycone have been detected in urine (< 25% of administered dose). The metabolic pathways responsible for producing these metabolites have not been identified; however, due to the relatively minor contribution of metabolism to the overall elimination of dalbavancin, drug-drug interactions via inhibition or induction of metabolism of dalbavancin are not anticipated. Hydroxy-dalbavancin and mannosyl aglycone show significantly less antibacterial activity compared to dalbavancin.
In vitro studies using human microsomal enzymes and hepatocytes indicate that dalbavancin is not a substrate, inhibitor, or inducer of CYP450 isoenzymes.
Elimination: Following administration of a single 1000 mg dose in healthy subjects, an average of 33% of the administered dalbavancin dose was excreted in urine as unchanged dalbavancin and approximately 12% of the administered dose was excreted in urine as the metabolite hydroxy-dalbavancin through 42 days post-dose. Approximately 20% of the administered dose was excreted in feces through 70 days post-dose.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of dalbavancin has been evaluated in 218 individual pediatric patients [4 days to 17.9 years of age, including preterm neonates (gestational age < 37 weeks; n=2) and term neonates (gestational age 37 to 40 weeks; n=5)] with CLCR 30 mL/min/1.73 m2 and above. There is insufficient information to assess the exposure of XYDALBA in the pediatric patients with CLCR less than 30 mL/min/1.73 m2. No clinically important differences in drug exposure between pediatric age groups (3 months to less than 18 years) and adults are expected following administration of the age-dependent recommended single dose of XYDALBA.
The median plasma AUC from 0 to 120 hours (AUC0-120h) of dalbavancin in pediatric patient age groups from 3 months to less than 18 years is expected to be comparable to that in adult patients (AUC0-120h, 10400 mg*h/L). In all pediatric age groups, the percentage of patients attaining PK/PD targets related to in vivo drug activity were above 90% or higher for minimum inhibitory concentrations (MICs) up to 0.125 mg/L.
A summary of dalbavancin exposure parameters following the administration of the recommended doses across studies is presented in Table 7.
Table 7 – Median (95% range) Dalbavancin Pharmacokinetic Parameters for Pediatrics and Adults Using Population PK Analysis
| Age group | Age range | n | Dose | Cmax (mg/L) | AUC0-120h (mg*h/L) |
|---|---|---|---|---|---|
| Preterm Neonate | Gestation age 26 to < 37 weeks | 2 | 22.5 mg/kg | 233 (201-265)a | 6565 (5850-7280)a |
| Term Neonate | Birth to < 1 month | 5 | 233 (169-376)a | 7020 (6090-10600)a | |
| Young Infant | 1 month to < 3 months | 10 | 229 (163-279)a | 6955 (5330-8340)a | |
| Infant | 3 months to < 2 years | 27 | 364 (220-1070) | 10900 (7010-25700) | |
| Toddler | 2 years to < 6 years | 46 | 322 (34-901) | 10450 (1941-15800) | |
| Child | 6 years to < 12 years | 60 | 18 mg/kg | 273 (161-547) | 9505 (5711-15923) |
| Adolescent | 12 years to < 18 years | 68 | 287 (123-658) | 9815 (5154-14455) | |
| Adult | ≥ 18 years | 1000b | 1500 mg | 412 (134-1420)a | 10400 (3720-31000)a |
a Median (minimum and maximum range)
b Simulated subjects
Geriatrics: Clinically significant age-related differences in dalbavancin pharmacokinetics have not been observed in patients with infections. No dosage adjustment is recommended based solely on age. The experience with dalbavancin in elderly is limited: 276 patients ≥ 75 years of age were included in the Phase 2/3 clinical studies, of which 173 received dalbavancin. Patients up to 93 years of age have been included in clinical studies.
Sex: Clinically significant gender-related differences in dalbavancin pharmacokinetics have not been observed in healthy subjects or in patients with infections. No dose adjustment is recommended based on gender.
Hepatic Insufficiency: The pharmacokinetics of dalbavancin were evaluated in 17 adult subjects with mild, moderate, or severe hepatic impairment (Child-Pugh class A, B or C) and compared to 9 matched healthy subjects with normal hepatic function. The mean AUC0-336h was unchanged in subjects with mild hepatic impairment compared to subjects with normal hepatic function; however, the mean AUC0-336h decreased by 28% and 31% in subjects with moderate and severe hepatic impairment respectively, compared to subjects with normal hepatic function. The clinical significance of the decreased AUC0-336h in subjects with moderate and severe hepatic function is unknown.
No dosage adjustment is recommended for adult patients with mild hepatic impairment. Caution should be exercised when prescribing dalbavancin to adult patients with moderate or severe hepatic impairment as no data are available to determine the appropriate dosing.
Caution should also be exercised when prescribing dalbavancin to pediatric patients with hepatic impairment (mild, moderate or severe) as no data are available to determine the appropriate dosing in these patients.
Renal Insufficiency: The pharmacokinetics of dalbavancin were evaluated in 28 adult subjects with varying degrees of renal impairment and in 15 matched control subjects with normal renal function. Following a single dose of 500 mg or 1000 mg dalbavancin, the mean plasma clearance (CLT) was reduced 11%, 35%, and 47% in subjects with mild (CLCR 50 to 79 mL/min), moderate (CLCR 30 to 49 mL/min), and severe (CLCR < 30 mL/min) renal impairment, respectively, compared to subjects with normal renal function. The clinical significance of the decrease in mean plasma CLT, and the associated increase in AUC0-∞ noted in these pharmacokinetic studies of dalbavancin in subjects with severe renal impairment has not been established.
No dosage adjustment is necessary for adult patients with CLCR greater than 30 mL/min or patients receiving hemodialysis (3 times/week). The recommended regimen for dalbavancin in patients with severe renal impairment who are not receiving regularly scheduled hemodialysis is 1000 mg, administered as a single dose, or 750 mg followed one week later by 375 mg.
Dalbavancin pharmacokinetic parameters in adult subjects with end-stage renal disease receiving regularly scheduled renal dialysis (3 times/week) were similar to those observed in subjects with mild to moderate renal impairment, and less than 6 % of an administered dose is removed after 3 hours of hemodialysis. Therefore, no dosage adjustment is recommended for adult patients receiving regularly scheduled hemodialysis, and dalbavancin may be administered without regard to the timing of hemodialysis in such patients.
Based on population pharmacokinetic modelling and simulation, the mean percentage increase in dalbavancin exposure in pediatric subjects 3 months to less than 18 years old with CLCR 30 mL/min/1.73m2 was 13-21% compared to those with normal renal function. Hence, no dosage adjustment is necessary for pediatric patients with mild to moderate renal impairment (CLCR ≥ 30 to 79 mL/min/1.73m2).
No observed PK data are available in pediatric patients with severe renal impairment (CLCR < 30 mL/min/1.73m2). Based on population pharmacokinetic simulation, the predicted dalbavancin mean AUC for pediatric subjects with severe renal impairment was approximately 15-30 % higher compared to pediatric patients with normal renal function treated with the same dose. There is insufficient information to recommend dosage adjustment for pediatric patients with CLCR less than 30 mL/min/1.73m2 and XYDALBA is therefore not recommended for use in pediatric patients with severe renal impairment.
Drug Interactions
Nonclinical studies demonstrated that dalbavancin is not a substrate, inhibitor, or inducer of CYP450 isoenzymes. In a population pharmacokinetic analysis, dalbavancin pharmacokinetics were not affected by co-administration with known CYP450 substrates, inducers or inhibitors, nor by individual medications including acetaminophen, aztreonam, fentanyl, metronidazole, furosemide, proton pump inhibitors (omeprazole, esomeprazole, pantoprazole, lansoprazole), midazolam, and simvastatin.
11 STORAGE, STABILITY AND DISPOSAL
Stability and Storage Recommendations
Unreconstituted XYDALBA (dalbavancin for injection) should be stored at 25°C; excursions permitted to 15 to 30°C. Refer to section 4.4 Reconstitution for storage conditions of reconstituted and diluted product.
Disposal
Discard any portion of the reconstituted solution that remains unused.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
12 SPECIAL HANDLING INSTRUCTIONS
For information on reconstitution, see 4 DOSAGE AND ADMINISTRATION.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Common name: dalbavancin (as dalbavancin hydrochloride)
Chemical name (INN Name) for Dalbavancin B0: 5,31-dichloro-38-de(methoxycarbonyl)-7- demethyl-19-deoxy-56-O-[2-deoxy-2-[(10-methylundecanoyl)amino]-β-D-glucopyranuronosyl]- 38-[[3-(dimethylamino)propyl]carbamoyl]-42-O-α-D-mannopyranosyl-15-N-methyl(ristomycin A aglycone) hydrochloride.
For XYDALBA, the drug substance is a mixture of the related homologs dalbavancin A0, A1, B0, B1, and B2, of which B0 is the most abundant. The substitution patterns of the homologs are shown in Table 8.
Structural formula:
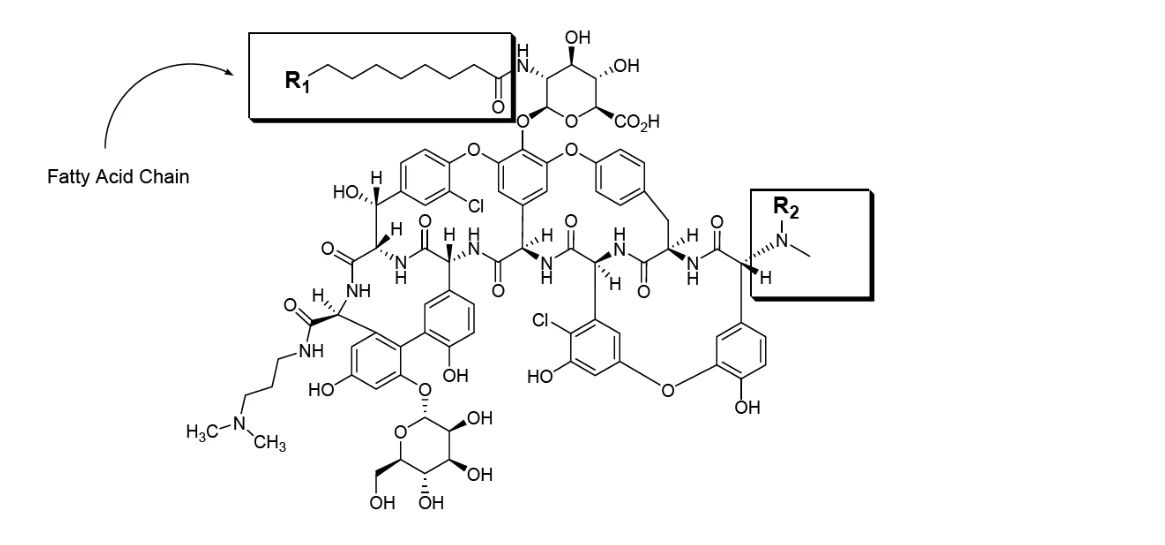
Table 8 – Substitution Patterns for Dalbavancin API Homologs
| Dalbavancin | R1 | R2 | Molecular Formula* | Molecular Weight (g/mol)* | Component Distribution (%) | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| A0 | CH(CH3)2 | H | C87H98N10O28Cl2 | 1802.7 | 1 - 6 | ||||||||||
| A1 | CH2CH2CH3 | H | C87H98N10O28Cl2 | 1802.7 | |||||||||||
| B0 | CH2CH(CH3) 2 | H | C88H100N10O28Cl2 | 1816.7 | 80 - 92 | ||||||||||
| B1 | CH2CH2CH2CH3 | H | C88H100N10O28Cl2 | 1816.7 | 3 - 11 | ||||||||||
| B2 | CH2CH(CH3) 2 | CH3 | C89H102N10O28Cl2 | 1830.7 | |||||||||||
*For free base. Overall HCl stoichiometry for drug substance, comprised of A0, A1, B0, B1 and B2, varies from 1.6 to 1.9
Physicochemical properties
Physical Characteristics: Dalbavancin is isolated in acidified conditions (pH 2.5 to 2.7) and forms a salt with hydrochloric acid with a chloride content of not more than 5%.
Appearance: White to tan solid.
Solution pH: 2.6 to 2.8.
Melting Point: Heated to ~300°C without apparent melting, as observed during hot stage microscopy.
Chloride Content: Varies as a function of the pH of isolation with hydrochloric acid levels typically between 1.6 and 1.9 equivalents per mole of dalbavancin.
Dissociation Constants (pKa): pK1= 1.7; pK2=6.0; pK3= 9.9 (Determined by titrating from pH 2 to pH 11.5).
Specific Rotation (optical rotation): -105.0° in water (0.85 g/100 mL) at 25°C and 589 nm.
Solubility: Freely soluble in water (Verified at ambient temperatures).
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Acute Bacterial Skin and Skin Structure Infections (ABSSSI) in Adults
Two-dose Regimen
Table 9 – Summary of Patient Demographics for Clinical Trials in ABSSSI Efficacy Studies with XYDALBA – Two-dose Regimen (1000 mg Day 1; 500 mg Day 8)
| Study # | Trial design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex | |||
| Study # | Trial design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex | |||
DUR001-301 (Trial 1) | IV dalbavancin: 1000 mg on Day 1, 500 mg on Day 8, possible switch to oral placebo q12h after 3 days | 288 | 48.8 (18-84) years dalbavancin | 59.0% Male dalbavancin | ||||
| IV vancomycin: 1000 mg or 15 mg/kg q12h, possible switch to oral linezolid 600 mg q12h after 3 days | 285 | 48.9 (18-84) years Vancomycin /linezolid | 60.7% Male Vancomycin /linezolid | |||||
| Duration: 10-14 days | ||||||||
DUR001-302 (Trial 2) | IV dalbavancin: 1000 mg on Day 1, 500 mg on Day 8, possible switch to oral placebo q12h after 3 days | 371 | 49.1 (18-85) years dalbavancin | 60.1% Male dalbavancin | ||||
| IV vancomycin: 1000 mg or 15 mg/kg q12h, possible switch to oral linezolid 600 mg q12h after 3 days | 368 | 51.4 (18-84) years vancomycin /linezolid | 54.6% Male Vancomycin /linezolid | |||||
| Duration 10-14 days | ||||||||
Abbreviations: IV – intravenous; q12h – every 12 hours.
Adult patients with ABSSSI were enrolled in two Phase 3, randomized, double-blind, double-dummy clinical trials of similar design (Trial 1 [DUR001-301] and Trial 2 [DUR001-302]). The Intent-to-Treat (ITT) population included 1312 patients randomized 1:1 to receive treatment with intravenous (IV) XYDALBA or IV vancomycin. Patients were treated for two weeks with either a two-dose regimen of intravenous XYDALBA (1000 mg followed one week later by 500 mg) or intravenous vancomycin (1000 mg or 15 mg/kg every 12 hours, with the option to switch to oral linezolid after 3 days). XYDALBA-treated patients with creatinine clearance of less than 30 mL/min received 750 mg followed one week later by 375 mg. Approximately 5% of patients also received a protocol-specified empiric course of treatment with intravenous aztreonam for coverage of gram-negative pathogens.
The specific infections in these trials included cellulitis (approximately 50% of patients across treatment groups), major abscess (approximately 30%), and wound infection (approximately 20%). The median lesion area at baseline was 341 cm2. In addition to local signs and symptoms of infection, patients were also required to have at least one systemic sign of disease at baseline, defined as temperature 38°C or higher (approximately 85% of patients), white blood cell count greater than 12000 cells/mm3 (approximately 40%), or 10% or more band forms on white blood cell differential (approximately 23%). Across both trials, 59% of patients were from Eastern Europe and 36% of patients were from North America. Approximately 89% of patients were Caucasian and 58% were males. The mean age was 50 years and the mean body mass index was 29.1 kg/m2.
The primary endpoint of these two ABSSSI trials was the clinical response rate where responders were defined as patients who had no increase from baseline in lesion area 48 to
72 hours after initiation of therapy, and had a temperature consistently at or below 37.6°C upon repeated measurement. Table 8 summarizes overall clinical response rates in these two ABSSSI trials using the pre-specified primary efficacy endpoint in the ITT population.
Results – Two-dose Regimen
Table 10 – Results of study Trial 1 and Trial 2 in ABSSSI with Suspected or Confirmed Gram-positive Bacterial Pathogens, Requiring Parental Therapy1,2
| Primary Endpoints | XYDALBA n/N (%) | Vancomycin/Linezolid n/N (%) | Difference (95% CL)3 |
| Trial 1: Clinical Responder at 48 to 72 Hours | 240/288 (83.3) | 233/285 (81.8) | 1.5% (-4.6, 7.9) |
| Trial 2: Clinical Responder at 48 to 72 Hours | 285/371 (76.8) | 288/368 (78.3) | -1.5% (-7.4, 4.6) |
1 There were 7 patients who did not receive treatment and were counted as non-responders: 6 XYDALBA patients (3 in each trial) and one vancomycin/linezolid patient in Trial 2.
2 Patients who died or used non-study antibacterial therapy or had missing measurements were classified as non-responders.
3 The 95% Confidence Interval (CI) is computed using the Miettinen and Nurminen approach, stratified by baseline fever status.
A key secondary endpoint in these two ABSSSI trials evaluated the percentage of ITT patients achieving a 20% or greater reduction in lesion area from baseline at 48-72 hours after initiation of therapy. Table 11 summarizes the findings for this endpoint in these two ABSSSI trials.
Table 11 – Secondary Efficacy Results - Patients in ABSSSI Trials with Reduction in Lesion Area of 20% or Greater at 48-72 Hours after Initiation of Therapy1,2
| XYDALBA n/N (%) | Vancomycin/Linezolid n/N (%) | Difference (95% CI)3 | |
|---|---|---|---|
| Trial 1 | 259/288 (89.9) | 259/285 (90.9) | -1.0% (-5.7, 4.0) |
| Trial 2 | 325/371 (87.6) | 316/368 (85.9) | 1.7% (-3.2, 6.7) |
1 There were 7 patients (as described in Table 8) who did not receive treatment and were counted as non-responders.
2 Patients who died or used non-study antibacterial therapy or had missing measurements were classified as non-responders.
3 The 95% CI is computed using the Miettinen and Nurminen approach, stratified by baseline fever status.
Another secondary endpoint in these two ABSSSI trials was the clinical success rate assessed at a follow-up visit occurring between Days 26 to 30. Clinical Success at this visit was defined as having a decrease in lesion size (both length and width measurements), a temperature of 37.6°C or lower, and meeting pre-specified criteria for local signs: purulent discharge and drainage absent or mild and improved from baseline, heat/warmth & fluctuance absent, swelling/induration & tenderness to palpation absent or mild.
Table 12 summarizes clinical success rates at a follow-up visit for the ITT and clinically evaluable (CE) population in these two ABSSSI trials. Note that there are insufficient historical data to establish the magnitude of drug effect for antibacterial drugs compared with placebo at the follow-up visits. Therefore, comparisons of XYDALBA to vancomycin/linezolid based on clinical success rates at these visits cannot be utilized to establish non-inferiority.
Table 12 – Secondary Efficacy Results in ABSSSI Patients - Clinical Success Rates in ABSSSI Trials at Follow-Up (Day 26 to 30)1,2
| XYDALBA n/N (%) | Vancomycin/Linezolid n/N (%) | Difference (95% CI)3 | |||||
|---|---|---|---|---|---|---|---|
| Trial 1 | |||||||
| ITT | 241/288 (83.7) | 251/285 (88.1) | -4.4% (-10.1, 1.4) | ||||
| CE | 212/226 (93.8) | 220/229 (96.1) | -2.3% (-6.6, 2.0) | ||||
| Trial 2 | |||||||
| ITT | 327/371 (88.1) | 311/368 (84.5) | 3.6% (-1.3, 8.7) | ||||
| CE | 283/294 (96.3) | 257/272 (94.5) | 1.8% (-1.8, 5.6) | ||||
1 There were 7 patients (as described in Table 8) who did not receive treatment and were counted as failures in the analysis.
2 Patients who died, used non-study antibacterial therapy, or had an unplanned surgical intervention 72 hours after the start of therapy were classified as Clinical Failures.
3 The 95% CI is computed using the Miettinen and Nurminen approach, stratified by baseline fever status. Abbreviations: ITT – intent to treat; CE – clinically evaluable.
Table 13 shows outcomes in patients with an identified baseline pathogen, using pooled data from Trials 1 and 2 in the microbiological ITT (microITT) population. The outcomes shown in the table are clinical response rates at 48 to 72 hours and clinical success rates at follow-up (Day 26 to 30), as defined above.
Table 13 – Secondary Efficacy Results in ABSSSI Patients - Outcomes by Baseline Pathogen (Trial 1, Trial 2; MicroITT)1,2
| Early Clinical Response at 48-72 hours | Clinical Success at Day 26 to 30 | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Early Responder3 | ≥ 20% Reduction in Lesion Size | |||||||||||||||||||
| Pathogen | XYDALBA n/N (%) | Comparato r n/N (%) | XYDALBA n/N (%) | Comparato r n/N (%) | XYDALBA n/N (%) | Comparato r n/N (%) | ||||||||||||||
| Staphylococcu s aureus | 206/257 (80.2) | 219/256 (85.5) | 239/257 (93.0) | 232/256 (90.6) | 217/257 (84.4) | 229/256 (89.5) | ||||||||||||||
| Methicillin-susceptible | 134/167 (80.2) | 163/189 (86.2) | 156/167 (93.4) | 173/189 (91.5) | 142/167 (85.0) | 171/189 (90.5) | ||||||||||||||
| Methicillin-resistant | 72/90 (80.0) | 56/67 (83.6) | 83/90 (92.2) | 59/67 (88.1) | 75/90 (83.3) | 57/67 (85.1) | ||||||||||||||
| Streptococcus agalactiae | 6/12 (50.0) | 11/14 (78.6) | 10/12 (83.3) | 10/14 (71.4) | 10/12 (83.3) | 11/14 (78.6) | ||||||||||||||
| Streptococcus pyogenes | 28/37 (75.7) | 24/36 (66.7) | 32/37 (86.5) | 27/36 (75.0) | 33/37 (89.2) | 32/36 (88.9) | ||||||||||||||
Streptococcus anginosus group | 18/22 (81.8) | 23/25 (92.0) | 21/22 (95.5) | 25/25 (100.0) | 21/22 (95.5) | 23/25 (92.0) | ||||||||||||||
| Streptococcus dysgalactiae | 3/3 (100.0) | 0/1 (0.0) | 3/3 (100.0) | 1/1 (100.0) | 3/3 (100.0) | 1/1 (100.0) | ||||||||||||||
| Enterococcus faecalis | 8/12 (66.7) | 10/13 (76.9) | 12/12 (100.0) | 12/13 (92.3) | 12/12 (100.0) | 11/13 (84.6) | ||||||||||||||
1 All XYDALBA dosing regimens in Trials 1 and 2 consisted of two doses.
2 There were 2 patients in the XYDALBA arm with methicillin-susceptible S. aureus at baseline who did not receive treatment and were counted as non-responders/failures.
3 Early Responders are patients who had no increase from baseline in lesion area 48 to 72 hours after initiation of therapy, and had a temperature consistently at or below 37.6°C upon repeated measurement.
Single-dose Regimen
Table 14 – Summary of Patient Demographics for Clinical Trials in ABSSSI Efficacy Studies with XYDALBA - 1500 mg Single Dose Regimen
| Study # | Trial design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex | ||||||
DUR001-303 (Trial 3) | Randomized double-blind, multi-center, controlled | Single-dose group: IV 1500 mg dalbavancin on Day 1 and IV placebo on Day 8 | 349 | 48.0 (18-85) years in the single-dose group | 58.5% Male single-dose | ||||||
| Two-dose group: IV dalbavancin 1000 mg on Day 1 and IV dalbavancin 500 mg on Day 8 | 349 | 48.3 (19-84) years in the two-dose group | 58.2% Male two-dose | ||||||||
| Duration: 14 days | |||||||||||
Abbreviations: IV – intravenous; mg – milligrams.
Adult patients with ABSSSI were enrolled in a Phase 3, double-blind, clinical trial (Trial 3 [DUR001-303]). The ITT population included 698 patients who were randomized to XYDALBA treatment with either a single 1500 mg dose or a two-dose regimen of 1000 mg followed one week later by 500 mg. Patients with creatinine clearance less than 30 mL/min had their dose adjusted. Approximately 5% of patients also received a protocol-specified empiric course of treatment with intravenous aztreonam for coverage of gram-negative pathogens. The specific infections and other patient characteristics in this trial were similar to those described above for previous ABSSSI trials.
The primary endpoint in this ABSSSI trial was the clinical response rate where responders were defined as patients who had at least a 20% decrease from baseline in lesion area 48 to 72 hours after randomization without receiving any rescue antibacterial therapy. The secondary endpoint was the clinical success rate at a follow-up visit occurring between Days 26 and 30, with clinical success defined as having at least a 90% decrease from baseline in lesion size, a temperature of 37.6°C or lower, and meeting pre-specified criteria for local signs: purulent discharge and drainage absent or mild and improved from baseline (for patients with wound infections), heat/warmth and fluctuance absent, swelling/induration and tenderness to palpation absent or mild.
Results – Single-dose Regimen
Table 15 and 16 summarize results for these two endpoints in the ITT and CE population. Note that there are insufficient historical data to establish the magnitude of drug effect for antibacterial drugs compared with placebo at the follow-up visit. Therefore, comparisons between treatment groups based on clinical success rates at this visit cannot be utilized to establish non-inferiority
Table 15 – Primary Efficacy Results in ABSSSI Patients (Trial 3)1,2
| Primary Endpoints | XYDALBA Single Dose (1500 mg) n/N (%) | XYDALBA Two Doses (1000 mg Day 1/500 mg Day 8) n/N (%) | Difference (95% CL)3 |
| Clinical Responders at 48-72 Hours | 284/349 (81.4) | 294/349 (84.2) | -2.9% (-8.5, 2.8) |
1 There were 3 patients in the two-dose group who did not receive treatment and were counted as non-responders.
2 Patients who died or used non-study antibacterial therapy or had missing measurements were classified as non-responders.
3 The 95% Confidence Interval (CI) is computed using the Miettinen and Nurminen approach. Abbreviation: ITT – intent to treat.
Table 16 – Secondary Efficacy Results in ABSSSI Patients (Trial 3)1,2
| Secondary Endpoints | XYDALBA Single Dose (1500 mg) n/N (%) | XYDALBA Two Doses (1000 mg Day 1/500 mg Day 8) n/N (%) | Difference (95% CL)3 |
| Clinical Success at Day 26-30 (ITT) | 295/349 (84.5) | 294/349 (85.1) | -0.6% (-6.0, 4.8) |
| Clinical Success at Day 26-30 (CE) | 250/271 (92.3) | 247/267 (92.5) | -0.3% (-4.9, 4.4) |
1 There were 3 patients in the two-dose group who did not receive treatment and were counted as non-responders.
2 Patients who died or used non-study antibacterial therapy or had missing measurements were classified as non-responders.
3 The 95% Confidence Interval (CI) is computed using the Miettinen and Nurminen approach. Abbreviations: ITT – intent to treat; CE – clinically evaluable.
Table 17 shows outcomes in patients with an identified baseline pathogen from Trial 3 in the microbiological ITT (microITT) population. The outcomes shown in the table are clinical response rates at 48 to 72 hours and clinical success rates at follow-up (Day 26 to 30), as defined above.
Table 17 – Secondary Efficacy Results - Outcomes by Baseline Pathogen (Trial 3; MicroITT)
| Early Clinical Response 48-72 Hours | Clinical Success at Day 26 to 30 | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ≥ 20% Reduction in Lesion Size | ||||||||||||||
| Pathogen | XYDALBA Single Dose (1500 mg) n/N (%) | XYDALBA Two Doses (1000 mg Day 1/500 mg Day 8) n/N (%) | XYDALBA Single Dose (1500 mg) n/N (%) | XYDALBA Two Doses (1000 mg Day 1/500 mg Day 8) n/N (%) | ||||||||||
| Staphylococcus aureus | 123/139 (88.5) | 133/156 (85.3) | 124/139 (89.2) | 140/156 (89.7) | ||||||||||
| Methicillin-susceptible | 92/103 (89.3) | 86/96 (89.6) | 93/103 (90.3) | 86/96 (89.6) | ||||||||||
| Methicillin-resistant | 31/36 (86.1) | 48/61 (78.7) | 31/36 (86.1) | 55/61 (90.2) | ||||||||||
| Streptococcus agalactiae | 6/6 (100.0) | 4/6 (66.7) | 5/6 (83.3) | 5/6 (83.3) | ||||||||||
| Streptococcus anginosus group | 31/33 (93.9) | 19/19 (100.0) | 29/33 (87.9) | 17/19 (89.5) | ||||||||||
| Streptococcus dysgalactiae | 4/4 (100.0) | 3/3 (100.0) | 4/4 (100.0) | 3/3 (100.0) | ||||||||||
| Streptococcus pyogenes | 14/14 (100.0) | 18/22 (81.8) | 13/14 (92.9) | 19/22 (86.4) | ||||||||||
| Enterococcus faecalis | 4/4 (100.0) | 8/10 (80.0) | 4/4 (100.0) | 9/10 (90.0) | ||||||||||
In the ABSSSI studies (Trial 1, Trial 2, and Trial 3), all patients had blood cultures obtained at baseline. A total of 40 ABSSSI patients who received XYDALBA had bacteremia at baseline caused by one or more of the following bacteria: 26 Staphylococcus aureus (21 MSSA and 5 MRSA), 6 Streptococcus agalactiae, 7 Streptococcus pyogenes, 2 Streptococcus anginosus group, and 1 Enterococcus faecalis. In patients who received XYDALBA, a total of 34/40 (85%) were clinical responders at 48-72 hours and 32/40 (80%) were clinical successes at Day 26 to 30, and all patients with a follow-up blood culture had documented clearance of their bacteremia.
Acute Bacterial Skin and Skin Structure Infections (ABSSSI) in Pediatric Patients (≥ 3 months of age)
Table 18 – Summary of Patient Demographics for Pediatric Clinical Trial in ABSSSI
| Study # | Trial design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex | |||
DUR001-306 (Trial 4) | Randomized open-label, multi-center, comparator-controlled | Single-dose group: | 84a | |||||
3 months to < 6 years old: 22.5 mg/kg on Day 1 (maximum 1500 mg) | 27 | 7.8 (0.04 – 17) | 57.8% Male | |||||
| ≥ 6 years to < 18 years old: 18 mg/kg on Day 1 (maximum 1500 mg) | 49 | |||||||
| Two-dose group: | 78 | |||||||
3 months to < 6 years old: 15 mg/kg on Day 1 (maximum 1000 mg), 7.5 mg/kg on Day 8 (maximum 500 mg) | 25 | 8.9 (0.25 – 17) | 67.9% Male | |||||
≥ 6 years to < 18 years old: 12 mg/kg on Day 1 (maximum 1000 mg), 6 mg/kg on Day 8 (maximum 500 mg) | 53 | |||||||
a includes 6 patients from 0 to less than 3 months.
The pediatric trial was a multicenter, open-label, randomized, actively controlled trial (DUR001-306, Trial 4) conducted in pediatric patients 3 months of age to less than 18 years with ABSSSI, not known or expected to be caused exclusively by Gram-negative organisms. Patients were randomized in a 3:3:1 ratio to receive either XYDALBA single-dose regimen, XYDALBA two-dose regimen, or comparator. The comparator regimens included IV vancomycin for methicillin-resistant Gram-positive infections, or IV oxacillin or flucloxacillin for methicillin-susceptible Gram-positive infections. Patients in the comparator arm received IV treatment for a minimum of 72 hours before an optional switch to oral therapy to complete a total of 10-14 days of antibacterial drug therapy. Additional 6 patients from birth to < 3 months of age were enrolled and assigned to the XYDALBA single-dose regimen.
Patients had diagnoses of major cutaneous abscess (52%), cellulitis (29%), or surgical site/traumatic wound infection (19%). The predominant pathogen at baseline was Staphylococcus aureus (84%).
Results – Pediatric Patients
The primary objective was to evaluate the safety and tolerability of XYDALBA. The trial was not powered for a comparative inferential efficacy analysis. Efficacy, a descriptive endpoint, was assessed in the modified intent-to-treat population (n=192) which included all randomized patients who received any dose of study drug and had a diagnosis of ABSSSI caused by Gram-positive organism(s). Patients with ABSSSI only caused by Gram-negative organisms were excluded. An early clinical response at 48-72 hours was defined as ≥ 20% reduction in lesion size compared to baseline and no receipt of rescue antibacterial therapy for patients aged 3 months to less than 18 years old. The proportion of patients with early clinical response was 96.4% (81/84) in the XYDALBA single-dose arm, 98.6% (73/74) in the XYDALBA two-dose arm, and 89.7% (26/29) in the comparator arm. These results include 6 patients from birth to less than 3 months old, whereby early clinical response at 48-72 hours was defined as cessation of increase in lesion size and decreased erythema or tenderness compared to baseline with no appearance of new lesions, and five of the six patients were evaluated as being clinical responder.
Clinical cure was defined as resolution of the clinical signs and symptoms of infection, when compared to baseline, and no additional antibacterial treatment for the disease under study. In pediatric patients (from birth to less than 18 years old) in the mITT population, the clinical cure rate at the test of cure (TOC) visit (28 ± 2 days) was 95.1% (78/82) in the XYDALBA single-dose arm, 97.3% (72/74) in the XYDALBA two-dose arm and 100% (30/30) in the comparator arm.
15 MICROBIOLOGY
Mechanism of Action
Dalbavancin, a semisynthetic lipoglycopeptide, interferes with cell wall synthesis by binding to the D-alanyl-D-alanine terminus of the stem pentapeptide in nascent cell wall peptidoglycan, thus preventing cross-linking. Dalbavancin is bactericidal in vitro against Staphylococcus aureus and Streptococcus pyogenes at concentrations similar to those sustained throughout treatment in humans according to the recommended dosage regimen.
Mechanism of Resistance
The development of bacterial isolates resistant to dalbavancin has not been observed, either in vitro, in studies using serial passage, or in animal infection experiments.
All gram-negative bacteria are inherently resistant to dalbavancin.
Resistance to dalbavancin in Staphylococcus spp. and Enterococcus spp. is mediated by VanA, a genotype that results in modification of the target peptide in nascent cell wall. The VanA phenotype is mediated by a cluster of genes, transferred from other organisms, and cannot simply be selected by exposure of susceptible bacteria to glycopeptides in the absence of a donor. Staphylococcal resistance mediated by VanA is rare.
Dalbavancin MICs are higher for vancomycin-intermediate staphylococci (VISA) than for fully vancomycin susceptible strains. If the isolates with higher dalbavancin MICs represent stable phenotypes and are correlated with resistance to the other glycopeptides, then the likely mechanism would be an increase in the number of glycopeptide targets in nascent peptidoglycan.
Cross-resistance between dalbavancin and other classes of antibiotics was not seen in in vitro studies. Methicillin resistance has no impact on dalbavancin activity.
Interaction with Other Antimicrobials
When tested in vitro, dalbavancin demonstrated synergistic interactions with oxacillin and did not demonstrate antagonistic or synergistic interactions with any of the following antibacterial agents of various classes: gentamicin, vancomycin, levofloxacin, clindamycin, quinupristin/dalfopristin, linezolid, aztreonam, rifampin or daptomycin. The clinical significance of these in vitro findings is unknown.
In in vitro studies, no antagonism has been observed between dalbavancin and other commonly used antibiotics (i.e., cefepime, ceftazidime, ceftriaxone, imipenem, meropenem, amikacin, aztreonam, ciprofloxacin, piperacillin/tazobactam and trimethoprim/sulfamethoxazole), when tested against 12 species of Gram-negative pathogens.
Spectrum of Activity
Dalbavancin has been shown to be active against the following microorganisms, both in vitro and in clinical infections:
Gram-positive bacteria
Staphylococcus aureus (including methicillin-resistant isolates)
Streptococcus pyogenes Streptococcus agalactiae Streptococcus dysgalactiae Streptococcus anginosus group (including S. anginosus, S. intermedius, S. constellatus)
Enterococcus faecalis (vancomycin-susceptible isolates only).
The following in vitro data are available, but their clinical significance is unknown. In addition, at least 90% of organisms in the following bacteria exhibit an in vitro minimum inhibitory concentration (MIC) less than or equal to the dalbavancin susceptible breakpoint of 0.25 mcg/mL. However, the safety and efficacy of dalbavancin in treating clinical infections due to these bacteria have not been established in adequate well-controlled clinical trials.
Gram-positive bacteria
Enterococcus faecium (vancomycin-susceptible isolates only)
Susceptibility Test Methods
When available, the clinical microbiology laboratory should provide the results of in vitro susceptibility test results for antimicrobial drug products used in resident hospitals to the physician as periodic reports that describe the susceptibility profile of nosocomial and community-acquired pathogens. These reports should aid the physician in selecting an antibacterial drug for treatment.
Dilution Techniques
Quantitative methods are used to determine minimum inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized test method. When determining dalbavancin MICs, polysorbate-80 (P-80) should be added at a final concentration of 0.002% to freshly prepared or frozen microtiter trays. The MIC values should be interpreted according to the criteria provided in Table 19.
Diffusion Techniques
Dalbavancin disks for diffusion susceptibility testing are not available. Disk diffusion is not a reliable method for determining the in vitro activity of dalbavancin.
Table 19 – Susceptibility Test Interpretive Criteria for Dalbavancin
| Pathogen | MIC (mcg/mL) | Zone Diameter (mm) | ||||
|---|---|---|---|---|---|---|
| S | I | R | S | I | R | |
| Staphylococcus aureus (including methicillin-resistant isolates) | ≤ 0.25 | -- | -- | -- | -- | -- |
| Streptococcus pyogenes, Streptococcus agalactiae, Streptococcus dysgalactiae, and Streptococcus anginosus group | ≤ 0.25 | -- | -- | -- | -- | -- |
| Enterococcus faecalis (vancomycin- susceptible isolates only) | ≤ 0.25 | -- | -- | -- | -- | -- |
a The current absence of data on resistant isolates precludes defining any category other than "Susceptible". Isolates yielding test results other than “Susceptible” should be retested, and if the result is confirmed, the isolate should be submitted to a reference laboratory for additional testing.
A report of "Susceptible" indicates that the antibacterial agent is likely to inhibit growth of the pathogen if the antibacterial compound reaches the concentrations at the infection site necessary to inhibit growth of the pathogen.
Quality Control
Standardized susceptibility test procedures require the use of laboratory controls to monitor and ensure the accuracy and precision of supplies and reagents used in the assay, and the techniques of the individuals performing the test. Standard dalbavancin powder should provide the following range of MIC values noted in Table 20.
Table 20 – Acceptable MIC Quality Control Ranges for Dalbavancin
| Quality Control Strain | MIC Range (mcg/mL) |
|---|---|
| Staphylococcus aureus ATCC® 29213 | 0.03-0.12 |
| Streptococcus pneumoniae ATCC® 49619a | 0.008-0.03 |
| Enterococcus faecalis ATCC® 29212 | 0.03-0.12 |
ATCC® = American Type Culture Collection.
a This organism may be used for validation of susceptibility test results when testing Streptococcus species other than S. pneumoniae.
16 NON-CLINICAL TOXICOLOGY
General Toxicity
Increases in serum levels of liver enzymes (ALT, AST), associated with microscopic findings in the liver were noted in toxicology studies in rats and dogs where dalbavancin was administered daily for 28 to 90 days. Hepatocellular necrosis was observed in dogs dosed at ≥10 mg/kg/day for longer than 2 months, i.e., at approximately 5 to 7 times the expected human dose on an exposure basis. Histiocytic vacuolation and hepatocyte necrosis were observed in rats dosed daily at 40 and 80 mg/kg/day, respectively, for 4 weeks, (approximately 3 and 6 times the expected human dose on an exposure basis, respectively). In addition, renal toxicity characterized by increases in serum BUN and creatinine and microscopic kidney findings was observed in rats and dogs at doses 5 to 7 times the expected human dose on an exposure basis. The relationship between these findings in the animal toxicology studies after 28 and 90 consecutive days of dosing to the indicated clinical dosing of 2 doses 7 days apart are unclear.
In dogs only, infusion reactions characterized by skin swelling and/or redness (not associated with the injection site), mucosal pallor, salivation, vomiting, sedation, and modest declines in blood pressure and increases in heart rate were observed in a dose-dependent manner. These infusion reactions were transient (resolved within 1 hour post-dosing) and were attributed to histamine release. Dalbavancin toxicity profile in juvenile rats was consistent with that previously observed in adult rats at the same dose (mg/kg /day) levels.
Reproductive and Developmental Toxicology
Reproductive toxicity studies in rats and rabbits showed no evidence of a teratogenic effect. In rats, at exposures approximately 3.5 times above clinical exposure, there was reduced fertility and an increased incidence of embryo-lethality, reductions in fetal weight and skeletal ossification and increased neonatal mortality. Impaired fertility in the rat was not observed at a dose of 15 mg/kg/day (1.2 times the human dose on an exposure basis). Reductions in male and female fertility and increased embryo resorptions occurred at a dose of 45 mg/kg/day (3.5 times the human dose on an exposure basis), at which signs of parental toxicity were also observed. In rabbits, abortion occurred in conjunction with maternal toxicity at exposures below the human therapeutic range. The maternal (No-Observed-effect level) NOEL was 5 mg/kg/day (abortion, reduced body weight gains, and reduced food consumption occurred at 15 mg/kg/day). The developmental NOEL was 15 mg/kg/day, the highest dosage tested. No dalbavancin-related gross, soft-tissue, or skeletal alterations were observed in fetuses.
Carcinogenicity
Long-term studies in animals to determine the carcinogenic potential of dalbavancin have not been conducted. Dalbavancin was not genotoxic in a mammalian HGPRT gene mutation assay, an in vitro chromosome aberration assay in Chinese Hamster Ovary cells, or an in vivo mouse micronucleus assay.