


Product Monograph - Pharma-Levetiracetam
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions, Cardiovascular | 03/2022 |
| 7 Warnings and Precautions, Neurologic | 03/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................ 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ................................................................. 4
- 1.
INDICATIONS ................................................................................................................. 4
1.1 Pediatrics ............................................................................................................... 4
1.2 Geriatrics ............................................................................................................... 4
- 2. CONTRAINDICATIONS .................................................................................................. 4
- 4.
DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.3 Reconstitution ...................................................................................................... 10
4.4 Administration ...................................................................................................... 10
4.5 Missed Dose ........................................................................................................ 11
- 5. OVERDOSAGE ............................................................................................................. 11
- 6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................... 12
- 7.
WARNINGS AND PRECAUTIONS ............................................................................... 12
7.1 Special Populations ............................................................................................. 18
1 7.1.1 Pregnant Women ............................................................................................18
7.1.2 Breast-feeding ..................................................................................................18
7.1.3 Pediatrics .........................................................................................................19
7.1.4 Geriatrics ..........................................................................................................19
8 ADVERSE REACTIONS ............................................................................................... 19
8.1 Adverse Reaction Overview ................................................................................. 19
8.2 Clinical Trial Adverse Reactions........................................................................... 19
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ....................................................22
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 24
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 25
8.5 Post-Market Adverse Reactions ........................................................................... 25
9 DRUG INTERACTIONS ................................................................................................ 26
9.2 Drug Interactions Overview .................................................................................. 26
9.3 Drug-Behavioural Interactions .............................................................................. 26
9.4 Drug-Drug Interactions ......................................................................................... 27
9.5 Drug-Food Interactions ........................................................................................ 29
9.6 Drug-Herb Interactions ......................................................................................... 29
9.7 Drug-Laboratory Test Interactions ........................................................................ 29
10 CLINICAL PHARMACOLOGY ...................................................................................... 29
10.1 Mechanism of Action ........................................................................................ 29
10.3 Pharmacokinetics ............................................................................................. 30
11 STORAGE, STABILITY AND DISPOSAL ..................................................................... 33
PART II: SCIENTIFIC INFORMATION ..................................................................................... 34
13 PHARMACEUTICAL INFORMATION ........................................................................... 34
14 CLINICAL TRIALS ........................................................................................................ 35
14.1 Clinical Trials by Indication ............................................................................... 35
Partial onset seizures (adults and pediatrics aged 1 month to 16 years) ........................35
Myoclonic seizures (adults and adolescents) .................................................................41
Primary generalized tonic-clonic seizures (adults and adolescents) ..............................42
15 MICROBIOLOGY .......................................................................................................... 43
16 NON-CLINICAL TOXICOLOGY .................................................................................... 43
PATIENT MEDICATION INFORMATION ................................................................................. 45
PATIENT MEDICATION INFORMATION ................................................................................. 51
PART I: HEALTH PROFESSIONAL INFORMATION
1. INDICATIONS
pharma-levetiracetam (levetiracetam oral solution and levetiracetam for injection) is indicated as:
- adjunctive therapy in the management of patients with epilepsy who are not satisfactorily controlled by conventional therapy.
pharma-levetiracetam (levetiracetam for injection) is indicated as:
- an alternative for patients when oral administration is temporarily not feasible.
1.1 Pediatrics
Pediatrics: pharma-levetiracetam (levetiracetam oral solution and levetiracetam for injection) is indicated in pediatric patients as adjunctive therapy in the treatment of:
- partial onset seizures with or without secondary generalization in adolescents, children and infants from 1 month of age with epilepsy.
- myoclonic seizures in adolescents from 12 years of age with Juvenile Myoclonic Epilepsy.
- primary generalized tonic-clonic seizures in adolescents from 12 years of age with Idiopathic Generalized Epilepsy.
pharma-levetiracetam (levetiracetam for injection) is indicated as:
- an alternative for patients when oral administration is temporarily not feasible (see 4.2 Recommended Dose and Dosage Adjustment, Pediatrics)
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 7.1.47.1.4 Geriatrics; and 010.3 Pharmacokinetics, Geriatrics).
2. CONTRAINDICATIONS
pharma-levetiracetam is contraindicated:
- in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- in patients who are hypersensitive to other pyrrolidine derivatives (see 7 WARNINGS AND PRECAUTIONS, Immune).
4. DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
pharma-levetiracetam is available in the form of an oral solution and an IV solution for injection.
4.2 Recommended Dose and Dosage Adjustment
Adults (> 18 years)
Add-on therapy in adults (>18 years) and adolescents (12 to 17 years) weighing 50 kg or more
Oral / IV Solution
Treatment should be initiated at a dose of 1000 mg/day, given as twice daily dosing (500 mg, b.i.d). Depending on the clinical response and tolerability, the daily dose may be increased every two weeks by increments of 1000 mg, to a maximum recommended daily dose of 3000 mg daily.
In clinical trials, daily doses of 1000 mg, 2000 mg, and 3000 mg, given as twice daily dosing were shown to be effective. Although there was a tendency towards a greater response rate with higher doses, a consistent statistically significant increase in response with increased dose has not been shown. There are limited safety data from controlled clinical trials at doses higher than 3000 mg/day (approximately 40 patients), therefore these doses are not recommended.
pharma-levetiracetam IV Solution is for intravenous use only as an alternative for patients when oral administration is temporarily not feasible. There is no experience with administration of intravenous levetiracetam for a period longer than 4 days.
Elderly Patients (65 years and older)
Dose selection and titration should proceed cautiously in elderly patients, as renal function decreases with age. Accordingly, adjustment of the dose is recommended in elderly patients with compromised renal function (see below).
Dosage Adjustments in Adult Patients with Impaired Renal Function
Renal excretion of unchanged drug accounts for approximately 66% of administered levetiracetam dose. Consistent with this, pharma-levetiracetam dosage should be reduced in patients with impaired renal function (see Table 1 below). Patients with end stage renal disease should receive supplemental doses following dialysis.
To use this dosing table, an estimate of the patient’s creatinine clearance (CLcr) in mL/min is needed. The CLcr in mL/min may be estimated from serum creatinine (mg/dL). To estimate creatinine clearance (Clcr) in mL/min for adults and adolescents weighing 50 kg or more, use the following formula
ClCr = [140 − age (years)] × weigℎt(kg) 72 × serum creatinine (mg/dl) (× 0.85 for female patients)
Then CLcr is adjusted for body surface area (BSA) as follows:
CLCr(mL/min/1.73 m2) = CLCr (mL/min) BSA Subject (m2) × 1.73
Table 1 Dosing Adjustment for Adult and Adolescent Patients weighing more than 50 kg with Impaired Renal Function
| Renal Function | Creatinine Clearance (mL/min/1.73 m2) | Dosage and Frequency |
| Normal | ≥80 | 500 to 1500 mg twice daily |
| Mild | 50-79 | 500 to 1000 mg twice daily |
| Moderate | 30-49 | 250 to 750 mg twice daily |
| Severe* | <30 | 250 to 500 mg twice daily |
| End-stage renal disease patients undergoing dialysis (1) (2) | - | 500 to 1000 mg once daily |
(1) A 750 mg loading dose is recommended on the first day of treatment with levetiracetam.
(2) Following dialysis, a 250 to 500 mg supplemental dose is recommended
*or according to best clinical judgement
Dosage Adjustments in Adult Patients with Impaired Hepatic Function
No dose adjustment is needed in patients with mild to moderate hepatic impairment. In patients with severe hepatic impairment, the creatinine clearance may underestimate the renal insufficiency. Therefore a 50% reduction of the daily maintenance dose is recommended when the creatinine clearance is ˂60 mL/min/1.73 m2.
Pediatrics
Pediatric weight-based dosing for add-on therapy in children aged <12 years and adolescents (12-17 years) weighing <50 kg.
The physician should prescribe the most appropriate pharmaceutical form, presentation and strength according to age, weight and dose.
pharma-levetiracetam Oral Solution is the preferred formulation over tablets for use in infants and children under the age of 6 years, or under 25 kg (see Table 3), and in any patients unable to swallow tablets.
Oral Solution Weight-Based Dosing Calculation for Pediatric Patients
The following calculation should be used to determine the appropriate daily dose of oral solution for pediatric patients:
Total daily dose (mL/day) = Daily dose (mg/kg/day)x patient weight (kg) 100 mg/mL
Add-on therapy in infants aged 1 month to <6 months
Oral Solution
The initial therapeutic dose is 7 mg/kg twice daily. Depending upon the clinical response and tolerability, the dose can be increased up to 21 mg/kg twice daily. Dose changes should not exceed increases or decreases of 7 mg/kg twice daily every 2 weeks. The lowest effective dose should be used.
Infants should start the treatment with pharma-levetiracetam 100 mg/mL Oral Solution. To ensure the accuracy of dosing for this age group, administer oral solution using a 1 mL dosing syringe.
Table 2 Dose recommendations for infants aged 1 month to <6 months
| Weight | Starting dose 7 mg/kg twice daily | Maximum dose 21 mg/kg twice daily |
| 4 kg | 28 mg (0.3 mL) twice daily | 84 mg (0.85 mL) twice daily |
| 5 kg | 35 mg (0.35 mL) twice daily | 105 mg (1.05 mL) twice daily |
| 7 kg | 49 mg (0.5 mL) twice daily | 147 mg (1.5 mL) twice daily |
IV Solution
IV dosing is the same as for the oral solution (see Table 2 above). pharma-levetiracetam for Injection is for intravenous use only as an alternative for patients when oral administration is temporarily not feasible. There is no experience with administration of intravenous levetiracetam for a period longer than 4 days.
Add-on therapy in infants aged 6 months to <4 years; children aged 4 to 11 years, and adolescents aged 12 to 17 years weighing less than 50 kg
Oral Solution
The initial therapeutic dose is 10 mg/kg twice daily. Depending upon the clinical response and tolerability, the dose can be increased up to 30 mg/kg twice daily. Dose changes should not exceed increases or decreases of 10 mg/kg twice daily every 2 weeks. The lowest effective dose should be used. For adolescents aged 12 to 17 years weighing 50 kg or more, see adult dosing recommendations.
For accuracy of dosing, use the correct age-appropriate dosing syringe.
- For infants aged 6 months to less than 4 years, administer using a 3 mL dosing syringe.
- For children aged 4 years and older; adolescents and adults, administer using a 10 mL dosing syringe.
Table 3 Dose recommendations for infants aged 6 months to <4 years; children aged 4 to 11 years and adolescents (12 to 17 years) weighing <50 kg
| Weight | Starting dose 10 mg/kg twice daily | Maximum dose 30 mg/kg twice daily |
| 6 kg1 | 60 mg twice daily | 180 mg twice daily |
| 10 kg1 | 100 mg twice daily | 300 mg twice daily |
| 15 kg1 | 150 mg twice daily | 450 mg twice daily |
| 20 kg1 | 200 mg twice daily | 600 mg twice daily |
| 25 kg | 250 mg twice daily | 750 mg twice daily |
| From 50 kg2 | 500 mg twice daily | 1500 mg twice daily |
1Children 25 kg or less should preferably start the treatment with pharma-levetiracetam 100 mg/mL Oral Solution/
2Dose in children and adolescents 50 kg or more is the same as in adults
IV Solution
IV dosing is the same as for the oral solution (see Table 3 above). pharma-levetiracetam for Injection is for intravenous use only as an alternative for patients when oral administration is temporarily not feasible. There is no experience with administration of intravenous levetiracetam for a period longer than 4 days.
Dose Adjustment for Children with Renal Impairment
For children with renal impairment, levetiracetam dose needs to be adjusted based on the renal function as levetiracetam clearance is related to renal function. This recommendation is based on a study in adult renally impaired patients.
The Clcr in mL/min/1.73 m2 may be estimated from serum creatinine (mg/dL). For young adolescents, children and infants, use the following formula (Schwartz formula):
CLCr(mL/min/1.73m2) = Heigℎt (cm) × ks Serum creatinine (mg mL)⁄
ks = 0.45 in term infants < 1 years old.
ks = 0.55 in children <13 years old; adolescent females.
ks = 0.7 in adolescent males.
Table 4 Dosing adjustment for infants, children and adolescent patients weighing less than 50 kg with impaired renal function.
| Group | Creatinine clearance (mL/min/1.73 m2) | Dose and Frequency (1) | |
Infants aged 1 to < 6 months | Infants aged 6 to 23 months*; Children aged 2 to 11 years Adolescents aged 12 – 17 years weighing < 50 kg | ||
| Normal | >80 | IV / Oral Solution 7 to 21 mg/kg (0.07 to 0.21 ml/kg) twice daily | IV / Oral Solution 10 to 30 mg/kg (0.10 to 0.30 ml/kg) twice daily |
| Mild | 50-79 | IV / Oral Solution 7 to 14 mg/kg (0.07 to 0.14 ml/kg) twice daily | IV / Oral Solution 10 to 20 mg/kg (0.10 to 0.20 ml/kg) twice daily |
| Moderate | 30-49 | IV / Oral Solution 3.5 to 10.5 mg/kg (0.035 to 0.105 ml/kg) twice daily | IV / Oral Solution 5 to 15 mg/kg (0.05 to 0.15 ml/kg) twice daily |
| Severe | <30 | IV / Oral Solution 3.5 to 7 mg/kg (0.035 to 0.07 ml/kg) twice daily | IV / Oral Solution 5 to 10 mg/kg (0.05 to 0.10 ml/kg) twice daily |
| End-Stage Renal Disease patients undergoing dialysis | - | IV / Oral Solution 7 to 14 mg/kg (0.07 to 0.14 ml/kg) once daily (2) (4) | IV Solution 10 to 20 mg/kg (0.10 to 0.20 ml/kg) once daily (a) (b) Oral Solution 10 to 20 mg/kg (0.10 to 0.20 ml/kg) once daily (3) (5) |
*Infants aged 6 months to 23 months should receive levetiracetam oral solution.
IV Solution
(a) A 15 mg/kg (0.15 mL/kg) loading dose is recommended on the first day of treatment.
(b) Following dialysis, a 5 to 10 mg/kg (0.05 to 0.10 mL/kg) supplemental dose is recommended.
Oral Solution
(1) The oral solution should be used for doses under 250 mg, for doses not multiple of 250 mg when dosing recommendation is not achieved by taking multiple tablets and for patients unable to swallow tablets.
(2) A 10.5 mg/kg (0.105 mL/kg) loading dose is recommended on the first day of treatment with levetiracetam.
(3) A 15 mg/kg (0.15 mL/kg) loading dose is recommended on the first day of treatment with levetiracetam.
(4) Following dialysis, a 3.5 to 7 mg/kg (0.035 to 0.07 mL/kg) supplemental dose is recommended.
(5) Following dialysis, a 5 to 10 mg/kg (0.05 to 0.10 mL/kg) supplemental dose is recommended.
Switching between IV and oral administration
Conversion to or from IV and oral administration can be done directly without titration. The total daily dose and frequency of administration should be maintained.
4.3 Reconstitution
IV Solution
pharma-levetiracetam for Injection is for single use only. Any unused solution should be discarded.
pharma-levetiracetam for Injection may be mixed with the following diluents and antiepileptic drugs and may be stored in propylene bottles and polyvinyl chloride (PVC) bags. The diluted solution should not be stored for more than 24 hours at a room temperature (15 - 30°C).
Diluents
- Sodium Chloride (0.9%) injection, USP
- Lactated Ringer’s injection
- Dextrose 5% injection, USP
Other antiepileptics
- Lorazepam
- Diazepam
- Valproate Sodium
There are no data to support the physical compatibility of pharma-levetiracetam for Injection with antiepileptic drugs that are not listed above.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit. Product with particulate matter or discoloration should not be used.
4.4 Administration
Levetiracetam therapy can be initiated with either intravenous or oral administration.
Oral Solution
For pediatric patients, dosing is weight-based (mg per kg) and in order to ensure accuracy of dosing, should be dispensed using the appropriate dosing syringe (not a household teaspoon or tablespoon).
- For infants under 6 months, use a 1 mL dosing syringe.
- For patients aged 6 months to less than 4 years, use a 3 mL dosing syringe.
- For all patients aged 4 years and older, use a 10 mL dosing syringe.
The daily dose is administered in two equally divided doses.
pharma-levetiracetam oral solution may be diluted (for example, in a glass of water or baby’s bottle) and may be taken with or without food.
IV Solution
One 5 mL vial of pharma-levetiracetam for Injection contains 500 mg levetiracetam (100 mg/ mL).
pharma-levetiracetam for Injection is for intravenous (IV) use only. The recommended dose must be diluted in 100 mL of a compatible diluent and administered intravenously as a 15-minute intravenous infusion. If a smaller volume is required (e.g. pediatric patients), the amount of diluent should be calculated to not exceed a maximum levetiracetam concentration of 15 mg per mL of diluted solution. Consideration should also be given to the total daily fluid intake of the patient.
There is no experience with administration of intravenous levetiracetam for a period longer than 4 days.
See Table 5 for the recommended preparation and administration of pharma-levetiracetam for Injection to achieve a total daily dose of 500 mg, 1000 mg, 2000 mg, or 3000 mg.
Table 5 Preparation and administration of pharma-levetiracetam for Injection
| Dose | Withdrawal Volume | Volume of Diluent | Infusion Time | Frequency of Administration | Total Daily Dose |
| 250 mg | 2.5 mL (0.5 x of 5 mL vial) | 100 mL | 15-minutes | Twice daily | 500 mg/day |
| 500 mg | 5 mL (1 x 5 mL vial) | 100 mL | 15-minutes | Twice daily | 1000 mg/day |
| 1000 mg | 10 mL (2 x 5 mL vials) | 100 mL | 15-minutes | Twice daily | 2000 mg/day |
| 1500 mg | 15 mL (3 x 5 mL vials) | 100 mL | 15-minutes | Twice daily | 3000 mg/day |
For example, to prepare a 1000 mg dose, dilute 10 mL of pharma-levetiracetam for Injection 100 mL of a compatible diluent and administer intravenously as a 15-minute infusion.
4.5 Missed Dose
If the patient misses a dose by a few hours, they should be instructed to take pharma-levetiracetam as soon as they remember. If it is almost time for their next dose, they should be instructed to take their medication at the next regular time. Patients should not take two doses at the same time.
5. OVERDOSAGE
Symptoms
The highest reported levetiracetam overdose is approximately 10 times the therapeutic dose. In the majority of overdose cases, multiple drugs were involved. Somnolence, agitation, aggression, depressed level of consciousness, respiratory depression, and coma were observed with levetiracetam overdoses. The minimal lethal oral dose in rodents is at least 233 times the maximum clinically studied dose.
Treatment
There is no specific antidote for overdose with levetiracetam; treatment is symptomatic and may include hemodialysis. If indicated, elimination of unabsorbed drug should be attempted by emesis or gastric lavage; usual precautions should be observed to maintain airway. General supportive care of the patient is indicated including monitoring of vital signs and observation of the patient’s clinical status.
Standard hemodialysis procedures result in significant clearance of levetiracetam (approximately 50% in 4 hours) and should be considered in cases of overdose. Although hemodialysis has not been performed in the few known cases of overdose, it may be indicated by the patient's clinical state or in patients with significant renal impairment.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 6 Dosage Forms, Strengths, Composition and Packaging.
- pharma-levetiracetam Oral Solution is available in a 300 mL amber glass bottle with a child-resistant screw cap.
- pharma-levetiracetam for Injection is available in a 5 mL glass vial.
7. WARNINGS AND PRECAUTIONS
General
pharma-levetiracetam is contraindicated in patients who are hypersensitive to pyrrolidine derivatives. Reactions have included anaphylaxis and angioedema (see 7 WARNINGS AND PRECAUTIONS, Immune).
Carcinogenesis and Mutagenesis
See section 16 NON-CLINICAL TOXICOLOGY for a discussion on animal data.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | 100 mg/mL Solution | Ammonium glycyrrhizinate; Citric acid monohydrate; Glycerol; Grapefruit flavour; Maltitol; Methylparahydroxybenzoate; Potassium acesulfame; Propylparahydroxybenzoate; Purified water; Sodium citrate dihydrate |
| Intravenous | 100 mg/mL Solution | Glacial Acetic Acid (to adjust pH), Sodium acetate trihydrate Sodium Chloride, Water for injection. |
Cardiovascular
QT Prolongation
The effect of pharma-levetiracetam on the QTc interval was evaluated in a randomized, double-blind, placebo and positive-controlled, single-dose, four-way crossover study of levetiracetam (1000 mg or 5000 mg) in 52 healthy subjects. The maximum difference from placebo in the mean change from baseline QTc was 4.0 ms (90% CI: 0.0, 8.0) for levetiracetam 1000 mg treatment at 4 h after dosing and 4.1 ms (90% CI: 0.1, 8.1) for the levetiracetam 5000 mg (supratherapeutic) treatment at 1.5 h after dosing.
Rare cases of ECG QT interval prolongation have been observed during post-marketing surveillance in patients with and without a prior history of cardiac conditions. pharma-levetiracetam should be used with caution, particularly in patients with QTc-interval prolongation, in patients concomitantly treated with drugs affecting the QTc-interval, or in patients with relevant pre-existing cardiac disease or electrolyte disturbances (see 8.5 Post-Market Adverse Reactions).
Increase in Blood Pressure in Patients < 4 years of age.
In a randomized, placebo-controlled study in patients 1 month to ˂ 4 years of age, a significantly higher risk of increased diastolic blood pressure was observed in levetiracetam-treated patients (17%), compared to the placebo-treated patients (2%). There was no overall difference in mean diastolic blood pressure between the treatment groups. This disparity between levetiracetam and placebo treatment groups was not observed in the studies of older children or in adults.
Monitor patients 1 month to ˂ 4 years of age for increases in diastolic blood pressure.
Dependence/Tolerance
As with all antiepileptic drugs, pharma-levetiracetam should be withdrawn gradually to minimize the potential of increased seizure frequency.
Driving and Operating Machinery
Levetiracetam may cause somnolence and fatigue, as well as other central nervous system related symptoms (e.g., coordination difficulties). Therefore, patients are advised not to drive or operated machinery or other skilled tasks until it is established that their ability to perform such activities is not affected.
Hematologic
Cases of decreased blood cell counts (neutropenia, agranulocytosis, leucopenia, thrombocytopenia and pancytopenia) have been described in association with levetiracetam administration. Post-market reports include a fatality in a 4-month-old, with swelling of the limbs appearing 5 days after treatment initiation as first-line monotherapy treatment initiation. Complete blood cell counts are advised in patients experiencing important weakness, pyrexia, recurrent infections or coagulation disorders (see 8.5 Post-Market Adverse Reactions).
Adults
Statistically significant decreases compared to placebo were seen in total mean RBC count, mean hemoglobin, and mean hematocrit in levetiracetam-treated patients in controlled trials. For hemoglobin values, the percentage of levetiracetam or placebo treated patients with possibly clinically significant abnormalities were less than 0.5% each. For hematocrit values, a total of 5.1% of levetiracetam treated versus 3.2% of placebo patients had at least one possibly significant decrease in hematocrit (≤ 37% in males and 32% in females).
For white blood cells (WBC), 2.9% of treated versus 2.3% of placebo patients had at least one possibly clinically significant decrease in WBC count (≤ 2.8 x 10⁹/L), while 2.6% of treated vs. 1.7% of placebo patients had at least one possibly significant decrease in neutrophil count (≤ 1.0 x 10⁹/L). Of the levetiracetam treated patients with a low neutrophil count, all but one rose towards or reached baseline with continued treatment. No patient was discontinued secondary to low neutrophil counts.
Pediatric Patients 4 Years to ˂ 16 Years
Statistically significant decreases in WBC and neutrophil counts were seen in levetiracetam-treated patients as compared to placebo. The mean decreases from baseline in the levetiracetam-treated group were -0.4 x 10⁹/L and -0.3 x 10⁹/L, respectively, whereas there were small increases in the placebo group. Mean relative lymphocyte counts increased by 1.7% in levetiracetam-treated patients, compared to a decrease of 4% in placebo patients (statistically significant).
In the controlled trial, more levetiracetam-treated patients had a possibly clinically significant abnormally low WBC value (3% of levetiracetam-treated patients versus 0% of placebo-treated patients), however, there was no apparent difference between treatment groups with respect to neutrophil count (5% of levetiracetam-treated patients versus 4.2% of placebo-treated patients). No patient was discontinued secondary to low WBC or neutrophil counts
In the controlled cognitive and neuropsychological safety study, 5 patients (8.6%) in the levetiracetam-treated group and two patients (6.1%) in the placebo-treated group had high eosinophil count values that were possibly clinically significant (≥ 10% or ≥ 0.7 x 10⁹/L).
Hepatic/Biliary/Pancreatic
Reports of hepatitis and hepatic failure in patients taking levetiracetam, with and without other medications, have been received in post-market surveillance (see 8.5 Post-Market Adverse Reactions). For information on dosage adjustment in patients with severe hepatic impairment, see Dosage Adjustments in Adult Patients with Impaired Hepatic Function.
Immune
Hypersensitivity Reactions
Skin and Subcutaneous tissue disorders
Serious hypersensitivity reactions with dermatological involvement have been reported in both children and adults in association with levetiracetam use, including Stevens-Johnson syndrome
(SJS), Toxic Epidermal Necrolysis (TEN), and Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS).
Such serious skin reactions may be life-threatening, and some patients have required hospitalization with very rare reports of fatal outcome. There is no way to tell if a mild rash will become a severe skin reaction. If any of these hypersensitivity reactions are suspected, and an alternative cause cannot be established, pharma-levetiracetam should be discontinued. Recurrence of the serious skin reactions following re-challenge with levetiracetam has been reported.
The median time to onset for reported cases of SJS and TEN was 12 days. The reporting rate of TEN and SJS associated with levetiracetam use, which is generally accepted to be an underestimate due to underreporting, is 9 cases/million patient years. This exceeds the background incidence rate estimates for these serious skin reactions in the general population; background estimates range between 0.5 to 6 cases per million-person years.
The time to onset of DRESS may be longer than for SJS and TEN, e.g. up to 6 weeks or more after treatment initiation. Typically, although not exclusively, DRESS initially presents with fever and rash, and then with other organ system involvement that may or may not include eosinophilia, lymphadenopathy, hepatitis, nephritis, and/or myocarditis. Because DRESS is variable in its expression, other organ system signs and symptoms not noted here may also occur. Organ involvement may be more severe than skin involvement.
Anaphylaxis and Angioedema
Levetiracetam can cause anaphylaxis or angioedema after the first dose or at any time during treatment. Signs and symptoms in cases reported in the post-marketing setting have included hypotension, hives, rash, respiratory distress, and swelling of the face, lip, mouth, eye, tongue, throat, and feet. In some reported cases, reactions were life-threatening and required emergency treatment. If a patient develops signs or symptoms of anaphylaxis or angioedema, levetiracetam should be discontinued and the patient should seek immediate medical attention. Levetiracetam should be discontinued permanently if a clear alternative etiology for the reaction cannot be established.
Monitoring and Laboratory Tests
Levetiracetam can cause hematologic abnormalities, including decreases in white blood cell (WBC) and neutrophil counts, decreases in red blood cell (RBC) counts, hemoglobin, and hematocrit, and increases in eosinophil counts. (see 7 WARNINGS and PRECAUTIONS, Hematologic).
Reports of increases in liver function tests in patients taking levetiracetam, with and without other medications, have been received in post-market surveillance (see 8.5 Post-Market Adverse Reactions).
Neurologic
Coordination Difficulties
Levetiracetam may cause coordination difficulties. In controlled clinical studies in adult patients with partial onset seizure studies, 3.4% of adult levetiracetam-treated patients experienced coordination difficulties, (reported as either ataxia, abnormal gait, or incoordination) compared to 1.6% of placebo-treated patients. These events occurred most frequently within the first 4 weeks of treatment (see also Central Nervous System Adverse Reactions).
Seizure Worsening
A paradoxical reaction of worsening of seizure may be observed especially when starting treatment or at increase in dose.
Psychiatric
Behavioural Abnormalities and Psychotic Symptoms
pharma-levetiracetam may cause behavioural abnormalities and psychotic symptoms. Patients treated with pharma-levetiracetam should be monitored for psychiatric signs and symptoms. Behavioural and psychiatric adverse reactions were more common in children than in adults (see also Central Nervous System Adverse Reactions; and 8.2.1 Clinical Trial Adverse Reactions - Pediatrics).
Behavioural Abnormalities
In clinical studies, 13% of adult levetiracetam-treated patients and 38% pediatric (4 to 16 years of age) levetiracetam-treated patients compared to 6% and 19% of adult and pediatric placebo-treated patients experienced non-psychotic behavioural symptoms (reported as aggression, agitation, anger, anxiety, apathy, depersonalization, depression, emotional lability, hostility, hyperkinesia, irritability, nervousness, neurosis, and personality disorder).
Irritability was reported in 12% of the levetiracetam-treated patients compared to 0% of placebo-treated patients in clinical studies in pediatric patients 1 month to <4 years of age. Overall, for 11% of levetiracetam-treated pediatric patients, compared to 6% of placebo-treated patients, behavioural symptoms were reported at the time of decision to discontinue or reduce dosage. In a post-market case, a 5-year-old was discontinued from levetiracetam monotherapy after 3 weeks due to neuropsychiatric behaviours, including self-harm attempts.
Worsening of Aggressive Behaviour in Pediatrics
A randomized double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioural effects of levetiracetam as adjunctive therapy in pediatric patients (4 to 16 years of age). The results from an exploratory analysis indicated a worsening in levetiracetam-treated patients on aggressive behaviour (one of eight behaviour dimensions) as measured in the Achenbach Child Behaviour Checklist (CBCL/6-18). Also, 1.6% of levetiracetam-treated patients experienced paranoia, and 3.1% experienced confusional state, compared to 0% of placebo-treated patients for both.
Psychotic Symptoms more Frequent in Pediatric Patients < 4 years
In clinical studies, 17% of levetiracetam-treated pediatric patients 1 month to <4 years of age, 2% of levetiracetam-treated pediatric patients 4 to 16 years of age, and 1% of levetiracetam-treated adult patients experienced psychotic symptoms, compared to 5%, 2%, and 0.2% of the corresponding age groups treated with placebo. Psychotic symptoms seen in both adults and children include hallucinations, psychosis, and psychotic depression.
Suicidal Behaviour and Ideation
Suicide ideation and behaviour have been reported in patients treated with antiepileptic agents in several indications.
All patients treated with antiepileptic drugs, irrespective of indication, should be monitored for signs of suicidal ideation and behaviour and appropriate treatment should be considered. Patients (and caregivers of patients) should be advised to seek medical advice should signs of suicide ideation or behaviour emerge.
An FDA meta-analysis of randomized placebo-controlled trials in which antiepileptic drugs were used for various indications has shown a small increased risk of suicide ideation and behaviour in patients treated with these drugs. The mechanism of this risk is not known.
There were 43,892 patients in the placebo controlled clinical trials that were included in the meta-analysis. Approximately 75% of patients in these clinical trials were treated for indications other than epilepsy and, for the majority of non-epilepsy indications the treatment (antiepileptic drug or placebo) was administered as monotherapy. Patients with epilepsy represented approximately 25% of the total number of patients treated in the placebo-controlled clinical trials, and for the majority of epilepsy patients, treatment (antiepileptic drug or placebo was administered as adjunct to other antiepileptic agents (i.e. patients in both treatment arms were being treated with one or more antiepileptic drug). Therefore, the small increased risk of suicide ideation and behaviour from the meta-analysis (0.43%) for patients on antiepileptic drugs compared to 0.24% for patients on placebo) is based largely on patients that received monotherapy treatment (antiepileptic drug or placebo) for non-epilepsy indications. The study design does not allow an estimation of the risk of suicide ideation and behaviour for patients with epilepsy that are taking antiepileptic drugs, due both to this population being the minority in the study, and the drug-placebo comparison in this population being confounded by the presence of adjunct antiepileptic drug treatment in both arms.
Patients should be monitored for signs of depression and/or suicide ideation and behaviours and appropriate treatment should be considered. Patients (and caregivers of patients) should be advised to seek medical advice should signs of depression and/or suicide ideation or behaviour change.
Renal
Renal excretion of unchanged drug accounts for approximately 66% of administered levetiracetam dose. Consistent with this, pharmacokinetic studies in renally-impaired patients indicate that apparent clearance is significantly reduced in subjects with renal impairment (see 10.3 Pharmacokinetics, Renal Insufficiency).
In patients with renal impairment, levetiracetam dosage should be appropriately reduced. Patients with end stage renal disease, i.e., those undergoing dialysis should be given supplemental doses after dialysis (see Dosage Adjustments in Adult Patients with Impaired Renal Function).
The use of levetiracetam has been very rarely associated with acute kidney injury, with a time onset ranging form a few days to several months.
Reproductive Health: Female and Male Potential
Fertility
The effect of this medication on human fertility is unknown. No adverse effects on male or female fertility or reproductive performance were observed in rats at doses up to
1800 mg/kg/day (see Reproductive and Developmental Toxicology)
Teratogenic Risk
There is non-clinical evidence suggesting that levetiracetam is embryotoxic and teratogenic (see Reproductive and Developmental Toxicology). pharma-levetiracetam should therefore be used during pregnancy only when the potential benefits outweigh the possible risks to the fetus (see 7.1.1 Pregnant Women).
7.1 Special Populations
1 7.1.1 Pregnant Women
Levetiracetam Blood Levels May Decrease During Pregnancy: As with other antiepileptic drugs, physiological changes during pregnancy may affect levetiracetam concentration. There have been reports of decreased levetiracetam concentration during pregnancy. This decrease is more pronounced during the third trimester (up to 60% of baseline concentration before pregnancy). It is recommended that clinical response should be monitored carefully in women receiving levetiracetam treatment during pregnancy, and determination of changes in plasma concentrations should be considered to ensure that adequate seizure control is maintained throughout pregnancy. In the event that medication is increased during pregnancy, the dose may need to be adjusted postpartum.
Anti-Epileptic Drugs and Risk to the Unborn Child: In reproductive toxicity studies in rats and rabbits, levetiracetam induced developmental toxicity at exposure levels similar to or greater than the human exposure. There was evidence of increased skeletal variations/minor anomalies, retarded growth, embryonic death, and increased pup mortality. In the rat, fetal abnormalities occurred in the absence of overt maternal toxicity. The systemic exposure at the observed no effect level in the rabbit was about 4 to 5 times the human exposure.
There are no adequate and well-controlled studies on the use of levetiracetam in pregnant women. Levetiracetam and/or its metabolites cross the placental barrier in animal species and in humans.
Information about the potential risk for humans is limited. Pregnancy registry data indicate that the risk of having a child with a birth defect is greater for women on antiepileptic polytherapy, including levetiracetam as a component, than for women not treated with antiepileptic drugs. pharma-levetiracetam should not be used during pregnancy unless potential benefits to mother and fetus are considered to outweigh potential risks to both. Discontinuation of antiepileptic treatments may result in disease worsening, which can be harmful to the mother and the fetus.
Pregnancy Registry: Pregnant patients taking pharma-levetiracetam should be encouraged to enroll in the North American Antiepileptic Drug Pregnancy Registry. This can be done by calling the toll-free number 1-888-233-2334, and must be done by patients themselves. Information on the registry can also be found at the following website: http://www.aedpregnancyregistry.org/
7.1.2 Breast-feeding
Levetiracetam is excreted in breast milk. Therefore, there is a potential for serious adverse reactions from pharma-levetiracetam in nursing infants. A decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Available data in children did not suggest an impact on growth and puberty. However, long-term effects on learning, intelligence, growth, endocrine function, puberty and childbearing potential in children remain unknown (see also 8.2.1 Clinical Trial Adverse Reactions - Pediatrics).
7.1.4 Geriatrics
There were 347 patients treated with levetiracetam in clinical trials that were 65 or over. No overall differences in safety were observed between these subjects and younger subjects. There were insufficient numbers of elderly patients in controlled trials for epilepsy to adequately assess the effectiveness of levetiracetam in these patients (see also Elderly Patients (65 years and older); and 10.3 Pharmacokinetics, Geriatrics).
Renal function can be decreased in the elderly and levetiracetam is known to be substantially excreted by the kidney. Therefore, the risk of adverse reactions to the drug may be greater in patients with impaired renal function. A pharmacokinetic study in 16 elderly subjects (age 61-88 years) showed a decrease in clearance by about 40% with oral administration of both single dose and 10 days of multiple twice-daily dosing. This decrease is most likely due to the expected decrease in renal function in these elderly subjects. Care should therefore be taken in dose selection for elderly patients, and it may be useful to monitor renal function (see Elderly Patients (65 years and older)).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
In well-controlled clinical studies, the most frequently reported adverse events associated with the use of levetiracetam in combination with other AEDs, not seen at an equivalent frequency among placebo-treated patients, were somnolence, asthenia, dizziness, infection; and most notably in pediatrics, altered mood and behaviour, as well as decreased appetite. Of the most frequently reported adverse events, asthenia, somnolence and dizziness appeared to occur predominantly during the first four weeks of treatment with levetiracetam.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adults
The partial onset seizure data below are representative of the adverse event findings from other seizure types.
Central Nervous System Adverse Reactions
Levetiracetam use is associated with the occurrence of central nervous system (CNS) adverse events; the most significant of these can be classified into 3 main categories: 1) somnolence and fatigue 2) behavioural/psychiatric, and 3) coordination difficulties.
There was no clear dose response relationship for any of the three categories of CNS adverse events, within the recommended dose range of up to 3000 mg/day. Somnolence/asthenia and coordination difficulties occurred most frequently within the first 4 weeks of treatment, and usually resolved while patients remained on treatment. In the case of behavioural/psychiatric symptoms (including such adverse events as aggression, agitation, anger, anxiety, emotional lability, hostility, and irritability), approximately half of the patients reported these events within the first 4 weeks, with the remaining events occurring throughout the duration of the trials. See Table 7 for the incidence rate of individual adverse events contained within each category.
Behavioural/psychiatric symptoms (including agitation, emotional lability, hostility, anxiety, etc.) have been reported approximately equally in patients with and without a psychiatric history.
Table 7 Total combined incidence rate for each of the three categories of CNS adverse events in placebo-controlled add-on clinical trials.
| Category of CNS Adverse Events | Levetiracetam* + Anti-epileptic Therapy (n=672) | Placebo + Antiepileptic Therapy (N=351) |
| Somnolence and Fatigue | ||
| Somnolence | 15% | 10% |
| Fatigue | 14% | 10% |
| Behavioural / Psychological Symptoms | ||
| Non-psychotic (1) | 14% | 6% |
| Psychotic (2) | 1% | 0% |
| Coordination Difficulties | ||
| Coordination Difficulties (3) | 3% | 2% |
*Reflects levetiracetam doses of 1000 mg, 2000 mg, 3000 mg, and 4000 mg per day.
(1) “Non-psychotic behavioural/psychiatric symptoms” encompasses the following terms: agitation, antisocial reaction, anxiety, apathy, depersonalization, depression, emotional lability, euphoria, hostility, euphoria, hostility, nervousness, neurosis, personality disorder, and suicide attempt.
(2) “Psychotic behavioural/psychiatric symptoms” encompasses the following terms: hallucination, paranoid reaction, psychosis, and psychotic depression.
(3) “Coordination difficulties” encompasses the following terms: ataxia, abnormal gait, incoordination.
There was no clear dose relationship for any of the three categories of CNS adverse events, within the recommended dose range of up to 3000 mg/day. In a controlled study including a dose of 4000 mg, administered without titration, the incidence rate of somnolence during the first 4 weeks of treatment for patient receiving the high dose was 42%, compared to 21% for patients receiving 2000 mg/day.
Table 8 Incidence (%) of treatment-emergent adverse events in placebo-controlled add-on studies by body system. Adverse events occurred in at least 1% of levetiracetam-treated patients and occurred more frequently than in placebo-treated patients (Studies N051, N052, N132, and N138).
| Adverse Event | Levetiracetam (N=769) | Placebo (N=439) |
| Body as a Whole | ||
| Asthenia | 14% | 10% |
| Infection | 13% | 7% |
| Digestive System | ||
| Tooth disorder | 2% | 1% |
| Hemic and Lymphatic System | ||
| Ecchymosis | 2% | 1% |
| Nervous System | ||
| Amnesia | 2% | 0% |
| Anxiety | 2% | 1% |
| Ataxia | 3% | 1% |
| Depression | 4% | 2% |
| Dizziness | 9% | 4% |
| Emotional lability | 2% | 0% |
| Hostility | 2% | 1% |
| Nervousness | 4% | 2% |
| Personality disorder | 1% | 0% |
| Somnolence | 15% | 10% |
| Thinking abnormal | 2% | 1% |
| Vertigo | 3% | 1% |
| Respiratory System | ||
| Pharyngitis | 6% | 4% |
| Rhinitis | 4% | 3% |
| Sinusitis | 2% | 1% |
Lack of dose-related incidence of adverse events within therapeutic range
Based on the data from the controlled clinical trials, there was no evidence of dose relationship within the recommended dose range of 1000 to 3000 mg/day.
Discontinuation or dose reduction in well controlled clinical studies
In well controlled clinical studies, 14.3% of patients receiving levetiracetam and 11.7% receiving placebo either discontinued or had a dose reduction as a result of an adverse event. Table 9 lists the most common (>1%) adverse events that resulted in discontinuation or dose reduction.
Table 9 Adverse events that most commonly resulted in discontinuation or dose reduction in placebo-controlled studies in patients with epilepsy.
| Adverse Event | Levetiracetam (N=672) | Placebo (N=351) |
| Asthenia | 9 (1.3%) | 3 (0.9%) |
| Headache | 8 (1.2%) | 2 (0.6%) |
| Convulsion | 16 (2.4%) | 10 (2.8%) |
| Dizziness | 11 (1.6%) | 0 |
| Somnolence | 31 (4.6%) | 6 (1.7%) |
| Rash | 0 | 5 (1.4%) |
The overall adverse event experience profile of levetiracetam was similar between females and males. There are insufficient data to support a statement regarding the distribution of adverse event experience reports by age and race.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
In patients aged 1 month to <4 years, a total of 190 patients have been treated with levetiracetam in placebo-controlled and open-label extension studies. Sixty of these patients were treated with levetiracetam in placebo-controlled studies. In patients aged 4 to 16 years, a total of 645 patients have been treated with levetiracetam in placebo-controlled and open-labels extension studies; 223 of which were treated with levetiracetam in placebo-controlled studies. In both these pediatric age ranges, these data are supplemented with the post-marketing experience of the use of levetiracetam.
In addition, 101 infants aged less than 12 months have been exposed in a post-authorization safety study. No new safety concerns for levetiracetam were identified for infants less than 12 months of age with epilepsy.
Adverse reaction profile
The adverse reaction profile of levetiracetam is generally similar across age groups and across the approved epilepsy indications.
Safety results in pediatric patients in placebo-controlled clinical studies were consistent with the safety profile of levetiracetam in adults except for behavioural and psychological adverse reactions, as well as anorexia / decreased appetite, which were more common in children than in adults (see Behavioural Abnormalities and Psychotic Symptoms).
The risk of anorexia is found to be higher when levetiracetam is co-administrated with topiramate.
Children aged 4 to 16 years
For the most frequent adverse reactions in children and adolescents aged 4 to 16 years, see Table 10.
Table 10 Adverse Reactions* occurring in ≥2% of patients in Pooled Placebo-Controlled, Add-On Studies in Pediatric Patients Ages 4 to 16 Years Experiencing Partial Onset Seizures
| Adverse Event | Levetiracetam (N=165) | Placebo (N=131) |
|---|---|---|
| Headache | 19% | 15% |
| Nasopharyngitis | 15% | 12% |
| Vomiting | 15% | 12% |
| Somnolence | 13% | 9% |
| Fatigue | 11% | 5% |
| Aggression | 10% | 5% |
| Abdominal Pain Upper | 9% | 8% |
| Cough | 9% | 5% |
| Nasal Congestion | 9% | 2% |
| Decreased Appetite | 8% | 2% |
| Abnormal Behaviour | 7% | 4% |
| Dizziness | 7% | 5% |
| Irritability | 7% | 1% |
| Pharyngolaryngeal Pain | 7% | 4% |
| Diarrhea | 6% | 2% |
| Lethargy | 6% | 5% |
| Insomnia | 5% | 3% |
| Agitation | 4% | 1% |
| Anorexia | 4% | 3% |
| Head Injury | 4% | 0% |
| Constipation | 3% | 1% |
| Contusion | 3% | 1% |
| Depression | 3% | 1% |
| Fall | 3% | 2% |
| Influenza | 3% | 1% |
| Mood Altered | 3% | 1% |
| Affect Lability | 2% | 1% |
| Anxiety | 2% | 1% |
| Adverse Event | Levetiracetam (N=165) | Placebo (N=131) |
|---|---|---|
| Arthralgia | 2% | 0% |
| Confusional State | 2% | 0% |
| Conjunctivitis | 2% | 0% |
| Ear Pain | 2% | 1% |
| Gastroenteritis | 2% | 0% |
| Joint Sprain | 2% | 1% |
| Mood Swings | 2% | 1% |
| Neck Pain | 2% | 1% |
| Rhinitis | 2% | 0% |
| Sedation | 2% | 1% |
*Adverse reactions that occurred in ≥2% of levetiracetam-treated patients and more frequently than in placebo-treated patients.
In the controlled pooled pediatric clinical studies in patients 4-16 years of age, 7% of patients receiving levetiracetam and 9% receiving placebo discontinued as a result of an adverse reaction.
Children 1 month to <4 years
Because of the short exposure period in this 7-day study, incidences of adverse reactions are expected to be less than in other pediatric studies in older patients. Therefore, other controlled pediatric data above, should be considered to apply to this group.
Table 11 Adverse Reactions* occurring in ≥5% of patients in a 7-day Placebo-Controlled, Add-On Study in Pediatric Patients Ages 1 Month to ˂ 4 Years Experiencing Partial Onset Seizures
| Adverse Event | Levetiracetam (N=60) | Placebo (N=56) |
| Somnolence | 13% | 2% |
| Irritability | 12% | 0% |
*Individual adverse reactions that occurred in ≥5% of levetiracetam-treated patients and were numerically more common than in placebo-treated patients.
8.3 Less Common Clinical Trial Adverse Reactions
Eye disorders: blurred vision, diplopia
Gastrointestinal disorders: nausea; dyspepsia
Hepatic/Biliary/Pancreatic: abnormal liver function test
Injury, Poisoning, and procedural complication: injury
Musculoskeletal and connective tissue disorder: myalgia, muscular weakness
Psychiatric disorders: suicide attempt, suicide ideation
Nervous system disorders: memory impairment, paraesthesia, disturbances in attention, hyperkinesia, balance disorder; tremor
Skin and subcutaneous tissue disorders: eczema, pruritis erythema multiforme, rash, peripheral nerve symptoms; alopecia
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Levetiracetam can cause hematologic abnormalities, including decreases in white blood cell (WBC) and neutrophil counts, decreases in red blood cell (RBC) counts, hemoglobin, and hematocrit, and increases in eosinophil counts (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
Increased Blood Pressure: Children aged 1 month to < 4 years should be monitored for increases in diastolic blood pressure (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
8.5 Post-Market Adverse Reactions
In post-marketing experience, nervous system and psychiatric disorders have most frequently been reported. In addition to adverse reactions during clinical studies, and listed above, the following adverse reactions have been reported in post-marketing experience. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and lymphatic disorders: agranulocytosis, leukopenia, neutropenia, pancytopenia (with bone marrow suppression identified in some cases), thrombocytopenia (see 7 WARNINGS AND PRECAUTIONS, Immune).
Cardiac disorders: electrocardiogram QT prolonged
Hepatic/Biliary/Pancreatic: Reports of increases in liver function tests, hepatitis, hepatic failure, and pancreatitis in patients taking levetiracetam, with and without other medications, have been received.
Immune system disorders: Hypersensitivity reactions such as SJS, TEN, DRESS and anaphylactic reactions (see 7 WARNINGS AND PRECAUTIONS, Immune).
Infections and infestations: Infection
Metabolism and nutrition disorders: weight decreased, cases of hypokalemia and hypomagnesaemia have been associated with the use of levetiracetam; hyponatremia
Musculoskeletal and connective tissue disorders: muscular weakness, rhabdomyolysis and/or blood creatine phosphokinase increase has been reported in diverse patient populations, however, a higher prevalence of these reports in Japanese patients may signal an elevated risk.
Nervous system disorders: paraesthesia, lethargy, choreoathetosis, dyskinesia, hyperkinesia, increase in seizure frequency.
Psychiatric: anger, panic attack, anxiety, confusional state, hallucination, psychotic disorders (including self-harm attempts by a 5 year-old on levetiracetam monotherapy (see Behavioural Abnormalities and Psychotic Symptoms), suicidal behaviour (including completed suicide); personality disorder; thinking abnormal (see Suicidal Behaviour and Ideation)
Renal and urinary disorders: Cases of acute kidney injury (including acute renal failure, nephritis)
Reproductive Health: Fetal toxicity associated with concomitant use of levetiracetam and other antiepileptic drugs has been reported in pregnancy registries (see 7.1.1 Pregnant Women).
Skin and subcutaneous tissue disorders: alopecia (in several cases, recovery was observed when levetiracetam was discontinued), erythema multiforme, angioedema; toxic epidermal necrosis; Stevens-Johnson syndrome
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
In Vitro Studies on Metabolic Interaction Potential
In vitro, levetiracetam and its primary metabolite have been shown not to inhibit the major human liver cytochrome P450 isoforms (CYP3A4, 2A6, 2C8/9/10, 2C19, 2D6, 2E1 and 1A2), glucuronyl transferase (paracetamol UGT i.e. UCT1A6, ethinyl estradiol UGT i.e. UGT1A1 and p-nitrophenol UGT i.e. UGT [p16.2]) and epoxide hydrolase activities. In addition, levetiracetam does not affect the in vitro glucuronidation of valproic acid. In human hepatocytes in culture, levetiracetam did not cause enzyme induction.
Levetiracetam circulates largely unbound (˂10% bound) to plasma proteins; therefore, clinically significant interactions with other drugs through competition for protein binding sites are unlikely.
Thus, in vitro data, in combination with the pharmacokinetic characteristics of the drug, indicate that levetiracetam is unlikely to produce, or be subject to, pharmacokinetic interactions.
9.3 Drug-Behavioural Interactions
The effect of lifestyle choices (e.g., smoking, alcohol consumption) on the use of pharma-levetiracetam has not been established.
9.4 Drug-Drug Interactions
Adults
The drugs listed in the table below are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 12 Established or Potential Drug-Drug Interactions.
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| phenytoin, valproate | Pharmacokinetic study | Levetiracetam was co-administered with either phenytoin or valproate at doses of 3000 mg/day and 1000 mg/day (500 mg BID), respectively. No clinically significant interactions were observed. | |
| Oral contraceptives ethinyl estradiol and levonorgesterol | Pharmacokinetic study | No clinically significant pharmacokinetic interactions were observed in healthy subjects between levetiracetam (500 mg BID) and the oral contraceptive containing 0.03 mg ethinyl estradiol and 0.15 mg levonorgesterol. | Given that the pharmacokinetic interactions study did not include using levetiracetam as adjunctive therapy nor did it cover the recommended dosage range, physicians should therefore advise their female patients to be alert to any irregular vaginal bleeding or spotting, and to immediately report to them any occurrences. |
| Digoxin | Pharmacokinetic study | Co-administration of levetiracetam (1000 mg BID) and digoxin (0.25 mg/day) did not influence the pharmacokinetics of either drug, nor the pharmacodynamics (ECG) of digoxin. | |
| Warfarin | Pharmacokinetic study | Co-administration of levetiracetam (1000 mg BID) and R and S warfarin (2.5 mg, 5 mg, or 7.5 mg daily) did not influence the pharmacokinetics either drug Prothrombin time was not affected by levetiracetam. |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Probenecid (a renal tubular secretion blocking agent) | Pharmacokinetic study | Probenacid at a dose of 500 mg four times a day, did not change the pharmacokinetics of levetiracetam 1000 mg BID Cssmax of the metabolite, ucb L057, was approximately doubled in the presence of probenecid and the renal clearance of the metabolite ucb L057 was decreased by 60%. This alteration is likely related to competitive inhibition of tubular secretion of ucb L057. The effect of levetiracetam on probenacid was not studied. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Other Antiepileptic Drugs (AEDs)
Potential drug interactions between levetiracetam and other AEDs (phenytoin, carbamazepine, valproic acid, phenobarbital, lamotrigine, gabapentin and primidone) were assessed by evaluating the serum concentrations of levetiracetam and these AEDs during placebo-controlled clinical studies. These data suggest that levetiracetam may not significantly influence the plasma concentrations of these other AEDs, and that the other AEDs may not significantly influence the plasma concentrations of levetiracetam.
Potentially Lethal Methotrexate Blood Levels
Concomitant administration of levetiracetam and methotrexate has been rarely reported to decrease methotrexate clearance, resulting in increased/prolonged blood methotrexate concentration to potentially toxic levels. Blood methotrexate and levetiracetam levels should be carefully monitored in patients treated concomitantly with the two drugs.
Carbamazepine
Based on post-market experience, concomitant use of carbamazepine and levetiracetam has been reported to increase carbamazepine-induced toxicity (e.g. nystagmus, nausea, vomiting).
Topiramate
Based on an analysis of clinical trial data, the risk of anorexia is higher when levetiracetam is co-administered with topiramate.
Laxative
Reports have indicated decreased levetiracetam efficacy when the osmotic laxative macrogol (polyethylene glycol) was administered concomitantly with oral levetiracetam. Therefore, macrogol should not be taken orally for one hour before and for one hour after taking pharma-levetiracetam.
Antacid
No data on the influence of antacids on the absorption of levetiracetam is available.
Pediatrics
As in adults, there is no evidence of clinically significant medicinal product interactions in pediatric patients receiving up to 60 mg/kg/day levetiracetam.
A retrospective assessment of pharmacokinetic interactions in children and adolescents with epilepsy (4 to 17 years) confirmed that adjunctive therapy with orally administered levetiracetam did not influence the steady-state serum concentrations of concomitantly administered carbamazepine and valproate. However, data suggested a 20% higher levetiracetam clearance in children taking enzyme-inducing antiepileptic medicinal products. Dose adjustment is not required.
9.5 Drug-Food Interactions
Levetiracetam is rapidly and almost completely absorbed after oral administration. The extent of absorption of levetiracetam was not altered by food, but the rate of absorption was slightly reduced.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Levetiracetam is a drug of the pyrrolidine class chemically unrelated to existing antiepileptic drugs (AEDs). As with other drugs in this class, the mechanism of action of levetiracetam in man is not known.
10.3 Pharmacokinetics
Single- and multiple-dose pharmacokinetics of levetiracetam have included healthy volunteers, adult and pediatric patients with epilepsy, elderly subjects, and subjects with renal and hepatic impairment. Results of these studies indicate that levetiracetam is rapidly and almost completely absorbed after oral administration. The pharmacokinetic profile is linear with low intra- and inter-subject variability. There is no modification of the clearance after repeated administration. Food does not affect the extent of absorption of levetiracetam, although the rate is decreased. Levetiracetam is not protein-bound (<10% bound) and its volume of distribution is close to the volume of intracellular and extracellular water. Sixty-six percent (66%) of the dose is renally excreted unchanged. The major metabolic pathway of levetiracetam (24% of the dose) is an enzymatic hydrolysis of the acetamide group. It is not liver cytochrome P450 dependent. The metabolites have no known pharmacodynamic activity and are renally excreted. Plasma half-life of levetiracetam across studies is 6-8 hours. Plasma half-life is increased in subjects with renal impairment, and in the elderly primarily due to impaired renal clearance.
Based on its pharmacokinetic characteristics, levetiracetam is unlikely to produce or to be subject to metabolic interactions.
The pharmacokinetic profile is comparable in healthy volunteers and in patients with epilepsy. Due to its complete and linear absorption, plasma levels can be predicted from the oral dose of levetiracetam expressed as mg/kg body weight. Therefore, there is no need for plasma level monitoring of levetiracetam.
The pharmacokinetics of levetiracetam have been characterized in single- and multiple-dose PK studies, with doses up to 5000 mg; these studies included healthy volunteers (N=98), patients with epilepsy (N=58 adult patients and N=24 pediatric patients), elderly subjects (N=16) and subjects with renal and hepatic impairment (N=36 and 16, respectively).
Absorption
Levetiracetam is rapidly and almost completely absorbed after oral administration. The oral bioavailability of levetiracetam tablets is 100%. Plasma peak concentrations (Cmax) are achieved at 1.3 hours after dosing. The extent of absorption is independent of both dose and the presence of food, but the latter delays Tmax by 1.5 hours and decreases Cmax by 20%. The pharmacokinetics of levetiracetam are linear over the dose range of 500 – 5000 mg. Steady-state is achieved after two days of a twice daily administration schedule. Mean peak concentrations (Cmax) are 31 and 43 μg/mL, respectively, following a single 1000 mg dose, and a repeated 1000 mg twice daily dose.
Distribution
Neither levetiracetam nor its primary metabolite is significantly bound to plasma proteins (<10%). The volume of distribution of levetiracetam is approximately 0.5 to 0.7 L/kg, a value that is close to the total body water volume. No tissue distribution data for humans are available.
Metabolism
Levetiracetam is not extensively metabolized in humans. The major metabolic pathway is the enzymatic hydrolysis of the acetamide group, which produces the carboxylic acid metabolite, ucb L057 (24% of dose). The production of this metabolite is not dependent on any liver cytochrome P450 isoenzymes and is mediated by serine esterase(s) in various tissues, including blood cells. The major metabolite is inactive in animal seizure models. Two minor metabolites were identified as the product of hydroxylation of the 2-oxo-pyrrolidine ring (2% of dose) and opening of the 2-oxo-pyrrolidine ring in position 5 (1% of dose). There is no enantiomeric interconversion of levetiracetam or its major metabolite.
Elimination
Levetiracetam plasma half-life in adults is 7 ± 1 hours and is unaffected by either dose or repeated administration. Levetiracetam is eliminated from the systemic circulation by renal excretion as unchanged drug which represents 66% of administered dose. The total body clearance is 0.96 mL/min/kg and the renal clearance is 0.6 mL/min/kg. The mechanism of excretion is glomerular filtration with subsequent partial tubular reabsorption. The primary metabolite, ucb L057, is excreted by glomerular filtration and active tubular secretion with a renal clearance of 4 mL/min/kg. Levetiracetam elimination is correlated to creatinine clearance. Levetiracetam clearance is reduced in patients with impaired renal function (see 7 WARNINGS AND PRECAUTIONS, Renal; and Dosage Adjustments in Adult Patients with Impaired Renal Function).
Special Populations and Conditions
Pediatrics
Children (4 to 12 years)
Pharmacokinetics of levetiracetam were evaluated in 24 pediatric patients (age 6-12 years) after single dose (20 mg/kg). The half-life of levetiracetam was 6.0 hours. The body weight adjusted apparent clearance of levetiracetam was approximately 40% higher than in adults.
A repeat dose pharmacokinetic study was conducted in pediatric patients (age 4-12 years) at doses of 20 mg/kg/day, 40 mg/kg/day, and 60 mg/kg/day. The evaluation of the pharmacokinetic profile of levetiracetam and its metabolite (ucb L057) in 14 pediatric patients demonstrated rapid absorption of levetiracetam at all doses with a Tmax of about 1 hour and a t1/2 of 5 hours across the three dosing levels. The pharmacokinetics of levetiracetam in children was linear between 20 to 60 mg/kg/day. The apparent body clearance was 1.1 mL/min/kg. The potential interaction of levetiracetam with other AEDs was also evaluated in these patients. The apparent body clearance was 1.1 mL/min/kg. Levetiracetam had no significant effect on the plasma concentrations of carbamazepine, valproic acid, topiramate or lamotrigine. However, there was about a 22% increase of apparent clearance of levetiracetam when it was co-administered with an enzyme-inducing AED (e.g. carbamazepine).
Infants and Children (1 month to 4 years)
Following single dose administration (20 mg/kg) of a 10% oral solution to children with epilepsy (1 month to < 4 years), levetiracetam was rapidly absorbed and peak plasma concentrations were observed approximately 1 hour after dosing. The pharmacokinetic results indicated that half-life was shorter (5.3 h) than for adults (7.2 h) and apparent clearance was faster (1.5 mL/min/kg) than for adults (0.96 mL/min/kg).
Population Pharmacokinetic Analysis
Population pharmacokinetic analysis conducted in patients from 1 month to 16 years of age showed that body weight was significantly correlated to the clearance of levetiracetam in pediatric patients; clearance increased with an increase in body weight and apparent volume of distribution. Age also had an influence on both parameters. This effect was pronounced for the younger infants and subsided as age increased, to become negligible around 4 years of age.
IV Solution: A population pharmacokinetic analysis for the intravenous formulation was conducted in 49 patients (1 month to <16 years of age) weighing 3-79 kg. Patients received levetiracetam as a 15-minute IV infusion at doses between 14 mg/kg/day and 60 mg/kg twice daily. Plasma concentrations and model derived steady-state exposure AUC (0-12) were within the range of the exposure observed in pediatric patients receiving equivalent doses of the oral solution.
Geriatrics
Pharmacokinetics of levetiracetam were evaluated in 16 elderly subjects, ranging in age from 61 to 88 years, with 11 of the 16 patients aged 75 years of age or over with creatinine clearance ranging from 30 to 74 mL/min. Following oral administration of 500 mg twice-daily dosing for 10 days, total body clearance decreased by 38% and the half-life was increased about 40% (10 to 11 hours) when compared to healthy adults. This is most likely due to the decrease in renal function in these subjects.
Sex
Levetiracetam Cmax and AUC were 20% higher in women (N=11) compared to men (N=12). However, clearances adjusted for body weight were comparable.
Pregnancy and Breast-feeding
Levetiracetam levels may decrease during pregnancy.
Ethnic origin
Formal pharmacokinetic studies of the effects of race have not been conducted. Because levetiracetam is primarily renally excreted and there are no important racial differences in creatinine clearance, pharmacokinetic differences due to race are not expected.
Hepatic Insufficiency
A single dose pharmacokinetic study was performed in 16 subjects with hepatic impairment (N=5 mild/Child-Pugh Grade A; N=6 moderate/Grade B; N=5 severe/Grade C vs 5 healthy controls). For the mild and moderate subgroups neither mean nor individual pharmacokinetic values were clinically different from those of controls. In patients with severe hepatic impairment, mean apparent body clearance was 50% that of normal subjects, with decreased renal clearance accounting for most of the decrease. Therefore a 50% reduction of the daily maintenance dose is recommended when the creatinine clearance is ˂60 mL/min/1.73 m2 (see Dosage Adjustments in Adult Patients with Impaired Hepatic Function; and 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Renal Insufficiency
Single dose pharmacokinetics were performed in 20 subjects with renal impairment (N=7 mild/CLcr of 50-79 mL/min; N=8 moderate/CLcr of 30-49 mL/min; N=5 severe/CLcr<30 mL/min), and N=11 matching healthy volunteers. Clearance of levetiracetam is correlated with creatinine clearance and levetiracetam pharmacokinetics following repeat administration were well predicted from single dose data. The apparent body clearance of the parent drug levetiracetam is reduced in patients with impaired renal function by approximately 40% in the mild group, 50% in the moderate group, and 60% in the severe renal impairment group. For the primary metabolite ucb L057, the decrease in clearance values from baseline was greater than that seen for the parent drug in all subject groups.
In anuric (end stage renal disease) patients, the apparent body clearance was approximately 30% compared to that of normal subjects. Approximately 50% of the pool of levetiracetam in the body is removed during a standard 4-hour hemodialysis procedure.
Dosage should be reduced in patients with impaired renal function receiving levetiracetam, and supplemental doses should be given to patients after dialysis (see Dosage Adjustments in Adult Patients with Impaired Renal Function; and 7 WARNINGS AND PRECAUTIONS, Renal).
11 STORAGE, STABILITY AND DISPOSAL
Oral Solution
Store solution at 15 - 30°C in the original container to protect from light. Store in an upright position. Discard 7 months after opening. Bring unused medication to your local pharmacist for proper disposal. Keep out of the reach and sight of children.
IV Solution
pharma-levetiracetam is a clear, colourless transparent solution. Check colour and consistency of pharma-levetiracetam prior to use. Any product with particulate matter or discoloration should not be used.
Un-diluted pharma-levETIRAcetam
Store in the original container to protect from light. Store concentrate at 15 - 30°C. This medicinal product is single use only; any unused solution should be discarded. Do not freeze.
Diluted pharma-levETIRAcetam
Dilution should be used immediately. Once diluted, pharma-levetiracetam is stable after dilution for 24 hours at 15 - 30°C in Polypropylene bottles and PVC Flexible bags.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: levetiracetam
Chemical name: (-)-(S)-α-ethyl-2-oxo-1-pyrrolidine acetamide
Molecular formula and molecular mass: C8H14N2O2 and 170.21
Structural formula:
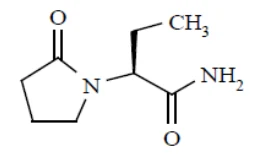
Physicochemical properties:
Physical Form: A white to off-white powder.
Solubility: It is very soluble in water, soluble in acetonitrile and practically insoluble in hexane.
pKa and pH values: The pKa of levetiracetam cannot be determined due to the absence of ioniziable groups. The pH of the oral solution is 6.5. The pH of the IV solution is approximately 5.5 and the pKa (base) is approximately 5.09.
Partition co-efficient: log P is 0.6.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Partial onset seizures (adults and pediatrics aged 1 month to 16 years)
Adults
Trial Design and Demographics
Table 13 Summary of patient demographics for clinical trials in Partial Onset Seizures in Adults with Epilepsy
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age ±SD (years) | Sex |
| N132 | Double-blind, randomized, placebo-controlled, parallel group, multicenter safety and efficacy trial | LEV: 1000 mg/day (500 mg, bid), LEV: 3000 mg/day (1000 mg, bid) Oral 4-week up-titration 14-week evaluation | Placebo: 95 LEV (1000 mg/day): 98 LEV (3000 mg/day): 101 | Placebo: 38 ± 11 LEV 1000 mg/day: 38 ± 11 LEV 3000 mg/day: 38 ± 11 | 178 M 116 F |
| N051 | Multicentre, double-blind, randomized, placebo-controlled safety and efficacy trial | LEV: 1000 mg/day (500 mg, bid), LEV: 2000 mg/day (1000 mg, bid) Oral 4-week titration 12-week evaluation | Placebo: 112 LEV (1000 mg/day): 106 LEV (2000 mg/day): 106 | Placebo: 37 ± 12 LEV1000 mg/day: 36 ± 10 LEV 2000 mg/day: 37 ± 12 | 157 M 167 F |
| N138 | Multicentre, double-blind, placebo-controlled, parallel group, responder-selected study | LEV: 3000 mg/day (1500 mg, bid) Oral 18-week Add-on: 4-week up-titration 14-week evaluation Monotherapy 12-week monotherapy | Placebo: 105 LEV (3000 mg/day): 181 | Placebo: 36 ± 12 LEV: 37 ± 12 | 137 M 149 F |
Study Results
The efficacy of levetiracetam as adjunctive therapy (added to other antiepileptic drugs) in adults was established in three multicenter, randomized, double-blind, placebo-controlled clinical studies in a total of 904 adult patients who had a history of partial onset seizures with or without secondary generalization.
General Methodology
Patient Population
Patients in these three studies had refractory partial onset seizure for a minimum of 1 (or 2) year(s) prior to enrollment. They had previously taken a minimum number of classical AEDs (either one or two), and at the time of the study were taking a stable dose regimen of at least one AED. During the baseline period, it was required that patients experienced a minimum of 12 partial onset seizures over 12 weeks (Study N132) or 4 partial onset seizures during each 4-week period (Study N051) or 2 partial onset seizures per 4-week period (Study N138).
Dosing Schedule
After a prospective baseline period of approximately 12 weeks, patents were randomized to placebo, or levetiracetam at 1000 mg, 2000 mg, or 3000 mg/day (depending on the study), given as twice daily doses. In all trials, there was a 2 or 4-week titration period, followed by a 12-14-week maintenance period.
Measure of Efficacy
The primary measure of efficacy was a between group comparison of the percent reduction in weekly partial seizure frequency relative to placebo over the entire randomized treatment period (titration + maintenance). Secondary efficacy parameters include the 50% and 100% responder rate in partial onset seizure frequency over the entire randomized treatment period. Efficacy results are based on the ITT population with the exception of a few patients lacking evaluable seizure frequency data.
The above trial description applies to all three studies below. Thus, for each trial, only partial distinguishing information is stated below.
Study N132
Study N132 was a parallel-group study conducted in the United States comparing placebo, levetiracetam 1000 mg/day, and levetiracetam 3000 mg/day in 95, 98, and 101 randomized patients, respectively. The efficacy for study N132 is display in Table 14.
Table 14 Median percent reduction from baseline in weekly frequency of Partial Onset Seizures in Study N132
| AED + Placebo | AEDs + Levetiracetam 1000 mg/day | AEDs + Levetiracetam 3000 mg/day | |
| N | 95 | 97 | 101 |
| Median Baseline Seizure Frequency | 1.77 | 2.53 | 2.08 |
| Percent reduction in partial seizure frequency from baseline | 6.9% | 36.9% | 38.1% |
*P<0.001 versus placebo
Study N051
Study N051 was a cross-over study conducted in Europe comparing placebo, levetiracetam 1000 mg/day, and levetiracetam 2000 mg/day in 112, 106, and 106 randomized patients, respectively.
The first period of the study (Period A) was designed to be analyzed as a parallel-group study. The efficacy results for Period A are displayed in Table 15.
Table 15 Median percent reduction from baseline in weekly frequency of Partial Onset Seizures in study N051 Period A
| AED + Placebo | AEDs + Levetiracetam 1000 mg/day | AEDs + Levetiracetam 2000 mg/day | |
| N | 111 | 106 | 105 |
| Median Baseline Seizure Frequency | 2.46 | 2.82 | 2.59 |
| Percent reduction in partial seizure frequency from baseline | 1.1% | 20.7% | 24.4% |
*P<0.001 versus placebo
Study N138
Study N138 was a parallel-group study conducted in Europe comparing placebo and levetiracetam 3000 mg/day in 105 and 181 randomized patients, respectively. Table 16 display the efficacy result for Study N138.
Table 16 Median percent reduction from baseline in weekly frequency of Partial Onset Seizures in study N138
| AED + Placebo | AEDs + Levetiracetam 3000 mg/day | |
| N | 104 | 180 |
| Median Baseline Seizure Frequency | 1.78 | 1.67 |
| Percent reduction in partial seizure frequency from baseline | 7.3% | 36.8% |
Responder Rates
Each patient is categorized according to their efficacy data: percent reduction from baseline in weekly frequency of partial onset seizures, calculated over the entire randomized treatment period. The percentage of patients who remained on levetiracetam for at least 21 days and achieved ≥50% reduction, or a 100% reduction (seizure free) within each of the three pivotal studies is presented in Table 17.
Table 17 Partial onset responder rate of the entire treatment period by randomized dose.
| Percent Reduction | AED + Placebo | AEDs + Levetiracetam 1000 mg/day | AEDs + Levetiracetam 2000 mg/day | AEDs + Levetiracetam 3000 mg/day |
|---|---|---|---|---|
| Study N132 | ||||
| N | 95 | 97 | - | 101 |
| ≥50% | 7% | 36% | - | 40% |
| seizure free (100%) | 0% | 3% | - | 6% |
| Study N051 | ||||
| N | 111 | 106 | 105 | - |
| ≥50% | 6% | 21% | 34% | - |
| seizure free (100%) | 1% | 2% | 3% | - |
| Study N138 | ||||
| N | 104 | - | - | 180 |
| ≥50% | 14% | - | - | 39% |
| seizure free (100%) | 0% | - | - | 7% |
Pediatrics
Trial Design and Demographics
Table 18 Summary of patient demographics for clinical trials in Partial Onset Seizures in Pediatric Patients 4 Years to 16 Years with Epilepsy
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Median age (Range) (years) | Sex |
| N159 | Randomized , double-blind, placebo-controlled, multicentre trial | LEV initial dose: 20 mg/kg/day (10 mg/kg, bid) Dose adjusted by 20 mg/kg/day every 2 weeks to a target dose of 60 mg/kg/day Oral 4-week up titration 10-week evaluation | Placebo: 97 LEV: 101 | Placebo: 9.7 (3-17) years LEV: 10.4 (4 – 17) years | 100 M 98 F |
LEV: levetiracetam.:
Table 19 Summary of patient demographics for clinical trials in Partial Onset Seizures in Pediatric Patients 1 Month to ˂4 Years with Epilepsy
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age ±SD (months) | Sex |
| N1009 | Double-blind, randomized, placebo-controlled, multicenter trial | Age 1 month to < 6 months: LEV initial dose: 20 mg/kg/day titrated to 40 mg/kg/day Age 6 months to < 4 years: LEV initial dose: 25 mg/kg/day titrated to 50 mg/kg/day Oral 5-day treatment 1 day up-titration 4 days stable-dose treatment | Placebo: 56 LEV: 60 | Placebo: 23.5 ± 12.1 LEV: 23.4 ± 13.4 | 57 M 59 F |
LEV: levetiracetam.
Study Results
Children 4 to 16 years
In pediatric patients (4 to 16 years of age), levetiracetam efficacy was established in a double-blind, placebo-controlled study, which included 198 patients and had a treatment duration of 14 weeks. In this study, the patients received levetiracetam as a fixed dose of 60 mg/kg/day (with twice a day dosing). Table 20 displays the efficacy result.
Table 20 Responder rate in children aged 4 to 16 years with partial onset seizures following adjunctive treatment with levetiracetam.
Levetiracetam 60 mg/kg/day N=101 | PBO N=97 | |
| ≥50% reduction in seizure frequency per week | 44.6% | 19.6% |
**with continued long-term treatment
In the open-label follow-up, 11.4% of the patients were seizure-free for at least 6 months, and 7.2% were seizure-free for at least 1 year.
Infants & Children 1 month to <4 years
In paediatric patients (1 month to less than 4 years of age), levetiracetam efficacy was established in a double-blind, placebo-controlled study, which included 116 patients and had a treatment duration of 5 days. In this study, patients were prescribed 20 mg/kg; 25 mg/kg, 40 mg/kg, or 50 mg/kg daily dose of oral solution based on their age titration schedule. A dose of 20 mg/kg/day titrating to 40 mg/kg/day for infants 1 month to less than 6 months, and a dose of 25 mg/kg/day titrating to 50 mg/kg/day for infants and children 6 months to less than 4 years old were used in this study. The total daily dose was administered twice daily.
The primary measure of effectiveness was the responder rate (percentage of patients with ≥50% reduction from baseline in average daily partial onset seizure frequency) assessed by a blinded central reader using a 48-hour video EEG. The efficacy analysis consisted of 109 patients who had at least 24 hours of video EEG in both baseline and evaluation periods. Table 21 displays the efficacy result.
Table 21 Responder rate in children aged 1 month to <4 years with partial onset seizures following adjunctive treatment with levetiracetam.
Levetiracetam 40 mg/kg/day or 50 mg/kg/day N=60 | PBO N=56 | |
| ≥50% reduction in seizure frequency per week | 43.6% | 19.6% |
The results are consistent across age groups. In the open-label follow-up, 8.6% of the patients were seizure-free for at least 6 months and 7.8% were seizure-free for at least 1 year.
Thirty-five infants aged less than 1 year with partial onset seizures have been exposed in placebo-control clinical studies of which only 13 were aged < 6 months.
Myoclonic seizures (adults and adolescents)
Trial Design and Demographics
Table 22 Summary of patient demographics for clinical trials in Myoclonic Seizures in Patients ≥ 12 Years of Age with Juvenile Myoclonic Epilepsy
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age ±SD (years) | Sex |
| N166 | Randomized, double-blind, placebo-controlled, multicenter trial | LEV: initial dose: 1000 mg/day (500 mg, bid) titrated to target 3000 mg/day over 4 weeks Oral 12-week evaluation | Placebo: 60 LEV: 61 | Placebo: 26.8 ± 9.5 LEV: 25 ± 7.4 | 44 M 77 F |
LEV: levetiracetam.
Study Results
Adjunctive therapy in the treatment of myoclonic seizures in adults and adolescents from 12 years of age with Juvenile Myoclonic Epilepsy.
Levetiracetam efficacy was established in a double-blind, placebo-controlled study of 16 weeks duration in patients 12 years of age and older suffering from idiopathic generalized epilepsy with myoclonic seizures in different syndromes. The majority of patients presented with juvenile myoclonic epilepsy. In this study, levetiracetam dose was 3000 mg/day given in 2 divided doses. Efficacy result is presented in Table 23.
Table 23 Responder rate in adults and adolescents aged 12 years and older with myoclonic seizures following adjunctive treatment with levetiracetam.
Levetiracetam 3000 mg/day N=61 | PBO N=60 | |
| ≥50% reduction in seizure frequency per week | 58.3% | 23.3% |
In the open-label follow-up, 28.6% of the patients were free of myoclonic seizures for at least 6 months and 21.0% were free of myoclonic seizures for at least 1 year.
Primary generalized tonic-clonic seizures (adults and adolescents)
Trial Design and Demographics
Table 24 Summary of patient demographics for clinical trials in Primary Generalized Tonic-Clonic Seizures in Patients ≥ 6 Years of Age
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age ±SD (years) | Sex |
| N1057 | Multicentre, randomized, double-blind, placebo-controlled, parallel group study | Adults: 3000 mg/day Children*: 60 mg/kg/day Oral 4-week up-titration 20-week evaluation | Placebo: 84 LEV: 80 | Placebo: 30.6 ± 12.1 LEV: 26.9 ± 11.2 | 73 M 91 F |
LEV: levetiracetam. *includes adolescents up to <16 years of age and weighing <50 kg.
Study Results
Adjunctive therapy in the treatment of primary generalized tonic-clonic seizures in adults and adolescents from 12 years of age with idiopathic generalized epilepsy.
Levetiracetam efficacy was established in a 24-week double-blind, placebo-controlled study which included adults, adolescents and a limited number of children suffering from idiopathic generalized epilepsy with primary generalized tonic-clonic (PGTC) seizures in different syndromes (juvenile myoclonic epilepsy, juvenile absence epilepsy, childhood absence epilepsy, or epilepsy with Grand Mal seizures on awakening). In this study, levetiracetam dose was 3000 mg/day for adults and adolescents or 60 mg/kg/day for children, given in 2 divided doses. Efficacy result is presented in Table 25.
Table 25 Responder rate in adults and adolescents aged 12 years and older with primary generalized tonic-clonic seizures following adjunctive treatment with levetiracetam.
Levetiracetam 3000 mg/day or 60 mg/kg/day N=80 | PBO N=81 | |
| ≥50% reduction in seizure frequency per week | 72.2% | 45.2% |
In the open-label follow-up, 47.4% of the patients were free of tonic-clonic seizures for at least 6 months and 31.5% were free of tonic-clonic seizures for at least 1 year.
Regarding the IV formulation:
All clinical studies supporting the efficacy of levetiracetam utilized the oral formulation. The finding of efficacy of levetiracetam injection is based on the results of studies using an oral formulation of levetiracetam, and on the demonstration of comparative bioavailability of the oral and parenteral formulations (see 10.3 Pharmacokinetics, Special Populations and Conditions).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
The general toxicity of levetiracetam was evaluated after oral administration in acute (mouse, rat, dog and monkey), subacute and chronic (two to 52 weeks or longer in the mouse, rat and dog) studies. Acute (mouse, rat and dog) and two-week (rat and dog) toxicity studies were also conducted using iv administration.
The single-dose studies in mice, rats and dogs indicate a low acute toxicity potential. Lethality was only reached after iv dosing in these studies; although in a subsequent study in mice (micronucleus test), lethality was reached at 10000 mg/kg orally. Oral administration is associated with only transient clinical signs (emesis, salivation, tremors, decreased motor activity, ataxia, tachypnea and side lying). In dogs, emesis is a dose-limiting effect.
Repeat administration of levetiracetam is well tolerated. Mortality is observed only following iv administration of 900 mg/kg in rats. In general, clinical signs are minimal across studies and species with the most consistent observations being neuromuscular effects, salivation, and emesis in dogs. In the rodent only, treatment-related changes in the liver and kidney were reported. In the liver, a reversible increase in liver weight and hypertrophy of centrilobular hepatocytes was observed in both sexes in rats and mice. Centrilobular vacuolation associated with lipid deposition occurred in male rats and in mice. Kidney pathology consisting of hyaline droplet nephropathy, exacerbation of chronic progressive nephropathy and associated changes was observed in male rats.
These changes are considered to be a male rat-specific pathology associated with α2-microglobulin accumulation in the proximal tubules that is not toxicologically relevant to man. There was no target organ identified in the dog. No lethality, organ failure or other irreversible toxicity was observed after long-term oral treatment up to 1800 mg/kg/day in the rat, 960 mg/kg/day in the mouse and 1200 mg/kg/day in the dog.
Studies in neonatal or juvenile animals do not indicate any greater potential for toxicity compared to adult animals. Investigations involving oral administration of up to 2 weeks of ucb L057, the major human metabolite, indicate a low potential for toxicity in rats and dogs.
Carcinogenicity
Rats were dosed with levetiracetam in the diet for 104 weeks at doses of 50, 300 and 1800 mg/kg/day. There was no evidence of carcinogenicity. Two studies have been conducted in mice. In one study, mice received levetiracetam in the diet for 80 weeks at doses of 60, 240 and 960 mg/kg/day (high dose is equivalent to 2 times the MRHD on a mg/m2 or exposure basis). In a second study, mice received levetiracetam by oral gavage for 2 years at dose levels of 1000, 2000 and 4000 mg/kg/day. Due to poor survival at the highest dose of 4000 mg/kg/day in this study, the high dose was reduced to 3000 mg/kg/day (equivalent to 12 times the MRHD). In neither study was evidence of carcinogenicity seen.
Genotoxicity
Levetiracetam was not mutagenic in the Ames test or in mammalian cells in vitro in the Chinese hamster ovary/HGPRT locus assay. It was not clastogenic in an in vitro analysis of metaphase chromosomes obtained from Chinese hamster ovary cells or in an in vivo mouse micronucleus assay. The hydrolysis product and major human metabolite of levetiracetam (ucb L057) was not mutagenic in the Ames test or the in vitro mouse lymphoma assay.
Reproductive and Developmental Toxicology
No adverse effects on male or female fertility or reproductive performance were observed in rats at doses up to 1800 mg/kg/day.
Administration to rats before mating and throughout pregnancy and lactation was associated with slightly retarded fetal growth and skeletal ossification in utero and slight increase in pup mortality between birth and day 8 postpartum at 1800 mg/kg/day and slightly retarded skeletal ossification at 350 mg/kg/day.
When female rats were administered levetiracetam orally up to 1800 mg/kg/day from day 15 of pregnancy to weaning (day 21 postpartum), no effects were observed on litter parameters, pup survival and development. The dose of 1800 mg/kg/day corresponds to 30-fold the upper recommended daily dose in man on a mg/kg/day basis or 6-fold when calculated on a mg/m2 body surface area basis.
In pregnant rats treated at 400, 1200 and 3600 mg/kg/day from day 6 to 15 of pregnancy, the no adverse effect level for embryo-fetal survival, growth and development is 1200 mg/kg/day. There was a slight increase in the proportion of fetuses with supernumerary ribs (thoracolumbar border) and a marginal reduction in skeletal ossification at 3600 mg/kg/day. The NOAEL was 3600 mg/kg/day for pregnant female rats (12 times the maximum recommended human dose [MRHD] on a mg/m2 basis).
In pregnant rabbits, the no-adverse effect level for embryo-fetal survival, growth and development was 200 mg/kg/day, a dose producing adverse effects in the mothers. At the highest dose of 1800 mg/kg/day, a 2.5-fold increase in fetal abnormalities was observed together with marked maternal toxicity. This was not seen in two other studies. The dose of 1800 mg/kg/day corresponds to 30-fold the upper recommended dose in man on a mg/kg/day basis or 11-fold when calculated on a mg/m2 basis.
In a study in pregnant mice, levetiracetam administered at 3000 mg/kg/day from day 6 to 15 of pregnancy produced a slight retardation of growth and skeletal ossification and no effect on survival and morphological development. Plasma levetiracetam concentrations at approximate peak time were 20-fold higher than peak concentrations measured in man after 3000 mg/day.