


Product Monograph - PMS-Hydrochlorothiazide (Pharmascience, 25 mg, 50 mg, 12.5 mg)
Recent Major Label Changes
| 4.2 Recommended dose and dosage adjustment | 2026-10 |
|---|---|
| 7 Warnings and Precautions, Ophthalmologic | 2026-10 |
| 7 Warnings and Precautions, Respiratory | 2026-10 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics ..................................................................................................................... 4
1.2. Geriatrics ..................................................................................................................... 4
- 2. Contraindications ............................................................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 5
4.1. Dosing Considerations ................................................................................................. 5
4.2. Recommended Dose and Dosage Adjustment ............................................................. 5
4.4. Administration ............................................................................................................. 6
4.5. Missed Dose ................................................................................................................. 6
- 5. Overdose ......................................................................................................................... 6
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 7
- 7. Warnings and Precautions ............................................................................................... 7
General................................................................................................................................... 7
Carcinogenesis and Genotoxicity ............................................................................................ 7
Endocrine and Metabolism ..................................................................................................... 8
Gastrointestinal ...................................................................................................................... 9
Hepatic/Biliary/Pancreatic ..................................................................................................... 9
Immune .................................................................................................................................. 9
Ophthalmologic ...................................................................................................................... 9
Renal .................................................................................................................................... 10
Respiratory ........................................................................................................................... 10
Skin ...................................................................................................................................... 10
7.1. Special Populations .................................................................................................... 10
7.1.1. Pregnant Women ....................................................................................................... 10
7.1.2. Breastfeeding ............................................................................................................. 10
7.1.3. Pediatrics .................................................................................................................... 10
7.1.4. Geriatrics .................................................................................................................... 11
- 8.
Adverse Reactions ......................................................................................................... 11
8.1. Adverse Reaction Overview .......................................................................................... 11
8.2. Clinical Trial Adverse Reactions .................................................................................... 11
8.5 Post-Market Adverse Reactions .................................................................................... 11
- 9.
Drug Interactions ........................................................................................................... 12
9.3. Drug-Behaviour Interactions ........................................................................................ 12
9.4. Drug-Drug Interactions ................................................................................................. 12
9.5. Drug-Food Interactions ................................................................................................ 16
9.6. Drug-Herb Interactions ................................................................................................. 16
9.7. Drug-Laboratory Test Interactions ................................................................................ 16
- 10.
Clinical Pharmacology ............................................................................................... 16
10.1. Mechanism of Action ................................................................................................... 16
10.2. Pharmacodynamics ...................................................................................................... 16
10.3. Pharmacokinetics ......................................................................................................... 16
- 11. Storage, Stability, and Disposal ...................................................................................... 16
Part 2: Scientific Information ................................................................................................ 17
- 13. Pharmaceutical Information .......................................................................................... 17
- 14.
Clinical Trials .................................................................................................................. 18
1.2. 14.1. Clinical Trials by Indication ............................................................................ 18
1.3. 14.2. Comparative Bioavailability Studies ............................................................... 18
- 15. Microbiology ............................................................................................................. 19
- 16. Non-Clinical Toxicology ............................................................................................. 19
Patient Medication Information ........................................................................................... 21
Part 1: Healthcare Professional Information
1. Indications
pms-HYDROCHLOROTHIAZIDE (hydrochlorothiazide) is indicated for the treatment of:
- Edema
- Hypertension
- Toxemia of Pregnancy
Edema
pms-HYDROCHLOROTHIAZIDE (hydrochlorothiazide) is indicated in edema associated with congestive heart failure, hepatic cirrhosis, corticosteroid and estrogen therapy, premenstrual tension with edema and in edema of renal origin (i.e. nephrotic syndrome, acute glomerulonephritis and chronic renal disease). In obese patients in whom fluid retention is a complicating factor, it may help to initiate a loss of fluid and, thus of weight.
Hypertension
pms-HYDROCHLOROTHIAZIDE may be used alone or as an adjunct to other antihypertensive drugs. Since it enhances the action of these agents, their dosage must be reduced to avoid an excessive drop in pressure and other unwanted side effects.
Toxemia of Pregnancy
pms-HYDROCHLOROTHIAZIDE may be effective in the treatment of toxemia of pregnancy (including eclampsia).
1.1. Pediatrics
Pediatrics (0 to 12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of hydrochlorothiazide in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.3 Pediatrics).
1.2. Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2. Contraindications
pms-HYDROCHLOROTHIAZIDE is contraindicated:
- In patients with anuria (as all diuretics are).
- If increasing azotemia and oliguria occur during treatment of severe progressive renal disease.
- In patients known to be sensitive to hydrochlorothiazide or to other sulfonamide-derived drugs.
- In patients who are hypersensitive to any ingredient in the formulation of pms-HYDROCHLOROTHIAZIDE or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
4. Dosage and Administration
4.1. Dosing Considerations
Therapy should be individualized according to the patient’s requirement. Use the smallest dosage necessary to achieve the required response.
4.2. Recommended Dose and Dosage Adjustment
Adult patients
- Diuresis
The recommended adult dosage is 50 mg to 100 mg once or twice a day. Many patients respond to intermittent therapy, i.e. administration on alternate days or on three to five days each week.
With an intermittent schedule, excessive response and the resulting undesirable electrolyte imbalance are less likely to occur.
- Toxemia of pregnancy
The recommended dosage is 100 mg daily or, in severe cases and for brief periods, 200 mg daily (in divided doses). Frequency of administration may range from once every four days to daily.
- Premenstrual tension with edema
The recommended dosage is 25 mg to 50 mg once or twice a day from the first appearance of symptoms until onset of the menses.
- Control of Hypertension
The usual recommended starting dosage is 50 mg or 100 mg a day as a single or divided dose. Dosage is increased or decreased according to the blood pressure response of the patient. Some patients may require doses of 200 mg a day in divided doses.
Careful observation for changes in blood pressure must be made when pms-HYDROCHLOROTHIAZIDE (hydrochlorothiazide) is used with other antihypertensive drugs, especially during initial therapy. The dosage of other agents must be reduced by at least 50%, as soon as it is added to the regimen, to prevent excessive drop in blood pressure. As the blood pressure falls under the potentiating effect of this agent, a further reduction in dosage, or discontinuation of other antihypertensive drugs may be necessary. A single daily dose as low as 12.5 mg of hydrochlorothiazide could be used in combination with another antihypertensive.
In the case of hypertension monotherapy, doses as low as a single daily dose 12.5 mg may be effective (especially in the elderly or as a starting dose), as well as a daily dose of 25 mg given in two divided doses.
Infants and Children
The usual recommended pediatric dosage is based on 1.0 mg of pms-HYDROCHLOROTHIAZIDE per pound of body weight per day in two doses. Infants under 6 months of age may require up to 1.5 mg per pound per day in two doses.
On this basis, infants up to 2 years of age may be given 12.5 mg to 37.5 mg daily in two doses. Children from 2 to 12 years of age may be given 37.5 mg to 100 mg daily in two doses. Dosage in both age groups should be based on body weight. (See 7.1.3 Pediatrics)
Drug Discontinuation
If a diagnosis of acute respiratory distress syndrome (ARDS) is suspected, pms-HYDROCHLOROTHIAZIDE should be withdrawn and the appropriate treatment given.
4.4. Administration
It is recommended that a patient’s dose of pms-HYDROCHLOROTHIAZIDE be taken at about the same time each day.
pms-HYDROCHLOROTHIAZIDE can be taken with or without food. If a patient complains that pms-HYDROCHLOROTHIAZIDE causes upset stomach, instruct them to take the tablet with food or milk.
Patients taking pms-HYDROCHLOROTHIAZIDE should be sure to include foods in their diet that contain potassium such as tomatoes, bananas, and beans.
4.5. Missed Dose
If a patient forgets to take their dose during the day, they should be instructed to omit that dose and carry on with their next scheduled dose at the usual time. Do not double dose.
5. Overdose
Symptoms
Overdosage of hydrochlorothiazide may produce diuresis accompanied with electrolyte imbalance (hypokalemia, hyponatremia and hypochloremic alkalosis) and dehydration.
The symptoms are as follows: dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, gastrointestinal disturbances, mental confusion, delirium, convulsions, shock, coma.
Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g. increased ventricular irritability).
Hydrochlorothiazide may precipitate hepatic coma in patients with cirrhosis; increase the effect of other antihypertensive agents and decrease arterial responsiveness to norepinephrine.
Treatment
No specific antidote is available.
Treatment is symptomatic and supportive. Induce emesis or perform gastric lavage. Correct dehydration, electrolyte imbalance, hepatic coma, and hypotension by established procedures. Administer oxygen or artificial respiration for respiratory impairment.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
pms-HYDROCHLOROTHIAZIDE (hydrochlorothiazide) tablets are supplied as:
12.5 mg: Round, peach colored, flat faced, bevel edged tablets debossed with a “P” logo on one side and plain on the other side. Supplied in bottles of 500 tablets.
25 mg: Round, light orange, flat faced, bevel edged tablets debossed with ″H″ over ″25″, separated by a score line on one side and plain on the other side. Supplied in bottles of 1000 tablets.
50 mg: Round, light orange, flat faced, bevel edged tablets debossed with ″H″ over ″50″, separated by a score line on one side and plain on the other side. Supplied in bottles of 100 tablets.
7. Warnings and Precautions
General
Patients on long therapy with hydrochlorothiazide are required to be on potassium rich diet. Periodic determinations of serum electrolytes to detect possible electrolyte imbalance should be performed.
The antihypertensive effects of the drug may be enhanced in the postsympathectomy patient.
Carcinogenesis and Genotoxicity
Non-melanoma skin cancer:
An increased risk of non-melanoma skin cancer (NMSC) [basal cell carcinoma (BCC) and squamous cell carcinoma (SCC) of the skin] after hydrochlorothiazide therapy was reported in some epidemiological
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| oral | Tablet 12.5 mg | Alginic acid, colloidal silicon dioxide, FD&C Yellow No. 6 Aluminum Lake, magnesium stearate, microcrystalline cellulose and sodium carboxymethylcellulose. |
| oral | Tablet 25 mg, 50 mg | Colloidal silicon dioxide, corn starch, dibasic calcium phosphate, FD&C Yellow No. 6 Lake, lactose monohydrate, magnesium stearate and pregelatinised starch. |
studies. The risk may be higher with increasing cumulative use. The certainty of the evidence was assessed by Health Canada (see 8.5 Post Market Adverse Reactions). The photosensitizing action of hydrochlorothiazide may be a possible mechanism for NMSC (see 16 Non-Clinical Toxicology, Carcinogenicity).
Patients taking hydrochlorothiazide should be informed of the potential risk of NMSC and advised to regularly check their skin for new lesions as well as changes to existing ones and promptly report any suspicious skin lesions. Patients should be advised to limit exposure to sunlight, to avoid the use of indoor tanning equipment, and to use adequate protection (e.g. a broad-spectrum sunscreen with a SPF of 30 or higher, clothing, and a hat) when exposed to minimize the risk of skin cancer.
Alternatives to hydrochlorothiazide may be considered for patients who are at a particularly high risk for NMSC (e.g., light coloured skin, known personal or family history of skin cancer, ongoing immunosuppressive therapy, etc.) (see 8.5 Post Market Adverse Reactions).
Endocrine and Metabolism
Calcium: Calcium excretion is decreased by thiazides.
Chloride: Chloride deficiency is generally mild and does not require specific treatment except under special conditions such as renal or/and hepatic disease.
Dilutional Hyponatremia: Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction rather than administration of salt except when hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Fluid and electrolyte imbalance: All patients receiving thiazide should be observed for clinical signs of fluid or electrolyte imbalance: namely hyponatremia, hypochloremic alkalosis, and hypokalemia. Serum and urine electrolyte determinations are particularly important when the patient is vomiting excessively, or receiving parenteral fluids. Warning signs of serum electrolyte imbalance, irrespective of cause are: dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, and gastrointestinal disturbances such as nausea and vomiting. Serum electrolytes may also be influenced by medication such as digitalis.
Hyperuricemia: Hyperuricemia may occur or frank gout may be precipitated in certain patients receiving thiazide therapy.
Hypokalemia: Hypokalemia may develop, especially with rapid diuresis, when severe cirrhosis is present or during concomitant use of corticosteroids or ACTH. Deficient oral electrolyte intake will also contribute to hypokalemia. Hypokalemia may sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g. increased ventricular irritability). Hypokalemia may be avoided or treated by the use of potassium supplements.
Insulin: Insulin requirements in diabetic patients may be increased, decreased, or remain unchanged. Latent diabetes mellitus may become manifest during thiazide therapy. Concomitant therapy with lithium is not recommended with diuretics because of the reduction of renal clearance of lithium and therefore an added risk of lithium toxicity.
Parathyroid gland: Pathological changes in the parathyroid gland with hypercalcemia and hypophosphatemia have been observed in a few patients on prolonged thiazide therapy. The common complications of hyperparathyroidism such as renal lithiasis, bone resorption, and peptic ulceration have not been reported. Use of thiazides should be discontinued before carrying out tests for parathyroid function.
Protein bound iodine (PBI): Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Gastrointestinal
Non-specific small bowel lesions consisting of stenosis with or without ulceration, may occur in association with the administration of enteric coated potassium salts, alone or with oral diuretics. These small bowel lesions have caused obstruction, hemorrhage and perforation. Surgery was frequently required and deaths have occurred. Available information tends to implicate enteric coated potassium salts, although lesions of this type also occur spontaneously. Such preparations should be used only when adequate dietary supplementation is not practical, and should be discontinued immediately if abdominal pain, distention, nausea, vomiting or gastrointestinal bleeding occur
Hepatic/Biliary/Pancreatic
pms-HYDROCHLOROTHIAZIDE should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance or of serum ammonia may precipitate hepatic coma.
Immune
The possibility of exacerbation or activation of systemic lupus erythematosus has been reported.
Sensitivity reactions may occur in patients with or without a history of allergy or bronchial asthma.
Ophthalmologic
Choroidal Effusion, Acute Myopia and Secondary Angle-Closure Glaucoma related to Hydrochlorothiazide: Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in choroidal effusion, acute transient myopia and/or acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity, blurred vision or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulphonamide or penicillin allergy.
Renal
In progressive renal impairment, therapy with pms-HYDROCHLOROTHIAZIDE should be withheld or discontinued.
Hydrochlorothiazide may commence or precipitate azotemia. It should be used with caution in patients with severely impaired renal function to avoid toxic or cumulative effect. If azotemia becomes more severe and oliguria occurs during treatment of patients with severe renal disease, administration of the diuretic must be stopped
Respiratory
Acute Respiratory Toxicity
Very rare severe cases of acute respiratory toxicity, including acute respiratory distress syndrome (ARDS) have been reported after taking hydrochlorothiazide. Pulmonary edema typically develops within minutes to hours after hydrochlorothiazide intake. At the onset, symptoms include dyspnea, fever, pulmonary deterioration and hypotension. Hydrochlorothiazide should not be administered to patients who previously experienced ARDS following hydrochlorothiazide intake.
Skin
Photosensitivity reactions have been reported with the use of thiazide diuretics.
If the photosensitivity reactions occur during treatment with hydrochlorothiazide-containing drugs, termination of the treatment is recommended.
7.1. Special Populations
7.1.1. Pregnant Women
Thiazides cross the placental barrier and appear in cord blood. When hydrochlorothiazide is used in pregnancy or in women of child-bearing age, the potential benefits of the drug should be weighed against the possible hazards to the fetus. These hazards include fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions which have occurred in the adult.
The routine use of diuretics in otherwise healthy pregnant women with or without mild edema is not indicated.
7.1.2. Breastfeeding
Since thiazides appear in breast milk, hydrochlorothiazide is contraindicated in nursing mothers. If use of the drug is deemed essential, the patient should stop nursing.
7.1.3. Pediatrics
There is no well controlled clinical trial in pediatric patients. Information on dosing in this age group is supported by evidence from empiric use in pediatric patients and published literature regarding the treatment of hypertension in such patients (See 4.2 Recommended Dose and Dosage and Adjustment).
7.1.4. Geriatrics
Safety and effectiveness in adults over 65 years of age have not been established.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Whenever adverse reactions are moderate or severe, thiazide dosage should be reduced or therapy withdrawn.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Cardiovascular: Orthostatic hypotension (may be aggravated by alcohol, barbiturates, or narcotics).
Central nervous system: Dizziness, vertigo, paresthesias, headache, xanthopsia.
Gastrointestinal system: Anorexia, gastric irritation, nausea, vomiting, cramps, diarrhea, constipation, jaundice (intrahepatic cholestatic jaundice), pancreatitis, sialadenitis.
Hematologic: Leukopenia, agranulocytosis, thrombocytopenia, aplastic anemia.
Hypersensitivity: Purpura, photosensitivity, rash, urticaria, necrotizing angitis (vasculitis), fever, respiratory distress including pneumonitis, anaphylactic reactions.
Other: Hyperglycemia, glycosuria, hyperuricemia, muscle spasm, weakness, restlessness, transient blurred vision.
8.5 Post-Market Adverse Reactions
Acute respiratory distress syndrome (ARDS): very rare
Eye disorders – choroidal effusion, acute myopia, acute angle-closure glaucoma: frequency unknown.
Non-melanoma skin cancer
Some pharmacoepidemiological studies have suggested a higher risk of squamous cell carcinoma (SCC) and basal cell carcinoma (BCC) of the skin with increasing use of hydrochlorothiazide. Noting substantial uncertainty, a systematic review and meta-analysis undertaken by Health Canada suggested that the use of hydrochlorothiazide for several years (>3 years) could lead to:
- 122 additional cases (95% CI, from 112 to 133 additional cases) of SCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 3 observational studies);
- 31 additional cases (95% CI, from 24 to 37 additional cases) of BCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 2 observational studies).
9. Drug Interactions
9.3. Drug-Behaviour Interactions
Alcohol may potentiate the risk of orthostatic hypotension in patients using pms-HYDROCHLOROTHIAZIDE. The interaction of pms-HYDROCHLOROTHIAZIDE with other individual behavioural risks (e.g. cigarette smoking, cannabis use) has not been studied.
9.4. Drug-Drug Interactions
Hydrochlorothiazide adds to or potentiates the action of other antihypertensive drugs. Potentiation occurs especially with ganglionic or peripheral adrenergic blocking drugs.
Table 2 – Established or Potential Drug-Drug Interactions
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
| Alcohol, barbiturates, or narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics | Monitor serum potassium level. |
| Antidiabetic agents (e.g. insulin and oral hypoglycemic agents) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
| Antihypertensive drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, beta- blockers, vasodilators, calcium channel blockers, ACEI, ARB, and direct renin inhibitors). | |
| Antineoplastic drugs, including cyclophosphami de and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Bile acid sequestrants, e.g. cholestyramine | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothaizide by 30-35%. | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of thiazide, if necessary. |
| Calcium and vitamin D supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Corticosteroids, and adrenocorticotropic hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia, may occur. | Monitor serum potassium, and adjust medications, as required. |
| Digoxin | CT | Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin levels closely. Supplement potassium or adjust doses of digoxin or thiazide, as required. Dose adjustment of thiazide may be required. |
| Drugs that alter GI motility, i.e., anti- cholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dosage adjustment of thiazides may be required |
| Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RC | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co-administration of hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Dosage adjustment of gout medications may be required. |
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high risk of lithium toxicity. | Concomitant use of thiazide diuretics with lithium is generally not recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor lithium levels closely. |
| Nonsteroidal anti-inflammatory drugs (NSAID) | CT | NSAID-related retention of sodium and water antagonises the diuretic and antihypertensive effects of thiazides. NSAID-induced inhibition of renal prostaglandins leading to decreases of renal blood flow, along with thiazide-induced decreases in GFR may lead to acute renal failure. Patients with heart failure may be at particular risk. | If combination use is necessary, monitor renal function, serum potassium, and blood pressure closely. Dose adjustments may be required. |
| Norepinephrine | C | Thiazides may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use. | |
| Selective serotonin reuptake inhibitors (SSRIs, e.g. citalopram, escitalopram, sertraline) | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Skeletal muscle relaxants of the curare family, e.g., tubocurare | C | Thiazide drugs may increase the responsiveness of some skeletal muscle relaxants, such as curare derivatives | |
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. |
Legend: C = Case Study; CT = Clinical Trial; RC = Retrospective Cohort Study T = Theoretical
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Hydrochlorothiazide is a diuretic and an antihypertensive agent. The exact mechanism of the antihypertensive effect is unknown. Hydrochlorothiazide has no effect on normal blood pressure.
Diuresis is effected by inhibition of renal tubular reabsorption of electrolytes and an accompanying volume of water.
10.2. Pharmacodynamics
Hydrochlorothiazide increases the excretion of sodium and chloride in approximately equivalent amounts and causes a simultaneous, usually minimal loss of bicarbonate. The excretion of ammonia is reduced slightly as a consequence of which concentrations of ammonia in the blood may be increased. Hydrochlorothiazide slightly increases the excretion of potassium. Calcium excretion is decreased and magnesium excretion is increased.
10.3. Pharmacokinetics
Absorption
Hydrochlorothiazide is rapidly absorbed from the gastrointestinal tract. Onset of action after oral administration occurs in 2 hours and the peak effect at approximately 4 hours. Duration of action persists for approximately 6 to 12 hours.
Distribution
The drug is distributed throughout the extracellular space and does not accumulate in tissues other than the kidney. It passes readily through the placental barrier to the fetus.
Metabolism
Hydrochlorothiazide does not undergo significant metabolism.
Elimination
Hydrochlorothiazide is mainly excreted unchanged in the urine.
- 11. Storage, Stability, and Disposal
pms-HYDROCHLOROTHIAZIDE (hydrochlorothiazide) tablets should be stored between 15°C and 30°C away from heat and light.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Hydrochlorothiazide
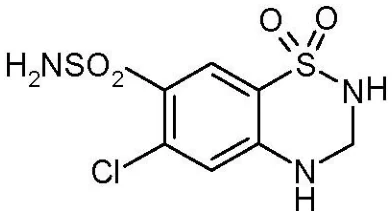
Chemical name: 6-chloro-3,4-dihydro-2H-1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide
Molecular formula and molecular mass: C7H8ClN304S2; 297.72 g/mol
Structural formula:
Physicochemical properties:
Description: Hydrochlorothiazide is a white or almost white odourless, crystalline powder with a slightly bitter taste.
Solubility: It is almost insoluble in water, benzene, chloroform, ether and dilute mineral acids, and soluble 1 in 500 of alcohol and 1 in 50 of acetone. It is freely soluble in dimethyl formamide, n-butylamine and solutions of alkali hydroxides.
Pharmaceutical standard: USP
14. Clinical Trials
1.2. 14.1. Clinical Trials by Indication
No clinical trials information is available.
1.3. 14.2. Comparative Bioavailability Studies
A double blind, balanced, randomized, two-treatment, two-period, two-sequence, single oral dose, crossover, bioequivalence study comparing pms-HYDROCHLOROTHIAZIDE 50 mg tablets (Pharmascience Inc.) to NOVO-HYDRAZIDE 50 mg tablets (Novopharm Ltd.) was conducted in 23 normal, healthy, adult, male subjects under fasting conditions.
Table 3 – Summary Table of the Comparative Bioavailability Data
Hydrochlorothiazide (1 × 50 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h / mL) | 2897.70 2950.83 (20.70) | 2793.70 2838.11 (18.40) | 103.7 | 99.5 - 108.2 |
AUCI (ng.h / mL) | 2969.20 3024.39 (20.90) | 2860.20 2906.61 (18.60) | 103.8 | 99.6 - 108.2 |
| Cmax (ng / mL) | 434.40 456.00 (34.80) | 386.60 397.55 (23.90) | 112.4 | 104.4 - 120.9 |
| Tmax 3 (h) | 2.00 (1.00 -3.68) | 2.33 (1.00 – 5.00) | ||
| T½4 (h) | 9.72 (11.4) | 9.60 (8.1) | ||
1 pms-HYDROCHLOROTHIAZIDE 50 mg tablets (Pharmascience Inc.).
2 NOVO-HYDRAZIDE 50 mg tablets (Novopharm Ltd.)
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV %) only.
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General toxicology
Acute Toxicity
Table 4 – Acute Toxicology Data for Various Animals
| Species | Route | LD50 (mg/kg) |
|---|---|---|
| Mouse | Oral | 10,000* |
| Mouse | I.V. | 884 |
| Rat | Oral | 10,000* |
| Rat | I.P. | 3,130* |
| Rabbit | I.V. | 461 |
| Dog | I.V. | 1,000 |
Dogs tolerated at least 2,000 mg/kg orally without signs of toxicity.
*Hydrocholorothiazide was administered as a suspension.
Subacute Toxicity
Rat
Hydrochlorothiazide administered to rats, orally as a suspension at doses of 500, 1,000 and 2,000 mg/kg/day, 5 days/week, for 3 weeks did not produce any toxic symptoms. Three of the ten rats which received 2,000 mg/kg/day of sodium hydrochlorothiazide salt died after the 5th day of treatment. The mortality was attributed to pneumonia.
Dog
Hydrochlorothiazide administered to dogs, orally at doses of 250, 500 and 1,000 mg/kg, 7 days/week for 8 weeks did not produce any observable adverse effects or gross signs of drug toxicity except for electrolytic imbalance.
Chronic Toxicity
Rat and Dog
The results of 6-month chronic oral toxicity on hydrochlorothiazide in rats and dogs indicated no toxicity attributable to the drug administered to rats at doses of up to 2 grams/kg/day and to dogs at doses of up to 250 mg/kg/day. On gross examination the following changes were observed in the dog: slight depression of plasma potassium; small amounts of yellow crystalline precipitate in the bladder in two of twelve dogs tested. Histomorphologic studies did not show any drug related changes.
Genotoxicity
The mutagenic potential was assessed in a series of in vitro and in vivo test systems. While some positive results were obtained in vitro, all in vivo studies provided negative results. Hydrochlorothiazide enhanced the UVA-induced formation of pyrimidine dimers in vitro and in the skin of mice following oral treatment. It is therefore concluded that although there is no relevant mutagenic potential in vivo, hydrochlorothiazide could enhance the genotoxic effects of UVA light. This mechanism of photosensitization could be associated with a higher risk for non-melanoma skin cancer.
Carcinogenicity
According to the experimental data available, hydrochlorothiazide revealed mitigated evidence of carcinogenic activity in rats and mice, with conflicting evidence of hepatic adenoma in male mice at the highest dose and adrenal pheocytochroma in one rat study but not in another. Current evidence is inadequate to draw a clear conclusion for a carcinogenic effect of hydrochlorothiazide in animals.