


Product Monograph - PMS-Vancomycin
RECENT MAJOR LABEL CHANGES
| N/A |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics ............................................................................................................... 4
1.2 Geriatrics ............................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................ 5
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 5
4.4 Administration ....................................................................................................... 5
4.5 Missed Dose .......................................................................................................... 5
5 OVERDOSAGE ............................................................................................................. 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 6
7 WARNINGS AND PRECAUTIONS ................................................................................. 7
7.1 Special Populations ................................................................................................ 8
7.1.1 Pregnant Women .................................................................................................. 8
7.1.2 Breast-feeding ....................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................... 9
7.1.4 Geriatrics ............................................................................................................... 9
8 ADVERSE REACTIONS ................................................................................................. 9
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 9
9 DRUG INTERACTIONS ............................................................................................... 10
9.4 Drug-Drug Interactions ........................................................................................ 10
9.5 Drug-Food Interactions ........................................................................................ 11
9.6 Drug-Herb Interactions ........................................................................................ 11
9.7 Drug-Laboratory Test Interactions ....................................................................... 11
10 CLINICAL PHARMACOLOGY ...................................................................................... 11
10.1 Mechanism of Action ........................................................................................... 11
10.3 Pharmacokinetics ................................................................................................ 12
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 12
PART II: SCIENTIFIC INFORMATION ...................................................................................... 13
13 PHARMACEUTICAL INFORMATION ........................................................................... 13
15 MICROBIOLOGY ....................................................................................................... 14
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 16
17 SUPPORTING PRODUCT MONOGRAPHS ................................................................... 17
PATIENT MEDICATION INFORMATION ................................................................................. 18
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
pms-VANCOMYCIN (vancomycin hydrochloride capsules) is indicated for:
The treatment of infections caused by susceptible strains of the designated microorganisms in the following diseases and specific conditions:
- staphylococcal enterocolitis, and
- antibiotic associated pseudomembranous colitis produced by Clostridium difficile
Parenteral administration of vancomycin is not effective for the indicated conditions; therefore pms-VANCOMYCIN must be given orally.
pms-VANCOMYCIN is not effective by the oral route for the treatment of other types of infection.
1.1 Pediatrics
Pediatrics (premature neonates and young infants): Evidence from clinical studies and experience suggests that use in premature neonates and young infants are associated with differences in safety and a brief discussion can be found in the 7 WARNINGS AND PRECAUTIONS section.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of pms-VANCOMYCIN and other antibacterial drugs, pms-VANCOMYCIN should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy. Because some strains are resistant to vancomycin, when applicable, appropriate specimens should be obtained before antibacterial treatment, to determine the causative organism(s) and susceptibility to vancomycin.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety and a brief discussion can be found in the 7 WARNINGS AND PRECAUTIONS section.
2 CONTRAINDICATIONS
- pms-VANCOMYCIN is contraindicated for patients who are hypersensitive to vancomycin hydrochloride or to any ingredient in the formulation or component of the container. For a complete listing, see the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- If parenteral and oral vancomycin are administered concomitantly an additive effect can occur. This should be taken into consideration when calculating the total dose. In this situation serum levels of the antibiotic should be monitored.
- pms-VANCOMYCIN capsules are formulated in a matrix gel that prevents administration by a nasogastric tube; if this route of administration is being considered, the IV dosage form should be used.
4.2 Recommended Dose and Dosage Adjustment
Adults:
The usual daily dosage for antibiotic-associated pseudomembranous colitis produced by C.difficile and staphylococcal entercolitis is 125 to 500 mg administered orally every 6 to 8 hours for 7 to 10 days.
Pediatrics:
The usual daily dosage is approximately 40mg/kg in 3 or 4 divided doses for 7 to 10 days administered orally. The total daily dosage should not exceed 2 g.
4.4 Administration
Oral administration.
4.5 Missed Dose
If a dose of this medication has been missed, it should be taken as soon as possible. However, if it is almost time for the next dose, skip the missed dose and resume the regular dosing schedule. Do not double doses.
5 OVERDOSAGE
Activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended.
Other than general supportive treatment, no specific antidote is known. Dialysis does not remove significant amounts of vancomycin. Hemofiltration and hemoperfusion with polysulfone resin have been reported to result in increased vancomycin clearance.
In managing overdosage, consider the possibility of multiple drug overdoses, interaction among drugs, and unusual drug kinetics in the patient.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Capsule 125 mg, 250 mg (as vancomycin HCl) | Polyethylene glycol 6000. Capsule shell contains titanium dioxide, iron oxide black, iron oxide yellow, iron oxide red, gelatin, and water. The 250 mg capsules also contain sodium lauryl sulfate. The markings on the capsules are in white ink, which contains shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, strong ammonia solution, titanium dioxide, potassium hydroxide, and purified water. |
pms-VANCOMYCIN capsules contain vancomycin hydrochloride, equivalent to 125 mg vancomycin and 250 mg vancomycin.
pms-VANCOMYCIN is supplied as hard gelatin capsules for oral administration:
pms-VANCOMYCIN 125 mg is a white to off white congealed liquid mixture as solid mass in size “2” grey cap and pink body.
pms-VANCOMYCIN 250 mg is a white to off white congealed liquid mixture as solid mass in size “0” brown cap and brown body.
pms-VANCOMYCIN 125 mg and 250 mg capsules are available in blister packs of 20 capsules.
7 WARNINGS AND PRECAUTIONS
General
Vancomycin is poorly absorbed orally. Toxic serum levels are therefore not expected from oral dosage. Clinically significant serum concentrations have been reported in some patients who have taken multiple oral doses of vancomycin for active C. difficile-induced pseudomembranous colitis; therefore, monitoring of serum concentrations may be appropriate in these patients.
When given intravenously, toxic serum levels can occur. During parenteral therapy, the risk of toxicity appears appreciably increased by high blood concentrations or prolonged treatment.
Driving and Operating Machinery
Ringing in your ears and dizziness have been reported and this may affect your ability to drive and use machines.
Ear/Nose/Throat
Ototoxicity has occurred when serum levels exceeded 80µg/mL. Deafness may be preceded by tinnitus. Deafness may be transient or permanent. The elderly are more susceptible to auditory damage. Deafness may be progressive despite cessation of treatment.
pms-VANCOMYCIN should be avoided (if possible) in patients with previous hearing loss. If it is used in such patients, the dose of pms-VANCOMYCIN should be regulated by periodic determination of drug levels in the blood. Patients with renal insufficiency and individuals over the age of 60 should be given serial tests of auditory function and of vancomycin blood levels.
Gastrointestinal
Some patients with inflammatory disorders of the intestinal mucosa may have significant systemic absorption of oral vancomycin and, therefore, may be at risk for the development of adverse reactions associated with the parenteral administration of vancomycin. The risk is greater if renal impairment is present.
Hematologic
Neutropenia can occur starting one week or more after onset of therapy with pms-VANCOMYCIN or after a total dose of more than 25 g. Neutropenia appears to be promptly reversible when treatment is discontinued.
Monitoring and Laboratory Tests
All patients receiving the drug should have periodic hematologic studies, urinalyses, and liver and renal function tests.
Renal
Because of its ototoxicity and nephrotoxicity, pms-VANCOMYCIN should be used with care in patients with renal insufficiency. Vancomycin is excreted fairly rapidly by the kidney and blood levels increase markedly with decreased renal clearance. There is an increased risk of renal failure in patients receiving large doses of pms-VANCOMYCIN.
In patients with underlying renal dysfunction or those receiving concomitant therapy with an aminoglycoside there is a risk of developing interstitial nephritis. When these patients are being treated with pms-VANCOMYCIN, serial monitoring of renal function should be performed.
Sensitivity/Resistance
Development of Drug Resistant Bacteria
The prolonged use of pms-VANCOMYCIN may result in overgrowth of non-susceptible organisms. If new infections due to bacteria or fungi appear during therapy with this product, appropriate measures should be taken, including withdrawal of pms-VANCOMYCIN.
In vitro resistance to vancomycin has been reported among some entercoccal and staphylococcal isolates.
Vancomycin is not effective in vitro against gram-negative bacilli, mycobacteria, or fungi.
Prescribing pms-VANCOMYCIN in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria
7.1 Special Populations
7.1.1 Pregnant Women
pms-VANCOMYCIN should be given to pregnant woman only if clearly needed. In a controlled study, vancomycin hydrochloride capsules were administered to 10 pregnant women for serious staphylococcal infections complicating intravenous drug abuse to evaluate potential ototoxic and nephrotoxic effects on the infant. Vancomycin levels of 13.2 and 16.6µg/mL were measured in core blood in two patients. No sensorineural hearing loss or nephrotoxicity attributable to vancomycin hydrochloride capsules was noted. One infant whose mother received vancomycin hydrochloride capsules in the third trimester experienced conductive hearing loss that was not attributed to the administration of vancomycin hydrochloride capsules. Because the number of patients treated in this study was limited and vancomycin hydrochloride capsules were administered only in the second and third trimesters, it is not known whether vancomycin hydrochloride capsules cause fetal harm.
7.1.2 Breast-feeding
Vancomycin is excreted in human milk. Caution should be exercised if pms-VANCOMYCIN is administered to a nursing woman. Because of the potential for adverse events, a decision should be made whether to discontinue nursing or discontinue administration of the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (premature neonates and young infants)
It may be appropriate to confirm desired vancomycin serum concentrations. Concomitant administration of vancomycin and anesthetic agents has been associated with erythema and histamine-like flushing in children.
7.1.4 Geriatrics
The natural decrease of glomerular filtration with increasing age may lead to elevated vancomycin serum concentrations if dosage is not adjusted. Vancomycin dosage schedules should be adjusted in elderly patients. It should be noted that the total systemic and renal clearances of vancomycin are reduced in the elderly. The elderly are more susceptible to auditory damage.
8 ADVERSE REACTIONS
8.3 Less Common Clinical Trial Adverse Reactions
Renal:
Nephrotoxicity
Rarely, renal failure, principally manifested by increased serum creatinine or blood urea nitrogen (BUN) concentrations, especially in patients given large doses of vancomycin hydrochloride capsules, has been reported. Rare cases of interstitial nephritis have been reported. Most of these have occurred in patients who were given aminoglycosides concomitantly or who had pre-existing kidney dysfunction. When vancomycin hydrochloride capsules were discontinued, azotemia resolved in most patients.
Ear/Nose/Throat:
Ototoxicity
A few dozen cases of hearing loss associated with vancomycin hydrochloride capsules have been reported. Most of these patients had kidney dysfunction, pre-existing hearing loss, or concomitant treatment with an ototoxic drug. Vertigo, dizziness, and tinnitus have been reported rarely.
Immune:
Hematopoietic
Reversible neutropenia, usually starting one week or more after onset of therapy with vancomycin hydrochloride capsules or after a total dose of more than 25 g, has been reported in several dozen patients. Neutropenia appears to be promptly reversible when vancomycin hydrochloride capsules are discontinued. Thrombocytopenia has rarely been reported. Although a causal relationship has not been established, reversible agranulocytosis (granulocyte count less than 500/mm3) has been reported rarely. Eosinophilia has been associated with the administration of vancomycin hydrochloride capsules.
Drug Reaction with Eosinophilia and Systemic Symptoms Syndrome (DRESS)
Toxic Epidermal Necrolysis (TEN)
Miscellaneous:
Anaphylaxis, drug fever, nausea, chills, hypotension, wheezing, dyspnea, urticaria, pruritus flushing of the upper body (“red neck”), pain and muscle spasm of the chest and back, rashes, including exfoliative dermatitis, Stevens-Johnson syndrome, linear IgA bullous dermatosis and rare cases of vasculitis have been associated with the administration of vancomycin hydrochloride capsules.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
Table 2: Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Anesthetic agents | C | Concomitant administration of vancomycin and anesthetic agents has been associated with erythema and histamine-like flushing in children. | Caution is warranted. |
| Antibiotics such as aminoglyuoside antibiotics, polymixin B, colistin, viomycin | T | Caution is warranted and therapeutic concentration monitoring is recommended | |
|---|---|---|---|
| Cysplatin | T | Caution is warranted and therapeutic concentration monitoring is recommended | |
| Nephrotoxic agents, particularly ethacrynic acid | T | Caution is warranted and therapeutic concentration monitoring is recommended | |
| Neuromuscular blocking agents | T | Caution is warranted and therapeutic concentration monitoring is recommended | |
| Neurotoxic agents | T | Caution is warranted and therapeutic concentration monitoring is recommended |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions studies between vancomycin hydrochloride capsules and food have not been conducted.
9.6 Drug-Herb Interactions
Interactions studies between vancomycin hydrochloride capsules and herbs have not been conducted.
9.7 Drug-Laboratory Test Interactions
Interactions studies between vancomycin hydrochloride capsules and laboratory tests have not been conducted.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
In vitro studies indicate that the bactericidal action of vancomycin hydrochloride against many gram- positive bacteria results from the inhibition of cell-wall synthesis. There is also evidence that vancomycin alters the permeability of the cell membrane and selectively inhibits RNA synthesis.
10.3 Pharmacokinetics
Absorption
Oral Administration:
Vancomycin is poorly absorbed after oral administration, only trace amounts being found in blood or urine. Following 125 mg orally 4 times daily, the mean concentration of vancomycin in stools was approximately 350µg/g. Following up to ten daily oral doses of 2 g, a mean level of 3100 µg/g with a range of 905 – 8760 µg/g was detected in feces of patients with pseudomembranous colitis.
Distribution:
Tissue Penetration and Distribution:
Central Nervous System:
Vancomycin does not readily diffuse across normal meninges into the spinal fluid; but when the meninges are inflamed, penetration into the spinal fluid occurs.
Other Tissues and Fluids:
Vancomycin concentration in human pericardial, pleural, bile, ascetic and synovial fluids reaches approximately one third of the equivalent serum level after single intravenous doses. A level of 7.6µg/mL was achieved in the brain cyst of one infant following intravenous infusion of 40 mg/kg daily for 4 days.
Special Populations and Conditions
Renal Insufficiency:
Adults
Infusions of 1 g vancomycin in 250mL D5-W were given over 30 minutes to 29 anephric patients. After 18 days with intermittent dialysis at three-day intervals, the serum concentration was still 3.5µg/mL. The elimination half-life was about 7.5 days.
11 STORAGE, STABILITY AND DISPOSAL
Store pms-VANCOMYCIN capsules at room temperature (15° to 25°C). Protect from moisture.
Keep out of sight and reach of children.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Vancomycin hydrochloride
Chemical name: (Sa)-(3S,6R,7R,22R,23S,26S,36R,38aR)-44-[[2-0-(3-Amino-2,3,6-trideoxy-3-C-methyl-α- L-lyxo-hexopyranosyl)-β-D-glucopyrano-syl]oxy]-3-(carbamoylmethyl)-10,19- dichloro-2,3,4,5,6,7,23,24,25,26,36,37,38,38a-tetradecahydro-7,22,28,30,32- pentahydroxy-6-[(2R)-4-methyl-2-(methylamino)valeramido]-2,5,24,38,39- pentaoxo-22H-8,11:18,21-dietheno-23,36-(iminomethano)-13,16:31,35-dimetheno- 1H,16H-[1,6,9]oxadiazacyclohexadecino[4,5-m][10,2,16]-benzoxadiazacyclo- tetracosine-26,carboxylic acid, monohydrochloride
Molecular formula : C66H75Cl2N9O24 ·HCl
Molecular mass: 1485.68 g/mol
Structural formula:
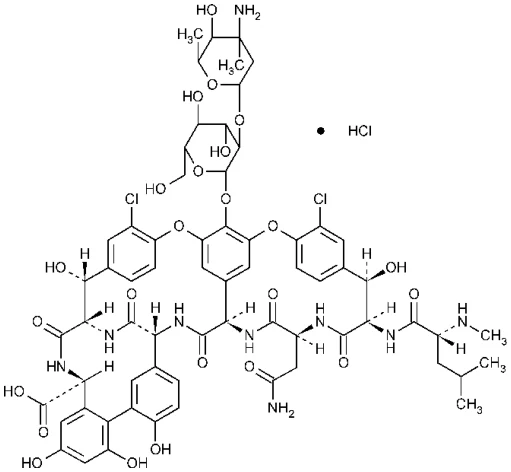
Physicochemical properties: Vancomycin hydrochloride is a chromatographically purified tricyclic glycopeptide antibiotic derived from Amycolatopsis orientalis (formerly Nocardia orientalis). It is an off-white free flowing powder, having essentially no odour. It is soluble in water and insoluble in organic solvents.
15 MICROBIOLOGY
Cross-resistance has not been demonstrated between vancomycin hydrochloride capsules and other classes of antibiotics. Laboratory-induced resistance has been reported to occur in a slow stepwise fashion. Its activity is not significantly altered by changes in pH or by the presence of serum.
Vancomycin is active against most strains of the following organisms in vitro and in clinical infections as described in the section 1 INDICATIONS:
- Staphylococcus aureus (including heterogeneous methicillin-resistant strains)
- Clostridium difficile
Vancomycin is active against most strains of the following organisms in vitro. However, the safety and effectiveness of vancomycin hydrochloride capsules in treating clinical infections due to these organisms have not been established in adequate and well-controlled trials.
- Staphylococcus epidermidis (including heterogeneous methicillin-resistant strains)
- Streptococcus pneumoniae (including multiple-resistant strains)
- Streptococcus pyogenes (group A beta-hemolytic)
- Streptococcus agalactiae (group B beta-hemolytic)
- Streptococcus bovis
- Alpha-hemolytic streptococci (viridans groups)
- Enterococci (e.g. E. faecalis)
- Bacillus sp.
- Listeria monocytogenes
- Lactobacillus sp.
- Neisseria sp.
- Diptheroids
- Actinomyces sp.
Note:
Many strains of streptococci, staphylococci, C. difficile, and other gram-positive bacteria are susceptible in vitro to concentrations of 0.5 to 5 µg/mL. Staphylococci are generally susceptible to less than 5 µg/mL of vancomycin hydrochloride, but a small proportion of S. Aureus strains require 10 to 20 µg/mL for inhibition.
In vitro resistance to vancomycin has been reported among some enterococcal and staphylococcal isolates.
Vancomycin is not effective in vitro against gram-negative bacilli, mycobacteria, or fungi.
Table 3: In Vitro Activity of Vancomycin
| Organism | No. of Strains | MIC* (µg/mL) Range | Median |
|---|---|---|---|
| Staphylococcus aureus | 55 | 1.0 – 2.0 | 1.0 |
| 101 | 0.78 – 12.5 | 3.1 | |
| 35 | 0.25 – 1.0 | 1.0 | |
| Staphylococcus aureus | 22 | 0.5 – 4.0 | 0.5 |
| (methicillin-resistant) | 38 | 0.3 – 12.0 | 1.5 |
| 12 | 0.2 – 3.12 | 0.4 | |
| Streptococcus epidermidis | 177 | 1.56 – 6.25 | 3.1 |
| 35 | 0.4 – 3.1 | 1.6 | |
| 27 | 0.2 – 6.25 | 3.12 | |
| Streptococcus pneumonia | 70 | 0.125 – 0.5 | 0.25 |
| Streptococcus pyogenes | 12 | 0.8 – 3.1 | 1.6 |
| Streptococcus viridans | 82 | 0.39 – 1.56 | 0.78 |
| Streptococcus group D enterococci | 382 | 0.8 - >100.0 | 3.1 |
| Clostridium perfringens | 43 | 0.4 – 1.6 | 0.8 |
| Clostridium ramosum | 49 | 3.1 – 12.5 | 6.2 |
| Clostridium difficile | 14 | <1.0 | <1.0 |
| 78 | 1.0 – 4.0 |
*Minimum Inhibitory Concentration (MIC)
Methods of Susceptibility Testing:
When the standardized method of disc susceptibility testing is used, a 30µg disc of vancomycin should produce a zone of more than 11 mm when in contact with “susceptible” organisms. A zone size of 10 – 11 mm indicates intermediate susceptibility, while a zone size of 9 mm or less indicates resistance.
With the WHO-ICS agar dilution and broth dilution methods, and MIC of <5 µg/mL indicates susceptibility to vancomycin.
Assay Methods:
Vancomycin serum and tissue levels may be determined by Bennett’s agar-well diffusion method. This test can quantitatively measure vancomycin concentrations from 0.5 to
0.8 µg/mL.
Two disc-diffusion assay methods are available for vancomycin. Both use Bacillus subtilis as the test organism. The first method, which uses antibiotic medium No. 5, is capable of measuring vancomycin levels from approximately 5 to 40 µg/mL. The second uses minimal salt agar and is capable of detecting vancomycin concentrations from about 0.8 to 25 µg/mL. A modification of this assay permits reliable bioassay for vancomycin (in concentrations of 0.78 to 50.0 µg/mL) in the presence of rifampin or aminoglycosides. Two commercially prepared assay methods are now available and include a radioimmunoassay and an automated fluorescence polarization immunoassay.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity:
Vancomycin was administered to mice, rats and dogs by various routes.
Table 4: LD50 ± SE (mg/kg) Following Vancomycin Administration
| Route of Administration | Rat | Mouse | Dog |
|---|---|---|---|
| Intravenous | 319 ± 14 | 489 ± 41 | 292 ± 29 |
| Intraperitoneal | 2218 ± 240 | 1734 ± 227 | |
| Subcutaneous | > 5000 | ||
| Oral | > 5000 |
Rats died quickly from CNS-mediated effects, while dogs died, generally from kidney failure, several days after the intravenous administration.
Vancomycin, when administered intravenously in a 5 percent solution to dogs at a rate of 0.6 mL/minute, caused a slight dose-related drop in blood pressure. When the same dogs were given the same doses at a rate of 15 mL/minute, blood pressure dropped dramatically, as much as 40 percent. Whether the response is due to a direct effect on histamine receptors or to release of histamine, possibly from mast cells, is not known.
Subchronic Toxicity:
Dogs were given daily I.V. doses of vancomycin at 12.5 mg and 50 mg/kg for 21 – 311 days. Renal damage was seen in 4/22 dogs receiving 50 mg/kg/day.
Monkeys tolerated I.V. doses of 25 and 50 mg/kg/day for 16 – 187 days, with irritation at the injection site as the only toxic effect.
Cats received I.V. doses of 25 and 50 mg/kg/day for three months with no systemic toxicity. Anaphylaxis could not be induced in 9 guinea pigs that received 100 mg vancomycin subcutaneously when challenged by a 25 mg I.V. dose, 25 days later.
Intraperitoneal doses of 150 mg vancomycin or 60 mg tobramycin given subcutaneously to rats, resulted in no nephrotoxicity; however, when administered together, significant renal toxicity occurred.
Vancomycin 1000 mg/kg administered subcutaneously concurrently with ethacrynic acid 40 mg/kg intravenously did not product ototoxicity in a guinea pig model.
Neuromuscular blocking has not been demonstrated in vancomycin-treated rabbits.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. VANCOCIN® Vancomycin hydrochloride capsules, 125 mg and 250 mg, submission control 278879, Product Monograph, Searchlight Pharma Inc. FEB 14, 2024