


Product Monograph - Pro-Diclofenac
RECENT MAJOR LABEL CHANGES
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX- Risk in Pregnancy | 04/2023 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, Pregnancy | 04/2023 |
| 7 WARNINGS AND PRECAUTIONS, Skin, Serious skin reactions | 04/2023 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women | 04/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ................................................................................. 2
TABLE OF CONTENTS ................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................... 4
1 INDICATIONS .................................................................................................... 4
1.1 Pediatrics ......................................................................................................... 4
1.2 Geriatrics ........................................................................................................... 4
2 CONTRAINDICATIONS ....................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................... 6
4 DOSAGE AND ADMINISTRATION ....................................................................... 7
4.1 Dosing Considerations ...................................................................................... 7
4.2 Recommended Dose and Dosage Adjustment ................................................. 7
4.4 Administration .................................................................................................. 8
4.5 Missed Dose ...................................................................................................... 8
5 OVERDOSAGE ................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................ 9
7 WARNINGS AND PRECAUTIONS ........................................................................ 9
7.1 Special Populations ......................................................................................... 19
7.1.1 Pregnant Women ............................................................................................ 19
7.1.2 Breast-feeding ................................................................................................ 20
7.1.3 Pediatrics ........................................................................................................ 20
7.1.4 Geriatrics ......................................................................................................... 20
8 ADVERSE REACTIONS ...................................................................................... 20
8.1 Adverse Reaction Overview ............................................................................ 20
8.2 Clinical Trial Adverse Reactions ...................................................................... 22
8.5 Post-Market Adverse Reactions ..................................................................... 22
9 DRUG INTERACTIONS ...................................................................................... 23
9.2 Drug Interactions Overview ............................................................................ 23
9.4 Drug-Drug Interactions ................................................................................... 23
9.5 Drug-Food Interactions ................................................................................... 28
9.6 Drug-Herb Interactions ................................................................................... 28
9.7 Drug Laboratory Test Interactions.................................................................. 29
10 CLINICAL PHARMACOLOGY .......................................................................... 29
10.1 Mechanism of Action ...................................................................................... 29
10.2 Pharmacodynamics......................................................................................... 29
10.3 Pharmacokinetics ........................................................................................... 29
11 STORAGE, STABILITY AND DISPOSAL ............................................................ 31
12 SPECIAL HANDLING INSTRUCTIONS.............................................................. 31
PART II: SCIENTIFIC INFORMATION ............................................................................ 32
13 PHARMACEUTICAL INFORMATION .............................................................. 32
14 CLINICAL TRIALS .......................................................................................... 32
14.1 Clinical Trials by Indication ............................................................................. 32
14.2 Study Results .................................................................................................. 32
14.3 Comparative Bioavailability Studies ............................................................... 33
15 MICROBIOLOGY .......................................................................................... 34
16 NON-CLINICAL TOXICOLOGY ........................................................................ 34
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................... 38
PATIENT MEDICATION INFORMATION ....................................................................... 39
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
PRO-DICLOFENAC (diclofenac sodium delayed-release tablets) is indicated for:
- the symptomatic treatment of rheumatoid arthritis and osteoarthritis, including degenerative joint disease of the hip.
Throughout this document, the term Nonsteroidal Anti-Inflammatory Drug (NSAID) refers to both non-selective NSAIDs and selective COX-2 inhibitor NSAIDs, unless otherwise indicated.
PRO-DICLOFENAC, particularly at higher doses, is associated with an increased risk of serious cardiovascular related adverse events that is comparable to COX-2 inhibitors. For patients with pre-existing risk factors for cardiovascular disease (including ischemic heart disease, cerebrovascular disease and/or congestive heart failure NYHA II-IV) other management strategies that do not include NSAlDs, particularly COX-2 inhibitors and diclofenac, should be considered first (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
For patients with increased risk of developing GI adverse events other management strategies that do not include NSAIDs should be considered first (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
Use of PRO-DICLOFENAC should be limited to the lowest effective dose for the shortest possible duration of treatment in order to minimize the potential risk for cardiovascular or gastrointestinal adverse events (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
PRO-DICLOFENAC, as NSAIDs, do NOT treat clinical disease or prevent its progression.
PRO-DICLOFENAC, as NSAIDs, only relieves symptoms and decreases inflammation for as long as the patient continues to take them.
1.1 Pediatrics
Pediatrics (< 16 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. (see 2 CONTRAINDICATIONS).
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and post-market experience suggests that use in the geriatric population is associated with differences in safety (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
PRO-DICLOFENAC is contraindicated in:
- the peri-operative setting of coronary artery bypass graft surgery (CABG). Although PRO-DICLOFENAC has NOT been studied in this patient population, a selective COX-2 inhibitor NSAID studied in such a setting has led to an increased incidence of cardiovascular/thromboembolic events, deep surgical infections and sternal wound complications.
- the third trimester of pregnancy, because of risks of premature closure of the ductus arteriosus, and prolonged parturition.
- women who are breastfeeding, because of the potential for serious adverse reactions in nursing infants.
- severe uncontrolled heart failure.
- patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- history of asthma, urticaria, or allergic-type reactions after taking ASA or other NSAIDs (i.e. complete or partial syndrome of ASA-intolerance - rhinosinusitis, urticaria/angioedema, nasal polyps, asthma). Fatal anaphylactoid reactions have occurred in such individuals. Individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse reaction. The potential for cross-reactivity between different NSAIDs must be kept in mind (see 7 WARNINGS AND PRECAUTIONS —Sensitivity/Resistance - Anaphylactoid Reactions).
- active gastric/duodenal/peptic ulcer, active GI bleeding or perforation, regional ulcer, gastritis or ulcerative colitis (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS).
- cerebrovascular bleeding or other bleeding disorders.
- inflammatory bowel disease.
- severe hepatic impairment or active liver disease.
- severe renal impairment (creatinine clearance <30 mL/min or 0.5 mL/sec) or deteriorating renal disease (individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs and must be monitored) (see 7 WARNINGS AND PRECAUTIONS - Renal).
- known hyperkalemia (see 7 WARNINGS AND PRECAUTIONS - Renal - Fluid and Electrolyte Balance).
- children and adolescents less than 16 years of age.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Risk of Cardiovascular (CV) Adverse Events: Cardiovascular Disease (including ischemic heart disease, Cerebrovascular Disease, Congestive Heart Failure (NYHA II-IV)): Diclofenac is associated with an increased risk of cardiovascular adverse events (such as myocardial infarction, stroke or thrombotic events, which can be fatal) that is comparable to COX-2 inhibitors. Meta-analyses of randomized clinical trials comparing several different NSAIDs suggest that diclofenac, particularly at higher doses, is associated with an increased risk of cardiovascular adverse events that is comparable to COX-2 inhibitors. Large population-based observational studies conducted in the general population also support these findings. The risk may increase with the dose and duration of use. Patients with cardiovascular disease or risk factors for cardiovascular disease may be at greater risk. For patients with a high risk of developing an adverse CV event, other management strategies that do NOT include NSAIDs, particularly COX-2 inhibitors and diclofenac, should be considered first. To minimize the potential risk for an adverse CV event, the lowest effective dose should be used for the shortest possible duration. Treatment with PRO-DICLOFENAC is not recommended in patients with pre-existing cardiovascular disease (congestive heart failure NYHA II-IV, ischemic heart disease, peripheral arterial disease) cerebrovascular disease, uncontrolled hypertension or patients with risk factors for cardiovascular disease (e.g. hypertension, hyperlipidemia, diabetes mellitus and smoking). These patients should be treated with PRO-DICLOFENAC only after careful consideration. See 7 WARNINGS AND PRECAUTIONS - Cardiovascular Use of NSAIDs, such as PRO-DICLOFENAC, can promote sodium retention in a dose-dependent manner, through a renal mechanism, which can result in increased blood pressure and/or exacerbation of congestive heart failure. See 7 WARNINGS AND PRECAUTIONS - Renal - Fluid and Electrolyte Balance. Risk of Gastrointestinal (GI) Adverse Events: Use of NSAIDs, such as PRO-DICLOFENAC, is associated with an increased incidence of gastrointestinal adverse events (such as peptic/duodenal ulceration, perforation, obstruction and gastrointestinal bleeding). See 7 WARNINGS AND PRECAUTIONS –Gastrointestinal (GI). Risk in Pregnancy: Caution should be exercised in prescribing PRO-DICLOFENAC during the first and second trimesters of pregnancy. Use of NSAIDS at approximately 20 weeks of |
|---|
| gestation or later may cause fetal renal dysfunction leading to oligohydramnios and neonatal renal impairment or failure (see 7.1.1 Pregnant Women). PRO-DICLOFENAC is contraindicated for use during the third trimester because of risks of premature closure of the ductus arteriosus and uterine inertia (prolonged parturition) (See 2 CONTRAINDICATIONS). |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Use of PRO-DICLOFENAC should be limited to the lowest effective dose for the shortest possible duration of treatment in order to minimize the potential risk for cardiovascular or gastrointestinal adverse events (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
Cardiovascular disease or cardiovascular risk factors: Treatment with PRO-DICLOFENAC is not recommended in patients with pre-existing cardiovascular disease (congestive heart failure NYHA II-IV, ischemic heart disease, peripheral arterial disease), cerebrovascular disease, uncontrolled hypertension, or patients with risk factors for cardiovascular disease (e.g. hypertension, hyperlipidemia, diabetes mellitus and smoking). These patients should be treated with PRO-DICLOFENAC only after careful consideration (see 3 SERIOUS WARNINGS AND PRECAUTIONS box).
4.2 Recommended Dose and Dosage Adjustment
PRO-DICLOFENAC is to be used for maintenance therapy only.
PRO-DICLOFENAC (delayed-release)
Rheumatoid arthritis and osteoarthritis patients may use PRO-DICLOFENAC (diclofenac sodium) delayed-release tablets if:
- They were previously initiated at the lowest dose of 75 mg (delayed-release) per day in 3 divided doses and required up-titration because they did not respond to that dose.
- The maximum recommended daily dose is 100 mg.
PRO-DICLOFENAC should be taken with food and the tablets should be swallowed whole.
Pediatrics (< 16 years of age): Health Canada has not authorized an indication for pediatric use. See 2 CONTRAINDICATIONS
Geriatrics (> 65 years of age): For such patients, consideration should be given to a starting dose lower than the one usually recommended, with individual adjustment when necessary and under close supervision Caution is indicated especially for frail elderly patients or those with a low body weight (see 7.1.4 Geriatrics).
Renal Impairment: PRO-DICLOFENAC is contraindicated in patients with severe renal impairment or deteriorating renal disease (see 2 CONTRAINDICATIONS). Lower doses of PRO-DICLOFENAC should be considered in patients with impaired renal function (see 7 WARNINGS AND PRECAUTIONS — Renal).
Hepatic Impairment: PRO-DICLOFENAC is contraindicated in patients with severe hepatic impairment or active liver disease (see 2 CONTRAINDICATIONS). Lower doses of PRO-DICLOFENAC should be considered in patients with impaired hepatic function (see 7 WARNINGS AND PRECAUTIONS — Hepatic/Biliary/Pancreatic).
4.4 Administration
PRO-DICLOFENAC should be taken with food and the tablets should be swallowed whole.
4.5 Missed Dose
Patients who miss one or more doses of PRO-DICLOFENAC (diclofenac sodium) should not increase the dose of PRO-DICLOFENAC (diclofenac sodium) to compensate for the missed dose or doses, but should continue with their therapy as soon as possible.
5 OVERDOSAGE
Symptoms
There is no typical clinical picture resulting from diclofenac overdosage. Overdosage can cause symptoms such as vomiting, gastrointestinal haemorrhage, diarrhoea, dizziness, tinnitus or convulsions. In the event of significant poisoning, acute renal failure and liver damage are possible.
Therapeutic measures
Management of acute poisoning with NSAIDs, including PRO-DICLOFENAC, essentially consists of supportive measures and symptomatic treatment. Supportive measures and symptomatic treatment should be given for complications such as hypotension, renal failure, convulsions, gastrointestinal disorder, and respiratory depression. Special measures such as forced diuresis, dialysis or haemoperfusion are probably of no help in eliminating NSAIDs, including PRO-DICLOFENAC, due to the high protein binding and extensive metabolism. Activated charcoal may be considered after ingestion of a potentially toxic overdose, and gastric decontamination (e.g. vomiting, gastric lavage) after ingestion of a potentially life threatening overdose.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging.
| Route of Administration | Dosage Form / Strength/ Composition | Non-medicinal Ingredients |
| Oral | Delayed-Release Tablets, 50 mg | Colloidal silicon dioxide, dextrates, FD & C yellow #6 aluminum lake, ferric oxide yellow, hydroxypropyl methylcellulose, methanol, magnesium stearate, methylcellulose, polyethylene glycol, polyvinylacetate phthalate, stearic acid, titanium dioxide and triethyl citrate. |
Description
PRO-DICLOFENAC (diclofenac sodium) Delayed-Release Tablets: mocha-brown, round, biconvex, coated tablet, engraved ‘50’ on one side, other side plain.
PRO-DICLOFENAC is available in bottles of 100 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Frail or debilitated patients may tolerate side effects less well and therefore special care should be taken in treating this population. To minimize the potential risk for an adverse event, the lowest effective dose should be used for the shortest possible duration. As with other NSAIDs, caution should be used in the treatment of elderly patients who are more likely to be suffering from impaired renal, hepatic or cardiac function. For high risk patients, alternate therapies that do not involve NSAIDs should be considered.
Diclofenac sodium is NOT recommended for use with other NSAIDs, with the exception of low-dose ASA for cardiovascular prophylaxis, because of the absence of any evidence demonstrating synergistic benefits and the potential for additive adverse reactions (see 9 DRUG INTERACTIONS – Drug/Drug Interactions - Acetylsalicylic acid (ASA) or other NSAIDs).
Diclofenac sodium should not be used concomitantly with diclofenac potassium since both exist in plasma as the same active organic ion.
Carcinogenesis and Mutagenesis
(See 16 NON-CLINICAL TOXICOLOGY)
Cardiovascular
PRO-DICLOFENAC is an NSAID.
Diclofenac is associated with an increased risk of cardiovascular adverse events (such as myocardial infarction, stroke or thrombotic events, which can be fatal) that is comparable to COX-2 inhibitors. Patients with cardiovascular disease or risk factors for cardiovascular disease may be at greater risk.
As the cardiovascular risks of diclofenac may increase with dose and duration of exposure, the lowest effective daily dose should be used for the shortest duration possible. The patient's need for symptomatic relief and response to therapy should be re-evaluated periodically.
Patients should remain alert for the signs and symptoms of serious arteriothrombotic events (e.g. chest pain, shortness of breath, weakness, slurring of speech), which can occur without warnings. Patients should be instructed to see a physician immediately in case of such an event.
Use of NSAIDs, such as PRO-DICLOFENAC, can lead to new hypertension or can worsen pre-existing hypertension, either of which may increase the risk of cardiovascular events as described below. Thus blood pressure should be monitored regularly. Consideration should be given to discontinuing PRO-DICLOFENAC should hypertension either develop or worsen with its use.
Use of NSAIDs, such as PRO-DICLOFENAC, can induce fluid retention and edema, and may exacerbate congestive heart failure, through a renally-mediated mechanism (see 7 WARNINGS AND PRECAUTIONS - Renal - Fluid and Electrolyte Balance).
Caution should be exercised in prescribing PRO-DICLOFENAC to patients with risk factors for cardiovascular disease, cerebrovascular disease or renal disease, such as any of the following (NOT an exhaustive list):
- Hypertension
- Dyslipidemia / Hyperlipidemia
- Diabetes Mellitus
- Congestive Heart Failure (NYHA II-IV)
- Ischemic heart disease
- Peripheral Arterial Disease
- Smoking
- Creatinine Clearance < 60 mL/min or 1 mL/sec
- Acute myocardial infarction, history of myocardial infarction and/or angina
- Stroke, cerebrovascular accident, transient ischemic attacks, and/or amaurosis fugax
If needed, these patients should be treated only after careful consideration (see 3 SERIOUS WARNINGS AND PRECAUTIONS box).
Driving and Operating Machinery
Patients experiencing visual disturbances, dizziness, vertigo, somnolence or other central nervous system disturbances while taking PRO-DICLOFENAC should refrain from driving or using machines.
Endocrine and Metabolism
Corticosteroids: PRO-DICLOFENAC is NOT a substitute for corticosteroids. It does NOT treat corticosteroid insufficiency. Abrupt discontinuation of corticosteroids may lead to exacerbation of corticosteroid-responsive illness. Patients on prolonged corticosteroid therapy should have their therapy tapered slowly if a decision is made to discontinue corticosteroids (see 9 DRUG INTERACTIONS - Drug-Drug Interactions -Glucocorticoids).
Gastrointestinal (GI)
Serious GI toxicity (sometimes fatal), such as peptic/duodenal ulceration, inflammation, perforation, peritonitis, obstruction, gastrointestinal bleeding, gastrointestinal stenosis and ischemic colitis can occur at any time, with or without warning symptoms, in patients treated with PRO-DICLOFENAC. Minor upper GI problems, such as dyspepsia, commonly occur at any time. Health care providers should remain alert for ulceration and bleeding in patients treated with PRO-DICLOFENAC, even in the absence of previous GI tract symptoms. Most spontaneous reports of fatal GI events are in elderly or debilitated patients and therefore special care should be taken in treating this population. To minimize the potential risk for an adverse GI event, the lowest effective dose should be used for the shortest possible duration. For high risk patients, alternate therapies that do not involve NSAIDs should be considered (see 7.1.4 WARNINGS AND PRECAUTIONS — Special Populations — Geriatrics).
Patients should be informed about the signs and/or symptoms of serious GI toxicity and instructed to discontinue using PRO-DICLOFENAC and seek emergency medical attention if they experience any such symptoms. The utility of periodic laboratory monitoring has NOT been demonstrated, nor has it been adequately assessed. Most patients who develop a serious upper GI adverse event on NSAID therapy have no symptoms. Upper GI ulcers, gross bleeding or perforation, caused by NSAIDs, appear to occur in approximately 1% of patients treated for 3 to 6 months, and in about 2 to 4% of patients treated for one year. These trends continue, thus increasing the likelihood of developing a serious GI event at some time during the course of therapy. Even a short-term therapy has its risks.
Diclofenac may be associated with increased risk of gastrointestinal anastomotic leak, serious outcomes of which have included multiple surgeries and death. Close medical surveillance and caution are recommended when using PRO-DICLOFENAC after gastrointestinal surgery.
Caution should be taken if prescribing PRO-DICLOFENAC to patients with a prior history of peptic / duodenal ulcer disease or gastrointestinal bleeding as these individuals have a greater than 10-fold higher risk for developing a GI bleed when taking a NSAID than patients with neither of these risk factors. Other risk factors for GI ulceration and bleeding include the following: Helicobacter pylori infection, increased age, prolonged use of NSAID therapy, excess alcohol intake, smoking, poor general health status or concomitant therapy with any of the following:
- Anti-coagulants (e.g. warfarin)
- Anti-platelet agents (e.g. ASA, clopidogrel)
- Oral corticosteroids (e.g. prednisone)
- Selective Serotonin Reuptake Inhibitors (SSRIs) (e.g. citalopram, fluoxetine, paroxetine, sertraline)
There is no definitive evidence that the concomitant administration of histamine H2-receptor antagonists and/or antacids will either prevent or reduce the occurrence of gastrointestinal adverse events associated with the use of the delayed-release formulation of diclofenac sodium. Concurrent administration of histamine H2-receptor antagonists and/or antacids with the delayed-release version of diclofenac sodium might result in altered absorption.
Genitourinary
Some NSAIDs are associated with persistent urinary symptoms (bladder pain, dysuria, urinary frequency), hematuria or cystitis. The onset of these symptoms may occur at any time after the initiation of therapy with an NSAID. Should urinary symptoms occur, in the absence of an alternate explanation, treatment with PRO-DICLOFENAC should be stopped to ascertain if symptoms disappear. This should be done before urological investigations or treatments are carried out.
Hematologic
NSAIDs inhibiting prostaglandin biosynthesis interfere with platelet function to varying degrees; patients who may be adversely affected by such an action, such as those on anti-coagulants or suffering from hemophilia or platelet disorders should be carefully observed when PRO-DICLOFENAC is administered.
Anti-coagulants: Numerous studies have shown that the concomitant use of NSAIDs and anticoagulants increases the risk of bleeding. Concurrent therapy of PRO-DICLOFENAC with warfarin requires close monitoring of the international normalized ratio (INR).
Even with therapeutic INR monitoring, increased bleeding may occur.
Anti-platelet Effects: NSAIDs inhibit platelet aggregation and have been shown to prolong bleeding time in some patients. Unlike acetylsalicylic acid (ASA), their effect on platelet function is quantitatively less, or of shorter duration, and is reversible.
Diclofenac sodium (delayed-release tablets) and other NSAIDs have no proven efficacy as anti-platelet agents and should NOT be used as a substitute for ASA or other anti-platelet agents for prophylaxis of cardiovascular thromboembolic diseases. Anti-platelet therapies (e.g. ASA) should NOT be discontinued. There is some evidence that use of NSAIDs with ASA can markedly attenuate the cardioprotective effects of ASA (see 9 DRUG INTERACTIONS - Drug-Drug Interactions - Acetylsalicylic Acid (ASA) or other NSAIDs).
Concomitant administration of PRO-DICLOFENAC with low dose ASA increases the risk of GI ulceration and associated complications.
Blood dyscrasias: Blood dyscrasias (such as neutropenia, leukopenia, thrombocytopenia, aplastic anemia and agranulocytosis) associated with the use of NSAIDs are rare, but could occur with severe consequences.
Anemia is sometimes seen in patients receiving NSAIDs, including PRO-DICLOFENAC. This may be due to fluid retention, GI blood loss, or an incompletely described effect upon erythropoiesis. Patients on long-term treatment with NSAIDs, including PRO-DICLOFENAC, should have their hemoglobin or hematocrit checked if they exhibit any signs or symptoms of anemia or blood loss.
Hepatic/Biliary/Pancreatic
As with other NSAIDs, including PRO-DICLOFENAC, borderline elevations of one or more liver enzyme tests (AST, ALT, alkaline phosphatase) may occur in up to 15% of patients. These abnormalities may progress, may remain essentially unchanged, or may be transient with continued therapy.
In post-marketing reports, cases of drug-induced hepatotoxicity have been reported in the first month, and in some cases, the first 2 months of therapy, but can occur at any time during treatment with diclofenac. Post-marketing surveillance has reported cases of severe hepatic reactions, including liver necrosis, jaundice, fulminant hepatitis with and without jaundice, and liver failure. Some of these reported cases resulted in fatalities or liver transplantation.
Physicians should regularly monitor hepatic function in patients receiving PRO-DICLOFENAC. If abnormal liver function tests persist or worsen, if clinical signs and symptoms consistent with liver disease develop (e.g. nausea, fatigue, lethargy, diarrhea, pruritus, jaundice, right upper quadrant tenderness, and «flu-like» symptoms), or if other manifestations occur (e.g. eosinophilia, associated with rash etc.), this drug should be discontinued. Hepatotoxic effects may occur with use of diclofenac without prodromal symptoms.
To minimize the possibility that hepatic injury will become severe between transaminase measurements, physicians should inform patients of the warning signs and symptoms of hepatotoxicity and the appropriate action patients should take if these signs and symptoms appear.
PRO-DICLOFENAC is contraindicated in severe liver impairment or active liver disease. If there is a need to prescribe this drug to other patients with liver impairment, it must be done under strict observation.
Caution is advised when using PRO-DICLOFENAC in patients with hepatic porphyria, since PRO-DICLOFENAC may trigger an attack.
Immune
PRO-DICLOFENAC, in common with other NSAIDs, may mask signs and symptoms of an underlying infectious disease.
Aseptic Meningitis: Rarely, with some NSAIDs, the symptoms of aseptic meningitis (stiff neck, severe headaches, nausea and vomiting, fever or clouding of consciousness) have been observed. Patients with autoimmune disorders (systemic lupus erythematosus, mixed connective tissue diseases, etc.) seem to be pre-disposed. Therefore, in such patients, the health care provider must be vigilant to the development of this complication.
Monitoring and Laboratory Tests
Cardiovascular (Hypertension): Blood pressure should be monitored regularly during therapy with PRO-DICLOFENAC.
Hematologic: Patients on long-term treatment with PRO-DICLOFENAC should have their hemoglobin, hematocrit, red blood cells (RBC), white blood cells (WBC), and platelets checked if they exhibit any signs or symptoms of anemia or blood loss or blood dyscrasia.
Concurrent therapy of PRO-DICLOFENAC with warfarin requires close monitoring of the international normalized ratio (INR).
Hepatic: Hepatic function (e.g. serum transaminases, bilirubin) should be monitored regularly during therapy with PRO-DICLOFENAC.
Ophthalmologic: Patients on long-term treatment with PRO-DICLOFENAC should have an ophthalmologic examination performed periodically, and if they experience blurred and/or diminished vision.
Pregnancy: If PRO-DICLOFENAC is administered in the middle (approximately 20 weeks) to the end of the second trimester, it is recommended that pregnant women on PRO-DICLOFENAC be closely monitored for amniotic fluid volume since PRO-DICLOFENAC may result in reduction of amniotic fluid volume and even oligohydramnios (see 7.1 Special Populations). PRO-DICLOFENAC is contraindicated for use in the third trimester of pregnancy.
Renal: Patients with pre-existing renal insufficiency (GFR < 60 mL/min or 1 mL/s), dehydrated patients, patients on salt restricted diets, those with congestive heart failure, cirrhosis, liver dysfunction, taking angiotensin-converting enzyme inhibitors, angiotensin-II receptor blockers, cyclosporine, diuretics, and the elderly should have their renal function monitored (e.g. urine output, serum creatinine, creatinine clearance and serum urea) during therapy with PRO-DICLOFENAC.
Electrolytes, including serum potassium, should be monitored periodically, especially in patients with diabetes mellitus, renal failure, increased age, or those receiving concomitant therapy with adrenergic blockers, angiotensin-converting enzyme inhibitors, angiotensin-II receptor antagonists, cyclosporine, tacrolimus, trimethoprim or some diuretics.
Neurologic
Some patients may experience drowsiness, dizziness, blurred vision, vertigo, insomnia, depression, tinnitus or hearing loss with the use of NSAIDs, such as PRO-DICLOFENAC. If patients experience such adverse reaction(s) they should exercise caution in carrying out activities that require alertness.
Ophthalmologic
Blurred and/or diminished vision has been reported with the use of NSAIDs, which may be reversible with discontinuation. If such symptoms develop, PRO-DICLOFENAC should be discontinued, and an ophthalmologic examination performed. Ophthalmologic examination should be carried out at periodic intervals in any patient receiving PRO-DICLOFENAC for an extended period of time.
Sun exposure in patients using PRO-DICLOFENAC might cause photosensitivity and vision changes. Patients should be advised to contact their physician for assessment and advice if this occurs.
Peri-Operative Considerations
(See 2 CONTRAINDICATIONS)
Psychiatric
(See 7 WARNINGS AND PRECAUTIONS - Neurologic)
Renal
Long term administration of NSAIDs to animals has resulted in renal papillary necrosis and other abnormal renal pathology. In humans, there have been reports of acute interstitial nephritis, hematuria, low grade proteinuria and occasionally nephrotic syndrome.
During long-term therapy, kidney function should be monitored periodically (see 10 CLINICAL PHARMACOLOGY-Special Populations and Conditions - Renal Impairment).
Renal insufficiency due to NSAID use is seen in patients with pre-renal conditions leading to reduction in renal blood flow or blood volume. Under these circumstances, renal prostaglandins help maintain renal perfusion and glomerular filtration rate (GFR). In these patients, administration of a NSAID may cause a reduction in prostaglandin synthesis leading to impaired renal function. Patients at greatest risk of this reaction are those with pre-existing renal insufficiency (GFR< 60 mL/min or 1 mL/s), dehydrated patients, patients on salt restricted diets, those with congestive heart failure, cirrhosis, liver dysfunction, taking angiotensin-converting enzyme inhibitors, angiotensin-II receptor blockers, cyclosporine, diuretics, and those who are elderly. Serious or life-threatening renal failure has been reported in patients with normal or impaired renal function after short term therapy with NSAIDs. Even patients at risk who demonstrate the ability to tolerate a NSAID under stable conditions may decompensate during periods of added stress (e.g. dehydration due to gastroenteritis). Discontinuation of NSAIDs is usually followed by recovery to the pre-treatment state.
Caution should be used when initiating treatment with NSAIDs, such as PRO-DICLOFENAC, in patients with considerable dehydration. Such patients should be rehydrated prior to initiation of therapy. Caution is also recommended in patients with pre-existing kidney disease
(see 7 WARNING AND PRECAUTIONS - Monitoring and Laboratory Tests - Renal).
Advanced Renal Disease: (see 2 CONTRAINDICATIONS)
Fluid and Electrolyte Balance: Use of NSAIDs, such as PRO-DICLOFENAC, can promote sodium retention in a dose-dependent manner, which can lead to fluid retention and edema, and consequences of increased blood pressure and exacerbation of congestive heart failure. Thus, caution should be exercised in prescribing PRO-DICLOFENAC in patients with a history of congestive heart failure, compromised cardiac function, hypertension, increased age or other conditions predisposing to fluid retention (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
Use of NSAIDs, such as PRO-DICLOFENAC, can increase the risk of hyperkalemia, especially in patients with diabetes mellitus, renal failure, increased age, or those receiving concomitant therapy with adrenergic blockers, angiotensin-converting enzyme inhibitors, angiotensin-II receptor antagonists, cyclosporine, tacrolimus, trimethoprim or some diuretics. Electrolytes should be monitored periodically (see 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS – Drug-Drug Interactions).
Respiratory
ASA-induced asthma is an uncommon but very important indication of ASA and NSAIDs sensitivity. It occurs more frequently in patients with asthma who have nasal polyps.
Pre-existing asthma: In patients with asthma, seasonal allergic rhinitis, swelling of the nasal mucosa (i.e. nasal polyps), chronic obstructive pulmonary diseases or chronic infections of the respiratory tract (especially if linked to allergic rhinitis-like symptoms), reactions on NSAIDs like asthma exacerbations (so-called intolerance to analgesics/analgesics-asthma), Quincke’s oedema or urticaria are more frequent than in other patients. Therefore, special precaution is recommended in such patients (readiness for emergency). This is applicable as well for patients who are allergic to other substances, e.g. with skin reactions, pruritus or urticaria.
Reproductive Health: Female and Male Potential
Fertility
The use of PRO-DICLOFENAC, as with any drug known to inhibit cyclooxygenase/prostaglandin synthesis, may impair fertility and is not recommended in women attempting to conceive. Therefore, in women who have difficulties conceiving, or who are undergoing investigation of infertility, withdrawal of PRO-DICLOFENAC should be considered.
Sensitivity/Resistance
Anaphylactoid reactions: As with NSAIDs in general, anaphylactoid reactions have occurred in patients without known prior exposure to PRO-DICLOFENAC. In post-marketing experience, rare cases of anaphylactic/anaphylactoid reactions and angioedema have been reported in patients receiving PRO-DICLOFENAC. PRO-DICLOFENAC should NOT be given to patients with the ASA-triad. This symptom complex typically occurs in asthmatic patients who experience rhinitis with or without nasal polyps, or who exhibit severe, potentially fatal bronchospasm after taking ASA or other NSAIDs (see 2 CONTRAINDICATIONS).
ASA-intolerance: PRO-DICLOFENAC should NOT be given to patients with complete or partial syndrome of ASA-intolerance (rhinosinusitis, urticaria/angioedema, nasal polyps, asthma) in whom asthma, anaphylaxis, urticaria/angioedema, rhinitis or other allergic manifestations are precipitated by ASA or other NSAIDs. Fatal anaphylactoid reactions have occurred in such individuals. As well, individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse reaction (see 2 CONTRAINDICATIONS).
Cross-sensitivity: Patients sensitive to any one of the NSAIDs may be sensitive to any of the other NSAIDs as well.
Serious Skin Reactions: (see 7 WARNINGS AND PRECAUTIONS - Skin)
Skin
Serious skin reactions: Use of some NSAIDs, such as PRO-DICLOFENAC, have been associated with rare post-market cases of serious, fatal or otherwise life-threatening skin reactions, including:
- Drug reaction with eosinophilia and systemic symptoms (DRESS)
- Stevens-Johnson syndrome (SJS)
- toxic epidermal necrolysis (TEN)
- exfoliative dermatitis
- erythema multiforme.
Patients appear to be at higher risk for these events early in the course of therapy, with the onset of cases usually occurring within the first month of treatment. These reactions may be reversible if the causative agent is discontinued and appropriate treatment instituted. Patients should be advised that they should discontinue their NSAID at the first appearance of a skin rash, mucosal lesions or any other sign of hypersensitivity, and contact their physician immediately for assessment and advice, including which therapies to discontinue.
DRESS typically, although not exclusively, presents with fever, rash, lymphadenopathy, and/or facial swelling. Other clinical manifestations may include hepatitis, nephritis, hematological abnormalities, myocarditis, or myositis. Sometimes symptoms of DRESS may resemble an acute viral infection, and eosinophilia is often present. Because this disorder is variable in its presentation, other organ systems not noted here may be involved. It is important to note that early manifestations of hypersensitivity, such as fever or lymphadenopathy, may be present even though rash is not evident.
Use of PRO-DICLOFENAC may cause photosensitivity upon exposure to sunlight or UV light causing symptoms such as sunburn, skin rash, skin blisters, pruritus, erythema and discoloration.
7.1 Special Populations
7.1.1 Pregnant Women
PRO-DICLOFENAC is CONTRAINDICATED for use during the third trimester of pregnancy because of risks of premature closure of the ductus arteriosus and the potential to prolong parturition (see 2 CONTRAINDICATIONS and 16 NON-CLINICAL TOXICOLOGY). Caution is recommended in prescribing PRO-DICLOFENAC during the first and second trimesters of pregnancy, particularly from the middle to end of the second trimester of pregnancy (onset at approximately 20 weeks) due to possible fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment or failure.
PRO-DICLOFENAC should not be used during the first two trimesters of pregnancy unless the expected benefits to the mother outweigh the risks to the fetus.
Published studies and postmarketing reports describe maternal NSAID (including diclofenac) use at approximately 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment or failure. NSAIDs were shown to cause significant reduction in fetal urine production prior to reduction of amniotic fluid volume. There have also been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction and renal impairment without oligohydramnios, some of which were irreversible, even after treatment discontinuation.
These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. Complications of prolonged oligohydramnios may for example, include limb contractures and delayed lung maturation. In some postmarketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required.
If after careful consideration of the benefit-risk, NSAID treatment is considered necessary to be administered anywhere from the middle (onset at approximately 20 weeks) to the end of the second trimester of pregnancy, the use should be limited to the lowest effective dose and shortest duration possible. It is also recommended that ultrasound monitoring of amniotic fluid be considered if PRO-DICLOFENAC treatment extends beyond 48 hours and that NSAIDs treatment be discontinued if oligohydramnios occurs, followed by appropriate medical follow up.
Inhibition of prostaglandin synthesis may adversely affect pregnancy and/or the embryo-fetal development. Data from epidemiological studies suggest an increased risk of miscarriage and of cardiac malformation after use of a prostaglandin synthesis inhibitor in early pregnancy.
In animals, administration of a prostaglandin synthesis inhibitor has been shown to result in increased pre- and post-implantation loss and embryo-foetal lethality. In addition, increased incidences of various malformations, including cardiovascular, have been reported in animals given a prostaglandin synthesis inhibitor during the organogenetic period.
Diclofenac sodium readily crosses the placental barrier.
7.1.2 Breast-feeding
PRO-DICLOFENAC is contraindicated in breast-feeding women. See 2 CONTRAINDICATIONS
7.1.3 Pediatrics
Pediatrics (< 16 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. See 2 CONTRAINDICATIONS
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Patients older than 65 years (referred to in this document as older or elderly) and frail or debilitated patients are more susceptible to a variety of adverse reactions from NSAIDs; the incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. Most reports of fatal GI events are in this population. Older patients are also at risk of lower esophageal injury including ulceration and bleeding.
For such patients, consideration should be given to a starting dose lower than the one usually recommended, with individual adjustment when necessary and under close supervision, especially in frail elderly patients or those with a low body weight.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Although not all adverse drug reactions have been reported with PRO-DICLOFENAC, the types of adverse drug reactions are expected to be similar to those of diclofenac potassium since both formulations exist in the plasma as the same active organic anion.
Gastrointestinal, dermatological, CNS and hepatic adverse reactions are the most commonly seen with diclofenac. The most severe gastrointestinal adverse reactions observed were ulceration and bleeding, while the most severe dermatological albeit rare reactions observed with diclofenac were erythema multiforme (Stevens-Johnson Syndrome and Lyell Syndrome). Fatalities have occurred on occasion, particularly in the elderly.
This section summarizes adverse drug reaction data pooled from clinical trials, published investigations and post-marketing experience with diclofenac potassium and diclofenac sodium.
Frequency estimate:
Very common: ≥10%
Common: ≥1% and < 10%
Uncommon: ≥0.01% and < 1%
Very rare: <0.01%, including isolated reports.
Table 2 Most Common Adverse Drug Reactions (≥1%)
| Gastrointestinal disorders | Very common | nausea, vomiting, diarrhea, dyspepsia, abdominal pain, flatulence, decreased appetite |
|---|---|---|
| Nervous system disorders | Common | dizziness, headache |
| Hepatic | Common | elevations (≥3 times the upper normal limit) of serum aminotransferase enzymes (SGOT or AST, SGPT or ALT). |
| Skin and subcutaneous disorders | Common | rash, pruritus |
| Ear and labyrinth disorders | Common | vertigo |
Table 3 Less Common Adverse Drug Reactions (<1%)
| Gastrointestinal disorders | Uncommon | gastritis, gastrointestinal hemorrhage, hemorrhagic diarrhea, melena, hematemesis, gastric and intestinal ulcerations (with or without bleeding or perforation) |
|---|---|---|
| Very rare | lower gut disorders (including hemorrhagic colitis and exacerbation of ulcerative colitis or Crohn’s disease), intestinal diaphragm disease, hyperacidity, stomatitis, glossitis, coated tongue, esophageal lesions, constipation, pancreatitis | |
| Nervous system disorders | Uncommon | somnolence, malaise, impaired concentration, tiredness |
| Very rare | sensory disturbances including paresthesia, memory impairment, convulsions, anxiety, tremor, aseptic meningitis, cerebrovascular accident (including transient ischemic attack, cerebral hemorrhage), dysgeusia | |
| Eye disorders | Very rare | visual impairment (blurred vision, diplopia) |
| Ear and labyrinth | Very rare | hearing impaired, tinnitus |
| disorders | ||
|---|---|---|
| Cardiac disorders | Uncommon | myocardial infarction, cardiac failure, palpitations, angina, arrhythmias, chest pain |
| Vascular disorders | Very rare | hypertension, vasculitis |
| Skin and subcutaneous disorders | Uncommon | urticaria |
| Very rare | bullous dermatitis, erythema, eczema, erythema multiforme, Stevens-Johnson Syndrome, Lyell Syndrome (toxic epidermal necrolysis), erythroderma (exfoliative dermatitis), alopecia, photosensitivity reactions, purpura, Henoch-Schonlein purpura | |
| Renal and urinary disorders | Uncommon | edema (facial, general, peripheral) |
| Very rare | acute kidney injury (acute renal failure), nephrotic syndrome, urinary abnormalities (e.g., hematuria and proteinuria), tubulointerstitial nephritis, renal papillary necrosis | |
| Hematologic | Very rare | thrombocytopenia, leukopenia, agranulocytosis, hemolytic anemia, aplastic anemia, anemia secondary to gastrointestinal bleeding |
| Hepatic | Uncommon | liver function disorders including hepatitis, hepatic necrosis, hepatic failure, jaundice |
| Very rare | hepatitis fulminant | |
| Immune system disorders | Uncommon | hypersensitivity anaphylactic / anaphylactoid systemic reactions (including hypotension and shock) |
| Very rare | angioedema (including face edema) | |
| Psychiatric disorders | Very rare | disorientation, depression, insomnia, nightmare, irritability, psychotic disorder |
| Respiratory disorders | Uncommon | asthma (including dyspnea) |
| Very rare | pneumonitis | |
8.2 Clinical Trial Adverse Reactions
The clinical trial data which the indications were originally approved is not available.
8.5 Post-Market Adverse Reactions
Hepatic: Severe hepatic reactions including liver necrosis, fulminant hepatitis with and without jaundice, and liver failure, some of them with fatal outcome or requiring liver transplantation (see 7 WARNINGS AND PRECAUTIONS – Hepatic/Biliary/Pancreatic).
Cardiovascular: Serious reactions including myocardial infarction, cardiac failure, palpitations, angina, arrhythmias, chest pain.
Meta-analysis and pharmacoepidemiological data point towards an increased risk of arteriothrombotic events associated with the use of diclofenac, particularly at a high dose (see 3 SERIOUS WARNINGS AND PRECAUTIONS box).
Gastrointestinal Disorders: Gastrointestinal stenosis, perforation which may lead to peritonitis, and ischemic colitis (which are sometimes fatal), anastomotic leak (see 7 WARNINGS AND PRECAUTIONS – Gastrointestinal (GI)).
Immune/Hypersensitivity: Kounis syndrome, a serious allergic reaction that can cause myocardial infarction.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Effect of Other Drugs on the Metabolism of diclofenac: Co-prescribing diclofenac with CYP2C9 inhibitors could result in a significant increase in peak plasma concentrations and exposure to diclofenac. Although there are no clinical data available on the drug interaction between diclofenac sodium (delayed-release tablets) and CYP2C9 inducers, the possibility of decreased efficacy of diclofenac resulting from concomitant administration with a CYP2C9 inducer cannot be excluded. Dosage adjustment may be required.
Drugs known to cause hyperkalemia: Concomitant treatment with potassium-sparing diuretics, cyclosporine, tacrolimus, trimethoprim, ACE inhibitors, angiotensin-II receptor antagonists or adrenergic blockers may be associated with increased serum potassium levels, which should therefore be monitored frequently (see 7 WARNINGS AND PRECAUTIONS - Renal – Fluid and Electrolyte Balance).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 Established Potential Drug-Drug Interactions
| Diclofenac sodium (delayed-release tablets) | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Acetaminophen | Controlled clinical studies | There may be an increased risk of adverse renal effects when administered concomitantly with NSAIDs. |
| Diclofenac sodium (delayed-release tablets) | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Acetylsalicylic acid (ASA) or other NSAIDs | Controlled clinical studies | The use of diclofenac sodium (delayed-release tablets) in addition to any other NSAID, including over the counter ones (such as ASA and ibuprofen) for analgesic and/or anti-inflammatory effects is NOT recommended because of the absence of any evidence demonstrating synergistic benefits and the potential for additive adverse reactions. The exception is the use of low dose ASA for cardiovascular protection when another NSAID is being used for its analgesic/anti-inflammatory effect, keeping in mind that combination NSAID therapy is associated with additive adverse reactions. Some NSAIDs (e.g. ibuprofen) may interfere with the anti-platelet effects of low dose ASA, possibly by competing with ASA for access to the active site of cyclooxygenase-1. | PRO-DICLOFENAC should not be used concomitantly with diclofenac potassium since both exist in plasma as the same active organic ion. Concomitant administration of PRO-DICLOFENAC and other systemic NSAIDs or corticosteroids may increase the frequency of gastrointestinal undesirable effects. |
| Alcohol | There may be an increased risk of gastrointestinal side effects, including ulceration or hemorrhage, when administered concomitantly with NSAIDs. | ||
| Antacids | Concomitant administration of antacids with NSAIDs may affect the rate, but generally not the extent of the absorption of the NSAID. | ||
| Anticoagulants | Numerous studies have shown that the concomitant use of NSAIDs and anti-coagulants increases the risk of bleeding. | Concurrent therapy of PRO-DICLOFENAC, with warfarin requires close monitoring of the international normalized ratio |
| Diclofenac sodium (delayed-release tablets) | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
(INR). Even with therapeutic INR monitoring, increased bleeding may occur. (See 7 WARNINGS AND PRECAUTIONS – Hematologic - Anti-coagulants) | |||
| Anti-hypertensives | NSAIDs may diminish the anti-hypertensive effect of Angiotensin Converting Enzyme (ACE) inhibitors. Combinations of ACE inhibitors, angiotensin-II antagonists, or diuretics with NSAIDs might have an increased risk for acute renal failure and hyperkalemia. Blood pressure and renal function (including electrolytes) should be monitored more closely in this situation, as occasionally there can be a substantial increase in blood pressure (see 7 WARNINGS AND PRECAUTIONS - Renal). | Therefore the combination should be administered with caution, especially in the elderly (see 7 WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests). | |
| Anti-platelet agents (including ASA) | There is an increased risk of bleeding, via inhibition of platelet function, when anti-platelet agents are combined with NSAIDs, such as diclofenac sodium (delayed-release tablets) (see 7 WARNINGS AND PRECAUTIONS — Hematologic – Anti-platelet Effects). | Concomitant administration of PRO-DICLOFENAC with low dose ASA increases the risk of GI ulceration and associated complication. | |
| Cyclosporine | Nephrotoxicity of cyclosporine may be increased because of the effect of NSAIDs on renal prostaglandins. | It should be given at doses lower than those that would be used in patients not receiving cyclosporine. | |
| CYP2C9 inducers | Caution is recommended when co- | Dosage adjustment |
| Diclofenac sodium (delayed-release tablets) | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| prescribing PRO-DICLOFENAC with CYP2C9 inducers (such as rifampin), which could result in a significant decrease in plasma concentration and exposure to diclofenac. | may be required. | ||
| CYP2C9 inhibitors | Caution is recommended when co-prescribing PRO-DICLOFENAC with CYP2C9 inhibitors (such as voriconazole or sulfinpyrazone), which could result in a significant increase in peak plasma concentrations and exposure to diclofenac. | Dosage adjustment may be required. | |
| Digoxin | PRO-DICLOFENAC and may increase the plasma concentration of digoxin. | Dosage adjustment may be required. Monitoring of serum digoxin level is recommended. | |
| Diuretics | Clinical studies as well as post-marketing observations | NSAIDs can reduce the effect of diuretics (see 7 WARNINGS AND PRECAUTIONS - Renal). | Concomitant treatment with potassium-sparing diuretics may be associated with increased serum potassium, thus making it necessary to monitor levels (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests – Renal). |
| Glucocorticoids | Some studies have shown that concomitant use of NSAIDs and oral glucocorticoids increases the risk of GI adverse events such as ulceration and bleeding. This is especially the case in older (>65 years of age) individuals. | ||
| Lithium | Monitoring of plasma lithium concentrations is advised when stopping or starting a NSAID, as increased lithium concentrations | Dosage adjustment of lithium may be required. |
| Diclofenac sodium (delayed-release tablets) | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| can occur in patients taking lithium. | |||
| Methotrexate | Caution should be exercised when NSAIDs, including PRO-DICLOFENAC, are administered less than 24 hours before or after treatment with methotrexate. Elevated blood concentrations of methotrexate may occur, increasing toxicity. | ||
| Oral Contraceptives | No drug interaction data are available for diclofenac sodium (delayed-release tablets) co-administered with oral contraceptives. | ||
| Oral Hypoglycemics | Pharmacodyna-mic studies | Pharmacodynamic studies have shown no potentiation of effect with concurrent administration with diclofenac; however, there are isolated reports of both hypoglycemic and hyperglycemic effects in the presence of diclofenac, which necessitated changes in the dosage of hypoglycemic agents. There have also been reports of metabolic acidosis when diclofenac was co-administered with metformin, particularly in the context of renal impairment. | Monitoring of the blood glucose level is recommended as a precautionary measure during concomitant therapy. Caution is recommended when co-prescribing PRO-DICLOFENAC with metformin. |
| Phenytoin | An expected increase in exposure to phenytoin. | When using phenytoin concomitantly with PRO-DICLOFENAC, monitoring of phenytoin plasma concentrations is recommended | |
| Probenecid | May decrease the excretion and increase serum concentrations of NSAIDs possibly enhancing effectiveness and/or increasing potential for toxicity. | Concurrent therapy of NSAIDs with probenecid requires close monitoring to be certain that no | |
| Diclofenac sodium (delayed-release tablets) | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| change in dosage is necessary. | |||
| Quinolone antibacterials | There have been isolated reports of convulsions which may have been due to concomitant use of quinolones and NSAIDs. | ||
| Selective serotonin reuptake inhibitors (SSRIs) | Concomitant administration of NSAIDs, including PRO-DICLOFENAC, and SSRIs may increase the risk of gastrointestinal ulceration and bleeding (see 7 WARNINGS AND PRECAUTIONS – Gastrointestinal (GI)). | ||
| Sulfinpyrazone | Caution is recommended when co-prescribing PRO-DICLOFENAC with CYP2C9 inhibitors (such as sulfinpyrazone, which could result in a significant increase in peak plasma concentrations and exposure to diclofenac. | Dosage adjustment may be required. | |
| Tacrolimus | Nephrotoxicity of tacrolimus may be increased because of the effect of NSAIDs on renal prostaglandins. | Therefore, it should be given at doses lower than those that would be used in patients not receiving tacrolimus. | |
| Voriconazole | Caution is recommended when co-prescribing PRO-DICLOFENAC with CYP2C9 inhibitors (such as voriconazole), which could result in a significant increase in peak plasma concentrations and exposure to diclofenac. | Dosage adjustment may be required. |
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug Laboratory Test Interactions
Diclofenac increases platelet aggregation time but does not affect bleeding time, plasma thrombin clotting time, plasma fibrinogen, or factors V and VII to XII. Statistically significant changes in prothrombin and partial thromboplastin times have been reported in normal volunteers. The mean changes were observed to be less than 1 second in both instances, and are unlikely to be clinically important.
Persistently abnormal or worsening renal, hepatic or hematological test values should be followed up carefully since they may be related to therapy.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Diclofenac sodium is a non-steroidal anti-inflammatory drug (NSAID). The mode of action is not fully known but it does not act through the pituitary-adrenal axis. Diclofenac sodium inhibits prostaglandin synthesis by interfering with the action of prostaglandin synthetase. This inhibitory effect may partially explain its actions.
10.2 Pharmacodynamics
The effects of diclofenac sodium (delayed-release tablets) are largely mediated by inhibition of cyclooxygenases (COXs, COX-1, COX-2). These enzymes are found throughout the body and produce prostaglandins, which are important mediators of pain, fever, and adaptive and protective reactions in many organs and (inflamed) tissues.
10.3 Pharmacokinetics
Absorption
In humans, orally-administered diclofenac sodium is rapidly and almost completely absorbed and distributed to blood, liver, and kidneys. The plasma concentrations show a linear relationship to the amount of drug administered. No accumulation occurs provided the recommended dosage intervals are observed.
Enteric coating may delay the onset of absorption from 50 mg tablets. Absorption occurs more rapidly when the drug is administered on an empty stomach (Tmax 2.5 hours), than with meals (Tmax 6 hours). The bioavailability remains the same under both conditions. The mean peak plasma concentration of 1.5 mcg/mL (5 mcmol/L) is attained, on average, 2 hours after ingestion of one 50 mg delayed-release tablet.
Distribution
Diclofenac sodium is extensively bound (99%) to serum albumin. The apparent volume of distribution is 0.12 to 0.17 L/kg. Single-dose (P.O. or I.M) studies in rheumatoid patients with joint effusions have shown that diclofenac is distributed to the synovial fluid, where Tmax occurs 2 to 4 hours after plasma Tmax. Synovial fluid concentrations exceed plasma levels within 4 to 6 hours of administration. This elevation above plasma concentrations can be maintained for up to 12 hours. The synovial fluid elimination half-life is at least 3 times greater than that for plasma.
Diclofenac was detected in a low concentration (100 ng/mL) in breast milk in one nursing mother. The estimated amount ingested by an infant consuming breast milk is equivalent to a 0.03 mg/kg/day dose (see 2 CONTRAINDICATIONS).
Metabolism
Diclofenac undergoes single and multiple hydroxylation and methoxylation, producing 3’-, 4’-, 5-hydroxy, 4’- 5-hydroxy and 3’-hydroxy-4’-methoxy derivatives of diclofenac. These phenolic metabolites are largely inactive, and (along with the parent compound) are mostly converted to glucuronide conjugates.
Elimination
Plasma clearance of diclofenac is 263 ± 56 mL/min. The mean terminal drug half-life in plasma is 1.8 hours after oral doses. In humans about 60% of the drug and its metabolites are eliminated in the urine and the balance through bile in the feces. More than 90% of an oral dose is accounted for in elimination products within 72 hours. About 1% of an oral dose is excreted unchanged in urine.
Special Populations and Conditions
Renal Impairment: In patients suffering from renal impairment, no accumulation of the unchanged active substance can be inferred from the single-dose kinetics when applying the usual dosage schedule. At a creatinine clearance of <10 mL/min, the calculated steady-state plasma levels of the hydroxy metabolites are about 4 times higher than in normal subjects. However, the metabolites are ultimately cleared through the bile. Although no accumulation of pharmacologically active substance seem to occur, caution is advised while administering PRO-DICLOFENAC to patients with impaired kidney function (i.e. GFR < 60 mL/min or 1 mL/sec) (see 7 WARNINGS AND PRECAUTIONS - Renal). PRO-DICLOFENAC is contraindicated in patients with severely impaired or deteriorating renal function (creatinine clearance < 30 mL/min (0.5 mL/s) (see 2 CONTRAINDICATIONS).
Hepatic impairment: In a study of ten patients with impaired hepatic function (chronic hepatitis and non-decompensated cirrhosis) receiving a single oral dose of 100 mg diclofenac sodium, the kinetics and metabolism of diclofenac, were the same as in patients without liver disease.
Pediatrics: PRO-DICLOFENAC is contraindicated in children and adolescents less than 16 years of age (see 2 CONTRAINDICATIONS).
Geriatrics: The ability of elderly subjects to absorb, metabolize and excrete diclofenac sodium (delayed-release tablets) does not appear to differ significantly from those of younger subjects.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15°C to 30°C) and protect from high humidity.
12 SPECIAL HANDLING INSTRUCTIONS
Not Applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Diclofenac sodium
Chemical name: Sodium-[o-[(2,6-dichlorophenyl)-amino]-phenyl]- acetate
Molecular formula and molecular mass: C14H10Cl2NNaO2; 318.1 g/mol
Structural formula:
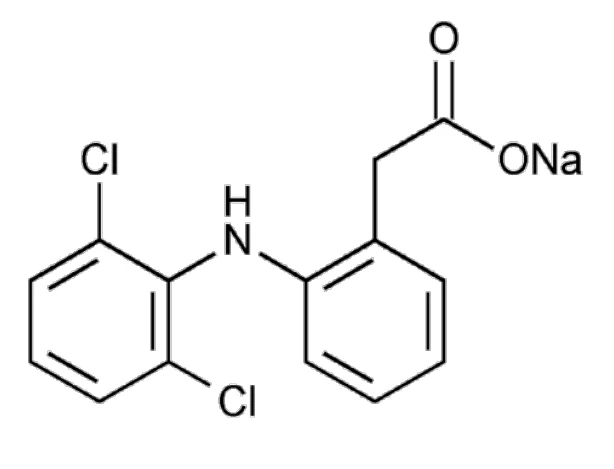
Physicochemical properties: White or slightly yellowish, slightly hygroscopic crystalline powder.
Solubility: Sparingly soluble in water, freely soluble in methanol, soluble in ethanol (96%), slightly soluble in acetone.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
The clinical trial data on which the original indication was authorized is not available.
14.2 Study Results
Randomized clinical trials with diclofenac sodium (delayed-release tablets) have NOT been designed to detect differences in cardiovascular adverse events in a chronic setting.
However, large population-based observational studies, meta-analyses and systematic reviews suggest that diclofenac use is associated with an increased risk of cardiovascular thrombotic events, including myocardial infarction and ischemic stroke. Results of some studies suggest that the CV risk is related to the dose and duration of diclofenac exposure and is greater in patients with risk factors for CV disease.
Large meta-analyses of randomized clinical trials show that diclofenac is associated with an increased risk of stroke, cardiovascular death, and death from any cause when compared with placebo. Data also suggest that diclofenac, particularly when used at a high dose (150 mg daily) may have a higher risk of thrombotic CV events than other NSAIDs.
The information provided below supported the original registration and its subsequent amendments. These studies were conducted in accordance with the standards and regulations in force at the time of conduct of these studies.
14.3 Comparative Bioavailability Studies
A bioavailability study was performed using normal human volunteers. The rate and extent of absorption after a single 50 mg oral dose of Diclofenac (diclofenac sodium) 25 mg and VOLTAREN 25 mg enteric coated tablets was measured and compared. The results are summarized as follows:
Table 5: Comparative Bioavailability Data for Enteric Coated Tablets
VOLTAREN 25 mg | Diclofenac 25 mg | % diffr. | |
|---|---|---|---|
| AUC0-12 (ng.hr/mL) | 1357.87 | 1338.55 | -1.4 |
| Cmax (ng/mL) | 1220.29 | 1236.58 | +1.3 |
| Tmax (hr) | 1.16 | 1.34 | +15.5 |
| t1/2 (hr) | 1.1 | 1.0 | -9.1 |
Enteric coated tablets
The therapeutic safety and efficacy of diclofenac sodium delayed-release tablets in arthritic conditions has been investigated in both short and long-term (three months) controlled clinical studies, followed by extended controlled and non-controlled studies. The majority of the comparative studies were double blind, within patient or between patient design, using placebo and indomethacin as controls. Acetylsalicylic acid (ASA), ibuprofen, phenylbutazone and acetaminophen were also used as comparative standards.
At time of approval, the safety and efficacy of diclofenac sodium delayed-release tablets for relief of the signs and symptoms of osteoarthritis and rheumatoid arthritis was demonstrated in short-term prospective comparative clinical trials conducted in 105 patients with osteoarthritis and 654 patients with rheumatoid arthritis. The controls used in these trials included: indomethacin, acetylsalicylic acid, acetaminophen and ibuprofen.
Several of the long-term double-blind, between patient studies comparing a three times daily dosing of diclofenac sodium delayed-release tablets to that of indomethacin were of three months duration. Patients received either drug at dosages ranging from 50 to 125 mg. In the treatment of patients with rheumatoid arthritis there was no clear difference between the treatment groups for therapeutic effect.
The safety and efficacy of diclofenac sodium delayed-release tablets compared to indomethacin for relief of the signs and symptoms of rheumatoid arthritis was also studied in longer-term studies of 6 to 30 months.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Diclofenac sodium is a phenyl-acetic acid derivative possessing anti-inflammatory activities as shown in various pharmacological models.
In vitro diclofenac sodium does not suppress proteoglycan biosynthesis in cartilage at concentrations equivalent to the concentrations reached in humans.
Anti-Inflammatory Activity in Rats
The anti-inflammatory potency was assessed by testing inhibition of paw edema (carrageenin solution and kaolin suspension) and reduction of adjuvant arthritis (Freund’s adjuvant).
| Preparation | Inhibition of edema induced by | |
|---|---|---|
Carrageenin (ED50 mg/kg) P.O.* | Kaolin (ED50 mg/kg) P.O.* | |
| Diclofenac sodium | 2.1 | 1.2 |
*determined by graphic interpolation from 3 or more doses.
Inhibition of Prostaglandin
A close correlation exists between certain febrile reactions and increased prostaglandin levels in the brain. Diclofenac (0.5 mcg/mL) reduces prostaglandin E2 formation which parallels antipyresis but does not induce hypothermia in the afebrile animal. The inhibition of prostaglandin synthesis in vitro (IC50 mcM/L) is 1.6.
Platelet Adhesiveness
At 15 mcg/mL, diclofenac reduces collagen-induced aggregation in rabbit platelets by 50%. ADP-induced adhesiveness at the same dosage is similarly affected. At 10 mg/kg P.O., diclofenac protected rabbits against the lethal action of thrombokinase without untoward effects.
Gastrointestinal Tolerability
In rats, oral doses of 17 mg/kg diclofenac sodium caused a blood loss of 150 mcL in 72 hours, as measured by the administration of 51Cr-labelled erythrocytes.
General Toxicology:
Acute Toxicity
| Species | Route | LD50 (mg/kg) | 95% Confidence Limits (mg/kg) |
|---|---|---|---|
| Mouse | P.O. I.V. | 389 133 | 197- 595 126 - 140 |
| Rat | P.O. I.V. | 173 106 | 133 - 213 80 - 132 |
| Guinea-pig | P.O. I.V. | 1110 127 | 950 - 1270 123 - 132 |
| Rabbit | P.O. | 194 | 151 - 259 |
The symptoms included bradycardia and convulsions.
The most frequent autopsy findings in animals that died were gastric irritation, perforation and their sequelae.
Long-Term Toxicity Studies
| SPECIES | PERIOD | DAILY DOSE mg/kg/day P.O. | ||
|---|---|---|---|---|
| No signs of intoxication | Reversible signs of toxicity, mainly GI Tract | Minimum lethal dose | ||
| Rat | 3 months 6 months 98 weeks | 2 1 0.25 | - 2 - | 6 4 1 |
| Dog | 3 months | - | 0.5 | 2 |
| Rhesus Monkey | 6 months | - | 5-15 | 75 |
| Baboon | 12 months | - | 5 | 10 |
Diclofenac sodium was given orally to male and female rats in doses of 0.25, 1.0 and 2.0 mg/kg/day from 59 weeks (high-dose groups) to 98 weeks (low- and intermediate-dose groups). High dose-related mortality rates resulted in termination of the high-dose administration after 59 weeks; the high mortality rate was caused by severe dose-dependent ulceration of the gastrointestinal tract, with perforated ulcers leading to peritonitis and sequelae. Body-weight gains and feed consumption of the treated groups were close to the controls. Hematologic patterns showing neutrophilic leucocytosis and anemia were seen in the high- and intermediate-dose groups, particularly females at weeks 52 and 98, respectively. Female animals tended to develop enlarged adrenals and eventually experienced depressed glucose and elevated alkaline phosphatase levels. Histology studies carried out on the tissues of the control, low- and intermediate-dose groups showed drug-related changes including mucosal ulceration of the small intestine, lymphangiectasis, lymphoid hypoplasia, and plasma cell hypoplasia of the mesenteric lymph nodes, foci of hepatocytic hyperplasia, adrenal cortical atrophy and prostatitis. No increase in tumour incidence was observed in the drug-treated groups as compared to the control group.
Diclofenac sodium was administered orally in gelatin capsules once daily to baboons (Papio spp.) at dose levels of 0, 5, 15 (reduced to 10 on day 254) and 50 (reduced to 30 on day 38) mg/kg/day for up to 52 weeks. At all dose levels studied, diclofenac caused ulceration of the gastrointestinal tract. Ulceration was confined to the colon in the low-dose group but was present in the stomach and small intestine also in the other two groups. Body weights were below controls. Constipation, with occasional episodes of diarrhea, was a marked feature. In all treated groups, there was a dose-related fall in serum albumin levels. Anemia and an increased ESR were observed in the high-dose group. In the recovery groups (control, low, and intermediate), no intestinal lesions were present. Food consumption and body-weight gains were within normal limits. Hematology parameters were comparable to controls and serum albumin levels returned towards normal values.
Carcinogenicity Studies
Long-term carcinogenicity studies in rats given diclofenac sodium up to 2 mg/kg/day have revealed no significant increases in tumour incidence. There was a positive dose-related trend with respect to adrenal medullary hyperplasia, mammary fibroadenomas and subcutaneous tissue fibromas in females, as well as of C-cell adenomas of the thyroid in males. The differences in the incidence between the various groups, including control, were small and were considered to reflect the variation in the spontaneous occurrence of these incidental lesions, common in old laboratory rats.
In a 2-year mouse study, only controls and animals at the two lower daily doses of 0.1 and 0.3 mg/kg showed survival sufficient for assessment of carcinogenic potential. The two higher daily doses of 1 and 2 mg/kg resulted in a shortening of lifespan, particularly in males, as a consequence of ulceration and/or perforation of the small intestine and therefore prevented evaluation. The known susceptibility of rodents to non-steroidal anti-inflammatory drugs, resulting in high mortality at dose levels close to the therapeutic dose, is considered to be a rodent-specific effect. Diclofenac sodium was not carcinogenic to mice under the conditions of this study.
Genotoxicity
Mutagenicity studies were carried out in vitro using bacteria with, and without microsomal activation, and in mammalian cells. Studies in vivo were also performed. Diclofenac sodium was not mutagenic in any of these test systems.
Reproductive and Developmental Toxicology
Rats: Doses of 2 and 4 mg/kg/day were given orally to male and female rats with no noticeable effect on fertility. Dosing was carried out during premating, mating, gestation, and lactation periods. At the higher dose, prolonged gestation and dystocia were observed. Embryotoxicity (low birth weight, failure to survive) was observed at both doses but it was minimal at 2 mg/kg/day. Post-natal survival and growth of pups from drug-treated animals were comparable to those of controls except for slightly retarded growth at the higher dose.
Mice and Rats: Teratology studies at oral doses of 2, 3, 10, and 20 mg/kg/day showed no teratogenic effects on fetuses. At the higher doses, pronounced gastrointestinal effects were observed in the dams and a marked toxic effect noted in fetuses (reduced birth weights and increased fetal deaths).
Rabbits: Pregnant females treated with oral doses of 5 or 10 mg/animal/day throughout the gestation period showed a dose-dependent increase in resorption rates, diminished fetus weights, and abnormal skeletal findings. Definite embryotoxicity was observed at the highest dose although there was no evidence to suggest teratogenicity.
Administration of NSAIDs (including diclofenac) inhibited ovulation in the rabbit and implantation and placentation in the rat, and led to premature closure of the ductus arteriosus in the pregnant rat. Maternally toxic doses of diclofenac were associated with dystocia, prolonged gestation, decreased fetal survival, and intrauterine growth retardation in rats. The slight effects of diclofenac on reproduction parameters and delivery as well as constriction of the ductus arteriosus in utero are pharmacologic consequences of this class of prostaglandin synthesis inhibitors (see 2 CONTRAINDICATIONS and 7.1 WARNINGS AND PRECAUTIONS – Special Populations).
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. VOLTAREN® and VOLTAREN® SR (diclofenac sodium) Suppositories 50 mg and Slow-Release Tablets 100 mg, submission control number 260554, Product Monograph, Novartis Pharmaceuticals Canada Inc. JUN 08, 2022.