


Product Monograph - Propofol Injection (Pfizer Canada)
INDICATIONS AND CLINICAL USE
Induction and Maintenance of General Anaesthesia
Propofol is a short-acting i.v. general anaesthetic agent that can be used for both induction and maintenance of anaesthesia as part of a balanced anaesthesia technique, including total intravenous anaesthesia (TIVA), for inpatient and outpatient surgery.
Propofol is also indicated for paediatric anaesthesia in children 3 years of age and older.
Conscious Sedation for Surgical and Diagnostic Procedures
Adults
Propofol, when administered i.v. as directed, can be used to initiate and maintain sedation in conjunction with local/regional anaesthesia in patients undergoing surgical procedures. Propofol may also be used for sedation during diagnostic procedures (see WARNINGS and PRECAUTIONS).
Pediatrics
Propofol is not recommended for sedation in children under the age of 18 during surgical/diagnostic procedures as safety and efficacy have not been established.
Sedation During Intensive Care
Adults
Propofol should only be administered to intubated, mechanically ventilated patients in the Intensive Care Unit (ICU) to provide continuous sedation and control of stress responses. In this setting, propofol should be administered only by or under the supervision of persons trained in general anaesthesia or critical care medicine.
Pediatrics
See CONTRAINDICATIONS
CONTRAINDICATIONS
Propofol is contraindicated:
- when general anaesthesia or sedation are contraindicated
- in patients with a known allergy and/or hypersensitivity to propofol or to lipid emulsions.
- for the sedation of children 18 years or younger receiving intensive care
WARNINGS
For general anaesthesia or sedation for surgical/diagnostic procedures, propofol should be administered only by persons trained in the administration of general anaesthesia and not involved in the conduct of surgical/diagnostic procedures. Patients should be continuously monitored and facilities for maintenance of a patent airway, artificial ventilation, and oxygen enrichment and circulatory resuscitation must be immediately available.
For sedation of intubated, mechanically ventilated, adult patients in the Intensive Care Unit (ICU), propofol should be administered only by persons trained in general anaesthesia or critical care medicine.
In the elderly, debilitated and ASA III or IV patients, rapid (single or repeated) bolus administration should not be used during general anaesthesia or sedation in order to minimize undesirable cardiorespiratory depression including hypotension, apnea, airway obstruction and/or oxygen desaturation.
Propofol should not be coadministered through the same i.v. catheter with blood or plasma because compatibility has not been established. In vitro tests have shown that aggregates of the globular component of the emulsion vehicle have occurred with blood/plasma/serum from humans and animals. The clinical significance is not known.
The neuromuscular blocking agents, atracurium and mivacurium should not be given through the same i.v. line as propofol without prior flushing.
Propofol should not be used in obstetrics including Caesarean section deliveries, because propofol crosses the placenta and may be associated with neonatal depression.
Propofol should not be used for Intensive Care Unit (ICU) sedation in patients who have severely disordered fat metabolism because the vehicle of propofol is similar to that of INTRALIPID 10%.
The restrictions that apply to INTRALIPID 10% should also be considered when using propofol in the ICU.
Extreme care should be used in administering propofol in patients with impaired left ventricular function because propofol may produce a negative inotropic effect.
Extreme care should be used in administering propofol in patients who are hypotensive, hypovolemic or in shock because propofol may cause excessive arterial hypotension.
Extreme care should be used in administering propofol in elderly, debilitated or other ASA III or IV patients.
Strict aseptic techniques must always be maintained during handling as propofol is a single-use parenteral product, for use in an individual patient, and contains no antimicrobial preservatives. The vehicle is capable of supporting rapid growth of microorganism (see PRECAUTIONS and DOSAGE AND ADMINISTRATION). Failure to follow aseptic handling procedures may result in microbial contamination causing fever/infection/sepsis which could lead to life-threatening illness.
Propofol lacks vagolytic activity and has been associated with reports of bradycardia, (occasionally profound) and also asystole. The intravenous administration of an anticholinergic agent before induction, or during maintenance of anaesthesia should be considered, especially in situations where vagal tone is likely to predominate or when propofol is used in conjunction with other agents likely to cause a bradycardia.
Since various manifestations of seizures have been reported during propofol anaesthesia, special care should be taken when giving the drug to epileptic patients.
Patients receiving propofol on an outpatient basis should not engage in hazardous activities requiring complete mental alertness such as driving a motor vehicle or operating machinery until the effects of propofol have completely subsided. Alcohol must be avoided.
PRECAUTIONS
General
In adults and children, attention should be paid to minimize pain on administration of propofol. Transient local pain during intravenous injection may be reduced by prior injection of i.v. lidocaine (1.0 mL of a 1% solution).
Patients should be continuously monitored for early signs of significant hypotension and/or bradycardia. Treatment may include increasing the rate of intravenous fluid, elevation of lower extremities, use of pressor agents or administration of anticholinergic agents (e.g. atropine) or use of plasma volume expanders. Apnea often occurs during induction and may persist for more than 60 seconds. Ventilatory support may be required. Because propofol is a lipid emulsion, caution should be exercised in patients with disorders of lipid metabolism such as primary hyperlipoproteinemia, diabetic hyperlipemia and pancreatitis.
When propofol is administered as a sedative for surgical or diagnostic procedures, patients should be continuously monitored by persons not involved in the conduct of the surgical/diagnostic procedure.
Oxygen supplementation should be immediately available and provided where clinically indicated; and oxygen saturation should be monitored in all patients. Patients should be continuously monitored for early signs of hypotension, apnea, airway obstruction and/or oxygen desaturation. These cardiorespiratory effects are more likely to occur following rapid initiation (loading) boluses or during supplemental maintenance boluses, especially in the elderly, debilitated and ASA III or IV patients.
Since propofol is rarely used alone, an adequate period of evaluation of the awakened patient is indicated to ensure satisfactory recovery from general anaesthesia or sedation prior to discharge of the patient from the recovery room or to home. Very rarely the use of propofol may be associated with the development of a period of post-operative unconsciousness, which may be accompanied by an increase in muscle tone. This may or may not be preceded by a period of wakefulness. Although recovery is spontaneous, appropriate care of an unconscious patient should be administered.
Intensive Care Unit (ICU) Sedation: Adults
Strict aseptic techniques must be followed when handling propofol as the vehicle is capable of supporting rapid growth of microorganisms (see WARNINGS and DOSAGE AND ADMINISTRATION).
The administration of propofol should be initiated as a continuous infusion and changes in the rate of administration made slowly (>5 min) in order to minimize hypotension and avoid acute overdosage.
Patients should be monitored for early signs of significant hypotension and/or cardiovascular depression, which may be profound. These effects are responsive to discontinuation of propofol, i.v. fluid administration, and/or vasopressor therapy.
As with other sedative medications, there is wide interpatient variability in propofol dosage requirements, and these requirements may change with time.
Patients who receive large doses of narcotics during surgery may require very small doses of propofol for appropriate sedation.
Abrupt discontinuation of propofol infusion prior to weaning should be avoided since, due to the rapid clearance of propofol, it may result in rapid awakening with associated anxiety, agitation and resistance to mechanical ventilation. Infusions of propofol should be adjusted to maintain a light level of sedation throughout the weaning process.
Since propofol is formulated in an oil-water emulsion, elevations in serum triglycerides may occur when PROPOFOL INJECTION is administered for extended periods of time. Patients at risk of hyperlipidemia should be monitored for increases in serum triglycerides or serum turbidity. Administration of propofol should be adjusted if fat is being inadequately cleared from the body. A reduction in the quantity of concurrently administered lipids is indicated to compensate for the amount of lipid infused as part of the propofol formulation; 1.0 mL of propofol contains approximately 0.1 g of fat (1.1 kcal).
The long-term administration of propofol to patients with renal failure and/or hepatic insufficiency has not been evaluated.
Intensive Care Unit (ICU) Sedation: Children under 18 years of age
See CONTRAINDICATIONS
Sedation during surgical/diagnostic procedures in children under 18 years of age
Propofol is not recommended for sedation during surgical/diagnostic procedures, in children under the age of 18, as safety and efficacy have not been established. See ADVERSE REACTIONS.
Paediatric Use for General Anaesthesia
In the absence of sufficient clinical experience, propofol is not recommended
for anaesthesia in children less than 3 years of age (see INDICATIONS AND CLINICAL USE and DOSAGE AND ADMINISTRATION).
Use in Pregnancy
Propofol should not be used during pregnancy. Propofol has been used during termination of pregnancy in the first trimester. Teratology studies in rats and rabbits show some evidence of delayed ossification or abnormal cranial ossification, however such developmental delays are not considered indicative of a teratogenic effect. Reproductive studies in rats suggest that administration of propofol to the dam adversely affects perinatal survival of the offspring.
Nursing Mothers
Propofol is not recommended for use in nursing mothers because preliminary findings indicate that it is excreted in human milk and the effects of oral absorption of small amounts of propofol are not known.
Use in the Elderly
Elderly patients may be more sensitive to the effects of propofol; therefore, the dosage of propofol should be reduced in these patients according to their condition and clinical response (see PHARMACOKINETICS and DOSAGE AND ADMINISTRATION).
Cardiac Anaesthesia
Propofol was evaluated in 328 patients undergoing coronary artery bypass graft (CABG). Of these patients 85% were males (mean age 61, range 32-83) and 15% were females (mean age 65, range 42-86).
The majority of patients undergoing CABG had good left ventricular function. Experience in patients with poor left ventricular function, as well as, in patients with hemodynamically significant valvular or congenital heart disease is limited.
Slower rates of administration should be utilized in premedicated patients, geriatric patients, patients with recent fluid shift, or patients who are hemodynamically unstable. Any fluid deficits should be corrected prior to administration of propofol. In those patients where additional fluid therapy may be contraindicated, other measures, e.g. elevation of lower extremities, or use of pressor agents, may be useful to offset the hypotension which is associated with the induction of anaesthesia with propofol.
Neurosurgical Anaesthesia
When using propofol in patients with increased intracranial pressure (ICP) or impaired cerebral circulation, significant decreases in mean arterial pressure should be avoided because of the resultant decreases in cerebral perfusion pressure. When increased ICP is suspected, hyperventilation and hypocarbia should accompany the administration of propofol. (See DOSAGE AND ADMINISTRATION).
Drug Interactions
Propofol has been used in association with spinal and epidural anaesthesia and with a range of premedicants, muscle relaxants, inhalational agents, analgesic agents and with local anaesthetic agents; no significant adverse interactions have been observed.
The induction dose requirements of propofol injection may be reduced in patients with intramuscular or intravenous premedication, particularly with narcotics and combinations of opioids and sedatives. These agents may increase the anesthetic or sedative effects of propofol and may result in more pronounced decreases in systolic, diastolic, and mean arterial pressures and cardiac output.
Other drugs that cause CNS depression (hypnotics/sedatives, inhalational anesthetics and opioids) can increase CNS depression induced by propofol. Morphine premedication with nitrous oxide in oxygen has been shown to decrease the necessary propofol injection maintenance infusion rate and therapeutic blood concentrations when compared to non-narcotic (lorazepam) premedication.
After suxamethonium and neostigmine, bradycardia and cardiac arrest may occur.
Leukoencephalopathy has been reported with administration of lipid emulsions such as propofol in patients on cyclosporine.
ADVERSE REACTIONS
Anaesthesia And Sedation For Surgical/Diagnostic Procedures
During induction of anaesthesia in clinical trials, hypotension and apnea occurred in the majority of patients. The incidence of apnea varied considerably, occurring in between 30 and 100% of patients depending upon premedication, speed of administration and dose (see CLINICAL PHARMACOLOGY). Decreases in systolic and diastolic pressures ranged between 10 and 28%, but were more profound in the elderly and in ASA III and IV patients. Excitatory phenomena occurred in up to 14% of adult patients and in 33 to 90% of paediatric patients; they consisted most frequently of spontaneous musculoskeletal movements and twitching and jerking of the hands, arms, feet or legs. Epileptiform movements including convulsions, myoclonus, and opisthotonus have occurred rarely, but a causal relationship with propofol has not been established. Flushing and rash have occurred in 10 to 25% of paediatric patients. Local pain occurred during intravenous injection of propofol at an incidence of 28% when veins of the dorsum of the hand were used and 5% when the larger veins of the forearm and the antecubital fossa were used. Propofol increased plasma glucose concentrations significantly, but no other significant changes in hematological or biochemical values were observed.
In the sedation clinical trials, the adverse reaction profile of propofol was similar to that seen during anaesthesia. The most common adverse reactions included hypotension, nausea, pain and/or hotness at injection site and headache. Respiratory events included upper airway obstruction, apnea, hypoventilation, dyspnea and cough.
Rarely, clinical features of anaphylaxis, which may include angioedema, bronchospasm, erythema and hypotension, occur following propofol administration.
There have been reports of post-operative fever.
Pulmonary oedema may be a potential side effect associated with the use of propofol.
As with other anaesthetics, sexual disinhibition may occur during recovery.
Intensive Care Unit (ICU) Sedation: Adults
The most frequent adverse reactions during Intensive Care Unit (ICU) sedation were hypotension (31.5%), hypoxia (6.3%), and hyperlipemia (5.5%). In some patients, hypotension was severe. Other reactions considered severe were observed in single patients and included ventricular tachycardia, decreased cardiac output, decrease in vital capacity and negative inspiratory force, increase in triglycerides, and agitation. Two patients with head injury suffered renal failure with severe increases in BUN accompanied in one patient by an increase in creatinine.
There have been rare reports of rhabdomyolysis when propofol has been administered at doses greater than 4 mg/kg/hr for ICU sedation.
Very rarely pancreatitis has been observed following the use of propofol for induction and maintenance of anaesthesia, and for intensive care sedation. A causal relationship has not been clearly established.
The following table compares the overall occurrence rates of adverse reactions in propofol patients from non-ICU and ICU clinical trials where the rate of occurrence was greater than 1%. Major differences include lack of metabolic/nutritional (hyperlipemia) and respiratory events in the non-ICU group and lack of nausea, vomiting, headache, movement and injection site events in the ICU group.
Non-lCU vs. ICU Adverse Events Occurring in Greater than 1% of PROPOFOL INJECTION Patients
| Body System | Event | Non-lCU | ICU |
|---|---|---|---|
| Number of patients | 2588 | 127 | |
| Cardiovascular | Hypotension | 7.38% | 31.50% |
| Bradycardia | 2.82% | 3.94% | |
| Hypertension | 2.82% | 1.57% | |
| Arrhythmia | 1.24% | 0.79% | |
| Tachycardia | 0.81% | 3.15% | |
| Cardiovascular Disorder | 0.23% | 2.36% | |
| Hemorrhage | 0.23% | 1.57% | |
| Atrial Fibrillation | 0.15% | 1.57% | |
| Cardiac Arrest | 0.12% | 3.15% | |
| Ventricular Tachycardia | 0.08% | 1.57% | |
| Digestive | Nausea | 14.57% | 0% |
| Vomiting | 8.31% | 0% | |
| Abdominal Cramping | 1.24% | 0% | |
| Nervous | Movement | 4.44% | 0% |
| Headache | 1.78% | 0% | |
| Dizziness | 1.70% | 0% | |
| Twitching | 1.47% | 0% | |
| Agitation | 0.19% | 2.36% | |
| Intracranial Hypertension | 0% | 3.94% | |
| Metabolic/Nutritional | Hyperlipemia | 0.08% | 5.51% |
| Acidosis | 0.04% | 1.57% | |
| Creatinine Increased | 0% | 2.36% | |
| BUN Increased | 0% | 1.57% | |
| Hyperglycemia | 0% | 1.57% |
| Body System | Event | Non-lCU | ICU |
|---|---|---|---|
| Hypernaturemia | 0% | 1.57% | |
| Hypokalemia | 0% | 1.57% | |
| Respiratory | Dyspnea | 0.43% | 1.57% |
| Hypoxia | 0.08% | 6.30% | |
| Acidosis | 0% | 1.57% | |
| Pneumothorax | 0% | 1.57% | |
| Other | Injection Site: | ||
| Pain | 8.11% | 0% | |
| Burning/stinging | 7.77% | 0% | |
| Fever | 1.89% | 2.36% | |
| Hiccough | 1.78% | 0% | |
| Cough | 1.55% | 0% | |
| Rash | 1.20% | 1.57% | |
| Anemia | 0.35% | 1.57% | |
| Kidney Failure | 0% | 1.57% |
Adverse reactions reported at an incidence of 1.0% or less during anaesthesia and sedation for surgical/diagnostic procedures:
Body as a Whole: Asthenia, awareness, chest pain, extremity pain, increased drug effect, neck rigidity/stiffness, trunk pain, perinatal disorder.
Cardiovascular System: Significant hypotension, premature atrial contractions, premature ventricular contractions, tachycardia, syncope, abnormal ECG, bigeminy, edema, atrioventricular heart block, bleeding, bundle branch block, myocardial infarction, myocardial ischemia, ST segment depression, ventricular fibrillation.
Respiratory System: Burning in throat, tachypnea, dyspnea, upper airway obstruction, wheezing, bronchospasm, laryngospasm, hypoventilation, hyperventilation, sneezing, pharyngitis.
Excitatory: Hypertonia, dystonia, rigidity, tremor.
Central Nervous System: Confusion, dizziness, paresthesia, somnolence, shivering, abnormal dreams, agitation, delirium, euphoria, fatigue, amorous behaviour, anxiety, bucking/jerking/thrashing, combativeness, depression, emotional lability, hallucinations, hypotonia, hysteria, insomnia, moaning, neuropathy, tremor.
Injection Site: Phlebitis, thrombosis, hives/itching, redness/discolouration.
Digestive System: Hypersalivation, dry mouth, diarrhea, enlarged parotid, swallowing.
Hematologic/Lymphatic: Coagulation disorder, leukocytosis.
Metabolic/Nutritional: Hyperkalemia
Skin and Appendages: Flushing/rash (for incidence in children, see above), urticaria, pruritus, conjunctival hyperemia, diaphoresis.
Special Senses: Diplopia, amblyopia, tinnitus, ear pain, eye pain, nystagmus, taste perversion.
Musculoskeletal: Myalgia.
Urogenital: Urine retention, discolouration of urine.
Adverse reactions reported at an incidence of 1% or less during ICU sedation.
Cardiovascular: Arrhythmia, extrasystole, heart block, right heart failure, bigeminy, ventricular fibrillation, heart failure, myocardial infarction.
Respiratory: Lung function decreased, respiratory arrest.
Central Nervous System: Seizure, thinking abnormal, akathisia, chills, anxiety, confusion, hallucinations.
Digestive: Ileus, hepatomegaly.
Metabolic/Nutritional: Osmolality increased, dehydration.
Urogenital: Green urine, urination disorder, oliguria.
Body as a Whole: Sepsis, trunk pain, whole body weakness.
Post Marketing Experience
Clinical trial
A randomized, controlled, clinical trial that evaluated the safety and effectiveness of propofol versus standard sedative agents (SSA) in pediatric ICU patients has been conducted. In that study a total of 327 pediatric patients were randomized to receive either propofol 2% (113 patients), propofol 1%
(109 patients), or an SSA (eg, lorazepam, chloral hydrate, fentanyl, ketamine, morphine, or phenobarbital).
Propofol therapy was initiated at an infusion rate of 5.5 mg/kg/hr and titrated as needed to maintain sedation at a standardized level. The results of the study showed an increase in the number of deaths in patients treated with propofol as compared to SSAs. A total of 25 patients died during the trial or within the 28-day follow-up period:12 (11%) in the propofol 2%treatment group, 9 (8%) in the propofol 1% treatment group, and 4 (4%) in the SSA treatment group.
Spontanoeus reports and publications
There are several publications identifying an association in adults between high infusion rates (greater than 5 mg/kg/h) of propofol for more than 48 hours in ICUs and a potentially fatal constellation of adverse events characterized by metabolic acidosis, rhabdomyolysis and cardiovascular collapse.
The majority of the above-reported cases occurred in adults with head injury. These patients were treated with propofol at infusion rates greater than 5 mg/kg/h in an attempt to control intracranial hypertension. It is unclear at this time whether propofol at these high infusion rates can provide enhanced intracranial pressure reduction. A causal relationship between these adverse events and propofol and/or the lipid carrier cannot yet be established.
Similar findings were first reported in the literature in 1992 in children who received high doses of propofol in the ICU. Since the 1992 publication, several similar reports have been published, including an article that summarized 18 cases of children who received propofol infusions and suffered serious adverse events, including death.
Drug Abuse and Dependence
Rare cases of self administration of propofol by health care professionals have been reported, including some fatalities.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
To date, there is no known case of acute overdosage, and no specific information on emergency treatment of overdosage is available. If accidental overdosage occurs, propofol administration should be discontinued immediately. Overdosage is likely to cause cardiorespiratory depression. Respiratory depression should be treated by artificial ventilation with oxygen. Cardiovascular depression may require repositioning of the patient by raising the patient's legs, increasing the flow rate of intravenous fluids and if severe may require the administration of plasma volume expanders and/or pressor agents.
DOSAGE AND ADMINISTRATION
Strict aseptic techniques must always be maintained during handling as propofol is a single-use parenteral product, for use in an individual patient, and contains no antimicrobial preservatives. The vehicle is capable of supporting rapid growth of microorganisms. Failure to follow aseptic handling procedures may result in microbial contamination causing fever/infection/sepsis which could lead to life-threatening illness.
Propofol should be shaken well before use.
General
Dosage and rate of administration should be individualized and titrated to the desired effect according to clinically relevant factors including preinduction and concomitant medications, age, ASA status and level of debilitation of the patient. In heavily premedicated patients, both the induction and maintenance doses should be reduced.
Induction of General Anaesthesia
Most adult patients under 55 years of age and classified ASA I and II are likely to require 2.0 to 2.5 mg/kg of propofol for induction when unpremedicated or when premedicated with oral benzodiazepines or intramuscular narcotics. For induction, it is recommended that propofol should be titrated (approximately 40 mg every 10 seconds by bolus injection or infusion) against the response of the patient until the clinical signs show the onset of general anaesthesia.
It is important to be familiar and experienced with the appropriate intravenous use of propofol before treating elderly, debilitated and/or adult patients in ASA Physical Status Classes III and IV. These patients may be more sensitive to the effects of propofol; therefore, the dosage of propofol should be reduced in these patients by approximately 50% (20 mg every 10 seconds) according to their condition and clinical response. A rapid bolus should not be used as this will increase the likelihood of undesirable cardiorespiratory depression including hypotension, apnea, airway obstruction and/or oxygen desaturation (see WARNINGS, PRECAUTIONS and DOSAGE GUIDE).
During cardiac anaesthesia, a rapid bolus induction should be avoided. A slow rate of approximately 20 mg every 10 seconds until induction onset (0.5 to 1.5 mg/kg) should be used.
Most children over 8 years of age require approximately 2.5 mg/kg of propofol for induction of anaesthesia. Children 3 to 8 years of age may require somewhat higher doses, however the dose should be titrated by administering propofol slowly until the clinical signs show the onset of anaesthesia. Propofol is not recommended for induction of anaesthesia in children less than 3 years of age. Reduced dosage is recommended for children of ASA Classes III and IV.
Additionally, as with most anaesthetic agents, the effects of propofol may be potentiated in patients who have received intravenous sedative or narcotic premedications shortly prior to induction.
Maintenance of General Anaesthesia
Anaesthesia can be maintained by administering propofol by infusion or intermittent i.v. bolus injection. The patient's clinical response will determine the infusion rate or the amount and frequency of incremental injections.
When administering propofol by infusion, drop counters, syringe pumps or volumetric pumps must be used to provide controlled infusion rates.
Continuous Infusion
Propofol 0.10 to 0.20 mg/kg/min (6 - 12 mg/kg/h) administered in a variable rate infusion with 60% - 70% nitrous oxide and oxygen provides anaesthesia for patients undergoing general surgery. Maintenance by infusion of propofol should immediately follow the induction dose in order to provide satisfactory or continuous anaesthesia during the induction phase. During this initial period following the induction injection higher rates of infusion are generally required (0.15 - 0.20 mg/kg/min; 9 - 12 mg/kg/h) for the first 10 to 15 minutes. Infusion rates should subsequently be decreased by 30% - 50% during the first half-hour of maintenance. Changes in vital signs (increases in pulse rate, blood pressure, sweating and/or tearing) that indicate a response to surgical stimulation or lightening of anaesthesia may be controlled by the administration of propofol 25 mg (2.5 mL) to 50 mg (5.0 mL) incremental boluses and/or by increasing the infusion rate. If vital sign changes are not controlled after a five minute period, other means such as a narcotic, barbiturate, vasodilator or inhalation agent therapy should be initiated to control these responses.
For minor surgical procedures (ie. body surface) 60% to 70% nitrous oxide can be combined with a variable rate propofol infusion to provide satisfactory anaesthesia. With more stimulating surgical procedures (ie. intra-abdominal) supplementation with i.v. analgesic agents should be considered to provide a satisfactory anaesthetic and recovery profile. When supplementation with nitrous oxide is not provided, administration rate(s) of propofol and/or opioids should be increased in order to provide adequate anaesthesia.
Infusion rates should always be titrated downward in the absence of clinical signs of light anaesthesia until a mild response to surgical stimulation is obtained in order to avoid administration of propofol at rates higher than are clinically necessary. Generally, rates of 0.05 to 0.10 mg/kg/min should be achieved during maintenance in order to optimize recovery times.
During cardiac anaesthesia, when propofol is used as the primary agent, maintenance infusion rates should not be less than 0.10 mg/kg/min and should be supplemented with analgesic levels of continuous opioid administration. When an opioid is used as the primary agent, propofol maintenance rates should not be less than 0.05 mg/kg/min. Higher doses of propofol will reduce the opioid requirements.
For children, the average rate of administration varies considerably but rates between 0.10 to 0.25 mg/kg/min (6 - 15 mg/kg/h) should achieve satisfactory anaesthesia. These infusion rates may be subsequently reduced depending on patient response and concurrent medication.
Intermittent Bolus
Increments of propofol 25 mg (2.5 mL) to 50 mg (5.0 mL) may be administered with nitrous oxide in patients undergoing general surgery. The incremental boluses should be administered when changes in vital signs indicate a response to surgical stimulation or light anaesthesia.
Propofol has been used in conjunction with a wide variety of agents commonly used in anaesthesia such as atropine, scopolamine, glycopyrrolate, diazepam, depolarizing and nondepolarizing muscle relaxants, and narcotic analgesics, as well as with inhalational and regional anaesthetic agents. No pharmacological incompatibilities have been encountered.
Lower doses of propofol may be required when used as an adjunct to regional anaesthesia.
Sedation During Surgical Or Diagnostic Procedures: Adults
When propofol is administered for sedation, rates of administration should be individualized and titrated to clinical response. In most patients, the rates of propofol administration will be approximately 25 to 30% of those used for maintenance of general anaesthesia.
During initiation of sedation, slow injection or slow infusion techniques are preferable over rapid bolus administration. During maintenance of sedation, a variable rate infusion is preferable over intermittent bolus dose administration.
Initiation of sedation
Slow injection: most adult patients will generally require 0.5 to 1.0 mg/kg administered over 3 to 5 minutes and titrated to clinical response.
In the elderly, debilitated, hypovolemic and ASA III or IV patients, the dosage of propofol should be reduced to approximately 70 to 80% of the adult dosage and administered over 3 to 5 minutes.
Infusion: sedation may be initiated by infusing propofol at 0.066 to 0.100 mg/kg/min (4.0 - 6.0 mg/kg/h) and titrating to the desired level of sedation while closely monitoring respiratory function.
Maintenance of sedation
Patients will generally require maintenance rates of 0.025 to 0.075 mg/kg/min (1.5 - 4.5 mg/kg/h) during the first 10 to 15 minutes of sedation maintenance.
Infusion rates should always be titrated downward in the absence of clinical signs of light sedation until mild responses to stimulation are obtained in order to avoid sedative administration of propofol at rates higher than are clinically necessary.
In addition to the infusion, bolus administration of 10 to 15 mg may be necessary if a rapid increase in sedation depth is required.
In the elderly, debilitated, hypovolemic and ASA III or IV patients, the rate of administration and the dosage of propofol should be reduced to approximately 70 to 80% of the adult dosage according to their condition, responses, and changes in vital signs. Rapid (single or repeated) bolus dose administration should not be used for sedation in these patients (see WARNINGS).
Intensive Care Unit (ICU) Sedation
Propofol should be individualized according to the patient's condition and response, blood lipid profile, and vital signs.
Adults
For intubated, mechanically ventilated, adult patients, Intensive Care Unit (ICU) sedation should be initiated slowly with a continuous infusion in order to titrate to desired clinical effect and minimize hypotension. When indicated, initiation of sedation should begin at 0.005 mg/kg/min (0.3 mg/kg/h). The infusion rate should be increased by increments of 0.005 to 0.010 mg/kg/min (0.3 - 0.6 mg/kg/h) until the desired level of sedation is achieved. A minimum period of 5 minutes between adjustments should be allowed for onset of peak drug effect.
Most adult patients require maintenance rates of 0.005 to 0.050 mg/kg/min (0.3 - 3.0 mg/kg/h). Dosages of propofol should be reduced in patients who have received large dosages of narcotics. As with other sedative medications, there is interpatient variability in dosage requirements and these requirements may change with time. (See DOSAGE GUIDE).
Bolus administration of 10 to 20 mg should only be used to rapidly increase sedation depth in patients where hypotension is not likely to occur. A rapid bolus should not be used as this will increase the likelihood of hypotension. Patients with compromised myocardial function, intravascular volume depletion or abnormally low vascular tone (e.g. sepsis) may be more susceptible to hypotension.
Children under 18 years of age
Propofol is contraindicated for the sedation of children 18 years or younger receiving intensive care.
DOSAGE GUIDE
INDICATION DOSAGE AND ADMINISTRATION
INDUCTION OF GENERAL ANAESTHESIA
Dosage should be individualized.
Adult Patients Less than 55 Years of Age: Are likely to require 2.0 to 2.5 mg/kg (approximately 40 mg every 10 seconds until induction onset).
Elderly, Debilitated and/or Adult ASA III or IV Patients: Are likely to require 1.0 to 1.5 mg/kg (approximately 20 mg every 10 seconds until induction onset) but dose should be carefully titrated to effect.
Cardiac Anaesthesia: Patients are likely to require 0.5 to 1.5 mg/kg (approximately 20 mg every 10 seconds until induction onset).
Neurosurgical Patients: Are likely to require 1.0 to 2.0 mg/kg (approximately 20 mg every 10 seconds until induction onset).
Paediatric Patients: Children over 8 years of age require approximately 2.5 mg/kg. Children 3 to 8 years of age may require somewhat higher doses but doses should be titrated slowly to the desired effect. In the absence of sufficient clinical experience, propofol is not recommended for anaesthesia in children less than 3 years of age (see INDICATIONS AND CLINICAL USE and PRECAUTIONS). Reduced dosage is recommended for children of ASA Classes III and IV.
MAINTENANCE OF GENERAL ANAESTHESIA
Infusion: Variable rate infusion titrated to the desired clinical effect.
Adult Patients Less than 55 Years of Age: Generally, 0.10 to 0.20 mg/kg/min (6 to 12 mg/kg/h).
Elderly, Debilitated and/or Adult ASA III or IV Patients: Generally, 0.05 to 0.10 mg/kg/min (3 to 6 mg/kg/h).
Cardiac Anaesthesia: Most patients require:
Primary propofol with Secondary Opioid - 0.10 to 0.15 mg/kg/min (6 to 9 mg/kg/h).
Low Dose propofol with Primary Opioid - 0.05 to 0.10 mg/kg/min (3 to 6 mg/kg/h).
Neurosurgical Patients: Generally, 0.10 to 0.20 mg/kg/min (6 to 12 mg/kg/h).
Paediatric Patients: Generally, 0.10 to 0.25 mg/kg/min (6-15 mg/kg/h).
Intermittent Bolus: Increments of 25 mg to 50 mg, as needed.
SURGICAL/DIAGNOSTIC SEDATION
Dosage and rate should be individualized and titrated to the desired clinical effect.
Adult Patients Less than 55 Years of Age: Are likely to require 0.5 to 1.0 mg/kg over 3 to 5 min to initiate sedation, followed by 0.025 to 0.075 mg/kg/min (1.5 - 4.5 mg/kg/h) for continued sedation.
Elderly, debilitated, hypovolemic and/or ASA III or IV patients: The dosage and rate of administration may need to be reduced in these patients by approximately 20 to 30% (see previous section for details).
Paediatric Patients: propofol is not recommended for sedation during surgical/diagnostic procedures in children under the age of 18, as safety and efficacy have not been established (see INDICATIONS).
INITIATION AND MAINTENANCE OF ICU SEDATION IN INTUBATED, MECHANICALLY VENTILATED, ADULT PATIENTS
Dosage and rate of infusion should be individualized.
Adult Patients: For initiation, most patients require an infusion of 0.005 mg/kg/min (0.3 mg/kg/h) for at least 5 minutes. Subsequent increments of 0.005 to 0.010 mg/kg/min (0.3 - 0.6 mg/kg/h) over 5 to 10 minutes may be used until desired level of sedation is achieved.
For maintenance, most patients require 0.005 to 0.050 mg/kg/min (0.3 - 3.0 mg/kg/h).
The long-term administration of propofol to patients with renal failure and/or hepatic insufficiency has not been evaluated.
Paediatric Patients: See CONTRAINDICATIONS
Compatibility and Stability
Propofol should not be mixed with other therapeutic agents prior to administration.
The neuromuscular blocking agents, atracurium and mivacurium should not be given through the same i.v. line as propofol without prior flushing.
Dilution Prior to Administration
When propofol is diluted prior to administration, it should only be diluted with 5% Dextrose Injection, USP, and it should not be diluted to a concentration less than 2 mg/mL because it is an emulsion. Dilutions should be prepared aseptically immediately before administration and should not be used beyond 6 hours of preparation. In diluted form it has been shown to be more stable when in contact with glass than with plastic (95% potency after 2 hours of running infusion in plastic).
Administration into a Running I.V. Catheter
Compatibility of propofol with the co-administration of blood/serum/plasma has not been established (see WARNINGS). Propofol has been shown to be compatible with the following intravenous fluids when administered into a running i.v. catheter:
- 5% Dextrose Injection, USP
- Lactated Ringers Injection, USP
- Lactated Ringers and 5% Dextrose Injection
- 5% Dextrose and 0.45% Sodium Chloride Injection, USP
- 5% Dextrose and 0.2% Sodium Chloride Injection, USP
When administering PROPOFOL INJECTION by infusion, drop counters, syringe pumps or volumeric pumps must be used to provide controlled infusion rates.
Handling Procedures
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration whenever solution and container permit.
Do not freeze. Do not use if there is evidence of separation of the phases of the emulsion.
Aseptic techniques must be applied to the handling of the drug. Propofol contains no antimicrobial preservatives and the vehicle supports growth of microorganisms. When propofol is to be aspirated it should be drawn aseptically into a sterile syringe or intravenous administration set immediately after breaking the vial seal. Administration should commence without delay. Asepsis must be maintained for both propofol and the infusion equipment throughout the infusion period. Any drugs or fluids added to the infusion line must be administered close to the cannula site. Propofol must not be administered via a microbiological filter.
Propofol and any syringe containing propofol are for single use in an individual patient only. If a vial is utilized for infusion, both the reservoir of propofol and the infusion line must be discarded and replaced as appropriate at the end of the procedure or at 12 hours, whichever is sooner. (When using DILUTED propofol see Dilution Prior to Administration).
Since propofol contains no preservative or bacteriostatic agents, any unused portions of propofol or solutions containing propofol should be discarded at the end of the surgical procedure.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: propofol
Chemical Names: 2,6-diisopropylphenol or 2,6-bis(1-methylethyl)phenol
Chemical Structure:
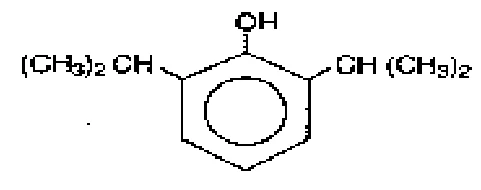
Molecular Formula: C12H18O
Molecular Weight: 178.27
Physical Form: Colourless to pale straw-coloured liquid at room temperature.
Solubility: Practically insoluble in water. Completely miscible in all proportions with the following solvents at 20°C: acetone, 95% ethanol, chloroform, cyclohexane, diethyl ether, n-hexane, methanol, isooctane.
pKa: 11.1 in water
Melting Point: 18°C
Composition
Propofol is a white, oil in water emulsion. Each mL contains 10 mg of propofol for i.v. administration. In addition to the active component, propofol, the formulation also contains soybean oil (100 mg/mL), glycerol (22.5 mg/mL), egg phosphatide (12 mg/mL) and water for injection with sodium hydroxide to adjust pH. It is isotonic with a pH of 6.5-8.5.
Stability and Storage Recommendations
Store between 15°C and 25°C; do not freeze. The emulsion should be visually inspected for particulate matter, emulsion separation and discolouration prior to use. Any unused portions of propofol or solutions containing propofol should be discarded at the end of the surgical procedure.
AVAILABILITY OF DOSAGE FORM
Availability
PROPOFOL INJECTION is available in a ready-to-use 20 mL glass infusion vial (List 3853) for single infusion only. Each vial contains 10 mg/mL of propofol. Carton of 5 x 20 mL vials.
PHARMACOLOGY
Propofol was administered as a 1% w/v aqueous emulsion containing 10% w/v soya bean oil, 1.2% w/v egg phosphatide and 2.25% w/v glycerol. Control animals received the vehicle. The drug was administered by the intravenous route unless otherwise indicated.
- 1)
Anaesthetic Activity
Mice
The HD50, i.e., the dose that abolished the righting reflex in 50% of the animals for 30 seconds or more, was 12.8 mg/kg. Induction times were significantly affected by the rate of injection. Namely, they were 4.6 and 12.6 seconds, respectively, after the injection of a 15 mg/kg dose over one or ten seconds. However, the rate of injection did not influence sleeping times or the duration of apnea to a significant degree. To evaluate the effect of repeated bolus injections, propofol was administered at a 25 mg/kg dose, which in previous experiments was shown to induce anaesthesia for approximately 4 minutes. When the mice regained their righting reflex, they were re-injected after an interval of 30 seconds. This procedure was repeated until the animals received a total of 10 injections. Sleeping times increased with subsequent injections. The mean sleeping time was 4.6 minutes after the first injection and 19.4 minutes after the 8th injection indicating a slight cumulative effect.
Rats
In rats propofol produced a very steep dose-response curve, thus, only a range could be established for the HD50 (5.0 to 7.5 mg/kg). In this species, the anaesthetic effect was sex dependent, female rats having significantly longer sleeping times than male rats. In a separate experiment, utilizing female rats, anaesthesia was induced by a 7.5-10 mg/kg bolus dose of propofol and then maintained by the infusion of a 50 mg/kg/h dose. Anaesthesia was maintained for either one or two hours. The experiment established that heart rate and rate of respiration remained stable over the two hour infusion and did not change vis à vis baseline. Recovery times were slightly longer after the two hour infusion but were significantly shorter in propofol-treated rats than in alphaxalone/alphadolone-treated animals.
- 2)
Cardiovascular and Respiratory Effects
The experiments were conducted in mini-pigs. Propofol was evaluated at a 3.75 mg/kg dose injected over a 30 second interval. All the changes mentioned were statistically significant. Maximal changes from baseline are indicated in brackets. Mean arterial pressure decreased (107→78 mmHg) and was accompanied by reflex tachycardia (105→189 beats/min). Rate of respiration became depressed (27.5→21.5 breaths/min) and was accompanied by decreased PO2 (94.6→79.1 mmHg) and increased PCO2 (40.4→44.3 mmHg). Total peripheral resistance decreased (2919→1902 dyne. sec. cm-5) while cardiac output increased (2.67→3.58 L/min). The hypotensive effect of propofol is probably due to reduced peripheral resistance.
- 3)
Drug Interaction Studies
- a)
Preanaesthetic Medications
The experiments were conducted in mice. Diazepam, droperidol, promethazine, atropine, amylobarbital or papaveretum were administered subcutaneously, 30 minutes before the induction of anaesthesia with propofol (18 mg/kg). At the doses tested, only diazepam (2 mg/kg) enhanced significantly the duration of sleep. Recovery times were prolonged significantly by both diazepam and atropine (1 mg/kg).
- b)
Drugs Used in Balanced Anaesthesia
The experiments were conducted in dogs. Anaesthesia was induced by propofol and maintained by halothane. In the first set of experiments, the dogs were premedicated with atropine and fentanyl, while in the second set of experiments premedication was not employed. The following changes were observed in the presence of atropine and fentanyl: the induction doses of propofol were smaller (4.3 versus 7.9 mg/kg) and the concentration of halothane lower (1% versus 2%). However, both tachycardia and apnea occurred. Recovery times were shorter, probably due to the lower dose of propofol.
- a)
- 4)
The Effect of Propofol on Adrenocortical Function
The effect of propofol was compared to that of etomidate on ACTH-stimulated cortisol production in two in vitro models, namely in guinea pig and bovine adrenal cells. Propofol affected cortisol production only at the 10-4M concentration, while etomidate exerted an activity at 10-7M concentration.
In propofol-anaesthetized rats, 5 μg ACTH elicited serum corticosterone levels of 37.2 μg/100 mL while in etomidate-anaesthetized rats, the value was 8.5 μg/100 mL. Since basal corticosterone levels ranged between 5.6 and 10.4 μg/100 mL, ACTH did not elevate corticosterone levels in etomidate-anaesthetized rats. The experiments indicated that propofol is only a very weak inhibitor of adrenal steroidogenesis.
- 5)
In Vitro Studies
The aim of the experiments was to establish whether or not propofol exerts agonist or antagonist activity at various receptor sites. Only weak antagonist activities were detected at the β1 adrenoceptor, muscarinic cholinergic and 5-HT2 receptor sites. The pA2 values were 5.23, 5.43 and 5.18, respectively. At the same receptor sites the pA2 values for the standards were as follow: propranolol: 8.55, hyoscine: 9.38 and cyproheptadine: 8.2.
- 6)
Behavioral Studies
The behaviour of mice was observed following the administration of 30, 100 and 300 mg/kg oral doses of propofol. None of the animals were anaesthetized by these oral doses. The lowest dose had no behavioral effects. The mid dose decreased locomotion. The highest dose produced sedation, ptosis, ataxia, slight tremors, hypothermia and decreased rate of respiration.
- 7)
Miscellaneous Studies
- a)
Histamine Release
The administration of propofol, 7.5 mg/kg to dogs was not associated either with elevated plasma histamine levels or with clinical signs indicative of histamine release.
- b)
Hypersensitivity
Mini-pigs were anaesthetized with propofol, 2.5 mg/kg on two occasions at one week interval. No reactions, indicative of an anaphylactoid response were seen following the second injection.
- c)
Bronchomotor Tone
In the guinea-pig Konzett-Rossler technique, propofol (2.5 mg/kg) was devoid of both bronchoconstrictor and bronchodilator activity. The latter effect was tested against histamine-induced bronchoconstriction.
- d)
Blood Coagulation
ADP-induced platelet aggregation was similar in propofol (15 mg/kg) and saline-treated rats. Whole blood clotting times were similar in propofol (15 mg/kg) and saline-treated rats.
- e)
Renal Function
In rats, propofol, 15 mg/kg, had little effect on urine volume and urinary potassium and chloride levels. Sodium levels were slightly but significantly decreased (81% of control).
- a)
- f)
Cat Nictitating Membrane Preparation
Propofol, in a dose-range of 0.5 to 5.0 mg/kg, did not affect the contraction of the nictitating membrane, evoked by preganglionic stimulation of the cervical sympathetic nerve. The study indicates that propofol is devoid of ganglion blocking activity. Furthermore, propofol did not affect the pressor effect of norepinephrine, indicating a lack of effect on α-adrenoceptors.
PHARMACOKINETICS
Pharmacokinetic studies were carried out in male and female rats, male and female dogs and female rabbits. In all species, following a single intravenous dose, the pharmacokinetics fit a two-compartment open model with a very rapid distribution phase (t½ α: 1.2-4.9 min) and a rapid elimination phase (t½ β : 15-27 min; Table 1). In rats, but not in dogs, a sex difference was observed regarding several pharmacokinetic parameters.
Table 1 Pharmacokinetic Parameters Following a Single Intravenous Dose of Propofol | |||||||
| Species | Dose | Sex (mg/kg) | Max Propofol Blood Conc. (μg/mL) | AUC (μg.mL-1min) | t1/2β (min) | Sleeping Time (min) | Waking Propofol Conc. (μg/mL) |
| Rat | 5 10 15 | M F F (preg.) M F M F | 0.57 2.55 2.35 4.3 11.3 11.3 20.8 | 13.7 34.4 34.8 48.3 87.9 97.2 174.9 | 23 22 25 23 18 22 27 | Rats did not sleep 6.1 7.9 9.6 11.4 | 1.7 2.8 1.0 3.7 |
| Dog | 5 10 30 (infusion) | M & F M & F M & F | 2.35 4.31 Css : 6.5 | 40.3 71.4 -- | 16 21 33 | ||
| Rabbit | 5 | F | 2.60 | 14.4 | 15 | ||
In rats, maximal mean propofol blood concentrations as well as AUC values and propofol blood concentrations at awakening were significantly higher in females. However, elimination half-lives were the same for the two sexes. Both propofol blood concentrations and AUC values increased in a dose-dependent manner. In contrast, waking blood concentrations were independent of the dose. In dogs, the pharmacokinetic parameters were determined either after a bolus injection of propofol (5 and 10 mg/kg) or in an infusion model where an initial bolus dose of 7.5 mg/kg was followed by an infusion at the rate of 0.5 mg/kg/min for 45 minutes (22.5 mg/kg). Steady-state blood concentrations (Css) in the infusion model were achieved within 25 minutes. The elimination half-life was significantly longer following the infusion than after the bolus doses (Table 1). In addition, total body clearance (TBCL) was significantly slower after the infusion (TBCL= 1.0 L/min) than after the 5 mg/kg (TBCL = 1.92 L/min) or 10 mg/kg (TBCL=2.12 L/min) bolus administrations. Waking propofol concentrations in the dog were ~ 1 μg/mL.
Distribution
Tissue levels of total radioactivity and propofol were determined in rats following the administration of a 9.7 mg/kg intravenous dose of 14C-propofol. In all tissues assayed, other than fat, the highest concentration of radioactivity were detected five minutes after dosing and decreased thereafter. Maximal concentration in brown fat occurred at 10 minutes and in white fat at 30 and 60 minutes in males and females, respectively. This indicated that the distribution of propofol into fat occurs after five minutes.
Table 2 Concentrations of Total Radioactivity and Propofol in Selected Tissues of Rats Five Minutes After the Intravenous Administration of 14C-propofol | ||||
| Tissue | Sex | Total radioactivity μg/equivalents/mL | Propofol μg/mL of g | Propofol % of total radioactivity |
Blood Brain Liver | M F M F M F | 5.18 6.83 5.54 9.87 32.77 32.12 | 1.47 3.42 5.12 9.16 1.58 15.10 | 28 50 92 93 5 47 |
Tissue concentrations of total radioactivity were similar in male and female rats, except in the brain where radioactivity was significantly higher in the females (Table 2). The rate of decrease of radioactivity was greatest in the brain; by 30 minutes total radioactivity decreased to 19% and 15% of the 5 minute levels in males and females, respectively. The concentration of propofol in the blood, brain and liver was significantly higher in females. While propofol comprised >90% of the radioactivity in the brain of both sexes, in the blood and liver propofol concentrations were considerably lower and a sex difference was evident. In the liver, propofol levels were about ten times higher in female rats indicating initial differences in the rate of metabolism between the sexes.
Metabolism and Elimination
14C-propofol (10 mg/kg) was extensively metabolized and rapidly eliminated in the urine and feces of rats and dogs. In the rabbit, excretion occurred almost exclusively in the urine (Table 3).
Table 3 The Excretion of 14C-propofol | |||||
| % Dose | |||||
| Species | Sex | Urine | Feces | Bile | Total Recovery |
Rat Dog Rabbit | M F F (pregnant) Mb Fb M & F F | 60 75 77 13 15 60 95 | 31 15 16 1 1 29 2 | 78 53 | 92a 91a 95a 95c 82c 90d 93e |
a Includes dose found in 14CO2 and carcass: 120-h collection b Bile-duct cannulated rats c Includes dose found in gastrointestinal tract and carcass: 24-h collection d 48-h collection e 24-h collection | |||||
In rats, the differences between the excretion data for the two sexes were statistically significant. Extensive biliary excretion and enterohepatic recirculation was observed in both sexes. In the urine, propofol was completely metabolized prior to elimination. In the feces, propofol comprised ~10% and 6% of the dose in male and female rats, respectively. The presence of propofol in the feces may be due to hydrolysis of propofol glucuronide. The radioactivity in the urine consisted of the 4-glucuronide and 4-sulphate conjugates of 2,6-diisopropyl 1,4 quinol and 4-sulphate of 2-(1-propionic acid)-6-isopropyl 1,4 quinol.
In dogs, the urine contained the 4-substituted glucuronic acid and sulphate conjugates of 2,6-diisopropyl 1,4-quinol and minor metabolites; unchanged propofol was <1%. The feces contained 2,6-diisopropyl 1,4-quinol and some uncharacterized polar metabolites. At 2 minutes, the blood concentration of radioactivity was 10.02 μg equivalents/mL, that of propofol was 2.7 μg/mL, constituting 26% of total radioactivity. At 2 hours, propofol comprised only ~1% of radioactivity.
In rabbits, urinary radioactivity consisted of the 4-glucuronide and 4-sulphate conjugates of propofol and 2,6-diisopropyl 1,4-quinol. Unchanged propofol was not detected. At 2 minutes, the blood concentration of radioactivity was ~30 μg equivalents/mL, that of propofol was 15.9 μg/mL, constituting 53% of total radioactivity. At 2 hours, propofol represented ~2% radioactivity.
Binding to Plasma Proteins
Propofol was 98% and 97% bound to plasma proteins in the dog and rat, respectively, over a concentration range of 0.1-20 μg/mL. In the rabbit, binding was concentration dependent; propofol binding decreased from 97% at 0.5 μg/mL to 95% at 50 μg/mL.
TOXICOLOGY
Acute Toxicity
- 1.
Studies in Rats and Mice
Rats and mice of the Alderley Park Albino strain received graded intravenous or oral doses of propofol. At each dose level, six male and six female animals were used. The drug was available as an emulsion for the i.v. studies and as a solution in soya bean oil for the oral studies. At the doses used, all animals became anaesthetized. Several rats and mice, both in the i.v. and oral studies, regained consciousness and then became re-anaesthetized before fully recovering. The LD50 values and observations are summarized in the table.
| Species | Route of Administration | LD50 mg/kg (95% confidence limits) | Observations |
Rats Mice | iv oral iv oral | 42 (38-46) 600 (540-660) 53 (46-60) 1230 (1010-1500) | Death occurred within 5 minutes of dosing. The majority of rats died 1 to 3 days after propofol administration. Following recovery from anaesthesia, several rats exhibited decreased activity, piloerection, hunched posture and tremors. Death occurred within 2 minutes of dosing and was due to respiratory depression. The majority of mice died 1 to 2 days after propofol administration. During anaesthesia, both the rate and depth of respiration was decreased. Following recovery from anaesthesia, several mice exhibited locomotor incoordination and tremors. |
- 2.
Single-Dose Tolerance Study in Rabbits
Three male and three female Dutch rabbits received propofol, 15 mg/kg, by the intravenous route. The drug was given at a rate of 0.5 mg/kg/second. All rabbits became lightly anaesthetized, with 6/6 rabbits retaining their pedal reflex and 2/6 rabbits retaining their palpebral reflex. Ten to 15 minutes after dosing, all rabbits recovered completely without any untoward effect.
Long-Term Toxicology
- 1.
One-Month Toxicity Study in Rats
Five groups of albino rats were dosed daily for 28 days. Injections were given intravenously into the tail vein. Group I received saline, Group II the emulsion vehicle, Groups III, IV and V propofol at doses of 5, 10 and 15 mg/kg/day, respectively.
Propofol induced anaesthesia in a dose-dependent manner; at 5 mg/kg rats were not anaesthetized while the duration of anaesthesia was significantly longer at the 15 mg/kg than at the 10 mg/kg dose. With repeated administration, the duration of anaesthesia became prolonged and on Day 26, anaesthesia lasted significantly longer than on Day 1.
High dose male rats gained slightly but significantly less weight than control rats (131 versus 150 g). In female rats, weight gain was slightly less in all treated animals, however, the effect was not dose-related. Urine volume was significantly but not dose-dependently elevated on Day 26 in all propofol-treated rats. In female rats, relative kidney weights were significantly and dose-dependently elevated in all propofol-treated groups.
- 2.
One-Month Toxicity Study in Dogs
Five groups of Beagle dogs were dosed intravenously over a 30-day period. Group I received saline, Group II the emulsion vehicle, and Groups III and IV propofol at doses of 5 and 10 mg/kg/day, respectively. Group V received propofol, 30 mg/kg 3 times weekly for a total of 13 doses.
Each dose consisted of a 7.5 mg/kg bolus dose and an infusion of 0.5 mg/kg/min for a total of 22.5 mg/kg.
Each group was comprised of 5 male and 5 female dogs. In addition, 3 dogs/sex were used to evaluate recovery in the control and high dose groups.
Propofol induced anaesthesia in a dose-dependent manner. With repeated administration, the duration of anaesthesia became prolonged and on Day 28, anaesthesia lasted significantly longer than on Day 1.
During the 30-day treatment period, Hb, RBC and PCV values declined below the normal range in a few animals. On Day 30, abnormally low values were recorded in 3/10 dogs in both Groups III and IV. (In both groups, the same three dogs were affected.) In Groups II and V, 1/16 dogs each showed similar changes.
REPRODUCTION AND TERATOLOGY
- 1.
Fertility and Reproductive Performance in Rats
Three groups of 50 rats each were dosed intravenously with the vehicle or propofol at doses of 10 or 15 mg/kg/day for two weeks prior to mating, during the mating period to untreated males and up to Day 7 of gestation. Generally, reproductive studies require that treatment be continued during both gestation and lactation, thus, this study provides information about propofol's effect upon fertility but not necessarily upon reproduction.
Approximately half of the females of the F0 generation were sacrificed on Day 21 of pregnancy. The remainder were allowed to litter and rear their offspring to weaning at Day 22 of lactation. At weaning, two females and one male were selected from each litter to form the F1 generation. These animals were kept until sexually mature and then mated. As with the F0 generation, approximately half the females were sacrificed on Day 21 of pregnancy and the remainder were allowed to litter and rear their young to weaning, when the F1 dams and their pups (the F2 generation) were sacrificed.
The administration of propofol was associated with the following changes:
In the F0 generation, treated rats gained significantly less weight than controls prior to mating (9.7, -0.8 and 1.7 g in the control, low and high dose groups, respectively). However, weight gains between Days 7 and 16, or 1 to 21 of pregnancy, were similar in all three groups.
Gestation period was dose-dependently decreased. In the control, low and high dose groups 9.5, 16 and 33% of the rats, respectively delivered on Day 21, rather than Day 22.
Survival of the F1 generation pups was lower in the treated groups. On Day 1, the number of alive pups was similar in all three groups. From Day 5 on, survival in treated groups was lower. Numerical values on Day 22 were as follows: 73, 49 and 52% of pups were alive in the control, low and high dose groups, respectively. Pups which died, were subjected to necropsy. None showed soft tissue abnormalities, however, reduced vertebral ossification was present in 13, 38 and 40% of pups in the control, low and high dose groups, respectively.
Postimplantation loss (as a % of implants) in the F1 generation was higher in rats born to high dose animals (2.3, 1.2 and 15.6% in control, low and high dose rats, respectively).
- 2.
Teratology Study in Rats
Four groups of 40 mated female rats each were dosed intravenously with the vehicle or propofol at doses of 5, 10 or 15 mg/kg/day from Day 6 to Day 15 of pregnancy. The rats were sacrificed on Day 20 of pregnancy and the pups checked for internal and skeletal anomalies.
Maternal weight gain during Days 6 to 15 was significantly less in propofol-treated rats than in controls. The incidence of abnormal cranial ossification was higher in fetuses born to high dose dams than in control fetuses (19.9% versus 11.0%).
In rats, sacrificed on Day 15 of pregnancy, 10 minutes after the last dose, propofol was detected in maternal blood, amniotic fluid and the developing embryo. Drug concentrations increased linearly with increasing doses.
The study indicated that propofol is not teratogenic in rats at the doses studied.
- 3.
Teratology Study in Rabbits
Four groups of 22 mated female rabbits each were dosed intravenously with the vehicle or propofol at doses of 5, 10 or 15 mg/kg/day from Day 6 to Day 18 of pregnancy. The rabbits were sacrificed on Day 28 of pregnancy.
Maternal weight gain during Days 6 to 18 was less in propofol-treated rabbits than in controls. Incomplete sternebral ossification increased dose-dependently in fetuses born to propofol-treated dams as compared to control fetuses.
Propofol was detected in maternal blood, amniotic fluid and embryonic tissue. Drug concentrations increased in a dose-dependent manner.
The study indicated that propofol is not teratogenic in rabbits at the doses studied.
- 4.
Perinatal and Postnatal Study in Rats
Three groups of 22 rats each were dosed intravenously with the vehicle or propofol at doses of 10 to 15 mg/kg/day from Day 16 of gestation through Day 22 of lactation. The number of rats in whom treatment was completed was 18, 16 and 12, in the control, low and high dose groups, respectively. In the high dose group, four dams died during dosing, the cause of death might have been due to respiratory depression. In addition, mothers were sacrificed if the litters died. Maternal weight gain, during the last week of pregnancy, was significantly less in high dose rats than in control animals (47.1 versus 60.3 g). Litter survival on Day 22 was slightly but dose-dependently decreased; the percent of litters which survived was 65, 61 and 53% in the control, low and high dose groups, respectively.
Propofol did not affect the gestation period, maternal weight gain during lactation or the weight gain and developmental landmarks of the litter.
BIBLIOGRAPHY
General
Bone ME, Mobley K, Fell D, Smith G. Comparison of the haemodynamic responses to induction of anaesthesia with either propofol or thiopentone in ASA III patients. Br J Anaesth 1987;59:1318P-1319P.
Briggs LP, White M. The effects of premedication on anaesthesia with propofol ("DIPRIVAN7"). Postgrad Med J 1985;61(Suppl 3):35-37.
Busse J, Von Bulow S, Kentgens A, Heidrich R. Comparison of propofol and isoflurane for maintenance of anaesthesia in ASA grade 3 and 4 patients. Anaesthesia 1988;43(Suppl):121.
Cannon M.L., et al. Metabolic acidosis, rhabdomyolysis, and cardiovascular collapse after prolonged propofol infusion. Journal of Neurosurgery 2001; 95 (6): 1053-1056.
Celleno D, Capogna G, Tomassetti M, Costantino P, Di Feo G, Nisini R. Neurobehavioural effects of propofol on the neonate following elective Caesarean section. Br J Anaesth 1989;62:649-654.
Claeys MA, Gepts E, Camu F. Haemodynamic changes during anaesthesia induced and maintained with propofol. Br J Anaesth 1988;60:3-9.
Clayton KC, Mills JP. Urological surgery in the elderly. An alternative anaesthetic technique using propofol. Anaesthesia 1988;43(Suppl);119.
Coates DP, Monk CR, Prys-Roberts C, Turtle M. Haemodynamic responses of hypertensive patients to an infusion of propofol to supplement nitrous oxide anaesthesia. Beit Anaesthesiol Intens 1987;20:107-108.
Cockshott ID, Briggs LP, Douglas EJ, White M. Pharmacokinetics of propofol in female patients. Br J Anaesth 1987;59:1103-1110.
Coley S, Mobley KA, Bone ME, Fell D. Haemodynamic changes after induction of anaesthesia and tracheal intubation following propofol or thiopentone in patients of ASA grade I and III. Br J Anaesth 1989;63:423-428.
Cremer,O.L. et al. Long-term propofol infusion and cardiac failure in adult head-injured patients. Lancet 2001; 357 (9250):117-118.
De Grood PRMR, Harbers JBM, Van Egmond J, Crul JF. Anaesthesia for laparoscopy. A comparison of five techniques including propofol, etomidate, thiopentone and isoflurane. Anaesthesia 1987;42:815-823.
Dixon J, Roberts FL, Tackley RM, Lewis GTR, Connell M, Prys-Roberts C. Study of the possible interaction between fentanyl and propofol using a computer controlled infusion of propofol. Br J Anaesth 1990;64:142
Dundee JW, Robinson FP, McCollum JSC, Patterson CC. Sensitivity to propofol in the elderly. Anaesthesia 1986;41:482-485.
Dundee JW, Wyant GM. Propofol chapter in: "Intravenous Anaesthesia". Churchill Livingstone, 1988;172-183.
Edelist G. A comparison of propofol and thiopentone as induction agents in outpatient surgery. Can J Anaesth 1987;34:110-116.
Fahmy NR, Matta E, Charchaflieh J, Almaz MG, Carr DB. Circulatory and adrenocortical effects of propofol infusion. A comparison with enflurane anesthesia. Anesthesiology 1989;71:A274.
Fragen RJ, Denissen PAF, Booij LHDJ, Crul JF. Disoprofol (ICI 35,868) for total intravenous anaesthesia. Acta Anaesthesiol Scand 1983;27:113-116.
Gepts E, Camu F, Cockshott ID, Douglas EJ. Disposition of propofol administered as constant rate intravenous infusions in humans. Anesth Analg 1987;66:1256-1263.
Gillies GWA, Lees NW. The effects of speed of injection on induction with propofol. A comparison with etomidate. Anaesthesia 1989;44:386-388.
Glass PSA, Markham K, Ginsberg B, Hawkins ED. Propofol concentrations required for surgery. Anesthesiology 1989;71:A273.
Goodman NW, Black AMS, Carter JA. Some ventilatory effects of propofol as sole anaesthetic agent. Br J Anaesth 1987;59:1497-1503.
Grant IS, MacKenzie N. Recovery following propofol ("DIPRIVAN7") anaesthesia. A review of three different anaesthetic techniques. Postgrad Med J 1985;61(Suppl 3):133-137.
Grounds RM, Moore M, Morgan M. The relative potencies of thiopentone and propofol. Eur J Anaesthesiol 1986;3:11-17.
Harris CE, Murray AM, Anderson JM, Grounds RM, Morgan M. Effects of thiopentone, etomidate and propofol on the hemodynamic response to tracheal intubation. Anaesthesia 1988;43(Suppl):32-36.
Heath PJ, Kennedy DJ, Ogg TW, Dunling C, Gilks WR. Which intravenous induction agent for day surgery? A comparison of propofol, thiopentone, methohexitone and etomidate. Anaesthesia 1988;43:365-368.
Herregods L, Capiau P, Rolly G, De Sommer M, Donadoni R. Propofol for arthroscopy in outpatients. Comparison of three anaesthetic techniques. Br J Anaesth 1988;60:565-569.
Hopkins CS. Recurrent opisthotonus associated with anaesthesia. Anaesthesia 1988;43:904.
Jones GW, Boykett MH, Klok M. Propofol, opisthotonus and epilepsy. Anaesthesia 1988;43:905.
Johnston R, Noseworthy T, Anderson B, Konopad E, Grace M. Propofol versus thiopental for outpatient anaesthesia. Anesthesiology 1987;67:431-433.
Kanto J. Propofol, the newest induction agent of anesthesia. Int J Clin Pharmacol Ther Toxicol 1988;26:41-57.
Kanto J, Gepts E. Pharmacokinetic implications for the clinical use of propofol. Clin Pharmacokinet 1989;17:308-326.
Kashtan H, Edelist G, Mallon J, Kapala D. Comparative evaluation of propofol and thiopentone for total intravenous anaesthesia. Can J Anaesth 1990;37:170-176.
Kirkpatrick T, Cockshott ID, Douglas EJ, Nimmo WS. Pharmacokinetics of propofol (DIPRIVAN) in elderly patients. Br J Anaesth 1988;60:146-150.
Kortilla K, Ostman PL, Faure E, Apfelbaum JL, Ekdawi M, Roizen MF. Randomized comparison of outcome after propofol-nitrous oxide or enflurane-nitrous oxide anaesthesia in operations of long duration. Can J Anaesth 1989;36:651-657.
Langley MS, Heel RC. Propofol. A review of its pharmacodynamic and pharmacokinetic properties and use as an intravenous anaesthetic. Drugs 1988;35:334-372.
Larsen R, Rathgeber J, Bagdahn A, Lange H, Reike H. Effects of propofol on cardiovascular dynamics and coronary blood flow in geriatric patients. A comparison with etomidate. Anaesthesia 1988;43(Suppl):25-31.
Lippmann M, Mok MS. Propofol causes cardiovascular depression. III. Anesthesiology 1990;72:395-396.
MacKenzie N, Grant IS. Comparison of the new emulsion formulation of propofol with methohexitone and thiopentone for induction of anaesthesia in day cases. Br J Anaesth 1985;57:725-731.
McCollum JSC, Dundee JW. Comparison of induction characteristics of four intravenous anaesthetic agents. Anaesthesia 1986;41:995-1000.
McCollum JSC, Milligan KR, Dundee JW. The antiemetic action of propofol. Anaesthesia 1988;43:239-240.
Merin RG. Propofol causes cardiovascular depression. I. Anesthesiology 1990;72:393-394.
Perrier, N.D. et al. Death related to propofol use in an adult patient. Critical Care Medicine 2000; 28 (8):3071-3074.
Perry SM, Bullington J, Davis L, Fisher K, Ramsay S, Wood M. Comparison of propofol and thiopental for the induction of anaesthesia. South Med J 1988;81:611-615.
Reike H, Seyde W, Larsen R. Total intravenous anesthesia with propofol/fentanyl in geriatric patients. Hemodynamic and myocardial perfusion. Anaesthetist 1987;36:533-534.
Rolly G, Versichelen L, Huyghe L, Mungroop H. Effect of speed of injection on induction of anaesthesia using propofol. Br J Anaesth 1985;57:743-746.
Sanders LD, Isaac PA, Yeomans WA, Clyburn PA, Rosen M, Robinson JO. Propofol-induced anaesthesia. Double-blind comparison of recovery after anaesthesia induced by propofol or thiopentone. Anaesthesia 1989;44:200-204.
Scheepstra GL, Booij LHDJ, Rutten CLG, Coenen LGJ. Propofol for induction and maintenance of anaesthesia: comparison between younger and older patients. Br J Anaesth 1989;62:54-60.
Scott RPF, Saunders DA, Norman J. Propofol: Clinical strategies for preventing the pain of injection. Anaesthesia 1988;43:492-494.
Servin F, Desmonts JM, Haberer JP, Cockshott ID, Plummer GF, Farinotti R. Pharmacokinetics and protein binding of propofol in patients with cirrhosis. Anesthesiology 1988;69:887-891.
Servin F, Trouvin JH, Farinotti R, Desmonts JM. Propofol pharmacokinetics in morbidly obese patients. Anesthesiology 1988;69:A463.
Shafer A, Doze VA, Shafer SL, White PF. Pharmacokinetics and pharmacodynamics of propofol infusions during general anesthesia. Anesthesiology 1988;69:348-356.
Spelina KR, Coates DP, Monk CR, Prys-Roberts C, Norley I, Turtle MJ. Dose requirements of propofol by infusion during nitrous oxide anaesthesia in man. I: Patients premedicated with morphine sulphate. Br J Anaesth 1986;58:1080-1084.
Stark RD, Binks SM, Dutka VN, O'Connor KM, Arnstein MJA, Glen JB. A review of the safety and tolerance of propofol (DIPRIVAN7). Postgrad Med J 1985;61(Suppl 3):152-156.
Steib A, Freys G, Beller JP, Curzola U, Otteni JC. Propofol in elderly high risk patients. A comparison of haemodynamic effects with thiopentone during induction of anaesthesia. Anaesthesia 1988;43(Suppl):111-114.
Stelow, E.B. et al. Propofol-associated rhabdomyolysis with cardiac involvement in adults B chemical and anatomic findings. Clinical Chemistry 2000; 46(4): 577-581.
Streisand JB, Nelson P, Bubbers S, Stocking-Korzen R, Posthuma W, East KA, Gillmor ST, Stanley TH. The respiratory effects of propofol with and without fentanyl. Anesth Analg 1987;66(2S):S171.
Thomson SJ, Yate PM. Bradycardia after propofol infusion. Anaesthesia 1987;42:430
Turtle MJ, Cullen P, Prys-Roberts C, Coates D, Monk CR, Faroqui MH. Dose requirements of propofol by infusion during nitrous oxide anaesthesia in man. II: Patients premedicated with lorazepam. Br J Anaesth 1987;59:283-287.
Valtonen M, Kanto J, Rosenberg P. Comparison of propofol and thiopentone for induction of anaesthesia for elective Caesarean section. Anaesthesia 1989;44:758-762.
Vanacker B, Dekegel D, Dionys J, Garcia R, Van Eeckhoutte L, Dralants G, Van de Walle J. Changes in intraocular pressure associated with the administration of propofol. Br J Anaesth 1987;59:1514-1517.
Van Aken H, Brussel T. Propofol causes cardiovascular depression. II. Anesthesiology 1990;72:394-395.
Van Aken H, Meinshausen E, Prien T, Brusses T, Heinecke A, Lawin P. The influence of fentanyl and tracheal intubation on the hemodynamic effects of anesthesia induction with propofol/N20 in humans. Anesthesiology 1988;68:157-163.
Vermeyen KM, Erpels FA, Bral JE, Meese G, Huyzen RJ, Adriaensen HF. Myocardial metabolism during anaesthesia with propofol - low dose fentanyl for coronary bypass surgery. 9th World Congr Anaesthesiol, Washington, DC 1988.
Vermeyen KM, Erpels FA, Janssen LA, Beeckman CP, Hanegreefs GH. Propofol-fentanyl anaesthesia for coronary bypass surgery in patients with good left ventricular function. Br J Anaesth 1987;59:1115-1120.
Victory RAP, Magee D. A case of convulsion after propofol anaesthesia. Anaesthesia 1988;43:904.
Williams JP, McArthur JD, Walker WE, Teunissen E, Reitsema K, Stanley TH. The cardiovascular effects of propofol in patients with impaired cardiac function. Anesth Analg 1986;65(2S):S166.
Wolf, A., et al. Impaired fatty acid oxidation in propofol infusion syndrome. The Lancet 2001; 357 (9256): 606-607.
Lessons learned from a Phase IV study of propofol: analysis of data of over 25,000 patients. Anesth Analg 1993;77(Suppl 4S).
Total Intravenous Anaesthesia (TIVA)
De Grood PMRM, Mitsukuri S, Van Egmond J. Rutten JM, Crul JF. Comparison of etomidate and propofol for anaesthesia in microlaryngeal surgery. Anaesthesia 1987;42:366-372.
Galletly DC, Short TG. Total intravenous anaesthesia using propofol infusion - 50 consecutive cases. Anaesth Intens Care 1988;16:150-157.
Hall RI, Murphy JT, Moffitt EA, Landymore R, Pollak PT, Poole L. A comparison of the myocardial metabolic and haemodynamic changes produced by propofol-sufentanil and enflurane-sufentanil anaesthesia for patients having coronary artery bypass graft surgery. Can J Anaesth 1991;38:996-1004.
Ledderose H, Rester P, Carlsson P, Peter K. Recovery times and side effects after propofol infusion and after isoflurane during ear surgery with addition infiltration anaesthesia. Anaesthesia 1988;43(Suppl):89-91.
Manara AR, Monk CR, Bolsin SN, Prys-Roberts C. Total i.v. anaesthesia with propofol and alfentanil for coronary artery bypass grafting. Br J Anaesth 1991;66:716-718.
Mele D, Consoletti L, Lattanzio A, Carrillo E. TIVA with propofol and fentanyl in neurosurgical patients. (Italian) Minerva Anestesiol 1990;56:833-834.
Milligan KR, Coppel DL, Johnston JR, Cosgrove J. Propofol anesthesia for major thoracic surgery. J Cardiothorac Anesth 1990;4:323-325.
Paediatrics
Ayala-Sandoval S, Gonzales-Guzman MDP, Pineda-Diaz, MV. Propofol as an agent for the induction and maintenance of intravenous anaesthesia in paediatric patients. Rev Mex Anesth 1991;14:55-62.
Borgeat A, Dessibourg C, Popovic MD, Meier D, Blanchard M, Schwander MD. Propofol and spontaneous movement: an EEG study. Anesthesiology 1991;74:24-27.
Borgeat A, Popovic V, Meier D, Schwander D. Comparison of propofol and thiopental/halothane for short-duration ENT surgical procedures in children. Anesth Analg 1990;71:511-515.
Braithwaithe P, Dawson S and Entress AH. Propofol and fentanyl infusions for cardiac surgery in children. J Cardiothoracic Anesth 1990;4(Suppl3):126.
Bray, R.J. Propofol infusion syndrome in children. Paediatric Anaesthesia 1998; 8 (6): 491-499.
Calamandrei M, Andreuccetti T, Messeri A, Romiti M, Busoni P. Propofol for regional blocks in neonate and children. Acta Anesth Italica 1990;41:30-33.
Cray, S.H., et al. Lactic acidemia and bradyarrhythmia in a child sedated with propofol. Critical Care Medicine 1998; 26(2): 2087-2092.
Halpern L, Crawford MW, Sloan M, Sikich N, Bissonnette B, Lerman J. Propofol for induction and maintenance of anesthesia in children: A comparative study. Anesthesiology 1991;75(3A): A962.
Hanna, J.P., and Ramundo, M.L. Rhabdomyolysis and hypoxia associated with prolonged propofol infusion in children. Neurology 1998; 50(1): 301-303.
Hannallah RS, Baker SB, Casey W, McGill WA, Broadman LM, Norden MSN. Propofol: effective dose and induction characteristics in unpremedicated children. Anesthesiology 1991;74:217-219.
Ingolotti C, Pellegrino A, De Bellis P. Induction and maintenance of anaesthesia with propofol and fentanyl in paediatric patients. Proceedings of the Symposium: Intravenous anaesthetics in anaesthesia, reanimation and intensive care, Padua 27-29 Apr, 1990:177-179.
Jones RDM, Chan K, Andrew LJ. Pharmacokinetics of Diprivan in Children. Br J Anaesth 1990;65:661-667.
Larson S, Asgeirsson B, Magnusson J. Propofol-fentanyl anesthesia compared to thiopental-halothane with special reference to recovery and vomiting after pediatric strabismus surgery. Acta Anaesthesiol Scand 1992;36(2):182-186.
Mehta, M., et al. Short-term propofol infusions in children. The Lancet 1999; 354(9181): 866-867.
Mirakhur RK. Induction characteristics of propofol in children: a comparison with thiopentone. Anaesthesia 1988;43:593-598.
Morton NS, Wee M, Christie G. Gray IG, Grant IS. Propofol for the induction of anaesthesia in children. A comparison with thiopentone and halothane induction. Anaesthesia 1988;43:350-355.
Motsch J. Experience with propofol for neurosurgical procedures in children. Focus on Infusion: Intravenous Anaesthesia. Cannes, 28-29 Apr 1991:175-7.
Parke, T.J. et al. Metabolic acidosis and fatal myocardial failure after propofol infusion in children. British Medical Journal 1992; 305(6854):613-616.
Patel DK, Keeling PA, Newman GB, Radford P. Induction dose of propofol in children. Anaesthesia 1988;43:949-952.
Puttick N, Rosen M. Propofol induction and maintenance with N20 in paediatric outpatients. Anaesthesia 1988;43:646-649.
Queinnec MC, de Dieuleveult C, Chupin AM, Pinaud M. Continuous propofol infusion vs enflurane for squint surgery in the child. Comparative study of anaesthetic and recovery conditions. Ann Fr Anesth Reanim 1989;8:37-41.
Saint Maurice C, Cockshott ID, Douglas EJ, Richard MO, Harmey JL. Pharmacokinetics of propofol in young children after a single dose. Br J Anaesth 1989;63(6):667-670.
Valtonen M, Iisalo E, Kanto J and Rosenberg P. Propofol as an induction agent in children: pain on injection and pharmacokinetics. Acta Anaesthesiol Scand 1989;33:152-155.
Vandermeersch E, Van Hemelrijck J, Byttebier G, Van Aken H. Pharmacokinetics of propofol during continuous infusion for pediatric anesthesia. Acta Anaesthesiol Belg 1989;40(3):161-165.
Sedation for Surgical/Diagnostic Procedures
Baldi M, Santini A, Tedeschi D, Oliva A. Potentiation of loco-regional anesthesia with propofol. Minerva Anestesiol 1990;56:797-798.
Blake DW, Donnan G, Novella J, Hackman C. Cardiovascular effects of sedative infusions of propofol and midazolam after spinal anaesthesia. Anaesth Intensive Care 1988;16:292-298.
Borms S, Dhulster D, Fassin W, Opsomer F, Alleman J. Comparison between propofol and flunitrazepam as sedative agents in patients undergoing orthopedic surgery under regional anaesthesia. 5th International Congress Belgian Society of Anesthesia and Reanimation 1988:86.
Conrad B, Larsen R, Rathgeber J, Lange H, Stueber H, Crozier T. Propofol infusion for sedation during surgery with regional blockade. A comparison with midazolam. Anasth Intensivther Notfallmed 1990;25:186-192.
David A, De Salvo R, Santamaria LB, Lucantoi T, Pratic C, Mondello E, Guzzo L, Fodale V, De Lieto I, Runci D. Combined anaesthesia with propofol. Acta Anaesthesiol Ital 1990;41:174-177.
Debaillon-Vesque P, Buffet, JP, Chaudon MP, Poitrey, HF, Dhedin G. Combining propofol with regional anaesthesia for cataract surgery. Cah Anesthesiol 1989;37:55-56.
Dertwinkel R, Nolte H. Continuous sedation for regional anesthesia with propofol (>Disoprivan=) and midazolam (>Dormicum=). A comparative study. Reg Anaesth 1988;11:84-91.
Johnston RG, Konopad E, Jivraj K, Hunt D. Propofol versus diazepam in outpatient arthroscopy. Can J Anaesth 1989;36(3,Part II):S110-S111.
MacKenzie N, Grant IS. Propofol for intravenous sedation. Anaesthesia 1987;42:3-6.
Pratila M. Fischer M, Alagesan R, Alagesan R, Reinsel R, Pratilas D. Propofol vs midazolam for sedation: A comparison of recovery parameters. Anesthesiology 1990;73(3A):A4.
Skipsey IG, Colvin JR, Mackenzie N, Kenny GNC. Sedation with propofol during surgery under regional block: evaluation of a computer controlled infusion system. Br J Anaesth 1991; 67:218P-219P.
Taylor E, Ghouri AF, White PF. Midazolam in combination with propofol for sedation during local anesthesia. J Clin Anesth 1992;4:213-216.
Vairo G, Marmo M, Nocerino A, Balsimelli M, Carillo A, De Luca P, Cozzolino V, Mangrella M. Propofol in blended anesthesia: experiences in ophthalmologic surgery of elderly patients. Riforma Med 1991;106:151-153.
Wilson E, MacKenzie N, Grant IS. A comparison of propofol and midazolam by infusion to provide sedation in patients who receive spinal anaesthesia. Anaesthesia 1988;43(Suppl):91-94.
Intensive Care Unit (ICU) Sedation
Aitkenhead AR, Willats SM, Park GR, Collins CH, Ledingham IM, Pepperman ML, Coates PD, Bodenham AR, Smith MB, Wallace PGM. Comparison of propofol and midazolam for sedation in critically ill patients. Lancet 1989;ii:704-709.
Albanese J, Martin C, Lacarelle B, Saux P, Durand A, Gouin F. Pharmacokinetics of long-term propofol infusion used for sedation in ICU patients. Anesthesiology 1990;73:214-217.
Boyle WA, Shear JM, White PF, Schuller D. Tolerance and hyperlipemia during long-term sedation with propofol. Anesthesiology 1990;73(3A):A245.
DuGres B, Flamens C. A comparison of propofol and midazolam infusion for post operative sedation after cardiac surgery. J Cardiothoracic Anesth 1990;4(Suppl 3):101.
Grant IS, Nimmo GR, Armstrong IR. Intensive care sedation with propofol: effects on haemodynamics and oxygen transport. J Drug Dev 1991;4(Suppl 3):86-88.
Harris CE, Grounds RM, Murray AM, Lumley J, Royston D, Morgan M. Propofol for long-term sedation in the intensive care unit. A comparison with papaveretum and midazolam. Anaesthesia 1990;45:366-372.
Herregods L, Mergaert C, Rolly G, Colardyn F. Comparison of the effects of 24-hour propofol or fentanyl infusions on intracranial pressure. J Drug Dev 1989;2(Suppl 2):99-100.
Mackenzie SJ, Kapadia F, Grant IS. Propofol infusion for control of status epilepticus. Anaesthesia 1990;45:1043-1045.
McMurray TJ, Collier PS, Carson IW, Lyons SM, Elliott P. Propofol sedation after open heart surgery. A clinical and pharmacokinetic study. Anaesthesia 1990;45:322-326.
Newman LH, McDonald JC, Wallace PGM, Ledingham IMcA. Propofol infusion for sedation in intensive care. Anaesthesia 1987;42:929-937.
O'Conner M, Stow P, Mortimer A, Fisher A, Sear JW. Propofol to provide sedation after coronary artery by-pass surgery - a comparison of three fixed-rate infusion regimens. J Drug Dev 1989;2(Suppl 2):135-137.
Pearson K, Kruse G, Demetrion E. Effects of propofol sedation on common laboratory measurements. Anesthesiology 1990; 73(3A):A299.
Reeve WG, Wallace PGM. A Survey of Sedation in Intensive Care. Care Crit Ill 1991;7:238-241.
Neurosurgery
Muzzi D, Losasso T, Weglinski M, Milde L. The effects of propofol on cerebrospinal fluid pressure in patients with supratentorial mass lesions. Anesthesiology 1992;77(3A):A216
Ravussin P, Guinard JP, Ralley F, Thorin D. Effects of propofol on cerebrospinal fluid pressure in patients undergoing craniotomy. Anaesthesia 1988;43(Suppl): 37-41.
Todd MM, Warner DS, Sokoll M, et al. A randomized trial of three anesthetics for neurosurgery. Anesthesiology 1992;77(3A):A218
Cardiac Surgery
Hall RI. Use of propofol for induction and maintenance of anesthesia in cardiac surgery patients. Sem Anesth 1992;11(Suppl 1):39-40.
Hall RI, Murphy JT, Moffitt EA. A randomized study of propofol-sufentanil vs enflurane-sufentanil anesthesia in patients undergoing coronary artery revascularisation surgery: effects on myocardial metabolism. Can J Anaesth 1991;38(4, Part II):A163.
Kaplan JA, Guffin AV, Mikula S, Dolman J, Profeta J. Comparative hemodynamic effects of propofol and thiamylal sodium during anesthetic induction for myocardial revascularization. J Cardiothoracic Anesth 1988;2(3):297-302
Mora CT, Dudek C, Epstein RH, Torjman MC, White PF. A comparison of fentanyl, enflurane, thiopental and propofol for maintenance of cardiac anesthesia. Proceedings of the 11th Annual Meeting of the Society of Cardiovascular Anesthesiologists. Seattle, 16-19 Apr 1989:193.
Mora CT, Henson M, Bailey J, Szlam F, Hug CC, Propofol plasma concentration affects alfentanil requirements for cardiac surgery. Anesthesiology 1992;77(3A):A408.
Williams JP, McArthur JD, Walker WE, Rietsema K, Teunissen E, Bonnenkamp H, Goderie P, Stanley TH. A comparison of the hemodynamics of Diprivan (propofol), thiopental, and etomidate for induction of anesthesia in patients with coronary artery disease. Sem Anesth 1988;7(Suppl 1):112-115.
Last revised: October 2, 2018
Pfizer Canada Inc.
Kirkland, Québec
H9J 2M5