


Product Monograph - Quaterna
RECENT MAJOR LABEL CHANGES
Not Applicable.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorisation are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ........................................................................................................................... 4
1.2 Geriatrics ........................................................................................................................... 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ....................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .................................................................. 6
4.4 Administration .................................................................................................................. 7
4.5 Missed Dose ...................................................................................................................... 8
5 OVERDOSAGE ............................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................... 9
7.1 Special Populations ......................................................................................................... 17
7.1.1 Pregnant Women ............................................................................................................ 17
7.1.2 Breast-feeding ................................................................................................................. 17
7.1.3 Pediatrics ......................................................................................................................... 17
7.1.4 Geriatrics ......................................................................................................................... 18
8 ADVERSE REACTIONS ................................................................................................. 18
8.1 Adverse Reaction Overview ............................................................................................ 18
8.2 Clinical Trial Adverse Reactions ....................................................................................... 19
8.3 Less Common Clinical Trial Adverse Reactions ................................................................ 22
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ................................................................................................................................. 26
8.5 Post-Market Adverse Reactions ...................................................................................... 27
9 DRUG INTERACTIONS ................................................................................................. 28
9.2 Drug Interactions Overview ............................................................................................. 28
9.3 Drug-Behavioural Interactions ........................................................................................ 28
9.4 Drug-Drug Interactions .................................................................................................... 28
9.5 Drug-Food Interactions ................................................................................................... 32
9.6 Drug-Herb Interactions .................................................................................................... 32
9.7 Drug-Laboratory Test Interactions .................................................................................. 32
10 CLINICAL PHARMACOLOGY ........................................................................................ 33
10.1 Mechanism of Action ...................................................................................................... 33
10.2 Pharmacodynamics ......................................................................................................... 33
10.3 Pharmacokinetics ............................................................................................................ 33
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 36
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 36
PART II: SCIENTIFIC INFORMATION ........................................................................................ 37
13 PHARMACEUTICAL INFORMATION ............................................................................. 37
14 CLINICAL TRIALS ......................................................................................................... 38
14.1 Clinical Trials by Indication .............................................................................................. 39
Prevention of Pregnancy ................................................................................................. 39
14.2 Comparative Bioavailability Studies ................................................................................ 41
15 MICROBIOLOGY ......................................................................................................... 43
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 43
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 44
PATIENT MEDICATION INFORMATION ................................................................................... 45
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
QUATERNATM (levonorgestrel 0.15 mg and ethinyl estradiol 0.03 mg combination tablets and ethinyl estradiol 0.01 mg tablets) is indicated for the prevention of pregnancy.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available in women under the age of 18 years; therefore, Health Canada has not authorized an indication for pediatric use.
Use of this product before menarche is not indicated.
1.2 Geriatrics
Geriatrics: QUATERNA is not indicated for use in post-menopausal women.
2 CONTRAINDICATIONS
QUATERNA should not be used in women who have the following conditions:
- Hypersensitivity to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- History of or actual thrombophlebitis or thromboembolic disorders.
- History of or actual cerebrovascular disorders.
- History of or actual myocardial infarction or coronary artery disease.
- Valvular heart disease with complications.
- History of/or actual prodromi of a thrombosis (e.g., transient ischemic attack, angina pectoris)
- Active liver disease or history of or actual benign or malignant liver tumours.
- Steroid-dependent jaundice, cholestatic jaundice, history of jaundice in pregnancy
- Known or suspected carcinoma of the breast.
- Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia.
- Undiagnosed abnormal vaginal bleeding.
- Any ocular lesion arising from ophthalmic vascular disease, such as partial or complete loss of vision or defect in visual fields.
- Known or suspected pregnancy.
Presence of severe or multiple risk factor(s) for arterial or venous thrombosis:
-diabetes mellitus with vascular involvement
-severe hypertension (persistent values of ≥160/100mm Hg)
-severe dyslipoproteinemia
-hereditary or acquired predisposition for venous or arterial thrombosis, such as Factor V Leiden mutation and activated protein C (APC-) resistance, antithrombin-III-deficiency, protein C deficiency, protein S deficiency, hyperhomocysteinaemia (e.g., due to MTHFR C677 T, A1298 mutations), prothrombin mutation G20210A and antiphospholipid-antibodies (anticardiolipin-antibodies, lupus anticoagulant).
-major surgery associated with an increased risk of post-operative thromboembolism
-prolonged immobilization
-heavy smoking (>15 cigarettes per day) and over age 35
- Current or history of migraine with focal aura.
- History of/or actual pancreatitis if associated with severe hypertriglyceridemia.
- Use of Hepatitis C drug combinations containing, glecaprevir/pibrentasvir and sofosbuvir/velpatasvir/voxilaprevir due to the potential for ALT elevations.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels. This risk increases with age and becomes significant in oral contraceptive users older than 35 years of age. For this reason, Combination Oral Contraceptives, including QUATERNA are contraindicated in women over 35 years of age and who smoke (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Cardiovascular sections).
Birth control pills DO NOT PROTECT against Sexually Transmitted Infections (STIs) including HIV/AIDS. For protection against STIs, it is advisable to use latex or polyurethane condoms IN COMBINATION WITH birth control pills.
Use of QUATERNA provides women with more hormonal exposure on a yearly basis than conventional monthly oral contraceptives containing similar strength synthetic estrogens and progestins (9 additional weeks of combined estrogen/progestin and 4 additional weeks of unopposed estrogen per year). While this added exposure may pose an additional risk of thrombotic and thromboembolic diseases, studies to date with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets have not suggested, nor can exclude, this additional risk.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
This product (like all oral contraceptives) is intended to prevent pregnancy. Oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases such as chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B and syphilis.
The patient should be advised to use a non-hormonal back-up method for the first 7 days of tablet-taking. However, if intercourse has already occurred, the possibility of ovulation and conception prior to initiation of medication should be considered.
The tablets should not be removed from the protective blister packaging to avoid damage to the product. The blister card should be kept in the foil pouch until dispensed to the patient.
4.2 Recommended Dose and Dosage Adjustment
The dosage of QUATERNA consists of the daily administration of one bluish-green (levonorgestrel/ethinyl estradiol) tablet taken for 84 consecutive days followed by 7 days of yellow (ethinyl estradiol) tablets; therefore patients should expect to have 4 menstrual periods per year. To achieve maximum contraceptive effectiveness, QUATERNA must be taken exactly as directed and at intervals not exceeding 24 hours. Ideally, the tablets should be taken at the same time of the day on each day of active treatment.
During the first cycle of medication, the patient is instructed to begin taking QUATERNA on the first Sunday after the onset of menstruation. If menstruation begins on a Sunday, the first bluish-green (levonorgestrel/ethinyl estradiol) tablet is taken that day. One bluish-green (levonorgestrel/ethinyl estradiol) tablet should be taken daily for 84 consecutive days, followed by a 7-day period during which a yellow (ethinyl estradiol) tablet is taken daily. Withdrawal bleeding should occur during the 7-day period following discontinuation of bluish-green active tablets.
During the first cycle, contraceptive reliance should not be placed on QUATERNA until bluish-green tablets have been taken daily for 7 consecutive days and a non-hormonal back-up method of birth control (such as condoms or spermicide) should be used during those 7 days. The possibility of ovulation and conception prior to initiation of medication should be considered.
The patient begins all subsequent 91-day courses of tablets without interruption and on the same day of the week on which she began her first course, i.e., Sunday. The same administration schedule is followed: daily administration of one bluish-green (levonorgestrel/ethinyl estradiol) tablet taken for 84 consecutive days followed by 7 days of yellow (ethinyl estradiol) tablets.
If in any cycle the patient starts the tablets later than the proper day, she should protect herself against pregnancy by using a non-hormonal back-up method of birth control until she has taken bluish-green tablets daily for 7 consecutive days.
Health Canada has not authorized an indication for pediatric use.
4.4 Administration
No hormonal contraceptive use in the preceding cycle: Tablet taking should start on the first Sunday after the onset of menstruation. See above.
Switching from another combined hormonal contraceptive (combined oral contraceptive (COC), vaginal ring or transdermal patch): The patient should start QUATERNA on the day she would normally start her next pack of combined oral contraceptive. In case a vaginal ring or transdermal patch has been used, the woman should start using QUATERNA preferably on the day of removal, but at the latest when the next application would have been due.
Switching from a progestogen-only method (mini-pill, injection): The patient may switch from the mini-pill to QUATERNA on any day of her cycle. Patients using a progestogen injection should start QUATERNA on the day the next injection is due. In all cases, the patient should be advised to use an additional (barrier) method for the first 7 days of QUATERNA use.
Following first trimester abortion: The patient may start using QUATERNA immediately. When doing so, she need not take additional contraceptive measures.
Following delivery or abortion: QUATERNA may be initiated immediately after a first-trimester abortion; if the patient starts QUATERNA immediately, additional contraceptive measures are not needed. Patients should be advised to start QUATERNA on day 21 to 28 after delivery or second trimester abortion, after consulting with their healthcare professional. When starting later, the patient should be advised to use an additional (barrier) method for the first seven days of QUATERNA use. However, if intercourse has already occurred, pregnancy should be excluded before the actual start of use, or the woman should be advised to wait for her next menstrual period prior to starting QUATERNA. When the tablets are administered in the postpartum period, the increased risk of thromboembolic disease associated with the postpartum period must be considered.
In the non-lactating mother, QUATERNA may be initiated no earlier than Day 28 of postpartum for contraception due to the increased risk of thromboembolism. When the tablets are administered in the postpartum period, the increased risk of thromboembolic disease associated with the postpartum period must be considered (see also 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
Spotting / Breakthrough bleeding: If spotting or breakthrough bleeding occurs while taking QUATERNA, the patient should be instructed to continue taking QUATERNA as instructed and by the regimen described above. She should be instructed that this type of bleeding is usually transient and without significance; however, if the bleeding is persistent or prolonged, the patient should be advised to consult her healthcare professional.
If withdrawal bleeding does not occur: Correct use of contraceptives can result in lower failure rates. If withdrawal bleeding does not occur while taking yellow (ethinyl estradiol) tablets, the possibility of pregnancy must be considered. Appropriate diagnostic measures to rule out pregnancy should be taken at the time of any missed menstrual period. QUATERNA should be discontinued if pregnancy is confirmed.
Advice in case of vomiting: If vomiting occurs within 3 to 4 hours after a tablet is taken, absorption may not be complete. In such an event, the advice concerning management of missed pills is applicable.
4.5 Missed Dose
Detailed patient instructions regarding missed pills are presented in Part III of the product monograph, in the subsection entitled “Missed Dose”.
If a patient misses one bluish-green tablet, she should take it as soon as possible, meaning she can take two tablets in one day. If a patient misses two bluish-green tablets, she should take 2 tablets on the day she remembers and 2 tablets on the following day. Should three or more tablets be missed, the regular dosing schedule should be resumed, that is one bluish-green tablet per day. Any time the patient misses two or more bluish-green tablets, she should also use another method of non-hormonal back-up contraception until she has taken bluish-green tablets daily for seven consecutive days. If the patient misses one or more yellow (ethinyl estradiol) tablets, she is still protected against pregnancy provided she begins taking bluish-green tablets again on the appropriate day. The possibility of ovulation increases with each successive day that scheduled bluish-green tablets are missed. The risk of pregnancy increases with each bluish-green tablet missed.
5 OVERDOSAGE
Serious ill effects have not been reported following accidental ingestion of large doses of oral contraceptives by young children. Symptoms of combined oral contraceptive (COC) overdosage in adults and children may include nausea, vomiting, breast tenderness, dizziness, abdominal pain, drowsiness/fatigue; withdrawal bleeding may occur in females. There is no specific antidote and further treatment of overdose, if necessary, is directed to the symptoms. Liver function tests should be conducted, particularly transaminase levels, 2 to 3 weeks after consumption.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 - Dosage Forms, Strengths, Composition and Packaging
Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablets 0.15 mg Levonorgestrel / 0.03 mg Ethinyl Estradiol and 0.01 mg Ethinyl Estradiol | Levonorgestrel 0.15 mg / Ethinyl Estradiol 0.03 tablet: lactose monohydrate, polacrilin potassium, D&C Yellow No. 10, FD&C Blue No. 1 aluminum lake, FD&C Yellow No. 6, magnesium stearate. Ethinyl Estradiol 0.01 mg tablet: anhydrous and monohydrate lactose, microcrystalline cellulose, polacrilin potassium, D&C Yellow No. 10 aluminum, FD&C Yellow No. 6/Sunset yellow FCF aluminum lake, povidone, dl-α-tocopherol, magnesium stearate and isopropyl alcohol (in traces). |
QUATERNATM (levonorgestrel 0.15 mg/ethinyl estradiol 0.03 mg combination and ethinyl estradiol 0.01 mg) tablets are available in Extended-Cycle Tablet Blister Cards. Altogether, the Tablet Blister Card holds 91 tablets consisting of 84 bluish-green tablets (each containing 0.15 mg of levonorgestrel and 0.03 mg ethinyl estradiol) and 7 yellow tablets (each containing 0.01 mg ethinyl estradiol). The bluish-green tablets are round, uncoated, biconvex, unscored tablets with a debossed 417 on one side and blank on the other side. The yellow tablets are round, biconvex, unscored with a debossed with 419 on one side and blank on the other side.
The Tablet Blister Card consists of three blisters. Each of these blisters contains either 28 or 35 holes for tablets to be pushed out of the blister cards through the aluminum foil. The first two blister cards contain 28 active bluish-green tablets and the third blister card contains 28 active bluish-green tablets and 7 active yellow tablets for a total of 35 tablets. The Blister Card is then packaged in a foil pouch.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Discontinue Medication at the Earliest Manifestation of:
- A. Thromboembolic and cardiovascular disorders such as thrombophlebitis, pulmonary embolism, cerebrovascular disorders, myocardial ischemia, mesenteric thrombosis and retinal thrombosis.
- B. Conditions that predispose to venous stasis and vascular thrombosis (e.g., immobilization after accidents or confinement to bed during long-term illness). Other non-hormonal methods of contraception should be used until regular activities are resumed. For use of oral contraceptives when surgery is contemplated, see 7 WARNINGS AND PRECAUTIONS, Peri-Operative Considerations, below.
- C. Visual defects - partial or complete
- D. Papilledema or ophthalmic vascular lesions
- E. Severe headache of unknown etiology or worsening of pre-existing migraine headache
- F. Increase in epileptic seizures
QUATERNA Oral Contraceptive
QUATERNA is a 91-day cyclic dosing regimen (84 days with tablets of 0.15 mg levonorgestrel and 0.03 mg ethinyl estradiol, followed by 7 days with tablets of 0.01 mg ethinyl estradiol).
Pregnancy should be ruled out in cases of unanticipated bleeding/spotting, missed withdrawal bleeding/ amenorrhea or signs and symptoms of pregnancy.
The following information is provided from studies of combination oral contraceptives (COCs).
The use of combination hormonal contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia and gallbladder disease, although the risk of serious morbidity and mortality is small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly if associated with the presence of other risk factors such as hypertension, hyperlipidemias, obesity and diabetes.
Other medical conditions which have been associated with adverse circulatory events include systemic lupus erythematosus, hemolytic uremic syndrome, chronic inflammatory bowel disease (Crohn’s disease or ulcerative colitis), sickle cell disease, valvular heart disease and atrial fibrillation.
The following conditions have been reported to occur or deteriorate with both pregnancy and
COC use, although a direct association with COCs has not been firmly established:
porphyria, systemic lupus erythematosus, hemolytic uremic syndrome, Sydenham’s chorea, herpes gestationis, and otosclerosis-related hearing loss.
The information contained in this section is principally from studies carried out in women who used combination oral contraceptives with higher formulations of estrogens and progestogens than those in common use today. The effect of long-term use of combination hormonal contraceptives with lower doses of both estrogen and progestogen administered orally remains to be determined.
Carcinogenesis and Mutagenesis
Breast cancer
Increasing age and a strong family history are the most significant risk factors for the development of breast cancer. Other established risk factors include obesity, nulliparity, and late age for first full-term pregnancy. The identified groups of women that may be at increased risk of developing breast cancer before menopause are long-term users of oral contraceptives (more than eight years) and starters at early age. In a few women, the use of oral contraceptives may accelerate the growth of an existing but undiagnosed breast cancer. Since any potential increased risk related to oral contraceptive use is small, there is no reason to change prescribing habits at present.
Women receiving oral contraceptives should be instructed in self-examination of their breasts. Their healthcare professional should be notified whenever any masses are detected. A yearly clinical breast examination is also recommended, because, if a breast cancer should develop, drugs that contain estrogen may cause a rapid progression.
Cervical cancer
The most important risk factor for cervical cancer is persistent human papillomavirus (HPV) infection. Some epidemiological studies have indicated that long term use of COCs may further contribute to this increased risk but there continues to be controversy about the extent to which this finding is attributable to confounding effects, e.g., cervical screening and sexual behaviour including use of barrier contraceptives.
Hepatocellular carcinoma
Hepatocellular carcinoma may be associated with oral contraceptives. The risk appears to increase with duration of hormonal contraceptive use. However, the attributable risk (the excess incidence) of liver cancers in oral contraceptive users is extremely small.
See also 16 NON-CLINICAL TOXICOLOGY.
Cardiovascular
See also 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS – General, Hematologic.
Use of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets provides women with more hormonal exposure on a yearly basis than conventional monthly oral contraceptives containing similar strength synthetic estrogens and progestins (9 additional weeks of combined estrogen/progestin and 4 additional weeks of unopposed estrogen per year). While this added exposure may pose an additional risk of thrombotic and thromboembolic diseases, studies to date with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets have not suggested, nor can exclude, this additional risk. Coagulation profile has not been studied with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets.
There was one case of venous thromboembolism in a woman with Factor V Leiden mutation and one case of non-Q wave myocardial infarction secondary to coronary spasm in another woman treated with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets in clinical studies. In the post-market period, there have been cases of cerebral thrombosis, cerebrovascular accident, pulmonary embolism and deep vein thrombosis reported in patients using levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets.
Prescribers are advised to carefully assess a patient’s baseline and cumulative risk of thromboembolism and discuss the risk of thromboembolism with all patients before prescribing QUATERNA.
Predisposing Factors for Coronary Artery Disease
Cigarette smoking increases the risk of serious cardiovascular side effects and mortality. Birth control pills increase this risk, especially with increasing age. Convincing data are available to support an upper age limit of 35 years for oral contraceptive use by women who smoke.
Other women who are independently at high risk for cardiovascular disease include those with diabetes, hypertension, abnormal lipid profile, or a family history of these. Whether oral contraceptives accentuate this risk is unclear.
In low-risk, non-smoking women of any age, the benefits of oral contraceptive use outweigh the possible cardiovascular risks associated with low-dose formulations. Consequently, oral contraceptives may be prescribed for these women up to the age of menopause.
Thromboembolism
See 7 WARNINGS AND PRECAUTIONS, Hematologic section.
Hypertension
Patients with essential hypertension whose blood pressure is well-controlled may be given hormonal contraceptives but only under close supervision. If a significant elevation of blood pressure in previously normotensive or hypertensive subjects occurs at any time during the administration of the drug, cessation of medication is necessary.
Endocrine and Metabolism
Diabetes
Current low-dose oral contraceptives exert minimal impact on glucose metabolism. Diabetic patients, or those with a family history of diabetes, should be observed closely to detect any worsening of carbohydrate metabolism. Patients predisposed to diabetes who can be kept under close supervision may be given oral contraceptives. Young diabetic patients whose disease is of recent origin, well-controlled, and not associated with hypertension or other signs of vascular disease such as ocular fundal changes, should be monitored more frequently while using oral contraceptives.
Lipid and other metabolic effects
A small proportion of women will have adverse lipid changes while on oral contraceptives. Alternative contraception should be used in women with uncontrolled dyslipidemias (see also 2 CONTRAINDICATIONS). Elevations of plasma triglycerides may lead to pancreatitis and other complications.
Gastrointestinal
Published epidemiological studies indicate a possible association of COC use and the development of Crohn’s disease and ulcerative colitis, although this has not been firmly established.
Genitourinary
Vaginal Bleeding and Bleeding Irregularities
In the pivotal trial for levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets, intermenstrual bleeding and menorrhagia were the most commonly reported treatment-emergent adverse events leading to study discontinuation, with 2.98% of patients treated with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets discontinuing due to intermenstrual bleeding and 2.78% of patients discontinuing due to menorrhagia. See also 8.2 Clinical Trial Adverse Reactions section.
Persistent irregular vaginal bleeding requires assessment to exclude underlying pathology.
Fibroids
Patients with fibroids (leiomyomata) should be carefully observed. Sudden enlargement, pain, or tenderness requires discontinuation of the use of oral contraceptives.
Hematologic
Epidemiological studies have shown that the incidence of venous thromboembolism (VTE) in users of oral contraceptives with low estrogen content (<50 mcg ethinyl estradiol) ranges from about 20 to 40 cases per 100,000 women-years, but this risk estimate varies according to the progestogen. This compares with 5 to 10 cases per 100,000 women-years for non-users.
The use of any combined oral contraceptive (COC) carries an increased risk of VTE compared with no use. The excess risk of VTE is highest during the first year a woman ever uses a combined oral contraceptive. The increased risk is less than the risk of VTE associated with pregnancy, which is estimated as 60 cases per 100,000 pregnancies. VTE is fatal in 1-2% of cases.
Other risk factors for venous thromboembolism
Other generalized risk factors for venous thromboembolism include but are not limited to a personal history, a family history (the occurrence of VTE in a direct relative at a relatively early age may indicate genetic predisposition), severe obesity (body mass index ≥30 kg/m2) and systemic lupus erythematosus. The risk of VTE also increases with age and smoking. The risk of VTE may be temporarily increased with prolonged immobilization, major surgery or trauma. Also, patients with varicose veins and leg cast should be closely supervised.
If a hereditary or acquired predisposition to venous thromboembolism is suspected, the woman should be referred to a specialist for advice before deciding on any COC use.
Hepatic/Biliary/Pancreatic
Jaundice
Patients who have had jaundice should be given oral contraceptives only with great care and under close observation. Oral contraceptive-related cholestasis has been described in women with a history of pregnancy-related cholestasis. Women with a history of cholestasis may have the condition recur with subsequent hormonal contraceptive use.
The development of severe generalized pruritus or icterus requires that the medication be withdrawn until the problem is resolved.
If a patient develops jaundice that proves to be cholestatic in type, the use of oral contraceptives should not be resumed. In patients taking oral contraceptives, changes in the composition of the bile may occur and an increased incidence of gallstones has been reported.
Hepatic nodules
Hepatic nodules (adenoma and focal nodular hyperplasia) have been reported, particularly in long-term users of oral contraceptives. Although these lesions are extremely rare, they have caused fatal intra-abdominal hemorrhage and should be considered in women presenting with an abdominal mass, acute abdominal pain, or evidence of intra-abdominal bleeding.
Risk of ALT Elevations with Concomitant Hepatitis C Treatment
Discontinue QUATERNA prior to starting therapy with the hepatitis C combination drug regimen glecaprevir/pibrentasvir and sofosbuvir/velpatasvir/voxilaprevir due to the potential for ALT elevations (see 2 CONTRAINDICATIONS).
QUATERNA can be restarted approximately 2 weeks following completion of treatment with the Hepatitis C combination drug regimen.
Gallbladder disease
Users of oral contraceptives have a greater risk of developing gallbladder disease requiring surgery within the first year of use. The risk may double after four or five years of use.
Immune
Angioedema
Exogenous estrogens may induce or exacerbate symptoms of angioedema, in particular in women with hereditary and acquired angioedema.
Chloasma
Chloasma may occur with combination oral contraceptives use including QUATERNA, especially in women with a history of chloasma gravidarum. Women who tend to develop chloasma should avoid exposure to the sun or ultraviolet radiation while taking QUATERNA.
Monitoring and Laboratory Tests
Physical Examination and Follow-up
Before oral contraceptives are used, a thorough history and physical examination should be performed, including a blood pressure determination and the family case history carefully noted. In addition, disturbances of the clotting system must be ruled out if any members of the family have suffered from thromboembolic diseases (e.g., deep vein thrombosis, stroke, myocardial infarction) at a young age. Breasts, liver, extremities and pelvic organs should be examined and a Papanicolaou (PAP) smear should be taken if the patient has been sexually active.
The first follow-up visit should be three months after the initiation of hormonal contraceptive therapy. Thereafter, examinations should be performed at least once a year, or more frequently if indicated. Women with a strong family history of breast cancer or who have breast nodules should be monitored with particular care. At each annual visit, examination should include those procedures that were done at the initial visit, as outlined above or as per the recommendations of the Canadian Task Force on the Periodic Health Examination.
Neurologic
Migraine and headache
The onset or exacerbation of migraine or the development of headaches with a new pattern that is recurrent, persistent or severe, requires discontinuation of hormonal contraceptives and evaluation of the cause. Women with migraine who take combination oral contraceptives may be at an increased risk of stroke (see 2 CONTRAINDICATIONS).
Epilepsy/seizures
Patients with epilepsy or other seizure disorders who are being treated with anticonvulsants should be monitored closely while using hormonal contraceptives. In some patients being treated with anticonvulsants, a method of contraception other than hormonal contraceptives may be recommended (see 9.4 Drug-Drug Interactions). If a woman experiences new onset or exacerbation of seizures while using QUATERNA, the use of QUATERNA should be re-evaluated.
Ophthalmologic
Patients who are pregnant or are taking oral contraceptives may experience corneal edema that may cause visual disturbances and changes in tolerance to contact lenses, especially of the rigid type. Soft contact lenses usually do not cause disturbances. If visual changes or alterations in tolerance to contact lenses occur, temporary or permanent cessation of wear may be advised.
Peri-Operative Considerations
There is an increased risk of thromboembolic complications in oral contraceptive users after major surgery. If feasible, oral contraceptives should be discontinued and an alternative method substituted at least one month prior to MAJOR elective surgery. Oral contraceptive use should not be resumed until the first menstrual period after hospital discharge following surgery.
Psychiatric
Emotional Disorders/Depression
Patients with a history of emotional disturbances, especially the depressive type, may be more prone to have a recurrence of depression while taking oral contraceptives. In case of a serious recurrence, QUATERNA should be discontinued and an alternate method of contraception should be used temporarily in order to help clarify the possible relationship. Women with premenstrual syndrome (PMS) may have a varied response to oral contraceptives, ranging from symptomatic improvement to worsening of the condition.
Renal
Fluid retention
Hormonal contraceptives may cause some degree of fluid retention. They should be prescribed with caution, and only with careful monitoring, in patients with conditions which might be aggravated by fluid retention.
Reproductive Health: Female Potential
Return to Fertility
After discontinuing oral contraceptive therapy, the patient should delay pregnancy until at least one normal spontaneous menstrual cycle has occurred in order to date the pregnancy. An alternative contraceptive method should be used during this time.
Amenorrhea
Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets are a 91-day cyclic dosing regimen (84 days with tablets of 0.15 mg levonorgestrel and 0.03 mg ethinyl estradiol, followed by 7 days with tablets of 0.01 mg ethinyl estradiol). In the case of unanticipated bleeding/spotting, missed withdrawal bleeding or amenorrhea, the possibility of pregnancy must be considered.
Women with a history of oligomenorrhea, secondary amenorrhea, or irregular cycles may remain anovulatory or become amenorrheic following discontinuation of estrogen-progestin combination therapy.
Amenorrhea, especially if associated with breast secretion, which continues for six months or more after withdrawal, warrants a careful assessment of hypothalamic-pituitary function.
Reduced Efficacy
The efficacy of COCs may be reduced in the event of missed tablets, gastro-intestinal disturbances or concomitant medication (see 9 DRUG INTERACTIONS).
7.1 Special Populations
7.1.1 Pregnant Women
Oral contraceptive use should be discontinued if pregnancy is confirmed. Oral contraceptives should not be taken by pregnant women. However, if conception accidentally occurs while taking the pill, there is no conclusive evidence that the estrogen and progestin contained in the oral contraceptive will damage the developing child.
7.1.2 Breast-feeding
In breast-feeding women, the use of hormonal contraceptives results in the hormonal components being excreted in breast milk and may reduce its quantity and quality. Published studies have indicated that during lactation, 0.1% of the daily maternal dose of levonorgestrel and 0.02% of the daily maternal dose of ethinyl estradiol could be transferred to the newborn via milk. Adverse effects on the child have been reported, including jaundice and breast enlargement. The nursing mother should be advised not to use combination oral contraceptives, but to use other forms of contraception until she has completely weaned her child. There have been no formal studies of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets in nursing women.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available in women under the age of 18 years; therefore, Health Canada has not authorized an indication for pediatric use.
Use of this product before menarche is not indicated.
7.1.4 Geriatrics
QUATERNA is not indicated for use in post-menopausal women.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives:
- benign hepatic tumours
- cerebral hemorrhage
- cerebral thrombosis
- congenital anomalies
- gallbladder disease
- hypertension
- mesenteric thrombosis
- myocardial infarction
- neuro-ocular lesions (e.g., retinal thrombosis)
- pulmonary embolism
- thrombophlebitis
The following adverse reactions also have been reported in patients receiving oral contraceptives: nausea and vomiting, usually the most common adverse reaction, occurs in approximately 10 % or fewer of patients during the first cycle.
The following other reactions, as a general rule, are seen less frequently or only occasionally:
Blood and lymphatic system disorders: hemolytic uremic syndrome.
Ear and labyrinth disorders: auditory disturbances.
Eye disorders: cataracts, change in corneal curvature (steepening), intolerance to contact lenses, retinal thrombosis.
Gastrointestinal disorders: abdominal pain, diarrhea, gastrointestinal symptoms (such as abdominal cramps and bloating), pancreatitis.
General disorders and administrative site conditions: edema.
Hepatobiliary disorders: cholestatic jaundice.
Immune system disorders: hypersensitivity.
Infections and infestations: rhinitis, vaginitis, vaginal candidiasis.
Investigations: change in weight (increase or decrease), reduced tolerance to carbohydrates.
Metabolism and nutritional disorders: changes in appetite, porphyria.
Neoplasm benign, malignant and unspecified (including cysts and polyps): increase in size of uterine leiomyomata.
Nervous system disorders: chorea, dizziness, headache, migraine, optic neuritis.
Psychiatric disorders: changes in libido, mental depression, nervousness.
Renal and urinary disorders: cystitis-like syndrome, impaired renal function.
Reproductive system and breast disorders: amenorrhea during and after treatment, breakthrough bleeding, breast changes (tenderness, enlargement, secretion), change in menstrual flow, dysmenorrhea, endocervical hyperplasia, premenstrual like syndrome, possible diminution in lactation when given immediately postpartum, spotting, temporary infertility after discontinuation of treatment, vaginal discharge.
Skin and subcutaneous tissue disorders: chloasma or melasma which may persist, erythema multiforme, erythema nodosum, hemorrhagic eruption, hirsutism, loss of scalp hair, rash (including allergic rash), urticaria.
Vascular disorder: Raynaud’s phenomenon.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety data set [intention-to-treat (ITT) cohort] for levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets includes 4035 91-day cycles (13,293 28-day cycles) from studies PSE-301, PSE-302 and PSE-304 combined. The ITT cohort includes patients with at least one complete cycle on treatment.
Pivotal study PSE-301 was a Phase III, randomized, multicenter clinical trial conducted to evaluate the efficacy and safety of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets and another 91-day oral contraceptive regimen for one year (4 91-day cycles). The second 91-day regimen is identical to levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets, except that higher dose of ethinyl estradiol-alone is administered during the last 7 days of each 91-day cycle (see 14 CLINICAL TRIALS). This second higher dose-regimen is investigational and is not approved for use in Canada.
Supportive study PSE-302 was a Phase III, randomized, multicenter, clinical trial conducted to evaluate the efficacy and safety of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets, an investigational 91-day regimen. The duration of study PSE-302 was one year (4 91-day cycles). Safety data with a 28-day oral contraceptive containing a similar strength of levonorgestrel (0.15 mg) and ethinyl estradiol (0.03 mg) but taken in a conventional monthly (21 days levonorgestrel/ethinyl estradiol followed by placebo for 7 days) regimen is also available for one year from study PSE-302.
Study PSE-304 was an extension safety study in which subjects who completed the one-year PSE-301 or PSE-302 studies were eligible to receive either levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets or the investigational higher dose 91-day regimen for up to an additional three years, following their one-year exposure to any of the regimens in the PSE-301/302 studies. Over the course of PSE-304, all patients initially assigned to receive the higher dose investigational 91-day regimen were ultimately switched over to receive levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets. Despite the switch, all subjects were analyzed in the group to which they were originally assigned.
Table 2 shows the adverse events reported by at least 2% or more of treated patients in pivotal study PSE-301.
Table 2: Treatment-emergent adverse events reported at a frequency of ≥ 2 % of subjects in Study PSE-301
| MedDRA System Organ Class and Preferred Term | Pivotal Study PSE-301 | Supportive Study PSE-302 | |||||||||||
Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets (N=1006) | Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets (N=95) | 21/7 Regimena (N=93) | |||||||||||
| N | % | N | % | N | % | ||||||||
| Gastrointestinal Disorders | |||||||||||||
| Nausea | 45 | 4.47 | 3 | 3.16 | 7 | 7.53 | |||||||
| Abdominal distension | 25 | 2.49 | 2 | 2.11 | 2 | 2.15 | |||||||
General Disorders and Administration Site Conditions | |||||||||||||
| Fatigue | 29 | 2.88 | 0 | 0.00 | 1 | 1.08 | |||||||
| MedDRA System Organ Class and Preferred Term | Pivotal Study PSE-301 | Supportive Study PSE-302 | |||||||||||
Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets (N=1006) | Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets (N=95) | 21/7 Regimena (N=93) | |||||||||||
| N | % | N | % | N | % | ||||||||
| Infections And Infestations | |||||||||||||
| Nasopharyngitis | 72 | 7.16 | 8 | 8.42 | 12 | 12.90 | |||||||
| Sinusitis NOS | 65 | 6.46 | 7 | 7.37 | 3 | 3.23 | |||||||
Upper respiratory tract infection NOS | 49 | 4.87 | 4 | 4.21 | 1 | 1.08 | |||||||
| Urinary tract infection NOS | 45 | 4.47 | 4 | 4.21 | 7 | 7.53 | |||||||
| Pharyngitis streptococcal | 31 | 3.08 | 5 | 5.26 | 2 | 2.15 | |||||||
| Fungal infection NOS | 26 | 2.58 | 1 | 1.05 | 4 | 4.30 | |||||||
| Bronchitis NOS | 25 | 2.49 | 3 | 3.16 | 1 | 1.08 | |||||||
| Investigations | |||||||||||||
| Weight increased | 53 | 5.27 | 0 | 0.00 | 1 | 1.08 | |||||||
Musculoskeletal and Connective Tissue Disorders | |||||||||||||
| Back pain | 21 | 2.09 | 1 | 1.05 | 2 | 2.15 | |||||||
| Nervous System Disorders | |||||||||||||
| Headache NOS | 39 | 3.88 | 3 | 3.16 | 3 | 3.23 | |||||||
| Psychiatric Disorders | |||||||||||||
| Mood swings | 35 | 3.48 | 2 | 2.11 | 2 | 2.15 | |||||||
| Depression | 30 | 2.98 | 4 | 4.21 | 1 | 1.08 | |||||||
| Reproductive system and Breast Disorders | |||||||||||||
| Intermenstrual bleeding | 116 | 11.53 | 10 | 10.53 | 2 | 2.15 | |||||||
| Menorrhagia | 58 | 5.77 | 4 | 4.21 | 2 | 2.15 | |||||||
| Dysmenorrhoea | 36 | 3.58 | 2 | 2.11 | 4 | 4.30 | |||||||
| Breast tenderness | 29 | 2.88 | 1 | 1.05 | 1 | 1.08 | |||||||
Skin And Subcutaneous Tissue Disorders | |||||||||||||
| Acne NOS | 52 | 5.17 | 8 | 8.42 | 1 | 1.08 | |||||||
a LNG 0.150 mg/ EE 0.03 mg for 21 days followed by 7 days of placebo
Treatment-emergent adverse events were similar with the 91-day higher dose supplemental EE regimen.
Treatment-emergent adverse events most commonly reported in study PSE-304 (3-year extension) were similar to those observed in study PSE-301 (1-year treatment).
8.3 Less Common Clinical Trial Adverse Reactions
Less Common Clinical Trial Adverse Drug Reactions (≥ 1% to < 2%)
The following adverse events were reported in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm at a frequency ≥ 1% to < 2% in study PSE-301:
Gastrointestinal Disorders: diarrhoea, vomiting, abdominal pain, dental discomfort, dyspepsia.
General Disorders and Administration Site Conditions: hypersensitivity.
Infections And Infestations: vaginosis fungal, influenza, vaginitis bacterial, gastroenteritis viral.
Musculoskeletal and Connective tissue Disorders: arthralgia, peripheral swelling.
Nervous System Disorders: migraine, headache aggravated, dizziness.
Psychiatric Disorders: libido decreased, anxiety, irritability.
Respiratory, Thoracic and Mediastinal Disorders: pharyngitis, sinus congestion.
Less Common Clinical Trial Adverse Drug Reactions (< 1%)
Blood and Lymphatic System Disorders: anemia NOS.
Cardiac disorders: mitral valve prolapse, palpitations, tachycardia.
Ear and labyrinth disorders: ear congestion, ear pain, vertigo.
Endocrine disorders: acquired hypothyroidism, goitre, thyroid nodule.
Eye disorders: conjunctivitis, dry eye, optic neuritis.
Gastrointestinal disorders: abdominal pain upper, abdominal pain lower, appendicitis, food poisoning, gastritis, haematemesis, haematochezia, haemorrhoids, hiatus hernia, loose stools, nausea aggravated, oesophageal reflux aggravated, pancreatitis, salivary gland calculus, small intestinal obstruction, tooth impacted.
General disorders and administration site conditions: chest pain, feeling hot, hangover, influenza like illness, malaise, mass, oedema, oedema peripheral, pain, pyrexia, thirst, ulcer, weakness.
Hepatobiliary disorders: cholelithiasis, cholecystitis.
Immune systems disorders: drug hypersensitivity, hypersensitivity NOS, seasonal allergy.
Infections and infestations: abscess, bacterial infection, bladder infection, breast cellulitis, candidial infection, cervicitis, cystitis NOS, dermatophytosis, dry socket, ear infection NOS, eye infection, gastroenteritis NOS, gastroenteritis salmonella, gastroenteritis shigella, genitourinary chlamydia infection, gingivitis infection, helicobacter infection, herpes simplex, herpes zoster, hordeolum, infected insect bite, infectious mononucleosis, kidney infection, laryngitis chronic, localised infection, otitis media, pelvic inflammatory disease, periodontitis, post procedural site wound infection, pneumonia NOS, respiratory tract infection NOS, sialoadenitis, skin and subcutaneous tissue abscess, skin infection, tooth caries, vaginal candidiasis, vaginal infection, vaginitis, vulvovaginitis trichomonal.
Injury, poisoning and procedural complications: abrasion NOS, animal bite, arthropod bite, arthropod sting, back injury NOS, clavicle fracture, foot fracture, hand fracture, joint sprain, laceration, ligament injury NOS, limb injury NOS, muscle strain, post procedural haemorrhage, post procedural pain, radius fracture, rib fracture, road traffic accident, tooth injury, thermal burn, wrist fracture.
Investigations: blood pressure diastolic increased, blood pressure increased, blood testosterone decreased, blood testosterone increased, blood triglycerides increased, heart rate increased, lipids increased, liver function tests abnormal, weight decreased.
Metabolism and nutrition disorders: anorexia, appetite decreased, appetite increased NOS, diabetes mellitus, fluid retention, hypercholesterolaemia, insulin resistance.
Musculoskeletal and connective tissue disorders: arthritis, axillary mass, chondritis, costochondritis, intervertebral disc degeneration, intervertebral disc herniation, joint swelling, joint stiffness, myalgia, muscle cramp, neck pain, neck stiffness, osteopenia, pain in extremity, pain in jaw, rheumatoid arthritis aggravated, temporomandibular joint disorder, tendonitis.
Neoplasms benign, malignant and unspecified (including cyst and polyps): cyst, fibrocystic breast disease, malignant melanoma, uterine fibroids, uterine fibroids aggravated.
Nervous system disorders: carpal tunnel syndrome, cervical root pain, convulsions, dizziness, facial palsy, hyperaesthesia, hypoasthesia, increased activity, migraine aggravated, migraine with aura, nerve compression, paraesthesia, sciatica, syncope, tension headaches, vasovagal attack, visual field defect.
Pregnancy, puerperium and perinatal conditions: Pregnancy NOS.
Psychiatric disorders: affect lability, anxiety aggravated, bruxism, depression aggravated, depressed mood, emotional distress, insomnia exacerbated, irritability, major depressive disorder NOS, orgasm abnormal, panic attack, paranoia, sleep disorder, stress symptoms, suicidal ideation.
Renal and urinary disorders: bladder spasm, calculus renal NOS, urinary frequency, urinary incontinence, urine odour abnormal, urinary retention, urinary tract obstruction, urinary tract pain.
Reproductive systems and breast disorders: breast discharge, breast pain, breast engorgement, breast enlargement, cervical dysplasia, dyspareunia NOS, endometriosis, galactorrhoea, genital pruritus female, genital rash, menstruation irregular, ovarian cyst, pelvic pain NOS, polycystic ovaries, post coital bleeding, uterine spasm, vaginal discharge, vaginal irritation, vulval disorder, vulvovaginal discomfort, vulvovaginal dryness.
Respiratory, thoracic and mediastinal disorders: asthma, asthma aggravated, cough, dyspnoea, hoarseness, laryngitis, paranasal sinus hypersecretion, pleurisy, rhinitis, rhinitis allergic NOS, rhinorrhoea, upper respiratory tract congestion.
Skin and subcutaneous tissue disorders: acne aggravated, contusion, dermatitis, dermatitis allergic, eczema, erythema nodosum, face oedema, folliculitis, hair disorder, hair growth abnormal, hair texture abnormal, hidradenitis, hypotrichosis, ingrowing nail, nail disorder, night sweats, photosensitivity reaction, pityriasis rosea, pruritus generalised, rash pruritic, skin atrophy, skin hyperpigmentation, skin irritation, swelling face, urticaria.
Social circumstances: exposure to communicable disease.
Vascular disorders: hypertension aggravated, orthostatic hypotension.
Vaginal bleeding
Intermenstrual bleeding and menorrhagia were the most commonly reported treatment-emergent adverse events leading to study discontinuation in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm in study PSE-301. See also 7 WARNINGS AND PRECAUTIONS, Genitourinary.
As well, in supportive study PSE-302, intermenstrual bleeding and menorrhagia were more commonly reported as treatment-emergent adverse events in the subjects treated with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets versus the subjects treated with LNG 0.150 mg/EE 0.03 mg for 21 days followed by 7 days placebo. See Table 2, above.
Unscheduled bleeding and/or spotting per 28-day patient-month
In pivotal study PSE-301, the median number of days of unscheduled bleeding and/or spotting decreased from 2.8 days per patient-month in the first 91-day cycle to 1.0 day per patient-month in the 4th 91-day cycle.
In supportive study PSE-302, the median number of days of unscheduled bleeding and/or spotting ranged from 2.5 days per patient-month in the first 91-day cycle, decreasing to 1.6 days per patient-month in the 4th 91-day cycle in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm. Subjects treated with LNG 0.150 mg/EE 0.03 mg for 21 days followed by 7 days placebo experienced a median 0-2 days per month of unscheduled bleeding and/or spotting, depending on the 28-day cycle evaluated.
Scheduled bleeding and/or spotting per 91-day or 28-day cycle
In pivotal study PSE-301, the median number of days of scheduled bleeding and/or spotting per 91-day cycle was consistent at 3 days in all four 91-day cycles in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm.
In supportive study PSE-302, the median number of days of scheduled bleeding and/or spotting in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm was 4 days per 91-day cycle in the first cycle, decreasing to 2.5 days in the 4th 91-day cycle. The median number of days of scheduled bleeding and/or spotting per 28-day cycle in the subjects treated with LNG 0.150 mg/EE 0.03 mg for 21 days followed by 7 days placebo ranged from 2-3 days from cycles 1 through to 13.
Total bleeding and/or spotting per 28-day patient-month
In pivotal study PSE-301, use of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets were associated with a median 4.3 days total bleeding and/ or spotting per patient month in the first 91-day cycle, decreasing to 2.0 days per patient-month in the 4th 91-day cycle.
In supportive study PSE-302, the median number of total bleeding and/or spotting days in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm decreased from 4.3 days per patient-month in the first 91-day cycle to 3.1 days per patient-month in the 4th 91-day cycle. The median number of total bleeding and/or spotting days in the subjects treated with LNG 0.150mg/EE 0.03mg for 21 days followed by 7 days placebo ranged from 3-5 days per month over the course of the 13 28-day cycles.
Endometrial biopsies
In supportive study PSE-302, endometrial biopsies were conducted in 63 women treated with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets both at baseline and during the last cycle of treatment. Forty-six (46) of these 63 women completed the full year of study. There were no reports of endometrial hyperplasia or endometrial cancer on end-of-treatment endometrial biopsy in any of the four treatment arms. See also 8.5 Post-Market Adverse Reactions section, below.
Thromboembolic events
There was one case of venous thromboembolism in a woman with Factor V Leiden mutation treated with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets in study PSE-301 and one case of non-Q wave myocardial infarction secondary to coronary spasm in another woman treated with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets in study PSE-304. See also 8.5 Post-Market Adverse Reactions section, below.
Weight
In PSE-301, median weight gain in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets group was 2.0 lbs. In supportive study PSE- 302, there was a potential for slightly greater weight gain from baseline in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets (median 2.0 lbs) treatment arm versus the LNG 0.15 mg/EE 0.03 mg (21/7 regimen) treatment arm (median 1.0 lbs).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Laboratory data with an oral contraceptive containing a similar strength of levonorgestrel (0.15 mg) and ethinyl estradiol (0.03 mg) but taken in a conventional 21/7 monthly regimen (21 days of combination estrogen/progestin therapy followed by 7 days of placebo) is available for one year only from study PSE-302.
In study PSE-302, 11.9% of subjects in the treatment arm versus 7.8% in the LNG 0.15 mg/EE 0.03 mg (21/7 regimen) treatment arm who had normal triglycerides at baseline had values at the end of treatment that exceeded the upper limit of normal. No subjects in either of these two treatment arms had a shift in LDL cholesterol from normal at baseline to above upper limit of normal at the end-of-treatment. No notable differences were observed between treatment groups for shifts to low HDL cholesterol at end of treatment. In PSE-301, 13.2 % of subjects in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm who had normal triglycerides at baseline had values at the end of treatment that exceeded the upper limit of normal, 5.8% had a shift in LDL cholesterol from normal at baseline to above the upper limit of normal at the end-of-treatment and 2.3% had a shift to low HDL cholesterol at the end of treatment.
In study PSE-302, 6.3% of subjects in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm versus 4.8% of subjects in the LNG 0.15 mg/EE 0.03 mg (21/7 regimen) treatment arm with normal serum glucose at baseline had values at end of treatment that exceeded the upper limit of normal. In PSE-301 2.1% of subjects on levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets with normal serum glucose levels at baseline had values at end of treatment that exceeded the upper limit of normal.
In study PSE-302, 6.1% of subjects in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm versus 0% of subjects in the LNG 0.15mg/EE 0.03mg (21/7 regimen) treatment arm with normal ALT at baseline had values at end of treatment that exceeded the upper limit of normal. As well, in study PSE-302, 4.5% of subjects in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets treatment arm versus 0% of subjects in the LNG 0.15 mg/EE 0.03 mg (21/7 regimen) treatment arm with normal AST at baseline had values at end of treatment that exceeded the upper limit of normal. In PSE-301, 8.2% of subjects on levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets with normal ALT levels at baseline had values at end of treatment that exceeded the upper limit of normal, and 5.3% with normal AST levels at baseline had values at end of treatment that exceeded the upper limit of normal.
The clinical significance of the laboratory results (median change from baseline) as noted above is unknown, however, as there was a large range of both decreases and increases in serum lipids, glucose and liver enzymes in all treatment arms in studies PSE-301 and PSE-302. See also 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS for information regarding lipids, glucose metabolism and liver disease as related to use of hormonal contraceptives in general.
8.5 Post-Market Adverse Reactions
The following other serious and unexpected adverse events have been reported in users of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets in the post marketing period. These adverse events are compiled from spontaneous reports and are listed regardless of frequency and whether or not a causal relationship with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets has been established.
Gastrointestinal Disorders: rectal spasm.
Infections and Infestations: appendicitis.
Investigations: blood lactate dehydrogenase increased.
Nervous System Disorders: brain oedema, cerebral thrombosis, cerebrovascular accident, intracranial pressure increased, loss of consciousness.
Neoplasm: uterine leiomyoma.
Respiratory, Thoracic and Mediastinal Disorders: pulmonary embolism.
Reproductive System and Breast Disorders: endometrial hyperplasia, haemorrhagic ovarian cyst, uterine enlargement, menometrorrhagia.
Vascular Disorders: deep vein thrombosis, thrombosis.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
The concurrent administration of oral contraceptives with other drugs may lead to breakthrough bleeding and/or may result in an altered response to either agent (see Tables 3 and 4). Reduced effectiveness of the oral contraceptive, should it occur, is more likely with the low-dose formulations. It is important to ascertain all drugs that a patient is taking, both prescription and non-prescription, before oral contraceptives are prescribed.
9.3 Drug-Behavioural Interactions
Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels. This risk increases with age and becomes significant in oral contraceptive users older than 35 years of age. Women should be counselled not to smoke.
No studies on the effects of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets on the ability to drive or use machines have been performed.
9.4 Drug-Drug Interactions
The drugs listed in Tables 3 and 4 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
| Table 3: | Drugs Which May Decrease the Efficacy of Oral Contraceptives | |||
Class of Compound | Drug | Effect | Clinical comment | |
| Antacids | Decreased intestinal absorption of progestins. | Dose two hours apart. | ||
| Antibiotics | Ampicillin Cotrimoxazole Penicillin | Enterohepatic circulation disturbance, intestinal hurry. | For short course, use additional method or use another drug. For long course, use another method. | |
Rifabutin Rifampin | Increased metabolism of progestins. Suspected acceleration of estrogen metabolism. | Use another method. | ||
Chloramphenicol Metronidazole Neomycin Nitrofurantoin Sulfonamides Tetracyclines | Induction of hepatic microsomal enzymes. Also disturbance of enterohepatic circulation. | For short course, use additional method or use another drug. For long course, use another method. | ||
| Table 3: | Drugs Which May Decrease the Efficacy of Oral Contraceptives | |||
Class of Compound | Drug | Effect | Clinical comment | |
| Troleandomycin | May retard metabolism of oral contraceptives, increasing the risk of cholestatic jaundice. | |||
| Anticonvulsants | Carbamazepine Ethosuximide Felbamate Lamotrigine Oxcarbazepine Phenobarbital Phenytoin Primidone Topiramate | Induction of hepatic microsomal enzymes. Rapid metabolism of estrogen and increased binding of progestin and ethinyl estradiol to SHBG. | Use higher dose oral contraceptives (50 mcg ethinyl estradiol), another drug or another method. | |
| Antifungals | Griseofulvin | Stimulation of hepatic metabolism of contraceptive steroids may occur. | Use another method. | |
Cholesterol Lowering Agents | Clofibrate | Reduces elevated serum triglycerides and cholesterol; this reduces oral contraceptive efficacy. | Use another method. | |
HIV protease inhibitors | Ritonavir | Induction of hepatic microsomal enzymes. | Use another drug or another method. | |
Non-nucleoside reverse transcriptase inhibitors | Nevirapine | Induction of hepatic microsomal enzymes. | Use another drug or another method. | |
Sedatives and Hypnotics | Barbiturates Benzodiazepines Chloral hydrate Glutethimide Meprobamate | Induction of hepatic microsomal enzymes. | For short course, use additional method or another drug. For long course, use another method or higher dose oral contraceptives. | |
| Other Drugs | Analgesics Antihistamines Antimigraine preparations Phenylbutazone Vitamin E | Reduced oral contraceptive efficacy has been reported. Remains to be confirmed. | ||
Oral contraceptives may interfere with the metabolism of other drugs. Accordingly, plasma and tissue concentrations may either increase (e.g., cyclosporine) or decrease (e.g., lamotrigine).
| Table 4: | Modification of Other Drug Action by Oral Contraceptives | |||
| Class of Compound | Drug | Effect | Clinical comment | |
| Alcohol | Possible increased levels of ethanol or acetaldehyde | Use with caution. | ||
Alpha-II adrenoreceptor agents | Clonidine | Sedation effect increased. | Use with caution. | |
| Anticoagulants | All | Oral contraceptives increase clotting factors, decrease efficacy. However, oral contraceptives may potentiate action in some patients. | Use another method. | |
| Anticonvulsants | All | Estrogens may increase risk of seizures. | Use another method. | |
| Lamotrigine | Combination oral contraceptives have been shown to significantly decrease plasma concentrations of lamotrigine likely due to induction of lamotrigine glucoronidation. Decreased lamotrigine levels may lead to breakthrough seizures. | Use another method. | ||
Antidiabetic drugs | Oral hypoglycaemics and insulin | Oral contraceptives may impair glucose tolerance and increase blood glucose. | Use low-dose estrogen and progestin oral contraceptive or another method. Monitor blood glucose. | |
Antihypertensive agents | Guanethidine and methyldopa | Estrogen component causes sodium retention, progestin has no effect. | Use low-dose estrogen oral contraceptive or use another method. | |
| Beta blockers | Increased drug effect (decreased metabolism). | Adjust dose of drug if necessary. Monitor cardiovascular status. | ||
| Antipyretics | Acetaminophen | Increased metabolism and renal clearance. | Dose of drug may have to be increased. | |
| Antipyrine | Impaired metabolism. | Decrease dose of drug. | ||
| ASA | Effects of ASA may be decreased by the short-term use of oral contraceptives. | Patients on chronic ASA therapy may require an increase in ASA dosage. | ||
Aminocaproic acid | Theoretically, a hypercoagulable state may occur because oral contraceptives augment clotting factors. | Avoid concomitant use. | ||
| Table 4: | Modification of Other Drug Action by Oral Contraceptives | |||
| Class of Compound | Drug | Effect | Clinical comment | |
| Betamimetic | Isoproterenol | Estrogen causes decreased response to these drugs. | Adjust dose of drug as necessary. Discontinuing oral contraceptives can result in excessive drug activity. | |
| agents | ||||
| Caffeine | The actions of caffeine may be enhanced as oral contraceptives may impair the hepatic metabolism of caffeine. | Use with caution. | ||
Cholesterol lowering agents | Clofibrate | Their action may be antagonized by oral contraceptives. Oral contraceptives may also increase metabolism of clofibrate. | May need to increase dose of clofibrate. | |
| Corticosteroids | Prednisone | Markedly increased serum levels. | Possible need for decrease in dose. | |
| Cyclosporine | May lead to an increase in cyclosporine levels and hepatotoxicity. | Monitor hepatic function. The cyclosporine dose may have to be decreased. | ||
| Folic acid | Oral contraceptives have been reported to impair folate metabolism. | May need to increase dietary intake, or supplement. | ||
Hepatis C drug combinations | glecaprevir/ pibrentasvir and sofosbuvir/ velpatasvir/ voxilaprevir | Potential ALT elevations | Avoid concomitant use. | |
| Meperidine | Possible increased analgesia and CNS depression due to decreased metabolism of meperidine. | Use combination with caution. | ||
Phenothiazine tranquilizers | All phenothiazines, reserpine and similar drugs | Estrogen potentiates the hyperprolactinemia effect of these drugs. | Use other drugs or lower dose oral contraceptives. If galactorrhea or hyperprolactinemia occurs, use other method. | |
Sedatives and hypnotics | Chlordiazepoxide Lorazepam Oxazepam Diazepam | Increased effect (increased metabolism). | Use with caution. | |
| Theophylline | All | Decreased oxidation, leading to possible toxicity. | Use with caution. Monitor theophylline levels. | |
Tricyclic antidepressants | Clomipramine (possibly others) | Increased side effects: i.e., depression | Use with caution. | |
| Table 4: | Modification of Other Drug Action by Oral Contraceptives | |||
| Class of Compound | Drug | Effect | Clinical comment | |
| Vitamin B12 | Oral contraceptives have been reported to reduce serum levels of Vitamin B12 | May need to increase dietary intake, or supplement. | ||
Several of the anti-HIV protease inhibitors (e.g., ritonavir) and non-nucleoside reverse transcriptase inhibitors (e.g. nevirapine) have been studied with co-administration of combination oral contraceptives; significant changes (increase and decrease) in the mean AUC of the estrogen and progestogen and the potential to affect hepatic metabolism have been noted in some cases. The efficacy and safety of oral contraceptive products may be affected. Healthcare providers should refer to the label of the individual anti-HIV protease inhibitor for further drug-drug interaction information.
No formal drug-drug interaction studies have been conducted with levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Herbal products containing St. John’s Wort (hypericum perforatum) may induce hepatic enzymes (cytochrome P450) and p-glycoprotein transporter and may reduce the effectiveness of contraceptive steroids. This may also result in breakthrough bleeding.
9.7 Drug-Laboratory Test Interactions
Results of laboratory tests should be interpreted with the knowledge that the patient is taking an oral contraceptive.
The following laboratory tests are modified:
Liver Function Tests
Aspartate serum transaminase (AST) - variously reported elevations.
Alkaline phosphatase and gamma-glutamyl transferase (GGT) - slightly elevated.
Coagulation Tests
Minimal elevation of test values reported for such parameters as prothrombin and Factors VII, VIII, IX and X.
Thyroid Function Tests
Protein binding of thyroxine is increased as indicated by increased total serum thyroxine concentrations and decreased T3 resin uptake.
Lipoproteins
Small changes of unproven clinical significance may occur in lipoprotein cholesterol fractions.
Gonadotropins
LH and FSH levels are suppressed by the use of oral contraceptives. Wait two weeks after discontinuing the use of oral contraceptives before measurements are made.
Glucose tolerance
Oral glucose tolerance remained unchanged or was slightly decreased.
Tissue Specimens
Pathologists should be advised of hormonal contraceptive use when specimens from surgical procedures and/or Pap smears are submitted for examination.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and changes in the endometrium (which reduce the likelihood of implantation).
10.2 Pharmacodynamics
Norgestrel is a racemate containing equal parts of D- and L-enantiomers. The L-enantiomer has been tested in a broad range of biological assays and its inactivity has been confirmed. The D-enantiomer (named levonorgestrel) accounts for all the biological activity found in norgestrel, as levonorgestrel was twice as potent as the racemate in experiments in which norgestrel was effective.
10.3 Pharmacokinetics
Absorption: Ethinyl estradiol and levonorgestrel are rapidly absorbed with maximum plasma concentrations occurring within 2 hours after levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets administration. No specific investigation of the absolute bioavailability of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets in humans has been conducted. However, published literature indicates that levonorgestrel is rapidly and completely absorbed after oral administration (bioavailability nearly 100%) and is not subject to first-pass metabolism. Ethinyl estradiol is rapidly and almost completely absorbed from the gastrointestinal tract but, due to first-pass metabolism in gut mucosa and liver, the bioavailability of ethinyl estradiol is approximately 55%.
The effect of food on the rate and extent of absorption of levonorgestrel and ethinyl estradiol following oral administration of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets has not been evaluated.
The single-dose and steady state pharmacokinetics of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets after daily dosing over the entire 91-day extended cycle was evaluated. The daily exposure to levonorgestrel and ethinyl estradiol on Day 21, corresponding to the end of a typical 3-week contraceptive regimen, and on Day 84, at the end of an extended cycle regimen, were similar. The mean plasma pharmacokinetic parameters of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets following a single daily dose of one levonorgestrel/ethinyl estradiol combination tablet, for 84 days, in normal healthy women are reported in Table 5.
Table 5: Mean Pharmacokinetic Parameters for Levonorgestrel / Ethinyl Estradiol Tablets and Ethinyl Estradiol Tablets During Daily One Tablet Dosing for 84 Days
AUC0-24 (mean ± SD) | Cmax (mean ± SD) | Tmax (mean ± SD) | T1/2 el (h) | ||||||
| Levonorgestrel (N= 28-30) | |||||||||
| Day 1 | 18.2 ± 6.1 ng•hr/mL | 3.0 ± 1.0 ng/mL | 1.3 ± 0.4 hours | ||||||
| Day 21 | 64.4 ± 25.1 ng•hr/mL | 6.2 ± 1.6 ng/mL | 1.3 ± 0.4 hours | ||||||
| Day 84 | 60.2 ± 24.6 ng•hr/mL | 5.5 ± 1.6 ng/mL | 1.3 ± 0.3 hours | 39 ± 12 hours | |||||
| Ethinyl Estradiol (N= 28-30) | |||||||||
| Day 1 | 509.3 ± 172.0 pg•hr/mL | 69.8 ± 25.9 pg/mL | 1.5 ± 0.3 hours | ||||||
| Day 21 | 837.1 ± 271.2 pg•hr/mL | 99.6 ± 31.3 pg/mL | 1.5 ± 0.3 hours | ||||||
| Day 84 | 791.5 ± 215.0 pg•hr/mL | 91.3 ± 32.5 pg/mL | 1.6 ± 0.3 hours | ||||||
| Day 91 | 867.5 ± 277.6 pg•hr/mL | 102.3 ± 50.4 pg/mL | 1.4 ± 0.4 hours | 18 ± 4 hours | |||||
Distribution: The apparent volume of distribution of each levonorgestrel and ethinyl estradiol are reported to be approximately 1.8 L/kg and 4.3 L/kg, respectively. Levonorgestrel is about 97.5-99% protein-bound, principally to the sex hormone binding globulin (SHBG) and, to a lesser extent, serum albumin. Ethinyl estradiol is about 95-97% bound to serum albumin. Ethinyl estradiol does not bind to SHBG, but induces SHBG synthesis, which leads to decreased levonorgestrel clearance. Following repeated daily dosing of combination levonorgestrel and ethinyl estradiol oral contraceptives, levonorgestrel plasma concentrations accumulate more than predicted based on single-dose kinetics, due in part, to increased SHBG levels that are induced by ethinyl estradiol and a possible reduction in hepatic metabolic capacity.
Metabolism: Following absorption, levonorgestrel is conjugated at the 17β-OH position to form sulfate and to a lesser extent, glucuronide conjugates in plasma. Significant amounts of conjugated and unconjugated 3α,5β-tetrahydrolevonorgestrel are also present in plasma, along with much smaller amounts of 3α,5α-tetrahydrolevonorgestrel and 16β-hydroxylevonorgestrel. Levonorgestrel and its Phase I metabolites are excreted primarily as glucuronide conjugates. Metabolic clearance rates may differ among individuals by several-fold, and this may account in part for the wide variation observed in levonorgestrel concentrations among users.
First-pass metabolism of ethinyl estradiol involves formation of ethinyl estradiol-3-sulfate in the gut wall followed by 2-hydroxylation of a portion of the remaining untransformed ethinyl estradiol by hepatic CYP3A4. Levels of CYP3A4 vary widely among individuals and can explain the variation in rates of ethinyl estradiol hydroxylation. Hydroxylation at the 4-, 6- and 16- positions may also occur, although to a much lesser extent than 2-hydroxylation. The various hydroxylated metabolites are subject to further methylation and/or conjugation.
Elimination: About 45% of levonorgestrel and its metabolites are excreted in the urine and about 32% are excreted in feces, mostly as glucuronide conjugates. The terminal elimination half-life for levonorgestrel after a single dose of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets was found to be about 39 hours. Ethinyl estradiol is excreted in the urine and feces as glucuronide and sulfate conjugates and it undergoes enterohepatic recirculation. The terminal elimination half-life of ethinyl estradiol after a single dose of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets was found to be about 18 hours.
Special Populations and Conditions
Pediatrics: The safety and efficacy of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets has not been established in women under the age of 18 years.
Use of this product before menarche is not indicated.
Geriatrics: QUATERNA is not indicated for use in post-menopausal women.
Genetic Polymorphism: No data are available.
Ethnic Origin: No formal studies on the effect of race on the pharmacokinetics of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets have been conducted.
Hepatic Insufficiency: No formal studies have been conducted to evaluate the effect of hepatic disease on the pharmacokinetics of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets. However, steroid hormones may be poorly metabolized in patients with impaired liver function.
Renal Insufficiency: No formal studies have been conducted to evaluate the effect of renal disease on the pharmacokinetics of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15°C to 30°C). Keep out of reach and sight of children and pets.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Levonorgestrel
Ethinyl Estradiol
Chemical name: Levonorgestrel: 13β-ethyl-17β-hydroxy-18,19-dinor-17α-pregn-4-en-20-yn-3-one
Ethinyl Estradiol: 17α-Ethynyl-1,3,5(10)-estratriene-3,17-β-diol
Molecular formula: Levonorgestrel: C21H28O2
Ethinyl Estradiol: C20H24O2
Molecular mass: Levonorgestrel: 312.45 g/mol
Ethinyl Estradiol: 296.40 g/mol
Structural formula:
Levonorgestrel:
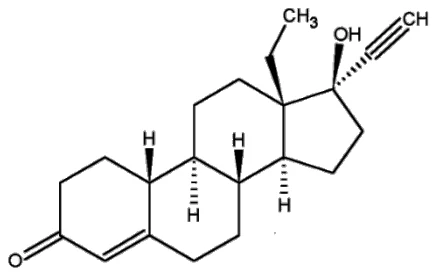
Ethinyl Estradiol:
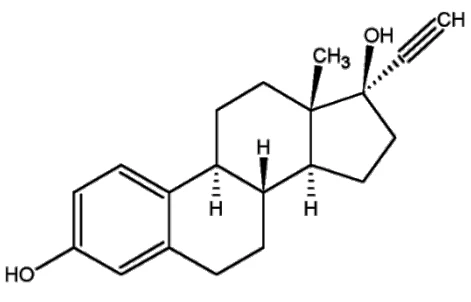
Solubility: Levonorgestrel: Practically insoluble in water and n-hexane, slightly soluble in acetone and ethanol, sparingly soluble in dichloromethane and soluble in chloroform
Ethinyl Estradiol: Freely soluble in ether, ethanol, acetone, dioxane, soluble in alkali hydroxide solutions, sparingly soluble in chloroform and practically insoluble in water.
Melting points:
Levonorgestrel: 232-239°C
Ethinyl Estradiol: 180-186°C
Biological properties:
Levonorgestrel: This is a synthetic progestogen in the (-)-isomer of norgestrel. It is the biologically active form of the racemic norgestrel.
Ethinyl Estradiol: This is a synthetic estrogen.
14 CLINICAL TRIALS
General Information
The following table gives reported pregnancy rates for various forms of birth control, including no birth control. The reported rates represent the number of women out of 100 who would become pregnant in one year.
Reported Pregnancies per 100 Women per Year:
Combination pill less than 1 to 2
Intrauterine device (IUD) less than 1 to 6
Condom with spermicidal foam or gel 1 to 6
Mini-pill 3 to 6
Condom 2 to 12
Diaphragm with spermicidal foam or gel 3 to 18
Spermicide 3 to 21
Sponge with spermicide 3 to 28
Cervical cap with spermicide 5 to 18
Periodic abstinence (rhythm), all types 2 to 20
No birth control 60 to 85
14.1 Clinical Trials by Indication
Prevention of Pregnancy
Table 6 - Summary of patient demographics for clinical trials in the prevention of pregnancy
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| PSE-301 | Phase III, randomized, multicenter clinical trial to evaluate the efficacy and safety of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets and another 91-day oral contraceptive regimen | LNG (150 mcg) and EE (30 mcg) 84 days active combination drug followed by 7 days EE monotherapy (30 mcg), orala LNG (150 mcg) and EE (30 mcg) 84 days active combination drug followed by 7 days EE monotherapy (10 mcg), oral Duration: One year (4 x 91-Day Cycles) | Randomized: 1024 Treated patients (Safety): 1006 Treated at least 1 Complete Cycle (ITT): 799 ITT, 18-35 Years of Age (PITT): 708 | 26.2b (18.0-35.0) | Female (100%) |
a The 91-day regimen with a higher dose of ethinyl estradiol-alone administered during the last 7 days of each cycle is not approved for use in Canada.
b For the PITT cohort.
A total of 1006 subjects were treated with at least one dose of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets. Of these, 799 subjects completed at least one 91-day complete cycle on treatment (ITT cohort). The PITT cohort was the primary cohort used for the efficacy analyses, and was comprised of patients 18-35 years of age with at least one complete cycle on treatment.
In the PITT cohort, 708 women 18 to 35 years of age (mean: 26.2), were studied to assess the safety and efficacy of levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets. The racial demographic of all enrolled women was: Caucasian (79.4%), African-American (11.3%), Hispanic (4.8%), Asian (2.3%), and Other (2.3%). The weight range for these women treated was
94 to 360 lb (BMI: 17.1 to 56.5), with a mean weight of 154.9 lb (BMI: 25.9). Among the women in the trial, 19.5% were current smokers; 68.4% had a history of oral contraceptive (OC) use prior to enrollment, 21.5% a history of OC use but not within the six months prior to enrollment, and 10.2% no prior history of OC use. Demographics were generally similar for the ITT cohort.
The discontinuation rate was 50.3% in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets arm (506/1006 patients discontinued the study early). Among all treated patients, the most common reasons for discontinuation were adverse events (16.3% in the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets arm). The most commonly reported adverse events (AEs) leading to study discontinuation were intermenstrual bleeding and menorrhagia. In the levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets arm, 62 of 164 (37.8%) AEs that lead to study discontinuation were related to bleeding and/or spotting.
In all cohorts (safety, ITT and PITT), over 95% of the patients took their daily pill over 80% of the time.
Study results
As noted above, the PITT cohort was the primary cohort used for the efficacy analyses, and was comprised of patients 18-35 years of age with at least one complete cycle on treatment. Cycles in which another form of birth control was used (including condoms) were excluded from the assessment of the Pearl Index. The Pearl Index for levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets for the PITT cohort, excluding cycles in which another birth control method was used was 1.77 (95% CI 0.71-3.65), based on 7 pregnancies that occurred on-treatment over 5125.25 28-day equivalent patient months (1577 91-day cycles). The Pearl Index for levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets for the subset of the PITT cohort with compliant use, excluding cycles in which another birth control method was used 0.78 (95% CI 0.16-2.28), based on 3 pregnancies that occurred on-treatment over 4982.25 28-day equivalent patient-months (1533 91-day cycles). In the compliant-use subset analysis, patient cycles that were deemed non-compliant (where non-compliance is defined as all cycles in which a patient skipped two or more consecutive pills or had a pattern of substantial non-compliance with study medication or used a prohibited concomitant medication that may interact with oral contraceptive therapy) were not used. Substantial non-compliance was defined as an overall pill compliance of less than 80%.
The cumulative failure rate for levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets at the end of one year of treatment, estimated by the life table method, was 0.89% (95% CI 0.37%, 2.18%).
See summary table of Pearl Indices and Life Table Analyses for levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets, below.
Pearl Index Calculation of Treatment Failure Rates: Patients 18-35 Years of Age With at Least One Complete Cycle of Treatment (PITT) – Excluding Cycles in Which Another Birth Control Method was Used
| Treatment Group | Number of Cycles | Number of 28-Day Patient Months | Number of On-Drug Pregnancies | Pearl Index (95% CI) |
|---|---|---|---|---|
| Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets | 1577 | 5125.25 | 7 | 1.77 (0.71,3.65) |
Life Table Estimates of Treatment Failure Rates - Patients 18-35 Years of Age With at Least One Complete Cycle of Treatment (PITT)
| Levonorgestrel / ethinyl estradiol tablets and ethinyl estradiol tablets | |||
| Cycle | N | Pregnancy Rate | 95% C.I. |
| 1 | 709 | 0.0029 | 0.0007-0.0115 |
| 2 | 667 | 0.0045 | 0.0015-0.0140 |
| 3 | 530 | 0.0065 | 0.0024-0.0174 |
| 4 | 464 | 0.0089 | 0.0037-0.0218 |
See also 8.2 Clinical Trial Adverse Reactions section for discussion of safety results from PSE-301.
14.2 Comparative Bioavailability Studies
A randomized, single dose (2 x levonorgestrel 0.15 mg/ethinyl estradiol 0.03 mg), crossover comparative bioavailability study of QUATERNA (Mylan Pharmaceuticals ULC) and SEASONIQUE® (Teva Canada Limited) was conducted in healthy, adult, female human subjects under fasting conditions. A summary of the data from the 26 subjects that were included in the statistical analysis are presented in the tables below.
Table 7 - SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILTY DATA
Levonorgestrel (levonorgestrel / ethinyl estradiol tablets)
Levonorgestrel (2 x levonorgestrel 0.15 mg/ethinyl estradiol 0.03 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUC0-72h (ng·h/mL) | 88.1 98.2 (45.4) | 85.1 96.6 (48.6) | 103.5 | 98.1 – 109.2 |
Cmax (ng/mL) | 6.5 7.2 (45.6) | 6.9 7.5 (41.9) | 94.3 | 87.9 – 101.2 |
Tmax3 (h) | 1.8 (1.0 – 4.0) | 1.5 (1.0 – 3.5) | ||
1 QUATERNA (levonorgestrel /ethinyl estradiol) tablets 0.15 mg/0.03 mg (Mylan Pharmaceuticals ULC)
2 SEASONIQUE® (levonorgestrel /ethinyl estradiol) tablets 0.15 mg/0.03 mg (Teva Canada Limited)
3 Expressed as the median (range) only
Due to the long elimination half-life of levonorgestrel AUCI and T1/2 could not be accurately calculated from the data obtained in this study.
Table 8 - SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILTY DATA
Ethinyl Estradiol (levonorgestrel / ethinyl estradiol tablets)
Ethinyl Estradiol (2 x levonorgestrel 0.15 mg/ethinyl estradiol 0.03 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (pg·h/mL) | 1587.7 1754.2 (47.9) | 1602.4 1757.6 (43.7) | 99.1 | 95.6 – 102.7 |
| AUCI 3 (pg·h/mL) | 1755.9 1965.8 (43.7) | 1768.7 1925.5 (41.4) | 99.3 | 96.0 – 102.7 |
Cmax (pg/mL) | 148.6 158.8 (37.6) | 156.2 168.3 (38.7) | 95.2 | 90.9 – 99.6 |
Tmax4 (h) | 1.5 (1.5 – 2.5) | 1.5 (1.5 – 2.5) | ||
T½5 (h) | 1.7 (20.4) | 1.7 (16.9) | ||
1 QUATERNA (levonorgestrel /ethinyl estradiol) tablets 0.15 mg/0.03 mg (Mylan Pharmaceuticals ULC)
2 SEASONIQUE® (levonorgestrel /ethinyl estradiol) tablets 0.15 mg/0.03 mg (Teva Canada Limited)
3 n=25
4 Expressed as the median (range) only
5 Expressed as the arithmetic mean (range) only
A randomized, single dose (2 x ethinyl estradiol 0.01 mg), crossover comparative bioavailability study of QUATERNA (Mylan Pharmaceuticals ULC) and SEASONIQUE® (Teva Canada Limited) was conducted in healthy, adult, female human subjects under fasting conditions. A summary of the data from the 26 subjects that were included in the statistical analysis are presented in the table below.
Table 9 - SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILTY DATA
Ethinyl Estradiol (ethinyl estradiol tablets)
Ethinyl Estradiol (2 x 0.01 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (pg·h/mL) | 1587.7 1754.2 (47.9) | 1602.4 1757.6 (43.7) | 99.1 | 95.6 – 102.7 |
| AUCI (pg·h/mL) | 1755.9 1965.8 (43.7) | 1768.7 1925.5 (41.4) | 99.3 | 96.0 – 102.7 |
Cmax (pg/mL) | 148.6 158.8 (37.6) | 156.2 168.3 (38.7) | 95.2 | 90.9 – 99.6 |
Tmax3 (h) | 2.0 (1.5 – 2.0) | 1.5 (1.0 – 2.5) | ||
T½4 (h) | 1.7 (20.4) | 1.7 (16.9) | ||
1 QUATERNA (ethinyl estradiol) tablets 0.01 mg (Mylan Pharmaceuticals ULC)
2 SEASONIQUE® (ethinyl estradiol) tablets 0.01 mg (Teva Canada Limited)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (range) only
15 MICROBIOLOGY
Not applicable.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Levonorgestrel and ethinyl estradiol have been extensively studied and are well-characterized pharmaceuticals. These approved pharmaceuticals in combination are both safe and effective when indicated for the prevention of pregnancy.
Carcinogenicity:
The association of mammary tumours in beagle dogs and steroid contraceptive use has been extensively reported in the published literature. Much of the published literature looked at the suitability of the beagle dog as a test model to assess the tumourigenic potential of certain progestogens in inducing mammary tumours and comparing it to the human model. Early toxicology studies in beagle dogs showed the overall incidence of mammary tumours were more common and frequent by a factor of three to four than in women. However, the beagle dog differs significantly from other animal species and humans mainly due to its differences in reproductive physiology and endocrinology. The beagle dog species is more susceptible to show mammary tumours as it has a fairly high natural incidence of mammary cancer. Some of the published literature has reported that many of the more potent progestogens have been shown to induce mammary tumours compared to the less potent progestational compounds. Evidence has shown that long-term administration of norgestrel has less progestational activity and incidence of mammary tumours over more potent progestogens.
Steroid-related canine mammary tumours were unlikely to be indicative of a potential hazard to women.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrSEASONIQUE® Tablets, 0.15 mg and 0.03 mg (levonorgestrel and ethinyl estradiol) and 0.01 (ethinyl estradiol), submission control 279038, Product Monograph, Teva Canada Limited. (FEB 14, 2024)
IM