


Product Monograph - Natazia
SUMMARY PRODUCT INFORMATION
| Table 1 – Product Information Summary | |||
| Route of Administration | Dosage Form, Strength | Clinically Relevant Nonmedicinal Ingredients | |
| Oral | 3.0 mg estradiol valerate tablets 2.0 mg estradiol valerate and 2.0 mg dienogest tablets 2.0 mg estradiol valerate and 3.0 mg dienogest tablets 1.0 mg estradiol valerate tablets | Lactose monohydrate For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING section. | |
INDICATIONS AND CLINICAL USE
NATAZIA (estradiol valerate, and estradiol valerate and dienogest) is indicated for:
- Conception control
- Treatment of idiopathic heavy menstrual bleeding following appropriate diagnostic investigations in women who choose to use NATAZIA as their method of contraception
The efficacy of NATAZIA in women with a body mass index (BMI) of >30 kg/m2 has not been evaluated.
CONTRAINDICATIONS
NATAZIA should not be used in women with:
- a history of or actual thrombophlebitis or thromboembolic disorders
- a history of or actual cerebrovascular disorders
- a history of or actual myocardial infarction or coronary artery disease
- valvular heart disease with complications
- a history of or actual prodromi of a thrombosis (eg, transient ischemic attack, angina pectoris)
presence of severe or multiple risk factor(s) for arterial or venous thrombosis:
- severe hypertension (persistent values of ≥ 160/100 mmHg)
- hereditary or acquired predisposition for venous or arterial thrombosis, such as Factor V Leiden mutation and activated protein C (APC-) resistance, antithrombin-III-deficiency, protein C deficiency, protein S deficiency, hyperhomocysteinemia and antiphospholipid antibodies (anticardiolipin antibodies, lupus anticoagulant)
- severe dyslipoproteinemia
- smoking, if over age 35
- diabetes mellitus with vascular involvement
- major surgery associated with an increased risk of postoperative thromboembolism
- prolonged immobilization
- active liver disease or history of, or actual benign or malignant liver tumors
- known or suspected carcinoma of the breast
- carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia
- undiagnosed abnormal uterine/vaginal bleeding
- steroid-dependent jaundice, cholestatic jaundice, history of jaundice in pregnancy
- any ocular lesion arising from ophthalmic vascular disease, such as partial or complete loss of vision or defect in visual fields
- known or suspected pregnancy
- current or history of migraine with focal aura
- history of or actual pancreatitis if associated with severe hypertriglyceridemia
- hypersensitivity to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions Women over 35 years old who smoke should not use NATAZIA. Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. Women should be counselled not to smoke (see WARNINGS AND PRECAUTIONS - Cardiovascular section below). Hormonal contraceptives DO NOT PROTECT against sexually transmitted infections (STIs) including HIV/AIDS. While using hormonal contraceptives, it is advisable to use latex or polyurethane condoms IN COMBINATION WITH hormonal contraceptives to protect against STIs. |
General
Discontinue Medication at the Earliest Manifestation of:
A. Thromboembolic and Cardiovascular Disorders such as thrombophlebitis, pulmonary embolism, cerebrovascular disorders, myocardial ischemia, mesenteric thrombosis, and retinal thrombosis
B. Conditions that Predispose to Venous Stasis and to Vascular Thrombosis (eg, immobilization after accidents or confinement to bed during long-term illness). Other nonhormonal methods of contraception should be used until regular activities are resumed. For use of oral contraceptives when surgery is contemplated, see WARNINGS AND PRECAUTIONS – Perioperative Considerations.
C. Visual Defects - Partial or Complete
D. Papilledema or Ophthalmic Vascular Lesions
E. Severe Headache of Unknown Etiology or Worsening of Pre-existing Migraine Headache
F. Increase in Epileptic Seizures
The following information is provided from studies of COCs.
The use of combination hormonal contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity and mortality is small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly if associated with the presence of other risk factors such as hypertension, hyperlipidemias, obesity, and diabetes. Other medical conditions which have been associated with adverse circulatory events include systemic lupus erythematosus, (1) hemolytic uremic syndrome, (2-4) chronic inflammatory bowel disease, (Crohn’s disease or ulcerative colitis), (5) sickle cell disease, (6) valvular heart disease, and atrial fibrillation. (7, 8)
The following conditions have been reported to occur or deteriorate with both pregnancy and COC use, although a direct association with COCs has not been firmly established: porphyria, (9) systemic lupus erythematosus, (10) hemolytic uremic syndrome, (11) Sydenham’s chorea, (12, 13) herpes gestationis, (14, 15) and otosclerosis-related hearing loss. (16)
The information contained in this section is principally from studies carried out in women who used COCs with higher formulations of estrogens and progestins than those in common use today. The effect of long-term use of combination hormonal contraceptives with lower doses of both estrogen and progestin administered orally remains to be determined.
Drug Interactions
Women who take medications that are strong CYP3A4 inducers (eg, carbamazepine, phenytoin, rifampicin, and St. John’s wort) should not choose NATAZIA as their oral contraceptive (OC) while using these inducers and for at least 28 days after discontinuation of these inducers due to the possibility of decreased contraceptive efficacy (see also DRUG INTERACTIONS).
Carcinogenesis and Mutagenesis
Malignancies may be life-threatening or may have a fatal outcome.
Breast Cancer
Cases of breast cancer have been reported in users of NATAZIA (see ADVERSE REACTIONS).
Increasing age and a strong family history are the most significant risk factors for the development of breast cancer. Other established risk factors include obesity, nulliparity, and late age for first full-term pregnancy. The identified groups of women that may be at increased risk of developing breast cancer before menopause are long-term users of oral contraceptives (more than 8 years) and starters at early age. In a few women, the use of oral contraceptives may accelerate the growth of an existing but undiagnosed breast cancer. Since any potential increased risk related to oral contraceptive use is small, there is no reason to change prescribing habits at present.
A meta-analysis from 54 epidemiological studies reported that there is a slightly increased relative risk (RR = 1.24) of having breast cancer diagnosed in women who are currently using OCs, mainly estrogen-progestin preparations. The excess risk gradually disappears during the course of the 10 years after cessation of COC use. (17) Because breast cancer is rare in women under 40 years of age, the excess number of breast cancer diagnoses in current and recent COC users is small in relation to the overall lifetime risk of breast cancer.
Women receiving oral contraceptives should be instructed in self-examination of their breasts. Their physicians should be notified whenever any masses are detected. A yearly clinical breast examination is also recommended, because, if breast cancer should develop, drugs that contain estrogen may cause a rapid progression.
Cervical Cancer
The most important risk factor for cervical cancer is persistent human papillomavirus infection (HPV). Some epidemiological studies have indicated that long-term use of COCs may further contribute to this increased risk, but there continues to be controversy about the extent to which this finding is attributable to confounding effects, eg, cervical screening and sexual behaviour including use of barrier contraceptives.
Hepatocellular Carcinoma
Hepatocellular carcinoma may be associated with oral contraceptives. The risk appears to increase with duration of hormonal contraceptive use. However, the attributable risk (the excess incidence) of liver cancers in oral contraceptive users is extremely small. A liver tumor should be considered in the differential diagnosis when severe upper abdominal pain, liver enlargement, or signs of intra-abdominal hemorrhage occur in women taking COCs.
Cardiovascular
There have been reports of cardiovascular events including myocardial infarction and deep vein thrombosis in women using NATAZIA (see ADVERSE REACTIONS).
Predisposing Factors for Coronary Artery Disease
Cigarette smoking increases the risk of serious cardiovascular side effects and mortality. Birth control pills increase this risk, particularly in women over 35 years of age, and with the number of cigarettes smoked. Convincing data are available to support an upper age limit of 35 years for oral contraceptive use by women who smoke. For this reason, combination oral contraceptives, including NATAZIA, should not be used by women who are over 35 years of age and smoke.
Other women who are independently at high risk for cardiovascular disease include those with diabetes, hypertension, abnormal lipid profile, or a family history of these. Whether oral contraceptives accentuate this risk is unclear.
In low-risk, non-smoking women of any age, the benefits of oral contraceptive use outweigh the possible cardiovascular risks associated with low-dose formulations. Consequently, oral contraceptives may be prescribed for these women up to the age of menopause.
Hypertension
Patients with essential hypertension whose blood pressure is well-controlled may be given hormonal contraceptives, but only under close supervision. If a significant elevation of blood pressure in previously normotensive or hypertensive subjects occurs at any time during the administration of the drug, cessation of medication is necessary. An increase in blood pressure has been reported in women taking COCs, and this increase is more likely in older women and with extended duration of use. The incidence of hypertension increases with increasing concentration of progestin.
Also see WARNINGS AND PRECAUTIONS - Hematologic and ADVERSE REACTIONS - Postmarket Adverse Drug Reactions.
Endocrine and Metabolism
Diabetes
Current low-dose oral contraceptives exert minimal impact on glucose metabolism. Diabetic patients, or those with a family history of diabetes, should be observed closely to detect any worsening of carbohydrate metabolism. Patients predisposed to diabetes who can be kept under close supervision may be given oral contraceptives. Young diabetic patients whose disease is of recent origin, well-controlled, and not associated with hypertension or other signs of vascular disease such as ocular fundal changes, should be monitored more frequently while using oral contraceptives.
Lipid and Other Metabolic Effects
A small proportion of women will have adverse lipid changes while on oral contraceptives. Alternative contraception should be used in women with uncontrolled dyslipidemia (see also CONTRAINDICATIONS). Elevations of plasma triglycerides may lead to pancreatitis and other complications.
Gastrointestinal
Published epidemiological studies indicate a possible association of COC use and the development of Crohn’s disease and ulcerative colitis, although this has not been firmly established. (18-23)
Genitourinary
Uterine/Vaginal Bleeding
Persistent irregular uterine/vaginal bleeding requires assessment to exclude underlying pathology.
Based on patient diaries from three clinical trials evaluating the safety and efficacy of NATAZIA, 10-23% of women per cycle experienced intracyclic bleeding (see ADVERSE REACTIONS -Clinical Trial Adverse Drug Reactions).
Fibroids
Patients with fibroids (leiomyomata) should be carefully observed. Sudden enlargement, pain, or tenderness requires discontinuation of the use of oral contraceptives.
Hematologic
Epidemiological studies have suggested an association between the use of ethinyl estradiol - containing COCs and an increased risk of arterial and venous thrombotic and thromboembolic diseases such as myocardial infarction, deep venous thrombosis, pulmonary embolism, and of cerebrovascular accidents. These events occur rarely.
The use of any combined oral contraceptive carries an increased risk of venous thromboembolism (VTE) compared with no use. The excess risk of VTE is highest during the first year a woman ever uses a combined oral contraceptive or restarts (following a 4-week or greater pill-free interval) the same or a different COC. Data from a large, prospective 3-armed cohort study suggest that this increased risk is mainly present during the first 3 months. (24) VTE is life-threatening and is fatal in 1% to 2% of cases.
A large, prospective 3-armed cohort study has shown that the frequency of VTE diagnosis ranges from about 8 to 10 per 10 000 woman-years in users of oral contraceptives with low estrogen content (<50 µg ethinyl estradiol). (25) The most recent data suggest that the frequency of VTE diagnosis is approximately 4.4 per 10 000 woman-years in nonpregnant, non-COC users and ranges from 20 to 30 per 10 000 woman-years in pregnant women or postpartum. (25, 26)
Overall the risk for VTE in users of oral contraceptives with low estrogen content (<50 µg ethinyl estradiol) is two- to three-fold higher than for nonusers of COCs who are not pregnant and remains lower than the risk associated with pregnancy and delivery.
VTE, manifesting as deep venous thrombosis (DVT) and/or pulmonary embolism (PE), may occur during the use of all COCs.
Extremely rarely, thrombosis has been reported to occur in other blood vessels (eg, hepatic, mesenteric, renal, cerebral, or retinal veins and arteries) in COC users.
Symptoms of DVT can include: unilateral swelling of the leg or along a vein in the leg; pain or tenderness in the leg, which may be felt only when standing or walking; increased warmth in the affected leg; red or discolored skin on the leg.
Symptoms of PE can include: sudden onset of unexplained shortness of breath or rapid breathing; sudden coughing which may bring up blood; sharp chest pain which may increase with deep breathing; sense of anxiety; severe light headedness or dizziness; rapid or irregular heartbeat. Some of these symptoms (eg, “shortness of breath”, “coughing”) are nonspecific and might be misinterpreted as more common or less severe events (eg, respiratory tract infections).
The risk for arterial thromboembolism (ATE) in users of oral contraceptives with low estrogen content (<50 µg ethinyl estradiol) ranges from about 1 to 3 cases per 10 000 woman-years.
An arterial thromboembolic event (ATE) can include cerebrovascular accident, vascular occlusion, or myocardial infarction (MI). Symptoms of a cerebrovascular accident can include: sudden numbness or weakness of the face, arm, or leg, especially on one side of the body; sudden confusion, trouble speaking or understanding; sudden trouble seeing in one or both eyes; sudden trouble walking, dizziness, loss of balance or coordination; sudden, severe or prolonged headache with no known cause; loss of consciousness or fainting with or without seizure. Other signs of vascular occlusion can include: sudden pain, swelling, and slight blue discoloration of an extremity; acute abdomen.
Symptoms of MI can include: pain, discomfort, pressure, heaviness, sensation of squeezing or fullness in the chest, arm, or below the breastbone; discomfort radiating to the back, jaw, throat, arm, stomach; fullness, indigestion or choking feeling; sweating, nausea, vomiting, or dizziness; extreme weakness, anxiety, or shortness of breath; rapid or irregular heartbeats.
Arterial thromboembolic events are life-threatening and may have a fatal outcome.
Also see WARNINGS AND PRECAUTIONS - Cardiovascular and ADVERSE REACTIONS - Postmarket Adverse Drug Reactions.
Other Risk Factors for Venous or Arterial Thromboembolism or of a Cerebrovascular Accident
Other generalized risk factors for venous or arterial thromboembolism include, but are not limited to, age, severe obesity (body mass index >30 kg/m2), a personal history, a positive family history (the occurrence of VTE/ATE in a direct relative at a relatively early age may indicate genetic predisposition) and systemic lupus erythematosus. If a hereditary or acquired predisposition for venous or arterial thromboembolism is suspected, the woman should be referred to a specialist for advice before deciding on any COC use. The risk of VTE/ATE may be temporarily increased with prolonged immobilization, major surgery, or trauma. In these situations, it is advisable to discontinue COC use (in the case of elective surgery at least four weeks in advance) and not to resume COC use until two weeks after complete remobilization. Also, patients with varicose veins and leg cast should be closely supervised. Other risk factors may include smoking (with heavier smoking and increasing age, the risk further increases, especially in women over 35 years of age), dyslipoproteinemia, hypertension, migraine, valvular heart disease, and atrial fibrillation.
Biochemical factors that may be indicative of hereditary or acquired predisposition for venous or arterial thrombosis include Activated Protein C (APC) resistance, hyperhomocysteinemia, antithrombin-III deficiency, protein C deficiency, protein S deficiency, antiphospholipid antibodies (anticardiolipin antibodies, lupus anticoagulant).
When considering risk/benefit, the physician should take into account that adequate treatment of a condition may reduce the associated risk of thrombosis and that the risk associated with pregnancy is higher than that associated with low-dose COCs (<0.05 mg ethinyl estradiol).
Hepatic/Biliary/Pancreas
Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal (see CONTRAINDICATIONS).
Jaundice
Patients who have had jaundice should be given oral contraceptives with great care and under close observation. Oral contraceptive-related cholestasis has been described in women with a history of pregnancy-related cholestasis. Women with a history of cholestasis may have the condition recur with subsequent hormonal contraceptive use.
The development of severe generalized pruritus or icterus requires that the medication be withdrawn until the problem is resolved.
If a patient develops jaundice that proves to be cholestatic in type, the use of oral contraceptives should not be resumed. In patients taking hormonal contraceptives, changes in the composition of the bile may occur and an increased incidence of gallstones has been reported (see CONTRAINDICATIONS).
Gallbladder Disease
Patients taking oral contraceptives have a greater risk of developing gallbladder disease requiring surgery within the first year of use. The risk may double after 4 or 5 years.
Hepatic Nodules
Hepatic nodules (adenoma and focal nodular hyperplasia) have been reported, particularly in long-term users of oral contraceptives. Although these lesions are extremely rare, they have caused fatal intra-abdominal hemorrhage and should be considered in women presenting with an abdominal mass, acute abdominal pain, or evidence of intra-abdominal bleeding.
Immune
Angioedema
Exogenous estrogens may induce or exacerbate symptoms of angioedema, in particular, in women with hereditary angioedema. (27-29)
Neurologic
Migraine and Headache
The onset or exacerbation of migraine or the development of headache of a new pattern that is recurrent, persistent, or severe requires discontinuation of hormonal contraceptives and evaluation of the cause. Women with migraine headaches who take oral contraceptives may be at increased risk of stroke (see CONTRAINDICATIONS).
Ophthalmologic
Ocular Disease
Patients who are pregnant or are taking oral contraceptives may experience corneal edema that may cause visual disturbances and changes in tolerance to contact lenses, especially of the rigid type. Soft contact lenses usually do not cause disturbances. If visual changes or alterations in tolerance to contact lenses occur, temporary or permanent cessation of wear may be advised.
Ocular Lesions
There have been clinical case reports of retinal thrombosis associated with the use of oral contraceptives. Oral contraceptives should be discontinued if there is unexplained partial or complete loss of vision, onset of proptosis or diplopia, papilledema, or retinal vascular lesions. Appropriate diagnostic and therapeutic measures should be undertaken immediately.
Perioperative Considerations
There is an increased risk of thromboembolic complications in oral contraceptive users after major surgery. If feasible, oral contraceptives should be discontinued and an alternative method substituted at least 1 month prior to MAJOR elective surgery. Oral contraceptive use should not be resumed until the first menstrual period after hospital discharge following surgery.
Psychiatric
Patients with a history of emotional disturbances, especially the depressive type, may be more prone to have a recurrence of depression while taking oral contraceptives. In cases of a serious recurrence, a trial of an alternate method of contraception should be made, which may help to clarify the possible relationship. Women with premenstrual syndrome (PMS) may have a varied response to oral contraceptives, ranging from symptomatic improvement to worsening of the condition.
Renal
Fluid Retention
Hormonal contraceptives may cause some degree of fluid retention. They should be prescribed with caution and only with careful monitoring in patients with conditions which might be aggravated by fluid retention.
Sexual Function/Reproduction
Reproduction/Fertility
A high incidence of embryolethality was observed with estradiol valerate in rabbits and rats, and impaired fertility of rat female offspring exposed in utero to dienogest (1.0 mg/kg/day) given to mothers during late pregnancy (gestational day 17) and end of lactation. It is therefore recommended that pregnancy outcome and postnatal development following inadvertent intrauterine exposure of the fetus should be monitored in women using NATAZIA for contraception.
Return to Fertility
After discontinuing oral contraceptive therapy, the patient should delay pregnancy until at least 1 normal spontaneous menstrual cycle has occurred in order to date the pregnancy. An alternate contraceptive method should be used during this time.
Amenorrhea
In some women, withdrawal bleeding may not occur during the tablet-free interval. (30) If the COC has been taken according to directions, it is unlikely that the woman is pregnant. However, if the COC has not been taken according to directions prior to the first missed withdrawal bleed, or if two withdrawal bleeds are missed, pregnancy must be ruled out before COC use is continued.
Women who are not pregnant and use NATAZIA may experience amenorrhea. Based on patient diaries, amenorrhea occurs in approximately 16% of cycles in women using NATAZIA. Pregnancy should be ruled out in the event of amenorrhea occurring in two or more consecutive cycles. Some women may encounter amenorrhea or oligomenorrhea after stopping COCs, especially when such a condition was pre-existent.
Women having a history of oligomenorrhea, secondary amenorrhea, or irregular cycles may remain anovulatory or become amenorrheic following discontinuation of estrogen-progestin combination therapy.
Amenorrhea, especially if associated with breast secretion that continues for 6 months or more after withdrawal, warrants a careful assessment of hypothalamic-pituitary function.
Reduced Efficacy
The efficacy of COCs may be reduced in the event of missed tablets, gastrointestinal disturbances or concomitant medication (see DOSAGE AND ADMINISTRATION and DRUG INTERACTIONS).
Skin
Chloasma may occasionally occur with use of COCs, especially in women with a history of chloasma gravidarum. Women with a tendency to chloasma should avoid exposure to the sun or ultraviolet radiation while taking COCs.
Special Populations
Body Mass Index
The safety and efficacy of NATAZIA in women with a BMI of >30 kg/m2 has not been evaluated.
Pregnant Women
Oral contraceptives should not be taken by pregnant women. If pregnancy occurs during treatment with NATAZIA, further intake must be stopped. However, if conception accidentally occurs while taking the pill, there is no conclusive evidence that the estrogen and progestin contained in the oral contraceptive will damage the developing child.
Nursing Women
In breastfeeding women, the use of oral contraceptives results in the hormonal components being excreted in breast milk and may reduce its quantity and quality. If the use of oral contraceptives is initiated after the establishment of lactation, there does not appear to be any effect on the quantity and quality of the milk. There is no evidence that low-dose oral contraceptives are harmful to the nursing infant.
If possible, the nursing mother should be advised not to use oral contraceptives, but to use other forms of contraception until she has completely weaned her child.
Pediatrics
The safety and efficacy of NATAZIA have not been established in women under the age of 18 years. Use of this product before menarche is not indicated.
Geriatrics
NATAZIA is not indicated for use in postmenopausal women.
Monitoring and Laboratory Tests
Physical Examination and Follow-up
Before oral contraceptives are used, a thorough history and physical examination should be performed, including a blood pressure determination and the family case history carefully noted. In addition, disturbances of the clotting system must be ruled out if any members of the family have suffered from thromboembolic diseases (eg, deep vein thrombosis, stroke, myocardial infarction) at a young age. Breasts, liver, extremities, and pelvic organs should be examined and a Papanicolaou (PAP) smear should be taken if the patient has been sexually active.
The first follow-up visit should be done 3 months after oral contraceptives are prescribed. Thereafter, examinations should be performed at least once a year, or more frequently if indicated. At each annual visit, examination should include those procedures that were done at the initial visit as outlined above or per recommendations of the Canadian Task Force on the Periodic Health Examination.
Interference with Laboratory Tests
The use of COCs may change the results of some laboratory tests, such as coagulation factors, lipids, glucose tolerance, and binding proteins. Women on thyroid hormone replacement therapy may need increased doses of thyroid hormone because serum concentrations of thyroid-binding globulin increase with the use of COCs.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives:
- benign and malignant hepatic tumors
- cerebral hemorrhage
- cerebral thrombosis
- congenital anomalies
- gallbladder disease
- hypertension
- mesenteric thrombosis
- myocardial infarction
- neuro-ocular lesions (eg, retinal thrombosis)
- pulmonary embolism
- thrombophlebitis
The following adverse reactions also have been reported in patients receiving oral contraceptives: nausea and vomiting, usually the most common adverse reaction, occurs in approximately 10% or fewer of patients during the first cycle. The following other reactions, as a general rule, are seen less frequently or only occasionally:
- abdominal pain
- amenorrhea during and after treatment
- auditory disturbances
- breakthrough bleeding
- breast changes (tenderness, enlargement, and secretion)
- cataracts
- changes in appetite
- change in corneal curvature (steepening)
- changes in libido
- change in menstrual flow
- change in weight (increase or decrease)
- chloasma or melasma which may persist
- cholestatic jaundice
- chorea
- cystitis-like syndrome
- mental depression
- diarrhea
- dizziness
- dysmenorrhea
- edema
- endocervical hyperplasia
- erythema multiforme
- erythema nodosum
- gastrointestinal symptoms (such as abdominal cramps and bloating)
- headache
- hemolytic uremic syndrome
- hemorrhagic eruption
- hirsutism
- hypersensitivity
- impaired renal function
- increase in size of uterine leiomyomata
- intolerance to contact lenses
- loss of scalp hair
- migraine
- nervousness
- optic neuritis
- pancreatitis
- porphyria
- possible diminution in lactation when given immediately postpartum
- premenstrual-like syndrome
- rash (allergic)
- Raynaud’s phenomenon
- reduced tolerance to carbohydrates
- retinal thrombosis
- rhinitis
- spotting
- temporary infertility after discontinuation of treatment
- urticaria
- vaginal candidiasis
- vaginal discharge
- vaginitis
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The clinical development programs were conducted independently for each of the 2 indications and utilized indication-specific inclusion criteria, study designs, and settings. Thus, the safety results of the studies are presented separately and are not pooled.
The following adverse drug reactions were reported at a frequency ≥1% in three clinical trials using NATAZIA as an oral contraceptive: breast discomfort including breast pain, nipple disorder and nipple pain (5.0%), intracyclic bleeding (metrorrhagia) including irregular menstruation (4.9%), headache including tension headache (3.1%), acne (2.8%), abdominal pain including abdominal distension (1.7%), amenorrhea (1.7%), dysmenorrhea (1.7%) and increased weight (1.5%).
The following adverse drug reactions were reported at a frequency ≥1% in pivotal clinical trials in patients who used NATAZIA in the treatment of heavy menstrual bleeding in women without organic pathology who desire oral contraception: breast discomfort including breast pain and breast tenderness (9.0%), headache (8.3%), acne (3.4%), intracyclic bleeding (metrorrhagia) (3.4%), nausea (3.4%), increased weight (3.0%), abdominal pain (2.7%), dysmenorrhea (2.7%), uterine/vaginal bleeding including spotting (2.3%), migraine (1.9%), mood changes (1.9%), fatigue (1.5%), decreased libido (1.5%), genital discharge (1.5%), increased liver enzymes (1.1%), vulvovaginal mycotic infection (1.1%), blood pressure changes (1.1%), emotional disorder (1.1%), insomnia (1.1%), and menorrhagia (1.1%).
The following serious drug reactions were reported in three clinical trials using NATAZIA as an oral contraceptive: deep vein thrombosis, myocardial infarction, focal nodular hyperplasia of the liver, uterine leiomyoma, and ruptured ovarian cyst.
The following serious drug reactions were reported in pivotal clinical trials in patients who used NATAZIA in the treatment of heavy menstrual bleeding in women without organic pathology who desire oral contraception: myocardial infarction, breast cancer in situ, chronic acalculous cholecystitis.
The following adverse drug reactions leading to study discontinuation were reported in three clinical trials using NATAZIA as an oral contraceptive: 10.2% of the women discontinued from the clinical trials due to an adverse reaction; the most frequent adverse reactions leading to discontinuation were intracyclic bleeding (metrorrhagia) including irregular menstruation (1.7%), acne (1.1%), headache (0.7%), and weight increase (0.7%).
The following adverse drug reactions leading to study discontinuation were reported in pivotal clinical trials in patients who used NATAZIA in the treatment of heavy menstrual bleeding in women without organic pathology who desire oral contraception: 10.2% of the women discontinued from the clinical trials due to an adverse reaction; the most frequent adverse reactions leading to discontinuation (each occurring at 0.8%) were anemia, nausea, headache, migraine, decreased libido, altered mood, and dysmenorrhea.
The comparative data of NATAZIA with an oral contraceptive on lipid profile, liver functions and coagulation are only available for up to 7 cycles. (31)
Less Common Clinical Trial Adverse Drug Reactions
The following adverse drug reactions were seen at a frequency of <1% and ≥0.1% in three clinical trials in patients who used NATAZIA as an oral contraceptive:
Gastrointestinal disorders: diarrhea, nausea, vomiting.
General disorders and administration site conditions: edema, irritability.
Infections and infestations: fungal infection, vaginal candidiasis, vaginal infection.
Metabolism and nutrition disorders: increased appetite, weight decreased.
Nervous system disorders: dizziness.
Psychiatric disorders: depression/depressed mood, libido decreased, mental disorder, mood change.
Reproductive system and breast disorders: breast enlargement, breast mass, cervical dysplasia, dysfunctional uterine bleeding, dyspareunia, fibrocystic breast disease, menorrhagia, menstrual disorder, ovarian cyst, pelvic pain, premenstrual syndrome, uterine leiomyoma, uterine spasm, vaginal discharge, vulvovaginal dryness.
Skin and subcutaneous tissue disorders: alopecia, pruritus, rash.
Vascular disorders: hypertension, migraine.
The following adverse drug reactions were seen at a frequency of <1% and ≥0.1% in pivotal clinical trials in patients who used NATAZIA in the treatment of heavy menstrual bleeding in women without organic pathology who desire oral contraception:
Cardiac disorders: Myocardial infarction, palpitations.
Eye disorders: Dry eye, eye swelling.
Gastrointestinal disorders: Constipation, dry mouth, vomiting.
General disorders and administration site conditions: Edema peripheral, pyrexia.
Hepatobiliary disorders: Cholecystitis chronic.
Infections and infestations: Pelvic inflammatory disease.
Lab tests: Smear cervix abnormal.
Metabolism and nutrition disorders: Fluid retention, increased appetite.
Musculoskeletal and connective tissue disorders: Muscle spasms, pain in jaw.
Neoplasm benign, malignant and unspecified (including cysts and polyps): Breast cancer in situ.
Psychiatric disorders: Depression/depressed mood, nightmare.
Renal and urinary disorders: Urinary tract pain.
Reproductive system and breast disorders: Breast discharge, breast enlargement, cervical polyp, cervix erythema, fibrocystic breast disease, menstrual disorder, ovarian cyst, pelvic pain, premenstrual syndrome, vulvovaginal dryness.
Respiratory, thoracic and mediastinal disorders: Asthma, dyspnea, epistaxis.
Skin and subcutaneous tissue disorders: Alopecia, hirsutism, hyperhidrosis, pruritus generalized, rash.
Vascular disorders: Hot flush, hypertension, phlebitis superficialis, vein pain.
Postmarket Adverse Drug Reactions
The following adverse reactions have been identified during post-approval use of NATAZIA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Gastrointestinal disorders: gastrointestinal symptoms (eg, abdominal pain)
Hepatobiliary disorders: gallbladder disease, hepatitis
Immune system disorders: hypersensitivity
Infections and infestations: vulvovaginal candidiasis
Metabolism and nutrition disorders: fluid retention, hypertriglyceridemia
Nervous system disorders: dizziness
Skin and subcutaneous tissue disorders: angioedema, chloasma, erythema multiforme, erythema nodosum
Vascular disorders: hypertension, venous and arterial thromboembolic events (including pulmonary emboli, deep vein thrombosis, cerebral thrombosis, myocardial infarction and stroke)
DRUG INTERACTIONS
Overview
The concurrent administration of oral contraceptives with other drugs may lead to breakthrough bleeding and/or may result in an altered response to either agent (see Table 2 and Table 3). Reduced effectiveness of the oral contraceptive, should it occur, is more likely with the low-dose formulations. It is important to ascertain all drugs that a patient is taking, both prescription and nonprescription, before oral contraceptives are prescribed.
Drug-Drug Interactions
| Table 2: Drugs Which May Decrease the Efficacy of Oral Contraceptives | |||||||
|---|---|---|---|---|---|---|---|
| Class of Compound | Drug | Proposed Mechanism | Suggested Management | ||||
| Antacids | Decreased intestinal absorption of progestins. | Dose 2 hours apart. | |||||
| Antibiotics (32) | Ampicillin Cotrimoxazole Penicillin | Enterohepatic circulation disturbance, intestinal hurry. | For short course, use additional non-hormonal method of contraception or use another drug. For long course, use another non-hormonal method of contraception. | ||||
Rifabutin Rifampin | Increased metabolism of progestins. Suspected acceleration of estrogen metabolism. Coadministration of a dienogest/estradiol valerate combination with rifampin led to significant decreases in steady-state concentrations and systemic exposures of dienogest and estradiol. The systemic exposures of dienogest and estradiol at steady state, measured by AUC(0-24h) were decreased by 83% and 44%, respectively. | Use another non-hormonal method of contraception. | |||||
Chloramphenicol Metronidazole Neomycin Nitrofurantoin Sulfonamides Tetracyclines | Induction of hepatic microsomal enzymes. Also disturbance of enterohepatic circulation. | For short course, use additional non-hormonal method of contraception or use another drug. For long course, use another non-hormonal method of contraception. | |||||
| Troleandomycin | May retard metabolism of oral contraceptives, increasing the risk of cholestatic jaundice. | ||||||
Anticonvulsants (33-35) | Carbamazepine Ethosuximide Felbamate Lamotrigine Oxcarbazepine Phenobarbital Phenytoin Primidone Topiramate | Induction of hepatic microsomal enzymes. Rapid metabolism of estrogen and increased binding of progestin and ethinyl estradiol to SHBG. | Use higher dose oral contraceptives (50 μg ethinyl estradiol), another drug or another non-hormonal method of contraception. | ||||
| Antifungals | Griseofulvin | Stimulation of hepatic metabolism of contraceptive steroids may occur. | Use another non-hormonal method of contraception. | ||||
| Cholesterol Lowering Agents | Clofibrate | Reduces elevated serum triglycerides and cholesterol; this reduces oral contraceptive efficacy. | Use another non-hormonal method of contraception. | ||||
| HCV Protease Inhibitors | Boceprevir Telaprevir | Remains to be confirmed. | Use another drug or another non-hormonal method of contraception. | ||||
| Table 2: Drugs Which May Decrease the Efficacy of Oral Contraceptives |
|---|
| Class of Compound | Drug | Proposed Mechanism | Suggested Management |
|---|---|---|---|
| HIV Protease Inhibitors | Ritonavir | Induction of hepatic microsomal enzymes. | Use another drug or another non-hormonal method of contraception |
| Non-nucleoside reverse transcriptase inhibitors (36, 37) | Nevirapine | Induction of hepatic microsomal enzymes. | Use another drug or another non-hormonal method of contraception. |
| Sedatives and Hypnotics | Barbiturates Benzodiazepines Chloral hydrate Glutethimide Meprobamate | Induction of hepatic microsomal enzymes. | For short course, use additional non-hormonal method of contraception or another drug. For long course, use another non-hormonal method of contraception or higher dose oral contraceptives. |
| Other Drugs | Analgesics Antihistamines Antimigraine preparations Phenylbutazone preparations Vitamin E | Reduced oral contraceptive efficacy has been reported. Remains to be confirmed. |
Oral contraceptives may interfere with the metabolism of other drugs. Accordingly, plasma and tissue concentrations may either increase (eg, cyclosporine) or decrease (eg, lamotrigine).
| Table 3: Modification of Other Drug Action by Oral Contraceptives | |||||||
|---|---|---|---|---|---|---|---|
| Class of Compound | Drug | Modification of Drug Action | Suggested Management | ||||
| Alcohol | Possible increased levels of ethanol or acetaldehyde | Use with caution. | |||||
Alpha-II adrenoreceptor agents | Clonidine | Sedation effect increased. | Use with caution. | ||||
| Anticoagulants | All | Oral contraceptives increase clotting factors, decrease efficacy. However, oral contraceptives may potentiate action in some patients. | Use another non-hormonal method of contraception. | ||||
| Anticonvulsants | All | Estrogens may increase risk of seizures. | Use another non-hormonal method of contraception. | ||||
| Lamotrigine | Decreased lamotrigine levels, may lead to breakthrough seizures. | Use another non-hormonal method of contraception. | |||||
| Antidiabetic drugs | Oral hypoglycemics and insulin | Oral contraceptives may impair glucose tolerance and increase blood glucose. | Use low-dose estrogen and progestin oral contraceptive or another non-hormonal method of contraception. Monitor blood glucose. | ||||
| Antihypertensive agents | Guanethidine and methyldopa | Estrogen component causes sodium retention, progestin has no effect. | Use low-dose estrogen oral contraceptive or use another non-hormonal method of contraception. | ||||
| Beta blockers | Increased drug effect (decreased metabolism). | Adjust dose of drug if necessary. Monitor cardiovascular status. | |||||
| Antipyretics | Acetaminophen | Increased metabolism and renal clearance. | Dose of drug may have to be increased. | ||||
| Antipyrine | Impaired metabolism. | Decrease dose of drug. | |||||
| ASA | Effects of ASA may be decreased by the short-term use of oral contraceptives. | Patients on chronic ASA therapy may require an increase in ASA dosage. | |||||
| Aminocaproic acid | Theoretically, a hypercoagulable state may occur because oral contraceptives augment clotting factors. | Avoid concomitant use. | |||||
| Betamimetic agents | Isoproterenol | Estrogen causes decreased response to these drugs. | Adjust dose of drug as necessary. Discontinuing oral contraceptives can result in excessive drug activity. | ||||
| Caffeine | The actions of caffeine may be enhanced as oral contraceptives may impair the hepatic metabolism of caffeine. | Use with caution. | |||||
| Cholesterol lowering agents | Clofibrate | Their action may be antagonized by oral contraceptives. Oral contraceptives may also increase metabolism of clofibrate. | May need to increase dose of clofibrate. | ||||
| Corticosteroids | Prednisone | Markedly increased serum levels. | Possible need for decrease in dose. | ||||
| Table 3: Modification of Other Drug Action by Oral Contraceptives |
|---|
| Class of Compound | Drug | Modification of Drug Action | Suggested Management |
|---|---|---|---|
| Cyclosporine | May lead to an increase in cyclosporine levels and hepatotoxicity. | Monitor hepatic function. The cyclosporine dose may have to be decreased. | |
| Folic acid | Oral contraceptives have been reported to impair folate metabolism. | May need to increase dietary intake, or supplement. | |
| Meperidine | Possible increased analgesia and CNS depression due to decreased metabolism of meperidine. | Use combination with caution. | |
| Phenothiazine tranquilizers | All phenothiazines, reserpine and similar drugs | Estrogen potentiates the hyperprolactinemia effect of these drugs. | Use other drugs or lower dose oral contraceptives. If galactorrhea or hyperprolactinemia occurs, use other non-hormonal method of contraception. |
| Sedatives and hypnotics | Chlordiazepoxide Diazepam Lorazepam Oxazepam | Increased effect (increased metabolism). | Use with caution. |
| Theophylline | All | Decreased oxidation, leading to possible toxicity. | Use with caution. Monitor theophylline levels. |
| Tricyclic antidepressants | Clomipramine (possibly others) | Increased side effects: eg, depression. | Use with caution. |
| Vitamin B12 | Oral contraceptives have been reported to reduce serum levels of Vitamin B12. | May need to increase dietary intake, or supplement. |
Substances increasing the clearance of COCs (diminished efficacy of COCs by enzyme-induction)
Drugs or herbal products that induce certain enzymes, including CYP3A4, may decrease the effectiveness of COCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include barbiturates, bosentan, felbamate, griseofulvin, oxcarbazepine, and topiramate. Women should be counselled to use an alternative method of contraception or a back-up method when moderate or weak enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability.
Dienogest is a substrate of cytochrome P450 (CYP) 3A4. Women who take medications that are strong CYP3A4 inducers (eg, carbamazepine, phenytoin, rifampicin, and St. John’s wort) should not choose NATAZIA as their OC while using these inducers and for at least 28 days after discontinuation of these inducers due to the possibility of decreased contraceptive efficacy.
The effect of the CYP3A4 inducer rifampicin was studied in healthy postmenopausal women. Co-administration of rifampicin with estradiol valerate/dienogest tablets led to a 52% and 83% decrease in the mean Cmax and AUC(0-24h), respectively, for dienogest and a 25% and 44% decrease in Cmax and AUC(0-24h), respectively, for estradiol at steady state.
Substances decreasing the clearance of COCs (enzyme inhibitors)
Strong and moderate CYP3A4 inhibitors such as azole antifungals (eg, ketoconazole, itraconazole, voriconazole, fluconazole), verapamil, macrolides (eg, clarithromycin, erythromycin), diltiazem and grapefruit juice, can increase plasma concentrations of the estrogen or the progestin or both.
In a clinical study investigating the effect of CYP3A4 inhibitors (ketoconazole and erythromycin), steady-state dienogest and estradiol plasma levels were increased. Co-administration with the strong CYP3A4 enzyme inhibitor ketoconazole resulted in a 2.86-fold and 1.57-fold increase of AUC(0-24h) at steady state for dienogest and estradiol, respectively. There was also a 1.94-fold and 1.65-fold increase of Cmax at steady state for dienogest and estradiol, respectively. Concomitant administration of the moderate inhibitor erythromycin resulted in a 1.62-fold and 1.33-fold increase of AUC(0-24h) at steady state for dienogest and estradiol, respectively. The clinical relevance of these interactions is unknown. There was also a 1.33-fold and 1.51-fold increase of Cmax at steady state for dienogest and estradiol, respectively.
Substances with variable effects on the clearance of COCs
Several of the anti-HIV/HCV protease inhibitors (eg, ritonavir, boceprevir, telaprevir) and nonnucleoside reverse transcriptase inhibitors (eg, nevirapine) have been studied with co-administration of oral combination hormonal contraceptives; significant changes (increase or decrease) in the mean AUC of the estrogen or progestin have been noted in some cases. The efficacy and safety of oral contraceptive products may be affected. Health care providers should refer to the label of the individual anti-HIV/HCV protease inhibitor for further drug-drug interaction information.
Drug-Food Interactions
There are no clinically relevant effects of food intake on the pharmacokinetics of NATAZIA. NATAZIA can be taken with or without food.
Drug-Herb Interactions
Herbal products containing St. John’s wort (Hypericum perforatum) may induce hepatic enzymes (cytochrome P450) and p-glycoprotein transporter and may reduce the effectiveness of contraceptive steroids. This may also result in breakthrough bleeding.
Drug-Laboratory Test Interactions
Results of laboratory tests should be interpreted with the knowledge that the patient is taking an oral contraceptive. The following laboratory tests are modified:
A. Liver Function Tests
Aspartate serum transaminase (AST) - variously reported elevations
Alkaline phosphatase and gamma glutamine transaminase (GGT) - slightly elevated
B. Coagulation Tests
Minimal elevation of test values reported for such parameters as prothrombin and factors VII, VIII, IX, and X.
C. Thyroid Function Tests
Protein binding of thyroxine is increased as indicated by increased total serum thyroxine concentrations and decreased T3 resin uptake.
D. Lipoproteins
Small changes of unproven clinical significance may occur in lipoprotein cholesterol fractions.
E. Gonadotropins
Luteinizing hormone (LH) and follicle-stimulating hormone (FSH) levels are suppressed by the use of oral contraceptives. Wait 2 weeks after discontinuing the use of oral contraceptives before measurements are made.
F. Glucose Tolerance
Oral glucose tolerance remained unchanged or was slightly decreased.
Tissue Specimens
Pathologists should be advised of oral contraceptive therapy when specimens obtained from surgical procedures and PAP smears are submitted for examination.
Drug-Lifestyle Interactions
No studies on the effects of NATAZIA on the ability to drive or operate machinery have been performed. No effects on the ability to drive or operate machinery have been observed in users of COCs.
Noncontraceptive Benefits of Oral Contraceptives
Several health advantages other than contraception have been reported:
- 1. Combination oral contraceptives reduce the incidence of cancer of the endometrium and ovaries.
- 2. Oral contraceptives reduce the likelihood of developing benign breast disease and, as a result, decrease the incidence of breast biopsies.
- 3. Oral contraceptives reduce the likelihood of development of functional ovarian cysts.
- 4. Pill users have less menstrual blood loss and have more regular cycles, thereby reducing the chance of developing iron-deficiency anemia.
- 5. The use of oral contraceptives may decrease the severity of dysmenorrhea and premenstrual syndrome and may improve acne vulgaris, hirsutism, and other androgen-mediated disorders.
- 6. Oral contraceptives decrease the incidence of acute pelvic inflammatory disease and, thereby, reduce as well the incidence of ectopic pregnancy.
- 7. Oral contraceptives have potential beneficial effects on endometriosis.
DOSAGE AND ADMINISTRATION
NATAZIA (estradiol valerate, and estradiol valerate and dienogest) tablets are available in blister packs. Each blister pack contains 28 film-coated tablets in the following order:
- 2 dark yellow tablets each containing 3 mg estradiol valerate
- 5 medium red tablets each containing 2 mg estradiol valerate and 2 mg dienogest
- 17 light yellow tablets each containing 2 mg estradiol valerate and 3 mg dienogest
- 2 dark red tablets each containing 1 mg estradiol valerate
- 2 white tablets (inert)
To achieve maximum contraceptive effectiveness, NATAZIA must be taken exactly as directed. Take one tablet by mouth the same time every day. Tablets must be taken in the order directed on the blister pack. Tablets should not be skipped or intake delayed by more than 12 hours.
Instruct the patient to begin taking NATAZIA on Day 1 of her menstrual cycle (that is, the first day of her menstrual bleeding). Instruct the patient to use a non-hormonal contraceptive as back-up during the first 9 days.
For postpartum women who do not breastfeed or after a second trimester abortion, NATAZIA may be started no earlier than 4 weeks postpartum. Recommend use of a non-hormonal back-up method for the first 9 days. When combined oral contraceptives (COCs) are used during the postpartum period, the increased risk of thromboembolic disease associated with the postpartum period must be considered. The possibility of ovulation and conception before starting COCs should also be considered.
If the patient is switching from a combination hormonal method such as:
- Another birth control pill
- Vaginal ring
- Patch
- Instruct her to take the first dark yellow tablet on the first day of her withdrawal bleed. She should not continue taking the tablets from her previous birth control pack. If she does not have a withdrawal bleed, rule out pregnancy before starting NATAZIA.
- If she previously used a vaginal ring or transdermal patch, she should start NATAZIA on the day the ring or patch is removed.
- Instruct the patient to use a non-hormonal back-up method such as a condom or spermicide for the first 9 days.
If the patient is switching from a progestin-only method such as a:
- Progestin-only pill
- Implant
- Intrauterine system
- Injection
- Instruct her to take the first dark yellow tablet on the day she would have taken her next progestin-only tablet or on the day of removal of her implant or intrauterine system or on the day when she would have had her next injection.
- Instruct the patient to use a non-hormonal back-up method such as a condom or spermicide for the first 9 days.
Management of Missed Tablets:
If a patient has forgotten to start a new blister pack, she may already be pregnant. Instruct the patient to use back-up contraception (such as condoms and spermicides) anytime she has sex.
- Do not take more than 2 tablets in one day. On the days the patient takes 2 tablets to make up for missed tablets, she may feel a little nauseous.
- If a patient starts vomiting or has diarrhea within 4 hours of taking a tablet, she should be advised to take another tablet of the same color from her extra blister pack.
If the patient is less than 12 hours late taking her tablet she should be advised to
- Take her tablet as soon as she remembers
- Take the next tablet at the usual time
- She does not need to use back-up contraception
If the patient misses ONE TABLET for more than 12 hours she should be advised to
Days 1-17
- Take her missed tablet immediately
- Take her next tablet at the usual time (she may have to take two tablets that day)
- Use back-up contraception for the next 9 days
- Continue taking one tablet each day at the same time for the rest of her cycle
Days 18-24
- Do not take any tablets from her current blister pack and throw the pack away
- Take Day 1 tablet from a new blister pack
- Use back-up contraception for the next 9 days
- Continue taking one tablet from the new blister pack at the same time each day
Days 25-28
- Take her missed tablet immediately
- Take her next tablet at the usual time (she may have to take two tablets that day)
- No back-up contraception is needed
- Continue taking one tablet each day at the same time for the rest of her cycle
If the patient misses TWO TABLETS in a row she should be advised to
Days 1-17 (if she misses the tablets for Days 17 and 18, follow the instructions for Days 17-25 instead)
- Do not take the missed tablets. Instead, take the tablet for the day on which she first noticed she had missed tablets.
- Use back-up contraception for the next 9 days
- Continue taking one tablet each day at the same time for the rest of her cycle
Days 17-25 (if she misses the tablets for Days 25 and 26, follow the instructions for Days 25-28 instead)
- Do not take any tablets from her current blister pack and throw the pack away.
- Take Day 3 tablet from a new blister pack
- Use back-up contraception for the next 9 days
- Continue taking one tablet from the new blister pack at the same time each day
Days 25-28
- Do not take any tablets from her current blister pack and throw the pack away.
- Start a new pack on the same day or start a new pack on the day she usually starts a new pack.
- No back-up contraception is needed
- Continue taking one tablet from the new pack at the same time each day, for the rest of her cycle.
Advice in case of vomiting: In case of severe vomiting or diarrhea, absorption may not be complete and additional contraceptive measures should be taken. If vomiting or diarrhea occurs within 3 to 4 hours after taking a colored tablet, this can be regarded as a missed tablet.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
Serious ill effects have not been reported following accidental ingestion of large doses of NATAZIA. Overdosage may cause nausea and vomiting, and withdrawal bleeding may occur in females. There are no antidotes and further treatment should be symptomatic based on the knowledge of the pharmacological action of the constituents.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
NATAZIA is a multiphasic, sequential, estrogen step-down, progestin step-up, combination oral contraceptive (COC). NATAZIA contains the estrogen, estradiol valerate (EV) alone or in combination with the progestin dienogest (DNG). Estradiol valerate (EV) is a prodrug and is converted in the digestive system to 17β-estradiol which is identical to the estrogen that is naturally produced by the female body. Combination oral contraceptives (COCs) act by suppression of gonadotropins. Although the primary mechanism of action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increases the difficulty of sperm entry into the uterus) and the endometrium (which reduces the likelihood of implantation).
Dienogest (DNG) binds to the progesterone receptor of the human uterus with only 10% of the relative affinity of progesterone. Despite its low affinity for the progesterone receptor, DNG has a strong progestogenic effect in vivo which is thought to be responsible for the efficacy in the treatment of heavy menstrual bleeding.
Pharmacodynamics
The contraceptive effect of COCs is based on the interaction of various factors, the most important of which are the inhibition of ovulation and the changes in the cervical secretion. The estrogen in NATAZIA is estradiol valerate, a synthetic prodrug of 17ß-estradiol. The progestin in NATAZIA is dienogest (DNG). DNG displays properties of 19-nortestosterone derivatives as well as properties associated with progesterone derivatives.
Cardiac Electrophysiology
The effect of NATAZIA on QT prolongation was evaluated in a randomized, double-blind, positive (moxifloxacin 400 mg) and negative (placebo) controlled crossover study in healthy subjects. A total of 53 subjects were administered NATAZIA (containing 3 mg dienogest and 2 mg estradiol valerate), dienogest 10 mg, and placebo as once daily doses for 4 days, and moxifloxacin 400 mg as a single oral dose. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc based on Fridericia’s correction method (QTcF) was below 10 msec (milliseconds), the threshold for regulatory concern.
Pharmacokinetics
Absorption
After oral administration of estradiol valerate, cleavage to 17β-estradiol and valeric acid takes place during absorption by the intestinal mucosa or in the course of the first liver passage. This gives rise to estradiol and its metabolites, estrone and other metabolites. Maximum serum estradiol concentrations of 73.3 pg/mL are reached at a median of approximately 6 hours (range: 1.5-12 hours) and the area under the estradiol concentration curve [AUC(0–24hr)] was 1301 pg·h/mL after single ingestion of a tablet containing 3 mg estradiol valerate under fasted condition on Day 1 of the 28-day sequential regimen.
Bioavailability of dienogest is about 91%. Maximum serum dienogest concentrations of 91.7 ng/mL are reached at a median of approximately 1 hour (range: 0.5–1.5 hour) and the area under the dienogest concentration curve [AUC(0–24h)] was 964 ng/mL after single oral administration of a tablet containing 2 mg estradiol valerate/3 mg dienogest under fasted conditions. The pharmacokinetics of dienogest are dose-proportional within the dose range of 1-8 mg. Steady state is reached after 4 days of the same dosage of 2 mg dienogest. The mean accumulation ratio for AUC (0–24h) is approximately 1.24.
The mean plasma pharmacokinetic parameters at steady state following repeated oral doses of a 2 mg estradiol valerate/3 mg dienogest combination tablet in fertile women under fasted condition are reported in Table 4.
| Table 4: Arithmetic Mean (SD) Serum Pharmacokinetic Parameters at Steady-state (on Day 24) following Repeated Oral Doses of 2 mg EV/3 mg DNG on Days 8–24 of the 28 day Regimen in Fertile Women under Fasted Condition (N=15) | |||||||
| Parameter | Dienogest | Estradiol | Estrone | ||||
| Cmax | 85.2 (19.7) ng/mL | 70.5 (25.9) pg/mL | 483 (198) pg/mL | ||||
| Tmax (h)a | 1.5 (1–2) | 3 (1.5–12) | 4 (3–12) | ||||
| AUC(0–24h) | 828 (187) ng·h/mL | 1323 (480) pg·h/mL | 7562 (3403) pg·h/mL | ||||
| t½ (h) | 12.3 (1.4) | NA | NA | ||||
a Median (range) for Tmax Cmax = Maximum serum concentration Tmax = Time to reach maximum concentration AUC(0–24h) = Area under the concentration-time curve from 0 h data point up to 48 h post-administration NA: Data not available | |||||||
Food Effect
Concomitant food intake in women resulted in a 28% decrease for dienogest Cmax and 23% increase of estradiol Cmax while the exposure (AUC) of both dienogest and estradiol did not change.
Distribution
In serum, 38% of estradiol is bound to sex hormone-binding globulin (SHBG), 60% to albumin and 2–3% circulates in free form. An apparent volume of distribution of approximately 1.2 L/kg was determined after intravenous (IV) administration.
A relatively high fraction (10%) of circulating dienogest is present in the free form, with approximately 90% being bound non-specifically to albumin. Dienogest does not bind to SHBG and corticosteroid-binding globulin (CBG). The volume of distribution at steady state (Vd,ss) of dienogest is 46 L after the IV administration of 85 µg 3H-dienogest.
Metabolism
After oral administration of estradiol valerate, approximately 3% of the dose is directly bioavailable as estradiol. Estradiol undergoes an extensive first-pass effect and a considerable part of the dose administered is already metabolized in the gastrointestinal mucosa. The CYP 3A family is known to play the most important role in human estradiol metabolism. Together with the pre-systemic metabolism in the liver, about 95% of the orally administered dose becomes metabolized before entering the systemic circulation. The main metabolites are estrone and its sulfate or glucuronide conjugates.
Dienogest is extensively metabolized by the known pathways of steroid metabolism (hydroxylation, conjugation), with the formation of metabolites that are mostly inactive endocrinologically. CYP3A4 was identified as a predominant enzyme catalyzing the metabolism of dienogest.
Excretion
Estradiol and its metabolites are mainly excreted in urine, with about 10% being excreted in the feces. The terminal half-life of estradiol is approximately 14 hours.
Dienogest is mainly excreted renally in the form of metabolites and unchanged dienogest is the dominating fraction in plasma. The terminal half-life of dienogest is approximately 11 hours.
Steady-State Conditions
In young women, the measured estradiol plasma levels are a composite of the endogenous estradiol and the estradiol generated from NATAZIA. During the treatment phase of 2 mg EV and 3 mg DNG, maximum and average serum estradiol concentrations at steady state are 66.0 pg/mL, and 51.6 pg/mL, respectively. Throughout the 28-day cycle, stable minimum estradiol concentrations were maintained and ranged from 28.7 pg/mL to 64.7 pg/mL.
For DNG, steady state is reached after 3 days of the same dosage of 3 mg dienogest in combination with 2 mg estradiol valerate. Trough, maximum and average dienogest serum concentrations at steady state are 11.8 ng/mL, 82.9 ng/mL and 33.7 ng/mL, respectively. The mean accumulation ratio for AUC(0-24h) was determined to be 1.24.
Special Populations and Conditions
Body Mass Index
The safety and efficacy of NATAZIA in women with a BMI of >30 kg/m2 has not been evaluated.
Pediatrics
The safety and efficacy of NATAZIA has not been established in women under the age of 18 years. Use of this product before menarche is not indicated.
Geriatrics
NATAZIA is not indicated for use in postmenopausal women.
Race
No clinically relevant interethnic differences among Caucasian and Japanese patients were observed with respect to the pharmacokinetics and pharmacodynamics of DNG or EV.
Hepatic Insufficiency
NATAZIA is contraindicated in patients with active hepatic disease (see also CONTRAINDICATIONS).
The pharmacokinetics of NATAZIA has not been studied in subjects with hepatic impairment. Steroid hormones may be poorly metabolized in patients with impaired liver function. Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal (see also CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Renal Insufficiency
NATAZIA has not been studied in renally impaired patients. Available data do not suggest a change in treatment in this patient population.
STORAGE AND STABILITY
Store in original packaging between 15°C and 30°C.
Medicines should not be disposed of via wastewater or household waste. Ask your pharmacist how to dispose of medicines no longer required. These measures will help to protect the environment.
SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
DOSAGE FORMS, COMPOSITION AND PACKAGING
NATAZIA (estradiol valerate, and estradiol valerate and dienogest) tablets are available in a 28-day regimen.
Each blister pack contains the following film-coated, round tablets (in the following order):
- 2 hormone-containing dark yellow tablets, one side embossed with the letters “DD” in a regular hexagon, each containing 3 mg estradiol valerate
- 5 hormone-containing medium red tablets, one side embossed with the letters “DJ” in a regular hexagon, each containing 2 mg estradiol valerate and 2 mg dienogest
- 17 hormone-containing light yellow tablets, one side embossed with the letters “DH” in a regular hexagon, each containing 2 mg estradiol valerate and 3 mg dienogest
- 2 hormone-containing dark red tablets, one side embossed with the letters “DN” in a regular hexagon, each containing 1 mg estradiol valerate
- 2 hormone-free white tablets, one side embossed with the letters “DT” in a regular hexagon,
Nonmedicinal ingredients for hormone-containing tablets: hydroxypropyl methylcellulose, lactose monohydrate, macrogol 6000, magnesium stearate, maize starch, maize starch pregelatinized, povidone 25, red ferric oxide, talc, titanium dioxide, yellow ferric oxide.
Nonmedicinal ingredients for hormone-free tablets: hydroxypropyl methylcellulose, lactose monohydrate, magnesium stearate, maize starch, povidone 25, talc, titanium dioxide.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Estradiol Valerate
| Proper name: | estradiol valerate |
| Chemical name: | Estra–1,3,5(10)–triene–3,17β–diol–17–valerate (WHO) |
| Estradiol 17–valerate | |
| Estradiol 17β–valerate | |
| Estra–1,3,5(10)–triene–3,17–diol (17β), 17–pentanoate | |
| 1,3,5(10)–Estratriene–3,17β–diol–17–valerate | |
| Molecular formula: | C23H32O3 |
| Molecular weight: | 356.50 |
| Structural formula: | O CH3 OH H H H O |
| Physicochemical properties: | White to almost-white crystalline powder or colorless crystals. Freely soluble in acetone and dichloromethane, soluble in ethanol, methanol, dioxane, and dimethylether, slightly soluble in n-hexane and practically insoluble in petroleum ether and water at 25°C. Melting range is 143°C to 150°C. |
Dienogest
| Common name: | dienogest |
| Chemical name: | 17-hydroxy-3-oxo-19-nor-17α-pregna-4,9-diene-21-nitrile (IUPAC) 19-norpregna-4,9-diene-21-nitrile, 17-hydroxy-3-oxo-17α-cyanomethyl-17β-hydroxy-estra-4,9-dien-3-one (CAS Index Name) |
| Molecular formula: | C20H25NO2 |
| Molecular weight: | 311.43 |
| Structural formula: | 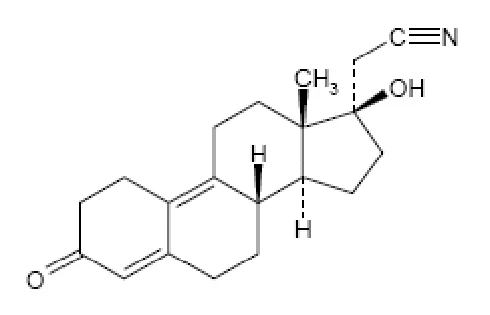 |
| Physicochemical properties: | White to off-white crystalline powder. Practically insoluble in water and neutral within the physiologically relevant pH range. Melting range is 210°C to 218°C. Dienogest is a neutral molecule within pH 2-12. |
CLINICAL TRIALS
General Information
The following table gives reported pregnancy rates for various forms of birth control, including no birth control. The reported rates represent the number of women out of 100 who would become pregnant in 1 year.
| Table 5: Reported Pregnancies per 100 Women per Year | |
|---|---|
| Combination pill | less than 1 to 2 |
| Intrauterine device (IUD) | less than 1 to 6 |
| Condom with spermicidal foam or gel | 1 to 6 |
| Mini-pill | 3 to 6 |
| Condom | 2 to 12 |
| Diaphragm with spermicidal foam or gel | 3 to 18 |
| Spermicide | 3 to 21 |
| Sponge with spermicide | 3 to 28 |
| Cervical cap with spermicide | 5 to 18 |
| Periodic abstinence (rhythm), all types | 2 to 20 |
| No birth control | 60 to 85 |
Contraception
Study Demographics and Trial Design
The study conducted in North America (U.S. and Canada) was a multicenter, open-label, single-arm, unintended pregnancy study. There were 490 healthy subjects between 18 and 35 years of age (mean age: 25.1 years) who were treated for up to 28 cycles of 28 days each. The racial demographic of enrolled women was: Caucasian (76%), Hispanic (13%), African-American (7%), Asian (3%), and Other (1%). The weight range for treated women was 40 to 100 kg (mean weight: 62.5 kg) and the BMI range was 14 to 30 kg/m2 (mean BMI: 23.3 kg/m2). Of treated women, 15% discontinued the study treatment due to an adverse event, 13% were lost to follow up, 10% withdrew their consent, 8% discontinued due to other reason, 1% discontinued due to protocol deviation, and 1% discontinued due to pregnancy.
The study conducted in Europe (Germany, Austria and Spain) was a multicenter, open-label, single-arm contraceptive reliability study. There were 1377 healthy subjects between 18 and 50 years of age (mean age: 30.3 years) who were treated for 20 cycles of 28 days each. The racial demographic of enrolled women was predominantly Caucasian (99.2%). The weight range for treated women was 38 to 98 kg (mean weight: 63.8 kg) and the BMI range was 15 to 31.8 kg/m2 (mean BMI: 22.8 kg/m2). Of treated women, 10% discontinued the study treatment due to an adverse event, 5% discontinued due to other reason, 2% were lost to follow up, 2% discontinued due to protocol deviation, 2% withdrew their consent, and 1% discontinued due to pregnancy.
Study Results
The Pearl Index (PI) was the primary efficacy endpoint used to assess contraceptive reliability and was assessed in each of the two studies, assuming all subjects were at risk of pregnancy in all medication cycles unless back-up contraception was documented. The PI is based on pregnancies that occurred after the onset of treatment and within 7 days after the last pill intake. Cycles in which conception did not occur, but which included the use of back-up contraception, were not included in the calculation of the PI. The PI also includes patients who did not take the drug correctly. The estimated PI for the North American study is 1.64 and the estimated PI for the European study is 1.04. The Kaplan-Meier method was also used to calculate the contraceptive failure rate.
The summary of the Pearl Indexes and cumulative contraceptive failure rates are provided in Table 6:
| Table 6: Summary of the Pearl Indexes and the Cumulative Contraceptive Failure Rates | |||||||||||
| Study | Age Group | Relative Treatment Exposure Cyclesa | Number of Pregnancies within 13 Cycles and 7 Days after Last Treatment | Pearl Index | Upper Limit of 95% CI | Contraceptive Failure Rate at the End of First Year | |||||
| North America | 18–35 | 3969 | 5 | 1.64 | 3.82 | 0.016 | |||||
| Europe (38) | 18–35 | 11 275 | 9 | 1.04 | 1.97 | 0.010 | |||||
| a Total treatment exposure time without back-up contraception | |||||||||||
Heavy Menstrual Bleeding
Study Demographics and Trial Design
The efficacy and safety of NATAZIA for the treatment of heavy menstrual bleeding in women without organic pathology who desire oral contraception was evaluated in two multi-regional, multicenter, double-blind, randomized, placebo-controlled, pivotal phase III studies.
Study 308960 was performed in the United States and Canada (39) and study 308961 was performed in Australia and 9 European countries. (40) Both studies were identical in design. Women 18 to 54 years of age, with a diagnosis of dysfunctional uterine bleeding (DUB) characterized as heavy, prolonged, and/or frequent bleeding without organic pathology, who desire oral contraception were included. The documentation of HMB was done through the collection of used sanitary protection items (pads and tampons) to objectively quantify blood loss according to the alkaline hematin method. HMB was defined as menstrual blood loss of 80 mL or more in at least 2 bleeding episodes. Overall, a total of 421 women with a mean age of 38.2 and a mean BMI of 25.5 were randomized to the two clinical studies, that is, 269 women in the NATAZIA group and 152 women in the placebo group, and treated for 7 consecutive treatment cycles of 28 days each. Approximately 85% of the subjects qualified for the study because they had symptoms of HMB. Approximately 81% were Caucasian, 13% were Black, and 6% were Hispanic or Asian or Other.
The primary efficacy variable was the proportion of subjects who were completely relieved of symptoms defined by the number of subjects with the absence of any DUB symptom and who met all of the 8 strictly defined criteriaa for success during the 90-day efficacy assessment phase. In Study 308960, the proportion of the intent-to-treat subjects with complete symptom relief was 29.2% in the NATAZIA group compared to 2.9% in the placebo group. In Study 308961, the proportion of the intent-to-treat subjects with complete symptom relief was 29.5% in the NATAZIA group compared to 1.2% in the placebo group. In both studies, NATAZIA was effective in treating the symptoms of HMB in women who entered the study with symptoms specific to HMB. Among patients with HMB, menstrual blood loss (MBL) was statistically significantly reduced in the group treated with NATAZIA compared with placebo (p<0.0001 for both studies). Figure 1 and Figure 2 display the MBL volume by cycle and by study. The decrease in MBL in the NATAZIA group was accompanied by a statistically significant improvement in iron metabolism parameters (hemoglobin, hematocrit and ferritin) and a decrease in use of sanitary protection items.
a No bleeding episodes lasting >7 days; No more than 4 bleeding episodes per 90-day efficacy period; No bleeding episodes with a blood loss volume of ≥80 mL; No more than 1 bleeding episode increase from baseline; Total number of bleeding days ≤24 per 90-day efficacy period; No increase from baseline in total number of bleeding days; Decrease of ≥2 days between maximum duration during run-in phase and efficacy phase (if enrolled with prolonged bleeding); Blood loss volume associated with each episode <80 mL and decreased by 50% or more from the average of the qualifying bleeding episodes (where the qualifying bleeding episodes are those with a blood loss volume ≥80 mL per episode) that occurred during the run-in phase (if enrolled with heavy bleeding)
| Figure 1: Study 308960 – Median Menstrual Blood Loss Volume by Cycle |
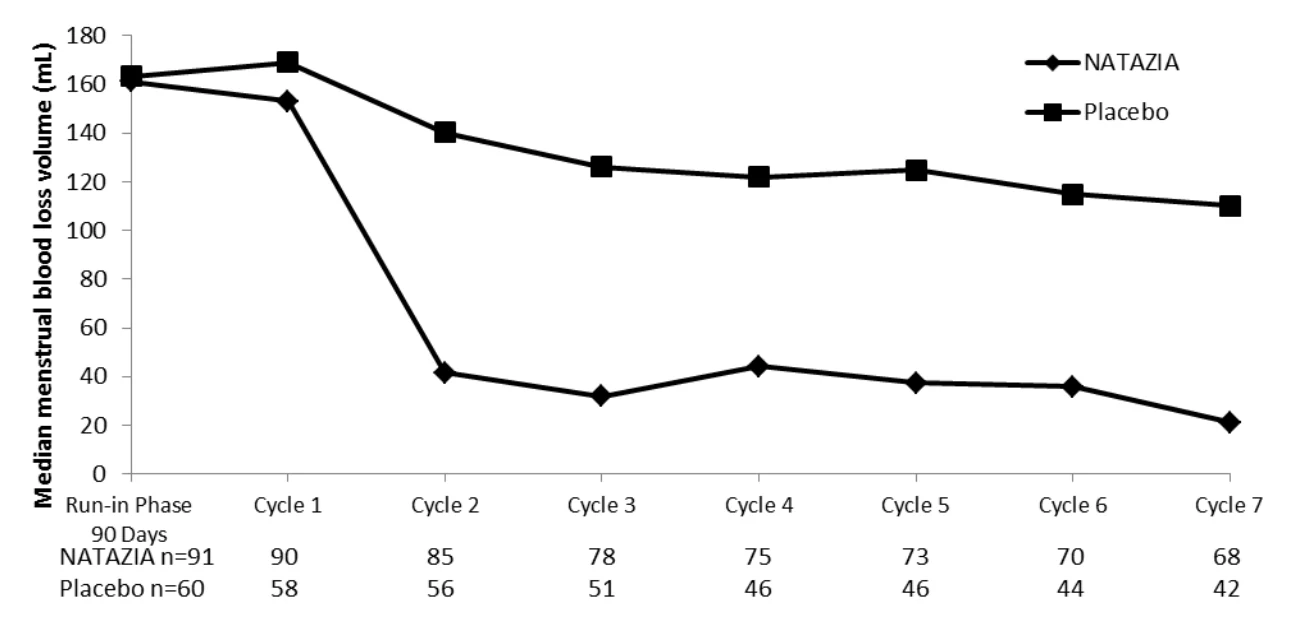 |
| Note: Run-in phase 90 days is normalized to 28 days: menstrual blood loss volume value is multiplied by 28 days and divided by 90 days |
| Figure 2: Study 309861 – Median Menstrual Blood Loss Volume by Cycle |
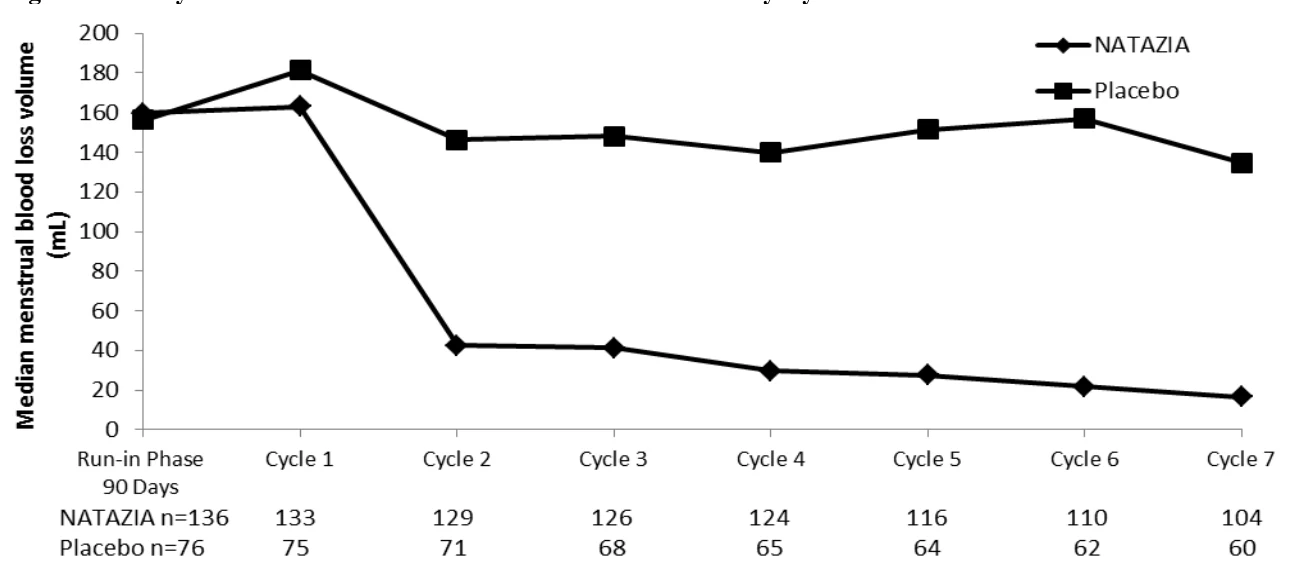 |
| Note: Run-in phase 90 days is normalized to 28 days: menstrual blood loss volume value is multiplied by 28 days and divided by 90 days |
DETAILED PHARMACOLOGY
Animal Pharmacology
Estradiol Valerate
Soon after oral or parenteral administration, EV is completely converted into the natural hormone E2 (estradiol) and valeric acid. The E2 produced by ester cleavage is the pharmacologically active compound. (41, 42) The hormone diffuses passively through cell membranes, distributes itself throughout the cell, and ultimately binds to the nuclear estrogen receptors. Nuclear estrogen receptors are key elements in the mechanism of action of estrogenic hormones. (43)
The estrogenic effects observed in various animal studies are almost identical qualitatively and quantitatively after administration of E2 and EV. (41)
In the Allen-Doisy vaginal smear test in the castrated rat, changes in the vaginal epithelium which typify estrogenic effects (proliferation and cornification) are observed after both subcutaneous (sc) and oral (po) administration of EV. (41)
Estradiol (E2) gives rise to a significant dose-dependent increase in the weights of the vagina and uterus in ovariectomized rodents. This is considered a specific estrogenic effect. (44) Premature vaginal opening can be provoked within 5 days in infantile rats with E2 and with EV. (41)
Estrogens play an important role in maintaining bone mass by suppressing bone remodeling and maintaining a balance between osteoblastic and osteoclastic activities. When estrogen levels are deficient, there is an increase in the frequency of new bone remodeling units and an increase in remodeling imbalance.
Dienogest
Primary Pharmacodynamics
In vivo studies with DNG revealed strong progestogenic activity in the endometrial transformation assay in rabbits after oral and subcutaneous administration of doses ≥0.01 mg/kg. Dienogest (DNG) was 10 times more active than progesterone and 2-10 times more active than levonorgestrel in this test.
In bonnet monkeys, dienogest effectively blocked ovulation starting from the lowest tested dose of 0.3 mg/kg/day when given subcutaneously. Equally strong effects on menstrual cycling and/or inhibition of ovulation were observed in the repeated-dose toxicity studies in other monkey species after oral dosing.
In vitro studies revealed a low relative binding affinity of dienogest to the uterine progesterone receptor in rats. Compared to progesterone, the relative binding affinity of dienogest was less than 20%. In human uterine cytosol, the relative binding affinity of dienogest to the progesterone receptor was about one order of magnitude less than that of progesterone.
The progesterone receptor-mediated activity (alkaline phosphatase induction) of dienogest was tested in human breast carcinoma T47D cells and revealed a 2-fold weaker progestogenic activity than progesterone.
Secondary Pharmacodynamics
In vitro studies showed that DNG had only a weak binding affinity to the androgen receptor of rat prostate (relative binding affinity: 2.6% to 6.6% of testosterone) and to the glucocorticoid receptor of rat liver (relative binding affinity: 0.96% of dexamethasone). Dienogest (DNG) did not bind to any appreciable extent to the estrogen receptor of the rabbit uterus or to the mineralocorticoid receptor of the rat kidney.
In vivo studies with orally administered DNG showed only marginal androgenic activity and no anabolic, glucocorticoid, or mineralocorticoid activity in rats at doses up to 100 mg/kg.
Dienogest possesses antiandrogenic activities. In the Hershberger assay in rats, dienogest showed clear antiandrogenic properties. (45) The antiandrogenic potency of dienogest was 40% that of cyproterone acetate. (46) Unlike other 19-nortestosterone derivatives, dienogest has no androgenic activity.
Dienogest does not bind to the estrogen receptor. In a transactivation assay in the human breast cancer cell line MCF-7/2A, dienogest did not induce estrogen receptor-dependent transactivation.
Dienogest itself has no estrogenic activity, but the major rodent plasma metabolite, aromatic dienogest, has estrogenic activity. Therefore, in rodents, dienogest acts as an estrogen when given orally or subcutaneously. This finding of estrogenicity has no relevance for primates, as this aromatic metabolite does not occur in relevant amounts in monkey or human plasma.
There was only low binding to the glucocorticoid receptor in rat liver and rat thymus and to the mineralocorticoid receptor in rat kidney. (46) Dienogest did not affect hepatic glycogen content in adrenalectomized rats. Dienogest-medicated rats failed to exhibit any changes in either urine volume or the urinary Na/K ratio, even when the dose was as high as 100 mg/kg orally. This indicates no glucocorticoid or mineralocorticoid activity. (45)
The conclusion drawn from the detailed endocrinological characterization of dienogest is that this drug substance has a potent progestational activity on the endometrium and a medium antigonadotrophic activity. A moderate antiandrogenic activity was observed in rats and mice. The estrogenic activity of dienogest observed in rats and mice was considered to represent a species-specific response related to the presence of an aromatic dienogest metabolite that occurs only in these species.
Safety Pharmacology
In rats, dienogest did not influence general symptoms and behavior at doses up to 30 mg/kg. Effects on the central nervous system in mice, rats, and rabbits revealed effective doses after oral or parenteral administration as high as 100 mg/kg dienogest, with the exception of a slight decrease in body temperature in mice which was observed after intraperitoneal administration of 10 mg/kg dienogest.
Some temporary effects of dienogest on body temperature or kidney function in rats were noted at lower doses (≥ 10 mg/kg), which are at least 2 orders of magnitude above the intended therapeutic dose in humans.
Cardiovascular effects of dienogest were studied in vitro on the isolated heart atrium of rats and guinea pigs and revealed changes of spontaneous contraction parameters only at high concentrations of about 3 x 10⁻⁴ mol/L. In vivo studies in rabbits did not reveal effects on blood pressure, heart rate, blood flow, arterial oxygen partial pressure, arterial carbon dioxide pressure, and ECG after intraduodenally administered dienogest at a dose of 30 mg/kg. In addition, studies to investigate particular cardiovascular effects on the duration of the action potential in isolated papillary muscles of guinea pigs did not show effects on action potential parameters up to a dienogest concentration of 10-5 mol/L. The effect of dienogest on the human hERG potassium channel was also investigated. Dienogest was tested at concentrations of 10-6 mol/L, 10-5 mol/L and 10-4 mol/L. The outward current amplitudes of the hERG-mediated potassium current were not significantly reduced during application of 10-6 mol/L and 10-5 mol/L. At a concentration of 10-4 mol/L, dienogest showed a significant but reversible current reduction.
In vivo, in conscious monkeys, ECG parameters (PR interval, QRS widths, or QT interval) were not affected by oral administration of dienogest up to a dose of 30 mg/kg. The measurement of blood pressure and heart rate did not reveal any effects.
Effects on the autonomic and somatic nervous system were studied in vitro and revealed changes related to dienogest treatment only at high concentrations in the 10-4 mol/L range.
Safety pharmacology studies with dienogest concluded that compound-related changes were observed for the majority of investigated parameters only at very high doses (≥ 30 mg/kg) or at dienogest in vitro concentrations in the 10-4 mol/L range. In humans, a maximum concentration of about 80 ng/mL of dienogest in blood plasma (ca 2 x 10⁻⁷ mol/L) was determined during clinical studies. Therefore, no impact of dienogest on cardiovascular or ECG parameters in humans is expected in the therapeutic range.
Special Populations
Pediatrics
The safety and efficacy of NATAZIA has not been established in women under the age of 18 years. Use of this product before menarche is not indicated.
Geriatrics
NATAZIA is not indicated for use in postmenopausal women.
Race
No clinically relevant interethnic differences among Caucasian and Japanese patients were observed with respect to the pharmacokinetics and pharmacodynamics of DNG or EV.
TOXICOLOGY
Acute Toxicity
Estradiol Valerate
High, oral doses of estradiol valerate were well tolerated at maximum dose levels in rats and mice (4000 mg/kg) and dogs (1000 mg/kg).
Dienogest
Single-dose toxicity studies were conducted in several species including mice, rabbits, rats, and dogs. All of the studies revealed a very low toxicity of dienogest after single oral or parenteral administration. Nonlethal doses were between 1000 and 4000 mg/kg with the exception of male rabbits where it was below, but close to, 1000 mg/kg. Toxic signs observed at high doses were central depression in mice, none in rats, anorexia, weight loss, convulsions in rabbits, and a transient increase in GPT in dogs without histopathological findings.
Repeated-Dose Toxicity
Estradiol Valerate
The repeated-dose toxicity after oral administration was studied in rats and dogs after treatment for up to 90 weeks (rats) or 53 weeks (dogs). Only findings characteristic of the exaggerated pharmacological effects of estrogens were observed in these studies.
The repeated dose toxicity of EV has also been investigated in 3-month oral studies in mice and rats which were primarily performed to assess the combination toxicity of both EV and DNG. No unexpected signs of toxicity were observed in these studies.
Dienogest
Repeated-dose systemic toxicology studies of dienogest were conducted for various durations, up to 13 weeks in mice, 12 months in rats, 6 months in dogs, and up to 12 months in monkeys.
In general, the principle findings observed in all studies were pharmacological or exaggerated pharmacological effects associated with the repeated administration of high dose levels of a progestogenic compound to laboratory animals.
In mice, dienogest was well tolerated when given orally at dose levels up to 125 mg/kg/day for 13 weeks. Principle changes were pharmacological in nature (lower uterus and cervix weights at dose levels of 25 mg/kg/day and higher ovary and lower seminal vesicle weights at dose levels of 125 mg/kg/day). At the high-dose level (125 mg/kg/day), increased absolute and relative liver weights were observed in male and female mice and were accompanied by periacinar hepatocyte hypertrophy in males.
Repeated-dose systemic toxicity studies were conducted in female rats for 3, 6, and 12 months. In these studies, dienogest was well tolerated and not lethal when orally administered daily for
3 months at dose levels up to 30 mg/kg or for 6 and 12 months at doses up to 10 mg/kg/day. In the 3-month study, 3.0 mg/kg/day was identified as the NOAEL. In the 12-month study, 1.0 mg/kg/day was identified as the NOAEL. Body weights were unaffected in the 3-month study in animals given doses as high as 30 mg/kg/day, but were 9% and 12% higher than controls after daily oral administration of 0.1 and 1.0 mg/kg/day, respectively, for 12 months. Compared with controls, changes observed across the rat studies were predominantly pharmacological in nature and included persistent diestrus (30 mg/kg/day), lower average serum total cholesterol (≥3 mg/kg) and alanine and/or aspartate aminotransferase values (≥10 mg/kg/day), slightly higher serum triglyceride and nonesterified fatty acid values (≥0.1 mg/kg/day), alterations in coagulation parameters (higher platelet counts, fibrinogen values or longer prothrombin times after administration of doses ≥10 mg/kg), higher absolute and relative liver weights (≥1.0 mg/kg/day), and microscopic changes in target organs (ovaries, uterus, and vagina) at most dose levels ≥1.0 mg/kg/day. Slightly lower erythrocytic parameters (typically erythrocyte counts, hemoglobin, and hematocrit), compared with controls were also observed in some of the studies. Microscopic liver changes including basophilic foci of cellular alteration, periportal fat deposition, and vacuolated hepatocytes were observed after oral administration of 10 mg/kg/day for 12 months. The liver changes seen only in this chronic study most likely reflect earlier onset of age-related changes in female rats, and similar findings have been described after high dose levels of progestins were administered in chronic toxicity studies in rodents.
In another, supportive study, dienogest or levonorgestrel was administered to rabbits in their daily diet for 19 to 20 months at concentrations intended to deliver 0.14 or 0.70 mg/day. No intrinsic organ toxicity was observed following dietary administration of dienogest or levonorgestrel. In general, changes observed were limited to pharmacologic or exaggerated pharmacologic effects of progestins.
Dienogest was orally administered to female Beagle dogs in 3 studies. In the first supportive study, dienogest was administered as powder in gelatin capsules once daily for 1 month at doses of 0.1 to 10 mg/kg/day. In the second study, dienogest, as a liquid suspension in gelatin capsules, was administered once daily for 3 months at doses of 0.3 to 3.0 mg/kg/day. In a second supportive study, dienogest was administered as coated tablets once daily for 6 months at doses of 0.01 to 1 mg/kg/day. In general, dienogest was well tolerated and non-lethal. Pharmacological changes observed in the female dogs included slight increases in body weight, enlargement of the mammary gland accompanied microscopically by lobular hyperplasia, and histopathological changes in the ovaries, vagina, pituitary, and uterus. Clinical pathology changes included lower-than-control erythrocytic parameters (erythrocyte counts, hemoglobin, hematocrit) which were sometimes accompanied by alterations in lipid parameters and/or alterations in coagulation parameters. Sulfobromophthalein (BSP)-retention showed a slight, dose-dependent increase under dienogest in female animals at the mid- and high-dose level, which was prominent in one animal in the second BSP test performed during the study. However, there was no morphological correlate in the liver of this dog.
Dienogest was orally administered to female Cynomolgus monkeys, once daily for 13 weeks at dose levels of 0.4, 2.0, and 10.0 mg/kg. Drug-induced cessation of menses occurred at all dose levels. No signs of intolerance or organ toxicity were observed at any dose level tested. AUC(0-24h) values for the highest dose (10 mg/kg) in this GLP compliant study were 78 times higher than systemic exposure in women administered 2 mg EV plus 3 mg DNG (on cycle day 24).
In repeated-dose studies in female Rhesus monkeys, dienogest was orally (intragastrically) administered at dose levels of 0.1, 1, and 10 mg/kg/day for 3 or 12 months. An additional dose level of 0.3 mg/kg/day was also evaluated in the 12-month study. No compound-related mortality, effects on body weight, food consumption, ECG, ophthalmology, or urinalysis parameters were observed in either study. The NOAEL was identified as 1 mg/kg/day. Pharmacological effects, such as cessation of menstruation (all dose levels, and shown to be reversible in the 3-month study), serum biochemistry changes (lower than control alkaline phosphatase values after administration of 10 mg/kg/day), alterations in coagulation parameters (such as increases in fibrinogen and plasminogen activity but without effect on coagulation times or thromboelastograms), and intimal thickening and hypertrophy of the uterus were observed in each study. Furthermore, apart from a two-fold increase in GPT in a single high-dose monkey and only in week 4 (as compared to the mean in controls) of the 3-month study, there was no indication of liver toxicity in any of the three monkey studies. The highest dose of 10 mg/kg in the pivotal 1-year monkey study resulted in 50 times the human dienogest exposure (on cycle day 24). The maximum serum concentration in Rhesus monkeys after a dose of 10 mg/kg (day 361) resulted in 53 times the maximum serum concentration in humans on cycle day 24.
Carcinogenicity
Estradiol Valerate
Tumor formation in experimental animal species treated with steroidal estrogens in general has been demonstrated in hormone responsive tissues such as the vagina, cervix, uterus, mammary gland, testis, lymphatic tissue, and osseous tissue in mice; for the mammary gland and pituitary gland in rats; and for the kidney in hamsters. (47)
Dienogest
Slightly increased incidences of malignant lymphomas and pituitary adenomas were seen in male mice during a 2-year carcinogenicity study. Female mice showed an increased incidence of uterine stromal polyps at the highest tested dose level. These findings are considered to be related to the weak estrogenic partial activity of dienogest in rodents. In one of the two rat carcinogenicity studies, there was an increased incidence of pituitary adenomas and fibroepithelial tumors of the mammary gland in male animals. There was no change in tumor incidence in female rats in both studies. These observations do not suggest particular human risks apart from those which are generally assumed for the use of progestogenic compounds.
Reproductive Toxicity
Estradiol Valerate
Embryolethality is the most prominent finding after treatment of rodents and rabbits with estrogens during pregnancy. (48) Clinical studies in pregnant women have shown that very high doses of the potent estrogen EE were unable to induce abortions during early pregnancy after nidation of the ovum had occurred. (49) Therefore, the embryolethality observed in preclinical studies after treatment with estrogens is not considered predictive for the human situation.
Dienogest
Reproductive toxicity studies with dienogest gave no indication of a teratogenic potential up to embryolethal doses. The inhibition of implantation in rats might be due to an estrogenic effect and the impairment of tubal transport of ova and the postimplantational losses further indicate a disturbance of the endocrine milieu. The fertility of female offspring was impaired after high doses of dienogest given during late pregnancy and lactation. Taken together, the results of reproductive toxicity testing with dienogest do not differentiate this drug from other progestins. (50)
Mutagenesis
Estradiol Valerate
Estradiol valerate (EV) was not mutagenic in a battery of mutagenicity studies in vitro and in vivo. Therefore, no relevant mutagenic risk for humans of EV or its metabolite estradiol has to be assumed.
Dienogest
Two reverse mutation tests in bacteria (Ames test) were conducted. In both tests, dienogest was negative up to a dose of 5 mg per plate. Furthermore, dienogest in concentrations up to a cytotoxic dose of 500 μg/mL (with and without metabolic activation) did not induce mutations in the TK locus in L5178Y mouse lymphoma cells.
Dienogest also did not induce chromosomal aberrations in Chinese hamster lung cells in culture up to a cytotoxic dose of 110 μg/mL (without metabolic activation) and 220 μg/mL (with metabolic activation). In a chromosomal aberration test in human lymphocytes, dienogest was negative.
Oral doses up to 2 g/kg did not induce micronuclei of polychromatic erythrocytes in the bone marrow of female mice above the control level in two studies.
In a rat liver initiation-promotion model in vivo, dienogest did not induce preneoplastic enzyme-altered foci up to a dose of 140 mg/kg for 5 consecutive days followed by treatment with clophen A50 over 11 weeks. In the same test, diethylnitrosamine was clearly positive.
Dienogest did not induce chromosomal aberrations in the bone marrow cells of pregnant baboons or in the lymphocytes of their newborns up to a dose of 1.6 mg dienogest. (51, 52)
A dose of 100 mg/kg dienogest injected intraperitoneally to mice slightly suppressed the incorporation of radioactively labeled thymidine into DNA of the kidney and somewhat more of the liver. However, the difference was not significant at the specified significance limit of 1%.
Other negative tests briefly reported by Schöneich et al (53) included the rec-type repair test with Proteus mirabilis, another Ames test, a host-mediated assay with Salmonella typhimurium in the rat, the cytogenetic assays with ascites tumor or bone-marrow cells in mice, and a dominant lethal test with male and female mice. In all tests performed (which exceeded the extent requested by international guidelines), dienogest showed no mutagenic potential.
Additionally, a UDS (unscheduled DNA synthesis) test was conducted in primary hepatocytes of female rats in vitro. Two independent experiments were performed in which freshly isolated hepatocytes were exposed to dienogest for 18 hours in the presence of methyl-3H-thymidine. The uptake of radioactivity was determined by autoradiography. In the first series of experiments, a significant increase in net grains was found with 2 AAF and 10 or 15 μg/mL CMA, but also with the dienogest concentrations evaluated between 1.72 and 220 μg/mL. In the second experiment, 2 AAF was positive, but to a much lesser degree, and dienogest was only positive at the highest concentration of 220 μg/mL, which was slightly cytotoxic. Dienogest showed a weak genotoxic potential only in this UDS test of the female rat. In a second UDS test in male rat hepatocytes, dienogest did not induce UDS at concentrations up to a cytotoxic dose of 250 μg/mL in either of two independent experiments.
To support the evaluation of the above-mentioned UDS results in female rat hepatocytes, an in vivo/in vitro UDS assay in female rats was performed. Dienogest was given orally at extremely high dosages of 2000 mg/kg and 200 mg/kg. The animals were anesthetized and sacrificed by enzymatic liver perfusion 2 and 16 hours after dosing. Primary hepatocyte cultures were established and exposed for 4 hours to methyl-3H-thymidine. The maximal dose of 2000 mg/kg bw corresponds to 60,000-fold of the daily human dienogest dose. Dienogest was considered noneffective in inducing DNA damage, leading to increased repair synthesis in this in vivo/in vitro UDS assay.
Dienogest was tested for its potential to generate DNA adducts in human liver slices after in vitro incubation over 6 hours. After incubation with dienogest or spironolactone, DNA-adduct levels were below or at the level of quantification. No DNA-adducts were observed in any female livers after incubation with dienogest up to concentrations of 5000 ng/mL. In 2 of 3 male livers no adducts were found and in only one liver a very low DNA adduct level (3.94/109 nucleotides) at the limit of quantification was found at an extremely high dienogest concentration of 5000 ng/mL. It was concluded that dienogest did not produce DNA-adducts in human liver slices to a relevant degree.
REFERENCES
- 1. Asherson RA, Cervera R, Font J. Multiorgan thrombotic disorders in systemic lupus erythematosus: a common link? Lupus. 1992 Aug;1(4):199-203.
- 2. Kwaan HC, Soff GA. Management of thrombotic thrombocytopenic purpura and hemolytic uremic syndrome Semin Hematol. 1997;34(2):81-9.
- 3. Sibai BM, Kustermann L, Velasco J. Current understanding of severe preeclampsia, pregnancy-associated hemolytic uremic syndrome, thrombotic thrombocytopenic purpura, hemolysis, elevated liver enzymes, and low platelet syndrome, and postpartum acute renal failure: different clinical syndromes or just different names? Curr Opin Nephrol Hypertens. 1994 Jul;3(4):436-45.
- 4. Stewart CL, Tina LU. Hemolytic uremic syndrome. Pediatr Rev. 1993 Jun;14(6):218-24.
- 5. Koenigs KP, McPhedran P, Spiro HM. Thrombosis in inflammatory bowel disease. J Clin Gastroenterol. 1987 Dec;9(6):627-31.
- 6. Knijff SCM, Goorissen EM, Velthuis-te Wierik EJM, Korver T, Grimes DA. Sickle Cell Disease. Summary of contraindications to oral contraceptives. New York: Parthenon Publishing Group; 2000. p. 243-6.
- 7. Adams HP, Biller J. Ischemic cerebrovascular disease. In: Bradley WG, Daroff RB, Fenichel GM, Marsden CD, editors. Neurology in clinical practice. Boston: Butterworth-Heinemann; 1996. p. 1014-9.
- 8. Carlone JP, Keen PD. Oral contraceptive use in women with chronic medical conditions. Nurse Pract. 1989 Sep;14(9):9-10, 2-3, 6.
- 9. Gross U, Honcamp M, Daume E, Frank M, Dusterberg B, Doss MO. Hormonal oral contraceptives, urinary porphyrin excretion and porphyrias. Horm Metab Res. 1995 Aug;27(8):379-83.
- 10. Petri M, Robinson C. Oral contraceptives and systemic lupus erythematosus. Arthritis Rheum. 1997 May;40(5):797-803.
- 11. Knijff SCM, Goorissen EM, Velthuis-te Wierik EJM, Korver T, Grimes DA. Hemolytic uremic syndrome. Summary of contraindications to oral contraceptives New York: Parthenon Publishing Group; 2000. p. 211-8.
- 12. Galimberti D. Chorea induced by the use of oral contraceptives. Report of a case and review of the literature. Ital J Neurol Sci. 1987 Aug;8(4):383-6.
- 13. Knijff SCM, Goorissen EM, Velthuis-te Wierik EJM, Korver T, Grimes DA. Herpes gestationis. Summary of contraindications to oral contraceptives. New York: Parthenon Publishing Group; 2000. p. 367-70.
- 14. Knijff SCM, Goorissen EM, Velthuis-te Wierik EJM, Korver T, Grimes DA. Otosclerosis. Summary of contraindications to oral contraceptives. New York: Parthenon Publishing Group; 2000. p. 387-91.
- 15. Morgan JK. Herpes gestationis influenced by an oral contraceptive. Br J Dermatol. 1968 Jul;80(7):456-8.
- 16. Knijff SCM, Goorissen EM, Velthuis-te Wierik EJM, Korver T, Grimes DA. Otosclerosis. Summary of contraindications to oral contraceptives New York: Parthenon Publishing Group; 2000. p. 387-91.
- 17. Collaborative Group on Hormonal Factors in Breast Cancer. Breast cancer and hormonal contraceptives: Collaborataive reanalysis of individual data on 53,297 women with breast cancer and 100,239 women without breast cancer from 54 epidemiological studies. . Lancet. 1996(347):1713-27.
- 18. Boyko EJ, Theis MK, Vaughan TL, Nicol-Blades B. Increased risk of inflammatory bowel disease associated with oral contraceptive use. Am J Epidemiol. 1994 Aug 1;140(3):268-78.
- 19. Godet PG, May GR, Sutherland LR. Meta-analysis of the role of oral contraceptive agents in inflammatory bowel disease. Gut. 1995 Nov;37(5):668-73.
- 20. Logan RF, Kay CR. Oral contraception, smoking and inflammatory bowel disease--findings in the Royal College of General Practitioners Oral Contraception Study. Int J Epidemiol. 1989 Mar;18(1):105-7.
- 21. Ramcharan S, Pellegrin FA, Ray R, Hsu J-P, Vessey MP. General summary of findings; general conclusions; implications. The Walnut Creek Contraceptive Drug Study: a prospective study of the side effects of oral contraceptives Volume III: An interim report: a comparison of disease occurrence leading to hospitalization or death in users and nonusers of oral contraceptives NIH Publication No 81-564 Bethesda (MD): US Department of Health, Education, and Welfare, Center for Population Research; 1981. p. 211-38.
- 22. Sutherland LR, Ramcharan S, Bryant H, Fick G. Effect of oral contraceptive use on reoperation following surgery for Crohn's disease. Dig Dis Sci. 1992 Sep;37(9):1377-82.
- 23. Vessey M, Jewell D, Smith A, Yeates D, McPherson K. Chronic inflammatory bowel disease, cigarette smoking, and use of oral contraceptives: findings in a large cohort study of women of childbearing age. Br Med J (Clin Res Ed). 1986 Apr 26;292(6528):1101-3.
- 24. EMEA. CPMP Public assessment report: combined oral contraceptives and venous thromboembolism. London: EMEA Committee for Proprietary Medicinal Products (CPMP)2001 Sep 28. Report No.: EMEA/CPMP/2201/01/en Final.
- 25. Dinger JC, Heinemann LA, Kuhl-Habich D. The safety of a drospirenone-containing oral contraceptive: final results from the European Active Surveillance Study on oral contraceptives based on 142,475 women-years of observation. Contraception. 2007 May;75(5):344-54.
- 26. Heit JA, Kobbervig CE, James AH, Petterson TM, Bailey KR, Melton LJ, 3rd. Trends in the incidence of venous thromboembolism during pregnancy or postpartum: a 30-year population-based study. Ann Intern Med. 2005 Nov 15;143(10):697-706.
- 27. Binkley KE, Davis A, 3rd. Clinical, biochemical, and genetic characterization of a novel estrogen-dependent inherited form of angioedema. J Allergy Clin Immunol. 2000 Sep;106(3):546-50.
- 28. Bork K, Fischer B, Dewald G. Recurrent episodes of skin angioedema and severe attacks of abdominal pain induced by oral contraceptives or hormone replacement therapy. Am J Med. 2003 Mar;114(4):294-8.
- 29. Nzeako UC, Frigas E, Tremaine WJ. Hereditary angioedema: a broad review for clinicians. Arch Intern Med. 2001 Nov 12;161(20):2417-29.
- 30. Ahrendt HJ, Makalova D, Parke S, Mellinger U, Mansour D. Bleeding pattern and cycle control with an estradiol-based oral contraceptive: a seven-cycle, randomized comparative trial of estradiol valerate/dienogest and ethinyl estradiol/levonorgestrel. Contraception. 2009 Nov;80(5):436-44.
- 31. Junge W, Mellinger U, Parke S, Serrani M. Metabolic and haemostatic effects of estradiol valerate/dienogest, a novel oral contraceptive: a randomized, open-label, single-centre study. Clin Drug Investig. 2011;31(8):573-84.
- 32. Barditch-Crovo P, Trapnell CB, Ette E, Zacur HA, Coresh J, Rocco LE, et al. The effects of rifampin and rifabutin on the pharmacokinetics and pharmacodynamics of a combination oral contraceptive. Clin Pharmacol Ther. 1999 Apr;65(4):428-38.
- 33. Krauss GL, Brandt J, Campbell M, Plate C, Summerfield M. Antiepileptic medication and oral contraceptive interactions: a national survey of neurologists and obstetricians. Neurology. 1996;46:1534-9.
- 34. Riva R, Albani F, Contin M, Baruzzi A. Pharmacokinetic interactions between antiepileptic drugs: clinical considerations. Clin Pharmacokinet. 1996 Dec;31(6):470-93.
- 35. Saano V, Glue P, Banfield CR, Reidenberg P, Colucci RD, Meehan JW, et al. Effects of felbamate on the pharmacokinetics of a low-dose combination oral contraceptive. Clin Pharmacol Ther. 1995 Nov;58(5):523-31.
- 36. Mildvan D, Yarrish R, Marshak A, Hutman HW, McDonough M, Lamson M, et al. Pharmacokinetic interaction between nevirapine and ethinyl estradiol/norethindrone when administered concurrently to HIV-infected women. J Acquir Immune Defic Syndr. 2002 Apr 15;29(5):471-7.
- 37. WHO. Medical eligibility criteria for contraceptive use. Geneva: World Health Organization, Reproductive Health and Research2004: 1-178.
- 38. Palacios S, Wildt L, Parke S, Machlitt A, Romer T, Bitzer J. Efficacy and safety of a novel oral contraceptive based on oestradiol (oestradiol valerate/dienogest): A Phase III trial. Eur J Obstet Gynecol Reprod Biol. 2010 Dec 5:57-62.
- 39. Jensen JT, Parke S, Mellinger U, Machlitt A, Fraser IS. Effective treatment of heavy menstrual bleeding with estradiol valerate and dienogest: a randomized controlled trial. Obstet Gynecol. 2011 Apr;117(4):777-87.
- 40. Fraser IS, Romer T, Parke S, Zeun S, Mellinger U, Machlitt A, et al. Effective treatment of heavy and/or prolonged menstrual bleeding with an oral contraceptive containing estradiol valerate and dienogest: a randomized, double-blind Phase III trial. Hum Reprod. 2011 Oct;26(10):2698-708.
- 41. Dusterberg B, Nishino Y. Pharmacokinetic and pharmacological features of oestradiol valerate. Maturitas. 1982 Dec;4(4):315-24.
- 42. Kuhnz W, Putz B. Pharmacokinetic interpretation of toxicity tests in rats treated with oestradiol valerate in the diet. Pharmacol Toxicol. 1989 Sep;65(3):217-22.
- 43. Hewitt SC, Korach KS. Estrogen receptors: structure, mechanisms and function. Rev Endocr Metab Disord. 2002 Sep;3(3):193-200.
- 44. Tamaya T, Kawabata I, Iida K, Imai A. Effects of estradiol-17 beta and estriol on their binding sites in the rabbit uterus. Comp Biochem Physiol B. 1990;95(2):415-8.
- 45. Katsuki Y, Sasagawa S, Takano Y, Shibutani Y, Aoki D, Udagawa Y, et al. Animal studies on the endocrinological profile of dienogest, a novel synthetic steroid. Drugs Exp Clin Res. 1997;23(2):45-62.
- 46. Oettel MK, G. Schröder, J. Präklinik und Klinik des Gestagens Dienogest (Preclinical and clinical properties of the progestin Dienogest). Gynäko-Endokrinologie. 1993;2:17-29.
- 47. Marselos M, Vainio H. Carcinogenic properties of pharmaceutical agents evaluated in the IARC Monographs programme. Carcinogenesis. 1991 Oct;12(10):1751-66.
- 48. Günzel P, Putz B, Lehmann M, Hasan S, Hümpel M, Eletreby M. Steroid toxicology and the pill: comparative aspects of experimental test systems and the human. In: Dayan AD and Paine AJ eds Advances in Applied Toxicology Taylor and Francis ltd. 1989:19-49.
- 49. Bacic M, Wesselius de Casparis A, Diczfalusy E. Failure of large doses of ethinyl estradiol to interfere with early embryonic development in the human species. Am J Obstet Gynecol. 1970 Jun 15;107(4):531-4.
- 50. Lehmann MP, B. Poggel, HA. et al. Experimental toxicity studies with contraceptive steroids and their relevance for human risk estimation. In: Dayan AD, Paine AJ, eds Advances in Applied Toxicology London, New York, Philadelphia: Taylor & Francis. 1989:51-79.
- 51. Jemilev ZA, Komor A, Strecke J, Oettel M, Schubert K. [Chromosomal analysis of baboons and their mothers, following application to mothers of potentially post-ovulation fertility-inhibiting steroids (author's transl)]. Zentralbl Gynakol. 1981;103(20):1215-9.
- 52. Strecke JK, A. Jemilew, Z. et al. Chromosomenanalytische Untersuchungen an weiblichen Pavianen nach Behandlung mit STS 557 und Levonorgestrel. (Chromosome analysis on female baboons after treatment with STS 557 or Levonorgestrel). Zentralblatt Gynäkologie. 1985;107:304-07.
- 53. Schoneich J, Becker K, Braun R. Investigations on the mutagenic activity of STS 557. Exp Clin Endocrinol. 1983 Feb;81(2):210-6.