


Product Monograph - Ratio-Ramipril
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Capsules 1.25 mg 2.5 mg 5.0 mg 10.0 mg 15.0 mg | $ 1.25 mg capsule: pre-gelatinized starch, gelatine, yellow iron oxide, titanium dioxide. $ 2.5 mg capsule: pre-gelatinized starch, gelatine, yellow iron oxide, FD&C red no.3, titanium dioxide $ 5.0 mg capsule: pre-gelatinized starch, gelatine, FD&C blue no.2, FD&C red no.3, titanium dioxide. $ 10.0 mg capsule: pre-gelatinized starch, gelatine, FD&C blue no.2, FD&C red no.3, black iron oxide, titanium dioxide. $ 15.0 mg capsule: pre-gelatinized starch, gelatine, D&C red no.28, FD&C blue no.1, black iron oxide, titanium dioxide. |
INDICATIONS AND CLINICAL USE
ratio-RAMIPRIL (ramipril) is indicated for:
Essential Hypertension
ratio-RAMIPRIL is indicated in the treatment of essential hypertension. It may be used alone or in association with thiazide diuretics.
ratio-RAMIPRIL can also be tried as an initial agent in those patients in whom use of diuretics and/or beta blockers are contraindicated or in patients with medical conditions in which these drugs frequently cause serious adverse effects.
The safety and efficacy of ratio-RAMIPRIL in renovascular hypertension have not been established and therefore, its use in this condition is not recommended.
The safety and efficacy of concurrent use of ratio-RAMIPRIL with antihypertensive agents other than thiazide diuretics or calcium channel blocker felodipine have not been established.
Treatment Following Acute Myocardial Infarction
ratio-RAMIPRIL is indicated following acute myocardial infarction in clinically stable patients with signs of left ventricular dysfunction to improve survival and reduce hospitalizations for heart failure.
Sufficient experience in the treatment of patients with severe (NYHA class IV) heart failure immediately after myocardial infarction is not yet available. (See WARNINGS AND PRECAUTIONS-Cardiovascular, Hypotension)
Management of Patients at Increased Risk of Cardiovascular Events
ratio-RAMIPRIL may be used to reduce the risk of myocardial infarction, stroke or cardiovascular death in patients over 55 years of age who are at high risk of cardiovascular events because of a history of coronary artery disease, stroke, peripheral artery disease, or diabetes that is accompanied by at least one other cardiovascular risk factor such as hypertension, elevated total cholesterol levels, low high density lipoprotein levels, cigarette smoking, or documented microalbuminuria.
General
Geriatrics (> 65 years of age)
Although clinical experience has not identified differences in response between the elderly (> 65 years) and younger patients, greater sensitivity of some older individuals cannot be ruled out (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Pediatrics
The safety and effectiveness of ratio-RAMIPRIL in children have not been established; therefore use in this age group is not recommended.
CONTRAINDICATIONS
ratio-RAMIPRIL is contraindicated in:
- Patients who are hypersensitive to this drug, to any other ACE inhibitor, or to any ingredient in the formulation. For a complete listing of ingredients see Dosage Forms, Composition and Packaging section of the product monograph.
- Patients who have a history of angioedema.
- During pregnancy
- In breast feeding-women
- In patients with haemodynamically relevant bilateral renal artery stenosis, or unilateral in the single kidney.
- Patients with hypotensive states
Concomitant use of ACE inhibitors and extracorporeal treatment leading to contact of blood with negatively charged surfaces must be avoided (see WARNINGS AND PRECAUTIONS, Immune section).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
When used in pregnancy, angiotensin converting enzyme (ACE) inhibitors can cause injury or even death of the developing fetus. When pregnancy is detected ratio-RAMIPRIL should be discontinued as soon as possible.
General
Cough
A dry, persistent cough, which usually disappears only after withdrawal or lowering of the dose of ramipril, has been reported. Such possibility should be considered as part of the differential diagnosis of cough (see ADVERSE REACTIONS).
Patient alertness
ratio-RAMIPRIL may lower the state of patient alertness and/or reactivity, particularly at the start of treatment (see ADVERSE REACTIONS).
Cardiovascular
Aortic Stenosis:
There is concern, on theoretical grounds, that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Hypotension:
Symptomatic hypotension has occurred after administration of ramipril, usually after the first or second dose or when the dose was increased. It is more likely to occur in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, vomiting, or in other situations in which a significant activation of the renin-angiotensin system is to be
anticipated such as in patients with severe, and particularly with malignant hypertension, in patients with haemodynamically relevant left-ventricular outflow impediment (e.g., stenosis of the aortic valve) or in patients with haemodynamically relevant renal artery stenosis.
In patients with ischemic heart disease or cerebrovascular disease, an excessive fall in blood pressure could result in a myocardial infarction or cerebrovascular accident (see ADVERSE REACTIONS-Clinical Trial Adverse Drug Reactions, Treatment Following Acute Myocardial Infarction-Management of Patients at Increased Risk of Cardiovascular Events-Less Common Clinical Trial Adverse Drug Reactions (<1%), Cardiovascular). Because of the potential fall in blood pressure in these patients, therapy with ratio-RAMIPRIL should be started under close medical supervision. Such patients should be followed closely for the first weeks of treatment and whenever the dose of ratio-RAMIPRIL is increased. In patients with severe congestive heart failure, with or without associated renal insufficiency, ACE inhibitor therapy may cause excessive hypotension and has been associated with oliguria, and/or progressive azotemia, and rarely, with acute renal failure and/or death.
Generally, it is recommended that dehydration, hypovolaemia or salt depletion be corrected before initiating treatment (in patients with heart failure, however, such corrective action must be carefully weighed against the risk of volume overload). When these conditions have become clinically relevant, treatment with ratio-RAMIPRIL must only be started or continued if appropriate steps are taken concurrently to prevent an excessive fall in blood pressure and deterioration of renal function.
If hypotension occurs, the patient should be placed in a supine position and, if necessary, receive an intravenous infusion of 0.9% sodium chloride. A transient hypotensive response may not be a contraindication to further doses which usually can be given without difficulty once the blood pressure has increased after volume expansion in hypertensive patients. However, lower doses of ratio-RAMIPRIL and/or reduced concomitant diuretic therapy should be considered. In patients receiving treatment following acute myocardial infarction, consideration should be given to discontinuation of ratio-RAMIPRIL (see ADVERSE REACTIONS-Clinical Trial Adverse Drug Reactions, Treatment Following Acute Myocardial Infarction, DOSAGE & ADMINISTRATION-Recommended Dose and Dosage Adjustment, Treatment Following Acute Myocardial Infarction).
Hematologic
Hyperkalemia and Potassium-Sparing Diuretics
Elevated serum potassium (greater than 5.7 mEq/L) was observed in approximately 1% of hypertensive patients in clinical trials treated with ramipril. In most cases these were isolated values which resolved despite continued therapy. Hyperkalemia was not a cause of discontinuation of therapy in any hypertensive patient. Risk factors for the development of hyperkalemia may include renal insufficiency, diabetes mellitus, and the concomitant use of agents to treat hypokalemia or other drugs associated with increases in serum potassium (see DRUG INTERACTIONS-Drug-Drug Interactions).
Neutropenia/agranulocytosis
Agranulocytosis and bone marrow depression have been caused by ACE inhibitors. Several cases of agranulocytosis, neutropenia or leukopenia have been reported in which a causal relationship to ramipril cannot be excluded. Current experience with the drug shows the incidence to be rare. Periodic monitoring of white blood cell counts should be considered especially in patients with collagen vascular disease and/or renal disease. (see WARNINGS AND PRECAUTIONS- Monitoring and Laboratory Tests, and ADVERSE REACTIONS- Less Common Adverse Drug reactions, Hematologic)
Hepatic/Biliary
Hepatitis (hepatocellular and/or cholestatic), elevations of liver enzymes and/or serum bilirubin have occurred during therapy with ACE inhibitors in patients with or without pre-existing liver abnormalities. In most cases the changes were reversed on discontinuation of the drug.
Elevations of liver enzymes and/or serum bilirubin have been reported with ramipril (see ADVERSE REACTIONS). Should the patient receiving ratio-RAMIPRIL experience any unexplained symptoms particularly during the first weeks or months of treatment, it is recommended that a full set of liver function tests and any other necessary investigations be carried out. Discontinuation of ratio-RAMIPRIL should be considered when appropriate.
There are no adequate studies in patients with cirrhosis and/or liver dysfunction. In patients with impaired liver function, response to the treatment with ratio-RAMIPRIL may be either increased or reduced. In addition, in patients in whom severe liver cirrhosis with oedema and ascites is present, the renin-angiotensin system may be significantly activated. ratio-RAMIPRIL should be used with particular caution in patients with pre-existing liver abnormalities. In such patients baseline liver function tests should be obtained before administration of the drug and close monitoring of response and metabolic effects should apply (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations and conditions, Hepatic Insufficiency).
Rarely, ACE inhibitors, including ramipril, have been associated with a syndrome that starts with cholestatic jaundice and progresses to fulminant hepatic necrosis and (sometimes) death. The mechanism of this syndrome is not understood. Patients receiving ACE inhibitors who develop jaundice or marked elevations of hepatic enzymes should discontinue the ACE inhibitor and receive appropriate medical follow-up.
Immune
Angioedema – Head, and Neck
Angioedema has been reported in patients with ACE inhibitors including ramipril. Angioedema associated with laryngeal involvement may be fatal. If laryngeal stridor or angioedema of the face, extremities, lips, tongue, or glottis occurs, ratio-RAMIPRIL should be discontinued immediately, the patient treated appropriately in accordance with accepted medical care, and
carefully observed until the swelling disappears. In instances where swelling is confined to the face and lips, the condition generally resolves without treatment, although antihistamines may be useful in relieving symptoms. Where there is involvement of tongue, glottis, or larynx, likely to cause airway obstruction, appropriate therapy (including, but not limited to 0.3 to 0.5 ml of subcutaneous epinephrine solution 1:1000) should be administered promptly (see ADVERSE REACTIONS-Clinical Trial Adverse Drug Reactions, Essential Hypertension-Less Common Clinical Trial Adverse Drug Reactions (<1%), Body as a whole).
Angioedema – Intestinal
Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases facial angioedema also occurred. The intestinal angioedema symptoms resolved after stopping the ACE inhibitor.
The incidence of angioedema during ACE inhibitor therapy has been reported to be higher in black than in non-black patients.
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see CONTRAINDICATIONS).
Angioedema, including laryngeal edema, may occur especially following the first dose of ratio-RAMIPRIL.
Anaphylactoid reactions during membrane exposure
Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes [e.g. polyacrylonitrile (PAN)] and treated concomitantly with an ACE inhibitor. Dialysis should be stopped immediately if symptoms such as nausea, abdominal cramps, burning, angioedema, shortness of breath and severe hypotension occur. Symptoms are not relieved by antihistamines. In these patients consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agents.
Anaphylactoid reactions during LDL apheresis
Rarely, patients receiving ACE inhibitors during low density lipoprotein apheresis with dextran sulfate have experienced life-threatening anaphylactoid reactions. These reactions were avoided by temporarily withholding the ACE inhibitor therapy prior to each apheresis.
Anaphylactoid reactions during desensitization
There have been isolated reports of patients experiencing sustained life threatening anaphylactoid reactions while receiving ACE inhibitors during desensitization treatment with hymenoptera (e.g. bees, wasps) venoma. In the same patients, these reactions have been avoided when ACE inhibitors were temporarily withheld for at least 24 hours, but they have reappeared upon inadvertent rechallenge.
Peri-Operative Considerations
Surgery/anesthesia
In patients undergoing surgery or anesthesia with agents producing hypotension, ratio-RAMIPRIL may block angiotensin II formation secondary to compensatory renin release. If hypotension occurs and is considered to be due to this mechanism, it may be corrected by volume repletion.
Renal
As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk; therefore, discontinuation of diuretic therapy may be required.
Use of ratio-RAMIPRIL should include appropriate assessment of renal function.
ratio-RAMIPRIL should be used with caution in patients with renal insufficiency as they may require reduced or less frequent doses (see DOSAGE AND ADMINISTRATION). Close monitoring of renal function during therapy should be performed as deemed appropriate in patients with renal insufficiency.
Special Populations
Pregnant Women
ACE inhibitors can cause fetal and neonatal morbidity and mortality when administered to pregnant women. When pregnancy is detected, ratio-RAMIPRIL should be discontinued as soon as possible.
The use of ACE inhibitors during the second and third trimesters of pregnancy has been associated with fetal and neonatal injury including hypotension, neonatal skull hypoplasia, anuria, reversible or irreversible renal failure, and death. Oligohydramnios has also been reported, presumably resulting from decreased fetal renal function, associated with fetal limb contractures, craniofacial deformation, and hypoplastic lung development.
Prematurity, and patent ductus arteriosus and other structural cardiac malformations, as well as neurologic malformations, have also been reported following exposure in the first trimester of pregnancy.
Infants with a history of in utero exposure to ACE inhibitors should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit.
It is not known if ramipril or ramiprilat can be removed from the body by hemodialysis.
Animal Data: No teratogenic effects of ramipril were seen in studies of pregnant rats, rabbits, and cynomolgus monkeys. The doses used were: 10, 100, or 1000 mg/kg in rats (2500 times maximum human dose), 0.4, 1.0, or 2.5 mg/kg in rabbits (6.25 times maximum human dose), and 5, 50, or 500 mg/kg in cynomolgus monkeys (1250 times maximum human dose). In rats, the highest dose caused reduced food intake in the dams, with consequent reduced birth weights of the pups and weight development during the lactation period. In rabbits, maternal effects were mortalities (high and middle dose) and reduced body weight. In monkeys, maternal effects were mortalities (high and middle dose), vomiting, and reduced weight gain.
Nursing Women
The presence of concentrations of ACE inhibitor have been reported in human milk. The use of ratio-RAMIPRIL is contraindicated during breast-feeding.
Pediatrics
The safety and effectiveness of ratio-RAMIPRIL in children have not been established; therefore use in this age group is not recommended.
Geriatrics (> 65 years of age)
Although clinical experience has not identified differences in response between the elderly (> 65 years) and younger patients, greater sensitivity of some older individuals cannot be ruled out (see ACTION AND CLINICAL PHARMACOLOGY-Special Populations and Conditions, Geriatrics).
Monitoring and Laboratory Tests
Hematological monitoring
Periodic monitoring of white blood cell counts should be considered to permit detection of a possible leukopenia. More frequent monitoring is advised in the initial phase of treatment and in patients with impaired renal function, those with concomitant collagen disease (e.g. lupus erythematosus or scleroderma) or those treated with other drugs that can cause changes in the blood picture (see DRUG INTERACTIONS – Drug-Drug Interactions, Allopurinol, Immunosuppressants, Corticosteroids, Procainamide, Cytostatics and other substances that may change the blood picture).
Renal function monitoring
Use of ratio-RAMIPRIL should include appropriate assessment of renal function, particularly in the initial weeks treatment with an ACE inhibitor. Close monitoring of renal function during therapy should be performed as deemed appropriate in patients with renal insufficiency. Particularly careful monitoring is required in patients with:
- heart failure
- renovascular disease, including patients with haemodynamically relevant unilateral renal artery stenosis. In the latter patient group, even a small increase in serum creatinine may be indicative of unilateral loss of renal function
- impairment of renal function
- kidney transplant
Electrolyte monitoring
It is recommended that serum potassium be monitored regularly. More frequent monitoring of serum potassium is necessary in patients with impaired renal function.
Driving a vehicle or performing other hazardous tasks
Some adverse effects (e.g. some symptoms of a reduction in blood pressure such as lightheadedness, dizziness, syncope) may impair the patient's ability to concentrate and react and, therefore, constitute a risk in situations where these abilities are of particular importance (e.g. operating a vehicle or machinery).
Information for the Patient
Cardiovascular
Hypotension:
Patients should be cautioned to report lightheadedness, especially during the first few days of ratio-RAMIPRIL therapy. If actual syncope occurs, the patients should be told to discontinue the drug and consult with their physician.
All patients should be cautioned that excessive perspiration and dehydration may lead to an excessive fall in blood pressure because of reduction in fluid volume. Other causes of volume depletion such as vomiting or diarrhea may also lead to a fall in blood pressure, patients should be advised to consult with their physician.
Hematologic
Hyperkalemia and Potassium–Sparing Diuretics:
Patients should be told not to use salt substitutes containing potassium without consulting their physician.
Neutropenia/agranulocytosis:
Patients should be told to report promptly to their physician any indication of infection (e.g. sore throat, fever) as this may be a sign of neutropenia (see ADVERSE REACTIONS).
Hepatic/Biliary
Patients should be advised to return to their physician if they experience any symptoms possibly related to liver dysfunction. This would include "viral-like symptoms" in the first weeks to months of therapy (such as fever, malaise, muscle pain, rash or adenopathy which are possible indicators of hypersensitivity reactions), or if abdominal pain, nausea or vomiting, loss of appetite, jaundice, itching or any other unexplained symptoms occur during therapy.
Immune
Angioedema:
Patients should be so advised and told to report immediately any signs or symptoms suggesting angioedema, such as swelling of face, extremities, eyes, lips, tongue, difficulty in swallowing or breathing. They should immediately stop taking ratio-RAMIPRIL and consult with their physician.
Special Populations
Pregnancy:
Since the use of ratio-RAMIPRIL during pregnancy can cause injury and even death of the developing foetus, patients should be advised report promptly to their physician if they become pregnant and the use of ratio-RAMIPRIL should be stopped.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
As ramipril is an antihypertensive; the most common adverse reactions are effects secondary to its blood-pressure-lowering action.
The long-term safety of ramipril, as monotherapy was assessed in patients with hypertension. The most commonly reported serious adverse reactions were hypotension (0.1%); myocardial infarction (0.3%); cerebrovascular accident (0.1%); edema (0.2%); syncope (0.1%). Angioedema occurred in 0.1% patients treated with ramipril and a diuretic.
The most frequent adverse events occurring in these trials were: headache (15.1%); dizziness (3.7%); asthenia (3.7%); chest pain (2.0%); nausea (1.8%); peripheral edema (1.8%); somnolence (1.7%); impotence (1.5%); rash (1.4%); arthritis (1.1%); dyspnea (1.1%). Discontinuation of therapy due to clinical adverse events was required in 0.8% of patients treated
with ramipril. Approximately 1% of patients in North American controlled clinical trials have required discontinuation because of cough.
Post Acute Myocardial Infarction Adverse reactions (AIRE Study) considered possibly/probably related to study drug that occurred in more than 1% of patients and more frequently on ramipril were: Hypotension, Cough increased, Dizziness/Vertigo, Nausea/Vomiting, Angina pectoris, Postural hypotension, Syncope, Heart failure, Severe/resistant heart failure, Myocardial infarct, Vomiting, Headache, Abnormal kidney function, Abnormal chest pain and Diarrhea. Discontinuation of therapy due to adverse reactions was required in post-AMI patients taking ramipril (36.7%), compared to patients receiving placebo (40.8%).
The safety profile of ramipril in patients at Increased Risk of Cardiovascular Events (HOPE Study) was consistent with the post-marketing surveillance experience. Reasons for discontinuation of therapy, were cough (ramipril 7.3%, placebo 1.8%), hypotension/dizziness (ramipril 1.9%, placebo 1.5%) and edema (ramipril 0.4%, placebo 0.2%).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Essential Hypertension
Ramipril has been evaluated for safety in over 4000 hypertensive patients. Almost 500 elderly patients have participated in controlled trials. Long-term safety has been assessed in almost 700 patients treated for 1 year or more. There was no increase in the incidence of adverse events in elderly patients given the same daily dose. The overall frequency of adverse events was not related to duration of therapy or total daily dose.
Serious adverse events occurring in North American placebo-controlled clinical trials with ramipril monotherapy in hypertension (n=972) were: hypotension (0.1%); myocardial infarction (0.3%); cerebrovascular accident (0.1%); edema (0.2%); syncope (0.1%). Among all North American ramipril patients (n=1,244), angioedema occurred in 0.1% patients treated with ramipril and a diuretic.
The most frequent adverse events occurring in these trials with Ramipril monotherapy in hypertensive patients that were treated for at least one year (n=651) were: headache (15.1%); dizziness (3.7%); asthenia (3.7%); chest pain (2.0%); nausea (1.8%); peripheral edema (1.8%); somnolence (1.7%); impotence (1.5%); rash (1.4%); arthritis (1.1%); dyspnea (1.1%). Discontinuation of therapy due to clinical adverse events was required in 5 patients (0.8%).
In placebo-controlled trials, an excess of upper respiratory infection and flu syndrome was seen in the ramipril group. As these studies were carried out before the relationship of cough to ACE inhibitors was recognized, some of these events may represent ramipril-induced cough. In a later 1-year study, increased cough was seen in almost 12% of ramipril patients, with about 4% of these patients requiring discontinuation of treatment. Approximately 1% of patients treated with ramipril monotherapy in North American controlled clinical trials (n=972) have required discontinuation because of cough.
Treatment Following Acute Myocardial Infarction
1004 post-AMI patients received ramipril in a controlled clinical trial. In both the ramipril and placebo groups, myocardial infarction, heart failure, atrial fibrillation, peripheral vascular disease and urinary tract infection were more common in elderly than in younger patients. Gastrointestinal disturbances were more frequent in elderly patients on ramipril. Cough and hypotension were more frequent in women receiving ramipril.
Adverse events (except laboratory abnormalities) considered possibly/probably related to study drug that occurred in more than one percent of stabilized patients with clinical signs of heart failure treated with ramipril following an acute myocardial infarction are shown below. The incidences represent the experiences from the AIRE (Acute Infarction Ramipril Efficacy) study. The follow-up time was between 6 and 48 months for this study (mean follow up = 15 months).
Table 1: Percentage of Patients with Adverse Events Possibly/Probably Related to Study Drug Placebo-Controlled (AIRE) Mortality Study
| Adverse Event | Ramipril (n=1004) | Placebo (n=982) |
Hypotension Cough increased Dizziness/Vertigo Nausea/Vomiting Angina pectoris Postural hypotension Syncope Heart failure Severe/resistant heart failure Myocardial infarct Vomiting Headache Abnormal kidney function Abnormal chest pain Diarrhea | 10.7 7.6 5.6 3.8 2.9 2.2 2.1 2.0 2.0 1.7 1.6 1.2 1.2 1.1 1.1 | 4.7 3.7 3.9 1.9 2.0 1.4 1.4 2.2 3.0 1.7 0.5 0.8 0.5 0.9 0.4 |
Table 2: Percentage of Patients with Serious Adverse Events Possibly related to Study Drug Placebo-Controlled (AIRE) Mortality Study
| Event | Ramipril (n = 1004) | Placebo (n = 982) |
| Hypotension | 3.0% | 1.1% |
| Angina pectoris | 2.0% | 1.2% |
| Severe/resistant heart failure | 1.9% | 2.9% |
| Myocardial infarct | 1.7% | 1.7% |
| Heart failure | 1.5% | 1.5% |
| Syncope | 1.3% | 0.8% |
| Chest pain | 0.7% | 0.9% |
| Nausea | 0.6% | 0.5% |
| Vomiting | 0.5% | 0.1% |
| Dizziness | 0.5% | 0.5% |
| Abnormal kidney function | 0.5% | 0.2% |
| Chest infection | 0.2% | 0.0% |
| Postural hypotension | 0.2% | 0.2% |
| Headache | 0.1% | 0.0% |
Isolated cases of death have been reported with the use of ramipril that appear to be related to hypotension (including first dose effects), but many of these are difficult to differentiate from progression of underlying disease (see WARNINGS AND PRECAUTIONS-Cardiovascular, Hypotension).
Discontinuation of therapy due to adverse reactions was required in 368/1004 post-AMI patients taking ramipril (36.7%), compared to 401/982 patients receiving placebo (40.8%).
Management of Patients at Increased Risk of Cardiovascular Events
In the Heart Outcome Prevention Evaluation (HOPE) study, based on a total of 4645 patients treated with ramipril, the safety profile of ramipril was consistent with the post-marketing surveillance experience. The reasons for stopping the treatment, where the incidence was greater in the ramipril than in the placebo group, were cough (ramipril 7.3%, placebo 1.8%), hypotension/dizziness (ramipril 1.9%, placebo 1.5%) and edema (ramipril 0.4%, placebo 0.2%).
Less Common Adverse Drug Reactions (<1%)
Clinical adverse events occurring in less than 1% of patients treated with ramipril in controlled clinical trials are listed below by body system:
Body as a whole: angioedema.
Cardiovascular: symptomatic hypotension, flushing, syncope, angina pectoris, arrhythmia, chest pain, palpitations, tachycardia, myocardial infarction, disturbed orthostatic regulation, vascular stenosis, exacerbation of perfusion disturbances due to vascular stenoses.
CNS: anxiety, amnesia, confusion, convulsions, depression, impaired hearing, hearing loss, insomnia, sleep disturbances, nervousness, neuralgia, neuropathy, paresthesia, polyneuritis, somnolence, tinnitus, tremor, vertigo, vision disturbances (including blurred vision), disorders of balance, lightheadness, restlessness.
Dermatologic: apparent hypersensitivity reactions (with manifestations of urticaria, pruritus, or rash, with or without fever), photosensitivity, purpura.
In addition, the following cutaneous or mucosal reactions may occur: maculopapular rash, maculo-papular exanthema, psoriasiform exanthema, erythroderma/exfoliative dermatitis, and onycholysis.
Gastrointestinal: pancreatitis (cases of fatal outcome have been very exceptionally reported), abdominal pain (sometimes with enzyme changes suggesting pancreatitis), upper abdominal pain, gastritis, intestinal angioedema, glossitis, increased levels of pancreatic enzymes, anorexia, decreased appetite, constipation, diarrhea, digestive disturbances, dry mouth, dyspepsia, dysphagia, gastroenteritis, nausea, increased salivation, taste disturbance, vomiting, abdominal discomfort.
Rarely, ACE inhibitors, including ramipril, have been associated with a syndrome that starts with cholestatic jaundice and progresses to fulminant hepatic necrosis and (sometimes) death.
Haematologic: agranulocytosis, leucopenia, eosinophilia, thrombocytopenia (see WARNINGS AND PRECAUTIONS - Hematologic, Neutropenia/agranulocytosis section).
Renal: increases in blood urea nitrogen (BUN) and serum creatinine, impaired renal function, Oliguria. Rarely, a deterioration of pre-existing proteinuria may develop (though ACE inhibitors usually reduce proteinuria) or an increase in urinary output (in connection with an improvement in cardiac performance).
Respiratory: increased cough, nasal congestion, sinusitis, bronchitis, and bronchospasm (including aggravated asthma).
Other: arthralgia, arthritis, dyspnea, edema, epistaxis, impotence, transient erectile impotence, increased sweating, malaise, myalgia, weight gain, conjunctivitis, muscle cramps, reduced libido, loss of taste, depressed mood.
A symptom complex has been reported which may include fever, vasculitis, myalgia, arthralgia/arthritis, elevated ESR, eosinophilia and leucocytosis. Rash, photosensitivity or other dermatologic manifestations may also occur.
Abnormal Hematologic and Clinical Chemistry Findings
Increased creatinine; increases in blood urea nitrogen (BUN); decreases in red blood cell count, hemoglobin or hematocrit; hyponatraemia; elevations of liver enzymes, serum bilirubin, uric acid, blood glucose; proteinuria and significant increases in serum potassium.
Post-Market Adverse Drug Reaction
Body as a whole: anaphylactoid reactions, angioedema (cases of fatal outcome have been reported).
Cardiovascular: cerebrovascular disorders (including ischaemic stroke).
CNS: burning sensation (mainly to skin of face or extremities), smell disturbances, precipitation or intensification of Raynaud’s phenomenon, impaired psychomotor skills (impaired reactions), attention disturbances.
Dermatologic: erythema multiforms, pemphigus, Stevens-Johnson syndrome, exacerbation of psoriasis, lichenoid exanthema, pemphigoid exanthema and enanthema, reversible alopecia, toxic epidermal necrolysis.
Gastrointestinal: hepatic failure, cholestatic jaundice, hepatitis (cases of fatal outcome have been very exceptionally reported), aphtous stomatitis; in isolated cases liver damage (including acute liver failure) may occur.
Haematologic: pancytopaenia, bone marrow depression and hemolytic anemia (see WARNINGS AND PRECAUTIONS - Hematologic, Neutropenia/agranulocytosis section).
Laboratory test findings: decrease in blood sodium.
Other: gynaecomastia, positive ANA.
DRUG INTERACTIONS
Drug-Drug Interactions
Concomitant Diuretic Therapy: Patients concomitantly taking ACE inhibitors and diuretics, and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy. The possibility of hypotensive effects after the first dose of ratio-RAMIPRIL can be minimized by either discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with ratio-RAMIPRIL. If it is not possible to discontinue the diuretic, the starting dose of ratio-RAMIPRIL should be reduced and the patient should be closely observed for several hours following the initial dose and until blood pressure has stabilized (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION). Regular monitoring of serum sodium is recommended in patients undergoing concurrent diuretic therapy.
Other substances with antihypertensive potential (e.g. nitrates): potentiation of the antihypertensive effect is to be anticipated.
Vasopressor sympathomimetics: These may reduce the antihypertensive effect of ratio-RAMIPRIL. Particularly close blood pressure monitoring is recommended.
Agents Increasing Serum Potassium: Since ratio-RAMIPRIL decreases aldosterone production, elevation of serum potassium may occur. Potassium sparing diuretics such as spironolactone, triamterene or amiloride, or potassium supplements should be given only for documented hypokalemia and with caution and frequent monitoring of serum potassium, since they may lead to a significant increase in serum potassium. Salt substitutes which contain potassium should also be used with caution (See also Non-steroidal anti-inflammatory agents).
Agents Causing Renin Release: The antihypertensive effect of ramipril is augmented by antihypertensive agents that cause renin release (e.g. diuretics).
Lithium: Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving ACE inhibitors during therapy with lithium. These drugs should be administered with caution, and frequent monitoring of serum lithium levels is recommended. If a diuretic is also used, the risk of lithium toxicity may be further increased.
Antacids: In one open-label, randomized, cross-over single dose study in 24 male subjects, it was determined that the bioavailability of ramipril and the pharmacokinetic profile of ramiprilat were not affected by concomitant administration of the antacid, magnesium and aluminum hydroxides.
Digoxin: In one open-label study in 12 subjects, administered multiple doses of both ramipril and digoxin, no changes were found in serum levels of ramipril, ramiprilat, and digoxin.
Warfarin: The co-administration of ramipril with warfarin did not alter the anticoagulant effects.
Acenocoumarol: In a multi-dose double-blind, placebo-controlled, pharmacodynamic interaction study with 14 patients with mild hypertension administered both ramipril and therapeutic doses of acenocoumarol, blood pressure, thrombotest time and coagulation factors were not significantly changed.
Non-steroidal anti-inflammatory agents and acetylsalicylic acid: The antihypertensive effects of ACE inhibitors may be reduced with concomitant administration of non-steroidal anti-inflammatory agents (e.g. indomethacin). Concomitant treatment of ACE inhibitors and Non-Steroidal Anti-Inflammatory drugs may lead to an increased risk of worsening of renal function and an increase in serum potassium. (See also Agents Increasing Serum Potassium).
Heparin: rise in serum potassium concentration possible.
Antidiabetic agents (e.g. insulin and sulfonylurea derivates): ACE inhibitors may reduce insulin resistance. In isolated cases, such reduction may lead to hypoglycaemic reactions in patients concomitantly treated with antidiabetics. Particularly close blood glucose monitoring is, therefore, recommended in the initial phase of co-administration.
Allopurinol, immunosuppressants, corticosteroids, procainamide, cytostatics and other substances that may change the blood picture: increased likelihood of haematological reactions.
Alcohol: increased vasodilatation. Alcohol may potentiate the effect of ratio-RAMIPRIL®.
Salt: increased dietary salt intake may attenuate the antihypertensive effect of ratio-RAMIPRIL®.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Essential Hypertension
Dosage of ratio-RAMIPRIL must be individualized. Initiation of therapy requires consideration of recent antihypertensive drug treatment, the extent of blood pressure elevation and salt restriction. The dosage of other antihypertensive agents being used with ratio-RAMIPRIL may need to be adjusted.
Monotherapy
The recommended initial dosage of ratio-RAMIPRIL in patients not on diuretics is 2.5 mg once daily. Dosage should be adjusted according to blood pressure response, generally, at intervals of at least two weeks. The usual dose range is 2.5 to 10 mg once daily. A daily dose of 20 mg should not be exceeded.
In some patients treated once daily, the antihypertensive effect may diminish towards the end of the dosing interval. This can be evaluated by measuring blood pressure just prior to dosing to determine whether satisfactory control is being maintained for 24 hours. If it is not, either twice daily administration with the same total daily dose, or an increase in dose should be considered. If blood pressure is not controlled with ratio-RAMIPRIL alone, a diuretic may be added. After the addition of a diuretic, it may be possible to reduce the dose of ratio-RAMIPRIL .
Concomitant Diuretic Therapy
Symptomatic hypotension occasionally may occur following the initial dose of ratio-RAMIPRIL and is more likely in patients who are currently being treated with a diuretic. The diuretic should, if possible, be discontinued for two to three days before beginning therapy with ratio-RAMIPRIL to reduce the likelihood of hypotension (see WARNINGS AND PRECAUTIONS). If the diuretic cannot be discontinued, an initial dose of 1.25 mg ratio-RAMIPRIL should be used with careful medical supervision for several hours and until blood pressure has stabilized. The dosage of ratio-RAMIPRIL should subsequently be titrated (as described above) to the optimal response.
Use in renal impairment
For patients with a creatinine clearance below 40ml/min/1.73m2 (serum creatinine above 2.5 mg/dL), the recommended initial dose is 1.25 mg ratio-RAMIPRIL once daily. Dosage may be titrated upward until blood pressure is controlled or to a maximum total daily dose of 5 mg. In patients with severe renal impairment (creatinine clearance below 10ml/min/1.73m2) the maximum total daily dose of 2.5 mg ratio-RAMIPRIL should not be exceeded.
Treatment Following Acute Myocardial Infarction
Dosage of ratio-RAMIPRIL must be individualized. Initiation of therapy requires consideration of concomitant medication and baseline blood pressure and should be instituted under close medical supervision, usually in a hospital, three to ten days following an acute myocardial infarction in haemodynamically stable patients with clinical signs of heart failure.
The recommended initial dosage of ratio-RAMIPRIL is 2.5 mg given twice a day (b.i.d.), one in the morning and one in the evening. If tolerated, and depending on the patient's response, dosage may be increased by doubling at intervals of one to three days. The maximum daily dose of ratio-RAMIPRIL should not exceed 5 mg twice daily (b.i.d.).
After the initial dose of ratio-RAMIPRIL, the patient should be observed under medical supervision for at least two hours and until blood pressure has stabilized for at least an additional hour. If a patient becomes hypotensive at this dosage, it is recommended that the dosage be lowered to 1.25 mg b.i.d. following effective management of the hypotension. (see WARNINGS AND PRECAUTIONS-Cardiovascular, Hypotension).
Patients who have been fluid or salt depleted, or treated with diuretics are at an increased risk of hypotension (see WARNINGS AND PRECAUTIONS-Cardiovascular, Hypotension). An excessive fall in blood pressure may occur particularly in the following: after the initial dose of ratio-RAMIPRIL; after every first increase of dose of ratio-RAMIPRIL; after the first dose of a concomitant diuretic and/or when increasing the dose of the concomitant diuretic. If appropriate, the dose of any concomitant diuretic should be reduced which may diminish the likelihood of hypotension (see DRUG INTERACTIONS-Drug-Drug Interactions). Consideration should be given to reducing the initial dose to 1.25 mg of ratio-RAMIPRIL in these patients.
Use in renal impairment
In patients with impaired renal function (creatinine clearance of 20-50 mL/min/1.73 m2 body surface area), the initial recommended dosage is generally 1.25 mg of ratio-RAMIPRIL once daily. This dosage may be increased with caution up to 1.25 mg of ratio-RAMIPRIL twice daily, depending upon clinical response and tolerability.
Insufficient data is available concerning the use of ramipril following acute myocardial infarction in patients with heart failure and severe renal failure. (see ACTION & CLINICAL PHARMACOLOGY-Pharmacokinetics, WARNINGS AND PRECAUTIONS - Renal).
Use in hepatic impairment
Insufficient data is available concerning the use of ramipril following acute myocardial infarction in patients with heart failure and hepatic dysfunction. Dose reduction and careful monitoring of these patients is required (see ACTIONS & CLINICAL PHARMACOLOGY-Pharmacokinetics, WARNINGS AND PRECAUTIONS-Hepatic/Biliary/Pancreatic).
Management of Patients at Increased Risk of Cardiovascular Events
Recommended initial dose: 2.5 mg of ratio-RAMIPRIL once daily. Depending on the tolerability, the dose is gradually increased. It is recommended to double the dose after one week of treatment and - after another three weeks - to increase it to 10 mg. Usual maintenance dose: 10 mg of ratio-RAMIPRIL daily (see ACTION AND CLINICAL PHARMACOLOGY, WARNINGS AND PRECAUTIONS).
Dosage recommendations for special risk groups such as patients with renal or hepatic impairment, or at an increased risk of hypotension (fluid or salt depletion, treated with diuretics) are to be followed as previously described (see WARNINGS AND PRECAUTIONS).
OVERDOSAGE
Limited data are available regarding overdosage of ratio-RAMIPRIL in humans. Two cases of overdosage have been reported.
In the case of an overdose with ramipril, the most likely clinical manifestation would be symptoms attributable to severe hypotension, which should normally be treated by intravenous volume expansion with normal saline.
Overdosage may cause excessive peripheral vasodilatation (with marked hypotension, shock), bradycardia, electrolyte disturbances, and renal failure.
Management
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Primary detoxification by, for example, gastric lavage, administration of adsorbents, sodium sulfate; (if possible during the first 30 minutes). In the event of hypotension administration of α1-adrenergic agonists (e.g. norepinephrine, dopamine) or angiotensin II (angiotensinamide), which is usually available only in scattered research laboratories, must be considered in addition to volume and salt substitution.
No experience is available concerning the efficacy of forced diuresis, alteration in urine pH, haemofiltration, or dialysis in speeding up the elimination of ramipril or ramiprilat. If dialysis or haemofiltration is nevertheless considered, see also WARNINGS AND PRECAUTIONS, Immune, Anaphylactoid reactions during membrane exposure section.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
ratio-RAMIPRIL is an angiotensin converting enzyme (ACE) inhibitor, which is used in the treatment of essential hypertension, following acute myocardial infarction in stabilized patients with clinically confirmed heart failure, and for the management of patients at increased risk of cardiovascular events.
Following oral administration, ratio-RAMIPRIL is rapidly hydrolyzed to ramiprilat, its principal active metabolite.
Angiotensin-converting enzyme catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex. Inhibition of ACE activity leads to decreased levels of angiotensin II thereby resulting in decreased vasoconstriction and decreased aldosterone secretion. The latter decrease may result in a small increase in serum potassium (see WARNINGS AND PRECAUTIONS-Hematologic, Hyperkalemia and Potassium-Sparing Diuretics). Decreased levels of angiotensin II and the accompanying lack of negative feedback on renal renin secretion result in increases in plasma renin activity.
ACE is identical to kininase II. Thus, ramipril may also block the degradation of the vasodepressor peptide bradykinin, which may contribute to its therapeutic effect.
Pharmacodynamics
Administration of ramipril to patients with mild to moderate essential hypertension results in a reduction of both supine and standing blood pressure usually with little or no orthostatic change or change in heart rate. Symptomatic postural hypotension is infrequent, although this may occur in patients who are salt-and/or volume-depleted (see WARNINGS AND PRECAUTIONS).
In single dose studies, doses of 5-20 mg of ramipril lowered blood pressure within 1-2 hours, with peak reductions achieved 3-6 hours after dosing. At recommended doses given once daily, antihypertensive effects have persisted over 24 hours.
The effectiveness of ramipril appears to be similar in the elderly (over 65 years of age) and younger adult patients given the same daily doses.
In studies comparing the same daily dose of ramipril given as a single morning dose or as a twice daily dose, blood pressure reductions at the time of morning trough blood levels were greater with the divided regimen.
While the mechanism through which ramipril lowers blood pressure appears to result primarily from suppression of the renin-angiotensin-aldosterone system, ramipril has an antihypertensive effect even in patients with low-renin hypertension.
The antihypertensive effect of ramipril and thiazide diuretics used concurrently is greater than that seen with either agent used alone.
Abrupt withdrawal of ramipril has not resulted in rapid increase in blood pressure.
Pharmacokinetics
Table 3: Summary of pharmacokinetic parameters of ramipril after single doses of 2.5 mg, 5 mg and 10 mg capsules
| Mean values ± SD and (range) n=12 (11 subjects in 5 mg capsule data) | |||
| Single Dose | Cmax [ng/mL] | tmax [h] | AUC(0-12) [ng*h/mL] |
2.5 mg capsule 5 mg capsule 10 mg capsule | 10.40 ± 6.93 (3.20-29.10) 21.54 ± 8.10 (11.00-35.20) 50.96 ± 22.24 (13.60-89.70) | 0.69±0.22 (0.50 – 1.25) 0.70±0.31 (0.50 – 1.50) 0.79±0.42 (0.25 – 1.50) | 13.23 ± 9.34 (4.30-34.30) 31.71±20.57 (11.60-70.50) 70.78±33.65 (17.30 – 128.80) |
Absorption:
Following oral administration, ramipril is rapidly absorbed with peak plasma concentrations occurring within 1 hour. The extent of absorption of ramipril is 50-60% and is not significantly altered by the presence of food in the gastrointestinal tract, although the rate of absorption is reduced.
Following a single administration of up to 5 mg of ramipril, plasma concentrations of ramipril and ramiprilat increase in a manner that is greater than proportional to dose; after a single administration of 5 mg to 20 mg of ramipril the plasma concentrations for both are dose-proportional. The non-linear pharmacokinetics observed at the lower doses of ramipril can be explained by the saturable binding of ramiprilat to ACE. At steady-state, the 24-hour AUC for ramiprilat is dose-proportional over the recommended dose range. The absolute bioavailabilities of ramipril and ramiprilat were 28% and 44% respectively when 5 mg of oral ramipril was compared to 5 mg given intravenously.
Plasma concentrations of ramiprilat decline in a triphasic manner. The initial rapid decline, which represents distribution of the drug, has a half life of 2-4 hours. Because of its potent binding to ACE and slow dissociation from the enzyme, ramiprilat shows two elimination phases. The apparent elimination phase has a half-life of 9-18 hours, and the terminal elimination
phase has a prolonged half-life of > 50 hours. After multiple daily doses of ramipril 5-10 mg, the half-life of ramiprilat concentrations was 13-17 hours, but was considerably prolonged at 2.5 mg (27-36 hours).
After once daily dosing, steady state plasma concentrations of ramiprilat are reached by the fourth dose. Steady-state concentrations of ramiprilat are higher than those seen after the first dose of ramipril especially at low doses (2.5 mg).
Distribution:
Following absorption, ramipril is rapidly hydrolyzed in the liver to its active metabolite, ramiprilat. Peak plasma concentrations of ramiprilat are reached 2-4 hours after drug intake. The serum protein binding of ramipril is about 73% and that of ramiprilat is 56%.
Metabolism:
Ramipril is almost completely metabolized to the active metabolite ramiprilat, and to the diketopiperazine ester, the diketopiperazine acid, and the glucuronides of ramipril and ramiprilat, all of which are inactive.
Excretion:
After oral administration of ramipril, about 60% of the parent drug and its metabolites is excreted in the urine, and about 40% is found in the feces. Drug recovered in the feces may represent both biliary excretion of metabolites and/or unabsorbed drug. Less than 2% of the administered dose is recovered in urine as unchanged ramipril.
Special Populations and Conditions
Geriatrics:
A single dose pharmacokinetic study conducted in a limited number of elderly patients indicated that peak ramiprilat levels and the AUC for ramiprilat are higher in older patients (see WARNINGS AND PRECAUTIONS-Special Populations, Geriatrics).
Race:
The antihypertensive effect of angiotension converting enzyme inhibitors is generally lower in black patients than in non-blacks.
Hepatic Insufficiency:
In patients with impaired liver function, plasma ramipril levels increased about 3-fold, although peak concentrations of ramiprilat in these patients were not different from those seen in patients with normal hepatic function.
Renal Insufficiency:
The urinary excretion of ramipril, ramiprilat, and their metabolites is reduced in patients with impaired renal function. In patients with creatinine clearance < 40 ml/min/1.73 m2, increases in
Cmax and AUC of ramipril and ramiprilat compared to normal subjects were observed following multiple dosing with 5 mg ramipril (see DOSAGE AND ADMINISTRATION-Recommended Dose and Dosage Adjustment, Use in renal impairment).
STORAGE AND STABILITY
Store ratio-RAMIPRIL in original container at room temperature, (15-30ºC) and not beyond the date indicated on the container.
DOSAGE FORMS, COMPOSITION AND PACKAGING
ratio-RAMIPRIL capsules 1.25 mg, 2.5 mg, 5.0 mg, 10.0 mg and 15.0 mg contain the medicinal ingredient ramipril in quantities of 1.25 mg, 2.5 mg, 5.0 mg, 10.0 mg and 15.0 mg respectively.
The nonmedicinal ingredients for all potencies of ratio-RAMIPRIL are: pre-gelatinized starch and hard gelatin capsules.
Hard gelatin capsules for all potencies of ratio-RAMIPRIL are composed of gelatin and coloring agents specific to each potency (see below).
| Potency | Cap | Body |
| 1.25 mg | Yellow iron oxide Titanium dioxide | Titanium dioxide |
| 2.5 mg | Yellow iron oxide FD & C red no. 3 Titanium dioxide | Titanium dioxide |
| 5.0 mg | FD & C blue no. 2 FD & C red no. 3 Titanium dioxide | Titanium dioxide |
| 10.0 mg | FD & C blue no. 2 FD & C red no. 3 Black iron oxide Titanium dioxide | Titanium dioxide |
| 15.0 mg | D&C Red no.28 FD&C Blue no.1 Titanium dioxide | Black iron oxide Titanium dioxide |
ratio-RAMIPRIL is available in hard gelatin capsules in the following potencies (colors indicated in parentheses):
1.25 mg Hard gelatin capsules size no. 4
(white opaque body, imprinted with “RAMIPRIL”; yellow opaque cap, imprinted with "1.25").
2.5 mg Hard gelatin capsules size no. 4
(white opaque body, imprinted with “RAMIPRIL”; orange opaque cap, imprinted with "2.5").
5.0 mg Hard gelatin capsules size no. 4
(white opaque body, imprinted with “RAMIPRIL”; red opaque cap, imprinted with "5").
10.0 mg Hard gelatin capsules size no. 4
(white opaque body, imprinted with “RAMIPRIL”; blue opaque cap, imprinted with "10").
15.0 mg Hard gelatin capsules size no. 3
(grey opaque body with imprinted “RAMIPRIL”;
power blue opaque cap imprinted with “15”)
ratio-RAMIPRIL capsules 1.25 mg are packaged in cartons of 30 (2 x 15 blister-packed) capsules and in white high-density polyethylene (HDPE) bottles of 100 capsules.
ratio-RAMIPRIL capsules 2.5 mg, 5.0 mg , 10.0 mg and 15.0 mg are packaged in cartons of 30 (2 x 15 blister-packed) capsules and in white high-density polyethylene (HDPE) bottles of 100 or 500 capsules.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ramipril
Chemical name: 2-[N-[(S)-1-ethoxycarbonyl-3-phenylpropyl]-L-alanyl]-
(1S,3S,5S)-2-azabicyclo-[3.3.0]octane-3-carboxylic acid
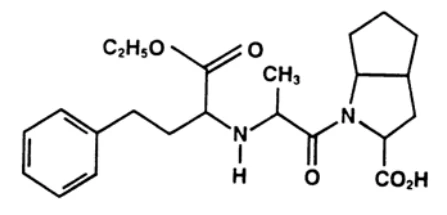
Structural formula:
Molecular formula: C23H32N2O5
Molecular mass: 416.52
Physicochemical properties: A white to off-white crystalline powder with a melting point of 105oC to 112oC. Slightly soluble in water, and freely soluble in ethanol and methanol.
CLINICAL TRIALS
Patients at increased risk of cardiovascular events:
The effects of ramipril were assessed in patients who were at high risk for cardiovascular events, but did not have left ventricular dysfunction or heart failure. Heart Outcome Prevention Evaluation (HOPE) study included 9297 patients older than 55 years of age with a history of coronary artery disease, stroke, peripheral vascular disease or diabetes mellitus plus at least one additional cardiovascular risk factor (hypertension, elevated total cholesterol levels, low high-density lipoprotein cholesterol levels, cigarette smoking, or documented microalbuminuria). Patients were excluded if they had heart failure, low ejection fraction (<0.40), were taking an angiotensin converting enzyme inhibitor or vitamin E, had uncontrolled hypertension or overt nephropathy, or had had a myocardial infarction or stroke within four weeks before the study
began. The patients were randomly assigned to receive ramipril 10 mg once daily or matching placebo for a mean of five years.
Due to the positive outcome the study was terminated prematurely by an independent monitoring board. The primary end point, the composite of death from cardiovascular causes, myocardial infarction and stroke was reached by a total of 651 ramipril treated patients (14%), as compared to 826 placebo treated patients (17.8%) (relative risk, 0.78; P<0.001). When analyzed separately, the rates of individual component of the composite primary outcome in patients treated with ramipril and placebo were as follows: death from cardiovascular causes 6.1% vs. 8.1% (RR 0.74, p<0.001), myocardial infarction 9.9% vs. 12.3% (RR 0.80, p<0.001) and stroke 3.4% vs. 4.9% of patients (RR 0.68, p<0.001), respectively.
Permanent discontinuation of treatment occurred in 28.9% of the ramipril treated patients versus 27.3% of placebo treated patients. The reasons for stopping the treatment, where the incidence was greater in the ramipril than in the placebo group, were cough (ramipril 7.3%, placebo 1.8%), hypotension/dizziness (ramipril 1.9%, placebo 1.5%) and edema (ramipril 0.4%, placebo 0.2%).
DETAILED PHARMACOLOGY
Table 4: Mechanism of Action
| Study | Species | #/group | Route | Dose | Results |
| Inhibition of Angiotensin I-induced pressor response after oral ramipril | Rat Dog | n=6 n=3 | oral oral | 0.1 0.3 1.0 mg/kg | A dose-dependent inhibition was observed, lasting more than 6 hours |
| Effect of pre-treatment with ramipril on b.p. changes induced by i.v. Angiotensin I, Angiotensin II, and sympathomimetics | Rat | n=5 or n=6 | oral | 1.0 mg/kg | Effects of Ang. I and indirect-acting sympathomimetics are inhibited, while the effects of Ang. II and direct-acting sympathomimetics are unaffected by ramipril |
| Effect of ramipril on Na-depleted (furosemide treated) dogs | Dog | n=6 | oral | 10 mg/kg | Ramipril-induced increase in plasma renin activity is enhanced by furosemide; Ramipril has no influence on heart rate |
| In vitro inhibition of ACE by ramipril | Rabbit lung | in vitro | IC50= 26±8 nmol/L |
Table 4: Mechanism of Action (Continued)
| Study | Species | #/group | Route | Dose | Results |
| Effect of ramipril and captopril on renal blood flow, renal vasculature resistance, and blood pressure | Rat | n=5 | i.a. | 0.1 mg/kg | Ramipril caused a greater increase in renal blood flow and decrease in renal vasculature resistance than a 10-fold higher dose of captopril; this without the decrease in systemic b.p. observed with captopril |
Table 5: Effects on Blood Pressure
| Hypertensive Model | Species | #/group | Route | Dose | Duration | Result |
| Spontaneously hypertensive rats | Rat | n=5 | oral | 1 mg/kg 0.01,0.1, 1,10 mg/ kg/day | acute 5 weeks | Significant decreases in b.p.(all doses); which persisted for: 2 weeks (chronic) 72 hrs. (acute) |
Kidney perinephretic hypertension (no increase in plasma renin activity) | Dog | n=5 | oral | 10 mg/kg 1 mg/ kg/day | acute 5 days | Significant decrease of systemic blood pressure |
| 2 kidney, 1 clip hypertension | Rat | n=8 | oral | 1,10 mg/kg | acute | Blood pressure was normalized |
| Release of an occluded renal pedicle | Rat | n=6 | oral | 0.1 mg/kg | acute | Hypertension was completely prevented |
Table 6: Pharmacokinetics and Bioavailability
| Study Parameter (after oral ramipril) | Results | ||
| Rat (2 mg/kg) | Dog (2 mg/kg) | Human (10 mg) | |
| GI absorption of 14C-ramipril | 56% | 43% | 56% |
| Maximal blood levels of radioactivity | 0.5 hrs | 0.5-1 hrs | 0.3 hrs |
| Plasma t½ of radioactivity | 0.6 hrs | 1.0 and 3.8 hrs (biphasic) | 0.5 and 2.9 hrs (biphasic) |
| Distribution of radioactivity | High concentration in liver, kidney and particularly lungs. Total foetus : 0.05% Breast milk: 0.25% | - | - |
Table 6: Pharmacokinetics and Bioavailability
| Study Parameter (after oral ramipril) | Results | ||
| Rat (2 mg/kg) | Dog (2 mg/kg) | Human (10 mg) | |
| Serum protein binding (concentration range of 0.01-10 µg/ml) | ramipril:- ramiprilat: 41% | ramipril: 72% ramiprilat: 47% | ramipril: 73% ramiprilat: 56% |
| Metabolism | metabolized to ramiprilat | metabolized to ramiprilat and inactive diketopiperazines | |
| Excretion of radioactivity | urine: 26% feces: 71% t½ (both): 1.6-4.8 and 23-42 h | urine: 15% t½: 9.3 h feces: 79% t½: 8 h | urine: 56% t½: 7.2 and 127 h feces: 40% t½: 11 and 110 h |
TOXICOLOGY
Acute Toxicity:
Below are summarized species-specific LD50 values for both oral and intravenous administrations of ramipril.
Table 7 - Acute Toxicity
| Routes | Species | Sex | LD50 |
| Oral | Mouse | Male | 10,933 mg/kg |
| Female | 10,048 mg/kg | ||
| Rat | Male | > 10,000 mg/kg | |
| Female | > 10,000 mg/kg | ||
| Dog | Male | > 1,000 mg/kg | |
| Intravenous | Mouse | Male | 1,194 mg/kg |
| Female | 1,158 mg/kg | ||
| Rat | Male | 688 mg/kg | |
| Female | 609 mg/kg |
The symptoms observed in mice were decreased spontaneous activity, crouching, hypothermia, dyspnea, and clonic convulsions; deaths occurred within 30 minutes after intravenous and 24 hours after oral administration. In survivors, the symptoms disappeared by 1 to 5 days after administration; necropsies revealed no abnormality in any of the surviving animals. In rats, reduced spontaneous activity was noted (oral administration), while after intravenous administration similar signs occurred as in mice; the sign of lethal toxicity was clonic convulsions (intravenous administration).
Table 8 - Chronic Toxicity
| Species | Duration | No. of animals per group | Route | Dose (mg/kg/day) | Effects |
| Mouse | 28 days 90 days | 2M, 2F 3M, 3F | Oral | 1000 | Reduced erythrocytes, hemoglobin, hematocrit, increased reticulocytes. Hyperplasia of juxtaglomerular apparatus. |
| Rat | 30 days | 10-15M, 10-15F | Oral | 2.5, 80, 2500 | At all doses: decrease in body weight, reduced liver weight, increased kidney weight. At 80 & 2500 mg/kg/d: Reduced heart weight. At 2500 mg/kg/d: Reduced erythrocytes, hematocrit and bilirubin, increased BUN. |
| Rat | 3 months | 10-15M, 10-15F | Oral | 2.5, 80, 500 | At all doses: Reduced chloride and GOT, increased phosphorus and BUN. At 80 mg/kg/d: Reduced heart, liver, prostate weight, increased kidney weight. Atrophic segments of renal tubules. Increased serum creatinine. At 500 mg/kg/d: Reduced body and heart weight, increased kidney and adrenal weight. Reduced erythrocytes, hemoglobin, hematocrit, increased bilirubin. Increased number of atrophic renal tubular segments. Moderate gastric mucosa necroses. |
| Rat | 3 months | 10M, 10F | Oral | 500, 1/3 Ringer solution for drinking | Increased number of tubular atrophies. |
Table 8 - Chronic Toxicity (Continued)
| Species | Duration | No. of animals per group | Route | Dose (mg/kg/day) | Effects |
| Rat | 6 months | 10-20M, 10-20F | Oral | 0.1, 0.25, 3.2, 40, 500 | At all doses: Serum bilirubin increased, reduced heart weight. At 40 and 500 mg/kg/d: Increased kidney weight. Reduced erythrocytes, haemoglobin, hematocrit, increased BUN. Distal tubular atrophies, fibromuscular pad formations in gastric mucosa/ muscularis not proliferative in nature. |
| Rat | 6 months | 20M, 20F | Oral | 3.2, 40, 500, 1/3 Ringer solution for drinking | All doses: Fibromuscular or solitary pad formation in gastric fundus mucosa/ muscularis. |
| Rat | 18 months | 20-25M, 20-25F | Oral | 0.25, 3.2, 40, 500 | At 3.2 to 500 mg/kg/d: Fibromuscular pads in gastric fundus mucosa, focal atrophies in renal cortex, partly with cysts. At 40 and 500 mg/kg/d: Anemia, increased BUN and serum creatinine, urinary epithelial cells. Reduced heart weight and increased kidney and adrenal weight. |
| Dog | 30 days | 2M, 2F | Oral | 3.2, 32 | No pathological findings. |
| Dog | 3 months | 3-4M, 3-4F | Oral | 3.2, 32, 320 | At 320 mg/kg/d: Anemia, increased BUN and serum creatinine, impaired erythropoiesis. Juxtaglomerular hyperplasia. |
| Dog | 6 months | 6M, 6F | Oral | 3.2, 32, 320 | At 32 mg/kg/d: Anemia, juxtaglomerular hyperplasia. At 320 mg/kg/d: Reduced body weight. Increased BUN and serum creatinine. Distal tubular atrophies with round cell infiltrations. Anemia, juxtaglomerular hyperplasia. |
Table 8 - Chronic Toxicity (Continued)
| Species | Duration | No. of animals per group | Route | Dose (mg/kg/day) | Effects |
| Dog | 12 months | 6M, 6F | Oral | 2.5, 25, 250 | At all doses: Reduced body weight. At 25 and 250 mg/kg/d: Anemia and leukopenia, impaired erythropoiesis, increased hemosiderin deposition in liver and spleen, juxtaglomerular hyperplasia. At 250 mg/kg/d: Increased BUN and serum creatinine. |
| Monkey | 6 months | 4-5M, 4-5F | Oral | 0.5, 16, 500 | At 16 and 500 mg/kg/d: Increased BUN, juxtaglomerular hyperplasia. Reduced body weight. At 500 mg/kg/d: Diarrhea, anemia, increased serum creatinine, some urinary casts, leukocytes and epithelial cells. |
| Monkey | 6 months | 5M 5F | Oral | 2, 8 | No pathological findings. |
Table 9 - Reproduction and Teratology
| Species | No. of animals per group | Dose (mg/kg/day) | Duration of dosing | Results |
Rat (Wistar) | 32M, 32F | 5, 50, 500 | M 60 days before mating F14 days before mating to end of lactation | At 50 and 500 mg/kg/d: Parents renal pelvis enlargement, off-spring light brown discoloration of kidney tissue and dilatation of renal pelvis. At 500 mg/kg/d: Parents yellow-white coloring and induration of renal marrow.Fertility normal. |
Rat (Wistar) | 20F | 10, 100, 1000 | Days 7-17 of gestation | At 1000 mg/kg/d: Reduced food consumption of mothers, reduced body weight gains of young. One young circular non-ossified area in supraoccipital bone, 1 young distortion of right scapula. No teratogenic effects. |
Rat (Wistar) | 20-30F | 0.32, 1.25, 5, 10, 100, 1000 | Day 17 of gestation to day 21 of lactation | At 100 and 1000 mg/kg/d: Decreased gestation body weight of young, enlarged to day 21 renal pelvis up to hydronephrosis with light brown coloring of renal cortex and marrow. |
Rat (Sprague-Dawley) | 20F | 100 | Day 17 of gestation to day 21 of lactation | Young: Enlarged renal pelvis and light brown coloration of kidney tissue. |
Rabbit (Himalayan) | 15F | 0.4, 1, 2.5 | Day 6 to day 18 of gestation | At 0.4 mg/kg/d: One abortion, one foetus with diaphragm hernia. At 1 mg/kg/d: One abortion, one premature delivery, two animals died, no animals gained weight. One dead foetus with possible hydrocephalus. At 2.5 mg/kg/d: Two animals died, no animals gained weight, one foetus with diaphragm hernia, one with first cervical aplasia and aplasia of one thorax vertebra and one rib pair. |
Table 9 - Reproduction and Teratology (Continued)
| Species | No. of animals per group | Dose (mg/kg/day) | Duration of dosing | Results |
Monkey (Cynomolgus) | 4-13F | 5, 50, 500 | Days 20-25 of gestation | At all doses: No sign of terato-genesis. At 5 mg/kg/d: Two abortions, seven diarrhea, two vomiting, ten weight loss. At 50 mg/kg/d: One animal died, three abortions, seven diarrhea, two vomiting, ten weight loss. At 500 mg/kg/d: Three animals died, one abortion, four weight loss, four vomiting, four diarrhea. |
Mutagenicity:
Ramipril was not mutagenic in the Ames microbial mutagen test, the HGPRT test in V79 cells, the micronucleus test in mice and the UDS test in human A549 cells.
Carcinogenicity:
There was no evidence of a carcinogenic effect when ramipril was administered for 104 weeks to NMRI mice at doses up to 1000 mg/kg/day and to Wistar rats at doses up to 500 mg/kg/day.
REFERENCES
- 1.
Benetos A, Vasmant D, Thiéry P, et al. Effects of Ramipril on Arterial Hemodynamics. J of
Cardiovascular Pharmacology 1991, 18(Suppl 2): S153-S156.
- 2.
Burris JF. The Effect of Ramipril on Ambulatory Blood Pressure: A Multicenter Trial. J of
Cardiovascular Pharmacology 1991, 18(Suppl 2): S131-S133.
- 3.
Carré A, Vasmant D, Elmalem J, et al. Tolerability of Ramipril in a Multicenter Study of
Mild-to-Moderate Hypertension in General Practice. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S141-S143.
- 4.
Hall AS, Winter C, Bogle SM, Mackintosh AF, Murray GD, Ball SG, on behalf of the AIRE
Study Investigators: The Acute Ramipril Efficacy (AIRE) study: rationale, design, organization and outcome definitions. J Cardiovasc Pharmacol 1991, 18(Suppl.2): S105-S109.
- 5. Heidbreder K, Froer K-L, Bauer B et al. Efficacy and Safety of Ramipril in Combination with Hydrochlorothiazide: Results of a Long-Term Study. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S169-S173.
- 6.
Hosie J and Meredith P. The Pharmacokinetics of Ramipril in a Group of Ten Elderly
Patients with Essential Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S125-S127.
- 7.
Lenox-Smith AJ, Street RB and Kendall FD. Comparison of Ramipril Against Atenolol in
Controlling Mild-to-Moderate Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl.2): S150-S152.
- 8. Manhem PJO, Ball SG, Morton JJ, Murray GD, Leckie BJ, Fraser R, Robertson JIS. A dose-response study of Hoe 498, a new non-sulphydryl converting enzyme inhibitor, on blood pressure, pulse rate and the renin-angiotensin-aldosterone system in normal man. Br J Clin Pharmacol 1985, 20: 27-35.
- 9.
McCarron D and The Ramipril Multicenter Study Group. 24-Hour Blood Pressure Profiles in
Hypertensive Patients Administered Ramipril or Placebo Once Daily: Magnitude and Duration of Antihypertensive Effects. Clin Cardiol 1991, 14: 737-742.
- 10.
Mills TP. Ramipril: A review of the new ACE inhibitor. J of the Arkansas Medical Society,
February 1992, 88(9): 437-440.
- 11. Reinich W, Hoffmann H, Hoffmann W. Treatment of hypertension with the new ACE-inhibitor Ramipril. (Translation) Therapiewoche Österreich 1992, 7: 112-119.
- 12.
Rosenthal J, Buehler G, Koenig W, et al. Effect of Angiotensin-Converting Enzyme
Inhibition on Human Tissue Renin. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S122-S124.
- 13.
Saalbach R, Wochnik G, Mauersberger H, et al. Antihypertensive Efficacy, Tolerance, and
Safety of Ramipril in Young vs. Old Patients: A Retrospective Study. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S134-S136.
- 14.
Schnaper HW. Dose-Response Relationship of Ramipril in Patients with Mild-to-Moderate
Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl. 2): S128-S130.
- 15. Schreiner M, Berendes B, Verho M, et al. Antihypertensive Efficacy, Tolerance, and Safety of Long-Term Treatment with Ramipril in Patients with Mild-to-Moderate Essential Hypertension. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S137-S140.
- 16.
Vasmant D, Lendresse P, Lemarie J-C, et al. Comparison of Response Rates to the
Angiotensin-Converting Enzyme Inhibitor Ramipril in Mild-to-Moderate Hypertension in a Double-Blind, Parallel-Group Study and an Open Single-Blind Study. J of Cardiovascular Pharmacology 1991, 18(Suppl 2): S144-S146.
- 17. Vierhapper H, Witte U, Waldhausl W. Unchanged pressor effect of norepinephrine in normal man following the oral administration of two angiotensin converting enzyme inhibitors, captopril and Hoe 498. J Hypertens 1986, 4: 9-11.
- 18. The Acute Ramipril Efficacy (AIRE) Study Investigators: Effect of ramipril on mortality and morbidity of survivors of acute myocardial infarction with clinical evidence of heart failure. Lancet 1993, 342: 821-828.
- 19.
The Heart Outcomes Prevention Evaluation Study Investigators: Effects of an Angiotensin-
Converting-Enzyme Inhibitor, Ramipril, on Cardiovascular Events in High-risk Patients. N Engl J Med 2000; 342:145-153.
- 20.
Product Monograph, ALTACE® (ramipril capsules), sanofi-aventis Canada Inc., Date of
Revision: December 3, 2009.
IMPORTANT: PLEASE READ
- 21.
PART III: CONSUMER INFORMATION
Pr ratio-RAMIPRIL (ramipril capsules)
This leaflet is part III of the three-part "Product Monograph" published when ratio-RAMIPRIL was approved for sale in Canada and is designed specifically for Consumers. This leaflet is a summary and will not tell you everything about ratio-RAMIPRIL. Contact your doctor or pharmacist if you have any questions about the drug.
| ABOUT THIS MEDICATION |
What the medication is used for:
For Patients with High Blood Pressure
Your doctor has prescribed ratio-RAMIPRIL, a medication that helps to control high blood pressure.
For Patients Following a Recent Heart Attack
Your doctor has prescribed ratio-RAMIPRIL to reduce the effort required by your heart to pump blood. This is to compensate for the reduced pumping power that may have resulted from your heart attack. ratio-RAMIPRIL has been shown to improve survival and reduce hospitalizations for heart failure in patients that are now clinically stable and recovering from recent heart attacks.
For the Management of Patients at Increased Risk of Cardiovascular Events
Your doctor has prescribed ratio-RAMIPRIL because:
You have coronary heart disease (such as chest pains or
angina, or have had a heart attack in the past)
- You had a stroke
You have peripheral vascular disease (poor blood
circulation)
You have diabetes and at least one of the following
physical conditions: high blood pressure, elevated total cholesterol levels, low high-density lipoprotein (HDL) levels, cigarette smoking or documented tiny amounts of albumin from your blood detected in your urine (microalbuminuria).
ratio-RAMIPRIL may lower the risk of heart attack, stroke, or death from heart disease in some patients who have a heart problem or poor blood circulation. Take your medication as instructed by your doctor.
Managing your lifestyle
Keeping your blood pressure controlled
It takes more than just medication to reduce blood pressure. Discuss the risk factors, and how they apply to your lifestyle, with
your doctor. You may have to modify some of your daily habits to keep your blood pressure down.
Exercise regularly. It will help to keep your weight down, make you feel more energetic and is a good way to deal with stress. If you are not exercising regularly, be sure to discuss a fitness plan with your doctor.
Remember, hypertension is a long-term disease without symptoms. Just because you feel fine does not mean you can stop taking your medication. If you stop, serious complications of the disease may occur. Therefore, you should continue to take ratio-RAMIPRIL regularly, as prescribed by your doctor.
The "lifestyle" part of your treatment is as important as your medication. By working as a team with your doctor, you can help reduce the risk of complications to maintain the style of life you are accustomed to.
- Alcohol: Avoid alcoholic beverages until you have discussed their use with your doctor. Alcohol consumption may alter your blood pressure and/or increase the possibility of dizziness or fainting.
- Diet: Generally, avoid fatty foods and food that is high in salt or cholesterol.
- Smoking: Avoid it completely.
What it does:
ratio-RAMIPRIL opens blood vessels to reduce blood pressure, just like the way opening a hose reduces water pressure. It is not, however, a cure.
When it should not be used:
If:
- You have had an allergic reaction to ramipril and/or any components of ratio-RAMIPRIL capsules (see what are the important nonmedicinal ingredients) or to any other medication of the same group of medicines called ACE (angiotensin converting enzyme) inhibitors (see Warnings and Precautions).
You have a history of a condition called angioedema
(dysfiguring type of temporary swelling which can be hazardous) (see Side Effects).
- You are pregnant or breast-feeding
You have narrowing of the arteries to one or both kidneys
(renal artery stenosis).
- You have hypotension (low blood pressure).
What the medicinal ingredient is:
ratio-RAMIPRIL contains ramipril.
IMPORTANT: PLEASE READ
What the nonmedicinal ingredients are:
Pre-gelatinized starch and hard gelatin capsules (which are composed of: titanium dioxide, and/or yellow iron oxide, and/or black iron oxide, and/or FD&C red no. 3, and/or D&C red no. 28 and/or FD&C blue no. 1, and/or FD&C blue no. 2).
What dosage forms it comes in:
Capsules 1.25 mg, 2.5 mg, 5.0 mg, 10.0 mg, and 15.0 mg.
WARNINGS AND PRECAUTIONS
Serious Warning and Precautions
ratio-RAMIPRIL should not be used during pregnancy. If you discover that you are pregnant while taking ratio-RAMIPRIL, stop the medication and please contact your physician as soon as possible.
BEFORE you use ratio-RAMIPRIL talk to your doctor or pharmacist if:
You are currently taking any other medications, whether on prescription or otherwise (see Interactions with this Medication)?
You should not be taking salt substitutes, potassium supplements or potassium containing medicine without the advice of your doctor. If you have to undergo any dental or other surgery, inform the dentist or physician in charge that you are taking this medicine
You suffer from any other condition?
The presence of other medical problems may affect the use of ratio-RAMIPRIL. If you have developed heart failure after a heart attack, you may have to limit your physical activities: before you begin exercising, be sure to consult with your doctor. Make sure you tell your doctor if you have any other medical problems, especially if you have diabetes, heart or blood vessel disease.
If you have liver problems or disease, you may have a different response to ratio-RAMIPRIL. Your doctor should take blood tests to measure your liver function before you start taking ratio-RAMIPRIL and occasionally throughout your treatment.
If you have kidney problems or disease, your doctor should take regular blood tests to measure your kidney function and the levels of potassium in your blood.
Raynaud's phenomenon is a condition resulting from poor circulation in the extremities (i.e., fingers and toes). It may begin or get worse.
Your doctor may order regular blood tests or blood pressure checks, to monitor your health while on ratio-RAMIPRIL especially if you take other medications, like diuretics (water pills) (See the section on Interactions with this Medication).
You are pregnant, breast-feeding or thinking of becoming pregnant?
Taking ratio-RAMIPRIL during pregnancy can cause injury and even death to your baby. This medicine should not be used during pregnancy. If you become pregnant while taking ratio-RAMIPRIL, stop the medication and report promptly to your doctor as soon as possible. It is possible that ratio-RAMIPRIL passes into breast milk. You should not breast-feed while taking ratio-RAMIPRIL.
Remember
Use this drug as directed by your doctor. All drugs can have both helpful and harmful effects. Both depend on the person and his or her condition. This leaflet alerts you to some of the times you should call your doctor. Other situations, which cannot be predicted, can arise. Nothing in this leaflet should stop you from calling your doctor or pharmacist with any questions or concerns you have about ratio-RAMIPRIL.
| INTERACTIONS WITH THIS MEDICATION |
Some drugs may have a negative effect on ratio-RAMIPRIL or ratio-RAMIPRIL may have a negative effect on other drugs. If you are currently taking any other medications, whether on prescription or otherwise, inform your doctor or pharmacist. This is especially important if you are taking diuretics (water pills) or any other medication to reduce blood pressure which may add to the blood pressure lowering effect of ratio-RAMIPRIL.
Drugs that may interact with ratio-RAMIPRIL include agents that increase potassium in the blood such as potassium supplements, salt substitutes or medicines which contain potassium. These should be used with caution.
Other drugs that may affect the efficacy of ratio-RAMIPRIL include: nitrates, ASA (aspirin), heparin, allopurinol, immunosuppressants, corticosteroids, procainamide, cytostatics and other substances that may change the normal results expected to be measured on a routine blood test.
| PROPER USE OF THIS MEDICATION |
Usual dose:
It is important to take ratio-RAMIPRIL at the same time every day as prescribed by your doctor.
High Blood Pressure: The recommended initial dosage of ratio-RAMIPRIL is 2.5 mg once daily. Your doctor will determine the appropriate dosage.
Treatment Following Heart Attack: The recommended initial dosage of ratio-RAMIPRIL is 2.5 mg given twice a day in the morning and in the evening for patients with clinical signs of heart failure (a condition in which the heart has difficulty pumping enough blood to the body's other organs). Treatment should be started under close medical supervision.
IMPORTANT: PLEASE READ
For patients taking diuretics or with impaired kidney function: The recommended initial dosage of ratio-RAMIPRIL is 1.25 mg daily.
Management of Patients at Increased Risk of Cardiovascular Events: The recommended initial dosage of ratio-RAMIPRIL is 2.5 mg once daily. Your doctor will determine the appropriate dosage.
Overdose:
In case of an overdose, contact your doctor, the nearest hospital or Regional Poison Control Centre immediately so that medical attention may be given promptly. If possible, take your ratio-RAMIPRIL package with you to show the doctor.
Missed Dose:
If you forgot to take your ratio-RAMIPRIL capsule, take it as soon as possible. However, if it is almost time for your next dose, skip the missed dose and go back to your regular dosing schedule. Do not double dose.
| SIDE EFFECTS AND WHAT TO DO ABOUT THEM |
Along with its intended action, any medication, including ratio-RAMIPRIL, may cause side effects. After you have started taking ratio-RAMIPRIL, it is important that you tell your doctor at once about any unexplained symptom you might experience. Examples of this are unexplained fever, rash, itching, any sign of infection, viral-like symptoms, flu-like symptoms, coughing, sore throat, abdominal pain, decreased appetite or loss of appetite, sad mood, jaundice, dizziness, fatigue, muscle pain, nausea/vomiting, headache or flushing. These side effects may disappear once your system becomes used to the medication. If they persist, discuss this with your doctor. Your medication might have to be reduced or changed.
Dizziness or lightheadedness may occur after the first dose of this medicine. Make sure you know how you react to this medicine before you drive, operate machinery, or do anything requiring you to be alert. If fainting occurs after using ratio-RAMIPRIL, discontinue use and consult your doctor.
If you are suffering from excessive sweating, vomiting or diarrhea, this may cause you to lose too much water and lead to problems with low blood pressure. See your doctor.
Other side effects may include: difficulty in maintaining your balance while standing, nasal or sinus congestion, swollen lymph nodes, bronchitis, loss of hair, muscle cramps, impotence/reduced libido, difficulty with sleep, restlessness, depressed mood, inflammation of the eye (pink eye) and taste modifications or loss of taste, vision or hearing modifications, attention disturbances, skin inflammation or red skin, burning sensation, inflammation of the mouth or tongue, aggravated asthma, breast enlargement in males.
SERIOUS SIDE EFFECTS, HOW OFTEN THEY HAPPEN AND WHAT TO DO ABOUT THEM
| Symptom/Effect | Talk with your doctor or pharmacist | Stop taking ratio- RAMIPRIL and call your doctor or pharmacist | ||
| Only if severe | In all Cases | |||
| Rare: | Low blood pressure | √ | ||
| Swelling | √ | |||
| Heart Attack | √ | |||
Cerebro- vascular accident/stroke | √ | |||
| Syncope (or fainting) | √ | √ | ||
Angioedema: swelling of the face, arms and legs, eyes, lips, tongue or difficulty swallowing or breathing | √ | √ | ||
| Unexplained fever, rash or itching | √ | √ | ||
Intestinal Angioedema: abdominal pain (with or without nausea or vomiting) | √ | √ | ||
This is not a complete list of side effects. For any unexpected effects while taking ratio-RAMIPRIL, contact your doctor or pharmacist.
| HOW TO STORE IT |
Store in original container at room temperature, between 15-30ºC and not beyond the expiry date.
Keep this medication out of the reach of children.
IMPORTANT: PLEASE READ
REPORTING SUSPECTED SIDE EFFECTS
To monitor drug safety, Health Canada through the Canada Vigilance Program collects information on serious and unexpected side effects of drugs. If you suspect you have had a serious or unexpected reaction to this drug you may notify Canada Vigilance:
By toll-free telephone: 866-234-2345
By toll-free fax: 866-678-6789
On-line: www.healthcanada.gc.ca/medeffect
By email: CanadaVigilance@hc-sc.gc.ca
By regular mail:
Canada Vigilance National Office
Marketed Health Products Safety and
Effectiveness Information Bureau
Marketed Health Products Directorate
Health Products and Food Branch
Health Canada
Tunney’s Pasture, AL 0701C
Ottawa ON K1A 0K9
NOTE: Should you require information related to the management of the side effects, please contact your health care provider before notifying Canada Vigilance. The Canada Vigilance Program does not provide medical advice.
| MORE INFORMATION |
This document plus the full product monograph, prepared for health professionals can be obtained by contacting ratiopharm inc., at: 1-800-337-2584.
Date of Revision: February 19, 2010