


Product Monograph - Rebyota
1 Indications
REBYOTA (fecal microbiota, live) is indicated for the prevention of:
- recurrence of Clostridioides difficile infection (CDI) in adults following antibiotic treatment for recurrent CDI.
- REBYOTA is not indicated for the treatment of CDI.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Of the 978 adults who received REBYOTA, 48.8% were 65 years of age and over (n=477), and 25.7% were 75 years of age and over (n=251). Data from clinical studies of REBYOTA are not sufficient to determine if adults 65 years of age and older respond differently than younger adults.
2 Contraindications
- REBYOTA is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition And Packaging.
4 Dosage And Administration
4.2 Recommended Dose and Dosage Adjustment
- Administer one dose of REBYOTA from 24 to 72 hours after the last dose of antibiotics for CDI. Do not administer during antibiotic treatment for CDI.
- The recommended dose of REBYOTA is one single dose of 150 mL microbiota suspension by rectal administration.
- Additional REBYOTA treatment may be administered in the event of CDI recurrence.
- Health Canada has not authorized an indication for pediatric use.
4.4 Administration
Prior to use, thaw REBYOTA completely by placing the carton in a refrigerator, 2°C to 8°C (36°F to 46°F), for approximately 24 hours. REBYOTA carton may be stored in the refrigerator at 2°C to 8°C (36°F to 46°F) and used within 5 days, including thawing time.
DO NOT thaw using a heat source such as microwave or hot water.
Condensation is normal after thawing.
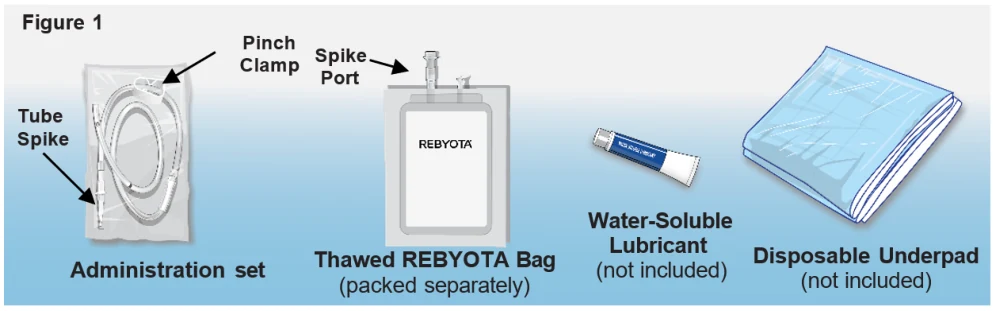
Remove the thawed REBYOTA carton from the refrigerator. Remove the bag containing thawed REBYOTA from the outer carton and the inner carton insert. DO NOT remove the bag containing thawed REBYOTA from the sealed outer bag. Locate an Administration Set (supplied), water-soluble lubricant (not included) and a disposable underpad (not included) (See Figure 1).
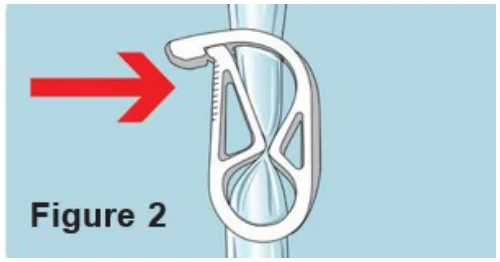
- 1. Open the administration set and close the pinch clamp by pushing the clamp until it is fully closed (See Figure 2).
- 2. Remove the tab from the spike port of the bag containing thawed REBYOTA and remove the cap from the administration tube spike. Insert the administration tube spike through the spike port of the bag containing thawed REBYOTA (See Figure 3).
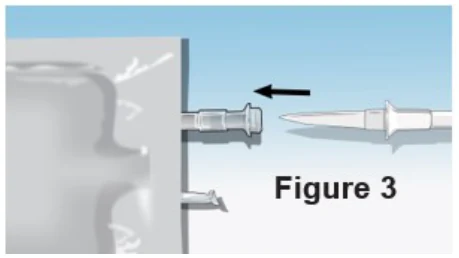
DO NOT remove air from the administration tube prior to insertion to avoid loss of REBYOTA.
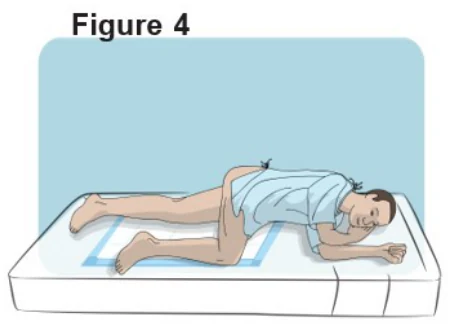
- 3. Prepare the patient for administration by requesting they empty their bladder and bowel, if possible. Place the patient in the left-side position with a disposable underpad beneath the patient (See Figure 4).
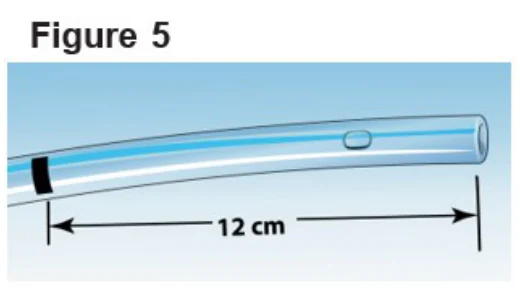
- 4. Apply water-soluble lubricant to the administration tube tip. Gently insert the administration tube tip into the rectum about 12 cm (5 inches) in a direction pointed slightly toward the navel (umbilicus) (See Figure 5).
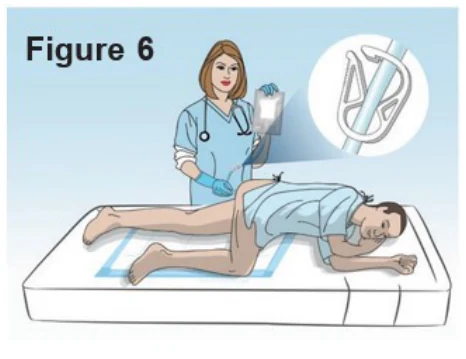
- 5. Hold the administration tube in place with one hand for the entire procedure to maintain the tube position in the rectum. With the other hand, open the pinch clamp on the administration tube, and then gradually raise the bag to allow delivery of REBYOTA via gravity flow (See Figure 6).
DO NOT allow the administration tube to sag or loop as this will prevent the entire dose from being delivered.
DO NOT squeeze the bag to deliver REBYOTA as this could be uncomfortable for the patient.
DO NOT hang the bag from an IV stand.
- 6. When the entire dose has been delivered, close the pinch clamp and then slowly withdraw from the tube. Take care to prevent any residual REBYOTA remaining in the rube from leaking out.
NOTE: Some REBYOTA will remain in the tube after administration.
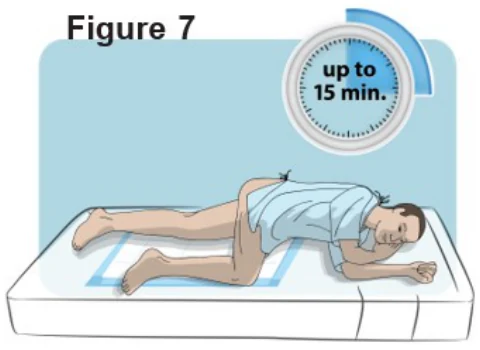
- 7. Keep the patient in the left-side position for up to 15 minutes to minimize any cramping that may occur (see Figure 7). There are no restrictions on the patient’s use of the restroom.
Dispose of all components in medical waste.
Inform patients to notify their physician if persistent diarrhea, defined as 3 or more loose bowel movements within a 24-hour period for 2 consecutive days, returns following REBYOTA administration. Inform patients that they should complete their antibiotic treatment as directed before REBYOTA is administered. REBYOTA does not replace their antibiotic treatment for their C. difficile infection. Patients should not take any oral antibiotic therapy for up to 8 weeks after administration of REBYOTA unless directed by their physician.
4.5 Missed Dose
Not applicable.
5 Overdose
There is no clinical experience with overdosage of REBYOTA. Up to two doses have been administered within 7 days in a REBYOTA clinical program.
6 Dosage Forms, Strengths, Composition And Packaging
REBYOTA is a pre-packaged single-dose 150 mL microbiota suspension of 1×10⁸ to 5×10¹⁰ colony forming units (CFU/mL), including Bacteroides.
REBYOTA is supplied in a carton that contains one labeled single-dose REBYOTA suspension bag.
A REBYOTA Administration Set is packaged separately to facilitate rectal administration. To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Rectal | Suspension (enema) / 150 mL of 1×10⁸ to 5×10¹⁰ colony forming units (CFU/mL), including Bacteroides | Excipient Solution of PEG/Saline Less than 6 grams of Polyethylene Glycol 3350 (PEG) 0.9 % Sodium Chloride Irrigation (Saline) |
7 Warnings And Precautions
General
The fecal microbiota, live, are suspended in a solution of polyethylene glycol 3350 and 0.9% sodium chloride irrigation. PEG 3350 is known to be associated with localized GI irritation. Saline irrigation may be potentially harmful in sodium-restricted individuals, such as patients with congestive heart failure and chronic renal failure.
Hypersensitivity reactions
Do not use in patients with a previous hypersensitivity to REBYOTA or any of the product components. Appropriate medical treatment must be immediately available in the event an acute anaphylactic reaction occurs following administration of REBYOTA.
Potential presence of food allergens
REBYOTA is manufactured from human fecal matter and may contain food allergens. The potential for REBYOTA to cause adverse reactions due to food allergens is unknown.
Transmissible Infectious agents
Because REBYOTA is manufactured from human fecal matter it may carry a risk of transmitting infectious agents. Any infection suspected by a physician possible to have been transmitted by this product should be reported by the physician or other healthcare provider to Ferring Pharmaceuticals Inc.
7.1 Special Populations
7.1.1 Pregnancy
Adequate and well-controlled studies with REBYOTA have not been conducted in pregnant or breastfeeding women. REBYOTA is not absorbed systemically following rectal administration, and maternal use is not expected to result in fetal exposure to the drug.
7.1.2 Breastfeeding
Adequate and well-controlled studies with REBYOTA have not been conducted in pregnant or breastfeeding women. REBYOTA is not absorbed systemically by the mother following rectal administration, and breastfeeding is not expected to result in exposure of the child to REBYOTA.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for REBYOTA and any potential adverse effects on the breastfed child from REBYOTA or from the underlying maternal condition.
7.1.3 Pediatrics
Safety and effectiveness of REBYOTA in individuals younger than 18 years of age have not been established.
7.1.4 Geriatrics
Of the 978 patients treated with REBYOTA, 48.8% were 65 years of age and over, and 25.7% were 75 years of age and over. No overall differences in safety and efficacy were observed between these subjects and younger subjects.
8 Adverse Reactions
8.1 Adverse Reaction Overview
The most common adverse reactions following treatment with REBYOTA (reported by ≥3% of all subjects and greater than placebo) were abdominal pain (8.9%), diarrhea (7.2%), abdominal distension (3.9%), flatulence (3.3%), and nausea (3.3%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety of REBYOTA was evaluated in 2 randomized, double-blind clinical studies (Study 1: NCT03244644 and Study 2: NCT02299570) and 3 open-label clinical studies (NCT01925417, NCT02589847, NCT03931941) conducted in the United States and Canada. A total of 978 adults 18 years of age and older with a history of 1 or more recurrences of Clostridioides difficile (CDI) infection and whose symptoms were controlled 24 – 72 hours post-antibiotic treatment were enrolled and received 1 or more doses of REBYOTA; 595 of whom received a single dose of REBYOTA. In the 2 randomized, double-blind clinical studies, 131 adults were originally randomized to receive placebo and 48 crossed over to receive an open-label dose of REBYOTA after additional CDI recurrence. Overall, across the 5 studies, the median age of participants was 64 years and 67.2 % were female. The racial and ethnic distribution was as follows: 93.8% were white, and 2.4% were of Hispanic or Latino ethnicity. No meaningful differences in demographic characteristics occurred across the treatment groups. Study 1 and Study 2 excluded individuals with celiac disease, Inflammatory Bowel Disease, Irritable Bowel
Syndrome, and chronic diarrhea. Individuals with these conditions were not excluded from one of the open-label studies (NCT03931941), and individuals with food allergies were not excluded from any of the 5 clinical studies.
Across the 5 clinical studies, participants recorded solicited adverse events in a diary for the first 7 days after each dose of REBYOTA or placebo. Participants were monitored for all other adverse events by queries during scheduled visits, with duration of follow-up ranging from 6 to 24 months after the last dose. In Study 1, a multi- center, double-blind randomized (2:1), placebo-controlled trial conducted in the United States and Canada, 180 adults 18 years of age and older received a single dose of REBYOTA and 87 received placebo. Participants with a recurrence of CDI (rCDI) during the first 8 weeks after receipt of REBYOTA or placebo were censored from analysis at the time of rCDI. During the first two weeks following a dose of REBYOTA or placebo, 34 participants (18.9%) and 24 participants (27.6%) respectively, were censored. Overall, during the 8 week follow up period, 47 REBYOTA recipients (26.1%) and 30 placebo recipients (34.5%) were censored from analysis. In an analysis of solicited and unsolicited adverse events reported in Study 1, the most common adverse reactions (defined as adverse events assessed as definitely, possibly, or probably related to Investigational Product by the investigator) reported by ≥3% of REBYOTA recipients, and at a rate greater than that reported by placebo recipients, were abdominal pain, (8.9%), diarrhea (7.2%), abdominal distention (3.9%), flatulence (3.3%), and nausea (3.3%).
Table 2 - Adverse Reactions in the Safety Population with an Incidence of ≥3% Reported in REBYOTA-Treated Adults in the Blinded Portion of the Phase 3 Study 1.
System Organ Class / Preferred Term* | REBYOTA n = 180 (%) | Placebo n = 87 (%) |
| n (%) | n (%) | |
Gastrointestinal Abdominal Pain Diarrhea | 16 (8.9) 13 (7.2) | 6 (6.9) 3 (3.4) |
| Abdominal distension | 7 (3.9) | 2 (2.3) |
| Flatulence | 6 (3.3) | 0 |
| Nausea | 6 (3.3) | 1 (1.1) |
*Adverse reactions occurred within 8 weeks after receipt of REBYOTA or placebo.
Most adverse reactions occurred during the first 2 weeks after treatment. After this, the proportion of patients with adverse reactions declined in subsequent 2-week intervals. Beyond 2 weeks after treatment only a few single adverse reactions were reported. Most adverse drug reactions were mild to moderate in severity. No life threatening adverse reaction was reported.
Serious Adverse Reactions
In a pooled analysis of the 5 clinical studies, 10.1% (60/595) of REBYOTA recipients (1 dose only) and 7.2% (6/83) of placebo recipients reported a serious adverse event within 6 months post last dose of investigational product. None of these events were considered related to the investigational product.
8.3 Less Common Clinical Trial Adverse Reactions
Cardiac disorders: Bradycardia (0.2%)
Gastrointestinal Disorders: Constipation (2.6%), Anorectal discomfort (1.3%), Proctalgia (0.7%), Rectal haemorrhage (0.5%), Abdominal discomfort (0.4%), Dyspepsia (0.4%), Haematochezia 0.3%), Vomiting (0.3%), Haemorrhoids (0.2%), Irritable bowel syndrome (0.2%)
General disorders and administration site conditions: Pyrexia (1.5%), Chills (1.4%), Fatigue (0.5%), Malaise (0.3%)
Infections and infestations: Clostridium difficile infection (0.4%), Gastroenteritis viral (0.2%)
Investigations: Blood pressure diastolic decreased 0.6%), Blood pressure increased (0.2%)
Metabolism and nutrition disorders: Decreased appetite (0.2%)
Nervous system disorders: Dizziness (0.3%), Headache (0.3%)
Skin and subcutaneous tissue disorders: Hyperhidrosis (0.2%), Rash (0.2%)
Vascular disorders: Hypotension (0.8%)
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Not applicable
Post-Market Findings
Not applicable
8.5 Post-Market Adverse Reactions
Majority of the adverse drug reactions from post-marketing sources were in the system organ class ‘gastrointestinal disorders’, covering 4 events of diarrhea, 1 event of abdominal pain, 1 event of discoloured feces, and 1 event of nausea, in a total of 4 patients.
9 Drug Interactions
9.2 Drug Interactions Overview
Not applicable.
9.3 Drug-Behavioural Interactions
The interaction of REBYOTA with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4 Drug-Drug Interactions
Since REBYOTA is not absorbed into the body, no metabolic drug-drug interactions are expected.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
The exact mechanism of action of REBYOTA has not been established.
10.2 Pharmacodynamics
In Study 1 (Trial 2017-01), treatment success was associated with increased Clostridia- and Bacteroidia-class bacteria and decreased Gammaproteobacteria- and Bacilli-class bacteria. Fecal sequencing analysis showed that the microbiome composition of subjects with treatment success was significantly shifted by 1 week after study treatment to more closely resemble the REBYOTA composition, and this shift continued through at least 6 months post-treatment. These changes were significantly more extensive among patients responding to REBYOTA treatment compared to placebo-treated responders.
10.3 Pharmacokinetics
REBYOTA is comprised of microbiota and is not systemically absorbed. Consequently, no pharmacokinetic studies have been conducted.
11 Storage, Stability And Disposal
REBYOTA contains live microorganisms. It is important to follow the storage requirements.
The shelf-life of REBYOTA is thirty-six (36) months in an ultracold freezer from date of manufacture.
Upon Receipt:
REBYOTA can be stored either in an ultracold freezer at -60° to -90°C (- 76° to -130°F) until its expiration or stored in the refrigerator at 2° to 8°C (36° to 46°F) for up to 5 days (including the 24 hour thawing period).
Before Using:
Prior to use, thaw REBYOTA completely by placing carton in a refrigerator at 2˚C to 8˚C (36˚F to 46˚F) for approximately 24 hours.
DO NOT thaw at room temperature or using a heat source such as a microwave or hot water.
DO NOT refreeze once thawed.
For storage condition of the REBYOTA Administrative Set follow the instruction for use provided with the REBYOTA Administration Set.
Dispose of all components in medical waste.
12 Special Handling Instructions
REBYOTA must be administered only when completely thawed.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Fecal microbiota, live
Chemical name: NA
Molecular formula and molecular mass: NA
Structure: NA
Physicochemical properties: NA
Pharmaceutical standard: NA
Product Characteristics:
REBYOTA is an opaque fecal microbiota, live, suspension for rectal administration. REBYOTA is manufactured from human fecal matter sourced from individual qualified donors. The human fecal matter is tested for a panel of transmissible pathogens. Donors do not have dietary restrictions with respect to potential food allergens. The fecal microbiota, live, suspension is the filtrate generated by processing the fecal matter in a predefined ratio with a solution of polyethylene glycol (PEG) 3350 and saline. Each 150 mL dose of REBYOTA contains between 1x10⁸ and 5x10¹⁰ colony forming units (CFU) per mL of fecal microbes including >1x10⁵ CFU/mL of Bacteroides, and contains less than 6 grams of PEG3350 in saline. In order to ensure consistency and quality, the suspension is tested and processed under current Good Manufacturing Practice (GMP) to provide a stable, cryopreserved medicinal product.
14 Clinical Trials
14.1 Clinical Trials by Indication
Clostriodioides difficile infection (CDI)
Table 3 - Summary of patient demographics for main clinical trials in Clostriodioides difficile infection (CDI)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| Study 1 (2017-01 / NCT 0324464 4) | Prospective, randomised, multicentre, double-blind, placebo-controlled | FE 999322 and Placebo; one rectal enema | 262 (FE 999322 N=180, Placebo N=85 | 60.1 (19-93) | Female n=181 (69%) Male n=81 (31%) |
| Study 2 (2014-01/ NCT0229 9570) | Prospective, randomised, multicentre, double-blind, placebo-controlled | FE 999322 and Placebo; 2 rectal enemas 7 ± 2 days apart (Group A: 2 × FE 999322, Group B: 2 × Placebo, Group C: 1 × FE 999322 and 1 × Placebo) | 128 (Group A N=42, Group B N=44, Group C N=42) | 61.1 (18-92) | Female n= 79 (61.7%) Male n=49 (38.3%) |
The efficacy of REBYOTA was evaluated using a Bayesian analysis of data from a randomized, double- blind, placebo-controlled, multicenter Phase 3 study (Study 1), which formally integrated treatment success rates from a placebo-controlled Phase 2 study (NCT02299570; referred to as Study 2). Enrolled adults in both studies were 18 years of age or older and had a confirmed diagnosis of recurrent CDI (one or more episodes in Study 1; two or more episodes in Study 2) which was defined as diarrhea (passage of 3 or more loose bowel movements within a 24-hour period for 2 consecutive days) and a positive stool test for C. difficile toxin or toxigenic C. difficile, or had at least two episodes of severe CDI resulting in hospitalization within the last year. Enrolled adults were required to have completed at least 10 consecutive days of antibiotic therapy and have their CDI under control (<3 unformed/loose, i.e., Bristol Stool Scale type 6-7, stools/day for 2 consecutive days). A minimum of 24 hours to a maximum of 72 hours (Study 1) antibiotic washout period was required prior to administration of the assigned study treatment. In Study 1, enrolled adults were randomized 2:1 to a single dose of REBYOTA or placebo respectively. In Study 2, randomization was 1:1:1 to receive two doses of REBYOTA, two doses of placebo, or one dose of REBYOTA and one dose of placebo, administered 7±2 days apart. Only data from the REBYOTA one-dose group and the placebo group from Study 2 were integrated with the efficacy data in Study 1 through a Bayesian hierarchical modeling approach
In the integrated efficacy analysis set, the demographic profile and baseline recurrent CDI characteristics of treated adults were similar in the REBYOTA and placebo groups. In Study 1, a total of 262 adults were randomized and treated, of which 177 adults received REBYOTA and 85 received placebo. Adults had a mean age of 60.1 years with 45.4% of adults 65 years of age or older, were mainly white (92.0%) and female (69.1%). In this study, 32.8% of subjects had a history of one previous CDI recurrence episode and the remaining subjects had a history of 2 or more previous CDI recurrence episodes. In Study 1, 87.4% of adults had received vancomycin alone prior to treatment.
In Study 2, 39 adults received one dose of REBYOTA and one dose of placebo and 43 adults received two doses of placebo. Adults in these two groups had a mean age of 59.8 years with 42.7% of adults 65 years of age or older, were mainly white (97.6%) and female (63.4%). In this study, 89.0% of adults had received vancomycin prior to treatment.
Treatment success was defined as the absence of CDI diarrhea within 8 weeks of blinded treatment. CDI diarrhea was defined as the passage of ≥ 3 unformed/loose stools in ≤ 24 hours for at least 2 consecutive days and a positive stool test for the presence of C difficile toxin at the time of the diarrhea.
Based on the Bayesian analysis, which integrates treatment success rate from Study 2, the estimated rate of treatment success was significantly higher in the REBYOTA group (70.6%) than in the Placebo group (57.5%) through 8 weeks after completing blinded treatment, resulting in a higher treatment success rate by 13.1% (95% Credible Interval: 2.3, 24.0) in the REBYOTA group compared to the placebo group. The posterior probability that REBYOTA is superior to Placebo was 99.1% (Table 4).
Table 4 – Efficacy Results: Treatment Success at 8 weeks Post-Treatment (mITT Population*)
CrI=credible interval *mITT includes all randomized subjects excluding: 1) those who withdrew prior to treatment; 2) those in whom treatment was attempted but not completed; 3) those who discontinued from the study prior to evaluation of treatment outcome for the primary endpoint if the reason for exit was not related to CDI symptoms.
#Pre-defined threshold was 0.975
Study 1 also evaluated sustained clinical response which was defined as treatment success at 8 weeks and no CDI event through 6 months after the last dose during the blinded period. The difference in sustained clinical response rates (9.1%; 95% CI: -3.6%, 21.7%) was not statistically significant between the REBYOTA (65.5%) and the placebo groups (56.5%).
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
No animal studies have been performed to evaluate carcinogenic or mutagenic potential or whether REBYOTA affects fertility in males or females.
| Parameter | REBYOTA Mean (95% CrI) | Placebo Mean (95% CrI) | Treatment Effect (REBYOTA – Placebo) Mean (95% CrI) |
| Model-Estimated Treatment Success (%) | 70.6 (64.1, 76.8) | 57.5 (48.1, 67.1) | 13.1 (2.3, 24.0) |
| Posterior Probability of Superiority | - | - | 0.991# |