


Product Monograph - Regular Ibuprofen
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | tablet / 200mg, 400 mg caplet / 200 mg | none For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN are indicated for fast and effective relief of:
- headache pain (including mild to moderate migraine and tension headache)
- menstrual pain
- toothache (dental pain)
pain from inflammation associated with conditions including:
- arthritis
- physical or athletic overexertion, (e.g. sprains or strains)
- minor aches and pains in muscles, bones and joints
- backache
- the aches and pain due to the common cold and flu
- reduction of fever
For patients with an increased risk of developing CV and/or GI adverse events, other management strategies that do NOT include the use of NSAIDs should be considered first. (See Contraindications and Warnings and Precautions)
Use of REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN should be limited to the lowest effective dose for the shortest possible duration of treatment in order to minimize the potential risk for cardiovascular or gastrointestinal adverse events. (See Contraindications and Warnings and Precautions)
REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN as a NSAID, does NOT treat clinical disease or prevent its progression. REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN as a NSAID, only relieves symptoms and decreases inflammation for as long as the patient continues to take it.
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggest that use in the geriatric population is associated with differences in safety or effectiveness and a brief discussion can be found in the appropriate sections (e.g., Warnings and Precautions).
Pediatrics (<12 years of age): Safety and efficacy have not been established in the pediatric population.
CONTRAINDICATIONS
The following are contraindications to the use of REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN:
- REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN are contraindicated in the peri-operative setting of coronary artery bypass graft surgery (CABG). Although ibuprofen has NOT been studied in this patient population, a selective COX-2 inhibitor NSAID studied in such a setting has led to an increased incidence of cardiovascular / thromboembolic events, deep surgical infections and sternal wound complications.
- Patients who are hypersensitive to ibuprofen, other non-steroidal anti-inflammatory drugs (NSAIDs), or to any ingredient in the formulation. For a complete listing of ingredients, see the Dosage Forms, Composition and Packaging section of the product monograph. The potential for cross-reactivity between different NSAIDs must be kept in mind.
Ibuprofen should not be used in patients with the complete or partial syndrome of acetylsalicylic acid (ASA) intolerance (rhinosinusitis,
urticaria/angioedema, nasal polyps, asthma) in whom asthma, anaphylaxis, urticaria/angioedema, rhinitis or other allergic manifestations are precipitated by ASA or other nonsteroidal anti-inflammatory agents. Fatal anaphylactoid reactions have occurred in such individuals. As well, individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse effects.
Active gastric or duodenal ulcer, a history of recurrent ulceration,
gastrointestinal bleeding, or active inflammatory disease of the gastrointestinal system.
- Significant hepatic impairment or active liver disease.
- Severely impaired or deteriorating renal function (creatinine clearance <30 ml/min).
- Ibuprofen should not be used in the presence of known hyperkalemia (also see Warnings and Precautions – Renal section).
- Ibuprofen is contraindicated in patients with systemic lupus erythematosus as an anaphylaxis-like reaction with fever may occur, particularly when ibuprofen has been administered previously.
- Ibuprofen should not be used during pregnancy.
- Ibuprofen is contraindicated in women who are breastfeeding, because of the potential for serious adverse reactions in nursing infants
- Ibuprofen should not be used in case of severe uncontrolled heart failure.
- Ibuprofen is contraindicated in patients with cerebrovascular bleeding or other bleeding disorders
- Ibuprofen is contraindicated in patients with inflammatory bowel disease
- Children with kidney disease and/or suffered significant fluid loss.
WARNINGS AND PRECAUTIONS
- Patients with heart disease and high blood pressure should not take this drug unless directed by a physician
- Caution in patients with heart failure, hypertension or other conditions predisposing to fluid retention.
- Caution in patients prone to gastrointestinal tract irritation, particularly those with a history of peptic ulcer, diverticulosis or other inflammatory disease of the gastrointestinal tract such as ulcerative colitis and Crohn’s disease.
- The elderly and patients with impaired renal function, heart failure, liver dysfunction, and those taking diuretics are at increased risk of renal toxicity.
- If persistent urinary symptoms (bladder pain, dysuria, urinary frequency), hematuria and cystitis occur, the drug should be stopped immediately.
- Ibuprofen use during nursing should be avoided
General
Frail or debilitated patients may tolerate side effects less well and therefore special care should be taken in treating this population. To minimize the potential risk for an adverse event, the lowest effective dose should be used for the shortest possible duration. As with other NSAIDs, caution should be used in the treatment of elderly patients who are more likely to be suffering from impaired renal, hepatic or cardiac function. For high risk patients, alternate therapies that do not involve NSAIDs should be considered.
REGULAR IBUPROFEN AND EXTRA STRENGTH IBUPROFEN are is NOT recommended for use with other NSAIDs, with the exception of low-dose ASA for cardiovascular prophylaxis, because of the absence of any evidence demonstrating synergistic benefits and the potential for additive adverse reactions. (See Drug Interactions - Drug/Drug Interactions - Acetylsalicylic acid (ASA) or other NSAIDs)
Several medical conditions that can predispose patients to the adverse effects of non-steroidal anti-inflammatory drugs in general may be applicable to ibuprofen.
Patients with any serious medical condition should consult a physician before using ibuprofen as an analgesic or antipyretic (1).
In common with other anti-inflammatory drugs, ibuprofen may suppress fever.
Carcinogenesis and Mutagenesis
Please see Toxicology for animal data.
Cardiovascular
REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN are a non-steroidal anti-inflammatory drug (NSAID). Use of some NSAIDs is associated with an increased incidence of cardiovascular adverse events (such as myocardial infarction, stroke or thrombotic events) which can be fatal. The risk may increase with duration of use. Patients with cardiovascular disease or risk factors for cardiovascular disease may be at greater risk.
Caution should be exercised in prescribing REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN to patients with risk factors for cardiovascular disease, cerebrovascular disease or renal disease, such as any of the following:
- Hypertension
- Dyslipidemia / Hyperlipidemia
- Diabetes Mellitus
- Congestive Heart Failure (NYHA I)
- Coronary Artery Disease (Atherosclerosis)
- Peripheral Arterial Disease
- Smoking
- Creatinine Clearance < 60 mL/min or 1 mL/sec
Some patients with pre-existing hypertension may develop worsening of blood pressure control when placed on an NSAID and regular monitoring of blood pressure should be performed under such circumstances. NSAIDs may exacerbate congestive heart failure.
Use of NSAIDs, such as REGULAR IBUPROFEN and EXTRA STRENGTH IBUPROFEN, can induce fluid retention and edema, and may exacerbate congestive heart failure, through a renally-mediated mechanism (See Warnings and Precautions - Renal).
For patients with a high risk of developing an adverse CV event, other management strategies that do NOT include the use of NSAIDs should be considered first. To minimize the potential risk for an adverse CV event, the lowest effective dose should be used for the shortest possible duration.
Patients who are taking low-dose ASA as cardio protective therapy should consult with a health professional prior to taking ibuprofen (see also Drug Interactions - Acetylsalicylic Acid).
Gastrointestinal
Serious GI toxicity, such as ulceration, perforation, obstruction and gastrointestinal bleeding, sometimes severe and occasionally fatal, can occur at any time, with or without symptoms in patients treated with nonsteroidal anti-inflammatory drugs (NSAIDs) including ibuprofen.
GI symptoms, such as dyspepsia, are common, usually developing early in therapy. Health providers should remain alert for ulceration and bleeding in patients treated with non-steroidal anti-inflammatory drugs, even in the absence of previous GI tract symptoms.
In patients observed in clinical trials of such agents, symptomatic upper GI ulcers, gross bleeding, or perforation occur in approximately 1% of patients treated for 3-6 months and in about 2-4% of patients treated for one year. The risk continues beyond one year. The incidence of these complications is related to dose, past history of known ulcer disease, and advanced age (see Special Populations). Studies have shown that the use of oral corticosteroids increases the risk of upper gastrointestinal complications associated with NSAIDs (2,3,4,5,6)
Ibuprofen should be given under close medical supervision to patients with a history of ulcer of the upper gastrointestinal tract or inflammatory disease of the gastrointestinal tract such as ulcerative colitis and Crohn's disease. In these cases the health provider must weigh the benefits of treatment against the possible hazards.
Health providers should inform patients about the signs and symptoms of serious GI toxicity and instruct them to contact a health provider immediately if they experience persistent dyspepsia or other symptoms or signs suggestive of gastrointestinal ulceration or bleeding.
Because serious GI tract ulceration and bleeding can occur without warning symptoms, health providers should follow chronically treated patients and watch for the signs and symptoms of ulceration and bleeding and should inform the patients of the importance of this follow-up.
If ulceration is suspected or confirmed, or if GI bleeding occurs ibuprofen should be discontinued immediately, appropriate treatment instituted and the patient monitored closely.
No studies, to date, have identified any group of patients not at risk of developing ulceration and bleeding. The major risk factors are a prior history of serious GI events and increasing age. Possible risk factors include Helicobacter pylori infection, excess
alcohol intake, smoking, and concomitant oral steroids, anti-coagulants, anti-platelet agents (including ASA), or selective serotonin reuptake inhibitors (SSRIs).
The administration of ibuprofen with food or milk is recommended since occasional and mild heartburn, upset stomach or stomach pain may occur with its use. Patients should be advised to seek the consultation of a physician if gastrointestinal side effects occur consistently, persist, or appear to worsen (1).
Genitourinary
Some NSAIDs are associated with persistent urinary symptoms (bladder pain, dysuria, urinary frequency), hematuria or cystitis. The onset of these symptoms may occur at any time after the initiation of therapy with an NSAID. Should urinary symptoms occur, in the absence of an alternate explanation, treatment with ibuprofen should be stopped to ascertain if symptoms disappear. This should be done before urological investigations or treatments are considered.
Hematologic
Ibuprofen, like other non-steroidal anti-inflammatory agents, can inhibit platelet aggregation but the effect is quantitatively less than that seen with acetylsalicylic acid. Ibuprofen has been shown to prolong bleeding time (but within the normal range) in normal subjects. Because this prolonged bleeding effect may be exaggerated in patients with underlying haemostatic defects, ibuprofen should be avoided by persons with intrinsic coagulation defects and by those on anticoagulant therapy. Concurrent therapy of ibuprofen with warfarin requires close monitoring of INR (see Drug Interactions).
Also, patients with underlying medical or pharmacologically - induced haemostatic defects could experience further prolongation of bleeding time through the inhibition of platelet aggregation induced to varying degrees by this class of drugs (1).
Blood dyscrasias (such as neutropenia, leukopenia, thrombocytopenia, aplastic anemia and agranulocytosis) associated with the use of non-steroidal anti-inflammatory drugs are rare, but could occur with severe consequences.
Hepatic
As with other nonsteroidal anti-inflammatory drugs, borderline elevations of one or more liver enzyme tests (AST, ALT, ALP) may occur in up to 15% of patients. These abnormalities may progress, may remain essentially unchanged, or may be transient with continued therapy.
A patient with symptoms and/or signs suggesting liver dysfunction, or in whom an abnormal liver test has occurred, should be evaluated for evidence of the development of a more severe hepatic reaction while on therapy with this drug. Severe hepatic reactions
including jaundice and cases of fatal hepatitis have been reported with nonsteroidal anti-inflammatory drugs.
Although such reactions are rare, if abnormal liver tests persist or worsen, if clinical signs and symptoms consistent with liver disease develop (e.g. jaundice), or if systemic manifestations occur (e.g. eosinophilia, associated with rash, etc.), this drug should be discontinued.
If there is a need to prescribe this drug in the presence of impaired liver function, it must be done under strict observation.
Immune
Patients sensitive to any one of the nonsteroidal anti-inflammatory drugs may be sensitive to any of the other NSAIDs also.
As with NSAIDs in general, some patients may experience urticaria and angioedema upon exposure to ibuprofen. Ibuprofen should not be given to patients with the complete or partial syndrome of ASA-intolerance (See Contraindications).
Neurologic
Some patients may experience drowsiness, dizziness, vertigo, tinnitus or hearing loss with the use of ibuprofen. If patients experience these side effects, they should exercise caution in carrying out activities that require alertness.
In occasional rare cases, with some NSAIDs, the symptoms of aseptic meningitis (stiff neck, severe headaches, nausea and vomiting, fever or clouding of consciousness) have been observed. Patients with autoimmune disorders (systemic lupus erythematosus, mixed connective tissues diseases, etc.) seem to be pre-disposed. Therefore, in such patients, the health provider must be vigilant to the development of this complication.
Ophthalmologic
Blurred and/or diminished vision, scotoma, and/or changes in colour vision have been reported. If a patient develops such complaints while taking ibuprofen, the drug should be discontinued. Patients with any visual disturbances should have an ophthalmologic examination.
Peri-Operative Considerations
In general, NAIDS should be discontinued prior to surgeries to decrease the risk of post-operative bleeding.
Renal
Long-term administration of nonsteroidal anti-inflammatory drugs to animals has resulted in renal papillary necrosis and other abnormal renal pathology. In humans, there have been reports of acute interstitial nephritis with hematuria, proteinuria, and occasionally nephrotic syndrome.
A second form of renal toxicity has been seen in patients with pre-renal conditions leading to reduction in renal blood flow or blood volume, where the renal prostaglandins have a supportive role in the maintenance of renal perfusion. In these patients, administration of a non-steroidal anti-inflammatory drug may cause a dose dependent reduction in prostaglandin formation and may precipitate overt renal decompensation. Patients at greatest risk of this reaction are those with impaired renal function (Glomerular Filtration Rate (GFR) < 60 ml/min or 1 ml/sec), patients on salt restricted diets, those with congestive heart failure, cirrhosis, liver dysfunction, those taking diuretics, angiotensin-converting enzyme inhibitors, angiotensin-II receptor blockers, cyclosporin, ASA and the elderly. Serious or life-threatening renal failure has been reported in patients with normal or impaired renal function after short-term therapy with NSAIDs. Even patients at risk who demonstrate the ability to tolerate an NSAID under stable conditions may decompensate during periods of added stress, for example during states of fluid restriction as can occur during gastroenteritis. Discontinuation of nonsteroidal anti-inflammatory therapy is usually followed by recovery to the pretreatment state.
NSAIDs can increase the risk of hyperkalemia. In patients on dialysis, NSAIDs should be used with caution.
Fluid retention and edema have been observed in patients treated with ibuprofen. Therefore, as with many other NSAIDs, the possibility of precipitating congestive heart failure in elderly patients or those with compromised cardiac function should be borne in mind. Ibuprofen should be used with caution in patients with heart failure, hypertension or other conditions predisposing to fluid retention. Ask patients who are on chronic therapy and at risk for fluid retention to weigh themselves at regular intervals to assist in monitoring for fluid accumulation.
With nonsteroidal anti-inflammatory treatment there is a potential risk of hyperkalemia, particularly in patients with conditions such as diabetes mellitus or renal failure; elderly patients; or in patients receiving concomitant therapy with angiotensin-II receptor antagonists, adrenergic blockers, angiotensin-converting enzyme inhibitors or some diuretics. Patients at risk should be monitored periodically during long-term therapy.
Respiratory
ASA-induced asthma is an uncommon but very important indication of ASA and NSAID sensitivity. It occurs more frequently in patients with asthma who have nasal polyps.
Skin
In rare cases, serious skin reactions such as Stevens-Johnson syndrome, toxic epidermal necrolysis, exfoliative dermatitis and erythema multiforme have been associated with the use of some NSAIDs. Because the rate of these reactions is low, they have usually been noted during post-marketing surveillance in patients taking other medications also associated with the potential development of these serious skin reactions. Thus, causality is not clear. These reactions are potentially life threatening but may be reversible if the causative agent is discontinued and appropriate treatment instituted. Patients should be advised that if they experience a skin rash they should discontinue their NSAID and contact their physician for assessment and advice, including which additional therapies to discontinue.
Special Populations
Pregnant Women:
No evidence specifically identifies exposure to analgesic doses of ibuprofen as a cause of harm to either mother or fetus during pregnancy (1, 7). Non-steroidal anti-inflammatory drugs in general, however, are known to affect the action of prostaglandin synthetase which could alter a variety of the physiological functions of prostaglandins or platelets during delivery such as facilitating uterine contraction in the mother, closure of the ductus arteriosus in the fetus, and platelet-related haemostasis. Patients should therefore be advised not to use ibuprofen during pregnancy without the advice of a physician, particularly during the last trimester (1). Clinical information is limited on the effects of ibuprofen in pregnancy.
Nursing Women:
Pharmacokinetic studies indicated that following oral administration of ibuprofen 400 mg the level of drug that appeared in breast milk was below detection levels of 1 µg/mL. The amount of ibuprofen to which an infant would be exposed through this source was considered negligible (8). However, since the absolute safety of ibuprofen ingested under these circumstances has not been determined, nursing mothers should be advised to consult a physician before using ibuprofen (1).
Geriatrics (> 65 years of age):
Patients older than 65 years and frail or debilitated patients are most susceptible to a variety of adverse reactions from nonsteroidal anti-inflammatory drugs (NSAIDs); the incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. Most reports of fatal GI events are in this population, especially those with cardiovascular disease. Older patients are also at risk of lower esophageal ulceration and bleeding. Elderly patients appear to be more susceptible to the central nervous system reactions; cognitive dysfunction (forgetfulness, inability to concentrate, a feeling of separation from the surroundings) in such patients has been reported.
For such patients, consideration should be given to a starting dose lower than the one usually recommended, with individual adjustment when necessary and under close supervision.
ADVERSE REACTIONS
Post-Market Adverse Drug Reactions
The most common adverse reactions encountered with nonsteroidal anti-inflammatory drugs are gastrointestinal, of which gastric or duodenal ulcer, with or without bleeding, is the most severe. Fatalities have occurred, particularly in the elderly.
Experience reported with prescription use of ibuprofen has included the following adverse reactions. Note: Reactions listed below under Causal Relationship Unknown are those where a causal relationship could not be established; however, in these rarely reported events, the possibility of a relationship to ibuprofen also cannot be excluded.
DRUG INTERACTIONS
Serious Drug Interactions
- Use with acetylsalicylic acid (ASA) or other NSAIDs, including ibuprofen, may result in possible additive adverse side effects.
- Use with acetaminophen, may increase the risk of adverse renal effect.
- Use with anticoagulants may increase the risk of GI adverse events (e.g., bleeding)
- Use with hypoglycemic agents (oral agents and insulin) may increase the risk of hypoglycaemia.
- Use with antihypertensives may interference with circulatory control.
- Use with diuretics may reduce the diuretic effect.
- Use with methotrexate may increase the risk of methotrexate toxicity.
- Use with lithium may increase the risk of lithium toxicity.
Drug-Drug Interactions:
Acetylsalicylic acid (ASA) or other NSAIDs
The use of ibuprofen in addition to any other NSAID is not recommended because of the absence of any evidence demonstrating synergistic benefits and the potential for additive side effects.
Animal studies show that ASA given with NSAID agents, including ibuprofen, yield a net decrease in anti-inflammatory activity with lowered blood levels of the non-ASA drug. Single dose bioavailability studies in normal volunteers have failed to show an effect of ASA on ibuprofen blood levels. Correlative clinical studies have not been done.
Also, some NSAIDs may interfere with the anti-platelet effects of low dose ASA, possibly by competing with ASA for access to the active site of cyclooxygenase-I.
The concomitant administration of ibuprofen but not acetaminophen has been shown to antagonize the irreversible platelet inhibition induced by ASA (9). Regular use of ibuprofen in patients with increased cardiovascular risk may limit the cardio protective effects of ASA (9,10).
Anticoagulants: See Warnings and Precautions -Hematologic section.
Coumarin Type Anticoagulants:
Several short-term controlled studies failed to show that ibuprofen significantly affected prothrombin time or a variety of other clotting factors when administered to individuals on coumarin-type anticoagulants. However, bleeding has been reported when ibuprofen and other NSAID agents have been administered to patients on coumarin-type anticoagulants. The use of ibuprofen in patients who are taking anticoagulants should therefore be avoided because of the possibility of enhanced GI bleeding or an additive effect due to ibuprofen’s reversible anti-platelet actions.
Anti-hypertensives
NSAIDs may diminish the antihypertensive effect of Angiotensin Converting Enzyme (ACE) inhibitors.
Combinations of ACE inhibitors, diuretics and NSAIDs might have an increased risk for acute renal failure and hyperkalemia. In longer term therapy blood pressure and kidney function should be monitored more closely, as occasionally there can be a substantial increase in blood pressure.
Anti-Platelet Agents (including ASA): See Warnings and Precautions - Hematologic section.
Diuretics
Ibuprofen, because of its fluid retention properties, can decrease the diuretic and anti-hypertensive effects of diuretics, and increased diuretic dosage may be needed. Patients with impaired renal function taking potassium-sparing diuretics who develop ibuprofen-induced renal insufficiency might be in serious danger of fatal hyperkalemia.
Glucocorticoids
Some studies have shown that the concomitant use of NSAIDs and oral glucocorticoids increases the risk of GI side effects such as ulceration and bleeding. This is especially the case in older (>65 years of age) individuals.
Lithium
Monitoring of plasma lithium concentrations is advised when stopping or starting an NSAID, as increased lithium concentrations can occur.
Oral hypoglycemics
Ibuprofen may increase the hypoglycemic effects of oral sulfonylurea hypoglycemic agents.
Other Drug Interactions
Although ibuprofen binds to a significant extent to plasma proteins, interactions with other protein-bound drugs occur uncommonly. Nevertheless, caution should be observed when other drugs also having a high affinity for protein binding sites are used concurrently. Some observations have suggested a potential for ibuprofen to interact with digoxin, methotrexate, and phenytoin. However, the mechanisms and clinical significance of these observations are presently not known.
Patients taking other prescribed medications should consult a physician before using ibuprofen to assure its compatibility with the other medications (1).
DOSAGE AND ADMINISTRATION
Dosing Considerations
Do not take for pain for more than 5 consecutive days or fever for more than 3 days unless directed by a physician.
If your condition deteriorates or new symptoms occur (such as the painful area becomes unusually red, swollen or tender), consult a physician.
Individuals older than 65 years who are frail or debilitated should be given a starting dose lower than the one usually recommended, with individual adjustments when necessary.
Missed Dose
If you miss a dose, take the missed dose as soon as you remember. If it is almost time for your next dose, wait until then to take your medicine and skip the missed dose. Do not take two doses at the same time.
Recommended Dose
Mild to moderate pain or fever.
Adults: Single oral dose may be taken every 4–6 hours, as required, not to exceed the maximum daily dose (1200 mg) in 24 hours unless directed by a physician.
Children: Suitable ibuprofen formulations are available for children.
OVERDOSAGE
Clinical Features
A clear pattern of clinical features associated with accidental or intentional overdose of ibuprofen has not been established. Reported cases of overdose have often been complicated by co-ingestions or additional suicidal gestures. The range of symptoms observed has included nausea, vomiting, abdominal pain, drowsiness, nystagmus, diplopia, headache, tinnitus, impaired renal function, coma and hypotension. A review of four fatalities associated with ibuprofen overdose indicates other contributing factors co-existed so it would be difficult to identify the toxicity of ibuprofen as a specific cause of death (0, 11).
Post-ingestion blood levels may be useful to confirm a diagnosis and to quantify the degree of exposure but otherwise have not been helpful in predicting clinical outcome. Generally, full recovery can be expected with appropriate symptomatic management.
The following cases of overdose have been reported. A 19-month-old child, 1-1/2 hours after the ingestion of seven to ten 400 mg tablets of ibuprofen, presented apnea, cyanosis and responded
only to painful stimuli. After treatment with 02, NaHCO3, infusion of dextrose and normal saline, the child was responsive and 12 hours after ingestion appeared completely recovered. Blood levels of ibuprofen reached 102.9 µg/mL, 8-1/2 hours after the accident. Two other children weighing approximately 10 kg had taken an estimated 120 mg/kg. There were no signs of acute intoxication or late sequelae. In one child the ibuprofen blood level at 90 minutes after ingestion was approximately 700 µg/mL. A nineteen-year-old male who ingested 8000 mg of ibuprofen reported dizziness and nystagmus was noted. He recovered with no reported sequelae after parenteral hydration and 3 days of bed rest.
For perspective, a single 200 mg oral dose study in 6 fasting healthy men produced a peak plasma concentration of 15.0 Fg/mL at 0.75 hr (12). Another study using a single oral 400 mg dose in humans produced a peak serum level of 31.9 ± 8.8 Fg/mL 0.5 hour after ingestion, and at 16 hours serum concentrations had dropped to 1 Fg/mL (13). (See Detailed Pharmacology – Human Studies – Pharmacokinetics - Absorption)
Management of Overdose
Appropriate interventions to decontaminate the gastrointestinal tract may be beneficial within the first four hours after ingestion. Routine symptomatic and supportive treatment is then recommended (11). Physicians should contact the Regional Poison Control Centre for additional guidance about ibuprofen overdose management.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Ibuprofen is a member of the class of agents commonly known as non-steroidal anti-inflammatory drugs (NSAID). Like all NSAIDs, ibuprofen is an analgesic, antipyretic, and anti-inflammatory medication (14).
It is generally accepted that the basic mechanism of pharmacological action of ibuprofen, and other NSAIDs, is the inhibition of prostaglandin synthesis (15, 16).
Nonselective NSAIDs (such as ibuprofen) and ASA act by inhibiting systemic (peripheral and central) prostaglandin G/H synthase isoenzymes, also known as cyclooxygenase-1 (COX-1) and cyclooxygenase-2 (COX-2). These isoenzymes are responsible for the conversion of arachidonic acid to various tissue specific prostaglandins and thromboxanes (17,15). COX-1 is constitutively expressed in all tissues and is responsible for generating prostaglandins that maintain organ function, protect the integrity of the gastric mucosa and generate platelet-derived thromboxane responsible for platelet aggregation and vasoconstriction (18). During the inflammatory process COX-2 is induced, generating prostaglandins that mediate pain and inflammation (19). COX-2 is also present constitutively in the kidneys and vascular endothelium (15). Reported adverse experiences with ASA and other NSAIDs can be understood on the basis of this mechanism of action.
Pharmacodynamics
Consistent with the NSAID classification, ibuprofen exhibits anti-inflammatory activity at higher dosage ranges (20). At lower adult single doses relevant to a nonprescription dosage (200 mg to 400 mg) ibuprofen relieves pain of mild to moderate intensity (21, 22, 23, 24, 25) and reduces fever (26, 27, 28). Analogous to acetylsalicylic acid, the prototype of this class, this analgesic/antipyretic activity of ibuprofen occurs at lower doses than necessary for anti-inflammatory effects, which are thought to require sustained administration of higher individual doses (16).
Clinical studies indicate a duration of clinical effect for up to 8 hours for fever and up to 6 hours for pain.
Pharmacokinetics
Absorption: Ibuprofen is rapidly absorbed after oral administration, with peak serum or plasma levels generally appearing within 1 to 2 hours. Oral absorption is estimated to be 80% of the dose. Both the rate of absorption and peak plasma concentrations are reduced when the drug is taken with food, but bioavailability as measured by total area under the concentration-time curve is minimally altered.
Distribution: Ibuprofen, like most drugs of its class, is highly protein bound (>99% bound at 20 Fg/mL) (29, 30). Tissue distribution of ibuprofen is also extensive in humans. Studies comparing synovial fluid levels with serum concentrations indicated that equilibration time post-ingestion occurred within approximately 3 to 5 hours (31).
Metabolism: It is rapidly metabolized through oxidation and glucuronic acid conjugation with urinary excretion of the inactive metabolites usually complete within 24 hours. Less than 10% is excreted unchanged in the urine (8).
Excretion: Ibuprofen has an elimination half-life of approximately two hours.
Special Populations and Conditions
Geriatrics: Studies demonstrate no apparent clinically significant alterations in ibuprofen pharmacokinetics in the elderly (32).
Hepatic Insufficiency: Ibuprofen pharmacokinetics have also been studied in patients with alcoholic liver disease who have been assessed to have fair to poor hepatic function. Results suggest that, despite the liver being the primary organ of metabolism of ibuprofen, its kinetic parameters are not substantially altered by this condition (33).
STORAGE AND STABILITY
Store between 15°C and 30°C. Unit dose strips should be stored between 15°C and 25 °C and protected from high humidity.
DOSAGE FORMS, COMPOSITION AND PACKAGING
REGULAR IBUPROFEN (ibuprofen) is available as 200 mg yellow coloured, capsule-shaped, film-coated caplets, engraved modified N on one side and 200 on the reverse, in bottles of 24, 50 and 100.
REGULAR IBUPROFEN (ibuprofen) is also available as 200 mg yellow coloured, film-coated tablets in bottles of 100, 500 and 1,000.
EXTRA STRENGTH IBUPROFEN (ibuprofen) is available as 400 mg orange coloured, round bi-convex, film-coated tablets, engraved on one side and plain on the reverse,
in bottles of 100, 500 and 1,000 and in unit dose boxes of 100 as unit dose strips.
REGULAR IBUPROFEN (ibuprofen) 200 mg caplets contain ibuprofen 200 mg and the following non-medicinal ingredients in alphabetic order: carnauba wax, colloidal silicon dioxide, D&C yellow # 10 aluminum lake, FD&C yellow # 6 aluminum lake, hydroxypropyl methyl cellulose, magnesium staerate, microcrystalline cellulose, polydextrose, polyethylene glycol, pregelatinized starch, silicon dioxide, sodium lauryl sulfate, sodium starch glycolate and titanium dioxide.
EXTRA STRENGTH IBUPROFEN (ibuprofen) 400 mg tablets contain ibuprofen 400 mg and the following non-medicinal ingredients in alphabetic order: carnauba wax, colloidal silicon dioxide, FD&C yellow # 6 aluminum lake, hydroxypropyl methyl cellulose, magnesium staerate, microcrystalline cellulose, polydextrose, polyethylene glycol, pregelatinized starch, silicon dioxide, sodium lauryl sulfate, sodium starch glycolate and titanium dioxide.
N 400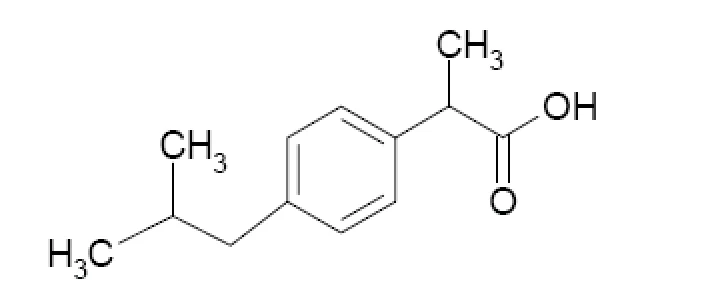
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: Ibuprofen
Chemical name: 2 - (4-isobutylphenyl) propionic acid
Molecular formula and molecular mass: C13H18O2, 206.3
Structural formula:
Physicochemical properties:
- Ibuprofen is a white crystalline solid. It is non-hygroscopic and relatively insoluble in water. The compound is readily soluble in organic solvent and aqueous alkalis. (The sodium salt is highly soluble in water.)
- The apparent pKa of ibuprofen is 5.2
- Melting point is about 75 °C.
CLINICAL TRIALS
A single dose comparative bioavailability study was performed on Ibuprofen 300 mg sugar-coated tablets (SCT), Ibuprofen 600 mg film-coated tablets (FCT) and MOTRIN 600 mg film-coated tablets (FCT). A total dose of 600 mg of the three test products was administered in a standard 3 cross-over design to twelve normal volunteers. The results of the study is summarized in Table 1:
Table 1: Comparative bioavailability study on Ibuprofen 300 mg sugar-coated tablets (SCT), Ibuprofen 600 mg film-coated tablets (FCT) and MOTRIN 600 mg film-coated tablets (FCT)
Ibuprofen (2 x 300 mg SCT) Ibuprofen (1 x 600 mg FCT) Ibuprofen (1 x 600 mg FCT) MOTRIN From measured data Geometric Mean | |||||
| Parameter | Test* | Test** | Reference† | % Ratio of Geometric Means | Confidence Interval |
| AUC0-12 hrs (µg•h/mL) | 187.90 ± 19.55 | 191.50 ± 29.78 | 192.80 ± 32.94 | ||
CMAX (µg•h/mL) | 46.27 ± 8.89 | 43.78 ± 9.89 | 53.96 ± 13.78 | ||
| TMAX2 (h) | 2.15 ± 1.02 | 1.92 ± 0.68 | 1.64 ± 1.00 | ||
* Ibuprofen Sugar-coated Tablets 2 x 300 mg ((Teva Canada Limited, Canada).
** Ibuprofen Film-coated Tablets 600 mg ((Teva Canada Limited, Canada).
† MOTRIN 600 mg FCT (Mc Neil Consumer Healthcare, Canada), purchased in Canada. 2 Expressed as the arithmetic mean (CV%) only.
A second comparative bioavailability study was conducted in twelve normal volunteers in order to assess the bioequivalence of Ibuprofen 300 mg film-coated tablets (FCT) and MOTRIN 300 mg sugar-coated tablets (SCT). The pharmacokinetic data (mean ± standard deviation) for the Ibuprofen and MOTRIN tablet formulations is tabulated in Table 2:
Table 2: Comparative bioavailability study on Ibuprofen 300 mg film-coated tablets (FCT)
and MOTRIN 300 mg sugar-coated tablets (SCT)
Ibuprofen (1 x 300 mg FCT) Ibuprofen (1 x 300 mg SCT) MOTRIN From measured data Geometric Mean | ||||||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval | ||||
| AUC0-12 hrs (µg•h/mL) | 103.01 ± 12.42 | 101.60 ± 16.31 | ||||||
CMAX (µg•h/mL) | 27.94 ± 3.21 | 31.82 ± 6.47 | ||||||
| TMAX2 (h) | 1.44 ± 0.61 | 1.27 ± 1.04 | ||||||
* IbuprofenFilm-coated Tablets 300 mg ((Teva Canada Limited, Canada).
† MOTRIN 300 mg SCT (Mc Neil Consumer Healthcare, Canada), purchased in Canada. 2 Expressed as the arithmetic mean (CV%) only.
The efficacy of ibuprofen as an analgesic and antipyretic has been demonstrated by a variety of clinical studies and pain models.
Dental Pain
In adults, the effects of a drug on post-surgical dental extraction pain serves as a standard model for relief of pain of mild to moderate intensity. Ibuprofen 200 mg and 400 mg has been clearly demonstrated to provide pain relief significantly superior to placebo. When compared to the "standard" non-prescription analgesics, ibuprofen 200 mg is found to be comparable to ASA 650 mg (21, 41).
Dysmenorrhea
Nonsteroidal anti-inflammatory drugs, which inhibit prostaglandin synthesis such as ibuprofen, are particularly suitable for management of primary dysmenorrhea. Menstrual pain is now thought to result from abnormal uterine activity, which is secondary to increased production and release of endometrial prostaglandins at the time of menstruation.
Several adequate and well-controlled clinical trials provide substantial evidence of the safety and efficacy of ibuprofen at doses of 200 to 400 mg in relieving the pain of menstrual cramps (44, 45, 46).
A summary of trials of ibuprofen in the treatment of dysmenorrhea indicates the usual dose administered to be 400 mg. The few studies, which are available at a 200 mg dosage, indicate superiority of both ibuprofen 200 mg and 400 mg compared with ASA 650 mg (47).
Pain of Osteoarthritis
Several controlled clinical studies in adults provide substantial evidence of the safety and efficacy of ibuprofen at doses of 1200 mg or less per day in relieving the pain of osteoarthritis (48, 49, 50, 51, 52). Collectively, these studies support an indication for the temporary relief of minor pains of arthritis and, in conjunction with single dose analgesia studies, support the broader indication: for the temporary relief of minor aches and pains.
Headache
Ibuprofen has also been used satisfactorily in the management of headache. The efficacy of 200 mg of ibuprofen has been reported to be significantly superior to placebo and ASA 650 mg in the treatment of muscle contraction headaches (24). No differences in the frequency of side effects were found in the treatment groups. Similar results were reported in a study with patients referred to a Headache Clinic with frequent muscle contraction headache (53).
Soft Tissue Injury
Several studies also document the efficacy of analgesic doses of ibuprofen in the treatment of soft tissue injuries such as muscular aches or athletic injuries (54, 55).
Fever
Studies of its efficacy in the management of fever in adults and children demonstrate ibuprofen to be an effective antipyretic (26, 27, 28, 56, 57), with a duration of action of up to eight hours when administered at a dose of 7.5 mg/kg.
Controlled clinical trials comparing doses between 5 and 10mg/kg of ibuprofen and 10-15 mg/kg of acetaminophen have been conducted in children 6 months to 12 years of age with fever
primarily due to viral illnesses. In these studies, there were few differences between treatments in fever reduction in the first hour and maximum fever reduction occurred between 2 and 4 hours. There was some evidence that the higher dosage range of ibuprofen (10mg/kg) resulted in a prolonged duration of effect (from six to eight hours) and that it was more effective for children with higher baseline temperatures (above 102.5F/39.1EC) but the numbers of patients were not adequate to draw definitive conclusions. In children with baseline temperatures at or below 102.5F (39.1EC) both ibuprofen doses and acetaminophen were equally effective in their maximum effect.
One controlled clinical trial comparing a single dose of ibuprofen 7.5 mg/kg with acetaminophen 12.5 mg/kg demonstrated the superiority of ibuprofen over an eight-hour period.
DETAILED PHARMACOLOGY
Animal Studies
Pharmacodynamics
While the mechanism of action of ibuprofen is not definitely known, the generally accepted mechanism is the inhibition of prostaglandin synthesis. Inhibition of prostaglandin biosynthesis prevents sensitization of tissues by prostaglandins to other inflammatory, pain and thermoregulatory mediators, hence accounting for the activity of ibuprofen and other nonsteroidal anti-inflammatory drugs against pain, inflammation and fever (16).
Inhibition of prostaglandin synthesis by ibuprofen has been demonstrated in several different experimental models: bull seminal vesicle microsomes (34), stomach, duodenum, kidney and brain of the rat, (35) microsomal preparations from rabbit brain and kidney medulla (36).
The analgesic efficacy of ibuprofen has been demonstrated in several animal models: phenylbenzoquinone-induced writhing in the mouse, acetylcholine-induced writhing in the mouse, the Randall-Selitto inflammed paw model in the rat, the mouse hot plate and adjuvant-induced arthritis model in the rat (37, 38, 39).
The antipyretic activity of ibuprofen has been demonstrated in yeast-induced fever in rats (37, 38, 39).
Pharmacokinetics
Several aspects of the pharmacokinetics of ibuprofen have been studied in vivo in rats, rabbits, dogs and baboons.
Studies in rats indicate that while limited absorption of ibuprofen occurs in the stomach, the principal site of absorption is the intestine. Single dose studies using C14
labelled ibuprofen in rats, rabbits and dogs show rapid absorption rates (40).
Tissue distribution studies performed in rats after both single and repeated doses of 20 mg/kg of C14
labelled ibuprofen demonstrate broad distribution with accumulation of radioactivity in the thyroid, adrenals, ovaries, fat and skin. Transplacental passage of ibuprofen was also noted with similar plasma levels measured in both the pregnant rats and fetuses (40).
Protein binding studies with plasma levels of 20 µg/mL indicate the percent bound in rats 96%, dogs 99%, baboons 95% and man 99% (29).
Four metabolites of ibuprofen have been found in the plasma of rabbits, three in rats, none in dogs, two in baboons and two in man, with the liver suggested as the principal organ of metabolism (40, 29). Excretion of metabolites was noted to varying degrees through both urine and feces indicating species variability in the bile and kidney excretion ratios.
Human Studies
Pharmacokinetics
The pharmacokinetics of ibuprofen has also been studied in humans. Although there is little evidence of clinically significant age dependent kinetics in febrile children ages 3 months to 12 years (58), some differences in the pharmacokinetic parameters of volume of distribution and clearance have been observed between adults and children (59).
Absorption: In-vivo studies indicate that ibuprofen is well absorbed orally with peak plasma levels usually occurring within 1 to 2 hours. A single 200 mg oral dose study in 6 fasting healthy men produced a peak plasma concentration of 15.0 Fg/mL at 0.75 hr (12). Another study using a single oral 400 mg dose in humans produced a peak serum level of 31.9 ± 8.8 Fg/mL 0.5 hour after ingestion, and at 16 hours serum concentrations had dropped to 1 Fg/mL (13). Comparable serum levels and time to peak within 1-2 hours were confirmed by other investigations with 200 mg and 400 mg solid doses (60, 31). A multiple dose study of administration of a 200 mg ibuprofen tablet three times a day for 2 weeks showed no evidence of accumulation of ibuprofen (29).
Distribution: Ibuprofen, like most drugs of its class, is highly protein bound (>99% bound at 20 Fg/mL) (29, 30). Based on oral dosing data there is an age-or fever-related change in volume of distribution for ibuprofen. Febrile children <11 years old have a volume of approximately 0.2 L/kg while adults have a volume of approximately 0.12L/kg. The clinical significance of these findings is unknown (59). Tissue distribution of ibuprofen is also extensive in humans. Studies comparing synovial fluid levels with serum concentrations indicated that equilibration time post-ingestion occurred within approximately 3 to 5 hours (31).
Metabolism: Ibuprofen is extensively metabolized in humans with approximately 84% recoverable in the urine, primarily as conjugated hydroxy- and carboxy- metabolites, with only approximately l% excreted unchanged (8). The two major metabolites of ibuprofen in humans have been found to have no activity in the ultraviolet erythema test in guinea pigs and in the acetylcholine-induced mouse writhing test at doses of l0 mg/kg and l5 mg/kg respectively (38).
Elimination: Ibuprofen is rapidly metabolized and eliminated in the urine. The excretion of ibuprofen is virtually complete 24 hours after the last dose. It has a biphasic plasma elimination time curve with a half-life of approximately 2.0 hours. There is no difference in the observed terminal elimination rate or half-life between children and adults, however, there is an age-or fever-related change in total clearance (59). This suggests that the observed difference in clearance is due to differences in the volume of distribution of ibuprofen, as described above. The clinical relevance of these differences in clearance is unknown, although extensive clinical experience with ibuprofen in children at the pertinent dosage range (5 - 10 mg/kg) indicates a wide margin of safety.
TOXICOLOGY
Toxicity studies have been conducted using a variety of species, including: mice, rats, rabbits, guinea pigs and beagle dogs.
Acute Toxicity Studies
Single-dose acute toxicity studies indicate that ibuprofen in lethal doses depresses the central nervous system of rodents and that large doses are ulcerogenic in both rodents and nonrodents. Ulcerogenesis may occur with both parenteral and oral administration indicating that the mechanism may have both a systemic as well as topical component.
Acute toxicity of ibuprofen in the rodent was studied in a number of models.
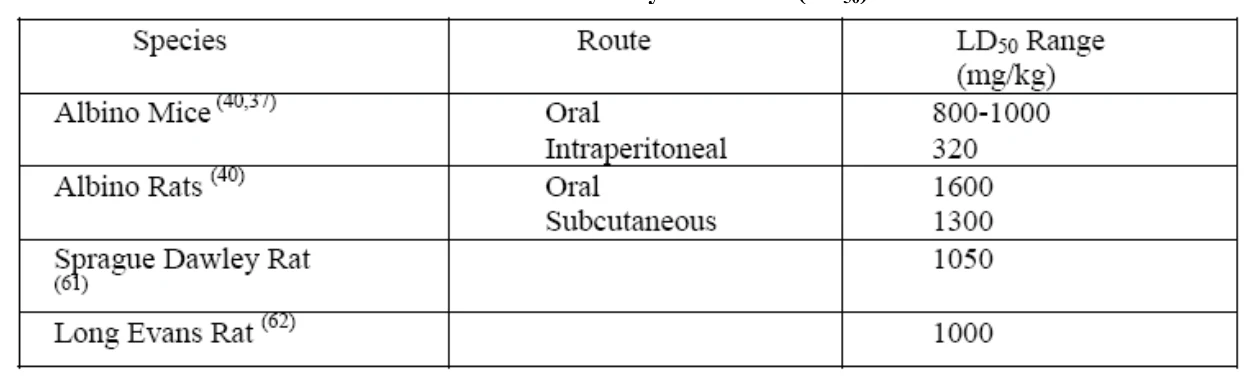
Single graded doses of ibuprofen were administered by oral intubation or by intraperitoneal or subcutaneous injection to groups of l0 male albino mice and male albino rats. Gross reactions were observed and mortalities recorded over a period of l4 days. The LD values determined by this method were 800 mg/kg orally and 320 mg/kg intraperitoneally in the mouse and l600 mg/kg orally and l300 mg/kg subcutaneously in the rat. Acute signs of poisoning were prostration in mice, and sedation, prostration, loss of righting reflex and labored respiration in rats. Death occurred within 3 days from perforated gastric ulcers in mice and intestinal ulceration in rats, irrespective of the route of administration (40).
Similar LD50 determinations in other strains of rats and mice are summarized in the following Table 3.
Table 3: Acute Toxicity in Rodents (LD50)
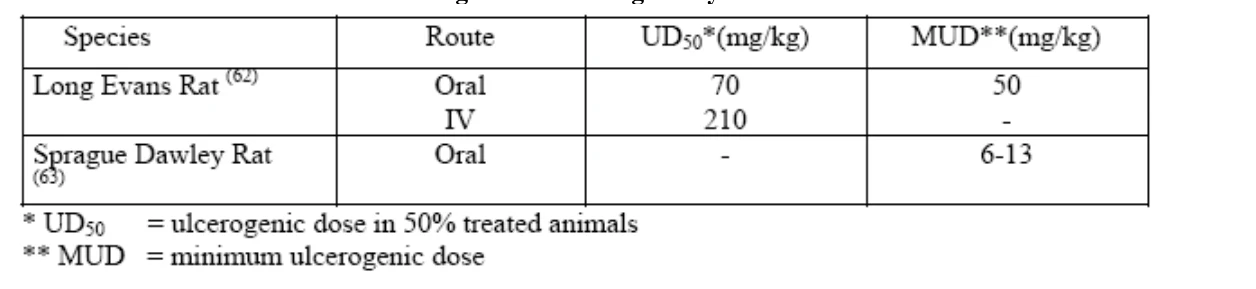
In a comparison of several non-steroidal anti-inflammatory drugs (NSAID) including ibuprofen, male rats were sacrificed and the stomachs removed and examined for ulceration either 3 or 24 hours after oral administration of various single doses of ibuprofen (63). Using a standard scoring technique a mean score for each dosage group was calculated and the ulcerogenic potential was expressed as a minimum ulcerogenic dose. The minimum oral ulcerogenic dose for ibuprofen in rats was calculated to be 6-13 mg/kg.
Another group studied the production of gastrointestinal lesions in the rat comparing ulcerogenic doses of ibuprofen and other NSAIDs after oral or intravenous administration (62). Both male and female Long Evans rats were used in all experiments. Prior to drug administration the animals were fasted for 8 hours. After treatment they were fed a normal diet and sacrificed after l7 hours. Gastric and intestinal mucosa was examined for presence of ulcers. The ulcerogenic dose in 50% of treated animals (UD50) was calculated. The UD50 following oral administration of ibuprofen was determined to be 70 mg/kg while for intravenous ibuprofen it was 210 mg/kg. The intestinal UD50 was 88 mg/kg following oral and 172 mg/kg with intravenous administrations. A calculated "severity index" of gastric lesions was higher by the oral than the IV route at all doses tested.
Studies of the ulcerogenic potential of ibuprofen are summarized in the following Table 4.
Table 4: Single Dose Ulcerogenicity Studies in Rodents
Acute toxicity has also been studied in dogs.
Various single oral doses of ibuprofen were administered to dogs with subsequent hematologic examination and biochemical analyses of blood and urine, and examination of feces for occult 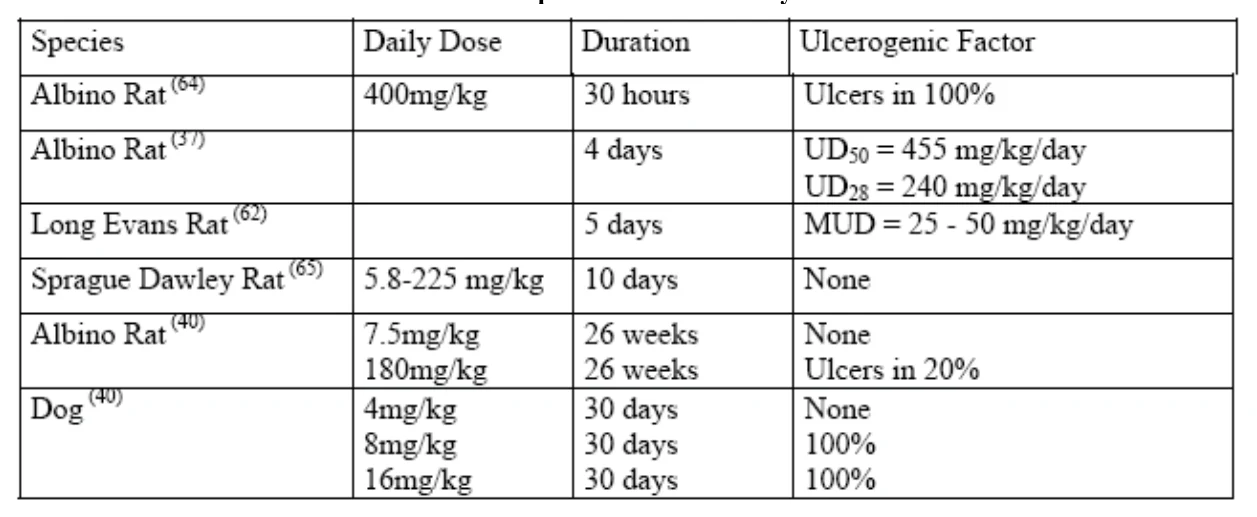
blood (40). Gross examination of the major organs occurred after the animals were sacrificed. No ill effects were seen following doses of 20 or 50 mg/kg. Oral doses of 125 mg/kg or greater produced emesis, scouring, albuminuria, fecal blood loss and erosions in the gastric antrum and pylorus.
Multiple Dose Toxicity Studies
Multiple dose ulcerogenicity studies of ibuprofen have also been conducted.
Rats were dosed by the oral route for a specific number of consecutive days, then sacrificed for examination. The ulcerogenic effect of oral ibuprofen was graded and reported by various scoring systems such as percent of animals in which ulcers were produced by a specific dose, or the UD50.
In one typical such study, Long Evans rats were administered comparative NSAIDs orally once a day for 5 days (62). The gastric and small intestinal mucosa were then examined for ulceration. The UD50, MUD and potency ratio of the drugs tested were calculated. The minimal ulcerogenic doses of ibuprofen were 25 mg/kg for the stomach and 50 mg/kg for the intestine.
Similar studies of multiple dose ulcerogenic potential of ibuprofen are summarized in the following Table 5.
Table 5: Multiple Oral Dose Toxicity Studies
No other organ systems were generally noted to be significantly affected by these chronic administration studies. In one 30-day study (66), Wistar rats receiving 157 mg/kg/day ibuprofen had serum transaminase levels approximately double of those of a control, untreated group. Lower doses of ibuprofen in the same study had no significant effect on the activity of these enzymes.
Chronic toxicity studies in dogs demonstrated no gross or clinical signs of toxicity at 4, 8 or 16 mg/kg/day for 30 days (40). However, in all dogs given 8 or 16 mg/kg/day, postmortem
examination revealed gastric ulcers or erosions. No lesions were observed in dogs given 4 mg/kg/day.
A more complete assessment of chronic toxicity of ibuprofen in dogs studied the effects of administration of oral doses of 0, 2, 4 or 26 mg/kg/day over 26 weeks (40). Periodic blood, urine and fecal sample analyses were performed. Histologic examination of selected organs and tissues was performed at the completion of the study. During the 26 week period, some reversible signs of gastrointestinal disturbance characterized by frequent vomiting, diarrhea, occasional passage of fresh blood and weight loss occurred in the 2 female dogs but not the males receiving 16 mg/kg ibuprofen. Occult blood was irregularly detected in fecal samples but urinalysis, liver function tests and other hematologic and blood biochemical values were not altered significantly. Gross examination of organs was normal except for ulcerative lesions in the gastrointestinal tract of organs of all dogs receiving 16 mg/kg/day. Dogs given 2 and 4 mg/kg/day suffered no adverse reactions or gastrointestinal damage.
Carcinogenicity
A study to evaluate the potential carcinogenic activity of ibuprofen involved administration of a minimum of 100 mg/kg/day to mice for 80 weeks and 60 mg/kg/day to rats for 2 years (67). The proportion of animals with tumors of all types examined did not differ from those in the control group. The studies confirm that in the rat and mouse, ibuprofen does not induce tumors of the liver or other organs. Further, despite prolonged treatment, no other drug-induced hepatic lesions were seen in either species.
Teratogenicity and Reproduction Studies
Teratogenicity studies of ibuprofen have been conducted in rabbits and rats (40). Results of the experiments indicate that ibuprofen is not teratogenic when given in toxic doses to rabbits nor is there embryotoxic or teratogenic activity in pregnant rats even when administered in ulcerogenic doses.
Effects of ibuprofen on circular strips of fetal lamb ductus arterious indicate that exposure may produced contraction of the ductus (68). Such an effect might be anticipated because of the known prostaglandin inhibiting properties of ibuprofen.
REFERENCES
- 1. Arthritis Advisory Committee. Transcript of proceedings. Review of ibuprofen for non-prescription sale. Food and Drug Administration, Department of Health and Human Services, Bethesda. August 18, 1983.
- 2. Wolfe MM, Lichtenstein DR, Singh G. Gastrointestinal toxicity of nonsteroidal anti-inflammatory drugs. N Engl J Med 1999; 340: 1888-1899.
- 3. García Rodríguez LA, Hernández-Díaz S. The risk of upper gastrointestinal complications associated with non-steroidal anti-inflammatory drugs, glucocorticoids, acetaminophen, and combinations of these agents. Arthritis Res 2001; 3: 98-101.
- 4. Piper JM, Ray WA, Daugherty JR, Griffin MR. Corticosteroid use and peptic ulcer disease: role of nonsteroidal anti-inflammatory drugs. Ann Internal Med 1991; 114: 735-740.
- 5. Gabriel SE, Jaakkimainen L, Bombardier C. Risk for serious gastrointestinal complications related to use of nonsteroidal anti-inflammatory drugs. Ann Internal Med 1991; 115: 787-796.
- 6. Moller Hansen J, Hallas J, Lauritsen JM, Bytzer P. Non-steroidal anti-inflammatory drugs and ulcer complications: a risk factor analysis for clinical decision-making. Scand J Gastroenterol 1996; 31: 126-130.
- 7.
Barry WS, Meinzinger MM, Howse CR. Ibuprofen overdose and exposure in utero:
results from a postmarketing voluntary reporting system. Am J Med 1984; 77(1A):35-39.
- 8.
Albert KS, Gernaat CM. Pharmacokinetics of ibuprofen. Amer J Med 1984; 77(1A): 40-
46.
- 9.
Catella-Lawson F, Reilly MP, Kapoor SC, Cucchiara AJ, DeMarco S, Tournier B et al.
Cyclooxygenase inhibitors and the antiplatelet effects of aspirin. N Engl J Med. 2001:345:1809-1817.
- 10. Kurth T, Glynn RJ, Walker AM, Chan KA, Buring JE, Hennekens CH, et al. Inhibition of clinical benefits of aspirin on first myocardial infarction by nonsteroidal anti-inflammatory Drugs. Circulation. 2003; 108: 1191 – 1195.
- 11. Court H, Volans GN. Poisoning after overdose with non-steroidal anti-inflammatory drugs. Adverse Drug React Acute Poisoning Rev 1984; 3:1-21.
- 12. Adams SS, Cliffe EE, Lessel B, Nicholson JS. Some biological properties of 2-(4-isobutylphenyl)-propionic acid. J Pharm Sci 1967; 56:1686.
- 13.
Kaiser DG, Martin RS. Electron-capture GLC determination of ibuprofen in serum. J
Pharm Sci 1978; 67:627-630.
- 14. Insel PA. Analgesic-antipyretic and anti-inflammatory agents and drugs employed in the treatment of gout. In Molinoff PB, Ruddon RW, editors. Goodman & Gilman’s The Pharmacological Basis of Therapeutics. New York: McGraw-Hill, 1996: 617-657.
- 15.
Hillis WS. Areas of emerging interest in analgesia: Cardiovascular complications. Am J
Ther 2002; 9:259-269.
- 16.
Flower RJ, Moncada S, Vane JR. Analgesic-antipyretics and anti-inflammatory agents;
drugs employed in the treatment of gout. In: Gilman AG, Goodman LS, Rall TW, Murad F. Goodman and Gilman's The pharmacological basis of therapeutics. Toronto: Collier MacMillan, Canada 1985; 674-689, 700-703.
- 17.
FitzGerald GA, Patrono C. The Coxibs, selective inhibitors of cyclooxygenase-2. N Engl
J Med 2001; 345: 433-442. Review
- 18. Konstam MA, Weir MR, Reicin A, Shapiro D, Sperling RS, Barr E, et al. Cardiovascular thrombotic events in controlled, clinical trials of refecoxib. Circulation 2001; 104:2280-2288.
- 19.
Bombardier C, Laine L, Reicin A, Shapiro D, Burgo-Vargas R, Davis B, et al.
Comparison of upper gastrointestinal toxicity of refecoxib and naproxen in patients with rheumatoid arthritis. N Engl J Med 2000; 343: 1520-1528.
- 20. Brooks CD, Schlagel CA, Sekhar NC, Sobota JT. Tolerance and pharmacology of ibuprofen. Curr Ther Res 1973; 15:180-190.
- 21. Cooper SA, Needle SE, Kruger GO. Comparative analgesic potency of aspirin and ibuprofen. J Oral Surgery 1977; 35:898-903.
- 22. Gallardo F, Rossi E. Double-blind evaluation of naproxen and ibuprofen in periodontal surgery. Pharm Ther Dent 1980; 5:69-72.
- 23. Jain AK, Ryan JR, McMahon FG, Kuebel JO, Walters PJ, Noveck C. Analgesic efficacy of low doses of ibuprofen in dental extraction pain. Clin Pharmacol Ther 1984; 35:249.
- 24. Vecchio TJ, Heilman CJ, O'Connel MJ. Efficacy of ibuprofen in muscle extraction headache. Clin Pharmacol Ther 1983; 33:199.
- 25.
Iles JD. Relief of postoperative pain by ibuprofen: a report of two studies. Can J Surg
1980; 23:288-290.
- 26.
Gaitonde BB, Dattani K, Morwani K. Antipyretic activity of ibuprofen (Brufen). J Assoc
Physicians India 1973; 21:579-584.
- 27. Sheth UK, Gupta K, Paul T, Pispati PK. Measurement of antipyretic activity of ibuprofen and paracetamol in children. J Clin Pharmacol 1980; 20:672-675.
- 28.
Simila S, Kouvalainen K, Keinanen S. Oral antipyretic therapy: evaluation of ibuprofen.
Scand J Rheumatol 1976; 581-583.
- 29. Mills RF, Adams SS, Cliffe EE, Dickinson W, Nicholson JS. The metabolism of ibuprofen. Xenobiotica 1973: 3:589-598.
- 30. Kober A, Sjoholm I. The binding sites of human serum albumin for some nonsteroidal antiinflammatory drugs. Mol Pharmacol 1980; 18:421-426.
- 31. Glass RC, Swannell AJ. Concentrations of ibuprofen in serum and synovial fluid from patients with arthritis. Br J Clin Pharmacol 1978; 6:453-454.
- 32. Albert KS, Gillespie WR, Wagner JG, Pau A, Lockwood GF. Effects of age on the clinical pharmacokinetics of ibuprofen. Am J Med 1984; 77(1A):47-50.
- 33. Juhl RP, Van Thiel DH, Dittert LW, Albert KS, Smith RB. Ibuprofen and sulindac kinetics in alcoholic liver disease. Clin Pharmacol Ther 1983; 34:104-109.
- 34. Cushman DW, Cheung HS. Effect of substrate concentration on inhibition of protaglandin synthetase of bull seminal vesicles by anti-inflammatory drugs and fenamic acid analogs. Biochim Biophys Acta 1976; 424:449-459.
- 35. Fitzpatrick FA, Wynalda MA. In Vivo suppression of prostaglandin biosynthesis by non-steroidal anti-inflammatory agents. Prostaglandins 1976; 12:1037-1051.
- 36.
Szczeklik A, Gryglewski RJ, Czerniawska-Mysik G, Zmuda A. Aspirin induced asthma:
hypersensitivity to fenoprofen and ibuprofen in relation to their inhibitory action on prostaglandin generation by different microsomal enzymic preparations. J Allergy Clin Immunol 1976; 58:10-18.
- 37. Aparicio L. Some aspects of the pharmacology of butibufen, a non-steroidal anti-inflammatory agent. Arch Int Pharmacodyn Ther 1977; 227:130-141.
- 38. Adams SS, McCullough KF, Nicholson JS. The pharmacological properties of ibuprofen, an anti-inflammatory, analgesic and antipyretic agent. Arch Int Pharmacdyn Ther 1969; 178:115-129.
- 39.
Romer D. Pharmacological evaluation of mild analgesics. Br J Clin Pharmacol 1980;
10:247S-251S.
- 40. Adams SS, Bough RG, Cliffe EE, Lessel B, Mills RFN. Absorption, distribution and toxicity of ibuprofen. Toxicol Appl Pharmacol 1969; 15:310-330.
- 41.
Cooper SA. Five studies on ibuprofen for postsurgical dental pain. Am J Med 1984;
77(1A):70-77.
- 42.
Bertin L, Pons G, d'Athis P, Lasfargues G, Maudelonde C, Duhamel JF,, et al.
Randomized, double-blind, multicentre, controlled trial of ibuprofen versus acetaminophen (paracetamol) and placebo for treatment of symptoms of tonsillitis and pharyngitis in children. J. Pediatr 1991; 119:811-814.
- 43. Schachtel BP, Thoden WR. A placebo-controlled model for assaying systemic analgesics in children. Clin Pharmacol Ther 1993; 53:593-601.
- 44. Molla AL, Donald JF. A comparative study of ibuprofen and paracetamol in primary dysmenorrhea. J Int Med Res 1974; 2:395-399.
- 45.
Shapiro SS, Diem K. The effect of ibuprofen in the treatment of dysmenorrhea. Curr Ther
Res 198l: 30:327-334.
- 46. Gookin KS, Forman ES, Vecchio TJ, Wiser WL, Morrison JC. Comparative efficacy of ibuprofen, indomethacin and placebo in the treatment of primary dysmenorrhea. South Med J 1983; 76:1361-1362, 1367.
- 47. Dawood MY. Ibuprofen and dysmenorrhea. Am J Med 1984; 77(1A):87-94.
- 48.
Miller AC, Buckler JW, Sheldrake FE. Clinical studies of ibuprofen. Curr Med Res Opin
1975; 3:589-593
- 49. de Blecourt JJ. A comparative study of ibuprofen (‘Brufen’) and indomethacin in uncomplicated arthroses. Curr Med Res Opin 1975; 3:477-480.
- 50. Chahade WH, Federico WA, Josef H, Cohen M. The evaluation of the analgesic activity and anti-inflammatory activity of ibuprofen in comparison with aspirin in patients suffering from osteoarthritis of the hips, knee and/or cervical, dorsal and/or lumbar spinal column in a double blind study. Revista Brasileria de Medicina 1976; 33:347-350.
- 51. Tyson VC, Glynne A. A comparative study of benoxaprofen and ibuprofen in osteoarthritis in general practice. J Rheumatol (Suppl 6)1980; 7:132-138.
- 52. Ruoff G, Williams S, Cooper W, Procaccini RL. Aspirin-acetaminophen vs ibuprofen in a controlled multicenter double-blind study with patients experiencing pain associated with osteoarthritis. Curr Ther Res 1982; 31:821-831.
- 53. Diamond S. Ibuprofen versus aspirin and placebo in the treatment of muscle contraction headache. Headache 1983; 23:206-210.
- 54.
Muckle DS. Comparative study of ibuprofen and aspirin in soft-tissue injuries. Rheumatol
Rehab 1974; 13:141-147.
- 55.
Nasution AR. Study of the analgesic activities of ibuprofen compared with paracetamol.
Proceeding of the 13th International Congress of Rheumatology, Kyoto, Japan 1973.
- 56. Walson PD, Galletta G, Braden NJ, Alexander L. Ibuprofen, acetaminophen, and placebo treatment of febrile children. Clin Pharmacol Ther 1989; 46:9-17.
- 57. Wilson JT, Brown RD, Kearns GL, Eichler VF, Johnson VA, Bertrand KM, et al. Single-dose, placebo-controlled comparative study of ibuprofen and acetaminophen antipyresis in children. J Pediatr 1991; 119:803-811.
- 58.
Kauffman RE, Fox B, Gupta N. Ibuprofen antipyresis and pharmacokinetics in children.
Clin Pharmacol Ther 1989; 45:139 (abstract).
- 59.
McEvoy GK, Editor. Ibuprofen. In: AHFS DI 1997. Bethesda: American Society of
Health - Systems Pharmacists, 1997. p. 1499 – 1503
- 60.
Kaiser DG, Vangiessen GJ. GLC determination of ibuprofen [(+)-2-(p-isobutylphenyl)
propionic acid] in plasma. J Pharm Sci 1974; 63:219-221.
- 61. Fukawa K, Kanezuka T, Ohba S, Kawano O, Hibi M, Misaki N, et al. Studies on an anti-inflammatory agent. III. Pharmacological investigations of a new non-steroidal anti-inflammatory agent: 2-oxo-3-[4-(1-oxo-2-isoindolinyl)-phenyl]-butanamide (GP 650). Arzneimittelforschung 1982; 32:225-230.
- 62. Cioli V, Putzolu S, Rossi V, Corradino C. A toxicological and pharmacological study of ibuprofen guaiacol ester (AF 2259) in the rat. Toxicol Appl Pharmacol 1980; 54:332-339.
- 63. Atkinson DC, Leach EC. Anti-inflammatory and related properties of 2-(2,4-diochlorphenoxy) phenylacetic acid (fenclofenac). Agent Actions 1976; 6:657-666.
- 64. Parmar NS, Ghosh MN. Gastric anti-ulcer activity of (+)-cyanidanol-3, a histidine decarboxylase inhibitor. Eur J Pharmacol 1981; 69:25-32.
- 65. Paroli E, Nencini P, Anania MC. Correlations of DNA, RNA and protein levels in duodenal mucosa with antiinflammatory potency and disposition to gut damage of non-steroidal agents. Comparative behaviour of glucametacine, indomethacin, phenylbutazone and ibuprofen. Arzneimittelforschung 1978; 28:819-824.
- 66.
Dudkiewicz J. Ibuprofen-induced gastrointestinal changes. Acta Physiol Pol (Poland)
1981: 32:693-701.
- 67. Adams SS, Bough RG, Cliffe EE, Dickinson W, Lessel B, McCullough KF, et al.. Some aspects of the pharmacology, metabolism and toxicology of ibuprofen. Rheumatol Phys Med 1970; 10 (Suppl 10):9-26.
- 68. Coceani F, White E, Bodach E, Olley PM. Age-dependent changes in the response of the lamb ductus arteriosus to oxygen and ibuprofen. Can J Physiol Pharmacol 1979; 57:825-831.
- 69.
Proceedings of Joint Meeting, Arthritis Drugs Advisory Committee and Nonprescription
Drugs Advisory Committee. Centre for Drug Evaluation and Research. Department of Health and Human Services, Rockville, Maryland. March 28, 1995.
- 70.
Product Monograph for MOTRIN* IB, Extra Strength MOTRIN* IB and Super Strength
MOTRIN* IB, McNeilConsumer Healthcare, Control No.: 096753, Date of Revision: June 14, 2005.