


Product Monograph - Renflexis
1 INDICATIONS
Indications have been granted on the basis of similarity between Renflexis® and the reference biologic drug Remicade®.
RENFLEXIS® (Infliximab for Injection) is indicated for:
- use in combination with methotrexate for the reduction in signs and symptoms, inhibition of the progression of structural damage and improvement in physical function in adult patients with moderately to severely active rheumatoid arthritis.
- the reduction of signs and symptoms and improvement in physical function in patients with active ankylosing spondylitis who have responded inadequately, or are intolerant to, conventional therapies.
- reduction of signs and symptoms, induction and maintenance of clinical remission and mucosal healing and reduction of corticosteroid use in adult patients with moderately to severely active Crohn’s disease who have had an inadequate response to a corticosteroid and/or aminosalicylate. Renflexis® can be used alone or in combination with conventional therapy.
- reduction of signs and symptoms and induction and maintenance of clinical remission in pediatric patients with moderately to severely active Crohn’s disease who have had an inadequate response to conventional therapy (corticosteroid and/or aminosalicylate and/or an immunosuppressant). The safety and efficacy of Renflexis® is not established in patients less than 9 years of age.
- treatment of fistulising Crohn’s disease, in adult patients who have not responded despite a full and adequate course of therapy with conventional treatment.
- reduction of signs and symptoms, induction and maintenance of clinical remission and mucosal healing, and reduction or elimination of corticosteroid use in adult patients with moderately to severely active ulcerative colitis who have had an inadequate response to conventional therapy (i.e., aminosalicylate and/or corticosteroid and/or an immunosuppressant).
- reduction of signs and symptoms, induction and maintenance of clinical remission, and induction of mucosal healing in pediatric patients with moderately to severely active ulcerative colitis who have had an inadequate response to conventional therapy (i.e., aminosalicylate and/or corticosteroid and/or an immunosuppressant). The safety and efficacy of Renflexis® have not been established in patients less than 6 years of age.
- reduction of signs and symptoms, induction of major clinical response, and inhibition of the progression of structural damage of active arthritis, and improvement in physical function in patients with psoriatic arthritis.
- treatment of adult patients with chronic moderate to severe plaque psoriasis who are candidates for systemic therapy. For patients with chronic moderate plaque psoriasis, Renflexis® should be used after phototherapy has been shown to be ineffective or inappropriate. When assessing the severity of psoriasis, the healthcare professional should consider the extent of involvement, location of lesions, response to previous treatments, and impact of disease on the patient’s quality of life.
Renflexis® should be used by healthcare professionals who have sufficient knowledge of rheumatoid arthritis and/or ankylosing spondylitis and/or Crohn’s disease and/or ulcerative colitis and/or psoriatic arthritis and/or plaque psoriasis and who have fully familiarized themselves with the efficacy/safety profile of Renflexis®.
1.1 Pediatrics
Pediatrics (6-17 years of age): Renflexis® is indicated for reducing signs and symptoms and for inducing and maintaining clinical remission in pediatric patients with moderately to severely active Crohn’s disease who have had an inadequate response to conventional therapy. Renflexis® is also indicated for reducing signs and symptoms, inducing and maintaining clinical remission and inducing mucosal healing in pediatric patients with moderately to severely active ulcerative colitis who have had an inadequate response to conventional therapy (i.e., aminosalicylate and/or corticosteroid and/or an immunosuppressant). In general, the adverse events in pediatric patients with Crohn’s disease or ulcerative colitis who received infliximab for injection were similar to those seen in adult patients with Crohn’s disease or ulcerative colitis respectively. It should be noted that in the Phase 3 trial (REACH) of pediatric patients with Crohn’s disease, all patients were required to be on a stable dose of either 6-mercaptopurine (6-MP), azathioprine (AZA), or methotrexate (MTX). (See 1 INDICATIONS, 7.1.3 Pediatrics, 8.2.1 Clinical Trial Adverse Reactions - Pediatrics, 4 DOSAGE AND ADMINISTRATION and 14 Clinical trials.)
The safety and efficacy of infliximab for injection has not been established in pediatric patients with Crohn’s disease <9 years of age or with ulcerative colitis <6 years of age. The safety and efficacy of infliximab for injection in pediatric patients with plaque psoriasis, psoriatic arthritis, ankylosing spondylitis, and in juvenile rheumatoid arthritis have not been established.
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies suggests that the use in geriatric population is associated with no overall differences in safety and efficacy.
In rheumatoid arthritis clinical trials (ATTRACT) and plaque psoriasis trials, no overall differences were observed in the effectiveness or safety in 181 patients with rheumatoid arthritis and 75 patients with plaque psoriasis, aged 65 or older compared to younger patients although the incidence of serious adverse events in patients aged 65 or older was higher in both infliximab for injection and control groups compared to younger patients. In Crohn’s disease, ulcerative colitis, ankylosing spondylitis and psoriatic arthritis studies, there were insufficient numbers of patients aged 65 and over to determine whether they respond differently from patients aged 18 to 64. Because there is a higher incidence of infections in the elderly population in general, caution should be used in treating the elderly (see 8.2 Clinical Trial Adverse Reactions, Infections).
2 CONTRAINDICATIONS
- Patients with severe infections such as sepsis, abscesses, tuberculosis and opportunistic infections (see 7 WARNINGS AND PRECAUTIONS, Risk of Infections).
Patients with moderate or severe (NYHA Class III/IV) congestive heart failure (see 7
WARNINGS AND PRECAUTIONS, Cardiovascular and 8.2 Clinical Trial Adverse Reactions, Congestive Heart Failure).
- Patients with a history of hypersensitivity to infliximab for injection, to other murine proteins, or to any of the excipients. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions RISK OF INFECTIONS
Tuberculosis (frequently disseminated or extrapulmonary at clinical presentation), invasive fungal infections, and other opportunistic infections, have been observed in patients receiving Renflexis®. Some of these infections have been fatal.
Patients must be evaluated for the risk of tuberculosis, including latent tuberculosis, prior to initiation of Renflexis®. This evaluation should include a detailed medical history of tuberculosis or possible previous contact with tuberculosis and previous and/or current immunosuppressive therapy. Appropriate screening tests, i.e. tuberculin skin test and chest x-ray (if indicated), should be performed in all patients.3 Prescribers are reminded of the risk of false negative tuberculin skin test results especially in patients who are severely ill or immunocompromised. Treatment of latent tuberculosis infection should be initiated prior to therapy with Renflexis® (see 7 WARNINGS AND PRECAUTIONS, Risk of Infections). Hepatosplenic T-cell lymphoma
Post-marketing cases of hepatosplenic T-cell lymphoma have been reported in patients treated with TNF-blockers including infliximab for injection. This rare type of T-cell lymphoma has a very aggressive disease course and is usually fatal. Almost all patients had received treatment with azathioprine or 6-mercaptopurine concomitantly with or immediately prior to a TNF-blocker. The vast majority of infliximab for injection cases have occurred in patients with Crohn’s disease or ulcerative colitis and most were reported in adolescent or young adult males (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis). Pediatric Malignancy
Lymphoma and other malignancies, some fatal, have been reported in children and adolescent patients treated with TNF-blockers, including infliximab for injection (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The infusion solution must be administered over a period of not less than 2 hours, except as noted in 4.4 Administration.
All patients administered Renflexis® should be observed for at least 1-2 hours post-infusion for side effects. Emergency equipment, such as adrenaline, antihistamines, corticosteroids and an artificial airway must be available (see 8.2 Clinical Trial Adverse Reactions, Infusion-related Reactions).
At the discretion of the treating healthcare professional, treatment with Renflexis® may be delayed if the patient has a planned surgical procedure (see risk of post-procedural complication in 8.5 Post-Market Adverse Reactions), considering the long half-life of infliximab.
The Organon HarmonyTM Infusion Network has been established to facilitate the administration of Renflexis®. This network consists of clinics located across Canada that are staffed by qualified healthcare professionals specially trained in the administration of Renflexis® infusions. Information about the Organon HarmonyTM Infusion Network can be obtained by contacting Organon HarmonyTM at: 1-866-556-5663
4.2 Recommended Dose and Dosage Adjustment
For recommended intravenous infusion duration for patients with each of the indications described below, see 4.4 Administration.
Rheumatoid Arthritis
The recommended dose of Renflexis® is 3 mg/kg given as an intravenous infusion followed by additional 3 mg/kg doses at 2 and 6 weeks after the first infusion then every 8 weeks thereafter. Renflexis® should be given in combination with methotrexate. For patients who have an incomplete response, consideration may be given to adjusting the dose up to 10 mg/kg and/or treating as often as every 4 weeks. Duration of treatment needed to achieve a response after dose escalation is not known. However, higher doses of infliximab for injection were associated with a slightly higher proportion of patients experiencing adverse events (97% for the 3 mg/kg dose given every 8 weeks vs. 100% for the 10 mg/kg dose given every 4 weeks), including infections (84% for the 3 mg/kg dose given every 8 weeks vs. 91% for the 10 mg/kg dose given every 4 weeks).
Ankylosing Spondylitis
The recommended dose of Renflexis® is 5 mg/kg given as an intravenous infusion followed by additional 5 mg/kg doses at 2 and 6 weeks after the first infusion, then every 6 to 8 weeks thereafter.
Ulcerative Colitis
The recommended dose of Renflexis® is 5 mg/kg given as an induction regimen at 0, 2 and 6 weeks followed by 5 mg/kg every 8 weeks thereafter, for the treatment of adults and pediatric patients (≥ 6 years of age) with moderately to severely active ulcerative colitis. In some adult patients, consideration may be given to adjusting the dose up to 10 mg/kg to sustain clinical response and remission. Some adult patients may not benefit from dose escalation. In addition to the healthcare professional’s clinical assessment, measurement of infliximab for injection trough levels and titers of antibodies to infliximab for injection should be taken into account before considering dose adjustment.
Crohn’s Disease
Adults
The recommended dose of Renflexis® is 5 mg/kg given as an induction regimen at 0, 2 and 6 weeks followed by a maintenance regimen of 5 mg/kg every 8 weeks thereafter for the treatment of moderate to severe, active Crohn’s disease. For patients who have an incomplete response, consideration may be given to adjusting the dose up to 10 mg/kg. Some adult patients may not benefit from dose escalation. In addition to the healthcare professional’s clinical assessment, measurement of infliximab for injection trough levels and titers of antibodies to infliximab for injection should be taken into account before considering dose adjustment.
The recommended dose of Renflexis® is 5 mg/kg given as an induction regimen at 0, 2 and 6 weeks followed by a maintenance regimen of 5 mg/kg every 8 weeks thereafter for the treatment of fistulising Crohn’s disease. Patients who do not respond by Week 14 are unlikely to respond with continued dosing and consideration should be given to discontinue Renflexis® in these patients. For patients who respond and then lose their response, consideration may be given to treatment with 10 mg/kg. In the ACCENT II clinical study, among patients who lost response at 5 mg/kg infliximab for injection and re-established response following dose escalation to 10 mg/kg infliximab for injection, most had done so after 1 dose and all had done so after 2 doses of 10 mg/kg.
Pediatric
The recommended dose of Renflexis® for pediatric patients (≥ 9 years of age) with moderately to severely active Crohn’s disease is 5 mg/kg given as an induction regimen at 0, 2 and 6 weeks followed by a maintenance regimen of 5 mg/kg every 8 weeks. Patients who do not respond by week 14 are unlikely to respond with continued dosing and consideration should be given to discontinue Renflexis® in these patients.
Psoriatic Arthritis
The recommended dose of Renflexis® is 5 mg/kg given as an intravenous infusion followed with additional similar doses at 2 and 6 weeks after the first infusion then every 8 weeks thereafter. Renflexis® can be used with or without methotrexate. If a patient shows no response at 24 weeks, no additional treatment with Renflexis® should be given.
Plaque Psoriasis
The recommended dose of Renflexis® is 5 mg/kg given as an intravenous infusion followed by additional 5 mg/kg doses at 2 and 6 weeks after the first infusion, then every 8 weeks thereafter. If a patient does not show an adequate response at Week 14, after infusions at weeks 0, 2, and 6, no additional treatment with Renflexis® should be given.
Special Populations
Renal Impairment
Renflexis® has not been studied in patients with renal impairment. No dose recommendations can be made (see 10.3 Pharmacokinetics, Special Populations and Conditions).
Hepatic Impairment
Renflexis® has not been studied in patients with hepatic impairment. No dose recommendations can be made (see 10.3 Pharmacokinetics, Special Populations and Conditions).
4.3 Reconstitution
Table 1: Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL |
| 100 mg as lyophilized powder | 10 mL Sterile water for injection, USP | 250 mL The total volume of the reconstituted product must be further diluted to 250 mL with 0.9% Sodium Chloride Injection, USP | Between 0.4 mg/mL and 4 mg/mL |
Since no preservative is present, it is recommended that the Renflexis® infusion be started within 3 hours of reconstitution and dilution unless the Renflexis® infusion is prepared under controlled and validated aseptic conditions (see 11 STORAGE, STABILITY AND DISPOSAL, After Reconstitution and Dilution and Handling Under Controlled and Validated Aseptic Conditions.
4.4 Administration
Use aseptic technique.
Renflexis® vials do not contain antibacterial preservatives. Therefore, after reconstitution, the vials should be used immediately, not re-entered or stored. The diluent to be used for reconstitution is 10 mL of Sterile Water for Injection, USP. The total dose of the reconstituted product must be further diluted to 250 mL with 0.9% Sodium Chloride Injection, USP. The infusion concentration should range between 0.4 mg/mL and 4 mg/mL. Since no preservative is present, it is recommended that the Renflexis® infusion be started within 3 hours of reconstitution and dilution.
- 1. Calculate the dose and the number of Renflexis® vials needed. Each Renflexis® vial contains 100 mg of infliximab for injection. Calculate the total volume of reconstituted Renflexis® solution required.
- 2. Reconstitute each Renflexis® vial with 10 mL of Sterile Water for Injection, USP, using a syringe equipped with a 21-gauge or smaller needle. Remove the flip-top from the vial and wipe the top with an alcohol swab. Insert the syringe needle into the vial through the centre of the rubber stopper and direct the stream of Sterile Water for Injection, USP, to the glass wall of the vial. Gently swirl the solution by rotating the vial to dissolve the lyophilized powder. Avoid prolonged or vigorous agitation. DO NOT SHAKE. Foaming of the solution on reconstitution is not unusual. Allow the reconstituted solution to stand for 5 minutes. The solution should be colourless to light yellow and opalescent, and the solution may develop a few translucent particles as infliximab for injection is a protein. Do not use if opaque particles, discolouration, or other foreign particles are present.
- 3.
Dilute the total volume of the reconstituted Renflexis® solution dose to 250 mL with 0.9%
Sodium Chloride Injection, USP, by withdrawing a volume of 0.9% Sodium Chloride Injection, USP, equal to the volume of reconstituted Renflexis® from the 0.9% Sodium Chloride Injection, USP, 250 mL bottle or bag. Slowly add the total volume of reconstituted Renflexis® solution to the 250 mL infusion bottle or bag. Gently mix. For volumes greater than 250 mL, either use a larger infusion bag (e.g. 500 mL, 1000mL) or use multiple 250 mL infusion bags to ensure that the concentration of the infusion solution does not exceed 4 mg/mL.
- 4.
For patients with ankylosing spondylitis, psoriatic arthritis, and plaque psoriasis, the infusion solution must be administered over a period of not less than 2 hours.
For patients with rheumatoid arthritis, the recommended infusion duration is over a period of not less than 2 hours in patients not previously treated with Renflexis®. At the discretion of the treating healthcare professional, some patients with rheumatoid arthritis who have tolerated 3 initial 2-hour infusions of Renflexis® may be considered for receiving subsequent infusions at the same dose over a period of not less than 1 hour (see 8.2 Clinical Trial Adverse Reactions, Infusion-Related Reactions and 14.5 Clinical trials – reference biologic drug, Rheumatoid Arthritis). The safety of shortened infusions at doses > 6 mg/kg has not been studied.
For pediatric and adult patients with Crohn’s disease or ulcerative colitis, the recommended infusion duration is over a period of not less than 2 hours. At the discretion of the treating health professional, adult patients with Crohn’s disease or ulcerative colitis who have tolerated at least 3 consecutive 2-hour infusions of Renflexis® may be considered for receiving subsequent infusions of the 5 mg/kg dose over a period of not less than 1 hour (see 8.2 Clinical Trial Adverse Reactions, Infusion-Related Reactions). For patients receiving the 10 mg/kg dose, administration should still occur over a period of not less than 2 hours.
Use only an infusion set with an in-line, sterile, non-pyrogenic, low-protein-binding filter (pore size of 1.2 μm or less). Do not store any unused portion of the infusion solution for reuse.
- 5. Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration, whenever solution and container permit. If visibly opaque particles, discolouration or other foreign particulates are observed, the solution should not be used.
- 6. No physical biochemical compatibility studies have been conducted to evaluate the co-administration of Renflexis® with other agents. Renflexis® should not be infused concomitantly in the same intravenous line with other agents.
4.5 Missed Dose
Patients who forget or miss an appointment to receive Renflexis® should be advised to make another appointment as soon as possible.
5 OVERDOSAGE
Single doses up to 20 mg/kg have been administered without any direct toxic effect. In case of overdosage, it is recommended that the patient be monitored for any signs or symptoms of adverse reactions or effects and appropriate symptomatic treatment instituted immediately.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognize the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 2: Dosage Forms, Strengths, Composition and Packaging
Renflexis® (infliximab for injection) is supplied as a sterile white lyophilized powder for intravenous infusion. Each vial contains 100 mg infliximab for injection, 500 mg sucrose, 0.5 mg polysorbate 80, 6.30 mg monobasic sodium phosphate monohydrate and 1.20 mg dibasic sodium phosphate heptahydrate. No preservatives are present.
Renflexis® (infliximab for injection) lyophilised concentrate for IV injection is supplied in individually boxed single-use 20 mL vials in the following strength: 100 mg infliximab for injection.
Vial stopper is free of natural rubber latex.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Renflexis® should be used by health professionals who have sufficient knowledge of rheumatoid arthritis and/or ankylosing spondylitis and/or Crohn’s disease, ulcerative colitis and/or psoriatic arthritis and/or plaque psoriasis and who have fully familiarized themselves with the efficacy/safety profile of Renflexis®.
In order to improve the traceability of biological medicinal products, the trademark and the batch number of the administered product should be clearly recorded (or stated) in the patient file.
Risk of Infections
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous injection | Powder for Solution / 100mg/vial | Dibasic sodium phosphate heptahydrate, monobasic sodium phosphate monohydrate, polysorbate 80, sucrose |
Serious infections due to bacterial (including sepsis and pneumonia), invasive fungal, viral, and other opportunistic pathogens, have been reported in patients receiving TNF-blocking agents. Some of these infections have been fatal. Many of the serious infections in patients treated with infliximab for injection have occurred in patients on concomitant immunosuppressive therapy that, in addition to their underlying disease, could predispose them to infections.
Renflexis® should not be given to patients with a clinically important, active infection, including tuberculosis. Caution should be exercised when considering the use of Renflexis® in patients with a chronic infection or a history of recurrent infection. Patients should be monitored for signs and symptoms of infection while on or after treatment with Renflexis®. New infections should be closely monitored. If a patient develops a serious infection, Renflexis® therapy should be discontinued (see 8.2 Clinical Trial Adverse Reactions, Infections).
Cases of histoplasmosis, coccidioidomycosis, blastomycosis, listeriosis, pneumocystosis, and tuberculosis have been observed in patients receiving infliximab for injection. For patients who have resided in or travelled to regions where histoplasmosis, coccidioidomycosis, or blastomycosis are endemic, the benefits and risks of Renflexis® treatment should be carefully considered before initiation or continuation of Renflexis® therapy.
Invasive Fungal Infections:
In patients treated with Renflexis®, an invasive fungal infection such as aspergillosis, candidiasis, pneumocystosis, histoplasmosis, coccidioidomycosis or blastomycosis should be suspected if they develop a serious systemic illness. Invasive fungal infections may present as disseminated rather than localized disease, and antigen and antibody testing may be negative in some patients with active infection. Appropriate empiric antifungal therapy should be considered while a diagnostic workup is being performed. The decision to administer empiric antifungal therapy should be made in consultation with a healthcare professional with expertise in the diagnosis and treatment of invasive fungal infections and should take into account both the risk for severe fungal infection and the risks of antifungal therapy.
Tuberculosis:
Cases of active tuberculosis have occurred in patients treated with infliximab for injection during and after treatment for latent tuberculosis. Patients receiving Renflexis® should be monitored closely for signs and symptoms of active tuberculosis during and after treatment, including patients who tested negative for latent tuberculosis infection. The possibility of undetected latent tuberculosis should be considered, especially in patients who have immigrated from or traveled to countries with a high prevalence of tuberculosis or had close contact with a person with active tuberculosis. All patients treated with Renflexis® should have a thorough history taken prior to initiating therapy. Some patients who have previously received treatment for latent or active tuberculosis have developed active tuberculosis while being treated with infliximab for injection. Anti-tuberculosis therapy should be considered prior to initiation of Renflexis® in patients with a past history of latent or active tuberculosis in whom an adequate course of treatment cannot be confirmed. Anti-tuberculosis therapy prior to initiating Renflexis® should also be considered in patients who have several or highly significant risk factors for tuberculosis infection and have a negative test for latent tuberculosis. The decision to initiate anti-tuberculosis therapy in these patients should only be made following consultation with a healthcare professional with expertise in the treatment of tuberculosis and taking into account both the risk for latent tuberculosis infection and the risks of anti-tuberculosis therapy.
Opportunistic Infections:
Opportunistic infections due to bacterial, mycobacterial, invasive fungal, viral, or parasitic organisms including aspergillosis, blastomycosis, candidiasis, coccidioidomycosis, histoplasmosis, legionellosis, listeriosis, pneumocystosis and tuberculosis have been reported with TNF-blockers, including infliximab for injection. Patients have frequently presented with disseminated rather than localized disease.
Concurrent Administration of TNF-alpha Inhibitor and Anakinra:
Serious infections and neutropenia were seen in clinical studies with concurrent use of anakinra and another TNFα-blocking agent, etanercept, with no added clinical benefit compared to etanercept alone. Because of the nature of the adverse events seen with combination of etanercept and anakinra therapy, similar toxicities may also result from the combination of anakinra and other TNFα-blocking agents. Therefore, the combination of Renflexis® and anakinra is not recommended.
Concurrent Administration of Renflexis® with Abatacept:
In clinical studies, concurrent administration of TNF-blocking agents and abatacept has been associated with an increased risk of infections including serious infections compared with TNF-blocking agents alone, without increased clinical benefit. Because of the nature of the adverse events seen with the combination of TNF-blocking agents and abatacept therapy, the combination of Renflexis® and abatacept is not recommended.
Concurrent Administration with other Biological Therapeutics:
There is insufficient information regarding the concomitant use of Renflexis® with other biological therapeutics used to treat the same conditions as Renflexis®. The concomitant use of Renflexis® with these biologics is not recommended because of the possibility of an increased risk of infection.
Switching between Biological Therapeutics:
When switching from one biologic to another, patients should continue to be monitored, since overlapping biological activity may further increase the risk of infection.
Carcinogenesis and Mutagenesis
Pediatric malignancy
Malignancies, some fatal, have been reported among children, adolescents and young adults who received treatment with TNF-blocking agents (initiation of therapy ≤18 years of age), including infliximab for injection. Approximately half of these cases were lymphomas, including Hodgkin’s and non-Hodgkin’s lymphoma. The other cases represented a variety of malignancies, including rare malignancies that are usually associated with immunosuppression and malignancies that are not usually observed in children and adolescents. The malignancies occurred after a median of 30 months (range 1 to 84 months) after the first dose of TNF-blocker therapy. Most of the patients were receiving concomitant immunosuppressants. These cases were reported post-marketing and are derived from a variety of sources, including registries and spontaneous post-marketing reports.
Lymphoma
Lymphomas have been observed in patients treated with TNF-blocking agents, including infliximab for injection. In clinical trials, patients treated with infliximab for injection had a higher incidence of lymphoma than the expected rate in the general population. Patients with rheumatoid arthritis and Crohn’s disease, particularly those with highly active disease and/or chronic exposure to immunosuppressant therapies, may be at a higher risk (up to several fold) for the development of lymphoma than the general population, even in the absence of TNF-blocking therapy. The role of TNF-blockers in the development of malignancy is not known.
Hepatosplenic T-cell lymphoma
Post-marketing cases of hepatosplenic T-cell lymphoma have been reported in patients treated with TNF-blockers including infliximab for injection. This rare type of T-cell lymphoma has a very aggressive disease course and is usually fatal. Almost all patients had received treatment with azathioprine or 6-mercaptopurine concomitantly with or immediately prior to a TNF-blocker. The vast majority of infliximab for injection cases have occurred in patients with Crohn’s disease or ulcerative colitis and most were reported in adolescent or young adult males. Cases of hepatosplenic T-cell lymphoma have also occurred in Crohn’s disease and ulcerative colitis patients receiving azathioprine or 6-mercaptopurine who were not treated with infliximab for injection. Before initiating or continuing Renflexis® therapy in a patient who is receiving an immunosuppressant such as azathioprine or 6-mercaptopurine, carefully assess the need for continuing the immunosuppressant therapy in light of the potential risks of concomitant treatment. The causal relationship of hepatosplenic T-cell lymphoma to Renflexis® therapy remains unclear.
Leukemia
Cases of acute and chronic leukemia have been reported with post-marketing TNF-blocker use in rheumatoid arthritis and other indications. Even in the absence of TNF-blocker therapy, patients with rheumatoid arthritis may be at a higher risk (approximately 2-fold) than the general population for the development of leukemia.
Non-lymphoma malignancy
In the controlled portions of clinical trials of some TNF-blocking agents, including infliximab for injection, more malignancies (excluding lymphoma and non-melanoma skin cancer [NMSC]) have been observed in patients receiving those TNF-blockers compared with control patients (see 8.2 Clinical Trial Adverse Reactions, Malignancies/Lymphoproliferative Disease). The rate of non-lymphoma malignancies among infliximab for injection-treated patients was similar to that expected in the general population whereas the rate among control patients was lower than expected.
In an exploratory clinical trial evaluating the use of infliximab for injection in patients with moderate to severe chronic obstructive pulmonary disease (COPD), more malignancies were reported in infliximab for injection-treated patients compared with control patients. All patients had a history of heavy smoking.
Cervical cancer
A population-based retrospective cohort study using data from Swedish national health registries found an increased incidence of cervical cancer in women with rheumatoid arthritis treated with infliximab for injection compared to biologics-naïve patients or the general population, including those over 60 years of age. A causal relationship between infliximab for injection and cervical cancer cannot be excluded. Periodic screening should continue in women treated with Renflexis®, including those over 60 years of age.
Skin cancers
Melanoma and Merkel cell carcinoma have been reported in patients treated with TNF-blocker therapy, including infliximab for injection (see 8.5 Post-Market Adverse Reactions). Periodic skin examination is recommended for all patients, particularly those with risk factors for skin cancer.
Psoriasis patients should be monitored for nonmelanoma skin cancers (NMSCs), particularly those patients who have had prior prolonged phototherapy treatment. In the maintenance portion of clinical trials for infliximab for injection, NMSCs were more common in patients with previous phototherapy (see 8.2 Clinical Trial Adverse Reactions,
Malignancies/Lymphoproliferative Disease).
The potential role of TNF-blocking therapy in the development of malignancies is not known. Caution should be exercised when considering TNF-blocking therapy for patients with a history of malignancy or when considering continuing treatment in patients who develop a malignancy (see 8.2 Clinical Trial Adverse Reactions, Malignancies/Lymphoproliferative Disease).
Long-term studies in animals have not been performed to evaluate the carcinogenic potential. No clastogenic or mutagenic effects of infliximab for injection were observed in the in vivo mouse micronucleus test or the Salmonella–Escherichia coli (Ames) assay, respectively. Chromosomal aberrations were not observed in an assay performed using human lymphocytes. Tumourigenicity studies in mice deficient in TNFα demonstrated no increase in tumours when challenged with known tumour initiators and/or promoters.
Cardiovascular
Doses greater than 5 mg/kg should not be administered to patients with congestive heart failure (CHF). Renflexis® should be used with caution in patients with mild heart failure (NYHA Class I/II). Patients should be closely monitored, and Renflexis® must not be continued in patients who develop new or worsening symptoms of heart failure (see 2 CONTRAINDICATIONS and 8.2 Clinical Trial Adverse Reactions, Congestive Heart Failure).
The results of a randomized study evaluating the use of infliximab for injection in patients with heart failure (NYHA Functional Class III/IV) suggested higher mortality in patients who received 10 mg/kg infliximab for injection, and higher rates of cardiovascular adverse events at doses of 5 mg/kg and 10 mg/kg.
Driving and Operating Machinery
Renflexis® may have a minor influence on the ability to drive and use machines. Dizziness may occur following administration of Renflexis®.
Hematologic
There have been reports of pancytopenia, leukopenia, neutropenia, and thrombocytopenia in patients receiving TNF-blockers, including infliximab for injection. Caution should be exercised in patients treated with Renflexis® who have a current or past history of significant cytopenias. All patients should be advised to seek immediate medical attention if they develop signs and symptoms suggestive of blood dyscrasias (e.g. persistent fever, bruising, bleeding, pallor). Discontinuation of Renflexis® therapy should be considered in patients with confirmed significant hematologic abnormalities.
Hepatic/Biliary/Pancreatic
Cases of jaundice and non-infectious hepatitis, some with features of autoimmune hepatitis, have been observed in the post-marketing experience of infliximab for injection. Isolated cases of liver failure resulting in liver transplantation or death have occurred. A causal relationship between infliximab for injection and these events has not been established. Patients with symptoms or signs of liver dysfunction should be evaluated for evidence of liver injury. If jaundice and/or ALT elevations ≥5 times the upper limit of normal develop, Renflexis® should be discontinued immediately, and a thorough investigation of the abnormality should be undertaken. As also observed with the use of other immunosuppressive drugs, reactivation of hepatitis B has occurred very rarely in patients receiving infliximab for injection who are chronic carriers of this virus (i.e., surface antigen positive). Patients should be tested for hepatitis B virus (HBV) infection before initiating treatment with immunosuppressants, including Renflexis®. For patients who test positive for hepatitis B surface antigen, consultation with a healthcare professional with expertise in the treatment of hepatitis B is recommended. Chronic carriers of hepatitis B should be appropriately evaluated prior to the initiation of Renflexis® therapy and monitored closely during treatment and for several months following discontinuation of therapy.
Immune
To minimize the incidence of hypersensitivity reactions, including infusion reactions and serum sickness-like reactions, Renflexis® should be administered as regular maintenance therapy after an induction regimen at weeks 0, 2 and 6 (see 4 DOSAGE AND ADMINISTRATION).
Hypersensitivity Reactions
Infliximab for injection has been associated with hypersensitivity reactions that vary in their time of onset. Hypersensitivity reactions, which include urticaria, dyspnea, and/or bronchospasm, laryngeal edema, pharyngeal edema and hypotension, have occurred during or within 2 hours of infliximab for injection infusion. However, in some cases, serum sickness-like reactions have been observed in Crohn’s disease and rheumatoid arthritis patients 3 to 12 days after infliximab for injection therapy was reinstituted following an extended period without infliximab for injection treatment. Symptoms associated with these reactions include fever, rash, headache, sore throat, myalgias, polyarthralgias, hand and facial edema and/or dysphagia. These reactions were associated with marked increase in antibodies to infliximab for injection, loss of detectable serum concentrations of infliximab for injection, and possible loss of drug efficacy. Renflexis® should be discontinued for severe reactions. Medications for the treatment of hypersensitivity reactions (e.g., acetaminophen, antihistamines, corticosteroids and/or epinephrine) should be available for immediate use in the event of a reaction (see 8.2 Clinical Trial Adverse Reactions, Infusion-related Reactions).
During clinical trials, infliximab for injection was sometimes readministered within 14 weeks following the last infusion. After a drug free interval of 15 weeks to 2 years, the risk of delayed hypersensitivity following readministration has not been accurately determined (see 8.2 Clinical Trial Adverse Reactions, Infusion-related Reactions, Delayed hypersensitivity/Reactions following readministration of infliximab for injection).
Infusion reactions following readministration of Renflexis®
In a rheumatoid arthritis clinical trial where subjects were receiving low dose methotrexate and in a psoriasis clinical trial, a 3-dose induction of infliximab for injection after a period of no treatment resulted in a higher incidence of serious and severe infusion reactions during the reinduction regimen than had been observed in rheumatoid arthritis, psoriasis and Crohn’s disease trials in which a period of no drug treatment was followed by regular maintenance therapy without reinduction. Most of these reactions occurred during the second reinduction infusion at Week 2. The serious infusion reactions included anaphylaxis, urticaria, facial edema, chills and itching. Retreatment with a reinduction regimen after a period of no treatment is not recommended (see 8.2 Clinical Trial Adverse Reactions, Infusion-related Reactions, Infusion Reactions following readministration of infliximab for injection).
The Organon HarmonyTM Infusion Network has been established to facilitate the administration of Renflexis®. This network consists of clinics located across Canada that are staffed by qualified healthcare professionals specially trained in the administration of Renflexis® infusions. Information about the Organon HarmonyTM Infusion Network can be obtained by contacting Organon HarmonyTM at: 1-866-556-5663
Autoimmunity
Treatment with infliximab for injection may result in the formation of autoantibodies and in the development of a lupus-like syndrome. If a patient develops symptoms suggestive of a lupus-like syndrome following treatment with Renflexis®, treatment should be discontinued (see 8.2 Clinical Trial Adverse Reactions, Autoantibodies/Lupus-like Syndrome).
Immunogenicity
Treatment with infliximab for injection can be associated with the development of antibodies to infliximab for injection (see 7 WARNINGS AND PRECAUTIONS, Immune). Approximately 10% of patients were antibody positive. The majority of antibody positive patients had low titers.
In a Phase III study of Crohn’s disease (SONIC) in patients who were immunomodulator-naïve, antibodies occurred at Week 30 in 14% of patients receiving infliximab for injection monotherapy and in 1% of patients receiving infliximab for injection in combination with azathioprine (AZA). Through Week 50, anti-infliximab for injection antibodies occurred in 19% and 2.5% of patients, respectively. In the 20 patients on infliximab for injection monotherapy who were positive for anti-infliximab for injection antibodies at some point during the study through Week 50, 10 patients had an infusion reaction, one of which was serious. None of the 3 patients on infliximab for injection in combination with AZA who were positive for anti-infliximab for injection antibodies had an infusion reaction.
Patients who were antibody-positive were more likely to have higher rates of clearance, reduced efficacy and to experience an infusion reaction (see 8.2 Clinical Trial Adverse Reactions, Infusion-related Reactions) than were patients who were antibody negative. Antibody development was lower among adult rheumatoid arthritis, Crohn’s disease, and psoriatic arthritis patients receiving immunosuppressant therapies such as 6-mercaptopurine (6-MP), azathioprine (AZA), or methotrexate (MTX), although among patients with juvenile rheumatoid arthritis antibody development occurred in a high percentage of patients receiving 3 mg/kg infliximab for injection with concomitant MTX (see 8.2.1 Clinical Trial Adverse Reactions - Pediatrics, Juvenile Rheumatoid Arthritis).
With repeated dosing of infliximab for injection, serum concentrations of infliximab for injection were higher in rheumatoid arthritis patients who received concomitant MTX. In the 2 Phase 3 studies of psoriasis (EXPRESS and EXPRESS II), infliximab for injection was administered as induction followed by maintenance and without concomitant immunosuppressive therapy. In these studies, antibodies occurred in approximately 26.5% – 35.8% of patients who received 5 mg/kg every 8 week maintenance for 1 year and at higher rates (up to 1.4-fold) with other dose regimens (3 mg/kg q8 week, 3 mg/kg dosed as needed, and 5 mg/kg dosed as needed). Despite the increase in the rate of antibody formation, the infusion reaction rates in the 2 psoriasis Phase 3 studies (EXPRESS and EXPRESS II) in patients treated with 5 mg/kg induction followed by every 8 week maintenance for 1 year (14.1% and 23.0%, respectively) and serious infusion reaction rates (<1%) were similar to those observed in other study populations. In the Phase 3 study of psoriatic arthritis (IMPACT 2), where patients received 5 mg/kg with and without MTX, antibodies to infliximab for injection occurred in 15.4% of patients.
Immunogenicity tests are generally product-specific. Comparison of antibody rates to those from other products, or comparison of the incidence of antibodies between different tests without cross-validation is not appropriate.
Vaccinations
It is recommended that all patients, if possible, be brought up to date with all vaccinations in agreement with current vaccination guidelines prior to initiating Renflexis® therapy.
Live Vaccines/Therapeutic Infectious Agents
In patients receiving anti-TNF therapy, limited data are available on the response to vaccination with live vaccines or on the secondary transmission of infection by live vaccines. Use of live vaccines can result in clinical infections, including disseminated infections. The concurrent administration of live vaccines with Renflexis® is not recommended.
Infant exposure in utero
Fatal outcome due to disseminated Bacille Calmette-Guérin (BCG) infection has been reported in an infant who received BCG vaccine after in utero exposure to infliximab. A twelve month waiting period following birth is recommended before the administration of live vaccines to infants exposed in utero to infliximab. Administration of the live vaccine prior to 12 months of age might be considered if infliximab exposure was limited to the first trimester of pregnancy, or if infant infliximab serum levels are undetectable, or if there is a clear clinical benefit for the individual infant (see 7.1.1 Pregnant Women).
Infant exposure via breast milk
Administration of a live vaccine to a breastfed infant while the mother is receiving infliximab is not recommended unless infant infliximab serum levels are undetectable (see 7.1.2 Breast-feeding).
Therapeutic Infectious Agents
Other uses of therapeutic infectious agents such as live attenuated bacteria (e.g., BCG bladder instillation for the treatment of cancer) could result in clinical infections, including disseminated infections. It is recommended that therapeutic infectious agents not be given concurrently with Renflexis®.
Non-Live Vaccines
In a subset of patients from the ASPIRE study, a similar proportion of patients in each treatment group mounted an effective two-fold increase in titers to a polyvalent pneumococcal vaccine indicating that infliximab did not interfere with T-cell independent humoral immune responses.
Neurologic
Infliximab for injection and other agents that inhibit TNF have been associated with seizure, and new onset or exacerbation of clinical symptoms and/or radiographic evidence of central nervous system demyelinating disorders, including multiple sclerosis and optic neuritis, and peripheral demyelinating disorders, including Guillain-Barré syndrome. Prescribers should exercise caution in considering the use of Renflexis® in patients with these neurological disorders, and should consider discontinuation of Renflexis® if these disorders develop.
Health professionals should alert patients to the presence of the Patient Package Insert, provide this information to them, and ensure full understanding of the content.
Peri-Operative Considerations
There is limited safety experience of infliximab for injection treatment in patients who have undergone surgical procedures, including arthroplasty. The long half-life of infliximab for injection should be taken into consideration if a surgical procedure is planned. A patient who requires surgery while on Renflexis® should be closely monitored for infections, and appropriate actions should be taken.
Reproductive Health: Female and Male Potential
Fertility
Women of childbearing potential must use adequate contraception to prevent pregnancy and continue its use for at least 6 months after the last Renflexis® treatment.
It is not known whether Renflexis® can affect reproductive potential.
7.1 Special Populations
7.1.1 Pregnant Women
Available observational studies in pregnant women exposed to infliximab showed no increased risk of major malformations among live births as compared to those exposed to non-biologics. However, findings on other birth outcomes were not consistent across the studies. In one study conducted in a North America IBD pregnancy registry, infliximab exposure was not associated with increased rates of miscarriage/stillbirth, low birth weight, small for gestational age, or infant infection in the first year of life as compared to exposure to non-biologics. In another study in Northern Europe among IBD and non-IBD patients, exposure to infliximab in combination with immunosuppressants (mainly systemic corticosteroids and azathioprine), but not infliximab as monotherapy, was associated with increased rates of preterm birth, small for gestational age, low birth weight, and infant hospitalization for infection compared with non-biologic systemic treatment. Both studies have potential for confounding (e.g., the concomitant use of other medications or treatments was not controlled and disease severity was not assessed).
Since infliximab for injection does not cross-react with TNFα in species other than humans and chimpanzees, animal reproduction studies have not been conducted with Renflexis®. No evidence of maternal toxicity, embryotoxicity or teratogenicity was observed in a developmental toxicity study conducted in mice using an analogous antibody that selectively inhibits the functional activity of mouse TNFα. Doses of 10 to 15 mg/kg in pharmacodynamic animal models with the anti-TNF analogous antibody produced maximal pharmacologic effectiveness. Doses up to 40 mg/kg were shown to produce no adverse effects in animal reproduction studies.
As with other IgG antibodies, infliximab for injection crosses the placenta. Infliximab for injection has been detected in the serum of infants up to 12 months following birth. The clinical significance of low serum levels of infliximab on the immune status in infants is unknown. After in utero exposure to infliximab for injection, infants may be at increased risk of infection, including disseminated infection that can become fatal (see 7 WARNINGS AND PRECAUTIONS, Immune).
7.1.2 Breast-feeding
Infliximab has been detected at low levels in human milk and in infant serum via breast milk. While systemic exposure in a breastfed infant is expected to be low because infliximab is largely degraded in the gastrointestinal tract, the administration of live vaccines to a breastfed infant when the mother is receiving infliximab is not recommended unless infant infliximab serum levels are undetectable. Limited data from published literature reported that infants exposed to infliximab through breast milk had no increase in rates of infections and developed normally. The consideration of infliximab use during breast-feeding should take into account the importance of the drug to the mother and health benefits of breast-feeding for the infant.
7.1.3 Pediatrics
Pediatrics (6-17 years of age): Renflexis® is indicated for reducing signs and symptoms and for inducing and maintaining clinical remission in pediatric patients with moderately to severely active Crohn’s disease who have had an inadequate response to conventional therapy. Renflexis® is also indicated for reducing signs and symptoms, inducing and maintaining clinical remission and inducing mucosal healing in pediatric patients with moderately to severely active ulcerative colitis who have had an inadequate response to conventional therapy (i.e., aminosalicylate and/or corticosteroid and/or an immunosuppressant). In general, the adverse events in pediatric patients with Crohn’s disease or ulcerative colitis who received infliximab for injection were similar to those seen in adult patients with Crohn’s disease or ulcerative colitis respectively. It should be noted that in REACH, all patients were required to be on a stable dose of either 6-MP, AZA, or MTX. (See 1.1 Pediatrics; 8.2.1 Clinical Trial Adverse Reactions - Pediatrics, Crohn’s Disease and Ulcerative Colitis; 4 DOSAGE AND ADMINISTRATION and 14.5 Clinical trials – reference biologic drug. For additional pediatric information also see 7 WARNINGS AND PRECAUTIONS, Immune and 10.3 Pharmacokinetics).
The safety and efficacy of infliximab for injection has not been established in pediatric patients with Crohn’s disease <9 years of age or with ulcerative colitis <6 years of age. The safety and efficacy of infliximab for injection in pediatric patients with plaque psoriasis, psoriatic arthritis, ankylosing spondylitis, and juvenile rheumatoid arthritis have not been established.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): In rheumatoid arthritis clinical trials (ATTRACT) and in plaque psoriasis studies, no overall differences were observed in the effectiveness or safety in 181 patients with rheumatoid arthritis and 75 patients with plaque psoriasis, aged 65 or older compared to younger patients although the incidence of serious adverse events in patients aged 65 or older was higher in both infliximab for injection and control groups compared to younger patients. Mean duration of infliximab for injection treatment in this population (154) was approximately 50 weeks. In Crohn’s disease, ulcerative colitis, ankylosing spondylitis, and psoriatic arthritis studies, there were insufficient numbers of patients aged 65 and over to determine whether they responded differently from patients aged 18 to 64. There is a greater incidence of infections in the elderly population in general. The incidence of serious infections in infliximab for injection-treated patients 65 years and older was greater than in those under 65 years of age; therefore caution should be used in treating the elderly (see 8.2 Clinical Trial Adverse Reactions, Infections).
8 ADVERSE REACTIONS
The adverse drug reaction profiles reported in clinical studies that compared Renflexis® to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
The most common adverse drug reactions reported from both clinical trials and post-marketing reports are infections, allergic reactions and infusion-related reactions. Less common adverse drug reactions from these sources which may be serious and clinically relevant include hepatobiliary events (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic), demyelinating disorders (see 7 WARNINGS AND PRECAUTIONS, Neurologic), and lymphoma (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis). One of the most common reasons for discontinuation of treatment in clinical trials was infusion-related reactions (dyspnea, flushing, headache and rash) (see 7 WARNINGS AND PRECAUTIONS, Immune). Adverse events have been reported in a higher proportion of rheumatoid arthritis patients receiving the 10 mg/kg dose than the 3 mg/kg dose, however, no differences were observed in the frequency of adverse events between the 5 mg/kg dose and the 10 mg/kg dose in patients with Crohn’s disease or ulcerative colitis and between the 3 mg/kg and 5 mg/kg dose in patients with plaque psoriasis.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Description of Data Sources
The data described herein reflect the exposure infliximab for injection in 5561 patients in adequate and well-controlled studies. Infliximab for injection was studied in patients with rheumatoid arthritis (1304 patients exposed), juvenile rheumatoid arthritis (117 patients exposed), Crohn’s disease (1566 patients exposed, including 1427 adult and 139 pediatric patients), ulcerative colitis (544 patients exposed, including 484 adults and 60 children), plaque psoriasis (1373 patients exposed), psoriatic arthritis (293 patients exposed), ankylosing spondylitis (347 patients exposed) and other conditions (17 patients exposed), primarily in double-blind, placebo-controlled trials. In general, integration of data in the following sections is based on clinical trials in rheumatoid arthritis and adult Crohn’s disease. See 14.5 Clinical trials
- reference biologic drug for a description of the individual studies conducted in each indication.
Relative Frequency of Adverse Drug Reactions
Adverse events occurring at a frequency of at least 5% in infliximab for injection-treated adult patients with rheumatoid arthritis, Crohn’s disease, ankylosing spondylitis, plaque psoriasis, psoriatic arthritis, and ulcerative colitis are shown in Table 3. Adverse events occurring at a frequency of at least 5% in infliximab for injection-treated pediatric patients with Crohn’s disease or ulcerative colitis are shown in Table 4. Adverse events occurring at a frequency of ≥1% to <5% in infliximab for injection-treated adult patients are shown in Table 5. Adverse events occurring at a frequency of ≥1% to <5% in infliximab for injection-treated pediatric patients with Crohn’s disease or ulcerative colitis are shown in Table 6. Adverse events in a juvenile rheumatoid arthritis (JRA) trial are set forth in the section 8.2.1 Clinical Trial Adverse Reactions
- Pediatrics, Juvenile Rheumatoid Arthritis. In general, the adverse events in pediatric patients with Crohn’s disease or ulcerative colitis who received infliximab for injection were similar in frequency and type to those seen in adult patients with Crohn’s disease or ulcerative colitis respectively. Differences from adults and other special considerations are discussed in the section 8.2.1 Clinical Trial Adverse Reactions - Pediatrics, Crohn’s Disease and Ulcerative Colitis.
Table 3. Number of patients with 1 or more adverse events (with frequency of ≥ 5%) by WHOART system-organ class and preferred term; treated patients ≥ 18 years of age
RA studies CD studies AS studies UC studies PsO studies PsA studies PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX Treated
patients ≥ 18
years of
agea,b
427 1304 217 1427 76 275 248 493 334 1373 98 191
Avg duration
of follow-up
(weeks)
52.0 59.9 29.8 44.8 25.3 87.8 31.9 40.5 18.1 41.9 20.2 42.8
Patients with
1 or more
adverse
events
353
(82.7%)
1198
(91.9%)
179
(82.5%)
1297 (90.9%)
57
(75.0%)
268
(97.5%)
199
(80.2%)
425
(86.2%)
210 (62.9%)
1209 (88.1%)
66
(67.3%)
162 (84.8%)
System-organ class/preferred term
Respiratory system disorders
URTI 22% 29% 15% 23% 14% 49% 17% 18% 16% 25% 13% 24% Pharyngitis 7% 12% 6% 13% 5% 20% 6% 10% 4% 9% 4% 10% Sinusitis 7% 13% 6% 9% 1% 11% 5% 9% 3% 8% 4% 11% Coughing 7% 12% 6% 7% 3% 13% 4% 6% 1% 5% 1% 7% Rhinitis 4% 8% 5% 6% 5% 21% 2% 4% 1% 6% 2% 4% Bronchitis 8% 9% 3% 5% 1% 8% 3% 4% 2% 4% 3% 6% Gastro-intestinal system disorders
Nausea 19% 19% 25% 21% 9% 11% 9% 11% 4% 8% 6% 5% Abdominal
pain
7% 12% 17% 24% 4% 16% 13% 12% 1% 4% 2% 5%
Diarrhea 11% 11% 7% 9% 5% 20% 5% 5% 2% 5% 3% 2% Vomiting 6% 7% 13% 12% 4% 6% 7% 6% 1% 3% 2% 1% Dyspepsia 6% 9% 2% 6% 4% 4% 2% 3% 1% 2% 2% 2% Skin and appendages disorders
Rash 5% 9% 6% 10% 7% 10% 8% 8% 1% 2% 0% 2% Pruritus 2% 6% 3% 6% 7% 12% 4% 6% 4% 9% 3% 6% Body as a whole-general disorders
Pain 7% 7% 6% 13% 5% 29% 12% 11% 5% 10% 1% 4% Fatigue 6% 8% 13% 14% 4% 15% 8% 10% 2% 7% 3% 4% Musculo-skeletal system disorders
Arthralgia 6% 7% 8% 15% 1% 8% 10% 15% 2% 10% 2% 4%
| RA studies | CD studies | AS studies | UC studies | PsO studies | PsA studies | |||||||
| PBO | IFX | PBO | IFX | PBO | IFX | PBO | IFX | PBO | IFX | PBO | IFX | |
| Back pain | 4% | 7% | 6% | 8% | 3% | 12% | 8% | 4% | 3% | 5% | 6% | 9% |
| Myalgia | 3% | 3% | 4% | 6% | 3% | 4% | 5% | 6% | 1% | 6% | 0% | 2% |
| Central & peripheral nervous system disorders | ||||||||||||
| Headache | 12% | 17% | 15% | 23% | 11% | 20% | 18% | 19% | 8% | 17% | 5% | 10% |
| Dizziness | 6% | 7% | 6% | 10% | 4% | 10% | 5% | 6% | 2% | 4% | 4% | 4% |
| Resistance mechanism disorders | ||||||||||||
| Fever | 4% | 7% | 11% | 11% | 0% | 8% | 9% | 10% | 1% | 4% | 1% | 2% |
a Rheumatoid Arthritis Studies include C0168T07, C0168T09, C0168T14, C0168T15, C0168T18, C0168T22, and C0168T29. Crohn's Disease Studies include C0168T08, C0168T11, C0168T16, C0168T20, C0168T21, C0168T26, and C0168T67. Ankylosing Spondylitis Studies include C0168T51. Ulcerative Colitis Studies include C0168T12, C0168T37 (through Week 54), and C0168T46 (through Week 54 including 24-week study extension). Psoriasis Studies include C0168T31, C0168T38, and C0168T44. Psoriatic Arthritis Studies include C0168T50. b The adverse events included in this table are determined by the frequency of events in the combined infliximab for injection group over all indications in this table. Percentages are rounded to an integer value after the adverse event frequency is determined. IFX – Infliximab; PBO – Placebo; URTI – Upper respiratory tract infection. | ||||||||||||
Table 4. Number of patients with 1 or more adverse events (with frequency of ≥ 5%) by WHOART system-organ class and preferred term; treated patients < 18 years of age in ulcerative colitis and Crohn's disease studies
| CD studiesa | UC studiesb | |||
| Placebo | Infliximab for injection 5 mg/kg | Placebo | Infliximab for injection 5 mg/kg | |
| Treated patients < 18 years of age in ulcerative colitis and Crohn's disease studiesc | 0 | 139 | 0 | 60 |
| Avg duration of follow-up (weeks) | N/A | 44.1 | N/A | 38.0 |
| Patients with 1 or more adverse events | 0 (N/A) | 125 (89.9%) | 0 (N/A) | 57 (95.0%) |
| System-organ class/preferred term | ||||
| Gastro-intestinal system disorders | ||||
| Colitis ulcerative | N/A | 0% | N/A | 47% |
| Abdominal pain | N/A | 22% | N/A | 13% |
| Vomiting | N/A | 22% | N/A | 8% |
| Nausea | N/A | 19% | N/A | 5% |
| Blood in stool | N/A | 7% | N/A | 3% |
| Diarrhea | N/A | 13% | N/A | 3% |
| Crohn's disease | N/A | 27% | N/A | 0% |
| Respiratory system disorders | ||||
| Upper respiratory tract infection | N/A | 29% | N/A | 23% |
| Pharyngitis | N/A | 19% | N/A | 18% |
| Coughing | N/A | 11% | N/A | 10% |
| Sinusitis | N/A | 8% | N/A | 5% |
| Rhinitis | N/A | 8% | N/A | 2% |
| Resistance mechanism disorders | ||||
| Fever | N/A | 17% | N/A | 13% |
| Skin and appendages disorders | ||||
| Rash | N/A | 10% | N/A | 5% |
| Pruritus | N/A | 9% | N/A | 2% |
| Body as a whole-general disorders | ||||
| Pain | N/A | 9% | N/A | 8% |
| Central &peripheral nervous system disorders | ||||
| Headache | N/A | 31% | N/A | 13% |
| Musculo-skeletal system disorders | ||||
| Arthralgia | N/A | 9% | N/A | 2% |
| Red blood cell disorders | ||||
| Anemia | N/A | 9% | N/A | 10% |
| White cell and res disorders | ||||
| Neutropenia | N/A | 6% | N/A | 3% |
| Leukopenia | N/A | 8% | N/A | 2% |
| Vascular (extracardiac) disorders | ||||
| Flushing | N/A | 8% | N/A | 3% |
a CD Studies include C0168T23, C0168T47 (through Week 54), and C0168T55. b UC Study include C0168T72. c The adverse events included in this table are determined by the frequency of events in the combined infliximab for injection group. Percentages are rounded to an integer value after the adverse event frequency is determined. | ||||
Table 5. Number of patients with 1 or more adverse events (with frequency of ≥ 1% to < 5%) by WHOART system-organ class and preferred term; treated patients ≥ 18 years of age
RA studies CD studies AS studies UC studies PsO studies PsA studies PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX Treated patients ≥
18 years of agea,b
427 1304 217 1427 76 275 248 493 334 1373 98 191
Avg duration of
follow-up (weeks)
52.0 59.9 29.8 44.8 25.3 87.8 31.9 40.5 18.1 41.9 20.2 42.8
Patients with 1 or
more adverse
events
353
(82.7%)
1198
(91.9%)
179
(82.5%)
1297
(90.9%)
57
(75.0%)
268
(97.5%)
199
(80.2%)
425
(86.2%)
210
(62.9%)
1209 (88.1%)
66 (67.3%)
162 (84.8%)
System-organ class/preferred term
Respiratory system disorders
Dyspnea 2% 5% 1% 4% 3% 5% 2% 3% 1% 3% 1% 3% Pneumonia 1% 4% 1% 1% 0% 1% 0% 2% 0% 1% 0% 3% Respiratory tract
allergic reaction 1% 2% 0% 1% 0% 1% 0% 1% 0% 2% 1% 2% Epistaxis 1% 1% 0% 1% 0% 2% 0% 1% 0% 1% 0% 1% Gastro-intestinal system disorders
Gastroenteritis 3% 4% 6% 4% 4% 7% 2% 3% 1% 3% 3% 1% Crohn's disease 0% 0% 12% 13% 0% 0% 0% 0% 0% 0% 0% 0% Stomatitis
ulcerative
5% 6% 1% 3% 1% 1% 1% 0% 1% 1% 1% 1%
Flatulence 1% 2% 3% 6% 0% 1% 2% 4% 0% 0% 0% 1% Constipation 3% 2% 2% 4% 1% 3% 1% 2% 0% 1% 2% 0% Gastroesophageal
reflux
1% 2% 0% 2% 0% 3% 2% 1% 0% 1% 1% 2%
Colitis ulcerative 0% 0% 0% 0% 0% 0% 25% 16% 0% 0% 0% 0% Tooth ache 0% 1% 1% 2% 0% 1% 0% 1% 1% 2% 0% 1% Anorexia 1% 1% 2% 2% 0% 0% 1% 1% 0% 0% 0% 1% Blood in stool 1% 1% 1% 2% 0% 1% 1% 1% 0% 0% 0% 0% Intestinal
obstruction
0% 0% 2% 4% 0% 0% 0% 0% 0% 0% 0% 0%
Skin and appendages disorders
Urticaria 1% 4% 0% 2% 0% 2% 0% 1% 1% 4% 0% 4% Sweating
increased
0% 2% 3% 3% 5% 4% 3% 3% 0% 2% 0% 2%
Alopecia 2% 3% 2% 3% 0% 1% 1% 3% 1% 1% 2% 3% RA studies CD studies AS studies UC studies PsO studies PsA studies PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX Dermatitis 1% 2% 0% 2% 1% 7% 2% 1% 0% 2% 0% 1% Dermatitis fungal 1% 3% 1% 1% 0% 5% 3% 1% 0% 2% 1% 2% Psoriasis 0% 0% 1% 1% 1% 5% 1% 0% 7% 5% 2% 4% Eczema 1% 2% 0% 3% 0% 3% 3% 1% 1% 1% 0% 1% Acne 0% 1% 1% 3% 0% 3% 1% 2% 1% 1% 0% 0% Skin dry 0% 1% 1% 2% 0% 7% 1% 3% 1% 1% 0% 0% Skin wound 2% 2% 1% 1% 0% 2% 0% 1% 0% 2% 0% 1% Erythema 0% 2% 1% 1% 0% 3% 1% 1% 0% 1% 1% 0% Rash
erythematous
1% 1% 0% 1% 1% 5% 0% 1% 0% 0% 0% 1%
Folliculitis 0% 1% 1% 1% 0% 1% 0% 1% 1% 1% 0% 0% Body as a whole-general disorders
Chest pain 3% 4% 4% 5% 1% 6% 2% 3% 0% 4% 2% 4% Edema peripheral 4% 4% 2% 5% 1% 4% 4% 4% 2% 3% 0% 3% Chills 2% 3% 1% 2% 3% 3% 2% 4% 1% 3% 0% 1% Infusion syndrome 0% 2% 0% 2% 1% 3% 0% 2% 0% 3% 0% 2% Wound 1% 1% 0% 1% 1% 3% 0% 1% 0% 3% 1% 3% Hot flushes 0% 2% 1% 2% 1% 3% 2% 1% 0% 1% 0% 2% Allergic reaction 0% 1% 1% 2% 0% 5% 0% 2% 1% 1% 1% 1% Asthenia 1% 1% 0% 3% 0% 2% 0% 1% 0% 1% 1% 1% Reaction
unevaluable
0% 1% 2% 2% 0% 2% 1% 1% 1% 1% 0% 0%
Musculo-skeletal system disorders
Arthritis 1% 1% 2% 4% 5% 14% 1% 1% 3% 7% 5% 5% Bone fracture 3% 4% 0% 1% 0% 4% 0% 1% 1% 1% 0% 4% Skeletal muscle
strain
2% 2% 0% 1% 0% 1% 1% 0% 1% 3% 1% 2%
Tendinitis 2% 0% 0% 1% 1% 5% 1% 1% 0% 1% 2% 1% Central &peripheral nervous system disorders
Paresthesia 2% 3% 2% 3% 0% 7% 3% 3% 1% 3% 0% 0% Muscle
contractions
involuntary
2% 4% 2% 2% 1% 3% 3% 2% 0% 2% 1% 1%
Hypesthesia 1% 2% 1% 2% 4% 3% 1% 1% 0% 2% 1% 1% Migraine 1% 1% 1% 2% 0% 1% 0% 1% 0% 1% 0% 1% Vertigo 2% 2% 0% 1% 3% 1% 1% 1% 0% 1% 1% 2% Resistance mechanism disorders
RA studies CD studies AS studies UC studies PsO studies PsA studies PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX PBO IFX Abscess 3% 4% 4% 9% 3% 6% 3% 3% 1% 3% 2% 2% Flu syndrome 3% 4% 1% 6% 1% 8% 2% 4% 1% 3% 0% 3% Moniliasis 3% 5% 0% 5% 0% 5% 2% 3% 0% 1% 0% 1% Influenza-like
symptoms
0% 2% 2% 3% 1% 2% 2% 3% 1% 2% 0% 2%
Herpes simplex 1% 2% 2% 2% 0% 9% 2% 1% 1% 2% 1% 4% Infection 2% 3% 0% 2% 3% 4% 1% 1% 1% 2% 0% 1% Influenza 1% 2% 2% 3% 1% 1% 2% 2% 1% 2% 0% 1% Cellulitis 1% 2% 0% 1% 0% 2% 0% 1% 1% 1% 1% 3% Herpes zoster 1% 1% 0% 1% 0% 0% 0% 1% 1% 1% 0% 2% Infection bacterial 1% 1% 2% 1% 0% 1% 0% 0% 0% 1% 0% 2% Psychiatric disorders
Insomnia 4% 4% 3% 6% 1% 4% 2% 4% 1% 2% 1% 0% Depression 5% 5% 2% 4% 0% 4% 2% 3% 1% 3% 2% 3% Anxiety 1% 3% 1% 3% 1% 2% 3% 2% 0% 2% 1% 0% Liver and biliary system disorders
Sgpt increased 4% 5% 1% 3% 5% 12% 1% 1% 1% 4% 1% 8% Sgot increased 2% 3% 1% 2% 3% 9% 0% 1% 1% 3% 2% 5% Hepatic enzymes
increased
3% 4% 1% 1% 0% 2% 0% 1% 0% 4% 0% 2%
Hepatic function
abnormal
1% 2% 2% 1% 0% 2% 0% 0% 0% 1% 1% 2%
Vascular (extracardiac) disorders
Flushing 0% 3% 1% 2% 3% 4% 1% 2% 0% 5% 0% 3% Ecchymosis 2% 4% 0% 2% 0% 2% 1% 1% 0% 2% 0% 1% Hemorrhoids 1% 1% 0% 2% 1% 3% 3% 1% 0% 0% 0% 1% Urinary system disorders
Urinary tract
infection
5% 7% 3% 4% 0% 2% 2% 2% 1% 2% 4% 3%
Metabolic and nutritional disorders
Hypokalemia 0% 2% 1% 4% 0% 0% 0% 1% 0% 0% 0% 1% Weight increase 2% 2% 0% 0% 1% 3% 0% 0% 0% 1% 0% 0% Cardiovascular disorders, general
Hypertension 5% 6% 2% 3% 5% 8% 2% 2% 3% 4% 2% 3% Hypotension 1% 2% 0% 2% 1% 3% 0% 2% 0% 1% 0% 2% Eye and vision disorders
Conjunctivitis 2% 4% 2% 4% 1% 4% 3% 1% 0% 1% 1% 1%
| RA studies | CD studies | AS studies | UC studies | PsO studies | PsA studies | |||||||
| PBO | IFX | PBO | IFX | PBO | IFX | PBO | IFX | PBO | IFX | PBO | IFX | |
| Vision abnormal | 1% | 2% | 1% | 2% | 0% | 4% | 2% | 1% | 0% | 1% | 0% | 2% |
| Ear and hearing disorders | ||||||||||||
| Otitis | 0% | 2% | 1% | 1% | 0% | 2% | 1% | 1% | 0% | 1% | 0% | 0% |
| White cell and res disorders | ||||||||||||
| Leukopenia | 1% | 2% | 3% | 2% | 0% | 2% | 0% | 2% | 0% | 1% | 0% | 1% |
| Lymphadenopathy | 0% | 1% | 1% | 2% | 0% | 2% | 1% | 1% | 0% | 1% | 0% | 1% |
| Neutropenia | 0% | 1% | 0% | 1% | 0% | 3% | 0% | 0% | 0% | 1% | 0% | 3% |
| Red blood cell disorders | ||||||||||||
| Anemia | 4% | 4% | 4% | 4% | 1% | 4% | 10% | 5% | 0% | 1% | 0% | 0% |
| Heart rate and rhythm disorders | ||||||||||||
| Tachycardia | 2% | 2% | 0% | 1% | 1% | 1% | 2% | 1% | 1% | 1% | 1% | 1% |
| Palpitation | 1% | 2% | 0% | 1% | 0% | 3% | 1% | 1% | 0% | 1% | 0% | 1% |
| Administration/application site disorders | ||||||||||||
| Injection site infiltration | 3% | 2% | 0% | 1% | 0% | 0% | 1% | 0% | 0% | 2% | 0% | 0% |
| Collagen disorders | ||||||||||||
Arthritis rheumatoid | 6% | 7% | 0% | 0% | 0% | 0% | 0% | 0% | 0% | 0% | 0% | 0% |
a Rheumatoid Arthritis Studies include C0168T07, C0168T09, C0168T14, C0168T15, C0168T18, C0168T22, and C0168T29. Crohn's Disease Studies include C0168T08, C0168T11, C0168T16, C0168T20, C0168T21, C0168T26, and C0168T67. Ankylosing Spondylitis Studies include C0168T51. Ulcerative Colitis Studies include C0168T12, C0168T37 (through Week 54), and C0168T46 (through Week 54 including 24-week study extension). Psoriasis Studies include C0168T31, C0168T38, and C0168T44. Psoriatic Arthritis Studies include C0168T50. b The adverse events included in this table are determined by the frequency of events in the combined infliximab for injection group over all indications in this table. Percentages are rounded to an integer value after the adverse event frequency is determined. IFX – Infliximab; PBO – Placebo. | ||||||||||||
Table 6. Number of patients with 1 or more adverse events (with frequency of ≥ 1% to < 5%) by
WHOART system-organ class and preferred term; treated patients < 18 years of age in ulcerative colitis and Crohn's disease studies
| CD studiesa | UC studiesb | |||
| Placebo | Infliximab for injection 5 mg/kg | Placebo | Infliximab for injection 5 mg/kg | |
| Treated patients < 18 years of age in ulcerative colitis and Crohn's disease studiesc | 0 | 139 | 0 | 60 |
| Avg duration of follow-up (weeks) | N/A | 44.1 | N/A | 38.0 |
| Patients with 1 or more adverse events | 0 (N/A) | 125 (89.9%) | 0 (N/A) | 57 (95.0%) |
| System-organ class/preferred term | ||||
| Gastro-intestinal system disorders | ||||
| Stomatitis ulcerative | N/A | 2% | N/A | 5% |
| Diarrhea bloody | N/A | 1% | N/A | 2% |
| Pancreatitis | N/A | 2% | N/A | 2% |
| Anal fistula | N/A | 3% | N/A | 0% |
| Anorexia | N/A | 3% | N/A | 0% |
| Constipation | N/A | 6% | N/A | 0% |
| Dyspepsia | N/A | 6% | N/A | 0% |
| Dysphagia | N/A | 1% | N/A | 0% |
| Enterocolitis | N/A | 3% | N/A | 0% |
| Flatulence | N/A | 4% | N/A | 0% |
| Gastroenteritis | N/A | 5% | N/A | 0% |
| Hemorrhage rectum | N/A | 1% | N/A | 0% |
| Intestinal obstruction | N/A | 1% | N/A | 0% |
| Intestinal stenosis | N/A | 2% | N/A | 0% |
| Oral pain | N/A | 1% | N/A | 0% |
| Proctalgia | N/A | 2% | N/A | 0% |
| Tooth ache | N/A | 2% | N/A | 0% |
| Respiratory system disorders | ||||
| Dyspnea | N/A | 4% | N/A | 5% |
| Bronchitis | N/A | 5% | N/A | 3% |
| Asthma | N/A | 1% | N/A | 2% |
| Respiratory tract allergic reaction | N/A | 4% | N/A | 2% |
| Bronchospasm | N/A | 1% | N/A | 0% |
| Epistaxis | N/A | 3% | N/A | 0% |
| Pneumonia | N/A | 2% | N/A | 0% |
| Resistance mechanism disorders | ||||
| Influenza | N/A | 3% | N/A | 5% |
| Cellulitis | N/A | 1% | N/A | 3% |
| Infection | N/A | 3% | N/A | 3% |
| Influenza-like symptoms | N/A | 1% | N/A | 3% |
| Moniliasis | N/A | 4% | N/A | 3% |
| Herpes simplex | N/A | 1% | N/A | 2% |
| Herpes zoster | N/A | 1% | N/A | 2% |
| Infection bacterial | N/A | 5% | N/A | 2% |
| Infection viral | N/A | 6% | N/A | 2% |
| Abscess | N/A | 4% | N/A | 0% |
| Flu syndrome | N/A | 5% | N/A | 0% |
| Infectious mononucleosis | N/A | 1% | N/A | 0% |
| Skin and appendages disorders | ||||
| CD studiesa | UC studiesb | |||
| Placebo | Infliximab for injection 5 mg/kg | Placebo | Infliximab for injection 5 mg/kg | |
| Alopecia | N/A | 1% | N/A | 3% |
| Eczema | N/A | 4% | N/A | 3% |
| Acne | N/A | 2% | N/A | 2% |
| Dermatitis | N/A | 1% | N/A | 2% |
| Onychocryptosis | N/A | 1% | N/A | 2% |
| Skin lesion | N/A | 3% | N/A | 2% |
| Sweating increased | N/A | 1% | N/A | 2% |
| Urticaria | N/A | 1% | N/A | 2% |
| Verruca | N/A | 2% | N/A | 2% |
| Cracking of skin | N/A | 4% | N/A | 0% |
| Dermatitis contact | N/A | 2% | N/A | 0% |
| Dermatitis fungal | N/A | 2% | N/A | 0% |
| Rash erythematous | N/A | 2% | N/A | 0% |
| Skin dry | N/A | 2% | N/A | 0% |
| Skin hypertrophy | N/A | 1% | N/A | 0% |
| Body as a whole-general disorders | ||||
| Chest pain | N/A | 3% | N/A | 3% |
| Fatigue | N/A | 5% | N/A | 3% |
| Chills | N/A | 1% | N/A | 2% |
| Cyst (type unknown) | N/A | 1% | N/A | 2% |
| Edema | N/A | 1% | N/A | 2% |
| Edema peripheral | N/A | 1% | N/A | 2% |
| Reaction unevaluable | N/A | 1% | N/A | 2% |
| Allergic reaction | N/A | 4% | N/A | 0% |
| Asthenia | N/A | 1% | N/A | 0% |
| Central &peripheral nervous system disorders | ||||
| Hypesthesia | N/A | 0% | N/A | 3% |
| Dizziness | N/A | 6% | N/A | 2% |
| Muscle contractions involuntary | N/A | 1% | N/A | 2% |
| Migraine | N/A | 1% | N/A | 0% |
| Paresthesia | N/A | 2% | N/A | 0% |
| Musculo-skeletal system disorders | ||||
| Back pain | N/A | 2% | N/A | 3% |
| Bone development abnormal | N/A | 1% | N/A | 2% |
| Joint swelling | N/A | 1% | N/A | 2% |
| Sprain | N/A | 1% | N/A | 2% |
| Bone fracture | N/A | 6% | N/A | 0% |
| Myalgia | N/A | 4% | N/A | 0% |
| Red blood cell disorders | ||||
| Anemia iron deficiency | N/A | 1% | N/A | 2% |
| Psychiatric disorders | ||||
| Anxiety | N/A | 2% | N/A | 2% |
| Depression | N/A | 2% | N/A | 2% |
| Insomnia | N/A | 4% | N/A | 2% |
| Thinking abnormal | N/A | 1% | N/A | 2% |
| Irritability | N/A | 1% | N/A | 0% |
| Somnolence | N/A | 3% | N/A | 0% |
| Suicide attempt | N/A | 1% | N/A | 0% |
| Urinary system disorders | ||||
| Urinary tract infection | N/A | 1% | N/A | 8% |
| Dysuria | N/A | 1% | N/A | 0% |
| CD studiesa | UC studiesb | |||
| Placebo | Infliximab for injection 5 mg/kg | Placebo | Infliximab for injection 5 mg/kg | |
| Liver and biliary system disorders | ||||
| Hepatic enzymes increased | N/A | 2% | N/A | 3% |
| Hepatic function abnormal | N/A | 2% | N/A | 2% |
| Sgot increased | N/A | 1% | N/A | 2% |
| Sgpt increased | N/A | 1% | N/A | 2% |
| White cell and res disorders | ||||
| Neutrophilia | N/A | 1% | N/A | 2% |
| Eosinophilia | N/A | 3% | N/A | 0% |
| Lymphadenopathy | N/A | 1% | N/A | 0% |
| Monocytosis | N/A | 1% | N/A | 0% |
| Eye and vision disorders | ||||
| Conjunctivitis | N/A | 4% | N/A | 3% |
| Eye pain | N/A | 3% | N/A | 0% |
| Metabolic and nutritional disorders | ||||
| Dehydration | N/A | 2% | N/A | 0% |
| Weight decrease | N/A | 3% | N/A | 0% |
| Vascular (extracardiac) disorders | ||||
| Ecchymosis | N/A | 4% | N/A | 0% |
| Cardiovascular disorders, general | ||||
| Hypotension | N/A | 1% | N/A | 0% |
| Syncope | N/A | 2% | N/A | 0% |
| Collagen disorders | ||||
| Antinuclear factor test positive | N/A | 3% | N/A | 2% |
| Ear and hearing disorders | ||||
| Otitis | N/A | 1% | N/A | 2% |
| Otitis media | N/A | 2% | N/A | 2% |
| Earache | N/A | 2% | N/A | 0% |
| Platelet, bleeding & clotting disorders | ||||
| Thrombocythemia | N/A | 1% | N/A | 3% |
| Thrombocytopenia | N/A | 1% | N/A | 0% |
| Heart rate and rhythm disorders | ||||
| Palpitation | N/A | 1% | N/A | 2% |
| Administration/application site disorders | ||||
| Injection site infiltration | N/A | 4% | N/A | 0% |
| Reproductive disorders | ||||
| Dysmenorrhea | N/A | 2% | N/A | 0% |
| Ovarian cyst | N/A | 1% | N/A | 0% |
a CD Studies include C0168T23, C0168T47 (through Week 54), and C0168T55. b UC Study include C0168T72. c The adverse events included in this table are determined by the frequency of events in the combined infliximab for injection group. Percentages are rounded to an integer value after the adverse event frequency is determined. | ||||
Infusion-related Reactions
Acute infusion reactions
An infusion reaction was defined in clinical trials as any adverse event occurring during an infusion or within 1 hour after an infusion. In Phase 3 clinical studies, 18% of infliximab for injection-treated patients experienced an infusion reaction compared with 5% of placebo-treated patients. Of infliximab for injection-treated patients who had an infusion reaction during the induction period, 27% experienced an infusion reaction during the maintenance period. Of patients who did not have an infusion reaction during the induction period, 9% experienced an infusion reaction during the maintenance period. Approximately 3% of patients discontinued infliximab for injection because of infusion reactions, and all patients recovered with treatment and/or discontinuation of infusion.
In clinical trials, approximately 3% of infliximab for injection infusions were accompanied by nonspecific symptoms such as fever or chills, 1% were accompanied by cardiopulmonary reactions (primarily chest pain, hypotension, hypertension or dyspnea), <1% were accompanied by pruritus, urticaria, or the combined symptoms of pruritus/urticaria and cardiopulmonary reactions. Serious infusion reactions occurred in less than 1% of patients and included anaphylaxis, convulsions, erythematous rash and hypotension.
Infliximab for injection infusions beyond the initial infusion were not associated with a higher incidence of reactions. In psoriatic arthritis (IMPACT 2), infusion reactions were reported in 12% of infliximab for injection-treated patients compared with 7% of placebo-treated patients. Among the 1376 infliximab for injection infusions, 2% of these led to an infusion reaction. In plaque psoriasis, infusion reactions were reported in 22% of infliximab for injection-treated patients compared with 5% of placebo-treated patients. Among the 8366 infliximab for injection infusions, 5% of these led to an infusion reaction. In the ankylosing spondylitis study ASSERT, infusion reactions were reported in 19% of infliximab for injection-treated patients compared with 9% of placebo-treated patients. Among the 4257 infliximab for injection infusions, 2% of these led to an infusion reaction.
In a clinical study of patients with early rheumatoid arthritis (ASPIRE), 66% of all treated patients (686 out of 1040) received at least one shortened infusion of 90 minutes or less and 44% of the patients (454 out of 1040) received at least one shortened infusion of 60 minutes or less. Of the infliximab for injection-treated patients who received at least one shortened infusion of 90 minutes or less at the dose of 3 mg/kg, infusion-related reactions occurred in 19% (48/248) of patients and serious infusion reactions occurred in 0.4% (1/248) of patients. Of the infliximab for injection-treated patients who received at least one shortened infusion of 90 minutes or less at the dose of 6 mg/kg, infusion related reactions occurred in 11% (26/246) of patients and serious infusion reactions occurred in 0.4% (1/246) of patients. Shortened infusions at doses >6 mg/kg have not been studied (see 14.5 Clinical trials – reference biologic drug, Rheumatoid Arthritis).
In the UC studies ACT 1 and ACT 2 through Week 30, the proportion of subjects with infusion reactions was comparable in the placebo and combined infliximab for injection treatment groups. Through Week 54, the proportion of subjects with infusion reactions rose and was greater in the combined infliximab for injection treatment group than in the placebo treatment group (13.4% versus 9.4%, respectively). A greater proportion of subjects in the 10 mg/kg than in the 5 mg/kg infliximab for injection treatment group (16.1% versus 10.7%) experienced an infusion reaction.
In a clinical study of patients with Crohn’s disease (SONIC), infusion-related reactions occurred in 17% of patients receiving infliximab for injection monotherapy, 5% of patients receiving infliximab for injection in combination with azathioprine (AZA) and 6% of patients receiving AZA monotherapy. One patient experienced a serious infusion reaction with infliximab for injection monotherapy.
Patients who became positive for antibodies to infliximab for injection were more likely to develop infusion reactions than were those who were negative (approximately 3-fold). Use of concomitant immunosuppressant agents appeared to reduce the frequency of antibodies to infliximab for injection and infusion reactions (see 7 WARNINGS AND PRECAUTIONS, Immune and 9 DRUG INTERACTIONS).
In post-marketing experience, cases of anaphylactic-like reactions, including laryngeal/pharyngeal edema, severe bronchospasm, and seizure have been associated with infliximab for injection administration (see 7 WARNINGS AND PRECAUTIONS, Neurologic). Cases of transient visual loss occurring during or within 2 hours of infliximab for injection infusion have been reported. Cerebrovascular accidents, myocardial ischemia/infarction (some fatal), and arrhythmia occurring within 24 hours of initiation of infusion have also been reported.
Infusion reactions following readministration of infliximab for injection
In rheumatoid arthritis, Crohn’s disease and psoriasis clinical trials, readministration of infliximab for injection after a period of no treatment resulted in a higher incidence of infusion reactions relative to regular maintenance treatment.
In a clinical trial of patients with moderate to severe psoriasis designed to assess the efficacy of long-term maintenance therapy versus re-treatment with an induction cycle of infliximab for injection, 4% (8/219) of patients in the intermittent therapy arm experienced serious infusion reactions versus <1% (1/222) in the maintenance therapy arm. Patients enrolled in this trial did not receive any concomitant immunosuppressant therapy. Intermittent therapy in this trial was defined as the readministration of an induction cycle (maximum of four infusions at 0, 2, 6, and 14 weeks) of infliximab for injection upon disease flare after a period of no treatment. In this study, the majority of serious infusion reactions occurred during the second infusion at Week 2. Symptoms included, but were not limited to, dyspnea, urticaria, facial edema, and hypotension. In all cases, infliximab for injection treatment was discontinued and/or other treatment instituted with complete resolution of signs and symptoms (see 7 WARNINGS AND PRECAUTIONS, Immune ).
Delayed hypersensitivity/Reactions following readministration of infliximab for injection
In a clinical study where 37 of 41 patients with Crohn’s disease were retreated with infliximab for injection following a 2 to 4 year period without infliximab for injection treatment, 10 patients experienced adverse events manifesting 3 to 12 days following infusion of which 6 were considered serious. Signs and symptoms included myalgia and/or arthralgia with fever and/or rash, with some patients also experiencing pruritus, facial, hand or lip edema, dysphagia, urticaria, sore throat, and headache. Patients experiencing these adverse events had not experienced infusion-related adverse events associated with their initial infliximab for injection therapy. Of these patients, adverse events occurred in 9 of 23 (39%) who had received liquid formulation which is no longer in use and 1 of 14 (7%) who received lyophilized formulation. The clinical data are not adequate to determine if occurrence of these reactions is due to differences in formulation. Patients’ signs and symptoms improved substantially or resolved with treatment in all cases. There are insufficient data on the incidence of these events after drug-free intervals of 1 to 2 years. These events have been observed only infrequently in clinical studies and post-marketing surveillance with retreatment intervals up to 1 year.
In 3 other psoriasis studies, 1% (15/1373) of patients experienced a possible delayed hypersensitivity reaction with symptoms of arthralgia, myalgia, fever, and rash, often early in the treatment course following infliximab for injection infusions. There were no possible delayed hypersensitivity reactions identified in the psoriatic arthritis study (IMPACT 2) (see 7 WARNINGS AND PRECAUTIONS, Immune).
Infections
In infliximab for injection clinical studies, primarily of RA and CD, treated infections were reported in 36% of infliximab for injection-treated patients (average of 53 weeks of follow-up) and in 28% of placebo-treated patients (average of 47 weeks of follow-up). In the ATTRACT1† study, 60% of infliximab for injection-treated RA patients (average of 97 weeks of follow-up) had treated infections reported vs. 43% of placebo-treated patients (average of 75 weeks of follow-up); treated infections were more common with higher doses of infliximab for injection. In the ASPIRE2† study, 37% of infliximab for injection-treated RA patients (average of 54 weeks of follow-up) had treated infections reported vs. 30% of placebo-treated patients (average of 52 weeks of follow-up). The infections most frequently reported in the RA studies were respiratory tract infections (including URI, sinusitis, pharyngitis, and bronchitis) and urinary tract infections. No increased risk of serious infections or sepsis was observed with infliximab for injection compared with placebo in the ATTRACT or ACCENT I3† and II4† studies. However, in the ATTRACT study, the incidence of serious events of pneumonia and lobar pneumonia combined was higher in patients receiving infliximab for injection plus MTX vs. MTX alone (2.6% vs. 1.2%, respectively). In the ASPIRE study, the incidence of serious pneumonia was also higher in patients receiving infliximab for injection plus MTX vs. MTX alone (2.5% vs. 0%, respectively). In other RA trials, the incidence of serious infections including pneumonia was higher in infliximab for injection plus MTX treated patients compared with methotrexate alone, especially at higher than recommended induction regimen of infliximab for injection 6 mg/kg or greater. Among infliximab for injection-treated patients, serious infections included pneumonia, cellulitis, abscess and sepsis. In ATTRACT, one patient died with miliary tuberculosis, one died with disseminated coccidioidomycosis and one died due to sepsis. In the ASPIRE study, four patients were diagnosed with tuberculosis. In the ACCENT I study, one patient was diagnosed with tuberculosis. In EXPRESS II5†, two patients with psoriasis were diagnosed with tuberculosis. Other cases of tuberculosis, including disseminated tuberculosis, also have been reported post-marketing. Most of the cases of tuberculosis occurred within the first two months after initiation of therapy with infliximab for injection and may reflect recrudescence of latent disease (see 7 WARNINGS AND PRECAUTIONS, Risk of Infections). In the ACCENT II study, serious infections of nocardiosis (one patient) and cytomegalovirus (one patient) were reported. Twelve percent of patients with fistulising Crohn’s disease developed a new abscess 8 to 16 weeks after the last infusion of infliximab for injection in the T20 study. In the ACCENT II study, there was no difference between the infliximab for injection and placebo maintenance arms for proportions of patients with newly diagnosed fistula-related abscesses. (see 14.5 Clinical trials – reference biologic drug, Fistulising Crohn’s Disease). In the psoriasis studies, 1.5% of patients (average of 41.9 weeks of follow up) receiving infliximab for injection and 0.6% of patients (average of 18.1 weeks of follow up) receiving placebo developed serious infections. In EXPRESS6†, one patient died due to sepsis. In the IMPACT 27† study of psoriatic arthritis, 1.6% of patients (average 42.8 weeks of follow-up) receiving infliximab for injection and 2.0% of patients (average 20.2 weeks of follow-up) receiving placebo developed serious infections.
In the infliximab clinical studies in patients with ulcerative colitis (ACT 1 and ACT 28†), the most frequently reported infections were upper respiratory infection (URI), sinusitis, pharyngitis, bronchitis and moniliasis. In the UC studies, infections were reported in 30.6% and 40.1% of infliximab -treated patients at Week 30 (average 26.9 weeks of follow-up) and at Week 54 (average 41.1 weeks of follow-up) and in 29.5% and 32.8% of placebo-treated patients at Week 30 (average 22.2 weeks of follow up) and at Week 54 (average 32.2 weeks of follow-up). The types of infections, including serious infections, reported in patients with ulcerative colitis were similar to
1† ATTRACT (the Anti-TNF Trial in Rheumatoid Arthritis with Concomitant Therapy)16
2† ASPIRE (the Active-controlled Study of Patients Receiving Infliximab for the Treatment of Rheumatoid Arthritis of Early Onset
3† ACCENT I (the Anti-TNF Trial in Long-term Treatment of Moderately to Severely Active Crohn’s Disease)19, 20 4† ACCENT II (the Anti-TNF Trial in Long-term Treatment of Fistulising Crohn’s Disease)23
5† EXPRESS II Evaluation of Infliximab for Psoriasis in a REMICADE Efficacy and Safety Study 6† EXPRESS European infliximab for Psoriasis (REMICADE) Efficacy and Safety Study 32
7† IMPACT 2 Induction and Maintenance Psoriatic Arthritis Clinical Trial 33
8† ACT 1 and ACT 2 (the Anti-TNF Trials in moderately to severely active ulcerative colitis)
those reported in other clinical studies, and included one case of tuberculosis and a fatal case of histoplasmosis.
In post-marketing experience, infections have been observed with various pathogens including viral, bacterial, fungal, and protozoal organisms. Infections have been noted in all organ systems and have been reported in patients receiving infliximab for injection alone or in combination with immunosuppressive agents.
Autoantibodies/Lupus-like Syndrome
Approximately 55% of 1598 infliximab for injection-treated patients in clinical trials (primarily RA and CD) who were antinuclear antibody (ANA) negative at baseline developed a positive ANA during the trial compared with approximately 20% of 265 placebo-treated patients. Anti-dsDNA antibodies were newly detected in approximately 19% of 2116 infliximab for injection-treated patients compared with 0% of 422 placebo-treated patients. Reports of lupus and lupus-like syndromes, however, remain uncommon.
In the ATTRACT rheumatoid arthritis study through Week 102, 62% of infliximab for injection-treated patients developed antinuclear antibodies (ANA) between screening and last evaluation, compared with 27% of placebo-treated patients. In the ASPIRE study through Week 58, 66% of infliximab for injection-treated patients developed antinuclear antibodies (ANA) between screening and last evaluation, compared with 21% of placebo-treated patients. In both RA studies, anti-dsDNA antibodies developed in approximately 15% of infliximab for injection-treated patients, compared to none of the placebo-treated patients. No association was seen between infliximab for injection dose/schedule and development of ANA or anti-dsDNA antibodies.
Of Crohn’s disease patients treated with infliximab for injection who were evaluated for antinuclear antibodies (ANA), 40% developed ANA between screening and last evaluation. Anti-dsDNA antibodies developed in approximately 20% of Crohn’s disease patients treated with infliximab for injection. The development of anti-dsDNA antibodies was not related to either the dose or duration of infliximab for injection treatment. However, baseline therapy with an immunosuppressant in Crohn’s disease patients was associated with reduced development of anti-dsDNA antibodies (3% compared to 21% in patients not receiving any immunosuppressant). Crohn’s disease patients were approximately 2 times more likely to develop anti-dsDNA antibodies if they were ANA-positive at study entry.
In the EXPRESS plaque psoriasis study through Week 50, 59% of infliximab for injection-treated patients developed antinuclear antibodies following infliximab for injection treatment compared to 2% of placebo-treated patients. Anti-dsDNA antibodies developed in 16% of infliximab for injection-treated patients, compared to none of the placebo-treated patients. In the EXPRESS II plaque psoriasis study through Week 50, 65% of infliximab for injection-treated patients developed antinuclear antibodies following infliximab for injection treatment compared to 8% of placebo-treated patients. Anti-dsDNA antibodies developed in 27% of infliximab for injection-treated patients, compared to none of the placebo-treated patients. No association was seen between infliximab for injection dose/schedule and development of ANA or anti-dsDNA antibodies.
In the IMPACT 2 psoriatic arthritis study through Week 66, 59% of infliximab for injection-treated patients developed antinuclear antibodies following infliximab for injection treatment compared to 11% of placebo-treated patients. Anti-dsDNA antibodies developed in 12% of infliximab for injection-treated patients, compared to none of the placebo-treated patients.
In the ASSERT ankylosing spondylitis study through week 102, 35% of infliximab for injection-treated patients developed antinuclear antibodies following infliximab for injection treatment compared to 1% of placebo-treated patients. Anti-dsDNA antibodies developed in 30% of infliximab for injection-treated patients, compared to none of the placebo-treated patients.
In clinical studies, 22 patients were diagnosed with a possible lupus-like syndrome, four with Crohn’s disease, eight patients with plaque psoriasis [seven (0.5%) patients treated with infliximab for injection and one (0.3%) patient treated with placebo], 8 patients with ankylosing spondylitis, and two with rheumatoid arthritis. Twenty-one patients improved following discontinuation of therapy and/or appropriate medical treatment. One psoriasis patient on concomitant hydralazine had central nervous system involvement. No patients had renal involvement. No cases of lupus-like syndromes were reported in the psoriatic arthritis studies. The lupus-like syndrome in one patient with rheumatoid arthritis and one patient with ankylosing spondylitis remained ongoing at the end of the study. One case of a lupus-like reaction has been observed in a Crohn’s disease patient in up to three years of long-term follow-up (see 7 WARNINGS AND PRECAUTIONS, Immune).
Hepatobiliary Events
In post-marketing surveillance, cases of jaundice and hepatitis, some with features of autoimmune hepatitis, have been reported in patients receiving infliximab for injection (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
In clinical trials, mild or moderate elevations of ALT and AST have been observed in patients receiving infliximab for injection without progression to severe hepatic injury. Elevations of aminotransferases were observed (ALT more common than AST) in a greater proportion of patients receiving infliximab for injection than in controls, both when infliximab for injection was given as monotherapy and when it was used in combination with other immunosuppressive agents. Most aminotransferase abnormalities were transient; however, a small number of patients experienced more prolonged elevations. In general, patients who developed ALT and AST elevations were asymptomatic, and the abnormalities decreased or resolved with either continuation or discontinuation of infliximab for injection, or modification of concomitant medications.
Malignancies/Lymphoproliferative Disease
The potential role of TNF-blocking therapy in the development of malignancies is not known. Rates in clinical trials for infliximab for injection cannot be compared to rates in clinical trials of other TNF-blockers and may not predict rates observed in a broader patient population. Caution should be exercised in considering infliximab for injection treatment in patients with a history of malignancy or in continuing treatment in patients who develop malignancy while receiving infliximab for injection.
In the controlled portions of clinical trials of all the TNF-blocking agents, more cases of lymphoma have been observed among patients receiving a TNF-blocker compared with control patients. In the controlled and open-label portions of infliximab for injection clinical trials, 5 patients developed lymphomas among 5780 patients treated with infliximab for injection (median duration of follow-up 1.0 years) vs. 0 lymphomas in 1600 control patients (median duration of follow-up 0.4 years). In rheumatoid arthritis patients, 2 lymphomas were observed for a rate of 0.08 cases per 100 patient-years of follow-up, which is approximately 3-fold higher than expected in the general population. In the combined clinical trial population for rheumatoid arthritis, Crohn’s disease, psoriatic arthritis, psoriasis, ankylosing spondylitis, and ulcerative colitis, 5 lymphomas were observed for a rate of 0.09 cases per 100 patient-years of follow-up, which is approximately 4-fold higher than expected in the general population. Patients with Crohn’s disease or rheumatoid arthritis, particularly patients with highly active disease and/or chronic exposure to immunosuppressant therapies, may be at a higher risk (up to several fold) than the general population for the development of lymphoma, even in the absence of TNF-blocking therapy.
In the controlled portions of clinical trials of some TNF-blocking agents including infliximab for injection, more cases of non-lymphoma malignancies have been observed in patients receiving those TNF-blockers compared with control patients. During the controlled portions of infliximab for injection trials in patients with moderately to severely active rheumatoid arthritis, Crohn’s disease, psoriatic arthritis, psoriasis, ankylosing spondylitis, and ulcerative colitis, 14 patients were diagnosed with non-lymphoma malignancies among 4019 infliximab for injection-treated patients vs. 1 among 1597 control patients (at a rate of 0.52/100 patient-years among infliximab for injection-treated patients vs. a rate of 0.11/100 patient-years among control patients), with median duration of follow-up 0.5 years for infliximab for injection-treated patients and 0.4 years for control patients. Of these, the most common malignancies were breast, colorectal, and melanoma. The rate of non-lymphoma malignancies among infliximab for injection-treated patients was similar to that expected in the general population whereas the rate in control patients was lower than expected.
Among the 345 patients who received infliximab for injection in ankylosing spondylitis trials, 3 patients developed malignancies (1 patient had a squamous cell and a basal cell carcinoma, 1 patient had a pulmonary carcinoma, and 1 patient had breast cancer). Additionally, 1 patient in ASSERT developed a nonseminoma testicular carcinoma after leaving the trial, approximately 1 year after his last dose of infliximab for injection.
In the IMPACT 2 study of psoriatic arthritis, 2 malignancies were reported through Week 54 (Stage I Hodgkin’s lymphoma in a infliximab for injection-treated patient and basal cell carcinoma in a placebo-treated patient). No malignancies were reported through Week 50 of IMPACT. An adenocarcinoma of the pancreas was reported 2 months after completing the year 2 extension of IMPACT.
During the infliximab for injection plaque psoriasis trials, no patients developed lymphoma. In the placebo-controlled portions of the psoriasis studies, 7 of 1123 patients who received infliximab for injection at any dose (443 patient-years) were diagnosed with a nonmelanoma skin cancer (NMSC) compared to 0 of 334 patients who received placebo (113 patient-years). Among the 1373 patients with psoriasis who received infliximab for injection at any dose in the controlled and uncontrolled portions of the psoriasis studies (1101 patient-years), a total of 17 were diagnosed with NMSC (12 basal cell cancers, 5 squamous cell cancers). The size of the placebo group and limited duration of the controlled portions of studies precludes the ability to draw firm conclusions. Patients on infliximab for injection should be monitored for the development of NMSC. Two noncutaneous malignancies (breast cancer and adenocarcinoma) were reported during the psoriasis clinical trials.
A population-based retrospective cohort study found an increased incidence of cervical cancer in women with rheumatoid arthritis treated with infliximab for injection compared to biologics-naïve patients or the general population, including those over 60 years of age.
Congestive Heart Failure
In a phase II study evaluating infliximab for injection in NYHA Class III/IV CHF patients (left ventricular ejection fraction ≤35%), higher incidences of mortality and hospitalization due to worsening heart failure were seen in infliximab for injection-treated patients, especially those treated with 10 mg/kg. One hundred and fifty patients were treated with 3 infusions of infliximab for injection 5 mg/kg, 10 mg/kg, or placebo over 6 weeks. At 28 weeks, 4 of 101 patients treated with infliximab for injection (1 at 5 mg/kg and 3 at 10 mg/kg) died compared with no deaths among the 49 placebo-treated patients. In follow-up, at 38 weeks, 9 patients treated with infliximab for injection (2 at 5 mg/kg and 7 at 10 mg/kg) died compared with one death among the placebo-treated patients. At 28 weeks, 14 of 101 patients treated with infliximab for injection (3 at 5 mg/kg and 11 at 10 mg/kg) were hospitalized for worsening CHF compared with 5 of the 49 placebo-treated patients (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
There have also been post-marketing reports of new onset heart failure, including heart failure in patients without known pre-existing cardiovascular disease. Some of these patients have been under 50 years of age.
8.2.1 Clinical Trial Adverse Reactions - Pediatrics
Crohn’s Disease
Adverse events occurring at a frequency of ≥5% or from ≥1% to <5% in infliximab for injection-treated pediatric patients with Crohn’s disease are shown in Table 4 and Table 6, respectively. In general, the adverse events in pediatric patients who received infliximab for injection were similar in frequency and type to those seen in adult patients with Crohn’s disease. Differences from adults and other special considerations are discussed in the following paragraphs.
The following adverse events were reported more commonly in the 103 randomised pediatric patients with Crohn’s disease (Phase 3 Trial, REACH) who received 5 mg/kg infliximab for injection through 54 weeks than in the 385 adult patients with Crohn’s disease (ACCENT I) where 193/385 patients received 5 mg/kg and 192/385 received 10 mg/kg infliximab for injection through 54 weeks: anemia (10.7%), blood in stool (9.7%), leukopenia (8.7%), flushing (8.7%), viral infection (7.8%), neutropenia (6.8%), bone fracture (6.8%), bacterial infection (5.8%), and respiratory tract allergic reaction (5.8%). The Phase 3 study (REACH) enrolled 112 pediatric patients 6 to 17 years old (median age 13.0 years) with moderately to severely active Crohn’s disease and an inadequate response to conventional therapies.
Infections were reported in 56.3% of randomised pediatric patients in the REACH trial, and in 50.3% of patients in the ACCENT I Study. In the pediatric Phase 3 trial, infections were reported more frequently for subjects who received q8 week as opposed to q12 week infusions (73.6% and 38.0%, respectively), while serious infections were reported for 3 patients in the q8 week and 4 patients in the q12 week maintenance treatment group. The most commonly reported infections were upper respiratory tract infection and pharyngitis, and the most commonly reported serious infection was abscess. Pneumonia was reported for 3 patients, 2 in the q8 week and 1 in the q12 week maintenance treatment groups. Herpes zoster was reported for 2 patients in the q8 week maintenance treatment group.
In REACH, 17.5% of randomised patients experienced 1 or more infusion reactions, with no notable difference between treatment groups (17.0% and 18.0% of patients in the q8 week and q12 week maintenance treatment groups, respectively). There were no serious infusion reactions, and 2 patients had non-serious anaphylactic reactions.
Antibodies to infliximab for injection developed in 3 (2.9%) pediatric patients in the REACH trial and in none of the patients in the Phase 2 trial (T23).
Juvenile Rheumatoid Arthritis
The efficacy of infliximab for injection in the treatment of children with juvenile rheumatoid arthritis, JRA, has not been established. In a clinical trial where children were treated with either 3 mg/kg or 6 mg/kg of infliximab for injection, the proportion of children with infusion reactions, most commonly vomiting, fever, headache and hypotension, was 35% at a dosage of 3 mg/kg. Four of these reactions were serious, and three were considered to be possible anaphylactic reactions. Two of the 4 patients who experienced serious infusion reactions at a dose of 3 mg/kg received infliximab for injection by rapid infusion (duration time less than 2 hours). Antibodies to infliximab for injection developed in 37.7% of children receiving that dosage, but only in 12.2% receiving a higher dosage (6 mg/kg).
Ulcerative Colitis
Overall, the adverse reactions reported in the pediatric ulcerative colitis (Study Peds UC) and adult ulcerative colitis (ACT 1 and ACT 2) studies were generally consistent. In Study Peds UC, the most common adverse reactions were upper respiratory tract infection, pharyngitis, abdominal pain, fever, and headache. In Study Peds UC, there were a total of 20 serious adverse events: 10 were serious adverse events of ulcerative colitis, 7 were infections (which included cellulitis, urinary tract infection, pneumonia, pharyngitis, ulcerative colitis, viral infection, and infection not otherwise specified) and one event each of anemia, neutropenia and pancreatitis. An additional 12 adverse events were considered to be severe (4 events of ulcerative colitis, 3 of abdominal pain and 1 event each of pharyngitis, sinusitis, malnutrition, inflammation and headache). None of these serious or severe adverse events were opportunistic infections.
Infections were reported in 31 (51.7%) of 60 treated patients in Study Peds UC and 22 (36.7%) required oral or parenteral antimicrobial treatment. The proportion of patients with infections in Study Peds UC was similar to that in the pediatric Crohn’s disease study (REACH) but higher than the proportion in the adults ulcerative colitis studies (ACT 1 and ACT 2). Unlike REACH, in which infections were reported more frequently for patients who received q8 week as opposed to q12 week infusions; in Study Peds UC, the overall incidence of infections was similar in the q8 week (13/22 [59.1%]) and q12 week (14/23 [60.9%]) maintenance treatment groups. In Study Peds UC, serious infections were reported for 3 of 22 (13.6%) patients in the q8 week and 3 of 23 (13.0%) patients in the q12 week maintenance treatment group. Upper respiratory tract infection (7/60 [11.7%]) and pharyngitis (5/60 [8.3%]) were the most frequently reported respiratory system infections among all treated patients. The infections occurring in more than one patient in a treatment group that required antimicrobial treatment were pharyngitis (4/60 [6.7%]), urinary tract infection (4/60 [6.7%]), and bronchitis (2/60 [3.3%]).
Overall, 8 (13.3%) of 60 treated patients experienced one or more infusion reactions, with 4 of 22 (18.2%) in the q8 week and 3 of 23 (13.0%) in the q12 week treatment maintenance group. No serious infusion reactions were reported. All infusion reactions were mild or moderate in intensity.
Antibodies to infliximab for injection were detected in 4 of 52 (7.7%) patients through week 54.
In Study Peds UC, there were more patients in the 12 to 17 year age group than in the 6 to 11 year age group (45/60 [75.0%]) vs.15/60 [25.0%]). While the numbers of patients in each subgroup are too small to make any definitive conclusions about the effect of age on safety events, there were higher proportions of patients with serious adverse events and discontinuation due to adverse events in the younger age group than in the older age group. While the proportion of patients with infections was also higher in the younger age group, the proportions of patients with serious infections were similar in the two age groups. Overall proportions of adverse events and infusion reactions were similar between the 6 to 11 and 12 to 17 year age groups.
8.3 Less Common Clinical Trial Adverse Reactions
Other medically relevant adverse events occurring at a frequency <1% were as follows, presented by body system:
Administration / Application Site: injection site inflammation, injection site ecchymosis, injection site swelling, injection site infection
Autonomic Nervous System: fecal incontinence
Body as a Whole: anaphylactoid reaction, diaphragmatic hernia, generalized edema, surgical/procedural sequela, substernal chest pain, rigors
Blood: pancytopenia, splenomegaly
Cardiovascular: circulatory failure, hypotension postural, pallor
Collagen: LE syndrome, anti-DNA antibodies, positive antinuclear factor test, anticardiolipin antibodies
Ear and Hearing: otitis externa
Endocrine: adrenal insufficiency, hypothyroidism
Eye and Vision: lacrimation abnormal, iritis, scleritis, eye pain, glaucoma Gastrointestinal: ileus, intestinal stenosis, pancreatitis, peritonitis, rectal hemorrhage, appetite increased, anal fistula, diarrhea bloody, gastritis, intestinal obstruction, intestinal perforation Central & Peripheral Nervous: meningitis, neuritis, optic neuritis, peripheral neuropathy, neuralgia, ataxia, dysesthesia, tremor, hyperkinesia
Heart Rate and Rhythm: arrhythmia, bradycardia, cardiac arrest, palpitations Liver and Biliary: cholelithiasis, hepatitis, bilirubinemia, cholecystitis, hepatocellular damage, elevated GGT, fatty liver, hepatomegaly
Metabolic and Nutritional: hypercholesterolemia
Musculoskeletal: intervertebral disk herniation, tendon disorder, joint stiffness Myo-, Endo-, Pericardial and Coronary Valve: myocardial infarction, mitral insufficiency, heart murmur, cardiac failure
Platelet, Bleeding and Clotting: thrombocytopenia
Neoplasms: adenocarcinoma, basal cell carcinoma, breast cancer, lymphoma, malignant melanoma, squamous cell carcinoma, bladder carcinoma, rectal carcinoma, uterine cancer, pulmonary carcinoma
Psychiatric: confusion, suicide attempt, irritability, nervousness, amnesia Red Blood Cell: iron deficiency anemia, hemolytic anemia
Reproductive: menstrual irregularity, dysmenorrhea, menorrhagia, breast fibroadenosis, amenorrhea, female breast pain
Resistance Mechanism: sepsis, serum sickness, tuberculosis, fungal infection, viral infection, sarcoid-like reaction
Respiratory: Adult respiratory distress syndrome, respiratory tract infection, pleural effusion, lobar pneumonia, pulmonary edema, respiratory insufficiency, bronchospasm, asthma, hemoptysis, epistaxis, laryngitis
Skin and Appendages: erythema nodosum, rash maculopapular, rash pustular, photosensitivity reaction, edema periorbital, fascitis
Special Senses, Other: taste perversion, taste loss
Urinary: renal failure, dysuria, renal calculus, pyelonephritis
Vascular (Extracardiac): brain infarction, thrombophlebitis, vasculitis, brain ischemia, pulmonary embolism
White Cell and Reticuloendothelial: neutropenia, neutrophilia, lymphocytosis Investigations: Weight Increased*
* At month 12 of the controlled period for adult clinical trials across all indications, the median weight increase was 3.50 kg for infliximab-treated subjects vs. 3.00 kg for placebo-treated subjects. The median weight increase for inflammatory bowel disease indications was 4.14 kg for infliximab-treated subjects vs. 3.00 kg for placebo-treated subjects, and the median weight increase for rheumatology indications was 3.40 kg for infliximab-treated subjects vs. 3.00 kg for placebo-treated subjects.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data
Serious, medically relevant hematologic adverse events ≥ 0.2%, or clinically relevant hematologic adverse reactions observed in clinical trials include: pancytopenia, thrombocytopenia, anemia, hemolytic anemia, neutropenia and leukopenia.
The proportion of patients with abnormal ALT levels in response to the reference product is presented in Table 7.
Table 7. Proportion of patients with elevated ALT in clinical trials
| Proportion of patients with elevated ALT | ||||||
| > 1 to < 3 X ULN | ≥ 3 X ULN | ≥ 5 X ULN | ||||
| Placebo | Infliximab for injection | Placebo | Infliximab for injection | Placebo | Infliximab for injection | |
| Rheumatoid arthritis1 | 24.0% | 34.4% | 3.2% | 3.9% | 0.8% | 0.9% |
| Crohn’s disease2 | 24.1% | 34.9% | 2.2% | 4.9% | 0.0% | 1.5% |
| Ulcerative colitis3 | 12.4% | 17.4% | 1.2% | 2.5% | 0.4% | 0.6% |
| Psoriatic arthritis4 | 16.3% | 49.5% | 0.0% | 6.8% | 0.0% | 2.1% |
| Plaque psoriasis5 | 23.8% | 49.4% | 0.4% | 7.7% | 0.0% | 3.4% |
| Pediatric Crohn’s Disease6 | N/A | 18.2% | N/A | 4.4% | N/A | 1.5% |
| Ankylosing Spondylitis7 | 14.5% | 51.1% | 0.0% | 9.5% | 0.0% | 3.6% |
| Pediatric Ulcerative Colitis8 | N/A | 16.7% | N/A | 6.7% | N/A | 1.7% |
1 Note that placebo patients received methotrexate while infliximab patients received both infliximab and methotrexate. Median follow-up was 58 weeks for placebo patients and infliximab-treated patients. RA trials include ATTRACT (T22) and ASPIRE (T29). 2 Note that placebo patients in 2 of the 3 Phase III trials in Crohn’s disease, ACCENT I and ACCENT II, received an initial dose of 5 mg/kg infliximab at study start and were on placebo in the maintenance phase. Patients who were randomized to the placebo maintenance group and then later crossed over to infliximab are included in the infliximab group in this table. Median follow-up time was 54 weeks. In SONIC, placebo patients received AZA 2.5 mg/kg/day. 3 Ulcerative colitis trials include ACT I (C0168T37) through Week 54 and ACT II (C0168T46) through Week 30; median duration of follow up was 30.8 weeks for the infliximab group and 30.1 weeks for placebo group. 4 IMPACT 2 median duration of follow up was 39.1 weeks for the infliximab group and 18.1 weeks for placebo group. 5 EXPRESS and EXPRESS II median duration of follow up was 16.1 weeks for placebo and 50.1 weeks for infliximab groups. 6 Patients from pediatric Crohn’s disease trials T23, T55 and T47 (REACH). Median follow-up was 53.0 weeks. 7 Patients from the ASSERT trial (T51); median duration of follow-up was 24.1 weeks for placebo and 101.9 weeks for the infliximab group. 8 Data from the pediatric ulcerative colitis study T72. | ||||||
The difference in rates of ALT elevations ≥ 3 X ULN between infliximab for injection and placebo treatment groups tended to be greater in ankylosing spondylitis, psoriasis and psoriatic arthritis clinical trials than in rheumatoid arthritis, Crohn’s disease and ulcerative colitis clinical trials. See 8.2 Clinical Trial Adverse Reactions, Hepatobiliary Events.
8.5 Post-Market Adverse Reactions
Additional adverse events, some with fatal outcome, reported from worldwide post-marketing experience with infliximab for injection are included in Table 8. (see 8.2 Clinical Trial Adverse Reactions, Infections and Infusion-related Reactions). Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to infliximab for injection exposure. The most common serious adverse events reported in the post-marketing experience in children were infections (some fatal) including opportunistic infections and tuberculosis, infusion reactions, and hypersensitivity reactions. Spontaneous serious adverse events in the post-marketing experience with infliximab for injection in the pediatric population have also included malignancies, transient hepatic enzyme abnormalities, lupus-like syndromes, and the development of autoantibodies.
Post-marketing cases of hepatosplenic T-cell lymphoma have been reported in patients treated with infliximab for injection with the vast majority of cases occurring in Crohn’s disease and ulcerative colitis, most of whom were adolescent or young adult males (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis). Hemophagocytic lymphohistiocytosis (HLH) has been very rarely reported in patients treated with infliximab.
Table 8. Post-marketing Reports
Blood and Lymphatic System
Disorders
Agranulocytosis (including infants exposed in utero to infliximab for injection), idiopathic thrombocytopenic purpura, hemolytic anemia, pancytopenia, thrombotic thrombocytopenic purpura
General Disorders and
Administration Site Conditions
Anaphylactic reactions, anaphylactic shock, infusion-related reactions, serum sickness
Cardiac Disorders Pericardial effusion, myocardial ischemia/myocardial infarction (within 24 hours of initiation of infusion), arrhythmia (within 24 hours of initiation of infusion) Eye Disorders Transient visual loss occurring during or within 2 hours of infusion
Immune System Disorders Vasculitis, sarcoidosis, paradoxical drug-induced immune disorders (e.g., new onset psoriasis)
Neoplasm Benign and Malignant Hepatosplenic T-cell lymphoma (the vast majority in Crohn’s disease and ulcerative colitis: primarily adolescents and young adults) , pediatric malignancy, leukemia, melanoma, Merkel cell carcinoma, cervical cancer
Hepatobiliary System Disorders Hepatocellular damage, hepatitis, jaundice, autoimmune hepatitis, liver failure
Nervous System Disorders Central nervous system demyelinating disorders (such as multiple sclerosis and optic neuritis), peripheral demyelinating disorders (such as Guillain-Barré syndrome, chronic inflammatory demyelinating polyneuropathy, and multifocal motor neuropathy), neuropathies, numbness, seizure, tingling, transverse myelitis, cerebrovascular accidents occurring within approximately 24 hours of initiation of infusion, orbital apex syndrome
Infections and Infestations Opportunistic infections (such as aspergillosis, atypical mycobacteria, coccidioidomycosis, cryptococcosis, candidiasis, histoplasmosis, legionellosis, listeriosis, pneumocystosis), salmonellosis, sepsis, tuberculosis, protozoal infections, hepatitis B reactivation and vaccine breakthrough infection (after in utero exposure to infliximab for injection)*
Respiratory, Thoracic and
Mediastinal Disorders
Interstitial lung disease, including pulmonary fibrosis/interstitial pneumonitis, and rapidly progressive disease
Skin and Subcutaneous Tissue
Disorders
Vasculitis (primarily cutaneous), psoriasis including new onset and pustular (primarily palmar/plantar), erythema multiforme, Stevens-Johnson Syndrome, toxic epidermal necrolysis, linear IgA bullous dermatosis (LABD), acute generalized exanthematous pustulosis (AGEP), lichenoid reactions
Injury, poisoning, and procedural
complications
Post-procedural complication (including infectious and non-infectious complications)
* including bovine tuberculosis (disseminated BCG infection), see 7 WARNINGS AND PRECAUTIONS, Live Vaccines/Therapeutic Infectious Agents.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Specific drug interaction studies have not been conducted. The majority of patients in rheumatoid arthritis, Crohn’s disease or ulcerative colitis clinical trials received one or more concomitant medications. In rheumatoid arthritis, concomitant medications besides MTX were nonsteroidal anti-inflammatory agents, folic acid, corticosteroids and/or narcotics. Concomitant Crohn’s disease medications were antibiotics, antivirals, corticosteroids, 6-mercaptopurine/azathioprine (6- MP/AZA), methotrexate (MTX), and aminosalicylates Patients with Crohn’s disease who received immunosuppressants tended to experience fewer infusion reactions compared to patients using no immunosuppressants (see 7 WARNINGS AND PRECAUTIONS, Immune and 8 ADVERSE REACTIONS, Infusion-related Reactions).
9.3 Drug-Behavioural Interactions
Drug-lifestyle interactions have not been established.
9.4 Drug-Drug Interactions
Concurrent Use of Renflexis® with other Biological Therapeutics
The combination of Renflexis® with other biological therapeutics used to treat the same conditions as Renflexis®, including anakinra or abatacept, is not recommended (see 7 WARNINGS AND PRECAUTIONS, Risk of Infections).
Live Vaccines/Therapeutic Infectious Agents
It is recommended that live vaccines not be given concurrently with Renflexis®. It is also recommended that live vaccines not be given to infants after in utero exposure to infliximab for at least 12 months following birth. Administration of the live vaccine prior to 12 months of age might be considered if infliximab exposure was limited to the first trimester of pregnancy, or if infant infliximab serum levels are undetectable, or if there is a clear benefit for the individual infant (see 7 WARNINGS AND PRECAUTIONS, Immune and 7.1.1 Pregnant Women).
Administration of a live vaccine to a breastfed infant while the mother is receiving infliximab is not recommended unless infant infliximab serum levels are undetectable (see 7 WARNINGS AND PRECAUTIONS, Immune and 7.1.2 Breast-feeding).
It is recommended that therapeutic infectious agents not be given concurrently with Renflexis® (see 7 WARNINGS AND PRECAUTIONS).
Cytochrome P450 Substrates
The formation of CYP450 enzymes may be suppressed by increased levels of cytokines (e.g., TNFα, IL-1, IL-6, IL-10, IFN) during chronic inflammation. Therefore, it is expected that for a molecule that antagonizes cytokine activity, such as infliximab for injection, the formation of CYP450 enzymes could be normalized. Upon initiation or discontinuation of Renflexis® in patients being treated with CYP450 substrates with a narrow therapeutic index, monitoring of the effect (e.g., warfarin) or drug concentration (e.g., cyclosporine or theophylline) is recommended and the individual dose of the drug product may be adjusted as needed.
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Infliximab for injection is a chimeric immunoglobulin G1 kappa (IgG1κ) monoclonal antibody with an approximate molecular weight of 149,100 daltons. It is composed of human constant and murine variable regions. Infliximab for injection binds specifically to human tumour necrosis factor alpha (TNFα) with an association constant of 1010 M-1. Infliximab for injection is produced by a recombinant cell line cultured by continuous perfusion and is purified by a series of steps that includes measures to inactivate and remove viruses.
Infliximab for injection neutralises the biological activity of TNFα by binding with high affinity to the soluble and transmembrane forms of TNFα and inhibits binding of TNFα with its receptors. 7-9
Infliximab for injection does not neutralise TNFβ (lymphotoxin α), a related cytokine that utilises the same receptors as TNFα. Biological activities attributed to TNFα include: induction of pro-
7 Siegel SA, Shealy DJ, Nakada MT, Le J, Woulfe DS, Probert L, Kollias G, Ghrayeb J, Vilcek J, Daddona PE. The mouse/human chimeric monoclonal antibody cA2 neutralizes TNF in vitro and protects transgenic mice from cachexia and TNF lethality in vivo. Cytokine 1995;7:15-25.
8 Beutler B. Tumour necrosis factor. The molecules and their emerging roles in medicine. Raven Press, NY, 1992. 9 Boussiotis VA, Nadler LM, Strominger JL, Goldfeld AE. Tumour necrosis factor α is an autocrine growth factor for normal human B cells. Proc Natl Acad Sci USA 1994;91:7007-7011.
10 Cope AP, Londei M, Chu NR, Cohen SBA, Elliott MJ, Brennan FM, Maini RN, Feldmann M. Chronic exposure to tumour necrosis factor (TNF) in vitro impairs the activation of T cells through the T cell receptor/CD3 complex; reversal in vivo by anti-TNF antibodies in patients with rheumatoid arthritis. J Clin Invest 1994;94:749-760.
11 Watkins PE, Warren BF, Stephens S, Ward P, Foulkes R. Treatment of ulcerative colitis in the cottontop tamarin using antibody to tumour necrosis factor alpha. Gut 1997;40:628-633.
12 Jones M, Symmons D, Finn J, Wolfe F. Does exposure to immunosuppressive therapy increase the 10 year malignancy and mortality risks in rheumatoid arthritis? A matched cohort study. Br J Rheum 1996;35:738-45.
13 Chu CQ, Field M, Feldmann M, et al. Localization of tumor necrosis factor α in synovial tissues and at the cartilage-pannus junction in patients with rheumatoid arthritis. Arthritis and Rheum 1991;34:1125-1132.
inflammatory cytokines such as interleukins (IL) 1 and 6, enhancement of leukocyte migration by increasing endothelial layer permeability and expression of adhesion molecules by endothelial cells and leukocytes, activation of neutrophil and eosinophil functional activity, and induction of acute phase reactants and other liver proteins.10 Cells expressing transmembrane TNFα bound by infliximab for injection can be lysed in vitro by complement or effector cells.8 Infliximab for injection inhibits the functional activity of TNFα in a wide variety of in vitro bioassays utilising human fibroblasts, endothelial cells, neutrophils,7 B and T lymphocytes,11,12 and epithelial cells. Anti-TNFα antibodies reduce disease activity in a cotton-top tamarin colitis model13, and decrease synovitis and joint erosions in a murine model of collagen-induced arthritis. Infliximab for injection prevents disease in transgenic mice that develop polyarthritis as a result of constitutive expression of human TNFα, and, when administered after disease onset, facilitates eroded joints to heal.
10.2 Pharmacodynamics
Preclinical
Infliximab for injection binds to the soluble and transmembrane forms of TNFα with high affinity and blocks the interaction of TNFα with its receptors, thereby neutralising the biological activity of TNFα.7-8 Cells expressing transmembrane TNFα can be lysed in vitro by complement or effector cell-mediated mechanisms after infliximab for injection binds.8 Infliximab for injection inhibits the functional activity of TNFα in a wide variety of in vitro bioassays utilising human fibroblasts, endothelial cells, neutrophils,9 B and T lymphocytes,11-12 and epithelial cells.12
Infliximab for injection specifically neutralises TNFα-induced cell cytotoxicity but not lymphotoxin α.8 Lymphotoxin α is a cytokine that shares 30% homology with TNFα and utilises the same receptors as TNFα. Species cross-reactivity of infliximab for injection is limited to human and chimpanzee TNFα. In vivo, infliximab for injection rapidly forms stable complexes with human TNFα, a process that parallels the loss of TNFα bioactivity.
In a transgenic mouse (Tg197) that constitutively expresses human TNFα, infliximab for injection administered twice weekly at 5 mg/kg or once weekly at 10 mg/kg prevents the development of polyarthritis by Week 10, demonstrating that infliximab for injection neutralises TNFα in vivo.
Clinical
Elevated concentrations of TNFα have been found in the joints of rheumatoid arthritis patients,15 in the joints of psoriatic arthritis patients, in the skin lesions of plaque psoriasis patients, and in the stools of Crohn’s disease and ulcerative colitis patients. This correlates with elevated disease activity.15 In rheumatoid arthritis, treatment with infliximab for injection reduced infiltration of inflammatory cells into inflamed areas of the joint as well as expression of molecules mediating cellular adhesion [E-selectin, intercellular adhesion molecule-1 (ICAM-1) and vascular cell adhesion molecule-1 (VCAM-1)], chemoattraction [IL-8 and monocyte chemotactic protein (MCP-1)] and tissue degradation [matrix metalloproteinase (MMP) 1 and 3].15 In Crohn’s disease, treatment reduces infiltration of inflammatory cells and TNFα production in inflamed areas of the intestine, and reduces the proportion of mononuclear cells in the lamina propria able to express TNFα and interferon γ ex vivo.15 After treatment with infliximab for injection, patients with rheumatoid arthritis or Crohn’s disease exhibited decreased levels of serum IL-6 and C-reactive protein compared to baseline. Peripheral blood lymphocytes from infliximab for injection-treated patients showed no decrease in proliferative responses to in vitro mitogenic stimulation when compared to cells from untreated patients. In psoriatic arthritis, treatment with infliximab for injection resulted in a reduction
15 Plevy SE, Landers CS, Prehn J, Carramanzana NM, Deem RL, Shealy D, Targan SR. A role for TNFα and mucosal T helper-1 cytokines in the pathogenesis of Crohn’s disease. J Immunol 1997;159:6276-6282.
in the number of T cells and blood vessels in the synovium and psoriatic skin lesions as well as a reduction of macrophages in the synovium. Infliximab for injection treatment alters the histopathological features of plaque psoriasis as demonstrated in lesional skin biopsies collected at baseline, day 3 and Week 10 following initiation of treatment. Infliximab for injection treatment reduced epidermal thickness and infiltration of inflammatory cells, downregulated the percentage of activated and cutaneous lymphocyte antigen (CLA)-positive inflammatory cells, including CD3-, CD4-, and CD8-positive lymphocytes, and upregulated the percentage of CD1a-positive epidermal Langerhans cells. In ulcerative colitis, treatment with infliximab for injection showed changes consistent with histological healing and decreased expression of pharmacodynamic markers of tissue injury and inflammation in colonic biopsies. Treatment with infliximab for injection also decreased serum levels of the proinflammatory molecules with statistically significant and consistent decreases observed for IL-2R, and ICAM-1. In patients with ankylosing spondylitis, infliximab for injection was more effective at decreasing levels of serum markers of inflammation (IL-6 and VEGF) at both weeks 2 and 24 than placebo. In addition, serum levels of markers of bone formation (bone alkaline phosphatase and osteocalcin) were increased at both weeks 2 and 24 in patients with ankylosing spondylitis treated with infliximab for injection compared with patients receiving placebo.
10.3 Pharmacokinetics
Single intravenous infusions of 1 to 20 mg/kg showed a linear relationship between the dose administered and the maximum serum concentration. The volume of distribution at steady state was independent of dose and indicated that infliximab for injection was distributed primarily within the vascular compartment. Median pharmacokinetic results for the doses of 3 mg/kg to 10 mg/kg in rheumatoid arthritis, 5 mg/kg in Crohn’s disease and 3 mg/kg to 5 mg/kg in plaque psoriasis indicate that the terminal half-life of infliximab for injection is approximately 7.7 to 10 days. The terminal half-life in ulcerative colitis trials was 12.3 to 14.7 days.
Table 9. Summary of infliximab for injection Pharmacokinetic Parameters in Rheumatoid Arthritis and Crohn’s Disease
| Rheumatoid Arthritis | Crohn’s Disease | |||
| Study | T09 (n=14) | T09 (n=29) | T11 (n=5) | T11 (n=5) |
| Dose | 3 mg/kg | 10 mg/kg | 5 mg/kg | 10 mg/kg |
| Cmax (μg/mL) | 77.3 | 277 | 74.9 | 181.0 |
| AUC (μg·day/mL) | 461 | 2282 | 788 | 2038 |
| CL (mL/day/kg) | 6.4 | 4.4 | 6.3 | 4.9 |
| Vss (mL/kg) | 67.5 | 57.2 | 80 | 65 |
| t1/2 (day) | 8 | 9.1 | 7.8 | 10 |
Absorption: Infliximab for injection is administered intravascularly and thus has no absorption profile.
Distribution: Infliximab for injection is primarily distributed into the blood, its apparent median steady state volume of distribution of 57.2 to 80 mL/kg estimated to 4.0 to 5.60 litres in a 70 kg individual corresponds to the total blood volume.
Metabolism: It is believed that infliximab for injection is metabolized in a similar manner to other proteins in the body. It is probably hydrolysed into its component amino acids and recycled or catabolized.
Excretion: Infliximab for injection as a whole molecule was not detected in the urine after its intravenous infusion.
Following an initial dose of infliximab for injection, repeated infusions at 2 and 6 weeks resulted in predictable concentration-time profiles following each treatment. No systemic accumulation of infliximab for injection occurred upon continued repeated treatment with 3 mg/kg or 10 mg/kg at 4- or 8-week intervals in rheumatoid arthritis patients or patients with moderate or severe Crohn’s disease retreated with 4 infusions of 10 mg/kg infliximab for injection at 8-week intervals. No systemic accumulation of infliximab for injection occurred upon continued repeated treatment with 3 mg/kg or 5 mg/kg at 8-week intervals in patients with psoriatic arthritis or plaque psoriasis. The proportion of patients with rheumatoid arthritis who had undetectable infliximab for injection concentrations at 8 weeks following an infusion was approximately 25% for those receiving 3 mg/kg every 8 weeks, 15% for patients administered 3 mg/kg every 4 weeks, and 0% for patients receiving 10 mg/kg every 4 or 8 weeks. At steady state, the proportion of patients with plaque psoriasis who had undetectable infliximab for injection concentrations at 8 weeks following an infusion ranged from 71.4% to 73.1% for patients receiving 3 mg/kg every 8 weeks (EXPRESS II), and from 25.9% to 46.4% for those administered 5 mg/kg every 8 weeks (EXPRESS and EXPRESS II). The proportion of patients with psoriatic arthritis who had undetectable infliximab for injection concentrations was 15.8% at Week 38 when administered 5 mg/kg every 8 weeks (IMPACT 2). In IMPACT 2, approximately half of the patients received concomitant MTX.
Special Populations and Conditions
No major differences in clearance or volume of distribution were observed in patient subgroups defined by age. It is not known if gender differences, genetic polymorphism, renal insufficiency or hepatic insufficiency have effects on clearance or volume of distribution of infliximab for injection.
Pediatrics
Infliximab for injection pharmacokinetic characteristics (including peak and trough concentrations) were generally similar in pediatric patients (aged 6 to 17 years) with Crohn’s disease or ulcerative colitis following the administration of 5 mg/kg infliximab for injection. Similar terminal half-life values were also observed in pediatric patients with Crohn’s disease, and adult patients with Crohn’s disease or ulcerative colitis. However, for pediatric patients with ulcerative colitis, median serum peak and steady-state trough infliximab for injection concentrations were about 13% and 25% lower than those in adult patients with ulcerative colitis, respectively; the clinical significance of the relatively lower serum infliximab for injection concentrations in pediatric patients is unknown (see 1.1 Pediatrics, and 7.1.3 Pediatrics).
11 STORAGE, STABILITY AND DISPOSAL
Renflexis® is stored in the original carton under refrigeration at 2°C and 8°C (36°F to 46°F). Do not use beyond the refrigerated expiration date printed on the carton.
After Reconstitution and Dilution
Chemical and physical in-use stability of the reconstituted solution has been demonstrated for 24 hours at room temperature (25°C). Also, chemical and physical in-use stability of diluted Renflexis® infusion solution is stable for 24 hours when stored between 2°C and 30°C (36°F to 86°F). This product contains no preservative. Since no preservative is present, it is recommended that the administration of the infusion solution should begin within 3 hours of reconstitution and dilution. If the infusion solution is not used immediately (i.e., within 3 hours of preparation), the in-use storage times and conditions prior to its use are the responsibility of the user and would not normally be longer than 24 hours between 2°C and 8°C, unless reconstitution and dilution have taken place in controlled and validated aseptic conditions.
Handling Under Controlled and Validated Aseptic Conditions
Chemical and physical in use stability of the diluted solution in the infusion bag has been demonstrated for up to 34 days at 2 to 8°C and for an additional 24 hours at 25°C after removal from refrigeration when Renflexis® reconstitution and dilution has taken place in controlled and validated aseptic conditions. If stored refrigerated after reconstitution and dilution, the infusion solution must be allowed to equilibrate at room temperature to 25°C for 3 hours prior to administration.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Infliximab
Chemical name: Infliximab
Molecular formula and molecular mass: 149,100 daltons
Structural formula:
The infliximab molecule contains 1328 amino acids and consists of 2 identical H chains and 2 identical L chains which associate by non-covalent H-H and H-L interactions and covalent H-H and H-L disulfide bonds. Infliximab is a glycoprotein consisting of 5 major glycoforms, each containing 2 (1 on each H chain) asparagine-linked (N-linked) asialo-, core-fucosylated, biantennary oligosaccharide chains with terminal galactose microheterogeneity. The oligosaccharide is bound exclusively to Asn-300 in the CH2 region of both H chains.
Physicochemical properties:
Renflexis® is a sterile, white, lyophilized powder for concentrate for solution for infusion.
Product Characteristics
Infliximab drug substance is a purified, recombinant DNA-derived, chimeric human-mouse IgG monoclonal antibody (MAb) which binds to and neutralises human tumour necrosis factor α (TNFα) with high affinity (Ka=1 X 10¹⁰ M-1). Infliximab contains murine heavy (H) and light (L) chain variable regions (VH and VL, respectively) derived from the murine anti-TNFα MAb, A2, and genomic DNA-derived human H and L chain constant regions (CH and CL, respectively).
14 CLINICAL TRIALS
14.5 Clinical trials – reference biologic drug
Rheumatoid Arthritis
Table 10. Summary of patient demographics for clinical trials in rheumatoid arthritis
The safety and efficacy of infliximab for injection were assessed in two multi-center, randomised double- blind, well controlled trials: ATTRACT16 and ASPIRE. Concurrent use of stable doses of folic acid, oral corticosteroids (≤10 mg/day) and/or nonsteroidal anti-inflammatory drugs was also permitted. The primary endpoints were the reduction of signs and symptoms as assessed by the American College of Rheumatology criteria, the prevention of structural joint damage, and the improvement in physical function. A summary of the design and subject demographics of the two studies is presented in Table 10.
ATTRACT (T22) Study Results
The safety and efficacy of infliximab for injection when given in conjunction with methotrexate (MTX) were assessed in a multicenter, randomized, double-blind, placebo-controlled study of 428 patients with active rheumatoid arthritis despite treatment with MTX (the Anti-TNF Trial in Rheumatoid Arthritis with Concomitant Therapy or ATTRACT).15 Patients enrolled had a median age of 54 years, median disease duration of 8.4 years, median swollen and tender joint count of 20 and 31 respectively, and were on a median dose of 15 mg/week of MTX. Patients received either placebo + MTX or one of 4 doses/schedules of infliximab for injection + MTX: 3 mg/kg or 10 mg/kg of infliximab for injection by IV infusion at Weeks 0, 2 and 6 followed by additional infusions every 4 or 8 weeks thereafter.
Clinical response
All doses/schedules of infliximab for injection + MTX resulted in improvement in signs and symptoms as measured by the American College of Rheumatology response criteria (ACR 20)15 with a higher percentage of patients achieving an ACR 20, 50 and 70 compared to placebo + MTX
15 Plevy SE, Landers CS, Prehn J, Carramanzana NM, Deem RL, Shealy D, Targan SR. A role for TNFα and mucosal T helper-1 cytokines in the pathogenesis of Crohn’s disease. J Immunol 1997;159:6276-6282.
16 Lipsky PE, van der Heijde D., St. Clair EW et al. Infliximab and methotrexate in the treatment of rheumatoid arthritis. N Engl J Med 2000;343:1594-1602.
| Study | Design | Dosage, route of administration and duration | Number of patients | Mean age (range) | Gender and Race n (%) |
T2216 (ATTRACT) | Randomised, multicentre. double-blind, placebo- controlled, 5-arm parallel study in patients with active RA despite treatment with MTX | Infliximab for injection 3 mg/kg, 10/mg/kg, or placebo administered intravenously at Weeks 0, 2 and 6, followed by additional infusions every 4 or 8 weeks thereafter through Week 54 | 428 | 52 (19 to 80) | 96 (22%) male 332 (78%) female 389 (91%) Caucasian 22 (5%) Black 3 (1%) Asian 14 (3%) Other |
T29 (ASPIRE) | Randomised, multicentre, double-blind, active- controlled, 3-arm parallel study in MTX- naïve subjects with early RA | Infliximab for injection 3 mg/kg, 6mg/kg, or placebo administered intravenously at Weeks 0, 2, 6, and every 8 weeks thereafter through Week 46 MTX 7.5 mg/wk po at Week 0; gradually increased to 20 mg/wk by Week 8 and maintained through Week 46 | 1004 | 50 (18 to 76) | 290 (29%) male 714 (71%) female 870 (86.7%) Caucasian 50 (5%) Black 15 (1.5%) Asian 69 (6.8%) Other |
(Table 11). Statistically significant improvement was observed at as early as Week 2 and maintained through Week 102. Greater effects on each component of the ACR 20 were observed in all patients treated with infliximab for injection + MTX compared with placebo + MTX (Table 12). Approximately 10% of patients treated with infliximab for injection achieved a major clinical response, defined as maintenance of an ACR 70 response over a 6-month period compared to 0% of placebo-treated patients (p=0.018).
Table 11. Percentage of patients who achieved an ACR response at Weeks 30 and 54 [ATTRACT]
| Infliximab for injection + MTX | |||||
| Placebo + MTX | 3 mg/kga | 10 mg/kga | |||
| Response | q8 wks | q4 wks | q8 wks | q4 wks | |
| n=88 | n=86 | n=86 | n=87 | n=81 | |
| ACR 20 | |||||
| Week 30 | 20% | 50% | 50% | 52% | 58% |
| Week 54 | 17% | 42% | 48% | 59% | 59% |
| ACR 50 | |||||
| Week 30 | 5% | 27% | 29% | 31% | 26% |
| Week 54 | 9% | 21% | 34% | 40% | 38% |
| ACR 70 | |||||
| Week 30 | 0% | 8% | 11% | 18% | 11% |
| Week 54 | 2% | 11% | 18% | 26% | 19% |
| a p<0.05 for each outcome compared to placebo | |||||
Table 12. Components of ACR 20 at baseline and 54 weeks [ATTRACT]
| Placebo + MTX | Infliximab for injection+ MTXa | |||
| (n=88) | (n=340) | |||
| Parmeter (medians) | Baseline | Week 54 | Baseline | Week 54 |
| No. of Tender Joints | 24 | 16 | 32 | 8 |
| No. of Swollen Joints | 19 | 13 | 20 | 7 |
| Painb | 6.7 | 6.1 | 6.8 | 3.3 |
| Physician’s Global Assessmentb | 6.5 | 5.2 | 6.2 | 2.1 |
| Patient’s Global Assessmentb | 6.2 | 6.2 | 6.3 | 3.2 |
| Disability Index (HAQ)c | 1.8 | 1.5 | 1.8 | 1.3 |
| CRP (mg/dL) | 3 | 2.3 | 2.4 | 0.6 |
a All doses/schedules of Infliximab for injection + MTX b Visual Analog Scale (0=best, 10=worst) c Health Assessment Questionnaire, measurement of 8 categories: dressing and grooming, arising, eating, walking, hygiene, reach, grip, and activities (0=best, 3=worst) | ||||
Radiographic response
Structural damage in both hands and feet was assessed radiographically at Week 54 by the change from baseline in the van der Heijde-modified Sharp score, a composite score of structural damage that measures the number and size of joint erosions and the degree of joint space narrowing in hands/wrists and feet.16 Approximately 80% of patients had paired x-ray data at 54 weeks and approximately 70% at 102 weeks. The inhibition of progression of structural damage was observed at 54 weeks (Table 13) and maintained through 102 weeks.
Table 13. Radiographic change from baseline to Week 54
| Infliximab for injection + MTX [ATTRACT] | ||||||
Median (10,90 percentiles) | Placebo + MTX | 3 mg/kga | 10 mg/kga | |||
| q8 wks | q4 wks | q8 wks | q4 wks | p valuea | ||
| Patients Evaluated | (n=64) | (n=71) | (n=71) | (n=77) | (n=66) | |
| Randomized | (n=88) | (n=86) | (n=86) | (n=87) | (n=81) | |
| Completed 54 wks | (n=44) | (n=63) | (n=66) | (n=75) | (n=65) | |
| Total Score | ||||||
| Baseline | 55 (14, 188) | 57 (15, 187) | 45 (8,162) | 56 (6, 143) | 43 (7, 178) | |
| Change from Baselilne | 4.0 (-1.0, 19.0) | 0.5 (-3.0, 5.5) | 0.1 (-5.2, 9.0) | 0.5 (-4.8, 5.0) | -0.5 (-5.7, 4.0) | p<0.001 |
| Erosion Score | ||||||
| Baseline | 25 (8, 110) | 29 (9, 100) | 22 (3, 91) | 22 (3, 80) | 26 (4, 104) | |
| Change from Baseline | 2.0 (-1.0, 9.7) | 0.0 (-3.0, 4.3) | -0.3 (-3.1, 2.5) | 0.5 (-3.0, 2.5) | -0.5 (-2.7, 2.5) | p<0.001 |
| JSN Score | ||||||
| Baseline | 26 (3, 88) | 29 (4, 80) | 20 (3, 83) | 24 (1, 79) | 25 (3, 77) | |
| Change from baseline | 1.5 (-0.8, 8.0) | 0.0 (-2.5, 4.5) | 0.0 (-3.4, 5.0) | 0.0 (-3.0, 2.5) | 0.0 (-3.0, 3.5) | p<0.001 |
| a For comparisons of each does against placebo | ||||||
Physical function response
Physical function and disability were assessed using the Health Assessment Questionnaire (HAQ) and the general health-related quality of life questionnaire SF-36. All doses/schedules of infliximab for injection + MTX showed significantly greater improvement from baseline in HAQ and SF-36 physical component summary score averaged over time through Week 54 compared to placebo + MTX, and no worsening in the SF-36 mental component summary score.
The median (interquartile range) improvement from baseline to Week 54 in HAQ was 0.1 (-0.1, 0.5) for the placebo + MTX group and 0.4 (0.1, 0.9) for infliximab for injection + MTX (p<0.001). Both HAQ and SF-36 effects were maintained through Week 102. Approximately 80% of patients in all doses/schedules of infliximab for injection + MTX remained in the trial through 102 weeks.
ASPIRE (T29) Study Results
The ASPIRE trial (T29) evaluated efficacy at 54 weeks in 1004 MTX-naïve patients with early active RA (≤3 years’ duration). All patients received MTX (optimized to 20 mg/wk by Week 8) and either placebo, 3 mg/kg, or 6 mg/kg infliximab for injection at Weeks 0, 2, and 6 and every 8 weeks thereafter. In this trial, infusions were to be administered over 2 hours for the first 3 infusions. The duration of subsequent infusions could be shortened to not less than 40 minutes in patients who did not experience serious infusion reactions. The primary endpoints were improvement of signs and symptoms (change from baseline ACR score) at Week 54, prevention of structural damage (change from baseline in the van der Heijde-modified-Sharp score) at Week 54, and prevention of physical disability (change from baseline HAQ) from Week 30 to Week 54. The results for the 3 co-primary endpoints and key secondary endpoints are summarized in Table 14.
Table 14. Efficacy results of study T29 (ASPIRE) in early RA
Infliximab for injection + MTX | |||
Placebo + MTX | 3 mg/kg q8 wks | 6 mg/kg q8 wks | |
| Patients randomized | n=282 | n=359 | n=363 |
| Parameter | |||
| Primary Endpoints | |||
Percentage ACR improvement from baseline at Week 54 Mean Median | 24.8% 26.4% | 37.3% 38.9% p<0.001 | 42.0% 46.7% p<0.001 |
Change from baseline total vdH-S score at Week 54 Mean Median | 3.70 0.43 | 0.42 0.00 p<0.001 | 0.51 0.00 p<0.001 |
Improvement from baseline HAQ from Week 30 to Week 54 (averaged over time) Mean Median | 0.68 0.75 | 0.80 0.78 p=0.030 | 0.88 0.79 p<0.001 |
| Secondary Endpoints | |||
| Proportion of subjects with clinical response at Week 54 | n=274 | n=351 | n=355 |
| ACR 20 | 54% | 62% p=0.028 | 66% p=0.001 |
| ACR 50 | 32% | 46% p<0.001 | 50% p<0.001 |
| ACR 70 | 21% | 33% p=0.002 | 37% p<0.001 |
| Radiographic change from baseline at Week 54 | n=226 | n=306 | n=306 |
Erosion score Mean Median | 2.97 0.25 | 0.31 0.00 p<0.001 | 0.07 0.00 p<0.001 |
Joint space narrowing (JSN) score Mean Median | 0.57 0.00 | 0.05 0.00 p<0.001 | 0.24 0.00 p=0.130 |
| Patients with erosion score=0 at baseline and at Week 54 | 58% (23/40) | 78% (39/50) p=0.037 | 79% (38/48) p=0.028 |
| Patients with no new erosion in previously uninvolved joints | 41% (93/227) | 51% (155/306) p=0.027 | 55% (168/306) p=0.001 |
| Improvement in physical function | n=275 | n=354 | n=358 |
Improvement from baseline HAQ from baseline to Week 54 (averaged over time) Mean Median | 0.55 0.57 | 0.70 0.64 p<0.001 | 0.77 0.76 p<0.001 |
Change from baseline to Week in SF-36 physical component Mean Median | 10.1 8.9 | 11.7 10.9 p=0.099 | 13.2 11.8 p=0.003 |
Study Results
Clinical response
After 54 weeks of treatment, both doses of infliximab for injection resulted in statistically significantly greater improvement in signs and symptoms compared with MTX alone as measured by the proportion of patients achieving ACR 20, 50, and 70 response. In the combined infliximab for injection+ MTX groups, 15% of patients achieved a major response vs. 8% of patients treated with MTX alone.
Radiographic response
Greater than 90% of patients had at least two evaluable x-rays. Inhibition of progression of structural damage was observed at Week 30 and Week 54 in the infliximab for injection + MTX groups compared with MTX alone. Infliximab for injection + MTX stopped the progression of joint disease in more patients compared with MTX alone, 97% vs. 86%, respectively. Infliximab for injection + MTX maintained an erosion-free state in a significantly greater proportion of patients than MTX alone, 79% vs. 58%, respectively. Fewer patients in the infliximab for injection + MTX groups (47%) developed erosions in uninvolved joints compared with MTX alone (59%).
Physical function response
Both infliximab for injection treatment groups showed statistically significantly greater improvement in HAQ from baseline averaged over time through Week 54 compared with MTX alone; 0.7 for infliximab for injection + MTX vs. 0.6 for MTX alone (p<0.001). There was no worsening in the SF-36 mental component summary score.
Ankylosing Spondylitis
Table 15. Patient demographics and study design in ankylosing spondylitis
| Study # | Study Design | Dosage, route of administration and duration | Number of subjects (n) | Mean age (range) | Gender and Race n (%) |
| P01522 | Randomised, double-blind, placebo-controlled phase (0 to 12 weeks) followed by open-label noncomparative phase (12 – 54 weeks) | Phase A: 5 mg/kg infliximab for injection or placebo administered intravenously at weeks 0, 2, and 6 Phase B: open-label 5 mg/kg infliximab for injection administered intravenously at weeks 12 and every 6 weeks up to Week 54 | 70 | 39.5 (21 to 61) | 46 (66%) male 24 (34%) female Race not available |
| C0168T51 (ASSERT) | Randomized, double-blind, placebo controlled, multicenter study. | Stage 1: placebo (Group 1) or 5 mg/kg infliximab for injection (Group 2) administered intravenously at weeks 0, 2, 6, 12, and 18. Stage 2: Group 1: Infliximab for injection 5 mg/kg infusions at Weeks 24, 26, 30, and every 6 weeks thereafter through Week 96. Group 2: Infliximab for injection 5 mg/kg infusion every 6 weeks through Week 96. Starting at Week 36, if subjects in Group 2 had a BASDAI ≥3 at 2 consecutive visits, they were to receive a 7.5 mg/kg infliximab for injection infusion and continued to receive 7.5 mg/kg infliximab for injection infusions every 6 weeks thereafter through Week 96. | 279 | 39.8 (18 - 74) | M: 225 (80.6%) F: 54 (19.4%) Caucasian: 273 (97.8%) Black: 2 (0.7%) Asian: 2 (0.7%) Other: 2 (0.7%) |
The safety and efficacy of infliximab for injection were assessed in two multicenter, double-blind, placebo-controlled studies in patients with active ankylosing spondylitis (Bath Ankylosing Spondylitis Disease Activity Index [BASDAI] score ≥ 4 and spinal pain ≥ 4 on a scale of 1-10). The study design and demographics of the study population are summarized in Table 15. Disease activity was measured using the Ankylosing Spondylitis Assessment (ASAS) 20 response criteria and/or the BASDAI. Physical function was assessed using the Bath Ankylosing Spondylitis Functional Index (BASFI).
The first trial (P01522) evaluated infliximab for injection in 70 patients with active ankylosing spondylitis. During the 3-month double-blind phase, patients received either 5 mg/kg infliximab for injection or placebo at Weeks 0, 2, 6 (35 patients in each group). Starting at Week 12, placebo patients were switched to infliximab for injection and all patients subsequently received 5 mg/kg infliximab for injection every 6 weeks up to Week 54. The results of this study were similar to those seen in 8 additional investigator-initiated studies of 169 patients with active ankylosing spondylitis. One-year efficacy was assessed at week 54. Fifty-three patients continued in an open-label long- term extension from week 54 to week 102.
In the second trial (ASSERT), 279 patients with ankylosing spondylitis were randomized to receive either placebo (78 patients, Group 1) or 5 mg/kg infliximab for injection (201patients, Group 2) at 0, 2, 6, 12 and 18 weeks. At week 24, patients receiving placebo were crossed over to receive 5 mg/kg infliximab for injection at week 24, 26 and 30 and then every 6 weeks through to week 96; patients in Group 2 continued at 5 mg/kg infliximab for injection every 6 weeks through to week 96. Starting with the week-36 infusion and continuing through the week-96 infusion, if a patient in Group 2 had a BASDAI ≥3 at 2 consecutive visits, this patient would receive a 7.5 mg/kg infliximab for injection infusion and would continue to receive 7.5 mg/kg infliximab for injection infusions every 6 weeks thereafter through week 96. Patients had a final evaluation at week 102. The demographics and disease characteristics at baseline for the 2 phase III studies are shown in Table 16.
Table 16. Summary of demographics and disease characteristics at baseline
| ASSERT | P01522 | |||
| Placebo | Infliximab for injection | Placebo | Infliximab for injection | |
| Subjects randomized | 78 | 201 | 35 | 35 |
| Sex | ||||
| Male | 87.2% | 78.1% | 62.9% | 68.6% |
| Female | 12.8% | 21.9% | 37.1% | 31.4% |
| Median age (yrs) | 41.0 | 40.0 | 38.0 | 40.0 |
| Median disease duration (yrs)a | 13.2b | 7.7b | 14.0 | 15.0 |
| Median BASDAI (0-10) | 6.5 | 6.6 | 6.3 | 6.5 |
| Median BASFI (0-10) | 6.0 | 5.7 | 5.1 | 5.2 |
| SF-36 physical component summary score | 30.1 | 28.8 | 28.9 | 30.1 |
| HLA-B27c | ||||
| Positive | 88.5% | 86.5% | 85.7% | 91.4% |
| Negative | 11.5% | 13.5% | 11.4% | 8.6% |
a Disease duration in ASSERT is diagnosis duration and in P01522 is symptom duration. b Mean disease duration in ASSERT was 11.9 years for the placebo group and 10.1 years for the infliximab for injection group. c One subject in the placebo group of P01522 was missing HLA-B27 status results at baseline. | ||||
Study Results
The primary efficacy endpoint in study P01522 was improvement in signs and symptoms at Week 12, as assessed by the BASDAI. Treatment with infliximab for injection resulted in significant improvement, with 57% of infliximab for injection-treated patients achieving at least 50% reduction from baseline in BASDAI score, compared with 9% of placebo patients (p<0.01). Improvement was observed at Week 2, and was maintained through Week 54 (Figure 1). At the end of the second year of treatment, 56.6% of patients achieved at least a 50% reduction in BASDAI.
Figure 1. Percentage of subjects with at least 50% improvement in BASDAI score
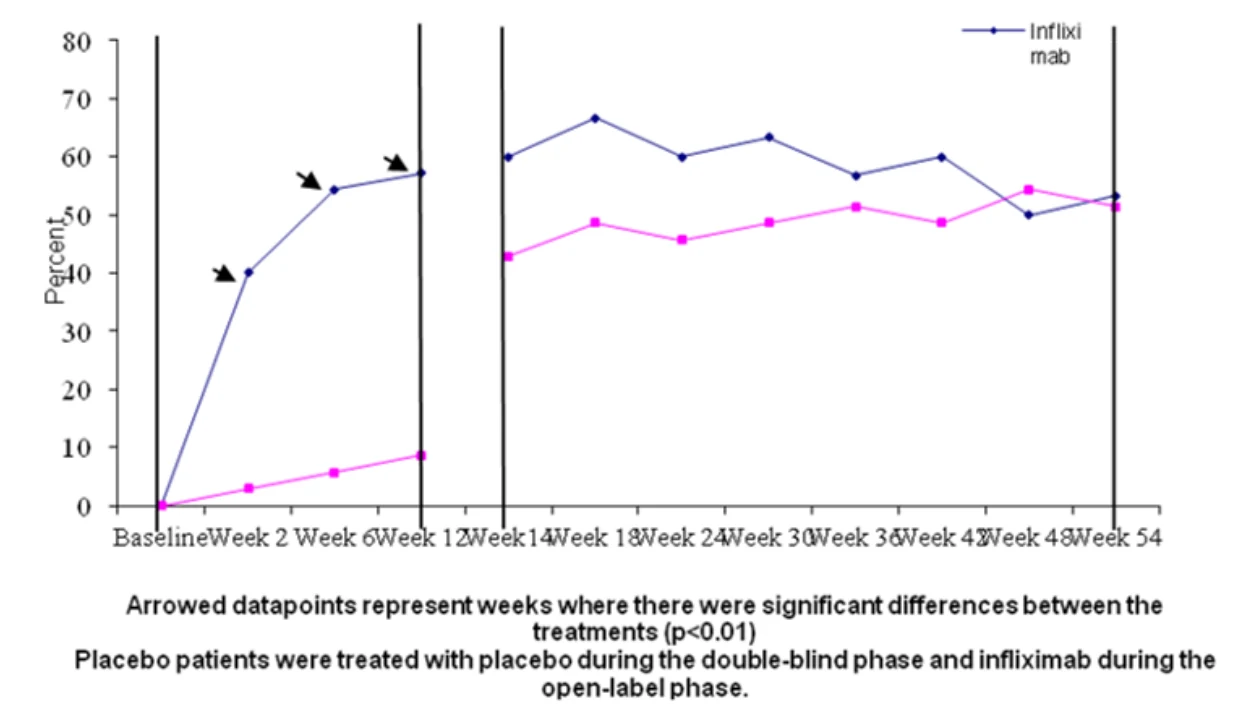
The primary efficacy endpoint in ASSERT was improvement in signs and symptoms at week 24, as assessed by the ASAS. The proportion of patients achieving an ASAS 20 response at 24 weeks was 61% in the infliximab for injection-treated group vs. 19% in the placebo group (p<0.001). Improvement was observed at week 2 and continued through week 24 (Figure 2 and Table 17). The percentage of patients achieving an ASAS 20 response at week 102 was 73.9% in the infliximab for injection group.
Figure 2. Proportion of subjects achieving ASAS 20 response over time through Week 24 in ASSERT
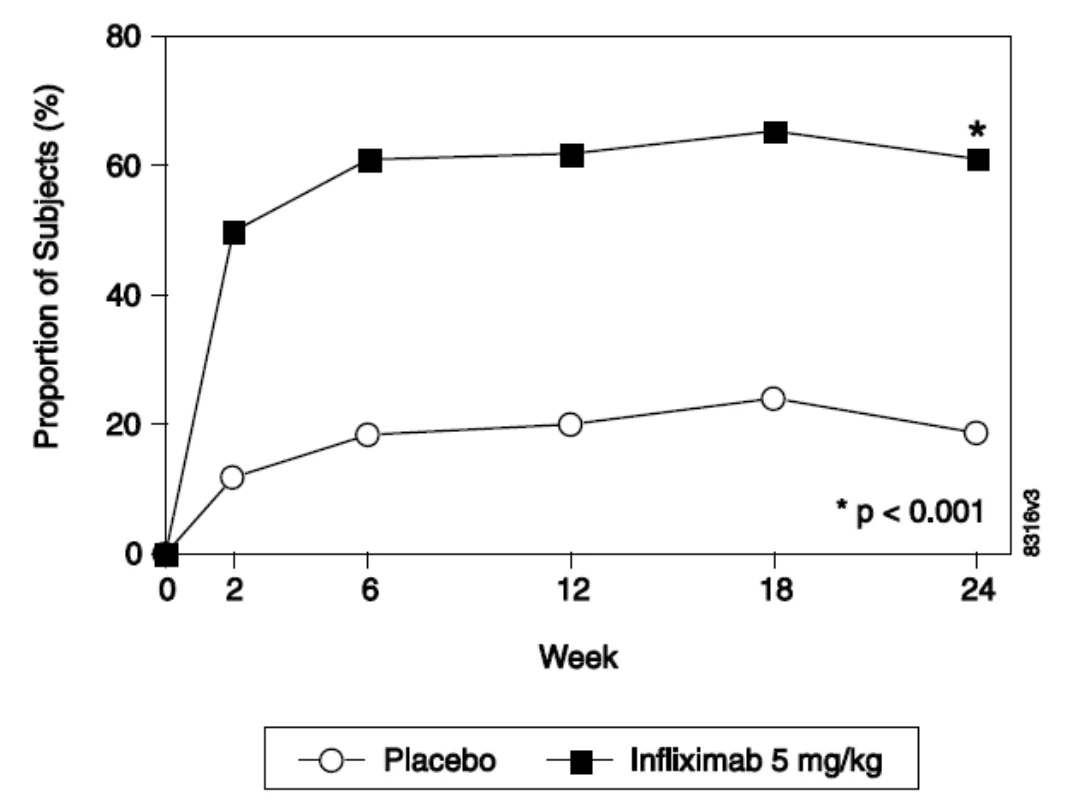
At 24 weeks, the proportions of patients achieving a 50% and a 70% improvement in the signs and symptoms of ankylosing spondylitis, as measured by ASAS response criteria (ASAS 50 and ASAS 70, respectively), were 44% and 28%, respectively, for patients receiving infliximab for injection, compared to 9% and 4%, respectively, for patients receiving placebo (p<0.001, infliximab for injection vs. placebo). A low level of disease activity (defined as a value <20 [on a scale of 0-100 mm] in each of the four ASAS response parameters) was achieved in 22% of infliximab for injection-treated patients vs. 1% in placebo-treated patients (p<0.001).
Table 17. Components of Ankylosing Spondylitis Disease Activity
| Placebo (n=78) | Infliximab for injection 5mg/kg (n=201) | ||||
| Baseline | 24 Weeks | Baseline | 24 Weeks | p-value | |
| ASAS 20 response Criteria (Mean) | |||||
| Patient global assessmenta | 6.6 | 6.0 | 6.8 | 3.8 | <0.001 |
| Spinal paina | 7.3 | 6.5 | 7.6 | 4.0 | <0.001 |
| BASFIb | 5.8 | 5.6 | 5.7 | 3.6 | <0.001 |
| Inflammationc | 6.9 | 5.8 | 6.9 | 3.4 | <0.001 |
| Acute Phase Reactants | |||||
| Median CRPd (mg/dL) | 1.7 | 1.5 | 1.5 | 0.4 | <0.001 |
| Spinal Mobility (cm, Mean) | |||||
| Modified Schober’s teste | 4.0 | 5.0 | 4.3 | 4.4 | 0.75 |
| Chest expansione | 3.6 | 3.7 | 3.3 | 3.9 | 0.04 |
| Tragus to walle | 17.3 | 17.4 | 16.9 | 15.7 | 0.02 |
| Lateral spinal flexione | 10.6 | 11.0 | 11.4 | 12.9 | 0.03 |
a measured on a VAS with 0=”none” and 10=”severe” b Bath Ankylosing Spondylitis Functional Index (BASFI), average of 10 questions c Inflammation, average of last 2 questions on the 6 question BASDAI d CRP normal range 0-1.0 mg/dL e Spinal mobility normal values: modified Schober’s test: >4 cm; chest expansion: >6 cm; tragus to wall: <15 cm; lateral spinal flexion: >10 cm | |||||
Physical function was assessed in both studies using the BASFI. In study P01522, the mean (SD) change at Week 12 from baseline BASFI score was -2.1 (1.6) in patients treated with infliximab for injection compared to -0.1 (1.8) in the placebo group (p<0.01). In ASSERT the median change (range) at Week 24 from baseline BASFI score was -1.7 (-8.7, 1.8) in patients treated with infliximab for injection compared to 0.0 (-5.9, 3.0) in the placebo group (p<0.001). The mean (SD) change from baseline was -2.1 (2.2) in patients treated with infliximab for injection compared to -0.2 (1.7) in the placebo group. The mean (SD) change from baseline through Week 102 in patients treated with infliximab for injection was -2.7 (2.2) in ASSERT and -2.1 (2.2) in study P01522.
In ASSERT the number of patients who achieved a ≥2 unit improvement in BASFI was also assessed. In the infliximab for injection group 47.5% of subjects showed a ≥2 units improvement from baseline in BASFI score at Week 24 compared to 13.3% in the placebo group (p<0.001). In the infliximab for injection group, 80.9% (76/94) of the subjects who showed a ≥2 units improvement at week 24 also showed a ≥2 units improvement at week 102.
The BASFI results are supported by an analysis of the physical component summary score of the SF-
- 36. In ASSERT the median change (range) at Week 24 from baseline SF-36 physical component summary score was 10.2 (-8.5, 37.7) in patients treated with infliximab for injection compared to 0.8 (-14.1, 21.8) in the placebo group (p<0.001). The mean (SD) change from baseline was10.8 (9.5) in patients treated with infliximab for injection compared to 1.5 (7.0) in the placebo group. In study P01522 the mean (SD) change at Week 12 from baseline SF-36 physical component summary score was 10.3 (8.3) in patients treated with infliximab for injection compared to -0.3 (8.3) in the placebo group (p<0.01). The mean (SD) change from baseline through Week 102 in patients treated with infliximab for injection was 12.5 (9.8) in ASSERT and 11.0 (10.4) in study P01522.
Psoriatic Arthritis
Table 18. Summary of demographics at baseline; randomized subjects in IMIPACT and IMPACT 2
| IMPACT | IMPACT 2 | |||
| Placebo | 5 mg/kg | Placebo | 5 mg/kg | |
| Subjects randomized | 52 | 52 | 100 | 100 |
| Sex | ||||
| N | 52 | 52 | 100 | 100 |
| Male | 30 (57.7%) | 30 (57.7%) | 51 (51.0%) | 71 (71.0%) |
| IMPACT | IMPACT 2 | |||
| Placebo | 5 mg/kg | Placebo | 5 mg/kg | |
| Female | 22 (42.3%) | 22 (42.3%) | 49 (49.0%) | 29 (29.0%) |
| Race | ||||
| N | 100 | 100 | ||
| Caucasian | NA | NA | 94 (94.0%) | 95 (95.0%) |
| NA | NA | 3 (3.0%) | 2 (2.0%) | |
| Asian | NA | NA | 0 (0.0%) | 3 (3.0%) |
| Other | NA | NA | 3 (3.0%) | 0 (0.0%) |
| Age (yrs) | ||||
| N | 52 | 52 | 100 | 100 |
| Mean±SD | 45.2±9.7 | 45.7±11.1 | 46.5±11.3 | 47.1±12.8 |
| Median | 46.5 | 47.0 | 47.0 | 46.5 |
| Range | (26, 70) | (22, 72) | (24.0, 71.0) | (18.0, 80.0) |
| Weight (kg) | ||||
| N | 52 | 52 | 100 | 100 |
| Mean±SD | 81.1±16.0 | 82.9±17.6 | 84.5±20.3 | 87.9±16.5 |
| Median | 81.2 | 81.0 | 81.9 | 86.8 |
| Range | (51, 115) | (49, 120) | (46.8, 175.0) | (56.3, 155.5) |
| Height (cm) | ||||
| N | 48 | 45 | 99 | 100 |
| Mean±SD | 170.8±9.6 | 170.4±9.4 | 169.3±10.0 | 172.4±9.4 |
| Median | 172.5 | 171.0 | 168.0 | 174.0 |
| Range | (149, 192) | (153, 190) | (145.0, 203.0) | (137.0, 193.0) |
Safety and efficacy infliximab for injection were assessed in a multicenter, double-blind, placebo- controlled study (IMPACT 2) in 200 adult patients with active psoriatic arthritis despite DMARD or NSAID therapy (≥5 swollen joints and ≥5 tender joints) with one or more of the following subtypes: arthritis involving DIP joints (n=49), arthritis mutilans (n=3), asymmetric peripheral arthritis (n=40), polyarticular arthritis (n=100), and spondylitis with peripheral arthritis (n=8). Patients also had plaque psoriasis with a qualifying target lesion ≥ 2 cm in diameter. Forty-six percent of patients continued on stable doses of methotrexate (≤25 mg/week). During the 24-week double-blind phase, patients received either 5 mg/kg infliximab for injection or placebo at Weeks 0, 2, 6, 14, and 22 (100 patients in each group). At Week 16, placebo patients with <10% improvement from baseline in both swollen and tender joint counts were switched to infliximab for injection induction (early escape). At Week 24, all placebo-treated patients crossed over to infliximab for injection induction. Dosing continued for all patients through Week 46. At Week 38, patients in the randomized infliximab for injection treatment group with <20% improvement from baseline in the combined swollen and tender joint counts were to have their infliximab for injection dose increased to 10 mg/kg (dose escalation).
IMPACT and IMPACT 2 demographic information of the study populations are summarized in Table
18.
Study Results
Clinical response
Treatment with infliximab for injection resulted in improvement in signs and symptoms, as assessed by the ACR criteria, with 58% of infliximab for injection-treated patients achieving ACR 20 at Week 14, compared with 11% of placebo-treated patients (p<0.001). The response was similar regardless of concomitant use of methotrexate. Improvement was observed as early as Week 2. At 6 months, the ACR 20/50/70 responses were achieved by 54%, 41%, and 27%, respectively, of patients receiving infliximab for injection compared to 16%, 4%, and 2%, respectively, of patients receiving placebo. Similar responses were seen in patients with each of the subtypes of psoriatic arthritis, although few patients were enrolled with the arthritis mutilans and spondylitis with peripheral arthritis subtypes.
Compared to placebo, treatment with infliximab for injection resulted in improvements in the components of the ACR response criteria, as well as in dactylitis and enthesopathy (Table 19). The clinical response was generally maintained through Week 54, and positive results were also observed in placebo-treated patients who crossed over to infliximab for injection therapy.
The results of this study were similar to those seen in an earlier multicenter, randomized, placebo-controlled study (IMPACT) of 104 patients with psoriatic arthritis. Improvement in signs and symptoms were also generally sustained in that study through 98 weeks in the subset of patients who continued during the second year open-label extension.
Table 19. Components of ACR 20 and percentage of patients with 1 or more joints with dactylitis and percentage of patients with enthesopathy at baseline and Weeks 24 and 54
Placebo → Infliximab for injection 5 mg/kga | Infliximab for injection 5mg/kg | |||||
| Patients Randomized | (n=100) | (n=100) | ||||
| Baseline | Week 24 | Week 54 | Baseline | Week 24b | Week 54 | |
| No. of Patients | 100 | 100 | 91 | 100 | 100 | 100 |
| Parameter (medians) | ||||||
| No of Tender Jointsc | 24 | 20 | 8 | 20 | 6 | 7 |
| No. of Swollen Jointsd | 12 | 9 | 3 | 12 | 3 | 3 |
| Paine | 6.4 | 5.6 | 2.0 | 5.9 | 2.6 | 2.6 |
| Physician’s Global Assessmente | 6.0 | 4.5 | 1.1 | 5.6 | 1.5 | 1.1 |
| Patient’s Global Assessmente | 6.1 | 5.0 | 2.5 | 5.9 | 2.5 | 2.8 |
Placebo → Infliximab for injection 5 mg/kga | Infliximab for injection 5mg/kg | |||||
| Patients Randomized | (n=100) | (n=100) | ||||
| Baseline | Week 24 | Week 54 | Baseline | Week 24b | Week 54 | |
| Disability Index (HAQ- DI)f | 1.1 | 1.1 | 0.5 | 1.1 | 0.5 | 0.5 |
| CRP (mg/dL)g | 1.2 | 0.9 | 0.5 | 1.0 | 0.4 | 0.4 |
| % Patients with 1 or more digits with dactylitis | 41 | 33 | 15 | 40 | 15 | 16 |
| % Patients with enthesopathy | 35 | 36 | 20 | 42 | 22 | 21 |
aplacebo-treated patients crossed over to Infliximab for injection at Week 24 b p<0.001 for percent change from baseline in all components of ACR 20 at Week 24, p<0.05 for % of patients with dactylitis, and p=0.004 for % of patients with enthesopathy at Week 24 cScale 0-68 dScale 0-66 eVisual Analog Scale (0=best, 10=worst) f Health Assessment Questionnaire, measurement of 8 categories: dressing and grooming, arising, eating, walking, hygiene, reach, grip, and activities (0=best, 3=worst) g Normal range 0-0.6 mg/dL | ||||||
Improvement in PASI in patients with baseline body surface area (BSA) ≥3% (n=87 placebo, n=83 infliximab for injection) was achieved at Week 14, regardless of concomitant methotrexate use, with 64% of infliximab for injection-treated patients achieving at least 75% improvement from baseline vs. 2% of placebo-treated patients; improvement was observed as early as Week 2. At 6 months, the PASI 75 and PASI 90 responses were achieved by 60% and 39%, respectively, of patients receiving infliximab for injection compared to 1% and 0%, respectively, of patients receiving placebo. The PASI response was generally maintained through Week 54, and positive results were also observed in placebo-treated patients who crossed over to infliximab for injection therapy.
A post-hoc analysis of major clinical response (defined as achieving an ACR 70 response at all visits for a continuous 24 week period during the study) in IMPACT 2 and IMPACT, revealed that 12.1% of infliximab for injection-treated patients were in major clinical response at Week 54. Due to the shorter period of placebo treatment (24 weeks or less), placebo-treated patients were assumed to have had a major clinical response if they achieved an ACR 70 response at the last visit on placebo. Two percent of placebo-treated patients achieved an ACR 70 response at the last visit before receiving infliximab for injection (p=0.006).
In the IMPACT study, 30.8% of patients randomized to infliximab for injection at baseline achieved a major clinical response during the 2-year study. In contrast, 0.0% of patients in the placebo group achieved an ACR 70 response at the last visit before receiving infliximab for injection therapy (p<0.001).
Radiographic response
Structural damage in both hands and feet was assessed radiographically by the change from baseline in the van der Heijde-Sharp (vdH-S) score, modified by the addition of hand DIP joints. The total modified vdH-S score is a composite score of structural damage that measures the number and size of joint erosions and the degree of joint space narrowing in the hands and feet. Table 20 summarizes the mean and median change scores at Weeks 24 and 54. Differences in mean changes at Week 24 indicated that significantly more progression in structural damage was observed in the placebo group (mean=0.82 total score) than in the infliximab for injection group (mean=-0.70 total score). The median change from baseline was 0.00 for both treatment groups. Overall, between-group differences were statistically significant for the total score (p<0.001) and the erosion (p<0.001) and JSN (p=0.013) component scores.
The infliximab for injection-treated patients continued to demonstrate inhibition of structural damage at Week 54 (mean change from baseline in total score=-0.94, p=0.001). Improvement in the placebo group was also demonstrated after these patients crossed over from placebo to infliximab for injection treatment, as evidenced by a decrease in their total modified vdH-S score from 0.82 at Week 24 to 0.53 at Week 54. Between-group differences were also statistically significant for the erosion (p<0.001) and JSN (p=0.047) component scores.
Table 20. Radiographic response at Weeks 24 and 54
Placebo → Infliximab for injection 5 mg/kga | Infliximab for injection 5 mg/kg | |
| Subjects randomized | 100 | 100 |
| Change from baseline Week 24 | ||
| Total modified vdH-S score | ||
| N | 100 | 100 |
| Mean±SD | 0.82±2.62 | -0.70±2.53 |
| Median | 0.00 | 0.00 |
| IQ range | (0.00, 0.50) | (-0.80, 0.00) |
| Range | (-4.50, 12.68) | (-15.00, 4.00) |
| p-value | <0.001 | |
| Erosion score | ||
| N | 100 | 100 |
| Mean±SD | 0.51±1.68 | -0.56±2.09 |
| Median | 0.00 | 0.00 |
| IQ range | (0.00, 0.50) | (-0.51, 0.00) |
| Range | (-3.00, 9.00) | (-12.00, 3.00) |
| p-value | <0.001 | |
| JSN score | ||
| N | 100 | 100 |
| Mean±SD | 0.31±1.29 | -0.14±0.81 |
| Median | 0.00 | 0.00 |
| IQ range | (0.00, 0.00) | (0.00, 0.00) |
| Range | (-2.50, 9.51) | (-4.00, 2.50) |
| p-value | 0.013 | |
| Chase from baseline Week 54 |
Placebo → Infliximab for injection 5 mg/kga | Infliximab for injection 5 mg/kg | |
| Total modified vdH-S score | ||
| N | 100 | 100 |
| Mean±SD | 0.53±2.60 | -0.94±3.40 |
| Median | 0.00 | 0.00 |
| IQ range | (0.00, 0.00) | (-0.50, 0.00) |
| Range | (-6.13, 12.12) | (-29.00, 3.00) |
| p-value | 0.001 | |
| Erosion score | ||
| N | 100 | 100 |
| Mean±SD | 0.42±2.02 | -0.61±2.16 |
| Median | 0.00 | 0.00 |
| IQ range | (0.00, 0.00) | (-0.50, 0.00) |
| Range | (-3.18, 12.12) | (-18.00, 2.00) |
| p-value | <0.001 | |
| JSN score | ||
| N | 100 | 100 |
| Mean±SD | 0.11±0.97 | -0.33±1.37 |
| Median | 0.00 | 0.00 |
| IQ range | (0.00, 0.00) | (0.00, 0.00) |
| Range | (-3.00, 6.01) | (-11.00, 1.00) |
| p-value | 0.047 | |
| a placebo crossed over to infliximab for injection at Week 24 | ||
Radiographic progression was defined as a worsening from baseline in the modified vdH-S score that was greater than the smallest detectable change (SDC) at Week 24. The SDC captures changes greater than measurement error. Significantly more patients in the placebo group (12.0%) had radiographic progression compared with the proportion of patients in the infliximab for injection group (3.0%; p=0.017). Similarly, significant treatment group differences in favor of infliximab for injection were found for radiographic progression based on erosion scores (12.0% of placebo patients vs. 2.0% of infliximab for injection patients; p=0.006) and JSN scores (11.0% vs. 1.0%; p=0.003)
In addition to the analyses based on the change in vdH-S score, and to confirm the radiographic benefit in an individual patient, a radiographic assessment was also done on a subset of patients based on the clinical judgment of the readers, instead of the detailed scoring system.
In the IMPACT study, all radiographic observations of structural damage were from patients at Week 50 who had films of the same hands and feet taken at baseline and Week 50. Although there was no radiographic evaluation at the end of the placebo-controlled period, the IMPACT data showed no radiographic progression from baseline at Week 50 in both treatment groups as measured by changes in the total modified vdH-S scores.
Physical function
Infliximab for injection-treated patients demonstrated improvement in physical function as assessed by HAQ (median percent improvement in HAQ score from baseline to Week 14 and 24 of 42.9% for infliximab for injection-treated patients vs. 0.0% for placebo-treated patients, p<0.001). The median HAQ score at baseline was 1.1 in each treatment group. These responses were maintained through Week 54 in the infliximab for injection-treated patients, and positive results were also observed in the placebo-treated patients who crossed over to infliximab for injection therapy.
Infliximab for injection treatment results in a clinically meaningful response in HAQ scores. During the placebo-controlled portion of the trial (24 weeks), 54.0% of infliximab for injection-treated patients achieved a ≥0.3 units decrease in HAQ compared to 22% of placebo-treated patients (p<0.001). The durability of this response was demonstrated through Week 54. In infliximab for injection-treated patients who achieved >0.3 units decrease in HAQ at Week 14, 74.1% were able to maintain the decrease at Week 54. Over 90% of infliximab for injection-treated patients who achieved >0.3 units decrease in HAQ at both Weeks 14 and 24, were able to maintain the response at Week 54.
In the IMPACT study conducted in 104 patients with psoriatic arthritis, over 84% of infliximab for injection-treated patients who achieved ≥0.3 units decrease in HAQ at the end of 1 year and entered the year 2 extension were able to maintain the response at Week 98.
Infliximab for injection treated patients also demonstrated improvement in health-related quality of life as measured by the physical and mental component summary scores of the SF-36 (median change from baseline to Week 14 of 8.7 and 2.1 for infliximab for injection-treated patients, respectively, vs. 1.0 and 0.5, respectively, for placebo-treated patients). Median baseline scores for the physical component summary score were 32.5 and 29.8 for the infliximab for injection and placebo groups, respectively; median baseline mental component summary scores were 47.0 and 49.7 for the infliximab for injection and placebo groups, respectively. These responses were maintained through Week 54 in the infliximab for injection-treated patients, and positive results were also observed in the placebo-treated patients who crossed over to infliximab for injection therapy.
Active Crohn’s Disease
Table 21. Summary of patient demographics for clinical trials in active Crohn’s disease
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Mean age (range) | Gender and Race n (%) |
| T1618 | Randomised, double-blind, placebo- controlled, single dose-ranging | Single dose of 5 mg/kg, 10 mg/kg, or 20 mg/kg infliximab for injection or placebo administered intravenously | 108 | 37.7 (20 to 65) | 55 (51%) male 53 (49%) female 108 (100%) Caucasian |
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Mean age (range) | Gender and Race n (%) |
T2119,20 (ACCENT I) | Randomised, double-blind, placebo- controlled | Induction therapy: Infliximab 5 mg/kg administered intravenously at Week 0 Maintenance therapy: Placebo at Weeks 2 and 6, then every 8 weeks to Week 46 Infliximab 5 mg/kg at Weeks 2 and 6, then every 8 weeks to Week 46 Infliximab for injection 5 mg/kg at Weeks 2 and 6, then 10 mg/kg every 8 weeks to Week 46 | 573 randomized; 580 enrolled | 37 (18 to 76) | 239 (42%) male 334 (58%) female 549 (96%) Caucasian 12 (2%) Black 5 (1%) Asian 7 (1%) Other |
T67 (SONIC)34 | Phase 3b, multicenter, randomized, double-blind, active -controlled | Group I: Placebo infusions administered at Weeks 0, 2, 6, then every 8 weeks and AZA daily (2.5 mg/kg) Group II: Infliximab for injection infusions (5 mg/kg) administered at Weeks 0, 2. 6, then every 8 weeks and placebo daily Group III: Infliximab for injection infusions (5 mg/kg) administered at Weeks 0, 2, 6 then every 8 weeks and AZA daily (2.5 mg/kg) | Main study (entered/completed): 508 /318 Group I: 170/86 Group II: 169/111 Group III: 169/121 Study extension (entered/completed): Group I: 75/67 Group II: 97/85 Group III: 108/90 | Main study 36.3 (18-80) Study extension: 36.9 (18-80) | Main Study: M: 262 (52%) F: 246 (48%) 435 Caucasian (92.8%) 21 Black (4.5%) 2 Asian (0.4%) 11 Other (2.3%) |
The safety and efficacy of single and multiple doses of infliximab for injection were assessed in two randomised, double-blind, placebo-controlled clinical studies in adult patients with moderately to severely active Crohn’s disease [Crohn’s Disease Activity Index (CDAI) 220 and 400]. Patients receiving aminosalicylates, corticosteroids and/or immunomodulatory agents were permitted. The safety and efficacy of infliximab for injection was also assessed in a randomized, double-blind, active-controlled clinical study (SONIC) in immunomodulator - naïve adult patients with moderate to severe Crohn’s disease (CDAI ≥220 and ≤450). A summary of the design and subject demographics of the three studies is presented in Table 21.
Study Results
In the single-dose trial18 of 108 patients (T16), 16% of placebo patients achieved a clinical response (decrease in CDAI 70 points) at Week 4 vs. 81% of patients receiving 5 mg/kg infliximab for injection (p<0.001). Additionally, 4% of placebo patients and 48% of patients receiving 5 mg/kg infliximab for injection achieved clinical remission (CDAI<150) at Week 4 (Table 22).
Table 22. Number of patients achieving clinical response or clinical remission at Week 4 following a single intravenous infusion
| Parameter | Placebo | 5 mg/kg Infliximab for injection | p-valuea |
| Number of patients achieving clinical responseb | 4/25 (16%) | 22/27 (81%) | <0.001 |
| Number of patients achieving clinical remissionc | 1/25 (4%) | 13/27 (48%) | <0.01 |
a two-sided Fisher’s Exact test b 70-point reduction in CDAI c reduction in CDAI to below 150 points | |||
In a multidose trial19,20 (ACCENT I), 580 patients received 5 mg/kg at Week 0. Patients assessed by the investigator to be in clinical response (decrease in CDAI score of ≥25% and ≥70 points) at Week 2 were randomized to one of three treatment groups; the placebo maintenance group received placebo at Weeks 2 and 6, and then every 8 weeks; the 5 mg/kg maintenance group received 5 mg/kg at Weeks 2 and 6, and then every 8 weeks; and the 10 mg/kg maintenance group received 5 mg/kg at Weeks 2 and 6, and then 10 mg/kg every 8 weeks. The co-primary endpoints were the proportion of patients in clinical remission (CDAI <150) at Week 30 and time to loss of response through Week 54. Corticosteroid taper was permitted after Week 6. The results for the two co-primary endpoints and key secondary endpoints are summarized in Table 23.
Table 23. Efficacy results of study T21 (ACCENT I) in active Crohn’s disease: Patients randomized as responders
| Parameter | Placebo | Infliximab for injection Maintenance | ||
| 5 mg/kg | 10 mg/kg | Combined | ||
| Number of patients achieving clinical remissiona at Week 30 | 23/110 (21%) | 44/113 (39%) p=0.003 | 50/112 (45%) p<0.001 | 94/225 (42%) p<0.001 |
| Median time to loss of responseb through 54 (weeks) | 19 | 38 p=0.002 | >54 p<0.001 | 46 p<0.001 |
| IBDQ median change from baseline at Week 30 | 12 | 24 p=0.015 | 30 p=0.001 | 28 p=0.001 |
| Proportion of patients in clinical remissiona and not receiving steroids at Week 30 (patients not on steroids at baseline) | 6/56 (11%) | 18/58 (31%) p=0.008 | 21/57 (37%) p=0.001 | 39/115 (34%) p=0.001 |
a reduction in CDAI to below 150 points b reduction in CDAI score of >25% and >70 points | ||||
18 Targan SR, Hanauer SR, van Deventer SJH, Mayer L, Present D, Braakman T, DeWoody K, Schaible TF, Rutgeerts PJ. A short-term study of chimeric monoclonal antibody cA2 to tumour necrosis factor α for Crohn’s disease. N Engl J Med 1997;337(15):1029-1035. 19 Hanauer SB, Feagan BG, Lichtenstein GR et al. Maintenance infliximab for Crohn’s disease: the ACCENT I randomised trial. Lancet 2002;359:1541-1549.
20 Rutgeerts P, Feagan BG, Lichtenstein GR et al. Comparison of scheduled and episodic treatment strategies of infliximab in Crohn’s disease. Gastroenterology 2004;126:402-413.
At Week 2, 58% (335) of 573 randomized patients were assessed by the investigator to be in clinical response. A significantly greater proportion of these patients in the 5 mg/kg and 10 mg/kg maintenance groups achieved clinical remission at Week 30, compared with patients in the placebo maintenance group (Figure 3) and similar results were seen at Week 54. Patients in the infliximab for injection maintenance groups had significantly longer time to loss of response than patients in the placebo maintenance group (p<0.001). The median time to loss of response was 46 weeks in the combined infliximab for injection maintenance group versus 19 weeks in the placebo maintenance group. Eighty-nine percent (50/56) of patients who lost clinical response on infliximab for injection 5 mg/kg every eight week maintenance dosing, responded to a 10 mg/kg infliximab for injection infusion.
Figure 3. Proportion of patients who were in clinical remission (CDAI<150) at Week 30. Patients included all those randomized as responders.
Improvement in health-related quality of life was assessed using the SF-36 and the disease- specific Inflammatory Bowel Disease Questionnaire (IBDQ).25 Median improvement from baseline in IBDQ score was significantly greater in the 5 mg/kg (p=0.015) and 10 mg/kg (p=0.001) maintenance groups compared to the placebo maintenance group at Week 30 with similar results at Week 54.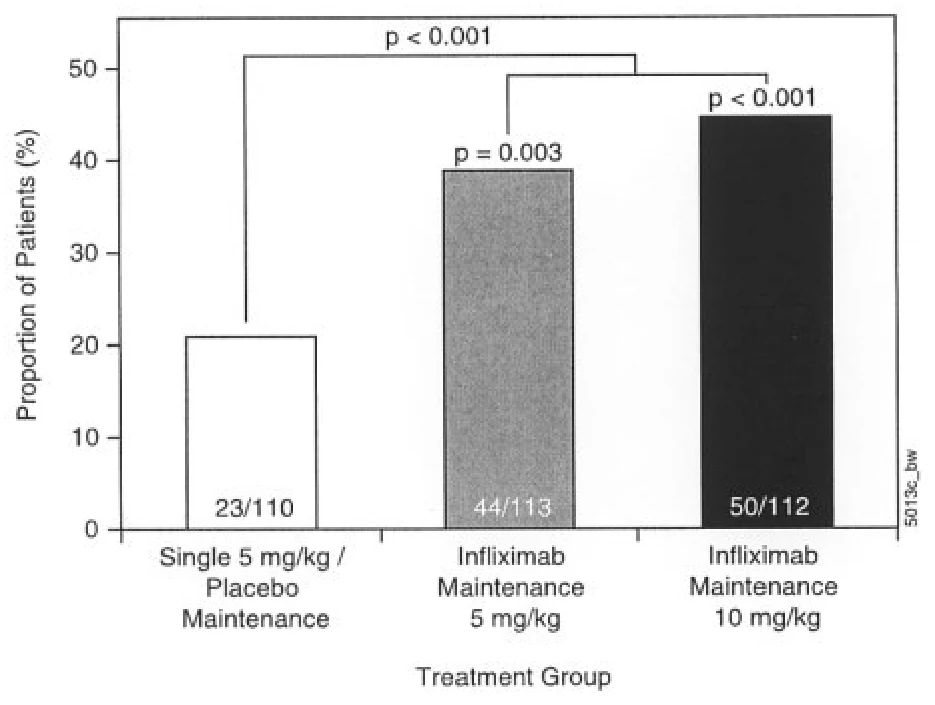 25
As shown in Figure 4 for patients receiving corticosteroids at baseline, the proportion of these patients in clinical remission and not receiving corticosteroids at Week 30 was 31% for the 5 mg/kg maintenance group and 37% for the 10 mg/kg maintenance group, compared with 11% of patients in the placebo maintenance group (p=0.008 and p=0.001, for the 5 mg/kg and 10 mg/kg maintenance groups, respectively). By Week 22, the median corticosteroid dose at baseline (20 mg/day) was reduced to 10 mg/day in the placebo maintenance group; in the infliximab for
25 Irvine EJ, Feagan B, Rochon J, et al. Quality of life: a valid and reliable measure of therapeutic efficacy in the treatment of inflammatory bowel disease. Canadian Crohn’s Relapse Prevention Trial Study Group. Gastroenterol. 1994;106(2):287-296. injection maintenance group it was reduced to 0 mg/day, indicating that at least 50% of these patients were able to discontinue steroid use. Results were similar at Week 54.
Figure 4. Proportion of patients who were in clinical remission (CDAI <150) and were not receiving corticosteroid at Week 30. Patients included all those randomized as responders.
In a subset of patients who had mucosal ulceration at baseline and who participated in an endoscopic substudy, 10 of 32 patients in the infliximab for injection maintenance group had endoscopic evidence of mucosal healing compared with 0 of 17 patients in the placebo group at Week 10. Of the infliximab for injection treated patients showing mucosal healing at Week 10, 7 of 19 patients also showed mucosal healing at 54 weeks.
The safety and efficacy of infliximab for injection were assessed in a randomized, double-blind, 30-week study (SONIC) in 508 adult patients with moderate to severe Crohn’s disease (CDAI ≥220 and ≤450) naïve to biologics and immunomodulators such as azathioprine (AZA). Two infliximab for injection treatment regimens; infliximab for injection combination therapy (infliximab for injection 5 mg/kg at 0, 2, 6 weeks then every 8 weeks plus a comparator [azathioprine (AZA) 2.5 mg/kg daily]) and infliximab for injection monotherapy (infliximab for injection 5 mg/kg at 0, 2, 6 weeks then every 8 weeks plus placebo capsules), were compared to the comparator [azathioprine (AZA) 2.5 mg/kg daily]) alone. Of the 318 randomized patients who completed the study through Week 30, 280 patients entered a double-blind study extension to evaluate the long-term efficacy and safety of infliximab for injection and/or AZA through Week 54. Patients were permitted to take concomitant doses of corticosteroids and/or aminosalicylates; 42% and 54% of patients, respectively, were taking these medications at study start.
A significantly greater proportion of patients receiving infliximab for injection combination therapy or infliximab for injection monotherapy achieved the primary endpoint of corticosteroid-free clinical remission (defined as patients in clinical remission [CDAI of <150] who had not taken oral systemic corticosteroids [prednisone or equivalent] for at least 3 weeks and had not taken budesonide at a 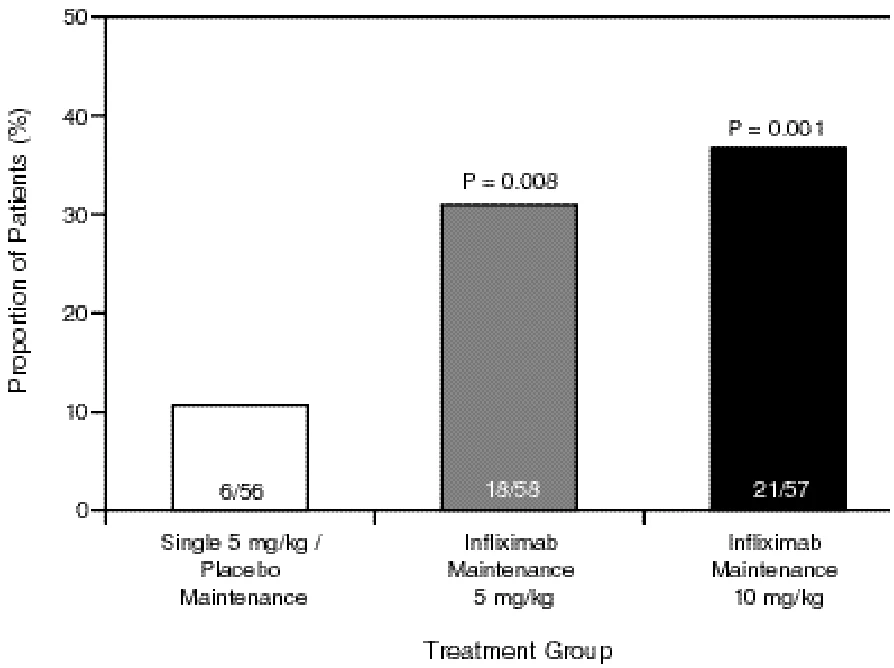 dose >6 mg/day for at least 3 weeks) at Week 26 compared to patients receiving AZA monotherapy (Figure 5).
Figure 5. Proportion of patients in corticosteroid-free clinical remission at Week 26 – all patients randomized in SONIC
At Week 50, 35% (P=0.028) of patients in the infliximab for injection monotherapy treatment group and 46% (P<0.001) of patients in the infliximab for injection combination treatment group were in corticosteroid-free clinical remission compared to 24% of patients in the AZA monotherapy arm.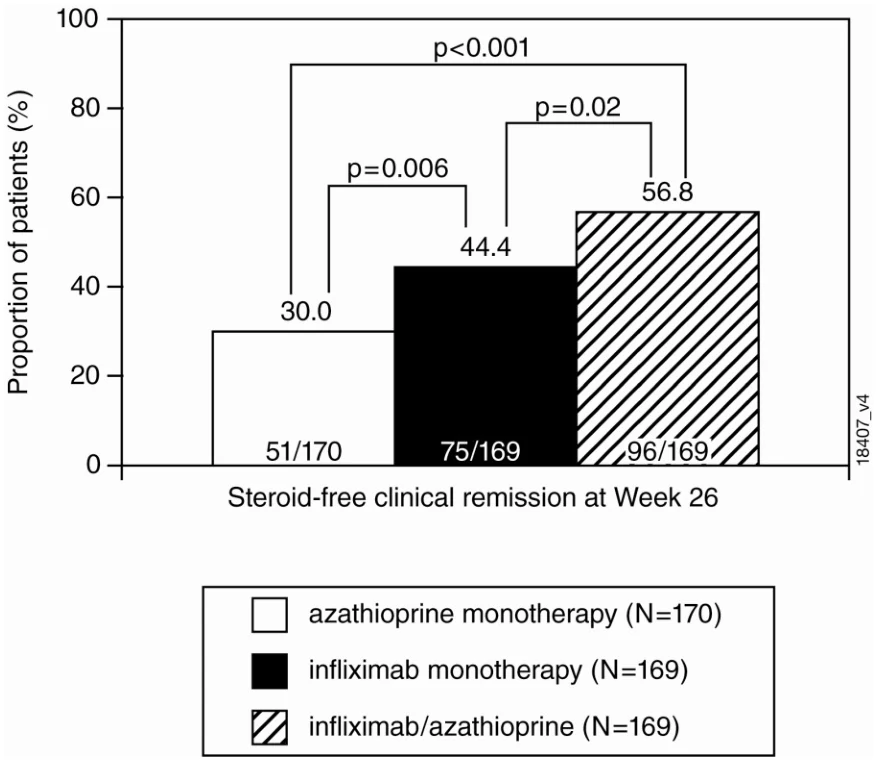 *
At Week 26 and 50, comparable numbers of patients remained corticosteroid free for ≥3 weeks in the three treatment groups.
Among the 508 patients randomized in SONIC, 309 patients had mucosal ulcerations at baseline (as determined by a video endoscopy). Of these patients, significantly more patients receiving infliximab for injection as combination therapy achieved mucosal healing (defined as the complete absence of mucosal ulcerations in the colon and terminal ileum as assessed by video endoscopy) at Week 26 compared to patients receiving AZA alone (43.9%; 47/107 vs. 16.5%; 18/109; p<0.001). More patients receiving infliximab for injection as monotherapy achieved mucosal healing than those receiving AZA alone (30.1%; 28/93 vs.16.5%; 18/109; p=0.02).
Fistulising Crohn’s Disease
*When controlling the overall Type I error rate of 0.05 using the Bonferroni multiple comparisons method, the P value considered to be statistically significant was set at 0.008 (2-sided).
Table 24. Summary of patient demographics for clinical trials in Fistulising Crohn’s Disease
| Study # | Study design | Dosage, route of administration, and duration | Number of subjects | Mean age (years) (range) | Gender |
| T20 | Randomised, double-blind, placebo- controlled. | 5 mg/kg infliximab for injection, 10 mg/kg infliximab for injection or placebo administered intravenously at Weeks 0, 2 and 6. | 94 | 37 (18 to 63) | 47% male 53% female |
| ACCENT II | Randomised, double-blind, placebo- controlled. | 5 mg/kg Infliximab for injection, administered intravenously at Weeks 0, 2 and 6 followed by 5 mg/kg infliximab for injection or placebo maintenance dosing every 8 weeks through Week 46. | 306 | 39 (18 to 78) | 51% male 49% female |
The safety and efficacy of infliximab for injection were assessed in two randomised, double-blind, placebo controlled studies. These studies, T20 and T26 (ACCENT II), included patients with fistulising Crohn’s disease with fistula(s) that were of at least 3 months duration.22,23 Concurrent use of stable doses of corticosteroids, 5-ASA, antibiotics, methotrexate (MTX), 6- mercaptopurine (6-MP) and/or azathioprine (AZA) was permitted.
A summary of patient demographics and design of the two studies is presented in Table 24. In ACCENT II, patients may have been enrolled with rectovaginal fistulas as well as draining enterocutaneous (perianal, abdominal) fistula(s). At Week 14 in ACCENT II, patients in fistula response (defined as ≥50% reduction from baseline in the number of draining fistulas) at both Weeks 10 and 14 were randomised separately from those not in response to receive either placebo or 5 mg/kg infliximab for injection maintenance dosing at Week 14 and then every eight weeks through Week 46.
Study Results
Table 25 presents the results of the primary and secondary endpoints of study T20. In addition to these results, the median time to onset of response and median duration of response in infliximab for injection treated patients in the T20 study were 2 and 12 weeks, respectively.
Table 25. Results of study T20 in fistulizing Crohn’s diseasea
| Primary Endpoint | Placebo | Infliximab for injection |
| ≥50% reduction from baseline in the number of draining fistulas for at least 2 consecutive visits | 8/31 (26%) | 5 mg/kg: 21/31 (68%), p=0.002 10 mg/kg: 18/32 (56%), p=0.021 Combined: 39/63 (62%), p=0.002 |
| Secondary Endpoint | ||
| Closure of all fistulas | 4/31 (13%) | 5 mg/kg: 20/31 (65%), p≤0.001 10 mg/kg: 13/32 (41%), p=0.022 Combined: 33/63 (52%), p≤0.001 |
| a all p-values are compared to placebo | ||
22 Present DH, Rutgeerts P, Targan S, et al. Infliximab for the treatment of fistulas in patients with Crohn’s disease. N Engl J Med 1999;340:1398-1405.
23 Sands BE, Anderson FH, Bernstein CN, et al. Infliximab maintenance therapy fistulizing Crohn’s disease. N Engl J Med 2004;350:876-885.
The primary endpoint of ACCENT II study was the time from randomization to loss of fistula response among patients who were in fistula response at Week 14. At the time of randomization (Week 14), 69% (195/282) of patients were in fistula response. A significantly longer time to loss of fistula response was seen in the infliximab for injection maintenance group compared with the placebo maintenance group (p<0.001, Figure 6). The median time to loss of fistula response following randomization was >40 weeks for patients in the infliximab for injection maintenance group compared with 14 weeks for patients in the placebo maintenance group. Subgroup analyses of the proportion of patients in fistula response at Week 54 showed that infliximab for injection maintenance was significantly better than placebo maintenance for patients with baseline CDAI ≥150. The analyses also suggested that infliximab for injection maintenance was better than placebo maintenance for patients with baseline CDAI<150; however, these analyses were based on a small number of patients and the results were not significant.
Figure 6. Fistula response over time 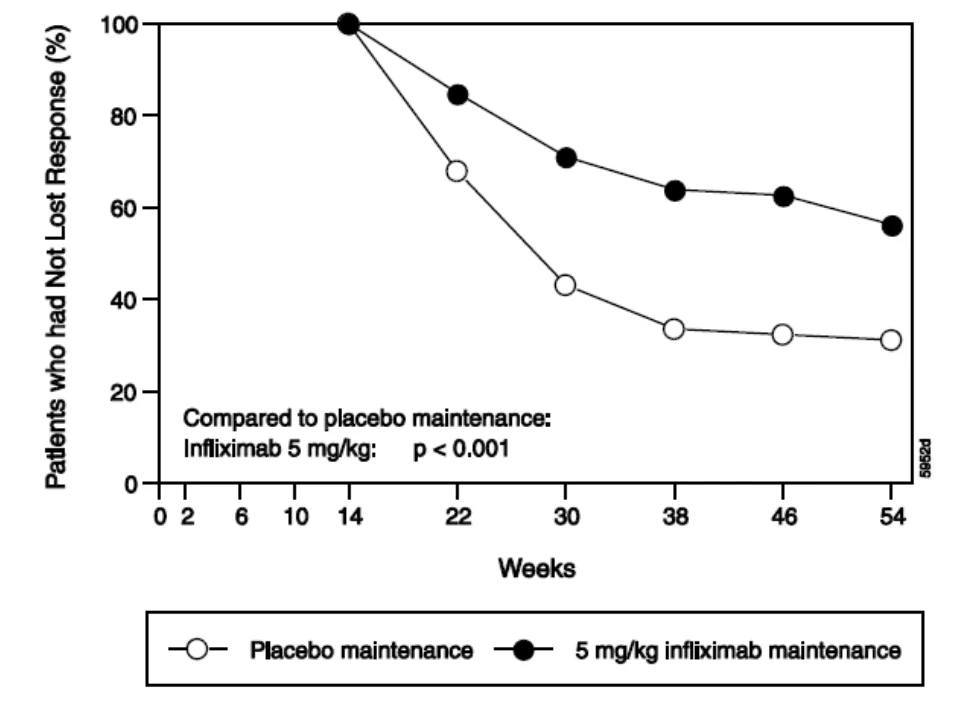
Table 26. Number of patients randomized as responders who lost fistula response by category
| Placebo Maintenance | Infliximab for injection Maintenance | |
| Patients randomized | 99 | 96 |
| Patients who lost fistula response | 61 (62%) | 40 (42%) |
| Loss of response category | ||
| Reduction from baseline in number of draining fistulas that was <50% over 4 weeks or more | 16 (16%) | 13 (14%) |
| Change in medication | 31 (31%) | 19 (20%) |
| Surgical procedure for Crohn’s disease | 0 (0%) | 1 (1%) |
| Crossover to treatment with increased dose of Infliximab for injection | 13 (13%) | 7 (7%) |
| Discontinuation due to lack of efficacy | 1 (1%) | 0 (0%) |
The results of secondary endpoints in ACCENT II are presented in Table 27.
Table 27. Results of study T26 (ACCENT II) in fistulising Crohn’s diseasea
| Secondary Endpoints | Placebo Maintenance | Infliximab for injection Maintenance |
| Number of patients with all fistulas closed at Week 30 | 26/98 (27%) | 46/96 (48%), p=0.002 |
| Number of patients with all fistulas closed at Week 54 | 19/98 (19%) | 33/91 (36%), p=0.009 |
| Median duration of fistula closure | 23 weeks | 40 weeks, p<0.001 |
| Number of patients developing new fistulas | 19/99 (19%) | 14/96 (15%), p=0.391 |
| Number of patients with all fistulas closed at every week from Week 22 to Week 54 | 16/99 (16%) | 23/96 (24%), p=0.174 |
| Number of patients in CDAI response at Week 30b | 9/31 (29%) | 17/33 (52%), p=0.067 |
| Number of patients in CDAI response at Week 54b | 2/31 (7%) | 12/33 (36%), p=0.004 |
Number of patients in CDAI remission at Week 30 who were not in remission at baselineb | 11/57 (19%) | 24/57 (42%), p=0.008 |
Number of patients in CDAI remission at Week 54 who were not in remission at baselineb | 6/57 (11%) | 17/57 (30%), p=0.010 |
| Number of patients in CDAI remission at Week 30 who were in remission at baselineb | 18/40 (45%) | 26/39 (67%), p=0.053 |
| Number of patients in CDAI remission at Week 54 who were in remission at baselineb | 15/40 (38%) | 21/39 (54%), p=0.145 |
| Secondary Endpoints | Placebo Maintenance | Infliximab for injection Maintenance |
| Median IBDQ improvement from baseline at Week 30c | 4 | 14, p=0.002 |
| Median IBDQ improvement from baseline at Week 54c | 5 | 10, p=0.029 |
| Mean number of hospitalizations per patients | 0.31 | 0.11, p=0.021 |
| Mean number of surgeries and procedures per patients | 1.26 | 0.65, p=0.111 |
a all p-values are compared to placebo b CDAI response is a reduction from baseline CDAI score of ≥25% and ≥70 points in patients with a baseline score of ≥220. CDAI remission is a CDAI score of <150 points. The possible range for CDAI scores is from 0 to >750. c The possible range for IBDQ scores is from 32 to 224. ACCENT II did not specify a minimally important difference for a change in IBDQ score. | ||
Patients who responded to treatment and subsequently lost their fistula response in ACCENT II were eligible to cross over to treatment with infliximab for injection at 5 mg/kg, if receiving placebo, or to a higher dose of infliximab for injection (10 mg/kg), if receiving infliximab for injection. For patients who lost fistula response, treatment with an increased dose tended to re-establish fistula response.
Reduction in average daily corticosteroid dose was greater in the infliximab for injection maintenance group compared with the placebo maintenance group at all time points.
In the ACCENT II study, there was no difference between maintenance arms for proportions of patients with newly diagnosed fistula-related abscesses. The adverse event proctalgia was reported more frequently in subjects receiving infliximab for injection maintenance compared with placebo maintenance.
Active Crohn’s Disease in Pediatric Patients
Table 28. Summary of patient demographics for clinical trials in active pediatric Crohn’s disease
| Study # | Study Design | Dosage, route of administration and duration | Study Subjects (n) | Mean age (range) | Gender and Race n (%) | |
| T55 | Phase 1 Open-label, single- dose study | Single intravenous infusion of 5 mg/kg infliximab for injection | 6 | 9.5 (9.0 – 11.0) | 4 (66.7%) 2 (33.3%) 6 (100.0%) 0 (0.0%) 0 (0.0%) 0 (0.0%) | female male Caucasian Black Asian Other |
The safety and efficacy of infliximab for injection was assessed in a randomised, single-dose, multicenter Phase 2 study (T23) of 21 pediatric patients who were 11 to 17 years old (median age 15.0) with active Crohn’s disease (median Pediatric Crohn’s Disease Activity Index [PCDAI] of 43) despite use of corticosteroids or immunomodulators (57% were receiving 6-MP or AZA and an additional 14% were receiving MTX; and 91% were receiving corticosteroids at study entry). Eight of the 21 pediatric patients enrolled in T23 participated in its extension. The safety and efficacy of infliximab for injection were also assessed in a randomised, multiple-dose, open-label, multicenter Phase 3 study (REACH) in 112 pediatric patients 6 to 17 years old (median age 13.0 years) with moderately to severely active Crohn’s disease (median PCDAI of 40) and an inadequate response to conventional therapies. In REACH, all subjects were required to be on a stable dose of 6-MP, AZA, or MTX (35% were also receiving corticosteroids at baseline).
A summary of patient demographics and design of the REACH trial is presented in Table
28.
In the Phase 2 single-dose trial (T23) of 21 pediatric patients, all patients achieved a clinical response (decrease in CDAI ≥70 points or decrease in PCDAI ≥10 points) at some point in the 20 weeks following the single dose of infliximab for injection. Clinical remission, defined as a reduction in the modified CDAI score to below 150 points or a reduction in the PCDAI to below 10 points, was achieved in 10 patients (47.6%; 16.7% in the 1 mg/kg, 57.1% in the 5 mg/kg, and 62.5% in the 10 mg/kg infliximab for injection treatment groups). All 7 patients who had fistulising disease had their fistulas closed at a minimum of 1 evaluation visit.
| T23 | Phase 1/2 Randomised, dose- blinded, single-dose study with an open- label retreatment extension | Single intravenous infusion of 1 mg/kg, 5 mg/kg, or 10 mg/kg infliximab for injection Retreatment extension: up to 8 intravenous infusions of 5 mg/kg infliximab for injection over a 48-week period | 21 8 / 21 | 14.6 (11.0-17.0) | 6 (28.6%) 15 (71.4%) 19 (90.5) 2 (9.5%) 0 (0.0%) 0 (0.0%) | female male Caucasian Black Asian Other |
| T47 | Phase 3 Randomised, open- label study of induction and maintenance therapy | Intravenous infusions of infliximab for injection 5 mg/kg for all patients at weeks 0, 2, and 6 Patients in clinical response at week 10 randomised to maintenance treatment with intravenous infusions of 5 mg/kg infliximab for injection either q8 weeks or q12 weeks | 112 103 / 112 | 13.3 (6.0 – 17.0) | 46 (41.1%) 66 (58.9%) 94 (83.9%) 15 (13.4%) 1 (0.9%) 2 (1.8%) | female male Caucasian Black Asian Other |
In the Phase 3 multidose trial (REACH), 112 patients received 5 mg/kg infliximab for injection at weeks 0, 2, and 6. Patients assessed by the investigator to be in clinical response (defined as a decrease from baseline in the PCDAI score of ≥15 points and total PCDAI score of ≤30 points) at week 10 (n=103) were randomised to 1 of 2 treatment groups and received either 5 mg/kg infliximab for injection q8 weeks or q12 weeks as a maintenance treatment regimen. If response was lost during maintenance treatment, crossing over to a higher dose (10 mg/kg) or shorter dosing interval (q8 weeks) was allowed.
In REACH, the proportion of patients achieving clinical response at week 10 was 88.4% (99/112) compared with 66.7% (128/192) in adults (ACCENT I). Similarly, the proportion of patients achieving clinical remission, defined as a PCDAI score of ≤10 points, at week 10 was 58.9% (66/112) compared with 39.1% (75/192) in adults (ACCENT 1).
In REACH, at weeks 30 and 54, the proportion of patients in clinical response was determined for both maintenance treatment groups (Figure 7). At week 30, the proportion of patients in clinical response was significantly higher in the q8 week (73.1%, 38/52) than in the q12 week maintenance treatment group (47.1%, 24/51; p=0.007). At week 54, the proportion of patients in clinical response was also significantly higher for subjects in the q8 week (63.5%, 33/52) than in the q12 week maintenance treatment group (33.3%, 17/51; p=0.002).
Figure 7. Clinical response at Week 30 and 54 – Infliximab for injection 5 mg/kg q8 weeks and
Infliximab for injection 5 mg/kg q12 weeks
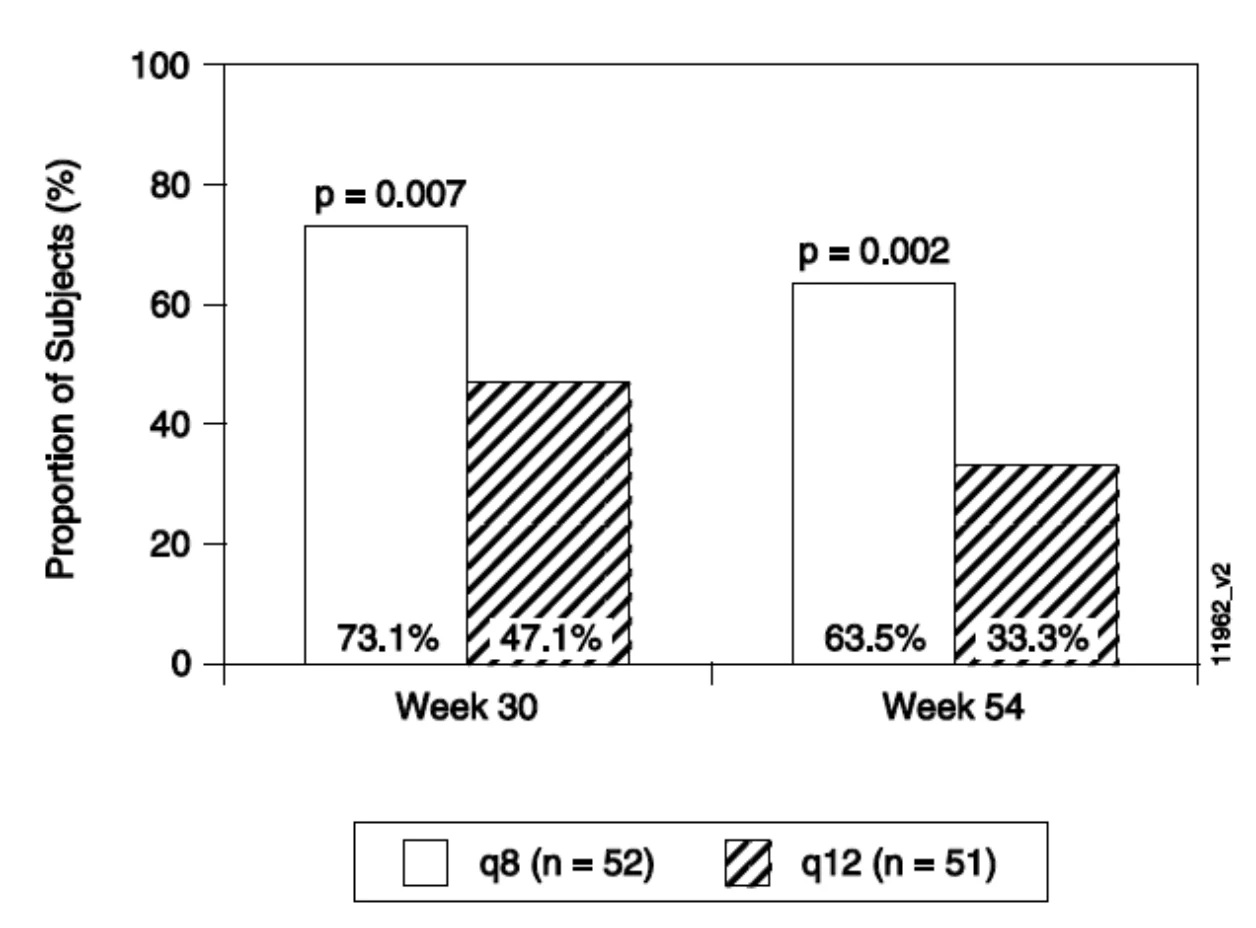
At week 30 of the REACH trial, the proportion of patients in clinical remission was significantly higher in the q8 week maintenance treatment group (59.6%, 31/52) than in the q12 week maintenance treatment group (35.3%, 18/51; p=0.013). At week 54, the proportion of patients in clinical remission was also significantly higher for patients in the q8 week (55.8%, 29/52) than in the q12 week (23.5%, 12/51; p<0.001) maintenance treatment groups (Figure 8).
Figure 8. Clinical remission at Week 30 and 54 – Infliximab for injection 5 mg/kg q8 weeks and
Infliximab for injection 5 mg/kg q12 weeks
For randomised patients in REACH, the average daily corticosteroid dose was significantly lower than baseline at weeks 10, 30, and 54. The proportion of patients able to discontinue corticosteroids while in remission at week 30 was 45.8% and 33.3% for the q8 week and q12 week maintenance groups, respectively. At week 54, the proportion of patients able to discontinue corticosteroids while in remission was 45.8% and 16.7% for the q8 and q12 week maintenance groups, respectively. In both groups, the average corticosteroid dose decreased so that half of the patients had discontinued corticosteroids by their first maintenance visit 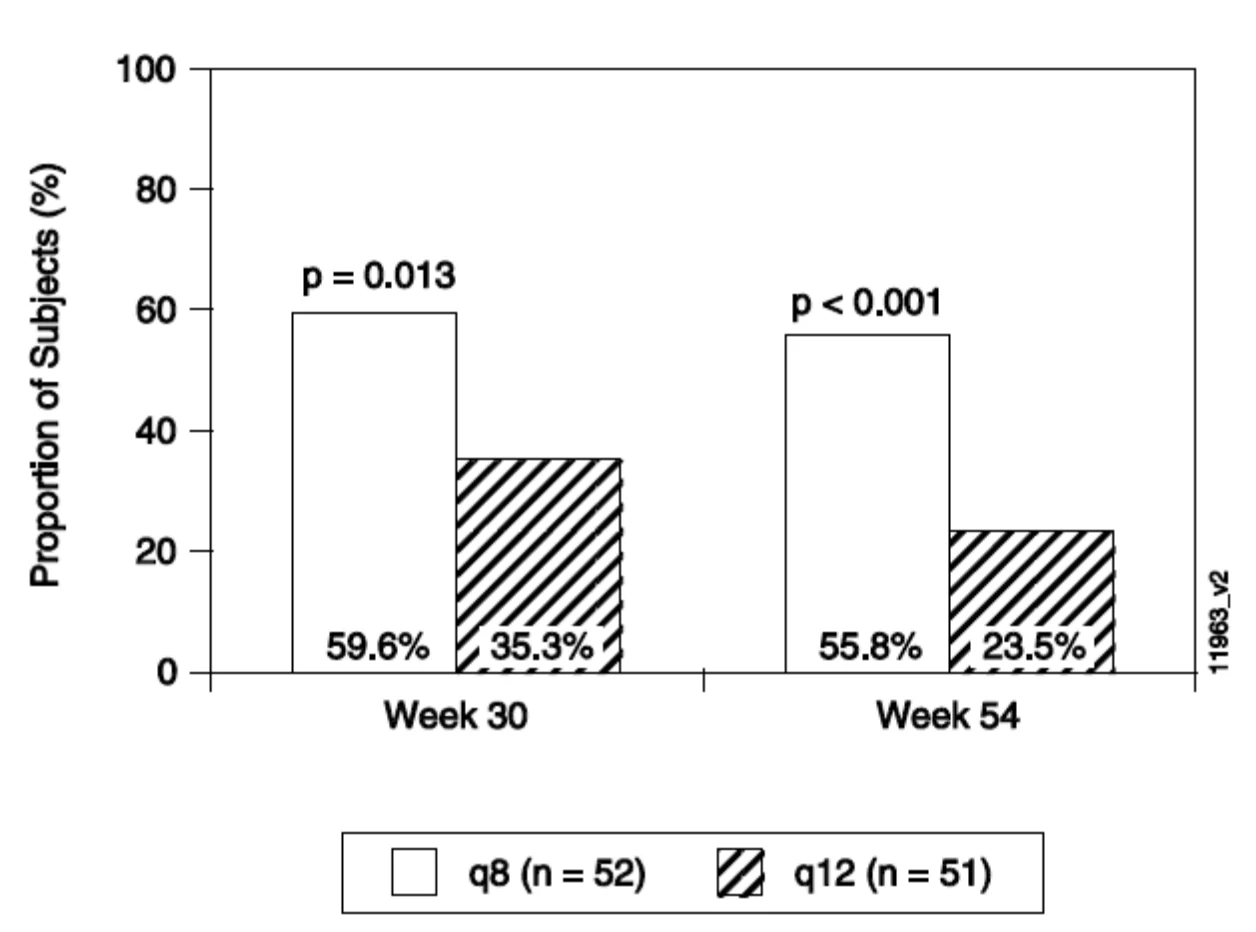 (week 14 for the q8 week and week 18 for the q12 week maintenance treatment group) (Figure 9).
Figure 9. Summary of median daily corticosteroid (prednisone equivalent) dose (mg/kg/day) through Week 54; randomized subjects taking corticosteroids at baseline
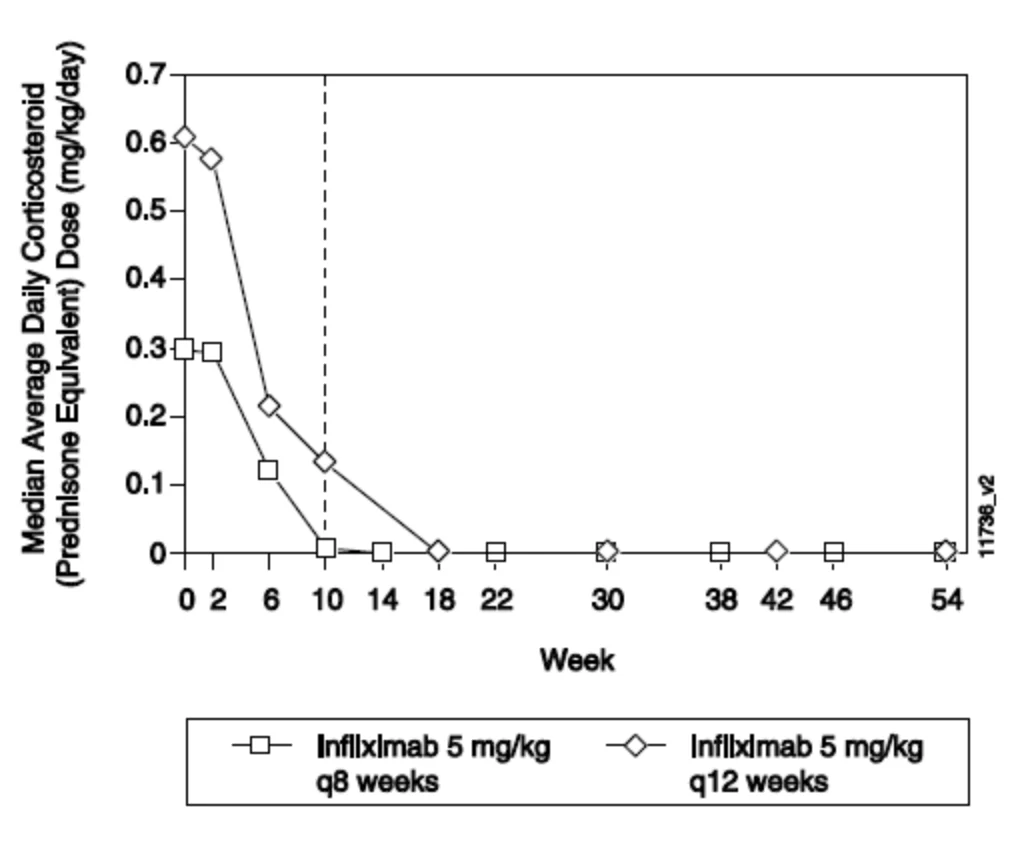
Table 29 presents the results of the primary and secondary endpoints of the REACH trial.
Table 29. Results of study T47 (REACH) in pediatric patients with Crohn’s disease (all randomized subjects)
| Primary and Secondary Endpoints | Infliximab for injection | ||
| q8 weeks | q12 weeks | Combined | |
| Number of subjects in clinical responsea | |||
| Week 10 (Primary Endpoint) | 99/112 (88.4%)e | ||
| Week 30 | 38/52 (73.1%) | 24/51 (47.1%), p=0.007b | 62/103 (60.2%) |
| Week 54 | 33/52 (63.5%) | 17/51 (33.3%), p=0.002b | 50/103 (48.5%) |
| Number of subjects in clinical remissionc | |||
| Week 10 | 66/112 (58.9%)e | ||
| Week 30 | 31/52 (59.6%) | 18/51 (35.3%), p=0.013b | 49/103 (47.6%) |
| Week 54 | 29/52 (55.8%) | 12/51 (23.5%), p<0.001b | 41/103 (39.8%) |
| Primary and Secondary Endpoints | Infliximab for injection | ||
| q8 weeks | q12 weeks | Combined | |
| Number of subjects in clinical remissionc off corticosteriods | |||
| Week 30 | 11/24 (45.8%) | 4/12 (33.3%), p=0.473b | 15/36 (41.7%) |
| Week 54 | 11/24 (45.8%) | 2/12 (16.7%), p=0.086b | 13/36 (36.1%) |
| Mean improvement from baseline in daily corticosteroid (P.Eq) dose (mg/kg/day) | |||
| Week 10 | - | - | 0.3, p<0.001d |
| Week 30 | -0.3 | -0.5, p=0.449b | 0.4, p<0.001d |
| Week 54 | -0.3 | -0.5, p=0.434b | 0.4, p=0.001d |
| Mean improvement from baseline in IMPACT III | |||
| Week 10 | - | - | 23.9, p<0.001d |
| Week 30 | - | - | 21.1, p<0.001d |
| Week 54 | - | - | 24.3, p<0.001d |
| Mean improvement from baseline in z-score | |||
| Week 30 | - | - | 0.3, p<0.001d |
| Week 54 | - | - | 0.5, p<0.001d |
| Number of subjects with at least 0.5 SD improvement in z-score | |||
| Week 30 | 8/23 (34.8%) | 2/15 (13.3%) | 10/38 (26.3%) |
| Week 54 | 10/23 (43.5%) | 3/15 (20.0%) | 13/38 (34.2%) |
| Number of subjects with at least 1.0 SD improvement in z-score | |||
| Week 30 | 1/23 (4.3%) | 0/15 (0%) | 1/38 (2.6%) |
| Week 54 | 3/23 (13.0%) | 1/15 (6.7%) | 4/38 (10.5%) |
a Clinical response is defined as a decrease from baseline in the PCDAI score of at least 15 points with a total score of no more than 30 points. b p-values are comparing the q8 and q12 week maintenance treatment groups using a chi-square test. c Clinical remission is defined as a PCDAI score of ≤10 points. d p-values are comparing the post baseline measurement with the baseline measurement using a paired t-test. e All treated subjects. | |||
The incidence of infections at Week 10 and at Week 54 was reported as numerically greater in the q8 week maintenance treatment group than in the q12 week maintenance treatment group, however, the incidence of serious infections was similar.
The extent to which patients were affected by their bowel disease was assessed using IMPACT III (a questionnaire with a possible score ranging from 35 to 175 specifically developed and validated for use in pediatric inflammatory bowel disease) in a subset of North American patients. Significant improvement from baseline in the IMPACT III score was observed at week 10 (23.9 for randomised subjects and 22.9 for treated subjects, p<0.001) and at weeks 30 and 54 (21.1 and 24.3, for all randomised subjects, respectively, p<0.001 for all time points) in patients treated with infliximab for injection.
The height z-score is a measure of the deviation of the pediatric patient’s height from the expected height for a population of the same age and gender. By week 54, in children with a delayed bone age who had received 5 mg/kg of infliximab for injection q8 weeks (n=23 at baseline), 43.5% had improved their height z-score by at least ½ standard deviation, and 13.0% had improved their height z-score by at least 1 standard deviation by week 54 (based on the reference population).
Plaque Psoriasis
Table 30. Summary of demographics at baseline; randomized subjects in EXPRESS, and EXPRESS II
| EXPRESS | EXPRESS II | |
| Subjects randomized | 378 | 835 |
| Sex | ||
| N | 378 | 835 |
| Male | 268 (70.9%) | 554 (66.3%) |
| Female | 110 (29.1%) | 281 (33.7%) |
| Race | ||
| N | 378 | 835 |
| Caucasian | 369 (97.6%) | 773 (92.6%) |
| 2 (0.5%) | 19 (2.3%) | |
| Asian | 4 (1.1%) | 23 (2.8%) |
| Other | 3 (0.8%) | 20 (2.4%) |
| Age (yrs) | ||
| N | 378 | 835 |
| Mean±SD | 42.8±11.9 | 44.0±12.7 |
| Median | 42 | 44 |
| IQ range | (34.0, 51.0) | (34.0, 53.0) |
| Range | (19.0, 76.0) | (18.0, 80.0) |
| Weight (kg) | ||
| N | 375 | 835 |
| Mean±SD | 86.6±19.8 | 91.9±22.8 |
| Median | 86 | 88.9 |
| IQ range | (73.2, 96.5) | (76.0, 104.0) |
| Range | (43.0, 162.3) | (44.3, 184.2) |
| Height (cm) | ||
| N | 377 | 835 |
| Mean±SD | 172.6±10.0 | 171.8±9.8 |
| EXPRESS | EXPRESS II | |
| Median | 173.0 | 172.0 |
| IQ range | (166.0, 180.0) | (165.0, 179.0) |
| Range | (145.0, 194.0) | (137.0, 200.0) |
The safety and efficacy of infliximab for injection were assessed in two randomized double-blind placebo-controlled studies in adults with chronic, stable plaque psoriasis involving ≥10% BSA, a minimum PASI score of 12, and who were candidates for systemic anti-psoriatic therapy or phototherapy. Patients with guttate, pustular, or erythrodermic psoriasis were excluded from the study. No concomitant anti-psoriatic therapies were allowed during the study, with the exception of low-potency topical corticosteroids on the face and groin after Week 10. Demographic information for both study populations are summarized in Table 30.
The EXPRESS study evaluated 378 patients who received placebo or infliximab for injection at a dose of 5 mg/kg at Weeks 0, 2, and 6 (induction therapy), followed by maintenance therapy every 8 weeks through Week 22. At Week 24, the placebo group crossed over to infliximab for injection induction therapy (5 mg/kg), followed by maintenance therapy every 8 weeks (placebo/infliximab for injection group) through Week 46. Patients originally randomized to infliximab for injection continued to receive infliximab for injection 5 mg/kg every 8 weeks through Week 46.
The EXPRESS II study evaluated 835 patients who received placebo or infliximab for injection at doses of 3 mg/kg or 5 mg/kg at Weeks 0, 2, and 6 (induction therapy). At Week 14, within each dose, patients in the two infliximab for injection groups were randomized to either scheduled (every 8 weeks) or as needed (PRN) maintenance treatment through Week
- 46. At Week 16, the placebo group crossed over to infliximab for injection induction therapy (5 mg/kg), followed by maintenance therapy every 8 weeks through Week 46.
The primary endpoint was the proportion of patients who achieved a reduction in score of at least 75% from baseline at Week 10 by the Psoriasis Area and Severity Index (PASI 75). The PASI is a composite score that takes into consideration both the fraction of body surface area affected and the nature and severity of psoriatic changes within the affected regions (induration, erythema, and scaling).
In EXPRESS, other evaluated outcomes included the proportion of patients who achieved a score of “cleared” or “minimal” by the Static Physician’s Global Assessment (sPGA) and the proportion of patients with a reduction of PASI of at least 90% from baseline. The sPGA is a 6 category scale ranging from “5=severe” to “0=cleared” indicating the healthcare professional’s overall assessment of the psoriasis severity focusing on induration, erythema, and scaling. Treatment success of “cleared” or “minimal” consisted of none or minimal elevation in plaque, up to faint red coloration in erythema, and none or minimal fine scale over <5% of the plaque.
EXPRESS II evaluated the proportion of patients who achieved a score of “clear” or “excellent” by the Relative Physician’s Global Assessment (rPGA) and the proportion of patients with a reduction of PASI of at least 90% from baseline. The rPGA is a 6 category scale ranging from “6=worse” to “1=clear” that was assessed relative to baseline. Overall lesions were graded with consideration to the percent of body involvement as well as overall induration, scaling, and erythema. Treatment success of “clear” or “excellent” consisted of some residual pigmentation (Wornoff’s ring may be present) to marked improvement (nearly normal skin texture; some erythema may be present).
Patients in all treatment groups and in both studies had a median baseline PASI score ranging from 17 to 22. In EXPRESS, the percentage of patients with baseline sPGA classifications ranged from 52% for moderate, 36% for marked, and 2% for severe. Across all treatment groups, the percentage of patients who previously received systemic therapy for psoriasis was 71% in EXPRESS and 55% in EXPRESS II; and those who previously received UVB ranged from 65% to 71% in EXPRESS, and 50% to 55% in EXPRESS II.
Study Results
In both studies, at Week 10, more patients randomized to infliximab for injection 3 mg/kg or 5 mg/kg than placebo achieved PASI 75 (Table 31 and Table 32). By Week 6, in EXPRESS II, 78% and 48% of patients on 3 mg/kg infliximab for injection achieved a PASI 50 and 75 respectively and across both studies, 88-90% and 56-62% of patients on 5 mg/kg infliximab for injection achieved a PASI 50 and PASI 75 respectively. At Week 10, the individual components of the PASI (induration, erythema, and scaling) contributed comparably to the overall treatment- associated improvement in PASI. In addition, most patients in all infliximab for injection treatment groups achieved an assessment of minimal/cleared on the sPGA or excellent/clear on the rPGA when compared with placebo.
In both studies, at Week 10, significant improvement from baseline was seen among the infliximab for injection-treated group compared to the placebo group in the condition specific Dermatology Life Quality Index (DLQI) and the general health status questionnaire SF-36.
Table 31. PASI and sPGAb responses at Weeks 10, 24, and 50 (EXPRESS)
| Placebo | 5 mg/kg Infliximab for injection | |
| (n=77) | (n=301) | |
| Week 10 | 77 | 301 |
| PASI 90 | 1 (1.3%) | 172 (57.1%) |
| PASI 75 | 2 (2.6%) | 242 (80.4%)a |
| PASI 50 | 6 (7.8%) | 274 (91.0%) |
| Week 24 | 77 | 276 |
| PASI 90 | 1 (1.3%) | 161 (58.3%) |
| PASI 75 | 3 (3.9%) | 227 (82.2%)a |
| PASI 50 | 5 (6.5%) | 248 (89.9%) |
| Week 50 | N/A | 281 |
| PASI 90 | N/A | 127 (45.2%) |
| PASI 75 | N/A | 170 (60.5%) |
| PASI 50 | N/A | 193 (68.7%) |
| sPGA of minimal or cleared | ||
| Week 10 | 3 (3.9%) | 242 (82.9%)a |
| Week 24 | 2 (2.6%) | 203 (73.6%) |
| Week 50 | N/A | 149 (53.0%) |
a p<0.001 compared with placebo b Static Physician’s Global Assessment N/A – Not applicable; Note no data is available for placebo group due to patients crossing over to Infliximab for injection prior to Week 50. | ||
Table 32. PASI and rPGAb responses at Week 10 (EXPRESS II)
| Placebo | 3 mg/kg infliximab for injection | 5 mg/kg infliximab for injection | |
| (n=208) | (n=313) | (n=314) | |
| Week 10 | |||
| PASI 50 | 17 (8.2%) | 270 (86.3%) | 291 (92.7%) |
| PASI 75 | 4 (1.9%) | 220 (70.3%)a | 237 (75.5%)a |
| PASI 90 | 1 (0.5%) | 116 (37.1%) | 142 (45.2%) |
| rPGA of excellent or clear | |||
| Week 10 | 2 (1.0%) | 217 (69.8%)a | 234 (76.0%)a |
a p<0.001 compared with placebo b Relative Physician’s Assessment | |||
In EXPRESS, at Weeks 24 and 50, 82% and 61% of patients respectively achieved a PASI
- 75. At Week 50, 45% achieved a PASI 90. Among PASI 75 responders at Week 10, 89% achieved a PASI 75 and 65% achieved a PASI 90 at Week 24. At Week 50, 65% of PASI responders achieved a PASI 75 and 50% achieved a PASI 90.
In EXPRESS, the Nail Psoriasis Severity Index (NAPSI) evaluated 4 components of nail matrix disease and 4 components of nail bed disease with scores ranging from 0 to 8, with a higher score representing more severe disease. The median baseline NAPSI score was 4. Maximum improvement in the infliximab for injection group occurred at Week 24 with a median improvement of 2 compared to 0 in the placebo group. At Week 50, in the infliximab for injection group, the median improvement of 2 in NAPSI was maintained.
In EXPRESS II, among the 4 maintenance regimens, response was best maintained in the 5 mg/kg infliximab for injection every 8 weeks group. At Weeks 26 and 50, 78% and 55% respectively achieved a PASI 75. At Weeks 26 and 50, 56% and 34% respectively achieved a PASI 90. Among PASI 75 responders at Week 10 in the 5 mg/kg every 8 weeks group, 83% maintained a PASI 75 and 61% a PASI 90 at Week 26. At Week 50, 60% maintained a PASI 75 and 40% a PASI 90.
The median duration of maintaining PASI 75 among Week 10 PASI responders after induction therapy in the PRN groups was between 12 to 16 weeks.
In both EXPRESS and EXPRESS II, a post hoc analysis was perform to evaluate patients achieving a major clinical response as defined by maintaining ≥ 90% improvement in PASI at consecutive visits for at least 24 weeks. In EXPRESS, 36% and in EXPRESS II, 31% of patients in the 5 mg/kg every 8 week maintenance group achieved a major clinical response.
In EXPRESS II, response to retreatment was evaluated in patients who were randomized as responders at Week 14 in the PRN groups and subsequently lost response after a 12-40 week gap of therapy. Approximately 67% of patients in the 3 mg/kg PRN group and 84% of patients in the 5 mg/kg PRN group regained response.
Efficacy and safety of infliximab for injection treatment beyond 12 months has not been evaluated in patients with plaque psoriasis.
Ulcerative Colitis
Table 33. Summary of patient demographics for clinical trials in ulcerative colitis
| Study # | Study Design | Dosage, route of administration and duration | Study Subjects (n) | Median age (range) | Gender and Race n (%) |
T37 (ACT 1) | Randomised, multicentre, double- blind, placebo- controlled, parallel- group study in patients with moderately to severely active UC despite current or historical treatment with standard therapy | Infliximab for injection 5 mg/kg, 10/mg/kg, or placebo administered intravenously at Weeks 0, 2, and 6, followed by additional infusions every 8 weeks thereafter through Week 46 | 364 | 41.9 (18.0, 81.0) | 222 (61.0%) male 142 (39.0%) female 340 (93.4%) Caucasian 6 (1.6% 4 (1.1%) Asian 14 (3.8%) Other |
T46 (ACT 2) | Randomised, multicentre, double- blind, placebo- controlled, parallel- group study in patients with moderately to severely active UC despite current or historical treatment with standard therapy | Infliximab for injection 5 mg/kg, 10/mg/kg, or placebo administered intravenously at Weeks 0, 2, and 6, followed by additional infusions every 8 weeks thereafter through week 22 | 364 | 40.0 (18.0, 82.0) | 215 (59.1%) male 149 (40.9%) female 344 (94.5%) Caucasian 8 (2.2%) 5 (1.4%) Asian 7 (1.9%) Other |
The safety and efficacy of infliximab for injection were assessed in two multicentre, randomized, double- blind, placebo-controlled clinical studies in adult patients with moderately to severely active ulcerative colitis (Mayo score 6 to 12; Endoscopy subscore ≥ 2) with an inadequate response to conventional therapies. Concomitant stable doses of oral aminosalicylates, corticosteroids, and/or immunomodulatory agents were permitted. In both studies, patients were randomized at week 0 to receive either placebo, 5 mg/kg infliximab for injection, or 10 mg/kg infliximab for injection at Weeks 0, 2, 6, and every 8 weeks thereafter through week 46 in ACT 1 and at weeks 0, 2, 6, and every 8 weeks thereafter through week 22 in ACT 2. Corticosteroid taper was permitted after Week 8. The study design and demographics of the study population for the two trials are summarized in Table 33.
In the first study (ACT 1), 364 patients were randomized who were on current treatment or had failed to respond to or tolerate oral corticosteroids, 6-mercaptopurine (6-MP) or azathioprine (AZA). Patients randomized in the second study (ACT 2) (n=364) were on or had failed to respond to or tolerate oral corticosteroids, 6-MP, AZA, or aminosalicylates. In both studies, baseline concomitant medications for ulcerative colitis were generally similar across treatment groups. However, because of differences in entry criteria, there were more subjects in ACT 2 (25.8%) than in ACT 1 (11.3%) who were solely taking aminosalicylates for their ulcerative colitis.
In both studies, clinical response and clinical remission were defined based on the Mayo score, which consists of four subscores: stool frequency, rectal bleeding, findings of endoscopy, and healthcare professional’s global assessment. Each subscore is rated on a scale from 0 to 3, indicating normal (0) to severe (3) activity. The Mayo score is the sum of the 4 subscores. Clinical response was defined as a decrease from baseline in the Mayo score of ≥ 30% and ≥ 3 points, accompanied by a decrease in the rectal bleeding subscore of ≥ 1 or a rectal bleeding subscore of 0 or 1. Clinical remission was defined as a Mayo score ≤ 2 points, with no individual subscore > 1.
Clinical Response, Clinical Remission and Mucosal Healing
In both the ACT 1 and ACT 2 studies, a significantly greater percentage of patients in the infliximab for injection groups were in clinical response at Week 8 (the primary endpoint) when compared to placebo (Figure 10). Table 34 and Table 35 present the primary and secondary endpoints of the ACT 1 and ACT 2 studies, respectively.
Table 34. Efficacy results of study T37 (ACT 1) in ulcerative colitis
| Infliximab for injection | |||
| Placebo | 5 mg/kg | 10 mg/kg | |
| Patients randomized | n=121 | n=121 | n=122 |
| Parameter | |||
| Primary Endpoint | |||
| Clinical response at Week 8 n (%) | 45 (37.2%) | 84 (69.4%) p<0.001 | 75 (61.5%) p<0.001 |
| Secondary Endpoints | |||
| Clinical response at Week 30 n (%) | 36 (29.8%) | 63 (52.1%) p<0.001 | 62 (50.8%) p=0.002 |
| Clinical response at Week 54 n (%) | 24 (19.8%) | 55 (45.5%) p<0.001 | 54 (44.3%) p<0.001 |
| Clinical remission at Week 8 n (%) | 18 (14.9%) | 47 (38.8%) p<0.001 | 39 (32.0%) p=0.002 |
| Clinical remission at Week 30 n (%) | 19 (15.7%) | 41 (33.9%) p=0.001 | 45 (36.9%) p<0.001 |
| Clinical remission at Week 54 n (%) | 20(16.5%) | 42 (34.7%) p=0.001 | 42 (34.4%) p=0.001 |
| Mucosal healing at Week 8 n (%) | 41 (33.9%) | 75 (62.0%) p<0.001 | 72 (59.0%) p<0.001 |
| Mucosal healing at Week 30 n (%) | 30 (24.8%) | 61 (50.4%) p<0.001 | 60 (49.2%) p<0.001 |
| Mucosal healing at Week 54 n (%) | 22 (18.2%) | 55 (45.5%) p<0.001 | 57 (46.7%) p<0.001 |
| Subjects receiving corticosteroids at baseline, in clinical remission and not receiving corticosteroids at Week 30 | 8 (10.1%) | 17 (24.3%) p=0.030 | 14 (19.2%) p=0.125 |
| Subjects receiving corticosteroids at baseline, in clinical remission and not receiving corticosteroids at Week 54 | 7 (8.9%) | 18 (25.7%) p=0.006 | 12 (16.4%) p=0.149 |
| Subjects in sustained response through Week 54 (clinical response at Weeks 8, 30 and 54) | 17 (14.0%) | 47 (38.8%) p<0.001 | 45 (36.9%) p<0.001 |
| Infliximab for injection | |||
| Placebo | 5 mg/kg | 10 mg/kg | |
| Subjects in sustained remission through Week 54 (clinical remission at Weeks 8, 30 and 54) | 8 (6.6%) | 24 (19.8%) p=0.002 | 25 (20.5%) p=0.002 |
| Median change from baseline in IBDQ at Week 8 | 16 | 39 p<0.001 | 33 p=0.001 |
| Median change from baseline in IBDQ at Week 30 | 0 | 27 p=0.002 | 31 p=0.004 |
| Median change from baseline in IBDQ at Week 54 | 0 | 26 <0.001 | 19 <0.001 |
Table 35. Efficacy results of study T46 (ACT 2) in ulcerative colitis
| Infliximab for injection | |||
| Placebo | 5 mg/kg | 10 mg/kg | |
| Patients randomized | n=123 | n=121 | n=120 |
| Parameter | |||
| Primary Endpoint | |||
| Clinical response at Week 8 n (%) | 36 (29.3%) | 78 (64.5%) p<0.001 | 83 (69.2%) p<0.001 |
| Secondary Endpoints | |||
| Clinical response for the Week 30 n (%) | 32 (26.0%) | 57 (47.1%) p<0.001 | 72 (60.0%) p<0.001 |
| Clinical remission at Week 8 n (%) | 7 (5.7%) | 41 (33.9%) p<0.001 | 33 (27.5%) p<0.001 |
| Clinical remission at Week 30 n (%) | 13 (10.6%) | 31 (25.6%) p=0.003 | 43 (35.8%) p<0.001 |
| Mucosal healing at Week 8 n (%) | 38 (30.9%) | 73 (60.3%) p<0.001 | 74 (61.7%) p<0.001 |
| Mucosal healing at Week 30 n (%) | 37 (30.1%) | 56 (46.3%) p=0.009 | 68 (56.7%) p<0.001 |
| Subjects receiving corticosteroids at baseline, in clinical remission and not receiving corticosteroids at Week 30 | 2 (3.3%) | 11 (18.3%) p=0.010 | 18 (27.3%) p<0.001 |
| Subjects in sustained response through Week 30 (clinical response at Weeks 8 and Week 30) | 19 (15.4%) | 50 (41.3%) p<0.001 | 64 (53.3%) p<0.001 |
| Subjects in sustained remission through Week 30 (clinical remission at Weeks 8 and Week 30) | 3 (2.4%) | 18 (14.9%) p<0.001 | 27 (22.5%) p<0.001 |
| Median change from baseline in IBDQ at Week 8 | 7 | 38 p<0.001 | 33 p<0.001 |
| Median change from baseline in IBDQ at Week 30 | 0 | 20 p=0.005 | 32 p<0.001 |
In both studies, a significantly greater percentage of patients in both infliximab for injection groups achieved clinical response, clinical remission and mucosal healing than patients in the placebo groups (Table 36). Each of these effects was maintained through the end of each trial (through Week 54 in ACT 1, and through Week 30 in ACT 2). In addition, a greater proportion of patients in the infliximab for injection groups (approximately twice as many) demonstrated sustained response and sustained remission than patients in the placebo groups.
Figure 10. Proportion of randomized subjects in clinical response at Week 8 (primary endpoint) in ACT 1 and ACT 2
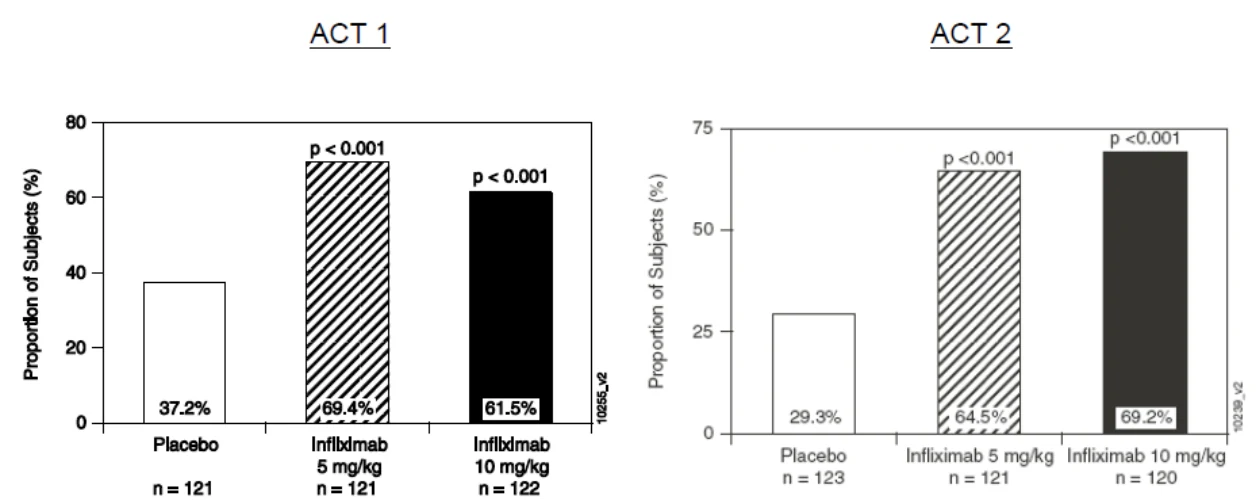
In both ACT 1 and ACT 2, a significantly greater proportion of patients treated with 5 mg/kg or 10 mg/kg infliximab for injection experienced clinical response at Week 30 compared to placebo treatment (Table 36). In addition, the proportion of patients in sustained response (i.e., were in clinical response at both Week 8 and Week 30) in the infliximab for injection groups was approximately twice as large as the proportion of patients in sustained response in the placebo group.
In ACT 1, the proportion of patients in clinical response at Week 54 and the proportion of patients in sustained response through Week 54 (i.e., clinical response at Weeks 8, 30 and
- 54) was significantly greater in the infliximab for injection-treated subjects compared to placebo-treated subjects (Table 36).
Table 36. Proportion of subjects in clinical response, and in sustained response
| ACT 1 | ACT 2 | |||||
| Infliximab for injection | Infliximab for injection | |||||
| Placebo | 5 mg/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg | |
| Subjects randomized | 121 | 121 | 122 | 123 | 121 | 120 |
| Subjects in clinical response at Week 8 | 37.2% | 69.4% | 61.5% | 29.3% | 64.5% | 69.2% |
| p-value | <0.001 | <0.001 | <0.001 | <0.001 | ||
| ACT 1 | ACT 2 | |||||
| Infliximab for injection | Infliximab for injection | |||||
| Placebo | 5 mg/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg | |
| Subjects in clinical response at Week 30 | 29.8% | 52.1% | 50.8% | 26.0% | 47.1% | 60.0% |
| p-value | <0.001 | 0.002 | <0.001 | <0.001 | ||
| Subjects in sustained response through Week 30 (clinical response at weeks 8 and 30) | 23.10% | 48.8% | 45.9% | 15.4% | 41.3% | 53.3% |
| p-value | <0.001 | <0.001 | <0.001 | <0.001 | ||
| Subjects in clinical response at week 54 | 19.8% | 45.5% | 44.3% | N/A | N/A | N/A |
| p-value | <0.001 | <0.001 | ||||
| Subjects in sustained response through week 54 (clinical response at weeks 8, 30 and 54) | 14.0% | 38.8% | 36.9% | N/A | N/A | N/A |
| p-value | <0.001 | <0.001 | ||||
In ACT 1 through Week 46, a total of 46.7% of subjects discontinued study infusions, 62.0% of placebo-treated and 39.1% of infliximab for injection-treated subjects. The most common reason for discontinuation of study infusions was lack of efficacy, which occurred in nearly twice as many placebo-treated subjects as infliximab for injection-treated subjects (46.3% vs. 24.3%, respectively). Overall, in ACT 2, 29.1% of subjects discontinued study infusions prior to Week 22. In particular, 45.5% of placebo-treated subjects and 20.7% of infliximab for injection-treated subjects discontinued study infusions. As was observed with ACT 1, the most common reason for discontinuation of study infusions in ACT 2 was lack of efficacy, which occurred in 32.5% of placebo-treated and 16.6% of infliximab for injection-treated subjects.
In ACT 1 and ACT 2, response to infliximab for injection was consistently greater compared to placebo across all Mayo subscores at Week 8 and Week 30 and Week 54 (ACT 1 only) (Table 37).
Table 37. Proportion of subjects in ACT 1 and ACT 2 with Mayo subscores indicating no disease activity or mild disease
| ACT 1 | ACT 2 | |||||
| Infliximab for injection | Infliximab for injection | |||||
| Placebo | 5 mg/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg | |
| (n=121) | (n=121) | (n=122) | (n=123) | (n=121) | (n=120) | |
| Stool frequency | ||||||
| Baseline | 16.5% | 16.5% | 9.8% | 13.0% | 15.7% | 16.7% |
| Week 8 | 34.7% | 59.5% | 58.2% | 31.7% | 62.8% | 59.2% |
| Week 30 | 34.7% | 51.2% | 52.5% | 30.9% | 50.4% | 53.3% |
| Week 54 | 31.4% | 52.1% | 50.8% | N/A | N/A | N/A |
| Rectal bleeding | ||||||
| Baseline | 53.7% | 39.7% | 47.5% | 43.1% | 57.0% | 45.8% |
| Week 8 | 73.6% | 86.0% | 80.3% | 63.4% | 81.8% | 85.0% |
| Week 30 | 65.3% | 73.6% | 71.3% | 56.9% | 75.2% | 80.0% |
| Week 54 | 62.0% | 69.4% | 67.2% | N/A | N/A | N/A |
| Physician’s global assessment | ||||||
| Baseline | 4.1% | 5.8% | 2.5% | 3.3% | 5.0% | 3.3% |
| Week 8 | 43.8% | 73.6% | 63.9% | 35.0% | 68.6% | 65.8% |
| Week 30 | 35.5% | 57.0% | 54.9% | 35.0% | 54.5% | 62.5% |
| Week 54 | 26.4% | 52.9% | 53.3% | N/A | N/A | N/A |
| Findings of endoscopy | ||||||
| Baseline | 0.0% | 0.0% | 0.0% | 0.8% | 0.0% | 1.7% |
| Week 8 | 33.9% | 62.0% | 59.0% | 31.7% | 60.3% | 62.5% |
| Week 30 | 25.6% | 51.2% | 51.6% | 32.5% | 50.4% | 59.2% |
| Week 54 | 20.7% | 49.6% | 50.8% | N/A | N/A | N/A |
In ACT 1 and ACT 2, at Week 8 and at Week 30, a significantly greater proportion of subjects in the infliximab for injection-treated group experienced clinical remission compared to placebo (p≤0.003 for all comparisons) (Table 38). Remission was sustained (i.e., in clinical remission at both Week 8 and Week 30) in more subjects receiving infliximab for injection compared to placebo. Of patients treated with corticosteroids at baseline, a significantly greater proportion of patients in the infliximab for injection -treated groups in ACT 1 and ACT 2 were in clinical remission at Week 30 and able to discontinue corticosteroids compared to the placebo-treated patients (22.3% versus 7.2%, respectively).
In ACT 1, the proportion of subjects in clinical remission at week 54 and the proportion of subjects in sustained remission through week 54 (i.e., were in clinical remission at weeks 8, 30, and 54) was significantly greater in the infliximab for injection-treated subjects compared to the placebo- treated subjects. Approximately twice the proportion of subjects in the infliximab for injection-treated groups were in clinical remission at Week 54 and able to discontinue corticosteroids compared to the placebo-treated subjects (Table 38).
Table 38. Proportion of subjects in clinical remission, in sustained remission, and in clinical remission and not receiving corticosteroids
| ACT1 | ACT2 | |||||
Infliximab for injection | Infliximab for injection | |||||
| Placebo | 5 m/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg | |
| Subjects randomized | 121 | 121 | 122 | 123 | 121 | 120 |
| ACT1 | ACT2 | |||||
Infliximab for injection | Infliximab for injection | |||||
| Placebo | 5 m/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg | |
| Subjects in clinical remission at Week 8 | 14.9% | 38.8% | 32.0% | 5.7% | 33.9% | 27.5% |
| p-value | <0.001 | 0.002 | <0.001 | <0.001 | ||
| Subjects in clinical remission at Week 30 | 15.7% | 33.9% | 36.9% | 10.6% | 25.6% | 35.8% |
| p-value | 0.001 | <0.001 | 0.003 | <0.001 | ||
Subjects in sustained remission through Week 30 (clinical remission at Weeks 8 and 30) | 8.3% | 23.1% | 26.2% | 2.4% | 14.9% | 22.5% |
| p-value | 0.001 | <0.001 | <0.001 | <0.001 | ||
| Subjects in clinical remission at Week 54 | 16.5% | 34.7% | 34.4% | N/A | N/A | N/A |
| p-value | 0.001 | 0.001 | ||||
| Subjects in sustained remission through Week 54 (clinical remission at Weeks 8 ,30, and 54) | 6.6% | 19.8% | 20.5% | N/A | N/A | N/A |
| p-value | 0.002 | 0.002 | ||||
| Subjects on corticosteroids at baseline | 79 | 70 | 73 | 60 | 60 | 66 |
Subjects in clinical remission at Week 30 able to discontinue corticosteroid use | 10.1% | 24.3% | 19.2% | 3.3% | 18.3% | 27.3% |
| p-value | 0.030 | 0.125 | 0.01 | <0.001 | ||
Subjects in clinical remission at Week 54 able to discontinue corticosteroid use | 8.9% | 25.7% | 16.4% | N/A | N/A | N/A |
| p-value | 0.006 | 0.149 | N/A | N/A | N/A | |
Mucosal healing was defined as an endoscopy subscore (from the Mayo score) of 0 or 1. At Weeks 8, 30 and 54 in ACT 1 and at Weeks 8 and 30 in ACT 2, a significantly greater proportion of patients in the 5 mg/kg and 10 mg/kg dose groups achieved mucosal healing compared to patients in the placebo group (Table 39). The proportion of subjects with mucosal healing was similar between the 2 infliximab for injection dose groups in the two studies.
Table 39. Proportion of subjects with mucosal healing
| ACT1 | ACT2 | |||||
| Infliximab for injection | Infliximab for injection | |||||
| Mucosal Healing1 | Placebo | 5 m/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg |
| Subjects randomized | 121 | 121 | 122 | 123 | 121 | 120 |
| at Week 8 | 33.9% | 62.0% | 59.0% | 30.9% | 60.3% | 61.7% |
| p-value | <0.001 | <0.001 | <0.001 | <0.001 | ||
| at Week 30 | 24.8% | 50.4% | 49.2% | 30.1% | 46.3% | 56.7% |
| p-value | <0.001 | <0.001 | 0.009 | <0.001 | ||
| at Week 54 | 18.2% | 45.5% | 46.7% | N/A | N/A | N/A |
| p-value | <0.001 | <0.001 | ||||
| ACT1 | ACT2 | |||||
| Infliximab for injection | Infliximab for injection | |||||
| Mucosal Healing1 | Placebo | 5 m/kg | 10 mg/kg | Placebo | 5 mg/kg | 10 mg/kg |
| 1 Proportion of subjects with mucosal healing may not equal the proportion of subjects with a value of 0 or 1 for the findings of endoscopy Mayo subscore. This is due to different data handling rules being used in the two analyses. | ||||||
Health-related quality of life was assessed in ACT 1 and ACT 2 using the IBDQ and the SF-36. The IBDQ is a questionnaire specifically designed for subjects with inflammatory bowel disease. The SF-36 is a generic health status questionnaire that has been widely used in various diseases and conditions to assess patients’ physical and mental well being.
The median total IBDQ scores at baseline were similar among the treatment groups. At both Week 8 and Week 30 in ACT 1 and ACT 2, and at Week 54 in ACT 1, the combined infliximab for injection treatment group had a median improvement from baseline that was greater than that observed in the placebo treatment group (p<0.001 for all comparisons) (Table 40). Similar improvements were also observed in all 4 dimensional (i.e. bowel, emotional, systemic and social) scores of the IBDQ (p≤0.015 for all comparisons between the combined infliximab for injection-treatment group and the placebo treatment group). At both Week 8 and Week 30 in ACT 1 and ACT 2 and Week 54 in ACT 1, subjects in the combined infliximab for injection treatment group had greater improvement in the physical and mental component summary scores of the SF-36 compared with the placebo treatment group (p≤0.044 for all comparisons) (Table 40).
Table 40. Summary [mean (median)] of baseline and change from baseline in total IBDQ score and physical and mental component summary scores of SF-36
| ACT 1 | ACT 2 | |||
| Placebo | Infliximab for injection*, p-value | Placebo | Infliximab for injection*, p-value | |
| Subjects randomized | 121 | 243 | 123 | 241 |
| IBDQ | ||||
| Total | ||||
| Baseline | 123 (121) | 127 (127) | 125 (127) | 128 (127) |
| 21 (16) | 39 (36), <0.001 | 20 (7) | 37 (34), <0.001 | |
| Change at Week 8 | ||||
| 18 (0) | 34 (27), <0.001 | 18 (0) | 34 (29), <0.001 | |
| Change at Week 30 | ||||
| Change at week 54 | 13(0) | 32 (23), <0.001 | N/A | N/A |
| SF-36 | ||||
| Physical component summary | ||||
| Baseline | 36.5 (35.9) | 38.0 (37.8) | 39.0 (39.1) | 39.5 (39.5) |
| Change at Week 8 | 4.5 (1.4) | 6.2 (5.0), 0.042 | 2.9 (0.0) | 6.5 (5.2), <0.001 |
| Change at Week 30 | 3.4 (0.0) | 5.7 (2.6), 0.044 | 2.6 (0.0) | 5.3 (4.6), 0.007 |
| Change at week 54 | 2.7 (0.0) | 6.0 (2.5), 0.002 | N/A | N/A |
| Mental component summary | ||||
| ACT 1 | ACT 2 | |||
| Placebo | Infliximab for injection*, p-value | Placebo | Infliximab for injection*, p-value | |
| Baseline | 39.5 (38.8) | 41.2 (42.7) | 39.3 (39.0) | 40.3 (42.3) |
| Change at Week 8 | 3.1 (0.0) | 6.1 (3.6), 0.020 | 3.0 (0.0) | 6.2 (3.2), 0.003 |
| Change at Week 30 | 3.1 (0.0) | 5.9 (1.8), 0.012 | 4.4 (0.0) | 6.5 (3.5), 0.021 |
| Change at Week 54 | 1.3 (0.0) | 5.1 (0.0), 0.001 | N/A | N/A |
| * 5 & 10 mg/kg Infliximab Groups Combined | ||||
From baseline through Week 30 in the pooled data from ACT 1 and ACT 2, the mean number of ulcerative colitis-related hospitalizations was 50% lower in the combined infliximab for injection treatment group than in the placebo treatment group (9 versus 18 hospitalizations per 100 subjects, p=0.005). No notable differences were observed between the 5 mg/kg and 10 mg/kg infliximab for injection treatment groups, both of which had a significantly lower mean number of ulcerative colitis-related hospitalizations than the placebo treatment group (p≤0.030). A similar benefit was seen through 54 weeks in ACT 1.
Time to first ulcerative colitis-related hospitalization was longer in the combined infliximab for injection treatment group than in the placebo treatment group in both the ACT 1 and ACT 2 studies.
Upon completion of 54 weeks in ACT 1 or 30 weeks in ACT 2, patients who in the opinion of the investigator would benefit from further study agent were eligible to enter a study extension for up to 3 years. Patients who received study agent within ACT 1 or ACT 2 were encouraged to participate in a long term safety follow-up observational study, upon completion of or discontinuation from either UC study or its extension. Patients who did not have complete follow-up through 54 weeks following their first study infusion in either ACT 1 or ACT 2 and who did not participate in the long term safety follow up study were encouraged to participate in a substudy of each ACT study to retrospectively collect targeted information on ulcerative colitis related hospitalizations and surgical procedures, including colectomy.
Time to colectomy was measured in all patients who participated in the UC studies through 54 weeks from their first study infusion. Colectomy data was pooled from ACT 1 and ACT 2 (including retrospective substudy data collections), the ACT 2 Extension, and the long term safety follow-up study. Complete follow-up data on colectomy were collected on 630 of the 728 ACT patients; 98 patients (13.5%) had incomplete follow-up data. Among the 630 patients with complete follow-up, complete colectomy follow-up was obtained retrospectively in 37 patients. The proportion of patients who underwent colectomy at any time within 54 weeks following the first infusion were: 11.6 % (28/242) in the 5 mg/kg infliximab for injection group, 7.4% (18/242) in the 10 mg/kg infliximab for injection group, and 14.8% (36/244) in the placebo group.
Ulcerative colitis in pediatric patients
Table 41. Study of patient demographics for clinical trials in pediatric ulcerative colitis
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Gender and Race n (%) |
| T72 | Phase 3 multi-center, randomized, open-label, parallel-group | Intravenous infusions of infliximab for injection 5 mg/kg for all patients at weeks 0, 2, and 6 Patients in clinical response at week 8 randomised to maintenance treatment with intravenous infusions of 5 mg/kg infliximab for injection either q8 weeks through week 46 or q12 weeks through week 42. | 60 6 of 15 (6-11 years of age) and 23 of 45 (12-17 years of age) completed the study | 14.5 years (6.0-17.0) | Gender: Male 28 (46.7) Female 32 (53.3) Race: Caucasian 49 (81.7) Black 5 (8.3) Asian 3 (5.0) Other 3 (5.0) |
The safety and efficacy of infliximab for injection were assessed in a multi-center, randomized, open- label, parallel-group Phase 3 clinical study in 60 pediatric patients aged 6 through 17 years (median age 14.5 years) with moderately to severely active ulcerative colitis (Mayo score of 6 to 12; Endoscopic subscore ≥ 2) with an inadequate response to conventional therapies (Study Peds UC). At baseline 53% of patients were receiving immunomodulator therapy (6- MP/AZA/MTX), 53% of patients were receiving aminosalicylates and 62% of patients were receiving corticosteroids. Discontinuation of immunomodulators and corticosteroid taper were permitted after Week 0.
All patients received an induction regimen of 5 mg/kg infliximab for injection at Weeks 0, 2, and 6. Patients (15) who did not respond to infliximab for injection at Week 8 received no further drug and returned for safety follow-up. At Week 8, 45 patients were randomized in a 1:1 ratio to one of two maintenance treatment regimens: 5 mg/kg infliximab for injection every 8 weeks (q8 week) through Week 46 or every 12 weeks (q12 week) through Week 42.
A summary of patient demographics and design of the pediatric ulcerative colitis study is presented in Table 41.
The primary endpoint was clinical response at Week 8, defined as a decrease from baseline in the Mayo score by ≥ 30% and ≥ 3 points, with a decrease in the rectal bleeding subscore of ≥ 1 or a rectal bleeding subscore of 0 or 1.
Major secondary endpoints included clinical remission measured by the Mayo score at Week 8 and remission by the Pediatric Ulcerative Colitis Activity Index (PUCAI)34 score at Week 8 and Week 54, and mucosal healing at Week 8. For patients receiving corticosteroids at baseline, reduction in median corticosteroid use, and remission combined with elimination of corticosteroid use at Week 54 were evaluated as pre-specified analyses but not designated as primary or secondary efficacy endpoints.
Study Results
Clinical Response, Clinical Remission and Mucosal Healing
34 Turner D, Otley AR, Mack D, et al. Development, validation, and evaluation of a pediatric ulcerative colitis activity index: A prospective multicenter study. Gastroenterology. 2007;133:423–432.
Of the 60 patients treated, 44 (73.3%) were in clinical response at Week 8 (95% CI: 62.1%, 84.5%). The proportions of patients achieving clinical response at Week 8 were similar between those taking concomitant immunomodulators at baseline (72%) and those not taking concomitant immunomodulators at baseline (75%).
Clinical remission was defined by a Mayo score of ≤ 2 points, with no individual subscore > 1. Remission was also defined by a PUCAI score of <10 points. At Week 8, infliximab for injection induced clinical remission in 40% (24/60) of patients as measured by the Mayo score and in 33.3% (17/51) of patients as measured by the PUCAI score.
The proportion of patients in remission at Week 54 as measured by the PUCAI score was 38% (8/21) in the q8 week maintenance treatment group and 18% (4/22) in the q12 week maintenance treatment group.
Nine out of 22 patients in the 5 mg/kg q8 week group required dose escalation to 10 mg/kg q8 week.
Mucosal healing was defined as an endoscopy subscore (from the Mayo score) of 0 or 1. At Week 8, 68.3% (41/60) of patients were in mucosal healing with 33.3% (20/60) having an endoscopy subscore of 0 (indicating normal or inactive disease).
Overall, although some differences were noted between the age groups in the efficacy measures examined, efficacy was observed in both age groups and no consistent pattern indicating greater efficacy in one of the age groups was apparent. The differences between the 6 to 11 and the 12 to 17 year old age groups, however, are difficult to assess because of the small sample sizes, particularly in the 6 to 11 year old age group (15 patients).
16 NON-CLINICAL TOXICOLOGY
General Toxicity
Acute and Multiple Dose Toxicity
Since the chimpanzee is the only species to have similar cross-reactivity as humans, safety studies in this species provide the most relevant safety information on infliximab for injection administration to humans. Although infliximab for injection does not inhibit rat TNFα, single dose and one-week repeat dose toxicity studies were performed only to evaluate potential non-specific effects.
In the rat studies, minimal and reversible hepatic changes (Kupffer cell and hepatocellular hyperplasia) and slight reduction in erythrocyte count, hemoglobin and hematocrit values were observed at single doses ≥10 mg/kg and at seven daily doses ≥ 10 mg/kg/day. These changes are not the result of the pharmacodynamic effects of the antibody because infliximab for injection does not neutralize the cytotoxicity of rat TNFα. They are likely the result of a normal rat reticuloendothelial system response to the administration of large doses of chimeric (human-murine) antibody, a completely foreign protein to this test animal. Thus, the infliximab for injection-related hematologic and hepatic effects observed in the rat are not considered relevant to humans.
A number of safety studies with infliximab for injection in chimpanzees were conducted. The results of these studies showed that infliximab for injection was well tolerated at doses up to 30 mg/kg/day for at least 3 consecutive days and at doses up to 15 mg/kg/day for at least 5 days. No infliximab for injection-related signs of toxicity, including abnormal hepatic or hematologic effects, similar to the findings in rats, were observed during these chimpanzee studies. Based on the results of these studies it is demonstrated that single doses of infliximab for injection up to 30 mg/kg, which is 6 times the proposed single dose for humans (5 mg/kg), can be administered without producing overt signs of toxicity. In addition, infliximab for injection has been administered to chimpanzees in single doses up to 30 mg/kg and up to a total dosage of 90 mg/kg (30 mg/kg/dose X 3 doses) over three consecutive days without producing overt signs of toxicity, which is approximately 3.5-6.0 times the proposed total dosage for humans of 15 mg/kg (5 mg/kg/dose X 3 doses) administered at 0, 2 and 6 weeks for closure of fistula(s) and for moderate to severe Crohn’s disease treatment (5 mg/kg/dose X 5 doses) at 8 week intervals.
Since infliximab for injection does not cross react with species other than chimpanzees, a 6-month toxicity study was performed using cV1q anti-mouse TNFα monoclonal antibody, a murine analog of human anti-TNFα. One hundred and twenty mice received weekly intravenous doses of (control), 10 or 40 mg/kg of cV1q. Each group was further divided into necropsy groups: Interim (Week 13), Main (Week 26), and Recovery (Week 39). There were no effects of cV1q treatment on clinical observations, body weight, food consumption, hematology, serum chemistry and ophthalmology evaluations. There were no pathological findings considered treatment-related. Therefore, the no-observed-adverse-effect-level (NOAEL) is greater than 40 mg/kg. The clinical significance of the results of toxicity studies with specific anti-TNFα monoclonal antibody tested in homologous system is uncertain.
Carcinogenicity
No findings suggestive of carcinogenic or mutagenic activity were observed in laboratory studies (in vivo and in vitro) performed with infliximab for injection, nor have any carcinogenic or mutagenic effects been associated with any of the excipients used to formulate infliximab for injection.
Human lymphocytes were used to evaluate in vitro the potential of infliximab for injection to induce chromosomal aberrations. In the Salmonella typhimurium - Escherichia coli-microsome plate assay, infliximab for injection was evaluated for its potential ability to induce reverse mutations. Potential clastogenic effects were determined in vivo using the mouse micronucleus test. Infliximab for injection did not exhibit mutagenic activity in any one of the 3 assays.
Infliximab for injection does not cause generalised suppression of immune system function. Analysis indicated that differential white blood cell counts (WBC) from chimpanzees treated with high doses of infliximab for injection were minimally effected.
Reproductive and Developmental Toxicity
Reproductive and developmental non clinical toxicity studies have not been performed with infliximab for injection because the species cross-reactivity of infliximab for injection is limited to chimpanzees. Based on the lack of cross-reactivity, standard reproductive/developmental toxicity studies (Segments I, II, and III) in rats and rabbits are considered inappropriate to provide relevant information on the potential of infliximab for injection to produce adverse reproductive or developmental effects in humans.
Comprehensive developmental toxicity studies with a surrogate anti-mouse TNFα monoclonal antibody (cV1q) were performed in mice. Analogous to infliximab for injection, cV1q specifically binds and neutralises mouse TNFα. These developmental toxicity studies showed that cV1q, administered intravenously at 10 or 40 mg/kg/dose to pregnant mice on days 6 and 12 of gestation, produced no maternal or developmental toxicity. The clinical significance of the results of the developmental toxicity studies with a species-specific anti-TNFα monoclonal antibody tested in a homologous system is uncertain. Infliximab for injection should be given to a pregnant woman only if clearly needed (see 7.1.1 Pregnant Women).
An additional fertility and general reproductive toxicity study was performed. The male mice received weekly doses of vehicle control, 10 or 40 mg/kg beginning 56 days (8 weeks) before cohabitation and continuing through cohabitation (2 weeks) and the week before sacrifice. The female mice received the same doses weekly beginning 2 weeks prior to cohabitation with males (maximum of 14 days) and on days 0 and 7 of presumed gestation. No toxicologically important effects on estrous cycle, fertility, tubal transport, pregnancy, implantation, development of pre- implantation of embryos of female mice, libido (time to mate), reproductive organ weights and epididymal sperm maturation were observed. The clinical significance of the results of the developmental toxicity studies with a species-specific anti-TNFα antibody tested in a homologous system is uncertain. Infliximab for injection should be given to a pregnant woman only if clearly needed (see 7.1.1 Pregnant Women).
Special Toxicology
Local Tolerance
The local irritancy potential of infliximab for injection at a concentration of 5 mg/mL was evaluated in rabbits following a single intravenous infusion (3 hours), intramuscular or subcutaneous dose. All 3 routes of administration demonstrated that infliximab for injection was well tolerated and did not produce a degree of irritancy considered clinically significant. Infliximab for injection will be reconstituted and diluted to a concentration that may range from 0.4 to 4.0 mg/mL before infusion. Also, the recommended infusion time is over a period of not less than 2 hours (see 4.4 Administration). Therefore, the infliximab for injection concentration (5 mg/mL) and infusion time (3 hours) evaluated exceeded that recommended to humans.
Host Response to Infliximab for injection
No immune responses were detected in 4 cynomolgus monkeys following 4 treatments with infliximab for injection and evaluated for 14 weeks after the final treatment. In Tg197 transgenic mice, infliximab for injection was often immunogenic. However, in normal mice, multiple administrations of infliximab for injection appeared to be tolerogenic. The relevance of these studies to infliximab for injection immunogenicity in humans is uncertain since: infliximab for injection is a predominantly foreign protein in these species, the animals which were typically treated did not exhibit symptoms of Crohn’s disease, the animals were not treated with relevant concomitant medications for inflammatory bowel disease, and often did not possess TNFα that could be recognised by infliximab for injection.
In Vitro Human Tissue Cross-Reactivity
Two in vitro cross-reactivity studies were performed on normal, adult human tissue specimens. In the first study, reactivity was observed in Kupffer’s cells of the liver, macrophages in the lymph nodes and mononuclear cells in the skin and kidney. Reactivity in these organs was anticipated and considered physiologic because of the presence of TNFα in these cells. A second in vitro cross-reactivity study on normal human tissues was performed using an improved, more sensitive assay system to detect infliximab for injection. In this study, reactivity was observed with mononuclear and stromal cells in many tissues. This reactivity was consistent with the known cell and tissue expression patterns for TNFα. No unanticipated cross-reactivity with other cells and tissues was observed.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1.
Remicade®, Product Monograph, Control number: 290189; dated: January 30, 2025,
Janssen Inc.