


Product Monograph - Retrovir (Azt) (Viiv Healthcare, 10 mg, 50 mg)
RECENT MAJOR LABEL CHANGES
| Section | Date |
|---|---|
| 1 INDICATIONS, 1.1 Pediatrics | 06/2021 |
| 1 INDICATIONS, 1.2 Geriatrics | 06/2021 |
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 06/2021 |
| 4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations | 06/2021 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 06/2021 |
| 7 WARNINGS AND PRECAUTIONS, General | 06/2021 |
| 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic | 06/2021 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................ 4
1.2 Geriatrics ................................................................................................................ 5
2 CONTRAINDICATIONS ................................................................................................. 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 5
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 6
4.4 Administration ........................................................................................................ 9
5 OVERDOSAGE .............................................................................................................. 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................ 10
7.1 Special Populations............................................................................................... 14
7.1.1 Pregnant Women ........................................................................................... 14
7.1.2 Breast-feeding ................................................................................................ 15
7.1.3 Pediatrics ........................................................................................................ 15
7.1.4 Geriatrics ........................................................................................................ 15
8 ADVERSE REACTIONS ................................................................................................ 16
8.1 Adverse Reaction Overview .................................................................................. 16
8.2 Clinical Trial Adverse Reactions ............................................................................ 16
8.2.1 Clinical Trial Adverse Reactions - Pediatrics .................................................... 22
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 25
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 25
8.5 Post-Market Adverse Reactions ........................................................................... 26
9 DRUG INTERACTIONS ................................................................................................ 27
9.2 Drug Interactions Overview .................................................................................. 27
9.4 Drug-Drug Interactions ......................................................................................... 27
9.5 Drug-Food Interactions ......................................................................................... 32
9.6 Drug-Herb Interactions ......................................................................................... 32
9.7 Drug-Laboratory Test Interactions ........................................................................ 32
10 CLINICAL PHARMACOLOGY ....................................................................................... 33
10.1 Mechanism of Action ...................................................................................... 33
10.3 Pharmacokinetics ........................................................................................... 33
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 36
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 36
PART II: SCIENTIFIC INFORMATION ....................................................................................... 37
13 PHARMACEUTICAL INFORMATION ............................................................................ 37
14 CLINICAL TRIALS ........................................................................................................ 37
14.1 Clinical Trials by Indication ............................................................................. 37
15 MICROBIOLOGY ........................................................................................................ 38
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 42
PATIENT MEDICATION INFORMATION .................................................................................. 47
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
RETROVIR (AZT) (zidovudine syrup, and solution for infusion) is indicated for the treatment of HIV infection when antiretroviral therapy is warranted.
Therapy with RETROVIR (AZT) has been shown to prolong survival and decrease the incidence of opportunistic infections in patients with advanced HIV disease at the initiation of therapy and to delay disease progression in asymptomatic HIV-infected patients.
RETROVIR (AZT) in combination with certain antiretroviral agents has been shown to be superior to monotherapy in one or more of the following: delaying death, delaying development of AIDS, increasing CD4 cell counts, and decreasing plasma HIV RNA. Use of RETROVIR (AZT) in some combinations is based on surrogate marker data. The complete prescribing information for each drug should be consulted before initiating combination therapy with RETROVIR (AZT).
The duration of clinical benefit from antiretroviral therapy may be limited. Alterations in antiretroviral therapy should be considered if disease progression occurs during treatment.
Maternal-Fetal HIV Transmission
RETROVIR (AZT) is also indicated for the prevention of maternal-fetal HIV transmission as part of a regimen that includes oral RETROVIR (AZT) beginning between 14 and 34 weeks of gestation, intravenous RETROVIR (AZT) during labour, and administration of RETROVIR (AZT) Syrup to the newborn after birth. However, transmission to infants may still occur in some cases despite the use of this regimen. The efficacy of this regimen for preventing HIV transmission in women who have received RETROVIR (AZT) for a prolonged period before pregnancy has not been evaluated. The safety of RETROVIR (AZT) for the mother or fetus during the first trimester of pregnancy has not been assessed.
Please see 14.1 Clinical Trials by Indication, Prevention of Maternal-Fetal HIV Transmission.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of RETROVIR (AZT) in pediatric patients has been established; therefore, Health Canada has authorized indications applicable to pediatric patients, specifically for treatment of HIV infection and for prevention of maternal-fetal HIV transmission as combined with maternal zidovudine (see 1 INDICATIONS, 4 DOSAGE AND ADMINISTRATION and 8 ADVERSE REACTIONS ).
With regards to the treatment of HIV-1 infection, the safety and efficacy of orally-dosed RETROVIR (AZT) in pediatric patients weighing less than 4 kg has not been established. In addition, the safety and efficacy of RETROVIR (AZT) administered via infusion for treatment of HIV-1 infection in pediatric patients less than 3 months old has not been established.
1.2 Geriatrics
Geriatrics (>65 years of age): Zidovudine pharmacokinetics have not been studied in patients over 65 years of age and no specific data are available. However, since special care is advised in this age group due to age-associated changes such as the decrease in renal function and alterations in hematological parameters, appropriate monitoring of patients before and during use of zidovudine is advised.
2 CONTRAINDICATIONS
- RETROVIR (AZT) is contraindicated for patients who have potentially life-threatening allergic reactions to any of the components of the formulations (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ).
- Due to the active ingredient zidovudine, RETROVIR (AZT) is contraindicated in patients with abnormally low neutrophil counts (< 0.75 x 10⁹/L) or abnormally low hemoglobin levels (< 7.5 g/dL or 4.65 mmol/L).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
WARNING: RISK OF HEMATOLOGICAL TOXICITY, MYOPATHY, LACTIC ACIDOSIS Hematologic Toxicity RETROVIR (zidovudine) syrup, and injection have been associated with hematologic toxicity including neutropenia and severe anemia, particularly in patients with advanced HIV-1 disease (see 7 WARNINGS AND PRECAUTIONS). Myopathy Prolonged use of RETROVIR has been associated with symptomatic myopathy (see 7 WARNINGS AND PRECAUTIONS). Lactic Acidosis and Severe Hepatomegaly Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues alone or in combination, including RETROVIR and other antiretrovirals. Suspend treatment if clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity occur (see 7 WARNINGS AND PRECAUTIONS). |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Monitoring of Patients
Hematologic toxicities appear to be related to pre-treatment bone marrow reserve and to dose and duration of therapy. In patients with poor bone marrow reserve, particularly in patients with advanced symptomatic HIV disease, frequent monitoring of hematologic indices is recommended to detect serious anemia or granulocytopenia (see 8 ADVERSE REACTIONS). In patients who experience hematologic toxicity, reduction in hemoglobin may occur as early as 2 to 4 weeks, and granulocytopenia usually occurs after 6 to 8 weeks.
Patients treated with zidovudine should be under close clinical observation to manage potential opportunistic infections associated with HIV disease. Prompt recognition of infection or toxicities and appropriate management is required.
4.2 Recommended Dose and Dosage Adjustment
Treatment of HIV-1 Infection
Oral Administration
Adults and Adolescents weighing at least 30 kg
The recommended total oral daily dose of RETROVIR (AZT) is 600 mg per day in divided doses in combination with other antiretroviral agents.
Suggested dosing regimens are listed in the following Table 1.
Table 1 Suggested Dosing Regimens for Adults and Adolescents (weighing at least 30 kg)
| Formulation | Dosing Regimen | ||||
|---|---|---|---|---|---|
Twice daily (every 12 hours) | Three times daily (every 8 hours) | ||||
| Syrup | 6 teaspoonfuls (30 mL) RETROVIR (AZT) Syrup | 4 teaspoonfuls (20 mL) RETROVIR (AZT) Syrup | |||
Children weighing at least 4 kg
The recommended oral dose in children weighing ≥ 4 kg, in combination with other antiretroviral agents, is provided in Table 2 below.
The appropriate dose of RETROVIR (AZT) for each child should be calculated based on body weight (kg) and should not exceed the recommended adult dose.
Table 2 Recommended Dosage of RETROVIR (AZT) in Children and Adolescents weighing at least 4 kg
Body Weight (kg) | Total Daily Dose | Dosage Regimen and Dose | |
|---|---|---|---|
Twice daily (every 12 hours) | Three times daily (every 8 hours) | ||
| 4 to < 9 | 24 mg/kg/day | 12 mg/kg (1.2 mL/kg) | 8 mg/kg (0.8 mL/kg) |
| ≥ 9 to < 30 | 18 mg/kg/day | 9 mg/kg (0.9 mL/kg) | 6 mg/kg (0.6 mL/kg) |
| ≥ 30 | 600 mg/day | 300 mg (30 mL) | 200 mg (20 mL) |
Alternatively, dosing for RETROVIR (AZT) can be based on body surface area (BSA) for each child. The recommended oral dose of RETROVIR (AZT) is 480 mg/m2/day in divided doses (240 mg/m2 twice daily or 160 mg/m2 three times daily). In some cases the dose calculated by mg/kg will not be the same as that calculated by BSA.
Children weighing less than 4 kg
Available data are insufficient to propose specific dosing recommendations for children weighing < 4 kg.
With regards to the treatment of HIV-1 infection, the safety and efficacy of orally-dosed RETROVIR (AZT) in pediatric patients weighing less than 4 kg has not been established. In addition, the safety and efficacy of RETROVIR (AZT) administered via infusion for treatment of HIV-1 infection in pediatric patients less than 3 months old has not been established.
Solution for Infusion
Adults and Adolescents weighing at least 30 kg
The recommended dose is 1 to 2 mg/kg administered as a 1-hour infusion every 4 hours around the clock (6 times daily). Patients should receive intravenous RETROVIR (AZT) only until oral therapy can be administered.
The intravenous dosing regimen equivalent to the oral administration of 100 mg every 4 hours is approximately 1 mg/kg intravenously every 4 hours.
RETROVIR (AZT) solution for infusion is administered intravenously at a constant rate over 1 hour. Rapid infusion or bolus injection should be avoided. RETROVIR (AZT) solution for infusion should not be given intramuscularly.
Children at least 3 months of age to 12 years of age
The recommended dose of RETROVIR (AZT) solution for infusion in children 3 months to 12 years of age is 120 mg/m2 every 6 hours, infused over 1 hour (480 mg/m2 per day). Do not exceed 160 mg for any individual dose.
Children less than 3 month of age
With regards to the treatment of HIV-1 infection, the safety and efficacy of orally-dosed RETROVIR (AZT) in pediatric patients weighing less than 4 kg has not been established. In addition, the safety and efficacy of RETROVIR (AZT) administered via infusion for treatment of HIV-1 infection in pediatric patients less than 3 months old has not been established.
Prevention of Maternal-Fetal HIV Transmission
The recommended dosing regimen for administration to pregnant women (>14 weeks of pregnancy) and their neonate is:
- Maternal Dosing. 100 mg orally 5 times per day until the start of labour. During labour and delivery, intravenous RETROVIR (AZT) should be administered at 2 mg/kg (total body weight) over 1 hour followed by a continuous intravenous infusion at 1 mg/kg/h (total body weight) until clamping of the umbilical cord.
- Neonatal Dosing. 0.2 mL/kg (2 mg/kg) of syrup every 6 hours starting within 12 hours after birth and continuing through 6 weeks of age. An appropriate sized syringe with 0.1 mL graduation should be used to ensure accurate dosing of neonates. Neonates unable to receive oral dosing may be administered RETROVIR (AZT) intravenously at 1.5 mg/kg, infused over 30 minutes, every 6 hours. See 7 WARNINGS AND PRECAUTIONS if hepatic disease or renal insufficiency is present.
Dose Adjustment
Significant anemia (hemoglobin of < 7.5 g/dL or reduction of > 25% of baseline) and/or significant granulocytopenia (granulocyte count of < 750 cells/mm3 or reduction of > 50% from baseline) may require a dose interruption until evidence of marrow recovery is observed (see 8 ADVERSE REACTIONS). In patients who develop significant anemia, dose modification does not necessarily eliminate the need for transfusion.
For less severe anemia or granulocytopenia, a reduction in daily dose may be adequate. If marrow recovery occurs following dose modification, gradual increases in dose may be appropriate depending on hematologic indices and patient tolerance.
In end-stage renal disease patients maintained on hemodialysis or peritoneal dialysis, recommended dosing is 100 mg every 6 to 8 hours for oral administration and 1 mg/kg every 6 to 8 hours for intravenous infusion (see 10.3 Pharmacokinetics AND 10 CLINICAL PHARMACOLOGY).
There are insufficient data to recommend dose adjustment of RETROVIR (AZT) in patients with impaired hepatic function. Careful monitoring for hematologic toxicities is advised (see 7 WARNINGS AND PRECAUTIONS- Hepatic/Biliary/Pancreatic).
4.4 Administration
Method of Preparation of RETROVIR (AZT) Solution for Infusion
RETROVIR (AZT) Solution for Infusion must be diluted prior to administration. The calculated dose should be removed from the 20 mL vial and added to a recommended diluent to achieve a concentration no greater than 4 mg/mL. RETROVIR (AZT) Solution for Infusion does not contain preservatives. Unused portion of the vial should be discarded. RETROVIR (AZT) Solution for Infusion must not be given intra-muscularly.
Recommended Diluents
- 5% Dextrose Injection
- 0.9% Sodium Chloride Injection
- 5% Dextrose Injection and 0.45% Sodium Chloride Injection
- Lactated Ringer’s Injection
- 5% Dextrose and Lactated Ringer’s Injection
The diluted solution should be administered within 8 hours if stored at 25ºC (77ºF) or 24 hours if refrigerated at 2º to 8ºC to minimize potential administration of a microbially contaminated solution.
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration whenever solution and container permit. Should either be observed, the solution should be discarded and fresh solution prepared.
Incompatibility
Admixture in biologic or colloidal fluids (e.g., blood products, protein solutions) is not recommended.
5 OVERDOSAGE
No specific symptoms or signs have been identified following acute overdose with RETROVIR (AZT), apart from those listed as adverse reactions (see 8 ADVERSE REACTIONS).
Activated charcoal should be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended.
Patients should be observed closely for evidence of toxicity (see 8 ADVERSE REACTIONS) and given the necessary supportive therapy.
Hemodialysis and peritoneal dialysis appear to have a limited effect on elimination of zidovudine but enhance the elimination of the glucuronide metabolite.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 Dosage Forms, Strengths, Composition and Packaging.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
Oral Intravenous infusion | Syrup/50 mg/5mL zidovudine Solution for Infusion/ 10 mg/mL zidovudine | Syrup: artificial candied sugar flavor, citric acid, glycerine, purified water, sodium benzoate (0.2%) added as a preservative, sodium hydroxide (may have been added to adjust pH), strawberry flavour, sucrose. Solution for Infusion: hydrochloric acid or sodium hydroxide (may have been added to adjust pH) water for injection. RETROVIR (AZT) Solution for Infusion contains no preservatives. |
Dosage Forms
RETROVIR (AZT) Syrup is colourless to pale yellow, strawberry-flavoured solution.
RETROVIR (AZT) Solution for Infusion is a clear, colourless to slightly yellow solution.
Packaging
Syrup
Supplied in 240 mL bottles.
Solution for Infusion
Supplied as 20 mL single-use amber vial. Box of 5 vials.
7 WARNINGS AND PRECAUTIONS
General
Anemia (usually not observed before six weeks of zidovudine therapy but occasionally occurring earlier), neutropenia (usually not observed before four weeks therapy but sometimes occurring earlier) and leucopenia (usually secondary to neutropenia) can be expected to occur in patients with advanced symptomatic HIV disease receiving zidovudine. These occurred more frequently at higher dosages (1200 to 1500 mg/day) and in patients with poor bone marrow reserve prior to treatment, particularly with advanced HIV disease.
Hematological parameters should be carefully monitored. For patients with advanced symptomatic HIV disease it is generally recommended that blood tests are performed at least every two weeks for the first three months of therapy and at least monthly thereafter. Blood tests should be performed at least weekly in patients receiving RETROVIR (AZT) intravenously.
Dosage reduction or interruption of zidovudine therapy may be necessary in patients whose hemoglobin level falls to between 7.5 g/dL (4.65 mmol/L) and 9 g/dL
(5.59 mmol/L) or whose neutrophil count falls to between 0.75 x 10⁹/L and 1.0 x 10⁹/L
Serious Adverse Reactions
Several serious adverse events have been reported with use of RETROVIR (AZT) in clinical practice. Reports of pancreatitis, sensitization reactions (including anaphylaxis in one patient), vasculitis, and seizures have been rare. These adverse events, except for sensitization, have also been associated with HIV disease. Changes in skin and nail pigmentation have been associated with the use of RETROVIR (AZT).
Before combination therapy with RETROVIR (AZT) is initiated, consult the complete prescribing information for each drug. The safety profile of RETROVIR (AZT) plus other antiretroviral agents reflects the individual safety profiles of each component.
The incidence of adverse reactions appears to increase with disease progression, and patients should be monitored carefully, especially as disease progression occurs.
Endocrine and Metabolism
- Lipoatrophy
Treatment with zidovudine has been associated with loss of subcutaneous fat. The incidence and severity of lipoatrophy are related to cumulative exposure. This fat loss, which is most evident in the face, limbs and buttocks, may be only partially reversible and improvement may take several months when switching to a zidovudine-free regimen. Patients should be regularly assessed for signs of lipoatrophy during therapy with zidovudine and other zidovudine containing products (COMBIVIR), and if feasible, therapy should be switched to an alternative regimen if there is suspicion of lipoatrophy development.
- Serum lipids and blood glucose
Serum lipid and blood glucose levels may increase during antiretroviral therapy. Disease control and life style changes may also be contributing factors. Consideration should be given to the measurement of serum lipids and blood glucose. Lipid disorders and blood glucose elevations should be managed as clinically appropriate.
Hematologic
- Bone Marrow Suppression
RETROVIR (AZT) should be used with extreme caution in patients who have bone marrow compromise evidenced by granulocyte count <1000 cells/mm3 or hemoglobin< 9.5 g/dL. In all of the placebo-controlled studies, but most frequently in patients with advanced symptomatic disease, anemia and granulocytopenia were the most significant adverse events observed (see 8 ADVERSE REACTIONS). There have been reports of pancytopenia associated with the use of RETROVIR (AZT), which was reversible in most instances after discontinuation of the drug.
Hepatic/Biliary/Pancreatic
- Lactic Acidosis/Severe Hepatomegaly with Steatosis
Rare occurrences of lactic acidosis in the absence of hypoxemia, and severe hepatomegaly with steatosis, (even in the absence of marked transaminase elevations) have been reported with the use of antiretroviral nucleoside analogues either alone or in combination, including RETROVIR (AZT), and are potentially fatal; it is not known whether these events are causally related to the use of these drugs.
Lactic acidosis should be considered whenever a patient receiving therapy with RETROVIR (AZT) develops unexplained tachypnea, dyspnea, or a fall in serum bicarbonate level. Under these circumstances, therapy with RETROVIR (AZT) should be suspended until the diagnosis of lactic acidosis has been excluded.
Clinical features which may be indicative of the development of lactic acidosis include generalized weakness, anorexia and sudden unexplained weight loss, gastrointestinal symptoms and respiratory symptoms (dyspnea and tachypnea).
Caution should be exercised when administering RETROVIR (AZT), particularly to those with known risk factors for liver disease (obese women, hepatomegaly, hepatitis, or other known risk factors). These patients should be followed closely while on therapy with RETROVIR (AZT). The significance of elevated aminotransferase levels (suggesting hepatic injury) in HIV-infected patients prior to starting RETROVIR (AZT) or while on RETROVIR (AZT) is unclear. Treatment with RETROVIR (AZT) should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis with or without hepatitis which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations.
Coadministration of zidovudine with other drugs metabolized by glucuronidation should be avoided because the toxicity of either drug may be potentiated (see 9 DRUG INTERACTIONS).
Data in patients with cirrhosis suggest that accumulation of zidovudine may occur in patients with hepatic impairment because of decreased glucuronidation. Dosage adjustments may be necessary, but as there is only limited data available precise recommendations cannot be made. If monitoring of plasma zidovudine levels is not feasible, physicians will need to monitor for signs of intolerance and adjust the dose and/or increase the interval between doses as appropriate.
- Hepatic Impairment
RETROVIR (AZT) is primarily eliminated by hepatic metabolism and zidovudine concentrations appear to be increased in patients with impaired hepatic function, which may increase the risk of hematologic toxicity. Careful monitoring for hematologic toxicities is advised. There are insufficient data to recommend dose adjustment of RETROVIR (AZT) in patients with impaired hepatic function or liver cirrhosis.
- Patients co-infected with hepatitis C virus:
Exacerbation of anemia due to ribavirin has been reported when zidovudine is part of the regimen used to treat HIV although the exact mechanism remains to be elucidated. Therefore, the co-administration of ribavirin and zidovudine is not advised and consideration should be given to replacing zidovudine in a combination ART regimen if this is already established. This is particularly important in patients with a known history of zidovudine induced anemia.
- Use With Interferon- and Ribavirin-Based Regimens:
In vitro studies have shown ribavirin can reduce the phosphorylation of pyrimidine nucleoside analogues such as zidovudine. Although no evidence of a pharmacokinetic or pharmacodynamic interaction (e.g. loss of HIV/HCV virologic suppression) was seen when ribavirin was coadministered with zidovudine in HIV/HCV co-infected patients, hepatic decompensation (some fatal) has occurred in
HIV/HCV co-infected patients receiving combination antiretroviral therapy for HIV and interferon alfa with or without ribavirin. Patients receiving interferon alfa with or without ribavirin and RETROVIR (AZT) should be closely monitored for treatment-associated toxicities, especially hepatic decompensation, neutropenia, and anemia. Discontinuation of RETROVIR (AZT) should be considered as medically appropriate. Dose reduction or discontinuation of interferon alfa, ribavirin, or both should also be considered if worsening clinical toxicities are observed, including hepatic decompensation (e.g. Child Pugh >6) (see the complete prescribing information for interferon and ribavirin).
Immune
- Immune Reconstitution Inflammatory Syndrome
During the initial phase of treatment, patients responding to antiretroviral therapy may develop an inflammatory response to indolent or residual opportunistic infections [such as Mycobacterium avium-complex (MAC), cytomegalovirus (CMV), Pneumocystis jirovecii pneumonia (PCP), and tuberculosis (TB)], which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves’ disease, polymyositis, autoimmune hepatitis and Guillain-Barre syndrome) have also been reported to occur in the setting of immune reconstitution, however, the time to onset is more variable, and can occur many months after initiation of treatment and sometimes can be an atypical presentation.
Musculoskeletal
- Myopathy
Myopathy and myositis with pathological changes similar to that produced by HIV disease have been associated with prolonged use of RETROVIR (AZT).
Renal
Zidovudine is eliminated from the body primarily by renal excretion following metabolism in the liver (glucuronidation). In patients with severely impaired renal function, dosage reduction is recommended (see 10 CLINICAL PHARMACOLOGY and 4 DOSAGE AND ADMINISTRATION). Although very little data are available, patients with severely impaired hepatic function may be at greater risk of toxicity.
Very rare occurrences of pure red cell aplasia have been reported with zidovudine use. Discontinuation of zidovudine has resulted in normalization of hematological parameters in patients with suspected zidovudine-induced pure red cell aplasia.
Hemodialysis and peritoneal dialysis have no significant effect on zidovudine elimination whereas elimination of the glucuronide metabolite is increased. For patients with end-stage renal disease maintained on hemodialysis or peritoneal dialysis, the recommended dose is 100 mg every 6 to 8 h (see 10.3 Pharmacokinetics).
Sensitivity/Resistance
- Solution for Infusion: Latex Allergy
The rubber stopper of the RETROVIR (AZT) intravenous for infusion vial contains dry natural latex rubber that has the potential to cause allergic reactions in latex sensitive individuals.
7.1 Special Populations
7.1.1 Pregnant Women
The safe use of RETROVIR (AZT) in human pregnancy has not been established in adequate and well-controlled trials investigating congenital abnormalities. Therefore administration of RETROVIR (AZT) in pregnancy should be considered only if the expected benefit outweighs the possible risk to the fetus.
There are no data on the effect of zidovudine on human female fertility. In men, zidovudine has been shown to have no effect on sperm count, morphology, or motility.
A randomized, double-blind, placebo-controlled trial was conducted in HIV-infected pregnant women to determine the utility of RETROVIR (AZT) for the prevention of maternal-fetal HIV transmission. Congenital abnormalities occurred with similar frequency between neonates born to mothers who received RETROVIR (AZT) and neonates born to mothers who received placebo. Abnormalities were either problems in embryogenesis (prior to 14 weeks) or were recognized on ultrasound before or immediately after initiation of study drug.
Pregnant women considering the use of RETROVIR (AZT) during pregnancy for prevention of HIV transmission to their infants should be advised that transmission may still occur in some cases despite therapy. The long-term consequences of in utero and infant exposure to RETROVIR (AZT) are unknown. The long-term effects of early or short-term use of RETROVIR (AZT) in pregnant women are also unknown.
RETROVIR (AZT) has been associated with findings in animal reproductive studies (see 16 NON-CLINICAL TOXICOLOGY). Pregnant women considering using RETROVIR (AZT) during pregnancy should be made aware of these findings.
There have been reports of mild, transient elevations in serum lactate levels, which may be due to mitochondrial dysfunction, in neonates and infants exposed in utero or peripartum to nucleoside reverse transcriptase inhibitors (NRTIs). The clinical relevance of transient elevations in serum lactate is unknown. There have also been very rare reports of developmental delay, seizures and other neurological disease. However, a causal relationship between these events and NRTI exposure in utero or peripartum has not been established. These findings do not affect current recommendations to use antiretroviral therapy in pregnant women to prevent vertical transmission of HIV.
Antiretroviral Pregnancy Registry
To monitor maternal-fetal outcomes of pregnant women exposed to ART (antiretroviral therapy), including RETROVIR (AZT), an Antiretroviral Pregnancy Registry has been established. Healthcare providers are encouraged to register patients:
http://www.apregistry.com
Telephone: (800) 258-4263
Fax: (800) 800-1052
RETROVIR (AZT) has been evaluated in the Antiretroviral Pregnancy Registry in over 13,000 women during pregnancy and postpartum. Available human data from the Antiretroviral Pregnancy Registry do not show an increased risk of major birth defects for RETROVIR (AZT) compared to the background rate.
The Antiretroviral Pregnancy Registry has received reports of over 13,000 exposures to RETROVIR (AZT) during pregnancy resulting in live birth. These consist of over 4,100 exposures during the first trimester, over 9,300 exposures during the second/third trimester and included 133 and 264 birth defects respectively. The prevalence (95% CI) of defects in the first trimester was 3.2% (2.7, 3.8%) and in the second/third trimester, 2.8% (2.5, 3.2%). This proportion is not significantly higher than those reported in the two population based surveillance systems (2.72 per 100 live births and 4.17 per 100 live births respectively). The Antiretroviral Pregnancy Registry does not show an increased risk of major birth defects for RETROVIR (AZT) compared to the background rate.
7.1.2 Breast-feeding
HIV-1 infected mothers should not breastfeed their infants to avoid risking postnatal transmission of HIV. Zidovudine is excreted in human milk at similar concentrations to those found in serum. Because of both the potential for HIV transmission and the potential for serious adverse reactions in nursing infants, mothers should be instructed not to breastfeed if they are receiving RETROVIR (AZT).
Lactating mice administered zidovudine (200 mg/kg intraperitoneally) were found to have milk concentrations of zidovudine five times the corresponding serum zidovudine concentration. Milk concentrations of zidovudine declined at a slower rate than serum zidovudine concentrations.
7.1.3 Pediatrics
Use in Infancy
A positive test for HIV antibody in children under 15 months of age may represent passively acquired maternal antibodies, rather than an active antibody response to infection in the infant. Thus, the presence of HIV antibody in a child less than 15 months of age must be interpreted with caution, especially in the asymptomatic infant. Auxiliary diagnostic tests may be required to confirm infection in such children.
Use in Children
See 1 INDICATIONS , 8 ADVERSE REACTIONS and 4 DOSAGE AND ADMINISTRATION. The pharmacokinetics of zidovudine in pediatric patients greater than 3 months of age is similar to that of zidovudine in adult patients.
7.1.4 Geriatrics
Zidovudine pharmacokinetics have not been studied in patients over 65 years of age and no specific data are available. However, since special care is advised in this age group due to age-associated changes such as the decrease in renal function and alterations in hematological parameters, appropriate monitoring of patients before and during use of zidovudine is advised.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adults
The frequency and severity of adverse events associated with the use of RETROVIR (AZT) in adults are greater in patients with more advanced infection at the time of initiation of therapy.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adults
Anemia and Granulocytopenia
In all of the placebo-controlled studies, but most frequently in patients with advanced symptomatic HIV disease, anemia and granulocytopenia were the most significant adverse events observed.
Significant anemia most commonly occurred after 4 to 6 weeks of therapy and in many cases required dose adjustment, discontinuation of RETROVIR (AZT), and/or blood transfusions. Frequent blood counts are strongly recommended in patients with advanced HIV disease taking RETROVIR (AZT). For asymptomatic HIV-infected individuals and patients with early HIV disease, most of whom have better marrow reserve, blood counts may be obtained less frequently, depending upon the patient's overall status. If anemia or granulocytopenia develops, dosage adjustments may be necessary (see 4 DOSAGE AND ADMINISTRATION).
The following Table 4 summarizes the relative incidence of hematologic adverse events observed in clinical studies by severity of HIV disease present at the start of treatment:
Table 4 Relative Incidence of Hematologic Adverse Events Observed in Clinical Studies By Severity of HIV Disease Present at the Start of Treatment.
Asymptomatic HIV Infection Study (n = 1338) | Granulocytopenia (< 750 cells/mm3) | Anemia (Hgb < 8.0 g/dL) | ||||
|---|---|---|---|---|---|---|
| RETROVIR (AZT) | Placebo | RETROVIR (AZT) | Placebo | |||
1500 mg/day* | 500 mg/day | 1500 mg/day* | 500 mg/day | |||
| CD4 ≤ 500 | 6.4% (n = 457) | 1.8%** (n = 453) | 1.6% (n = 428) | 6.4% (n = 457) | 1.1%** (n = 453) | 0.2% (n = 428) |
Early Symptomatic HIV Disease Study (n = 713) | Granulocytopenia (< 750 cells/mm3) | Anemia (Hgb < 8.0 g/dL) | ||||
RETROVIR (AZT) 1200 mg/day* | Placebo | RETROVIR (AZT) 1200 mg/day* | Placebo | |||
| CD4>200 | 4% (n = 361) | 1% (n = 352) | 4% (n = 361) | 0% (n = 352) | ||
Advanced Symptomatic HIV Disease Study (n = 281) | Granulocytopenia (< 750 cells/mm3) | Anemia (Hgb < 7.5 g/dL) | |||||||
|---|---|---|---|---|---|---|---|---|---|
RETROVIR (AZT) 1500 mg/day* | Placebo | RETROVIR (AZT) 1500 mg/day* | Placebo | ||||||
CD4 > 200 CD4 ≤ 200 | 10% (n = 30)** 47% (n = 114) | 3% (n = 30) 10% (n = 107) | 3% (n = 30)** 29% (n = 114) | 0% (n = 30) 5% (n = 107) | |||||
Advanced Symptomatic HIV Disease Dose Comparison Study (n = 524) | Granulocytopenia (< 750 cells/mm3) | Anemia (Hgb < 7.5 g/dL) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
RETROVIR (AZT) 1200 mg/day* | RETROVIR (AZT) 600 mg/day | RETROVIR (AZT) 1200 mg/day* | RETROVIR (AZT) 600 mg/day | ||||||||
| CD4 ≤ 200 | 51% (n = 262) | 37% (n = 262) | 39% (n = 262) | 29% (n = 262) | |||||||
* The currently recommended dose is 600 mg/day
** Not statistically significant compared to placebo
Other Adverse Events (Advanced HIV Disease)
The anemia reported in patients with advanced HIV disease receiving RETROVIR (AZT) appeared to be the result of impaired erythrocyte maturation as evidenced by macrocytosis while on drug. Although mean platelet counts in patients receiving RETROVIR (AZT) were significantly increased compared to mean baseline values, thrombocytopenia did occur in some of these patients with advanced disease. Twelve percent of patients receiving RETROVIR (AZT) compared to 5% of patients receiving placebo had > 50% decreases from baseline platelet count. Mild drug-associated elevations in total bilirubin levels have been reported as an uncommon occurrence in patients treated for asymptomatic HIV infection. The HIV-infected adults participating in these clinical trials often had baseline symptoms and signs of HIV disease and/or experienced adverse events at some time during the study. It was often difficult to distinguish adverse events possibly associated with administration of RETROVIR (AZT) from underlying signs of HIV disease or intercurrent illnesses.
The following Table 5 summarizes clinical adverse events or symptoms which occurred in at least 5% of all patients with advanced HIV disease treated with 1500 mg/day of RETROVIR (AZT) in the original placebo-controlled study. Of the items listed in the table, only severe headache, nausea, insomnia and myalgia were reported at a significantly greater rate in patients receiving RETROVIR (AZT).
Table 5 Percentage (%) of Patients with Clinical Events in Advanced HIV Disease
| Adverse Event | RETROVIR (AZT) 1500 mg/day* (n = 144) % | Placebo (n=137) % |
|---|---|---|
| BODY AS A WHOLE | ||
| Asthenia | 19 | 18 |
| Diaphoresis | 5 | 4 |
| Fever | 16 | 12 |
| Headache | 42 | 37 |
| Malaise | 8 | 7 |
| GASTROINTESTINAL | ||
| Anorexia | 11 | 8 |
| Diarrhea | 12 | 18 |
| Dyspepsia | 5 | 4 |
| GI pain | 20 | 19 |
| Nausea | 46 | 18 |
| Vomiting | 6 | 3 |
| MUSCULOSKELETAL | ||
| Myalgia | 8 | 2 |
| NERVOUS | ||
| Dizziness | 6 | 4 |
| Insomnia | 5 | 1 |
| Paresthesia | 6 | 3 |
| Somnolence | 8 | 9 |
| RESPIRATORY | ||
| Dyspnea | 5 | 3 |
| SKIN | ||
| Rash | 17 | 15 |
| SPECIAL SENSES | ||
| Taste Perversion | 5 | 8 |
*The currently recommended dose is 600 mg daily.
Other Adverse Events (Early Symptomatic/Asymptomatic HIV Disease)
All events of a severe or life-threatening nature were monitored for adults in the placebo-controlled studies in early HIV disease and asymptomatic HIV infection. Data concerning the occurrence of additional signs or symptoms were also collected. No distinction was made between events possibly associated with the administration of the study medication and those due to the underlying disease. The following Table 6 and Table 7 summarize all those events reported significantly more frequently by patients receiving RETROVIR (AZT) in these studies:
Table 6 Percentage (%) of Patients with Clinical Events in Early Symptomatic HIV Disease Study
| Adverse Event | RETROVIR (AZT) 1200 mg/day* (n = 361) % | Placebo (n = 352) % |
|---|---|---|
| BODY AS A WHOLE | ||
| Asthenia | 69 | 62 |
| GASTROINTESTINAL | ||
| Dyspepsia | 6 | 1 |
| Nausea | 61 | 41 |
| Vomiting | 25 | 13 |
* The currently recommended dose is 600 mg daily.
Table 7 Percentage (%) of Patients with Clinical Events+ in an Asymptomatic HIV Infection Study
| Adverse Event | RETROVIR (AZT) 1500 mg/day* (n = 457) % | RETROVIR (AZT) 500 mg/day* (n = 453) % | Placebo (n = 428) % |
|---|---|---|---|
| BODY AS A WHOLE | |||
| Asthenia | 10.1 | 8.6♦ | 5.8 |
| Headache | 58.0♦ | 62.5 | 52.6 |
| Malaise | 55.6 | 53.2 | 44.9 |
| GASTROINTESTINAL | |||
| Anorexia | 19.3 | 20.1 | 10.5 |
| Constipation | 8.1 | 6.4♦ | 3.5 |
| Nausea | 57.3 | 51.4 | 29.9 |
| Vomiting | 16.4 | 17.2 | 9.8 |
| NERVOUS | |||
| Dizziness | 20.8 | 17.9♦ | 15.2 |
+ Reported in ≥ 5% of study population
* The currently recommended dose is 600 mg/day
♦ Not statistically significant versus placebo.
Several serious adverse events have been reported with the use of RETROVIR (AZT) in clinical practice. Myopathy and myositis with pathological changes similar to that produced by HIV disease have been associated with prolonged use of RETROVIR (AZT). Reports of hepatomegaly with steatosis, hepatitis, pancreatitis, lactic acidosis, sensitization reactions (including anaphylaxis in one patient), hyperbilirubinemia, vasculitis, and seizures have been rare. These adverse events, except for sensitization, have also been associated with HIV disease. A single case of macular edema has been reported with the use of RETROVIR (AZT). Changes in skin and nail pigmentation have been associated with the use of RETROVIR (AZT) (see 7 WARNINGS AND PRECAUTIONS).
8.2.1 Clinical Trial Adverse Reactions - Pediatrics
Anemia and Granulocytopenia
The incidences of anemia and granulocytopenia among children with advanced HIV disease receiving RETROVIR (AZT) occurred with similar incidence to that reported for adults with AIDS or advanced ARC (see above). The following Table 8 summarizes the occurrence of anemia (Hgb < 7.5 g/dL) and granulocytopenia (< 750 cells/mm3) among 124 children receiving RETROVIR (AZT) for a mean of 267 days (range 3 to 855 days):
Table 8 The Occurrence of Anemia (Hgb < 7.5 g/dL) and Granulocytopenia (< 750 cells/mm3) Among 124 Children Receiving RETROVIR (AZT) for a Mean of 267 days
Advanced Pediatric HIV disease (n =124) | Granulocytopenia (< 750 cells/mm3) | Anemia (Hgb < 7.5 g/dL) | ||||
|---|---|---|---|---|---|---|
| n | % | n | % | |||
| 48 | 39 | 28* | 23 | |||
* Twenty-two children received one or more transfusions due to a decline in hemoglobin to < 7.5g/dL; an additional 15 children were transfused for hemoglobin levels > 7.5 g/dL. Fifty-nine percent of the patients transfused had a pre-study history of anemia or transfusion requirement.
Management of neutropenia and anemia included, in some cases, dose modification and/or blood product transfusions. In the open-label studies, 17% had their dose modified (generally a reduction in dose by 30%) due to anemia, and 25% had their dose modified (temporary discontinuation or reduction by 30%) for neutropenia. Four children had RETROVIR (AZT) permanently discontinued because of neutropenia.
Macrocytosis was observed among the majority of children enrolled in the studies.
Other Adverse Events
The clinical adverse events reported among adult recipients of RETROVIR (AZT) may also occur in children.
In the open-label studies involving 124 children, 16 different clinical adverse events were reported by 24 children. No event was reported by more than 5.6% of the study populations. Due to the open-label design of the studies, it was difficult to determine possible events related to the use of RETROVIR (AZT) versus disease-related events. Therefore, all clinical events reported as associated with therapy with RETROVIR (AZT) or of unknown relationship to therapy with RETROVIR (AZT) are presented in the following Table 9:
Table 9 Percentage (%) of Pediatric Patients with Clinical Events in Open-Label Studies
| Adverse Event | n | % |
|---|---|---|
| BODY AS A WHOLE | ||
| Fever | 4 | 3.2 |
| Phlebitis*/Bacteremia | 2 | 1.6 |
| Headache | 2 | 1.6 |
| GASTROINTESTINAL | ||
| Nausea | 1 | 0.8 |
| Vomiting | 6 | 4.8 |
| Abdominal Pain | 4 | 3.2 |
| Diarrhea | 1 | 0.8 |
| Weight Loss | 1 | 0.8 |
| NERVOUS | ||
| Insomnia | 3 | 2.4 |
| Nervousness/Irritability | 2 | 1.6 |
| Decreased Reflexes | 7 | 5.6 |
| Seizure | 1 | 0.8 |
| CARDIOVASCULAR | ||
| Left Ventricular Dilation | 1 | 0.8 |
| Cardiomyopathy | 1 | 0.8 |
| S3 Gallop | 1 | 0.8 |
| Congestive Heart Failure | 1 | 0.8 |
| Generalized Edema | 1 | 0.8 |
| ECG Abnormality | 3 | 2.4 |
| UROGENITAL | ||
| Hematuria/Viral Cystitis | 1 | 0.8 |
* Peripheral vein I.V. catheter site
Combination Therapy with RETROVIR (AZT) and 3TC (lamivudine)
Pediatric Patients
Selected clinical adverse events and physical findings with a ≥ 5% frequency during therapy with 3TC 4 mg/kg twice daily plus RETROVIR (AZT) 160 mg/m2 three times daily compared with didanosine in patients without, or with, minimal (≤ 56 days ) prior antiretroviral therapy are listed in Table 10.
Table 10 Selected Clinical Adverse Events and Physical Findings (≥ 5% Frequency) in Pediatric Patients in Study ACTG300
| Adverse Event | 3TC plus RETROVIR (AZT) (n = 236) | Didanosine (n = 235) |
|---|---|---|
| Body as a whole | ||
| Fever | 25% | 32% |
| Digestive | ||
| Hepatomegaly | 11% | 11% |
| Nausea & vomiting | 8% | 7% |
| Diarrhea | 8% | 6% |
| Stomatitis | 6% | 12% |
| Splenomegaly | 5% | 8% |
| Respiratory | ||
| Cough | 15% | 18% |
| Abnormal breath sounds/wheezing | 7% | 9% |
| Ear, Nose and Throat | ||
| Signs or symptoms of ears* | 7% | 6% |
| Nasal discharge or congestion | 8% | 11% |
| Other | ||
| Skin rashes | 12% | 14% |
| Lymphadenopathy | 9% | 11% |
*Includes pain, discharge, erythema, or swelling of an ear.
Use for the Prevention of Maternal-Fetal Transmission of HIV
In a randomized, double-blind, placebo-controlled trial in HIV-infected women and their neonates conducted to determine the utility of RETROVIR (AZT) for the prevention of maternal-fetal HIV transmission, RETROVIR (AZT) Syrup at 2 mg/kg was administered every 6 hours for 6 weeks to neonates beginning within 12 hours after birth.
The most commonly reported adverse experiences were anemia (hemoglobin < 9.0 g/dL) and neutropenia (< 1000 cells/mm3). Anemia occurred in 22% of the neonates who received RETROVIR (AZT) and in 12% of the neonates who received placebo. The mean difference in hemoglobin values was less than 1.0 g/dL for neonates receiving RETROVIR (AZT) compared to neonates receiving placebo. No neonates with anemia required transfusion and all hemoglobin values spontaneously returned to normal within 6 weeks after completion of therapy with RETROVIR (AZT). Neutropenia was reported with similar frequency in the group that received RETROVIR (AZT) (21%) and in the group that received placebo (27%). The long-term consequences of in utero and infant exposure to RETROVIR (AZT) are unknown.
8.3 Less Common Clinical Trial Adverse Reactions
Clinical adverse events which occurred in less than 5% of all adult patients treated with 1500 mg/day of RETROVIR (AZT) in the advanced HIV study are listed below. Since many of these adverse events were seen in placebo-treated patients as well as patients treated with RETROVIR (AZT), their possible relationship to the drug is unknown.
Body as a whole: Back pain, body odour, chest pain, chills, edema of the lip, flu syndrome, hyperalgesia, lymphadenopathy
Cardiovascular: Vasodilation
Gastrointestinal: Bleeding gums, constipation, dysphagia, edema of the tongue, eructation, flatulence, mouth ulcer,
rectal hemorrhage
Musculoskeletal: Arthralgia, muscle spasm, tremor, twitch
Nervous: Anxiety, confusion, depression, emotional lability, loss of mental acuity, nervousness, syncope, vertigo
Respiratory: Cough, epistaxis, hoarseness, pharyngitis, rhinitis, sinusitis
Skin: Acne, pruritus, urticaria
Special senses: Amblyopia, hearing loss, photophobia
Urogenital: Dysuria, polyuria, urinary frequency, urinary hesitancy
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Selected laboratory abnormalities experienced by patients without or minimal (≤ 56 days) prior antiretroviral therapy are listed in Table 11.
Table 11 Frequencies of Selected Laboratory Abnormalities in Pediatric Patients in Study ACTG300
Test (Abnormal Level) | 3TC plus RETROVIR (AZT) | Didanosine |
|---|---|---|
| Neutropenia (ANC < 400/mm3) | 8% | 3% |
| Anemia (Hgb < 7.0 g/dL) | 4% | 2% |
| Thrombocytopenia (platelets < 50,000/mm3) | 1% | 3% |
| ALT (> 10 x ULN) | 1% | 3% |
Test (Abnormal Level) | 3TC plus RETROVIR (AZT) | Didanosine |
|---|---|---|
| AST (> 10 x ULN) | 2% | 4% |
| Lipase (> 2.5 x ULN) | 3% | 3% |
| Total Amylase (> 2.5 x ULN) | 3% | 3% |
ULN = Upper limit of normal.
ANC = Absolute neutrophil count.
8.5 Post-Market Adverse Reactions
The following events have been reported in patients treated with RETROVIR (AZT) without regard to causality. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. A reduction in dose or suspension of RETROVIR (AZT) therapy may be warranted in the management of these conditions.
Hematological: Anemia (which may require transfusions), neutropenia, leucopenia, aplastic anemia, thrombocytopenia, pancytopenia (with marrow hypoplasia) and pure red cell aplasia.
Anemia, neutropenia, leucopenia and aplastic anemia occur more frequently at higher dosages (1200-1500 mg/day) and in patients with advanced HIV disease (especially when there is poor bone marrow reserve prior to treatment), and particularly in patients with CD4 cell counts less than 100/mm3. Dosage reduction or cessation of therapy may become necessary (see 4 DOSAGE AND ADMINISTRATION). The incidence of neutropenia was also increased in those patients whose neutrophil counts, hemoglobin levels and serum vitamin B12 levels were low at the start of RETROVIR (AZT) therapy.
Body as a Whole: Loss of subcutaneous fat (see 7 WARNINGS AND PRECAUTIONS: Endocrine and Metabolism, Lipoatrophy). Convulsions, cardiomyopathy (thrombocytopenia, pancytopenia).
Gastrointestinal: Oral mucosa pigmentation.
Immune System: Immune Reconstitution Inflammatory Syndrome (see 7 WARNINGS AND PRECAUTIONS: Immune)
Liver/pancreas: Raised blood levels of liver enzymes and bilirubin.
Metabolism & Nutrition Anorexia, hyperlactatemia,
disorders: lactic acidosis (see 7 WARNINGS AND PRECAUTIONS: Hepatic/Biliary/Pancreatic, Lactic Acidosis/Severe Hepatomegaly with Steatosis).
Miscellaneous: Gynecomastia. Myopathy, hyperlactatemia.
Skin: Sweating. Nail and skin discoloration.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Coadministration of RETROVIR (AZT) with other drugs metabolized by glucuronidation should be avoided because the toxicity of either drug may be potentiated.
Nucleoside Analogues Affecting DNA Replication
Some nucleoside analogues affecting DNA replication, such as ribavirin, antagonize the in vitro antiviral activity of RETROVIR against HIV-1; concomitant use of such drugs should be avoided.
Doxorubicin
Concomitant use of zidovudine with doxorubicin should be avoided since an antagonistic relationship has been demonstrated in vitro.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 12 Established or Potential Drug-Drug Interactions
| Proper name | Effect | Clinical comment |
|---|---|---|
| Atovaquone | Zidovudine does not appear to affect the pharmacokinetics of atovaquone. | Pharmacokinetic data have shown that atovaquone appears to decrease the rate of metabolism of zidovudine to its glucuronide metabolite (steady state AUC of zidovudine was increased by 33% and peak plasma concentration of the glucuronide was decreased by 19%). At zidovudine dosages of 500 or 600 mg/day it would seem unlikely that a three week, concomitant course of atovaquone for the treatment of acute PCP would result in an increased incidence of adverse reactions attributable to higher plasma concentrations of zidovudine. Extra care should be taken in monitoring patients receiving prolonged atovaquone therapy. |
| Bone marrow suppressive agents/cytotoxic agents | Coadministration may increase risk of hematologic toxicity. | Coadministration of RETROVIR (AZT) with drugs that are cytotoxic or which interfere with RBC/WBC number or function (e.g. dapsone, flucytosine, vincristine, vinblastine, or adriamycin) may increase the risk of hematologic toxicity. |
| Clarithromycin | Clarithromycin tablets reduce the absorption of zidovudine. | This can be avoided by separating the administration of zidovudine and clarithromycin by at least two hours. |
| Fluconazole | Fluconazole interferes with the oral clearance and metabolism of RETROVIR (AZT). | Preliminary data suggest that fluconazole interferes with the oral clearance and metabolism of RETROVIR (AZT). In a pharmacokinetic interaction study in which 12 HIV-positive men received RETROVIR (AZT) alone and in combination with fluconazole, increases in the mean peak serum concentration (79%), AUC (70%) and half-life (38%) were observed at steady state. The clinical significance of this interaction is unknown. |
| Proper name | Effect | Clinical comment |
|---|---|---|
| Ganciclovir | Coadministration increases the risk of hematologic toxicities in some patients with advanced HIV disease. | Use of RETROVIR (AZT) in combination with ganciclovir increases the risk of hematologic toxicities in some patients with advanced HIV disease. Should the use of this combination become necessary in the treatment of patients with HIV disease, dose reduction or interruption of one or both agents may be necessary to minimize hematologic toxicity. Hematologic parameters, including hemoglobin, hematocrit, and white blood cell count with differential, should be monitored frequently in all patients receiving this combination. |
| Interferon-alpha | Hematologic toxicities have been seen when RETROVIR (AZT) is used concomitantly with interferon-alpha. | As with the concomitant use of RETROVIR (AZT) and ganciclovir, dose reduction or interruption of one or both agents may be necessary, and hematologic parameters should be monitored frequently. |
| Lamivudine | Coadministration resulted in an increase in Cmax of zidovudine. | RETROVIR (AZT) and lamivudine were coadministered to 12 asymptomatic HIV-positive patients in a single-centre, open-label, randomized, crossover study. No significant differences were observed in AUC∞ or total clearance for lamivudine or zidovudine when the two drugs were administered together. Coadministration of RETROVIR (AZT) with lamivudine resulted in an increase of 39% ± 62% (mean ± SD) in Cmax of zidovudine. |
| Methadone | Plasma levels of zidovudine can be elevated in some patients while remaining unchanged in others. | In a pharmacokinetic study of 9 HIV-positive patients receiving methadone maintenance (30 to 90 mg daily) concurrent with 200 mg of RETROVIR (AZT) every 4 hours, no changes were observed in the pharmacokinetics of methadone upon initiation of therapy with RETROVIR (AZT) and after 14 days of treatment with RETROVIR (AZT). No adjustments in methadone-maintenance requirements were reported. However, plasma levels of zidovudine were elevated in some patients while remaining unchanged in others. The exact mechanism and clinical significance of these data are unknown. |
| Proper name | Effect | Clinical comment |
|---|---|---|
| Phenytoin | A decrease in oral zidovudine clearance. | Phenytoin plasma levels have been reported to be low in some patients receiving RETROVIR (AZT), while in one case a high level was documented. These observations suggest that phenytoin levels should be carefully monitored in patients receiving both medicinal products. However, in a pharmacokinetic interaction study in which 12 HIV-positive volunteers received a single 300 mg phenytoin dose alone and during steady-state zidovudine conditions (200 mg every 4 hours), no change in phenytoin kinetics was observed. Although not designed to optimally assess the effect of phenytoin on zidovudine kinetics, a 30% decrease in oral zidovudine clearance was observed. |
| Probenecid | May increase zidovudine levels. | Limited data suggest that probenecid may increase zidovudine levels by inhibiting glucuronidation and/or reducing renal excretion of zidovudine. Some patients who have used RETROVIR (AZT) concomitantly with probenecid have developed flu-like symptoms consisting of myalgia, malaise, and/or fever and maculopapular rash. |
| Ribavarin | Coadministration of ribavirin and zidovudine may lead to increased ribavirin levels and increased risk of anemia. | Preliminary data suggest that the use of ribavirin and zidovudine lead to increased ribavirin levels and increased risk of anemia. The use of ribavirin concomitantly with zidovudine in the treatment of HIV / Hep C co-infected patients is not advised. Consideration should be given to replacing zidovudine in a combination ART regimen if this is already established. |
| Stavudine | Zidovudine may inhibit intracellular phosphorylation of stavudine | Zidovudine may inhibit the intracellular phosphorylation of stavudine when the two medicinal products are used concurrently. Stavudine is therefore not recommended to be used in combination with zidovudine. |
| Proper name | Effect | Clinical comment |
|---|---|---|
| Valproic acid | Increase in zidovudine AUC and a decrease in the plasma GZDV AUC. | The concomitant administration of valproic acid 250 mg (n=5) or 500 mg (n=1) every 8 hours and zidovudine 100 mg orally every 8 hours for 4 days to 6 HIV-infected, asymptomatic male volunteers resulted in a 79% ± 61% (mean ± SD) increase in the plasma zidovudine AUC and a 22% ± 10% decrease in the plasma GZDV AUC as compared to the administration of zidovudine in the absence of valproic acid. The GZDV/zidovudine urinary excretion ratio decreased 58% ± 12%. Because no change in the zidovudine plasma half-life occurred, these results suggest that valproic acid may increase the oral bioavailability of zidovudine through inhibition of first-pass metabolism. Although the clinical signification of this interaction is unknown, patients should be monitored more closely for a possible increase in zidovudine-related adverse effects. The effect of zidovudine on the pharmacokinetics of valproic acid was not evaluated. |
| Other agents | Some drugs such as trimethoprim-sulfamethoxazole, pyrimethamine, and acyclovir may be necessary for the management or prevention of opportunistic infections. In the placebo-controlled trial in patients with advanced HIV disease, increased toxicity was not detected with limited exposure to these drugs. However, there is one published report of neurotoxicity (profound lethargy) associated with concomitant use of RETROVIR (AZT) and acyclovir. Preliminary data from a drug interaction study (n=10) suggest that coadministration of 200 mg RETROVIR (AZT) and 600 mg rifampin decreases the area under the zidovudine plasma concentration curve by an average of 48% ± 34%. However, the effect of once-daily dosing of rifampin on multiple daily doses of RETROVIR (AZT) is unknown. |
| Proper name | Effect | Clinical comment |
|---|---|---|
Other active substances including but not limited to acetylsalicylic acid, codeine, morphine, methadone, indomethacin, ketoprofen, naproxen, oxazepam, lorazepam, cimetidine, clofibrate, dapsone and isoprinosine may alter the metabolism of zidovudine by competitively inhibiting glucuronidation or directly inhibiting hepatic microsomal metabolism. Careful thought should be given to the possibilities of interactions before using such medicinal products, particularly for chronic therapy, in combination with zidovudine. Concomitant treatment, especially acute therapy, with potentially nephrotoxic or myelosuppressive medicinal products (for example systemic pentamidine, dapsone, pyrimethamine, co-trimoxazole, amphotericin, flucytosine, ganciclovir, interferon, vincristine, vinblastine and doxorubicin) may also increase the risk of adverse reactions to zidovudine. If concomitant therapy with any of these medicinal products is necessary then extra care should be taken in monitoring renal function and hematological parameters and, if required, the dosage of one or more agents should be adjusted. |
9.5 Drug-Food Interactions
Pharmacological interactions with specific foods have not been established. When taken with food, zidovudine exposure may be reduced (see 10.3 Pharmacokinetics).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
RETROVIR (AZT) is a potent inhibitor of the in vitro replication of some retroviruses including human immunodeficiency virus, HIV. Zidovudine is a thymidine analogue in which the 3-hydroxy (-OH) group is replaced by an azido (-N3) group. Cellular thymidine kinase converts zidovudine into zidovudine monophosphate. The monophosphate is further converted into the diphosphate by cellular thymidylate kinase and to the triphosphate derivative by other cellular enzymes. Zidovudine triphosphate interferes with the HIV viral RNA dependent DNA polymerase (reverse transcriptase) and thus inhibits viral replication. Zidovudine triphosphate also inhibits cellular α-DNA polymerase, but at concentrations 100-fold higher than those required to inhibit reverse transcriptase. In vitro, zidovudine triphosphate has been shown to be incorporated into growing chains of DNA by viral reverse transcriptase. When incorporation by the viral enzyme occurs, the DNA chain is terminated. Studies in cell culture suggest that zidovudine incorporation by cellular α-DNA polymerase may occur, but only to a very small extent and not in all test systems. Cellular γ-DNA polymerase shows some sensitivity to inhibition by the zidovudine triphosphate with 50% inhibitory concentration (IC50) values 400 to 900 times greater than that for HIV reverse transcriptase.
10.3 Pharmacokinetics
Adults
Pharmacokinetic studies of RETROVIR (AZT) following intravenous dosing in adults indicate dose-independent kinetics over the range of 1 to 5 mg/kg with a mean zidovudine half-life of 1.1 hours. Zidovudine is rapidly metabolized in the liver to 3'-azido-3'-deoxy-5'-O-β-D- glucopyranuronosylthymidine (GZDV, formerly called GAZT), and both are rapidly eliminated by the kidney. A second metabolite, 3'-amino-3'-deoxythymidine (AMT) has been identified in the plasma following single-dose intravenous administration of zidovudine. After oral dosing in adults, zidovudine is rapidly absorbed from the gastrointestinal tract with peak serum concentrations occurring within 0.5 to 1.5 hours, with an average oral bioavailability of 65%. In pediatric patients older than 3 months, the pharmacokinetics of zidovudine are similar to those in adult patients.
The pharmacokinetics of zidovudine has been evaluated in 22 adult HIV-infected patients in a Phase I dose-escalation study. Cohorts of 3 to 7 patients received 1-hour intravenous infusions of zidovudine ranging from 1 to 2.5 mg/kg every 8 hours to 2.5 to 7.5 mg/kg every 4 hours (3 to 45 mg/kg/day) for 14 to 28 days followed by oral dosing ranging from 2 to 5 mg/kg every 8 hours to 5 to 10 mg/kg every 4 hours (6 to 60 mg/kg/day) for an additional 32 days. After oral dosing, zidovudine was rapidly absorbed from the gastrointestinal tract with peak serum concentrations occurring within 0.5 to 1.5 hours. Dose-independent kinetics were observed over the range of 2 mg/kg every 8 hours to 10 mg/kg every 4 hours. The mean zidovudine half-life was approximately 1 hour and ranged from 0.78 to 1.93 hours following oral dosing.
Additional pharmacokinetic data following intravenous dosing indicated dose-independent kinetics over the range of 1 to 5 mg/kg with a mean zidovudine half-life of 1.1 hours (range 0.48 to 2.86 hours). Total body clearance averaged 1900 mL/min/70 kg and the apparent volume of distribution was 1.6 L/kg. Renal clearance is estimated to be 400 mL/min/70 kg indicating glomerular filtration and active tubular secretion by the kidneys. Zidovudine plasma protein binding is 34 to 38%, indicating that drug interactions involving binding site displacement are not anticipated.
The zidovudine cerebrospinal fluid (CSF)/plasma concentration ratio was determined in 39 patients receiving chronic therapy with RETROVIR (AZT). The median ratio measured in 50 paired samples drawn 1 to 8 hours after the last dose of RETROVIR (AZT) was 0.6.
Zidovudine is rapidly metabolized to 3'-azido-3'-deoxy-5'-0-β-D- glucopyranuronosyl thymidine (GZDV) which has an apparent elimination half-life of 1 hour (range 0.61 to 1.73 hours). Following oral administration, urinary recovery of zidovudine and GZDV accounted for 14% and 74% of the dose, respectively, and the total urinary recovery averaged 90% (range 63% to 95%), indicating a high degree of absorption. However, as a result of first-pass metabolism, the average oral bioavailability of zidovudine is 65% (range 52% to 75%). A second metabolite, 3'-amino-3'-deoxythymidine (AMT) has been identified in the plasma following single-dose intravenous administration of zidovudine. AMT area-under-the-curve (AUC) was one-fifth of the AUC of zidovudine and had a half-life of 2.7 ± 0.7 hours. In comparison, GZDV AUC was about 3-fold greater than the AUC of zidovudine.
Syrup
In a multiple-dose bioavailability study conducted in 12 HIV-infected adults receiving doses of 100 or 200 mg every four hours, RETROVIR (AZT) Syrup was demonstrated to be bioequivalent to RETROVIR (AZT) Capsules with respect to area under the zidovudine plasma concentration time curve (AUC). The rate of absorption of RETROVIR (AZT) Syrup was greater than that of RETROVIR (AZT) Capsules, as indicated by mean times to peak concentration of 0.5 and 0.8 hours, respectively. Mean values for steady-state peak concentration (dose-normalized to 200 mg) were 1.5 and 1.2 μg/mL for syrup and capsules, respectively.
Effect of Food on Absorption
The bioavailability of RETROVIR (AZT) syrup, as determined by AUC, may not be affected by food. However, decreased peak plasma concentrations by greater than 50% may be observed.
Special Populations and Conditions
- Pediatrics
The pharmacokinetics and bioavailability of zidovudine have been evaluated in 21 HIV-infected children, aged 6 months through 12 years, following intravenous doses administered over the range of 80 to 160 mg/m2 every 6 hours, and following oral doses of the intravenous solution administered over the range of 90 to 240 mg/m2 every 6 hours. After discontinuation of the injection, zidovudine plasma concentrations decayed biexponentially, consistent with two-compartment pharmacokinetics. Proportional increases in AUC and in zidovudine concentrations were observed with increasing dose, consistent with dose-independent kinetics over the dose range studied. The mean terminal half-life and total body clearance across all dose levels administered were 1.5 hours and 30.9 mL/min/kg, respectively. These values compare to mean half-life and total body clearance in adults of 1.1 hours and 27.1 mL/min/kg.
The mean oral bioavailability of 65% was independent of dose. This value is the same as the bioavailability in adults. Doses of 180 mg/m2 four times daily in pediatric patients produced similar systemic exposure (24 hour AUC 10.7 hr•μg/mL) as doses of 200 mg six times daily in adult patients (10.9 hr•μg/mL).
The pharmacokinetics of zidovudine has been studied in neonates from birth to 3 months of life. In one study of the pharmacokinetics of zidovudine in women during the last trimester of pregnancy, zidovudine elimination was determined immediately after birth in 8 neonates who were exposed to zidovudine in utero. The half-life was 13.0 ± 5.8 hours. In another study, the pharmacokinetics of zidovudine was evaluated in infants (ranging in age from 1 day to 3 months) of normal birth weight for gestational age and with normal renal and hepatic function. In neonates less than or equal to 14 days old, mean ± SD total body clearance was 10.9 ± 4.8 mL/min/kg (n=18) and half-life was 3.1 ± 1.2 hours (n=21). In infants greater than 14 days, total body clearance was 19.0 ± 4.0 mL/min/kg (n=16) and half-life was 1.9 ± 0.7 hours (n=18). Bioavailability was 89% ± 19% (n=15) in the younger age group and decreased to 61% ± 19% (n=17) in infants older than 14 days.
Concentrations of zidovudine in cerebrospinal fluid were measured after both intermittent oral and I.V. drug administration in 21 children during Phase I and Phase II studies. The mean zidovudine CSF/plasma concentration ratio measured at an average time of 2.2 hours post-dose at doses of 120 to 240 mg/m2 was 0.52 ± 0.44 (n=28); after an injection of doses of 80 to 160 mg/m2 over 1 hour, the mean CSF/plasma concentration ratio was 0.87 ± 0.66 (n=23) at 3.2 hours after the start of the infusion. During continuous intravenous infusion the mean steady-state CSF/plasma ratio was 0.26 ± 0.17 (n=28).
As in adult patients, the major route of elimination in children was by metabolism to GZDV. After I.V. dosing, about 29% of the dose was excreted in the urine unchanged and about 45% of the dose was excreted as GZDV. Overall, the pharmacokinetics of zidovudine in pediatric patients older than 3 months of age are similar to those of zidovudine in adult patients.
- Pregnancy:
The pharmacokinetics of zidovudine has been studied in a Phase 1 study of eight women during the last trimester of pregnancy. As pregnancy progressed, there was no evidence of drug accumulation. The pharmacokinetics of zidovudine was similar to that of nonpregnant adults. Consistent with passive transmission of the drug across the placenta, zidovudine concentrations in neonatal plasma at birth were essentially equal to those in maternal plasma at delivery. Although data are limited, methadone maintenance therapy in five pregnant women did not appear to alter zidovudine pharmacokinetics. However, in another patient population, a potential for interaction has been identified (see 7 WARNINGS AND PRECAUTIONS).
- Hepatic Insufficiency:
Data describing the effect of hepatic impairment on the pharmacokinetics of zidovudine are limited. However, because zidovudine is eliminated primarily by hepatic metabolism, it is expected that zidovudine clearance would be decreased, and plasma concentrations would be increased in subjects with hepatic impairment. Data in patients with cirrhosis suggest that accumulation of zidovudine may occur in patients with hepatic impairment because of decreased glucuronidation. Dosage adjustment of RETROVIR (AZT) may be necessary in patients with impaired hepatic function or liver cirrhosis, but the available data are insufficient to propose specific dosing recommendations (see 4 DOSAGE AND ADMINISTRATION).
- Renal Insufficiency:
Adults with Impaired Renal Function
The pharmacokinetics of zidovudine has been evaluated in patients with impaired renal function following a single 200 mg oral dose. In 14 patients (mean creatinine clearance 18 ± 2 mL/min), the half-life of zidovudine was 1.4 hours compared to 1.0 hour for control subjects with normal renal function; AUC values were approximately twice those of controls. Additionally, GZDV half-life in these patients was 8.0 hours (vs 0.9 hours for control) and AUC was 17 times higher than for control subjects. The pharmacokinetics and tolerance were evaluated in a multiple-dose study in patients undergoing hemodialysis (n=5) or peritoneal dialysis (n=6). Patients received escalating doses of zidovudine up to 200 mg 5 times daily for 8 weeks. Daily doses of 500 mg or less were well tolerated despite significantly elevated plasma levels of GZDV. Total body clearance after oral administration of zidovudine was approximately 50% of that reported in patients with normal renal function. The plasma concentrations of AMT are not known in patients with renal insufficiency. Daily doses of 300 to 400 mg should be appropriate in HIV-infected patients with severe renal dysfunction. Hemodialysis and peritoneal dialysis appear to have a negligible effect on the removal of zidovudine, whereas GZDV elimination is enhanced.
11 STORAGE, STABILITY AND DISPOSAL
RETROVIR (AZT) Syrup should be stored at 15°C to 25°C and protected from light. Discard one month after first opening.
RETROVIR (AZT) Solution for Infusion should be stored at room temperature between 15°C and 25°C and protected from light. Do not freeze.
12 SPECIAL HANDLING INSTRUCTIONS
Solution for infusion
Zidovudine i.v. for infusion must be diluted prior to administration.
Since no antimicrobial preservative is included, dilution must be carried out under full aseptic conditions, preferably immediately prior to administration, and any unused portion of the vial should be discarded.
The required dose should be added to and mixed with glucose i.v. infusion 5% w/v to give a final zidovudine concentration of either 2 mg/ml or 4 mg/ml. These dilutions are chemically and physically stable for up to 48 hours at both 5°C and 25°C.
Should any visible turbidity appear in the product either before or after dilution or during infusion, the preparation should be discarded.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: zidovudine
Chemical name: 3'-azido-3'-deoxythymidine
Other Names: erythro-3'-azidothymidine, BW A509U, 509U81, azidothymidine (AZT)
Molecular formula and molecular mass: C10H13N5O4, 267.24
Structural formula:
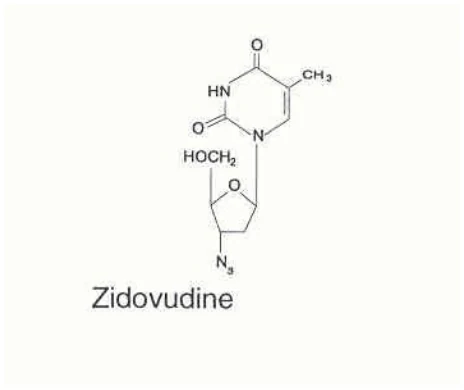
Physiochemical properties: zidovudine is a white to beige, odourless, crystalline solid. It has a melting point of 122-124°C and a solubility in water of 20.1 mg/mL at 25°C.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Prevention of Maternal-Fetal HIV Transmission
The utility of RETROVIR (AZT) for the prevention of maternal-fetal HIV transmission was demonstrated in a randomized, double-blind, placebo-controlled trial (ACTG 076) conducted in HIV-infected pregnant women who had little or no previous exposure to RETROVIR (AZT) and CD4 cell counts of 200 to 1818 cells/mm3 (median in the treated group: 560 cells/mm3). Oral RETROVIR (AZT) was initiated between 14 and 34 weeks of gestation (median 11 weeks of therapy) followed by intravenous administration of RETROVIR (AZT) during labour and delivery. After birth, neonates received oral RETROVIR (AZT) Syrup for 6 weeks. The study showed a statistically significant difference in the incidence of HIV infection in the neonates (based on viral culture from peripheral blood) between the group receiving RETROVIR (AZT) and the group receiving placebo. Of 363 neonates evaluated in the study, the estimated risk of HIV infection was 8.3% in the group receiving RETROVIR (AZT) and 25.5% in the placebo group, a relative reduction in transmission risk of 67.5%.
RETROVIR (AZT) was well tolerated by mothers and neonates. There was no difference in pregnancy-related adverse events between the treatment groups. The mean difference in hemoglobin values was less than 1.0 g/dL for neonates receiving RETROVIR (AZT) compared to neonates receiving placebo. Neonates did not require transfusion and hemoglobin values spontaneously returned to normal within 6 weeks after completion of therapy with RETROVIR (AZT). The long-term consequences of in utero and infant exposure to RETROVIR (AZT) are unknown.
Treatment of HIV
Pediatrics
Clinical Endpoint Study in Children
ACTG300 was a multicentre, randomized, double-blind study that provided for comparison of 3TC [4 mg/kg every 12 hours (max 150 mg every 12 hours)] plus RETROVIR (AZT) [160 mg/m2 TID (max 200 mg/dose)] to didanosine monotherapy. A total of 471 symptomatic, HIV-infected pediatric patients, without, or with, minimal (56 days) prior antiretroviral therapy, were enrolled in these two treatment arms. The median age was 2.7 years (range 6 weeks to 14 years), 58% were female, and 86% were non-Caucasian. The mean baseline CD4 cell count was 868 cells/mm3 (mean: 1060 cells/mm3 and range: 0 to 4650 cells/mm3 for patients 5 years of age; mean: 419 cells/mm3 and range: 0 to 1555 cells/mm3 for patients > 5 years of age) and the mean baseline plasma HIV RNA was 5.0 log10 copies/mL. The median duration on study was 10.1 months for the patients receiving 3TC plus RETROVIR (AZT) and 9.2 months for patients receiving didanosine monotherapy. Results are summarized in Table 13.
Study Results
Table 13 Number of Patients (%) Reaching a Primary Clinical Endpoint (Disease Progression or Death)
| Endpoint | 3TC plus RETROVIR (AZT) (n = 236) | Didanosine (n = 235) |
|---|---|---|
| HIV disease progression or death (total) | 15 (6.4%) | 37 (15.7%) |
| Physical growth failure | 7 (3.0%) | 6 (2.6%) |
| Central nervous system deterioration | 4 (1.7%) | 12 (5.1%) |
| CDC Clinical Category C | 2 (0.8%) | 8 (3.4%) |
| Death | 2 (0.8%) | 11 (4.7%) |
15 MICROBIOLOGY
Virology
Zidovudine is an inhibitor of the in vitro replication of some retroviruses including HIV. This drug is a thymidine analogue in which the 3'-hydroxyl (-OH) group is replaced by an azido (-N3) group. Cellular thymidine kinase converts zidovudine into zidovudine monophosphate. The monophosphate is further converted into the diphosphate by cellular thymidylate kinase and to the triphosphate derivative by other cellular enzymes. Zidovudine triphosphate interferes with the HIV viral RNA dependent DNA polymerase (reverse transcriptase) and thus inhibits viral replication. Zidovudine triphosphate also inhibits cellular α-DNA polymerase, but at concentrations 100-fold higher than those required to inhibit reverse transcriptase. In vitro, zidovudine triphosphate has been shown to be incorporated into growing chains of DNA by viral reverse transcriptase. When incorporation by the viral enzyme occurs, the DNA chain is terminated. Studies in cell culture suggest that zidovudine incorporation by cellular α-DNA polymerase may occur, but only to a very small extent and not in all test systems. Cellular γ-DNA polymerase shows some sensitivity to inhibition by the zidovudine triphosphate with 50% inhibitory concentration (IC50) values 400 to 900 times greater than that for HIV reverse transcriptase.
In Vitro Activity
The relationship between in vitro susceptibility of HIV to zidovudine and the inhibition of HIV replication in humans, or clinical response to therapy, has not been established. In vitro sensitivity results vary greatly depending upon the time between virus infection and zidovudine treatment of cell cultures, the particular assay used, the cell type employed, and the laboratory performing the test.
Zidovudine blocked 90% of detectable HIV replication in vitro at concentrations of ≤ 0.13 μg/mL (ID90) when added shortly after laboratory infection of susceptible cells. This level of antiviral effect was observed in experiments measuring reverse transcriptase activity in HIV-infected H9 cells, PHA-stimulated peripheral blood lymphocytes, and unstimulated peripheral blood lymphocytes. The concentration of drug required to produce a 50% decrease in supernatant reverse transcriptase was 0.013 μg/mL (ID50) in both HIV-infected H9 cells and peripheral blood lymphocytes. Zidovudine at concentrations of 0.13 μg/mL also provided > 90% protection from a strain of HIV (HTLV IIIB)-induced cytopathic effects in two tetanus-specific T4 cell lines. HIV-p24 antigen expression was also undetectable at the same concentration in these cells. Partial inhibition of viral activity in cells with chronic HIV infection (presumed to carry integrated HIV DNA) required concentrations of zidovudine (8.8 μg/mL in one laboratory to 13.3 μg/mL in another) which are approximately 100 times as high as those necessary to block HIV replication in acutely infected cells. HIV isolates from 18 untreated individuals with AIDS or ARC had ID50 sensitivity values between 0.003 to 0.013 μg/mL and ID95 sensitivity values between 0.03 to 0.3 μg/mL.
Zidovudine, in its nonphosphorylated form, does not inhibit the reverse transcriptase activity associated with purified HIV virions. Zidovudine was equally active against American, Haitian, and African isolates of HIV.
No antagonistic effects were seen in vitro with zidovudine and other antiretrovirals (tested agents: abacavir, didanosine, lamivudine and interferon-alpha). The major metabolite of zidovudine, 3'-azido-3'-deoxy-5'- 0-β-D-glucopyranuronosyl-thymidine (GZDV), does not inhibit HIV replication in vitro. GZDV does not antagonize the antiviral effect of zidovudine in vitro nor does GZDV compete with zidovudine triphosphate as an inhibitor of HIV reverse transcriptase.
The cytotoxicity of zidovudine for various cell lines was determined using a cell growth inhibition assay. ID50 values for several human cell lines showed little growth inhibition by zidovudine except at concentrations > 50 μg/mL. However, one human T-lymphocyte cell line was sensitive to the cytotoxic effect of zidovudine with an ID50 of 5 μg/mL. Moreover, in a colony-forming unit assay designed to assess the toxicity of zidovudine for human bone marrow, an ID50 value of < 1.25 μg/mL was estimated. Two of 10 human lymphocyte cultures tested were found to be sensitive to zidovudine at 5 μg/mL or less.
Acyclovir (ACV) has been shown to potentiate zidovudine protection of T4 cells from HTLV IIIB-induced cytopathic effects. Zidovudine alone provided 50% protection from cytopathic effects (ED50) at a concentration of 0.49 μg/mL. The ED50 decreased to 0.40 μg/mL in the presence of 0.5 μg/mL ACV and was further decreased to 0.22 μg/mL when the ACV concentration was increased to 1.0 μg/mL. The ED50 was less than 0.13 μg/mL at ACV concentrations above 2.0 μg/mL. 100% protection was observed with 0.13 μg/mL zidovudine plus 8 μg/mL ACV. The sum of fractional inhibitory concentrations is 0.14, indicating synergism. No potentiation of bone marrow cytotoxicity was observed.
Resistance
The development of resistance to zidovudine has been studied extensively. The emergence of resistance is a function of both duration of zidovudine therapy and stage of disease. Asymptomatic patients developed resistance at significantly slower rates than patients with advanced disease. In contrast, virus isolates from patients with AIDS who received a year or more of zidovudine may show more than 100-fold increases in ID50 compared to isolates pre-therapy.
In vitro resistance to zidovudine is due to the accumulation of specific mutations in the HIV reverse transcriptase coding region. Six amino acid substitutions (Met41→Leu, A67→Asn, Lys70→Arg, Leu210Trp, Thr215→Tyr or Phe, and Lys219→Gln) have been described in viruses with decreased in vitro susceptibility to zidovudine inhibition. Viruses acquire phenotypic resistance to thymidine analogues through the combination of mutations at codons 41 and 215 or by the accumulation of at least four to six mutations. These thymidine analogue mutations alone do not cause high-level cross-resistance to any of the other nucleosides, allowing for the subsequent use of other approved reverse transcriptase inhibitors.
A significant correlation between zidovudine resistance and poor clinical outcome in children with advanced disease has been reported; in addition, a correlation between reduced sensitivity to zidovudine and lower CD4 cell counts in symptom-free adults treated with zidovudine for up to three years has also been reported. However, the specific relationship between emergence of zidovudine resistance and clinical progression of disease in adults has not yet been defined.
Cross-Resistance
The potential for cross-resistance between HIV reverse transcriptase inhibitors and protease inhibitors is low because of the different enzyme targets involved. Combination therapy with zidovudine plus didanosine does not appear to prevent the emergence of zidovudine-resistant isolates. In vitro studies with zidovudine-resistant virus isolates indicate zidovudine-resistant strains are usually sensitive to didanosine. Combination therapy with RETROVIR (AZT) plus 3TC delayed the emergence of mutations conferring resistance to zidovudine. In some patients (4/34) harbouring zidovudine-resistant virus, combination therapy with RETROVIR (AZT) plus 3TC restored phenotypic sensitivity to zidovudine by 12 weeks of treatment. HIV isolates with multidrug resistance to zidovudine, didanosine, stavudine, and lamivudine were recovered from a small number of patients treated for ≥ 1 year with the combination of zidovudine and didanosine. The pattern of resistant mutations in the combination therapy was different (Ala62→Val, Val75→Ile, Phe77→Leu, Phe116 →Tyr and Gln151→Met) from monotherapy, with mutation 151 being most significant for multidrug resistance. Site-directed mutagenesis studies showed that these mutations could also result in resistance to lamivudine, and stavudine. A second pattern, typically involving a Thr69Ser mutation plus a 6 base-pair inserted at the same position, results in a phenotypic resistance to zidovudine as well as to the other approved nucleoside reverse transcriptase inhibitors. Either of these two patterns of multinucleoside resistance mutations severely limits future therapeutic options.
Other Retroviruses
Zidovudine has antiviral activity against some other mammalian retroviruses in addition to HIV. Human immunodeficiency Virus-2 (HIV-2) replication in vitro is inhibited by zidovudine with an ID50 of 0.015 μg/mL, while HTLV-1 transmission to susceptible cells is inhibited by 1 to 3 μg/mL concentrations of drug. Several strains of simian immunodeficiency virus (SIV) are also inhibited by zidovudine with ID50 values ranging from 0.13 to 6.5 μg/mL, depending upon species of origin and assay method used.
Non-Retroviruses
Zidovudine has been tested and found to be inactive in vitro as an inhibitor of Herpes Simplex Virus type 1, Adenovirus type 5, Coronavirus, Influenza A virus, Respiratory Syncytial virus, Measles virus, Rhinovirus IB, Bovine Rotavirus and Yellow Fever virus. Zidovudine had significant inhibitory activity against the Epstein-Barr virus with an ID50 of 1.4 to 2.7 μg/mL, but the clinical significance of this is unknown.
Other Microbiological Activities
The following microbiological activities of zidovudine have been observed in vitro but the clinical significance is unknown. Many Enterobacteriaceae, including strains of Shigella, Salmonella, Klebsiella, Enterobacter, Citrobacter and Escherichia coli are inhibited in vitro by low concentrations of zidovudine (0.005 to 0.5 μg/mL). Synergy of zidovudine with trimethoprim has been observed against some of these bacteria in vitro. Limited data suggest that bacterial resistance to zidovudine develops rapidly. Zidovudine has no activity against gram-positive organisms, anaerobes, mycobacteria, or fungal pathogens including Candida albicans and Cryptococcus neoformans. Although Giardia lamblia is inhibited by 1.9 μg/mL of zidovudine, no activity was observed against other protozoal pathogens.
In Vivo Antiviral Activity
The antiviral efficacy of zidovudine was assessed in BALB/c mice infected with Rauscher murine leukemia virus. Treatment with 15 mg/kg/day led to significant prolongation of life. No deaths occurred within 24 weeks in infected zidovudine-treated mice, whereas control animals given the same inoculum had a median survival of 36 days (p < 0.001). Bone marrow depression did not occur, but these doses of zidovudine did not prevent significant splenomegaly. At a dose of 145 mg/kg/day, drug toxicity was observed (3 of the 4 mice developed > 20% weight loss, severe white and red cell depression, and corneal opacities) although a significant survival advantage was shown for zidovudine-treated animals compared to control infected mice (p=0.03). These mice also had no evidence of viral replication after treatment and splenomegaly did not develop.
Efficacy of zidovudine therapy was assessed in healthy cats infected with feline leukemia virus. Eight of the 10 treated cats had some reduction in the number of FeLV antigen positive white blood cells and bone marrow cells.
16 NON-CLINICAL TOXICOLOGY
Acute Toxicity Studies
Acute toxicity studies in mice and rats at doses up to 750 mg/kg produced only one death, in a mouse given 487 mg/kg of zidovudine. Death was preceded by chronic convulsions. Decreased activity, ptosis and laboured breathing were noted in other animals for up to 35 minutes post-dose. No effects were seen during the 14-day post-dose observation period.
In a second set of acute toxicity studies at higher doses, the median lethal doses for mice were 3568 mg/kg and 3062 mg/kg for male and female, respectively. In rats, the median lethal doses were 3084 mg/kg for males and 3683 mg/kg for females.
Clinical signs noted prior to death included ptosis, decreased activity, ataxia, body tremors, urine stains and prostration in mice. In rats, decreased activity and salivation occurred in most animals; the males receiving 5000 mg/kg also exhibited rough coats and lacrimation.
Long-Term Toxicity Studies
Oral
The results of long-term toxicity studies in rats, dogs and monkeys are presented in Table 14 below.
Rats and monkeys received zidovudine by gavage, dogs were administered zidovudine capsules.
Table 14 Long – Term Toxicity Studies with Zidovudine in Rats, Dogs and Monkeys
| Species | No. per Group | Dose Levels (mg/kg/day) | Duration (weeks) | Effects | ||||
|---|---|---|---|---|---|---|---|---|
| M | F | |||||||
| CD Rat | 5 | 5 | 0, 60, 125, 250, 500 | 2 | Post-dose salivation. Weight loss in mid-dose (1/5) and high-dose (1/5) males. | |||
| CD Rat | 12 | 12 | 0, 56, 167, 500 | 13 | Anogenital staining in high-dose rats. Increased blood glucose levels in high-dose females at term. Occasional decreases in SGOT in both sexes at high dose. | |||
| CD Rat | 25 | 25 | 0, 50, 150, 450 | 52 | Salivation at high dose for the first 4 weeks. Moderate, reversible macrocytic anemia, with reticulocytosis, in the high-dose animals. Increased urine output in some high-dose animals. | |||
| Dog | 1 | 1 | 0, 125, 250, 500 | 2 | High-dose female sacrificed day 14, following 2 emesis. High-dose male had bloody vomitus on days 11, 14, 16. Marked leucopenia and thrombocytopenia in all treated dogs, most severe in high-dose. Alk. Phos., BUN and | |||
| Species | No. per Group | Dose Levels (mg/kg/day) | Duration (weeks) | Effects | ||||
|---|---|---|---|---|---|---|---|---|
| M | F | |||||||
| creatinine increased in high-dose female. Slight increase in kidney weight in both high-dose dogs and in mid-dose male. Focal to diffuse hemorrhage in GI tract and mesentery of both high-dose dogs and mid-dose female. Moderate hypoactivity in the lymph nodes, involution of the thymus (mid- and high-dose females, high-dose male) and splenic lymphoid atrophy (high-dose male only). Dose-related mild to marked hypocellularity of the bone marrow at all dose levels. | ||||||||
Monkey (Cynomolgus) | 1 | 1 | 0, 125, 250, 500 | 2 | Emesis in high-dose male. Decreased RBC, hematocrit and hemoglobin in all groups (all values within normal range). Increased SGPT in mid- and high-dose males, more marked in high-dose females. | |||
Monkey (Cynomolgus) | 4 | 4 | 0, 34, 100, 300 | 13 | Emesis in one high-dose male. Mild to moderate decrease in RBC, HCT and HB; slight to mild increase in MCV in mid- and high-dose groups. Slight decrease in WBC in high-dose males. | |||
Monkey (Cynomolgus) | 5 | 5 | 0, 35, 100, 300 | 26 | Decreased RBC, HCT and HB in all groups, generally dose-related. Increase in MCV and MCH more prominent in males. Dose-related retardation of bone marrow cell maturation, particularly in erythroid elements. Slight inconsistent increase in platelets in mid- and high-dose group. | |||
Monkey (Cynomolgus) | 6 | 6 | Males-35, 100, 300 Females-35, 100, 300 | 52 | Dose-related macrocytic anemia (i.e., decreased RBC, HCT and HB, increased MCV and MCH) maximized by week 26 at latest. After 4 weeks recovery, the bone marrow smears were similar in control and treated animals. The severity of anemia was similar to that in the 3-month and 6-month study. | |||
Carcinogenesis
Zidovudine was administered orally at three dosage levels to separate groups of mice and rats (60 females and 60 males in each group). Initial single daily doses were 30, 60 and 120 mg/kg/day in mice and 80, 220 and 600 mg/kg/day in rats. The doses in mice were reduced to 20, 30 and 40 mg/kg/day after day 90 because of treatment-related anemia, whereas in rats only the high dose was reduced to 450 mg/kg/day on day 91, and then 300 mg/kg/day on day 279.
In mice, seven late-appearing (after 19 months) vaginal neoplasms (5 non-metastasizing squamous cell carcinomas, one squamous cell papilloma and one squamous polyp) occurred in animals given the highest dose. One late-appearing squamous cell papilloma occurred in the vagina of a middle-dose animal. No vaginal tumours were found at the lowest dose.
In rats, two late-appearing (after 20 months), non-metastasizing vaginal squamous cell carcinomas occurred in animals given the highest dose. No vaginal tumours occurred at the low or middle doses in rats.
No other drug-related tumours were observed in either sex of either species.
Two transplacental carcinogenicity studies were conducted in mice. One study administered zidovudine at doses of 20 mg/kg per day or 40 mg/kg per day from gestation day 10 through parturition and lactation with dosing continuing in offspring for 24 months postnatally. The doses of zidovudine employed in this study produced zidovudine exposures approximately three times the estimated human exposure at recommended doses. After 24 months, an increase in incidence of vaginal tumours was noted with no increase in tumours in the liver or lung or any other organ in either gender. These findings are consistent with results of the standard oral carcinogenicity study in mice, as described earlier. A second study administered zidovudine at maximum tolerated doses of 12.5 mg/day or 25 mg/day (~ 1000 mg/kg nonpregnant body weight or ~ 450 mg/kg of term body weight) to pregnant mice from days 12 through 18 of gestation. There was an increase in the number of tumours in the lung, liver, and female reproductive tracts in the offspring of mice receiving the higher dose level of zidovudine.
It is not known how predictive the results of rodent carcinogenicity studies may be for humans. At doses that produced tumours in mice and rats, the estimated drug exposure (as measured by AUC) was approximately 3 times (mouse) and 24 times (rat) the estimated human exposure at the recommended therapeutic dose of 100 mg every 4 hours.
Mutagenesis
No evidence of mutagenicity (with or without metabolic activation) was observed in the Ames Salmonella mutagenicity assay at concentrations up to 10 μg per plate, which was the maximum concentration that could be tested because of the antimicrobial activity of zidovudine against the Salmonella species. In a mutagenicity assay conducted in L5178Y/TK+/- mouse lymphoma cells, zidovudine was weakly mutagenic in the absence of metabolic activation only at the highest concentrations tested (4000 and 5000 μg/mL). In the presence of metabolic activation, the drug was weakly mutagenic at concentrations of 1000 μg/mL and higher. In an in vitro mammalian cell transformation assay, zidovudine was positive at concentrations of 0.5 μg/mL and higher.
In an in vitro cytogenetic study performed in cultured human lymphocytes, zidovudine induced dose-related structural chromosomal abnormalities at concentrations of 3 μg/mL and higher. No such effects were noted at the two lowest concentrations tested, 0.3 and 1.0 μg/mL. In an in vivo cytogenetic study in rats given a single intravenous injection of zidovudine at doses of 37.5 to 300 mg/kg, there were no treatment-related structural or numerical chromosomal alterations in spite of plasma levels that were as high as 453 μg/mL five minutes after dosing.
In two in vivo micronucleus studies (designed to measure chromosome breakage or mitotic spindle apparatus damage) in male mice, oral doses of zidovudine of 100 to 1000 mg/kg/day administered once daily for approximately 4 weeks induced dose-related increases in micronucleated erythrocytes. Similar results were also seen after 4 or 7 days of dosing at 500 mg/kg/day in rats and mice.
In a study involving 11 AIDS patients, it was reported that the seven patients who were receiving RETROVIR (AZT) (1200 mg/day) as their only medication for 4 weeks to 7 months showed a chromosome breakage frequency of 8.29 ± 2.65 breaks per 100 peripheral lymphocytes. This was significantly (p <0.05) higher than the incidence of 0.5 ± 0.29 breaks per 100 cells that was observed in the four AIDS patients who had not received RETROVIR (AZT). A pilot study has demonstrated that zidovudine is incorporated into leukocyte nuclear DNA of adults, including pregnant women, taking zidovudine as treatment for HIV-1 infection, or for the prevention of mother-to-child viral transmission. Zidovudine was also incorporated into DNA from cord blood leukocytes of infants from zidovudine-treated mothers. The clinical significance of these findings is unknown.
Reproduction and Teratology
In an in vitro experiment with fertilized mouse oocytes, zidovudine exposure resulted in a dose-dependent reduction in blastocyst formation.
No effect on male or female fertility (judged by conception rates) was seen in rats given zidovudine orally at doses up to 450 mg/kg/day.
In a fertility and reproduction study, male rats were dosed for 85 days prior to mating and females for 26 days prior to mating and throughout gestation and lactation. No fetal malformations or variations occurred, but the mid- and high-doses were both embryotoxic, increasing the number of early resorptions and decreasing litter sizes. No embryotoxic effects occurred in untreated females mated with treated males.
No evidence of teratogenicity was found in rats given oral doses of zidovudine of up to 500 mg/kg/day on days 6 through 15 of gestation. The doses used in the teratology studies resulted in peak zidovudine plasma concentrations (after one half of the daily dose) in rats of 66 to 226 times the peak human plasma concentrations.
In a second teratology study in rats, an oral dose of 3000 mg/kg/day (very near the oral median lethal dose in rats of 3683 mg/kg/day) caused marked maternal toxicity and an increase in the incidence of fetal malformations including absent tail, anal atresia, fetal edema, situs inversus, diaphragmatic hernia, bent limb bones, atlas occipital defect and vertebral and/or rib anomalies. There was also a significant increase in the number of litters with bent ribs, reduced ossification of the vertebral arches, and presacral vertebrae. This dose resulted in peak zidovudine plasma concentrations 350 times peak human plasma concentrations. (Estimated area-under-the-curve AUC in rats at this dose level was 300 times the daily AUC in humans given 600 mg per day.) No evidence of teratogenicity was seen in the experiment at doses of 600 mg/kg/day or less.
In one of two studies in pregnant rabbits, the incidence of fetal resorptions was increased in rabbits given 500 mg/kg/day. There was no evidence of a teratogenic effect at any dose level. The doses used in these studies resulted in peak zidovudine plasma concentrations in rabbits of 12 to 87 times mean steady-state peak human plasma concentrations (after one sixth of the daily dose) achieved with the recommended daily dose (100 mg every 4 hours).
Peri- and Postnatal Studies
A separate peri- and postnatal study was conducted in pregnant rats given doses of 0, 50, 150 and 400 mg/kg/day from day 17 of gestation through to day 21 of lactation. There were no adverse effects noted in either generation. The reproductive capacity of those F1 generation pups which were raised to sexual maturity was not affected.
Neonatal animals were given 0, 80, 250 or 750 mg/kg/day for two months, starting on lactation day 8. Treatment-related alterations occurred only in the high-dose group and were reversible macrocytic anemia and increased urine output in both sexes, and decreased body weight gain in males. Mild to moderate increases in spleen weights were also noted.