


Product Monograph - Sandoz Tacrolimus
Recent Major Label Changes
| 2026/06 |
|---|---|
| 2026/06 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ..................................................................................................... 2
Table of Contents ...................................................................................................................... 2
Part 1: Healthcare Professional Information ............................................................................. 5
- 1. Indications ..................................................................................................................... 5
1.1. Pediatrics ........................................................................................................................... 6
1.2. Geriatrics ........................................................................................................................... 6
- 2. Contraindications .......................................................................................................... 6
- 3. Serious Warnings and Precautions Box .......................................................................... 7
- 4. Dosage and Administration ........................................................................................... 7
4.1. Dosing Considerations ....................................................................................................... 7
4.2. Recommended Dose and Dosage Adjustment ................................................................... 8
4.4. Administration ................................................................................................................. 10
4.5. Missed Dose .................................................................................................................... 10
- 5. Overdose ..................................................................................................................... 10
- 6. Dosage Forms, Strengths, Composition, and Packaging ............................................... 11
- 7. Warnings and Precautions ........................................................................................... 11
General ........................................................................................................................................ 12
Carcinogenesis and Genotoxicity ................................................................................................. 12
Cardiovascular ............................................................................................................................. 13
Driving and Operating Machinery ............................................................................................... 14
Gastrointestinal ........................................................................................................................... 14
Hematologic ................................................................................................................................ 14
Hepatic/Biliary/Pancreatic ........................................................................................................... 14
Immune ....................................................................................................................................... 15
Monitoring and Laboratory Tests ................................................................................................ 15
Neurologic ................................................................................................................................... 17
Renal ........................................................................................................................................... 18
Reproductive Health .................................................................................................................... 19
7.1. Special Populations .......................................................................................................... 19
7.1.1. Pregnancy .................................................................................................................... 19
7.1.2. Breastfeeding............................................................................................................... 21
7.1.3. Pediatrics ..................................................................................................................... 21
7.1.4. Geriatrics ..................................................................................................................... 21
- 8. Adverse Reactions ....................................................................................................... 21
8.1. Adverse Reaction Overview ............................................................................................. 21
8.2. Clinical Trial Adverse Reactions ....................................................................................... 22
8.3. Less Common Clinical Trial Adverse Reactions ................................................................ 36
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data….. ........................................................................................................................................ 37
8.5. Post-Market Adverse Reactions ....................................................................................... 37
- 9. Drug Interactions ......................................................................................................... 39
9.2. Drug Interactions Overview ............................................................................................. 39
9.3. Drug-Behaviour Interactions............................................................................................ 39
9.4. Drug-Drug Interactions .................................................................................................... 40
9.5. Drug-Food Interactions .................................................................................................... 47
9.6. Drug-Herb Interactions .................................................................................................... 47
9.7. Drug-Laboratory Test Interactions ................................................................................... 47
- 10. Clinical Pharmacology .................................................................................................. 47
10.1. Mechanism of Action ................................................................................................... 47
10.2. Pharmacodynamics ...................................................................................................... 48
10.3. Pharmacokinetics ........................................................................................................ 48
- 11. Storage, Stability, and Disposal ................................................................................... 58
- 12. Special Handling Instructions ....................................................................................... 58
Part 2: Scientific Information .................................................................................................. 59
- 13. Pharmaceutical Information ........................................................................................ 59
- 14. Clinical Trials ............................................................................................................... 60
14.1. Clinical Trials by Indication ...................................................................................... 60
14.2. Study Results ........................................................................................................... 63
14.3. Comparative Bioavailability Studies ......................................................................... 72
- 15. Microbiology ............................................................................................................... 76
- 16. Non-Clinical Toxicology ............................................................................................... 76
- 17. Supporting Product Monographs ................................................................................. 82
Patient Medication Information ............................................................................................. 83
TRANSPLANTATION ..................................................................................................................... 83
Patient Medication Information ............................................................................................. 93
RHEUMATOID ARTHRITIS ............................................................................................................ 93
Part 1: Healthcare Professional Information
1. Indications
Transplantation
Sandoz Tacrolimus (tacrolimus immediate-release capsule) is indicated for:
- prophylaxis of organ rejection in patients receiving allogeneic liver, kidney or heart transplants.
- treatment of refractory rejection in patients receiving allogeneic liver or kidney transplants.
Sandoz Tacrolimus is to be used concomitantly with adrenal corticosteroids and other immunosuppressive agents. The safety and efficacy of the use of tacrolimus with sirolimus has not been established.
Only physicians experienced in immunosuppressive therapy and management of organ transplant should prescribe Sandoz Tacrolimus. Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physician responsible for maintenance therapy should have complete information requisite for the follow-up of the patient.
Rheumatoid Arthritis
Sandoz Tacrolimus (tacrolimus immediate-release capsule) is indicated for:
- treatment of active rheumatoid arthritis in adult patients for whom disease modifying anti-rheumatic drug (DMARD) therapy is ineffective or inappropriate.
Sandoz Tacrolimus may be used as monotherapy or in combination with non-steroidal anti-inflammatory drugs (NSAIDs) and/or steroids, although the possibility of increased toxicity has not been fully explored (see 7. Warnings and Precautions and 9. Drug Interactions).
Combined use of tacrolimus with gold, penicillamine, hydroxychloroquine, sulfasalazine or azathioprine has not been studied.
There is currently insufficient data to support the concomitant use of tacrolimus and methotrexate.
Careful monitoring of Sandoz Tacrolimus-treated patients is mandatory. Sandoz Tacrolimus should only be prescribed for rheumatoid arthritis by physicians experienced with the use of immunosuppressants.
1.1. Pediatrics
Pediatrics (< 18 years of age): Experience with tacrolimus in pediatric kidney and heart transplant patients is limited. Successful liver transplants have been performed in pediatric patients (ages 4 months up to 16 years) using tacrolimus, with the majority of these patients under 5 years of age (see 7. Warnings and Precautions).
Sandoz Tacrolimus is not indicated for the use of rheumatoid arthritis in children younger than 18 years of age.
1.2. Geriatrics
Geriatrics (> 65 years of age): The safety and efficacy of tacrolimus in patients older than 65 years of age has not been established.
2. Contraindications
Sandoz Tacrolimus is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see the 6. Dosage Forms, Strengths, Composition, and Packaging section.
- 3. Serious Warnings and Precautions Box
Serious Warnings and Precautions
- Increased susceptibility to infection and the possible development of lymphoma and skin cancer may result from immunosuppression (see 7. Warnings and Precautions, Carcinogenesis and Genotoxicity, and Immune).
Transplant Patients
Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe Sandoz Tacrolimus. Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physician responsible for maintenance therapy should have complete information requisite for the follow-up of the patient and should be consulted if a patient is converted to an alternative formulation so that therapeutic drug monitoring can be instituted.
Rheumatoid Arthritis
Careful monitoring of tacrolimus-treated patients is mandatory. Sandoz Tacrolimus should only be prescribed for rheumatoid arthritis by physicians experienced with the use of immunosuppressants. Sandoz Tacrolimus is indicated for the treatment of active rheumatoid arthritis in adult patients for whom disease-modifying anti-rheumatic drug (DMARD) therapy is ineffective or inappropriate.
4. Dosage and Administration
4.1. Dosing Considerations
Due to intersubject variability following dosing with tacrolimus, individualization of the dosing regimen is necessary for optimal therapy.
Additional factors that may impact dosing include pre-existing conditions, such as renal or hepatic impairment, race, pediatric use and the concomitant use of other medications.
Tacrolimus has been used in combination with azathioprine. Tacrolimus has been used in combination with mycophenolate mofetil (MMF) in patients receiving deceased donor kidney transplants and heart transplants.
Medication errors, including inadvertent, unintentional or unsupervised substitution of Tacrolimus capsule (immediate-release) or Tacrolimus capsule (extended-release) tacrolimus formulations, have been observed. This has led to serious adverse events, including graft rejection, or other side effects which could be a consequence of either under- or over-exposure to tacrolimus. Patients should be maintained on a single formulation of tacrolimus with the corresponding daily dosing regimen; alterations in formulation or regimen should only take place under the close supervision of a transplant specialist.
Following conversion to any alternative formulation, therapeutic drug monitoring must be performed and dose adjustments made to ensure that systemic exposure to tacrolimus is maintained.
4.2. Recommended Dose and Dosage Adjustment
The initial dose of Sandoz Tacrolimus should be administered no sooner than 6 hours after transplantation. Adult patients should receive doses at the lower end of the dosing range. Concomitant adrenal corticosteroid therapy is recommended early post-transplantation.
Kidney Transplantation
The recommended starting oral dose of tacrolimus is 0.2 - 0.3 mg/kg/day administered every 12 hours in two divided doses. The initial dose of tacrolimus may be administered within 24 hours of transplantation but should be delayed until renal function has recovered (as indicated, for example, by a serum creatinine < 4 mg/dL). Black patients may require higher doses to achieve comparable blood levels. Dosage and typical tacrolimus whole blood trough concentrations are shown in the table below; blood concentration details are described under 7. Warnings and Precautions, Monitoring and Laboratory Tests, Blood Concentration Monitoring.
Table 1: Recommended Tacrolimus Oral Dosing in Kidney Transplant Patients
| Dosage | |
|---|---|
| Initial Oral Dose | 0.2 - 0.3 mg/kg/day |
| Dosing Regimen | two divided doses, q12h |
| Typical tacrolimus whole blood trough concentrations | |
Month 1-3 Month 4-12 | 7 - 20 ng/mL 5 - 15 ng/mL |
Liver Transplantation
It is recommended that patients be converted from IV to oral tacrolimus as soon as oral therapy can be tolerated. This usually occurs within 2-3 days. The first dose of oral therapy should be given 8-12 hours after discontinuing the IV infusion. The recommended starting oral dose of tacrolimus capsules is 0.1 - 0.15 mg/kg/day administered in two divided daily doses every 12 hours. The initial dose of tacrolimus should be administered no sooner than 6 hours after transplantation. Adult patients should receive doses at the lower end of the dosing range.
Some centres use lower tacrolimus doses during maintenance therapy post-transplantation. Dosing should be titrated based on clinical assessment of rejection and tolerability. Adjunct therapy with adrenal corticosteroids is recommended early post-transplant.
Heart Transplantation
The recommended starting oral dose of tacrolimus is 0.075 mg/kg/day administered every 12 hours in two divided doses. It is recommended that patients initiate oral therapy with tacrolimus capsules if possible. If IV therapy is necessary, conversion from IV to oral tacrolimus is recommended as soon as oral therapy can be tolerated. This usually occurs within 2-3 days. The initial dose of tacrolimus should be administered no sooner than 6 hours after transplantation. In a patient receiving an IV infusion, the first dose of oral therapy should be given 8-12 hours after discontinuing the IV infusion1.
Dosing should be titrated based on clinical assessments of rejection and tolerability. Lower tacrolimus dosages may be sufficient as maintenance therapy. Adjunct therapy with adrenal corticosteroids is recommended early post-transplant.
Rheumatoid Arthritis
The recommended adult oral dose of tacrolimus is 3 mg, administered once a day.
Regular monitoring of tacrolimus-treated patients for occurrence of adverse events is mandatory.
Patients with Hepatic or Renal Dysfunction
Due to the potential for nephrotoxicity, patients with renal or hepatic impairment should receive doses at the lowest value of the recommended oral dosing ranges. Further reductions in dose below these ranges may be required.
Conversion from Cyclosporine to Tacrolimus
Tacrolimus should not be used simultaneously with cyclosporine. Patients converted from cyclosporine to tacrolimus should receive the first tacrolimus dose no sooner than 24 hours after the last cyclosporine dose. Dosing may be further delayed in the presence of elevated cyclosporine levels.
Conversion from Tacrolimus to Cyclosporine
Patients converted from tacrolimus to cyclosporine should receive the first cyclosporine dose no sooner than 24 hours after the last tacrolimus dose. Dosing may be further delayed in the presence of elevated tacrolimus levels.
Pediatric Patients
Pediatric liver transplantation patients without pre-existing renal or hepatic dysfunction have required and tolerated higher doses than adults to achieve similar blood concentrations. Therefore, it is recommended that therapy be initiated in pediatric patients at a starting oral dose of 0.15 - 0.20 mg/kg/day. Dose adjustments may be required. Experience in pediatric kidney and heart transplantation patients is limited.
1 Sandoz Tacrolimus is not available in the intravenous form
Race
Although a formal study to evaluate the pharmacokinetics of tacrolimus in Black transplant patients has not been conducted, a retrospective comparison of Black and Caucasian kidney transplant patients indicated that Black patients required higher tacrolimus doses to attain similar trough concentrations.
4.4. Administration
Sandoz Tacrolimus (tacrolimus immediate-release capsules, USP) – Oral Administration
Sandoz Tacrolimus should be administered whole and should not be cut, crushed or chewed. Sandoz Tacrolimus can be administered with or without food; however, doses should be administered in a consistent manner, with doses spaced evenly throughout the day.
Based on immunosuppressive effects of tacrolimus, inhalation or direct contact with skin or mucous membranes of powder contained in tacrolimus products should be avoided during preparation. If such contact occurs, wash the skin and eyes.
4.5. Missed Dose
Transplant and Rheumatoid Arthritis
If a dose is missed, contact your physician or pharmacist immediately.
5. Overdose
Limited overdosage experience is available. Acute overdosages of up to 30 times the intended dose have been reported. All patients recovered with no sequelae. Acute overdosage has been followed by adverse reactions consistent with those listed in the Adverse Reactions section (see 8. Adverse Reactions), including mild elevations of renal function markers (creatinine), nausea, headache, hyperreflexia, oliguria, hypotension, tremor and elevations in liver enzymes. In one case, transient urticaria and lethargy were observed, and in another case, acute anuric renal insufficiency developed. Based on its high molecular weight, poor aqueous solubility and extensive erythrocyte and plasma protein binding, it is anticipated that tacrolimus is not dialyzable to any significant extent; there is no experience with charcoal hemoperfusion. The oral use of activated charcoal has been reported in treating acute overdoses, but experience has not been sufficient to warrant recommending its use. General supportive measures and treatment of specific symptoms should be followed in all cases of overdosage. In acute oral and intravenous toxicity studies, mortalities were seen at or above the following doses: in adult rats, 52X the recommended human oral dose: in immature rats, 16X the recommended oral dose, and in adult rats, 16X the recommended human intravenous dose (all based on body surface area corrections).
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 2: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Capsules 0.5 mg, 1 mg and 5 mg | black iron oxide, butyl alcohol, croscarmellose sodium, dehydrated alcohol, gelatin, hypromellose, isopropyl alcohol, lactose monohydrate, magnesium stearate, potassium hydroxide, propylene glycol, red iron oxide (5mg), shellac, strong ammonia, titanium dioxide, water, yellow iron oxide (0.5mg). |
Sandoz Tacrolimus is available for oral administration as capsules (tacrolimus immediate-release capsules) containing the equivalent of 0.5 mg, 1 mg or 5 mg of anhydrous tacrolimus.
Sandoz Tacrolimus 0.5 mg
White to off-white powder filled in size “4” capsule with light yellow opaque body imprinted with “Z” in black and light yellow opaque cap imprinted with “0.5 mg” in black. Supplied in bottles of 100 capsules.
Sandoz Tacrolimus 1 mg
White to off-white powder filled in size “4” capsule with white opaque body imprinted with “Z” in black and white opaque cap imprinted with “1 mg” in black. Supplied in bottles of 100 capsules.
Sandoz Tacrolimus 5 mg
White to off-white powder filled in size “3” capsule with Swedish orange opaque body imprinted with “Z” in black and Swedish orange opaque cap imprinted with “5 mg” in black. Supplied in bottles of 100 capsules.
7. Warnings and Precautions
Please see 3. Serious Warnings and Precautions Box.
General
Tacrolimus is extensively metabolized by the mixed-function oxidase system, primarily the cytochrome P450 system (CYP3A). Since tacrolimus is metabolized mainly by the CYP3A enzyme systems, substances known to inhibit these enzymes may decrease the metabolism or increase bioavailability of tacrolimus with resultant increases in whole blood or plasma levels. Drugs known to induce these enzyme systems may result in an increased metabolism of tacrolimus or decreased bioavailability as indicated by decreased whole blood or plasma levels. Monitoring of blood levels and appropriate dosage adjustments in transplant patients are essential when such drugs are used concomitantly (see 4. Dosage and Administration, 4.2. Recommended Dose and Dosage Adjustment, and 9. Drug Interactions).
Sandoz Tacrolimus contains lactose and is not recommended for patients with rare hereditary disease of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption.
For Transplant Patients
Sandoz Tacrolimus, when given orally, is a twice-a-day formulation of tacrolimus. Tacrolimus therapy requires careful monitoring by adequately qualified and equipped personnel. The medicinal product should only be prescribed, and changes in immunosuppressive therapy initiated, by physicians experienced in immunosuppressive therapy and the management of transplant patients.
Switching of tacrolimus immediate-release formulation to tacrolimus extended-release formulation should be done under supervision of a transplant specialist. Inadvertent, unintentional or unsupervised switching of tacrolimus immediate-release formulation to tacrolimus extended-release formulation is unsafe. This can lead to graft rejection or increased incidence of side effects, including under- or over-immunosuppression, due to clinically relevant differences in systemic exposure to tacrolimus. Patients should be maintained on a single formulation of tacrolimus with the corresponding daily dosing regimen; alterations in formulation or regimen should only take place under the close supervision of a transplant specialist (see 4. Dosage and Administration).
Following conversion to any alternative formulation, therapeutic drug monitoring must be performed and dose adjustments made to ensure that systemic exposure to tacrolimus is maintained.
Carcinogenesis and Genotoxicity
An increased incidence of malignancy is a recognized complication of immunosuppression in recipients of organ transplants. The most common forms of neoplasms are non-Hodgkin's lymphomas and carcinomas of the skin and Kaposi’s sarcoma. As with other immunosuppressive therapies, the risk of developing lymphomas and other malignancies, particularly of the skin or Kaposi’s sarcoma, may be higher in tacrolimus recipients than in the normal, healthy population. The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent.
Lymphoproliferative disorders associated with Epstein-Barr virus infection have been seen. It has been reported that reduction or discontinuation of immunosuppression may cause the lesions to regress (see 16. Non-Clinical Toxicology).
Kaposi’s sarcoma, including cases with aggressive forms of disease and fatal outcomes, has been reported in patients receiving tacrolimus. In some cases, regression of Kaposi’s sarcoma has been observed after reducing the intensity of immunosuppression.
Cardiovascular
Hypertension is a common side effect of tacrolimus therapy (see 8. Adverse Reactions). Mild or moderate hypertension is more frequently reported than severe hypertension. The incidence of hypertension decreases over time. Antihypertensive therapy may be required; the control of blood pressure can be accomplished with any of the common antihypertensive agents. Since tacrolimus may cause hyperkalemia, potassium-sparing diuretics should be avoided.
While calcium channel blocking agents can be effective in treating tacrolimus-associated hypertension, care should be taken since interference with tacrolimus metabolism may require a dosage reduction in the transplant patient (see 9. Drug Interactions). Hypertension and hyperkalemia have also been noted in patients with rheumatoid arthritis. Tacrolimus should be discontinued in patients in whom hypertension and hyperkalemia cannot be controlled.
Heart failure, myocardial hypertrophy and arrhythmia have been reported in association with the administration of tacrolimus. Myocardial hypertrophy is generally manifested by echocardiographically demonstrated concentric increases in left ventricular posterior wall and interventricular septum thickness. Hypertrophy has been observed in infants, children and adults. This condition appears reversible in most cases following dose reduction or discontinuance of therapy. In a group of 20 transplant patients with pre- and post-treatment echocardiograms who showed evidence of myocardial hypertrophy, mean tacrolimus whole blood concentrations during the period prior to diagnosis of myocardial hypertrophy ranged from 11 to 53 ng/mL in infants (N=10) age 0.4 to 2 years, 4 - 46 ng/mL in children (N=7) age 2 – 15 years and 11 - 24 ng/mL in adults (N=3) age 37 - 53 years.
Tacrolimus may prolong the QT interval and may cause Torsades de pointes. Caution should be exercised in patients with known risk factors for QT prolongation (including, but not limited to, congenital or acquired QT prolongation and concomitant medications known to prolong the QT interval or known to increase tacrolimus exposure) (see 9. Drug Interactions).
Driving and Operating Machinery
Tacrolimus may cause visual and neurological disturbances. No studies have been performed on the effects of tacrolimus on the ability to drive and use machines.
Gastrointestinal
Gastrointestinal perforation has been reported in patients treated with tacrolimus, although all cases were considered a complication of transplant surgery or were accompanied by infection, diverticulum, or malignant neoplasm. As gastrointestinal perforation may be serious or life-threatening, appropriate medical/surgical management should be instituted promptly (see 8. Adverse Reactions).
Hematologic
Cases of pure red cell aplasia (PRCA) have been reported in patients treated with tacrolimus.
A mechanism for tacrolimus-induced PRCA has not been elucidated. All patients reported risk factors for PRCA such as parvovirus B19 infection, underlying disease or concomitant medications associated with PRCA. If PRCA is diagnosed, discontinuation of tacrolimus should be considered.
Thrombotic microangiopathy (TMA) (including hemolytic uremic syndrome (HUS) and thrombotic thrombocytopenic purpura (TTP))
Concurrent use of tacrolimus and mTOR inhibitors may contribute to the risk of thrombotic microangiopathies (TMA) including hemolytic uremic syndrome (HUS) and thrombotic thrombocytopenic purpura (TTP).
Hepatic/Biliary/Pancreatic
The use of tacrolimus in liver transplant recipients experiencing post-transplant hepatic impairment may be associated with increased risk of developing renal insufficiency related to high whole blood levels of tacrolimus. These patients should be monitored closely and dose adjustments should be considered. Some evidence suggests that the use of lower doses may be warranted in these patients (see 4. Dosage and Administration).
Tacrolimus was shown to cause new onset diabetes mellitus in clinical trials of kidney, liver, and heart transplantation. New onset diabetes after transplantation may be reversible in some patients. Black and Hispanic kidney transplant patients are at an increased risk. Blood glucose concentrations should be monitored closely in patients using tacrolimus (see 8. Adverse Reactions).
Hyperglycemia, elevations in HbA1c, and overt diabetes have also been noted in rheumatoid arthritis patients treated with tacrolimus. Tacrolimus should be discontinued in patients in whom blood sugars cannot be controlled.
Immune
A lymphoproliferative disorder (LPD) related to Epstein-Barr Virus (EBV) infection has been reported in immunosuppressed organ transplant recipients. The risk of LPD appears greatest in young children who are at risk for primary EBV infection while immunosuppressed, or who are switched to tacrolimus following long-term immunosuppression therapy. Experience on combining tacrolimus with immunosuppressive drugs other than adrenal corticosteroids, azathioprine and mycophenolate mofetil is limited because of the potency of tacrolimus and the risk of over immunosuppression and such combinations are not recommended.
Immunosuppressed patients are at increased risk of developing bacterial, viral, fungal, and protozoal infections, including infection reactivation (e.g. Hepatitis B reactivation) and opportunistic infections, including activation of latent viral infections. These include BK virus-associated nephropathy and JC virus-associated progressive multifocal leukoencephalopathy (PML) which have been observed in patients receiving tacrolimus. These infections are often related to a high immunosuppressive burden and may lead to serious or fatal conditions that physicians should consider in the differential diagnosis in immunosuppressed patients with deteriorating renal function or neurological symptoms.
Cytomegalovirus (CMV) Infections
CMV is the most frequent opportunistic infection reported with tacrolimus. CMV seronegative transplant patients who receive an organ from a CMV seropositive donor disease are at higher risk of developing CMV viremia and CMV disease.
Monitoring and Laboratory Tests
Serum creatinine, potassium and fasting glucose should be assessed regularly. Routine monitoring of metabolic and hematologic systems should be performed as clinically warranted.
Blood Level Monitoring in Transplant Patients
Monitoring of tacrolimus blood levels in conjunction with other laboratory and clinical parameters is considered an essential aid to transplant patient management. During the immediate post-operative period, trough blood concentrations should be measured every 1-3 days. Tacrolimus doses are usually reduced in the post-transplant period. In patients with hepatic or renal dysfunction, or in those receiving or discontinuing concomitant interacting medications, more intensive monitoring may be required, since tacrolimus clearance may be affected under each of these circumstances. More frequent monitoring may also be required in patients early after transplantation since it is at this time patients experience the highest risk of rejection. Blood concentration monitoring is not a replacement for renal and liver function monitoring and tissue biopsies. Following discharge from the hospital, the frequency of patient monitoring will decrease with time post-transplant.
Although there is a lack of direct correlation between tacrolimus levels and drug efficacy, data from Phase II and III studies of kidney and liver transplant patients has shown an increasing incidence of adverse events with increasing trough blood concentrations. Most stable patients are maintained with 12 hours trough whole blood levels of 5 to 20 ng/mL. Long-term post-transplant patients often are maintained at the low end of this target range.
Two methods are available for the assay of tacrolimus: 1) microparticle enzyme immunoassay (MEIA) and 2) enzyme-linked immunosorbent assay (ELISA). Both methods use the same monoclonal antibody for the tacrolimus parent compound. Whole blood is the matrix of choice and specimens should be collected into tubes containing ethylene diamine tetraacetic acid (EDTA) anti-coagulant. Heparin anti-coagulation is not recommended because of the tendency to form clots on storage. Samples which are not analyzed immediately should be stored in a refrigerator and assayed within 3 days; if samples are to be kept longer, they should be deep frozen at -20oC for up to 12 months.
Kidney Transplantation
Data from the U.S. and European Phase III studies indicate that trough concentrations of tacrolimus in whole blood, as measured by IMx®, were most variable during the first week of dosing. During the first three months, 80% of the patients maintained trough concentrations between 7 - 20 ng/mL, and then between 5 - 15 ng/mL, through one year.
The relative risk of toxicity is increased with higher trough concentrations. Therefore, monitoring of whole blood trough concentrations is recommended to assist in the clinical evaluation of toxicity.
Liver Transplantation
Data from the U.S. clinical trial show that tacrolimus whole blood concentrations, as measured by ELISA, were most variable during the first week post-transplantation. After this early period, the median trough blood concentrations, measured at intervals from the second week to one year post-transplantation, ranged from 9.8 ng/mL to 19.4 ng/mL.
Heart Transplantation
Data from a European Phase III study indicates that trough concentrations of tacrolimus in whole blood, as measured by IMx®, were most variable during the first week of dosing. From 1 week to 3 months, 80% of patients maintained trough concentrations between 8 - 20 ng/mL and, from 3 months through 18 months, 80% of patients maintained trough concentrations between 6 - 18 ng/mL.
The relative risk of toxicity is increased with higher trough concentrations. Therefore, monitoring of whole blood trough concentrations is recommended to assist in the clinical evaluation of toxicity.
Blood Level Monitoring in Rheumatoid Arthritis Patients
Tacrolimus used in the treatment of rheumatoid arthritis patients, has resulted in a lower incidence rate of adverse events than previously seen in transplant patients. Trough blood levels of tacrolimus in this patient population have been demonstrated to be very close to the lower limit of quantitation in assays used to evaluate tacrolimus levels. The lower incidence rates of adverse events, as well as the lower levels of tacrolimus detected in rheumatoid arthritis patients, may be due to the lower daily dose of tacrolimus administered to this patient population. Consequently, monitoring tacrolimus trough levels in rheumatoid arthritis patients has not proven to be the most effective approach of managing this patient population. Management of these patients has proven to be effective based on the incidence of adverse events and monitoring serum creatinine levels. Current data further supports the fact that nephrotoxicity associated with tacrolimus is predictable and can be managed through the careful monitoring of serum creatinine, adjustments of concomitant medications, and if necessary, withdrawal of due to the treatment. Since tacrolimus can impair renal function, a reliable baseline level of serum creatinine should be established by at least two measurements prior to treatment. Serum creatinine should be monitored every 2 weeks during the first month of therapy and every four weeks for the next three months, then quarterly thereafter.
If serum creatinine is increased by more than 40% above baseline, the serum creatinine should be repeated in one week. If the repeated serum creatinine remains increased by more than 40% from baseline, dosing of tacrolimus should be interrupted for 14 days and the serum creatinine measurement should again be repeated. If the serum creatinine returns to a value less than a 40% increase from baseline, dosing with tacrolimus may be resumed. If the serum creatinine remains elevated by more than 40% from baseline, tacrolimus should be discontinued. These recommendations apply even if the patient’s values still lie within the laboratory normal range.
Neurologic
Tacrolimus may cause neurotoxicity, particularly when used at high doses.
Neurotoxicity, including tremor, headache, and other changes in motor function, mental status and sensory function were reported in approximately 55% of liver transplant recipients in the two randomized studies. Tremor occurred more often in tacrolimus-treated kidney transplant patients in the U.S. and European studies (54 and 35%, respectively), and heart transplant patients (15%) compared with cyclosporine-treated patients. The incidence of other neurological events in the two treatment groups in both kidney studies and heart transplant patients was similar. Tremor and headache have been associated with high whole blood concentrations of tacrolimus and may respond to dosage adjustment. Seizures have occurred in adult and pediatric patients receiving tacrolimus. Coma and delirium also have been associated with high plasma concentrations of tacrolimus.
Patients treated with tacrolimus have been reported to develop posterior reversible encephalopathy syndrome (PRES). Symptoms indicating PRES include headache, altered mental status, seizures and visual disturbances. Diagnosis should be confirmed by radiological procedure (e.g., MRI). If PRES is suspected or diagnosed, blood pressure and seizure control and immediate discontinuation of immunosuppression is advised. Most patients completely recover after appropriate measures are taken.
Renal
Tacrolimus may cause nephrotoxicity, and the likelihood increases with higher blood levels.
Nephrotoxicity has been noted in approximately 52% and 57% of kidney transplantation patients and in 40% and 36% of liver transplantation patients receiving tacrolimus in the U.S. and European randomized trials, respectively, and in 59% of heart transplantation patients in a European randomized trial (see 8. Adverse Reactions). Tacrolimus can result in renal function impairment in post-transplant patients. Acute renal impairment without active intervention may progress to chronic renal impairment. Patients with impaired renal function should be monitored closely as the dosage of tacrolimus may need to be reduced. The risk for nephrotoxicity may increase when tacrolimus is concomitantly administered with drugs associated with nephrotoxicity (see 9. Drug Interaction). When concurrent use of tacrolimus with other known nephrotoxic drugs is required, monitor renal function and tacrolimus blood concentrations frequently, and dose adjustments of both tacrolimus and/or concomitant medications should be considered upon initiation, throughout concurrent treatment and at discontinuation of such concomitant drugs. In particular, to avoid excess nephrotoxicity, when switching patients from a cyclosporine-based regimen to a tacrolimus-based regimen, cyclosporine should be discontinued at least 24 hours prior to initiating tacrolimus. Tacrolimus dosing may be further delayed in the presence of elevated cyclosporine levels (see 9. Drug Interactions). When switching from tacrolimus to cyclosporine, tacrolimus should be discontinued for at least 24 hours before initiating the other medication.
For patients with renal insufficiency, some evidence suggests that the use of lower doses may be warranted (see 10. Clinical Pharmacology and 4. Dosage and Administration).
Mild to severe hyperkalemia was reported in 31% and 21% of kidney transplant patients and in 45% and 13% of liver transplant recipients treated with tacrolimus in the U.S. and European randomized trials, respectively, and in 8% of heart transplant recipients in a European randomized trial and may require treatment (see 8 Adverse Reactions). Serum potassium levels should be monitored. Potassium-sparing diuretics should not be used and high intake of potassium should be avoided during tacrolimus therapy (see 7. Warnings and Precautions, Monitoring and Laboratory Tests).
Hyperkalemia has also been noted in patients with rheumatoid arthritis. Tacrolimus should be discontinued in patients in whom hypertension and hyperkalemia cannot be controlled. The adverse events associated with tacrolimus treatment in rheumatoid arthritis patients occurred at a lower rate of incidence than seen in transplant patients receiving tacrolimus. The majority of adverse events were mild or moderate in intensity, of limited duration and did not result in discontinuation of the study drug.
Reproductive Health
- Fertility
In reproduction studies in rats and rabbits, adverse effects on the fetus were observed mainly at dose levels that were toxic to dams. However, in female rats dosed during organogenesis, embryo toxicity (expressed as reduced pup weights) was seen at a dose, which was one-third of the maternally toxic dose. At this same dose, when administered prior to mating and during gestation, tacrolimus was associated with adverse effects on female reproductive parameters and embryolethality. This dose was equivalent to 0.5X the clinical dose (see 7. Warnings and Precautions).
7.1. Special Populations
7.1.1. Pregnancy
Tacrolimus should not be used during pregnancy unless the potential benefit to the mother outweighs potential risk to the fetus. There are no adequate and well-controlled studies in pregnant women. Tacrolimus is transferred across the placenta and infants exposed to tacrolimus in utero may be at risk of prematurity, birth defects/congenital anomalies, low birth weight, and fetal distress. The use of tacrolimus during pregnancy has been associated with preterm delivery, neonatal hyperkalemia and renal dysfunction.
Tacrolimus may increase hyperglycemia in pregnant women with diabetes (including gestational diabetes). Monitor maternal blood glucose levels regularly.
Tacrolimus may exacerbate hypertension in pregnant women and increase pre-eclampsia. Monitor and control blood pressure. Females and males of reproductive potential should consider the use of appropriate contraception prior to starting treatment with tacrolimus.
Tacrolimus at oral doses of 0.32 and 1.0 mg/kg during organogenesis in rabbits, was associated with maternal toxicity as well as an increase in incidence of abortions; these doses are equivalent to 0.33X and 1.0X (based on body surface area corrections) the recommended clinical dose (0.3 mg/kg). At the higher dose only, an increased incidence of malformations and developmental variations was also seen. Tacrolimus, at oral doses of 3.2 mg/kg during organogenesis in rats, was associated with maternal toxicity and caused an increase in late resorptions, decreased numbers of live births, and decreased pup weight and viability.
Tacrolimus, given orally at 1.0 and 3.2 mg/kg (equivalent to 0.5X and 1.5X), the recommended clinical dose based on body surface area corrections to pregnant rats after organogenesis and during lactation, was associated with reduced pup weights.
Tacrolimus, given orally at 1.0 mg/kg (0.5X the recommended clinical dose based on body surface area corrections) to male and female rats, prior to and during mating, as well as to dams during gestation and lactation, was associated with adverse effects on female reproduction and embryolethality. Effects on female reproductive function (parturition) and embryo lethal effects were indicated by a higher rate of pre-implantation loss and increased numbers of undelivered and nonviable pups. When given at 3.2 mg/kg (1.5X the recommended clinical dose based on body surface area correction), tacrolimus was associated with maternal and paternal toxicity as well as reproductive toxicity including marked adverse effects on estrous cycles, parturition, pup viability and pup malformations. Toxicities to parental rats were indicated by tremors and circling, as well as reduced weight gains and food consumption in males, and reduced food consumption during gestation and lactation in females. Adverse effects on reproductive parameters included: 1) increased copulatory intervals, 2) increased pre- and post-implantation loss of fetuses (resulting in smaller litter sizes), and 3) decreased numbers of dams delivering. No reduction in male or female fertility was evident. Adverse effects seen in pups were markedly reduced viability and a slight increase in the incidence of malformation (3 pups from 3 dams).
In experience reported by the University of Pittsburgh, eleven female transplant patients maintained on tacrolimus therapy throughout pregnancy delivered twelve babies, with one patient conceiving twice. These patients received tacrolimus from week one to 20 months prior to conception. Ten of the pregnancies were successful, four with C-sections. The neonates showed no growth retardation or congenital anomalies. Hyperkalemia was observed in the majority of babies, but resolved within 24-48 hours without adverse effects. Two babies (both premature 22 and 24 weeks) died shortly after birth. One pregnancy was complicated by diabetes, hypertension and proteinuria, the other by CMV infection requiring ganciclovir therapy. Additional information includes a report of one newborn who had temporary anuria associated with high cord blood tacrolimus concentration, however, renal function was normal within one week. Another reference reports on the successful pregnancy (normal healthy male) in a 28 year-old female with bolus steroids and increased doses of tacrolimus for liver graft rejection. In this case, the cord blood plasma concentration was approximately one half that noted in maternal plasma.
A post-authorization safety study analyzed 2,905 pregnancies from the Transplant Pregnancy Registry International (TPRI), assessing outcomes of pregnancies in women treated with regimens containing tacrolimus (number of pregnancies = 1299) or other immunosuppressants (number of pregnancies = 1606). The study results did not indicate an increased risk of major malformations. There was a trend towards a higher prevalence of spontaneous abortion among women treated with tacrolimus compared with alternative immunosuppressants. Among kidney transplant patients, there was also a trend towards a higher prevalence of pre-eclampsia in women treated with tacrolimus. Among kidney and liver transplant patients exposed to tacrolimus, 45%-55% of their live births were premature, with 75%-85% having a normal birth weight for gestational age. Similar results were observed for other immunosuppressants.
7.1.2. Breastfeeding
Tacrolimus is excreted in human milk. The effects of tacrolimus on the breastfed infant, or on milk production have not been assessed. As detrimental effects on the newborn cannot be excluded, women should not breastfeed while receiving tacrolimus.
7.1.3. Pediatrics
Heart failure, cardiomegaly and increased thickness of the myocardium have been reported in patients taking tacrolimus. Patients at risk for these effects are primarily children younger than 5 years undergoing liver “rescue”, small bowel or multivisceral transplantation with trough whole blood tacrolimus levels exceeding 25 ng/mL. Also, these patients at risk often have experienced fluid overload, renal and/or hepatic dysfunction, hypertension and are receiving large doses of corticosteroids and other concomitant medications. Cardiovascular function for such patients should be carefully monitored. In addition, tacrolimus trough whole blood levels should be maintained below 25 ng/mL. If cardiac abnormalities develop, dose reduction or discontinuation of tacrolimus should be considered in cases where the perceived risk to the patient outweighs the benefit.
The two randomized active-controlled trials of tacrolimus in primary liver transplantation included 56 pediatric patients. Thirty-one patients were randomized to tacrolimus and 25 to cyclosporine-based therapies. Additionally, a minimum of 120 pediatric patients (median age 22.5 months) who underwent 122 liver transplants were studied in an uncontrolled published trial of tacrolimus in living related donor liver transplantation. Pediatric patients generally required higher doses of tacrolimus to maintain blood trough concentrations of tacrolimus similar to adult patients (see 4. Dosage and Administration). This is thought to be a result of age-related differences in the oxidative capacity of the cytochrome P450 enzyme system (CYP3A) used to metabolize tacrolimus.
7.1.4. Geriatrics
No formal studies have been performed to evaluate the effect of tacrolimus specifically in the geriatric patient population.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Kidney Transplantation
The most common adverse reactions reported were infection, tremor, hypertension, decreased renal function, constipation, diarrhea, headache, abdominal pain and insomnia. Many of these adverse reactions were mild and responded to a reduction in dosage. Insulin-dependent post-transplant diabetes mellitus (PTDM) was related to increased whole blood trough concentrations of tacrolimus and higher doses of corticosteroids. The median time to onset of PTDM was 68 days.
Liver Transplantation
The principal adverse reactions of tacrolimus are tremor, headache, diarrhea, hypertension, nausea, and renal dysfunction. These occur with oral administration of tacrolimus and may respond to a reduction in dosing. Diarrhea was sometimes associated with other gastrointestinal complaints such as nausea and vomiting. Hyperkalemia and hypomagnesemia have occurred in patients receiving tacrolimus therapy. Hyperglycemia has been noted in many patients; some may require insulin therapy.
Heart Transplantation
The more common adverse reactions in tacrolimus-treated heart transplant recipients were kidney function abnormal, hypertension, diabetes mellitus, CMV infection, tremor, hyperglycemia, leukopenia, infection, and hyperlipemia.
Rheumatoid Arthritis
The adverse events associated with tacrolimus treatment in rheumatoid arthritis patients occurred at a lower rate of incidence than seen in transplant patients receiving tacrolimus. The majority of adverse events were mild or moderate in intensity, of limited duration and did not result in discontinuation of the study drug.
8.2. Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Kidney Transplantation
The incidence of adverse events was determined in two randomized Phase III comparative kidney transplant studies involving 508 patients receiving tacrolimus and 352 patients receiving cyclosporine. Adverse events that occurred in ≥ 15% of tacrolimus-treated patients (combined study results) are presented below for the two controlled trials in kidney transplantation:
Table 3: Kidney transplantation: Treatment-Emergent Adverse Events Occurring in ≥ 15% of tacrolimus-treated Patients
| Body System |
| U.S. STUDY | EUROPEAN STUDY | ||||||||
|---|---|---|---|---|---|---|---|---|---|
Tacrolimus N=205 % | CBIR** N=207 % | Tacrolimus N=303 % | CBIR** N=145 % | ||||||
Nervous System Tremor* | 54 | 34 | 35 | 12 | |||||
| Body System |
| U.S. STUDY | EUROPEAN STUDY | ||||||||
|---|---|---|---|---|---|---|---|---|---|
Tacrolimus N=205 % | CBIR** N=207 % | Tacrolimus N=303 % | CBIR** N=145 % | ||||||
Headache* Insomnia | 44 32 | 38 30 | 21 24 | 14 26 | |||||
Gastrointestinal Diarrhea Nausea Constipation Vomiting Dyspepsia | 44 38 35 29 28 | 41 36 43 23 20 | 22 17 31 13 16 | 10 16 35 8 13 | |||||
Cardiovascular Hypertension* | 50 | 52 | 37 | 39 | |||||
Urogenital Creatinine increased* | 45 | 42 | 35 | 21 | |||||
Metabolic and Nutritional Hypophosphatemia Hypomagnesemia Hyperkalemia* Diabetes mellitus* Hyperglycemia* | 49 34 31 24 22 | 53 17 32 9 16 | 3 4 21 12 16 | 5 1 16 2 7 | |||||
Hemic and Lymphatic Anemia Leukopenia | 30 15 | 24 17 | 18 17 | 17 15 | |||||
Body as a Whole Infection Peripheral edema Asthenia Abdominal pain Pain | 45 36 34 33 32 | 49 48 30 31 30 | 76 16 7 27 21 | 75 16 4 23 23 | |||||
| Body System |
| U.S. STUDY | EUROPEAN STUDY | ||||||||
|---|---|---|---|---|---|---|---|---|---|
Tacrolimus N=205 % | CBIR** N=207 % | Tacrolimus N=303 % | CBIR** N=145 % | ||||||
| Fever | 29 | 29 | 8 | 9 | |||||
Respiratory System Dyspnea | 22 | 18 | 12 | 11 | |||||
Musculoskeletal Arthralgia | 25 | 24 | 9 | 10 | |||||
*See 7. Warnings and Precautions **Cyclosporine-based immunosuppressive regimen.
Tacrolimus has been studied in combination with azathioprine and steroids (triple therapy) in recipients of kidney transplants. In a Phase II European trial, tacrolimus triple therapy was administered to 31 adults receiving deceased donor kidney transplants. Within six weeks post-transplant, there were no deaths or graft losses. Six patients (19.4%) experienced acute rejection, with one patient experiencing corticosteroid-resistant rejection. Three patients (9.7%) developed transient hyperglycemia, but no patient required long-term therapy for diabetes. Other adverse events reported frequently included infections (51.6%), minor neurological disorders (54.8%), and hypertension (48.8%) (Transpl Int 1995; 8:86-90). The University of Pittsburgh has studied double therapy (tacrolimus and steroids) compared to triple therapy in 204 adult recipients of kidney transplants between August 1991 and October 1992. (Clin Transplantation 1994; 8:508-515). The one year actuarial patient and graft survival of double therapy were 95 and 90% versus 91 and 82% for triple therapy (p=NS). The incidence of rejection was significantly lower with triple therapy in deceased donor recipients (39% versus 58%) but not significantly different in recipients from living related donors. New onset diabetes was seen in 20.2% of double therapy patients versus 7.7% of triple therapy patients. A U.S. Phase II trial studied 92 adult recipients of deceased donor kidney transplants randomized to three target whole blood concentration ranges of tacrolimus. All patients received antilymphoblast globulin induction with azathioprine and steroids followed by tacrolimus triple therapy initiated within 2 weeks post-transplant. With follow-up to six weeks post-transplant, there were no patient deaths, and one graft loss. The incidence of rejection was 14% combining all tacrolimus treatment groups. Adverse events requiring dose reduction were significantly associated with target tacrolimus blood concentrations (36%-62%).
Data on the safety and efficacy of tacrolimus in combination with immunosuppressants other than steroids in liver transplant patients is more limited. In the European multicentre liver transplant study, many patients received azathioprine or ATG/ALG when tacrolimus therapy was withheld. Seven patients received azathioprine in combination with tacrolimus and steroids. Of these 7 patients, one died and one lost their graft in the first year post-transplant.
Liver Transplantation
The incidence of adverse events reported in two randomized comparative liver transplant trials was determined in 514 patients receiving tacrolimus and steroids and 515 patients receiving a cyclosporine-based regimen (CBIR). The proportion of patients reporting more than one adverse event was 99.8% in the tacrolimus group and 99.6% in the CBIR group. Precautions must be taken when comparing the incidence of adverse events in the U.S. study to that in the European Study. The 12 month post-transplant information from the U.S. study and from the European study is presented below. The two studies included different patient populations and patients were treated with immunosuppressive regimens of differing intensities. Adverse events reported in ≥ 15% of tacrolimus patients (combined study results) are presented below for the two controlled trials in liver transplantation.
Table 4: Liver Transplantation: Treatment-Emergent Adverse Events Occurring in ≥ 15% of tacrolimus-treated Patients
| Body System |
| U.S. STUDY | EUROPEAN STUDY | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Tacrolimus N= 250 % | CBIR* N= 250 % | Tacrolimus N = 264 % | CBIR* N = 265 % | |||||||
Nervous System Headache Tremor Insomnia Paresthesia | 64 56 64 40 | 60 46 68 30 | 37 48 32 17 | 26 32 23 17 | ||||||
Gastrointestinal Diarrhea Nausea Constipation LFT Abnormal Anorexia Vomiting | 72 46 24 36 34 27 | 47 37 27 30 24 15 | 37 32 23 6 7 14 | 27 27 21 5 5 11 | ||||||
Cardiovascular Hypertension | 47 | 56 | 38 | 43 | ||||||
Urogenital Kidney Function Abnormal Creatinine Increased Hyperkalemia | 40 39 45 | 27 25 26 | 36 24 13 | 23 19 9 | ||||||
| Body System |
| U.S. STUDY | EUROPEAN STUDY | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Tacrolimus N= 250 % | CBIR* N= 250 % | Tacrolimus N = 264 % | CBIR* N = 265 % | |||||||
Hypokalemia BUN Increased Urinary Tract Infection Oliguria | 29 30 16 18 | 34 22 18 15 | 13 12 21 19 | 16 9 19 12 | ||||||
Metabolic and Nutritional Hyperglycemia Hypomagnesemia Peripheral Edema | 47 48 26 | 38 45 26 | 33 16 12 | 22 9 14 | ||||||
Hemic and Lymphatic Anemia Leukocytosis Thrombocytopenia | 47 32 24 | 38 26 20 | 5 8 14 | 1 8 19 | ||||||
Body as a Whole Abdominal Pain Pain Fever Asthenia Back Pain Ascites | 59 63 48 52 30 27 | 54 57 56 48 29 22 | 29 24 19 11 17 7 | 22 22 22 7 17 8 | ||||||
Respiratory System Pleural Effusion Atelectasis Dyspnea | 30 28 29 | 32 30 23 | 36 5 5 | 35 4 4 | ||||||
Skin and Appendages Pruritus Rash | 36 24 | 20 19 | 15 10 | 7 4 | ||||||
* Cyclosporine-based immunosuppressive regimen.
Heart Transplantation
The more common adverse reactions in tacrolimus-treated heart transplant recipients were kidney function abnormal, hypertension, diabetes mellitus, CMV infection, tremor, hyperglycemia, leukopenia, infection, and hyperlipemia.
Adverse events in heart transplant patients in the European trial are presented below:
Table 5: Heart Transplantation: Treatment-Emergent Adverse Events Occurring in ≥ 15% of tacrolimus-Treated Patients
COSTART Body System COSTART Term | Tacrolimus N=157 % | CBIR N=157 % |
|---|---|---|
| Cardiovascular System | ||
Hypertension Pericardial effusion | 62 15 | 69 14 |
| Body as a Whole | ||
CMV Infection Infection | 32 24 | 30 21 |
| Metabolic and Nutritional Disorder | ||
Hyperlipemia Diabetes Mellitus Hyperglycemia | 18 26 23 | 27 16 17 |
| Hemic and Lymphatic System | ||
Leukopenia Anemia | 48 50 | 39 36 |
| Urogenital System | ||
Kidney Function Abnormal Urinary Tract Infection | 56 16 | 57 12 |
| Respiratory System | ||
| Bronchitis | 17 | 18 |
| Nervous System | ||
| Tremor | 15 | 6 |
The incidence of hyperlipidemia or hypercholesterolemia as an adverse event at any time during the 18 month study was significantly lower in the tacrolimus group (45/157, 28.7%) than in the cyclosporine group (63/157, 40.1%) (p = 0.043, Fisher’s exact test).
In the US study, mean serum creatinine levels at 1 year post-transplant were significantly lower in the tacrolimus/MMF group compared with those in either the cyclosporine/MMF group (p = 0.002, one-way ANOVA) or the tacrolimus/sirolimus group (p = 0.020, one-way ANOVA).
Rheumatoid Arthritis
In a long-term study of rheumatoid arthritis patients receiving tacrolimus treatment, the adverse events seen in this patient population were similar in nature to those previously reported for patients receiving liver or kidney transplants. In this study, as well as two other studies, the incidence of treatment-emergent adverse events seen in the rheumatoid arthritis patient, has a lower incidence of occurrence than seen in the transplant patient.
A summary of treatment-emergent adverse events experienced by at least 5% of patients in any treatment group is presented in the following tables.
Table 6: Summary of Common Treatment-Emergent Adverse Events (≥ 5%) in Rheumatoid Arthritis Patients
| Body System | Phase II Study FK506RA-001 | |||
|---|---|---|---|---|
| Body System | Phase II Study FK506RA-001 | |||
Placebo N=71 % | Tacrolimus 1 mg N=69 % | Tacrolimus 3 mg N=64 % | Tacrolimus 5 mg N=64 % | |
Placebo N=71 % | Tacrolimus 1 mg N=69 % | Tacrolimus 3 mg N=64 % | Tacrolimus 5 mg N=64 % | |
| Body as a Whole | ||||
Flu Syndrome Accidental Injury Abdominal Pain Asthenia Allergic Reaction Infection | 19.7 1.4 4.2 4.2 2.8 2.8 | 26.1 10.1 7.2 2.9 5.8 1.4 | 20.3 3.1 9.4 4.7 6.3 6.3 | 15.6 7.8 9.4 6.3 1.6 1.6 |
| Digestive System | ||||
Diarrhea Nausea Dyspepsia Vomiting Gastroenteritis | 11.3 5.6 7.0 1.4 1.4 | 11.6 15.9 17.4 7.2 4.3 | 15.6 18.8 20.3 6.3 7.8 | 28.1 14.1 9.4 6.3 7.8 |
| Nervous System | ||||
Headache Tremor Paresthesia Anxiety | 11.3 0 1.4 1.4 | 10.1 4.3 2.9 1.4 | 20.3 3.1 3.1 1.6 | 15.6 21.9 9.4 10.9 |
| Cardiovascular | ||||
Hypertension Migraine Vasodilatation | 4.2 2.8 0 | 5.8 1.4 2.9 | 3.1 6.3 1.6 | 4.7 3.1 6.3 |
| Respiratory System | ||||
Pharyngitis Sinusitis Dyspnea | 2.8 0 0 | 10.1 4.3 5.8 | 3.1 7.8 0 | 3.1 3.1 1.6 |
| Metabolic and Nutritional Disorders | ||||
| Creatinine Increased | 0 | 2.9 | 3.1 | 6.3 |
| Musculoskeletal System | ||||
| Arthralgia | 5.6 | 5.8 | 4.7 | 4.7 |
| Urogenital System | ||||
| Urinary Tract Infection | 1.4 | 0 | 12.5 | 9.4 |
Table 7: Phase III Studies: Summary of Common Treatment-Emergent Adverse Events (≥5%) in Rheumatoid Arthritis Patients
| Body System |
| Study 98-0-049 | Study 98-0-51 | ||||||||
|---|---|---|---|---|---|---|---|---|---|
Placebo N=157 % | Tacrolimus 2 mg N=154 % | Tacrolimus 3 mg N=153 % | Tacrolimus 3 mg N=896 % | ||||||
| Body as a Whole | |||||||||
Flu Syndrome Accidental Injury Abdominal Pain Asthenia Back Pain Insomnia | 16.6 5.1 4.5 3.2 2.5 5.1 | 16.2 7.8 6.5 4.5 3.2 3.9 | 16.3 6.5 7.8 8.5 4.6 2.6 | 26.2 8.7 13.5 8.5 6.4 4.2 | |||||
| Digestive System | |||||||||
Diarrhea Nausea Dyspepsia Vomiting | 5.1 6.4 3.2 1.3 | 13.0 11.7 11.0 2.6 | 13.7 10.5 6.5 5.2 | 19.9 14.6 13.1 6.6 | |||||
| Nervous System | |||||||||
Headache Dizziness Tremor | 8.9 3.8 1.9 | 8.4 4.5 4.5 | 9.2 7.2 8.5 | 15.1 7.1 10.5 | |||||
| Cardiovascular | |||||||||
| Hypertension | 4.5 | 5.8 | 7.8 | 8.5 | |||||
| Respiratory System | |||||||||
Pharyngitis Sinusitis | 2.5 3.2 | 6.5 4.5 | 2.0 3.9 | 5.5 6.0 | |||||
| Skin and Appendages | |||||||||
| Rash | 6.4 | 7.1 | 3.3 | 6.8 | |||||
| Metabolic and Nutritional Disorders | |||||||||
| Creatinine Increased | 1.9 | 1.9 | 6.5 | 6.7 | |||||
| Musculoskeletal System | |||||||||
| Body System |
| Study 98-0-049 | Study 98-0-51 | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Placebo N=157 % | Tacrolimus 2 mg N=154 % | Tacrolimus 3 mg N=153 % | Tacrolimus 3 mg N=896 % | |||||||
| Cramps | 0 | 2.6 | 5.2 | 5.6 | ||||||
| Urogenital System | ||||||||||
| Urinary Tract Infection | 2.5 | 3.2 | 4.6 | 5.9 | ||||||
The overall incidence of treatment-emergent adverse events for any treatment group for the three studies (RA-001, 049, and 051) ranged from 72.0% to 90.6%. In the placebo-controlled studies (RA-001 and 049), the overall incidence of treatment-emergent adverse events for the tacrolimus-treated groups was significantly different from placebo. In the tacrolimus-treated groups, the most common adverse events seen across the three studies were flu syndrome, diarrhea, nausea, abdominal pain, dyspepsia, and tremor.
In the case of gastrointestinal events, the incidence of diarrhea in the tacrolimus-treated groups in the three studies varied from 13.0% to 28.1%, with incidence increasing with dose. Tacrolimus 5 mg/day in the RA-001 study elicited the highest incidence of diarrhea (28.1%); the next highest incidence of diarrhea was 19.9% in the 3 mg/day group in the 051 study. The incidences of diarrhea in the tacrolimus 5 mg/day group in the RA-001 study, and in the 2 mg and 3 mg groups in the 049 study were significantly different from placebo. Nausea was seen in the tacrolimus -treated groups with incidences of 10.5% to 18.8%. Only the incidence of nausea in the tacrolimus 3 mg/day group in the RA-001 study was significantly different from placebo, and the incidence did not increase with an increasing dose. Dyspepsia was observed in the tacrolimus-treated groups with incidences of 6.5% to 20.3%. In the three studies, the incidence of dyspepsia in patients taking 3 mg tacrolimus/day were 6.5% (049), 13.1% (051), and 20.3% (RA-001). The incidences of dyspepsia in the 2 mg tacrolimus/day group in the 049 study and in the tacrolimus 3 mg/day group in the RA-001 study were significantly different from placebo. No increase in incidence was seen with increasing dose in any study. Abdominal pain was reported in the tacrolimus-treated groups with incidences of 6.5% to 13.5%. There was no increase in incidence with increasing doses, and there was no significant difference from placebo in either placebo-controlled study.
The incidence of vasodilatation in the tacrolimus-treated groups varied from 1.6% to 6.3%. There was an increased incidence of vasodilatation with higher doses of tacrolimus. The incidences of vasodilatation in the tacrolimus 3 mg/day group in the 049 study and in the tacrolimus 5 mg/day group in the RA-001 study were significantly different from placebo.
Tremor occurred in the tacrolimus-treated groups with incidences of 3.1% to 21.9%. The incidence of tremor increased with an increasing dose, and in the tacrolimus 5 mg/day group in the RA-001 study, the incidence of tremor (21.9%) was more than twice the incidence of tremor seen with tacrolimus 3 mg/day in any of the three studies. The incidences of tremor in the tacrolimus 3 mg/day group in the 049 study and in the tacrolimus 5 mg/day group in the RA-001 study were significantly different from placebo. Paresthesia was seen in the tacrolimus-treated groups with incidences of 2.6% to 9.4%. The incidence of paresthesia increased with increasing dose, and in the tacrolimus 5 mg/day group in the RA-001 study, the incidence of paresthesia (9.4%) was more than twice the incidence of tremor seen with tacrolimus 3 mg/day in any of the three studies. The incidence of paresthesia in the tacrolimus 5 mg/day group in the RA-001 study was significantly different from placebo.
The incidence of urinary tract infections in the tacrolimus-treated groups varied from 3.2% to 12.5%. The incidence of urinary tract infection in the tacrolimus 3 mg/day group in the RA-001 study was significantly different from placebo; however, the incidence did not increase with increasing doses. The incidence of flu-like syndrome in the tacrolimus-treated groups ranged from 15.6% to 26.2%. There was no increase in incidence with larger doses, and no difference from placebo in any tacrolimus-treated group. The incidence of other infections was between 1.6% and 3.3% in the tacrolimus-treated groups. Increasing dose did not influence the incidence of infection, and there was no difference seen from placebo.
Comparisons of patient subpopulations were performed on data from patients in the 051 study, all of whom received tacrolimus 3 mg/day. In general, the incidence of adverse events was similar in patients < 65 years of age and ≥ 65 years of age, in patients with and without hypertension, in patients with and without hyperlipidemia, and in patients with and without diabetes.
A total of 213 patients (23.8%) were at least 65 years of age at study entry. The overall incidence of adverse events for patients ≥ 65 years of age (86.9%) was similar to that for patients < 65 years of age (88.7%). There were no notable differences between patients ≥ 65 years of age and those < 65 years of age for the incidence of any specific adverse events. The more common adverse events occurring in at least 10% of patients ≥ 65 years of age were flu syndrome (18.3%), diarrhea (16.9%), tremor (15.0%), nausea (13.6%), headache (12.7%), accidental injury (12.2%), hypertension (12.2%), dyspepsia (11.7%), and abdominal pain (11.3%). For patients < 65 years of age, the more common adverse events occurring in at least 10% of patients were flu syndrome (28.7%), diarrhea (20.8%), headache (15.8%), nausea (14.9%), abdominal pain (14.2%), and dyspepsia (13.5%). The incidences of tremor, accidental injury, and hypertension among these patients were 9.1%, 7.6%, and 7.3%, respectively.
Three hundred fifty patients (39.1%) had a history of hypertension at the time they entered the study. The overall incidence of adverse events for patients with a history of hypertension (91.1%) was similar to that for patients without a history of hypertension (86.4%). Among adverse events reported for at least 5% of patients with a history of hypertension, the incidences of bronchitis (6.9%) and peripheral edema (6.0%) were more than twice the incidences (3.1% and 2.4%, respectively) reported for patients without a history of hypertension. The more common adverse events occurring in at least 10% of patients with a history of hypertension were flu syndrome (26.9%), diarrhea (18.3%), nausea (15.7%), headache (13.4%), dyspepsia (13.1%), tremor (13.1%), abdominal pain (13.1%), and hypertension (11.7%). For patients without a history of hypertension, the more common adverse events occurring in at least 10% of patients were flu syndrome (25.8%), diarrhea (20.9%), headache (16.1%), nausea (13.9%), abdominal pain (13.7%), and dyspepsia (13.0%). The incidences of tremor and hypertension among these patients were 8.8% and 6.4%, respectively.
A total of 271 patients (30.2%) had a history of hyperlipidemia at the time they entered the study. The overall incidence of adverse events for patients with a history of hyperlipidemia (92.6%) was similar to that for patients without a history of hyperlipidemia (86.4%). There were no notable differences between patients with a history of hyperlipidemia and those without a history of hyperlipidemia for the incidence of any specific adverse events. The more common adverse events occurring in at least 10% of patients with a history of hyperlipidemia were flu syndrome (26.2%), diarrhea (18.1%), nausea (15.9%), dyspepsia (14.0%), headache (12.9%), tremor (12.2%), abdominal pain (11.8%), and asthenia (10.3%). For patients without a history of hyperlipidemia, the more common adverse events occurring in at least 10% of patients were flu syndrome (26.2%), diarrhea (20.6%), headache (16.0%), abdominal pain (14.2%), nausea (14.1%), and dyspepsia (12.6%). The incidences of tremor and asthenia among these patients were 9.8% and 7.7%, respectively. Hypercholesterolemia and hyperlipemia were reported as adverse events in 3.0% and 2.2%, respectively, of patients with a history of hyperlipidemia, and in 1.4% and 1.0%, respectively, of patients without a history of hyperlipidemia.
Seventy-five patients (8.4%) had a history of diabetes at the time of study entry. The overall incidence of adverse events for patients with a history of diabetes (89.3%) was similar to that for patients without a history of diabetes (88.2%). Among adverse events reported for at least 5% of patients with a history of diabetes, the incidences of urinary tract infection (13.3%), hyperglycemia (9.3%), and infection (8.0%) were more than twice the incidences (5.2%, 1.8%, and 2.9%, respectively) reported for patients without a history of diabetes, and the incidence of headache (6.7%) in patients with a history of diabetes was less than half the incidence (15.8%) reported for patients without a history of diabetes. The more common adverse events occurring in at least 10% of patients with a history of diabetes were flu syndrome (26.7%), diarrhea (18.7%), tremor (17.3%), dyspepsia (16.0%), urinary tract infection (13.3%), nausea (13.3%), and hypertension (12.0%). The incidences of headache and abdominal pain among these patients were 6.7% and 8.0% respectively. For patients without a history of diabetes, the more common adverse events occurring in at least 10% of patients were flu syndrome (26.2%), diarrhea (20.0%), headache (15.8%), nausea (14.7%), abdominal pain (14.0%), and dyspepsia (12.8%). The incidences of tremor and urinary tract infection among these patients were 9.9% and 5.2%, respectively.
In some Rheumatoid Arthritis patients, an increase in serum creatinine levels has been detected. In the long-term safety study (98-0-051), in which patients were treated with tacrolimus for up to 18 months, 65.5% of all patients who had increases in serum creatinine ≥
30% to < 40% above baseline had levels return to baseline during the study. For the remaining patients, creatinine levels either did not return to baseline or no documentation of follow-up levels was available. Patients with increases in serum creatinine levels ≥ 40% above baseline, had their levels return to baseline in 56.3% of all patients. These included patients who continued study drug therapy and patients who discontinued study drug therapy during the recovery period. For those patients whose creatinine levels returned to baseline, the median time to return to baseline creatinine levels was 40.5 days for patients with ≥ 30% to < 40% increase from baseline and 32.0 days for patients with ≥ 40% increases from baseline.
In Study FK506RA-001, patients who experienced an increase from baseline in serum creatinine levels of ≥ 30% and < 40%, 50% of the patients in the placebo group, 80% of patients in the 1 mg tacrolimus treatment group, 89% in the 3 mg tacrolimus treatment group and 78% of patients in the 5 mg tacrolimus treatment group experienced a return to baseline serum creatinine levels within 56 days for placebo-treated patients, 33 days for patients treated with 1 mg tacrolimus, 29 days for those treated with 3 mg and 57 days for those treated with 5 mg.
In those patients experiencing a serum creatinine increase of ≥ 40% above baseline, 50% of placebo-treated patients, 20% of the 1 mg treated patients, 75% of the patients treated with 3 mg tacrolimus and 31% of patients treated with 5 mg tacrolimus experienced a subsequent return to baseline creatinine levels. The duration of time for serum creatinine levels to return to baseline for this patient population occurred sooner than those patients experiencing a serum creatinine increase of ≥ 30% and < 40%. Patients treated with placebo demonstrated a return to baseline of serum creatinine levels within 28 days, an average of 6 days for patients treated with 1 mg, 20 days for those treated with 3 mg and 38 days for those treated with 5 mg. There were however, eight of nine patients with elevated creatinine levels (> 40%) who discontinued the study. These patients had creatinine values return to below a 40% increase from baseline and within normal limits (0.7 - 1.4 mg/dL) post discontinuation, with one patient lost to follow-up.
In study 98-0-049, of those patients who experienced an increase from baseline in creatinine of ≥ 30% to < 40%, 63.6% of these patients in the placebo treatment group, 50.0% of patients in the 2 mg tacrolimus treatment group, and 77.8% of patients in the 3 mg tacrolimus treatment group, experienced a documented subsequent return to baseline creatinine values, within 36 days for placebo-treated patients, 43 days for 2 mg treated patients and 41 days for 3 mg patients treated with tacrolimus. For those patients with a ≥ 40% increase from baseline, 33.3% of patients in the placebo treatment group, 53.3% of patients in the 2 mg tacrolimus treatment group, and 45.5% of patients in the 3 mg tacrolimus treatment group experienced a documented subsequent return to baseline creatinine values. Serum creatinine levels in this patient population returned to baseline levels sooner than patients who experienced an increase from baseline of ≥ 30% to < 40%. Patients with a serum creatinine increase > 40% demonstrated a return to baseline at 20 days for placebo-treated patients, 33 days for patients treated with 2 mg and 38 days for those patients treated with 3 mg tacrolimus per day. The remaining patients either had creatinine levels that did not return to baseline during the follow-up period or were not monitored for return to baseline values.
For 88.5% (139/157) of placebo-treated patients, 87.0% (134/154) of patients treated with 2 mg/day tacrolimus and 86.3% (132/153) of patients treated with 3 mg/day tacrolimus, creatinine levels were within the normal range at baseline, and remained within the normal range throughout the study. In total, four patients - all treated with 3 mg tacrolimus - discontinued treatment as a result of a reported adverse event of increased serum creatinine.
Table 8: Number of Patients with at Least a 30% Baseline Increase in Serum Creatinine that Returned to Baseline
| Evaluated Study Groups | Increase in Serum Creatinine Levels Above Baseline | |
|---|---|---|
| ≥ 30% to < 40%†† | ≥ 40%†† | |
| Study 98-0-051 | ||
| Combined De Novo† (n=685) | 46/78 (59.0%) | 90/177 (50.8%) |
| 2 mg‡ (n=103) | 8/11 (72.7%) | 20/37 (54.1%) |
| 3 mg* (n=108) | 20/24 (83.3%) | 37/47 (78.7%) |
| Total (n=896) | 74/113 (65.5%) | 147/261 (56.3%) |
| Study FK506RA-001 | ||
| Placebo (n=71) | 1/2 (50%) | 2/4 (50%) |
| 1 mg (n=69) | 4/5 (80%) | 1/5 (20%) |
| 3 mg (n=64) | 8/9 (88.9%) | 9/12 (75%) |
| 5 mg (n=64) | 7/9 (77.8%) | 4/13 (30.8%) |
| Study 98-0-049 | ||
| Placebo (n=157) | 7/11 (63.6%) | 5/15 (33.3%) |
| 2 mg (n=154) | 4/8 (50%) | 16/30 (53.3%) |
| 3 mg (n=153) | 7/9 (77.8%) | 20/44 (45.5%) |
Patient base: Full analysis set; all patients who received at least one dose of the study drug in study 98-0-051.
†† Percent increase from baseline during treatment. A patient could have been represented in both percentage increase groups if their creatinine increased, returned to baseline levels, and subsequently increased into the other percentage increase group.
† All de novo patients for study 98-0-051, all patients from study FK506RA-001, and all placebo rollover patients from study 98-0-049.
‡ All 2 mg tacrolimus rollover patients from study 98-0-049.
* All 3 mg tacrolimus rollover patients from study 98-0-049.
8.3. Less Common Clinical Trial Adverse Reactions
The following adverse events were reported in either liver, kidney, and/or heart transplant recipients who were treated with tacrolimus in clinical trials.
Body as a Whole: abdomen enlarged, abscess, accidental injury, allergic reaction, back pain, cellulitis, chills, fall, feeling abnormal, flu syndrome, generalized edema, hernia, mobility decreased, peritonitis, photosensitivity reaction, sepsis, temperature intolerance, ulcer, pain;
Cardiovascular: abnormal ECG, angina pectoris, arrhythmia, atrial fibrillation, atrial flutter, bradycardia, cardiac fibrillation, cardiopulmonary failure, cardiovascular disorder, chest pain, congestive heart failure, deep thrombophlebitis, echocardiogram abnormal, electrocardiogram QRS complex abnormal, electrocardiogram ST segment abnormal, heart rate decreased, heart failure, hemorrhage, hypotension, postural hypotension, peripheral vascular disorder, phlebitis, syncope, tachycardia, thrombosis, vasodilatation;
Endocrine System: (see 7. Warnings and Precautions) diabetes mellitus, Cushing’s Syndrome;
Gastrointestinal: anorexia, cholangitis, cholestatic jaundice, dyspepsia, duodenitis, dysphagia, esophagitis, flatulence, gastritis, gastrointestinal hemorrhage, gastroesophagitis, GGT increase, GI disorder, GI perforation, granulomatous liver disease, hepatitis, ileus, increased appetite, jaundice, liver damage, liver function test abnormal, esophagitis ulcerative, oral moniliasis, pancreatic pseudocyst, rectal disorder, stomatitis;
Hemic/Lymphatic: coagulation disorder, ecchymosis, febrile neutropenia, hematocrit increased, hemoglobin abnormal, hypochromic anemia, leukopenia, prothrombin decreased, leukocytosis, polycythemia, serum iron decreased, thrombocytopenia;
Metabolic/Nutritional: acidosis, alkaline phosphatase increased, alkalosis, AST (SGOT) increased, ALT (SGPT) increased, bicarbonate decreased, bilirubinemia, BUN increased, dehydration, edema, GGT increased, gout, healing abnormal, hypercalcemia, hypercholesterolemia, hyperlipemia, hypertriglyceridemia, hyperphosphatemia, hyperuricemia, hypocalcemia, hypervolemia, hypoglycemia, hypokalemia, hypophosphatemia, hyponatremia, hypoproteinemia, lactic dehydrogenase increase, weight gain;
Musculoskeletal: arthralgia, muscle spasms, generalized spasm, joint disorder, leg cramps, myalgia, myasthenia, osteoporosis, pain in extremity including Calcineurin-Inhibitor Induced Pain Syndrome (CIPS);
Nervous System: (see 7. Warnings and Precautions) abnormal dreams, agitation, amnesia, anxiety, confusion, crying, convulsion, depression, dizziness, elevated mood, emotional lability, encephalopathy, hemorrhagic stroke, hallucinations, hypertonia, incoordination, monoparesis, myoclonus, nerve compression, nervousness, neuralgia, neuropathy, paralysis flaccid, paresthesia, psychomotor skills impaired, psychosis, quadriparesis, somnolence, thinking abnormal, vertigo, writing impaired;
Respiratory System: asthma, bronchitis, cough increased, emphysema, hiccups, lung disorder, lung function decreased, pharyngitis, pneumothorax, pneumonia, pulmonary edema, respiratory disorder, rhinitis, sinusitis, voice alteration;
Skin & Appendages: acne, alopecia, exfoliative dermatitis, fungal dermatitis, herpes simplex, herpes zoster, hirsutism, pruritus, rash, neoplasm skin benign, skin discolouration, skin disorder, skin ulcer, sweating;
Special Senses: abnormal vision, amblyopia, ear pain, otitis media, tinnitus;
Urogenital: (see 7. Warnings and Precautions) acute kidney failure, albuminuria, BK nephropathy, bladder spasms, cystitis, dysuria, hematuria, hydronephrosis, kidney failure, kidney tubular necrosis, nocturia, oliguria, pyuria, toxic nephropathy, urge incontinence, urinary frequency, urinary tract infection, urinary incontinence, urinary retention, vaginitis;
The following nervous system adverse events were also reported at a frequency (< 3%): acute brain syndrome (0.2%), coma (2.1%), delirium (1.2%), dysarthria (0.4%), dystonia (0.4%), encephalopathy (2.5%), flaccid paralysis (0.4%), hemiplegia (0.8%), nystagmus (0.8%), paralysis (0.4%) and stupor (0.2%).
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Refer to 7. Warnings and Precautions (Hepatic, Renal, and Monitoring and Laboratory Tests).
8.5. Post-Market Adverse Reactions
The following adverse events have been reported from worldwide marketing experience with tacrolimus. Because these events are reported voluntarily from a population of uncertain size, are associated with concomitant diseases and multiple drug therapies and surgical procedures, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Decisions to include these events in labeling are typically based on one or more of the following factors: (1) seriousness of the event, (2) frequency of the reporting, or (3) strength of causal connection to the drug:
Cardiac Disorders: cardiac arrhythmia, cardiac arrest, congestive cardiomyopathy, electrocardiogram T wave abnormal, flushing, myocardial infarction, myocardial ischemia, QT prolongation with or without Torsades de pointes, venous thrombosis deep limb, ventricular extrasystoles, ventricular fibrillation;
Ear and Labyrinth Disorders: Hearing loss including deafness;
Endocrine Disorders: Hypothyroidism;
Gastrointestinal Disorders: colitis, enterocolitis, gastrointestinal obstruction, gastrooesophageal reflux disease, hepatocellular injury, impaired gastric emptying, liver fatty, Mikulicz’s syndrome, mouth ulceration, pancreatitis hemorrhagic, pancreatitis necrotizing, stomach ulcer;
Hepatobiliary Disorders: bile duct stenosis, cholestasis of pregnancy, hepatic cytolysis, hepatic necrosis, hepatotoxicity, venoocclusive liver disease;
Blood and Lymphatic System Disorders: agranulocytosis, disseminated intravascular coagulation, eosinophilia, febrile neutropenia, hemolytic anemia, hemolytic-uremic syndrome, neutropenia, pancytopenia, pure red cell aplasia, thrombocytopenic purpura, thrombotic thrombocytopenic purpura, thrombotic microangiopathy;
Infections and Infestations: eczema infected, Escherichia;
Investigations: blood urea increased, drug level below therapeutic, drug level fluctuating, immunosuppressant drug level decreased, platelet count increased, transaminases increased, weight decreased;
Injury, Poisoning and Procedural Complications: drug dispensing error, drug prescribing error, maternal exposure during pregnancy, medication error, primary graft dysfunction;
Metabolism and Nutritional Disorder: amylase increased, hyperammonaemia, ketoacidosis;
Musculoskeletal and Connective Tissue Disorders: immunoglobulin G4 related sclerosing disease, muscular weakness;
General Disorders and Administration Site Conditions: disease recurrence, drug effect delayed, drug effect increased, drug ineffective, drug interaction, drug intolerance, fatigue, feeling of body temperature change, feeling jittery, multi-organ failure, thirst;
Neoplasms benign, malignant and unspecified (including cysts and polyps): breast cancer, haematological malignancy, hepatic neoplasm malignant, Kaposi’s sarcoma, lung neoplasm malignant, pharyngeal cancer stage unspecified;
Nervous system Disorders: aphasia, balance disorder, brachial plexopathy, carpal tunnel syndrome, cerebral infarction, cerebrovascular accident, hemiparesis, incoherent, leukoencephalopathy, mutism, neurotoxicity, paraesthesia, peripheral nerve lesion, posterior reversible encephalopathy syndrome (PRES), progressive multifocal leukoencephalopathy (PML), quadriplegia, speech disorder, polyneuropathy, neuropathy peripheral, peripheral sensory neuropathy, mononeuropathy multiplex;
Psychiatric Disorders: intentional drug misuse, mental disorder;
Respiratory, Thoracic and Mediastinal Disorders: acute respiratory distress syndrome, interstitial lung disease (predominantly in rheumatoid arthritis), lung infiltration, respiratory distress, respiratory failure;
Skin and Subcutaneous Tissue Disorders: dermatosis, Stevens-Johnson syndrome, toxic epidermal necrolysis;
Eye Disorders: blindness, blindness cortical, diplopia, eyelid edema, optic neuropathy, photophobia;
Renal and Urinary Disorders: acute renal failure, cystitis hemorrhagic, glycosuria, micturition disorder, renal failure chronic;
Vascular Disorders: flushing, hot flush;
There have been rare spontaneous reports of myocardial hypertrophy associated with clinically manifested ventricular dysfunction in patients receiving tacrolimus therapy (see 7. Warnings and Precautions).
9. Drug Interactions
9.2. Drug Interactions Overview
Tacrolimus is extensively metabolized by the mixed-function oxidase system, primarily the cytochrome P450 system (CYP3A). Tacrolimus dose reductions and prolongation of dosing interval may be required in order to maintain similar tacrolimus exposure when co-administered with strong CYP3A4 inhibitor. Drugs known to induce these enzyme systems may result in an increased metabolism of tacrolimus or decreased bioavailability as indicated by decreased whole blood or plasma concentrations, thereby potentially requiring dose increases in order to maintain similar tacrolimus exposure when co-administered with strong CYP3A4 inducers (Refer to Table 9). Close monitoring of tacrolimus blood levels, renal function and other side effects (including ECG monitoring for QT prolongation) is strongly recommended when administered with strong CYP3A4 inhibitors (see 4. Dosage and Administration, 4.2. Recommended Dose and Dosage Adjustment, and 7. Warnings and Precautions, General).
9.3. Drug-Behaviour Interactions
As with other immunosuppressive agents, owing to the potential risk of malignant skin changes, exposure to sunlight and ultraviolet (UV) light should be limited by wearing protective clothing and using sunscreen with a high protection factor.
9.4. Drug-Drug Interactions
Drug Interactions Potentially Affecting Renal Function
Due to the potential for additive or synergistic impairment of renal function, care should be taken when administering tacrolimus with drugs that may be associated with renal dysfunction. These include, and are not limited to, aminoglycosides, amphotericin B, ganciclovir, acyclovir and cisplatin. NSAIDs may interact with tacrolimus causing deteriorations in blood pressure (BP) control and serum creatinine levels. The half-life of cyclosporine has been shown to increase when tacrolimus is given simultaneously. Initial clinical experience with tacrolimus and cyclosporine resulted in additive/synergistic nephrotoxicity when both agents were co-administered. For these reasons, the combined administration of cyclosporine and tacrolimus is not recommended and care should be taken when administering tacrolimus to patients who have previously received cyclosporine. Patients switched from cyclosporine to tacrolimus should receive the first tacrolimus dose no sooner than 24 hours after the last cyclosporine dose. Dosing may be further delayed in the presence of elevated cyclosporine levels.
Drug Interactions Potentially Affecting Tacrolimus Blood Concentrations
Since tacrolimus is metabolized mainly by the cytochrome P450 3A enzyme systems, substances known to inhibit these enzymes may decrease the metabolism or increase bioavailability of tacrolimus with resultant increases in whole blood or plasma levels. Drugs known to induce these enzyme systems may result in an increased metabolism of tacrolimus or decreased bioavailability as indicated by decreased whole blood or plasma levels.
Rapid increase in tacrolimus level may occur when co-administered with CYP3A4 inhibitors. Early, within the first few days of co-administration, and frequent continued monitoring of tacrolimus blood levels, as well as monitoring for renal function, for QT prolongation with ECG, and for other side effects is strongly recommended.
Monitoring of blood levels and appropriate dosage adjustments in transplant patients are essential when such drugs (Table 9) are used concomitantly with tacrolimus.
Table 9: Established or Potential Drug-Drug Interactions
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
|---|---|---|---|
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
Concomitant Drug Class: Drug Name | Reference | Effect on Concentrat ion of tacrolimus | Comment |
Antacid: magnesium-aluminium-hydroxide | CT | ↑ Tacrolimus | In a single-dose crossover study in healthy volunteers, co-administration of tacrolimus and magnesium-aluminium-hydroxide resulted in a 21% increase in the mean tacrolimus AUC and a 10% decrease in the mean tacrolimus Cmax relative to tacrolimus administration alone. |
Anti-Arrhythmic Agent: amiodarone† | T | ↑ Tacrolimus | The concomitant use of tacrolimus with amiodarone may lead to increased levels of tacrolimus and/or a potential pharmacodynamic interaction based on displacement of amiodarone from its plasma protein binding site. †When co-administered with amiodarone dose, adjustment may be required in most patients |
Azole antifungals: ketoconazole† | CT | ↑ Tacrolimus | In a study of 24 healthy male volunteers, co-administration of two 2 mg tacrolimus doses with ketoconazole (400 mg/day) increased the mean AUCinf and Cmax of tacrolimus by 723% and 250%, respectively. In a study of 6 normal volunteers, a significant increase in tacrolimus oral bioavailability (14 ± 5% vs 30 ± 8%) was observed with concomitant administration of ketoconazole (200 mg), a strong CYP3A4 and P-glycoprotein inhibitor. The apparent clearance of oral tacrolimus during ketoconazole administration was significantly decreased compared to tacrolimus alone (0.430 + 0.129 L/hr/kg vs. 0.148 + 0.043 L/hr/kg). Overall, clearance of IV tacrolimus was not significantly changed by ketoconazole co-administration, although it was highly variable between patients. †When co-administered with ketoconazole, a dose adjustment of tacrolimus is required in most patients. |
Azole antifungals, cont’d: clotrimazole fluconazole† itraconazole† voriconazole† | T | ↑ Tacrolimus | The concomitant use of tacrolimus with azole antifungals that are strong or moderate CYP3A4 and P-glycoprotein inhibitors (e.g., itraconazole, fluconazole, voriconazole) might lead to an increased tacrolimus concentration. †When co-administered with fluconazole, itraconazole and voriconazole, a dose |
| adjustment of tacrolimus is required in most patients. | |||
Calcium channel blockers: diltiazem nicardipine nifedipine verapamil | T | ↑ Tacrolimus | Co-administration of substrates and/or inhibitors of CYP3A4 and P-glycoprotein with tacrolimus might increase blood concentrations of tacrolimus. |
GI Prokinetic Agents: cisapride* metoclopramide | T | ↑ Tacrolimus | Co-administration of tacrolimus with substrates of CYP3A4 might increase blood concentrations of tacrolimus. |
Macrolide antibiotics: erythromycin† clarithromycin‡ troleandomycin | T | ↑ Tacrolimus | Co-administration of tacrolimus with substrates and/or inhibitors of CYP3A4 and P-glycoprotein might increase blood concentrations of tacrolimus. ‡ Cases have been reported in which a sharp rise in tacrolimus levels occurred very rapidly, as early as within 1-3 days after co-administration with clarithromycin despite an immediate reduction of tacrolimus dose. Early, within the first few days of co-administration, and frequent continued monitoring of tacrolimus whole blood trough levels within 1-3 days is strongly recommended when co-administered with strong CYP3A4 inhibitors. †When co-administered with erythromycin, a dose adjustment of tacrolimus is required in most patients. |
Proton pump inhibitor: lansoprazole omeprazole | T | ↑ Tacrolimus | Lansoprazole and omeprazole (CYP2C19 and CYP3A4 substrate, inhibitor) may potentially inhibit CYP3A4-mediated metabolism of tacrolimus and thereby substantially increase tacrolimus whole blood concentrations, |
| especially in transplant patients who are intermediate or poor CYP2C19 metabolizers, as compared to those patients who are efficient CYP2C19 metabolizers. | |||
Other drugs: bromocriptine cimetidine chloramphenicol cyclosporine danazol ethinyl estradiol methylprednisolone nefazodone | T | ↑ Tacrolimus | Co-administration of tacrolimus with substrates and/or inhibitors of CYP3A4 and P-glycoprotein might increase blood concentrations of tacrolimus. |
Protease inhibitors: boceprevir nelfinavir ritonavir saquinavir telaprevir | CT | ↑ Tacrolimus | Interaction studies with drugs used in HIV/HCV therapy have not been conducted. However, care should be exercised when drugs that are metabolized by CYP3A4 (for example, but not limited to boceprevir, nelfinavir, ritonavir, saquinavir, telaprevir) are administered concomitantly with tacrolimus. In a single dose study in 9 healthy volunteers, co-administration of tacrolimus (0.5 mg single dose) with telaprevir (750 mg TID for 13 days) increased tacrolimus dose-normalized Cmax by 9.3-fold and AUC by 70-fold. In a single dose study in 12 subjects, co-administration of tacrolimus (0.5 mg single dose) with boceprevir (800 mg three times daily for 11 days) increased tacrolimus Cmax by 9.9-fold and AUC by 17-fold compared to tacrolimus alone. Based on a clinical study of 5 liver transplant recipients, co-administration of tacrolimus (administration as tacrolimus [immediate-release formulation]) with nelfinavir increased |
blood concentrations of tacrolimus significantly and, as a result, a reduction in the tacrolimus dose by an average of 16-fold was needed to maintain mean trough tacrolimus blood concentrations of 9.7 ng/mL. Thus, frequent monitoring of tacrolimus blood concentrations and appropriate dosage adjustments are essential when used concomitantly with protease inhibitors. | |||
Cytomegalovirus (CMV) antivirals: letermovir | CT | ↑ Tacrolimus | Co-administration of tacrolimus with letermovir may result in clinically relevant increases in the plasma concentrations of tacrolimus. Monitor blood concentrations and if needed make appropriate dosage adjustments when letermovir is used concomitantly with tacrolimus. |
Anticonvulsants: carbamazepine phenobarbital phenytoin† | T | ↓ Tacrolimus | Co-administration of tacrolimus with inducers of CYP3A4 and P-glycoprotein might decrease blood concentrations of tacrolimus. †When co-administered with phenytoin, a dose adjustment of tacrolimus is required in most patients. |
Anti-Infectives: rifampicin† | CT | ↓ Tacrolimus | In a study of 28 healthy male volunteers, co-administration of two 5 mg tacrolimus doses with rifampicin (600 mg/day) decreased mean AUCinf and Cmax of tacrolimus by 62% and 24%, respectively. In a study of 6 normal volunteers, a significant decrease in tacrolimus oral bioavailability (14 ± 6% vs 7 ± 3%) was observed with concomitant administration of rifampicin (600 mg), a strong CYP3A4 and P-glycoprotein inducer. In addition, there was a significant increase in tacrolimus clearance (0.036 ± 0.008 L/hr/kg vs. 0.053 ± 0.010 L/hr/kg) with concomitant rifampicin administration. In a study of 9 normal volunteers, concomitantly |
administered 10 mL doses of aluminum hydroxide or milk of magnesia antacids did not affect the rate and extent of absorption of orally administered tacrolimus, as indicated by Cmax, Tmax and AUC0-t. †When co-administered with rifampicin, a dose adjustment of tacrolimus is required in most patients. | |||
Anti-infectives, cont’d: rifabutin | T | ↓ Tacrolimus | Co-administration of tacrolimus with inducers of CYP3A4 and P-glycoprotein might decrease blood concentrations of tacrolimus. |
Anti-infectives, cont’d: caspofungin | T | ↓ Tacrolimus | Caspofungin reduced the blood AUC0-12 of tacrolimus by approximately 20%, peak blood concentration (Cmax) by 16%, and 12-hour blood concentration (C12hr) by 26% in healthy adult subjects when tacrolimus (2 doses of 0.1 mg/kg 12 hours apart) was administered on the 10th day of CANCIDAS 70 mg daily, as compared to results from a control period in which tacrolimus was administered alone. |
Calcineurin inhibitor: sirolimus | CT | ↓ Tacrolimus | Following 14 days co-administration of tacrolimus and sirolimus (2 mg/day or 5 mg/day; a substrate for both CYP3A4 and P-glycoprotein) in stable renal transplant patients, tacrolimus AUC and Cmin decreased approximately 30% relative to tacrolimus alone. Mean tacrolimus AUC0-12 and Cmin following co-administration of 1 mg/day of sirolimus decreased approximately 3% and 11%, respectively. The safety and efficacy of the use of tacrolimus with sirolimus has not been established. |
Direct-acting antiviral (DAA): Sofosbuvir | T | ↓ or ↑ Tacrolimus | The pharmacokinetics of tacrolimus may be impacted by changes in liver function during DAA therapy, related to clearance of HCV virus. Impact on tacrolimus concentration may vary depending on the combination of DAA drugs used. A close monitoring and potential |
| dose adjustment of tacrolimus is warranted to ensure continued efficacy and safety. | |||
Herbal preparation: St. John’s Wort | T | ↓ Tacrolimus | St. John’s Wort (Hypericum perforatum) induces CYP3A4 and P-glycoprotein. Since tacrolimus is a substrate for CYP3A4, there is the potential that the use of St. John’s Wort in patients receiving tacrolimus could result in reduced tacrolimus levels. |
| Schisandra sphenanthera extracts | T | ↑ Tacrolimus | Co-administration of tacrolimus with substrates and/or inhibitors of CYP3A4 and P-glycoprotein might increase blood concentrations of tacrolimus. |
| Cannabidiol | T | ↑ Tacrolimus | Co-administration of tacrolimus with cannabidiol might increase blood concentrations of tacrolimus. Monitor tacrolimus whole blood trough concentrations and adjust the Sandoz Tacrolimus dose if needed. |
* No longer marketed in Canada CT = Clinical Trial T = Theoretical
Lack of Drug Interaction with Tacrolimus
At a given mycophenolate mofetil (MMF) dose, mycophenolic acid (MPA) exposure is higher with tacrolimus co-administration than with cyclosporine co-administration due to the inhibitory action of cyclosporine on biliary excretion of MPA-glucuronide by MRP-2 and the resulting reduction in enterohepatic recirculation of MPA. As a result, exposure to MPA when mycophenolate mofetil is given in combination with cyclosporine is approximately 30-40% lower than that observed when given alone or with tacrolimus. No effect on enterohepatic MPA-glucuronide recirculation is exerted by tacrolimus; thus, clinicians should be aware that there is a potential for increased MPA exposure after crossover from cyclosporine to tacrolimus in patients concomitantly receiving MMF or mycophenolate sodium (MPS). Conversely, there is a potential for decreased MPA exposure after crossover from tacrolimus to cyclosporine in patients concomitantly receiving MMF or MPS. Therapeutic drug monitoring of MPA is recommended.
Tacrolimus and Vaccinations
Immunosuppressants may affect vaccination. Therefore, during treatment with tacrolimus, vaccination may be less effective. The use of live vaccines should be avoided; live vaccines may include, but are not limited to: measles, mumps, rubella, oral polio, BCG, yellow fever and TY 21a typhoid.
9.5. Drug-Food Interactions
Grapefruit juice inhibits P450 3A-mediated metabolism and should be avoided.
9.6. Drug-Herb Interactions
St. John’s Wort (Hypericum perforatum) induces CYP3A4 and P-glycoprotein. Since tacrolimus is a substrate for CYP3A4, there is the potential that the use of St. John’s Wort in patients receiving tacrolimus immediate-release capsule could result in reduced tacrolimus levels.
Schisandra sphenanthera extracts inhibit CYP3A4 and P-glycoprotein and may increase blood concentrations of tacrolimus.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Tacrolimus, the active ingredient in Sandoz Tacrolimus, is a macrolide immunosuppressant produced by Streptomyces tsukubaensis.
Tacrolimus prolongs the survival of the host and transplanted graft in animal transplant models of liver, kidney, heart, bone marrow, small bowel and pancreas, lung and trachea, skin, cornea and limb.
Tacrolimus has been demonstrated to suppress some humoral immunity and, to a greater extent, cell-mediated reactions such as allograft rejection, delayed type hypersensitivity, Freund's adjuvant arthritis, experimental allergic encephalomyelitis and graft-versus-host disease in several animal species.
Tacrolimus inhibits T-lymphocyte activation, although the exact mechanism of action is not known. The minimum inhibitory tissue culture level of tacrolimus that prevents antigen stimulation of T-lymphocytes is 0.1 nM - 0.3 nM. Experimental evidence suggests that tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin and calcineurin is then formed and the phosphatase activity of calcineurin inhibited. This effect may prevent the generation of nuclear factor of activated T-cells (NF-AT), a nuclear component thought to initiate the gene transcription for the formation of lymphokines (interleukin-2, gamma interferon). The net result is the inhibition of T-lymphocyte activation (i.e., immunosuppression).
10.2. Pharmacodynamics
See 10. Clinical Pharmacology, 10.1. Mechanism of Action.
10.3. Pharmacokinetics
Tacrolimus activity is primarily due to the parent drug. After oral administration, absorption of tacrolimus into the systemic circulation from the gastrointestinal tract is incomplete and can be variable. Elimination of tacrolimus is via hepatic metabolism with a mean terminal elimination half-life of 18.8 hours in kidney transplant patients, 11.7 hours in liver transplant patients, 23.6 hours in heart transplant patients receiving a single intravenous dose of tacrolimus and 34.2 hours in healthy volunteers following intravenous administration. In rheumatoid arthritis patients, the administration of a single intravenous and oral dose of tacrolimus produced a mean terminal elimination half-life of 34.9 and 35.2 hrs respectively.
In transplant patients, the intersubject variability in tacrolimus pharmacokinetics has resulted in the need for the dosing regimen to be individualized. Dosing individualization can be achieved by therapeutic drug monitoring of tacrolimus blood concentrations and evaluation of clinical status (see 4. Dosage and Administration). Pharmacokinetic data indicate that whole blood concentrations rather than plasma concentrations serve as the more appropriate sampling compartment to describe tacrolimus pharmacokinetics.
Absorption
Absorption of tacrolimus from the gastrointestinal tract after oral administration is incomplete and can be variable. Mean (±S.D.) pharmacokinetic parameters of tacrolimus in whole blood after oral administration to volunteers in two studies are presented in the following table.
Table 10: Mean (±S.D.) Pharmacokinetic Parameters of Tacrolimus in Whole Blood after Oral Administration
| Parameter | Bioequivalence Study | Pharmacokinetic Study | |
|---|---|---|---|
| Age | 19-53 yrs | 19-50 yrs | |
| Number | 62 | 59 | 16 |
| Dose | 5 x 1 mg single dose | 1 x 5 mg single dose | 5 x 1 mg single dose |
| Absolute Bioavailability (%) | --- | --- | 17.8 ± 5.0 |
| Cmax (ng/mL) | 25.2 ± 9.7 | 26.5 ± 10.8 | 29.7 ± 7.2 |
| Tmax (hr) | 1.2 ± 0.4 | 1.4 ± 0.6 | 1.6 ± 0.7 |
| AUC 0-t (ng•hr/mL) | 196 ± 93† | 209 ± 97† | 243 ± 73†† |
† AUC (0-72), †† AUC (0-120)
The 1 mg and 5 mg dose strengths of tacrolimus capsules are bioequivalent as indicated in the table above.
Bioequivalence Study 0.5 mg Capsule
An open-label, four period, four sequence, randomized crossover study was done to determine the bioequivalence of the 0.5 mg tacrolimus capsule to the 1 mg tacrolimus capsule. In two periods of the study, a single dose of 6 x 0.5 mg capsules were consumed by healthy volunteers. In the two other periods of the study, 3 x 1 mg capsules were consumed in a single dose. The pharmaceutical parameters derived from this bioequivalence study are outlined in the table below.
Table 11: Bioequivalence of the 0.5 mg Tacrolimus Capsule to the 1 mg Tacrolimus Capsule in Healthy Volunteers: From Measured and Log Transformed Data, Uncorrected for Potency, Geometric Mean, Arithmetic Mean (CV %)
| Parameter | Test (6 X 0.5 mg capsules) | Reference (3 x 1 mg capsules) | % Ratio of Geometric Means | ||
|---|---|---|---|---|---|
| A1 | A2 | B1 | B2 | ||
AUCT (ng•h/mL) | 140 ± 52.4 | 122 ± 40.1 | 133 ± 53.9 | 125 ± 46.5 | 102.6 |
AUCI (ng•h/mL) | 168 ± 66.3 | 148 ± 50.4 | 160 ± 70.9 | 152 ± 62.1 | 102.9 |
Cmax (ng/mL) | 20.3 ± 6.94 | 18.7 ± 6.55 | 19.0 ± 6.91 | 18.7 ± 6.43 | 103.4 |
| Tmax * (h) | 1.4 ± 0.61 | 1.3 ± 0.44 | 1.4 ± 0.51 | 1.5 ± 0.50 | 92.5 |
| T1/2 * (h) | 34.4 ± 9.12 | 35.4 ± 11.1 | 32.6 ± 7.86 | 35.8 ± 9.10 | 102.2 |
* Expressed as arithmetic mean (CV%) only. A1 and A2 refer to data from two different study periods for test drug. B1 and B2 refer to data from two different study periods for reference drug.
Table 12: Bioequivalence of the 0.5 mg tacrolimus capsule to the 1 mg tacrolimus capsule in healthy volunteers: Corrected for Potency, Geometric Mean
| Parameter | Test | Reference | % Ratio of Geometric Means |
|---|---|---|---|
| AUCT (ng•h/mL) | 121.1a | 116.3a | 104.2 |
| AUCI (ng•h/mL) | 145.5a | 139.2a | 104.5 |
| Cmax (ng/mL) | 18.1a | 17.3a | 105.0 |
Potency corrections made using potencies of 100.8% for the 0.5 mg capsule and 102.3% for the 1.0 mg capsule.
a Values calculated using LS Means of log-transformed data.
In 26 kidney transplant patients, peak concentrations (Cmax) were achieved at approximately 1-3 hours. The absorption half-life of tacrolimus in 17 liver transplant patients averaged 0.6 hours (S.D. 1.0 hour) with peak concentrations (Cmax) in blood and plasma being achieved at approximately 1.5-3.5 hours. In rheumatoid arthritis patients, peak concentrations (Cmax) were achieved within 1.3 hours. Mean (± S.D.) pharmacokinetic parameters of tacrolimus in whole blood after initial dose in adult kidney and liver transplant patients and in rheumatoid arthritis patients are presented in the table below:
Table 13: Mean (±S.D.) Pharmacokinetic Parameters of Tacrolimus in Whole Blood after Initial Dose in Adult Transplant and Rheumatoid Arthritis Patients
| Population | N | Pharmacokinetic Parameters | |||
|---|---|---|---|---|---|
| Route (Dose) | Cmax (ng/mL) | Tmax (hr) | AUC (ng·hr/mL) | ||
| Kidney Transplant Patients | 26 | PO (0.2 mg/kg/day) | 19.2 ± 10.3 | 3.0 | 203§ ± 42 |
PO (0.3mg/kg/day) | 24.2 ± 15.8 | 1.5 | 288§ ± 93 | ||
| Liver Transplant Patients | 17 | PO (0.3 mg/kg/day) | 68.5 ± 30.0 | 2.3 ± 1.5 | 519§ ± 179 |
| Heart Transplant Patients | 11 | PO (0.075 mg/kg/day) | 24.9 ± 7.72 | 1.0 | 175†† ± 49.8 |
| Rheumatoid Arthritis Patients | 12 | PO (3 X 1 mg single dose) | 19.64 ± 6.32 | 1.3 ± 0.58 | 192.88 ± 86.42 |
PO: oral; § AUC0-inf; ††AUC0-12
The absolute bioavailability of tacrolimus is approximately 17% in kidney transplant patients, 22% in adult liver transplant patients, 34% in pediatric liver transplant patients, and approximately 25% in rheumatoid arthritis patients. In healthy volunteers, the absolute bioavailability of tacrolimus was found to be approximately 18% (previous table).
Food Effects: The rate and extent of tacrolimus absorption is greatest under fasted conditions.
The presence and composition of food decreased both the rate and extent of tacrolimus absorption when administered to healthy volunteers:
Table 14: Food Effects on the Rate and Extent of Tacrolimus Absorption in Healthy Volunteers
| Parameter | Fasted (n=15) | High Carbohydrate* (n=15) | High Fat** (n=15) |
|---|---|---|---|
| Cmax (ng/mL) | 25.6 ± 11.4 | 9.0 ± 3.8 | 5.9 ± 2.3 |
| Tmax (hr) | 1.4 ± 0.6 | 3.2 ± 1.1 | 6.5 ± 3.0 |
| AUC0-t (ng•hr/mL) | 233 ± 121† | 168 ± 59† | 147 ± 56† |
* 668 kcal (4% fat; 85% carbohydrate); ** 848 kcal (46% fat, 39% carbohydrate); † AUC0-96
The effect was most pronounced with the high-fat meal: mean area under the curve (AUC 0-96) and Cmax were decreased 37% and 77%, respectively; Tmax was lengthened 5-fold. The high-carbohydrate meal decreased AUC0-96 and Cmax by 28% and 65%, respectively.
The effect of food was also studied in 11 liver transplant patients. Tacrolimus was administered in the fasted state or 15 minutes after a breakfast of known fat content (34% of 400 total calories).
The results indicate that the presence of food reduces the absorption of tacrolimus in these patients (decrease in AUC and Cmax and increase in Tmax). The relative oral bioavailability (whole blood) was reduced by 27.0 (±18.2) % compared to administration in the fasting state.
In healthy volunteers, the time of the meal also affected tacrolimus bioavailability. Relative to the fasted state, there was little effect on tacrolimus bioavailability when administered one hour prior to a high-fat breakfast, whereas bioavailability (both extent and rate of absorption) was greatly reduced when the drug was administered immediately or 1.5 hours after the meal. When given immediately following the meal, Cmax was reduced 71%, AUC0-96 was reduced by 39%, and Tmax was delayed 1.6 hours relative to the fasting condition. When administered 1.5 hours following the meal, Cmax was reduced 63%, AUC0-96 was reduced 39%, and Tmax was delayed 1.4 hours relative to the fasted condition.
In fasted healthy volunteers given a single dose, the absorption of tacrolimus was proportional to dose; see table below.
Table 15: Absorption of Tacrolimus in Fasted Healthy Volunteers
| Parameter | Dose | ||
|---|---|---|---|
| Parameter | Dose | ||
3 mg n = 18 | 7 mg n = 18 | 10 mg n = 18 | |
3 mg n = 18 | 7 mg n = 18 | 10 mg n = 18 | |
| Cmax (ng/mL) | 14.5 ± 5.8 | 31.2 ± 10.1 | 45.1 ±15.0 |
| 14.5 ± 5.8* | 13.4 ± 4.3* | 13.5 ± 4.5* | |
| Tmax (hr) | 1.4 ± 0.4 | 1.4 ± 0.5 | 1.3 ± 0.4 |
| AUC 0-96 (ng•hr/mL) | 131 ± 77 | 303 ± 138 | 420 ± 166 |
| 131 ± 77* | 130 ± 59* | 126 ± 50* | |
* Adjusted to 3 mg dose
Distribution
The apparent volume of distribution (based on whole blood concentrations) of tacrolimus is approximately 1.41, 1.91, 0.85 and 2.37 L/kg in kidney transplant patients, healthy volunteers, adult liver transplant patients and adult rheumatoid arthritis patients, respectively (refer to table below).
Table 16: Volume of Distribution and Clearance in Transplant and Rheumatoid Arthritis Patients
| Parameter | Volunteers (n=8) | Kidney Transplant Patients (n=26) | Liver Transplant Patients (Adults, n=17) | Heart Transplant Patients (n=11) | Rheumatoid Arthritis Patients (Adults, n=12) |
|---|---|---|---|---|---|
| Mean IV Dose | 0.025 mg/kg/4 hr | 0.02 mg/kg/4 hr | 0.05 mg/kg/12hr | 0.01 mg/kg/day as a continuous infusion | 0.015 mg/kg/4hr |
| V (L/kg) | 1.91 ± 0.31 | 1.41 ± 0.66 | 0.85 ± 0.3 | NA | 2.37 ± 0.45 |
| Cl (L/hr/kg) | 0.040 ± 0.009 | 0.083 ± 0.050 | 0.053 ± 0.017 | 0.051±0.015 | 0.049 ± 0.014 |
NA: not available
The plasma protein binding of tacrolimus is approximately 99% and is independent of concentration over a range of 5 - 50 ng/mL. Tacrolimus is bound to proteins, mainly albumin and alpha-1-acid glycoprotein, and has a high level of association with erythrocytes. The distribution of tacrolimus between whole blood and plasma depends on several factors, such as hematocrit, temperature at the time of plasma separation, drug concentration, and plasma protein concentration. In a U.S. study, the ratio of whole blood concentration to plasma concentration ranged from 12 to 67 (mean 35).
In 18 kidney transplant patients, tacrolimus trough concentrations from 3 to 30 ng/mL measured at 10-12 hours post dose (Cmin) correlated well with the AUC0-12 (correlation coefficient 0.93). In 24 liver transplant patients over a concentration range of 10 to 60 ng/mL, the correlation coefficient was 0.94. In 25 heart transplant patients, the correlation coefficient was 0.89 after an oral dose of 0.075 or 0.15 mg/kg/day at steady-state.
Metabolism
Tacrolimus is extensively metabolized in the liver by the mixed-function oxidase systems, primarily the cytochrome P450-3A4 (CYP3A4) and the cytochrome P450-3A5 (CYP3A5) enzyme systems. A metabolic pathway leading to the formation of 8 possible metabolites has been proposed. Demethylation and hydroxylation were identified as the primary mechanisms of biotransformation in vitro. The major metabolite identified in incubations with human liver microsomes is 13-demethyl tacrolimus. In in vitro studies, a 31-demethyl metabolite has been reported to have the same activity as tacrolimus; the 13-demethyl, 15-demethyl and 15- and 31- double-demethylated metabolites were shown to retain an activity of less than 10%.
Elimination
The clearance of tacrolimus is 0.040, 0.083, 0.042 and 0.049 L/hr/kg in healthy volunteers, adult kidney transplant patients, adult liver transplant patients, and adult rheumatoid arthritis patients, respectively. In man, less than 1% of the dose administered is excreted unchanged in urine.
Human Studies
In vitro, several drugs have been shown to inhibit the metabolism of tacrolimus by human liver microsomes. Conversely, tacrolimus has been shown to inhibit the metabolism of other drugs (e.g., CyA). In vivo, the metabolism of tacrolimus is presumably by hepatic P4503A4. Therefore, there is a potential for a drug-drug interaction between tacrolimus and other drugs that are substrates for this P450 isozyme.
Five healthy volunteers received a single IV infusion of 0.03 mg/kg of tacrolimus. The mean (SD) pharmacokinetic parameters for whole blood concentrations were: half-life, 17.6 (4.6) h; volume of distribution, 0.63 (0.15) L/kg; and clearance, 0.032 (0.008) L/h/kg. The mean pharmacokinetic parameters for plasma concentrations were: half-life, 43.4 (14.7) h; volume of distribution, 16.9 (6.7) L/kg; and clearance, 0.43 (0.15) L/h/kg.
Table 17: Mean Pharmacokinetic Parameters for Tacrolimus Whole Blood Concentrations in Healthy Volunteers
| T½ (h) | Vd (L) | Vd (L/kg) | Cl (L/h) | Cl (L/h/kg) | |
|---|---|---|---|---|---|
| Blood | 17.6 | 47.6 | 0.63 | 2.4 | 0.032 |
| Plasma | 43.4 | 1303 | 16.9 | 33.6 | 0.43 |
The administration of tacrolimus did not result in clinically significant immunosuppression in the subjects. Four of the 5 subjects experienced decreases in creatinine clearance that returned to normal within 2-9 days post-dose. The average creatinine clearance decreased from 110 mL/min at baseline to 90 mL/min between 12-48 hours post-dose. There were no clinically significant changes observed during 24-hour electrocardiogram monitoring.
The following pharmacokinetic parameters were calculated following the first IV dose of FK506 in kidney transplant patients: Elimination half-life (T½), area under the concentration-time curve from 0 to 12 hours (AUC0-12), area under the concentration-time curve from 0 to infinity (AUC0-∞), total body clearance (Cl), and volume of distribution at steady-state (Vss).
Table 18: Mean Pharmacokinetic Parameters for Tacrolimus Whole Blood Concentrations following the Initial IV Dose of FK506 in Kidney Transplant Patients
T1/2 (h) | Cl (L/h/kg) | Vss (L/kg) | AUC0-12 (ng.h/mL) | AUC0-∞ (ng.h/mL) | |
|---|---|---|---|---|---|
| Blood | 8.04 ± 4.88 | 0.12 ± 0.05 | 1.0 ± 0.36 | 481.0 ± 129 | 755.0 ± 297 |
| Plasma | 6.86 ± 2.92 | 4.29 ± 2.1 | 29.2 ± 15.8 | 20.0 ± 19.5 | 25.3 ± 20.9 |
The following pharmacokinetic parameters were calculated following maintenance oral dosing with FK506 in kidney transplant patients: bioavailability (BA), time to maximum concentration (Tmax), maximum blood/plasma concentration (Cmax), plasma/blood concentration before dosing (C0h), and plasma/blood concentration 12 hours after dosing (C12h).
Table 19: Mean Pharmacokinetic Parameters for Tacrolimus Whole Blood Concentrations following the Maintenance Oral Dosing of FK506 in Kidney Transplant Patients
BA (%) | Tmax (h) | Cmax (ng/mL) | C0h (ng/mL) | C12h (ng/mL) | |
|---|---|---|---|---|---|
| Blood | 20.0 ± 17.8 | 4.2 ± 2.9 | 44.0 ± 4.2 | 15.0 ± 10 | 16.0 ± 12 |
| Plasma | 17.3 ± 12.0 | 3.1 ± 2.4 | 1.4 ± 1.7 | 0.4 ± 0.1 | 0.4 ± 0.2 |
There were great individual differences among the IV and oral pharmacokinetic parameters.
However, C0h and C12h in whole blood and plasma from each patient following oral dosing were almost identical. It was suggested that steady-state was obtained upon repeated dosing.
In a prospective, multicentre study, 37 kidney transplant patients received 0.075 mg/kg IV infused over 4 hours twice daily, and were converted to oral tacrolimus at a dose of 0.3 mg/kg/day in two divided doses when they were able to tolerate oral medication. The results of this study suggested that if the range of trough whole blood tacrolimus levels is maintained between 15 and 20 ng/mL, the incidence of adverse events is decreased. Maintaining optimal therapeutic levels may also decrease the incidence of rejection. Results suggested that tacrolimus is better monitored with whole blood than with plasma, and that patient’s trough tacrolimus levels in whole blood be maintained at 20 ng/mL for the initial 2 weeks following transplantation, then decreased to trough blood levels of 15 ng/mL for the next 12 weeks.
In an open-labelled study to evaluate the effect of hepatic dysfunction on the pharmacokinetics of tacrolimus, patients with and without liver impairment received 0.15 mg/kg IV tacrolimus over 1 to 2 hours and 0.15 mg/kg oral tacrolimus. The effect of T-tube clamping on the oral absorption of tacrolimus at 0.15 mg/kg was studied in 5 liver transplant patients, who had a duct-to-duct biliary reconstruction with a T-tube stent. In patients with moderate to severe hepatic dysfunction, the elimination half-life of tacrolimus was increased and the total body clearance was decreased, resulting in higher daily trough plasma concentrations. The bioavailability increased following oral administration of tacrolimus to hepatically impaired patients. Bile did not alter the absorption of tacrolimus. Dosage adjustments may be necessary for patients with severe hepatic impairment, but not for those patients with mild impairment.
The clearance of tacrolimus is independent of renal function; less than 1% is recovered unchanged in the urine. However, reducing the dose of tacrolimus may be necessary with deterioration of renal function in order to reduce the potential nephrotoxic effects of the drug.
Studies showed that as the dose of tacrolimus increased, a dose-proportional increase in AUC and Cmax resulted. However, a large interpatient variability was observed. Whole blood and plasma trough concentrations taken 10-12 hours after oral administration of tacrolimus (Cmin) correlated well with the AUC 0-12h r = 0.93-0.98, demonstrating that Cmin is an accurate indicator of overall patient exposure to drug.
Children ≤ 12 years of age required approximately twice the adult IV and oral doses to attain similar tacrolimus plasma trough concentrations following liver transplantation.
Tacrolimus concentrations measured by EIA have been shown to correlate well with those determined by HDLC-MS assay specific for the parent compound, (r = 0.86 - 0.93), indicating that EIA provides a reliable measure of tacrolimus concentrations.
Special populations and conditions
- Pediatrics
A study in liver transplantation has been conducted in sixteen pediatric patients (age range: 0.7 - 13.2 years). A mean terminal elimination half-life of 11.5 hours was determined following an intravenous dose of 0.037 mg/kg/day in twelve patients; the volume of distribution was 2.6 L/kg, whereas clearance was 0.135 L/hr/kg. In nine patients receiving capsule formulation, a mean Cmax of 48.4 ng/mL was attained at a mean Tmax of 2.7 hours following an oral dose of 0.152 mg/kg as tacrolimus capsules. The AUC (0-72hr) was 337 ng•hr/mL. The absolute bioavailability was 31%.
Whole blood trough concentrations from 31 pediatric patients (less than 12 years old) showed that pediatric patients need higher doses than adults to achieve similar tacrolimus trough concentrations, suggesting that the pharmacokinetic characteristics of tacrolimus are different in pediatric patients compared to adults (see 4. Dosage and Administration).
- Geriatrics
The pharmacokinetics of tacrolimus has not been established in the geriatric population.
- Sex
A formal study to evaluate the effect of gender on tacrolimus pharmacokinetics has not been conducted; however, there was no differences noted in dosing by gender in the kidney transplant trial. A retrospective comparison of pharmacokinetics in healthy volunteers, and in kidney and liver transplant patients, indicated no gender-based differences.
- Ethnic origin
A formal study to evaluate the pharmacokinetic disposition of tacrolimus in Black transplant patients has not been conducted; however, a retrospective comparison of Black and Caucasian kidney transplant patients indicated that Black patients required higher tacrolimus doses to attain similar trough concentrations (see 4. Dosage and Administration)
- Hepatic Insufficiency
Tacrolimus pharmacokinetics have been determined in six patients with mild hepatic dysfunction (mean Pugh score: 6.2) following single intravenous and oral administrations. The pharmacokinetic parameters obtained were as follows:
Table 20: Tacrolimus Pharmacokinetics in Patients with Mild Hepatic Impairment
Parameter (N = 6) | Dose and Route | |
|---|---|---|
| 7.7 mg P.O. | 1.3 mg IV | |
| Age Range (yrs) | 52-63 | |
| Absolute Bioavailability (%) | 22.3 ± 11.4 | - |
| Cmax (ng/mL) | 48.2 ± 17.9 | - |
| Tmax (hr) | 1.5 ± 0.6 | - |
| AUC 0-72 (ng•hr/mL) | 488 ± 320 | 367 ± 107 |
| V (L/kg) | 3.7 ± 4.7* | 3.1 ± 1.6 |
| Cl (L/hr/kg) | 0.034 ± 0.019* | 0.042 ± 0.020 |
| t1/2 (hr) | 66.1 ± 44.8 | 60.6 ± 43.8 |
* Corrected for bioavailability
The disposition of tacrolimus in patients with mild hepatic dysfunction was not substantially different from that in normal volunteers (see previous tables). In general, tacrolimus elimination half-life was longer and volume of distribution larger in patients with mild hepatic dysfunction compared to normal volunteers. The clearance in both populations was similar and since tacrolimus is extensively metabolized at multiple sites, patients with mild hepatic dysfunction may not require lower maintenance doses of tacrolimus than patients with normal hepatic function.
Tacrolimus pharmacokinetics were studied in 6 patients with severe hepatic dysfunction (mean Pugh score: > 10). The mean clearance was substantially lower in patients with severe hepatic dysfunction, irrespective of the route of administration.
Table 21: Tacrolimus Pharmacokinetics in Patients with Severe Hepatic Impairment
| Route, N | Dose | AUC ng•hr/mL (0-t) | T ½ (hr) | V (L/kg) | Cl (L/hr/kg) | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| IV, N=6 | 0.02 mg/kg/4hr IV (N=2) | 762 (t=120 hr) | 198 ± 158 Range: 81- 436 | - | - | ||||||
0.01 mg/kg/8hr IV (N=4) | 289 ± 117 (t=144 hr) | ||||||||||
| 3.9 ± 1.0 |
| 0.017 ± 0.013 |
| PO, N=5† | 8 mg PO (N=1) | 658 (t=120 hr) | 119 ± 35 Range: 85-178 | 3.1 ± 3.4 | 0.016 ± 0.011 | ||
|---|---|---|---|---|---|---|---|
5 mg PO (N=4) | 533 ± 156 (t=144 hr) | ||||||
4 mg PO (N=1) | - | ||||||
† 1 patient did not receive the PO dose.
- Renal Insufficiency
Tacrolimus pharmacokinetics following a single intravenous administration have been determined in 12 patients (7 not on dialysis and 5 on dialysis) prior to their kidney transplant. The pharmacokinetic parameters obtained are presented in the table below:
Table 22: Tacrolimus Pharmacokinetics in Patients with Renal Insufficiency
| Serum Creatinine (mg/dL) | 3.9 ± 1.6 (not on dialysis) 12.0 ± 2.4 (on dialysis) |
|---|---|
| Age range (yrs) | 25-65 |
| Route | IV |
| Dose (mg) | 1.17 ± 0.28 |
| AUC 0-60 (ng•hr/mL) | 393 ± 123 |
| AUC 0-inf (ng•hr/mL) | 499 ± 155 |
| V (L/kg) | 1.07 ± 0.20 |
| Cl (L/hr/kg) | 0.038 ± 0.014 |
| t1/2 (hr) | 26.3 ± 9.2 |
The disposition of tacrolimus in patients with renal dysfunction was not different from that in normal volunteers (see previous tables). The clearance was similar whereas volume of distribution was smaller and the mean terminal elimination half-life shorter than that of normal volunteers.
- 11. Storage, Stability, and Disposal
Sandoz Tacrolimus (tacrolimus immediate-release capsules, USP): Store and dispense at controlled room temperature, 15°C - 30°C. Protect from moisture.
12. Special Handling Instructions
Based on immunosuppressive effects of tacrolimus, inhalation or direct contact with skin or mucous membranes of powder contained in tacrolimus products should be avoided during preparation. If such contact occurs, wash the skin and eyes.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: tacrolimus
Chemical name: [3S-[3R*[E(1S*,3S*,4S*)],4S*,5R*,8S*,9E,12R*,14R*,15S*,16R*,18S*,
19S*,26aR*]]-5,6,8,11,12,13,14,15,16,17,18,19,24,25,26,26a-hexadecahydro-5,19-dihydroxy-3-[2-(4-hydroxy-3-methoxycyclohexyl)-1-methylethenyl]-14,16-dimethoxy-4,10,12,18-tetramethyl-8-(2-propenyl)-15,19-epoxy-3H-pyrido[2,1-c][1,4] oxaazacyclotricosine-1,7,20,21(4H,23H)-tetrone, monohydrate.
Molecular formula and molecular mass: C44H69NO12•H2O and 822.03 g/mol
Structural formula:
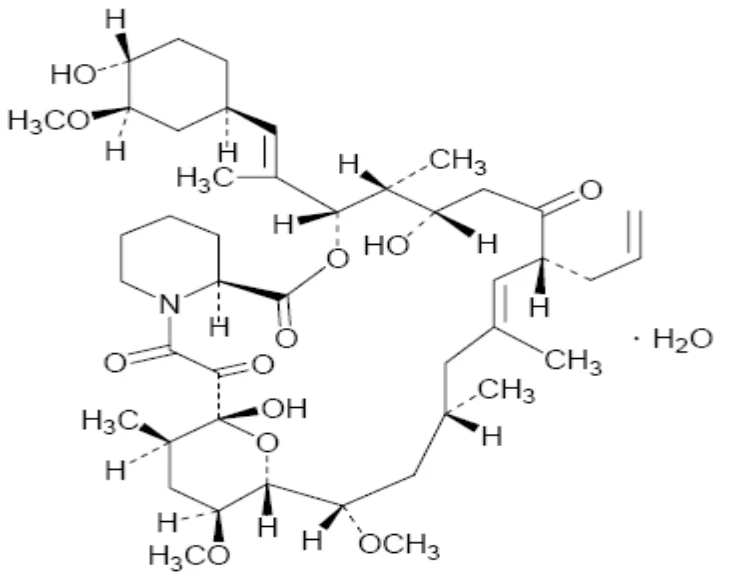
Physicochemical properties: Tacrolimus appears as white to almost white crystalline powder.
Solubility: It is practically insoluble in water, freely soluble in ethanol, and very soluble in methanol and chloroform.
Melting Point: 127 - 129°C by thermal analysis.
Partition Coefficient: > 1000 (in n-octanol/water).
14. Clinical Trials
14.1. Clinical Trials by Indication
Kidney Transplantation
Table 23: Summary of Patient Demographics for Tacrolimus Kidney Transplantation Trials
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (range) | Gender | Race (Caucasian/ Black/Other) |
|---|---|---|---|---|---|---|
93-0006 (U.S) | Randomized, multi-centre, open-label, comparative | 0.2 mg/kg per day tacrolimus BID orally (IV dose is 20% of oral dose), 1 year | N = 205 | 43.4 ± 13.1 (9-71 years) | M = 123 F = 82 | 114/56/35 |
Initial Dose: 10 mg/kg per day cyclosporine A BID orally (IV dose is 33% of oral dose), 1 year | N = 207 | 43.6 ± 12.4 (10-74 years) | M =129 F = 78 | 123/48/36 | ||
FG-02-02 (Europe) | Multicentre, open, parallel-group study, randomized | Initial dose 0.3 mg/kg per day BID to target whole blood trough concentrations of 10-20 ng/mL, oral, 1 year | N = 303 | 46.6 ± 13.5 (18-72 years) | M = 196 F = 107 | 300/1/2 |
| Initial dose 8.0 mg/kg per day to target blood level 100-300 ng/mL, oral, 1 year | N = 145 | 45.8 ± 12.5 (20-70 years) | M = 92 F = 53 | 143/0/2 |
Liver Transplantation
Table 24: Summary of Patient Demographics for tacrolimus Liver Transplantation Trials
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (range) | Gender | Race (Caucasian/ Black/Other) | ||||
|---|---|---|---|---|---|---|---|---|---|---|
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (range) | Gender | Race (Caucasian/ Black/Other) | ||||
| FPC-FK506-7 | Open-label, randomized, multicenter, | Tacrolimus: 0.075mg/kg then 0.15 mg/kg PO BID or 0.05 mg/kg IV BID, 360 days | N = 263 | 44.0 | M = 136 F = 127 | 208/13/42 | ||||
| active comparator, parallel study | CyA*: 1- 2 mg/kg IV BID, 5 mg/kg PO, 360 days | N = 266 | 44.0 | M = 140 F = 126 | 203/14/49 | |||||
| GHBA-157 | Randomized, multicenter, active comparator, open-label, parallel study | 0.075 mg/kg then 0.03 -0.05 IV BID, 360 days | N = 270 | 45.7 | M = 136 F = 134 | 260/2/8 | ||||
| CyA*: 1-15 mg/kg/day, 360days | N = 275 | 45.6 | M = 158 F = 117 | 260/2/13 | ||||||
| FPC-FK506-9 | Open-label, multicenter, rescue use of FK506 (tacrolimus) | 0.075 mg/kg then 0.15 mg/kg PO BID or 0.05 mg/kg IV BID, 360 days | N = 125 | 34.7 | M = 56 F = 69 | 79/18/28 | ||||
* CyA: Cyclosporine A
Heart Transplantation
Table 25: Summary of Patient Demographics for tacrolimus Heart Transplantation Trials
| Study # | Trial design | Dosage, route of administration and duration | Study Subjects (N) | Mean age (Range) | Gender | Race (Caucasian/ Black/ Other) | |||
|---|---|---|---|---|---|---|---|---|---|
| Study # | Trial design | Dosage, route of administration and duration | Study Subjects (N) | Mean age (Range) | Gender | Race (Caucasian/ Black/ Other) | |||
| Study # | Trial design | Dosage, route of administration and duration | Study Subjects (N) | Mean age (Range) | Gender | Race (Caucasian/ Black/ Other) | |||
| FG-506-05-02 | Open-label, randomized, parallel-group study | Antibody induction therapy; azathioprine, corticosteroids and tacrolimus. Tacrolimus initial oral dose, 0.075 mg/kg/day. At ≤ 3 months post-transplant, tacrolimus blood trough concentrations between 10 - 20 ng/mL. At > 3 months post-transplant, tacrolimus blood trough concentrations at 15ng/mL. | 157 | 50.8 ± 11.0 (18 - 65) | Female: 30 Male: 127 | 153/1/3 | |||
Antibody induction therapy; azathioprine, corticosteroids and cyclosporine. Cyclosporine microemulsion: Initial oral dose at 4-6 mg/kg/day. At ≤ 3months post-transplant, cyclosporine blood trough concentrations between 200-350 ng/mL. At > 3 months post-transplant, cyclosporine blood trough concentrations between 100-200 ng/mL thereafter. | 157 | 50.7 ± 9.9 (18 - 65) | Female: 28 Male: 129 | 151/4/2 | |||||
| 20-01-003 | Randomized, Prospective, Multi-center Comparison | Tacrolimus, MMF and steroid treatment therapy Tacrolimus: 2-4 mg/kg per day, in two divided oral doses, within 12 hours of transplant. Dosing was adjusted to achieve whole blood concentrations of 200-400 ng/mL in the first 3 months and 100 to 300 ng/mL thereafter. | 113 | 54.34 ± 10.9 (20 - 75) | M = 86 F = 21 | 95/9/3 | |||
Cyclosporine, MMF and Steroids Cyclosporine: 3 to 5 mg/kg per day, as two divided oral | 117 | 51.89 ± 11.5 (22 - 72) | M = 84 F = 31 | 91/20/4 | |||||
| doses, within 12 hours of transplant. Dosing was adjusted to achieve whole blood concentrations of 200-400 ng/mL in the first 3 months and 100 to 300 ng/mL thereafter. | |||||||||
Rheumatoid Arthritis
Table 26: Summary of Patient Demographics for tacrolimus Clinical Trials in Rheumatoid Arthritis
| Study # | Trial design | Dosage, route of administration and duration | Study Subjects (N) | Mean age (Range) | Gender | Race (Caucasian/ Black/ Other) |
|---|---|---|---|---|---|---|
| FK-506-RA-001 | Randomized, double-blind parallel group | Placebo, 1, 3 or 5 mg tacrolimus as a single daily oral dose for 24 weeks | N = 268 | 52.0 ± 10.4 | M = 59 F = 209 | 253/11/4 |
| 98-0-049 | Randomized, double-blind parallel group | Placebo, 2 mg tacrolimus, or 3 mg tacrolimus as a single daily dose for 6 months | N = 464 | 55.8±12.2 5 | M = 38 F = 119 | 421/25/18 |
| 98-0-051 | Open-label, Long-term safety study | 3 mg tacrolimus single daily oral dose for 12 months (roll-over from 98-0-049 in total patient received up to 18 months of treatment.) | N = 896 | 55.7 ± 11.84 | M = 242 F = 654 | 835/36/25 |
14.2. Study Results
Kidney Transplantation
The safety and efficacy of tacrolimus-based immunosuppression following kidney transplantation was assessed in two, Phase III randomized, multicentre, non-blinded, prospective studies. The active control groups were treated with cyclosporine-based immunosuppression. These studies were designed to evaluate whether the two regimens were therapeutically equivalent for one-year patient and graft survival. Based on the results from these two studies, the tacrolimus-based regimen was found to be therapeutically equivalent to the cyclosporine-based regimen.
In one trial, (Study 93-0006), 412 kidney transplant patients were enrolled at 19 clinical sites in the United States; 205 patients were randomized to tacrolimus-based immunosuppression and 207 patients were randomized to cyclosporine-based immunosuppression. All patients received prophylactic induction therapy consisting of an antilymphocyte antibody preparation, corticosteroids and azathioprine. Tacrolimus was initiated when renal function was stable as indicated by a serum creatinine ≤ 4 mg/dL (353.6 mc mol/L). Tacrolimus was initiated a median of 4 days after transplantation. Patients less than 6 years of age were excluded.
In the second trial, (Study FG-02-02), 448 kidney transplant patients were enrolled at 15 clinical sites in Europe; 303 patients were randomized to tacrolimus-based immunosuppression and 145 patients were randomized to cyclosporine-based immunosuppression. Tacrolimus was initiated within 24 hours of transplantation and was administered with corticosteroids and azathioprine. Patients less than 18 years of age were excluded.
One-year patient and graft survival in the tacrolimus-based treatment groups were equivalent to those in the cyclosporine-based treatment groups. The overall one-year patient survival (tacrolimus and cyclosporine combined) was 96.1% in the U.S. study and 94.2% in the European study. The overall one-year graft survival was 89.6% in the U.S. study and 83.7% in the European study.
The two large, randomized clinical trials demonstrated that significantly fewer tacrolimus-treated patients (approximately 16% fewer) experienced an episode of acute rejection during the one-year treatment period compared with cyclosporine-treated patients (p < 0.001).
Significantly fewer tacrolimus-treated patients crossed over to cyclosporine therapy due to adverse events and acute rejection episodes compared to cyclosporine-treated patients transferring to tacrolimus therapy (p = 0.007). The majority of patients who crossed over from the cyclosporine therapy to tacrolimus therapy were due to rejection (n = 27). The majority of patients who crossed over from tacrolimus therapy to cyclosporine therapy were due to adverse reactions (n = 13) and rarely for rejection (n = 2). Of 27 cyclosporine-treated patients demonstrating acute rejection episodes and transferred to tacrolimus, 21 of these patient rejection episodes resolved (77.8%). Of the 2 tacrolimus patients transferred to cyclosporine due to acute rejection, one of the rejection episodes resolved.
An open-label, rescue study, 93-0003, assessed the effect of tacrolimus on 73 kidney transplant patients with biopsy-proven, corticosteroid-resistant acute rejection. Responses to tacrolimus therapy included improvement in 78% of patients, stabilization in 11% and progressive deterioration in 11%. Patient and graft survival one year-post conversion to tacrolimus was 93% and 75% respectively.
The use of tacrolimus-based immunosuppression in combination with mycophenolate mofetil or azathioprine was evaluated in a Phase IV, randomized, 3-arm, multicenter, non-blinded, prospective study. A total of 176 deceased donor kidney transplant recipients were randomized to one of three treatment groups; azathioprine, mycophenolate mofetil 1 gram per day or mycophenolate mofetil 2 grams per day in two divided doses. All patients received prophylactic induction therapy consisting of an antilymphocyte antibody preparation and corticosteroids. The respective one year patient survival rates were 98.3%, 94.9% and 94.8% for the three treatment groups of azathioprine, mycophenolate mofetil 1 gram per day and mycophenolate mofetil 2 grams per day in two divided doses. Corresponding one year graft survival rates were 94.9%, 93.2% and 94.8%.
A long-term comparison study of tacrolimus (n = 205) and cyclosporine (n = 207) in kidney transplantation was conducted as a 5-year follow-up to study 93-0006. The study focused on the long-term impact of tacrolimus therapy. Patient and graft survival rates over the follow-up period were equivalent between tacrolimus and cyclosporine treatment arms (79.1% vs. 81.4% and 64.3% vs. 61.6%, respectively). The estimated graft half-life was 13.3 years for tacrolimus and 11.9 years for cyclosporine. However, the incidence of crossover from cyclosporine to tacrolimus was significantly greater than the crossover from tacrolimus to cyclosporine (27.5% vs. 9.3%).
Kidney function tests showed mean serum creatinine levels were higher among patients treated with cyclosporine than those treated with tacrolimus. Significantly fewer patients in the tacrolimus treatment arm developed serum creatinine levels >1.5 mg/dL (40.4% vs. 62.0%).
The risk of treatment failure (defined as the occurrence of graft loss or discontinuation of randomized drug) was significantly lower among patients treated with tacrolimus compared to those treated with cyclosporine (43.8% vs. 56.3%; p = 0.008). Graft failure due to rejection occurred more frequently among cyclosporine-treated patients (22.1% vs. 17.0%). At 5 years, fewer patients receiving tacrolimus-based therapy were treated with antihypertensive and antihyperlipidemia medications. It was found that significantly fewer patients maintained on tacrolimus-based therapy developed hypercholesterolemia compared to those receiving cyclosporine (4.7% vs. 17.4%).
Liver Transplantation
The safety and efficacy of tacrolimus administered in combination with adrenal corticosteroids was compared with cyclosporine-based immunosuppressive regimens in two randomized, prospective, open-labelled, multicentre studies after orthotopic liver transplantation. In addition, the efficacy of tacrolimus as rescue therapy in patients with liver allograft rejection refractory to standard therapy was examined in an open-labelled, nonrandomized, multicentre, historically-controlled trial.
In one controlled trial, (Study FPC-FK506-7), 529 patients were randomized to receive immunosuppression with tacrolimus immediate-release capsule (N=263) or cyclosporine-based regimens (N=266). Patient survival was equivalent with Kaplan-Meier actuarial one-year estimates of 88% for both tacrolimus and cyclosporine-based regimens. Actuarial one-year graft survival estimates were 82% for the tacrolimus group and 79% for the cyclosporine-based group. The incidences of acute rejection (68% vs. 76%), steroid-resistant rejection requiring treatment with OKT3 (19% vs. 36%), and refractory rejection (3% vs. 15%) were lower in recipients of the tacrolimus regimen compared with cyclosporine-based regimens (see table below). Cumulative adrenal corticosteroid use was lower in the tacrolimus group; however, equivalent doses of corticosteroids were not mandated for induction or maintenance in the two arms of the study. Other measures of efficacy, such as liver function tests and Karnofsky scores, showed similar improvement over time in both groups.
Table 27: Results for the Liver Transplantation Study FPC-FK506-7
| Efficacy Parameters | Tacrolimus (%) | CBIR* (%) | 95% Confidence Intervals (%)** |
|---|---|---|---|
| Actuarial One Year Patient Survival Estimates | 88 | 88 | -5, 7 |
| Actuarial One Year Graft Survival Estimates | 82 | 79 | -5, 10 |
| Incidence of Acute Rejection | 68 | 76 | -17, 1 |
Incidence of Steroid-Resistant Rejection Requiring Orthoclone OKT3 Treatment | 19 | 36 | -25, -8 |
| Incidence of Refractory Rejection | 3 | 15 | -18, -6 |
* Cyclosporine-Based Immunosuppressive Regimens ** Tacrolimus minus CBIR
In the second controlled study (Study GHBA-157), 545 patients were randomized to receive tacrolimus combined with adrenal corticosteroids (N=270) as a treatment for prevention of rejection of primary liver allograft patients, compared with cyclosporine-based therapy (N=275).
The estimated one-year Kaplan-Meier patient survival rates were 81% for the tacrolimus treatment group and 75% for the cyclosporine-based treatment group. One-year estimated Kaplan-Meier graft survival rates were 76% for the tacrolimus group and 70% for the cyclosporine-based group. The acute rejection rate was 42% for the tacrolimus group compared with 55% for the cyclosporine-based group. The incidence of refractory rejection was also less in the tacrolimus group (3%) compared with the cyclosporine-based group (10%). (See table below.) The cumulative amount of adrenal corticosteroids administered to patients in the tacrolimus group was less than in the cyclosporine-based group.
Table 28: Results for the Liver Transplantation Study GHBA-157
| Efficacy Parameters | Tacrolimus (%) | CBIR* (%) | 95% Confidence Intervals (%) ** |
|---|---|---|---|
| Actuarial One Year Patient Survival Estimates | 81 | 75 | -1, 13 |
| Actuarial One Year Graft Survival Estimates | 76 | 70 | -1, 14 |
| Incidence of Acute Rejection | 42 | 54.7 | -23, -4 |
| Incidence of Refractory Rejection | 2.6 | 9.2 | -12, -3 |
* Cyclosporine-Based Immunosuppressive Regimens ** Tacrolimus minus CBIR
In a non-randomized historically controlled trial (Study FPC-FK506-9), 125 patients previously treated with cyclosporine-based regimens with refractory acute or chronic liver allograft rejection were treated with tacrolimus plus adrenal corticosteroids as rescue therapy. Actuarial Kaplan-Meier estimates of survival at one year post-conversion to tacrolimus immediate-release capsule were 71% for patient survival and 56% for graft survival. Other measures of efficacy, such as clinical response scores, liver function test, and Karnofsky performance status showed improvement over time after conversion to tacrolimus.
Study 91-0045 was conducted in the United States to establish a safe and effective reduced dosage regimen for adult liver transplant patients. Patients were randomized to an initial low dose (0.15 mg/kg/day) or an initial high dose (0.30 mg/kg/day) of oral tacrolimus and all patients received the same initial dose of corticosteroids. Azathioprine was not allowed during the first 42 days of the study. Tacrolimus doses were adjusted upward or downward in the event of rejection or toxicity, respectively. The mean dose in the higher group shifted downward while the mean dose in the lower group shifted upward over time. By study day 42, both groups were receiving similar tacrolimus doses (0.13 mg/kg/day). At one year post-transplant, patient results based on the two initial dosing groups were as follows:
Table 29: Results for the Liver Transplantation Study 91-0045
| 12 Month Results | Low Dose (n = 100) | High Dose (n = 98) |
|---|---|---|
| Patient Survival | 91.9% | 89.7% |
| Graft Survival | 88.9% | 85.6% |
| Acute Rejection | 65.1% | 49.7% |
| Mean Whole Blood Trough Levels of Tacrolimus | 9.6 ng/mL (n = 76) | 10.6 ng/mL (n = 67) |
Two of 100 patients in the low dose group and 8 of 98 patients in the high dose group discontinued the study due to an adverse event during the first 6 weeks of therapy.
A long-term (5-year) comparison study of tacrolimus (n = 263) versus cyclosporine (n = 266) in primary liver transplantation was conducted in a 1-year randomized, multicenter trial (FPC-FK506-7) with a 4-year follow-up period.
The 5-year patient and graft survival rates were comparable among tacrolimus (79.0%, 71.8%) and cyclosporine (73.1%, 66.4%) treatment groups. However, patient half-life survival was significantly longer for tacrolimus-treated patients (25.1 ± 5.1 years vs. 15.2 ± 2.5 years), a similar trend occurred with graft half-life. Patient survival of hepatitis C-positive patients was also significantly longer with tacrolimus treatment (78.9% vs. 60.5%).
During the first year after transplant, patients in the tacrolimus group had a statistically significant lower incidence of acute rejection (68% vs. 76%) and steroid-resistant rejection (19% vs. 36%). There was no significant difference between treatment groups in the following years. The incidence of death or graft loss due to rejection was 3% in both treatment groups over the 5-year follow-up period. The incidence of malignancies, lymphoproliferative disorders, and late infections were low and comparable between treatment groups.
Heart Transplantation
Two open-label, randomized, comparative studies evaluated the safety and efficacy of tacrolimus-based and cyclosporine-based immunosuppression in primary orthotopic heart transplantation. In a Phase III study conducted in Europe, 314 patients received a regimen of antibody induction, corticosteroids and azathioprine in combination with tacrolimus or cyclosporine modified for 18 months. In the US study, all patients received corticosteroids in addition to tacrolimus plus mycophenolate (MMF) (113 patients) or cyclosporine modified plus MMF (117 patients) for 1 year.
In the European Phase III study, patient/graft survival at 18 months post-transplant was similar between treatment arms, 91.7% in the tacrolimus group and 89.2% in the cyclosporine group (treatment difference 2.4%; 95% CI: -4.0%, 8.9%). In the US study, patient and graft survival at 12 months was comparable between the treatment groups with 93.5% survival in the tacrolimus plus MMF group and 86.1% survival in the cyclosporine modified plus MMF group.
In the European Phase III study, the incidence of biopsy-verified acute rejection standardized grade ≥1B at 6 months post-transplantation was significantly lower (p = 0.029, Cochran-Mantel-Haenszel) in the tacrolimus group (54%) compared with the cyclosporine group (66.4%) based on blinded central assessments. The incidence of biopsy-verified acute rejection standardized grade ≥3A at 6 months post-transplantation was significantly lower with tacrolimus-based immunosuppression (29.3%) compared with cyclosporine-based immunosuppression (42%; p = 0.018, chi-square) based on blinded central assessments. The incidence of biopsy-verified acute rejection grade ≥3A with hemodynamic compromise was similar (tacrolimus: 0.6% vs cyclosporine modified 0%; treatment difference 0.6%; 95% CI: - 0.6%, 1.9%).
In the US comparative study, biopsy-verified acute rejection grade ≥3A and biopsy-verified acute rejection grade ≥3A with hemodynamic compromise at 1 year were similar between the treatment groups (tacrolimus/MMF: 24.3% and 3.7%; cyclosporine/MMF: 35.7% and 7.8%).
Rheumatoid Arthritis
Safety and efficacy of tacrolimus-based treatment in rheumatoid arthritis patients was evaluated in one Phase II study and two Phase III studies.
The results for the Phase II study, FK506RA-001 and a Phase III study, 98-0-049, depicting the ACR response rates and change from baseline to the end of treatment for individual component scores are depicted below.
Table 30: ACR Response Rates and Change from Baseline to End of Treatment for Individual Component Scores
| Variable | FK506RA-0011 | 98-0-0491 | |||||
|---|---|---|---|---|---|---|---|
| Variable | FK506RA-0011 | 98-0-0491 | |||||
| Placebo | 1 mg | 3 mg | 5 mg | Placebo | 2 mg | 3 mg | |
| Placebo | 1 mg | 3 mg | 5 mg | Placebo | 2 mg | 3 mg | |
ACR20 Response Rate | 15.5% | 29.9%# | 34.4%* | 50.0%*** | 13.4% | 21.4%# | 32.0%** * |
ACR20 Success Rate | 11.3% | 29.0%# | 23.4%# | 40.6%*** | 10.2% | 18.8%* | 26.8%** * |
ACR50 Response Rate | 1.4% | 14.5%* | 17.2%* | 14.1%* | 4.5% | 11.7% | 11.8%* |
ACR70 Response Rate | NA | NA | NA | NA | 0.6% | 5.2%* | 3.3% |
Swollen Joint Count2 (LS Mean) | -1.8 | -3.8 | -5.4* | -6.8** | -1.47 | -4.02* | -5.3*** |
Tender Joint Count2 (LS Mean) | -0.9 | -6.3* | -7.9** | -12.9*** | -1.87 | -3.09 | -7.25*** |
| Patient’s Assessment of Pain2 | -5.4 | -11.4 | -16.2* | -23.7*** | -2.13 | -11.3** | -10.6** |
Patient’s Global Assessment of Disease Activity 2 (mm) | -3.4 | -11.0 | -13.5# | -21.1*** | 2.5 | -7.2** | -6.6** |
Physician’s Global Assessment of Disease Activity 2 (mm) | -10.2 | -13.4 | -18.5# | -27.8*** | -9.0 | -15.8* | -18.2** |
Patient’s Assessment of Physical Function (MHAQ)2 | 0.0 | -0.1 | -0.3* | -0.4*** | 0.09 | -0.13*** | -0.03* |
| CRP2 (mg/dL) | 0.5 | -0.3# | -0.8** | -1.7*** | 0.01 | -0.8** | -0.6* |
| ESR2 (mm/hr) | 5.1 | -4.0* | -4.3* | -11.4* | 2.6 | -4.3** | -8.6 |
1 Patients who were randomized and received at least one dose of study medication.
2 Mean change from baseline. ACR20, ACR50 and ACR 70: ≥ 20%, ≥ 50% and ≥ 70%, respectively, improvement in tender or painful joint count and swollen joint count and ≥ 20%, ≥ 50% and ≥ 70% respectively, improvement in 3 of the 5 following parameters: patient’s assessment of pain, patient’s global assessment of disease activity, physician’s global assessment of disease activity, patient’s assessment of physical function (based on the modified health assessment questionnaire), and an acute-phase reactant (erythrocyte sedimentation rate or C-reactive protein).
LS Mean: Least square means are based on general linear model analysis with treatment group and DMARD strata included in the model.
#p ≤ 0.10, *p ≤ 0.05, **p ≤ 0.01, *** p ≤ 0.001. NA: not available
Phase II Study
In the randomized, double-blind, placebo-controlled study (Study FK-506-RA-001), patients intolerant or resistant to methotrexate were enrolled and were also being treated with corticosteroids, such as prednisone or its equivalent and/or nonsteroidal anti-inflammatory drugs (NSAIDS) and /or analgesics. Patients were randomized to receive one of the following oral doses of study medication capsules: 1 mg FK506, 3 mg FK506, 5 mg FK506 or placebo once a day, for 6 months.
The primary and secondary efficacy endpoints evaluated in this patient population included the ACR20, 50 and 70 responses, as defined by the American College of Rheumatology, for improvement assessment in rheumatoid arthritis at the end of treatment. These criteria are based in corresponding increases of 20, 50 or 70% improvement in tender or painful joint counts and swollen joint counts and a 20%, 50% or 70% improvement in 3 of 5 of the following parameters: patient’s assessment of pain, patient's global assessment of disease activity, physician’s global assessment of disease activity, patient’s assessment of physical function (based on the modified health assessment questionnaire), and an acute-phase reactant (ESR or C-reactive protein (CRP)).
The ACR20 response rate at the end of treatment was higher in all 3 dose groups: (29.0%) 1 mg, 34.4% (3 mg), 50.0% (5 mg) compared to placebo (15.5%). The response rates in the 3 mg and 5 mg groups were statistically significantly higher than placebo (p = 0.013 and <0.001, respectively), while the rate for the 1 mg group was not statistically significant (p = 0.058). A difference in ACR20 response rates between placebo and active dose groups was first observed at Week 8, with substantial increases seen in the proportion of patients in the 5 mg group who achieved ACR20 responses during Weeks 12 and 16.
While there were no differences in swollen and tender joint counts in all 3 dose groups at baseline, there was a definite dose response, with the greatest improvement occurring in the 5 mg dose group. Improvement in swollen joint count was significantly higher in the 3 mg and 5 mg groups than in the placebo group (p = 0.029 and 0.002, respectively). Improvement in tender joint counts was significantly greater for the 1, 3 and 5 mg dose groups versus placebo (p = 0.022, 0.004 and < 0.001, respectively).
There was a statistically significant linear dose relationship over the 4 groups with respect to ACR20 at the end of treatment (p < 0.001), swollen joint counts at end of treatment (p = 0.001) and tender joint counts at the end of treatment (p < 0.001). The primary efficacy measure indicated a dose response among the tacrolimus groups, with statistically significantly greater efficacy at the 3 and 5 mg dose levels versus placebo for all primary measures.
Phase III Studies
In a randomized, double-blind, placebo-controlled study (Study 98-0-049), 465 patients who were concomitantly using prednisone (or its equivalent) and/or NSAIDS and had previously demonstrated resistance or intolerance to one or more disease-modifying antirheumatic drugs (DMARDS), were enrolled to receive either placebo, 2 mg/day or 3 mg/day tacrolimus immediate-release capsule, for a duration of 6 months.
Patients treated with tacrolimus generally experienced notable improvements in the ACR components of tender or painful joint counts, swollen joint counts as well as the physician’s global assessment while experiencing either no change or a slight improvement in the other ACR components. The median time required for the first ACR20 response to be detected in the tacrolimus dose group (2 mg/day and 3 mg/day) was approximately 8 weeks and was achieved by approximately 42% of the patient population.
The ACR20 response rate at the end of treatment for the full analysis set was significantly greater in the 2 mg and 3 mg tacrolimus treatment groups as well as the combined treatment groups compared with placebo. The differences between the ACR20 response rates at the end of treatment for the 2 mg tacrolimus treatment group and the placebo treatment group were not statistically significant (p = 0.0595), while that for the 3 mg tacrolimus treatment group and placebo were statistically significant (p = 0.0001). The ACR20 response at the end of treatment demonstrated a dose-response relationship.
Based on the median percent change from baseline to the end of treatment, patients in the 2 mg and 3 mg tacrolimus treatment groups also generally experienced notable improvements in tender or painful joint counts, 10.5% (2 mg) and 30.0% (3 mg) versus 2.2% (placebo) as well as improvements in the swollen joint counts 16.7% (2 mg) and 30.0% (3 mg) versus 5.9% (placebo). With the exception of tender or painful joint counts for the 2 mg tacrolimus treatment group, statistically significantly greater improvements from baseline to the end of treatment in each of the ACR component scores were observed in the 2 mg tacrolimus treatment group, the 3 mg tacrolimus treatment group and the combined tacrolimus treatment group as compared to placebo.
Among DMARD intolerant patients (those patients unable to continue on methotrexate therapy as determined by documented adverse events as judged by the investigator), significantly greater proportions of patients in the combined 2 mg and 3 mg tacrolimus treatment groups achieved ACR20 and ACR50 responses at the end of treatment compared with patients in the placebo treatment group. Among DMARD resistant patients (a patient on 15 mg/wk or more of methotrexate for at least 8 weeks who still presented with active disease), the proportion of patients achieving an ACR20 response at the end of treatment was not significantly different for the 2 mg tacrolimus treatment group or the combined tacrolimus treatment group compared with the placebo treatment group. However, a significantly greater proportion of DMARD resistant patients treated with 3 mg tacrolimus achieved an ACR20 response at the end of treatment compared with placebo. Among tacrolimus-treated patients, ACR20, 50 and 70 response rates at the end of treatment were greater for DMARD intolerant patients compared with DMARD resistant patients.
In the long-term safety study, (Study 98-0-051), an extension of study 98-0-049, patients were treated for a 12 to 18 month duration. These patients demonstrated continued improvement in the ACR20 response rates with an overall response rate at the end of treatment of 37.6%. Approximately 30% of patients experienced an ACR20 response within 3 months of receiving tacrolimus treatment. The ACR20 response rate was higher among patients who had previously received tacrolimus therapy in 98-0-049, at 45.5% (96/211) than among de novo patients enrolled in this study 35.2% (241/685), thereby indicating that those patients receiving a longer duration of treatment experienced a greater rate of response. Two of the greatest improvements in the median percent change from baseline were the ACR component scores at the end of treatment observed for swollen joint counts (47.5%) and tender or painful joint counts (50.0%).
14.3. Comparative Bioavailability Studies
A blind, randomized, single dose, crossover bioequivalence study of Sandoz Tacrolimus (tacrolimus monohydrate) capsules 5 mg and Prograf® (tacrolimus monohydrate) capsules 5 mg (Astellas Pharma Canada, Inc.) in healthy Asian male subjects (between the ages of 20 to 42 years old) under fasting conditions. Eighty four (84) subjects completed the study and the resulting data were used in the statistical analysis.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Tacrolimus (1x5 mg tacrolimus capsule) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (ng.h / mL) | 360.79 396.87 (43.0) | 368.56 403.94 (42.2) | 97.9 | 94.26-101.59 |
AUC0-∞ (ng.h / mL) | 445.18 497.61 (46.6) | 454.92 506.78 (45.6) | 97.9 | 94.23 – 101.63 |
Cmax (ng / mL) | 41.03 43.01 (29.5) | 43.23 45.32 (29.9) | 95.1 | 91.38 – 98.99 |
| Tmax3 (h) | 1.50 (0.75 – 3.50) | 1.75 (0.75 – 4.00) | ||
| T½4 (h) | 37.82 (17.1) | 38.04 (17.2) | ||
1 Sandoz Tacrolimus 5 mg capsules manufactured for Sandoz Canada.
2 PROGRAF® Tacrolimus 5 mg capsules (Astellas Pharma Canada, Inc.), were purchased in Canada.
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
A blind, randomized, single dose, crossover bioequivalence study of Sandoz Tacrolimus (tacrolimus monohydrate) capsules 5 mg and Prograf® (tacrolimus monohydrate) capsules 5 mg (Astellas Pharma Canada, Inc.) in healthy Asian male subjects (between the ages of 18 to 43 years old) under fed conditions. Eighty (80) subjects completed the study and the resulting data were used in the statistical analysis.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Tacrolimus (1x5 mg tacrolimus capsule) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
Tacrolimus (1x5 mg tacrolimus capsule) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (ng.h / mL) | 183.48 199.82 (45.8) | 192.52 208.07 (40.1) | 95.2 | 92.53-97.96 |
AUC0-∞ (ng.h / mL) # | 224.70 250.12 (55.4) | 239.74 262.57 (45.0) | 93.8 | 91.02 – 96.69 |
Cmax (ng / mL) | 10.73 11.46 (37.6) | 10.49 11.32 (40.1) | 102.1 | 96.81 – 107.71 |
| Tmax3 (h) | 6.00 (2.00 – 14.00) | 6.00 (2.50 – 24.00) | ||
| T½4, 5 (h) | 32.13 (24.0) | 33.97 (21.9) | ||
1 Sandoz Tacrolimus 5 mg capsules manufactured for Sandoz Canada.
2 PROGRAF® Tacrolimus 5 mg capsules (Astellas Pharma Canada, Inc.), were purchased in Canada.
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
5 n = 78 for the Test and n = 79 for the Reference
A blind, randomized, single dose, crossover bioequivalence study of Sandoz Tacrolimus (tacrolimus monohydrate) capsules 0.5 mg and Prograf® (tacrolimus monohydrate) capsules 0.5 mg (Astellas Pharma Canada, Inc.) in healthy Asian male subjects (between the ages of 18 to 44 years old) under fasting conditions. One hundred and nineteen (119) subjects completed the study and the resulting data were used in the statistical analysis.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Tacrolimus (1x0.5 mg tacrolimus capsule) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (pg.h / mL) | 23166.17 26234.64 (50.1) | 22589.37 26144.80 (55.5) | 102.6 | 98.45-106.97 |
AUC0-inf5 (pg.h / mL) | 30047.90 34267.52 (52.6) | 29280.00 34394.82 (58.3) | 102.3 | 97.82-106.96 |
Cmax (pg / mL) | 2688.61 2923.07 (41.6) | 2856.69 3095.57 (39.6) | 94.1 | 89.82-98.68 |
| Tmax3 (h) | 1.50 (0.75– 3.50) | 1.50 (0.75– 4.00) | ||
| T½4, 5 (h) | 35.81 ( 23.2) | 37.93 (35.7) | ||
1 Sandoz Tacrolimus 0.5 mg capsules manufactured for Sandoz Canada.
2 PROGRAF® Tacrolimus 0.5 mg capsules (Astellas Pharma Canada, Inc.), were purchased in Canada.
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
5 n = 109 for the Test and n = 108 for the Reference
A blind, randomized, single dose, crossover bioequivalence study of Sandoz Tacrolimus (tacrolimus monohydrate) capsules 0.5 mg and Prograf® (tacrolimus monohydrate) capsules 0.5 mg (Astellas Pharma Canada, Inc.) in healthy Asian male subjects (between the ages of 18 to 43 years old) under fed conditions. One hundred and thirteen (113) subjects completed the study and the resulting data were used in the statistical analysis.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Tacrolimus (1x0.5 mg tacrolimus capsule) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (pg.h / mL) | 18255.19 20024.04 (45.6) | 18793.06 20712.06 (46.6) | 97.5 | 94.19 – 100.97 |
AUC0-∞5 (pg.h / mL) | 23578.01 26459.52 (51.0) | 24507.25 27685.47 (53.1) | 99.0 | 94.86 – 103.33 |
Cmax (pg / mL) | 1037.52 1117.77 (43.7) | 1035.73 1106.29 (35.7) | 100.3 | 95.65 – 105.21 |
| Tmax3 (h) | 6.50 (2.00 – 24.00) | 6.00 (2.00 – 24.00) | ||
| T½4, 5 (h) | 33.89 (31.2) | 34.03 (33.3) | ||
1 Sandoz Tacrolimus 0.5 mg capsules manufactured for Sandoz Canada.
2 PROGRAF® Tacrolimus 0.5 mg capsules (Astellas Pharma Canada, Inc.), were purchased in Canada.
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
5 n = 103 for both the Test and Reference
15. Microbiology
Not Applicable.
16. Non-Clinical Toxicology
Animal Studies
The primary mechanism of rejection following transplantation involves activation of T-lymphocytes and the subsequent formation of factors such as interleukin-2 (IL-2). Tacrolimus inhibits the activation of T-lymphocytes in both animals and humans, especially the activation that is calcium-dependent. The minimum inhibitory tissue culture level of tacrolimus that prevents antigen stimulation of T-lymphocytes is 0.1 nM - 0.3 nM. Tacrolimus interferes with the formation of active transcription factor NF-AT (nuclear factor of activated T-cells) and inhibits the formation of lymphokines such as IL-2, IL-3, IL-4, and interferon-γ. The net result is immunosuppression.
Tacrolimus significantly prolonged host survival and/or graft viability in animal transplant models involving the liver, kidney, heart, small bowel, lung, pancreas, pancreatic islet, bone marrow, skin, limb, cornea, and trachea. A dose range of 0.1 to 1 mg/kg/day PO or IM was used in most studies in various dosing regimens: pre- and post-surgery, short- and long-term administration.
At intravenous doses of 0.32 to 3.2 mg/kg, and at oral doses of 3.2 to 32 mg/kg, tacrolimus showed little effect on general activity and the central nervous system; little or no effect on somatic and autonomic nervous systems and smooth muscle.
Most of the effects shown by IV tacrolimus in dogs and cats were also shown by the tacrolimus-placebo IV formulation. Intravenous tacrolimus at ≥ 0.1 mg/kg increased the respiration rate in dogs only; blood pressure was decreased by IV tacrolimus at ≥ 0.1 mg/kg in dogs, to a lesser extent at 3.2 mg/kg in cats, and by PO tacrolimus at 32 mg/kg in rats; heart rate was decreased by IV tacrolimus at ≥ 0.1 mg/kg in dogs, at ≥ 0.32 mg/kg in cats, at 3.2 mg/kg in rats, and by PO tacrolimus at 10 and 32 mg/kg in rats; blood flow in femoral artery of dogs was decreased by IV tacrolimus at ≥ 0.1 mg/kg; carotid artery blood flow was increased at 3.2 mg/kg IV in cats.
Intravenous tacrolimus at ≥ 1.0 mg/kg increased pilocarpine-induced salivary secretion in rabbits and decreased gastric fluid secretion in rats; and, at 3.2 mg/kg, increased accumulation of intestinal fluid and slightly inhibited gastrointestinal transit rate in rats. Intravenous tacrolimus did not affect bile secretion nor produce irritation to gastric mucosa in rats. Gastrointestinal transit rate and accumulation of intestinal fluid in rats were not affected by PO tacrolimus. Bleeding time in mice and prothrombin time and activated partial thromboplastin time in rats were not affected by IV or PO tacrolimus. Tacrolimus did not affect ADP- or collagen-induced aggregation of rabbit platelets, or produce hemolysis in rabbit blood. Oral tacrolimus at 32 mg/kg slightly increased urine volume and Na+ excretion, but not excretion of K+, Cl-, or uric acid, in rats; IV tacrolimus at 3.2 mg/kg had no effect. Oral tacrolimus had no effect on carrageenin-induced paw edema in rats.
When 14C-tacrolimus was dosed orally to pregnant or lactating rats, trace amounts of tacrolimus were found in fetal liver and in breast milk, respectively.
When 14C-tacrolimus was administered to rats, either intravenously or orally, total recovery of radioactivity in urine and feces was over 95%. Trace amounts of unchanged tacrolimus, as well as small amounts of numerous metabolites, were detected in urine, feces, and bile, indicating that the drug is extensively metabolized. In vitro studies identified the main metabolite as 13-demethylated-tacrolimus in animals and humans.
Acute Toxicology
Table 31: Acute Toxicology Studies of Tacrolimus in Rats and Baboon
| Species | No./ Group (M/F) | Route | Dose Range (mg/kg) | Overt Signs of Toxicology | LD50 (mg/kg) |
|---|---|---|---|---|---|
| Species | No./ Group (M/F) | Route | Dose Range (mg/kg) | Overt Signs of Toxicology | LD50 (mg/kg) |
| Rat, Sprague-Dawley | 5/5 | Gavage | 32-320 | Tremor, ptosis, salivation, | 134 (M) 194 (F) |
hyperreactivity, decreased spontaneous motility | |||||
| 5/5 | IV | 10-100 | Bloody urine, prone position, ptosis, hyper-reactivity, salivation, decreased motility | 57.0 (M) 23.6 (F) | |
Rat, Sprague-Dawley (21 days old) | 5/5 | Gavage | 10-320 | Hyper-reactivity, salivation, decreased motility | 70 (M) 32-100 (F) |
| Baboon | 1/1 | Gavage | 5-250 | Huddled posture, emesis | ND* |
| 1/1 | IV | 2-50 | Debility and exhaustion: 1 of 2 | ND* | |
*Not determined
Subchronic and Chronic Toxicity
Both rats and baboons showed a similar toxicologic profile following oral or intravenous administration of tacrolimus. Toxicity following intravenous administration was evident at lower doses than after oral administration for both rats and baboons. Toxicity was seen at lower doses in rats than in baboons. The primary target organs of toxicity were the kidney, pancreatic islets of Langerhans and exocrine pancreas, spleen, thymus, gastrointestinal tract, and lymph nodes. In addition, decreases in erythrocyte parameters were seen. Effects such as atrophy of the spleen, lymph nodes, and thymus may be a reflection of the immunosuppressant actions of tacrolimus. In rats, chronic oral administration of tacrolimus at high doses resulted in changes in sex organs and glaucoma/eye changes.
Rats receiving oral doses greater than 1 mg/kg/day for two and 13 weeks experienced decreased body weight gain, hypersalivation, hematology changes, elevated BUN, atrophy of the thymus and kidney, mineralization of the kidney, vacuolation of the islets of Langerhans, lenticular opacity and degeneration, and prostate contraction. In a 52-week study, the no-observable effect level was 0.15 mg/kg/day PO.
A 4-week oral toxicity study of tacrolimus in immature rats showed a similar toxicological profile; however, the severity of the changes noted appeared to be increased relative to mature animals. The no-observable effect level in immature rats was 0.32 mg/kg/day PO.
Rats receiving intravenous doses showed a dose-dependent decrease in weight gain.
Micropathological changes were similar to those seen after oral administration of higher doses, and consisted of thymic, lymph node, and splenic atrophy, vacuolation of the pancreatic islets, reduced colloid and contraction of the prostate and seminal vesicles, uterine wall narrowing, and corticomedullary mineralization in the kidney. The no-observable effect level was 0.032 mg/kg/day IV.
Baboons receiving 10 mg/kg/day PO for 4 weeks, showed body weight loss, quiet behaviour, huddled behaviour, pelleted feces, and piloerection. There were no abnormal laboratory findings or lesions.
In a 13-week oral study, body weight gain increased after the first 4 weeks in a manner parallel to that of controls. There were incidences of drowsiness and 4 huddled and/or unnatural posture. Histopathological examination indicated atrophy of the thymus and spleen. The no-observable effect level was 1 mg/kg/day PO.
A second 13-week oral study additionally produced intermittent tremors, unsteadiness, gingivitis, and emesis. There was a slight reduction in packed cell volume and hemoglobin, and a slight increase in clotting time in the high-dosage group animals. Elevations in BUN and blood glucose levels and a reduction in serum cholesterol concentration were dose related. There were increased levels of total reducing substances and glucose, and significant reductions in absolute thymus and pancreas weight in both dosage groups. There were dose-related pathological changes in the thymus (atrophy), spleen (atrophy), lymph nodes (atrophy), pancreas (exocrine cell degranulation or increased eosinophilic islet cells), intestinal tract (lymphoid infiltration, ulceration), and kidneys (interstitial inflammation).
Oral administration to baboons for 52 weeks at doses of 0, 1, 3.2, or 10 mg/kg/day resulted in an initial decreased weight gain, increase in urinary glucose and reducing substances, and pathological changes in the thymus, lymph nodes, and pancreas. The no-observable effect level was 1 mg/kg/day PO.
IV administration of tacrolimus to baboons for 4 weeks at doses of 0.5, 1, or 2 mg/kg/day resulted in overt signs of toxicity in all animals. Body weight gain was reduced and animals displayed quiet behavior, huddled posture, sleepiness, and piloerection. One out of 3 female animals at 2 mg/kg was sacrificed because of overt toxicity. BUN and serum potassium were elevated in animals dosed at 1 and 2 mg/kg. Glucose and total reducing substances were present in urine samples from one animal in each of the treatment groups. Pathological changes were noted in the thymus (atrophy), lymph nodes (atrophy), spleen (atrophy), and pancreatic islets (angiectasis of islets).
Carcinogenicity
No evidence of genotoxicity was seen in bacterial (Salmonella and E. coli) or in mammalian (Chinese hamster lung-derived cells) in vitro assays of mutagenicity.
Tacrolimus did not cause unscheduled DNA synthesis in rodent hepatocytes in either the in vitro CHO/HGRPT assay of mutagenicity, or in the in vivo clastogenicity assays performed in mice.
An 80 week study in mice administered tacrolimus at oral doses of 0.3, 1.0 and 3.0 mg/kg/day showed no evidence of tumorigenicity. The 104 week studies in rats administered tacrolimus at oral doses of 0.2, 0.5, 1.25, 2.5 and 5.0 mg/kg/day demonstrated no evidence of tumorigenicity.
The carcinogenicity potential of FK506 has been evaluated in mice and rats. Mice (56/sex) were administered FK506 as a dietary admix at doses of 0 (control), 0 (placebo), 0.3, 1 and 3 mg/kg/day. There was no evidence of any tumorigenic potential of FK506 in this study. Signs of toxicity were evident in the form of reduced bodyweight gain in both sexes receiving 3.0 mg/kg/day and for males receiving 1 mg/kg/day. For males receiving 3.0 mg/kg/day, there was a reduction in the efficiency of food utilization. An increase in mortality for males at 3.0 mg/kg/day was accompanied by pathological findings of minimal adipose tissue and fur staining, evidence of dysfunctional testes/epididymides, prostate glands and seminal vesicles. Males and females at 3.0 mg/kg/day also demonstrated reduced islets of Langerhans and increased basophilia and cellularity of islets. The no-effect level was considered to be 0.3 mg/kg/day in both sexes. In addition, 1 mg/kg/day was a no-effect level for females only.
Rats (55/sex/group) were administered FK506 as a dietary admix at doses of 0 (basal diet), 0 (placebo), 0.2, 0.5 and 1.25 mg/kg/day. There was no evidence of any tumorigenic potential for FK506 in this study, nor were there any FK506 administration-related effects on factors contributory to death. Evidence of toxicity were reduced body weight gain in both sexes at 1.25 mg/kg/day and in males at 0.5 mg/kg/day. The non-toxic dose level in the study was 0.2 mg/kg/day for males and 0.5 mg/kg/day for females.
FK506 was administered to rats as a dietary admix in the supplementary study, at doses of 0 (placebo) to 50/sex, and 2.5 mg/kg/day (100/sex). In the absence of clear toxicity, at the end of week 26, the FK506-treated group was divided into two groups (50/sex/group). One group received a dose of 2.5 mg/kg/day whereas the dose in the other group was increased to 5.0 mg/kg/day. There was no evidence of tumorigenic potential at either dose level. Evidence of toxicity were dose-related mortality rates, reduced body weight gain and histopathological changes; toxicity was more pronounced in males. There was no non-toxic dose in this study.
Reproductive and developmental toxicity
The reproductive toxicity of tacrolimus was evaluated in Segment 1 (rats), Segment 2 (rats and rabbits) and Segment 3 (rats) studies. The results of these studies are summarized below in Table 32.
Table 32: Reproductive and Developmental Toxicity Studies of Orally Administered Tacrolimus
| Study | Oral Dose (mg/kg/day) | Major Findings |
|---|---|---|
| Study | Oral Dose (mg/kg/day) | Major Findings |
| Parenteral | F1 Offspring | |
| Parenteral | F1 Offspring | |
| Segment 1, Rat | ||
| 0.32 | No observable effect | No observable effect |
| 1 | Incomplete delivery | No observable effect |
| 3.2 | ↓ Body weight with ↓ food consumption | Some lethality; ↓ Implantation |
↓ Male copulatory index ↑ Copulatory interval Incomplete delivery ↑ Female diestrus period | ↑ Post-implantation loss ↓ Embryo/offspring viability | |
| Segment 2, Rat | ||
| 0.32 | No observable effect | No observable effect |
| 1 | No observable effect | ↓ Fetal body weight |
| 3.2 | Some lethality; ↓ Body weight with ↓ food consumption | ↓ Fetal body weight ↑ Post-implantation loss ↓Offspring viability ↑ Skeletal variations |
| Segment 2, Rabbit | ||
| 0.1 | ↓ Body weight | No observable effect |
| 0.32 | ↓ Body weight Abortions | ↑ Developmental variations |
| 1 | ↓ Body weight Abortions | ↑ Developmental variations ↑ Post-implantation loss ↓ Viable fetuses ↑ Morphological variations |
| Segment 3, Rat | ||
| 0.32, 1 | No observable effect | No observable effect |
| 3.2 | ↓ Body weight | ↓ Body weight |
Tacrolimus subcutaneously administered to male rats at doses of 2 or 3 mg/kg/day (1.6 to 6.4 times the clinical dose range based on body surface area) resulted in a dose-related decrease in sperm count.
Special toxicology
The toxicity of tacrolimus degradation products and a dosage form excipient were studied for antigenicity, effects on morphology and function of pancreas, and local irritation in several species. The acute IV toxicity of known heat- and light-degradation products of tacrolimus, a tacrolimus tautomer, related compounds, and a tacrolimus metabolite was assessed in mice. The acute toxicity of these compounds was not greater than that of tacrolimus as bulk drug or as the IV formulation.
Antigenicity studies produced no antibody formation in mice, and no skin reactions, sensitization, or delayed hypersensitivity reactions.
Tacrolimus produced a reversible, dose-dependent, pancreatic islet cell toxicity in rats; there were no effects on pancreatic exocrine function.
The irritation potential of the IV formulation of tacrolimus was similar to that of 0.425% acetic acid.
17. Supporting Product Monographs
- 1. PrPROGRAF®, tacrolimus immediate-release capsules, 0.5 mg, 1 mg and 5 mg, submission control 300195, product monograph, Astellas Pharma Canada Inc. (2025-12-17)