


Product Monograph - Teva-Doxazosin
ACTIONS AND CLINICAL PHARMACOLOGY
The mechanism of action of doxazosin mesylate is selective blockade of α1 subtype of post-synaptic, post-junctional α-adrenergic receptors.
Pharmacodynamics
Hypertension
Administration of doxazosin mesylate results in a reduction in systemic vascular resistance. In patients with hypertension there is little change in cardiac output. Maximum reductions in blood pressure usually occur 2-6 hours after dosing and are associated with a small increase in standing heart rate. Doxazosin mesylate has a greater effect on blood pressure and heart rate in the standing position. Tolerance has not been observed in long term therapy.
Systolic and diastolic blood pressure is lowered in both the supine and standing positions. In clinical trials, blood pressure responses were measured at the end of the dosing interval (24 hours), with the usual supine response 6-11 mm Hg systolic and 5-9 mm Hg diastolic. The response in the standing position tended to be larger by 3-5 mm Hg. Peak blood pressure effects (1-6 hours) were larger by about 50-75% (i.e., trough values were about 55-70% of peak effect), with the larger peak-trough differences seen in systolic pressures. There was no apparent difference in the blood pressure response of Caucasians and Blacks or of patients ≥ 65 years old and < 65 years old.
During controlled clinical studies, predominantly normocholesterolemic patients receiving doxazosin mesylate had small but statistically significant reductions in total serum cholesterol (2.7%) and low-density lipoprotein (LDL) cholesterol (4.3%), and increase in the high-density lipoprotein (HDL)/total cholesterol ratio (4.3%) relative to placebo. No significant changes were observed in HDL fraction and triglycerides compared to placebo.
Benign Prostatic Hyperplasia (BPH)
Benign Prostatic Hyperplasia (BPH) is a common cause of urinary outflow obstruction in aging males. Severe BPH may lead to urinary retention and renal damage. A static and a dynamic component contribute to the symptoms and reduced urinary flow rate associated with BPH. The static component is related to an increase in prostate size caused, in part, by a proliferation of smooth muscle cells in the prostatic stroma.
However, the severity of BPH symptoms and the degree of urethral obstruction do not correlate well with the size of the prostate. The dynamic component of BPH is associated with an increase in smooth muscle tone in the prostate and bladder neck. The degree of tone in this area is mediated by α1 adrenoceptors which are present in high density in the prostatic stroma, prostatic capsule and bladder neck. Blockage of the α1 receptor decreases urethral resistance and may relieve the obstruction and BPH symptoms. In 30 - 70% of patients with symptomatic BPH, placebo has also shown a remarkable and sometimes dramatic effect in controlled short-term studies.
The symptoms may subside or fade away without treatment in approximately 20% of patients.
Doxazosin antagonizes phenylephrine-induced contractions, in vitro, in the human prostate. Doxazosin is bound with high affinity to the α1A-adrenoceptor subtype, thought to be the predominant functional type in the prostate.
The effect of doxazosin mesylate in BPH is thought to result from selective blockade of the α1A-adrenoceptors located in the prostatic muscular stroma, capsule and bladder neck. This action results in relief of the urinary outlet obstruction and symptomatology associated with BPH.
In controlled clinical trials in >900 patients, the efficacy of doxazosin mesylate was evaluated. In two studies doxazosin mesylate 4-8 mg once daily significantly improved maximum urinary flow rate (MFR) by 2.3-3.3 mL/sec (placebo 0.1-0.7 mL/sec).
Significant improvements were usually noticed within 2 weeks of commencing doxazosin mesylate treatment and a significantly larger proportion of patients (32-42%) responded with MFR improvements ≥ 3 mL/sec (placebo 13-17%). Average flow rate also improved with doxazosin mesylate treatment (1.3-2.1 mL/sec vs.placebo 0.2-0.3 mL/sec). Doxazosin mesylate also resulted in a significant relief of the obstructive and irritative symptoms associated with BPH.
Using invasive urodynamics in a controlled clinical trial in 43 BPH patients, doxazosin mesylate 2 mg improved MFR 3.4 mL/sec, and reduced urethral resistance 7.5-13.5 cmH2O (placebo, MFR - 0.6 mL/sec and resistance of 3.3 cmH2O).
In a 29-week controlled BPH trial in 100 patients, doxazosin mesylate was significantly more effective than placebo in improving urinary flow rates and reducing BPH symptoms; the effect was sustained over the entire treatment period. No tolerance to the effect of doxazosin mesylate on urodynamics or BPH symptomatology was observed in patients treated for ≤ 4 years in open-label studies.
Both hypertensive and normotensive BPH patients treated with doxazosin mesylate demonstrate statistically significant improvements in urodynamics and symptomatology compared to placebo.
Pharmacokinetics
After oral administration of therapeutic doses of doxazosin mesylate absorption occurs with peak blood levels at about 2 hours. Bioavailability is approximately 65%. Food has little or no effect on the bioavailability.
Approximately 98% of the circulating drug is bound to plasma proteins. Plasma elimination is biphasic with a terminal elimination half-life of about 22 hours. There is an accumulation of plasma doxazosin levels following steady state dosing, consistent with the terminal elimination half-life.
In a study of elderly hypertensive patients, the pharmacokinetic parameters of doxazosin at steady state were similar to those observed in a previous study of young and elderly healthy subjects who received a single oral dose of doxazosin mesylate.
In a cross-over study in 24 normotensive subjects, the pharmacokinetics and safety of doxazosin were shown to be similar with morning and evening dosing regimens. Doxazosin mesylate may, therefore, be administered as a single daily morning or evening dose (see DOSAGE and ADMINISTRATION).
Doxazosin mesylate is primarily metabolized, mainly by O-demethylation of the quinazoline nucleus or hydroxylation of the benzodioxan moiety. Doxazosin is extensively metabolized in the liver. In vitro studies suggest that the primary pathway for elimination is via CYP 3A4; however, CYP 2D6 and CYP 2C9 metabolic pathways are also involved for elimination, but to a lesser extent (see PRECAUTIONS, Drug Interactions). Excretion is mainly via the feces with 9% of the dose excreted in urine as doxazosin (<0.5%) or metabolites. Less than 5% is excreted as the unchanged drug, mainly in the feces.
The disposition of doxazosin mesylate in patients with renal insufficiency is similar to that in patients with normal renal function. Only limited data are available in patients with liver impairment and on the effects of drugs known to influence hepatic metabolism (e.g., cimetidine) (see PRECAUTIONS - Use in Patients with Impaired Liver Function).
A single dose, randomized, blinded, two-way, crossover bioavailability study was performed to compare the rate and extent of absorption and bioequivalence of Teva-Doxazosin 1 mg Tablets with Cardura-1™ 1 mg Tablets in fasting volunteers. The pharmacokinetic mean plasma data calculated for the two products are tabulated below:
Doxazosin Mesylate 1 x1 mg From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference⊥ | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/mL) | 121.028 126.456 (29) | 114.469 119.684 (29) | 106 | 99-113 |
AUCI (ng.h/mL) | 128.313 133.615 (28) | 122.019 127.002 (28) | 105 | 99-111 |
AUC0-72 (ng.h/mL) | 121.337 125.678 (26) | 115.987 120.254 (26) | 105 | 99-111 |
Cmax (ng/mL) | 6.861 7.031 (23) | 6.696 6.926 (26) | 102 | 97-108 |
Tmax§ (h) | 2.2 (39) | 2.6 (49) | -- | |
T½ § (h) | 16.8 (22) | 16.3 (21) | -- | |
* Teva-Doxazosin 1 mg Tablets (Teva Canada Limited, Canada)
⊥ Cardura-1™ manufactured by Astra Pharma Inc., Mississauga, ON, Canada.
§ Expressed as the arithmetic means (CV %) only
INDICATIONS AND CLINICAL USE
Hypertension
TEVA-DOXAZOSIN (doxazosin mesylate) is indicated in the treatment of mild to moderate essential hypertension. It is employed in a general treatment program in association with a thiazide diuretic and/or other antihypertensive agents, as needed for proper patient response.
TEVA-DOXAZOSIN may be tried as a sole therapy in those patients for whom treatment with other agents caused adverse effects or is inappropriate.
Benign Prostatic Hyperplasia (BPH)
TEVA-DOXAZOSIN is also indicated for the treatment of symptoms of benign prostatic hyperplasia (BPH). The onset of effect is rapid, with improvement in peak flow and symptoms observed within 1-2 weeks. The effect on these variables was maintained over the entire study duration (≤4 years). TEVA-DOXAZOSIN may be used in BPH patients who are either hypertensive or normotensive. While the reduction in blood pressure in normotensive patients with BPH is clinically insignificant, patients with hypertension and BPH have both conditions effectively treated with doxazosin monotherapy (see DOSAGE AND ADMINISTRATION for dosage regimens).
A number of clinical conditions can mimic symptomatic BPH (i.e. stricture of urethra, stricture of bladder neck, urinary bladder stones, neurogenic bladder dysfunction secondary to diabetes, Parkinsonism, etc.). These conditions should therefore be ruled out before doxazosin therapy is initiated.
CONTRAINDICATIONS
TEVA-DOXAZOSIN is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see PHARMACEUTICAL INFORMATION, Composition section of the product monograph.
- Patients with a known sensitivity to other quinazolines (e.g. prazosin, terazosin).
- Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption because lactose is a non-medicinal ingredient in TEVA-DOXAZOSIN.
WARNINGS
Syncope and "First Dose" Effect
TEVA-DOXAZOSIN (doxazosin mesylate) can cause marked hypotension, especially postural hypotension and syncope in association with the first dose or first few doses of therapy. A similar effect can occur if therapy is reinstated following interruption for more than a few doses. Postural effects are most likely to occur between 2 - 6 hours after dose.
In controlled studies of doxazosin mesylate, the incidence of syncopal episodes was 0.7%. An initial dose of 1 mg/day resulted in a 4% incidence of postural side effects with no cases of syncope. In controlled clinical trials for BPH in normotensive patients, there was a 0.2% occurrence of syncope with doxazosin mesylate. In controlled trials in patients with both BPH and hypertension receiving doxazosin mesylate, the incidence of syncope was 0.8%.
The likelihood of syncopal episodes or excessive hypotension can be minimized by limiting the initial dose of doxazosin mesylate to 1 mg, by increasing the dosage slowly, and by introducing any additional antihypertensive drugs into the patient's regimen with caution (see DOSAGE AND ADMINISTRATION).
Patients should be advised of the possibility of syncopal and orthostatic symptoms, and to avoid driving or hazardous tasks for 24 hours after the initial dose of TEVA-DOXAZOSIN, after the dose is increased and after interruption of therapy when treatment is resumed. They should be cautioned to avoid situations where injury could result should syncope occur.
If syncope occurs, the patient should be placed in the supine position. If this measure is inadequate, volume expansion with intravenous fluids or vasopressor therapy may be used. A transient hypotensive response is not a contraindication to further doses of TEVA-DOXAZOSIN.
Orthostatic Hypotension
While syncope is the most severe orthostatic effect of TEVA-DOXAZOSIN, other symptoms of lowered blood pressure such as dizziness, light-headedness or vertigo can occur. These were common in clinical trials in hypertension, occurring in ≤23% of all patients treated and causing discontinuation of therapy in about 2%. In placebo- controlled titration trials there was an increased frequency of orthostatic effects in patients given ≥8 mg (10%) compared to patients given 1-4 mg (5%) or placebo (3%).
In placebo-controlled trials in BPH, the incidence of orthostatic hypotension with doxazosin mesylate was ≤1%. With maintenance doses of ≤8 mg/day in normotensive patients with BPH, the average decreases in both sitting and standing blood pressure were small: 5/2 mm Hg with doxazosin mesylate and 1/1 mm Hg with placebo.
Patients with occupations in which such events represent potential problems should be treated with particular caution.
Concomitant administration of doxazosin with a PDE-5 inhibitor such as sildenafil, tadalafil or vardenafil, should be used with caution as it may lead to symptomatic hypotension.
Patients should be advised of the need to lie down when symptoms of lowered blood pressure occur and to be careful when arising from a lying position. If dizziness, light-headedness or palpitations are bothersome, they should be reported to the physician so that dose adjustment can be considered. Patients should also be told that drowsiness or somnolence can occur with doxazosin mesylate, requiring caution in people who must drive or operate heavy machinery.
If hypotension occurs, place the patient in the recumbent position and institute supportive measures as necessary.
Priapism
Rarely (probably less frequently than once in every several thousand patients), α1-antagonists such as doxazosin have been associated with priapism. Because this condition can lead to permanent impotence if not promptly treated, patients should be advised about the seriousness of the condition.
Hematological Events
Analysis of hematologic data from patients receiving doxazosin mesylate in controlled clinical trials showed that the mean white blood cell (WBC) (n=474) and mean neutrophil counts (n=419) were decreased by 2.4% and 1.0% respectively, compared to placebo. A search through a data base of 2,400 patients revealed 4 cases in which drug-related neutropenia could not be ruled out. Two had a single low value on the last day of treatment. Two had stable, non-progressive neutrophil counts in the 1000/mm3 range over periods of 20 and 40 weeks. No patients became symptomatic as a result of the low WBC or neutrophil counts.
In BPH patients treated with doxazosin, the incidence of clinically significant WBC abnormalities was 0.4%.
In post-marketing experience, rare cases of hematopoietic events such as leukopenia and thrombocytopenia have been reported.
Hepatic Events
In post-marketing experience, rare cases of abnormal liver function tests, cholestasis, jaundice and hepatitis have been reported.
Peripheral Edema
Fluid retention resulting in weight gain may occur during TEVA-DOXAZOSIN therapy. In placebo controlled monotherapy trials, patients receiving doxazosin mesylate gained a mean of 0.6 kg compared to a mean loss of 0.1 kg for placebo-treated patients. The overall incidence of body weight gain reported as a side effect in controlled clinical trials was 0.8%.
PRECAUTIONS
General
TEVA-DOXAZOSIN (doxazosin mesylate) therapy does not modify the natural history of benign prostatic hyperplasia (BPH). It does not retard or stop the progression of BPH, nor does it improve urine flow sufficiently to significantly reduce the residual urine volume. However, significant reduction of the mean residual volume have been shown in patients with baseline residual volumes of >50 mL. The patient may continue to be at risk of developing urinary retention and other BPH complications during doxazosin therapy.
Long-Term Safety and Efficacy
The long-term safety and efficacy (i.e. >4 years) has not yet been established for the use of doxazosin in the treatment of benign prostatic hyperplasia.
Prostatic Cancer
Carcinoma of the prostate and BPH cause many of the same symptoms. These two diseases frequently coexist. Therefore, patients thought to have BPH should be examined prior to starting TEVA-DOXAZOSIN therapy to rule out the presence of carcinoma of the prostate.
TEVA-DOXAZOSIN should not be used in patients with PSA >10 ng/mL unless cancer of the prostate has been ruled out.
Ophthalmologic
The Intraoperative Floppy Iris Syndrome (IFIS, a variant of small pupil syndrome) has been observed during cataract surgery in some patients on or previously treated with α1 blockers. As IFIS may lead to increased procedural complications during the operation, current or past use of α blockers should be made known to the ophthalmologic surgeon in advance of surgery.
Use in Patients with Impaired Liver Function
As with any drug wholly metabolized by the liver; doxazosin should be administered with caution to patients with evidence of impaired hepatic function or to patients receiving drugs known to influence hepatic metabolism.
Use in Patients with Impaired Renal Function
The use of TEVA-DOXAZOSIN in patients with impaired renal function requires careful monitoring. Clinical studies indicate that the disposition of doxazosin mesylate in patients with renal insufficiency is similar to that in patients with normal renal function, however accumulation of the drug with chronic dosing may occur. Less than 10% of the dose of doxazosin is excreted in the urine as unchanged drug and metabolites.
Concomitant Conditions
Doxazosin should not be prescribed to patients with symptomatic BPH who have the following concomitant conditions:
- Chronic fibrous or granulomatous prostatitis,
- Chronic urinary retention,
- Gross hematuria,
- High residual urine (>200 mL),
- History of pelvic irradiation,
- History of prior prostatic surgery,
- Hydronephrosis,
- Peak urine flow of ≤5 mL/sec,
- Presence of calculi in urinary bladder,
- Presence of carcinoma of the prostate
- Presence of large median lobe of prostate,
- Presence of neurogenic bladder dysfunction (diabetes mellitus, parkinsonism, uninhibited neurogenic bladder, etc.),
- Presence of prostatic calculi,
- Recent history of epididymitis,
- Urethral stricture,
Doxazosin should also not be prescribed to patients having experienced within the past 6 months:
- A myocardial infarction,
- Transient ischemic attacks,
- Cerebrovascular accident
Use in Pregnancy
There are no studies in pregnant women. TEVA-DOXAZOSIN is not recommended in pregnant women unless the potential benefit outweighs the potential risk to mother and fetus.
TEVA-DOXAZOSIN crosses the placental barrier.
Animal data: Studies in pregnant rabbits and rats at daily oral doses of ≤40 and ≤20 mg/kg respectively have revealed no evidence of teratogenic effect. A dosage regimen of 82 mg/kg/day in the rabbit was associated with reduced fetal survival, an increase in embryomortality as well as increases in fetal and placental weights.
In peri-and post-natal studies in rats, postnatal development at maternal doses of 40 or 50 mg/kg/day of doxazosin was delayed as evidenced by slower body weight gain and a slightly later appearance of anatomical features and reflexes.
Use in Nursing Mothers
Animal data: Studies in lactating rats given a single oral dose of 1 mg/kg of [2-14C]-doxazosin indicate that doxazosin accumulates in rat breast milk with a maximum of concentration about 20 times greater than the maternal plasma concentration.
A single case report demonstrated transfer of doxazosin into human breast milk. Caution should be exercised when TEVA-DOXAZOSIN is administered to a nursing mother and in general, nursing should be interrupted.
Use in Children
The use of TEVA-DOXAZOSIN is not recommended in children since safety and efficacy have not been established.
Use in Elderly
TEVA-DOXAZOSIN should be used cautiously in elderly patients because of the possibility of postural hypotension. There was an age-related trend towards an increased incidence of postural hypotension and postural dizziness in elderly hypertensive patients treated with this drug.
Cardiac Toxicity in Animals
An increased incidence of myocardial necrosis or fibrosis was displayed by Sprague-Dawley rats after 6 months of dietary administration at concentrations calculated to provide 80 mg doxazosin/kg/day and after 12 months of dietary administration at concentrations calculated to provide 40 mg doxazosin/kg/day.
Myocardial fibrosis was observed in both rats and mice treated in the same manner with 40 mg doxazosin/kg/day for 18 months. No cardiotoxicity was observed at lower doses (≤10 or ≤20 mg/kg/day, depending on the study) in either species.
These lesions were not observed after 12 months of oral dosing in dogs and Wistar rats at maximum doses of 20 and 100 mg/kg/day respectively. There is no evidence that similar lesions occur in humans.
Drug Interactions
Doxazosin is highly (98%) bound to plasma protein. In vitro data in human plasma indicates that doxazosin mesylate has no effect on protein binding of digoxin, warfarin, phenytoin or indomethacin.
Doxazosin mesylate has been administered to patients receiving thiazide diuretics, beta-adrenergic blocking agents and non-steroidal anti-inflammatory drugs. No unexpected interactions were reported. An additive hypotensive effect was observed when doxazosin mesylate was co-administered with thiazide diuretics and beta-adrenergic blocking agents. There is limited experience with doxazosin mesylate in combination with ACE inhibitors or calcium channel blockers.
Digoxin
Serum digoxin concentrations were not affected by treatment with doxazosin.
Cimetidine
In a randomized, open-label, placebo-controlled, cross-over study in 22 healthy male subjects, the single co-administration of 1 mg doxazosin with 400 mg b.i.d. cimetidine resulted in a 10% increase in mean AUC of doxazosin (p = 0.006), and a slight but not statistically significant increase in mean Cmax and mean half-life of doxazosin. The effect of further administration of cimetidine has not been studied.
PDE-5 Inhibitors
Symptomatic hypotension has been reported during the concomitant use of PDE-5 inhibitors (e.g. sildenafil, tadalafil, vardenafil) and doxazosin mesylate (see WARNINGS).
CYP3A4 Inhibitors
In vitro studies suggest that doxazosin is a substrate of CYP 3A4. Caution should be exercised when concomitantly administering doxazosin with a strong CYP 3A4 inhibitor, such as clarithromycin, indinavir, itraconazole, ketoconazole, nefazodone, nelfinavir, ritonavir, saquinavir, telithromycin or voriconazole (see ACTIONS AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
ADVERSE REACTIONS
Hypertension
Doxazosin mesylate has been administered to approximately 4,000 patients in clinical trials of whom 1,679 patients were included in controlled trials. The most serious adverse event (AE) occurring in the controlled clinical trials was syncope occurring in 0.7% of patients and resulting in a discontinuation rate of 0.2%.
The most frequent AEs in controlled clinical trials were: headache (16.5%), fatigue/malaise (14.8%), dizziness (14.6%), postural dizziness (8.7%) and edema (6.6%). Discontinuation of doxazosin mesylate due to AEs was required in 7% of patients.
AEs which occurred with an incidence of ≥ 1% in the controlled clinical trials in patients with mild to moderate essential hypertension were as shown in the following table.
Table 1 – Incidence of Adverse Events ≥ 1% in the controlled clinical trials in patients with mild to moderate essential hypertension
| Body System/Adverse Event | Doxazosin n=1679 % |
| All Adverse Events | 49.0% |
| Nervous System Disorders | |
| Headache | 16.5 |
| Dizziness | 14.6 |
| Postural Dizziness | 8.7 |
| Somnolence | 4.9 |
| Paresthesia | 1.7 |
| Hypoesthesia | 1.6 |
| General Disorders and Administration Site | |
| Fatigue | 14.8 |
| Edema | 6.6 |
| Asthenia | 2.7 |
| Pain (general body) | 1.3 |
| Gastrointestinal Disorders | |
| Nausea | 3.9 |
| Dry Mouth | 3.4 |
| Diarrhea | 2.9 |
| Dyspepsia | 2.1 |
| Abdominal Pain | 1.6 |
| Flatulence | 1.4 |
| Constipation | 1.3 |
| Respiratory, Thoracic and Mediastinal Disorders | |
| Dyspnea | 3.9 |
| Rhinitis | 3.0 |
| Blood and Lymphatic Disorders | |
| Decrease in Platelets | 3.9 |
| Decrease in White Blood Cells | 2.4 |
| Decrease in Hematocrit | 1.6 |
| Decrease in Hemoglobin | 1.4 |
| Decrease in Neutrophil Count | 1.0 |
| Cardiac Disorders | |
| Palpitation | 3.6 |
| Chest Pain | 2.7 |
| Tachycardia | 1.6 |
| Reproductive System and Breast Disorder | |
| Sexual Dysfunction | 3.5 |
| Ear and Labrynth Disorders | |
| Vertigo | 3.0 |
| Eye Disorders | |
| Vision/Accommodation Abnormalities | 2.4 |
| Conjunctivitis/Eye Pain | 1.2 |
| Psychiatric Disorders | |
| Anxiety/Nervousness | 2.3 |
| Insomnia | 2.2 |
| Depression/Apathy | 1.6 |
| Skin and Subcutaneous Tissue Disorders | |
| Rash | 1.7 |
| Increased Sweating | 1.4 |
| Musculoskeletal and Connective Tissue Disorders | |
| Muscle Cramps | 1.7 |
| Myalgia | 1.3 |
| Renal and Urinary Disorders | |
| Micturition Frequency | 1.2 |
| Polyuria | 1.0 |
Less Common Clinical Trial Adverse Drug Reactions (<1%)
The following other AEs occurred in hypertensive patients with an incidence of <1% in controlled clinical trials (n=1679):
Blood and Lymphatic Disorders: lymphadenopathy
Cardiac Disorders: angina pectoris, arrhythmia
Ear and Labyrinth Disorders: tinnitus
Eye Disorders: abnormal lacrimation, photophobia
Gastrointestinal Disorders: fecal incontinence, vomiting
General Disorders and Administration Site Conditions: face edema, fever/rigors, general edema, thirst
Infections and infestations: infection
Metabolism and Nutrition Disorders: anorexia, gout, hypokalemia, increased appetite, weight increase
Musculoskeletal and Connective Tissue Disorders: arthralgia, back pain, muscle weakness, twitching
Nervous System Disorders: amnesia, ataxia, depersonalization, hypertonia, migraine, movement disorders, paresis, syncope, tremor
Psychiatric Disorders: abnormal thinking, agitation, emotional lability, paroniria
Renal and Urinary Disorders: urinary disorder, urinary incontinence
Reproductive System and Breast Disorder: breast pain
Respiratory, Thoracic and Mediastinal Disorders: bronchospasm/bronchitis, coughing, epistaxis, pharyngitis, sinusitis
Skin and Subcutaneous Tissue Disorders: alopecia, dry skin, eczema, pallor, pruritus, purpura
Special Senses: taste perversion
Vascular Disorders: flushing, hot flushes, hypotension, peripheral ischemia, postural hypotension
Benign Prostatic Hyperplasia
Doxazosin mesylate has been administered once daily to 665 both hypertensive and normotensive patients with BPH in controlled clinical trials. The most serious AEs occurring in the controlled trials was syncope (0.5%).
The most frequent AEs in controlled trials were dizziness (15.6%), headache (9.8%) and fatigue (8%).
Discontinuation rate of doxazosin mesylate due to AEs was 9%.
AEs which occurred with an incidence of ≥ 1% in the controlled clinical trials in normotensive or hypertensive patients with BPH were as shown in the following table.
Table 2 – Incidence of Adverse Events of ≥ 1% in the controlled clinical trials in normotensive or hypertensive patients with BPH
| ADVERSE EVENT | INCIDENCE | ||
|---|---|---|---|
| Short Term* (n=665) | Long Term** (n=450) | ||
| ADVERSE EVENT | INCIDENCE |
|---|
| Short Term* (n=665) | Long Term** (n=450) | |
|---|---|---|
| All Adverse Events | 45.0% | 66.0% |
| Nervous System Disorders | ||
| Dizziness | 15.6% | 20.7% |
| Headache | 9.8% | 12.2% |
| Somnolence | 3.0% | 4.9% |
| Hypertonia | <1% | 1.1% |
| Paresthesia | <1% | 1.1% |
| Tremor | - | 1.1% |
| General Disorders and Administration Site Conditions | ||
| Fatigue | 8.0% | 11.6% |
| Edema | 2.7% | 4.9% |
| Pain | 2.0% | 5.1% |
| Asthenia | <1% | 1.1% |
| Respiratory, Thoracic and Mediastinal Disorders | ||
| Dyspnea | 2.6% | <1% |
| Respiratory Disorder | 1.1% | 2.5% |
| Gastrointestinal Disorders | ||
| Diarrhea | 2.3% | 3.8% |
| Abdominal Pain | 2.3% | 1.8% |
| Dyspepsia | 1.8% | 2.4% |
| Nausea | 1.5% | 3.1% |
| Dry Mouth | 1.4% | <1% |
| Constipation | <1% | 1.3% |
| Musculoskeletal and Connective Tissue Disorders | ||
| Back Pain | 1.8% | 2.9% |
| Leg Cramps | <1% | 1.6% |
| Arthralgia | <1% | 1.3% |
| Vascular Disorders | ||
| Hypotension | 1.7% | 2.5% |
| Eye Disorders | ||
| Abnormal Vision | 1.4% | 2.2% |
| Cardiac Disorders | ||
| Palpitation | 1.2% | 1.8% |
| Chest Pain | 1.2% | 3.8% |
| Arrhythmia | - | 1.1% |
| Myocardial Infarction | <1% | 1.3% |
| ADVERSE EVENT | INCIDENCE |
|---|
| Short Term* (n=665) | Long Term** (n=450) | |
|---|---|---|
| Psychiatric Disorders | ||
| Insomnia | 1.2% | 1.3% |
| Anxiety | 1.1% | <1% |
| Depression | <1% | 3.1% |
| Decreased Libido | <1% | 2.7% |
| Infections and Infestations | ||
| Urinary Tract Infection | 1.2% | 1.1% |
| Reproductive System and Breast Disorder | ||
| Impotence | 1.1% | 4.9% |
| Prostatic Disorder | <1% | 1.8% |
| Ejaculation Failure | <1% | 1.1% |
| Skin and Subcutaneous Tissue Disorders | ||
| Increased Sweating | 1.1% | <1% |
| Dermatitis | - | 1.3% |
| Rash | <1% | 1.3% |
| Renal and Urinary Disorders | ||
| Urinary Retention | <1% | 1.6% |
| Hematuria | <1% | 1.8% |
| Ear and Labyrinth Disorders | ||
| Tinnitus | <1% | 1.3% |
* Placebo-controlled clinical trials; treated with doxazosin from 1-203 days.
** Open label extension of 3 placebo controlled clinical trials; treated for up to 50 months.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Short-term controlled clinical trials:
The following other AEs occurred in normotensive or hypertensive patients with BPH with an incidence of <1% in short-term controlled clinical trials (n=665):
Blood and Lymphatic Disorders: lymphadenopathy
Cardiac Disorders: angina, bradycardia, myocardial infarction, tachycardia
Ear and Labyrinth Disorders: earache, tinnitus
Eye Disorders: cataract, conjunctivitis, eye pain, visual field defect
Gastrointestinal Disorders: constipation, flatulence, gingivitis, melena, vomiting
General Disorders and Administration Site Conditions: allergy, asthenia, fever, influenza like symptoms, malaise, rigors, sudden death
Infections and infestations: fungal infection, sepsis, upper respiratory tract infection, viral infection
Metabolism and Nutrition Disorders: gout, hyperglycemia, increased appetite, weight increase
Musculoskeletal and Connective Tissue Disorders: arthralgia, arthritis, hernia, leg cramps, myalgia, tendon disorder
Neoplasms Benign, Malignant and Unspecified: carcinoma
Nervous System Disorders: amnesia, ataxia, depersonalization, hypertonia, hypoesthesia, paresthesia, speech disorder, syncope
Psychiatric Disorders: abnormal thinking, confusion, decreased libido, depression, emotional lability, impaired concentration, nervousness, paroniria
Renal and Urinary Disorders: abnormal urine, cystitis, dysuria, hematuria, micturition disorder, renal pain, urinary incontinence, urinary retention
Reproductive System and Breast Disorder: ejaculation failure, epididymitis, genital pruritus, prostatic disorder
Respiratory, Thoracic and Mediastinal Disorders: bronchitis, bronchospasm, coughing, epistaxis, pneumonia, rhinitis, sinusitis
Skin and Subcutaneous Tissue Disorders: aggravated psoriasis, dry skin, eczema, erythematous rash, maculopapular rash, pallor, pruritus, rash, urticaria
Special Senses: taste perversion
Vascular Disorders: flushing, hot flushes, postural hypotension, subarachnoid haemorrhage
Long-term controlled clinical trials:
The following other AEs occurred in normotensive or hypertensive patients with BPH with an incidence of <1% in long-term controlled clinical trials (n=450):
Cardiac Disorders: abnormal ECG, angina pectoris, atrial fibrillation, cardiac failure, extra systoles, myocardial ischemia, tachycardia
Ear and Labyrinth Disorders: deafness, earache, otitis media
Eye Disorders: conjunctivitis, diplopia, eye abnormality, eye pain, myopia, visual field defect
Gastrointestinal Disorders: diverticulitis, dry mouth, enlarged abdomen, esophagitis, flatulence, gastric ulcer, melena, rectal haemorrhage, tenesmus, tongue disorder, tooth disorder, tooth hypoplasia, vomiting
General Disorders and Administration Site Conditions: allergic reaction/allergy, fever, malaise, rigor
Hepatobiliary Disorders: cholelithiasis
Infections and Infestations: fungal infection, herpes simplex, herpes zoster
Metabolism and Nutrition Disorders: dehydration, hyperglycemia, hyperuricemia, increased appetite, SGOT increase, SGPT increase, weight increase
Musculoskeletal and Connective Tissue Disorders: arthritis, myalgia, polymyalgia rheumatica
Neoplasms Benign, Malignant and Unspecified: breast neoplasm, carcinoma, pulmonary carcinoma
Nervous System Disorders: amnesia, convulsions, depersonalization, encephalopathy, hypokinesia, migraine, syncope
Psychiatric Disorders: abnormal thinking, anxiety, impaired concentration, nervousness
Renal and Urinary Disorders: abnormal urine, cystitis, dysuria, oliguria, polyuria, urinary incontinence
Reproductive System and Breast Disorder: abnormal semen, epididymitis, perineal pain, sexual dysfunction
Respiratory, Thoracic and Mediastinal Disorders: bronchitis, epistaxis, pharyngitis, rhinitis
Skin and Subcutaneous Tissue Disorders: increased sweating, maculopapular rash, nail disorder, photosensitivity reaction, pruritus, purpura, seborrhea, skin disorder, skin hypertrophy, urticaria
Vascular Disorders: aggravated hypertension, aneurysm, cerebrovascular disorder/accident, flushing, hypertension, intermittent claudication
Data from long-term (≤50 months), open BPH studies (n=450) indicate higher rates of dizziness in younger hypertensive (27%) and normotensive (22%) patients, impotence in younger hypertensive (8%) patients, and discontinuation rates in patients due to AEs (16.7%) compared to data from short-term placebo-controlled BPH studies (n=665).
Uncontrolled Trials and Post-Marketing Experience
The following additional AEs have also been reported in patients with essential hypertension and in normotensive or hypertensive patients with BPH: cholestasis, ejaculation disorders such as retrograde ejaculation, gynecomastia, hepatitis, Intraoperative Floppy Iris Syndrome (see PRECAUTIONS, Ophthalmologic), jaundice, parosmia, priapism, renal calculus.
Laboratory Abnormalities
No clinically relevant adverse effects were noted on serum potassium, serum glucose, uric acid, blood urea nitrogen (BUN) or creatinine. Decreases in white blood cells, neutrophils, platelets (see WARNINGS), hemoglobin and hematocrit have been reported. Abnormal liver function tests have occurred.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
No data are available regarding overdosage with TEVA-DOXAZOSIN (doxazosin mesylate) in humans.
Should administration of TEVA-DOXAZOSIN lead to hypotension, support of the cardiovascular system is of first importance. Restoration of blood pressure and normalization of heart rate may be accomplished by keeping the patient in the supine position. If this measure is inadequate, shock should first be treated with volume expanders. If necessary, vasopressors should be used. Renal function should be monitored and supported as needed. As doxazosin mesylate is highly protein bound, dialysis may not be of benefit.
DOSAGE AND ADMINISTRATION
Dosage must be individualized. Doxazosin may be administered either in the morning or the evening.
The absorption of TEVA-DOXAZOSIN (doxazosin mesylate) is not affected by food.
When TEVA-DOXAZOSIN is being added to existing antihypertensive therapy, the patient should be carefully monitored for the occurrence of hypotension (see WARNINGS – Syncope and “First Dose” Effect). If a diuretic or other antihypertensive agent is being added to TEVA-DOXAZOSIN regimen, reducing the dose of TEVA-DOXAZOSIN and retitration with careful monitoring may be necessary.
If TEVA-DOXAZOSIN administration is discontinued for several days or longer, therapy should be reinstituted using the initial dosing regimen.
Hypertension -1-16 mg Once Daily
The initial dose of TEVA-DOXAZOSIN in patients with hypertension is 1 mg given once daily and this dose should not be exceeded. This starting dose is intended to minimize postural hypotensive effects. The maximum reduction in blood pressure normally occurs between 2 - 6 hours after a dose.
The dose may be slowly increased to achieve the desired blood pressure response. The usual dose range is 1 - 8 mg once daily. The maximum recommended daily dose is 16 mg once daily.
Increases in dose >4 mg increased the likelihood of excessive postural effects including syncope, postural dizziness/vertigo and postural hypotension. At a titrated dose of 16 mg once daily, the frequency of postural effects is about 12% compared to 3% for placebo.
Benign Prostatic Hyperplasia -1-8 mg Once Daily
The initial dosage of TEVA-DOXAZOSIN is 1 mg given once daily (see WARNINGS – Syncope and “First Dose” Effect). Depending on the individual patient's urodynamics and BPH symptomatology, dosage may then be increased to 2 mg and thereafter to 4 mg and 8 mg once daily, the maximum recommended dose. The recommended titration interval is 1-2 weeks. Blood pressure should be evaluated routinely in these patients.
Doxazosin should be discontinued if the drug has been increased to the maximum tolerated dose and improvement in urinary flowmetry is <25%, or if doxazosin side effects are more bothersome than BPH symptoms or if the patient develops a urinary complication secondary to BPH while on doxazosin therapy.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Center. |
PHARMACEUTICAL INFORMATION
Drug Substance
Common Name: Doxazosin mesylate
Chemical Name: 1-(4-Amino-6,7-dimethoxy-2-quinazolinyl)-4-(1,4-benzodioxan-2-ylcarbonyl)piperazine methanesulfonate
Structural Formula:
N N CH3O CH3O NH2 N N O O O CH3SO3H.
Molecular Formula: C23H25N5O5·CH4O3S
Molecular Weight: 547.6
Description: Doxazosin mesylate is a white to off-white crystalline solid of uniform appearance. It is freely soluble in dimethylsulphoxide, soluble in dimethylformamide, slightly soluble in methanol, ethanol, and water (0.8% w/v at 25°C), and very slightly soluble in acetone and methylene chloride. The pKa of the doxazosin moiety is 6.93 at 25°C and the melting point of doxazosin mesylate is 273.7°C.
Composition:
TEVA-DOXAZOSIN (doxazosin mesylate) Tablets are formulated to contain doxazosin mesylate equivalent to 1, 2 and 4 mg of doxazosin.
The following excipients are used in the manufacture of TEVA-DOXAZOSIN Tablets: microcrystalline cellulose, lactose, pregelatinized starch, sodium starch glycolate, magnesium stearate, and sodium lauryl sulphate.
STABILITY AND STORAGE RECOMMENDATIONS
TEVA-DOXAZOSIN (doxazosin mesylate) Tablets are packaged in white high density polyethylene bottles and are stored at controlled room temperature between 15° to 30°C.
AVAILABILITY
TEVA-DOXAZOSIN (doxazosin mesylate) tablets are available as:
1 mg: white round, scored tablet, engraved with N/N on scored side and C01 on the other.
2 mg: white, capsule-shaped, scored tablet, engraved 2 “N’s” and a vertical scoreline on one side and 2 on the unscored side.
4 mg: white, modified diamond-shaped, scored tablet, engraved 2 “N’s” and a vertical scoreline on one side and 4 on the unscored side.
Available in white high density polyethylene bottles of 100, 500 and 1000 tablets.
PHARMACOLOGY
Animal Pharmacology - In Vivo
In anaesthetized cats, doxazosin caused adrenaline reversal and was more effective in antagonizing pressor responses to phenylephrine (ED50=0.06 mg/kg, i.v.) than to noradrenaline, (ED50 <10 mg/kg, i.v.) indicating selective effect on post-junctional α1- as opposed to α2-adrenoceptors. This was confirmed by the lack of effect of doxazosin on the α2-mediated pressor responses induced by α-methylnoradrenaline. The lack of effect of doxazosin on prejunctional α2-adrenoceptors was confirmed in anaesthetized dogs.
Animal Pharmacology - In Vitro
In the perfused isolated rabbit ear artery and in the rabbit pulmonary artery rings, doxazosin had a selective effect on post-synaptic α1-adrenoceptors. The superfused rabbit pulmonary artery preparation was used to show that doxazosin is highly selective (pre-synaptic activity EC20=2 x 10⁻⁵M vs post-synaptic activity EC20=2.4 x 10⁻⁸M); for the post-as opposed to the pre-junctional α receptors in this tissue.
Miscellaneous Actions
At high doses, doxazosin increased both alcohol and pentobarbitone sleeping time in mice and may possess mild CNS sedative activity per se, increased basal gastric acid secretion and gastrointestinal motility in rats, and had antidiuretic activity in normotensive rats and dogs.
Human Pharmacology
Hypertension
A comparison of the blood pressure lowering effect of doxazosin mesylate in patients ≥65 years old (n=204), and those <65 years old (n=1,344) show similar falls in blood pressure. The changes in standing systolic/diastolic pressures were -15/-12 mm Hg for the patients ≥65 years old and -13/-11 mm Hg for the patients <65 years old.
Pharmacokinetic studies at steady state in hypertensive patients given doxazosin doses of 2-16 mg once daily showed linear kinetics and dose proportionality. In two studies, following the administration of 2 mg orally once daily, the mean accumulation ratios (steady state AUC vs first dose AUC) were 1.2 and 1.7.
Benign Prostatic Hyperplasia (BPH)
In three placebo-controlled studies of 14-16 weeks duration obstructive symptoms (hesitation, intermittency, dribbling, weak urinary stream, incomplete emptying of the bladder) and irritative symptoms (nocturia, daytime frequency, urgency, burning) of BPH were evaluated at each visit by patient-assessed symptom questionnaires. The bothersomeness of symptoms was measured with a modified Boyarsky questionnaire. Symptom severity/frequency was assessed using a modified Boyarsky questionnaire or an AUA-based questionnaire. Uroflowmetric evaluations were performed at times of peak (2-6 hours post-dose) and/or trough (24 hours post-dose) plasma concentrations of doxazosin mesylate.
The results from the three placebo-controlled studies (N=609) showing significant efficacy with 4 mg and 8 mg doxazosin are summarized in Table 3. In all three studies, doxazosin mesylate resulted in statistically significant relief of obstructive and irritative symptoms compared to placebo. Statistically significant improvements of 2.3-3.3 mL/sec in maximum flow rate were seen with doxazosin mesylate in Studies 1 and 2, compared to 0.1-0.7 mL/sec with placebo.
Table 3: Summary of effectiveness data in placebo controlled trials.
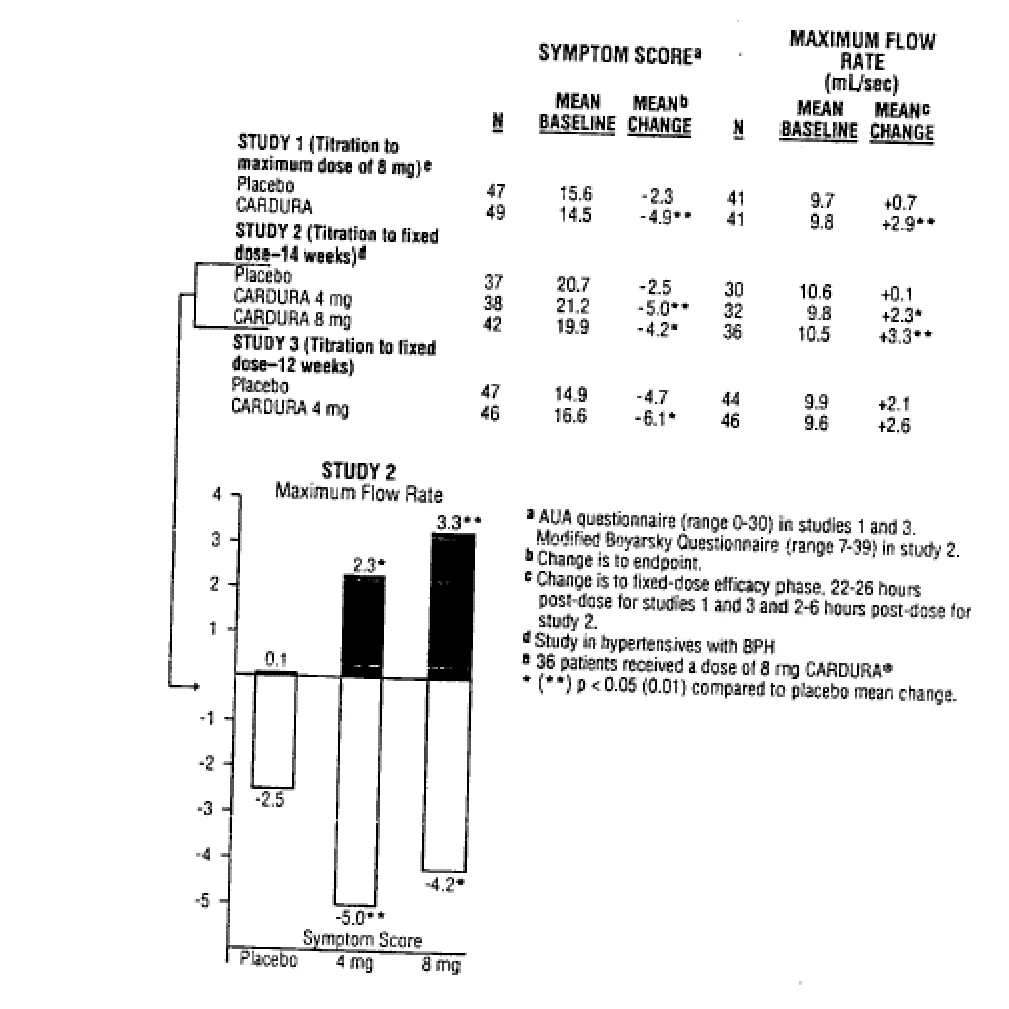
In one fixed dose study (study 2) doxazosin mesylate therapy (4-8 mg, once daily) resulted in a significant and sustained improvement in maximum urinary flow rate of 2.3-3.3 mL/sec (Table 3) compared to placebo (0.1 mL/sec). In this study, the only study in which weekly evaluations were made, significant improvement with doxazosin mesylate vs placebo was seen after 1 week. The proportion of patients who responded with a maximum flow rate improvement of ≥3 mL/sec was significantly larger with doxazosin mesylate (34-42%) than placebo (13-17%). A significantly greater improvement was also seen in average flow rate with doxazosin mesylate (1.5 mL/sec) than with placebo (0.2 mL/sec).
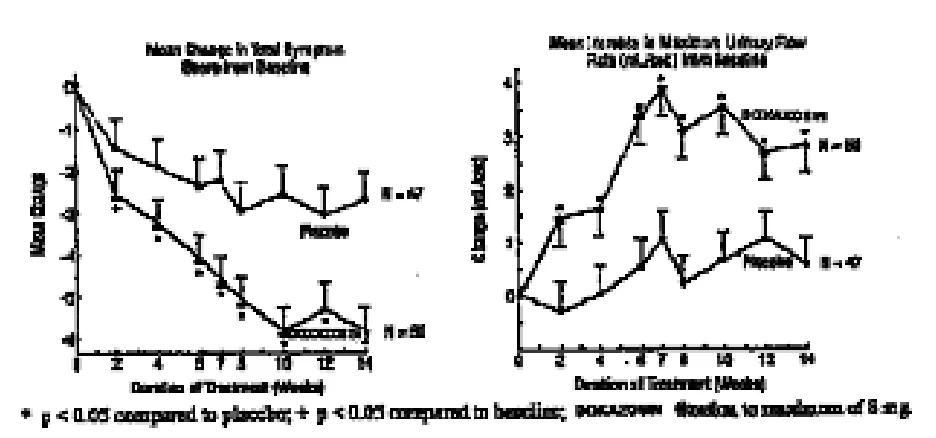
The onset and time course of symptom relief and increased urinary flow from study 1 are illustrated in Figure 1.
Figure 1:
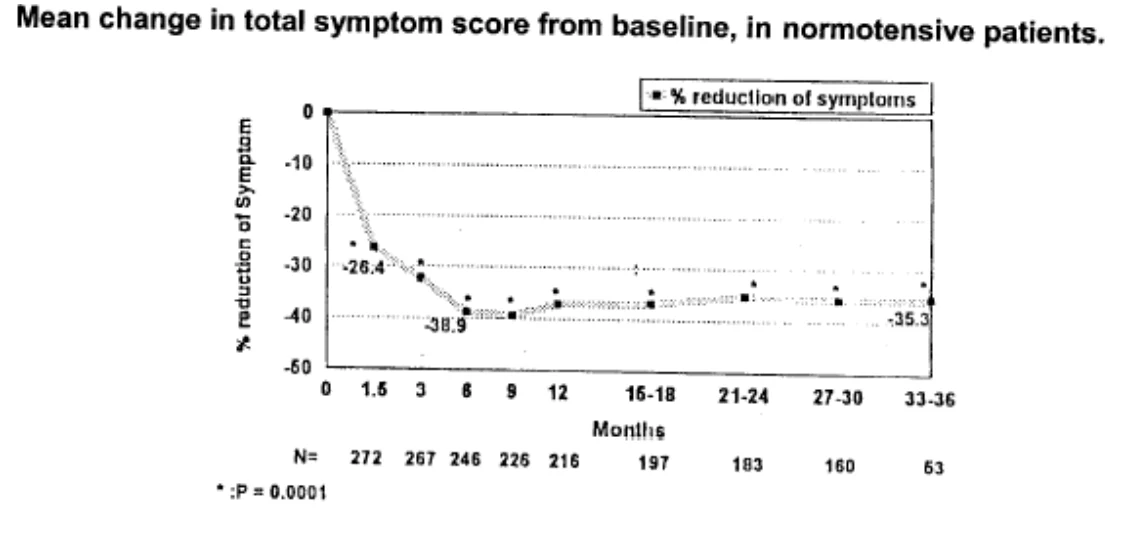
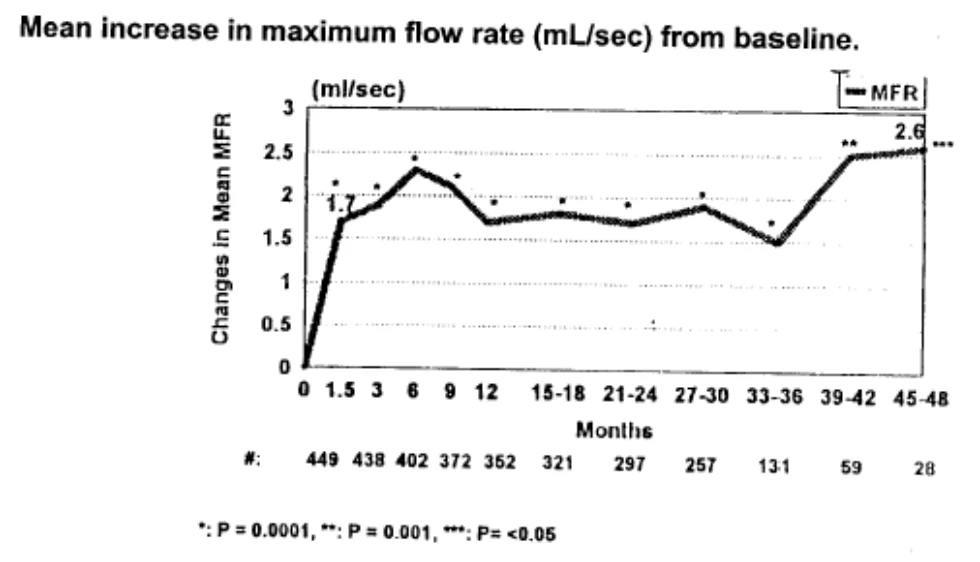
In BPH patients (n=450) treated for ≤4 years in open-label studies, doxazosin mesylate therapy resulted in significant improvement above baseline in urinary flow rates and BPH symptoms. The significant effects of doxazosin mesylate were maintained over the entire treatment period, as shown in figure 2.
Figure 2:
Although blockade of α1 adrenoceptors also lowers blood pressure in hypertensive patients with increased peripheral vascular resistance, doxazosin mesylate treatment of normotensive men with BPH did not result in a clinically significant blood pressure lowering effect (Table 4). The proportion of normotensive patients with a sitting systolic blood pressure <90 mm Hg and/or diastolic blood pressure <60 mm Hg at any time during treatment with doxazosin mesylate 1-8 mg once daily was 6.7% and not significantly different from that with placebo (5%).
Table 4: Mean changes in blood pressure from baseline to the mean of the final efficacy phase in normotensive (diastolic BP <90 mm Hg) in all double-blind, placebo-controlled U.S. studies.
| Group | N | Baseline | Mean Change | |
| Systolic BP | Doxazosin mesylate | 183 | 128.8 | -4.9* |
| Sitting (mmHg) | Placebo | 85 | 128.4 | -1.4 |
| Diastolic BP | Doxazosin mesylate | 183 | 79.6 | -2.4* |
| Sitting (mmHg) | Placebo | 85 | 79.2 | -1.2 |
* p < 0.05 compared to placebo
TOXICOLOGY
Acute Toxicology
| Species | Sex | Route | Ld50 (confidence limits) Mg/base/kg |
| Mice | M | p.o. | >1,000 |
| F | p.o. | >1,000 | |
| Rats | M | p.o. | >1,200 |
| F | p.o. | >1,200 |
After oral administration of the drug the animals displayed vulval opening (females), ptosis and prostration, with the signs lasting ≤2 days depending on dose level. The 3 deaths which occurred were between days 2 and 5.
| Toxicology | |||||
|---|---|---|---|---|---|
| Subacute and Chronic Toxicity | |||||
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
| rat | oral (gavage) | 0 5 10 20 | 10 or 20M +10 or 20F | 14 weeks followed by 4 weeks drug withdrawal | Dose-related ptosis, listlessness, subcutaneous vasodilation, vaginal dilatation & descended testes; reductions in plasma potassium & glucose levels in males at the end of the study which disappeared after withdrawal of treatment. Necropsy or histopathological examination revealed no drug related abnormalities. |
| rat (Japanese study) | oral (gavage | 0 20 60 150 300 600 | 20M 20F | 1 month | At all dose levels: dose related decrease in spontaneous movement, depression, ptosis, prostration, descent of testes & opening of vagina. At 150, 300 & 600 mg/kg/day dose-related growth inhibition was noted. At 600 mg/kg/day - decrease in food consumption & urinary incontinence was seen. An increase in hemoglobin, hematocrit, erythrocytes & neutrophils & a decrease in lymphocytes were also reported. Mortality occurred in 16/20 males & in 13/20 female rats within one month. Elevation in the SGOT & SGPT levels was seen at 600 & 300 mg/kg/day & at 150 mg/kg/day (males). The elevations of the SGOT & SGPT generally corresponded to the severity of the hepatic lesions. An increase in total bilirubin was noted at 300 & 600 mg/kg/day & at 150 mg/kg/day (males). Histological examination showed drug related changes at dose levels of 150 mg/kg & higher; dose related hepatic cell degeneration & necrosis in males; myocardial necrosis/fibrosis at 300 & 600 mg/kg & organ changes similar to those seen in wasting conditions due to malnutrition. |
| dog | oral | 0 1 4 16 | 3M + 3F | 13 weeks | At all doses: lowered blood pressure. Necropsy or histopathological examination revealed no drug related abnormalities. |
| rat | oral (diet) | 0 5 20 80 | 20M + 20F | 6 months | Ptosis, vasodilation, sedation, opening of the vagina & descended testes; at 80 mg/kg in females there was a reduction in the growth & food intake. Drug-related changes included decreases of plasma glucose & potassium & either an increase (at 5 mg/kg) or decrease (at 80 mg/kg) of total proteins, at months 3 & 6. Also at 5 & 20 mg/kg hemoconcentration & at 80 mg/kg hemodilution were observed. At 80 mg/kg in males there was an increase in the incidence of myocardial necrosis (16/20 treated vs 7/20 control rats). |
Toxicology
| Subacute and Chronic Toxicity |
|---|
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| rat | oral | 0 5 20 50 100 | 30M + 30F | 12 months (interim sacrifice at 3 months & post-treatment sacrifice at 3 months) | At 20, 50 & 100 mg/kg in males there was impairment of body weight gain. At 20 & 50 mg/kg a decrease in urinary volume was noted. Post-mortem showed an increase in heart weights of males at 100 mg/kg & of spleen weight of males at the 50 & 100 mg/kg dose levels & in all female groups. Hepatic single cell degeneration & necrosis was observed at 50 & 100 mg/kg after 3 months & at 100 mg/kg after 12 months. |
| rat (age 12 months old at start of study) | oral | 0 10 20 40 | 24 M | 12 months | At 40 mg/kg there was an adverse effect on body weight & in the 2nd half of the study, an increase in mortality. There was also an increase of myocardial fibrosis (22/23 rats at 40 mg/kg vs 15/24 in control rats). At 20 mg/kg & 40 mg/kg testicular atrophy was seen. The non-cardiotoxic dose level was 20 mg/kg. |
| dog | oral | 0 1 5 20 | 4M + 4F | 12 months | Dose related ptosis, sedation, asthenia, vasodilation, dacryorrhea, salivation & relaxation of nictitating membrane. Swollen vulvae of most of the treated females were seen. At 20 mg/kg decrease in body weight, lowered blood pressure & raised heart rate were shown to occur. At the end of the study at 5 & 20 mg/kg most dogs showed a persistent pupillary constriction which diminished within days of cessation of treatment. All treated dogs showed a bilateral prominence of the nictitating membrane. At 20 mg/kg, a swelling of the optic disc was seen at 6 months (2/8) & 12 months (5/8). There was also an increase in plasma cholesterol at the end of the study. There was no evidence of drug-related effect on organ weights, macroscopic or microscopic findings. |
Special Study (Ophthalmology Study) | |||||
| dog | oral | between 25 & 50 mg/kg (according to tolerance) | 2M + 2F | 28 days | The expected pupillary constriction & relaxation of the nictitating membrane was observed; there were no changes in the optic disc. Ocular reflexes were normal. The effects regressed over 2-3 weeks post-treatment. |
| Mutagenicity | |||||||||
| STUDY | TEST ORGANISM | DOSE | ROUTE | MAJOR FINDING | |||||
| Ames Test (modified: Quantitative Plate Assay & Metabolic Activation Assay with hepatic microsomes | Salmonella Typhimurium: strains TA 1535, TA 1538, TA 98 & TA 100 | 2.0-0.002 mg/plate for TA 98 & TA 100 1.0-0.01 mg/plate for TA 1535 & TA 1538 | in vitro | No evidence of mutation frequency. | |||||
Ellenberger & Mohn: Forward Mutation (galactose locus) Assay | Escherichia coli 341/113 | 10 to 0.1 mg/mL of culture medium | in vitro | No evidence for mutagenicity observed. | |||||
Slater et al: Assays utilizing DNA Repair deficient E. coli | Pol A (E. coli p3478 Pol A+ (E. coli W3110) | 5 and 10 mg/disc | in vitro | No evidence of DNA damaging activity. However, this result is somewhat impaired by the absence of any cytotoxic activity on either the Pol A+ or Pol A strain. | |||||
Quantitative Plate Assay of Mouse Urine | Salmonella Typhimurium: TA1535, TA98, TA100 TA1537 & TA1538 | 1.0 to 0.05 mg/kg | in vitro i.p. | No mutagenic activity was seen. | |||||
In-vivo Cytogenetics | mouse-bone marrow | 1 mg/kg (single dose) 0.5 mg/kg/day (for 5 days) | in vivo i.p. s.c. | No indication of chromosome breakage or mutagenicity observed. | |||||
In-vitro Cytogenetics | human lymphocytes | 10 g/mL of culture medium | in vitro | No evidence of induced-chromosome damage observed. | |||||
Mutagenicity studies revealed no drug or metabolite related effects at either chromosomal or subchromosomal levels.
Carcinogenicity
Chronic dietary administration (≤24 months) of doxazosin mesylate at maximally tolerated concentrations (highest dose 40 mg/kg/day) revealed no evidence of carcinogenicity in rats.
Doxazosin was also administered for ≤18 months in the diet of mice at doses ≤40 mg/kg/day with no evidence of carcinogenicity observed. This mouse study however, was compromised by the failure to use a maximally tolerated dose of doxazosin. A subsequent 24-month dietary study of doxazosin mesylate at maximally tolerated concentrations (highest dose 120 mg/kg/day), showed no carcinogenic effect in mice. The highest doses evaluated in the rat and mouse studies are associated with AUCs (a measure of systemic exposure) that are 8x and 4x, respectively, the human AUC at a dose of 16 mg/day.
| Reproduction and Teratology | ||||||||||
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMAL PER GROUP | DURATION | FINDINGS | |||||
| General Fertility | ||||||||||
| rat (Charles River CD) | oral | 0 5 10 20 | 10 or 20M +40F | Males 60-70 days prior to mating. Females 14 days prior to mating & throughout gestation | Male fertility At 10 & 20 mg/kg an effect on male fertility was observed: reduction in both the copulation frequency (~17%) & in the proportion of these copulations resulting in pregnancy (~23%). There was no evidence of teratogenicity, no effect on parturition, fetal growth or development, nor on postnatal development of reproductive performance of the offspring. | |||||
| Male Fertility Study (reversibility) | ||||||||||
| rat (Charles River CD) | oral | 0 20 | 25M | Males (25 group) dosed for 13, 27 or 62 days. Each allowed to mate with untreated female, at least 2 times, for up to 7 days & nights. Females sacrificed on day 14 post-copulation. | No effect on copulation frequency. For the duration of treatment (males): reduction in the proportion of copulations resulting in pregnancy (i.e., fewer, 70-78%, females became pregnant vs controls, 92-100%). This effect was reversible within 2 weeks of drug withdrawal. | |||||
| Teratology | ||||||||||
| rabbit (New Zealand White) | oral | 0 10 20 40 | 19F | Days 7 to 18 of gestation | No effects were observed. | |||||
| Peri- and Post-Natal Study | ||||||||||
| rats (Charles River CD) | oral | 0 2.5 10 40 | 20F | Day 15 of gestation until parturition & throughout lactation. | Dams: Ptosis, vasodilation & vaginal opening. At 10 & 40 mg/kg, increased weight gain during gestation. At 40 mg/kg increased weight gain during lactation. Food intake also increased during gestation. Pups: At 40 mg/kg/day: reduced body weights during lactation. Delayed development as evidenced by appearance of reflexes & incisors & opening of the auditory meatus & the palpebrae. The open-field test also revealed diminished defecation in the high dose group. | |||||
Studies in rats showed reduced fertility in males treated with doxazosin at oral doses of 20 (but not 5 or 10) mg/kg/day, about 4x the AUC exposures obtained with a 12 mg/day human dose. This effect was reversible within 2 weeks of drug withdrawal.
REFERENCES
- 1. Alabaster VA, Davey MJ. The alpha-1 adrenoceptor antagonist profile of doxazosin; preclinical pharmacology. Br J Clin Pharmacol 1986;21(Suppl 1):9s-17s.
- 2. Barry AC, Kirby RS. Doxazosin: Antihypertensive effect in hypertensive vs. normotensive BPH patients with BPH. AJH 1993;6(5 Pt. 2):94A(Abstract 1101).
- 3. Bartels ACC, de Vries PMJM, Oe LP, et al. Doxazosin in the treatment of patients with mild or moderate hypertension and mild or moderate renal insufficiency. Am Heart J 1988;116:1772-1777.
- 4. Castrignano R, D'Angelo M, Pati T, et al. A single-blind study of doxazosin in the treatment of mild to moderate essential hypertensive patients with concomitant non-insulin-dependent diabetes mellitus. Am Heart J 1988;116:1778-1784.
- 5. Cox DA, Leader JP, Milson JA, Singleton W. The antihypertensive effect of doxazosin: a clinical overview. Br J Clin Pharmacol 1986;21(Suppl 1):83s-90s.
- 6. Cubeddu LX, Pool JL, Bloomfield R. Effect of doxazosin monotherapy on blood pressure and plasma lipids in patients with essential hypertension. Am J Hypertens 1988;1:158-167.
- 7. de Leeuw PW, Van Es PN, De Bos R, Birkenhager WH. Acute renal effects of doxazosin in man. Br J Clin Phamacol 1986;21 (Suppl 1):41s-43s.
- 8. Elliott HL, Meredith PA, Vincent J, et al. Clinical pharmacological studies with doxazosin. Br J Clin Pharmacol 1986;21:27S-31S.
- 9. Englert RG, Mauersberger H. A single-blind study of doxazosin in the treatment of essential hypertension when added to nonresponders to angiotensin-converting enzyme inhibitor therapy. Am Heart J 1988,116:1826-1832.
- 10. Frick MH, Cox DA, Himanen P, et al. Serum lipid changes in a one-year, multicenter, double-blind comparison of doxazosin and atenolol for mild to moderate essential hypertension. Am J Cardiol 1987;59:61G-67G.
- 11. Gillenwater JY, Conn RL, Chrysant SG, Roy J, et al. Doxazosin for the treatment of benign prostatic hyperplasia in patients with mild to moderate essential hypertension: a double-blind, placebo-controlled, dose-response multicenter study. J Urol 1995;154:110-115.
- 12. Gillin AG, Fletcher MB, Horvath JS, Hutton BF, Bautovich GJ, Tiller DJ. Comparison of doxazosin and atenolol in mild hypertension, and effects on exercise capacity, hemodynamics and left ventricular function. Am J Cardiol 1989;63:950-954.
- 13. Graham RM. Selective alpha-1 adrenergic antagonists: therapeutically relevant antihypertensive agents. Am J Cardiol 1984;53(3):16A-20A.
- 14. Hayduk K, Schneider HT. Antihypertensive effects of doxazosin in systemic hypertension and comparison with terazosin. Am J Cardiol 1987; 59:95G-98G.
- 15. Holme I, Fauchald P, Rugstad HE, Stokke HP. Preliminary results of the Norwegian doxazosin postmarketing surveillance study: a twelve-week experience. Am Heart J 1991;121(Number 1, Part 2):2260-2267.
- 16. Horder M-H, Barlage U. Double-blind comparative study of doxazosin and captopril. Muench Med Wschr 1988; 130:819-822.
- 17. Kaplan SA, Meade D'Alisera P, Quiñones S, Solda KA. Doxazosin in physiologically and pharmacologically normotensive men with benign prostatic hyperplasia. Urology 1995;46(4):512-517.
- 18. Kaye B, Cussans NJ, Faulkner JK, Stopher DA, Reid JL. The metabolism and kinetics of doxazosin in man, mouse, rat and dog. Br J Clin Pharmacol 1986;21(Suppl 1):19s-25s.
- 19. Kirby RS, Chapple CR, Christmas TJ. Doxazosin: Minimal blood pressure effects in normotensive BPH patients. J Urol 1993; 149(4):434A (Abstract 886).
- 20. Kirby RS, Chapple CR, Sethia K, et al. Morning vs evening dosing with doxazosin in benign prostatic hyperplasia: efficacy and safety. Prostatic Cancer and Prostatic Diseases 1998;1:163-171.
- 21. Langdon CG, Packard RS. Doxazosin in hypertension: Results of a general practice study in 4809 patients. BJCP 1994;48(6):293-298
- 22. Lepor H, Baumann M, Shapiro E. Binding and functional properties of doxazosin in the human prostate adenoma and canine brain. The Prostate 1990;16:29-38.
- 23. Lund-Johansen P, Omvik P, Haugland H. Acute and chronic haemodynamic effects of doxazosin in hypertension at rest and during exercise. Br J Clin Pharmacol 1986;21:45S-54S.
- 24. Scott PJW, Hosie J, Scott MGB. A double-blind and crossover comparison of once-daily doxazosin and placebo with steady-state pharmacokinetics in elderly hypertensive patients. Eur J Clin Pharmacol 1988;34:119-123.
- 25. Smyth P, Pringle S, Jackson G, et al. 24 hour control of blood pressure by once daily doxazosin: a multicentre double-blind comparison with placebo. Eur J Clin Pharmacol 1988;34:613-618.
- 26. Torvick D, Madsbu H-P. An open one-year comparison of doxazosin and prazosin for mild to moderate essential hypertension. Am J Cardiol 1987;59:68G-72G.
- 27. Torvick D, Madsbu H-P. Multicenter 12 week double-blind comparison of doxazosin, prazosin and placebo in patients with mild to moderate essential hypertension. Br J Clin Pharmacol 1986;(21 Suppl 1):69s.
- 28. Trost BN, Wiedmann P, Riesen W, et al. Comparative effects of doxazosin and hydrochlorothiazide on serum lipids and blood pressure in essential hypertension. Am J Cardiol 1987;59:99G-104G.
- 29. van Zweften P, Timmermans P, van Brummelen P. Role of alpha adrenoceptors in hypertension and antihypertensive drug treatment. Am J Med 1984;(77):17.
- 30. Wessels F. Double-blind comparison of doxazosin and enalapril in patients with mild or moderate essential hypertension. Am Heart J 1991;121 (Number 1, Part 2):299-303.
- 31. Young RA, Brogden RN. Doxazosin: A review of its pharmacodynamic and pharmacokinetic properties, and therapeutic efficacy in mild or moderate hypertension. Drugs 1988;35:525-541.
- 32. Product Monograph for Cardura 1-2-4™ Tablets. Pfizer Canada Inc, Kirkland, Quebec. April 4, 2017, Control# 201486.
- 33. A two-way, single-dose, crossover bioavailability study of doxazosin mesylate 1 mg tablets in fasting volunteers. Completed March 01, 1999. Data on file at Teva Canada Limited.