


Product Monograph - Teva-Moxifloxacin (Teva Canada, 0.5 %)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Ophthalmic | Solution / 0.5% w/v | Boric acid, sodium chloride and water for injection. May also contain hydrochloric acid and/or sodium hydroxide to adjust pH. |
INDICATIONS AND CLINICAL USE
TEVA-MOXIFLOXACIN (moxifloxacin hydrochloride) ophthalmic solution is indicated for the treatment of patients 1 year of age and older with bacterial conjunctivitis caused by susceptible strains of the following organisms:
Aerobic, Gram-Positive:
Staphylococcus aureus
Staphylococcus epidermidis
Staphylococcus haemolyticus
Staphylococcus hominis
Streptococcus pneumoniae
Streptococcus viridans group
Aerobic, Gram-Negative:
Acinetobacter species
Haemophilus influenzae
CONTRAINDICATIONS
TEVA-MOXIFLOXACIN (moxifloxacin hydrochloride) ophthalmic solution is contraindicated in patients with a history of hypersensitivity to moxifloxacin, to other quinolones, or to any of the components in this medication (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
WARNINGS AND PRECAUTIONS
For ocular use only.
TEVA-MOXIFLOXACIN (moxifloxacin hydrochloride) ophthalmic solution is not for injection into the eye.
TEVA-MOXIFLOXACIN (moxifloxacin hydrochloride) ophthalmic solution should not be injected subconjunctivally, nor should it be introduced directly into the anterior chamber of the eye.
In patients receiving systemically administered quinolones, serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported, some following the first dose. Some reactions were accompanied by cardiovascular collapse, loss of consciousness, angioedema (including laryngeal, pharyngeal or facial edema), airway obstruction, dyspnea, urticaria, and itching. If an allergic reaction to moxifloxacin occurs, discontinue use of the drug. Serious acute hypersensitivity reactions may require immediate emergency treatment. Oxygen and airway management should be administered as clinically indicated.
Serious and sometimes fatal events, some due to hypersensitivity and some due to uncertain etiology, have been reported in patients receiving therapy with all oral antibiotics. These events may be severe and generally occur following the administration of multiple doses. Clinical manifestations may include one or more of the following: fever, rash or severe dermatologic reactions (e.g. toxic epidermal necrolysis, Stevens-Johnson Syndrome), vasculitis, arthralgia, myalgia, serum sickness, allergic pneumonitis, interstitial nephritis, acute renal insufficiency or failure, hepatitis, jaundice, acute hepatic necrosis or failure, anemia including hemolytic and aplastic, thrombocytopenia including thrombotic thrombocytopenic purpura, leukopenia, agranulocytosis, pancytopenia, and/or other hematologic abnormalities.
General: As with other anti-infectives, prolonged use may result in overgrowth of non-susceptible organisms, including fungi. If superinfection occurs, discontinue use and institute alternative therapy. Whenever clinical judgment dictates, the patient should be examined with the aid of magnification, such as slit-lamp biomicroscopy, and, where appropriate, fluorescein staining.
In general, patients with signs and symptoms of bacterial conjunctivitis should be advised not to wear contact lenses.
Tendon inflammation and rupture may occur with systemic fluoroquinolone therapy including moxifloxacin, particularly in elderly patients and in those treated concurrently with corticosteroids. Treatment with TEVA-MOXIFLOXACIN should be discontinued at the first sign of tendon inflammation.
There are no studies on the effect of ocular administration of moxifloxacin hydrochloride ophthalmic solution on fertility.
TEVA-MOXIFLOXACIN may cause temporary blurred vision or other visual disturbances, which may affect the ability to drive or use machines. If blurred vision occurs at application, the patient must wait until the vision clears before driving or using machinery.
Information for Patients: Avoid contaminating the applicator tip with material from the eye, fingers or other source.
Systemically administered quinolones have been associated with hypersensitivity reactions, even following a single dose. Discontinue use immediately and contact your physician at the first sign of a rash or allergic reaction.
The potential of moxifloxacin hydrochloride ophthalmic solution to produce arthropathy in animals has not been studied. Moxifloxacin and other members of the quinolone class have been shown to cause arthropathy in immature Beagle dogs following oral administration (see TOXICOLOGY).
Drug Interactions: Drug-drug interaction studies have not been conducted with moxifloxacin hydrochloride ophthalmic solution. Moxifloxacin can be chelated by polyvalent ions such as Mg++, A1+++, Fe++ and Zn++. There is limited information available on the concurrent use of moxifloxacin hydrochloride ophthalmic solution and other ophthalmic products.
Following oral administration, no clinically significant drug-drug interactions between theophylline, warfarin, digoxin, oral contraceptives or glyburide have been observed with moxifloxacin. Theophylline, digoxin, probenecid, and ranitidine have been shown not to alter the pharmacokinetics of moxifloxacin. In vitro studies indicate that moxifloxacin does not inhibit CYP3A4, CYP2D6, CYP2C9, CYP2C19 or CYP1A2 indicating that moxifloxacin is unlikely to alter the pharmacokinetics of drugs metabolized by these cytochrome P450 isozymes.
Special Populations
Pregnancy: Since there are no adequate and well-controlled studies in pregnant women moxifloxacin hydrochloride ophthalmic solution should only be used during pregnancy if the potential benefit justifies the potential risk to the fetus.
Moxifloxacin hydrochloride ophthalmic solution has not been studied in pregnant animals. Oral and IV studies in pregnant animals indicated that moxifloxacin is not teratogenic. Decreased fetal birth weights and slightly delayed fetal skeletal development were observed in rats and rabbits following oral and intravenous administration of moxifloxacin, respectively. An increased incidence of smaller fetuses was observed in monkeys following oral dosing (see TOXICOLOGY). When 14C-moxifloxacin was administered orally to pregnant rats, radioactivity penetrated the placenta and was absorbed to a moderate extent by the fetus. The ratio for AUC (0-24 h) for fetal plasma to maternal plasma was 0.656.
As with other members of the quinolone class, moxifloxacin has caused arthropathy in immature Beagle dogs following oral administration. The significance of these findings to humans is unknown (see TOXICOLOGY).
Nursing Mothers: Moxifloxacin is excreted in the breast milk of rats following oral and intravenous administration. Because of the potential for unknown effects from moxifloxacin in infants being nursed by mothers taking TEVA-MOXIFLOXACIN ophthalmic solution, a decision should be made to either discontinue nursing or discontinue the administration of TEVA-MOXIFLOXACIN ophthalmic solution, taking into account the importance of TEVA-MOXIFLOXACIN ophthalmic solution therapy to the mother and the possible risk to the infant (see TOXICOLOGY).
Pediatric Use: The safety and efficacy of moxifloxacin hydrochloride ophthalmic solution in patients less than one year of age has not been established.
The effect of TEVA-MOXIFLOXACIN ophthalmic solution on weight bearing joints has not been assessed. Oral administration of some quinolones, including moxifloxacin, has been shown to cause arthropathy in immature animals (see TOXICOLOGY).
Geriatric Use: No overall differences in safety and effectiveness have been observed between elderly and other adult patients.
ADVERSE REACTIONS
In clinical trials involving 1068 subjects/patients, moxifloxacin hydrochloride ophthalmic solution was administered twice-daily for three days, three-times-daily for four to fourteen days and eight-times-daily for fourteen days. During treatment with moxifloxacin hydrochloride ophthalmic solution, 6.6% (71 out of 1068) subjects/patients experienced treatment-related adverse drug reactions and of these only two (0.2%) discontinued study participation. No serious ophthalmic or systemic adverse reactions related to moxifloxacin hydrochloride ophthalmic solution were reported.
Clinical Trial Adverse Drug Reactions
The most frequently reported treatment-related adverse drug reactions were transient eye irritation (3.9%) (burning and/or stinging) and eye pruritus (1.1%).
Treatment-related adverse drug reactions that occurred at an incidence of 0.1% to less than 1.0% included the following:
Eye disorders: ocular hyperaemia, keratoconjunctivitis sicca, abnormal sensation in eye, ocular discomfort, corneal epithelium defect, conjunctivitis, conjunctival haemorrhage, visual acuity reduced, eyelid oedema, eye pain.
General disorders and administration site conditions: sensation of foreign body.
Investigations: corneal staining, alanine aminotransferase increased.
Nervous system disorders: dysgeusia, headache.
Respiratory, thoracic, and mediastinal disorders: pharyngolaryngeal pain.
Post-Market Adverse Drug Reactions
Adverse reactions identified from spontaneous reporting and subsequent clinical trials are listed below.
Blood and lymphatic system disorders: hemoglobin decreased
Cardiac disorders: palpitations
Eye disorders: anterior chamber cells, asthenopenia, blepharitis, conjunctival edema, corneal deposits, corneal disorders, corneal infiltrates, dry eye, endophthalmitis, erythema of eyelid, eye discharge, eye irritation, eye swelling, keratitis, lacrimination increased, photophobia, punctate keratitis, ulcerative keratitis, vision blurred, visual acuity reduced
Gastrointestinal disorders: nausea, vomiting
Hepatobiliary disorders: gamma-glutamyltransferase increased
Immune system disorders: hypersensitivity NOS
Nervous system disorders: dizziness, paresthesia
Respiratory, thoracic and mediastinal disorders: dyspnea, nasal discomfort
Skin and subcutaneous tissue disorders: erythema, pruritis, rash, urticaria
DOSAGE AND ADMINISTRATION
The recommended dosage regimen for patients one year of age and older is one drop in the affected eye(s) 3 times a day for 7 days.
OVERDOSE
No information is available on overdose of moxifloxacin hydrochloride ophthalmic solution in humans. A topical overdose of TEVA-MOXIFLOXACIN ophthalmic solution may be flushed from the eye(s) with warm tap water.
In an oral (gavage) monkey study, doses of moxifloxacin hydrochloride up to 15 mg/kg/day did not produce any toxicity. This dose is at least 10 times higher than the accidental ingestion of the contents of a 3 mL bottle of moxifloxacin hydrochloride ophthalmic solution by a 10 kg child.
No toxic effects are expected with an ocular overdose of the product, or in the event of accidental ingestion of the contents of one bottle.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Moxifloxacin is a synthetic fluoroquinolone antibacterial agent active in vitro against a broad spectrum of Gram-positive and Gram-negative ocular pathogens, atypical microorganisms and anaerobes.
The antibacterial action of moxifloxacin results from inhibition of topoisomerase II (DNA gyrase) and topoisomerase IV. DNA gyrase is an essential enzyme that is involved in the replication, transcription and repair of bacterial DNA. Topoisomerase IV is an enzyme known to play a key role in the partitioning of the chromosomal DNA during bacterial cell division (see MICROBIOLOGY).
Pharmacokinetics/Pharmacodynamics:
Following topical ocular administration of moxifloxacin hydrochloride ophthalmic solution, moxifloxacin was absorbed into the systemic circulation. Plasma concentrations of moxifloxacin were measured in 21 male and female adult subjects who received bilateral topical ocular doses of moxifloxacin hydrochloride ophthalmic solution every 8 hours for a total of 13 doses. The mean steady-state Cmax and AUC were 2.7 ng/mL and 41.9 ng·hr/mL, respectively. These systemic exposure values were at least 1,600 and 1,000 times lower than the mean Cmax and AUC reported after therapeutic 400 mg oral doses of moxifloxacin. The plasma half-life of moxifloxacin was estimated to be 13 hours. Moxifloxacin is widely distributed in the body and is excreted in feces or urine either unchanged or as glucuronide or sulfate conjugates.
Tear film concentrations were studied in 31 healthy male and female adult volunteers who were administered 1 drop of moxifloxacin hydrochloride ophthalmic solution to both eyes every 8 hours for a total of 10 doses. Mean tear concentrations at 5 minutes following the first and last topical dose were 46.0 and 55.2 µg/mL, respectively. Thereafter, they decline rapidly in a biphasic manner with the means ranging approximately 1 to 4 µg/mL over the 1 to 8 hour sampling period. Pre-dose morning tear concentrations on Days 2 to 4 averaged over 4 µg/mL. Studies conducted in animals indicate penetration into the conjunctiva and ocular tissues with prolonged binding to melanin.
STORAGE AND STABILITY
Store at 2°C - 25°C. Protect from light. Discard 28 days after opening.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Composition: Each mL of TEVA-MOXIFLOXACIN (moxifloxacin hydrochloride) ophthalmic solution contains 5.45 mg moxifloxacin hydrochloride equivalent to 5 mg moxifloxacin base.
TEVA-MOXIFLOXACIN ophthalmic solution contains the following inactive ingredients; sodium chloride, boric acid and water for injection. May also contain hydrochloric acid and/or sodium hydroxide to adjust pH.
TEVA-MOXIFLOXACIN ophthalmic solution is preservative-free, the product is self-preserved.
TEVA-MOXIFLOXACIN ophthalmic solution is isotonic and formulated at pH 6.4-7.2 with an osmolality of approximately 260-320 mOsm/kg.
TEVA-MOXIFLOXACIN ophthalmic solution, 0.5% is supplied as a 3 mL sterile ophthalmic solution in a white plastic bottle with dropper and a tan tamper evident closure cap.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance: Moxifloxacin hydrochloride
Proper Name: Moxifloxacin Hydrochloride
Chemical Name: 1-Cyclopropyl-6-fluoro-1,4-dihydro-8-methoxy-7-[(4aS,7aS)-octahydro-6H-pyrrolo[3,4-b]pyridine-6-yl]-4-oxo-3-quinolone carboxylic acid, monohydrochloride
1-Cyclopropyl-6-fluoro-8-methoxy-7-[(4aS,7aS)-octahydro-6H-pyrrolo[3,4-b]pyridin-6-yl]-4-oxo-1,4-dihydroquinoline-3-carboxylic acid hydrochloride
Structural Formula:
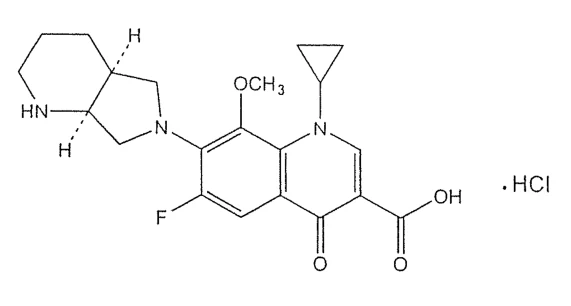
Molecular Formula: C21H24FN3O4•HCl
Molecular Weight: 437.93
Description: Moxifloxacin hydrochloride is light yellow to yellow crystalline powder. Moxifloxacin hydrochloride has a specific optical rotation of -125° to -138°. The pH of moxifloxacin hydrochloride is 3.65 and the pKa is 6.19 and 9.28.
CLINICAL STUDIES
In two, randomized, double-masked, multicenter, controlled trials in which 547 patients dosed with moxifloxacin hydrochloride ophthalmic solution 3 times a day for 4 days, moxifloxacin hydrochloride ophthalmic solution produced clinical cures on day 5 to 6 in 66% to 69% of patients treated for bacterial conjunctivitis. Microbiological success rates for the eradication of the baseline pathogens ranged from 84% to 94% at the test-of-cure visit (day 9). Please note that microbiologic eradication does not always correlate with clinical outcome in anti-infective trials.
DETAILED PHARMACOLOGY
Animal Pharmacokinetics:
Ocular tissue concentrations of moxifloxacin were determined in pigmented rabbits following a single bilateral 30 µL topical administration of 0.3% ophthalmic solution of moxifloxacin (n=3 rabbits sampled at each time point). Mean maximum concentrations (Cmax) in cornea and aqueous humor were 12.5 ± 3.8 µg/g and 1.78 ± 0.39 µg/mL, respectively, and were achieved within 30 minutes after dosing. In iris-ciliary body, a moxifloxacin Cmax of 10.4 ± 5.6 µg/g was observed at 1 hour and declined slowly relative to other tissues, presumably due to binding to melanin pigment, which is characteristic of fluoroquinolones. The accumulation in ocular tissues of moxifloxacin after multiple dosing has not been studied. Maximum plasma concentrations were low (approximately 0.01 µg/mL) and declined rapidly.
The distribution of radiolabeled moxifloxacin was also studied in pigmented rabbits after a single unilateral 30 µL dose of a 0.3% 14C-moxifloxacin solution (n=4 rabbits sampled at each time point). Mean Cmax values in cornea, conjunctiva, aqueous humor and iris-ciliary body were 10.6 ± 2.8 µg/g, 2.54 + 0.40 µg/g, 1.36 ± 0.33 µg/mL and 7.54 ± 3.34 µg/g, respectively. Maximum concentrations and half-lives in ocular tissues are summarized in Table 1.
Table 1: Maximum Concentrations and Half-Lives of Radiolabeled Moxifloxacin in Ocular Tissues from Pigmented Rabbits
| Tissue | Cmax (µg equivalents/g) ± SD | t½ (hours) |
|---|---|---|
| Cornea | 10.6 ± 2.8 | 92 |
| Conjunctiva | 2.54 ± 0.40 | 43 |
| Aqueous Humor | 1.36 ± 0.33 | 5.6 |
| Iris-Ciliary Body | 7.54 ± 3.34 | 649 |
| Lens | 0.08 ± 0.06 | 37 |
| Anterior Sclera | 2.86 ± 1.01 | 1080 |
| Posterior Sclera | 0.09 ± 0.03 | 92 |
| Choroid | 0.441 ±0.178 | 872 |
| Retina | 0.066 ± 0.016 | 48 |
Tear film concentrations of moxifloxacin were measured in pigmented rabbits (n=3) after single unilateral administration of 30 µL of a 0.3% moxifloxacin ophthalmic solution. The mean concentration of moxifloxacin was 366 ± 214 µg/mL at the first sampling point of 1 minute after dosing. The levels then declined rapidly such that by 5 minutes after dosing the concentrations were approximately 20 µg/mL. The concentrations in the tear film were 1.73 ± 1.50 µg/mL at 6 hours post-dosing. Tear concentration data are summarized in Table 2.
Table 2: Tear Concentrations of Moxifloxacin Following Administration of a 0.3% Moxifloxacin Solution to Pigmented Rabbits
| Time After Dose (minutes) | Mean Concentration ± SD (µg/mL) | Sample Size |
|---|---|---|
| 1 | 366 ± 214 | 3 |
| 2 | 74.2 ± 70.6 | 3 |
| Time After Dose (minutes) | Mean Concentration ± SD (µg/mL) | Sample Size |
|---|---|---|
| 3 | 60.9 ± 11.9 | 3 |
| 5 | 23.7 ± 17.2 | 3 |
| 10 | 19.4 ± 4.03 | 3 |
| 20 | 23.4 ± 11.6 | 3 |
| 30 | 10.3 ± 3.6 | 3 |
| 45 | 1.21 ± 0.65 | 3 |
| 60 | 7.14 ± 6.12 | 3 |
| 90 | 2.69 ± 1.32 | 3 |
| 120 | 7.27 ± 9.96 | 2* |
| 180 | 1.67 ± 1.06 | 2* |
| 360 | 1.73 ± 1.50 | 2* |
* 1 of 3 samples below quantitation limit of the assay. These samples were assigned a value of one half the limit of quantitation for calculation of the mean (1 µg/mL/2 = 0.5 µg/mL)
Human Pharmacokinetics:
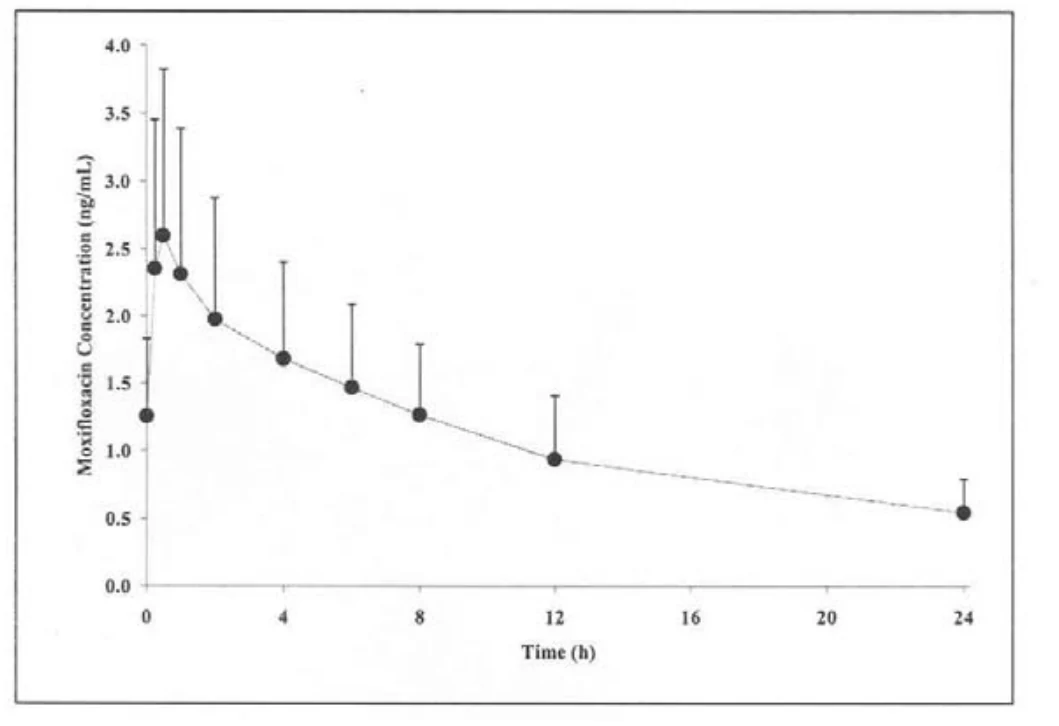
Plasma concentrations were studied in 21 healthy male and female subjects who were administered moxifloxacin hydrochloride ophthalmic solution to both eyes every 8 hours for a total of 13 doses. The results showed measurable plasma concentrations of moxifloxacin (≥ 0.75 ng/mL) in 16 of 21 subjects at 4-hours following the first dose, and in all subjects following the last dose. Figure 1 shows the mean moxifloxacin plasma concentrations following the last dose.
The mean steady-state estimates for Cmax and AUC were 2.7 ng/mL and 41.9 ng·hr/mL, respectively. The steady-state parameter estimates for Cmax and AUC were at least 1,600 and 1,000 fold lower than mean Cmax and AUC values reported after therapeutic 400 mg oral doses of moxifloxacin. The steady-state plasma half-life of moxifloxacin was estimated to be 13 hours.
Subgroup analysis by race (Caucasian, Asian) showed no meaningful differences in the mean steady-state pharmacokinetic parameters of moxifloxacin. Gender differences in the steady-state Cmax and AUC were seen; however, when adjusted for body weight, the differences were minimized and not clinically relevant.
Figure 1: Mean (+ SD) Moxifloxacin Plasma Profile Following the Last Topical Ocular Dose of Moxifloxacin Hydrochloride Ophthalmic Solution in Healthy Subjects
Tear film concentrations of moxifloxacin were studied in 31 healthy male and female adult volunteers who were administered 1 drop of moxifloxacin hydrochloride ophthalmic solution to both eyes every 8 hours for a total of 10 doses.
Mean tear concentrations at 5 minutes following the first and last topical dose were 46.0 and 55.2 µg/mL, respectively. Thereafter, mean tear concentrations rapidly declined in a biphasic manner with means ranging from approximately 1 to 4 µg/mL over the 1 to 8 hour sampling period. Pre-dose morning tear concentrations on Days 2 to 4 averaged over 4 µg/mL, demonstrating that concentrations are above the MICs for most of the common organisms in conjunctivitis over the 24-hour period.
Elimination and Metabolism: Moxifloxacin is widely distributed in the body tissues and approximately 50% is bound to serum proteins. Animal studies indicate some penetration into conjunctiva and ocular tissues with prolonged binding to melanin. Approximately 45% of an oral dose is excreted as unchanged drug, and most of the rest as glucuronide and sulfate conjugates in feces and urine. The cytochrome P450 enzyme system is not involved in metabolizing the drug.
Drug-Drug Interactions: Specific drug-drug pharmacokinetic interaction studies were not conducted with moxifloxacin hydrochloride ophthalmic solution. Given the low systemic exposure observed for moxifloxacin after topical ocular administration of moxifloxacin hydrochloride ophthalmic solution, clinically relevant drug-drug interactions through protein binding, renal elimination or hepatic metabolism are unlikely following topical ocular administration. Moxifloxacin can be chelated by polyvalent ions such as Mg++, A1+++, Fe++ and Zn++.
In vitro studies with cytochrome P450 isozymes have shown that moxifloxacin does not inhibit CYP3A4, CYP2D6, CYP2C9, CYP2C19 or CYP1A2 indicating that moxifloxacin is unlikely to alter the pharmacokinetics of drugs metabolized by these enzymes.
Special Populations:
The pharmacokinetics of moxifloxacin hydrochloride ophthalmic solution has not been studied in patients with hepatic or renal impairment. However, the pharmacokinetics of orally administered moxifloxacin has been studied in these special populations.
The pharmacokinetic parameters of oral moxifloxacin are not significantly altered by mild, moderate or severe renal impairment. No dosage adjustment of moxifloxacin hydrochloride ophthalmic solution is necessary in patients with renal impairment.
Pharmacokinetic parameters of oral moxifloxacin were not significantly altered in patients with mild to moderate hepatic insufficiency (Child Pugh Classes A and B). Studies were not performed in patients with severe hepatic impairment (Child Pugh Class C). Because of the low systemic exposure by the topical route of administration, no dosage adjustment of moxifloxacin hydrochloride ophthalmic solution is needed in patients with hepatic impairment.
MICROBIOLOGY
Moxifloxacin has in vitro activity against a wide range of Gram-positive and Gram-negative microorganisms.
The antibacterial action of moxifloxacin results from inhibition of topoisomerase II (DNA gyrase) and topoisomerase IV. DNA gyrase is an essential enzyme that is involved in the replication, transcription and repair of bacterial DNA. Topoisomerase IV is an enzyme known to play a key role in the partitioning of the chromosomal DNA during bacterial cell division. The presence of the bulky bicycloamine substituent at the C-7 position prevents active efflux, a proposed mechanism of fluoroquinolone resistance.
Moxifloxacin concentrations at twice the MIC are sufficient to be bactericidal for most strains of Staphylococcus aureus. Streptococcus pneumoniae, and Haemophilus influenzae. Concentrations of moxifloxacin somewhat greater than twice the MIC were bactericidal for strains of Escherichia coli while those greater than ten times the MIC were bactericidal for Streptococcus pyogenes.
Resistance: The mechanism of resistance of quinolones, including moxifloxacin, is different from that of macrolides, aminoglycosides, tetracyclines or ß-lactams. Therefore, moxifloxacin may be active against pathogens that are resistant to these antibiotics and these antibiotics may be active against pathogens that are resistant to moxifloxacin. There is no cross-resistance between moxifloxacin and the aforementioned classes of antibiotics. Cross resistance has been observed between systemic moxifloxacin and some other quinolones.
In vitro resistance to moxifloxacin develops slowly via multiple-step mutations and occurs in vitro at a general frequency of between 1.8 x 10⁻⁹ to less than 1 x 10-11 in one strain of Staphylococcus aureus and one strain of Streptococcus pneumoniae.
Moxifloxacin has been shown to be active against most strains of the following microorganisms (see Table 3), both in vitro and in clinical infections from the US and India (see INDICATIONS).
Table 3: Moxifloxacin In Vitro Activity Against Clinical Isolates
| Pathogen | N | MIC Range µg/mL | MIC50 µg/mL | MIC90 µg/mL |
| Aerobic, Gram-Positive | ||||
| Staphylococcus aureus | 49 | ≤ 0.016 – 2.0 | 0.06 | 1.0 |
| Staphylococcus epidermidis | 119 | ≤ 0.016 – 2.0 | 0.06 | 0.25 |
| Staphylococcus haemolyticus | 22 | 0.03 – 2.0 | 0.13 | 1.0 |
| Staphylococcus hominis | 11 | 0.06 – 1.0 | 0.06 | 0.13 |
| Streptococcus pneumoniae | 42 | 0.03 – 0.25 | 0.13 | 0.25 |
| Streptococcus viridans group | 22 | 0.06 – 2.0 | 0.25 | 0.25 |
| Aerobic, Gram-Negative | ||||
| Acinetobacter species | 15 | ≤ 0.016 – 0.25 | 0.03 | 0.06 |
| Haemophilus influenzae | 68 | ≤ 0.016 – 0.25 | 0.06 | 0.13 |
The following in vitro data (Table 4) are also available, but their clinical significance in ophthalmic infections is unknown. The safety and effectiveness of moxifloxacin hydrochloride ophthalmic solution in treating ophthalmic infections due to these organisms have not been established in adequate and well-controlled trials. The following organisms are considered susceptible when evaluated using systemic breakpoints. However, a correlation between the in vitro systemic breakpoint and ophthalmic efficacy has not been established. This list of organisms (Table 4) is provided as guidance only in assessing the potential treatment of conjunctival infections. Moxifloxacin exhibits in vitro minimal inhibitory concentrations (MICs) of 2 µg/mL or less (systemic breakpoint susceptibility) against most (greater than or equal to 90%) strains of the following ocular isolates:
Table 4: Susceptibility of Bacterial Conjunctivitis Isolates to Moxifloxacin
| Bacterial Species | N | MIC Range µg/mL | MIC50 µg/mL | MIC90 µg/mL |
|---|---|---|---|---|
| Aerobic Gram-positive Microogranisms | ||||
| Bacillus cereus | 15 | 0.032-0.25 | 0.13 | 0.13 |
| Corynebacterium species | 35 | 0.016-16 | 0.25 | 2.0 |
| Kocuria species | 11 | 0.25-0.50 | 0.25 | 0.50 |
| Micrococcus luteus | 35 | 0.03-1.0 | 0.5 | 1.0 |
| Staphylococcus capitis | 68 | 0.03-1.0 | 0.13 | 0.25 |
| Bacterial Species | N | MIC Range µg/mL | MIC50 µg/mL | MIC90 µg/mL |
|---|---|---|---|---|
| Staphylococcus caprae | 13 | 0.06-0.13 | 0.06 | 0.13 |
| Staphylococcus lugdunensis | 36 | 0.06-1.0 | 0.13 | 0.25 |
| Staphylococcus pasteuri | 15 | 0.06-1.0 | 0.13 | 0.25 |
| Staphylococcus saprophyticus | 18 | 0.13-0.25 | 0.13 | 0.25 |
| Staphylococcus warneri | 10 | 0.06-0.13 | 0.13 | 0.13 |
| Streptococcus mitis | 76 | 0.06-0.25 | 0.13 | 0.25 |
| Streptococcus oralis | 10 | 0.13-0.25 | 0.13 | 0.25 |
| Streptococcus parasanguinis | 18 | 0.06-1.0 | 0.13 | 0.25 |
| Aerobic, Gram-negative Microorganisms | ||||
| Acinetobacter baumannii | 23 | 0.03-0.50 | 0.13 | 0.25 |
| Acinetobacter junii | 27 | 0.03-8.0 | 0.06 | 0.13 |
| Acinetobacter schindleri | 10 | 0.03-0.06 | 0.03 | 0.06 |
| Acinetobacter ursingii | 10 | 0.06-1.0 | 0.25 | 0.50 |
| Citrobacter koseri | 12 | 0.016-0.25 | 0.03 | 0.13 |
| Enterobacter hormaechei | 13 | 0.06-8.0 | 0.13 | 0.5 |
| Escherichia coli | 21 | 0.03-32 | 0.06 | 1.0 |
| Klebsiella pneumoniae | 17 | 0.06-2.0 | 0.13 | 0.5 |
| Moraxella osloensis | 13 | 0.03-0.25 | 0.06 | 0.25 |
| Moraxella catarrhalis | 25 | 0.06-0.13 | 0.06 | 0.13 |
| Pseudomonas stutzeri | 67 | 0.03-2.0 | 0.25 | 0.50 |
| Serratia marcescens | 20 | 0.25-2.0 | 0.5 | 1.0 |
| Stenotrophomonas maltophilia | 18 | 0.25-2.0 | 0.5 | 2.0 |
Susceptibility Tests: There are currently no NCCLS approved standards for assessing in vitro susceptibility of conjunctival isolates to topical antibiotics, including moxifloxacin. Standardized systemic susceptibility tests may not be appropriate to predict clinical effectiveness in treating conjunctivitis.
TOXICOLOGY
Topical Ocular Studies: Ophthalmic solutions of moxifloxacin were evaluated in repeat-dose topical ocular studies in rabbits (pigmented) and Cynomolgus monkeys (see Table 5).
Table 5: Results of Topical Ocular Studies
| Species/No. per Group | Dose/Route | Duration of Treatment | Findings |
Rabbits (pigmented)/ 4 male, 4 female | 0.5%, 1%, 3% (80 µL, unilateral, 4 times daily) / topical ocular | 1 month | Low ocular irritation potential; no significant ocular or systemic effects |
Cynomolgus monkeys/ 4 male, 4 female | 0.5%, 1%, 3% (80 µL unilateral, 6 times daily Days 1-16, 3 times daily thereafter) / topical ocular | 3 months | Low ocular irritation potential; no significant ocular or systemic effects |
Ocular Toxicity Study: A special ocular toxicity study was conducted in dogs following systemic (oral) administration of moxifloxacin (see Table 6). The daily dosages of moxifloxacin evaluated in this study are significantly higher than the recommended daily dose of TEVA-MOXIFLOXACIN ophthalmic solution.
Table 6: Results of Ocular Toxicity Study
| Species/No. per Group | Dose/Route | Duration of Treatment | Findings |
Dog (Beagle)/ 4 males | 30, 60, 90 mg/kg moxifloxacin/orally 100 mg/kg nalidixic acid (positive control)/orally | 2 weeks (with 8 week recovery period) | ↓ in group mean amplitude of a- and b-waves at 60 and 90 mg/kg moxifloxacin and with nalidixic acid; Histopath: slight to marked atrophy in outer nuclear and plexiform layers and rod and cone layers of two high dose animal; NOEL = 30 mg/kg orally (over 1300 times > the human dose of moxifloxacin ophthalmic solution). |
Single and Repeat-Dose Oral and IV Studies: Oral and intravenous single-dose studies conducted with moxifloxacin are summarized in Table 7, and repeat-dose systemic studies that included ocular evaluations are summarized in Table 8. The daily dose levels of moxifloxacin evaluated in these studies are significantly higher than the recommended daily dose of moxifloxacin hydrochloride ophthalmic solution.
Table 7: Single-Dose Systemic Studies
| Species | Strain/Sex | No./Group | Route of Administration | LD50 mg/kg B.W. (Conf. Int. for 95%) |
| Mouse | NMRI/male NMRI/female NMRI/male NMRI/female WU/male WU/female WU/male WU/female | 5 | p.o. p.o. i.v. i.v. p.o. p.o. i.v. i.v | Approx. 435 Approx. 758 (440-1305) Approx. 105 (84-132) Approx. 130 (116-145) Approx. 1320 Approx. 1320 Approx. 112 Approx. 146 |
| Monkey | Cynomolgus/Male | 2 | p.o. | Approx. 1500 |
Table 8: Repeat-Dose Systemic Studies
Species/ No. Per Group | Dose/Route | Duration of Treatment | Findings |
|---|---|---|---|
Wistar rats/ 15 male, 15 female | 0, 20, 100, 500, 750 mg/kg/ orally by gavage | 13 weeks for all groups; 1 group examined after a 4 week recovery period | ↓ body wt gain at 100, 500, 750 mg/kg males; ocular evaluations (indirect ophthalmoscope and slit-lamp) unremarkable; ↑ ASAT, ALAT, LDH at 500, 750 mg/kg males and females at 750 mg/kg, |
Species/ No. Per Group | Dose/Route | Duration of Treatment | Findings | |||
|---|---|---|---|---|---|---|
| histopath unremarkable; NOAEL for females 100 mg/kg, 20 mg/kg for males | ||||||
Wistar rats/ 20 male, 20 female | 0, 20, 100, 500 mg/kg / orally by gavage | 28 weeks | ↓ body wt. gain at 500 mg/kg both sexes; ↑ ASAT, ALAT, LDH, bilirubin 500 mg/kg males; ocular evaluations (indirect ophthalmoscope and slit-lamp) unremarkable, histopath 500 mg/kg both sexes, thyroid 500 mg/kg males NOAEL females 100 mg/kg, males 20 mg/kg | |||
| Young Beagle pups/4 male, 4 female | 0, 10, 30, 90 mg/kg/p.o. | 4 weeks | Vacuolization of subcapsular lens cortex (indirect ophthalmoscope and slit-lamp) at 90 mg/kg; no evidence of co-cataractogenesis; prolongation of QT interval at 90 mg/kg; histopath chondropathy at 30 and 90 mg/kg. | |||
| Young Beagle pups/ 2 male, 2 female | 0, 10, 30, 90 mg/kg/p.o. | 4 weeks | Vomiting, salivation, ↓ body wt. gain at 90 mg/kg; ocular evaluations (indirect ophthalmoscope) unremarkable; histopath blistering of articular cartilage at 30 and 90 mg/kg | |||
| Rhesus monkeys/ 3 male, 3 female | 0, 100, 150 mg/kg / orally by gavage | 4 weeks | ↓ body wt. gain at 150 mg/kg; ocular evaluations (indirect ophthalmoscope) unremarkable; histopath liver and bone marrow at 100 and 150 mg/kg | |||
| Rhesus monkeys/ 4 male, 4 female | 0, 15, 45, 135 mg/kg/orally by gavage | 13 weeks | Salivation at 15 mg/kg; salivation, vomiting, ↓ body wt. gain at 135 mg/kg; ocular evaluations (indirect ophthalmoscope) unremarkable; NOAEL 15 mg/kg | |||
| Rhesus monkeys, 4 male, 4 female | 0, 15, 45, 135 mg/kg/orally by gavage | 26 weeks | 1 mortality at 135 mg/kg; ocular evaluations (indirect ophthalmoscope) unremarkable; ↑ ALAT and GLDH at 45 mg/kg; histopath liver and bone marrow at 135 mg/kg; NOAEL 15 mg/kg | |||
Mutagenicity: Moxifloxacin was not mutagenic in four bacterial strains used in the Ames Salmonella reversion assay. As with other quinolones, the positive response observed with moxifloxacin in strain TA 102 using the same assay may be due to the inhibition of DNA gyrase. Moxifloxacin was not mutagenic in the CHO/HGPRT mammalian cell gene mutation assay. An equivocal result was obtained in the same assay when v79 cells were used. Moxifloxacin was clastogenic in the v79 chromosome aberration assay, but it did not induce unscheduled DNA synthesis in cultured rat hepatocytes. There was no evidence of genotoxicity in vivo in a micronucleus test or dominant lethal test in mice.
Carcinogenicity: Long term studies in animals to determine the carcinogenic potential of moxifloxacin have not been performed. However, in an accelerated study with initiators and promoters, moxifloxacin was not carcinogenic following up to 38 weeks of oral dosing at 500 mg/kg/day.
Reproduction and Teratology: Moxifloxacin had no effect on fertility in male and female rats at oral doses as high as 500 mg/kg/day, approximately 21,700 times the highest recommended total daily human ophthalmic dose.
Moxifloxacin was not teratogenic when administered to pregnant rats during organogenesis at oral doses as high as 500 mg/kg/day (approximately 21,700 times the highest recommended total human ophthalmic dose); however, decreased fetal body weights and slightly delayed fetal skeletal development were observed. There was no evidence of teratogenicity when pregnant Cynomolgus monkeys were given oral doses as high as 100 mg/kg/day (approximately 4,300 times the highest recommended total daily human ophthalmic dose). An increased incidence of smaller fetuses was observed at 100 mg/kg/day. In an oral peri/postnatal development study conducted in rats, marginal effects observed at 500 mg/kg/day included extended duration of pregnancy, increased prenatal loss, reduced birth weight and decreased survival index. Maternal mortality occurred at 500 mg/kg/day.
In an intravenous rabbit study, moxifloxacin at 20 mg/kg (approximately 860 times the highest recommended total daily human ophthalmic dose) was found to decrease the gestation rate, decrease fetal weights and delay ossification.
REFERENCES
- 1. Blondeau JM. A review of the comparative in vitro activities of 12 antimicrobial agents, with a focus on five new ‘respiratory quinolones’. J Antimicrob Chemother 1999; 43 Suppl B: 1-11.
- 2. Blondeau JM, Felmingham D. In vitro and in vivo activity of moxifloxacin against community respiratory tract pathogens, Clin Drug Invest 1999;18:57-78.
- 3. Boswell FJ, Andrews JM, Wise R, Dalhoff A. Bactericidal properties of moxifloxacin and post-antibiotic effect. J Antimicrob Chemother 1999,43(Suppl B)43-9.
- 4. Brueggemann AB, Coffman SL, Rhomberg PR, Huynh HK, Almer L, Nilius A, Flamm R, Doern GV. Fluoroquinolone resistance in Streptococcus pneumoniae in United States since 1994-1995. Antimicrob Agents Chemother 2002;46:680-8.
- 5. Dalhoff A, Petersen U, Endermann R. in vitro activity of Bay 12-8039, a new 8-methoxyquinolone. Chemotherapy 1996; 42:410-25.
- 6. Doern GV, Heilmann KP, Huynh HK, Rhomberg PR, Coffman SL, Brueggemann AB. Antimicrobial resistance among clinical isolates of Streptococcus pneumoniae in the United States during 1999-2000, including a comparison of resistance rates since 1994-1995. Antimicrob Agents Chemother 2001,45: 1721 -9.
- 7. Esposito S, Noviello S, Ianniello F. Comparative in vitro activity of older and newer fluoroquinolones against respiratory tract pathogens Chemotherapy 2000;46:309-314.
- 8. Jones ME, Sahm DF, Martin N, Scheuring S, Heisig P. Thornsberry C, Kohrer K, Schmitz F-J. Prevalence of gyrA, gyrB, parC and parE mutations in clinical isolates of Streptococcus pneumoniae with decreased susceptibilities to different fluoroquinolones and originating from worldwide surveillance studies during 1997-1998 respiratory season. Antimicrob Agents Chemother 2000,44(2):462-6.
- 9. Klepser ME, Ernst EJ, Petzold R, Rhomberg P. Doern GV. Comparative bactericidal activities of ciprofloxacin, clinafloxacin, grepafloxacin, levofloxacin, moxifloxacin, and trovafloxacin against Streptococcus pneumoniae in a dynamic in vitro model. Antimicrob Agents Chemother 2001,45:673-8.
- 10. Mather R, Karenchak LM, Romanowski EG, Kowalski RP. Fourth generation fluoroquinolones: new weapons in the arsenal of ophthalmic antibiotics. Am J Ophthalmol 2002;133:463-6.
- 11. Pong A, Thomson KS, Moland, ES, Chartrand SA, Sanders CC. Activity of moxifloxacin against pathogens with decreased susceptibility to ciprofloxacin. J Antimicrob Chemother 1999;44(5):621-7
- 12. Schedletzky H, Wiedemann B, Heisig P. The effect of moxifloxacin on its target topoisomerases from Escherichia coli and Staphylococcus aureus. J Anticrob Chemother 1999; 43 Suppl B:31-7.
- 13. Schmitz FJ, Hofmann B, Hansen B, Scheuring S. Luckefahr M, Klootwijk M, Verhoef J, Fluit A, Heinz HP, Kohrer K, Jones ME. Relationship between ciprofloxacin, ofloxacin, levofloxacin, sparfloxacin and moxifloxacin (BAY 12-8039) MICs and mutations in grlA, grlB, gyrA and gyrB in 116 unrelated clinical isolates of Staphylococcus aureus J Antimicrob Chemother 1998;41: 41-484.
- 14. Siefert HM, Domdey-Bette A, Henninger K, Hucke F, Kohlsdorfer C, Stass HH. Pharmacokinetics of the 8-methoxyquinolone, moxifloxacin a comparison in humans and other mammalian species. J Antimicrob Chemother 1999;43(Suppl B):69-76.
- 15. Stass H, Kubitza D. Pharmacokinetics and elimination of moxifloxacin after oral and intravenous administration. J Antimicrob Chemother 1999;43 (Suppl B): 83 -90.
- 16. Tankovic J, Bachoual R, Ouabdesselam S, Boudjadja A, Soussy C-J. In vitro activity of moxifloxacin against fluoroquinolone-resistant strains of aerobic gram-negative bacilli and Enterococcus faecalis. J Antimicrob Chemother 1999; 43: 19-23.
- 17. Product Monograph for VIGAMOXTM (Moxifloxacin Hydrochloride Ophthalmic Solution), Alcon Canada Inc. Date of Revision: July 20, 2015, Control No. 183976