


Product Monograph - Teva-Prazosin
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential | 11/2024 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ................................................................................................. 3
TABLE OF CONTENTS .................................................................................................................... 3
PART I: HEALTH PROFESSIONAL INFORMATION .......................................................................... 5
1 INDICATIONS .............................................................................................................................. 5
1.1 Pediatrics ............................................................................................................................. 5
1.2 Geriatrics ............................................................................................................................. 5
2 CONTRAINDICATIONS ................................................................................................................ 5
4 DOSAGE AND ADMINISTRATION ............................................................................................... 5
4.1 Dosing Considerations ......................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ..................................................................... 5
4.4 Administration ..................................................................................................................... 7
4.5 Missed Dose ........................................................................................................................ 7
5 OVERDOSAGE ............................................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................................. 8
7 WARNINGS AND PRECAUTIONS ................................................................................................ 8
7.1 Special Populations .............................................................................................................. 9
7.1.1 Pregnant Women ............................................................................................................. 9
7.1.2 Breast-feeding ................................................................................................................ 10
7.1.3 Pediatrics ........................................................................................................................ 10
7.1.4 Geriatrics ........................................................................................................................ 10
8 ADVERSE REACTIONS ............................................................................................................... 10
8.1 Adverse Reaction Overview ............................................................................................... 10
8.2 Clinical Trial Adverse Reactions ......................................................................................... 10
8.5 Post-Market Adverse Reactions ......................................................................................... 11
9 DRUG INTERACTIONS ............................................................................................................... 12
9.2 Drug Interactions Overview ............................................................................................... 12
9.4 Drug-Drug Interactions ...................................................................................................... 12
9.5 Drug-Food Interactions ...................................................................................................... 12
9.6 Drug-Herb Interactions ...................................................................................................... 12
9.7 Drug-Laboratory Test Interactions ..................................................................................... 13
10 CLINICAL PHARMACOLOGY .................................................................................................... 13
10.1 Mechanism of Action ....................................................................................................... 13
10.2 Pharmacodynamics.......................................................................................................... 13
10.3 Pharmacokinetics ............................................................................................................ 14
11 STORAGE, STABILITY AND DISPOSAL ..................................................................................... 15
12 SPECIAL HANDLING INSTRUCTIONS ....................................................................................... 16
PART II: SCIENTIFIC INFORMATION ............................................................................................ 17
13 PHARMACEUTICAL INFORMATION ........................................................................................ 17
14 CLINICAL TRIALS ..................................................................................................................... 18
14.2 Comparative Bioavailability Studies ................................................................................. 18
15 MICROBIOLOGY ..................................................................................................................... 20
16 NON-CLINICAL TOXICOLOGY .................................................................................................. 20
17 SUPPORTING PRODUCT MONOGRAPHS ............................................................................... 22
PATIENT MEDICATION INFORMATION ....................................................................................... 23
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TEVA-PRAZOSIN (prazosin hydrochloride tablets) is indicated for:
the treatment of mild to moderate essential hypertension.
It is employed in a general treatment program in association with a thiazide diuretic and/or other antihypertensive agents as needed for proper patient response.
TEVA-PRAZOSIN may be tried as a sole therapy in those patients in whom treatment with other agents caused adverse effects or is inappropriate.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of prazosin hydrochloride in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada to establish differences in the safety and efficacy associated with the use of prazosin hydrochloride in geriatric patients.
2 CONTRAINDICATIONS
TEVA-PRAZOSIN is contraindicated in patients with known sensitivity to this drug or other quinazolines or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
When titration is to be undertaken using the tablet formulation it will be necessary to split the 1 mg scored tablet to obtain the 0.5 mg starting dose.
4.2 Recommended Dose and Dosage Adjustment
The starting dose of TEVA-PRAZOSIN is 0.5 mg. The dose should be built up gradually with 0.5 mg being given b.i.d. or t.i.d. for at least three days. Unless adverse effects
- the blood pressure lowering effect this dose should be increased to 1 mg given b.i.d. or t.i.d. for at least a further three days.
- Thereafter, as determined by the patient’s response to the blood pressure lowering effect, the dose should be increased gradually. Response to TEVA-PRAZOSIN is usually seen within one to fourteen days if it is to occur at any particular dose. When a response is seen, therapy should be continued at that dose until the degree of response has reached the optimum before the next dose increment is added.
- Incremental increases should be continued until a desired effect is achieved or a maximum daily dose of 20 mg is reached.
- The maintenance dose of TEVA-PRAZOSIN may be given as a twice or three times daily dosage regimen.
Patients With Renal Impairment:
- In patients with moderate to severe grades of renal impairment, it is recommended that therapy be initiated at 0.5 mg daily and that dose increases be instituted gradually. See 7 WARNINGS AND PRECAUTIONS, Renal.
Use With Other Drugs
Patients Receiving Diuretic Therapy
- The diuretic should be reduced to a maintenance dose level for the particular agent and TEVA-PRAZOSIN initiated at 0.5 mg h.s. then proceeding to 0.5 mg b.i.d. or t.i.d. After the initial period of observation, the dose of TEVA-PRAZOSIN should be gradually increased as determined by the patient’s response.
Patients Receiving Other Antihypertensive Agents
- Because some additive effect is anticipated, the other agent (e.g., propranolol* or other beta-adrenergic blocking agents*, alpha methyldopa, reserpine, clonidine*, etc.) should be reduced and TEVA-PRAZOSIN initiated at 0.5 mg h.s. then proceeding to 0.5 mg b.i.d. or t.i.d. Subsequent dosage increase should be made depending upon the patient’s response.
Patients on TEVA-PRAZOSIN to Whom Other Antihypertensive Agents Are Added
- When adding a diuretic or other antihypertensive agent, the dose of TEVA-PRAZOSIN should be reduced to 1 mg or 2 mg b.i.d. or t.i.d. and retitration then carried out.
* Appropriate precautions should be observed when the dosage of these other antihypertensive agents is reduced.
4.4 Administration
It is recommended that the TEVA-PRAZOSIN tablets should be given with food preferably with the evening meal, at least two or three hours before retiring.
4.5 Missed Dose
If the patient misses a dose, instruct the patient to take the dose as soon as they remember. If it is almost time for the next dose, inform the patient to skip the missed dose and continue the regular dosing schedule.
5 OVERDOSAGE
Symptoms
A few reports of prazosin hydrochloride overdose have been documented with prazosin hydrochloride. The most frequently observed symptoms of overdose include hypotension and somnolence.
Accidental ingestion of at least 50 mg of prazosin hydrochloride in a two-year-old child resulted in profound drowsiness and depressed reflexes. No decrease in blood pressure was noted. Recovery was uneventful.
Treatment
Should overdosage lead to hypotension, support of the cardiovascular system is of first importance. Restoration of blood pressure and normalization of heart rate may be accomplished by keeping the patient in the supine position. If necessary, vasopressors should be used. If this measure is inadequate, shock should then be treated with volume expanders. Renal function should be monitored and supported as needed. Laboratory data indicate prazosin hydrochloride is not dialysable because it is protein bound.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets 1 mg, 2 mg, 5 mg of prazosin | Colloidal silicon dioxide, FD&C yellow #6, magnesium stearate, microcrystalline cellulose (Avicel PH-102), sodium lauryl sulfate, sodium starch glycolate and starch - 1500 LM |
TEVA-PRAZOSIN is available as:
1 mg - Orange coloured, capsule-shaped, bi-convex, compressed tablets engraved no|vo on one side and ‘1’ on the reverse, containing prazosin hydrochloride equivalent to 1 mg prazosin.
2 mg - White, round, biconvex, compressed tablets engraved novo on one side and 2 between broken vertical scorelines on the reverse, containing prazosin hydrochloride equivalent to 2 mg prazosin.
5 mg - White, diamond-shaped, biconvex, compressed tablets; engraved no|vo on one side and 5 on the reverse, containing prazosin hydrochloride equivalent to 5 mg prazosin.
Supplied in bottles of 100.
7 WARNINGS AND PRECAUTIONS
Cardiovascular
TEVA-PRAZOSIN may cause syncope and/or excessive hypotension with sudden loss of consciousness. In most cases this is believed to be due to an excessive postural hypotensive effect, although occasionally the syncopal episode has been associated with about of severe tachycardia with heart rates of 120 to 160 beats per minute. The incidence of syncopal episodes is approximately 0.8% when the gradual dose build up described under dosage and administration is followed. The incidence is higher if the initial dose exceeds 0.5 mg. Syncopal episodes have occurred within 30 to 90 minutes of the initial dose of the drug. They have also been reported in association with dosage increases or the introduction of prazosin hydrochloride into the regimen of a patient taking another antihypertensive agent or a diuretic. Physicians are therefore advised to limit the initial dose of the drug to 0.5 mg b.i.d. or t.i.d., to subsequently increase the dosage slowly, and to introduce any additional antihypertensive drugs into the patient’s regimen with caution.
Patients whose blood pressure is not adequately controlled by high doses of a beta-adrenergic blocking agent such as propranolol may develop acute hypotension when TEVA-PRAZOSIN is added. To minimize the incidence of acute hypotension in such patients, the dose of beta-adrenergic blocking agent should be reduced before TEVA-PRAZOSIN is administered. A low initial dose of TEVA-PRAZOSIN is also strongly recommended. See 4.2 Recommended Dose and Dosage Adjustment.
If syncope occurs, the patient should be placed in the recumbent position and supportive measures instituted. This adverse effect is self-limiting and in most cases does not recur once a steady maintenance level is initiated. Patients should be cautioned to avoid situations where injury could result should syncope occur during TEVA-PRAZOSIN therapy especially in the initial dose adjustment period.
More common than loss of consciousness are the symptoms often associated with lowering of the blood pressure, namely, dizziness and light-headedness. The patient should be cautioned about these possible adverse effects and advised what measures to take should they develop.
Monitoring and Laboratory Tests
False positive results may occur in screening tests for pheochromocytoma in patients who are being treated with TEVA-PRAZOSIN due to increase in urinary vanillylmandelic acid (VMA) and methoxyhydroxyphenyl glysol (MHPG), urinary metabolites of norepinephrine. If an elevated VMA is found, TEVA-PRAZOSIN should be discontinued, and the patient retested after a month.
Renal
Use in Patients with Moderate to Severe Grades of Renal Impairment: Because some patients with moderate to severe grades of renal impairment have responded to smaller than usual doses of prazosin hydrochloride, it is recommended that therapy be initiated with TEVA-PRAZOSIN at 0.5 mg and that dose increases be instituted cautiously.
Reproductive health: Female and male potential
Priapism: Rarely, α1-antagonists such as prazosin have been associated with priapism. Because this condition can lead to permanent impotence if not promptly treated, patients should be advised about the seriousness of the condition.
7.1 Special Populations
7.1.1 Pregnant Women
Although no teratogenic effects were seen in animal testing, there are no adequate and well controlled studies which establish the safety of prazosin hydrochloride in pregnant women. Limited uncontrolled use in the management of hypertension in the later stages of pregnancy suggests that prazosin hydrochloride in combination with a beta-blocker can lower blood pressure in pregnant patients. The drug appears to be less effective in patients with proteinuria in whom the addition of i.v. hydralazine was usually required. Accordingly TEVA-PRAZOSIN should be used during pregnancy only if in the opinion of the physician the potential benefit outweighs potential risk to mother and child.
7.1.2 Breast-feeding
Prazosin has been shown to be excreted in small amounts in human milk. Caution should be exercised when TEVA-PRAZOSIN is administered to breast-feeding mothers.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada to establish differences in the safety and efficacy associated with the use of prazosin hydrochloride in geriatric patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common reactions associated with prazosin hydrochloride therapy are postural dizziness (11%), nausea (9.5%), drowsiness (8.7%), headache (8.4%), palpitations (6.6%), dry mouth (5.6%), weakness (4.6%), and fatigue/malaise (4.5%). In most instances side effects have disappeared with continued therapy or have been tolerated with no decrease in dose of drug.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The following reactions of unknown frequency have also been observed during prazosin hydrochloride administration.
Cardiac disorders: syncope (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular), tachycardia, faintness.
Ear and labyrinth disorders: vertigo, tinnitus.
Eye disorders: blurred vision, reddened sclera.
Gastrointestinal disorders: vomiting, diarrhea, constipation, abdominal discomfort and/or pain, pancreatitis.
General disorders and
administration site conditions: edema, fever.
Hepatobiliary disorders: liver function abnormalities (increase in AST or ALT).
Hematologic: decreased hematocrit/hemoglobin, positive ANA titer.
Musculoskeletal and
connective tissue disorders: arthralgia.
Nervous system disorders: paresthesia.
Psychiatric disorders: nervousness, depression, hallucinations.
Renal and urinary disorders: urinary frequency, incontinence.
Reproductive system and
breast disorders: impotence, priapism.
Respiratory, thoracic and
mediastinal disorders: dyspnea, epistaxis, nasal congestion.
Skin and subcutaneous disorders: rash, pruritus, alopecia, lichen planus, diaphoresis.
Vascular disorders: orthostatic hypotension.
Single reports of pigmentary mottling and serous retinopathy have been reported. In these instances, the exact causal relationship has not been established because the baseline observations were frequently inadequate.
In more specific slit-lamp and funduscopic studies, which included adequate baseline examinations, no drug-related abnormal ophthalmological findings have been reported.
Literature reports exist associating prazosin hydrochloride therapy with a worsening of pre-existing narcolepsy. A causal relationship is uncertain in these cases.
8.5 Post-Market Adverse Reactions
Allergic reaction.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Prazosin hydrochloride has been administered without any adverse drug interaction in limited clinical experience to date with the following: (1) cardiac glycosides - digitalis and digoxin; (2) hypoglycemics - insulin, chlorpropamide, tolazamide and tolbutamide; (3) tranquilizers and sedatives - chlordiazepoxide, diazepam and phenobarbital; (4) antigout - allopurinol, colchicine and probenecid; (5) antiarrhythmics -procainamide, propranolol (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular), and quinidine; and (6) analgesics, antipyretics and anti-inflammatories - propoxyphene, ASA, indomethacin and phenylbutazone.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Diuretic or other antihypertensive agent | T | Addition of a diuretic or other antihypertensive agent to prazosin hydrochloride has been shown to cause an additive hypotensive effect. An exaggerated hypotensive response has also been observed. | TEVA-PRAZOSIN should be initiated at 0.5 mg h.s. then proceeding to 0.5 mg b.i.d. or t.i.d. After the initial period of observation, the dose of TEVA-PRAZOSIN should be gradually increased as determined by the patient’s response. |
Legend: T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
False positive results may occur in screening tests for pheochromocytoma in patients who are being treated with TEVA-PRAZOSIN due to elevated levels of urinary vanillylmandelic acid (VMA) and methoxyhydroxyphenyl glysol (MHPG), urinary metabolites of norepinephrine.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
TEVA-PRAZOSIN is a formulation of prazosin hydrochloride and is a conventional release formulation. Prazosin causes a decrease in total peripheral resistance. Animal studies suggest that the vasodilator effect of prazosin is related to selective blockade of post-synaptic alpha1- adrenoceptors. The results of dog forelimb experiments demonstrate that the peripheral vasodilator effect is confined mainly to the level of the resistance vessels (arterioles). Hemodynamic studies have been carried out in man following acute single dose administration and during the course of long-term maintenance therapy. The results confirm that the therapeutic effect is a fall in blood pressure unaccompanied by a clinically significant change in heart rate, renal blood flow and glomerular filtration rate. In patients with hypertension there is little change in cardiac output. In addition, clinical pharmacology studies have shown that both prazosin and prazosin GITS antagonize the vasopressor effect of intravenous phenylephrine, an alpha1-agonist.
In man blood pressure is lowered in both the supine and standing positions. The hypotensive effect of prazosin hydrochloride is greater when the patient is standing, and a mild reflex tachycardia can result. Tolerance has not been observed to develop in long term hypertensive therapy. Rebound elevation of blood pressure does not seem to occur following abrupt cessation of therapy with prazosin hydrochloride.
Most clinical studies indicate that chronic therapy with prazosin hydrochloride has little effect on plasma renin activity. However one report suggests a transient increase in plasma renin activity following the initial dose, as well as attenuated transient increase with subsequent doses.
10.2 Pharmacodynamics
Hypotensive Action
The nature of the hypotensive action of prazosin hydrochloride was studied both by in vitro and in vivo methodology. Intravenously administered prazosin hydrochloride in dogs caused prolonged hypotension and reduction in total peripheral resistance. Cardiac output, heart rate, and blood flow in the femoral, renal, and splanchnic vascular beds were increased transiently. Cardiac responses to electrical stimulation of cardioaccelerator nerves were not depressed, nor was there sympathetic ganglion or adrenergic neurone blockade. Although prazosin hydrochloride reversed the epinephrine pressor response in intact animals, vasodilator activity was only slightly diminished when the vessels were deprived of sympathetic tone by ganglionic blockade.
Physiologic and direct radioligand binding data from studies in experimental animals indicates that the hypotensive effect of prazosin hydrochloride ascribed to peripheral vasodilation is achieved primarily by competitive blockade of the vascular postsynaptic alpha1-adrenergic receptors. As prazosin acts preferentially on postsynaptic alpha1-adrenergic receptors, the feedback control of neuronal norepinephrine release by presynaptic alpha2-receptors remains unchanged.
In the dog, the hypotensive effect of prazosin hydrochloride intravenously was reversed by metaraminol and norephinephrine given by intravenous infusion.
Miscellaneous Actions
At doses considerably higher than those required for antihypertensive activity, prazosin hydrochloride has mild CNS depressant activity, decreases heart norepinephrine and adrenal epinephrine in rats, causes diuresis in anesthetized dogs, but fluid retention in conscious dogs and mice, and is hyperglycemic in rats.
In clinical studies in which lipid profiles were followed, there were generally no adverse changes noted between pre- and post-treatment lipids levels.
10.3 Pharmacokinetics
Absorption
Following oral administration of prazosin hydrochloride in normal volunteers and hypertensive patients, plasma concentrations reach a peak at about 3 hours with a plasma half-life of 2 to 3 hours.
Distribution
The drug is highly bound to plasma protein (97%). After chronic administration, no apparent drug accumulation was observed nor were any obvious decreases in plasma concentrations noted. Secondary plasma drug peaks and shoulders suggested probable enterohepatic circulation.
Metabolism
Animal studies indicate that prazosin hydrochloride is extensively metabolized, primarily by demethylation and conjugation. Similar metabolism has been documented in human studies.
Elimination
Animal studies indicate that prazosin hydrochloride is excreted (primarily as glucuronide conjugates) mainly via bile and feces. Similar excretion has been documented in human studies.
Special Populations and Conditions
- Pediatrics (< 18 years of age): The safety and efficacy of prazosin hydrochloride in pediatric patients under the age of 18 years has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
- Geriatrics (> 65 years of age): No data are available to Health Canada to establish differences in the safety and efficacy associated with the use of prazosin hydrochloride in geriatric patients.
- Sex: This information is not available for this drug product.
Pregnancy and Breast-feeding: Prazosin hydrochloride should be used during pregnancy only if in the opinion of the physician the potential benefit outweighs potential risk to mother and child. See 7.1.1 Pregnant Women.
Caution should be exercised when prazosin hydrochloride is administered to breast feeding mothers. See 7.1.2 Breast-feeding.
- Genetic Polymorphism: This information is not available for this drug product.
- Ethnic Origin: This information is not available for this drug product.
- Hepatic Insufficiency: This information is not available for this drug product.
- Renal Insufficiency: See 7 WARNINGS AND PRECAUTIONS, Renal.
- Obesity: This information is not available for this drug product.
11 STORAGE, STABILITY AND DISPOSAL
TEVA-PRAZOSIN should be stored between 15°C to 30°C and protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
None.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Prazosin hydrochloride
Chemical name: 1-(4-amino-6,7-dimethoxy-2-quinazolinyl-4-(2-furoyl)-piperazine monohydrochloride
Structural formula:
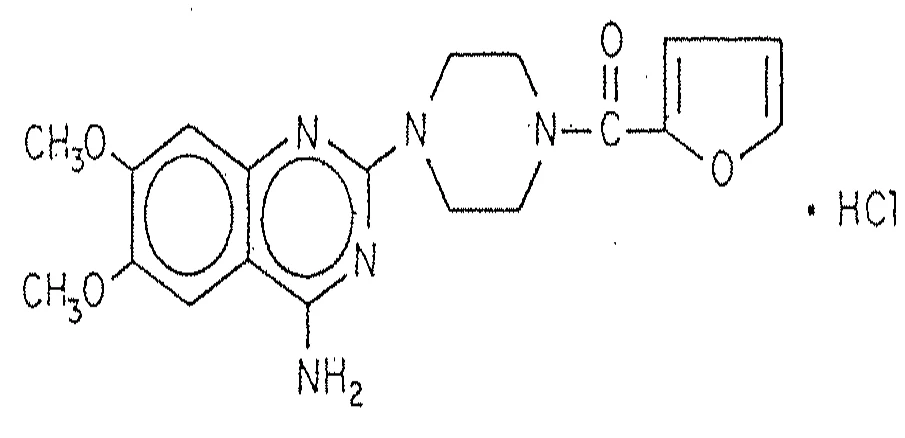
Molecular formula and molecular mass: C19H21N5O4•HCI & 419.87 g/mol
Physicochemical properties: Prazosin hydrochloride is a white crystalline substance which is slightly soluble in water and isotonic saline.
14 CLINICAL TRIALS
14.2 Comparative Bioavailability Studies
A randomized, two-way, single-dose, crossover comparative bioavailability study of TEVA-PRAZOSIN 5 mg tablets (Teva Canada Limited) and PrMINIPRESS® 5 mg tablets (Pfizer Canada Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 23 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Prazosin (1 x 5 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 200.2 205.0 (22.0) | 199.3 206.7 (28.2) | 100.3 | 94.7 - 106.3 |
AUCI (ng·h/mL) | 205.8 210.6 (21.7) | 206.2 213.5 (27.8) | 99.7 | 94.2 - 105.6 |
Cmax (ng/mL) | 44.0 45.5 (26.7) | 41.2 43.1 (31.4) | 106.4 | 97.5 - 116.1 |
Tmax3 (h) | 2.0 (1.0 – 3.0) | 2.5 (1.0 – 5.0) | ||
T½4 (h) | 2.6 (15.2) | 2.8 (16.3) | ||
1 TEVA-PRAZOSIN (prazosin hydrochloride) tablets, 5 mg (Teva Canada Limited)
2 PrMINIPRESS® (prazosin hydrochloride) tablets, 5 mg (Pfizer Canada Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV % only)
A randomized, single-dose, three-way, crossover comparative bioavailability study of TEVA-PRAZOSIN 1 mg tablets (Teva Canada Limited), TEVA-PRAZOSIN 2 mg tablets (Teva Canada Limited), and PrMINIPRESS® 2 mg tablets (Pfizer Canada Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 24 subjects that were included in the statistical analysis for the comparison of TEVA-PRAZOSIN 1 mg tablets (2 x 1 mg) and PrMINIPRESS® 2 mg tablets (1 x 2 mg) are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Prazosin (2 x 1 mg vs 1 x 2 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC8 (ng·h/mL) | 66.2 69.0 (27.4) | 62.6 65.2 (28.1) | 105.9 | 98.5 - 113.4 |
AUCT ng·h/mL) | 71.0 74.3 (28.5) | 67.2 69.9 (28.2) | 106.2 | 98.2 - 113.6 |
AUCI (ng·h/mL) | 74.9 78.2 (27.5) | 71.2 74.0 (27.3) | 105.7 | 98.3 - 112.5 |
Cmax (ng/mL) | 20.9 21.7 (25.8) | 18.1 19.0 (30.2) | 114.5 | 103.4 - 129.2 |
Tmax3 (h) | 0.8 (0.5 – 2.5) | 1.0 (0.5 – 2.5) | ||
T½4 (h) | 2.7 (26.8) | 2.6 (30.8) | ||
1 TEVA-PRAZOSIN (prazosin hydrochloride) tablets, 1 mg (Teva Canada Limited)
2 PrMINIPRESS® (prazosin hydrochloride) tablets, 2 mg (Pfizer Canada, Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV % only)
A randomized, single-dose, three-way, crossover comparative bioavailability study of TEVA-PRAZOSIN 1 mg tablets (Teva Canada Limited), TEVA-PRAZOSIN 2 mg tablets (Teva Canada Limited), and PrMINIPRESS® 2 mg tablets (Pfizer Canada Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 24 subjects that were included in the statistical analysis for the comparison of TEVA-PRAZOSIN 2 mg tablets and PrMINIPRESS® 2 mg tablets are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Prazosin (1 x 2 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC8 (ng·h/mL) | 64.2 66.4 (25.1) | 62.6 65.2 (28.1) | 101.9 | 95.6 - 110.0 |
AUCT (ng·h/mL) | 69.2 71.7 (25.5) | 67.2 69.9 (28.2) | 102.5 | 95.8 - 110.8 |
AUCI (ng·h/mL) | 73.6 76.0 (24.2) | 71.2 74.0 (27.3) | 102.7 | 96.6 - 110.6 |
Cmax (ng/mL) | 20.8 21.8 (30.8) | 18.1 19.0 (30.2) | 115.2 | 102.5 - 128.0 |
Tmax3 (h) | 1.0 (0.5 – 2.5) | 1.0 (0.5 – 2.5) | ||
T½4 (h) | 2.9 (30.2) | 2.6 (30.8) | ||
1 TEVA-PRAZOSIN (prazosin hydrochloride) tablets, 2 mg (Teva Canada Limited)
2 PrMINIPRESS® (prazosin hydrochloride) tablets, 2 mg (Pfizer Canada, Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV % only)
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute Toxicity
The results of single-dose acute toxicity studies on prazosin hydrochloride are presented in Table 3.
Table 3 - Acute Toxicity of Prazosin Hydrochloride
| Species | Sex | Oral LD50 mg/kg | Intraperitoneal LD50 (95% Confidence limits) mg/kg |
|---|---|---|---|
| Mouse | M & F | >5000 | 84 (62 – 113) |
| Rat | M & F | >2000 | 141 (121 – 165) |
The signs of toxicity observed following the administration of this compound were, for the most part, common to both mice and rats by both routes and included blanching, depression, decreased respiration, ptosis, writhing, ataxia, tremors and convulsions.
Mongrel dogs given 250 and 500 mg/kg as a single oral dose showed ataxia, depression, occasional diarrhea, relaxed nictitating membrane, ptosis, and occasional tremors. Tachycardia was also noted in the three dogs at 250 mg/kg. Anorexia was noted 48 hours post dose in one dog receiving 500 mg/kg.
Chronic Toxicity
Prazosin hydrochloride was administered to dogs in doses of 2, 10 and 25 mg/kg/day seven days per week for one year. Testicular atrophy and degeneration accompanied by prostatic atrophy and fibrosis occurred in male dogs receiving doses of 25 mg/kg/day.
(Urinary 17-ketosteroid excretion in human clinical studies was monitored in 105 patients for any possible effect on testicular function for periods ranging from 3 to 33 months. A trend analysis of the 17-ketosteroid data disclosed a seasonal variation, but did not suggest a drug effect. Routine semen analysis in 27 male patients on prazosin hydrochloride alone for up to 51 months revealed no semen abnormalities.)
Rats received prazosin hydrochloride in doses of 5, 25, 75 and 150 mg/kg/day for 18 months. During the first 18 weeks of study, drug-induced hepatocellular degeneration and/or necrosis and renal corticomedullary necrosis occurred at the dose level of 150 mg/kg; mild hepatocellular degenerative changes and/or necrosis were found at the dose level of 75 mg/kg.
Between 19 and 53 weeks, the following pathologic changes were observed at dose levels of 150 and 75 mg/kg: testicular necrosis with accompanying inguinal and/or scrotal adhesions; chronic nephrotoxic nephritis; degenerative folding and contracture of the retina (retinitis proliferans); adrenal plethora; gastric necrosis and hepatic necrosis. At the dose level of 25 mg/kg, there was a low percent incidence of testicular, renal and gastric alterations; since these same changes occurred in larger numbers of animals at the two higher dose levels, they appear drug-related.
Between 54 weeks and 18 months, the following changes occurred at dose levels of 150, 75 and 25 mg/kg: testicular atrophy and/or degeneration with accompanying inguinal and/or scrotal adhesions; retinitis proliferans (150 and 75 mg/kg levels only) and hepatic degeneration and/or necrosis. Additionally, bilateral cataracts (not observed previously) occurred at the dose levels of 150 and 75 mg/kg. Chronic nephritis and adrenal plethora (cystic degeneration) which previously (19 to 53 weeks) had a higher percent incidence at the dose levels of 150, 75 and 25 mg/kg, and 150 and 75 mg/kg respectively, appeared with approximately the same frequency at all dose levels including the controls.
Carcinogenicity
In a chronic study with rats, prazosin hydrochloride fed at levels up to 75 mg/kg/day for 18 months showed no evidence of carcinogenicity.
Reproductive and Developmental Toxicology
Reproductive and teratologic studies were carried out at dose levels of 25 and 75 mg/kg/day in rats and rabbits. No drug-induced changes were observed.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrMINIPRESS, tablets, 1 mg, 2 mg and 5 mg, submission control 277885, Product Monograph, AA Pharma Inc., (MAR 15, 2024)