


Product Monograph - Trulicity (Eli Lilly Canada, 0.75 mg, 1.5 mg)
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Subcutaneous | Solution for injection, 0.75 mg/0.5 mL and 1.5 mg/0.5 mL | Mannitol For a complete listing see Dosage Forms, Composition and Packaging section. |
DESCRIPTION
TRULICITY contains dulaglutide, which is a long-acting glucagon-like peptide 1 (GLP-1) receptor agonist. The molecule consists of 2 identical disulfide-linked chains, each containing a modified human GLP-1 analogue sequence covalently linked to a modified human immunoglobulin G4 (IgG4) heavy chain fragment (Fc) by a small peptide linker. The GLP-1 analogue portion of dulaglutide is approximately 90% homologous to native human GLP-1 (7-37).
TRULICITY is a clear, colourless sterile solution. Each single-use, prefilled syringe and single-use prefilled pen contains 0.5 mL of solution. Each 0.5 mL of TRULICITY solution contains 0.75 mg or 1.5 mg of dulaglutide.
INDICATIONS AND CLINICAL USE
TRULICITY is indicated for the once-weekly treatment of adult patients with type 2 diabetes mellitus to improve glycemic control, in combination with:
- diet and exercise in patients for whom metformin is inappropriate due to contraindication or intolerance.
- metformin, when diet and exercise plus maximal tolerated dose of metformin do not achieve adequate glycemic control.
- metformin and a sulfonylurea, when diet and exercise plus dual therapy with metformin and a sulfonylurea do not achieve adequate glycemic control.
sodium glucose co-transporter 2 inhibitor (SGLT2i) with metformin, when diet and exercise plus
SGLT2i with or without metformin do not achieve adequate glycemic control.
- basal insulin with metformin, when diet and exercise plus basal insulin with or without metformin do not achieve adequate glycemic control.
- prandial insulin with metformin, when diet and exercise plus basal or basal-bolus insulin therapy (up to two injections of basal or basal plus prandial insulin per day) with or without oral antihyperglycemic medications, do not achieve adequate glycemic control (see CLINICAL TRIALS).
TRULICITY is indicated as an adjunct to diet, exercise, and standard of care therapy to reduce the risk of non-fatal stroke in adults with type 2 diabetes mellitus who have multiple cardiovascular risk factors or established cardiovascular disease.
TRULICITY is not a substitute for insulin. TRULICITY should not be used in patients with Type 1 diabetes mellitus (formerly known as insulin-dependent diabetes mellitus or IDDM) or for the treatment of diabetic ketoacidosis.
Geriatrics (≥65 years of age):
No overall differences in safety or efficacy were observed in clinical trial subjects ≥65 years of age compared to younger patients, but greater sensitivity of some older individuals cannot be ruled out (see WARNINGS AND PRECAUTIONS, Special Populations; Geriatrics; DOSAGE AND ADMINISTRATION; and ACTION AND CLINICAL PHARMACOLOGY sections).
Pediatrics (<18 years of age):
The safety and efficacy of TRULICITY have not been studied in pediatric patients. Therefore, TRULICITY should not be used in this patient population.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
In patients with a personal or family history of medullary thyroid carcinoma or in patients with Multiple
Endocrine Neoplasia syndrome type 2 (MEN 2), (see WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis).
During Pregnancy or in breast-feeding women, (see WARNINGS AND PRECAUTIONS, Special
Populations).
WARNINGS AND PRECAUTIONS
In male and female rats, dulaglutide causes dose-dependent and treatment-duration-dependent thyroid C-cell tumors (adenomas and carcinoma) after lifetime exposure (see PART II, TOXICOLOGY). It is unknown whether TRULICITY causes thyroid C-cell tumors, including medullary thyroid carcinoma (MTC), in humans, as human relevance could not be ruled out by clinical or nonclinical studies.
TRULICITY is contraindicated in patients with a personal or family history of MTC and in patients with Multiple Endocrine Neoplasia syndrome type 2 (MEN 2). It is unknown whether monitoring with serum calcitonin or thyroid ultrasound will mitigate human risk of thyroid C-cell tumors. Patients should be counseled regarding the risk and symptoms of thyroid tumors (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, ADVERSE DRUG REACTIONS, and TOXICOLOGY).
General
TRULICITY should not be used in patients with type 1 diabetes mellitus or for the treatment of patients with diabetic ketoacidosis.
TRULICITY should not be administered intramuscularly.
Carcinogenesis and Mutagenesis
Risk of Thyroid C-cell Tumors
In both genders of rats in a two-year carcinogenicity study, dulaglutide caused a dose-related and treatment-duration dependent increase in the incidence of thyroid C-cell tumors (adenomas/carcinomas) at ≥7-fold the maximum recommended human dose (MRHD) of 1.5 mg per week based on area under the time-concentration curve (AUC) compared to controls (see PART II, TOXICOLOGY). A statistically significant increase in C-cell adenomas was observed in rats of both genders receiving dulaglutide at ≥7 times the human exposure. Numerical increases in C-cell carcinomas occurred at 58 times the MRHD based on AUC and were considered to be treatment related despite the absence of statistical significance. Dulaglutide did not produce increased incidences of thyroid C-cell tumors in a rasH2 transgenic mouse model of carcinogenicity.
It is unknown whether TRULICITY will cause thyroid C-cell tumors, including medullary thyroid cancer (MTC), in humans, as the human relevance of dulaglutide-induced rodent thyroid C-cell tumors could not be determined by clinical or nonclinical studies.
One (1) case of MTC was reported in a patient treated with TRULICITY. The patient with MTC had a markedly elevated calcitonin value at baseline, 8 times the upper limit of normal (ULN), suggesting pre-existing disease. This patient subsequently tested positive for a known RET (rearranged during transfection) proto-oncogene mutation.
TRULICITY is contraindicated in patients with a personal or family history of MTC or in patients with MEN 2. The clinical value of routine monitoring of serum calcitonin has not been established.
Patients should be counseled regarding the risk for MTC and the symptoms of thyroid tumours (e.g. a mass in the neck, dysphagia, dyspnea or persistent hoarseness).
Cardiovascular
Heart Rate Increase
TRULICITY causes an increase in heart rate (see ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology). Increases in heart rate may lead to worsening of cardiac conditions in patients with a history of ischemic heart disease or tachyarrhythmias. Caution should be observed in these patient populations.
In studies in patients with type 2 diabetes, TRULICITY 0.75 mg and 1.5 mg were associated with mean increases in heart rate of 2 to 4 beats per minute (bpm) and a 1.3% (TRULICITY 0.75 mg) and 2.2% (TRULICITY 1.5 mg) incidence of sinus tachycardia with a concomitant increase from baseline ≥15 bpm (see ADVERSE REACTIONS).
PR Interval Prolongation
TRULICITY causes a prolongation of the PR interval of the electrocardiogram (see ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology). Prolongation of the PR interval has also been associated with an increased risk of incident atrial fibrillation; therefore, caution is warranted in patients with a history of atrial fibrillation. Caution should be observed in patients with underlying structural heart disease, pre-existing conduction system abnormalities, ischemic heart disease, or cardiomyopathies, as these patients may be at increased risk for developing cardiac conduction abnormalities.
In studies in patients with type 2 diabetes, TRULICITY is associated with mean increases from baseline in PR interval of 2 to 3 milliseconds (msec) and a 1.7% (0.75 mg) and 2.3% (1.5 mg) incidence of first-degree AV block (see ADVERSE REACTIONS).
Endocrine and Metabolism
Hypoglycemia
Patients receiving TRULICITY in combination with an insulin secretagogue (for example, a sulfonylurea) or insulin may have an increased risk of hypoglycemia. The risk of hypoglycemia may be lowered by a reduction in the dose of the insulin secretagogue or insulin (see ADVERSE REACTIONS, Hypoglycemia).
Gastrointestinal
Severe Gastrointestinal Disease
Use of GLP-1 receptor agonists may be associated with gastrointestinal adverse reactions (see ADVERSE REACTIONS, Gastrointestinal Events). TRULICITY has not been studied in patients with severe gastrointestinal disease, including severe gastroparesis and is therefore not recommended in these patients.
In placebo-controlled clinical trials, gastrointestinal events were more frequently reported for TRULICITY compared to placebo and included nausea, diarrhea, and vomiting (see ADVERSE REACTIONS, Gastrointestinal Events).
Hepatic/Biliary/Pancreas
Pancreatitis
Pancreatitis has been reported with GLP-1 receptor agonists, including TRULICITY (see ADVERSE REACTIONS). After initiation of TRULICITY, observe patients carefully for signs and symptoms of pancreatitis, including persistent severe abdominal pain. If pancreatitis is suspected, TRULICITY and other suspect medications should be discontinued promptly, confirmatory tests should be performed and appropriate management should be initiated. If pancreatitis is confirmed, TRULICITY should not be restarted. TRULICITY has not been studied in patients with a prior history of pancreatitis. Consider other antidiabetic therapies in patients with a history of pancreatitis.
Hypersensitivity Reactions
Systemic hypersensitivity adverse reactions, sometimes severe (e.g., severe urticaria, systemic rash, facial edema, lip swelling) occurred in 0.5% of patients on TRULICITY in the four Phase 2 and five Phase 3 studies. There have been postmarketing reports of serious hypersensitivity reactions (e.g., anaphylactic reactions and angioedema) in patients treated with TRULICITY. If a hypersensitivity reaction occurs, discontinue use of TRULICITY and other suspect medications and promptly seek medical advice. TRULICITY should not be used following a hypersensitivity reaction (see CONTRAINDICATIONS).
Angioedema has also been reported with other GLP-1 receptor agonists. Use caution in a patient with a history of angioedema with another GLP-1 receptor agonist because it is unknown whether such patients will be predisposed to angioedema with TRULICITY.
Renal
Use of GLP-1 receptor agonists may be associated with gastrointestinal adverse reactions, which include nausea, vomiting, and diarrhea. These events may lead to dehydration, which could cause a deterioration in renal function including acute renal failure.
Patients treated with TRULICITY should be advised of the potential risk of dehydration and take precautions to avoid fluid depletion.
Special Populations
Pregnant Women:
No clinical trials in pregnant women have been conducted. Studies in animals have shown reproductive and developmental toxicity, including teratogenicity (see PART II: TOXICOLOGY).
TRULICITY should not be used during pregnancy (see CONTRAINDICATIONS). If a patient wishes to become pregnant, TRULICITY should be discontinued at least 1 month before due to the long wash out period for TRULICITY.
Nursing Women:
It is not known whether TRULICITY is excreted into human milk during lactation. Decreased body weight in offspring was observed in mice treated with TRULICITY during gestation and lactation (see TOXICOLOGY). Because of the potential tumorigenicity shown for GLP-1 receptor agonists in rodent studies, women who are nursing should discontinue TRULICITY treatment.
Pediatrics (<18 years of age):
The safety and effectiveness of TRULICITY have not been studied in pediatric patients. TRULICITY is not indicated for use in pediatric patients.
Geriatrics (≥65 years of age):
No dose adjustment is required in patients over 65 years of age (see ACTION AND CLINICAL PHARMACOLOGY).
Across nine Phase 2 and 3 clinical studies with TRULICITY, a total of 990 (16.5%) patients were ≥65 to <75 years, 115 (1.9%) were ≥75 to <85 years, and 3 (<0.1%) were ≥85 years of age. No overall differences in safety or efficacy were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
In the TRULICITY 1.5 mg treatment arm of the REWIND trial (see CLINICAL STUDIES), a total of 2619 (52.9%) patients were ≥65 years of age, and 484 (9.8%) patients were ≥75 years of age at baseline. No overall differences in safety or efficacy were observed based on age.
Hepatic Impairment
There is limited clinical experience in patients with mild, moderate, or severe hepatic impairment. Therefore, TRULICITY should be used with caution in these patient populations.
Renal Impairment
In patients treated with GLP-1 receptor agonists, there have been postmarketing reports of acute renal failure and worsening of chronic renal failure, which may sometimes require hemodialysis. Some of these events were reported in patients without known underlying renal disease. A majority of reported events occurred in patients who had experienced nausea, vomiting, diarrhea, or dehydration.
Because these reactions may worsen renal function, use caution when initiating or escalating doses of TRULICITY in patients with renal impairment. Monitor renal function in patients with renal impairment reporting severe adverse gastrointestinal reactions.
There is limited clinical experience in patients with end-stage renal disease (ESRD) (estimated glomerular filtration rate [eGFR] <15 mL/min/1.73 m2). TRULICITY should be used with caution in this patient population.
In the TRULICITY 1.5 mg arm of the REWIND trial (see CLINICAL STUDIES), 2435 (50.2%) patients had mild renal impairment, 1031 (21.2%) patients had moderate renal impairment, and 50 (1.0%) patients had severe renal impairment at baseline. Safety and efficacy analyses compared patients with moderate to severe renal impairment (eGFR <60 mL/min/1.73 m2) to patients with mild or no renal impairment (eGFR ≥ 60 mL/min/1.73 m2). No overall differences in safety or efficacy were observed between these 2 subgroups.
Cardiovascular – Patients with Recent Cardiovascular Event
In clinical trials of TRULICITY, subjects with an acute coronary or cerebrovascular event, within the 2 months prior to randomization, were not studied. Therefore, TRULICITY should be used with caution in this population.
Monitoring and Laboratory Tests
Response to all diabetic therapies should be monitored by periodic measurements of blood glucose and HbA1c levels, with a goal of decreasing these levels towards the normal range. HbA1c is especially useful for evaluating long-term glycemic control. Regular self-monitoring of blood glucose is not needed in order to adjust the dose of TRULICITY. However, when initiating treatment with TRULICITY in combination with a sulfonylurea or insulin, blood glucose self-monitoring may become necessary to reduce the dose of the sulfonylurea or insulin in order to reduce the risk of hypoglycemia.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The safety of TRULICITY in patients with type 2 diabetes mellitus was evaluated across nine Phase 2 and 3 clinical trials, including a total of 4006 patients (for 3531 patient-years) who received TRULICITY. A total of 3045 patients received TRULICITY for at least 24 weeks, with 2279 patients continuing treatment through at least 50 weeks. A total of 369 patients were treated with TRULICITY for approximately 2 years.
In placebo-controlled registration studies of at least 26-week duration, the incidence of discontinuation due to adverse events was 2.6% for TRULICITY 0.75 mg and 6.1% for TRULICITY 1.5 mg versus 3.7% for placebo. Through the full duration of the studies (up to 104 weeks), the incidence of discontinuation due to adverse events was 5.1% and 8.4% for TRULICITY 0.75 mg and 1.5 mg respectively. The most frequent adverse events leading to discontinuation for 0.75 mg and 1.5 mg TRULICITY were nausea (1.0%, 1.9%), diarrhea (0.5%, 0.6%), and vomiting (0.4%, 0.6%).
In placebo-controlled registration studies of 26-weeks duration, the proportion of patients reporting at least 1 TEAE was 68.1% in the TRULICITY 0.75 mg group, 71.6% in the TRULICITY 1.5 mg group, and 66.7% with placebo. Gastrointestinal adverse events, including nausea (12.4% for 0.75 mg, 21.1% for 1.5 mg versus 5.3% for placebo), diarrhea (8.9%, 12.6% versus 6.7%), and vomiting (6.0%, 12.6% versus 2.3%) were the most common adverse events reported with TRULICITY and were reported more frequently than with placebo-treated patients. In studies up to 104 weeks, GI events continued to be the most common TEAEs reported.
In placebo-controlled registration studies of 26-weeks duration, the incidence of serious adverse events (SAEs) was 3.9% for patients treated with TRULICITY 0.75 mg, 4.4% for patients treated with TRULICITY 1.5 mg and 4.4% for patients treated with placebo.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 1 provides a listing of the treatment-emergent adverse events reported with a frequency of ≥1% and occurring more frequently in TRULICITY-treated patients.
Table 1: Treatment Emergent Adverse Events Occurring in >1% in Either TRULICITY Group and
Occurring More Frequently with TRULICITY up to 104 Weeks
| Adverse Event | TRULICITYa | Placeboa (N = 568) n (%) | TRULICITYb | All Comparatorsb (N = 1844) n (%) | ||
| 0.75 mg (N = 836) n (%) | 1.5 mg (N = 834) n (%) | 0.75 mg (N = 1671) n (%) | 1.5 mg (N = 1671) n (%) | |||
| Blood and Lymphatic System Disorders | ||||||
| Anemia | 7 (0.8) | 10 (1.2) | 3 (0.5) | 21 (1.3) | 22 (1.3) | 20 (1.1) |
| Cardiac Disorders | ||||||
| Angina pectoris | - | - | - | 16 (1.0) | 5 (0.3) | 16 (0.9) |
| Palpitations | - | - | - | 19 (1.1) | 8 (0.5) | 13 (0.7) |
| Ear and Labyrinth Disorders | ||||||
| Vertigo | - | - | - | 17 (1.0) | 12 (0.7) | 11 (0.6) |
| Gastrointestinal Disorders | ||||||
| Nausea | 104 (12.4) | 176 (21.1) | 30 (5.3) | 216 (12.9) | 355 (21.2) | 180 (9.8) |
| Diarrhea | 74 (8.9) | 105 (12.6) | 38 (6.7) | 179 (10.7) | 229 (13.7) | 143 (7.8) |
| Vomiting | 50 (6.0) | 105 (12.6) | 13 (2.3) | 114 (6.8) | 192 (11.5) | 78 (4.2) |
| Constipation | 30 (3.6) | 31 (3.7) | 4 (0.7) | 56 (3.4) | 82 (4.9) | 23 (1.2) |
| Abdominal distension | 24 (2.9) | 19 (2.3) | 4 (0.7) | 49 (2.9) | 42 (2.5) | 24 (1.3) |
| Dyspepsia | 34 (4.1) | 48 (5.8) | 13 (2.3) | 68 (4.1) | 115 (6.9) | 60 (3.3) |
| Abdominal pain | 17 (2.0) | 25 (3.0) | 11 (1.9) | 42 (2.5) | 67 (4.0) | 41 (2.2) |
| Abdominal pain upper | 19 (2.3) | 28 (3.4) | 9 (1.6) | 52 (3.1) | 70 (4.2) | 41 (2.2) |
| Abdominal discomfort | 16 (1.9) | 24 (2.9) | 8 (1.4) | 25 (1.5) | 41 (2.5) | 26 (1.4) |
| Flatulence | 12 (1.4) | 28 (3.4) | 8 (1.4) | 23 (1.4) | 43 (2.6) | 17 (0.9) |
| Gastritis | - | - | - | 21 (1.3) | 25 (1.5) | 25 (1.4) |
| Eructation | 5 (0.6) | 13 (1.6) | 1 (0.2) | 16 (1.0) | 23 (1.4) | 7 (0.4) |
| Hyperchlorhydria | 6 (0.7) | 10 (1.2) | 1 (0.2) | 9 (0.5) | 17 (1.0) | 4 (0.2) |
| Gastroesophageal reflux disease | 14 (1.7) | 17 (2.0) | 3 (0.5) | 33 (2.0) | 27 (1.6) | 30 (1.6) |
| General Disorders and Administration Site Conditions | ||||||
| Fatigue | 22 (2.6) | 29 (3.5) | 10 (1.8) | 44 (2.6) | 58 (3.5) | 58 (3.1) |
| Asthenia | 10 (1.2) | 17 (2.0) | 4 (0.7) | 23 (1.4) | 29 (1.7) | 20 (1.1) |
| Pain | 9 (1.1) | 6 (0.7) | 5 (0.9) | 21 (1.3) | 12 (0.7) | 16 (0.9) |
| Edema peripheral | 18 (2.2) | 5 (0.6) | 11 (1.9) | 40 (2.4) | 27 (1.6) | 42 (2.3) |
| Non-cardiac chest pain | - | - | - | 27 (1.6) | 22 (1.3) | 29 (1.6) |
| Injection site haematoma | 9 (1.1) | 4 (0.5) | 2 (0.4) | - | - | - |
| Hepatobiliary Disorders | ||||||
| Hepatic steatosis | - | - | - | 14 (0.8) | 19 (1.1) | 13 (0.7) |
| Infections and Infestations | ||||||
| Nasopharyngitis | 65 (7.8) | 65 (7.8) | 42 (7.4) | - | - | - |
| Upper respiratory tract infection | 33 (3.9) | 30 (3.6) | 20 (3.5) | 89 (5.3) | 85 (5.1) | 93 (5.0) |
| Gastroenteritis | 5 (0.6) | 14 (1.7) | 3 (0.5) | 30 (1.8) | 44 (2.6) | 34 (1.8) |
| Urinary tract infection | 32 (3.8) | 35 (4.2) | 21 (3.7) | 85 (5.1) | 80 (4.8) | 89 (4.8) |
| Influenza | 22 (2.6) | 17 (2.0) | 10 (1.8) | 80 (4.8) | 69 (4.1) | 68 (3.7) |
| Pharyngitis | 8 (1.0) | 14 (1.7) | 4 (0.7) | 30 (1.8) | 38 (2.3) | 28 (1.5) |
| Bronchitis | 9 (1.1) | 10 (1.2) | 6 (1.1) | - | - | - |
| Pneumonia | - | - | - | 19 (1.1) | 13 (0.8) | 14 (0.8) |
| Adverse Event | TRULICITYa | Placeboa (N = 568) n (%) | TRULICITYb | All Comparatorsb (N = 1844) n (%) | ||
| 0.75 mg (N = 836) n (%) | 1.5 mg (N = 834) n (%) | 0.75 mg (N = 1671) n (%) | 1.5 mg (N = 1671) n (%) | |||
| Sinusitis | 15 (1.8) | 13 (1.6) | 10 (1.8) | 41 (2.5) | 40 (2.4) | 45 (2.4) |
| Cystitis | - | - | - | 17 (1.0) | 10 (0.6) | 16 (0.9) |
| Injury, Poisoning and Procedural Complications | ||||||
| Ligament sprain | 6 (0.7) | 8 (1.0) | 1 (0.2) | - | - | - |
| Investigations | ||||||
| Lipase increased | 15 (1.8) | 24 (2.9) | 10 (1.8) | 42 (2.5) | 41 (2.5) | 39 (2.1) |
| Amylase increased | 8 (1.0) | 15 (1.8) | 5 (0.9) | 25 (1.5) | 22 (1.3) | 19 (1.0) |
| Pancreatic enzymes increased | 6 (0.7) | 8 (1.0) | 3 (0.5) | 18 (1.1) | 30 (1.8) | 12 (0.7) |
| Weight decreased | 3 (0.4) | 17 (2.0) | 1 (0.2) | 5 (0.3) | 21 (1.3) | 4 (0.2) |
| Metabolic and Nutrition Disorders | ||||||
| Decreased appetite | 41 (4.9) | 72 (8.6) | 9 (1.6) | 85 (5.1) | 129 (7.7) | 39 (2.1) |
| Dyslipidemia | 5 (0.6) | 9 (1.1) | 5 (0.9) | 22 (1.3) | 31 (1.9) | 21 (1.1) |
| Musculoskeletal and Connective Tissue Disorders | ||||||
| Pain in extremity | - | - | - | 57 (3.4) | 50 (3.0) | 55 (3.0) |
| Arthralgia | 26 (3.1) | 22 (2.6) | 17 (3.0) | 67 (4.0) | 47 (2.8) | 74 (4.0) |
| Back pain | - | - | - | 78 (4.7) | 65 (3.9) | 87 (4.7) |
| Osteoarthritis | - | - | - | 19 (1.1) | 21 (1.3) | 24 (1.3) |
| Nervous System Disorders | ||||||
| Headache | 50 (6.0) | 67 (8.0) | 40 (7.0) | 111 (6.6) | 133 (8.0) | 140 (7.6) |
| Dizziness | 31 (3.7) | 31 (3.7) | 13 (2.3) | - | - | - |
| Sciatica | 5 (0.6) | 3 (0.4) | 3 (0.5) | 18 (1.1) | 13 (0.8) | 16 (0.9) |
| Hypoesthesia | - | - | - | 7 (0.4) | 17 (1.0) | 14 (0.8) |
| Psychiatric Disorders | ||||||
| Insomnia | 6 (0.7) | 14 (1.7) | 7 (1.2) | 11 (0.7) | 27 (1.6) | 27 (1.5) |
| Anxiety | 8 (1.0) | 3 (0.4) | 4 (0.7) | 21 (1.3) | 13 (0.8) | 19 (1.0) |
| Renal and Urinary Disorders | ||||||
| Nephrolithiasis | 8 (1.0) | 10 (1.2) | 4 (0.7) | 14 (0.8) | 16 (1.0) | 12 (0.7) |
| Diabetic nephropathy | 0 (0.0) | 8 (1.0) | 2 (0.4) | - | - | - |
| Respiratory, Thoracic and Mediastinal Disorders | ||||||
| Cough | - | - | - | 49 (2.9) | 61 (3.7) | 62 (3.4) |
| Sinus congestion | 5 (0.6) | 9 (1.1) | 3 (0.5) | - | - | - |
| Vascular Disorders | ||||||
| Hypertension | - | - | - | 42 (2.5) | 50 (3.0) | 55 (3.0) |
a Includes placebo-controlled studies of 26 weeks planned treatment period. Mean duration of exposure: 24.1 weeks for TRULICITY 0.75 mg, 23.5 weeks for TRULICITY 1.5 mg and 22.8 weeks for placebo.
b Includes all studies of at least 26-weeks and up to 104-weeks planned treatment period, including the placebo-controlled studies. Mean duration of exposure: 52.5 weeks for TRULICITY 0.75 mg, 51.4 weeks for TRULICITY 1.5 mg and 54.0 weeks for all comparators.
In Study GBDE, a 26-week combination study of TRULICITY plus metformin versus liraglutide plus metformin, the incidence of TEAEs was 61.9% for patients who received TRULICITY 1.5 mg once weekly and 63.0% for patients who received liraglutide 1.8 mg once daily. The 3 most frequently reported TEAEs overall through Week 26 were nausea, diarrhea, and headache.
The incidence of patients discontinuing the study or study drug due to adverse events was 6.0% in both the TRULICITY and liraglutide treatment groups. The most common gastrointestinal events resulting in discontinuation of the drug and/or study were nausea (TRULICITY, 1.7%; liraglutide, 1.7%) and diarrhea (TRULICITY, 0.7%; liraglutide, 1.3%).
In total, 16 (2.7%) patients (TRULICITY, 5 [1.7%]; and liraglutide, 11 [3.7%]) experienced ≥1 SAE through Week 26.
In Study GBDI, a 28-week combination study of TRULICITY plus titrated basal insulin with/without metformin versus placebo plus titrated basal insulin with/without metformin, the incidence of TEAEs was 64.0% for patients who received TRULICITY 1.5 mg once weekly and 50.0% for patients who received placebo once weekly. The 3 most frequently reported TEAEs for TRULICITY through Week 28 were nausea (12.0%), diarrhea (11.3%), and upper respiratory tract infection (7.3%).
The incidence of patients discontinuing the study due to adverse events was 4.0% in the TRULICITY group and 1.3% in the placebo treatment group. The most common gastrointestinal events resulting in discontinuation were diarrhea (TRULICITY, 1.3%; placebo, 0.0%), abdominal discomfort (TRULICITY, 0.7%; placebo, 0.0%), gastritis (TRULICITY, 0.7%; placebo, 0.0%), vomiting (TRULICITY, 0.7%; placebo, 0.0%), and nausea (TRULICITY 0.0%; placebo 0.7%).
In total, 16/300 patients (TRULICITY, 9/150 [6.0%]; and placebo, 7/150 [4.7%]) experienced ≥1 SAE through Week 28.
In Study GBDX, a 52-week combination study of TRULICITY plus titrated insulin lispro versus titrated insulin glargine plus titrated insulin lispro in patients with moderate to severe CKD (eGFR <60 and ≥15 mL/min/1.73 m2), the incidence of TEAEs was 88.4%, 89.6%, and 81.4% for patients who received TRULICITY 0.75 mg once weekly, TRULICITY 1.5 mg once weekly, and titrated insulin glargine daily, respectively. The most frequently reported TEAEs overall through Week 52 were blood creatinine increased (40.3%), diarrhea (13.4%), nausea (12.8%), and glomerular filtration rate decreased (10.4%).
The incidence of patients discontinuing the study or study drug due to adverse events was 10.0%, 12.5%, and 6.2% for patients receiving TRULICITY 0.75 mg once weekly, TRULICITY 1.5 mg once weekly, and titrated insulin glargine daily, respectively. The three most common gastrointestinal events resulting in discontinuation of the drug and/or study were diarrhea (TRULICITY 0.75 mg once weekly 1.1%, TRULICITY 1.5 mg once weekly 2.6%, titrated insulin glargine 0%), nausea (TRULICITY 0.75 mg once weekly 0.5%, TRULICITY 1.5 mg once weekly 1.6%, titrated insulin glargine 0%) and vomiting (TRULICITY 0.75 mg once weekly 0.5%, TRULICITY 1.5 mg once weekly 1.6%, titrated insulin glargine 0%).
In total, 135 (23.4%) patients (TRULICITY 0.75 mg once weekly, 45 [23.7%]; TRULICITY 1.5 mg once weekly, 38 [19.8%]; and titrated insulin glargine, 52 [26.8%]) experienced ≥1 SAE through Week 52.
In Study GBGE, a 24-week combination study of TRULICITY versus placebo, both as add-on to sodium glucose co-transporter 2 inhibitor (SGLT2i) therapy with or without metformin (≥1500 mg/day), the incidence of TEAEs was 58.9 %, 66.9%, and 57.9% for patients who received TRULICITY 0.75 mg once weekly, TRULICITY 1.5 mg once weekly, and patients who received placebo, respectively. The most frequently reported TEAEs overall through Week 24 were back pain (8.3%), nausea (7.8%), viral upper respiratory infection (6.6%), diarrhea (6.1%), and headache (6.1%).
The incidence of patients discontinuing the study or study drug due to adverse events was 0.7%, 4.9%, and 0.7% for patients receiving TRULICITY 0.75 mg once weekly, TRULICITY 1.5 mg once weekly, and placebo, respectively. Five patients on TRULICITY 1.5 mg once weekly discontinued study or study drug due to GI adverse events (nausea 2 patients, abdominal pain 2 patients, abdominal distention 1 patient).
In total, 14 (3.3%) patients who received study drug (TRULICITY 0.75 mg once weekly, 4 [2.8%]; TRULICITY 1.5 mg once weekly, 5 [3.5%]; and placebo, 5 [3.6%]) experienced ≥1 SAE through Week 24. One patient randomized to TRULICITY 0.75 mg had a SAE but never received study drug.
In Study GBDJ (REWIND), a long-term (median duration of follow-up was 5.4 years; median treatment duration was 5.2 years) cardiovascular (CV) event-driven study of TRULICITY versus placebo, both added to standard of care, the incidence of TEAEs was 92.4% for patients who received TRULICITY 1.5 mg once weekly and 91.6% for patients who received placebo once weekly. The 3 most frequently reported TEAEs for TRULICITY were nausea (14.9%), diarrhea (13.6%), and urinary tract infection (12.0%).
The incidence of patients permanently discontinuing the study drug due to adverse events was 9.1% in the TRULICITY group and 6.3% in the placebo group. The difference was primarily due to the higher incidence of gastrointestinal AEs leading to study drug discontinuation in the TRULICITY study arm. The most common gastrointestinal events resulting in discontinuation of study drug were nausea (TRULICITY 1.3%; placebo 0.1%). diarrhea (TRULICITY 0.7%; placebo 0.2%), vomiting (TRULICITY 0.6%; placebo 0.1%), dyspepsia (TRULICITY 0.2%; placebo 0.0%).
In total, 4053 patients (TRULICITY, 1997 [40.4%]; and placebo, 2056 [41.5%]) experienced ≥1 SAE.
Less Common Clinical Trial Adverse Drug Reactions (≥0.5% and <1%)
Cardiac disorders: palpitations, tachycardia, myocardial infarction
Ear and labyrinth disorders: vertigo
Eye disorders: conjunctivitis, vision blurred
Gastrointestinal disorders: abdominal pain lower, dry mouth, colitis
General disorders and administration site conditions: malaise, edema
Hepatobiliary disorders: cholelithiasis, hepatic steatosis
Immune system disorders: seasonal allergy
Infections and infestations: gastroenteritis viral, pneumonia, tooth infection, ear infection, lower respiratory tract infection, tinea pedis, tonsillitis
Injury, poisoning and procedural complications: accidental overdose, contusion, excoriation, muscle strain Investigations: blood calcitonin increased, blood creatine phosphokinase increased, gamma-glutamyltransferase increased
Metabolism and nutrition disorders: hypertriglyceridemia, vitamin D deficiency, hypokalemia Musculoskeletal and connective tissue: osteoporosis
Neoplasms benign, malignant and unspecified (includes cysts and polyps): basal cell carcinoma Nervous system disorders: migraine, diabetic neuropathy, sciatica, dysgeusia, syncope Renal and urinary disorders: proteinuria
Respiratory, thoracic and mediastinal disorders: asthma, nasal congestion, rhinorrhea Skin and subcutaneous tissue disorders: rash, pruritus, alopecia, hyperhidrosis, dermatitis contact
Cardiovascular
Heart Rate Increase
TRULICITY 0.75 mg and 1.5 mg were associated with mean increases in heart rate of 2 to 4 beats per minute (bpm) (see WARNINGS AND PRECAUTIONS, Cardiovascular; DRUG INTERACTIONS; ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology).
Adverse reactions of sinus tachycardia were reported in 3.0%, 2.8%, and 5.6% of patients treated with placebo, TRULICITY 0.75 mg and TRULICITY 1.5 mg, respectively. Persistence of sinus tachycardia (reported at more than 2 visits) was reported in 0.2%, 0.4% and 1.6% of patients treated with placebo, TRULICITY 0.75 mg and
TRULICITY 1.5 mg, respectively. Episodes of sinus tachycardia, associated with a concomitant increase from baseline in heart rate of ≥15 beats per minute, were reported in 0.7%, 1.3% and 2.2% of patient treated with placebo, TRULICITY 0.75 mg and TRULICITY 1.5 mg, respectively.
First Degree AV Block/PR Interval Prolongation
A mean increase from baseline in PR interval of 2-3 milliseconds was observed in TRULICITY-treated patients in contrast to a mean decrease of 0.9 milliseconds in placebo-treated patients. The adverse reaction of first degree AV block occurred more frequently in patients treated with TRULICITY than placebo (0.9%, 1.7% and 2.3% for placebo, TRULICITY 0.75 mg and TRULICITY 1.5 mg, respectively). On electrocardiograms, a PR interval increase to at least 220 milliseconds was observed in 0.7%, 2.5% and 3.2% of patients treated with placebo, TRULICITY 0.75 mg and TRULICITY 1.5 mg, respectively (see WARNINGS AND PRECAUTIONS, Cardiovascular; DRUG INTERACTIONS; ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology).
Pancreatitis
In Phase 2 and 3 studies, 19 patients (placebo or active comparator: 7; dulaglutide: 12) had TEAEs of pancreatitis reported by investigators. Nine (9) patients [placebo: 0.1% (1 of 703); sitagliptin: 0.7% (3 of 439); dulaglutide: 0.1% (5 of 4006)] were determined to have pancreatitis by adjudication. Six of these patients were considered to have acute pancreatitis, 2- chronic pancreatitis, and 1 -type unknown.
Dulaglutide was associated with increases in lipase, pancreatic amylase and, total amylase. Patients treated with TRULICITY had mean increases from baseline in lipase and/or pancreatic amylase of 14% to 20% compared to a mean increases of up to 3% in the placebo treated patients.
Gastrointestinal (GI) Events
In studies up to 104 weeks in duration, gastrointestinal adverse events were reported in 34.5% and 43.9% of TRULICITY-treated patients on 0.75 mg and 1.5 mg respectively. Events that were reported most frequently were nausea (12.9% for 0.75 mg and 21.2% for 1.5 mg), vomiting (6.8% for 0.75 mg and 11.5% for 1.5 mg), and diarrhea (10.7% for 0.75 mg and 13.7% for 1.5 mg).
The proportion of patients experiencing nausea was dose dependent, and when examined by time period, the prevalence also peaked in the first 2 weeks. The prevalence over time stabilized by approximately 6 to 8 weeks (3% for 0.75 mg and 6% for 1.5 mg) (see Figure 1).
Through the full duration of treatment, discontinuations due to nausea, diarrhea, and vomiting were reported in 1.0%, 0.5%, and 0.4%, respectively in 0.75 mg TRULICITY-treated patients and in 1.9%, 0.6%, and 0.6%, respectively in 1.5 mg TRULICITY-treated patients and were generally reported within the first 4-6 weeks of the trials.
In Study GBDJ (REWIND), cholelithiasis occurred at a rate of 0.62/100 patient-years in TRULICITY-treated patients and 0.56/100 patient-years in placebo-treated patients after adjusting for prior cholecystectomy. Serious events of acute cholecystitis were reported in 0.5% and 0.3% of patients on TRULICITY and placebo respectively.
In the pool of placebo-controlled trials, gastrointestinal adverse reactions were reported more frequently among patients receiving TRULICITY than placebo (placebo: 21.3%, 0.75 mg: 31.6%, 1.5 mg: 41.0%). Investigators graded the severity of gastrointestinal adverse reactions occurring on 0.75 mg and 1.5 mg of TRULICITY as “mild” in 58% and 48% of cases, respectively, “moderate” in 35% and 42% of cases, respectively, or “severe” in 7% and 11% of cases, respectively. More patients in TRULICITY 0.75 mg (1.3%) and 1.5 mg (3.5%) groups than placebo (0.2%) discontinued treatment due to gastrointestinal adverse events.
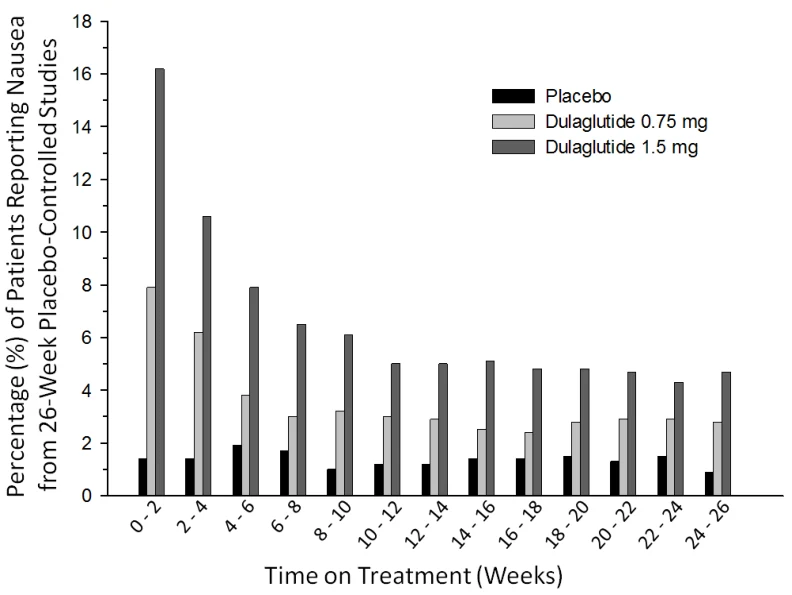
Figure 1: Prevalence of Nausea Symptoms
Injection Site Reactions
In the placebo –controlled clinical trials, injection site adverse events were reported in 38 (1.7%) dulaglutide treated patients compared to 6 (0.9%) patients in the placebo group. Injection site hematoma was the most frequently reported injection site reaction for both the placebo (3, 0.4%) and all dulaglutide (17, 0.8%) treatment groups. Injection site pain (6, 0.3%) and erythema (4, 0.2%) were only reported in the dulaglutide treatment group. Two dulaglutide-treated patients discontinued study drug due to injection site reaction.
In studies of up to 104 weeks, 1.9% of patients in TRULICITY 0.75 mg and 1.5 mg groups reported injection site reactions. Again injection site hematoma was the most commonly reported preferred term (TRULICITY 0.75 mg: 15, 0.9% and TRULICITY 1.5 mg: 10, 0.6%). One patient in this group discontinued study drug due to injection site reaction.
Across the clinical trials of 26 up to 104 week duration, potentially immune-mediated injection site adverse events (e.g., rash, erythema) have been reported in 0.5% and 0.7% of patients receiving TRULICITY 0.75 mg and 1.5 mg, respectively.
Immunogenicity
Across four Phase 2 and five Phase 3 clinical studies, 64 (1.6%) dulaglutide treated patients developed dulaglutide anti-drug antibodies (ADA). No dulaglutide-treated patients who developed dulaglutide ADAs reported a systemic hypersensitivity reaction. Patients with treatment-emergent dulaglutide ADA had significantly higher incidence of immune-mediated injection site adverse events (3.1%; 2 of 64 patients) compared to patients who did not develop treatment-emergent dulaglutide ADA (0.5%; 18 of 3843) patients. Of the 64 dulaglutide-treated patients that developed dulaglutide ADAs, 34 patients (0.9% of the overall population) had dulaglutide-neutralizing antibodies, and 36 patients (0.9% of the overall population) developed antibodies against native GLP-1.
Hypersensitivity
In clinical studies, systemic hypersensitivity events (e.g. severe urticaria, systemic rash, facial edema, lip swelling) have been reported in 0.5% of patients receiving TRULICITY.
Hypoglycemia
When TRULICITY was used as monotherapy or in combination with a non-secretagogue, documented symptomatic hypoglycemia occurred in 2.6% to 6.3% of patients treated with 0.75 mg and in 5.6% to 10.9% of patients treated with 1.5 mg. No episodes of severe hypoglycemia were reported.
When TRULICITY was used in combination with a sulfonylurea plus metformin, documented symptomatic hypoglycemia occurred in 39% of patients treated with 0.75 mg and 40.3% of patients treated with 1.5 mg. Severe hypoglycemia events occurred in 0% of patients treated with TRULICITY 0.75 mg and 0.7% of patients treated with TRULICITY 1.5 mg.
When TRULICITY was used in combination with insulin glargine, documented symptomatic hypoglycemia occurred in 35.3% of patients treated with 1.5 mg. Severe hypoglycemia events occurred in 0.7% of patients treated with TRULICITY 1.5 mg.
When TRULICITY was used in combination with prandial insulin, documented symptomatic hypoglycemia occurred in 85.3% of patients treated with 0.75 mg and 80.0% of patients treated with 1.5 mg. Severe hypoglycemia events occurred in 2.4% and 3.4% of patients respectively for TRULICITY 0.75 mg and 1.5 mg.
When TRULICITY was used in combination with prandial insulin over 52 weeks in patients with moderate to severe chronic kidney disease, documented symptomatic hypoglycemia occurred in 48.1% of patients treated with 0.75 mg and 40.5% of patients treated with 1.5 mg. Severe hypoglycemia events occurred in 2.6% and 0.0% of patients respectively for TRULICITY 0.75 mg and 1.5 mg.
When TRULICITY was used in combination with SGLT2i with or without metformin, documented symptomatic hypoglycemia occurred in 2.1% of patients treated with 0.75 mg and 1.4% of patients treated with 1.5 mg. Severe hypoglycemia events occurred in 0.7% and 0.0% of patients respectively for TRULICITY 0.75 mg and 1.5 mg.
In the REWIND cardiovascular outcome trial, in which TRULICITY 1.5 mg was used either alone or in combination with other antihyperglycemic agents (95.6%), severe hypoglycemia events occurred in 1.3% of patients treated with TRULICITY and 1.5% of patients treated with placebo. The incidence rates for severe hypoglycemia were 0.25 patients with events/100 person-years and 0.29 patients with events/100 person-years for TRULICITY and placebo, respectively.
A summary of documented symptomatic and severe hypoglycemia across phase 3 studies is presented in Table
2.
Table 2: By-Study Summary of Incidence (%) and Rate (Events/Patient/Year) of Total, Documented
Symptomatic and Severe Hypoglycemia – Dulaglutide and Comparator-Treated Patients in Phase 3 Studies
| Percentage of Patients [Rate] | |||
Monotherapy (52 weeks) Total Documented symptomatic Severe | MET (N=268) 12.7 [0.28] 4.9 [0.09] 0 [0.0] | Dulaglutide 0.75 mg (N=270) 11.1 [0.47] 5.9 [0.15] 0 [0.0] | Dulaglutide 1.5 mg (N=269) 12.3 [0.89] 6.3 [0.62] 0 [0.0] |
In Combination with MET (26-week placebo-controlled period) Total Documented symptomatic Severe | Placebo (N=177) 1.1 [0.08] 1.1 [0.08] 0 [0.0] | Dulaglutide 0.75 mg (N=302) 4.0 [0.18] 2.6 [0.13] 0 [0.0] | Dulaglutide 1.5 mg (N=304) 7.9 [0.39] 5.6 [0.26] 0 [0.0] |
In Combination with MET (104 weeks) Total Documented symptomatic Severe | Sitagliptin (N=315) 8.6 [0.20] 5.7 [0.17] 0 [0.0] | Dulaglutide 0.75 mg (N=302) 8.6 [0.21] 6.3 [0.18] 0 [0.0] | Dulaglutide 1.5 mg (N=304) 12.8 [0.26] 10.9 [0.19] 0 [0.0] |
In Combination with MET+SU (78 weeks) Total Documented symptomatic Severe | Insulin glargine (N=262) 71.4 [6.90] 51.1 [3.02] 0.8 [0.01] | Dulaglutide 0.75 mg (N=272) 56.6 [4.18] 39.0 [1.67] 0 [0.0] | Dulaglutide 1.5 mg (N=273) 58.6 [4.27] 40.3 [1.67] 0.7 [0.01] |
In Combination with SGLT2i ±MET (24 weeks) Total Documented symptomatic Severe | Placebo (N=140) 2.9 [0.21] 2.1 [0.12] 0 [0.0] | Dulaglutide 0.75 mg (N=141) 3.5 [0.26] 2.1 [0.16] 0.7 [0.02] | Dulaglutide 1.5 mg (N=142) 3.5 [0.31] 1.4 [0.16] 0 [0.0] |
In Combination with Insulin lispro±MET (52 weeks) Total Documented symptomatic Severe | Insulin glargine (N=296) 89.9 [57.17] 83.4 [40.95] 5.1 [0.09] | Dulaglutide 0.75 mg (N=293) 90.1 [48.38] 85.3 [35.66] 2.4 [0.05] | Dulaglutide 1.5 mg (N=295) 86.1 [41.74] 80.0 [31.06] 3.4 [0.06] |
In Combination with Insulin lispro (patients with moderate to severe CKD, 52 weeks) Total Documented symptomatic Severe | Insulin glargine (N=194) 74.7 [14.36] 63.4 [9.62] 6.7 [0.09] | Dulaglutide 0.75 mg (N=189) 59.8 [7.59] 48.1 [4.34] 2.6 [0.03] | Dulaglutide 1.5 mg (N=190) 50.0 [5.82] 40.5 [4.44] 0 [0] |
In Combination with Titrated Basal Insulin Glargine ± MET (28 weeks) Total Documented symptomatic Severe | Placebo (N=150) 50.7 [8.6] 30.0 [4.4] 0.0 [0.0] | N/A | Dulaglutide 1.5 mg (N=150) 54.7 [7.7] 35.3 [3.4] 0.7 [0.0] |
By-Study Summary of Total Hypoglycemia (events with or without symptoms but with plasma glucose less than or equal to 3.9 mmol/L, plus events with symptoms of hypoglycemia but without a plasma glucose determination, plus severe hypoglycemia), Documented Symptomatic Hypoglycemia (symptoms of hypoglycemia with plasma glucose less than or equal to 3.9 mmol/L), and Severe Hypoglycemia (an episode requiring the assistance of another person to actively administer carbohydrate, glucagon, or other resuscitative actions), all excluding post-rescue visits - Dulaglutide and Comparator-Treated Patients in Phase 3 Studies Abbreviations: MET = metformin; N = total number of patients in specified treatment group; SU = sulfonylurea; SGLT2i = sodium glucose co-transporter 2 inhibitor; CKD=chronic kidney disease
Post-Market Adverse Drug Reaction
The following additional adverse reaction has been reported rarely during post-approval use of TRULICITY. Because these events are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Anaphylactic reactions (see PART I: CONTRAINDICATIONS and WARNINGS AND
PRECAUTIONS and PART III: Serious side effects and what to do about them).
Malignancies/Thyroid Cancer
In Phase 2 and 3 clinical trials, there was one event of MTC in a patient who received dulaglutide. This patient had pre-treatment calcitonin levels approximately 8 times the upper limit of normal (ULN).
DRUG INTERACTIONS
Drug-Drug Interactions
The potential effect of coadministered medications on the pharmacokinetics of dulaglutide and vice-versa was studied in several single- and multiple- dose studies in healthy subjects, patients with type 2 diabetes mellitus, and in patients with hypertension.
Dulaglutide causes a delay of gastric emptying, and thereby has the potential to impact the absorption of concomitantly administered oral medications. In clinical pharmacology studies, dulaglutide did not affect the absorption of the tested, orally administered medications to any clinically relevant degree (see below and Figure 2).
Acetaminophen
Following a single dose of 1 and 3 mg dulaglutide, acetaminophen Cmax was reduced by 36% and 50%, respectively, and the median tmax occurred later (3 and 4 hours, respectively). After coadministration with up to 3 mg of dulaglutide at steady state, there were no statistically significant differences on AUC, Cmax or tmax of acetaminophen.
Atorvastatin
Coadministration of dulaglutide with atorvastatin decreased Cmax and AUC up to 70% and 21%, respectively, for atorvastatin and its major metabolite o-hydroxyatorvastatin. The mean t1/2 of atorvastatin and o-hydroxyatorvastatin were increased by 17% and 41%, respectively, following dulaglutide administration. These observations are not considered clinically relevant.
Digoxin
After coadministration of steady state digoxin with 2 consecutive doses of dulaglutide, overall exposure (AUC) and tmax of digoxin were unchanged; and Cmax decreased by up to 22%. This change is not expected to have clinical consequences.
Anti-hypertensives
Statistically significant delays in lisinopril tmax of approximately 1 hour were observed on Days 3 and 24 of the study. When a single dose of dulaglutide and metoprolol were coadministered, the AUC and Cmax of metoprolol increased by 19% and 32%, respectively. Metoprolol tmax was delayed by 1 hour.
Warfarin
Following dulaglutide coadministration, S- and R-warfarin exposure and R-warfarin Cmax were unaffected, and S-warfarin Cmax decreased by 22%. AUCINR increased by 2%, and there was no effect on maximum international normalized ratio response (INRmax). The time of international normalized ratio response (tINRmax) was delayed by 6 hours, consistent with delays in tmax of approximately 4 and 6 hours for S- and R-warfarin, respectively.
Oral Contraceptives
Coadministration of dulaglutide with an oral contraceptive (norgestimate 0.18 mg/ethinyl estradiol 0.025 mg) did not affect the overall exposure to norelgestromin and ethinyl estradiol. Statistically significant reductions in
Cmax of 26% and 13% and delays in tmax of 2 and 0.30 hours were observed for norelgestromin and ethinyl estradiol, respectively.
Metformin
Following coadministration of multiple dose dulaglutide with steady state metformin (immediate release formula [IR]), metformin AUC increased up to 15% and Cmax decreased up to 12%, respectively, with no changes in tmax. These changes are consistent with the gastric emptying delay of dulaglutide and within the PK variability of metformin.
Sitagliptin
Sitagliptin exposure was unaffected when coadministered with a single dose of dulaglutide. Following coadministration with 2 consecutive doses of dulaglutide, sitagliptin AUC and Cmax decreased by approximately 7.4% and 23.1%, respectively. Sitagliptin tmax increased approximately 0.5 hours following coadministration with dulaglutide compared to sitagliptin alone.
Sitagliptin can produce up to 80% inhibition of DPP-4 over a 24-hour period. Dulaglutide coadministration with sitagliptin increased dulaglutide exposure and Cmax by approximately 38% and 27%, respectively, and median tmax increased approximately 24 hours. Therefore, dulaglutide does have a high degree of protection against DPP-4 inactivation.
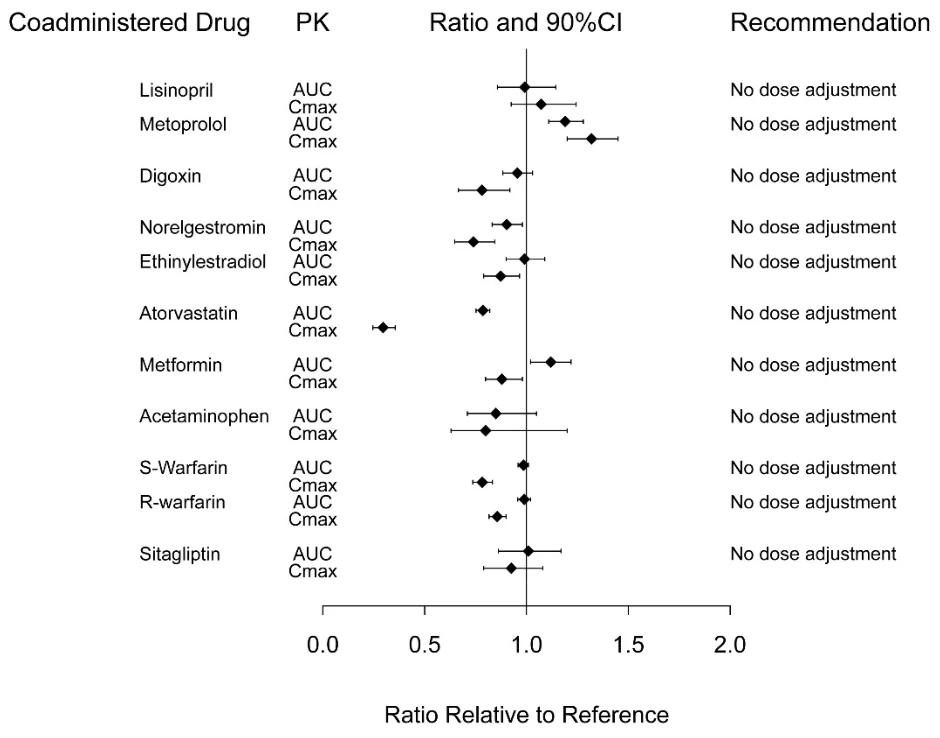
Abbreviations: AUC = area under the time-concentration curve; CI = confidence interval; Cmax = maximum concentration; PK = pharmacokinetics.
Note: Reference group is co-administered medication given alone.
Figure 2 Impact of dulaglutide on the pharmacokinetics of co-administered medications.
Drugs that Increase Heart Rate
TRULICITY causes an increase in heart rate (see ADVERSE REACTIONS, ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology). Caution should be observed if TRULICITY is administered with other drugs that also increase heart rate, such as drugs with sympathomimetic or anticholinergic activity.
Drugs that Cause PR Interval Prolongation
TRULICITY causes an increase in the PR interval (see ADVERSE REACTIONS, ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology). The impact on the PR interval of co-administration of TRULICITY with other drugs that prolong the PR interval (including, but not limited to, antiarrhythmics, non-dihydropyridine calcium channel blockers, beta adrenoceptor blockers, digitalis glycosides, HIV protease inhibitors, and somatostatin analogues) has not been evaluated. As a result, co-administration of TRULICITY with these drugs should be undertaken with caution.
Drug-Food Interactions
Interactions with food have not been studied.
Drug-Herb Interactions
Interactions with herbal products have not been studied.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been studied.
Drug-Lifestyle Interactions
No studies on the effects on ability to drive and use machines have been performed. When dulaglutide is used in combination with a sulfonylurea or insulin, patients should be advised to take precautions to avoid hypoglycemia while driving and using machines.
DOSAGE AND ADMINISTRATION
Dosing Considerations
When initiating TRULICITY, consider reducing the dose of concomitantly administered insulins and insulin secretagogues (such as sulfonylureas) to reduce the risk of hypoglycemia (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS).
Recommended Dose and Dosage Adjustment
The recommended initiating dose of TRULICITY is 0.75 mg once weekly, administered subcutaneously. The dose may be increased to 1.5 mg once weekly for additional glycemic control. The maximum recommended dose is 1.5 mg once weekly.
Renal Insufficiency: No dose adjustment is required in patients with renal impairment (ACTION AND CLINICAL PHARMACOLOGY and Special Populations and Conditions). Monitor renal function in patients with renal impairment reporting severe gastrointestinal reactions which may worsen the renal function.
Hepatic Insufficiency: There is a limited experience in patients with mild, moderate, or severe hepatic impairment. Therefore, TRULICITY should be used with caution in these patient populations (see ACTION AND CLINICAL PHARMACOLOGY and Special Populations and Conditions). No dose adjustment is recommended in patients with hepatic insufficiency.
Geriatrics (≥65 years): Refer to Special Populations and ACTION AND CLINICAL PHARMACOLOGY
Pediatrics (<18 years): The safety and effectiveness of TRULICITY have not been studied in patients under 18 years of age.
Missed Dose
If a dose is missed, it should be administered as soon as possible if there are at least 3 days (72 hours) until the next scheduled dose. If less than 3 days remain before the next scheduled dose, the missed dose should be skipped and the next dose should be administered on the regularly scheduled day. In each case, patients can then resume their regular once weekly dosing schedule.
Changing Weekly Dosing Schedule
The day of weekly administration can be changed, if necessary, as long as the last dose was administered 3 days (72 hours) or more before.
Administration
TRULICITY can be administered any time of day, with or without meals, and should be injected subcutaneously in the abdomen, thigh, or upper arm.
TRULICITY should be administered subcutaneously with no dilution.
TRULICITY solution should be inspected prior to each injection, and the solution should be used only if it is clear, colourless, and contains no particles.
TRULICITY and insulin should not be mixed in the same syringe, and must be administered as two separate injections in two different injection sites.
OVERDOSAGE
Overdoses have been reported in clinical studies. Effects associated with these overdoses were primarily mild or moderate gastrointestinal events (e.g., nausea, vomiting) and non-severe hypoglycemia. In the event of overdose, appropriate supportive care (including frequent plasma glucose monitoring) should be initiated according to the patient’s clinical signs and symptoms.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
TRULICITY contains dulaglutide which is a long-acting human GLP-1 receptor agonist with 90% amino acid sequence homology to endogenous human GLP-1 (7-37). Dulaglutide activates the GLP-1 receptor, a membrane-bound cell-surface receptor coupled to adenylyl cyclase by the stimulatory G-protein, Gs, in pancreatic beta cells. Dulaglutide increases intracellular cyclic AMP (cAMP) in beta cells leading to insulin release in the presence of elevated glucose concentrations. This insulin secretion subsides as blood glucose concentrations decrease and approach euglycemia. Dulaglutide also decreases glucagon secretion and slows gastric emptying.
Native GLP-1 (7-37) has a half-life of 1.5 to 2 minutes due to degradation by DPP-4 and renal clearance. In contrast to native GLP-1, dulaglutide is stable against metabolic degradation by DPP-4 and has an extended plasma half-life of approximately 4.7 days, which makes it suitable for once-weekly administration. The pharmacokinetic profile of dulaglutide is the result of the fusion of two molecules of a GLP-1 (7-37) analogue, which include a modification to amino acid 8, linked to a modified human IgG4 chain.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Pharmacodynamics
TRULICITY lowers fasting, and postprandial glucose (PPG) concentrations in patients with type 2 diabetes mellitus through the actions described below. The reduction in fasting and PPG can be observed after the first TRULICITY administration.
Fasting and Postprandial Glucose
In a clinical pharmacology study in adults with type 2 diabetes mellitus, treatment with once weekly TRULICITY resulted in a reduction from baseline of fasting and 2-hour postprandial glucose (PPG) concentrations on day 3 after the first injection, when compared to placebo (-1.42, -3.30 mmol/L respectively); these effects were sustained after six weeks of dosing with the 1.5 mg dose.
First and Second Phase Insulin Secretion
Both first and second phase insulin secretion were increased in patients with type 2 diabetes treated with TRULICITY compared to placebo.
Glucose−Dependent Insulin Secretion
The effect of steady state dosing of TRULICITY 1.5 mg on glucose-dependent insulin secretion rates (ISR) was assessed in a test meal study in patients with type 2 diabetes mellitus at the 26-week endpoint. In these patients, the ISR response was increased in a glucose-dependent manner.
Glucagon Secretion
TRULICITY lowered blood glucose by stimulating insulin secretion and decreasing glucagon secretion. In a clinical study in patients with type 2 diabetes mellitus, TRULICITY reduced fasting glucagon levels at the 26-week time point. In addition, a test meal study also showed decreases in postprandial glucagon AUC (0-3 hours post-meal) after 26 weeks of treatment with TRULICITY.
Gastric Emptying
TRULICITY causes a delay of gastric emptying. The delay is largest after the first dose and diminishes with subsequent doses.
Serum Pancreatic Enzymes
TRULICITY is associated with mean increases from baseline in pancreatic enzymes (pancreatic amylase and/or lipase) of up to 14% to 20% (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreas). Serial measurements of pancreatic enzymes in Phase 2 and Phase 3 trials did not predict the onset of acute pancreatitis. The clinical meaning of these findings is unknown.
Cardiac Electrophysiology
The effect of dulaglutide on cardiac repolarization was tested in a thorough QTc study. Dulaglutide did not produce QTc prolongation at supratherapeutic doses of 4 and 7 mg.
Healthy Subjects: A multicentre, double-blind, randomized, 3-period, single dose placebo- and active-controlled crossover ECG assessment study was conducted in healthy subjects. It was originally planned to study a 7 mg dose of dulaglutide; however, the 7 mg dose was not well tolerated, and therefore, the dose of dulaglutide was lowered from 7 mg to 4 mg. Overall 147 subjects were enrolled (placebo N=109, dulaglutide 4 mg N=55, dulaglutide 7 mg N=54, and moxifloxacin 400 mg N=115).
Heart Rate: In the QTc study using supratherapeutic doses of dulaglutide in healthy subjects, increases in heart rate were observed. For the 4 mg treatment, statistically significant positive mean differences from placebo were observed at 24 hours, 48 hours, and 168 hours, with a maximum mean difference from placebo of 6.9 bpm
(90% CI 2.9, 10.8) at 48 hours (Figure 3) (see WARNINGS AND PRECAUTIONS, Cardiovascular, ADVERSE REACTIONS and DRUG INTERACTIONS, Drugs that Increase Heart Rate).
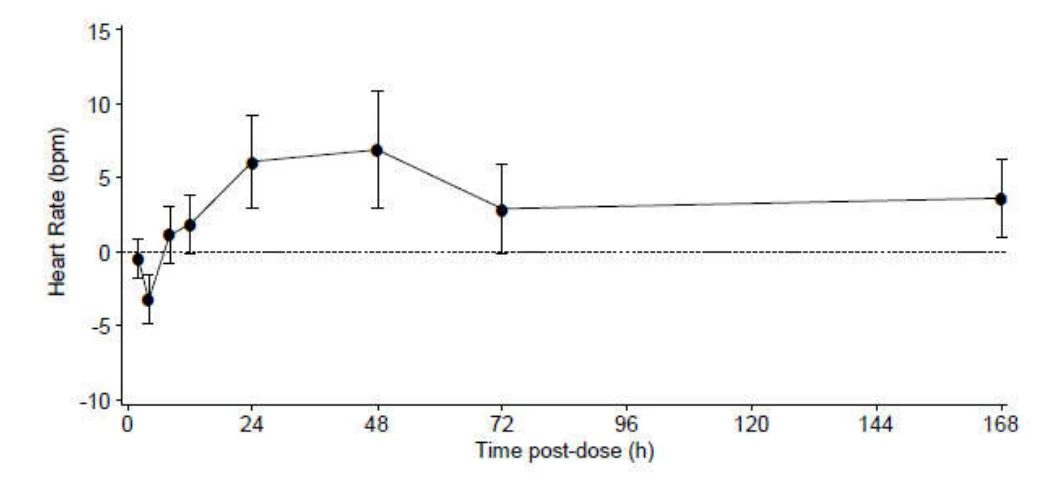
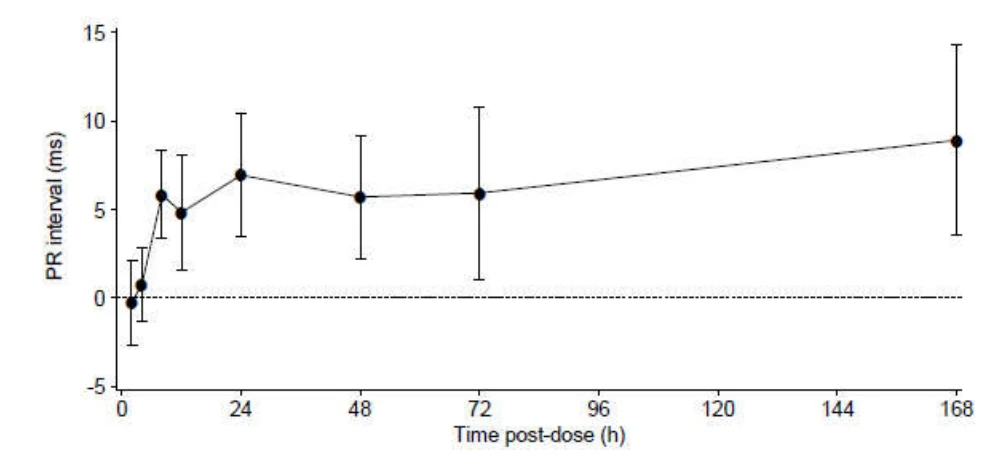
Figure 3: Mean (90% CI) Placebo and Baseline Adjusted Heart Rate Data for 4 mg of Dulaglutide in
Healthy Subjects
PR Interval: Dulaglutide resulted in PR interval prolongation. Statistically significant PR interval prolongation was observed with dulaglutide 4 mg from 8 to 168 hours post-dosing, with a maximum mean difference from placebo of 8.9 ms (90% CI 3.5, 14.3) at 168 hours post-dosing (Figure 4). See WARNINGS AND PRECAUTIONS, Cardiovascular and DRUG INTERACTIONS, Drugs that Cause PR Interval Prolongation.
Figure 4: Mean (90% CI) Placebo and Baseline Adjusted PR Interval Data for 4 mg of Dulaglutide in
Healthy Subjects
QTc Interval: Treatment with dulaglutide was associated with shortening of the QTcP interval (QTcP=QT/RR0.307). During treatment with dulaglutide 4 mg, statistically significant QTcP shortening was observed at 4 hours and from 24-168 hours post-dosing, with a maximum mean difference from placebo of -10.6 ms (90% CI -13.7, -7.6) at 48 hours post-dosing (Figure 5). The clinical significance of an acquired, drug-induced QTcP shortening of this magnitude is not known.
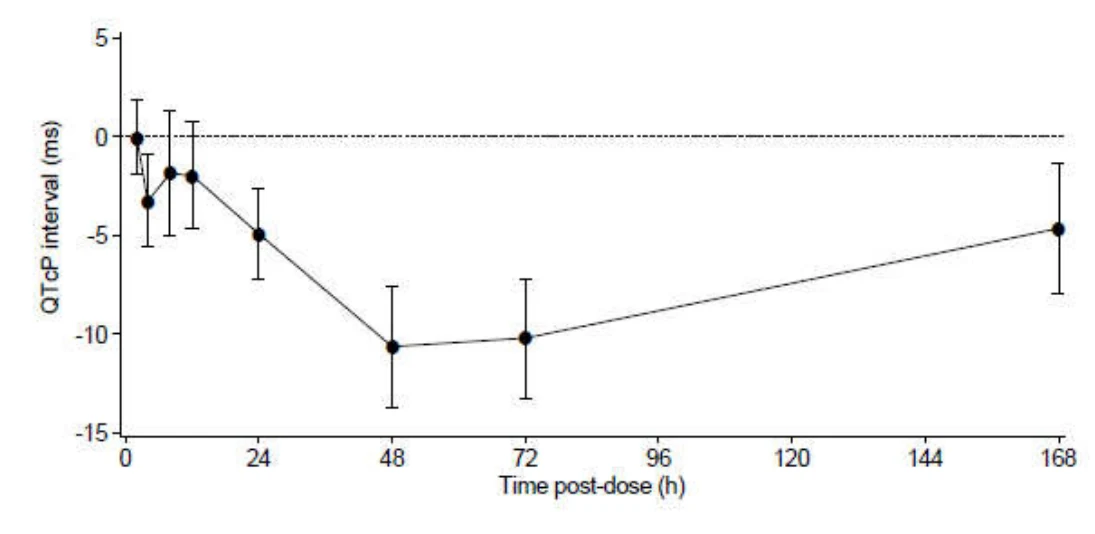
Figure 5: Mean (90% CI) Placebo and Baseline Adjusted QTcP Interval Data for 4 mg of Dulaglutide in Healthy Subjects
Type 2 Diabetes Mellitus Patients: In a multicentre, randomised, double-blind, placebo-controlled parallel arm study of 26-weeks in duration performed in 755 patients with type 2 diabetes mellitus receiving TRULICITY at once-weekly doses of 0.75 mg and 1.5 mg, ECG readings were scheduled to occur at baseline and at Weeks 16 and 26, 2-4 days after the TRULICITY injection, to capture the effects of TRULICITY at steady-state near maximal plasma concentrations. At Week 16 of treatment, the placebo-adjusted LS mean change from baseline in heart rate was 2.02 bpm (95% CI 0.56, 3.48) in the 0.75 mg group and 4.76 bpm (95% CI 3.27, 6.26) in the 1.5 mg group, whilst the placebo-adjusted LS mean change from baseline in the PR interval was 3.66 ms (95% CI 1.15, 6.18) in the 0.75 mg group and 4.95 ms (95% CI 2.37, 7.53) in the 1.5 mg group. The QTcF interval was shortened, with a placebo-adjusted LS mean change from baseline of -2.02 ms (95% CI -4.49, 0.46) in the 0.75 mg group and -3.37 ms (95% CI -5.91, -0.84) in the 1.5 mg group. Similar results were obtained at Week
26.
Pharmacokinetics
The pharmacokinetics of dulaglutide is similar between healthy subjects and patients with type 2 diabetes mellitus. Following subcutaneous administration, the time to maximum plasma concentration of dulaglutide (0.75 mg and 1.5 mg) at steady state ranges from 24 to 72 hours, with a median of 48 hours. After multiple-dose administration of dulaglutide 1.5 mg to steady state, the mean peak plasma concentration (Cmax) and total systemic exposure (AUC)for dulaglutide 0.75 mg were 44 ng/mL (range 21 to 75 ng/mL) and 5240 ng•hr/mL (range 2670 to 8570 ng•hr/mL); and for dulaglutide 1.5 mg were 114 ng/mL (range 56 to 231 ng/mL) and 14000 ng•hr/mL (range 6940 to 26000 ng•hr/mL) respectively; accumulation ratio was approximately 1.56. Steady-state plasma dulaglutide concentrations were achieved between 2 and 4 weeks of once-weekly administration. Site of subcutaneous administration (abdomen, upper arm, and thigh) had no statistically significant effect on the exposure to dulaglutide.
Absorption: The mean absolute bioavailability of dulaglutide following subcutaneous administration of a single 0.75 mg and 1.5 mg dose was 65% and 47% respectively.
Distribution: The mean volume of distribution after subcutaneous administration of dulaglutide 0.75 mg and 1.5 mg to steady state in patients with type 2 diabetes mellitus were approximately 19.2 L (range 14.3 to 26.4) and 17.4 L (range 9.3 to 33) respectively. The mean volume of distribution after intravenous administration of a single dose of 0.1 mg dulaglutide in healthy subjects was approximately 5.32 L (range 3.6 to 7.3).
Metabolism: Dulaglutide is presumed to be degraded into its component amino acids by general protein catabolism pathways.
Elimination: The mean apparent clearance, at steady state, following subcutaneous administration of multiple doses of dulaglutide 0.75 mg and 1.5 mg is approximately 0.111 L/hr (range 0.059 to 0.180 L/h) and 0.107 L/h (range 0.058 to 0.216 L/h) respectively. The elimination half-life of dulaglutide for both doses is approximately 5 days (range 3.9 to 6.1 days), making dulaglutide suitable for once-weekly administration.
Special Populations and Conditions
Pediatrics: Studies characterizing the pharmacokinetics of dulaglutide in pediatric patients have not been performed.
Geriatrics: Age had no clinically relevant effect on the pharmacokinetic and pharmacodynamic properties of dulaglutide.
Gender and Race: Gender and race had no clinically meaningful effect on the pharmacokinetics of dulaglutide.
Body Weight or Body Mass Index: Pharmacokinetic analyses have demonstrated a statistically significant inverse relationship between body weight or body mass index (BMI) and dulaglutide exposure, although there was no clinically relevant impact of weight or BMI on glycemic control.
Hepatic Insufficiency: The pharmacokinetics of dulaglutide were evaluated in subjects with varying degrees of hepatic impairment. Subjects with hepatic impairment had statistically significant decreases in dulaglutide exposure of up to 30% to 33% for mean Cmax and AUC, respectively, compared to healthy controls. There was a general increase in tmax of dulaglutide with increased hepatic impairment (see WARNINGS AND PRECAUTIONS, Special Population, and DOSAGE AND ADMINISTRATION).
Renal Insufficiency: The pharmacokinetics of dulaglutide were evaluated in a clinical pharmacology study and were generally similar between healthy subjects and patients with mild to severe renal impairment (CrCl < 30 ml/min), including end stage renal disease (requiring dialysis).
STORAGE AND STABILITY
TRULICITY should be stored in the refrigerator at 2° to 8°C, up to the expiration date. Do not use TRULICITY beyond the expiration date.
Do not freeze TRULICITY. Do not use TRULICITY if it has been frozen.
Do not store in the freezer.
TRULICITY must be protected from light.
Each single-use, prefilled pen or prefilled syringe may be stored unrefrigerated for up to 14 days at a temperature not to exceed 30ºC.
The TRULICITY prefilled pen or prefilled syringe must be discarded after use in a puncture-resistant container.
DOSAGE FORMS, COMPOSITION AND PACKAGING
TRULICITY is available as a single-use prefilled pen or a prefilled syringe. Each 0.5 mL solution includes the following non-medicinal ingredients: trisodium citrate dihydrate, citric acid anhydrous, mannitol, and polysorbate 80 in water for injection.
TRULICITY is packaged in a cardboard outer carton and is available in packs of 2 or 4 single-use, prefilled pens or 4 single-use, prefilled syringes. Not all pack sizes and presentations may be marketed.
Single-Use, Prefilled Pen or Syringes‡ – 0.75 mg / 0.5 mL
Each single-use, prefilled pen or syringe provides 0.75 mg TRULICITY per 0.5 mL of solution.
Single-Use, Prefilled Pen or Syringes‡ – 1.5 mg / 0.5 mL
Each single-use, prefilled pen or syringe provides 1.5 mg TRULICITY per 0.5 mL of solution.
‡ The pre-filled syringe is not currently marketed in Canada.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: dulaglutide
Chemical name:
USAN: dulaglutide
IUPAC:
7-37-Glucagon-like peptide I [8-glycine, 22-glutamic acid, 36-glycine] (synthetic human) fusion protein with peptide (synthetic 16-amino acid linker) fusion protein with immunoglobulin G4 (synthetic human Fc fragment), dimer
[Gly8,Glu22,Gly36]human glucagon-like peptide 1-(7-37)-peptidyltetraglycyl-L-seryltetraglycyl-L-seryltetraglycyl-L-seryl-L-alanyldes-Lys229-[Pro10,Ala16,Ala17]human immunoglobulin heavy constant γ4 chain H-CH2-CH3 fragment, (55-55':58-58')-bisdisulfide dimer
Molecular formula and molecular mass:
C2646 H4044 O836 N704 S18 (non-glycosylated)
62,561 Da (glycosylated, all Cys residues disulfide bonded)
59,671 Da (non-glycosylated, all Cys residues disulfide bonded)
Structural formula:
Dulaglutide is produced as a disulfide-linked two-chain molecule (homodimer). The amino acid sequence of the single polypeptide chain is below:
Physicochemical properties: Clear to slightly opalescent, colourless to slightly brown solution
CLINICAL TRIALS
TRULICITY® (dulaglutide) has been studied as monotherapy and in combination with metformin, metformin and sulfonylurea, sodium glucose co-transporter 2 inhibitor (SGLT2i) with or without metformin, prandial insulin with or without metformin, and basal insulin with or without metformin. Table 3 summarizes the study demographics and study designs of eight phase 3 placebo and/or active controlled studies.
1 HGEGTFTSDV SSYLEEQAAK EFIAWLVKGG GGGGGSGGGG SGGGGSAESK
51 YGPPCPPCPA PEAAGGPSVF LFPPKPKDTL MISRTPEVTC VVVDVSQEDP
101 EVQFNWYVDG VEVHNAKTKP REEQFNSTYR VVSVLTVLHQ DWLNGKEYKC
151 KVSNKGLPSS IEKTISKAKG QPREPQVYTL PPSQEEMTKN QVSLTCLVKG
201 FYPSDIAVEW ESNGQPENNY KTTPPVLDSD GSFFLYSRLT VDKSRWQEGN
251 VFSCSVMHEA LHNHYTQKSL SLSLG
Study demographics and trial design
Table 3: Summary of patient demographics for clinical trials in specific indication
| Study # | Trial design and duration | Dosage, route of administration | Background Therapy | Study subjects (n=number) | Mean age (SD) Range | Gender % (#) |
| Add on Combination Therapy to Metformin | ||||||
| GBCF | 104-week, Phase 2/3, adaptive, inferentially seamless, multicentre, randomized, placebo-controlled, double-blind, parallel-arm, dose finding trial | TRULICITY: 0.75, 1.5 mg, SC, QW Placebo: PO, QD; SC, QW up to 26 weeks Sitagliptin: 100 mg, PO, QD | Patients added assigned therapy to MET ≥1500 mg/day | 972 randomized | 54.3 yrs (9.7) Range: 20-75 yrs | Female: 51.9% (504) Male: 48.1% (468) |
| GBDE | 26-week, Phase 3, multicentre randomized, parallel-arm, active comparator, open-label, noninferiority trial | TRULICITY: 1.5 mg, SC, QW Liraglutide: 1.8 mg, SC, QD | Patients added assigned therapy to MET ≥1500 mg/day | 599 randomized | 56.7 yrs (9.6) Range: 19-80 yrs | Female: 52% (312) Male: 48% (287) |
| Add on Combination Therapy to Metformin and Sulfonylurea | ||||||
| GBDB | 78-week, Phase 3, multicentre, randomized, parallel-arm, open-label to active comparator, double-blind to dulaglutide trial | TRULICITY: 0.75, 1.5 mg SC, QW Insulin glargine: starting dose 10 IU, SC; thereafter, titrated to target, QD | Patients added assigned therapy to maximally tolerated dose of MET ≥1500 mg/day and glimepiride ≥4 mg/day | 810 randomized | 56.7 yrs (9.5) Range: 27-87 yrs | Female: 48.7% (393) Male: 51.3% (414) |
| Add on Combination Therapy to SGLT2 inhibitor with or without Metformin | ||||||
| GBGE | 24-week, Phase 3, multicentre, randomized, parallel-arm, double-blind | TRULICITY: 0.75, 1.5 mg SC, QW Placebo SC, QW | Patients added assigned therapy to SGLT2i with or without MET ≥1500 mg/day | 424 randomized | 57.3 yrs (9.4) Range: 25-79 yrs | Female: 49.9% (211) Male: 50.1% (212) |
| Combination Therapy with Insulin Lispro with or without Metformin | ||||||
| GBDD | 52-week, Phase 3, multicentre, randomized, parallel-arm, open-label, active comparator trial | TRULICITY: 0.75, 1.5 mg SC, QW Insulin glargine: starting dose 50% of prerandomized total daily insulin dose (TDI), SC, at bedtime; thereafter, titrated to target. | All patients added assigned therapy and insulin lispro TID (starting daily dose: 50% of TDI, titrated to target). Prior oral and insulin therapies with the exception of metformin were discontinued. | 884 randomized | 59.4 yrs (9.2) Range: 28-84 yrs | Female: 46.5% (411) Male: 53.5% (473) |
| Combination Therapy with Insulin Lispro in Patients with Moderate to Severe CKD | ||||||
| GBDX | 52-week, Phase 3, multicentre, randomized, parallel-arm, open-label, active comparator | Trulicity: 0.75, 1.5 mg SC, QW Insulin glargine: SC, at bedtime, titrated to target | All patients added assigned therapy to insulin lispro TID titrated to target. Prior oral therapies and pramlintide were discontinued. | 577 randomized | 64.6 yrs (8.6) Range: 29-84 yrs | Female: 47.7% (275) Male: 52.3% (301) |
| Combination Therapy with Insulin Glargine with or without Metformin | ||||||
| GBDI | 28-week, Phase 3, multicentre, randomized, parallel-arm, double-blind, placebo-controlled trial | TRULICITY: 1.5 mg SC, QW Placebo: SC, QW | All patients added assigned therapy to basal insulin glargine with/without metformin. Basal insulin glargine was titrated to target in both study arms after a 4-week initial stabilization period. | 300 randomized | 60.4 yrs (9.8) Range: 28-83 yrs | Female: 42.3% (127) Male: 57.7% (173) |
| In Combination with 0-2 OADs +/- Basal Insulin in Patients with Established Cardiovascular Disease or Multiple Cardiovascular Risk Factors | ||||||
| GBDJ (REWIND) | Multicenter, multi-national, randomized, double-blind, placebo controlled Cardiovascular Outcome Trial (CVOT) with event driven treatment period. Median follow up 5.4 years | TRULICITY 1.5 mg SC, QW + SOC OR Placebo SC, QW + SOC | 0-2 OADs +/- Basal Insulin (baseline therapy) | 9901 randomized | 66.2 yrs (6.5) Range: 50-92 yrs | Female: 46.3% (4589) Male: 53.7% (5312) |
BID=twice daily; MET = metformin; PO = orally; QD = once daily; QW = once weekly; SC = subcutaneous; TID=three times daily; SGLT2i = sodium glucose co-transporter 2 inhibitor; CKD=chronic kidney disease; CV = cardiovascular; OAD = oral antihyperglycemic drug; SOC = standard of care
A total of 4561 patients with type 2 diabetes mellitus and inadequate glycemic control were randomized, of whom 4561 received at least one dose of study drug, in seven placebo- and/or active-controlled, glycemic control Phase 3 studies to evaluate the safety and efficacy of TRULICITY. Of these, 1161 (25.5%) patients were ≥65 years of which 151 (3.3%) were ≥75 years. Patients had an overall mean age of 58 years (range 19 to 87 years). Fifty-one percent were male and 49% were female. The racial distribution of patients in these studies was 73.3% white, 9.9% Asian, 6.0% African American, and 10.7% other racial origin. The mean body mass index (BMI) overall was 32 kg/m2 at baseline, and the duration of diabetes was 10.5 years.
Study results
Add on Combination Therapy to Metformin
Study GBCF (AWARD-5) - In this 104-week placebo-controlled, double-blind study, following dose selection, 972 patients were randomized to TRULICITY (dulaglutide 0.75 mg or 1.5 mg) once weekly, placebo, or sitagliptin 100 mg/day (after 26 weeks, patients in the placebo treatment group received blinded sitagliptin 100 mg/day for the remainder of the study), all as add-on to metformin. Randomization occurred after an 11-week lead-in period to allow for a metformin titration period followed by a 6-week glycemic stabilization period. The primary objective of the study was to demonstrate that the HbA1c change from baseline for dulaglutide 1.5 mg once weekly was noninferior to sitagliptin at 52 weeks, with a noninferiority margin of 0.25%.
Treatment with TRULICITY once weekly resulted in a statistically significant reduction in HbA1c compared to placebo (at 26 weeks) and compared to sitagliptin (at 52 weeks) (Table 4).
Table 4: Results at the 52-Week Primary Endpoint of TRULICITY Compared to Placebo and
Sitagliptin, All as Add-On to Metformina
| 26-Week Placebo-Controlled Period | 52-Week Primary Time Point | |||||
| TRULICITY | Placebo + MET | TRULICITY | SITA 100 mg + MET | |||
| 0.75 mg + MET | 1.5 mg + MET | 0.75 mg + MET | 1.5 mg + MET | |||
| Intent-to-Treat (ITT) Population (N) | 281 | 279 | 139 | 281 | 279 | 273 |
| HbA1c (%) (Mean) | ||||||
| Baseline HbA1c | 8.2 | 8.1 | 8.1 | 8.2 | 8.1 | 8.0 |
| Change from baseline, adjusted meanb | -1.0 | -1.2 | 0.1 | -0.9 | -1.1 | -0.4 |
| Difference from placebo + MET armb (95% CI) | -1.0 (-1.2, -0.9) | -1.2 (-1.4, -1.1) | - | - | - | - |
| P value (superiority) † | <0.001 | <0.001 | - | - | - | - |
| Difference from SITA + MET arm, adjusted meanb (95% CI) | - | - | - | -0.5 (-0.7, -0.3) | -0.7 (-0.9, -0.5) | - |
| P value (superiority) † | - | - | - | <0.001 | <0.001 | |
| P value (non-inferiority) † | - | - | - | <0.001 | <0.001 | |
| Percentage of patients HbA1c <7.0% | - | - | - | 49 | 59 | 33 |
| Fasting Serum Glucose (mmol/L) (Mean) | ||||||
| Baseline | - | - | - | 9.65 | 9.62 | 9.48 |
| Change from baseline, adjusted mean | - | - | - | -1.64 | -2.27 | -0.80 |
| Body Weight (kg) (Mean) | ||||||
| Baseline | - | - | - | 85.5 | 86.5 | 85.8 |
| Change from baseline, adjusted mean | - | - | - | -2.7 | -3.1 | -1.5 |
Abbreviation: HbA1c = hemoglobin A1c; MET = metformin; SITA = sitagliptin
a All intent-to-treat patients randomized after the dose finding portion of the study. At Week 52, 14%, 19% and 19% of individuals randomized to TRULICITY 0.75 mg, TRULICITY 1.5 mg and sitagliptin, respectively, had missing data and had their last observation carried forward for analysis.
b Least-squares mean from ANCOVA model adjusted for baseline value and country.
† Overall Type I error rate for treatment comparisons was controlled using a tree-gatekeeping strategy.
Study GBDE (AWARD-6) - In this 26-week, open-label study 599 patients were randomized to once weekly TRULICITY 1.5 mg or once daily liraglutide 1.8 mg, both as add-on to metformin. Patients randomized to liraglutide were initiated at 0.6 mg QD for 1 week, then escalated to 1.2 mg QD for one week and then escalated to 1.8 mg QD for the remainder of the study. The primary objective of the study was to demonstrate the noninferiority of dulaglutide 1.5 mg once weekly compared to liraglutide 1.8 mg once daily, both added on to metformin, in change in HbA1c from baseline at 26 weeks, with a noninferiority margin of 0.4%.
At 26 weeks, treatment with once weekly TRULICITY 1.5 mg once weekly was noninferior to once daily liraglutide 1.8 mg (Table 5).
Table 5: Results of a 26-Week Study of TRULICITY Compared to Liraglutide, as Add-On to
Metformina
| 26-Week Primary Time Point | ||
TRULICITY 1.5 mg | Liraglutide 1.8 mg | |
| Intent-to-Treat (ITT) Population (N) | 299 | 300 |
| HbA1c (%) (Mean) | ||
| Baseline HbA1c | 8.1 | 8.1 |
| Change from baseline, adjusted meanb | -1.4 | -1.4 |
| Difference from liraglutideb (95% CI) | -0.1 (-0.2, 0.1) | - |
| P value (non-inferiority) | <0.001 | |
| Percentage of patients HbA1c <7.0% | 68 | 68 |
| Fasting Serum Glucose (mmol/L) (Mean) | ||
| Baseline | 9.28 | 9.16 |
| Change from baseline, adjusted mean | -1.93 | -1.90 |
| Body Weight (kg) (Mean) | ||
| Baseline | 93.8 | 94.4 |
| Change from baseline, adjusted mean | -2.9 | -3.6 |
| Postprandial Glucose (mmol/L) (Mean) | ||
| Baseline | 10.65 | 10.58 |
| Change from baseline, adjusted mean | -2.56 | -2.43 |
Abbreviation: HbA1c = hemoglobin A1c; CI = confidence interval
a Intent-to-treat population excluding data following any rescue therapy. Over the 26-week study period, the percentage of patients who required glycemic rescue was 0.3% in the TRULICITY treatment group, and 1.0% in the liraglutide treatment group. b Least-squares mean from a mixed-effects model for repeated measures with the baseline value, country, treatment, visit, treatment-by-visit interaction and the patient as a random effect.
Add on Combination Therapy to Metformin and Sulfonylurea
Study GBDB (AWARD-2) - In this 78-week open-label comparator study (double-blind with respect to TRULICITY dose assignment), 807 patients were randomized and received TRULICITY (dulaglutide 0.75 mg or 1.5 mg) once weekly, or insulin glargine once daily, all as add-on to maximally tolerated doses of metformin and glimepiride. Randomization occurred after a 10-week lead-in period; during the initial 2 weeks of the lead-in period, patients were titrated to maximally tolerated doses of metformin and glimepiride. This was followed by a 6 to 8 week glycemic stabilization period prior to randomization. Patients randomized to insulin glargine were started on a dose of 10 U once daily. Insulin glargine dose adjustments occurred twice weekly for the first
4 weeks of treatment based on self-measured fasting plasma glucose (FPG), followed by once weekly titration through Week 8 of study treatment, utilizing an algorithm with an FPG target of <5.6 mmol/L. After Week 8, patients continued to self-adjust insulin glargine to the FPG target; insulin glargine dose was also reviewed and revised, as needed, at subsequent office visits (Weeks 14, 20, 26, 35, 44, 52, 65, and 78). The dose of glimepiride could be reduced or discontinued after randomization (at the discretion of the investigator) in the event of persistent hypoglycemia. The primary objective of the study was to demonstrate the noninferiority of dulaglutide 1.5 mg once weekly compared to insulin glargine (titrated to target fasting glucose of <5.6 mmol/L), both on a background of metformin and glimepiride, in HbA1c reduction from baseline at 52 weeks, with a noninferiority margin of 0.4%. Only 23.5% of patients in the glargine group achieved the target fasting glucose. The dose of glimepiride was reduced or discontinued in 28%, 32%, and 29% of patients randomized to TRULICITY 0.75 mg, TRULICITY 1.5 mg, and glargine.
At the 52-week time point, TRULICITY 0.75 mg and 1.5 mg were noninferior to insulin glargine for HbA1c change from baseline (Table 6).
Table 6: Results at the 52-Week Primary Endpoint of TRULICITY Compared to Insulin Glargine,
Both as Add-on to Metformin and Sulfonylureaa
| 52-Week Primary Time Point | |||
| TRULICITY | Insulin Glargine + MET + GLIM | ||
0.75 mg + MET + GLIM | 1.5 mg + MET + GLIM | ||
| Intent-to-Treat (ITT) Population (N) | 272 | 273 | 262 |
| HbA1c (%) (Mean) | |||
| Baseline HbA1c | 8.1 | 8.2 | 8.1 |
| Change from baseline, adjusted meanb | -0.8 | -1.1 | -0.6 |
| Difference from insulin glargine + MET/GLIM arm, adjusted meanb (95% CI) | -0.1 (-0.3, 0.0) | -0.5 (-0.6, -0.3) | - |
| P value (non-inferiority) † | <0.001 | <0.001 | |
| Percentage of patients HbA1c <7.0% | 37 | 53 | 31 |
| Fasting Serum Glucose (mmol/L) (Mean) | |||
| Baseline | 8.96 | 9.16 | 9.08 |
| Change from baseline, adjusted mean | -0.87 | -1.50 | -1.76 |
| Body Weight (kg) (Mean) | |||
| Baseline | 86.4 | 85.2 | 87.6 |
| Change from baseline, adjusted mean | -1.3 | -1.9 | 1.4 |
| Postprandial Glucose (mmol/L) (Mean) | |||
| Baseline | 10.54 | 10.68 | 10.45 |
| Change from baseline, adjusted mean | -1.64 | -1.95 | -1.60 |
Abbreviation: GLIM = glimepiride; HbA1c = hemoglobin A1c; MET = metformin
a Intent-to-treat population using last observation on study prior to any rescue therapy. At Week 52, 15%, 9%, and 11% of individuals randomized to TRULICITY 0.75 mg, TRULICITY 1.5 mg and insulin glargine respectively, had missing data or were receiving rescue therapy and had their last observation prior to rescue or missing data carried forward for analysis. b Least-squares mean from ANCOVA model adjusted for baseline value and country.
† Overall Type I error rate for treatment comparisons was controlled using a tree-gatekeeping strategy.
Add on Combination Therapy to SGLT2i With or Without Metformin
Study GBGE (AWARD-10) - In this 24-week placebo controlled double-blind study, 423 patients were randomized and received TRULICITY (dulaglutide 0.75 mg or 1.5 mg) once weekly, or placebo, all as add-on to sodium glucose co-transporter 2 inhibitor (SGLT2i) with (96%) or without (4%) metformin. SGLT2i were used according to the local country label. Patients were randomized in a 1:1:1 ratio to Trulicity 0.75 mg, Trulicity 1.5 mg or placebo, with stratification for baseline HbA1c (≤8.0% [64 mmol/mol], >8.0% [64 mmol/mol]), dose of SGLT2i (“low” or “high”), and metformin use (“yes” or “no”).
The primary objective of the study was to demonstrate the superiority of dulaglutide (0.75 mg and/or 1.5 mg once weekly) to placebo, in HbA1c reduction from baseline at 24 weeks, in patients with inadequately controlled Type 2 diabetes as defined as HbA1c 7-9.5% on concomitant SGLT2i therapy with or without metformin.
At 24 weeks of treatment, TRULICITY 0.75 mg and 1.5 mg treatment resulted in a statistically significant greater reduction of HbA1c from baseline compared to placebo, each in combination with SGLT2 inhibitors with or without metformin (Table 7).
Table 7: Results at the 24-Week Primary Endpoint of TRULICITY Compared to Placebo, Both as
Add-on to SGLT2i With or Without Metformina
| TRULICITY | Placebo + SGLT2i ± MET | ||
0.75 mg + SGLT2i ± MET | 1.5 mg + SGLT2i ± MET | ||
| Intent-to-Treat (ITT) Population (N) | 141 | 142 | 140 |
| HbA1c (%) (Mean) | |||
| Baseline HbA1c | 8.0 | 8.0 | 8.1 |
| Change from baselineb | -1.2 | -1.3 | -0.5 |
| Difference from placebob (95% CI) | -0.7 (-0.8, -0.5) †† | -0.8 (-1.0, -0.6) †† | -- |
| Percentage of patients HbA1c < 7.0%c | 58†† | 67†† | 31 |
| Fasting Serum Glucose (mmol/L) (Mean) | |||
| Baseline | 8.99 | 8.91 | 8.50 |
| Change from baseline, adjusted meanb | -1.40 | -1.67†† | -0.37 |
| Body Weight (kg) (Mean) | |||
| Baseline | 91.1 | 92.9 | 90.5 |
| Change from baseline, adjusted meanb | -2.8 | -3.2† | -2.3 |
| Postprandial Glucose (mmol/L) (Mean) | |||
| Baseline | 10.34 | 10.16 | 10.36 |
| Change from baseline, adjusted meanb | -1.94 | -2.22 | -0.92 |
Abbreviations: HbA1c = hemoglobin A1c; SGLT2i = sodium glucose co-transporter 2 inhibitors; MET=metformin a For the ITT population, at Week 24, primary efficacy was missing for 3.5%, 5.6%, and 2.9% of individuals treated with
TRULICITY 0.75 mg, TRULICITY 1.5 mg, and placebo, respectively.
b Least-squares mean adjusted for baseline value and other stratification factors. All values, including post-rescue data, were used in the analyses. Placebo multiple imputation, using baseline and 24-week values from the placebo arm, was applied to model a washout of the treatment effect for patients missing 24-week values (HbA1c, fasting serum glucose, body weight and postprandial glucose).
c Patients with missing HbA1c data at Week 24 were considered as non-responders.
†† p<0.001, † p<0.05 for superiority of TRULICITY compared to placebo, overall type I error controlled using a graphical testing scheme.
Combination Therapy with Insulin Lispro with or without Metformin
Study GBDD (AWARD-4) - In this 52-week open-label comparator study (double-blind with respect to TRULICITY dose assignment), 884 patients on 1 or 2 insulin injections per day, alone or with oral antihyperglycemic therapy, were enrolled. Randomization occurred after a 9-week lead-in period; during the initial 2 weeks of the lead-in period, patients continued their pre-study insulin regimen but could be initiated and/or up-titrated on metformin, based on investigator discretion; this was followed by a 7-week glycemic stabilization period prior to randomization. At randomization, patients discontinued their pre-study insulin regimen and were randomized to TRULICITY (dulaglutide 0.75 mg or 1.5 mg) once weekly, or insulin glargine once daily, all in combination with prandial insulin lispro 3 times daily, with or without metformin. Insulin lispro was titrated in both arms based on preprandial and bedtime glucose, and insulin glargine was titrated based on a target fasting glucose of <5.6 mmol/L. The primary objective of the study was to demonstrate noninferiority of dulaglutide 1.5 mg once weekly compared to insulin glargine, both in combination with prandial insulin lispro, in HbA1c reduction from baseline at 26 weeks, with a noninferiority margin of 0.4%. Only 35.8% of patients in the glargine arm achieved their target fasting glucose.
At the 26-week time point, TRULICITY 1.5 mg was noninferior to insulin glargine for HbA1c change from baseline. TRULICITY 0.75 mg was also noninferior to insulin glargine (Table 8).
The mean total daily insulin lispro dose at Week 26 was 67.8 units, 96.7 units, and 93.2 units for the insulin glargine, TRULICITY 0.75 mg, and TRULICITY 1.5 mg study arms respectively. The differences in total daily insulin lispro dose based upon pairwise comparisons with insulin glargine were statistically significantly higher for both doses of TRULICITY.
Table 8: Results at the 26-Week Primary Endpoint of TRULICITY Compared to Insulin Glargine,
Both in Combination with Insulin Lisproa with or without Metformin
| 26-Week Primary Time Point | |||
| TRULICITY | Insulin Glargine + Insulin Lispro ± MET | ||
| 0.75 mg + Insulin Lispro ± MET | 1.5 mg + Insulin Lispro ± MET | ||
| Intent-to-Treat (ITT) Population (N) | 293 | 295 | 296 |
| HbA1c (%) (Mean) | |||
| Baseline HbA1c | 8.4 | 8.5 | 8.5 |
| Change from baseline, adjusted meanb | -1.6 | -1.6 | -1.4 |
| Difference from insulin glargine + insulin lispro arm, adjusted meanb (95% CI) | -0.2 (-0.3,-0.0) | -0.2 (-0.4, -0.1) | - |
| P value (non-inferiority) † | <0.001 | <0.001 | |
| Percentage of patients HbA1c <7.0% | 69 | 68 | 57 |
| Fasting Serum Glucose (mmol/L) (Mean) | |||
| Baseline | 8.34 | 8.73 | 8.56 |
| Change from baseline, adjusted mean | 0.22 | -0.27 | -1.58 |
| Body Weight (kg) (Mean) | |||
| Baseline | 91.7 | 91.0 | 90.8 |
| Change from baseline, adjusted mean | 0.2 | -0.9 | 2.3 |
| Postprandial Glucose (mmol/L) (Mean) | |||
| Baseline | 11.18 | 11.22 | 11.40 |
| Change from baseline, adjusted mean | -4.12 | -4.23 | -3.87 |
a Intent-to-treat population using last observation on study prior to any rescue therapy. At Week 26, 8%, 7% and 7% of individuals randomized to TRULICITY 0.75 mg, TRULICITY 1.5 mg and insulin glargine respectively, had missing data or were receiving rescue therapy and had their last observation prior to rescue or missing data carried forward for analysis. b Least-squares mean from ANCOVA adjusted for baseline value, country, and use of metformin. † Overall Type I error rate for treatment comparisons was controlled using a tree-gatekeeping strategy.
Combination Therapy with Insulin Lispro in Patients with Moderate to Severe CKD Study GBDX (AWARD-7) – In this 52-week (26-week primary endpoint) randomized, open-label to active comparator (double-blind with respect to TRULICITY dose assignment), 577 patients with Type 2 diabetes and moderate to severe CKD on insulin therapy alone or with oral anti-hyperglycemic medications (OAMs) ± pramlintide were randomized to TRULICITY (dulaglutide 0.75 mg or 1.5 mg) weekly or titrated insulin glargine at bedtime daily, all in combination with titrated lispro insulin before meals.
Randomization occurred after a 13-week lead-in period for patients on OAMs ± pramlintide and insulin during which OAMs ± pramlintide were discontinued and baseline insulin was optimized. Randomization occurred after a 3-week lead-in period for patients on insulin therapy alone during which the insulin regimen and doses remained stable.
Patients were stratified for randomization according to severity of CKD (Stage 3a, 3b, or 4) and a composite of macroalbuminuria and geography. The total enrollment was controlled to ensure a 2:1 ratio of patients with moderate (Stage 3a or 3b) or severe (Stage 4) CKD, respectively. The numbers and proportions of patients with moderate (Stage 3a or 3b) or severe (Stage 4) CKD were 402 (70%) and 175 (30%), respectively.
At randomization, patients discontinued their prestudy insulin regimen and patients were randomized to TRULICITY 0.75 mg once weekly, TRULICITY 1.5 mg once weekly, or insulin glargine once daily, all in combination with prandial insulin lispro. For patients randomized to insulin glargine, the initial insulin glargine dose was based on the basal insulin dose prior to randomization. Insulin glargine was allowed to be titrated with a fasting plasma glucose goal of ≤8.3 mmol/L. Insulin lispro doses were adjusted based on pre-lunch, pre-dinner, and bedtime plasma target glucose values of ≤ 10.0 mmol/L.
The primary objective of the study was to demonstrate that the effect of TRULICITY on HbA1c (measured as change from baseline) in the treatment of patients with type 2 diabetes and moderate or severe CKD was at least non-inferior compared with insulin glargine at 26 weeks (non-inferiority margin of 0.4%).
At the 26-week time point, TRULICITY 0.75 mg and 1.5 mg were noninferior to insulin glargine for HbA1c change from baseline (Table 9). The mean total daily insulin lispro dose at Week 26 was 37.4 units, 47.1 units, and 39 units for the insulin glargine, TRULICITY 0.75 mg, and TRULICITY 1.5 mg study arms respectively.
Table 9: Results at the 26-Week Primary Endpoint of TRULICITY Compared to Insulin Glargine,
Both in Combination with Insulin Lisproa in Patients with Moderate or Severe CKD
| 26-Week Primary Time Point | |||
| TRULICITY | Insulin Glargine + Insulin Lispro | ||
0.75 mg + Insulin Lispro | 1.5 mg + Insulin Lispro | ||
| Intent-to-Treat (ITT) Population (N)a | 190 | 192 | 194 |
| HbA1c (%) (Mean) | |||
| Baseline HbA1c | 8.6 | 8.6 | 8.6 |
| Change from baseline, adjusted meanb | -0.9 | -1.0 | -1.0 |
| Difference from insulin glargine + insulin lispro arm, adjusted meanb (95% CI) | 0.0 (-0.2, 0.3) | -0.1 (-0.3, 0.2) | - |
| P value (non-inferiority) † | <0.001 | <0.001 | - |
| Percentage of patients HbA1c <7.0% | 31 | 35 | 35 |
| Percentage of patients HbA1c <8.0% | 73 | 75 | 74 |
| Fasting Serum Glucose (mmol/L) (Mean) | |||
| Baseline | 9.28 | 8.91 | 9.42 |
| Change from baseline, adjusted mean | 0.36 | 0.77 | -1.29 |
| Body Weight (kg) (Mean) | |||
| Baseline | 90.9 | 88.1 | 88.2 |
| Change from baseline, adjusted mean | -1.1 | -2.0 | 1.9 |
| Postprandial Glucose (mmol/L) (Mean) | |||
| Baseline | 11.70 | 11.34 | 11.40 |
| Change from baseline, adjusted mean | -2.60 | -2.69 | -2.73 |
a All randomized patients who received at least 1 dose of study drug. At Week 26, 12%, 15%, and 9% of individuals randomized to
TRULICITY 0.75 mg, TRULICITY 1.5 mg, and insulin glargine were missing primary efficacy data. b Least-squares mean adjusted for baseline and stratification factors. All values, regardless of whether the patient was on study drug and/or received rescue medication, were included in the analyses. Multiple imputation by treatment group and adherence (yes, no) was applied for patients missing 26-week values.
† Overall Type I error rate for treatment comparisons was controlled using a gatekeeping strategy.
Fasting serum glucose increased from baseline by 0.36 mmol/L and 0.77 mmol/L in the TRULICITY 0.75 mg and TRULICITY 1.5 mg arms respectively, compared to a decrease of 1.29 mmol/L in the glargine arm.
Add on Combination Therapy to Insulin Glargine with or without Metformin
Study GBDI (AWARD-9) - In this 28-week randomized double-blind, parallel arm, placebo-controlled study, 300 patients on insulin glargine for at least 3 months, alone or with stable metformin therapy, were enrolled. Randomization occurred after a 2-week lead-in period in patients who required further up-titration of the insulin glargine dose per TTT (treat-to-target) algorithm at the end of the lead-in period. At randomization, patients were randomized to TRULICITY (dulaglutide 1.5 mg) once weekly, or matching placebo once weekly, added to insulin glargine with metformin [88%] or without metformin [12%]. At randomization, the initial insulin glargine dose in patients with HbA1c < 8.0% was reduced by 20%. After an initial 4 week stabilization period, insulin glargine was titrated based on a target fasting glucose of <5.6 mmol/L. The primary objective of the study was to demonstrate superiority of TRULICITY 1.5 mg once weekly compared to placebo, both in combination with titrated basal insulin glargine with or without metformin, in HbA1c reduction from baseline at 28 weeks.
At the 28-week time point, TRULICITY 1.5 mg was superior to placebo for HbA1c change from baseline (p<0.001) (Table 10). There were 49.3% and 37.9% of patients on TRULICITY and placebo respectively who achieved the target fasting serum glucose <5.6 mmol/L.
The least-squares mean daily insulin glargine dose at Week 28 was 51.4 units, and 64.6 units for the TRULICITY and placebo study arms respectively. The least-squares mean daily insulin glargine increase from baseline was 12.8 units for TRULICITY and 25.9 units for placebo.
Table 10: Results of a 28-Week Study of TRULICITY Compared to Placebo, as Add-On to Titrated
Basal Insulin Glargine With or Without Metformina
| 28-Week Primary Time Point | ||
TRULICITY 1.5 mg | Placebo | |
| Intent-to-Treat (ITT) Population (N) | 150 | 150 |
| HbA1c (%) (Mean) | ||
| Baseline HbA1c | 8.4 | 8.3 |
| Change from baseline, adjusted meanb | -1.4 | -0.7 |
| Difference from placebob (95% CI) | -0.7 (-0.9, -0.5) | - |
| P value (superiority) | <0.001 | |
| Percentage of patients HbA1c <7.0%c | 67 | 33 |
| Fasting Serum Glucose (mmol/L) (Mean) | ||
| Baseline | 8.71 | 8.68 |
| Change from baseline, adjusted meanb | -2.44 | -1.68 |
| Body Weight (kg) (Mean) | ||
| Baseline | 93.3 | 92.6 |
| Change from baseline, adjusted meanb | -1.3 | 0.8 |
| Postprandial Glucose (mmol/L) (Mean) | ||
| Baseline | 11.51 | 11.22 |
| Change from baseline, adjusted meanb | -3.05 | -2.23 |
Abbreviation: ANCOVA = analysis of covariance; CI = confidence interval; HbA1c = hemoglobin A1c; N = total number of patients. a Intent-to-treat population. At Week 28, 12% of placebo patients and 8% of dulaglutide 1.5 mg patients had missing data. Rescue therapy was not allowed in Study GBDI.
b Least-squares mean from ANCOVA adjusted for baseline value and other stratification factors. Placebo multiple imputation, with respect to baseline values, was used to model a wash-out of the treatment effect for subjects having missing Week 28 data. c Patients with missing HbA1c data at Week 28 were considered as non-responders.
Use in Patients with Type 2 Diabetes who have Multiple Cardiovascular Risk Factors or Established Cardiovascular Disease
Study GBDJ (REWIND) was a multi-national, multi-center, randomized, placebo-controlled, double-blind trial. In this study, 9901 adult patients with type 2 diabetes mellitus and multiple cardiovascular risk factors or established cardiovascular (CV) disease were randomized to TRULICITY 1.5 mg or placebo. The median follow-up duration was 5.4 years. The primary endpoint was the time to the first occurrence of a composite 3-component Major Adverse Cardiovascular Events (MACE) outcome, which included cardiovascular death, non-fatal myocardial infarction, and non-fatal stroke. The study evaluated if TRULICITY reduces MACE compared to placebo, when added to standard of care treatments for patients with type 2 diabetes.
Patients eligible to enter the trial were 50 years of age or older who had type 2 diabetes mellitus, had an HbA1c value ≤9.5% at screening, and had either established cardiovascular disease, or did not have established cardiovascular disease but had multiple cardiovascular risk factors. Patients who were confirmed to have established cardiovascular disease (31.5% of randomized patients) had a history of at least one of the following: myocardial infarction; myocardial ischemia by a stress test or with cardiac imaging; ischemic stroke; coronary, carotid, or peripheral artery revascularization; unstable angina; or hospitalization for unstable angina with at least one of the following: ECG changes, myocardial ischemia on imaging, or a need for percutaneous coronary intervention. Patients confirmed to be without established cardiovascular disease, but with multiple cardiovascular risk factors, comprised 62.8% of the randomized trial population.
At baseline, demographic and disease characteristics were balanced between treatment groups. Patients had a mean age of 66 years; 46% were female; race: White, Black, and Asian were 76%, 7%, and 4%, respectively.
The median baseline HbA1c was 7.2%; the majority of patients had a baseline HbA1c ranging from 6.0% - 8.9% (10th - 90th percentile). The mean duration of type 2 diabetes was 10.5 years and the mean BMI was 32.3 kg/m2.
At baseline 50.5% of patients had mild renal impairment (eGFR ≥60 but <90 mL/min/1.73 m2), 21.6% had moderate renal impairment (eGFR ≥30 but <60 mL/min/1.73 m2), and 1.1% of patients had severe renal impairment (eGFR <30 mL/min/1.73 m2) out of 9713 patients whose eGFR were available.
At baseline, 94.7% of patients were taking antidiabetic medication, with 10.5% of patients taking three or more antidiabetic drugs. The most common background antidiabetic drugs used at baseline were metformin (81.2%), sulfonylurea (46.0%), and insulin (23.9%). At baseline, cardiovascular disease and risk factors were managed with ACE inhibitors or angiotensin receptor blockers (81.5%), beta blockers (45.6%), calcium channel blockers (34.4%), diuretics (46.5%), statin therapy (66.1%), antithrombotic agents (58.7%) including aspirin (51.7%). The dulaglutide and placebo groups were generally balanced in terms of concomitant medications (anti-diabetic and cardiovascular medications including antihypertensives, diuretics, lipid-lowering, and platelet aggregation inhibitors). During the trial, investigators were to modify anti-diabetic and cardiovascular medications to achieve local standard of care treatment targets with respect to blood glucose, lipids, and blood pressure, and manage patients recovering from an acute coronary syndrome or stroke event per local treatment guidelines.
The primary analysis model was a Cox proportional hazards regression model for the time to the first occurrence of a primary endpoint event, with treatment as a fixed effect calculated using the Intent to Treat (ITT) population (all randomized patients).
TRULICITY reduced the risk of MACE by 12% as compared to placebo (HR: 0.88, 95% CI 0.79, 0.99) in persons with type 2 diabetes mellitus who have multiple cardiovascular risk factors or established cardiovascular disease (Figure 6 and Figure 7).
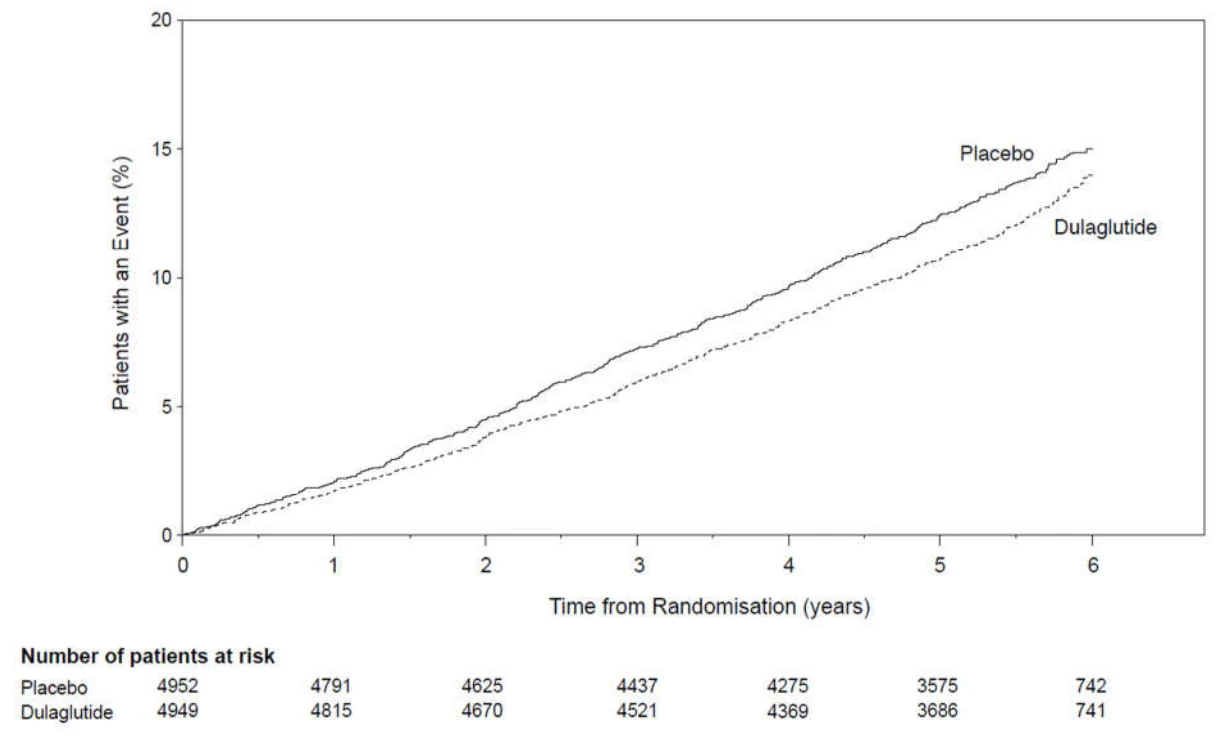
Figure 6: Kaplan-Meier plot of time to first MACE in the REWIND trial
Figure 7: Treatment Effect for MACE and the Individual Components in the REWIND Trial, Median
Study Observation Time of 5.4 yearsa
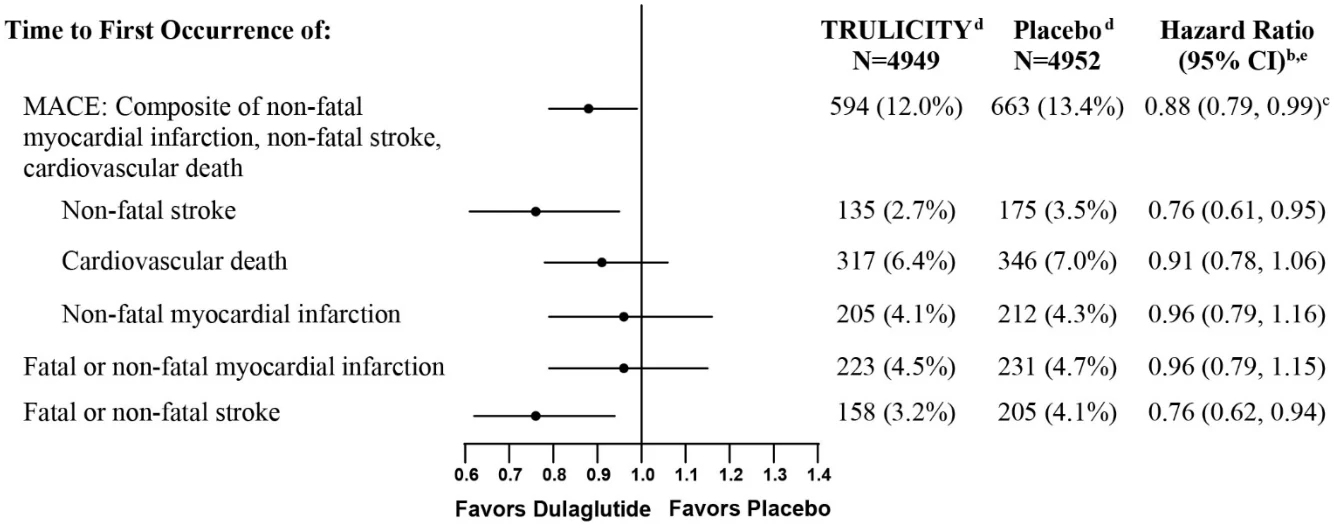
a All randomized patients.
b Cox-proportional hazards model with treatment as a factor. Type I error was controlled for the primary and secondary endpoints. c p=0.026 for superiority (2-sided).
d Number and percentage of patients with events.
e Results for components of MACE, fatal or non-fatal stroke, and fatal or non-fatal MI are listed descriptively for supportive purposes. CIs are not adjusted for multiplicity.
At month 3, the LS mean difference (95% CI) in HbA1c between Trulicity and placebo was - 0.82 (-0.86, -0.79)%. At month 60, the LS mean difference (95% CI) in HbA1c between Trulicity and placebo was -0.51 (-0.57, -0.45)%.
DETAILED PHARMACOLOGY
Dulaglutide is a biosynthetic fusion protein molecule produced using mammalian cell cultures and consists of 2 identical, disulfide-linked chains each containing an N-terminal GLP-1 receptor agonist sequence covalently linked to a modified human IgG4 Fc chain by a small peptide linker.
Dulaglutide increased insulin secretion in a dose-dependent fashion in rats and monkeys in Intravenous Glucose Tolerance Tests (IVGTT). Dulaglutide increased insulin secretion after both single and multiple SC administrations in a Stepped Glucose Infusion (SGI) model.
TOXICOLOGY
Repeat Dose Toxicity
Dulaglutide was administered by subcutaneous injection twice weekly to rats and cynomolgus monkeys, up to doses of 20 mg/kg body weight (215x human exposure) and 10 mg/kg bw (490x human exposure), respectively. Primary findings were consistent with the pharmacological activity of GLP-1R agonists and included decreased food consumption, transient reductions in body weight gain and clinical signs, including rough hair coat (rats), transient vomiting and dehydration (monkeys), thin appearance and reduced/absent feces.
Carcinogenicity
A 2-year carcinogenicity study was conducted with dulaglutide in male and female rats at doses of 0.05, 0.5, 1.5, and 5.0 mg/kg body weight (bw) administered by subcutaneous injection twice weekly. In both genders of rats, >0.5 mg/kg bw dulaglutide caused a dose-related and treatment-duration-dependent increase in the incidence of thyroid C-cell tumors (adenomas and/or carcinomas) compared to controls. A statistically significant increase in C-cell adenomas was observed in rats of both genders receiving dulaglutide at doses >0.5 mg/kg bw. Numerical increases in thyroid C-cell carcinomas occurred at doses of 0.5 mg/kg bw and were considered to be treatment-related despite the absence of statistical significance.
A 6-month carcinogenicity study was conducted with dulaglutide in rasH2 transgenic mice at doses of 0.3, 1.0, and 3.0 mg/kg bw administered by subcutaneous injection twice weekly. Dulaglutide did not produce increased incidences of thyroid C-cell hyperplasia or neoplasia at any dose.
Human relevance of thyroid C-cell tumors in rats is unknown and could not be determined by clinical studies or nonclinical studies (see Serious Warnings and Precautions Box and WARNINGS AND PRECAUTIONS).
Mutagenicity
Mutagenicity studies have not been conducted with dulaglutide.
Reproductive and Developmental Toxicity
In fertility and early embryonic development studies in male and female rats, no adverse effects of dulaglutide on sperm morphology, mating, fertility, conception, and embryonic survival were observed at doses up to 16.3 mg/kg bw. An increase in the number of females with prolonged diestrus and decreased numbers of corpus lutea resulting in lower number or implantation sites and viable embryos was observed at doses ≥4.89 mg/kg bw. Fetal evaluation revealed dose related decreases in body weight and higher litter proportions of reduced ossification of the skull and vertebral arches, and unossified sternebrae and hyoid at doses ≥4.89 mg/kg bw. These changes in skeletal ossification were considered secondary to reduced fetal weight.
In a juvenile toxicity study in rats, no dulaglutide-related effects were observed on neurobehavioral endpoints including motor activity, auditory startle responsiveness, and learning and memory assessments at the highest dose of 7 mg/kg (91-fold the maximum recommended human dose [MRHD] based on AUC). Changes in reproductive endocrine hormones (LH, GH, and estrogen) in male and female rats and earlier sexual maturation in female rats were observed at 91-fold the MRHD based on AUC. The apparent earlier onset of puberty in the female rats was still within the normal range for this strain of rats and was only seen at 91-fold the MRHD based on AUC. Thus, this effect was not considered to have relevance for humans in a recommended dosing range.
Other Toxicology Studies
Zucker diabetic fatty (ZDF) rats were administered dulaglutide twice weekly by subcutaneous injections at doses of 0.5, 1.5, or 5.0 mg/kg bw. Increases of 12% to 33% in total and pancreatic amylase, but not lipase, were observed at all doses without microscopic pancreatic inflammatory correlates in individual animals. Other changes in the dulaglutide-treated animals included increased interlobular ductal epithelium without active ductal cell proliferation (≥0.5 mg/kg bw), increased acinar atrophy with/without inflammation (≥1.5 mg/kg bw), and increased neutrophilic inflammation of the acinar pancreas (5 mg/kg bw).
Treatment of monkeys for 12 months with 8.15 mg/kg bw dulaglutide twice weekly showed no evidence of pancreatic inflammation or pancreatic intraepithelial neoplasia. In 4 of 19 monkeys on dulaglutide treatment, there was an increase in goblet cells within the pancreatic ducts, but no differences from the control group in total amylase or lipase at study termination. There were no proliferative changes in the thyroid C-cells.