


Product Monograph - Verdeso
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Topical use | Foam, 0.05% w/w Ethanol-free | Preservative: phenoxyethanol For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
VERDESO™ (desonide) Foam is indicated for the treatment of mild to moderate atopic dermatitis for up to 4 weeks in patients 1 year of age and older.
Geriatrics (> 65 years of age): No data are available.
Pediatrics (< 17 years of age): The safety and efficacy of VERDESO™ Foam have been established in children 1 year of age and older. VERDESO™ Foam has not been studied sufficiently in patients under 1 year of age to establish its safety in this age group (see WARNINGS AND PRECAUTIONS and CLINICAL TRIALS).
CONTRAINDICATIONS
- Patients who are hypersensitive to desonide or to the excipients. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
- Patients who are hypersensitive to other corticosteroids.
- Patients with viral (e.g. herpes or varicella) lesions of the skin, bacterial or fungal skin infections, parasitic infections, skin manifestations relating to tuberculosis or syphilis, eruptions following vaccinations, acne vulgaris, rosacea, pruritus without inflammation.
- Topical application to the eye.
WARNINGS AND PRECAUTIONS
General
Patients should be advised to inform subsequent physicians of the prior use of corticosteroids.
VERDESO™ Foam should not be used under occlusion, due to increased risk of systemic exposure and infection. When used under occlusive dressing, over extensive areas or on the face, scalp, axillae or scrotum, sufficient absorption may occur to result in adrenal suppression and other systemic effects (see WARNINGS AND PRECAUTIONS — Endocrine and Metabolism, Immune and Ophthalmologic).
Carcinogenesis and Mutagenesis
A photocarcinogenicity study in hairless albino mice showed that dermal administration of the vehicle foam alone enhanced the UVR-induced skin tumor development. Desonide foam had no additional effect on tumor development beyond the vehicle effect (see TOXICOLOGY). Exposure to natural or artificial sunlight of the treated skin areas should be minimized.
Desonide revealed no evidence of mutagenic potential based on the results of two in vitro genotoxicity assays (Ames and mouse lymphoma cell assay) and an in vivo genotoxicity assay (mouse micronucleus).
Cardiovascular
Suitable precautions should be taken when using topical corticosteroids in patients with stasis dermatitis and other skin diseases with impaired circulation.
Use of corticosteroids around chronic leg ulcers may be associated with a higher occurrence of local hypersensitivity reactions and an increased risk of local infection.
Endocrine and Metabolism
Systemic absorption of topical corticosteroids has produced reversible hypothalamic-pituitary-adrenal (HPA) axis suppression, manifestations of Cushing’s syndrome, hyperglycemia, and glucosuria in some patients.
Conditions which augment systemic absorption include the formulation and potency of the topical corticosteroid, the application of topical corticosteroids over large body surface areas, application to intertriginous areas (such as the axillae), frequency of application, prolonged use or the addition of occlusive dressings. Other risk factors for increased systemic effects include increasing hydration of the stratum corneum, use on thin skin areas (such as the face), use on broken skin or conditions where the skin barrier may be impaired.
If patients must be treated over large body surface areas, they should be evaluated periodically for evidence of HPA axis suppression (see WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests). If HPA axis suppression is noted, an attempt should be made to withdraw the drug by reducing the frequency of the application.
Recovery of HPA axis function is generally prompt upon discontinuation of topical corticosteroids. Infrequently, signs and symptoms of glucocorticosteroid insufficiency may occur requiring supplemental systemic corticosteroids. For information on systemic corticosteroid supplementation, see prescribing information for those products.
The effect of VERDESO™ Foam on HPA axis function was investigated in pediatric patients in one study. In this study, patients with atopic dermatitis covering at least 25% of their body applied VERDESO™ Foam twice daily for 4 weeks. Three out of 75 patients (4%) displayed adrenal suppression after 4 weeks of use based on the cosyntropin stimulation test. The laboratory suppression was transient; all subjects had returned to normal when tested 4 weeks post treatment.
Pediatric patients may absorb larger amounts of topical corticosteroids and thus be more susceptible to systemic toxicity from equivalent doses because of their larger skin surface to body mass ratios as compared with adults (see WARNINGS AND PRECAUTIONS – Special Populations, Pediatrics).
Immune
Topical corticosteroids may increase the risk of infections including aggravation of cutaneous infection, masked infection and secondary infections. In particular, bacterial infection is encouraged by warm, moist conditions within skin-fold areas or caused by occlusive dressings. If concomitant skin infections develop, VERDESO™ Foam should be discontinued and antimicrobial therapy administered.
Ophthalmologic
Topical corticosteroids should be used with caution on lesions close to the eye because systemic absorption may cause increased intraocular pressure, glaucoma or cataracts.
Sensitivity
Local hypersensitivity reactions (see ADVERSE REACTIONS) may resemble symptoms of the condition under treatment. If hypersensitivity reactions occur, the drug should be discontinued and appropriate therapy initiated.
Allergic contact dermatitis with corticosteroids is usually diagnosed by observing a failure to heal rather than noticing a clinical exacerbation. Such an observation should be corroborated with appropriate diagnostic patch testing.
Sexual Function/ Reproduction
There are no data in humans to evaluate the effect of topical corticosteroids on fertility.
Skin
If significant irritation develops, VERDESO™ Foam should be discontinued and appropriate therapy instituted.
Prolonged use of topical corticosteroid preparations may produce striae or atrophy of the skin or subcutaneous tissue. Topical corticosteroids should be used with caution on lesions of the face, groin and axillae as these areas are more prone to atrophic changes than other areas of the body. Frequent observation is important if these areas are to be treated. If skin atrophy is observed, treatment should be discontinued.
Special Populations
| Pregnant Women: | Corticosteroids have been shown to be teratogenic in laboratory animals when administered systemically at dosage levels that are similar to therapeutic doses. Some corticosteroids have been shown to be teratogenic after dermal application in laboratory animals. The relevance of this finding to human beings has not been established. No long-term reproductive studies in animals have been performed with VERDESO™ Foam. Dermal embryofetal development studies were conducted in rats and rabbits with a 0.05% desonide cream formulation and teratogenic effects characteristic of corticosteroids were noted in both species (see TOXICOLOGY). There are no adequate and well-controlled studies of VERDESO™ Foam in pregnant women. VERDESO™ Foam should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The minimum quantity should be used for the minimum duration. |
| Nursing mothers: | Systemically administered corticosteroids appear in human milk and could suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects. The safe use of topical corticosteroids during lactation has not been established. It is not known whether topical administration of corticosteroids could result in sufficient systemic absorption to produce detectable quantities in human milk. Because many drugs are excreted in human milk, caution should be exercised when VERDESO™ Foam is administered to a nursing woman. Administration of VERDESO™ during lactation should only be considered if the expected benefit to the mother outweighs the risk to the infant. If used during |
| lactation, VERDESO™ Foam should not be applied to the breasts to avoid accidental ingestion by the infant. | |
Pediatrics (< 17 years of age): | Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of HPA axis suppression and Cushing’s syndrome when they are treated with topical corticosteroids. They are therefore also at greater risk of adrenal insufficiency during and/or after withdrawal of treatment. Adverse effects including striae have been reported with use of topical corticosteroids in infants and children. HPA axis suppression, Cushing’s syndrome, linear growth retardation, delayed weight gain, and intracranial hypertension have been reported in children receiving topical corticosteroids. Manifestations of adrenal suppression in children include low plasma cortisol levels and an absence of response to ACTH stimulation. Manifestations of intracranial hypertension include bulging fontanelles, headaches, and bilateral papilledema. Chronic corticosteroid therapy may interfere with the growth and development of children. Administration of topical corticosteroids to children should be limited to the least amount and for the shortest duration compatible with an effective therapeutic regimen. The effect of VERDESO™ Foam on HPA axis function was investigated in pediatric patients, aged 6 months to 17 years, in one study. In this study, patients with atopic dermatitis covering at least 25% of their body applied VERDESO™ Foam twice daily for 4 weeks. Three out of 75 patients (4%) displayed adrenal suppression after 4 weeks of use based on the ACTH stimulation test. The suppression was transient; all subjects’ cortisol levels had returned to normal when tested 4 weeks post treatment. The safety of VERDESO™ Foam has not been adequately studied in pediatric patients younger than 1 year of age. |
Geriatrics (> 65 years of age): | Clinical studies of VERDESO™ Foam did not include any subjects aged 65 or over to determine whether they respond differently from younger subjects. In general, topical corticosteroids should be used cautiously in elderly patients, reflecting their increased skin fragility and greater frequency of hepatic, renal, or cardiac dysfunction, and of concomitant disease or other drug therapy. The greater frequency of decreased hepatic or renal function in the elderly may delay elimination if systemic absorption occurs. The minimum quantity should be used for the minimum duration. |
| Patients with renal / hepatic impairment: | In case of systemic absorption, metabolism and elimination may be delayed leading to increased risk of systemic toxicity; therefore, minimum quantity should be used for the minimum duration. |
Monitoring and Laboratory Tests
The cosyntropin (ACTH1-24) stimulation test may be helpful in evaluating patients for HPA axis suppression.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most common adverse reactions reported in association with VERDESO™ Foam occurred mainly at the application site and included mild to moderate: burning, atrophy, erythema, and dryness.
Hypothalamic-pituitary-adrenal (HPA) axis suppression has been reported with topical corticosteroids. Manifestations of HPA axis suppression include increased weight / obesity, delayed weight gain / growth retardation in children, Cushing’s syndrome, cushingoid features (e.g., moon face, central obesity), HPA disorder, decreased endogenous cortisol levels, hyperglycemia / glucosuria, hypertension, osteoporosis, cataract, glaucoma, steroid withdrawal syndrome (see WARNINGS AND PRECAUTIONS).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Two controlled clinical trials (a large pivotal study and a smaller supportive study) provide safety information on 687 patients with mild to moderate atopic dermatitis treated with twice daily applications of VERDESO™ Foam (n=459) or Vehicle Foam (n=228) for 4 weeks. The most frequently reported treatment-related adverse reaction was application site burning, which occurred in 2% of patients receiving VERDESO™ Foam and 7% of patients receiving Vehicle Foam.
Table 1 summarizes adverse reactions reported by at least 1% of patients in any treatment group in these two studies. The majority of adverse reactions were transient and mild to moderate in severity.
Similarly, in an open label study investigating the effect of VERDESO™ Foam on HPA axis function in 81 pediatric patients with atopic dermatitis covering at least 25% of their body, 7(9%) of patients reported adverse reactions, all of which were mild to moderate application site reactions of burning, dryness, erythema and pruritus.
Table 1 Incidence of common (≥1%) adverse drug reactions reported during the controlled clinical trials (Descending order of frequency, Intent to Treat Population)
System Organ Class and Preferred Term | VERDESO™ Foam n=459 | Vehicle Foam n=228 | ||
|---|---|---|---|---|
| General Disorders and Administration Site Conditions | ||||
| Application site burning | 11 (2%) | 16 (7%) | ||
| Application site reaction | 3 (1%) | 7 (3%) | ||
| Application site erythema | 2 (<1%) | 4 (2%) | ||
| Application site atrophy* | 5 (1%) | 0 (0%) | ||
Less Common Clinical Trial Adverse Drug Reactions (<1%)
General Disorders and Administration Site Conditions: Application site pruritus, Application site dermatitis, Application site pigmentation change, Application site dryness
Infections and Infestations: Cellulitis
Psychiatric Disorders: Irritability, Sleep disorder
Skin and Subcutaneous tissue disorders: Dry skin
Abnormal Hematologic and Clinical Chemistry Findings
No abnormal hematologic and clinical chemistry findings were identified during clinical trials with VERDESO™ Foam.
Post-Market Adverse Drug Reactions
The following adverse reactions have been identified during post approval use of VERDESO™ Foam. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Endocrine Disorders: see ADVERSE DRUG REACTIONS, Overview
Immune System Disorders: hypersensitivity
Infections and Infestations: Opportunistic infection, secondary infection
Skin and Subcutaneous Tissue Disorders: skin exfoliation, erythema, pain of skin, rash, pruritis, urticaria, discoloration/pigmentation changes*, exacerbation of underlying symptoms, alopecia, local burning, itching, irritation, dryness, folliculitis, hypertrichosis, acneiform eruptions, hypopigmentation, perioral dermatitis, allergic contact dermatitis/dermatitis, secondary infection, facial swelling, skin atrophy, striae and miliaria, as well as application site irritation, erythema, discolouration, swelling, pain, erosion and vesicles.
*Skin features secondary to local and/or systemic effects of hypothalamic-pituitary adrenal (HPA) axis suppression.
DRUG INTERACTIONS
Overview
No clinical trials were specifically designed to assess potential drug-drug, drug-food, drug-herb or drug-laboratory interactions with VERDESO™ Foam.
Co-administered drugs that can inhibit CYP3A4 (e.g., ritonavir, itraconazole) have been shown to inhibit the metabolism of corticosteroids leading to increased systemic exposure. The extent to which this interaction is clinically relevant depends on the dose and route of administration of the corticosteroids and the potency of the CYP3A4 inhibitor.
Drug-Drug Interactions
Interactions with other drugs have not been established.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Patients/caregivers should be instructed to use VERDESO™ Foam for the minimum amount of time necessary to achieve the desired results because of the potential for corticosteroids to suppress the hypothalamic-pituitary-adrenal (HPA) axis and cause skin atrophy (see WARNINGS AND PRECAUTIONS).
- VERDESO™ Foam is for topical use only and not for ophthalmic, oral or intravaginal use.
- Pediatric patients may be more susceptible to local and systemic toxicity from equivalent doses because of their larger skin surface to body weight ratios.
- Geriatric patients may be more susceptible to percutaneous absorption and the potential effects of systemic absorption. The greater the frequency of decreased hepatic or renal function in the elderly may delay elimination if systemic absorption occurs.
Recommended Dose and Dosage Adjustment
A thin layer of VERDESO™ Foam should be applied to the affected area(s) twice daily for a maximum of 4 consecutive weeks.
Avoid abrupt discontinuation of topical corticosteroids when control is achieved as rebound of pre-existing dermatoses can occur. An emollient should be continued as maintenance therapy.
If the condition worsens or no improvement is seen within 2-4 weeks, reassessment of diagnosis and treatment may be necessary.
Pediatrics (< 17 years of age): VERDESO™ Foam is not recommended for use in infants below 1 year of age. For children beyond 1 year of age, the minimum quantity should be used for the shortest duration to achieve the desired clinical benefit (see WARNINGS AND PRECAUTIONS – Special Populations, Pediatrics).
Geriatrics (>65 years of age): VERDESO™ Foam should be used with caution due to increased risk of renal or hepatic impairment in this population. The minimum quantity should be used for the shortest duration to achieve the desired clinical benefit (see WARNINGS AND PRECAUTIONS – Special Populations, Geriatrics).
Renal/Hepatic Impairment: The minimum quantity should be used for the shortest duration to achieve the desired clinical benefit (see WARNINGS AND PRECAUTIONS — Special Populations, Patients with renal / hepatic impairment).
Missed Dose
Any missed dose should be applied as soon as possible and then continue with the regular frequency of doses (i.e., no extra doses should be applied).
Administration
VERDESO™ Foam should not be used with occlusive dressings.
Shake the can before use. VERDESO™ Foam should be dispensed by inverting the can (upright actuation will cause loss of the propellant which may affect product delivery).
Dispense the smallest amount of foam necessary to adequately cover the affected area(s) with a thin layer.
Application to affected areas of the face: The medication should not be dispensed directly on the face. Dispense in hands and gently massage into affected areas of the face until the medication disappears.
Application to affected areas other than the face: For areas other than the face, the medication may be dispensed directly onto the affected area. Gently massage into the affected area until the medication disappears.
Take care to avoid contact with the eyes or other mucous membranes.
VERDESO™ is extremely flammable, avoid fire, open flame, spark or smoking during and immediately following application.
OVERDOSAGE
Topically applied corticosteroids can be absorbed in sufficient amounts to produce systemic effects. Excessive prolonged use or misuses may suppress hypothalamic-pituitary-adrenal (HPA) axis function, resulting in secondary adrenal insufficiency. If symptoms of HPA axis suppression occur, VERDESO™ Foam should be gradually discontinued by reducing the frequency of application, as clinically indicated. If toxic effects occur, VERDESO™ Foam should be discontinued and symptomatic therapy administered (see WARNINGS AND PRECAUTIONS).
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
VERDESO™ Foam belongs to a class of topical drugs called topical corticosteroids. It is considered to be a mild or low potency corticosteroid. Topical corticosteroids share anti-inflammatory, anti-pruritic, and vasoconstrictive actions. The mechanism of anti-inflammatory activity of topical corticosteroids is unclear. However, corticosteroids are thought to act by the induction of phospholipase A2 inhibitory proteins, collectively called lipocortins. It is postulated that these proteins control the biosynthesis of potent mediators of inflammation such as prostaglandins and leukotrienes by inhibiting the release of their common precursor arachidonic acid. Arachidonic acid is released from membrane phospholipids by phospholipase A2.
Pharmacokinetics
The pharmacokinetics of VERDESO™ Foam (absorption, distribution, excretion and metabolism) have not been specifically investigated in any studies. Pharmacokinetic properties of the drug class of topically applied corticosteroids remain incompletely understood.
Topical corticosteroids can be systemically absorbed from intact healthy skin. The extent of percutaneous absorption of topical corticosteroids is determined by many factors, including the product formulation, potency, vehicle, frequency and duration of application, as well as integrity of the epidermal barrier, skin thickness, application to intertriginous areas (such as the axillae) and to large skin surface areas. Occlusion, hydration of the stratum corneum, inflammation and/or other disease processes in the skin may also increase percutaneous absorption. The use of pharmacodynamic endpoints for assessing the systemic exposure of topical corticosteroids may be necessary due to the fact that circulating levels are often below the level of detection.
Once absorbed through the skin, topical corticosteroids are handled through pharmacokinetic pathways similar to systemically administered corticosteroids. They are metabolized, primarily in the liver, and are then excreted by the kidneys. Some corticosteroids and their metabolites are also excreted in the bile.
Pharmacodynamics
The vasoconstriction activity of VERDESO™ Foam in normal skin was assessed in comparison to that of other commercially available topical corticosteroid formulations in two studies (one a pilot assay) in healthy adult male and female subjects. There was no significant difference in the vasoconstriction response between VERDESO™ Foam and a cream formulation of desonide 0.05% that is generally recognized as having mild or low potency.
The effect of VERDESO™ Foam on hypothalamic-pituitary-adrenal (HPA) axis function was studied in 81 pediatric patients aged 6 months to 17 years with mild to moderate atopic dermatitis covering at least 25% body surface area, who applied VERDESO™ Foam twice daily. In this study, 3 of 75 (4%) patients experienced reversible suppression of the adrenal glands following 4 weeks of therapy (see WARNINGS AND PRECAUTIONS - Endocrinology and Metabolism and Special Population, Pediatrics).
STORAGE AND STABILITY
Store upright at controlled room temperature (20-25 C). Avoid storage in an inverted position. Keep container tightly closed when not in use. Keep out of reach and sight of children.
SPECIAL HANDLING INSTRUCTIONS
DANGER
EXTREMELY FLAMMABLE, AVOID FIRE, OPEN FLAME, SPARK OR SMOKING DURING AND IMMEDIATELY FOLLOWING APPLICATION.
Warning: Contents under pressure. Do not puncture or incinerate container. Do not expose to heat or store at temperatures above 49°C. Do not place in hot water or near radiators, stoves or other sources of heat.
DOSAGE FORMS, COMPOSITION AND PACKAGING
VERDESO™ Foam is a white to off-white petrolatum-based emulsion aerosol foam to provide patients with an easily applied product containing occlusive agents and excipients with emollient properties which may have moisturizing effect on the skin of patients with atopic dermatitis.
Each gram of VERDESO™ Foam contains 0.5 mg desonide. The foam also contains white petrolatum, light mineral oil, isopropyl myristate, cyclomethicone, anhydrous citric acid, cetyl alcohol, polyoxyl 20 cetostearyl ether, potassium citrate (monohydrate), propylene glycol, purified water, sorbitan monolaurate, and phenoxyethanol as a preservative.
VERDESO™ Foam is dispensed from an aluminum can pressurized with a hydrocarbon (propane/butane) propellant, supplied in 100 g aluminium cans.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Common name: | desonide |
| Chemical name: | (11β,16α)-11,21-dihydroxy-16,17- [(1-methylethylidene)bis(oxy)]- pregna-1,4-diene-3,20-dione 16 ,17 -isopropylidenedioxyprednisolone |
| Molecular formula: | C24H32O6 |
| Molecular mass: | 416.51 |
| Structural formula: | 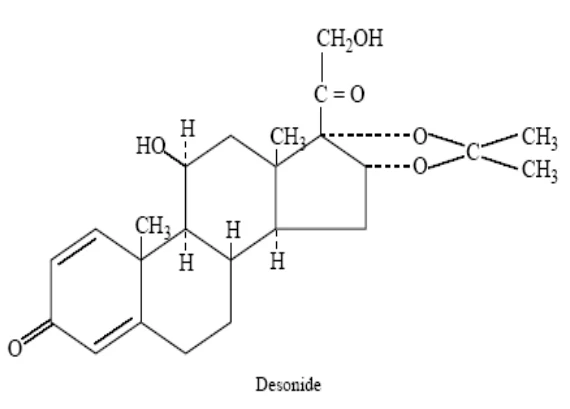 |
| Physicochemical properties: | Desonide is a white to off-white powder or crystal that is practically insoluble in water, sparingly soluble in ethanol and in acetone, and soluble in chloroform. |
CLINICAL TRIALS
In a double-blind, randomized study of 581 patients aged 3 months to 17 years old with mild to moderate atopic dermatitis, VERDESO™ Foam was applied twice daily for 4 weeks. Treatment success was defined as the proportion of patients who had all of the following: an Investigator’s Static Global Assessment (ISGA) score of clear or almost clear, a minimum improvement in the 5 point ISGA score of 2 grades from Baseline to Week 4, and a score of absent or minimal for both erythema and induration/papulation at Week 4. The results of this study demonstrated that VERDESO™ Foam was significantly more effective than vehicle foam in reducing the manifestations of atopic dermatitis, as measured by treatment success. There were insufficient numbers of patients under 1 year of age to establish the safety of VERDESO™ Foam in this age group.
Study demographics and trial design
Table 2 Summary of patient demographics for pivotal clinical trials in the treatment of adolescent and pediatric subjects with mild to moderate atopic dermatitis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| DES.C.301 | Phase 3, multicentre, randomized, double-blind, vehicle- controlled study | VERDESO™ Foam twice daily topical application for 4 weeks | 387 | 7.0 (0.3, 18.0) | 198M/189F |
Vehicle Foam twice daily topical application for 4 weeks | 194 | 6.8 (0.4, 18.0) | 90M/104F |
Overall enrollment by gender in the Intent-to-Treat (ITT) population was 49% (288/581) male and 51% (293/581) female. The distribution of the age of the subjects in the Intent-to-Treat (ITT) population was 19% (110/581) 12 to < 18 years of age, 30% (176/581) ≥ 6 to < 12 years of age, 23% (133/581) ≥3 to < 6 years of age, 28% (162/581) ≥ 3 months to < 3 years of age. The enrolled study subject population was 50% (291/581) Caucasian. African- American subjects comprised 26% (143/581), Hispanic 17% (98/581), Asian 3% (23/581), and Other 4% (26/581) of the study population. The majority of the subjects enrolled (62%, 361/581) had a Baseline ISGA score of 3 (moderate) and 38% (219/581) had a baseline ISGA score of 2 (mild). The mean extent of atopic dermatitis (% BSA) at Baseline was 21.3% for the VERDESO™ Foam group and 19.8% for the Vehicle Foam group.
Study results
Results for the primary endpoint, the proportion of patients with treatment success at Week 4/End of treatment, are presented in Table 3.
Table 3 Efficacy of VERDESO™ Foam in mild to moderate atopic dermatitis (Study DES.C.301, ITT population)
| Primary Endpoints | VERDESO™ Foam ( n = 387) | Vehicle Foam ( n = 194) |
| Patients Achieving Treatment Success* | 152 (39%) | 18 (9%) p ≤ 0.0001 |
* Success is defined as the proportion of subjects with an Investigator's Static Global Assessment (ISGA) score of 0 (clear) or 1(almost clear), a score of 0 or 1 for both erythema and induration/papulation at Week 4, and a minimum improvement in the ISGA score of 2 grades from Baseline to Week 4.
The mean percent reduction in the sum of the scores of erythema, induration/papulation, lichenification, scaling, and oozing/crusting from Baseline to Week 4 (principal secondary endpoint) was 60.0% for VERDESO™ Foam vs. 20.9% for Vehicle Foam.
DETAILED PHARMACOLOGY
(See also ACTION AND CLINICAL PHARMACOLOGY, Part I)
Topical corticosteroids share anti-inflammatory, anti-pruritic, and vasoconstrictive actions. Desonide is a hydrocortisone analog that was first synthesized in 1959 in an effort to maximize anti-inflammatory properties while minimizing mineralocorticoid activity and adverse effects of hydrocortisone.
Pharmacodynamics
No pharmacodynamic studies have been conducted with VERDESO™ Foam.
Studies conducted with the active pharmaceutical ingredient desonide included four animal models of anti-inflammatory activity (liver glycogen deposition, cotton pellet granuloma, ear edema, and ocular inflammation). These studies showed desonide to be more potent than hydrocortisone and prednisolone. (1)
In addition to their anti-inflammatory activity, an important pharmacological effect of corticosteroids for treating dermatoses relies on their anti-proliferative activity in the epidermis since some dermatoses are manifested by the hyper-proliferation of keratinocytes.
Pharmacokinetics
No pharmacokinetic studies have been conducted with VERDESO™ Foam.
Studies evaluating the active pharmaceutical ingredient desonide include a tissue distribution study in rats via intravenous administration and a percutaneous absorption study in rabbits.
Desonide and its metabolites are rapidly distributed throughout body tissues after intravenous administration with the highest levels found in the liver and the lowest level in the brain.
The extent of percutaneous absorption of topical corticosteroids is determined by many factors, including the product formulation, use of occlusion, and the integrity of the epidermal barrier. Absorption studies conducted with desonide indicate that occlusion alone did not significantly increase the percutaneous absorption of desonide across healthy skin of rabbits in a cream formulation compared to application to non-occluded skin. However, percutaneous absorption of desonide from a cream formulation approximately doubled when applied to abraded skin under occlusion compared to application to non-occluded abraded skin of rabbits. (1)
An in vitro skin penetration study with VERDESO™ Foam and other desonide formulations revealed that desonide penetration is formulation dependent with the highest penetration resulting from desonide lotions followed by VERDESO™ Foam, followed by desonide gel, cream and ointment formulations. After 10 hrs of exposure, VERDESO™ Foam delivered 30% less desonide through the in vitro skin preparation compared to a lotion formulation and approximately 2 to 4 fold more desonide than gel, cream, or ointment formulations delivered.
While not completely understood, once absorbed through the skin, topical corticosteroids are thought to be handled through pharmacokinetic pathways similar to systemically administered corticosteroids. They are metabolized, primarily in the liver, and are then excreted by the kidneys. (1) Some corticosteroids and their metabolites are also excreted in the bile. In general these metabolites are conjugated at the 3-hydroxyl site with sulfate or glucuronic acid to form water-soluble metabolites. (2)
TOXICOLOGY
No acute or chronic toxicological studies have been carried out with VERDESO™ Foam. However, these studies are available for desonide.
Single-dose oral toxicity studies of desonide in an ointment formulation (0.05%) were conducted in both rats and rabbits. The acute oral dose lethal to 50% of animals (LD50) for 0.05% desonide ointment in the rat and in the rabbit were greater than 42.5 g/kg and 38.3 g/kg, respectively.
Toxicity of desonide in cream formulations (0.05% or 0.2%) was assessed in rats, rabbits, and dogs by either oral or topical administration (5). Slight to moderate erythema and slight edema were reported in the rabbit treated with 16 g/kg of a 0.2% cream formulation and resolved within 1 week of treatment. No significant findings were reported in the rat or dog after oral exposure to a 0.2% cream formulation in an aqueous suspension at dose levels of 33.3 g/kg or 10 g/kg respectively, or in the rat dosed dermally with 16 g/kg of a 0.05% desonide cream formulation.
The potential toxicity of desonide after repeated doses up to 13 weeks was evaluated in three nonclinical studies conducted in rabbits with intact and abraded skin by topical administration. Thirteen weeks of topical dosing of a 0.05% desonide cream formulation to rabbits resulted in none to moderate erythema, with dermal irritation related to the amount of cream applied daily
(0.2, 0.6, or 2 g/kg). Significant changes related to the test article included increased liver weights in high-dose males and increased liver weight ratios in mid- and high-dose males and high-dose females, decreased adrenal weights and weight ratios at all dose levels in both sexes, decreased gonad weight in high-dose males and females, and decreased spleen weight in high-dose females. No corresponding changes were observed by histopathological examination of the organ tissues. It was concluded that the risk of toxicity resulting from topical application of up to 2 g/kg of 0.05% desonide cream for up to 3 months is quite low.
Special Toxicity Studies
Two acute irritation studies (skin and eye) and a dermal sensitization study performed on VERDESO™ Foam.
Table 4 Tabulation of Special Toxicity studies with BMV Foams
| Species | Route | Test Substance | Study Type |
| Rabbit | Topical | VERDESO™ Foam 0.05% | Acute Dermal Irritation |
| Rabbit | Intraocular | VERDESO™ Foam 0.05% | Acute Eye Irritation |
| Guinea pig | Topical | VERDESO™ Foam 0.05% | Skin Sensitization (repeat dose) |
In these studies VERDESO™ Foam was found to be non-irritating to both intact and abraded skin of the rabbit, non-irritating to the eyes of the rabbit, and did not produce a dermal hypersensitivity response in guinea pigs.
Developmental and Reproduction Studies
No long-term reproductive studies in animals have been performed with VERDESO™ Foam.
Dermal embryofetal development studies were conducted in rats and rabbits with a 0.05% desonide cream formulation. Topical doses of 0.2, 0.6, and 2 g cream/kg/day or 2 g/kg/day of the cream base were administered to pregnant rats (gestational days 6–15) and pregnant rabbits (gestational days 6–18). Maternal body weight loss was noted at all dose levels in rats and rabbits. Teratogenic effects characteristic of corticosteroids were noted. In rats, significantly more resorption sites and fewer viable fetuses were observed, body weights of the fetuses were decreased and skeletal abnormalities including abnormal interparietal development resulted from exposure to doses above 0.6 g cream/kg/day. In rabbits, a significant increase in the number of resorption sites was noted, fetuses were significantly smaller, and skeletal anomalies including poorly developed parietals resulted at a dose of 2 g cream/kg/day.
Mutagenicity/Carcinogenicity
A battery of genotoxicity studies (Ames assay, mouse lymphoma assay and mouse micronucleus assay) were completed for desonide. These studies did not show desonide to be mutagenic.
In a 52 week dermal photo-carcinogenicity study (40 weeks of treatment followed by 12 weeks of observation), albino hairless mice were treated with desonide foams 0.025%, 0.05%, and
0.125% or vehicle foam and exposed to solar-simulated ultraviolet radiation (low and high UVR). Vehicle foam enhanced UVR-induced skin tumor development. The addition of desonide to the vehicle foam resulted in a slight reduction in UVR-induced skin tumor development compared with the vehicle alone group.
REFERENCES
- 1. Phillips BM, Sanen FJ, Leeling JL et al. The physical, animal and human pharmacologic, and toxicologic properties of desonide, a new, topically active, antiinflammatory steroid. Toxicol Appl Pharmacol. 1971; 20:522-37.
- 2. Schimmer BP, Parker KL. Adrenocorticotropic Hormone; adrenocortical steroids and their synthetic analogs; Inhibitors of synthesis and actions of adrenocortical hormones. In: The pharmacological basis of therapeutics (ninth edition) (Hardman JG, Limbird LE, eds): McGraw-Hill. 1996:1459-85.