


Product Monograph - Voltaren Emulgel Joint Pain Regular Strength
1 Indications
Adults and adolescents aged 16 years and over:
VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active (diclofenac diethylamine gel 1.16% w/w) are indicated for:
- Relief of pain associated with recent (acute), localized muscle or joint injuries such as sprains, strains or sports injuries (e.g. sprain of ankle, strain of shoulder or back muscles). This is typically as an adjunct to other measures, such as rest, for the relief of discomfort associated with such injuries.
1.1. Pediatrics
Pediatrics (< 16 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (>65 years of age): The usual adult dosage may be used.
2 Contraindications
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
- Hypersensitivity to diclofenac, acetylsalicylic acid or other non-steroidal anti-inflammatory drugs.
- Patients with or without chronic asthma in whom attacks of asthma, angioedema, urticaria or acute rhinitis are precipitated by acetylsalicylic acid or other non-steroidal anti-inflammatory agents.
- Concomitant use of other products containing diclofenac.
- Concomitant use of oral non-steroidal anti-inflammatory drugs (NSAIDs).
- During the last trimester of pregnancy.
- Following coronary artery bypass grafting surgery.
4 Dosage and Administration
4.1. Dosing Considerations
- See 4.2 Recommended Dose and Dosage Adjustment
4.2. Recommended Dose and Dosage Adjustment
Adults and adolescents 16 years and older:
- VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active should be applied to the affected area 3 or 4 times daily and should be rubbed gently into the skin. It should not be used more than 4 times in 24 hours.
The duration of treatment depends on the natural course of healing, rest and also on clinical response. The gel should not be used for more than 7 days for muscle and joint injuries, unless recommended by a doctor. If the condition does not improve or worsens within 7 days of starting treatment, patients should consult their doctor to exclude an alternative underlying cause of pain.
Health Canada has not authorized an indication for pediatric use in children under 16 years of age.
4.4. Administration
For topical use only.
The amount needed depends on the size of the painful area: 2g to 4g of gel is sufficient to treat an area of about 400-800 cm2.
VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength
1g equals a strip approx. 2 cm long.
VOLTAREN EMULGEL Active
For each application, hold the tube upright and squeeze the gel from the tube. Two grams (2 g) is represented by filling the dosing ring on the cap. After use, clean the cap with a tissue until visibly clean and dry.
After application, the hands should be wiped with a tissue and then washed. The tissue should be thrown in the trash after use. Patients should wait until the gel dries before showering or bathing.
4.5. Missed Dose
If a dose of VOLTAREN EMULGEL (or VOLTAREN EMULGEL Back & Muscle Pain or VOLTAREN EMULGEL Joint Pain Regular Strength or VOLTAREN EMULGEL Active) is missed, it should be applied when the consumer remembers and then again at the next scheduled time. A double quantity should not be applied.
5 Overdosage
The low systemic absorption of topical diclofenac renders overdose very unlikely. However undesirable effects, similar to those observed following an overdose of VOLTAREN tablets, can be expected if VOLTAREN EMULGEL (or VOLTAREN EMULGEL Back & Muscle Pain or VOLTAREN EMULGEL Joint Pain Regular Strength or VOLTAREN EMULGEL Active) is ingested (1 unit of 100 g contains the equivalent of 1 g diclofenac sodium) respectively.
In the event of accidental ingestion, resulting in significant systemic side effects, general therapeutic measures normally adopted to treat poisoning with non-steroidal anti-inflammatory drugs should be used. Further management should be as clinically indicated, or as recommended by the regional Poison Control Centre.
Management of overdosage with NSAIDs essentially consists of supportive and symptomatic measures. Supportive and symptomatic treatment should be given for complications such as hypotension, renal failure, convulsions, gastro-intestinal irritation, and respiratory depression; specific therapies such as forced diuresis, dialysis or haemoperfusion are probably of no help in eliminating NSAIDs due to their high rate of protein binding and extensive metabolism.
There are 173 worldwide cases of overdose with diclofenac diethylamine in the company safety database. Fifty concern patients of age up to 18 years; 78 concern the adult and elderly population, and 45 concern patients of unspecified age.
In the paediatric population, no adverse event was reported in 39 out of 50 cases; 5 out of 11 cases with clinical adverse events (with patient’s age ranging from 5 months to 11 years) reported listed skin reactions after topical application (e.g. rash, urticaria, erythema). Other adverse events reported were burning sensation; skin disorder, alopecia, thermal burn, decreased appetite, thyroid disorder, headache, diarrhoea, nausea, skin reaction, erythema (in this medically confirmed case, the causal relationship with diclofenac diethylamine gel was assessed as unlikely); vomiting, headache and dizziness; inflammation; eye swelling, nasal inflammation and eye inflammation in two children who accidentally received a small amount of gel near the eyes; nausea and feeling abnormal.
There were no cases of accidental ingestion. A 19-month-old child accidentally ran her lips around an opened tube, but no adverse events were reported.
Diclofenac diethylamine gel 1.16% w/w should not be used in adults and adolescents under 16 years.
In the adult population, out of 78 cases, 24 reported clinical adverse events after topical application: e.g. skin reactions (rash, burning sensation, skin exfoliation, eczema, erythema, dermatitis), hypersensitivity symptoms (e.g. swollen tongue, dyspnoea), peripheral swelling, feeling hot, gastrointestinal reactions (e.g. epigastric discomfort in a case with co-suspect celecoxib; abdominal pain upper, vomiting), hypotension (case confounded by concomitant medications), events related to the underlying condition (e.g. pain, arthralgia, chondropathy). A 79-year-old polymedicated patient with a medical history of hypertension, type 2 diabetes mellitus, and respiratory disease developed acute renal failure after using two full tubes of 120 grams in a 10-day period. Angina pectoris occurred in a 46-year-old polymedicated (not further specified) male patient treated with diclofenac free acid for nearly 20 years with a dose of 2 tablets 3 times a day (overdose) in addition to recently started diclofenac diethylamine. A 78-year-old patient treated with fluindione developed haematoma after application of excessive amounts (a tube of 100 ml in 4 days) of diclofenac diethylamine gel.
In the population of unspecified age, out of 45 cases, only 16 cases reported clinical adverse events after topical application: e.g. skin reactions (e.g. application site pruritus, skin irritation, rash), sensory loss, burning sensation, peripheral swelling, gastritis in a patient with a history of stress-induced gastritis, poisoning (not further specified). In one case, a female patient developed unspecified circulatory system complaints, dizziness and nausea after applying too much product, summarized as misuse of 2 x 150 g per week. Final outcome was complete recovery. A female consumer wanted to commit suicide with diclofenac diethylamine gel; no other adverse event than suicide attempt was reported. In another case, a male patient with an unspecified renal disorder developed comatose state and possible renal failure after use of the product regularly and continuously for more than one year over a large area of skin including the back, the shoulder and the legs. The patient used about 2 tubes every three weeks. In another case, a female patient with alcohol and narcotic addiction used the product to get intoxicated. Diclofenac diethylamine gel was heated, and the vapours were being aspirated with a specific syringe. The content was injected into the mouth or the ear to achieve intoxication from the alcohol that had been extracted from the process. No adverse event other than alcohol poisoning and drug abuse was reported.
There was one case of ingestion: An elderly female patient accidentally swallowed diclofenac diethylamine gel 25g but most of it was not absorbed because the patient spontaneously vomited most of the drug. No further adverse event occurred.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition, and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Topical | Gel, 11.6 mg/g diclofenac diethylamine | carbomer, cocoyl caprylocaprate, diethylamine, fragrance (containing benzyl |
This product contains paraffin (see 7 Warnings and Precautions).
VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active are white to practically white, soft, homogenous, cream-like gel and packaged in:
- An aluminium tube with a sealing membrane, coated internally with a phenol-epoxy lacquer. The tube is closed with a polypropylene screw cap, incorporating a point to pierce the aluminium sealing membrane before first use; or
- An aluminium laminated tube fitted with a high-density polyethylene shoulder and closed by a moulded seal. The tube is closed with a polypropylene screw cap, incorporating a moulded feature used to insert, twist and remove the seal before first use.
- An aluminium laminated tube fitted with a high-density polyethylene shoulder. The tube is closed with a snapped-on flip-top massage applicator made of polypropylene for the chassis and high-density polyethylene for the massage head. The flip-top cap has a polypropylene security tab located on one side of the cap.
Pack sizes:
VOLTAREN EMULGEL and VOLTAREN EMULGEL Back & Muscle Pain
30 g, 50 g, 100 g, and 150 g tubes.
VOLTAREN EMULGEL Joint Pain Regular Strength
120 g tubes.
VOLTAREN EMULGEL Active
75 g and 120 g.
7 Warnings and Precautions
General
Diclofenac diethylamine gel 1.16% w/w is for topical use only and should be applied only to intact, non-diseased skin and not to skin wounds or open injuries. It should not be used with occlusion. It should not be allowed to come into contact with the eyes, or mucous membranes, and should never be taken by mouth.
VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active contain propylene glycol and
| (1.16% w/w) | benzoate), isopropyl alcohol, liquid paraffin, macrogol cetostearyl ether, propylene glycol, purified water. |
fragrance (containing benzyl benzoate), which may cause mild, localized skin irritation in some people. For a complete list of the non-medicinal ingredients see 6 Dosage Forms, Strengths, Composition and Packaging.
Discontinue the treatment if a skin rash develops after applying the product.
VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength, VOLTAREN EMULGEL Active can be used with non-occlusive bandages but should not be used with an airtight occlusive dressing.
Patients should be instructed to be cautious when smoking or near open flames due to risk of severe burns. VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active contain paraffin which is potentially flammable when it builds up on fabric (clothing, bedding, dressings etc.). Washing clothing and bedding may reduce product build up but not totally remove it.
Systemic availability of diclofenac diethylamine through percutaneous absorption is low compared with plasma levels obtained following ingestion of oral forms of diclofenac. Nevertheless, the possibility of systemic side effects cannot be completely excluded. Chances of this may be increased where Diclofenac diethylamine gel 1.16% w/w is applied to a relatively large area of skin and/or over an extended period of time (e.g., especially if this goes beyond the maximum duration recommended for use).
Gastrointestinal
Some possibility of gastro-intestinal bleeding in patients with a significant history of peptic ulceration has been reported in isolated cases in users of diclofenac diethylamine gel. Diclofenac diethylamine gel 1.16% w/w should therefore be used with caution by patients under medication for active peptic ulcers in the stomach or duodenum (e.g., proton pump inhibitors or histamine H2 receptor antagonists). If the patient is uncertain, they should be advised to consult their doctor or pharmacist.
Monitoring and Laboratory Tests
No monitoring parameters or laboratory tests are required to monitor response to therapy or possible adverse reactions.
Respiratory
Like other drugs that inhibit prostaglandin synthetase activity, diclofenac and other NSAIDs can precipitate bronchospasm if administered to patients suffering from or with a previous history of bronchial asthma.
Asthma has been rarely reported in patients using topical NSAID preparations.
Skin
Local irritation, erythema, pruritus or dermatitis may occasionally occur with topical diclofenac diethylamine. Skin photosensitivity, desquamation, discoloration and bullous or vesicular eruptions have been reported in isolated cases. Patients should be warned against excessive exposure to sunlight in order to reduce the incidence of photosensitivity.
The following side effects have been observed with oral forms of diclofenac sodium.
Cardiac and vascular disorders
Uncommon: myocardial infarction, cardiac failure, palpitations, angina, arrhythmias, chest pain.
Very Rare: hypertension, vasculitis.
Ear and labyrinth disorders
Common: vertigo.
Very rare: hearing impaired, tinnitus.
Eye disorders
Very rare: visual impairment (blurred vision, diplopia).
Gastrointestinal disorders
Very common: nausea, vomiting, diarrhea, dyspepsia, abdominal pain, flatulence, decreased appetite.
Uncommon: gastritis, gastrointestinal hemorrhage, hemorrhagic diarrhea, melena, hematemesis, gastric and intestinal ulcerations (with or without bleeding or perforation).
Very rare: lower gut disorders (including haemorrhagic colitis and exacerbations of ulcerative colitis or Crohn's disease), intestinal diaphragm disease, hyperacidity, stomatitis, glossitis, coated tongue, oesophageal lesions, constipation, pancreatitis.
Haematologic
Very rare: thrombocytopenia, leucopenia, agranulocytosis, haemolytic anaemia, aplastic anaemia, anemia secondary to gastrointestinal bleeding.
Hepatic
Common: elevations (> 3 times the upper normal limit) of serum aminotransferase enzymes (SGPT or ALT, SGOT or AST).
Uncommon: liver function disorders including hepatitis, hepatic necrosis, hepatic failure, jaundice.
Very rare: hepatitis fulminant.
Immune system disorders
Uncommon: hypersensitivity anaphylactic / anaphylactoid systemic reactions (including hypotension and shock).
Very rare: angioedema (including face edema).
Nervous system disorders
Common: dizziness, headache.
Uncommon: somnolence, malaise, impaired concentration, tiredness.
Very rare: sensory disturbances including paraesthesia, memory impairment, convulsions, anxiety, tremor, aseptic meningitis, cerebrovascular accident (including transient ischemic attack, cerebral hemorrhage), dysgeusia.
Psychiatric disorders
Very rare: disorientation, depression, insomnia, nightmare, irritability, psychotic disorder.
Renal and urinary disorders
Uncommon: edema (facial, general, peripheral).
Very rare: acute kidney injury (acute renal failure), nephrotic syndrome, urinary abnormalities (e.g. haematuria and proteinuria), tubulointerstitial nephritis, renal papillary necrosis.
Respiratory disorders
Uncommon: asthma (including dyspnea).
Very rare: pneumonitis.
Skin and subcutaneous disorders
Common: rash, pruritus.
Uncommon: urticaria.
Very rare: bullous dermatitis, erythema, eczema, erythema multiforme, Stevens-Johnson syndrome, Lyell syndrome (toxic epidermal necrolysis), erythroderma (exfoliative dermatitis), alopecia, photosensitivity reactions, purpura, Henoch-Schonlein purpura.
7.1. Special Populations
7.1.1 Pregnancy
Since no experience has been acquired with diclofenac diethylamine gel in pregnancy, it is not recommended for use in these circumstances.
It is contraindicated during the last trimester of pregnancy, owing to the possibility of uterine inertia, fetal renal impairment with subsequent oligohydramnios and/or premature closure of the ductus arteriosus.
Animal data has shown an increased incidence of dystonia and delayed parturition when drug administration is continued into late pregnancy.
If diclofenac is used by a woman attempting to conceive, or during the first and second trimester of pregnancy, the dose should be kept as low and duration of treatment as short as possible and consult your doctor.
7.1.2 Breastfeeding
It is not known whether topical diclofenac is excreted in breast milk. However, studies in animals detected diclofenac in milk after oral administration. Precaution should be exercised because many drugs are excreted in human milk.
Diclofenac should only be used during lactation if the expected benefit justifies the potential risk to the newborn. If there are compelling reasons for using it, it should not be applied to the breasts nor should it be used at a higher dosage or for a longer period of time than recommended. Nursing women should consult their doctor before using the product.
7.1.3 Pediatrics
Pediatrics (< 16 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
No specific hazards are associated with geriatric use of diclofenac diethylamine 1.16% w/w gel.
8 Adverse Reactions
8.1. Adverse Reaction Overview
The adverse event incidence in the clinical studies was very low. The benign safety profile documented in the clinical studies is confirmed in the post-marketing experience in millions of patients worldwide. The adverse events occurring in studies were usually either moderate or mild. Serious adverse events observed in all the studies, conducted over more than a decade, were very few in number and all unrelated to study treatment.
In post-marketing surveillance, approximately 90% of case reports are non-serious. Cutaneous adverse events, occurring mostly at the application site, constitute the most common symptoms reported. Serious adverse events associated with oral forms of diclofenac, including gastrointestinal bleeding, have been reported occasionally. No causal relationship has been established between diclofenac diethylamine gel and these systemic adverse events.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The clinical data set includes data obtained in approximately 4926 patients with either the target indication of soft-tissue injuries (e.g. sprains, strains, bruises), osteoarthritis or soft-tissue rheumatism, 2728 of whom received VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w), 1267 of whom received an active comparator, and 931 of whom received placebo. Patients were treated from 3-28 days as befitted the nature of the conditions under study.
Data from the safety population with the target indication investigated, who received short term exposure to VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) in controlled trials and uncontrolled trials, confirm that a dose of 2-4 g of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) applied topically 3-4 times a day is safe and that the systemic adverse event profile observed for systemic NSAIDs is not seen with the topical formulation.
No subgroup analyses were performed. Long-term safety data from patients was not obtained in these studies as this is not relevant to a product intended for only short-term use up to 1 week.
The safety of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) was demonstrated in the safety population in clinical trials, which all showed that the incidence and type of rare or serious events resembles those of active controls or placebo.
The adverse events (AEs) whether or not drug related reported in 33 clinical trials are summarized in Table 1 (WHO-ART coding).
| Table 1 - Adverse events (AEs) Reported in Clinical Trials (WHO-ART coding) with a Frequency of ≥1% | ||||||
VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) n= 2258 (100) | <placebo> n= 633 (100) | Reference* n= 1112 (100) | ||||
| Local skin AEs | 76 (3.4) | 35 (5.5) | 29 (2.6) | |||
*Topical reference drugs (number of patients): felbinac (195), piroxicam (306), etofenamate (140), Mobilat containing adrenocortical extract, mucopolysaccharide, salicylic acid (113), Movelat containing mucopolysaccharide polysulphate, salicylic acid (78), ketoprofen (15), naproxen (15), benzydamine HCl (52), indomethacin (55), Dolobene containing dimethylsulfoxid heparin (39), monosalicylic acid (15-20). * Oral reference drug: ibuprofen (155) | ||||||
Similar percentages of local skin reactions including mostly itching, burning, erythema, local allergy and blistering were reported after VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) (3.4%) and placebo (5.5%). Most of the local AEs were mild to moderate. There were no reports of photosensitivity, although one case report referred to exposure to the sun. Approximately 0.3% of patients were withdrawn due to local skin AEs after applying VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) or placebo.
In conclusion, the absolute numbers of reported adverse events were relatively small and there are no clinically significant differences in the incidence of adverse events in the VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) placebo and reference drug treatment groups. Most of the AEs are local, mild to moderate and reversible.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
No clinical efficacy and safety pediatric studies have been conducted for VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w).
8.3. Less Common Clinical Trial Adverse Reactions
WHO-ART-coded clinical trials
Digestive: Dyspepsia was observed in 0.58, 0.32, and 0.18% of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) Placebo, and Reference groups, respectively.
Body as a whole: Allergic events were observed in 0.04, 0.16, and 0.09% of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w), Placebo, and Reference groups, respectively.
CNS: CNS events were observed in 0.09, 0.32, and 0.45% of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w), Placebo, and Reference groups, respectively.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical laboratory evaluations were not routinely performed in the studies undertaken for the indication of muscle and joint soft tissue injuries. The treatments were given for short periods only.
8.5. Post-Market Adverse Reactions
List of adverse reactions
The list includes adverse reactions from the clinical trials as well as from the post-marketing experience where causal relationship has been established.
Adverse reactions are listed below, by system organ class and frequency. Frequencies are defined as: very common (≥ 1/10); common (≥ 1/100 to < 1/10); uncommon (≥ 1/1,000 to <1/100); rare (≥ 1/10,000 to < 1/1,000); very rare (< 1/10,000). Within each frequency grouping, undesirable effects are presented in order of decreasing seriousness.
Infections and infestations
Very rare: Rash pustular.
Immune system disorders
Very rare: Hypersensitivity (including urticaria), angioedema.
Respiratory, thoracic and mediastinal disorders
Very rare: Asthma.
Skin and subcutaneous tissue disorders
Common: Dermatitis (including contact dermatitis), rash, erythema, eczema, pruritus.
Rare: Dermatitis bullous.
Very rare: Photosensitivity reaction.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorization of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product.
Healthcare professionals are asked to report any suspected adverse reactions via the Canada Vigilance Program.
9 Drug Interactions
9.2. Drug Interactions Overview
No drug and substance interaction studies have been performed as part of the clinical development of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w).
From the pharmacokinetic point of view, diclofenac is extensively (>99.7%) protein bound, mainly to albumin (99.4%). Binding to serum albumin is characterised by 2 classes of binding sites: the high affinity sites are likely to be shared with benzodiazepines and the low affinity site with warfarin. Diclofenac does not modify other strongly protein bound drugs but may, in vitro, be displaced by salicylic acid.
There is a considerable body of literature regarding interactions of oral NSAIDs, and diclofenac in particular, with other medicinal products. No interactions with other drugs are to be expected due to very low plasma levels observed after topical application of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w).
9.4. Drug-Drug Interactions
No drug-drug interactions were noted in the clinical studies presented. Isolated interaction cases have been reported for topical diclofenac diethylamine gel from the marketplace.
Eighty-six worldwide cases of possible drug interactions with diclofenac diethylamine gel over more than 4 billion patients treatment courses have been entered to the company world-wide safety database since first marketing:
In 64 cases, a possible interaction between diclofenac diethylamine gel and only one other interacting drug was reported:
- Twenty cases with other anti-inflammatory medications (diclofenac, ibuprofen, acetylsalicylic acid, naproxen, piroxicam, celecoxib, and an unknown anti-inflammatory medication); clinical adverse events reported were e.g. pain, arthralgia, somnolence, gastrointestinal haemorrhage, gastric ulcer, haemorrhoids, diarrhoea, renal failure, hypertension, tachycardia, rash).
Twenty-four cases with oral anticoagulant therapy (acenocoumarol, warfarin, phenprocoumon, fluindione, clopidogrel, and an unknown anticoagulant); only 2 cases did not report any clinical adverse event. The most frequently reported clinical adverse events were haemorrhages (in five cases, e.g. gastrointestinal haemorrhage, epistaxis,
- gingival bleeding) and international normalized ratio increased (6 cases). Other adverse events reported included renal failure, prothrombin level decreased.
- Six cases with anti-hypertensives (with an unknown anti-hypertensive, candesartan, losartan, lisinopril, captopril, valsartan; clinical adverse events reported were e.g. blood pressure increased, acute kidney injury).
- Three cases of psychiatric disorders (3 cases of confusional state with rivastigmine).
- Five cases with unspecified medications (with clinical adverse events such as dermatitis allergic, skin irritation, renal disorder).
- Two cases of gastrointestinal haemorrhage associated with fluoxetine.
- One case of headache associated with pantoprazole.
- One case of toxicity to lithium associated with lithium.
- One case of erythema and urticaria associated with heat therapy.
- One case of renal disorder associated with torasemide.
In the remaining twenty-two cases, there were more than one possibly interacting medication, with no particular drugs and adverse events pattern identified.
The customary drug-drug interactions between oral NSAIDs and anticoagulants, oral antidiabetic agents and certain other classes are usually based on the high protein-binding nature of the NSAID. With significantly lower amounts of active substance in circulation following topical application compared with after oral administration, such interactions may be predicted to be very unlikely with use of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w).
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1. Mechanism of Action
Diclofenac is a well characterized, potent nonsteroidal anti-inflammatory drug (NSAID) with clinically proven anti-inflammatory, analgesic and antipyretic properties. NSAIDs, including diclofenac, reduce pain principally by inhibiting formation of prostaglandins, leukotrienes and free oxygen radicals.
All non-salicylate NSAIDs reversibly block cyclooxygenase activity, which is responsible for converting arachidonic acid to prostaglandins. Diclofenac is a potent, non-selective inhibitor of COX-1 and COX-2 (preferentially COX-2), which may underlie both its therapeutic efficacy and potential side effects. In addition, diclofenac, when compared to NSAIDs such as ibuprofen, also blocks the lipoxygenase pathway of the arachidonic acid cascade, thereby inhibiting the formation of leukotriene B4 (LTB4), which is a known pain mediator and has been shown to stimulate pain receptors in the peripheral nerves. The inhibition of lipoxygenase also prevents the pro-inflammatory and gastrointestinal damaging effects of leukotrienes. Prostaglandins, along with thromboxanes and LTB4, are responsible for several inflammatory effects. The lipoxygenase inhibition produced by diclofenac may therefore play a significant role in its efficacy as an analgesic and anti-inflammatory agent.
Systemic absorption of diclofenac following topical application of diclofenac diethylamine gel is about 6% of the administered dose and the peak plasma levels attained are 50 times (repeated doses) to 100 times (single dose) lower than those observed after an oral dose. Supportive of efficacy is adequate tissue concentrations of diclofenac in the targeted area after topical application. Overall, diclofenac diethylamine gel can be expected to produce a direct anti-inflammatory and analgesic effect with significantly less AEs than after the oral administration of diclofenac.
10.2. Pharmacodynamics
Pharmacotherapeutic group: Topical products for joint and muscular pain. Anti- inflammatory preparations, non-steroids for topical use, ATC code: M02A A15.
As with other NSAIDs, the ability of diclofenac to inhibit prostaglandin synthesis is instrumental in the anti-inflammatory response. Data from in vitro studies show that most topical NSAIDs are able to inhibit prostaglandin synthesis to a significant degree. In this respect, diclofenac has a high intrinsic activity, as demonstrated in vitro in human rheumatoid synovial microsomes.
Prostaglandins, along with thromboxanes and leukotriene B4 (LTB4), are responsible for several inflammatory effects such as vasodilatation, increased vascular permeability, hyperalgesia and increased platelet aggregation. Free oxygen radicals, also mediators of inflammation, are by-products of prostaglandin synthesis. Diclofenac non-specifically inhibits the cyclo-oxygenase pathway with a subsequent reduction in prostaglandin, prostacyclin and thromboxane production. Although nonspecific, diclofenac inhibits preferentially COX-2 pathway. The production of leukotrienes is also decreased following the administration of diclofenac, suggesting an inhibitory effect on the lipoxygenase pathway with direct impact on LTB4 and inhibition of pain.
Pharmacodynamics studies - analgesic activity
Interestingly, diclofenac also blocks the lipoxygenase pathway of the arachidonic cascade, thereby inhibiting the formation of LTB4 which is known to be a pain mediator stimulating the pain receptors in the peripheral sensory nerves. Inhibition of lipoxygenase also decreases the formation of the slow-reacting substance of anaphylaxis (composed of leukotriene C4, D4 and E4).
In animals, using the Randall and Sellito's test, VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) has been shown to increase the pain threshold after a single subcutaneous injection of yeast suspension.
The pharmacodynamic properties of diclofenac have been demonstrated for each of the sodium, potassium and diethylamine salts administered either orally or topically in standard animal models of acute and chronic inflammation.
It has also been reported that topically applied diclofenac diethylamine 1.16% actively inhibited methyl nicotinate induced skin inflammation, which is known to involve prostaglandins and free arachidonic acid. Topical diclofenac was shown to exhibit a prolonged potent anti-inflammatory effect, even 48 hours after application.
The anti-inflammatory properties of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) were demonstrated in two placebo-controlled, double-blind, randomized trials (refer to Table 2), one in healthy volunteers using the urate crystal induced inflammation model (NGB5) and the other in patients with chronic synovitis of the knee (NGB 8855). VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) proved to be superior to placebo in significantly reducing the diameter of erythema at 24 hours in study NGB 5 (p<0.05), and significantly reducing the thermal index in study NGB 8855 (p<0.04). Due to the small size of the studies, only objective parameters of erythema and thermal index could be evidenced.
| Table 2 - Summary of Studies NGB 5 and NGB 8855 | ||||||||
Study Investigator Country | Regimen Design Comparator | Condition | Population | Criteria | Efficacy | |||
| NGB 5 P.A. Dieppe UK | 5 applications in 48 hours (every 12 hr) DB, CO Placebo | Urate crystal induced inflammation Model | Total: 19 (healthy volunteers) Age range: 18-50 years | Lesion diameter, tenderness, intensity of erythema, subject and investigator preference. | VE vs. Placebo: significantly reduced erythema diameter at 24 hours. Investigator’s and volunteer’s preference at 48 hours (p<0.05). | |||
| NGB 8855 B. Hazelman UK | 3/day up to 7 days DB, CO Placebo | Mild to moderate chronic synovitis of knee | Total: 13 Male: 38% Mean age: 55 years Age range: 13-82 years | Thermal index, tenderness, pain on passive movement, swelling, rescue medication. | VE vs. Placebo: reduced thermal index (p<0.04). | |||
The potency of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) was compared with that of five other topical NSAIDs (indomethacin, ibuprofen, phenylbutazone, bufexamac and niflumic acid) and three topical corticosteroids (clobetasol, hydrocortisone and hydrocortisone butyrate) in healthy volunteers. Four hours after a single application of each drug to the forearm, inhibition of methyl-nicotinate induced inflammation was greatest with VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) and indomethacin cream (84% and 85%, respectively, relative to a control vehicle). VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) demonstrated the most sustained anti-inflammatory effect, providing 75% inhibition when re-tested 48 hours after application.
10.3. Pharmacokinetics
Evidence in humans and animals with topical NSAIDs, including diclofenac, demonstrates lower plasma concentrations than with systemically administered NSAIDs, while drug concentrations in the soft tissues around the area of application are still of a magnitude considered sufficient to exert an anti-inflammatory response.
Percutaneous Absorption, Distribution, Metabolism, Excretion
Absorption: Absorption of various NSAIDs, including diclofenac, occurs to a depth of at least 3-4 mm through the underlying dermis and subcutaneous tissue. At that level, uptake of drug from the dermal microcirculation into the systemic circulation occurs but the concentration of drug in these layers is always higher than the plasma concentration. Although only a small proportion of the dose is absorbed, the skin acts as reservoir from which there is a sustained release of drug into underlying tissues.
The quantity of diclofenac absorbed through the skin is proportional to the size of the treated area, and depends on both the total dose applied and the degree of skin hydration. Following topical application of a typical dose, 2.5 g VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) on 500 cm² skin, absorption amounts to about 6% of the applied dose of diclofenac after topical application of 2.5 g VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) on 500 cm² skin, determined by the total renal elimination, compared with Voltaren tablets. A 10-hour occlusion leads to a 3-fold increase in the amount of diclofenac absorbed.
Distribution: Diclofenac concentrations have been measured from plasma, synovial tissue and synovial fluid after topical administration of diclofenac diethylamine gel to hand and knee joints. Maximum plasma concentrations are approximately 100 times lower than after oral administration of the same quantity of diclofenac. 99.7% of diclofenac is bound to serum proteins, mainly albumin (99.4%).
Diclofenac accumulates in the skin which acts as reservoir from where there is a sustained release of drug into underlying tissues. From the skin and underlying tissue, diclofenac preferentially distributes and persists in deep inflamed tissues (such as the joint), rather than in the bloodstream. Diclofenac is found in tissues at concentrations up to 20 times higher than in plasma.
Metabolism: Biotransformation of diclofenac involves partly glucuronidation of the intact molecule, and mainly single and multiple hydroxylations, most of which are converted to glucuronide conjugates (hydroxyl-gluconates). The main metabolite is 4-hydroxy-diclofenac (30%-40%). All the metabolites are biologically active, but to a much smaller extent than diclofenac.
Elimination: The total systemic clearance of diclofenac from plasma is 263 ± 56 ml/min. The terminal plasma half-life is 1-2 hours. Four of the metabolites, including the two active ones, also have short plasma half-lives of 1-3 hours. One metabolite, 3'-hydroxy-4'-methoxy-diclofenac, has a longer half-life but is virtually inactive. Diclofenac and its metabolites are excreted mainly in the urine.
A recent multiple-dose, 7 day PK study (VOPO-PE-102) was conducted with VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) and VOLTAREN EMULGEL Extra Strength
(diclofenac diethylamine gel 2.32% w/w). On day 1, mean diclofenac plasma concentrations from the two topical treatments did not exceed the LLOQ (0.5 ng/mL) until at least 14 hours after the first dose, and steadily increased to 2-3 ng/ml after 24 hours. The reservoir function is important during the first day after application where the concentration of diclofenac in the stratum corneum is highest.
Mean trough values were similar over days 5 through 7, indicating that steady state was reached by Day 5 with mean diclofenac plasma concentrations of roughly 3 ng/ml. On Day 7, the mean plasma concentrations were low and the peak-to-trough fluctuation was modest. In contrast, after oral dosing, Day 7 mean plasma concentrations increased sharply and returned approximately to pre-dose levels within the 6-hour dose interval.
The data can be described by a linear one-compartment model with the absorption as the rate limiting factor, (i.e. flip-flop kinetics when absorption is considerably slower than disposition) which is often seen with topical formulations due to the persistence of the compound in the skin reservoir.
The concentration of the drug is higher in the dermis and subcutaneous tissue below the application site than at greater depths where the drug concentration becomes less than the corresponding plasma concentration. Thus, anti-inflammatory effects at deeper tissue levels may be influenced by both direct and systemic drug concentrations.
Systemic absorption amounts to approximately 3-7% of the dose of diclofenac after topical application of 2.5g VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) per 500 cm2 skin, left for 12 hours on non-occluded skin. Plasma drug concentrations are well below those observed after a standard oral or intramuscular dose and below the range at which systemic AEs usually occur. Maximum plasma concentrations of diclofenac after topical administration of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) are between 50 (repeated dose) and 100 (single dose) times lower than after oral administration of VOLTAREN tablets. The steady state is reached after 2 days of twice-daily administration and the low plasma levels remain in the same range over the full day indicating prolonged absorption from the application site. Absorption of diclofenac through the skin can be increased by 3-10 times after application of an occlusive dressing.
Diclofenac in target tissues
After topical administration of diclofenac diethylamine gel to hand and knee joints in patients, diclofenac can be measured in the synovial tissue and synovial fluid with concentrations as high as 20 times the plasma concentration. In study C.R.B. R8/1986 plasma concentrations of diclofenac recorded on the fourth day in 7 patients ranged from 6 to 52 ng/ml with one extreme value of 698 ng/ml. In synovial fluid, the concentrations of diclofenac ranged from 119 to larger than 3320 ng/ml and in synovial tissue ranged from 131 to 1740 ng/ml. In the other patient study T13/1987 diclofenac could not be detected in plasma samples. In synovial fluid from knee joints the diclofenac concentrations were in the range of 6.5-22.1 ng/g sample. These patient studies confirm that topically applied diclofenac will reach the target tissues (soft tissue/joint) at sufficient concentrations to exert a therapeutic response.
Special Populations and Conditions
There are no gender differences in the pharmacokinetics of diclofenac. No safety or efficacy concerns relating to ethnicity have been identified from the marketplace. Publications have discussed the influence of age on diclofenac pharmacokinetics with relevance in the very young and elderly. Also, changes to the skin in the elderly will affect absorption in some patients. However, as plasma levels will be very low after topical application these factors are not a clinical concern. For similar reasons, any effect of hepatic or renal impairment on the pharmacokinetics of diclofenac is unlikely to be clinically significant. In patients with chronic hepatitis or non-decompensated cirrhosis, the kinetics and metabolism of diclofenac are the same as in patients without liver disease.
11 Storage, Stability, and Disposal
VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active (diclofenac diethylamine gel 1.16% w/w) should be stored between 15°C and 30°C.
12 Special Handling Instructions
There are no special handling instructions for VOLTAREN EMULGEL, VOLTAREN EMULGEL Back & Muscle Pain, VOLTAREN EMULGEL Joint Pain Regular Strength and VOLTAREN EMULGEL Active.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Proper name: Diclofenac diethylamine
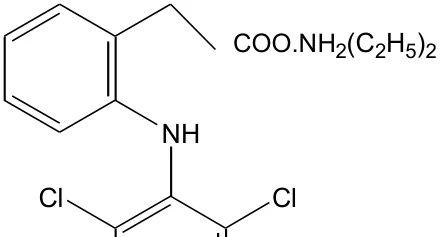
Chemical name: Diethylammonium{o-[(2,6-dichlorophenyl)-amino]-phenyl} acetate
Molecular formula and molecular mass: C18H22Cl2N2O2, 369.3
Structural formula:
Physicochemical properties: Diclofenac diethylamine is a white to light beige crystalline powder. No polymorphic forms of diclofenac diethylamine have been observed. The solubility of diclofenac diethylamine in water is 15.8 g/L at a pH of 7.8 and a temperature of 18°C, 17.4 g/L at a pH of 7.6 and a temperature of 25°C, and 22.8 g/L at a pH of 7.6 and a temperature of 37°C. Diclofenac diethylamine has a pH range of 6.5-8.3 in a 1% solution in 10% ethanol. Diclofenac diethylamine has a pKa value of 3.9 ± 0.2 in water at 25°C.
14 Clinical Trials
14.1. Clinical Trials by Indication
For the indication “pain in muscles and joints injuries”, the studies NF 113 and D458 L7/D141 are considered pivotal. Study demographics and trial design for these studies are presented in Table 3.
| Table 3 - Summary of patient demographics for clinical trials in muscle and joint injuries | |||||
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Sex |
| NF113 | Multicentre, parallel-group, randomised, double-blind, placebo-controlled Subjects had soft tissue trauma resulting in a minor sprain, dislocation, tear of muscle or tendon, or pulled muscle/contusion | VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) or placebo gel was applied topically 4 times daily at a mean dose of 2.2 g (actual dose was determined by physician) | n=254 | VOLTAREN: 34.1 (7-88) Placebo: 35.5 (12-84) | Men VOLTAREN: 72 (57%) Placebo: 83 (65%) Women VOLTAREN: 54 (43%) Placebo: 45 (35%) |
| D458 L7/D141 | Single-centre parallel-group, randomised double-blind, placebo-controlled Subjects were soldiers with acutely sprained ankles | VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) or placebo gel was applied 3 times daily for up to 14 days | n= 80 | VOLTAREN: 22.4 (19-29) Placebo: 22.2 (19-31) | All 80 subjects were male |
Soft tissue trauma
Study NF113
There was a significant difference in favour of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) for spontaneous pain on deliberate movement on day 7 with 44% (51) of the active treatment group having no pain, 43% (50) having only moderate pain and 13% (15) marked pain compared with 35% (41), 38% (44) and 24% (28) of the subjects in the placebo group respectively. Three (3) subjects (3%) of the placebo group had very marked pain at 7 days whereas no active treatment subject had marked pain (p=0.05 for day 7 evaluation) and similar results were found for pain on pressing, also on day 7 (p=0.02). The need for rescue medication was lower in the active treatment group, and of significantly shorter duration i.e., those in the active treatment group stopped using rescue medication before those receiving placebo (p=0.02). The regression of haematoma was also faster in the active treatment group (p=0.04). These data concur with the investigator’s general assessments rating the results on day 7 as ‘excellent’ in 64% of patients receiving active treatment and 52% in those receiving placebo.
Study D458 L7/D141
There was a significant difference for articular pain at rest and on movement (100 mm VAS) and joint swelling at days 3 and 4 in the VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) treated group compared to the placebo group (p<0.001). (The mean pain at rest
(mornings) fell from 61.15 on the VAS to 24.13 by day 4 for the active treatment group compared to a fall from 53.33 at baseline to 29.71 on day 4 for the placebo treated group- p<0.001.) Patients withdrew as they got better and so by the 7th day, only those who had not yet healed still remained in the study. At this point there was no difference between active and placebo for joint swelling. Similar numbers of patients in each group required rescue analgesia. 60% of actively treated patients were able to stop using the gel before the 14th day as they were free of symptoms compared with 38% of the placebo group. Interruptions for inadequate efficacy occurred in the placebo group only (2 subjects). During the first 10 days of treatment, nearly twice as many active treatment patients became free of symptoms than the placebo treated group (n=17 and n=8 respectively, p value not given in final study report). This gives an indication of the effect of treatment on the natural time course for pain relief.
14.2. Comparative Bioavailability Studies
Report 17727B-510.20-02-01-B describes a single and multiple dose (7 days), open, randomized, three-way cross-over, comparative bioavailability trial of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w), diclofenac enteric coated tablet and a diclofenac patch formulation that was in development in the Company, in 24 healthy volunteers. The main pharmacokinetic findings are summarized in Table 4.
Table 4 - Summary of pharmacokinetic data for Study NCH 17727B-510.20-02-01B
Parameter
Voltaren Emulgel (diclofenac diethylamine gel 1.16% w/w) 4g (40 mg diclofenac-Na equivalent) t.i.d
VOLTAREN tablet 25 mg t.i.d
After first administration (day 1)
Cmax (ng/ml)
5.36 (0.502 - 42.6)
370 (92.0 - 984)
tmax (h)
20.00 (10.00 - 23.95)
4.00 (1.00 - 18.00)
AUC0-24 (ng.h/ml)
43.6 (0.502 - 240)
1190 (231 - 3800)
After last morning administration (day 7)
Cmax (ng/ml)
12.0 (2.54 - 45.1)
380 (51.0 - 1330)
tmax (h)
18.00 (0.00 - 20.00)
4.00 (1.00 - 20.00)
AUC0-24 (ng.h/ml)
179 (51.8 - 332)
1360 (327 - 4690)
Cmin (ng/ml)
4.07 (1.19 - 8.06)
2.11 (<0.5 - 4.79)
PTF (%)
95.0 (36.2 - 313)
664 (360 - 1250)
tmax values are median (range), other values are geometric means (range); N=24 for patch and gel, N=23 for the tablet
As expected, these data demonstrate that the relative bioavailability of VOLTAREN EMULGEL (diclofenac diethylamine gel 1.16% w/w) versus tablets remained low (Cmax <2% and 3% and AUC 4% and 13% respectively) after first and last administration.
Diclofenac is extensively protein bound in plasma (>99.7%), mainly to albumin (99.4%). The liver is the primary site of metabolism for diclofenac to virtually inactive metabolites. The total systemic clearance of diclofenac from plasma is 263±56 ml/min (mean value ± SD). The terminal plasma half-life is 1 to 2 hours. Diclofenac and its metabolites are excreted mainly in urine (60%).
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General Toxicology: The toxicology of VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel (1.16% w/w) was investigated in a series of in vivo studies, including acute and three-month repeat dose toxicity, but concentrating particularly on potential local tolerance and photo-safety issues, as outlined in Table 5 below.
Table 5 - Diclofenac Diethylamine Toxicology Program
Study type and duration
Route of administration
Species
Compound administered
Single–dose toxicity
Topical, occluded
Rat
VOLTAREN EMULGEL 11.6 mg/g
Single–dose toxicity
Oral
Rat
(Diclofenac diethylamine gel (1.16% w/w)
Repeat-dose toxicity: 3 months
Topical, occluded
Rabbit
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
Local tolerance / photo-safety
Phototoxicity, single dose
Topical
Mouse
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
Phototoxicity, single dose
Topical
Guinea pig
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
Photo-allergenicity
Topical
Guinea pig
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
Skin sensitization
Topical, occluded
Guinea pig
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
Skin irritation, 5 days
Topical, occluded
Rabbit
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
Skin irritation, 5 days
Topical, occluded
Rabbit
VOLTAREN EMULGEL 11.6 mg/g
(Diclofenac diethylamine gel 1.16% w/w)
Eye irritation, single dose
Ocular
Rabbit
VOLTAREN EMULGEL 11.6 mg/g (Diclofenac diethylamine gel 1.16% w/w)
VOLTAREN EMULGEL (diclofenac diethylamine gel 11.6 mg/g / 1.16% w/w) gel was generally well tolerated. The acute toxicity of diclofenac diethylamine was essentially the same as that of diclofenac sodium when expressed in terms of the base. There was no evidence of any significant local irritancy, unexpected toxicity or of any photo-safety concerns.
There have been no other studies specifically designed to investigate toxicity of the drug substance, diclofenac diethylamine, or of the drug product, VOLTAREN EMULGEL (diclofenac diethylamine gel 11.6 mg/g/ 1.16% w/w). The non-clinical toxicology of diclofenac sodium is directly relevant to diclofenac diethylamine and is summarized below.
Single dose experiments in mice, rats, rabbits and dogs indicate an acute intravenous LD50 in the region of 100 mg/kg and an oral LD50 nearer 200 mg/kg with little evidence to suggest any significant influence of age or sex on the outcome. An oral study in baboons suggests significantly greater tolerance with a probable LD50 of more than 600 mg/kg. Death following intravenous administration was usually attributed to respiratory or cardiac failure, those following oral administration to gastrointestinal problems.
Repeat dose oral gavage studies of up to 6 months duration in rats indicate a no observed adverse effect level (NOAEL) of 1 to 2 mg/kg/day. A similar result was obtained in a one-month mouse study by dietary administration. At doses greater than 4 mg/kg/day, deaths were common and usually associated with mild anaemia, neutrophilia, disturbance of plasma proteins, increased extramedullary haematopoiesis and, most prominently, ulceration of the gastrointestinal tract with accompanying peritonitis. These latter were commonly associated with hypertrophy or reactive hyperplasia of the mesenteric lymph nodes.
In a series of baboon studies, similar changes were apparent with deaths consistently seen within 3 months of treatment at 20 mg/kg/day or more. In a 1-year study, 5 of 14 animals treated at 15 mg/kg/day had died by 8.5 months when this dosage was reduced to 10 mg/kg/day. Both constipation and diarrhoea were apparent and there was a high incidence of skin ulcers the severity of which was treatment-related. In both three-month studies, but not in the one-year study, there was evidence of nephropathy at the high dose with increased blood urea nitrogen and disturbance of plasma electrolytes in one study. In the one-year study only and at the high dose only (where 13 of 14 animals died despite a dosage reduction) adrenal cortical hyperplasia was noted in several animals. Other changes seen in baboons were essentially similar to those in rats and the deaths were all associated with gastrointestinal changes. Gastrointestinal changes were seen at the lowest dosages studied in baboons (around 3-5 mg/kg/day) but were generally considered to reflect an exacerbation of pre-existing conditions rather than a primary effect of treatment with diclofenac.
Carcinogenicity: One mouse and two rat carcinogenicity studies have been conducted. Exposure levels, as judged from plasma concentration data obtained during the more recent of these studies, were 12-45 ng/g in mice at the NOAEL (0.3 mg/kg/day) and 10-48 ng/ml in rats at the lowest dosage (0.25 mg/kg/day). In all 3 studies there was a dosage-related increase in mortality at 1 and 2 mg/kg/day with only isolated animals surviving at the high dose. Most deaths were associated with gastrointestinal ulceration and peritonitis. There were few changes that could be ascribed to treatment at lower dosages (0.1 to 0.5 mg/kg/day) and there was no treatment-related increase in the incidences of benign or malignant tumours in any of these studies.
Genotoxicity: The potential genetic toxicology of diclofenac sodium has been studied in a wide variety of in vitro and in vivo studies. Most of these studies were carried out many years ago and include:
- Ames tests of the drug, of urine and bile concentrates, and of the major hydroxy-metabolites of diclofenac.
- In vitro mammalian cell mutation studies of diclofenac sodium and its hydroxy-metabolites.
- In vivo chromosome aberration and nucleus anomaly tests in Chinese hamsters after both short-term treatment and repeated administration for 12 weeks.
- Metaphase analyses of spermatogonia and spermatocytes following five administrations.
- A dominant lethal study in mice.
None of these studies gave any indication of a positive outcome. Recently fully GLP compliant in vitro photo-mutagenicity and photo-chromosome aberration studies have been carried out. The photo-mutagenicity study (Ames test) was also negative. Chromosome aberrations were seen in the other study at 25 µg/ml and with 16 minutes of UV radiation. These conditions were associated with a reduced mitotic index and the apparently positive result is attributed to cytotoxicity. No chromosome aberrations were seen at lower doses of UV or at lower concentrations of diclofenac. An additional conventional in vivo GLP compliant chromosome aberration study has also been completed with diclofenac sodium and was also negative.
Reproductive and Developmental Toxicology: Reproduction toxicity has been assessed in a series of pre-ICH design studies, including Segment I and III studies in rats and a variety of Segment II studies in mice, rats and rabbits. Almost all studies included treatment at toxic dosages and death of the dams, usually attributed to peritonitis, was a common finding. Treatment with diclofenac sodium in the Segment I and III studies was generally associated with a slight increase in gestation and occasional dystocia resulting in increased peri-natal mortality. Even discounting this, there was usually an increase in embryo-foetal and/or perinatal losses. Birth weight was reduced. Foetal changes extended to the lowest dosage examined, 2 mg/kg/day, in both studies. Other than deaths associated with dystocia, post-natal survival was not affected.
In the Segment II studies in mice, there was no clear effect of treatment at 2 or 4 mg/kg/day when given orally, even when administered through days 0-17 of gestation. Reductions in foetal numbers and reduced ossification at higher dosages were associated with severe maternal toxicity. In oral rat studies a similar picture emerged. There were some minor contradictory findings at 4 mg/kg/day but none at 2 mg/kg/day and clear effects at higher dosages, including reduced ossification, that were attributed to maternal toxicity. An intramuscular study indicated no changes in the foetuses at 10 mg/kg/day, despite maternal sedation and local injection site responses. In a GLP compliant subcutaneous rat study, however, minimally reduced ossification was identified at 1.2 mg/kg/day; 0.4 mg/kg/day was a NOAEL. In an oral rabbit Segment II study, 5 mg/kg/day was a clear NOAEL, changes at 10 mg/kg/day included increased embryonic and foetal resorptions and reduced foetal ossification in three foetuses. An intramuscular rabbit study identified 3 mg/kg/day as the
NOAEL with increased abortions and dead foetuses, reduced number of fully formed foetuses and reduced ossification, and reduced foetal viability at higher dosages, associated with maternal toxicity.