


Product Monograph - Zolmitriptan-ODT
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, 1.1 Pediatrics | 01/2026 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics | 01/2026 |
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
- 1.
INDICATIONS ............................................................................................................................................ 4
1.1 Pediatrics ........................................................................................................................................... 4
1.2 Geriatrics ........................................................................................................................................... 4
- 2. CONTRAINDICATIONS ............................................................................................................................... 4
- 3. SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................................................... 5
- 4.
DOSAGE AND ADMINISTRATION .................................................................................................................... 5
4.1 Dosing Considerations ...................................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .................................................................................. 6
4.3 Administration ................................................................................................................................. 6
5 OVERDOSAGE ................................................................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................................................... 7
7 WARNINGS AND PRECAUTIONS ..................................................................................................................... 7
General .................................................................................................................................................... 7
Cardiovascular ......................................................................................................................................... 7
Dependence, Tolerance and/or Abuse Liability .................................................................................... 10
Driving and Operating Machinery ......................................................................................................... 11
Hepatic/Biliary/Pancreatic .................................................................................................................... 11
Immune ................................................................................................................................................. 11
Neurologic ............................................................................................................................................. 11
Ophthalmologic ..................................................................................................................................... 12
7.1 Special Populations .......................................................................................................................... 12
7.1.1 Pregnant Women: ........................................................................................................................ 12
7.1.2 Breast-feeding .............................................................................................................................. 12
7.1.3 Pediatrics ...................................................................................................................................... 12
7.1.4 Geriatrics ...................................................................................................................................... 13
8 ADVERSE REACTIONS .................................................................................................................................... 13
8.1 Adverse Reaction Overview ............................................................................................................ 13
8.2 Clinical Trial Adverse Reactions ....................................................................................................... 14
8.2.1. Clinical Trial Adverse Reactions – Pediatrics ............................................................................... 17
8.3 Less Common Clinical Trial Adverse Reactions .............................................................................. 18
8.3.1 Less Common Clinical Trial Adverse Reactions - Pediatrics ......................................................... 19
8.5 Post-Market Adverse Reactions .................................................................................................... 19
9 DRUG INTERACTIONS ................................................................................................................................... 20
9.1 Serious Drug Interactions ................................................................................................................ 20
9.2 Drug Interactions Overview ............................................................................................................ 20
9.3 Drug-Behavioural Interactions ........................................................................................................ 21
9.4 Drug-Drug Interactions .................................................................................................................. 21
9.5 Drug-Food Interactions .................................................................................................................. 23
9.6 Drug-Herb Interactions ................................................................................................................... 23
9.7 Drug-Laboratory Test Interactions ................................................................................................. 23
10 CLINICAL PHARMACOLOGY ......................................................................................................................... 23
10.1 Mechanism of Action .................................................................................................................... 23
10.2 Pharmacodynamics ....................................................................................................................... 24
10.3 Pharmacokinetics .......................................................................................................................... 25
11 STORAGE, STABILITY AND DISPOSAL .......................................................................................................... 27
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................................................ 27
PART II: SCIENTIFIC INFORMATION ....................................................................................... 28
13 PHARMACEUTICAL INFORMATION ............................................................................................................. 28
14 CLINICAL TRIALS .......................................................................................................................................... 28
14.1 Clinical Trials by Indication ............................................................................................................ 28
14.2 Comparative Bioavailability Studies .............................................................................................. 31
15 MICROBIOLOGY ......................................................................................................................................... 31
16 NON-CLINICAL TOXICOLOGY ....................................................................................................................... 32
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................................................... 33
PATIENT MEDICATION INFORMATION .................................................................................. 34
PART I: HEALTH PROFESSIONAL INFORMATION
1. INDICATIONS
ZOLMITRIPTAN-ODT (zolmitriptan orally disintegrating tablets) is indicated for:
- The acute treatment of migraine attacks with or without aura, in adults.
ZOLMITRIPTAN-ODT is not intended for the prophylactic therapy of migraine or for use in the management of hemiplegic, basilar, or ophthalmoplegic migraine (see 2 CONTRAINDICATIONS). Safety and efficacy have not been established for cluster headache, which is present in an older, predominantly male population.
1.1 Pediatrics
Pediatrics (< 6 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for use in this pediatric population (see 7.1.3 Pediatrics).
Pediatrics (6 - 17 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of zolmitriptan in pediatric patients 6-17 years of age has not been established; therefore, Health Canada has not authorized an indication for use in this pediatric population (see 7.1.3 Pediatrics).
1.2 Geriatrics
The safety and efficacy of zolmitriptan in patients over 65 years has not been established and its use in this age group is not recommended ( see 7.1.4 Geriatrics).
2. CONTRAINDICATIONS
ZOLMITRIPTAN-ODT (zolmitriptan) is contraindicated:
- in patients with history, symptoms, or signs of ischemic cardiac, cerebrovascular or peripheral vascular syndromes, valvular heart disease or cardiac arrhythmias (especially tachycardias). In addition, patients with other significant underlying cardiovascular diseases (e.g., atherosclerotic disease, congenital heart disease) should not receive ZOLMITRIPTAN-ODT. Ischemic cardiac syndromes include, but are not restricted to, angina pectoris of any type (e.g., stable angina of effort and vasospastic forms of angina such as the Prinzmetal’s variant), all forms of myocardial infarction, and silent myocardial ischemia. Cerebrovascular syndromes include, but are not limited to, strokes of any type as well as transient ischemic attacks (TIAs). Peripheral vascular disease includes, but is not limited to, ischemic bowel disease, or Raynaud’s syndrome (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
- in patients with uncontrolled or severe hypertension, as ZOLMITRIPTAN-ODT can give rise to increases in blood pressure (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
- within 24 hours of treatment with another 5-HT1 agonist, or an ergotamine-containing or ergot-type medication like dihydroergotamine or methysergide (see 9.4 Drug-Drug Interactions).
- in patients with hemiplegic, basilar or ophthalmoplegic migraine.
- concurrent administration of MAO inhibitors or use of zolmitriptan within 2 weeks of discontinuation of MAO inhibitor therapy (see 9.4 Drug-Drug Interactions).
- in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- SERIOUS WARNINGS AND PRECAUTIONS BOX
4. DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- ZOLMITRIPTAN-ODT should only be used where a clear diagnosis of migraine has been established.
- ZOLMITRIPTAN-ODT is not indicated for prophylaxis of migraine.
- The recommended adult starting dose for ZOLMITRIPTAN-ODT is 2.5 mg. The maximum recommended single dose is 5 mg.
- If the headache returns, the dose may be repeated after 2 hours. A dose should not be repeated, regardless of dosage form, within 2 hours. A total cumulative dose of 10 mg should not be exceeded in any 24 hour period.
- Controlled trials have not established the effectiveness of a second dose, should the initial dose be ineffective.
Serious Warnings and Precautions
- Risk of Myocardial Ischemia and/or Myocardial Infarction: Serious adverse cardiac events, including acute myocardial infarction, have been reported to occur within a few hours of zolmitriptan administration. ZOLMITRIPTAN-ODT is contraindicated for use in patients who have documented ischemic or vasospastic coronary artery disease (see 2 CONTRAINDICATIONS). ZOLMITRIPTAN-ODT should not be given to patients who have risk factors for coronary artery disease (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
- Cardiac Arrythmias: Life-threatening disturbances of cardiac rhythm, including ventricular tachycardia and ventricular fibrillation leading to death have been reported within a few hours of zolmitriptan administration (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
- Angina Pectoris: ZOLMITRIPTAN-ODT may cause coronary artery vasospasm (Prinzmetal angina), even in patients without a history of coronary artery disease (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
- Cerebrovascular Events: Cerebral haemorrhage, subarachnoid haemorrhage, stroke, and other cerebrovascular events have been reported in patients treated with 5-HT1 agonists, and some have resulted in fatalities (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular)
- The safety of treating more than 3 migraine headaches with zolmitriptan in a one-month period has not been established.
- Patients with mild to moderate hypertension should be treated cautiously at the lowest effective dose. ZOLMITRIPTAN-ODT is contraindicated in patients with severe or uncontrolled hypertension (see 2 CONTRAINDICATIONS).
- Hepatic impairment reduces zolmitriptan clearance. Lower doses are recommended (see 4.2 Recommended Dose and Dosage Adjustment; 10.3 Pharmacokinetics).
- Patients taking cimetidine and other 1A2 inhibitors should not exceed a dose of 5 mg ZOLMITRIPTAN-ODT in any 24 hour period (see 9.4 Drug-Drug Interactions).
4.2 Recommended Dose and Dosage Adjustment
Adults (≥ 18 Years Of Age):
ZOLMITRIPTAN-ODT (Zolmitriptan Orally Disintegrating Tablets): The minimal effective single adult dose of ZOLMITRIPTAN-ODT is 1 mg. The recommended single dose is 2.5 mg. the ZOLMITRIPTAN-ODT 2.5 mg orally dispersible tablet cannot be broken in half to approximate a 1 mg dose.
Pediatrics (< 18 Years Of Age): Health Canada has not authorized an indication for pediatric use.
Geriatrics: The safety and efficacy of ZOLMITRIPTAN-ODT in patients 65 years of age and older has not been established and its use in this population is not recommended (see 7.1.4 Geriatrics).
Hepatic Insufficiency: Zolmitriptan is metabolized primarily in the liver. Patients with moderate to severe hepatic impairment have decreased clearance of zolmitriptan and significant elevation in blood pressure was observed in some patients. ZOLMITRIPTAN-ODT should be administered with caution to patients with moderate or severe hepatic impairment, using a dose lower than 2.5 mg. Total dose should not exceed 5 mg in 24 hours. Blood pressure monitoring is recommended (see 7 WARNINGS AND PRECAUTIONS - Hepatic/Biliary/Pancreatic; 10.3 Pharmacokinetics).
Renal Insufficiency: No dosage adjustment is required in patients with a creatinine clearance ≥15 mL/min. ZOLMITRIPTAN-ODT should not be used in patients with end-stage renal disease (CrCl <15 mL/min).
4.3 Administration
ZOLMITRIPTAN-ODT (zolmitriptan orally disintegrating tablets): The tablet should be placed on the tongue, where it will dissolve with the saliva. Water is not needed for the dispersible tablet
5 OVERDOSAGE
There is no experience with clinical overdose. Volunteers receiving single 50 mg oral doses of zolmitriptan commonly experienced sedation.
The elimination half-life of zolmitriptan is 2.5 - 3 hours (see 10.3 Pharmacokinetics), and therefore monitoring of patients after overdose with ZOLMITRIPTAN-ODT should continue for at least 15 hours or while symptoms or signs persist.
There is no specific antidote to zolmitriptan. In cases of severe intoxication, intensive care procedures are recommended, including establishing and maintaining a patent airway, ensuring adequate oxygenation and ventilation, and monitoring and support of the cardiovascular system.
It is unknown what effect hemodialysis or peritoneal dialysis has on the serum concentrations of zolmitriptan.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Formulation | Route of Administration | Dosage Form / Strength/ Composition | Non-Medicinal Ingredients |
|---|---|---|---|
| ZOLMITRIPTAN -ODT | Oral | Orally Disintegrating Tablets / 2.5 mg Zolmitriptan | Acesulfame Potassium, Amino Methacrylate Copolymer, Colloidal Silicon Dioxide, Crospovidone, Low-Substituted Hydroxypropyl Cellulose, Magnesium Aluminometasilicate, Magnesium Stearate, Mannitol, Peppermint Flavor, Sodium Lauryl Sulfate, Talc. |
Description
ZOLMITRIPTAN-ODT Tablets 2.5 mg are white, round shaped, flat face, beveled edge, debossed with ‘C’ on one side and ‘J’ on other side, having a characteristic flavor. Available in packs of 2 blister strips, each containing 3 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
ZOLMITRIPTAN-ODT (zolmitriptan) should only be used where a clear diagnosis of migraine has been established.
Cardiovascular
Risk of Myocardial Ischemia and/or Infarction and Other Adverse Cardiac Events:
Zolmitriptan has been associated with transient chest and/or neck pain and tightness which may resemble angina pectoris. Following the use of other 5-HT1 agonists, in rare cases these
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
symptoms have been identified as being the likely result of coronary vasospasm or myocardial ischemia. Rare cases of serious coronary events or arrhythmia have occurred following use of zolmitriptan. In very rare cases angina pectoris has been reported.
ZOLMITRIPTAN-ODT should not be given to patients who have documented ischemic or vasospastic coronary artery disease (see 2 CONTRAINDICATIONS). It is strongly recommended that ZOLMITRIPTAN-ODT not be given to patients in whom unrecognised coronary artery disease (CAD) is predicted by the presence of risk factors (e.g., hypertension, hypercholesterolemia, smoking, obesity, diabetes, strong family history of CAD, female who is surgically or physiologically postmenopausal, or male who is over 40 years of age) unless a cardiovascular evaluation provides satisfactory clinical evidence that the patient is reasonably free of coronary artery and ischemic myocardial disease or other significant underlying cardiovascular disease. The sensitivity of cardiac diagnostic procedures to detect cardiovascular disease or predisposition to coronary artery vasospasm is unknown. If, during the cardiovascular evaluation, the patient’s medical history or electrocardiographic investigations reveal findings indicative of or consistent with coronary artery vasospasm or myocardial ischemia, ZOLMITRIPTAN-ODT should not be administered (see 2 CONTRAINDICATIONS).
These evaluations, however, may not identify every patient who has cardiac disease, and in very rare cases, serious cardiac events, such as myocardial infarction or coronary ischemia have occurred in patients without evidence of underlying cardiovascular disease.
For patients with risk factors predictive of CAD who are considered to have a satisfactory cardiovascular evaluation, the first dose of ZOLMITRIPTAN-ODT should be administered in the setting of a physician’s office or similar medically staffed and equipped facility. Because cardiac ischemia can occur in the absence of clinical symptoms, consideration should be given to obtaining electrocardiograms in patients with risk factors during the interval immediately following ZOLMITRIPTAN-ODT administration on the first occasion of use. However, an absence of drug-induced cardiovascular effects on the occasion of the initial dose does not preclude the possibility of such effects occurring with subsequent administrations.
Intermittent long-term users of ZOLMITRIPTAN-ODT, who have or acquire risk factors predictive of CAD, as described above, should receive periodic interval cardiovascular evaluations over the course of treatment.
If symptoms consistent with angina occur after the use of ZOLMITRIPTAN-ODT, ECG evaluation should be carried out to look for ischemic changes.
The systematic approach described above is intended to reduce the likelihood that patients with unrecognized cardiovascular disease will be inadvertently exposed to ZOLMITRIPTAN-ODT.
As with other 5HT1B/1D agonists, atypical sensations over the precordium have been reported after the administration of zolmitriptan. Where such symptoms are thought to indicate ischemic heart disease, no further doses of zolmitriptan should be given and appropriate evaluation carried out.
Discomfort in the chest, neck, throat and jaw (including pain, pressure, heaviness and tightness) has been reported after administration of zolmitriptan. Because 5-HT1 agonists may cause coronary vasospasm, patients who experience signs or symptoms suggestive of angina following ZOLMITRIPTAN-ODT should be evaluated for the presence of CAD or a predisposition to variant angina before receiving additional doses, and should be monitored electrocardiographically if dosing is resumed and similar symptoms recur. Similarly, patients who experience other symptoms or signs suggestive of decreased arterial flow, such as ischemic bowel syndrome or Raynaud’s syndrome following ZOLMITRIPTAN-ODT administration should be evaluated for atherosclerosis or predisposition to vasospasm (see 2 CONTRAINDICATIONS).
Cardiac Events and Fatalities Associated with 5-HT1 agonists
As with other triptans, zolmitriptan may cause coronary artery vasospasm. Serious adverse cardiac events, including acute myocardial infarction, life-threatening disturbances of cardiac rhythm, and death have been reported within a few hours following the administration of other 5-HT1 agonists. Considering the extent of use of 5-HT1 agonists in patients with migraine, the incidence of these events is extremely low.
Patients with symptomatic Wolff-Parkinson-White syndrome or arrhythmias associated with other cardiac accessory conduction pathway disorders should not receive ZOLMITRIPTAN-ODT.
Pre-marketing Experience with Zolmitriptan
Among the more than 2,500 patients with migraine who participated in premarketing controlled clinical trials of zolmitriptan conventional tablets, no deaths or serious cardiac events were reported.
Post-marketing Experience with zolmitriptan
Serious cardiovascular events have been reported in association with the use of zolmitriptan. The uncontrolled nature of post-marketing surveillance, however, makes it impossible to determine definitively the proportion of reported cases that were actually caused by zolmitriptan or to reliably assess causation in individual cases.
Cerebrovascular Events and Fatalities With 5-HT1 Agonists
Migraineurs may be at risk of certain cerebrovascular events. Cerebral haemorrhage, subarachnoid haemorrhage, stroke, and other cerebrovascular events have been reported in patients treated with 5-HT1 agonists, and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the agonist having been administered in the incorrect belief that the symptoms were a consequence of migraine, when they were not. Before treating migraine headaches with ZOLMITRIPTAN-ODT in patients not previously diagnosed as migraineurs, and in migraineurs who present with atypical symptoms, care should be taken to exclude other potentially serious neurological conditions. If a patient does not respond to the first dose, the opportunity should be taken to review the diagnosis before a second dose is given. It should be noted that patients with migraine may be at increased risk of certain cerebrovascular events (e.g., stroke, haemorrhage, TIA).
Special Cardiovascular Pharmacology Studies With Another 5-HT1 Agonist
In subjects (n=10) with suspected coronary artery disease undergoing angiography, a 5-HT1 agonist at a subcutaneous dose of 1.5 mg produced an 8% increase in aortic blood pressure, an 18% increase in pulmonary artery blood pressure, and an 8% increase in systemic vascular resistance. In addition, mild chest pain or tightness was reported by four subjects. Clinically significant increases in blood pressure were experienced by three of the subjects (two of whom also had chest pain/discomfort). Diagnostic angiogram results revealed that 9 subjects had normal coronary arteries and 1 had insignificant coronary artery disease.
In an additional study with this same drug, migraine patients (n=35) free of cardiovascular disease were subjected to assessments of myocardial perfusion by positron emission tomography while receiving a subcutaneous 1.5 mg dose in the absence of a migraine attack. Reduced coronary vasodilatory reserve (~10%), increased coronary resistance (~20%), and decreased hyperaemic myocardial blood flow (~10%) were noted. The relevance of these findings to the use of the recommended oral dose of this 5-HT1 agonist is not known.
Similar studies have not been done with zolmitriptan. However, owing to the common pharmacodynamic actions of 5-HT1 agonists, the possibility of cardiovascular effects of the nature described above should be considered for any agent of this pharmacological class.
- Other Vasospasm-Related Events: 5-HT1 agonists may cause vasospastic reactions other than coronary artery vasospasm. Peripheral vascular ischemia has been reported with 5-HT1 agonists (see 8.1 Adverse Reaction Overview). Very rare reports of splenic infarction and gastrointestinal ischemic events including ischemic colitis, gastrointestinal infarction or necrosis, which may present as bloody diarrhea or abdominal pain, have been received.
Increased Blood Pressure: Significant elevation in blood pressure, including hypertensive crisis, has been reported on rare occasions in patients receiving other 5-HT1 agonists with and without a history of hypertension. Very rarely these increases in blood pressure have been associated with significant clinical events. Isolated reports of chest pain, pulmonary edema, coronary vasospasm, transient cerebral ischemia, angina and subarachnoid hemorrhage have been received (see 2 CONTRAINDICATIONS). In patients with controlled hypertension, ZOLMITRIPTAN-ODT should be administered with caution, as transient increases in blood pressure and peripheral vascular resistance have been observed in a small portion of patients.
In pharmacodynamic studies, an increase of 1 and 5 mm Hg in the systolic and diastolic blood pressure, respectively, was seen in volunteers with 5 mg zolmitriptan. In the headache trials, vital signs were measured only in a small, single-centre inpatient study, and no effect on blood pressure was seen. In a study of patients with moderate to severe liver disease, 7 of 27 patients experienced 20 to 80 mm Hg elevations in systolic or diastolic blood pressure after a 10 mg zolmitriptan dose. Significant elevations in systemic blood pressure, including hypertensive crisis, have been reported on rare occasions in patients with and without a history of hypertension who received 5-HT1 agonists. ZOLMITRIPTAN-ODT is contraindicated in patients with uncontrolled or severe hypertension (see 2 CONTRAINDICATIONS).
Dependence, Tolerance and/or Abuse Liability
Zolmitriptan has not been studied for its potential to cause dependence, tolerance and/or abuse. However, there may be a theoretical risk of the occurrence of one or more of these risks. Health Professionals should consider the patient’s history of drug use and monitor appropriately.
Overuse of analgesics or other medications, such as triptans, can result in the worsening of headache symptoms (medication overuse headache) (see 7 WARNINGS AND PRECAUTIONS - Neurologic).
Driving and Operating Machinery
Although zolmitriptan did not interfere with psychomotor performance in healthy volunteers, some patients in clinical trials experienced sedation with zolmitriptan. While taking ZOLMITRIPTAN-ODT, patients should be cautioned not to drive, operate dangerous machinery or engage in activities that require alertness or physical coordination until they are reasonably certain that ZOLMITRIPTAN-ODT does not affect them adversely.
Hepatic/Biliary/Pancreatic
ZOLMITRIPTAN-ODT should be administered with caution to patients with moderate or severe hepatic impairment, using a dose lower than 2.5 mg (see 4.1 Dosing Considerations; 4.2 Recommended Dose and Dosage Adjustment; 10.3 Pharmacokinetics.
Immune
Rare hypersensitivity (anaphylaxis/anaphylactoid) reactions may occur in patients receiving 5-HT1 agonists such as ZOLMITRIPTAN-ODT. Such reactions can be life threatening or fatal. In general, hypersensitivity reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens. Owing to the possibility of cross-reactive hypersensitivity reactions, ZOLMITRIPTAN-ODT should not be used in patients having a history of hypersensitivity to chemically-related 5-HT1 receptor agonists (see 8.2 Clinical Trial Adverse Reactions).
Neurologic
Care should be taken to exclude other potentially serious neurologic conditions before treating headache in patients not previously diagnosed with migraine or who experience a headache that is atypical for them. There have been rare reports where patients received 5-HT1 agonists for severe headache that were subsequently shown to have been secondary to an evolving neurological lesion. For newly diagnosed patients or patients presenting with atypical symptoms, the diagnosis of migraine should be reconsidered if no response is seen after the first dose of ZOLMITRIPTAN-ODT.
- Medication Overuse Headache (MOH): Prolonged use of any type of painkiller for headaches can make them worse. If this situation is experienced or suspected, medical advice should be obtained, and treatment should be discontinued. The diagnosis of MOH should be suspected in patients who have frequent or daily headaches despite (or because of) the regular use of headache medications. In patients with MOH, discontinuation of ZOLMITRIPTAN-ODT may result in withdrawal symptoms, such as a transient worsening of headache (see 7 WARNINGS AND PRECAUTIONS - Dependence, Tolerance and/or Abuse Liability).
- Seizures: Caution should be observed if ZOLMITRIPTAN-ODT is to be used in patients with a history of epilepsy or structural brain lesions, which lower the convulsion threshold.
Serotonin toxicity / Serotonin syndrome: Serotonin toxicity, also known as serotonin syndrome, is a potentially life-threatening condition and has been reported with triptans, including zolmitriptan, particularly during combined use with selective serotonin reuptake inhibitors (SSRIs)/serotonin norepinephrine reuptake inhibitors (SNRIs). Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered
mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°c and ocular clonus or inducible clonus
If concomitant treatment with ZOLMITRIPTAN-ODT and SSRIs (e.g., fluoxetine, paroxetine, sertraline) or SNRIs (e.g., venlafaxine) is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Ophthalmologic
No systematic monitoring of ophthalmologic function was undertaken in clinical trials, and no specific recommendations for ophthalmologic monitoring are offered. However, prescribers should be aware of the possibility of long-term ophthalmologic effects. Animal studies suggest zolmitriptan may accumulate in melanin-rich tissues over time, which could cause toxicity in these tissues, with extended use (see 16 NON-CLINICAL TOXICOLOGY).
7.1 Special Populations
7.1.1 Pregnant Women:
The safety of zolmitriptan for use during human pregnancy has not been established. ZOLMITRIPTAN-ODT should only be used during pregnancy if the potential benefit justifies the potential risk to the fetus. In reproductive toxicity studies in rats and rabbits, oral administration of zolmitriptan to pregnant animals showed no apparent signs of teratogenicity (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
It is not known whether zolmitriptan and/or its metabolites are excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when considering the administration of ZOLMITRIPTAN-ODT to nursing women. Lactating rats dosed with zolmitriptan had milk levels equivalent to maternal plasma levels at 1 hour and 4 times higher than plasma levels at 4 hours.
7.1.3 Pediatrics
Pediatrics (<6 years of age):
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. (see 1.1 Pediatrics).
Pediatric (6-17 years of age):
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of zolmitriptan have not been established in patients 6-17 years of age. Therefore, Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics; 8.2.1 Clinical Trial Adverse Reactions – Pediatrics; 10.3 Pharmacokinetics).
Systemic exposure to the parent compound does not differ significantly between adolescents (aged 12- 17 years) and adults, however exposure to the active metabolite, 2-6 times more potent, is greater in adolescents (see 10.3 Pharmacokinetics). Some clinically serious adverse events, reported as rare occurrences in adults, have been reported in pediatric patients (see 8.5 Post-Market Adverse Reactions).
7.1.4 Geriatrics
The safety and efficacy of zolmitriptan have not been studied in individuals over 65 years of age. The risk of adverse reactions to this drug may be greater in elderly patients as they are more likely to have decreased hepatic function, be at higher risk for coronary artery disease, and experience blood pressure increases that may be more pronounced. Clinical studies did not include patients over 65 years of age. Its use in this age group is, therefore, not recommended.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Zolmitriptan is generally well tolerated. Across all doses, most adverse reactions were mild to moderate in severity as well as transient and self-limiting. The incidence of adverse events in controlled clinical trials was not affected by gender, weight, or age of patients; use of prophylactic medications; or presence of aura. There were insufficient data to assess the impact of race on the incidence of adverse events.
Serious cardiac events, including some that have been fatal, have occurred following the use of 5-HT1 agonists. These events are very rare and most have been reported in patients with risk factors predictive of coronary artery disease. Events reported have included coronary artery vasospasm, transient myocardial ischemia, angina pectoris, myocardial infarction, ventricular tachycardia, and ventricular fibrillation (see 2 CONTRAINDICATIONS; 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
As with other 5HT1 agonists, transient increases in systemic blood pressure have been reported in patients with and without a history of hypertension; very rarely these increases in blood pressure have been associated with significant clinical events. Isolated reports of chest pain, pulmonary edema, coronary vasospasm, transient cerebral ischemia, angina and subarachnoid hemorrhage have been received (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
As with other 5-HT1 agonists, zolmitriptan has been associated with sensations of heaviness, pressure, tightness or pain which may be intense. These may occur in any part of the body including the chest, throat, neck, jaw and upper limb.
There have been rare reports of hypersensitivity reactions including urticaria and angioedema (see 7 WARNINGS AND PRECAUTIONS - Immune).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Experience in Controlled Clinical Trials with Zolmitriptan Tablets
Acute Safety: In placebo-controlled migraine trials, 1,673 patients received at least one dose of zolmitriptan tablets. The following table (Table 2) lists adverse events that occurred in five placebo-controlled clinical trials in migraine patients. Events that occurred at an incidence of 1% or more in any one of the zolmitriptan tablets 1 mg, 2.5 mg or 5 mg dose groups and that occurred at a higher incidence than in the placebo group are included. The events cited reflect experience gained under closely monitored conditions in clinical trials, in a highly selected patient population. In actual clinical practice or in other clinical trials, these frequency estimates may not apply, as the conditions of use, reporting behaviour, and the kinds of patients treated may differ.
Several of the adverse events appear dose related, notably paresthesia, sensation of heaviness or tightness in chest, neck, jaw and throat, dizziness, somnolence, and possibly asthenia and nausea.
Table 2 Treatment Emergent Adverse Events in Five Single-Attack Placebo-Controlled Migraine Trials, Reported by ≥1% Patients Treated With Zolmitriptan Tablets
Placebo
Zolmitriptan Tablets
1 mg
Zolmitriptan Tablets
2.5 mg
Zolmitriptan Tablets
5 mg
Number of patients
401
163
498
1012
% incidence
Symptoms of potential cardiac origin:
Neck/Throat/Jaw Sensations*
3.0
6.1
7.0
10.9
Chest/Thorax Sensations*
1.2
1.8
3.4
3.8
Upper Limb Sensations*
0.5
2.4
4.2
4.1
Palpitations
0.7
0
0.2
2.2
Other Body Systems:
Neurological:
Dizziness
4.0
5.5
8.4
9.5
Placebo
Zolmitriptan Tablets
1 mg
Zolmitriptan Tablets
2.5 mg
Zolmitriptan Tablets
5 mg
Number of patients
401
163
498
1012
% incidence
Nervousness
0.2
0
1.4
0.7
Somnolence
3.0
4.9
6.0
7.7
Thinking Abnormal
0.5
0
1.2
0.3
Tremor
0.7
0.6
1.0
0.7
Vertigo
0
0
0
1.5
Hyperesthesia
0
0
0.6
1.1
Digestive:
Diarrhea
0.5
0.6
1.0
0.6
Dry mouth
1.7
4.9
3.2
3.2
Dyspepsia
0.5
3.1
1.6
1.0
Dysphagia
0
0
0
1.8
Nausea
3.7
3.7
9.0
6.2
Vomit
2.5
0.6
1.4
1.5
Miscellaneous:
Asthenia
3.2
4.9
3.2
8.8
Limb Sensations (upper and lower)*
0.7
0.6
0.4
1.6
Limb Sensations (lower)*
0.7
1.2
0.4
1.8
Sensations - location unspecified*
5.2
4.9
5.8
9.2
Abdominal Pain
1.7
1.2
0.6
1.3
Reaction Aggravated
1.0
1.2
1.0
0.7
Head/face Sensations*
1.7
6.7
8.6
10.9
Myalgia
0.2
0
0.2
1.3
Myasthenia
0.2
0
0.6
1.9
Dyspnea
0.2
0.6
0.2
1.2
Rhinitis
0.2
1.2
1.2
0.9
Sweating
1.2
0
1.6
2.5
Taste Perversion
0.5
2.5
0.6
0.7
*The term sensation encompasses adverse events described as pain, discomfort, pressure, heaviness, tightness, heat/burning sensations, tingling and paresthesia
Zolmitriptan tablets are generally well tolerated. Across all doses, most adverse events were mild to moderate in severity as well as transient and self-limiting. The incidence of adverse events in controlled clinical trials was not affected by gender, weight, or age of patients; use of prophylactic medications; or presence of aura. There were insufficient data to assess the impact of race on the incidence of adverse events.
Long Term Safety: In a long-term open label study in which patients were allowed to treat multiple migraine attacks for up to one year, 8% (167 of 2,058) of patients withdrew from the study due to an adverse experience. In this study, migraine headaches could be treated with either a single 5 mg dose of zolmitriptan tablets, or an initial 5 mg dose followed by a second 5 mg dose if necessary (5+5 mg). The most common adverse events (defined as occurring at an incidence of at least 5%) recorded for the 5 mg and 5+5 mg doses, respectively, comprised, in descending order of frequency: neck/throat sensations* (16%, 15%), head/face sensations* (15%, 14%), asthenia (14%, 14%), sensations* location unspecified (12%, 11%), limb sensations* (11%, 11%), nausea (12%, 8%), dizziness (11%, 9%), somnolence (10%, 10%), chest/thorax sensations* (7%, 7%), dry mouth (4%, 5%), and hyperesthesia (5%, 4%). Due to the lack of a placebo arm in this study, the role of zolmitriptan tablets in causation cannot be reliably determined. (*See footnote for Table 2). The long term safety of a 2.5 mg dose was not assessed in this study.
Experience in Controlled Clinical trials with Zolmitriptan Orally Disintegrating Tablets
Acute safety: In an international, placebo-controlled, double-blind trial to evaluate the efficacy and tolerability of zolmitriptan orally disintegrating tablets 2.5 mg in the acute treatment of adult patients with migraine, 231 patients received at least one dose of zolmitriptan orally disintegrating tablets. Most of the adverse events were of mild or moderate intensity, and no patients withdrew from the trial because of adverse events. The types of adverse events reported were consistent with known effects of this class of compound (5- HT1B/1D) and were similar to those reported with the zolmitriptan conventional tablet. The most frequently reported adverse events (>2%) for zolmitriptan orally disintegrating tablets 2.5 mg versus placebo, respectively, were asthenia (3% vs. 1%), tightness (3% vs. <1%), somnolence (3% vs. 2%), dizziness (3% vs. 1%), paresthesia (3% vs. 2%), hyperesthesia (2% vs. 0%), pharyngitis (2% vs. 0%), and nausea (2% vs. 1%).
Overall Results of Clinical Trials
In a pool of 51 placebo-controlled and open labelled studies the above adverse events were reported at the described frequencies, with the exception of the following adverse events which were reported at a greater frequency. In total 17,301 patients with migraine were treated with zolmitriptan. Events are classified within body system categories and enumerated in order of decreasing frequency.
Cardiac Disorders: Uncommon was tachycardia.
Gastrointestinal Disorders: Common was dysphagia, vomiting and abdominal pain.
Nervous System Disorders: Common was headache.
Vascular Disorders: Uncommon was transient increases in systemic blood pressure.
Sensations of heaviness, tightness, pain or pressure in the throat, neck, limbs or chest were common and consistent with those observed in Table 2.
8.2.1. Clinical Trial Adverse Reactions – Pediatrics
Pediatrics (6-11 years of age)
Health Canada has not authorized an indication for use in any pediatric population (see 1.1 Pediatrics).
Limited data from a single multicenter, double-blind, randomized, placebo-controlled, cross-over clinical trial involving 168 pediatric patients (6-11 years) with migraine headache suggest the type and severity of adverse reactions may be similar to those in adults. No new safety issues have been identified from the completed pediatric trial for the age group investigated. However, the safety database for this pediatric population is too limited for the accurate identification of common, less common, rare, or very rare adverse reactions or their frequencies.
While no definitive conclusions can be made regarding relative frequencies, some cardiac arrhythmias, reported as rare in adults, were reported more frequently in the pediatric population.
Pediatrics (12-17 years of age)
Health Canada has not authorized an indication for use in any pediatric population (see 1.1 Pediatrics; 8.5 Post-Market Adverse Reactions).
Table 3 lists the adverse events observed in a single randomized placebo-controlled study of 696 adolescent migraineurs aged 12-17 years (see 7.1.3 Pediatrics; 10.3 Pharmacokinetics ).
Table 3: Adverse events in a single placebo-controlled adolescent study, reported by ≥ 1% of patients treated with zolmitriptan tablets
Percentage Of Patients Zolmitriptan Tablets | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Body System And Adverse Event (COSTART Term) | Placebo (N=176) | 2.5 mg (N=171) | 5 mg (N=174) | 10 mg (N=178) | ||||||||
| Cardiovascular | ||||||||||||
| Vasodilatation | 0.6 | 0 | 2.9 | 3.9 | ||||||||
| Palpitation | 0 | 0 | 1.1 | 0 | ||||||||
| Whole Body | ||||||||||||
| Tightness | 1.1 | 2.9 | 5.7 | 11.2 | ||||||||
| Asthenia | 1.1 | 1.8 | 1.1 | 5.1 | ||||||||
| Pain | 0 | 1.8 | 1.7 | 5.1 | ||||||||
| Neck Pain | 0 | 0.6 | 1.7 | 3.4 | ||||||||
| Abdominal Pain | 0.6 | 1.2 | 0 | 1.7 | ||||||||
| Headache | 0 | 1.2 | 2.9 | 1.1 | ||||||||
| Malaise | 0 | 0 | 2.3 | 0.6 | ||||||||
| Pressure | 0 | 1.8 | 0.6 | 0.6 | ||||||||
| Stiffness | 0 | 0 | 0.6 | 2.8 | ||||||||
| Heaviness | 1.1 | 0.6 | 0 | 1.1 | ||||||||
| Digestive | ||||||||||||
| Nausea | 1.1 | 5.8 | 2.9 | 7.9 | ||||||||
| Vomiting | 1.1 | 0.6 | 1.7 | 4.5 | ||||||||
| Dry Mouth | 0.6 | 1.8 | 1.1 | 1.1 | ||||||||
| Nervous System | ||||||||||||
| Dizziness | 2.3 | 4.7 | 4.6 | 9.0 | ||||||||
| Paresthesia | 0 | 1.8 | 4.6 | 6.2 | ||||||||
| Somnolence | 1.7 | 1.2 | 1.7 | 2.8 | ||||||||
| Hypertonia | 0 | 0.6 | 1.7 | 1.1 | ||||||||
| Internasal Paresthesia | 0 | 2.3 | 0.6 | 0 | ||||||||
| Tremor | 0 | 0 | 0 | 1.7 | ||||||||
| Hyperesthesia | 0 | 0 | 0 | 1.1 | ||||||||
| Respiratory System | ||||||||||||
| Pharyngitis | 0.6 | 2.9 | 2.3 | 1.7 | ||||||||
| Dyspnea | 0.6 | 0 | 1.1 | 0.6 | ||||||||
| Musculoskeletal | ||||||||||||
| Myalgia | 0 | 0 | 1.1 | 0.6 | ||||||||
| Skin and Appendages | ||||||||||||
| Sweating | 0 | 0 | 0 | 1.7 | ||||||||
| Special Senses | ||||||||||||
| Eye Pain | 0 | 0.6 | 1.1 | 0.6 | ||||||||
| Ambylopia | 0 | 0 | 0 | 1.1 | ||||||||
8.3 Less Common Clinical Trial Adverse Reactions
The frequencies of less commonly reported adverse clinical events are presented below. Because the reports include events observed in open and uncontrolled studies, the role of zolmitriptan in their causation cannot be reliably determined. Furthermore, variability associated with adverse event reporting, the terminology used to describe adverse events, etc., limit the value of the quantitative frequency estimates provided. Event frequencies are calculated as the number of patients who used zolmitriptan (n=4,027) and reported an event divided by the total number of patients exposed to zolmitriptan. All reported events are included except those already listed in the previous table, those too general to be informative, and those not reasonably associated with the use of the drug. Events are further classified within body system categories and enumerated in order of decreasing frequency.
Blood and lymphatic system disorders: ecchymosis, cyanosis, thrombocytopenia, eosinophilia and leucopenia.
Cardiac disorders: arrhythmias, hypertension, syncope, bradycardia, extrasystoles, postural hypotension, QT prolongation, thrombophlebitis, tachycardia, palpitations and transient increases in systemic blood pressure in patients with or without a history of hypertension (7 WARNINGS AND
PRECAUTIONS - Cardiovascular).
Ear and labyrinth disorders: hyperacusis, ear pain, tinnitus
Eye disorders: dry eye, eye pain, diplopia, lacrimation
Gastrointestinal disorders: increased appetite, tongue edema, esophagitis, gastroenteritis, liver function abnormality, thirst, anorexia, constipation, gastritis, hematemesis, pancreatitis, melena, ulcer
General disorders and administration site conditions: allergy reaction, chills, facial edema, fever, malaise, parosmia, photosensitivity
Metabolism and nutrition disorders: edema, hyperglycemia, alkaline phosphatase increased
Musculoskeletal and connective tissue disorders: back pain, leg cramps, tenosynovitis, arthritis, tetany, twitching
Nervous system disorders: agitation, anxiety, depression, emotional lability, insomnia, akathisia, amnesia, apathy, ataxia, dystonia, euphoria, hallucinations, cerebral ischemia, hyperkinesia, hypotonia, hypertonia, irritability, headache, hyperesthesia
Renal and urinary disorders: hematuria, cystitis, polyuria, urinary frequency, urinary urgency
Reproductive system and breast disorders: miscarriage, dysmenorrhea
Respiratory, thoracic and mediastinal disorders: bronchitis, bronchospasm, epistaxis, hiccup, laryngitis, yawn, apnea, voice alteration
Skin and subcutaneous tissue disorders: pruritus, rash, urticaria, angioedema
8.3.1 Less Common Clinical Trial Adverse Reactions - Pediatrics
There is insufficient data available for the accurate identification of less common clinical trial adverse reactions in pediatric patients.
8.5 Post-Market Adverse Reactions
In addition to the adverse experiences reported during clinical testing of zolmitriptan, the following adverse experiences have been reported in patients receiving marketed zolmitriptan from worldwide use since approval. There are insufficient data to support an estimate of their incidence or to establish causality.
Serious adverse events have occurred during post-marketing surveillance following the use of zolmitriptan oral tablets. These events are extremely rare and most have been reported in patients with risk factors predictive of CAD. Events reported have included coronary artery vasospasm, transient myocardial ischemia, angina pectoris and myocardial infarction (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
Post-market reports show that dysphagia has been reported commonly when using zolmitriptan.
As with other 5-HT1B/1D agonists, there have been very rare reports of anaphylaxis or anaphylactoid and hypersensitivity reactions, including angioedema, in patients receiving zolmitriptan. There have also been reports of gastrointestinal ischemic events including ischemic colitis, gastrointestinal infarction, splenic infarction, or necrosis, which may present as bloody diarrhea or abdominal pain.
Post-marketing experience with other triptans include a limited number of reports that describe pediatric (under 12 years of age) and adolescent (12 - 17 years of age) patients who have experienced clinically serious adverse events that are similar in nature to those reported as rare occurrences in adults.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
Due to the potential for additive pharmacodynamic effects, serious drug-drug interactions may occur when ZOLMITRIPTAN-ODT is used concomitantly with ergot-containing or ergot-type medications, increasing the risk of prolonged vasospastic reactions. There is also a potential increased risk of coronary vasospasm with co-administration of other 5-HT1 agonists. The use of ZOLMITRIPTAN-ODT within 24 hours of ergot-containing drugs or other 5-HT1 agonists is contraindicated (see 2 CONTRAINDICATIONS; 9.1 Serious Drug Interactions).
Co-administration of ZOLMITRIPTAN-ODT with other 5-HT1 agonists, monoamine oxidase (MAO) inhibitors, serotonin reuptake inhibitors (SSRIs), and serotonin norepinephrine reuptake inhibitors (SNRIs) can increase the risk of life-threatening serotonin toxicity/serotonin syndrome (see 7 WARNINGS AND PRECAUTIONS- Neurologic). Concomitant use of ZOLMITRIPTAN-ODT with any of these medications is contraindicated (see 2 CONTRAINDICATIONS; 9.1 Serious Drug Interactions).
Zolmitriptan is metabolized in the liver primarily by CYP1A2 and monoamine oxidase. Drugs that inhibit these enzymes can significantly increase exposure to both zolmitriptan and its active metabolite, N-desmethylzolmitriptan. Patients taking cimetidine and other CYP1A2 inhibitors should not exceed a dose of 5 mg ZOLMITRIPTAN-ODT in any 24 hour period. Co-administration of ZOLMITRIPTAN-ODT with any MAO inhibitor is contraindicated (see 2 CONTRAINDICATIONS).
Propranolol, at a dose of 160 mg/day for 1 week, increased Cmax and AUC of zolmitriptan by 1.5-fold, while reducing Cmax and AUC of N-desmethylzolmitriptan by 30% and 15%, respectively. However, there were no changes in the pharmacological effect on blood pressure or pulse rate.
Retrospective analysis of pharmacokinetic data across studies indicate that oral contraceptives increase mean Cmax and AUC of zolmitriptan by 30% and 50%, respectively and delay Tmax by 30
Serious Drug Interactions
- Ergot-Containing Drugs (see 2 CONTRAINDICATIONS; 9.4 Drug-Drug Interactions)
- Other 5-HT1 Agonists (see 2 CONTRAINDICATIONS; 9.4 Drug-Drug Interactions)
- MAO Inhibitors (see 2 CONTRAINDICATIONS; 9.4 Drug-Drug Interactions)
- Selective Serotonin Reuptake Inhibitors/Serotonin Norepinephrine Reuptake Inhibitors (see
9.4 Drug-Drug Interactions)
minutes. Effects of zolmitriptan on the pharmacokinetics of oral contraceptives has not been studied.
Constituents in St. John’s Wort possess high potency in the inhibition of CYP enzymes involved in the metabolism of zolmitriptan and use with ZOLMITRIPTAN-ODT should be avoided. Green tea extract is a mild inhibitor of CYP1A2 and its use with ZOLMITRIPTAN-ODT should be limited.
Smoking and alcohol consumption may increase the risk of serious cardiac adverse events (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Zolmitriptan does not induce or inhibit cytochrome P450 enzymes and is unlikely to affect clearance of drugs metabolized by these enzymes.
9.3 Drug-Behavioural Interactions
Smoking or tobacco use may increase the risk of serious cardiac events (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Alcohol use can increase the risk of certain central nervous system adverse events, including dizziness, somnolence, and abnormal thinking. The use of alcohol should be avoided or limited during treatment with ZOLMITRIPTAN-ODT.
Interaction studies were performed with caffeine and found no clinically relevant differences in the pharmacokinetics of zolmitriptan or its active metabolite.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4: Established or Potential Drug-Drug Interaction
| Drug Name/Class | Source Of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Ergot-containing Drugs (e.g. dihydroergotamine, ergotamine, methysergide) | T, C | Potential additive pharmacodynamic effects, causing prolonged vasospastic reactions. | The use of ZOLMITRIPTAN-ODT within 24 hours of ergot-containing or ergot-type medications is contraindicated (see 2 CONTRAINDICATIONS). |
Other 5-HT1 Agonists (e.g.. sumaptriptan, rizatriptan, almotriptan, eletriptan, | T | Potential additive effect, increasing the risk of coronary vasospasm. Potential risk of serotonin toxicity/serotonin syndrome (see 7 | Use of ZOLMITRIPTAN-ODT within 24 hours of other 5-HT1 agonists is contraindicated (see 2 CONTRAINDICATIONS). |
| naratriptan, frovatriptan) | WARNINGS AND PRECAUTIONS - Neurologic) | ||
MAO-A Inhibitors (e.g. clorgyline, moclobemide) | CT | Increased exposure (26% increase in both AUC and Cmax for zolmitriptan and a 3-fold increase in the AUC and Cmax of the active metabolite N-desmethylzolmitriptan). Potential risk of serotonin toxicity/serotonin syndrome (see 7 WARNINGS AND PRECAUTIONS - Neurologic). | ZOLMITRIPTAN-ODT is contraindicated in patients taking any MAO inhibitor (see 2 CONTRAINDICATIONS). |
MAO-B Inhibitors (e.g. selegiline, rasagiline) | CT | No effect on the pharmacokinetic parameters of zolmitriptan or the active metabolite, N-desmethylzolmitriptan. | The specificity of MAO-B inhibitors, such as selegiline, diminishes with higher doses and varies between patients. ZOLMITRIPTAN-ODT is contraindicated in patients taking any MAO inhibitor (see 2 CONTRAINDICATIONS). |
Cimetidine and other CYP1A2 Inhibitors (e.g. fluvoxamine, ciprofloxacin) | CT | 2-fold increase in exposure to both zolmitriptan and its active metabolite, N-desmethylzolmitriptan | Patients taking cimetidine or specific inhibitors of CYP1A2 should not exceed a dose of 5 mg ZOLMITRIPTAN-ODT in any 24 hour period. |
| Oral Contraceptives | CT | Increased exposure to zolmitriptan (30% higher Cmax and 50% higher AUC) and delayed Tmax. Effects of zolmitriptan on oral contraceptives have not been determined. | No dosage adjustment is required. |
| Propranolol | CT | 1.5-fold increase in zolmitriptan exposure | There were no interactive effects on blood pressure or pulse rate following administration of propranolol with zolmitriptan. |
| No dosage adjustment required. | |||
Selective Serotonin Reuptake Inhibitors (SSRIs) (e.g. citalopram, sertraline, paroxetine) Serotonin Norepinephrine Reuptake Inhibitors (SNRIs) (e.g. duloxetine, venlafaxine) | CT, T | Cases of life-threatening serotonin toxicity/ serotonin syndrome have been reported during combined use of SSRIs or SNRIs and triptans (see 7 WARNINGS AND PRECAUTIONS - Neurologic) | ZOLMITRIPTAN-ODT is contraindicated in patients taking SSRIs or SNRIs (see 2 CONTRAINDICATIONS). |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
No clinically significant pharmacokinetic interactions were observed when zolmitriptan was co-administered with acetaminophen, metoclopramide, rifampicin, or xylometazoline.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions of zolmitriptan with herbal products have not been studied.
St John’s Wort: Undesirable effects may be more common during concomitant use of triptans and herbal preparations containing St John’s Wort (Hypericum perforatum). Concomitant use of ZOLMITRIPTAN-ODT with St John’s Wort should be avoided.
Green tea: Green tea extracts are mild inhibitors of CYP1A2 enzymes. The ingestion of green tea extract or its associated catechins is not expected to result in clinically significant influences on zolmitriptan exposure. However, some caution is advised in the consumption of excessive amounts of green tea beverages or green tea extract in patients prescribed ZOLMITRIPTAN-ODT .
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Zolmitriptan is a selective 5-hydroxytryptamine1 (5-HT1B/1D) receptor agonist. It exhibits a high affinity at human recombinant 5-HT1B and 5-HT1D receptors and modest affinity for 5- HT1a receptors. Zolmitriptan has no significant affinity (as measured by radioligand binding assays) or pharmacological activity at 5-HT2, 5-HT3, 5-HT4, alpha1, alpha2, or beta1, - adrenergic; H1, H2, histaminic; muscarinic; dopamine1, or dopamine2, receptors. The N-desmethyl metabolite of zolmitriptan (N-desmethylzolmitriptan) also has high affinity for 5- HT1B/1D and modest affinity for 5-HT1A receptors.
It has been proposed that symptoms associated with migraine headaches arise from the activation of the trigemino-vascular system, which results in local cranial vasodilation and neurogenic inflammation involving the antidromic release of sensory neuropeptides [Vasoactive Intestinal Peptide (VIP), Substance P and calcitonin gene related peptide (CGRP)]. The therapeutic activity of zolmitriptan for the treatment of migraine headache is thought to be attributable to its agonist effects at 5-HT1B/1D receptors on the intracranial blood vessels, including the arterio-venous anastamoses, and sensory nerves of the trigeminal system which result in cranial vessel constriction and inhibition of pro-inflammatory neuropeptide release.
10.2 Pharmacodynamics
In clinical studies, the proportion of patients with undesirable effects has been shown to increase with increasing dose.
The remaining pharmacodynamic data was obtained from nonclinical studies.
In vitro: Receptor specificity studies using radioligand binding assays and isolated intact tissue assays have shown that zolmitriptan is a selective 5-HT1 partial receptor agonist which exhibits a high affinity at human recombinant 5-HT1D (pKi = 9.2) and 5-HT1B (pKi = 8.2) receptors and modest affinity for 5-HT1A receptors (pKi = 7.0). Zolmitriptan had no significant affinity or pharmacological activity at 5-HT2, 5-HT3, 5-HT4, alpha1, alpha2, or beta1, -adrenergic; H1, H2, histaminic; muscarinic; dopamine1, or dopamine2, receptors.
In vivo: In anesthetized animals, zolmitriptan (0.3 - 100 µg/kg i.v.) caused dose-related and sustained reductions in carotid arterial blood flow and conductance (ED50 for dogs: 2.9 µg /kg; for cats: 1.1 µg/kg). This reflected a constriction of cranial arteriovenous anastomoses (AVA), with a very minor contribution from the extracranial circulation. No equivalent reductions occurred in cerebral blood flow and conductance in these animals. At doses of 30 µg /kg and 100 µg /kg, i.v., zolmitriptan inhibited trigeminal ganglion electrically stimulated release of calcitonin gene related peptide in anesthetized cats. The effect of trigeminal ganglion stimulation on vasoactive intestinal peptide was also attenuated, in this animal model, by 100 µg/kg zolmitriptan administered i.v. Over a dose range of 3 - 30 µg/kg (i.v.), zolmitriptan caused a dose-related inhibition of neurogenic plasma protein extravasation into the ipsilateral dura mater following electrical stimulation of the trigeminal ganglion.
At higher doses (>100 µg /kg), zolmitriptan produced some systemic cardiovascular effects (notably inconsistent and poorly dose-related increases in blood pressure and heart rate in conscious animals). These systemic effects were species-specific and modified by anesthesia. Apart from its selective vasoconstrictor action in vascular beds supplied by the carotid artery, zolmitriptan had little or no effect at doses up to 1 mg/kg in other major systemic vascular beds, including the coronary and pulmonary circulations. Only in dog renal vasculature was zolmitriptan found also to cause dose-related vasoconstrictor responses.
Zolmitriptan elicited some central nervous system and behavioural effects at high doses (1 or 2 mg/kg), but the severity of these effects were species-specific.
Zolmitriptan exhibited no general autonomic effects, but at low doses (3 -100 µg/kg i.v.) had a selective effect on the sympathetic innervation to the carotid vasculature consistent with agonist activity at pre-junctional inhibitory 5-HT1D -like receptors.
Zolmitriptan did not cause any important respiratory effects except at high doses (>1 mg/kg). However, at these doses other central nervous system and behavioural effects may contribute.
Zolmitriptan had no effects on gastrointestinal function except at very high doses (30 mg/kg, P.O.). Likewise, the drug was without important effect on renal function and barbiturate sleeping times.
The metabolism of zolmitriptan in humans results in the formation of a pharmacologically active N-demethylated derivative (see 10.3 Pharmacokinetics). This metabolite exhibited the same pharmacological specificity as the parent molecule, but was 2 to 6 times more potent at 5-HT1D receptors. The cardiovascular profile of the metabolite was qualitatively the same as that of zolmitriptan.
10.3 Pharmacokinetics
Table 5 - Summary of Zolmitriptan Pharmacokinetic Parameters in Healthy Volunteers**
| Formulation | Cmax (ng/mL) | Tmax (h) | T½ (h) | AUC0-∞ (ng.h/mL) | CL* (L/hour) | Vd L/kg |
|---|---|---|---|---|---|---|
Zolmitriptan Tablets 2.5 mg | 3 | 2 | 2.58 | 17 | 183 | 7 |
| Zolmitriptan Orally Disintegrating Tablets 2.5mg*** | 3 | 3.3 | 2.58 | 17 | 183 | 7 |
* Systemic clearance
** parameters may vary slightly in migraineurs
*** the pharmacokinetic data upon which zolmitriptan orally disintegrating tablets was originally approved is not available. However, pharmacokinetic parameters are comparable to those observed following administration of zolmitriptan tablets, except the Tmax, which occurs somewhat later.
Zolmitriptan Orally Disintegrating Tablets
Absorption: In human, zolmitriptan is rapidly and well absorbed (at least 64%) after oral administration with peak plasma concentrations occurring in 3 hours for the ODT. The mean absolute bioavailability of the parent compound is approximately 40%. Food has no significant effect on the bioavailability of zolmitriptan.
During a moderate to severe migraine attack in male and female patients, mean AUC0-4 and Cmax for zolmitriptan were decreased by 40% and 25%, respectively and mean Tmax was delayed by one-half hour compared to the same patients during a migraine free period.
When given as a single dose to healthy volunteers, zolmitriptan displayed linear kinetics over the dose range of 2.5 to 50 mg.
Distribution: The mean apparent volume of distribution is 7.0 L/kg. Plasma protein binding of zolmitriptan over the concentration range of 10 - 1000 ng/L is 25%.
There is no evidence of accumulation on multiple dosing with zolmitriptan up to doses of 10 mg.
Metabolism: Metabolism of zolmitriptan is dependent on CYP1A2 and the metabolism of the active metabolite N-desmethylzolmitriptan is via the monoamine oxidase A (MAOA) enzyme system. The enzymes responsible for the metabolism of zolmitriptan remain to be fully characterized.
Conversion of zolmitriptan to the active metabolite N-desmethylzolmitriptan occurs such that metabolite concentrations are approximately two thirds that of zolmitriptan. Because the 5-HT1B/1D potency of N-desmethylzolmitriptan is 2 to 6 times that of the parent, the metabolite may contribute a substantial portion of the overall effect after zolmitriptan administration. The half-life of N-desmethylzolmitriptan is 3 hours and the Tmax is approximately 2 to 3 hours.
Elimination: Zolmitriptan is eliminated largely by hepatic biotransformation followed by urinary excretion of the metabolites. The mean elimination half-life of zolmitriptan is approximately 2.5 to 3 hours. Mean total plasma clearance of zolmitriptan is 31.5 mL/min/kg, of which one-sixth is renal clearance. The renal clearance is greater than the glomerular filtration rate suggesting renal tubular secretion.
In a study in which radiolabelled zolmitriptan was orally administered to healthy volunteers, 64% and 30% of the administered 14C-zolmitriptan dose was excreted in the urine and feces, respectively. About 8% of the dose was recovered in the urine as unchanged zolmitriptan. The indole acetic acid and N-oxide metabolites, which are inactive, accounted for 31% and 7% of the dose, respectively, while the active metabolite N-desmethylzolmitriptan accounted for 4% of the dose.
Special Populations and Conditions
- Pediatrics (<12 years of age): Zolmitriptan pharmacokinetics have not been established in children under the age of 12 years.
- Pediatrics (12 - 17 years of age): In a single dose pharmacokinetic study of 5 mg zolmitriptan, systemic exposure to the parent compound was not found to differ significantly between adolescents and adults. However, plasma levels of the active metabolite were significantly greater (40 - 50%) in adolescents than adults. The metabolite is 2 to 6 times more potent at 5-HT1D receptors (see 10.2 Pharmacodynamics).
- Geriatrics: Zolmitriptan pharmacokinetics in healthy elderly non-migraineur (non-migraine sufferers) volunteers (65-76 years of age) were similar to those in younger non-migraineur volunteers (18-39 years of age).
- Sex: Mean plasma concentrations of zolmitriptan were up to 1.5-fold greater in females than in males.
- Pregnancy and Breast-feeding: Zolmitriptan has not been studied in pregnant or breast-feeding women. Resulting exposures to the fetus, neonate, or infant have not been determined (see 7.1 Special Populations).
- Ethnic Origin: The effect of race on the pharmacokinetics of zolmitriptan has not been
- systematically evaluated. Retrospective analysis of pharmacokinetic data between Japanese and Caucasian subjects revealed no significant differences.
- Hepatic Insufficiency: A study to evaluate the effect of liver disease on the pharmacokinetics of zolmitriptan showed that the AUC and Cmax were increased by 94% and 50% respectively in patients with moderate liver disease and by 226% and 47% in patients with severe liver disease compared with healthy volunteers. Exposure to the metabolites, including the active metabolite N-desmethylzolmitriptan, was decreased. For N-desmethyl zolmitriptan, AUC and Cmax were reduced by 33% and 44% in patients with moderate liver disease and by 82% and 90% in patients with severe liver disease.
The plasma half-life (t½) of zolmitriptan was 4.7 hours in healthy volunteers, 7.3 hours in patients with moderate liver disease and 12 hours in those with severe liver disease. The corresponding t½ values for N-desmethylzolmitriptan were 5.7 hours, 7.5 hours and 7.8 hours respectively.
Seven out of 27 patients with hepatic impairment (4 with moderate and 3 with severe liver disease) experienced 20 to 80 mm Hg elevations in systolic and/or diastolic blood pressure after a 10 mg dose. Zolmitriptan should be administered with caution in subjects with moderate or severe liver disease (see 7 WARNINGS AND PRECAUTIONS - Hepatic/Biliary/Pancreatic; 4.1 Dosing Considerations)
Renal Insufficiency: Following oral dosing in patients with severe renal impairment (ClCr
≥5 - ≤25 mL/min), clearance of zolmitriptan was reduced by 25% compared to normal (ClCr
≥70 mL/min). There was no significant change observed in the clearance of zolmitriptan in patients with moderate renal impairment (ClCr ≥26 - ≤50 mL/min).
- Obesity: Zolmitriptan pharmacokinetics in obese patients have not been established.
- Hypertension: No differences in the pharmacokinetics of zolmitriptan were noted in mild to moderate hypertensive volunteers compared to normotensive controls. In this study involving a limited number of patients, small dose-dependent increases in systolic and diastolic blood pressure (approximately 3 mm Hg) did not differ between mild/moderate hypertensives and normotensive controls. ZOLMITRIPTAN-ODT is contraindicated in patients with uncontrolled or severe hypertension (see 2 CONTRAINDICATIONS;7 WARNINGS AND PRECAUTIONS - Cardiovascular).
11 STORAGE, STABILITY AND DISPOSAL
ZOLMITRIPTAN-ODT should be stored at room temperature between 15°C and 30°C
12 SPECIAL HANDLING INSTRUCTIONS
No special requirements for handling
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name:
Zolmitriptan
Chemical Name:
(4S)-4-[[3-[2-(Dimethylamino)ethyl]-1H-indol-5-yl]methyl]-2- oxazolidinone
Molecular Formula And Molecular Mass:
C16H21N3O2 and
287.36 g/mol
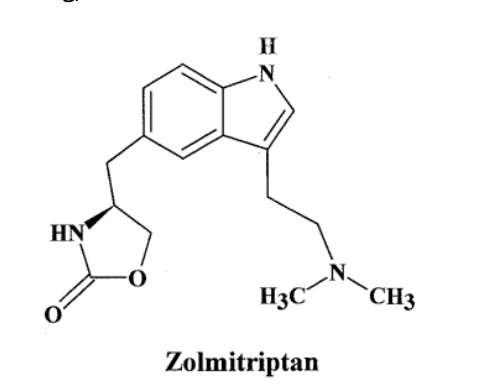
Structural Formula:
Physiochemical Properties:
White to cream coloured crystalline powder.
Solubility:
Freely soluble in methanol, slightly soluble in ethyl acetate, very slightly soluble in water.
Pka:
8.49
Partition Co-Efficient:
1.6
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Indication: Acute Treatment Of Migraine Attacks, With or Without Aura, in Adults
The efficacy of zolmitriptan was not affected by the presence of aura and was independent of headache duration pre-treatment, relationship to menses, gender, age or weight of the patient, pre-treatment nausea and concomitant use of common migraine prophylactic drugs.
Zolmitriptan Orally Disintegrating Tablets
Table 6 - Summary of patient demographics for clinical trials in the acute treatment of migraine attacks, with or without aura, in adults using zolmitriptan orally disintegrating tablets
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| 311C90 | International, randomized, placebo-controlled, double-blind trial | Zolmitriptan up to two 2.5 mg orally disintegrating tablets per os separated by at least 2 hours; placebo per os | Placebo: n=240 Zolmitriptan: n=231 | 41 years (18 – 62) | Males (13%) |
311CUS0 014 | Randomized, multi-centre, parallel-group, placebo-controlled, double- blind trial | Single oral dose: 2.5 mg. Optional second dose: 2.5 mg; oral; 2-24 hours after the first dose | Zolmitriptan: n =281 Placebo: n=284 | 41 years (18 -65) | Males (15%) |
The efficacy and tolerability of zolmitriptan orally disintegrating tablets 2.5 mg tablets in the acute treatment of adult patients with migraine was evaluated in an international, randomized, placebo-controlled, double-blind trial. A total of 471 patients [87% female; 97% Caucasian; mean age 41 years (18 - 62)] were exposed to trial medication, 231 were randomized to zolmitriptan and 240 to placebo. Each patient was instructed to treat a single migraine of moderate or severe intensity with double-blind medication. If sufficient relief was not obtained 2 hours after the first dose, a second dose or escape medication could be taken.
Headache response, defined as a reduction of headache pain from moderate or severe at the time of treatment to mild or none at assessment, was evaluated at 0.5, 1, 2, and 4 hours after the first dose. The primary endpoint was headache response at 2 hours.
Table 7 Percentage of Patients with Headache Response* at 2 hours Post-Dose by Treatment Group (ITT population)
| Zolmitriptan Orally Disintegrating Tablets group | Placebo Treatment Group | Statistical Comparison of Zolmitriptan Orally Disintegrating Tablets versus Placebo | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| N | Headache Response N (%)a | N | Headache Response N (%)a | p-value | |||||||
| 220 | 138 (63) | 236 | 53 (22) | <0.0001 | |||||||
a Percentages are based upon the total number of patients in the ITT population for which data were available at 2 hours following a single attack.
ITT Intent to treat population – the subset of randomized patients who received trial medication and who received at least one efficacy evaluation.
- Headache response is the diminution of headache pain from moderate or severe at the time
- of treatment to mild or none at the assessment.
When compared to the placebo treatment group, a statistically significant greater proportion of the zolmitriptan orally disintegrating tablets group experienced a headache response within 2 hours of initial dosing (primary endpoint, see Table 8). Patients treating with zolmitriptan orally disintegrating tablets also had statistically significant headache response relative to placebo at 0.5, 1 and 4 hours post-dose.
Assessment of the number of patients who were pain-free after treating a migraine attack revealed that 27% of patients treating with zolmitriptan orally disintegrating tablets were pain free at 2 hours compared to 7% treating with placebo (p<0.001). The number of patients pain-free through 24 hours after treatment with a single dose of trial medication was also greater in the zolmitriptan orally disintegrating tablets (23%) than in the placebo (7%) group.
The median time to second treatment (second dose or escape medication) was more than twice as long in the zolmitriptan orally disintegrating tablets treatment group relative to placebo, 5 hours and 45 minutes versus 2 hours and 10 minutes.
Table 8 Pain Free Response* at 2 hours Post-Dose by Treatment Group (ITT Population)
| Migraine Attack | Zolmitriptan Orally Disintegrating Tablets Group | Placebo Treatment Group | Statistical Comparison of Zolmitriptan Orally Disintegrating Tablets versus Placebo | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| N | Pain-free response N (%)a | N | Pain-free response N (%)a | p-value | |||||||||||
| Totalb | 526 | 211 (40) | 524 | 104 (20) | <0.001 | ||||||||||
| 1st attackc | 278 | 114 (41) | 282 | 55 (20) | Not analyzedc | ||||||||||
| 2nd attackc | 248 | 97 (39) | 242 | 49 (20) | Not analyzedc | ||||||||||
- a Percentages are based upon the total number of attacks (N) in the ITT population for which data were available at 2 hours.
- b Primary efficacy endpoint was the overall pain-free response rate over 2 migraine attacks.
- c The analysis of the first and second attacks individually was performed as a secondary variable and not statistically analysed.
ITT Intent to treat population – the subset of randomized patients who received trial medication and who received at least one efficacy evaluation.
- Pain-free response is the improvement in migraine headache pain intensity from mild, moderate or severe to no pain at the assessment.
The efficacy and tolerability of zolmitriptan orally disintegrating tablets 2.5 mg tablets in the acute treatment of adult patients with migraine was also evaluated in a second randomized, multi-centre, parallel-group, placebo-controlled, double-blind trial. A total of 565 patients [85% female; 85% Caucasian; mean age 41 years (18 - 65)] were randomized to zolmitriptan (n=281) or placebo (n=284) and consumed at least 1 dose of study medication. Each patient was instructed to treat two separate migraine headaches of mild, moderate, or severe intensity with double-blind medication. For each migraine, if sufficient relief was not obtained 2 hours after the first dose, a second dose or escape medication could be taken. The primary endpoint was the overall pain-free response rate over two migraine attacks at 2 hours after dosing. Pain-free response was defined as an improvement in headache pain from mild, moderate or severe to no pain at assessment (2 hours after dosing). When compared to the placebo treatment group, a statistically significant proportion of the zolmitriptan orally disintegrating tablets group experienced a pain-free response within 2 hours of dosing (see Table 8).
Remedication rates were higher in the placebo group for both attacks, compared to the zolmitriptan orally disintegrating tablets treatment group and time to remedication was statistically significantly shorter in the placebo group (p<0.001).
Patients treating migraines with zolmitriptan orally disintegrating tablets were more likely to experience relief of nausea, photophobia, and phonophobia relative to placebo at the primary endpoint of 2 hours.
14.2 Comparative Bioavailability Studies
A randomized, blinded, two-treatment, two-period, two-sequence, single oral dose (2.5 mg dose as 1 x 2.5 mg), crossover, comparative bioavailability study comparing ZOLMITRIPTAN-ODT with PrZOMIG RAPIMELT® was conducted in healthy, adult, human subjects under fasting conditions. Comparative bioavailability data from the 30 subjects who completed the study are summarized in the following table:
Summary Table of the Comparative Bioavailability Data
Zolmitriptan (1 x 2.5 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT | 25109.60 | 25683.96 | 97.8 | 85.5 - 111.8 |
| (pg·hr/mL) | 27618.42 (38.58) | 27396.82 (36.11) | ||
| AUCI | 25805.85 | 26431.29 | 97.6 | 85.8 - 111.2 |
| (pg·hr/mL) | 28304.75 (38.05) | 28096.00 (35.39) | ||
| Cmax | 4975.65 | 4733.96 | 105.1 | 92.5 - 119.5 |
| (pg/mL) | 5308.78 (36.72) | 4987.38 (32.01) | ||
Tmax3 (h) | 2.835 (0.50 – 5.00) | 2.165 (0.50 – 5.00) | ||
T½4 (h) | 4.08 (35.84) | 3.83 (38.10) | ||
1 ZOLMITRIPTAN-ODT (zolmitriptan) orally disintegrating tablets, 2.5 mg (Jubilant Generics Limited)
2 PrZOMIG RAPIMELT® (zolmitriptan) orally disintegrating tablets, 2.5 mg (AstraZeneca Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
In oral acute studies in mice the approximate lethal dose of zolmitriptan was 1000 mg/kg and in rats the approximate lethal dose was between 1000 and 1500 mg/kg. Although exposure was not measured, the approximate oral lethal dose of zolmitriptan in rodents is about 20,000 times the usual human dose of 2.5 mg. The approximate lethal dose was 50 - 100 mg/kg following intravenous administration. Animals were found dead without premonitory signs.
Long-Term Toxicity
Repeated dose studies in rats (up to 1000 mg/kg/day) and dogs (up to 100 mg/kg/day) have revealed little toxicity other than clinical signs, which are associated with an excess of the pharmacological action of this class of compound. Dose limiting factors were: in rats, sporadic deaths at the highest dose level, in dogs, clinical and behavioural changes, believed to be due to perturbations of 5-HT1D regulated central nervous system pathways.
In toxicity studies in which zolmitriptan nasal spray formulation was administered to rats (6 times daily for up to 6 months) and monkeys (8 times daily for 1 month) by the nasal route, the formulation was generally well tolerated. In monkeys, there was no indication of systemic toxicity or local irritation in the nasal cavity. In rats, a reversible minimal or mild rhinitis and nasopharyngitis was observed after 1 month at 72 mg/kg/day, with a no effect level of 18 mg/kg/day. This corresponds to approximately four-fold the maximum daily human exposure when expressed in terms of exposure per unit area of the nasal epithelium. There was no similar finding after 6 months of intranasal dosing at 72 mg/kg/day. Zolmitriptan nasal spray formulation is practically a non-irritant to the rabbit eye.
Genotoxicity: Zolmitriptan was mutagenic in an Ames test, in 2 of 5 strains of Salmonella typhimurium tested, in the presence of, but not in the absence of, metabolic activation. It was not mutagenic in an in vitro mammalian gene cell mutation (CHO/HGPRT) assay. The nasal spray formulation was not mutagenic in two further Ames tests. Zolmitriptan was clastogenic in an in vitro human lymphocyte assay both in the absence of and the presence of metabolic activation. Zolmitriptan was not clastogenic in an in vivo mouse micronucleus assay. In three rat bone marrow micronucleus assays with the nasal spray formulation, the results overall were negative. In a mouse bone marrow micronucleus assay with the nasal spray formulation, there were sporadic increases in micronucleus erythrocytes, but the results were equivocal. Zolmitriptan was not genotoxic in an unscheduled DNA synthesis study.
Carcinogenicity: Carcinogenicity studies by oral gavage were carried out in rats and mice at doses up to 400 mg/kg/day. In mice the total exposure at the highest dose level was approximately 800 times that seen after a single 10 mg dose in humans and there was no effect on tumour type or incidence. In male rats at this dose level, where total exposure was approximately 3000 times that seen after a single 10 mg dose in humans, there was an increase in the incidence of thyroid follicular hyperplasia and benign adenomata. This has been shown to be due to an increase in thyroxine clearance caused by zolmitriptan at this dose level with a resultant chronic stimulation of the thyroid. There was no effect on tumour profile at the dose level of 100 mg/kg/day that gave an exposure multiple of approximately 800.
Reproductive and Developmental Toxicology: Reproductive studies in male and female rats, at dose levels limited by toxicity, revealed no effect on fertility or reproduction. Evaluation of experimental animal studies does not indicate direct teratogenic effects. However, some findings in embryotoxicity studies suggested impaired embryo viability.
Reproduction studies in rats and rabbits dosed during the period of organogenesis have been performed at levels limited by maternal toxicity. In rats dosed orally by gavage at 1200 mg/kg/day, giving a total exposure 3000 - 5000 times that seen following a single 10 mg dose in humans, there was a slight increase in early resorptions but no effect on fetal malformations. At a dose of 400 mg/kg/day in rats, an exposure multiple of approximately 1100, there were no effects of any kind on the fetus. The maximum achieved dose in rabbits was 30 mg/kg/day that gave a total exposure 30 - 40 times that seen following a single 10 mg dose in humans.
In the teratology studies, the exposure to zolmitriptan and the metabolites were not significantly different between pregnant and non-pregnant rats. However, in female rabbits, there appeared to be an increase in exposure over the dosing period. After chronic dosing to the dog, there was a slight variation in exposure to the N-oxide metabolite that increased relative to zolmitriptan.
Juvenile Toxicity: No dedicated juvenile toxicity studies have been performed for zolmitriptan.
Special Toxicology: When pigmented rats were given a single oral dose of 10 mg/kg of radiolabelled zolmitriptan, the radioactivity in the eye after 7 days, the latest time point examined, was still 75% of the values measured after 4 hours. This suggests that zolmitriptan and/or its metabolites may bind to the melanin of the eye. Because there could be accumulation in melanin rich tissues over time, it raises the possibility that zolmitriptan could cause toxicity in these tissues after extended use. However, no effects on the retina related to treatment with zolmitriptan were noted in any of the toxicity studies.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrZOMIG RAPIMELT® (zolmitriptan orally disintegrating tablets, 2.5 mg) submission control 282422, Product Monograph, Xedition Pharmaceuticals Inc. (February 24, 2025)