


Product Monograph - Zyloprim 100
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Tablets / 100 mg, 200 mg and 300 mg | starch, lactose, magnesium stearate, povidone. In addition the 300 mg tablets also contain FD&C Yellow#6 Lake. |
INDICATIONS AND CLINICAL USE
ZYLOPRIM® (allopurinol) tablets are indicated for:
- treatment of gout, either primary, or secondary to hyperuricemia which occurs in blood dyscrasias and their therapy.
- treatment of primary or secondary uric acid nephropathy, with or without accompanying signs or symptoms of gout.
- prophylactically, to prevent tissue urate deposition or renal calculi in patients with leukemias, lymphomas or other malignancies, receiving antineoplastic treatment (radiation or cytotoxic drugs) which might induce increased uricemia levels. Also, in the therapy and prophylaxis of acute urate nephropathy and resultant renal failure in patients with neoplastic disease who are particularly susceptible to hyperuricemia and uric acid stone formation (especially after radiation therapy or use of antineoplastic drugs).
- prevention of the occurrence and recurrence of uric acid stones or gravel and renal calcium lithiasis in patients with hyperuricemia and/or hyperuricosuria.
CONTRAINDICATIONS
- ZYLOPRIM® (allopurinol) should not be given to patients who are hypersensitive to allopurinol or who have previously developed a severe reaction to this drug or to any ingredient in the formulation. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
- ZYLOPRIM® is contraindicated in nursing mothers and in children (except in those with hyperuricemia secondary to malignancy).
WARNINGS AND PRECAUTIONS
General
ZYLOPRIM® (allopurinol) should be discontinued immediately at the appearance of a skin rash, as the rash may be, in some instances, followed by a more severe hypersensitivity reaction (See ADVERSE REACTIONS).
Due to occasional occurrence of drowsiness, patients should be alerted to the need for precautions when engaging in activities where alertness is mandatory.
Adequate therapy with ZYLOPRIM® will lead to dissolution of large uric acid renal pelvic stones, with the remote possibility of impaction in the ureter.
Asymptomatic hyperuricemia per se is generally not considered an indication for use of ZYLOPRIM®. Fluid and dietary modification with management of the underlying cause may correct the condition.
ZYLOPRIM® treatment should not be started until an acute attack of gout has completely subsided, as further attacks may be precipitated.
Acute gouty attacks may be precipitated at the start of treatment with ZYLOPRIM® in new patients, and these may continue even after serum uric acid levels begin to fall. Prophylactic administration of colchicine is advisable, particularly in new patients and in those where the previous attack rate has been high. In addition, it is recommended that the patient start with a low dose of ZYLOPRIM® (100 mg and 200 mg daily) and the dose be built up slowly until a serum uric acid level of 6 mg/100 mL or less is attained (see DOSAGE AND ADMINISTRATION). If acute gouty attacks develop in patients receiving allopurinol, treatment should continue at the same dosage while the acute attack is treated with a suitable anti inflammatory agent.
In conditions where the rate of urate formation is greatly increased (e.g., malignant disease and its treatment; Lesch Nyhan syndrome), the absolute concentration of xanthine in urine could, in rare cases, rise sufficiently to allow deposition in the urinary tract. This risk may be minimized by adequate hydration to achieve optimal urine dilution.
Since adverse reactions such as somnolence, vertigo and ataxia have been reported in patients receiving allopurinol, patients should exercise caution before driving, using machinery or participating in dangerous activities until they are reasonably certain that allopurinol does not adversely affect performance.
Hepatic/Renal
Reduced doses should be administered to patients with renal or hepatic impairment. The drug should be withdrawn if increased abnormalities in hepatic or renal functions appear. Patients under treatment for hypertension or cardiac insufficiency, for example with diuretics or ACE inhibitors, may have some concomitant impairment of renal function and allopurinol should be used with care in this group.
Special Populations
Pregnant Women: ZYLOPRIM® is not recommended for use during pregnancy or in women of childbearing potential unless in the judgement of the physician, the potential benefits outweigh the possible risk to the fetus.
Nursing Women: Reports indicate that allopurinol and oxipurinol are excreted in human breast milk. Concentrations of 1.4 mg/litre allopurinol and 53.7 mg/litre oxipurinol have been demonstrated in breast milk from a woman taking ZYLOPRIM® 300 mg/day. However, there are no data concerning the effects of allopurinol or its metabolites on breast fed babies.
Pediatrics: ZYLOPRIM® should not be given to children with the exception of those with hyperuricemia secondary to malignancy or with Lesch-Nyhan syndrome, because safety and effectiveness have not been established in other conditions.
Monitoring and Laboratory Tests: Periodic liver function tests should be performed in all patients on ZYLOPRIM® therapy.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Adverse reactions in association with ZYLOPRIM® (allopurinol) are rare in the overall treated population and are mostly of a minor nature. The incidence is higher in the presence of renal and/or hepatic disorder (See WARNINGS AND PRECAUTIONS).
Skin and Hypersensitivity Reactions
These are the most common reactions and may occur at any time during treatment. They may be pruritic, maculopapular, sometimes scaly, sometimes purpuric and rarely exfoliative. Fixed drug eruptions occur very rarely. ZYLOPRIM® should be withdrawn immediately should such reactions occur. After recovery from mild reactions, ZYLOPRIM® may, if desired, be cautiously reintroduced at a small dose (e.g., 50 mg/day) and gradually increased. If the rash recurs, ZYLOPRIM® should be permanently withdrawn as more severe hypersensitivity reactions may occur.
Skin reactions associated with exfoliation, fever, chills, nausea and vomiting, lymphadenopathy, arthralgia and/or eosinophilia including Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis occur rarely. Associated vasculitis and tissue response may be manifested in various ways including hepatitis, renal impairment and very rarely, seizures. If such reactions do occur, it may be at any time during treatment. ZYLOPRIM® should be withdrawn immediately and permanently. Corticosteroids may be beneficial in overcoming such reactions. When generalized hypersensitivity reactions have occurred, renal and/or hepatic disorders have usually been present particularly when the outcome has been fatal.
Very rarely acute anaphylactic shock has been reported.
Angioimmunoblastic Lymphadenopathy
Angioimmunoblastic lymphadenopathy has been described rarely following biopsy of a generalised lymphadenopathy. It appears to be reversible on withdrawal of ZYLOPRIM®.
Hepatic Function
Rare reports of hepatic dysfunction ranging from asymptomatic rises in liver function tests to hepatitis (including hepatic necrosis and granulomatous hepatitis) have been reported without overt incidence of more generalised hypersensitivity.
Gastrointestinal Disorders
Diarrhea, intermittent abdominal pain, nausea and vomiting were reported. Gastrointestinal disorders diminish if ZYLOPRIM® is taken after meals. Recurrent hematemesis has been reported as an extremely rare event, as has steatorrhoea.
Blood and Lymphatic System
There have been occasional reports of reduction in the number of circulating formed elements of the blood, including agranulocytosis, thrombocytopenia and aplastic anemia, usually in association with renal and/or hepatic disorders or in whom concomitant drugs have been administered which have a potential for causing these reactions.
Miscellaneous
The following adverse effects have been reported occasionally: fever, general malaise, asthenia, headache, vertigo, ataxia, somnolence, coma, depression, paralysis, paraesthesia, taste perversion, stomatitis, changed bowel habit, infertility, hepatic necrosis, abnormal liver function tests, rise in BUN, hyperlipemia, visual disorder, cataracts, macular changes, neuropathy, impotence, diabetes mellitus, furunculosis, alopecia, discoloured hair, angina, hypertension, bradycardia, hematuria, edema, uremia, drowsiness, peripheral neuritis, angioedema and gynecomastia.
DRUG INTERACTIONS
Drug-Drug Interactions
Table 1 Established or Potential Drug-Drug Interactions
Name Effect Clinical comment Ampicilin/Amoxicillin An increase in the frequency
of skin rash has been
reported among patients receiving ampicillin or amoxicillin concurrently with allopurinol compared to patients who are not
receiving both drugs.
The cause of the reported association has not been established. However, it is recommended that in patients receiving allopurinol, an alternative to ampicillin or amoxicillin be used if available.
Chlorpropamide In the presence of
allopurinol, there may be competition in the renal tubule for the excretion of chlorpropamide.
When renal function is poor, the recognized risk of prolonged
hypoglycemic activity of chlorpropamide may be increased if ZYLOPRIM® is given concomitantly.
Coumarin
Anticoagulants
It has been reported that under experimental
conditions allopurinol prolongs the half-life of the anticoagulant, dicumarol.
There have been rare reports of increased effect of warfarin and other coumarin anticoagulants when co-administered with allopurinol, therefore, all patients receiving anticoagulants must be carefully monitored.
Cyclophosphamide,
Doxorubicin,
Bleomycin,
Procarbazine and
Mechloroethamine
Enhanced bone marrow suppression by
cyclophosphamide and other cytotoxic agents has been reported among patients with neoplastic disease, (other than leukemia), in the presence of allopurinol.
However, in a well-controlled study of patients treated with cyclophosphamide, doxorubicin, bleomycin, procarbazine and/or mechloroethamine (mustine hydrochloride) allopurinol did not appear to increase the toxic reaction of these cytotoxic agents.
Cyclosporin Reports suggest that the
plasma concentration of cyclosporin may be increased during concomitant treatment with allopurinol.
The possibility of enhanced cyclosporin toxicity should be considered if the drugs are co-administered.
Didanosine In healthy volunteers and
HIV patients receiving didanosine, plasma
didanosine Cmax and AUC values were approximately doubled with concomitant allopurinol treatment (300 mg daily) without affecting terminal half life.
Therefore, dose reductions of didanosine may be required when used
concomitantly with allopurinol.
Name Effect Clinical comment Mercaptopurine or
Azathioprine
In patients receiving mercaptopurine
(PURINETHOL®) or azathioprine (IMURAN®), the concomitant
administration of 300 to 600 mg of ZYLOPRIM® per day will require a reduction in dose to approximately one-third or one-fourth of the usual dose of mercaptopurine or azathioprine. Subsequent adjustment of doses of mercaptopurine or azathioprine should be made on the basis of therapeutic response and any toxic effects.
Phenytonin Allopurinol may inhibit
hepatic oxidation of
phenytoin.
The clinical significance has not been demonstrated.
Theophylline Inhibition of the metabolism
of theophylline has been reported.
The mechanism of the interaction may be explained by xanthine oxidase being involved in the biotransformation of theophylline in man. Theophylline levels should be monitored in patient starting or increasing allopurinol therapy.
Uricosurics and
Salicylates
The renal clearance of oxypurinol, the major
therapeutically active
metabolite of allopurinol, is increased by uricosuric agents such as probenecid or large doses of salicylate and, as a consequence, the
addition of a uricosuric agent may reduce the inhibition of xanthine oxidase by
oxypurinol.
However, such combined therapy may be useful in achieving minimum serum uric acid levels provided that total urinary uric acid load does not exceed the competence of the patient's renal function.
Vidarabine Evidence suggests that the
plasma half-life of vidarabine is increased in the presence of allopurinol.
When the two products are used concomitantly extra vigilance is necessary to recognize enhanced toxic effects.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Adults
General Considerations
ZYLOPRIM® (allopurinol) is administered orally. The total daily requirement should be divided into 1 to 3 doses. Daily doses up to and including 300 mg ZYLOPRIM® may be taken once a day after a meal. Larger doses should be administered as divided doses of not more than 300 mg. It should be noted that ZYLOPRIM® is generally better tolerated if taken following meals.
Treatment of Gout
The dose of ZYLOPRIM® varies with the severity of the disease. The minimum effective dose is 100 mg to 200 mg. The average is 200 mg to 300 mg per day for patients with mild gout, 400 mg to 600 mg per day for patients with moderately severe tophaceous gout, and 700 mg to 800 mg in severe conditions. The maximal recommended dose is 800 mg per day in patients with normal renal function.
Since allopurinol and its metabolites are excreted only by the kidney, accumulation of the drug can occur in renal failure and the dose of allopurinol should consequently be reduced. With a creatinine clearance of 20 to 10 mL/min., a daily dosage of 200 mg of ZYLOPRIM® is suitable. When the creatinine clearance is less than 10 mL/min., the daily dosage should not exceed 100 mg. With extreme renal impairment (creatinine clearance less than 3 mL/min.), the interval between doses may also need to be lengthened. As no simple method of measuring the blood concentrations of
ZYLOPRIM® is available, the correct size and frequency of dosage for maintaining the serum uric acid just within the normal range is best determined by using the serum uric acid level as an index.
Once the daily dose of allopurinol necessary to produce the desired serum uric acid level has been determined, this dose should be continued until the serum uric acid level indicates a need for dosage adjustment.
Normal serum urate levels are achieved in one to three weeks. The upper limit of normal is about 6 mg percent for men and postmenopausal women and 5 mg percent for premenopausal women. By the selection of the appropriate dose, together with the use of uricosuric agents in certain patients, it is possible to reduce the serum uric level to normal and, if desired, to hold it as low as 2 to 3 mg percent. Combined therapy of ZYLOPRIM® and uricosurics will often result in a reduction in dosage of both agents.
To reduce the possibility of an increase in acute attacks of gout during the early stages of allopurinol administration, it is recommended that the patient start with a low dose of allopurinol (100 mg to 200 mg daily) and increase at weekly intervals by 100 mg until a serum uric acid level of about 6 mg percent or less is attained. Also, a maintenance dose of colchicine should be given prophylactically when allopurinol is begun, and a high fluid intake is advisable.
In patients who are being treated with uricosuric agents, colchicine and/or antiinflammatory agents, it is wise to continue this therapy while adjusting the dosage of ZYLOPRIM® until a normal serum uric acid level and freedom from acute attacks have been maintained for several months. If desired, the patient may then be transferred to ZYLOPRIM® therapy exclusively.
For the Prevention of Uric Acid Nephropathy During the Vigorous Therapy of Neoplastic Disease
Treatment with 600 mg to 800 mg daily for two or three days prior to chemotherapy of X-irradiation is advisable. Treatment should be continued at a dosage adjusted to the serum uric acid level until there is no longer a threat of hyperuricemia and hyperuricosuria.
ZYLOPRIM® treatment can be maintained during the antimitotic therapy for prophylaxis of the hyperuricemia which may arise during the natural crises of the disease. In prolonged treatment, 300 mg to 400 mg of ZYLOPRIM® daily is usually enough to control the serum uric acid level.
It is essential that a daily urinary output of 2 litres or more be maintained during ZYLOPRIM® therapy, and neutral or alkaline urine is desirable.
Prophylaxis of Renal Calcium Lithiasis
The recommended starting dose of ZYLOPRIM® for the prevention of recurrent calcium stones is 200 mg to 300 mg daily as one dose or individual doses. Therapy should be continued indefinitely. Some patients have received maintenance dosages of 200 mg to 300 mg daily for more than 7 years. In some patients, the maintenance dosage may be reduced to 100 mg to 200 mg daily.
Children (6 to 10 years of age)
For the treatment of secondary hyperuricemia associated with malignancies and in the Lesch-Nyhan syndrome, ZYLOPRIM® should be given in doses of 10 mg/kg/day. The response should be evaluated after approximately 48 hours by monitoring serum uric acid and/or urinary uric acid levels and adjusting the dose if necessary.
OVERDOSAGE
Ingestion of up to 22.5 g ZYLOPRIM® (allopurinol) without adverse effect has been reported. Symptoms and signs including nausea, vomiting, diarrhea, and dizziness have been reported in a patient who ingested 20 g allopurinol. Recovery followed general supportive measures.
Massive absorption of ZYLOPRIM® may lead to considerable inhibition of xanthine oxidase activity, which should have no untoward effects unless affecting concomitant medication, especially with mercaptopurine and/or azathioprine. No treatment is normally required provided the drug is withdrawn and adequate hydration is maintained to facilitate excretion of the drug. If considered necessary hemodialysis may be used. If, however, other forms of acute distress are observed, gastric lavage should be considered, otherwise the treatment is symptomatic.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
ZYLOPRIM® (allopurinol) is a structural analogue of hypoxanthine. Reduction in both the serum and urinary uric acid levels is brought about by allopurinol inhibiting the action of xanthine oxidase, the enzyme responsible for the conversion of hypoxanthine to xanthine and xanthine to uric acid. Allopurinol is metabolized to the corresponding xanthine analogue, oxypurinol, which is also an inhibitor of xanthine oxidase. The action of allopurinol in blocking formation of urate differs from that of uricosuric agents which lower the serum uric acid level by increasing urinary excretion of uric acid.
When taken orally, allopurinol is rapidly absorbed and rapidly metabolized. The main metabolite is oxypurinol, which is itself a xanthine oxidase inhibitor. Allopurinol and its metabolites are excreted by the kidney. The renal handling is such that allopurinol has a plasma half-life of about one hour, whereas that of oxypurinol exceeds 18 hours. Thus, the therapeutic effect can be achieved by a once a day dosage of ZYLOPRIM® in patients taking 300 mg or less per day.
Administration of allopurinol generally results in a fall in both serum and urinary uric acid within 2-3 days. The magnitude of the decrease can be adjusted to a certain extent by varying the dose of allopurinol. The serum uric acid levels fall gradually and therefore a week or more of allopurinol treatment may be necessary before the full effect is obtained. Uric acid returns to pre-treatment levels slowly, usually after a cessation of therapy. This is due primarily to the accumulation and slow clearance of oxypurinol. In some patients, particularly those with tophaceous gout, a significant fall in urinary uric acid excretion may not occur, possibly due to the mobilization of urate from tissue deposits as the serum uric acid level begins to fall.
The combined increase in hypoxanthine and xanthine excreted in the urine is usually, but not always, considerably less than the accompanying decline in urinary uric acid. This may be due to pseudofeedback inhibition of purine biosynthesis by allopurinol ribotide.
It has been shown that reutilization of both hypoxanthine and xanthine for nucleotide and nucleic acid synthesis is markedly enhanced when their oxidations are inhibited by allopurinol. This reutilization and the normal feedback inhibition which would result from an increase in available purine nucleotides serve to regulate purine biosynthesis, and, in essence, the defect of the over-producer of uric acid is thereby compensated.
Innate deficiency of xanthine oxidase, which occurs in patients with xanthinuria, as an inborn error of metabolism has been shown to be compatible with comparative well-being. While urinary levels of oxypurines attained with full doses of allopurinol may in exceptional cases equal those (250-600 mg/day) which in xanthinuric subjects have caused formation of urinary calculi, they usually fall in the range of 50-200 mg and no evidence of renal damage has been clinically observed. Xanthine crystalluria has been reported in a few exceptional cases. The serum concentration of oxypurines in patients receiving allopurinol is usually in the range of 0.3 mg to 0.4 mg percent, compared with a normal level of approximately 0.15 mg percent. A maximum of 0.9 mg percent was observed when the serum urate was lowered to less than 2 mg percent by high doses of the drug. In one exceptional case, a value of 2.7 mg percent was reached. These are far below the saturation level at which precipitation of xanthine or hypoxanthine would be expected to occur so that tissue deposition is unlikely and has not been observed to date. The solubilities of uric acid and xanthine in the serum are similar (about 7 mg percent) while hypoxanthine is much more soluble.
The finding that the renal clearance of oxypurines is at least ten times greater than that of uric acid explains the relatively low serum oxypurine concentration at a time when the serum uric acid level has decreased markedly. At serum oxypurine levels of 0.3 to 0.9 mg percent, oxypurine: inulin clearance ratios were between 0.7 and 1.9. The glomerular filtration rate and urate clearance in patients receiving allopurinol do not differ significantly from those obtained prior to therapy. The rapid renal clearance of oxypurines suggests that allopurinol therapy should be of value in allowing a patient with gout to increase his total purine excretion.
STORAGE AND STABILITY
ZYLOPRIM® (allopurinol) should be stored between 15 and 30°C.
DOSAGE FORMS, COMPOSITION AND PACKAGING
ZYLOPRIM® (allopurinol) 100 mg tablets are available in bottles of 100. Each white, round, flat-faced, bevel-edged tablet contains 100 mg allopurinol and is scored on one side with ZYLOPRIM®/U4A.
ZYLOPRIM® 200 mg tablets are available in bottles of 100. Each white to off-white, round, biconvex tablet contains 200 mg allopurinol and is scored on one side with ZYLOPRIM®/F9B.
ZYLOPRIM® 300 mg tablets are available in bottles of 100. Each peach- coloured, round, biconvex tablet contains 300 mg allopurinol and is scored on one side with ZYLOPRIM®/C9B.
Each ZYLOPRIM® 100 mg, 200 mg and 300 mg tablet contains the following nonmedicinal ingredients: corn starch, lactose, magnesium stearate and povidone. In addition, the 300 mg tablet also contains FD&C yellow #6 Lake. 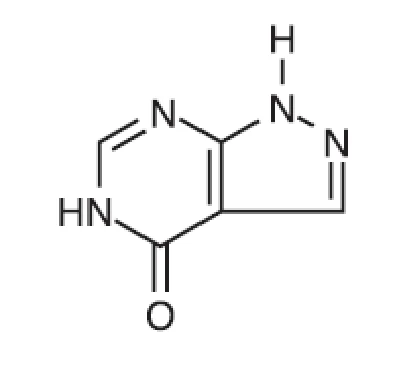
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: allopurinol
Chemical name: 1,5-dihydro-4H-pyrazolo[3,4-d]pyrimidin-4-one
Molecular formula and molecular mass: C5H4N4O, 136.11
Structural formula:
Physicochemical properties:
Description: Allopurinol is a position isomer of the natural purine base hypoxanthine. It is a colourless, odourless, tasteless, solid, insoluble in cold water and dissolves in about 250 parts of hot water. It can be dissolved in water by the addition of one molecular equivalent of sodium hydroxide.
TOXICOLOGY
Animals
In mice, the LD50 is 700 mg/kg p.o. In rats, the acute LD50 is greater than 6 g/kg p.o.
In a 13-week feeding experiment in rats, 2 of 10 rats treated at a drug level of 72 mg/kg/day, and 4 of 10 rats treated with 225 mg/kg/day, died before the completion of the experiment. Both groups exhibited renal tubular damage due to the deposition of xanthine that was more extensive at the higher dose. In chronic feeding experiments, rats showed no toxic effects at a level of 14 mg/kg/day after one year. At a level of 24 mg/kg/day for one year, the rats showed very slight depression of weight gain and food intake, and five out of ten of the animals showed minor changes in the kidney tubules of the type exhibited by the rats on the higher doses described above.
Dogs survived oral dosing at 30 mg/kg/day for one year with nil to minor changes in the kidney and no other significant abnormalities. At 90 mg/kg/day for one year, there was some accumulation of xanthine in the kidneys with resultant chronic irritation and slight tubular changes. Occasional hemosiderin-like deposits were seen in the reticuloendothelial system. A higher dose (270 mg/kg/day) resulted in large concretions in the renal pelves, with severe destructive changes in the kidney secondary to xanthine accumulation. The deposit of xanthine appears to be a f unction of both the metabolic turnover of purines (which is proportionately larger in the smaller animals) and the degree of inhibition of xanthine oxidase.
Reproductive studies in rats and rabbits indicated that allopurinol did not affect litter size, the mean weight of the progeny at birth or at three weeks postpartum, nor did it cause an increase in the number of animals born dead or with malformations.
Cytogenetic studies show that allopurinol does not induce chromosome aberrations in human blood cells in vitro at concentrations up to 100 µg/mL and in vivo at doses up to 600 mg/day for a mean period of 40 months.
Allopurinol does not produce nitroso compounds in vitro or affect lymphocyte transformation in vitro.
Evidence from biochemical and other cytological investigations strongly suggests that allopurinol had no deleterious effects on DNA at any stage of the cell cycle and is not mutagenic.
No evidence of carcinogenicity has been found in mice and rats treated with allopurinol for up to 2 years.
One study in mice receiving intraperitoneal doses of 50 or 100 mg/kg on days 10 or 13 of gestation resulted in fetal abnormalities, however in a similar study in rats at 120 mg/kg on day 12 of gestation no abnormalities were observed. Extensive studies of high oral doses of allopurinol in mice up to 150 mg/kg/day during days 8 to 16 of gestation produced no teratogenic effects.
An in vitro study using fetal mouse salivary glands in culture to detect embryotoxicity indicated that allopurinol would not be expected to cause embryotoxicity without also causing maternal toxicity.
REFERENCES
- 1. Elion GB, Kovensky A, Hitchings GH. Metabolic studies of allopurinol, an inhibitor of xanthine oxidase. Biochem Pharmacol. 15(7):863-880, 1966.
- 2. Elion GB, Yu TF, Gutman AB, Hitchings GH. Renal clearance of oxipurinol, the chief metabolite of allopurinol. Amer. J. Med. 45(1):69-77, 1968.
- 3. Krakoff, IH. Clinical pharmacology of drugs which influence uric acid production and excretion Clin. Pharmac. Ther. 8(1):124-138, 1967.
- 4.
Muggia F, Ball TJ Jr., Ultmann JE. Allopurinol in the Treatment of Neoplastic
Disease Complicated by Hyperuricemia, Archs. Intern. Med. 120(1):12-18, 1967.
- 5.
Rundles RW, Metz EN, Silberman HR. Allopurinol in the Treatment of Gout;
Ann. Intern. Med. 64(2):229-258, 1966.
- 6.
Rundles RW, Wyngaarden JB, Hitchings GH. Effects of a Xanthine Oxidase
Inhibitor on Thiopurine Metabolism, Hyperuricemia and Gout. Trans. Ass. Am. Phycns. 76:126-140, 1963.
- 7.
Seegmiller JE, Grayzel AI. Use of the Newer Uricosuric Agents in the
Management of Gout. J. Am. Med. Ass. 173:1076-1080, 1960.
- 8.
Woodbury JF, Mehta DM, Morse WI. Allopurinol in the Treatment of Gout;
Nova Scotia Med. Bull., 48:103-107 (August) 1969.
- 9.
Yue TF, Gutman AB. Effect of Allopurinol (4- hydroxypyrazolo-(3,4-D)
pyrimidine) on Serum and Urinary Uric Acid in Primary and Secondary Gout. Am. J. Med. 37:885-898, 1964.
- 10.
Smith MJ. Placebo versus Allopurinol for Renal Calculi; J. Urol. 117(6):690-692,
1977.
- 11. Coe FL. Treated and Untreated Recurrent Calcium Nephrolithiasis in Patients with Idiopathic Hypercalciuria, Hyperuricosuria, or No Metabolic Disorder; Ann. Intern. Med. 87(4):404-410, 1977.
- 12.
Coe FL, Raisen L. Allopurinol Treatment of Uric-Acid Disorders in the Calcium-
Stone Formers. Lancet. 1(7795):129-131, 1973.
- 13.
Coe FL, Kavalach AG. Hypercalciuria and Hyperuricosuria in Patients with
Calcium Nephrolithiasis; New Engl. J. Med. 291(25):1344-1350, 1974.
- 14.
Vabusek M. Prevention of Urinary Calculi in Hyperuricemia and Gout.
Urolithiasis Research, Ed. Fleisch et al., Plenum Press, New York, pp. 565-568, 1976.
- 15. Friedman HM, Grasela T. Adenine arabinoside and allopurinol possible adverse drug interaction. New Engl. J. Med. 304: 423, 1981.
- 16.
Yokochi K, Yokochi A, Chiba K, et al. Phenytoin--allopurinol interaction:
Michaelis-Menten kinetic parameters of phenytoin with and without allopurinol in a child with Lesch-Nyhan syndrome. Therap. Drug Monitoring. 4(4): 353-357, 1982.
- 17. Manfredi RL, Vesell ES. Inhibition of theophylline metabolism by long term allopurinol administration. Clin. Pharmac. Ther. 29(2): 224-229, 1981.
- 18. Jick H, Porter JB. Potentiation of ampicillin skin reactions by allopurinol or hyperuricaemia. J. Clin. Pharm. 21: 456 468, 1981.
- 19. Boston Collaborative Drug Surveillance Program. Allopurinol and cytotoxic drugs. Interaction in relation to bone marrow depression. J. Am. Med. Ass. 227: 1036-1040, 1974.
- 20.
Stolbach L, Begg C, Bennett JM, Silverstein M, Falkson G, Harris DT, et al.
Evaluation of bone marrow toxic reaction in patients treated with allopurinol. J. Am. Med. Ass. 247(3): 334-336, 1982.
- 21.
Stevens SL, Goldman MH. Cyclosporin toxicity associated with allopurinol.
South. Med. J. 85(12): 1265-1266, 1992.
- 22. Gorrie M, Beaman M, Nicholls A, Backwell P. Allopurinol interaction with cyclosporin. Brit. Med. J. 308:113, 1994.