


Product Monograph - Abrysvo
Recent Major Label Changes
| 1 Indications | 10/2025 |
|---|---|
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 10/2025 |
| 4 Dosage and Administration, 4.3 Reconstitution | 10/2025 |
| 4 Dosage and Administration, 4.4 Administration | 10/2025 |
| 7 WARNINGS AND PRECAUTIONS, Guillain-Barré Syndrome | 10/2025 |
| 7 Warnings and Precautions, 7.1.5 Immunocompromised individuals | 2026-04 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics .................................................................................................................. 4
1.2. Geriatrics .................................................................................................................. 4
- 2. Contraindications ............................................................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 4
4.2. Recommended Dose and Dosage Adjustment ......................................................... 4
4.3. Reconstitution .......................................................................................................... 4
4.4. Administration .......................................................................................................... 6
- 5. Overdose ......................................................................................................................... 6
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 6
- 7.
Warnings and Precautions ............................................................................................... 7
General ................................................................................................................................. 7
Concurrent illness ................................................................................................................. 7
Driving and Operating Machinery ......................................................................................... 8
Guillain-Barré Syndrome ....................................................................................................... 8
Hematologic ......................................................................................................................... 8
Hypersensitivity and Anaphylaxis ......................................................................................... 8
Immune ................................................................................................................................ 8
Reproductive Health ............................................................................................................. 8
7.1. Special Populations .................................................................................................. 8
7.1.1. Pregnancy ........................................................................................................ 8
7.1.2. Breastfeeding .................................................................................................. 8
7.1.3. Pediatrics ......................................................................................................... 9
7.1.4. Geriatrics ......................................................................................................... 9
7.1.5. Immunocompromised individuals ................................................................... 9
- 8.
Adverse Reactions ........................................................................................................... 9
8.1. Adverse Reaction Overview ...................................................................................... 9
8.2. Clinical Trial Adverse Reactions .............................................................................. 10
8.5 Post-Market Adverse Reactions ................................................................................ 22
- 9.
Drug Interactions ........................................................................................................... 23
9.4. Drug-Drug Interactions ........................................................................................... 23
- 10.
Clinical Pharmacology ................................................................................................... 24
10.1. Mechanism of Action .............................................................................................. 24
10.2. Pharmacodynamics ................................................................................................ 24
10.3. Pharmacokinetics ................................................................................................... 24
- 11. Storage, Stability, and Disposal ...................................................................................... 24
- 12. Special Handling Instructions ......................................................................................... 25
Part 2: Scientific Information ................................................................................................ 26
- 13. Pharmaceutical Information .......................................................................................... 26
- 14.
Clinical Trials .................................................................................................................. 26
14.1. Clinical Trials by Indication ..................................................................................... 26
- 16. Non-Clinical Toxicology .................................................................................................. 35
Patient Medication Information ........................................................................................... 36
Part 1: Healthcare Professional Information
1. Indications
ABRYSVO (Respiratory Syncytial Virus Stabilized Prefusion F Subunit Vaccine) is a bivalent vaccine indicated for:
- Active immunization of pregnant individuals from 32 through 36 weeks gestational age for the prevention of lower respiratory tract disease (LRTD) and severe LRTD caused by respiratory syncytial virus (RSV) in infants from birth through 6 months of age.
- Active immunization for the prevention of LRTD caused by RSV in individuals 60 years of age and older.
- Active immunization for the prevention of LRTD caused by RSV in individuals 18-59 years of age who are at increased risk for LRTD caused by RSV.
1.1. Pediatrics
The safety and efficacy of Abrysvo in individuals younger than 18 years of age have not been established. Limited data are available in pregnant adolescents and their infants.
1.2. Geriatrics
Clinical studies include participants 65 years of age and older and their data contribute to the overall assessment of safety and efficacy of Abrysvo (see 8 Adverse Reactions and 14 Clinical Trials).
2. Contraindications
Abrysvo is contraindicated in individuals who are hypersensitive to this vaccine or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
4. Dosage and Administration
4.2. Recommended Dose and Dosage Adjustment
Abrysvo is administered intramuscularly as a single dose (0.5 mL) for pregnant individuals in the third trimester of pregnancy (from 32 through 36 weeks gestation), individuals 60 years of age and older, and individuals 18-59 years of age who are at increased risk for LRTD caused by RSV.
4.3. Reconstitution
Parenteral Products:
The lyophilised vaccine (powder) must be reconstituted only with the diluent provided to form Abrysvo.
Table 1 - Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume1 | Concentration per mL2 |
| 2 mL | 0.65 mL | 0.68 mL | 120 mcg per 0.5 mL |
1 Total volume in vial after reconstitution with 0.65 mL Sterile Water diluent
2 Label Claim Volume of Total RSV Antigen Dose
Preparation for administration
For use of vial of RSVpreF vaccine, pre-filled syringe of diluent and vial adapter:
Vial containing lyophilized RSVpreF vaccine
Syringe containing diluent
Vial adapter
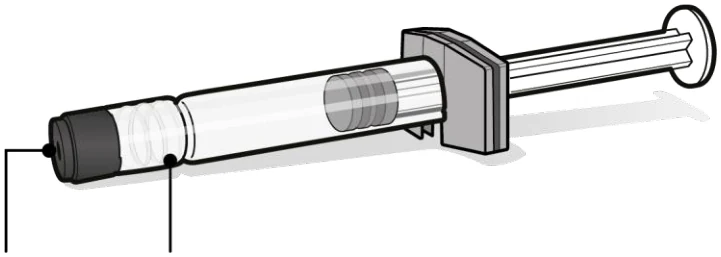
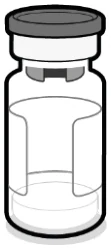
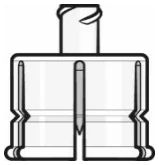
Syringe cap
Luer lock adapter
To form Abrysvo, reconstitute the Lyophilized Antigen Component with the accompanying Sterile Water Diluent Component as described in the panels below.
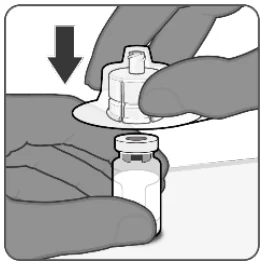
Step 1. Attach vial adapter
- Peel off the top cover from the vial adapter packaging and remove the flip off cap from the vial.
- While keeping the vial adapter in its packaging, centre over the vial’s stopper and connect with a straight downward push. Do not push the vial adapter in at an angle as it may result in leaking. Remove the packaging.
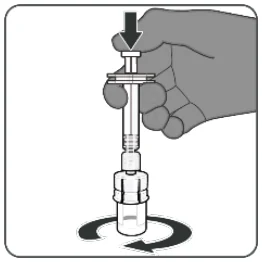
Step 2. Reconstitute lyophilized vaccine component to form Abrysvo
- For all syringe assembly steps, hold the syringe only by the Luer lock adapter. This will prevent the Luer lock adapter from detaching during use.
- Twist to remove the syringe cap, then twist to connect the syringe to the vial adapter. Stop turning when you feel resistance.
- Inject the entire contents of the syringe into the vial. Hold the plunger rod down and gently swirl the vial until the powder is completely dissolved. Do not shake.
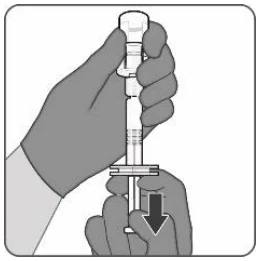
Step 3. Withdraw reconstituted vaccine
- Invert the vial completely and slowly withdraw the entire contents into the syringe to ensure a 0.5 mL dose of Abrysvo.
- Twist to disconnect the syringe from the vial adapter.
- Attach a sterile needle suitable for intramuscular injection.
For use of vial of RSVpreF vaccine and vial of diluent:
- 1. Using a sterile needle and sterile syringe, withdraw the entire contents of the vial containing the diluent.
- 2. Inject the entire contents of the syringe into the vial containing the powder. Gently swirl the vial in a circular motion until the powder is completely dissolved. Do not shake. Withdraw 0.5 mL from the vial containing the reconstituted vaccine.
4.4. Administration
For intramuscular use only. Do not administer Abrysvo intravascularly, intradermally or subcutaneously.
Each 0.5 mL dose is to be injected intramuscularly, into the deltoid muscle, with care to avoid injection into or near nerves and blood vessels.
Different injectable vaccines should always be given at different vaccination sites.
Do not mix Abrysvo with any other vaccines or products in the same syringe.
Reconstituted vaccine for administration
The prepared vaccine is a clear and colourless solution. Visually inspect the vaccine for large particulate matter and discolouration prior to administration. Do not use if large particulate matter or discolouration is found.
5. Overdose
In the event of an overdose, the individual should be monitored and provided with symptomatic treatment as appropriate.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of vaccines for patient immunization record-keeping as well as safety monitoring, health professionals should record the time and date of administration, quantity of administered dose (if applicable), anatomical site and route of administration, brand name and generic name of the vaccine, the product lot number and expiry date.
Abrysvo is a sterile solution for injection supplied as a single dose vial of lyophilized powder containing 120 micrograms (mcg) of RSV stabilized prefusion F protein (60 mcg subgroup A and 60 mcg subgroup B antigens, denoted preF A and preF B) that is reconstituted with sterile water (diluent) provided in a prefilled syringe.
A single dose after reconstitution is 0.5 mL.
Abrysvo is available in:
Vial of RSVpreF vaccine, pre-filled syringe of diluent and vial adapter:
- a carton containing 1 vial of powder, 1 pre-filled syringe of diluent and 1 vial adapter;
- a carton containing 5 vials of powder, 5 pre-filled syringes of diluent and 5 vial adapters;
- a carton containing 10 vials of powder, 10 pre-filled syringes of diluent and 10 vial adapters.
Vial of RSVpreF vaccine and vial of diluent:
- a carton containing 10 vials of powder and 10 vials of diluent.
The vial stopper, the tip cap and plunger stopper of the pre-filled syringe are not made with natural rubber latex.
Table 2 - Dosage Forms, Strengths, Composition and Packaging
Each 0.5 mL dose of the reconstituted Abrysvo includes the following ingredients: 60 mcg of each stabilized RSV prefusion F antigens (A and B), 22.5 mg mannitol, 0.08 mg polysorbate 80, 1.1 mg sodium chloride, 11.3 mg sucrose, 0.11 mg tromethamine, 1.04 mg trometamol hydrochloride, and sterile water as the diluent.
7. Warnings and Precautions
General
As with all injectable vaccines, appropriate medical treatment and supervision must always be readily available in case of a rare anaphylactic event following the administration of the vaccine.
Syncope (fainting) may occur in association with administration of injectable vaccines, including Abrysvo. Procedures should be in place to avoid injury from fainting.
As with other vaccines, the administration of Abrysvo may not protect all vaccine recipients.
Concurrent illness
Vaccination with Abrysvo should be postponed in individuals suffering from an acute febrile illness. However, the presence of a minor infection, such as a cold, should not result in the deferral of
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
| Intramuscular | Lyophilized Powder for Solution (0.5 mL, single dose) 120 mcg of total lyophilized RSV stabilized prefusion F protein | Powder: Mannitol, polysorbate 80, sodium chloride, sucrose, tromethamine, trometamol hydrochloride. Diluent: Sterile Water for injection |
vaccination.
Driving and Operating Machinery
Abrysvo is unlikely to affect your ability to drive or use machines.
Guillain-Barré Syndrome
The results of a post-marketing observational study in individuals ≥65 years of age suggest an increased risk of Guillain-Barré syndrome during the 42 days following vaccination with Abrysvo (see 8.5 Post-Market Adverse Reactions).
Healthcare professionals should be alert to signs and symptoms of Guillain-Barré syndrome to ensure correct diagnosis, in order to initiate adequate supportive care and treatment, and to rule out other causes.
Hematologic
As with other vaccines administered intramuscularly, Abrysvo must be administered with caution to individuals with thrombocytopenia or a coagulation disorder since bleeding may occur following an intramuscular administration.
Hypersensitivity and Anaphylaxis
Medical treatment and supervision should always be readily available in case of a rare anaphylactic event following the administration of Abrysvo (see 2 Contraindications).
Immune
Immunocompromised individuals, including those receiving immunosuppressive therapy, may have a diminished immune response to Abrysvo (see 7.1.5 Immunocompromised individuals).
Reproductive Health
Female and Male Potential
No human data on the effect of Abrysvo on fertility are available. Animal studies do not indicate direct or indirect harmful effects with respect to female fertility (see 16 Non-Clinical Toxicology).
7.1. Special Populations
7.1.1. Pregnancy
Abrysvo has been studied in pregnant individuals from 24 weeks through 36 weeks of gestation (see 14 Clinical Trials).
7.1.2. Breastfeeding
It is unknown whether Abrysvo is excreted in human milk. No safety signals were detected in breastfed newborns of vaccinated mothers in a clinical trial.
7.1.3. Pediatrics
The safety and efficacy of Abrysvo in non-pregnant individuals younger than 18 years of age have not been established.
7.1.4. Geriatrics
Abrysvo has been studied in the geriatric population (see 14 Clinical Trials).
7.1.5. Immunocompromised individuals
The safety and immunogenicity of Abrysvo in immunocompromised individuals 18 years of age and older was evaluated in a Phase 3 clinical trial (see Sections 8.1 Adverse Reaction Overview and 14 Clinical Trials).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The safety profile of Abrysvo presented in section 8.2 for pregnant individuals ≤49 years of age is based on data from the pivotal Phase 3 randomized, placebo-controlled, double-blind, multicentre clinical trial C3671008 (NCT04424316). The trial was conducted in the Northern Hemisphere (United States, Japan, Taiwan, Spain, Gambia, Netherlands, Finland, Mexico, Philippines, Denmark, Canada, and South Korea) and Southern Hemisphere (South Africa, Argentina, Chile, New Zealand, Brazil, and Australia) involving 7,420 maternal participants who were randomized to receive Abrysvo (n = 3,711) or placebo (n = 3,709). The safety population comprised 7,385 maternal participants, 3,697 of whom received Abrysvo and 3,688 who received placebo and 7,305 infant participants passively exposed to maternal antibodies following vaccination with Abrysvo (n = 3,658) or placebo (n = 3,647). Maternal participants were followed for 6 months postpartum; the infant participants in the first year of the study were followed for up to 24 months while those in the second year of the study were followed for up to 12 months.
Supportive safety data were generated from the Phase 2b randomized, placebo-controlled, observer-blind multicentre clinical trial (C3671003, NCT04032093) conducted in the Northern Hemisphere (United States) and Southern Hemisphere (Argentina, Chile and South Africa) involving 232 maternal participants who received Abrysvo (n = 115) or placebo (n = 117) and their corresponding 230 infant participants passively exposed to maternal antibodies following vaccination with Abrysvo (n = 114) or placebo (n = 116). Maternal and infant participants were followed for up to 12 months postpartum.
The safety profile for Abrysvo presented in section 8.2 for adult participants 60 years of age and older is based on data generated from the pivotal Phase 3 randomized, placebo-controlled, double-blind, muticentre clinical trial (C3671013, NCT05035212) conducted in the Northern Hemisphere (United States, Japan, Netherlands, Canada and Finland) and Southern Hemisphere (Argentina and South Africa). The safety population comprised 36,862 adult participants who received Abrysvo (n = 18,574) or placebo (n = 18,288). Study participants were planned to be followed for up to 25 months.
The safety profile of Abrysvo presented in section 8.2 for adult participants 18 through 59 years of age is based on data generated from interim safety analysis of a Phase 3 multicentre, randomised, double-blind, placebo-controlled trial (C3671023, NCT05842967) conducted in the United States involving 678 individuals at increased risk of developing lower respiratory tract disease caused by RSV due to certain chronic medical conditions who received Abrysvo (n = 453) or placebo (n = 225).
Adverse reactions are listed according to the following frequency categories: Very common (≥1/10); Common (≥1/100 to <1/10); Uncommon (≥1/1,000 to <1/100); Rare (≥1/10,000 to <1/1,000); Very rare (<1/10,000).
Adverse reactions reported are listed, in Table 3, per system organ class, in decreasing order of seriousness.
| Table 3 - Adverse reactions following administration of Abrysvo | |||||||||
Adverse Drug Reactions Study C3671008 Pregnant individuals ≤49 years N=3,697 | Adverse Drug Reactions Study C3671013 Individuals ≥60 years N=18,574 | ||||||||
| Immune system disorders | |||||||||
| Hypersensitivity | --- | Very rare | |||||||
| Nervous system disorders | |||||||||
| Headache | Very common | --- | |||||||
| Musculoskeletal and connective tissue disorders | |||||||||
| Muscle pain | Very common | --- | |||||||
| General disorders and administration site conditions | |||||||||
| Vaccination site pain | Very common | Very common | |||||||
| Vaccination site redness | Common | Common | |||||||
| Vaccination site swelling | Common | Common | |||||||
Immunocompromised individuals 18 years of age and older
In a Phase 3 single-arm, open-label, multicentre study (C3671023 Substudy B, NCT05842967), a total of 203 immunocompromised adults ≥18 years of age (96 participants 18 to <60 years of age and 107 participants ≥60 years of age) received 2 doses of RSVpreF (120 µg) with an interval of 1 month. Among of 203 participants, 47.8% had an autoimmune inflammatory disorder with active immunomodulator therapy; 36.9% had a history of solid organ transplant (SOT); 15.3% had end stage renal disease and were on hemodialysis; and 2.5% were on therapy for advanced NSCLC. This substudy was conducted at 11 sites in the United States.
All solicited local reactions were mild to moderate in severity and the majority had a median duration of 1-3 days. Reporting of local reactions trended lower after dose 1 than dose 2. Pain at the injection site was the most frequently reported local reaction. Solicited systemic reactions were mostly mild to moderate in severity and the majority had a median duration of 1-4 days, with reporting of any systemic reaction similar after each dose. The most frequently reported systemic reaction was fatigue. Severe systemic reactions were reported in 2% and 6% of participants 18 to <60 years and ≥60 years of age, respectively, after any dose.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Infants from birth through 6 months of age by active immunization of pregnant individuals
Of the maternal participants in the pivotal Study C3671008, 65% were White, 20% were Black or African American, 13% were Asian, and 29% were Hispanic/Latino. The median maternal age at the time of study vaccination was 29 years (range 14 to 47 years). The median gestational age at vaccination was 31 weeks and 2 days (range 24-36.9 weeks).
The median infant gestational age at birth was 39 weeks and 1 day (range 27 weeks and 3 days to 44 weeks and 2 days).
Among maternal participants, the most frequently reported adverse reactions in Study C3671008 were vaccination site pain, fatigue, headache and muscle pain.
Solicited Adverse Reactions
Maternal Participants
In Study C3671008, all maternal participants were monitored for solicited local and systemic adverse reactions using e-diary during the 7 days following administration of Abrysvo or placebo. Solicited local and systemic reactions reported within 7 days after vaccination in Study C3671008 are presented in Tables 4 and 5.
The majority of solicited local and systemic reactions in maternal participants were mild to moderate in severity and resolved within 2-3 days of onset.
Table 4 - Percentage of Maternal Participants with Solicited Local Adverse Reactions reported, by maximum severity, within 7 Days after Vaccination – Safety Population (Study C3671008)a
| Local Reactions | ABRYSVO N=3,678b n (%) | PLACEBO N=3,651b n (%) | |||||
|---|---|---|---|---|---|---|---|
| Injection site painc | |||||||
| Anyd | 1496 (40.7) | 371 (10.2) | |||||
| Severe | 4 (0.1) | 0 (0) | |||||
| Rednesse | |||||||
| Anyd | 265 (7.2) | 8 (0.2) | |||||
| Severe | 5 (0.1) | 0 (0) | |||||
| Swellinge | |||||||
| Anyd | 228 (6.2) | 8 (0.2) | |||||
| Severe | 3 (<0.1) | 0 (0) | |||||
a NCT04424316 (C3671008) b N = number of participants who provided e-diary data for a specific reaction after vaccination. c Mild: does not interfere with activity; moderate: interferes with activity; severe: prevents daily activity. d Any includes all participants who reported a reaction as mild, moderate, or severe during Day 1 to Day 7 after vaccination. e Mild: >2 cm to 5 cm; moderate: >5 cm to 10 cm; severe: >10 cm. | |||||||
Table 5 - Percentage of Maternal Participants with Solicited Systemic Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671008)a
| Systemic Reactions | ABRYSVO N=3,678b n (%) | PLACEBO N=3,651b n (%) | ||||
|---|---|---|---|---|---|---|
| Systemic Reactions | ABRYSVO N=3,678b n (%) | PLACEBO N=3,651b n (%) | ||||
| Fever (≥38.0°C) | ||||||
| ≥38.0°C | 94 (2.6) | 107 (2.9) | ||||
| ≥38.0°C to 38.4°C | 61 (1.7) | 55 (1.5) | ||||
| >38.5°C to 38.9°C | 29 (0.8) | 42 (1.2) | ||||
| >39.0°C to 40.0°C | 1 (<0.1) | 5 (0.1) | ||||
| >40.0°C | 3 (<0.1) | 5 (0.1) | ||||
| Fatiguec | ||||||
| Anyd | 1696 (46.1) | 1599 (43.8) | ||||
| Severe | 49 (1.3) | 52 (1.4) | ||||
| Headachec | ||||||
| Anyd | 1141 (31.0) | 1009 (27.6) | ||||
| Severe | 15 (0.4) | 13 (0.4) | ||||
| Muscle painc | ||||||
| Anyd | 977 (26. 6) | 626 (17.1) | ||||
| Severe | 14 (0.4) | 12 (0.3) | ||||
| Nauseac | ||||||
| Anyd | 734 (20.0) | 705 (19.3) | ||||
| Severe | 8 (0.2) | 8 (0.2) | ||||
| Joint painc | ||||||
| Anyd | 426 (11.6) | 384 (10.5) | ||||
| Severe | 6 (0.2) | 3 (<0.1) | ||||
| Diarrheae | ||||||
| Any | 414 (11.3) | 416 (11.4) | ||||
| Severe | 4 (0.1) | 6 (0.2) | ||||
| Vomitingf | ||||||
| Any | 289 (7. 9) | 254 (7.0) | ||||
| Severe | 7 (0.2) | 2 (<0.1) | ||||
a NCT04424316 (C3671008) b N = number of participants who provided e-diary data for a specific reaction after vaccination. c Mild: does not interfere with activity; moderate: some interference with activity; severe: prevents daily routine activity. d Any includes all participants who reported a reaction as mild, moderate, or severe during Day 1 to Day 7 after vaccination. e Mild: 2 to 3 loose stools in 24 hours; moderate: 4 to 5 loose stools in 24 hours; severe: 6 or more loose stools in 24 hours. f Mild: 1 to 2 times in 24 hours; moderate: >2 times in 24 hours; severe: requires intravenous hydration. | ||||||
Infant Participants
In Study C3671008, solicited local and systemic adverse reactions were not studied in infant participants, who were not directly vaccinated but received passive immunity from their actively immunized parents prior to delivery.
Unsolicited Adverse Events
Maternal Participants
All maternal participants were monitored for unsolicited adverse events during the 28 days following administration of Abrysvo or placebo. Unsolicited adverse events reported within 1 month after vaccination by maternal participants were 14.0% (n = 516) in the Abrysvo group and 13. 2% (n = 488) in the placebo group. The most commonly reported adverse event was premature delivery (2. 2% [n = 82] in the Abrysvo group and 2.0% [n = 73] in the placebo group). Severe adverse events were reported in 1. 8% (n = 66) of the Abrysvo group and 1. 4% (n = 50) of the placebo group.
Within 14 days of vaccination, lymphadenopathy was reported in 2 vaccine recipients and 0 placebo recipients and was considered related to Abrysvo.
Infant Participants
All infant participants were monitored for unsolicited adverse events during the 28 days following delivery as a newborn of a maternal participant administered of Abrysvo or placebo between 24 to 36 weeks gestation. Unsolicited adverse events in infants from birth to 1 month of age were observed in 38.0% (n = 1391) in the Abrysvo group compared to 35.4% (n = 1291) in the placebo group. The adverse event of Neonatal jaundice was observed in 7. 3% (n = 267) in the Abrysvo group versus 6. 9% (n = 250) in the placebo group. Severe adverse events were reported in 4. 6% (n = 168) of the Abrysvo group and 3. 9% (n = 142) of the placebo group.
Serious Adverse Events and Adverse Events of Special Interest
Maternal Participants
All maternal participants were monitored for serious adverse events and adverse events of special interest (e.g. premature delivery and positive SARS-CoV-2 tests) during the 6 months following delivery. Serious adverse events in maternal participants were reported by 16. 6% (n=613) in the Abrysvo group and 15. 8% (n=581) in the placebo group occurring any time during the study, with 4. 3% serious adverse events in the Abrysvo group and 3. 8% in the placebo group occurring within 1 month after vaccination. The most frequently reported serious adverse events were preeclampsia (1.8% [n= 67] in the Abrysvo group and 1.4% [n = 53] in the placebo group) and fetal distress syndrome (1.8% [n = 67] in the Abrysvo group and 1. 8% [n = 65] in the placebo group).
Adverse events of special interest were reported at a similar frequency, 5. 7% (n=212) versus 4. 8% (n=177) and 4.1% (n=153) versus 3. 1% (n=116) for the RSVpreF and placebo groups, respectively for premature delivery and positive SARS-CoV-2 tests when recorded after vaccination to 6 months after delivery.
Infant Participants
All infant participants were monitored for serious adverse events (including congenital anomalies) and adverse events of special interest from birth through 24 months of age for those enrolled in the first year of study, and from birth through 12 months of age for those enrolled in the second year of study. Serious adverse events in infant participants were reported by 19.0% (n = 697) in the Abrysvo group and 18.9% (n=689) in the placebo group occurring any time during the study. The most frequently reported serious adverse event was neonatal jaundice (2.1% [n= 77] in the Abrysvo group and 1.9% [n = 66] in the placebo group). Pregnant individuals with prior pregnancy complications (e.g., history of preterm birth ≤34 weeks gestation, prior stillbirth, neonatal death, previous infant with a known genetic disorder or significant congenital anomaly) could be included, based on the investigators’ judgment, but were generally not enrolled in the study.
At the time of the primary analysis, when 97% of mothers had delivered, a numerical imbalance in preterm births in all Abrysvo recipients compared with all placebo recipients was observed in study C3671008. Preterm birth events occurred in 5.7% (207 out of 3, 659) in the Abrysvo group and 4.7% (172 out of 3, 646) in the placebo group. No observed increase in mortality (1 in RSVpreF, 2 in placebo), was seen in preterm births.
The imbalance of preterm births in infant participants born to mothers immunized with Abrysvo was most pronounced in the 28 through 31 weeks' gestation subgroup. There was also an imbalance noted regarding low birth weight, but only in the earliest gestational age group for maternal immunization (Table 6). The majority of this imbalance came from investigational sites in South Africa and Argentina with no imbalance seen in the aggregate incidence among participants from high income countries such as Canada, as per World Bank Group categories.
| Table 6 - Adverse Events of Premature Baby and Low Birth Weight Baby by Maternal Vaccination Window - Infant Participants - Safety Population (Study C3671008) | |||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ABRYSVO | PLACEBO | ||||||||||||||||
| Gestational Week When Vaccine Administered | Nb | Median Maternal Age (Range) | Premature Babya n (%) | Low Birth Weight Babyc n (%) | Nb | Median Maternal Age (Range) | Premature Babya n (%) | Low Birth Weight Babyc n (%) | |||||||||
| All gestational weeks | 3659 | 29.0 (16 – 45) | 207 (5.7) | 186 (5.1) | 3646 | 29.0 (16 – 47) | 172 (4.7) | 158 (4.3) | |||||||||
| 24 to <28 weeks | 923 | 28.0 (17 – 45) | 63 (6.8) | 66 (7.2) | 893 | 28.0 (17 – 44) | 59 (6.6) | 51 (5.7) | |||||||||
| 28 to <32 weeks | 1069 | 29.0 (17 – 44) | 73 (6.8) | 52 (4.9) | 1113 | 28.0 (16 – 44) | 53 (4.8) | 51 (4.6) | |||||||||
| 32 to <37 weeks | 1667 | 30.0 (16 – 45) | 71 (4.3) | 68 (4.1) | 1640 | 30.0 (16 – 47) | 60 (3.7) | 56 (3.4) | |||||||||
| |||||||||||||||||
Additionally, no increase in overall infant mortality was observed (8 in RSVpreF, 14 in placebo), and no differences were observed in neonatal hospitalization / prolongation of hospitalization in infants overall (405 [11.1%] in RSVpreF, 372 [10.2%] in placebo), or in those born premature (84 [2.3%] in RSVpreF, 81 [2.2%] in placebo). Available data are insufficient to establish or exclude a causal relationship between preterm birth and Abrysvo. As a precaution, the indication for Abrysvo is currently limited to 32 through 36 weeks gestation in maternal participants.
Deaths and Withdrawals from Study
Maternal Participants
All maternal participants were monitored for deaths and withdrawals from the study following administration of Abrysvo or placebo. Approximately 95% of the maternal participants completed the study. There was a single withdrawal due to an adverse event in the placebo group. There were no maternal deaths in the placebo group and one maternal death in the Abrysvo group due to postpartum hemorrhage that was determined to be not likely associated with vaccination.
Infant Participants
All infant participants were monitored for deaths and withdrawals from the study following administration of Abrysvo or placebo. Approximately 91% of the infant participants completed the study. There were no infants withdrawn due to adverse events. Among live born infants, there were 8 (0.2%) deaths in the Abrysvo group and 14 (0.4%) in the placebo group. No deaths in the study were considered related to vaccination.
Adverse Events from Other Studies
In Study C3671003, the safety and immunogenicity of two dose levels of active RSV vaccine (i.e., Abrysvo and a higher dose formulation) with or without an adjuvant (i.e., aluminum hydroxide) vs placebo was investigated in vaccinated maternal participants and their infant participants following delivery. AEs in maternal and infant participants within 1 month after vaccination or birth respectively were reported in a similar frequency across all groups, including placebo, with no clear association with dose level or formulation. In the infants who were born to maternal participants receiving the final selected dose, preterm births occurred in 5.3% (6 out of 114) in the Abrysvo group and 2.6% (3 out of 116) in the placebo group.
Individuals 60 years of age and older
Of the study participants in the pivotal Study C3671013, 50.9% were male and 79.9% were White, 11.8% were Black or African American, and 41.6% were Hispanic/Latino. The median age of participants was 67 years (range 59-97 years).
The most frequently reported adverse reaction in Study C3671013 was vaccination site pain. The majority of reactions were mild to moderate in severity and resolved within 1-2 days of onset.
Solicited Adverse Reactions
In Study C3671013, a subset of study participants was monitored for solicited local and systemic adverse reactions using e-diary during the 7 days following administration of Abrysvo or placebo in 7,116 participants (3,669 Abrysvo participants and 3,447 placebo recipients) from a subset of sites. Solicited local and systemic reactions reported within 7 days after vaccination in Study C3671013 are presented in Tables 7 and 8. Solicited local and systemic reactions had a median duration of 1-2 days.
| Table 7 - Percentage of Adult Participants 60 Years of Age and Older with Solicited Local Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671013)a | |||||
|---|---|---|---|---|---|
| Local Reactions | ABRYSVO N=3,628b n (%) | PLACEBO N=3,447b n (%) | |||
| Injection site painc | |||||
| Anyd | 385 (10.6) | 209 (6.1) | |||
| Severe | 2 (<0.1) | (0) | |||
| Rednessd,e | |||||
| Anyd | 99 (2.7) | 20 (0.6) | |||
| Severe | 4 (0.1) | (0) | |||
| Swellingd,e | |||||
| Anyd | 90 (2.5) | 13 (0.4) | |||
| Severe | 4 (0.1) | 2 (<0.1) | |||
a NCT05035212 (C3671013) b N = number of participants who provided e-diary data for a specific reaction after vaccination. c Mild: does not interfere with activity; moderate: some interference with activity; severe: prevents daily activity. d Any includes all participants who reported a reaction as mild, moderate, or severe during Day 1 to Day 7 after vaccination. e Mild: 2.5 cm to 5 cm; moderate: >5 cm to 10 cm; severe: >10 cm (for data reported from e-diaries). | |||||
| Table 8 - Percentage of Adult Participants 60 Years of Age and Older with Solicited Systemic Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671013)a | ||||||
|---|---|---|---|---|---|---|
| Table 8 - Percentage of Adult Participants 60 Years of Age and Older with Solicited Systemic Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671013)a | ||||||
| Table 8 - Percentage of Adult Participants 60 Years of Age and Older with Solicited Systemic Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671013)a | ||||||
| Systemic Reactions | ABRYSVO N=3,628b n (%) | PLACEBO N=3,447b n (%) | ||||
| Systemic Reactions | ABRYSVO N=3,628b n (%) | PLACEBO N=3,447b n (%) | ||||
| Systemic Reactions | ABRYSVO N=3,628b n (%) | PLACEBO N=3,447b n (%) | ||||
| Fever (≥38.0°C) | ||||||
| ≥38.0°C | 52 (1.4) | 50 (1.5) | ||||
| ≥38.0°C to 38.4°C | 22 (0.6) | 28 (0.8) | ||||
| >38.4°C to 38.9°C | 29 (0.8) | 19 (0.6) | ||||
| >38.9°C to 40.0°C | 1 (<0.1) | 2 (<0.1) | ||||
| >40.0°C | 0 | 1 (<0.1) | ||||
| Fatiguec | ||||||
| Anyd | 568 (15.7) | 510 (14.8) | ||||
| Severe | 12 (0.3) | 5 (0.1) | ||||
| Headachec | ||||||
| Anyd | 468 (12.9) | 412 (12.0) | ||||
| Severe | 4 (0.1) | 3 (<0.1) | ||||
| Muscle painc | ||||||
| Anyd | 370 (10.2) | 293 (8.5) | ||||
| Severe | 8 (0.2) | 3 (<0.1) | ||||
| Joint painc | ||||||
| Anyd | 274 (7.6) | 241 (7.0) | ||||
| Severe | 3 (<0.1) | 2 (<0.1) | ||||
| Nauseac | ||||||
| Anyd | 126 (3.5) | 131 (3.8) | ||||
| Severe | 0 | 3 (<0.1) | ||||
| Vomitinge | ||||||
| Anyd | 33 (0.9) | 31 (0.9) | ||||
| Severe | 0 | 2 (<0.1) | ||||
| Diarrheaf | ||||||
| Anyd | 217 (6.0) | 183 (5.3) | ||||
| Severe | 4 (0.1) | 4 (0.1) | ||||
a NCT05035212 (C3671013) b N = number of participants who provided e-diary data for a specific reaction after vaccination. c Mild: does not interfere with activity; moderate: some interference with activity; severe: prevents daily routine activity. d Any includes all participants who reported a reaction as mild, moderate, or severe during Day 1 to Day 7 after vaccination. | ||||||
e Mild: 1 to 2 times in 24 hours; moderate: >2 times in 24 hours; severe: requires intravenous hydration. f Mild: 2 to 3 loose stools in 24 hours; moderate: 4 to 5 loose stools in 24 hours; severe: 6 or more loose stools in 24 hours. | ||||||
Unsolicited Adverse Events
Unsolicited adverse events occurring within 1 month after vaccination were similar between groups, reported in 10.8% and 10.5% of participants who received Abrysvo and placebo, respectively.
Within 30 days after vaccination, atrial fibrillation was reported in 11 vaccine recipients and 3 placebo recipients (of which 5 in the Abrysvo group and 2 in the placebo group were serious adverse events); the onset of symptoms was 18 to 30 days post vaccination. The currently available information on atrial fibrillation is insufficient to determine a causal relationship to the vaccine. Within 14 days of vaccination, lymphadenopathy was reported in 6 vaccine recipients, considered related to Abrysvo, and 3 placebo recipients. There were no other notable patterns or numerical imbalances between groups for specific categories of unsolicited adverse events.
Serious Adverse Events and Adverse Events of Special Interest
In Study C3671013, SAEs were reported in both the Abrysvo (6.2% )and placebo (6.1%) groups. Three participants in the Abrysvo group had SAEs which were assessed as possibly related to study vaccination: Guillain-Barré syndrome reported 7 days after vaccination (with diagnosis later revised to chronic inflammatory demyelinating polyneuropathy), Miller-Fisher syndrome reported 8 days after vaccination, and hypersensitivity reported 8 hours after vaccination.
Deaths and Withdrawals from Study
AEs leading to death were reported in 157 (0. 8%) RSVpreF recipients and 160 (0. 9%)placebo recipients. None of these deaths were assessed as related to study intervention.
AEs leading to withdrawal from the study were similar in the RSVpreF and placebo groups: 20 (<0.1%) and 17 (<0.1%) participants, respectively. None of the events were assessed as related.
Individuals 18 through 59 years of age at increased risk of LRTD caused by RSV
Of the study participants in the pivotal Study C3671023, 42.6% were male, 68.4% were White, 24% were Black or African American, and 22.1% were Hispanic/Latino. 52.13% were 18 to 49 years and 47.9% were 50 to 59 years. The median age of participants was 49 years.
The most frequently reported adverse reactions in C3671023 Substudy A were vaccination site pain and muscle pain. The majority of solicited local and systemic reactions were mild to moderate in severity and resolved within 1-2 days of onset.
Solicited Adverse Reactions
In Study C3671023, a subset of study participants was monitored for solicited local and systemic adverse reactions using e-diary. The e-diary safety population included 451 participants in the RSVpreF group and 225 in the placebo group with at least 1 day of e-diary data transmitted.) Solicited local and systemic reactions reported within 7 days after vaccination in C3671023 Substudy A are presented in Tables 9 and 10. Solicited local and systemic reactions had a median duration of 1-2 days.
| Table 9 - Percentage of Participants 18 through 59 Years of Age at Increased Risk with Solicited Local Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671023)a | |||||||
|---|---|---|---|---|---|---|---|
| Local Reactions | ABRYSVO N=451b n (%) | PLACEBO N=225b n (%) | |||||
| Injection site painc | |||||||
| Anyd | 159 (35.3) | 24 (10.7) | |||||
| Severe | (0) | (0) | |||||
| Rednessd | |||||||
| Anyd | 27 (6.0) | 1 (0.4) | |||||
| Severe | (0) | (0) | |||||
| Swellingd | |||||||
| Anyd | 32 (7.1) | 2 (0.9) | |||||
| Severe | 1 (0.2) | (0) | |||||
a NCT05842967 (C3671023) b N = number of participants reporting at least 1 response in the e-diary. c Mild: does not interfere with activity; moderate: some interference with activity; severe: prevents daily activity. d Mild is >2.0 cm to 5.0 cm; moderate is >5.0 cm to 10.0 cm; severe is >10.0 cm, or actual toxicity grade reported in the AE CRF. | |||||||
| Table 10 - Percentage of Participants 18 through 59 Years of Age at Increased Risk with Solicited Systemic Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671023)a | |||||||
|---|---|---|---|---|---|---|---|
| Table 10 - Percentage of Participants 18 through 59 Years of Age at Increased Risk with Solicited Systemic Adverse Reactions within 7 Days after Vaccination – Safety Population (Study C3671023)a | |||||||
| Systemic Reactions | ABRYSVO N=451b n (%) | PLACEBO N=225b n (%) | |||||
| Systemic Reactions | ABRYSVO N=451b n (%) | PLACEBO N=225b n (%) | |||||
| Fever (≥38.0°C) | |||||||
| ≥38.0°C | 7 (1.6) | 3 (1.3) | |||||
| ≥38.0°C to 38.4°C | 2 (0.4) | 1 (0.4) | |||||
| >38.4°C to 38.9°C | 5 (1.1) | 2 (0.9) | |||||
| >38.9°C to 40.0°C | (0) | (0) | |||||
| Fatiguec | |||||||
| Anyd | 168 (37.3) | 86 (38.2) | |||||
| Severe | 4 (0.9) | 1 (0.4) | |||||
| Headachec | |||||||
| Anyd | 128 (28.4) | 68 (30.2) | |||||
| Severe | 1 (0.2) | (0) | |||||
| Muscle painc | |||||||
| Anyd | 110 (24.4) | 36 (16.0) | |||||
| Severe | (0) | (0) | |||||
| Joint painc | |||||||
| Anyd | 56 (12.4) | 23 (10.2) | |||||
| Severe | 1 (0.2) | (0) | |||||
| Nauseac | |||||||
| Anyd | 53 (11.8) | 23 (10.2) | |||||
| Severe | (0) | 1 (0.4) | |||||
| Vomitingc | |||||||
| Anyd | 9 (2.0) | 3 (1.3) | |||||
| Severe | (0) | (0) | |||||
| Diarrheac | |||||||
| Any | 67 (14.9) | 38 (16.9) | |||||
| Severe | 3 (0.7) | 2 (0.9) | |||||
a NCT05842967 (C3671023) b N = number of participants reporting at least 1 response in the e-diary. c For data from e-diary, vomiting – mild: 1 to 2 times in 24 hours; moderate: >2 times in 24 hours; severe: requires intravenous hydration. For diarrhea – mild: 2 to 3 loose stools in 24 hours; moderate: 4 to 5 loose stools in 24 hours; severe: 6 or more loose stools in 24 hours. For other systemic events – mild: does not interfere with activity; moderate: some interference with activity; severe: prevents daily routine activity. | |||||||
Unsolicited Adverse Events
Unsolicited adverse events occurring within 1 month after vaccination were reported in 7.1% and 7.6% of participants who received Abrysvo and placebo, respectively.
Serious Adverse Events and Adverse Events of Special Interest
In Study C3671023, SAEs were reported in both the Abrysvo (1.1%) and placebo (3.1%) groups. None were assessed as related.
Deaths and Withdrawals from Study
One AE leading to death was reported in the RSVpreF recipients and was assessed as not related to study intervention.
AEs leading to withdrawal from the study were reported in the RSVpreF and placebo groups at 0.2 % and 0.4 % of participants, respectively. None of the events were assessed as related.
Serious Adverse Events Reported from Other Studies
Anaphylaxis was reported in a participant enrolled in a study (NCT06473519) in the US, with onset of symptoms 10 minutes after vaccination with Abrysvo. The study enrolled healthy female participants 18 years through 49 years of age (n=450).
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified from spontaneous reports during post-marketing use of Abrysvo. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to the vaccine.
Immune System Disorders: Hypersensitivity reactions including rash and urticaria.
Nervous System Disorders: Guillain-Barré syndrome.
Post-marketing Observational Study of the Risk of Guillain-Barré Syndrome following Vaccination with Abrysvo
The association between vaccination with Abrysvo and Guillain-Barré syndrome (GBS) was evaluated among Medicare beneficiaries 65 years of age and older. Using Medicare claims data, between May 2023 through July 2024, vaccinations with Abrysvo were identified through Current Procedural Terminology (CPT)/Healthcare Common Procedure Coding System (HCPCS) codes and National Drug Codes, and potential cases of hospitalized GBS among recipients of Abrysvo were identified through International Classification of Diseases (ICD) codes. GBS diagnoses in claims data were confirmed by medical record review when available.
The risk of GBS following vaccination with Abrysvo was assessed in self-controlled case series analyses using a risk window of 1 to 42 days post-vaccination and a control window of 43 to 90 days post vaccination. The analyses of all GBS cases based on claims data suggest an increased risk of GBS during the 42 days following vaccination with Abrysvo, with an incidence rate ratio (GBS cases in the risk window/control window) of 2.02 (95% CI: 0.93, 4.40) and an estimated 9 excess cases of GBS per million doses administered to individuals 65 years of age and older. The background risk of GBS in a study population influences the excess GBS case estimate and may differ between studies, precluding direct comparison to excess GBS case estimates from other vaccine studies or populations.
The analyses of GBS diagnoses in claims data were supported by analyses of GBS cases confirmed by medical record review and by analyses of GBS cases in individuals who received Abrysvo alone, without other concomitantly administered vaccines. While the results of this observational study suggest an increased risk of GBS with Abrysvo, available evidence is insufficient to establish a causal relationship.
9. Drug Interactions
9.4. Drug-Drug Interactions
Use with other vaccines
Immunogenicity data in healthy non-pregnant women who received concomitant administration of Abrysvo and a tetanus, diphtheria and acellular pertussis vaccine (Tdap) indicated the immune response induced by Abrysvo when administered concomitantly with Tdap was non-inferior to the immune response induced by Abrysvo alone. In addition, immunogenicity data indicated non-inferiority in immune response to the diphtheria and tetanus components. Immune response to the pertussis component of Tdap was lower when Abrysvo and Tdap were administered concomitantly as compared to Tdap administered alone. The clinical relevance of this observation is unknown.
Abrysvo can be administered concomitantly with COVID-19 mRNA vaccine, with or without high dose influenza vaccine administered concomitantly, based on the data from a study in adults 65 years of age and older. Immunologic non-inferiority was demonstrated for concomitant administration of Abrysvo and COVID-19 mRNA vaccine compared to individual administration. Immunologic non-inferiority was also demonstrated for concomitant administration of Abrysvo, COVID-19 mRNA vaccine, and high dose influenza vaccine compared to individual administration. In that analysis, all antigens including RSV A and RSV B NTs, both SARS COV-2 Omicron BA.4/BA.5 strain and reference strain, and each of the four strain-specific haemagglutination inhibition (HAI) titres met the predefined non-inferiority criterion.
Abrysvo can be administered concomitantly with seasonal influenza vaccine (standard dose adjuvanted or high dose unadjuvanted), based on the data from a study in adults 65 years of age and older, in which
Abrysvo was given concomitantly with an inactivated adjuvanted quadrivalent influenza vaccine (QIV) and the above study with Abrysvo, COVID-19 mRNA vaccine and high dose influenza vaccine.
Data on concomitant administration of Abrysvo and vaccines other than those listed above are not available.
Concomitant administration of Abrysvo with Tdap or seasonal influenza vaccines in pregnant subjects has not been studied.
Different injectable vaccines should always be given at different vaccination sites.
Do not mix Abrysvo with other vaccines or medicinal products in the same syringe (see 4.4 Administration).
10. Clinical Pharmacology
10.1. Mechanism of Action
Abrysvo is a bivalent formulation containing two recombinant stabilized RSV prefusion F antigens, each representing the two major virus subgroups, RSV A and RSV B. RSV F can exist in two antigenically distinct forms – prefusion and postfusion. Unlike postfusion F, prefusion F is the active form of the protein and is capable of mediating fusion of virus and host cell membranes during cell entry. Therefore, prefusion F is the primary target of the most potent neutralising antibodies that block RSV infection. Following intramuscular administration, the prefusion F antigens elicit an immune response, which protects against RSV associated lower respiratory tract disease.
In pregnant individuals, the action of neutralising antibodies conferring protection is mediated through passive transfer of these antibodies from mother to infant. Adults 18 years of age and older are protected by active immunization.
10.2. Pharmacodynamics
Not applicable.
10.3. Pharmacokinetics
Not applicable.
- 11. Storage, Stability, and Disposal
Store in a refrigerator between 2°C and 8°C in the original carton.
Do not freeze. Discard if the carton has been frozen.
The unopened vial of vaccine is stable for 5 days when stored at temperatures from 8°C to 30°C.
At the end of this period, Abrysvo should be used or discarded. This information is used to guide healthcare professionals in case of temporary temperature excursions only.
After reconstitution: Abrysvo should be administered immediately (within 4 hours) after reconstitution. Store the reconstituted vaccine between 15°C and 30°C. Do not freeze reconstituted vaccine.
12. Special Handling Instructions
Any unused product or waste material should be disposed of in accordance with local requirements.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Abrysvo (respiratory syncytial virus stabilized prefusion F subunit vaccine) is a bivalent, recombinant, powder for solution vaccine that consists of equal amounts of two stabilized RSV F antigens (RSV subgroup A stabilized prefusion F protein and RSV subgroup B stabilized prefusion F protein), denoted preF A and preF B, representing the two major subgroups A and B, respectively.
Product Characteristics:
Each RSV F antigen (preF A, preF B) is individually manufactured using a recombinant Chinese hamster ovary (CHO) cell line that contains the DNA encoding for the sequence for each antigen and is grown in suspension culture using chemically-defined (CD), animal-derived component-free (ACF) media.
The vaccine is a lyophilized white powder for solution provided in a single-dose vial that must be reconstituted with sterile water (diluent) before use. The final reconstituted solution is clear and colourless, with a dosage strength of 60 mcg of RSV preF A and 60 mcg of RSV preF B (120 mcg total protein) per 0.5 mL dose.
14. Clinical Trials
14.1. Clinical Trials by Indication
Indication 1: Active Immunization Of Pregnant Individuals (Maternal Indication)
Table 9 - Summary of patient demographics for clinical trials in pregnant individuals ≤49 years of age
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| C3671008 | Phase 3, multicentre, randomised, double-blind, placebo controlled global study | 120 mcg Abrysvo (60 mcg subgroup A and 60 mcg subgroup B) Intramuscular single dose of Abrysvo or placebo (1:1 ratio) Total duration of study: approximately 40 months | Abrysvo: 3711 Placebo: 3709 | 29 years (14-47 years) | Female |
| C3671003 | Phase 2b, multicentre, randomised, double-blind, placebo controlled global study | 120 mcg Abrysvo (60 mcg subgroup A and 60 mcg subgroup B, formulated with or without Al(OH)3) 240 mcg Abrysvo (120 mcg A and 120 mcg B, formulated with or without Al(OH)3) Intramuscular single dose of Abrysvo Total duration of study: approximately 26 months | Abrysvo: 462 [Abrysvo 120 mcg without Al(OH)3: 115] Placebo: 117 | 27.1 years (18-42 years) | Female |
C3671008 was a Phase 3, multicentre, randomised, double-blind, placebo-controlled study to assess the efficacy, safety and immunogenicity of Abrysvo in the prevention of RSV associated medically attended lower respiratory tract illness in infants born to healthy individuals vaccinated during pregnancy, and safety and immunogenicity in pregnant individuals. This was a global study, including study sites in both the northern and southern hemispheres, and spanned multiple RSV seasons. The study enrolled healthy pregnant individuals ≤49 years of age who were between 24 and 36 weeks of gestation. A total of 7420 maternal participants were randomized in a 1:1 ratio to receive one single dose (0.5 mL) of either Abrysvo (n=3711) or placebo (n=3709). The dose of RSV prefusion F antigen in Abrysvo was 120 mcg (60 mcg Subgroup A and 60 mcg Subgroup B). The need for revaccination with subsequent pregnancies has not been established.
RSV-associated lower respiratory tract illness was defined as a medically attended visit with a reverse transcription-polymerase chain reaction (RT-PCR) confirmed RSV illness with one or more of the following respiratory symptoms: fast breathing, low oxygen saturation (SpO2 <95% and chest wall indrawing). RSV-associated severe lower respiratory tract illness was defined as meeting the lower respiratory tract illness RSV criteria plus at least one of the following: fast breathing, low oxygen saturation (SpO2 <93%), high-flow nasal cannula or mechanical ventilation, ICU admission for >4 hours and/or failure to respond/unconscious.
Maternal participants with certain high-risk pregnancies were excluded from the study (BMI>40 kg/m2 prior to pregnancy, pregnancies resulting after in vitro fertilisation, preeclampsia, eclampsia, or uncontrolled gestational hypertension, placental abnormalities, polyhydramnios or oligohydramnios, significant bleeding or blood clotting disorder, unstable endocrine disorders, including untreated hyperthyroidism, untreated hypothyroidism or untreated disorders of glucose intolerance).
Demographic characteristics in Study C3671008 were generally similar with regard to age, race and ethnicity among participants who received Abrysvo and those who received placebo. Of the participants who received Abrysvo, 65% were White, 20% were Black or African American and 29% were Hispanic/Latino. The median age of participants was 29 years (range 16 - 45 years). The median gestational age at vaccination was 31 weeks and 2 days. The median infant gestational age at birth was 39 weeks and 1 day (range 27 weeks and 3 days to 43 weeks and 6 days). Among the infants born to maternal participants 51% were male and 49% were female.
Study Results
The study objective was assessment of vaccine efficacy (VE), defined as the relative risk reduction of the endpoint in the Abrysvo group compared to the placebo group, for infant participants born to maternal participants receiving 1 dose of Abrysvo. At the primary analysis, there were two primary efficacy endpoints, assessed in parallel, severe RSV positive medically attended lower respiratory tract illness and RSV positive medically attended lower respiratory tract illness, occurring within 90/120/150/180 days after birth. Secondary efficacy endpoints included hospitalizations due to RSV.
The VE results met the statistical criterion for success (a CI lower bound >20%) for reducing severe medically attended lower respiratory tract illness due to RSV, at all timepoints through 180 days. The VE results did not meet the statistical criterion for success (a CI lower bound >20%) for reducing medically attended lower respiratory tract illness due to RSV; however, clinically meaningful efficacy was observed from 90 days through 180 days after birth.
Vaccine efficacy information is presented in Tables 12 to 14.
| Table 12 - Vaccine efficacy of Abrysvo against severe medically attended lower respiratory tract illness caused by RSV - infants from birth through 6 months of age by active immunization of pregnant individuals – Study C3671008 | ||||||||
| Time period | Abrysvo Number of cases N=3,495b | Placebo Number of cases N=3,480b | VE % (CI)a | |||||
| 90 days | 6 | 33 | 81.8 (40.6, 96.3) | |||||
| 120 days | 12 | 46 | 73.9 (45.6, 88.8) | |||||
| 150 days | 16 | 55 | 70.9 (44.5, 85.9) | |||||
| 180 days | 19 | 62 | 69.4 (44.3, 84.1) | |||||
CI = confidence interval; VE = vaccine efficacy a 99.5% CI at 90 days; 97.58% CI at later intervals b Evaluable efficacy population | ||||||||
| Table 13 - Vaccine efficacy of Abrysvo against medically attended lower respiratory tract illness caused by RSV - infants from birth through 6 months of age by active immunization of pregnant individuals - Study C3671008 | ||||||||
| Time period | Abrysvo Number of cases N=3,495b | Placebo Number of cases N=3,480 b | VE % (CI)a | |||||
| 90 days | 24 | 56 | 57.1 (14.7, 79.8)c | |||||
| 120 days | 35 | 81 | 56.8 (31.2, 73.5) | |||||
| 150 days | 47 | 99 | 52.5 (28.7, 68.9) | |||||
| 180 days | 57 | 117 | 51.3 (29.4, 66.8) | |||||
CI = confidence interval; VE = vaccine efficacy a 99.5% CI at 90 days; 97.58% CI at later intervals b Evaluable efficacy population c The prespecified success criterion (a CI lower bound >20%) was not met for this endpoint | ||||||||
| Table 14 - Vaccine efficacy of Abrysvo against hospitalisation due to RSV - infants from birth through 12 months of age by active immunization of pregnant individuals – Study C3671008 | |||||||||
| Time period | Abrysvo Number of cases N=3,495 | Placebo Number of cases N=3,480b | VE % (CI)a | ||||||
| 90 days | 10 | 31 | 67.7 (15.9, 89.5) | ||||||
| 120 days | 15 | 37 | 59.5 (8.3, 83.7) | ||||||
| 150 days | 17 | 39 | 56.4 (5.2, 81.5) | ||||||
| 180 days | 19 | 44 | 56.8 (10.1, 80.7) | ||||||
| 360 days | 38 | 57 | 33.3 (-17.6, 62.9) | ||||||
CI = confidence interval; VE = vaccine efficacy a 99.17% CI b Evaluable efficacy population | |||||||||
Indication 2: Active Immunization Of Individual 60 years of Age And Older (Older Adult Indication)
Table 15 - Summary of patient demographics for clinical trials in individuals 60 years of age and older
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range)a | Sex |
| C3671013 | Phase 3, multicentre, randomised, double-blind, placebo controlled global study | 120 mcg Abrysvo (60 mcg subgroup A and 60 mcg subgroup B) Intramuscular single dose of Abrysvo or placebo (1:1 ratio) Total duration of study: approximately 29 months | Abrysvo: 18050 (EOS1) 16164 (EOS2) Placebo: 18074 (EOS1) 16059 (EOS2) | 68.2 years (60-97) (60-69 years: 63% 70-79 years: 32% ≥80 years: 6%) | Male and Female |
EOS1: End of RSV Season 1; EOS2: End of RSV Season 2
a Applicable for the total population, for both RSV seasons
C3671013 was a Phase 3, multicentre, randomised, double blind, placebo-controlled study to assess the efficacy, immunogenicity and safety of Abrysvo in the prevention of RSV associated lower respiratory tract illness in individuals 60 years of age and older during the first RSV season and the long-term efficacy, immunogenicity and safety of Abrysvo across two RSV seasons.
RSV-associated lower respiratory tract illness was defined as RT PCR confirmed RSV illness with two or more, or three or more, of the following respiratory symptoms within 7 days of symptom onset and lasting more than 1 day during the same illness - new or increased cough, wheezing, sputum production, shortness of breath or tachypnea (≥25 breaths/min or 15% increase from resting baseline). RSV-associated severe lower respiratory tract illness was defined as meeting the lower respiratory tract illness RSV criteria plus at least one of the following: hospitalisation due to RSV-associated lower respiratory tract illness, new or increased oxygen supplementation or mechanical ventilation including Continuous Positive Airway Pressure (CPAP).
The dose level of RSV prefusion F antigen in Abrysvo for this study was 120 micrograms (60 mcg A and 60 mcg B. Participants were randomised (1:1) to receive Abrysvo (n=18,487) or placebo (n=18,479). Enrollment was stratified by age, 60-69 years (63%), 70-79 years (32%) and ≥80 years (6%). Healthy adults and adults with stable chronic diseases were included. Among enrolled participants, (16%) were enrolled with stable chronic cardiopulmonary conditions such as chronic obstructive pulmonary disease (COPD), asthma or congestive heart failure (CHF).
Demographic characteristics in Study C3671013 were generally similar with regard to age, gender, race and ethnicity among participants who received Abrysvo and those who received placebo. Of the participants who received Abrysvo, 50.9% were male and 79.9% were White, 11.8% were Black or African American and 41.6% were Hispanic/Latino. The median age of participants was 67 years (range 59-97 years). No overall differences in the safety or effectiveness of Abrysvo were observed between age groups.
Study Results
The primary objective was assessment of vaccine efficacy (VE), defined as the relative risk reduction of first episode of RSV-associated lower respiratory tract illness starting 14 days after study vaccination in the Abrysvo group compared to the placebo group in the first RSV season.
The study met the pre-specified success criteria for demonstration of efficacy of Abrysvo for the primary objectives of prevention of RSV-LRTD with ≥2 symptoms and prevention of RSV-LRTD with ≥3 symptoms (lower bound of the VE CI >20% for first-episode cases for both objectives).
Vaccine efficacy information at the end of the first and second RSV seasons, and combined across the two RSV seasons is presented in Table 16 and Table 17. Vaccine efficacy is maintained through two RSV seasons.
| Table 16 - Primary Analysis of Vaccine Efficacy of ABRYSVO Against RSV-LRTD in individuals 60 Years of Age and Older – Study C3671013 | |||||||
Efficacy endpoint 7 months median follow-up | Abrysvo Number of cases N=16,306 | Placebo Number of cases N=16,308a | VE (%) (96.66% CI) | ||||
| First episode of RSV-associated lower respiratory tract illness with ≥2 symptomsb | 11 | 33 | 66.7 (28.8, 85.8) | ||||
| First episode of RSV-associated lower respiratory tract illness with ≥3 symptomsc | 2 | 14 | 85.7 (32.0, 98.7) | ||||
CI – confidence interval; RSV – respiratory syncytial virus; VE – vaccine efficacy (based on case count ratio calculated as 1-(P/[1-P]), where P is the number of RSVpreF cases divided by the total number of cases) a Evaluable efficacy population b In an exploratory analysis in RSV subgroup A (Abrysvo n=1, placebo n=9) VE was 88.9% (CI 10.6, 99.8); and in RSV subgroup B (Abrysvo n=10, placebo n=23) VE was 56.5% (CI -0.7, 82.8); CI 96.66%. c In an exploratory analysis in RSV subgroup A (Abrysvo n=1, placebo n=3) VE was 66.7% (CI -393.7, 99.6); and in RSV subgroup B (Abrysvo n=1, placebo n=10) VE was 90.0% (CI 21.8, 99.8); CI 96.66%. | |||||||
| Table 17 - Descriptive Vaccine Efficacy of ABRYSVO Against RSV LRTD in individuals 60 Years of Age and Older, End of First RSV Season and Across Two RSV Seasons - Study C3671013 | |||||||||||
| Efficacy endpoint | Subgroup | Abrysvo n/N | Placebo n/N | VE (%) (95% CI) | |||||||
| First RSV season (7.4 months median follow-up) | |||||||||||
| First episode of RSV-associated lower respiratory tract illness with ≥2 symptoms | Overall | 15/18,058 | 43/18,076 | 65.1 (35.9, 82.0) | |||||||
| Age 60-69 years | 10/11,305 | 25/11,351 | 60.0 (13.8, 82.9) | ||||||||
| Age 70-79 years | 4/5,750 | 12/5,742 | 66.7 (-10.0, 92.2) | ||||||||
| Age ≥ 80 years | 1/995 | 6/981 | 83.3 (-37.4, 99.6) | ||||||||
| With ≥1 significant underlying condition | 8/9,377 | 22/9,432 | 63.6 (15.2, 86.0) | ||||||||
| First episode of RSV-associated lower respiratory tract illness with ≥3 symptoms | Overall | 2/18,058 | 18/18,076 | 88.9 (53.6, 98.7) | |||||||
| Age 60-69 years | 2/11,305 | 11/11,351 | 81.8 (16.7, 98.0) | ||||||||
| Age 70-79 years | 0/5,750 | 4/5,742 | 100 (-51.5, 100.0) | ||||||||
| Age ≥ 80 years | 0/995 | 3/981 | 100 (-142.0, 100.0) | ||||||||
| With ≥1 significant underlying condition | 2/9,377 | 11/9,432 | 81.8 (16.7, 98.0) | ||||||||
| Across 2 RSV seasonsb (16.9 months median follow-up) | |||||||||||
| First episode of RSV-associated lower respiratory tract illness with ≥2 symptoms | Overall | 54/18,050 | 131/18,074 | 58.8 (43.0, 70.6) | |||||||
| Age 60-69 years | 34/11,305 | 80/11,351 | 57.5 (35.8, 72.4) | ||||||||
| Age 70-79 years | 15/5,750 | 40/5,742 | 62.5 (30.6, 80.8) | ||||||||
| Age ≥ 80 years | 5/995 | 11/981 | 54.5 (-41.9, 87.6) | ||||||||
| With ≥1 significant underlying condition | 36/9,387 | 71/9,448 | 49.3 (23.2, 67.0) | ||||||||
| First episode of RSV-associated lower respiratory tract illness with ≥3 symptoms | Overall | 10/18,050 | 54/18,074 | 81.5 (63.3, 91.6) | |||||||
| Age 60-69 years | 7/11,305 | 38/11,351 | 81.6 (58.2, 93.1) | ||||||||
| Age 70-79 years | 3/5,750 | 11/5,742 | 72.7 (-3.2, 95.1) | ||||||||
| Age ≥ 80 years | 0/995 | 5/981 | 100.0 (-9.1, 100.0) | ||||||||
| With ≥1 significant underlying condition | 9/9,387 | 34/9,448 | 73.5 (43.6, 88.8) | ||||||||
CI – confidence interval; n – number of cases; N – number of participants; RSV – respiratory syncytial virus; VE – vaccine efficacy a Exploratory analysis b RSV seasons 1 and 2 combined | |||||||||||
At the end of the first and second RSV seasons, subgroup analyses of VE by age, prespecified significant underlying conditions and RSV A and RSV B subgroups in Abrysvo recipients were consistent with the main analyses and support consistent VE across different age and risk groups.
Indication 3: Active immunization of individuals 18 through 59 years of age at increased risk of LRTD caused by RSV
| Table 18 - Summary of patient demographics for clinical trials in individuals 18 - 59 years of age at increased risk of LRTD | ||||||||
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex | |||
| C3671023 Substudy A | Phase 3, multicentre, randomised, double-blind, placebo-controlled global study | 120 mcg Abrysvo (60 mcg subgroup A and 60 mcg subgroup B) Intramuscular single dose of Abrysvo or placebo (2:1 ratio) Total duration of study: 6 months | Abrysvo: 453 Placebo: 225 | 49 years (18-59) (18-49 years: 52% 50-59 years: 48%) | Male and Female | |||
C3671023 Substudy A is a Phase 3, multicenter, randomized, double-blinded, placebo-controlled study to assess the safety, tolerability, and immunogenicity of RSVpreF in adults 18 through 59 years of age considered to be at increased risk of severe RSV disease due to certain chronic medical conditions, including chronic pulmonary (including asthma), cardiovascular (excluding isolated hypertension), renal, hepatic, neurologic, hematologic, or metabolic disorders (including diabetes mellitus).
The dose level of RSV prefusion F antigen in Abrysvo for this study was 120 micrograms (60 mcg A and 60 mcg B). Participants were randomised (2:1) to receive Abrysvo (n=453) or placebo (n=225). Enrollment was stratified by age (18-49 years: 52.1%, 50-59 years: 47.9%).
Demographic characteristics in C3671023 Substudy A were generally similar with regard to age, gender, race and ethnicity among participants who received Abrysvo and those who received placebo. Of the participants who received Abrysvo, 42.6% were male and 68.9% were White, 23.4% were Black or African American and 22.5% were Hispanic/Latino. The median age of participants was 49 years (range 18-59 years).
Study Results
Study C3671023 was conducted in individuals who had chronic pulmonary (including asthma), cardiovascular (excluding isolated hypertension), renal, hepatic, neurologic, hematologic or metabolic disorders (including diabetes mellitus and hyper/hypothyroidism). Effectiveness was inferred by comparison of the RSV neutralizing geometric mean titers (GMTs) and seroresponse rates of the evaluable immunogenicity population in Study C3671023 to those in a subgroup of the older adults ≥60 years of age in Study C3671013.
The non-inferiority criteria were met for increased risk individuals 18 through 59 years of age compared to individuals ≥60 years of age for the ratio of RSV neutralizing geometric mean titers (GMTs) by the lower bounds of the 2-sided 95% CIs >0.667 (1.5-fold non-inferiority margin), and for the difference in seroresponse rates by the lower bounds of the 2-sided 95% CIs > -10% for both RSV A and RSV B.
| Table 19 - Comparison of Model Adjusted RSV Neutralizing Titer GMTs at 1 Month After Vaccination with ABRYSVO, 18 Through 59 Years at Increased Risk of LRTD (Study C3671023)a versus 60 Years and Older (Study C3671013)b | |||||||||||
| RSV subgroups | Study C3671023a 18-59 years of age at increased risk | Study C3671013b ≥60 years | Adjusted GMR* (95% CI) | ||||||||
| nc | Adjusted GMT (95% CI) | nc | Adjusted GMT (95% CI) | ||||||||
| A | 435 | 41097 (37986, 44463) | 408 | 26225 (24143, 28486) | 1.57 (1.396, 1.759) | ||||||
| B | 437 | 37416 (34278, 40842) | 408 | 24680 (22504, 27065) | 1.52 (1.333, 1.725) | ||||||
CI; confidence interval; GMR – geometric mean ratio; GMT – geometric mean titer. *Analysis of covariance (ANCOVA) adjusted with baseline titer and sex a NCT05842967 = C3671023 b NCT05035212 = C3671013 c Evaluable immunogenicity population | |||||||||||
| Table 20 - Comparison of RSV neutralising titre GMTs seroresponse rates 1 month after vaccination with ABRYSVO, 18 Through 59 Years at Increased Risk (Study C3671023)a versus 60 Years and Older (Study C3671013)b | ||||||||||||||
| RSV subgroups | Population group | Difference (95% CI) | ||||||||||||
Study C3671023a 18-59 years of age at increased risk | Study C3671013b ≥60 years | |||||||||||||
| n/N (%) | 95% CI | n/N (%) | 95% CI | |||||||||||
| A | 405/435 (93) | 90.3, 95.3 | 359/408 (88) | 84.4, 91.0 | 5.1 (1.2, 9.2) | |||||||||
| B | 408/437 (93) | 90.6, 95.5 | 347/408 (85) | 81.2, 88.4 | 8.3 (4.2, 12.6) | |||||||||
CI – confidence interval; GMT – geometric mean titre Seroresponse is defined as achieving a ≥4-fold rise from baseline if the baseline measurement is above the lower limit of quantitation (LLOQ). If the baseline measurement is below the LLOQ, a post-vaccination assay result ≥4 × LLOQ is considered a seroresponse. Non-inferiority was met if the lower bound of the 2-sided CI for the percentage difference >-10% (10% NI criterion) for both RSV A and RSV B. a NCT05842967 = C3671023 b NCT05035212 = C3671013 c Evaluable immunogenicity population | ||||||||||||||
Immunogenicity in immunocompromised individuals 18 years of age and older
C3671023 Substudy B was a Phase 3, single-arm, open-label, multicentre study to assess the safety and immunogenicity of Abrysvo in immunocompromised individuals ≥18 years of age. Participants (N=203) had autoimmune inflammatory disorders with active immunomodulator therapy (47.8%); history of a solid organ transplant (kidney, liver, lung or heart) at least 3 months prior to enrollment (36.9%); end stage renal disease and on haemodialysis (15.3%); or advanced non-small cell lung cancer and receiving active immunomodulator therapy (2.5%). Participants received 2 doses of Abrysvo with an interval of 1 month.
A single dose of Abrysvo elicited robust neutralising responses approximately 8- or 9-fold above baseline against RSV A and RSV B in participants ≥18 years of age with immunocompromising conditions (n=188). Responses did not further increase with a second dose of Abrysvo 1 month after the first dose.
16. Non-Clinical Toxicology
Carcinogenicity:
Abrysvo has not been evaluated for the potential to cause carcinogenicity.
Genotoxicity:
Abrysvo has not been evaluated for the potential to cause genotoxicity.
Reproductive and Developmental Toxicology:
Non-clinical data reveal no special hazard for humans based on conventional studies of repeated dose toxicity and toxicity to reproduction and development.