


Product Monograph - Accel-Clopidogrel
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients | |
| Oral | Tablet 75 and 300 mg | Tablet Core: | Coating: |
| castor oil, colloidal silicon dioxide, crospovidone, hydroxypropyl cellulose, lactose monohydrate, mannitol, microcrystalline cellulose, polyethylene glycol | hypromellose, lactose monohydrate, titanium dioxide, triacetin, red iron oxide | ||
INDICATIONS AND CLINICAL USE
MI, Stroke or Established Peripheral Arterial Disease
- ACCEL-CLOPIDOGREL (clopidogrel bisulfate) is indicated for the secondary prevention of atherothrombotic events (myocardial infarction, stroke and vascular death) in patients with atherosclerosis documented by stroke, myocardial infarction, or established peripheral arterial disease.
Acute Coronary Syndrome
- ACCEL-CLOPIDOGREL, in combination with acetylsalicylic acid (ASA), is indicated for the early and long-term secondary prevention of atherothrombotic events (myocardial infarction, ischemic stroke, cardiovascular death and/or refractory ischemia) in patients with acute coronary syndromes - without ST segment elevation (ie. unstable angina or non-Q-wave myocardial infarction). These benefits of ACCEL-CLOPIDOGREL have been shown only when these patients were concomitantly treated with ASA in addition to other standard therapies. These benefits were also seen in patients who were managed medically and those who were managed with percutaneous coronary intervention (with or without stent) or CABG (coronary artery bypass graft).
For patients with ST-segment elevation acute myocardial infarction, ACCEL-
CLOPIDOGREL has been shown to reduce the rate of an endpoint of all-cause mortality and the rate of a combined endpoint of death, re-infarction or stroke.
Atrial Fibrillation
- In patients with atrial fibrillation (AF) who have at least one risk factor for vascular events, who are not suitable for treatment with an anticoagulant and who have a low risk of bleeding, ACCEL-CLOPIDOGREL in combination with low-dose ASA is indicated for the prevention of atherothrombotic and thromboembolic events, including stroke.
In patients with AF at increased risk of vascular events who can take vitamin K antagonist
(VKA) therapy, VKA has been shown to result in better clinical benefit than ASA alone or the combination of ACCEL-CLOPIDOGREL and ASA for the reductions of stroke.
- Pediatrics (< 18 years of age):
The safety and efficacy has not been established.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- Active bleeding such as peptic ulcer and intracranial hemorrhage.
- Significant liver impairment or cholestatic jaundice.
WARNINGS AND PRECAUTIONS
Cross-reactivity among thienopyridines
Patients should be evaluated for history of hypersensitivity to another thienopyridine (such as ticlopidine, prasugrel) since allergic cross-reactivity among thienopyridines has been reported (see ADVERSE REACTIONS). Thienopyridines may cause mild to severe allergic reactions such as rash, angioedema, or haematological reactions such as thrombocytopaenia and neutropaenia. Patients who had developed a previous allergic reaction and/or haematological reaction to one thienopyridine may have an increased risk of developing the same or another reaction to another thienopyridine. Monitoring for cross-reactivity is advised.
Bleeding and haematological disorders
As with other antiplatelet agents, when considering prescribing ACCEL-CLOPIDOGREL (clopidogrel bisulfate), physicians should inquire whether the patient has a history of bleeding. ACCEL-CLOPIDOGREL should be used with caution in patients who may be at risk of increased bleeding from recent trauma, surgery or other pathological condition(s), and in patients receiving treatment with acetylsalicylic acid, heparin, glycoprotein IIb/IIIa inhibitors, non-steroidal anti-inflammatory drugs (NSAIDs), or selective serotonin reuptake inhibitors (SSRIs).
Because of the increased risk of bleeding, the concomitant administration of warfarin with ACCEL-CLOPIDOGREL should be undertaken with caution (see DRUG INTERACTIONS).
Due to the risk of bleeding and haematological undesirable effects, blood cell count determination and/or other appropriate testing should be promptly considered whenever such suspected clinical symptoms arise during the course of treatment (see ADVERSE REACTIONS).
In patients with recent transient ischaemic attack (TIA) or stroke and who are at high risk of recurrent ischemic events, the combination of ASA and ACCEL-CLOPIDOGREL has not been shown to be more effective than ACCEL-CLOPIDOGREL alone, but the combination has been shown to increase major bleeding (see DRUG INTERACTIONS).
Platelet transfusion may be used to reverse the pharmacological effects of ACCEL-CLOPIDOGREL when quick reversal is required.
Thrombotic thrombocytopenic purpura (TTP) has been reported rarely following the use of clopidogrel, but it can occur anytime during the first year of exposure. Few cases have been reported after more than one year of exposure. TTP is a potentially fatal condition requiring prompt treatment with plasmapheresis. It is characterized by thrombocytopenia, microangiopathic hemolytic anemia, neurological findings, renal dysfunction, and fever.
Acquired haemophilia has been reported following use of clopidogrel, manifesting as a marked increase in bleeding or bruising. In cases of confirmed isolated activated partial thromboplastin time (aPTT) prolongation with or without bleeding, acquired haemophilia should be considered. Patients with a confirmed diagnosis of acquired haemophilia should be managed and treated by specialists, and clopidogrel should be discontinued.
Use of ACCEL-CLOPIDOGREL combined with low-dose ASA in patients with Atrial Fibrillation, who are considered unsuitable for anticoagulation therapy
The use of this dual antiplatelet therapy in patients with AF has been shown to reduce the incidence of cardiovascular events (fatal and non-fatal stroke, non-CNS systemic embolism, vascular death), but to significantly increase the incidence of major bleeding, severe bleeding and intracranial hemorrhage, and to increase the incidence of fatal bleedings, versus ASA therapy alone. Before initiating AF patients on this dual antiplatelet therapy, the patient’s bleeding risk should be carefully considered.
Cytochrome P450 2C19 (CYP2C19)
Clopidogrel is a pro-drug, which requires metabolism by the hepatic cytochrome CYP2C19 to form the active thiol metabolite. The function of this enzyme can be compromised, either through direct drug inhibition or dysfunctional genetic variants that lower enzyme activity, thus the effectiveness of clopidogrel could diminish correspondingly.
Pharmacogenetics – CYP2C19 Poor Metabolisers:
In patients who are CYP2C19 poor metabolisers, clopidogrel at recommended doses forms less of the active metabolite of clopidogrel and has a smaller effect on platelet function. Poor metabolisers with acute coronary syndrome or undergoing percutaneous coronary intervention treated with clopidogrel at recommended doses may exhibit higher cardiovascular event rates than do patients with normal CYP2C19 function. Consider alternative treatment or treatment strategies in patients identified as CYP2C19 poor metabolisers (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics, Pharmacogenetics, and Dosage and Administration).
Use with Proton Pump Inhibitors (PPI):
Omeprazole, a moderate CYP2C19 inhibitor, reduces the pharmacological activity of clopidogrel. Avoid use of strong or moderate CYP2C19 inhibitors with ACCEL-CLOPIDOGREL. Consider using another acid-reducing agent with less CYP2C19 inhibitory activity, or alternative treatment strategies. Pantoprazole, a weak CYP2C19 inhibitor, had less effect on the pharmacological activity of clopidogrel than omeprazole (see DRUG INTERACTIONS and ACTION AND CLINICAL PHARMACOLOGY).
Gastrointestinal
Active GI Lesions
Clopidogrel bisulfate prolongs bleeding time. Although clopidogrel has shown a lower incidence of gastrointestinal bleeding compared to ASA in a large controlled clinical trial (CAPRIE), ACCEL-CLOPIDOGREL should not be used in patients who have lesions with a propensity to bleed. In CURE, the incidence of major GI bleeding was 1.3% versus 0.7% (clopidogrel + ASA versus placebo + ASA, respectively).
In patients taking ACCEL-CLOPIDOGREL, drugs that might induce GI lesions should be used with caution.
Hepatic/Biliary/Pancreatic
Experience is limited in patients with moderate hepatic impairment who may have bleeding diatheses. As with any patient exhibiting hepatic impairment, liver function should be carefully monitored and ACCEL-CLOPIDOGREL should be used with caution.
In the CAPRIE study, there were 344 hepatically impaired patients (Alkaline phosphatase >300 U/L, or ALT >120 U/L, or AST >75 U/L) and 168 received clopidogrel for a mean duration of 18 months. The adverse events were more common in this population, compared to the rest of the CAPRIE population, and more common in the clopidogrel (N=168) than in the ASA (N=176) group (any bleeding disorders, N=17 vs N=14; any rash, N=11 vs N=6; diarrhea, N=8 vs N=3, respectively).
Peri-operative Considerations
If a patient is to undergo elective surgery, consideration should be given to discontinue ACCEL-CLOPIDOGREL 5 to 7 days prior to surgery to allow for a reversal of its effect (see ACTION AND CLINICAL PHARMACOLOGY and CLINICAL TRIALS).
Renal
Therapeutic experience with clopidogrel is limited in patients with severe and moderate renal impairment. Therefore ACCEL-CLOPIDOGREL should be used with caution in these patients.
Sensitivity to lactose
ACCEL-CLOPIDOGREL contains lactose. Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this medicine.
Special Populations
Pregnant Women: There are no adequate and well-controlled studies in pregnant women.
Reproduction studies have been performed in rats at doses up to 500 mg/kg per day and in rabbits at doses up to 300 mg/kg per day and have revealed no evidence of impaired fertility or harm to the fetus due to clopidogrel. Because animal reproduction studies are not always predictive of a human response, ACCEL-CLOPIDOGREL should be used during pregnancy only if the potential benefits outweigh the potential risks to the fetus.
Nursing Women: Studies in rats have shown that clopidogrel and/or its metabolites are excreted in milk. It is not known whether this drug is excreted in human milk. Therefore, clopidogrel should not be used by lactating women.
Pediatrics (< 18 of age): Safety and effectiveness in subjects below the age of 18 have not been established.
Driving a vehicle or performing other hazardous tasks
No impairment of driving or psychometric performance was observed following clopidogrel administration.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The safety profile of clopidogrel has been evaluated in clinical trials in more than 44,000 patients including over 1200 patients treated for 1 year or more and further assessed during post-marketing experience.
Of the patients who participated in the CAPRIE, CURE and CLARITY double-blind international clinical trials, approximately 50% were elderly patients (> 65 years) and 15% were 75 years and older. In the ACTIVE A trial, 75% of patients treated with clopidogrel were 65 years of age and older, and 41% were 75 years and older. In COMMIT study, approximately 58% of the patients treated with clopidogrel were 60 years and older, 26% of whom were 70 years and older.
The most frequent adverse drug reactions (≥1%) with clopidogrel (with or without associated ASA) in controlled clinical trials were hemorrhage and bleeding disorders including purpura, any rash, dyspepsia, abdominal pain and diarrhea (see "Clinical Trial Adverse Drug Reactions").
The most serious adverse drug reactions from controlled clinical trials rarely reported (<1%) were bleeding and clotting disorders including gastrointestinal hemorrhage, hemorrhagic ulcer and hemothorax.
Blood disorders: agranulocytosis/ granulocytopenia, aplastic anemia, neutropenia and thrombocytopenia.
Gastrointestinal system disorders: Duodenal, gastric or peptic ulcer, gastritis.
Skin disorders: Any rash and bullous eruption.
The overall incidence of study drug discontinuation because of adverse events was similar in both groups in CAPRIE (clopidogrel 11.9% and ASA 11.9%). In CURE, study drug discontinuation occurred in 5.8 % of patients with clopidogrel plus ASA and 3.9% of patients with placebo plus ASA. In CLARITY, study drug discontinuation was greater in the placebo group (8.6%) compared with the clopidogrel group (6.9%). In COMMIT, the overall incidence of discontinuations was similar between the two treatment groups (2.4% in the clopidogrel group versus 2.2% in the placebo group). In the ACTIVE A study, the overall incidence of discontinuation due to AEs was higher in the clopidogrel in combination with ASA group (10.3%) than in the ASA alone group (7.4%), mostly due to gastrointestinal disorders (2.5% vs 2.0 % respectively).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
CAPRIE:
With few exceptions (see Table 1) the overall tolerability of clopidogrel was similar regardless of age, sex and race. However, in women there was a slightly higher incidence of bleeding disorders in the clopidogrel group (11.36% vs 9.88%).
Clinically Important Adverse Events
The clinically important adverse events observed in CAPRIE were the following.
Bleeding and clotting disorders: One case of Henoch-Schönlein purpura (acute visceral symptoms: vomiting, diarrhea, abdominal distension, hematuria, renal colic) was reported in a patient taking clopidogrel. The patient recovered without sequellae within one month. Rare cases of platelet count ≤30,000/mm3 have been reported. The overall incidence of bleeding on clopidogrel and ASA was the same (9.3%). The incidence of severe cases was 1.4% and 1.6% in the clopidogrel and ASA groups respectively. The overall incidence of other bleeding disorders was higher in the clopidogrel group (7.3%) compared to ASA (6.5%). However, the incidence of severe events was similar in both treatment groups (0.6% vs 0.4%).
Gastrointestinal: Overall, the incidence of gastrointestinal events (e.g. abdominal pain, dyspepsia, gastritis and constipation) in patients receiving (clopidogrel bisulfate) was 27.1%, compared to 29.8% in those receiving ASA. The incidence of patients withdrawing from treatment because of gastrointestinal adverse reactions was 3.2% for clopidogrel and 4.0% for ASA.
Hepatic and biliary disorders: The overall incidence of hepatic and biliary disorders was similar in patients treated with clopidogrel (3.5%) compared to ASA (3.4%). The most frequent events were increased liver enzymes and bilirubinemia.
Skin disorders: The incidence of skin and appendage disorders in patients receiving clopidogrel was 15.8% (0.7% serious); the corresponding rate in ASA patients was 13.1% (0.5% serious). There was no notable difference between treatment groups in the incidence of bullous eruptions (0.23% clopidogrel versus 0.16% ASA). One case of a severe bullous eruption was reported in a patient taking clopidogrel. The overall incidence of patients withdrawing from treatment because of skin and appendage disorders adverse reactions was 1.5% for clopidogrel and 0.8% for ASA.
A summary of the clinically relevant adverse effects observed in CAPRIE are presented in Table 1 below. In CAPRIE, patients with a known intolerance to ASA were excluded from the study.
Table 1 - Summary of Adverse Events occurring in ≥ 1% of clopidogrel patients in CAPRIE Trial
| Adverse event | clopidogrel n= 9599 (%) | ASA n= 9586 (%) |
Body as a Whole Accidental / Inflicted Injury Chest pain Influenza-like symptoms Fatigue Pain | 7.9 8.3 7.5 3.3 6.4 | 7.3 8.3 7 3.4 6.3 |
Cardiovascular Dependent Edema Edema Heart and rhythm disorder Hypertension Peripheral edema | 1.2 1.0 4.3 4.3 1.2 | 1.3 1.2 5.0* 5.1 1.6 |
Central Nervous System Dizziness Headache | 6.2 7.6 | 6.7 7.2 |
Endocrine and Metabolism Hypercholesterolemia | 4.0 | 4.4 |
Gastrointestinal Any Event Abdominal pain Constipation Diarrhea
Dyspepsia Flatulence Nausea Vomiting | 27.1 5.6 2.4 4.5* 0.2 0.4 5.2 1.0 3.4 1.3 | 29.8 7.1* 3.3* 3.4 0.1 0.3 6.1* 1.1 3.8 1.4 |
Genitourinary Urinary tract infection | 3.1 | 3.5 |
Hemorrhages or bleeding Epistaxis Hematoma Gastrointestinal hemorrhage
Purpura (primarily bruising & ecchymosis) | 2.9 1.6 2.0 0.7 5.3* | 2.5 1.5 2.7* 1.1 3.7 |
Musculoskeletal Arthralgia Back pain | 6.3 5.8 | 6.2 5.3 |
Table 1 - Summary of Adverse Events occurring in ≥ 1% of clopidogrel patients in CAPRIE Trial
| Adverse event | clopidogrel n= 9599 (%) | ASA n= 9586 (%) |
Psychiatric Disorder Depression | 3.6 | 3.9 |
Skin Any Event Pruritus Rash
| 15.8 3.3* 4.2* 0.1 0.5 | 13.1 1.6 3.5 0.1 0.2 |
Respiratory Bronchitis Coughing Dyspnea Rhinitis Upper respiratory tract infection | 3.7 3.1 4.5 4.2 8.7 | 3.7 2.7 4.7 4.2 8.3 |
*: Statistically significant difference between treatments (p≤0.05)
(1): Patients may be included in more than one category
No clinically relevant events other than those observed in CAPRIE have been reported with a frequency ≥2.5% during the CURE, CLARITY, ACTIVE A and COMMIT controlled studies.
The number of patients discontinuing due to adverse reactions in CAPRIE are shown in Table 2.
Table 2 - Patients Discontinued because of Adverse Experiences in CAPRIE (number and percentage of patients)
| Adverse Experience | Study drug permanently discontinued | |
| clopidogrel n= 9599 (%) | ASA n= 9586 (%) | |
| Rash | 0.9 | 0.41* |
| Diarrhea | 0.42 | 0.27 |
| Indigestion/nausea/vomiting | 1.9 | 2.41* |
| Any bleeding disorder | 1.2 | 1.37 |
| Intracranial hemorrhage | 0.21 | 0.33 |
| Gastrointestinal hemorrhage | 0.52 | 0.93* |
| Abnormal liver function | 0.23 | 0.29 |
* statistically significant p < 0.05
CURE:
In CURE, clopidogrel was given with ASA and was not associated with a significant increase in life-threatening or fatal bleeds compared to placebo given with ASA; the incidences of non life threatening major bleeding and minor bleeding were significantly larger in the clopidogrel + ASA group. The incidence of intracranial hemorrhage was 0.1% in both groups. The principal sites for major bleeding were primarily gastrointestinal and at arterial puncture sites. In patients receiving both clopidogrel and ASA in CURE, the incidence of bleeding is described in Table 3 below:
Table 3 - Incidence of Bleeding Complications (% patients) - CURE Trial
| Event | clopidogrel + ASA* (N=6259) | PLACEBO + ASA* (N=6303) | p-value |
| Life-threatening bleeding | 2.2 | 1.8 | 0.13 |
| Fatal | 0.2 | 0.2 | |
| 5 g/dL hemoglobin drop | 0.9 | 0.9 | |
| Requiring surgical intervention | 0.7 | 0.7 | |
| Hemorrhagic strokes | 0.1 | 0.1 | |
| Requiring inotropes | 0.5 | 0.5 | |
| Requiring transfusions (≥4 units) | 1.2 | 1 | |
| Other major bleeding | 1.6 | 1 | 0.005 |
| Significantly disabling | 0.4 | 0.3 | |
| Intraocular bleeding with significant loss of vision | 0.05 | 0.03 | |
| Requiring 2-3 units of blood | 1.3 | 0.9 | |
| Major bleeding† | 3.7‡ | 2.7§ | 0.001 |
| Minor bleeding¶ | 5.1 | 2.4 | <0.001 |
| Total with bleeding complications | 8.5 | 5 | <0.001 |
* Other standard therapies were used as appropriate. All patients received ASA 75-325 mg daily (mean=160 mg) † Life threatening and other major bleeding necessitating transfusion of ≥ 2 units of blood .
‡ Major bleeding event rate for clopidogrel + ASA was dose-dependent on ASA:
<100 mg=2.6%; 100-200 mg=3.5%; >200 mg=4.9% § Major bleeding event rate for placebo + ASA was dose-dependent on ASA:
<100 mg=2.0%; 100-200 mg=2.3%; >200 mg=4.0% ¶ Led to interruption of study medication
The number of patients with bleeding that met the criteria for major bleeding established by the Thrombolysis in Myocardial Infarction (TIMI) trial was 68 (1.09%) in the clopidogrel group and 73 (1.16%) in the placebo group (relative risk, 0.94; p=0.70). The number with bleeding that met the criteria for life-threatening or severe bleeding established by the Global Utilization of Streptokinase and Tissue Plasminogen Activator for Occluded Coronary Arteries (GUST) trial was 78 in the clopidogrel group and 70 in the placebo group (relative risk, 1.12; p=0.48). Some patients had more than one bleeding episode.
Ninety-two percent (92%) of the patients in the CURE study received unfractionated or low molecular weight heparin, and the rate of bleeding in these patients was similar to the overall results.
There was no excess in major bleeds within seven days after coronary bypass graft surgery in patients who stopped therapy more than five days prior to surgery (event rate 4.4% clopidogrel + ASA; 5.3% placebo + ASA). In patients who remained on therapy within five days of bypass graft surgery, the event rate was 9.6% for clopidogrel + ASA, 6.3% for placebo + ASA, which was not significantly different.
Other potentially serious adverse events which may be of clinical interest but were rarely reported (<1%) in patients who received clopidogrel in the CAPRIE or CURE controlled clinical trials are listed below regardless of relationship to clopidogrel. In general, the incidence of these events was similar to that in patients receiving ASA (in CAPRIE) or placebo + ASA (in CURE).
Body as a whole: Allergic reaction and necrosis ischemic.
Cardiovascular disorders: Edema generalized.
Gastrointestinal system disorders: Gastric ulcer perforated, gastritis hemorrhagic and upper GI ulcer hemorrhagic.
Liver and biliary system disorders: Bilirubinemia, hepatitis infectious and liver fatty.
Platelet, bleeding and clotting disorders: hemarthrosis, hematuria, hemoptysis, hemorrhage intracranial, hemorrhage retroperitoneal, hemorrhage of operative wound, ocular hemorrhage, pulmonary embolism, pulmonary hemorrhage, purpura allergic.
Red blood cell disorders: Anemia aplastic, anemia hypochromic.
Reproductive disorders, female: Menorrhagia.
Respiratory system disorders: Hemothorax.
Skin and appendage disorders: Bullous eruption, rash erythematous, rash maculopapular, urticaria.
Urinary system disorders: Abnormal renal function, acute renal failure.
White cell and reticuloendothelial system disorders: Agranulocytosis, granulocytopenia, leukemia.
Other clinically relevant adverse drug reactions pooled from CAPRIE and CURE studies, or observed in other studies, with an incidence > 0.1% as well as serious and relevant adverse drug reactions with an incidence < 0.1% are presented below:
Central and peripheral nervous system disorders:
Uncommon: Dizziness and paraesthesia
Rare: Vertigo
Gastrointestinal system disorder:
Common: Dyspepsia, abdominal pain, diarrhea
Uncommon: nausea, gastritis, flatulence, constipation, vomiting, gastric ulcer, duodenal ulcer
Platelet bleeding and clotting disorders:
Uncommon: bleeding time increased, platelets decreased
Very rare: Thrombotic thrombocytopenic purpura (TTP)
Skin and appendages disorders:
Uncommon: rash, pruritus
White cell and RES disorders:
Uncommon: leucopenia, neutrophils decreased, eosinophilia
CLARITY:
In CLARITY, the incidence of major bleeding (defined as intracranial bleeding or bleeding associated with a fall in hemoglobin > 5 g/dL) was similar between groups (1.3% versus 1.1% in the clopidogrel + ASA and in the placebo + ASA groups, respectively). This was consistent across subgroups of patients defined by baseline characteristics, and type of fibrinolytics or heparin therapy. The incidence of fatal bleeding (0.8% versus 0.6% in the clopidogrel + ASA and in the placebo + ASA groups, respectively) and intracranial hemorrhage (0.5% versus 0.7%, respectively) was low and similar in both groups.
COMMIT:
The overall rate of noncerebral major bleeding or cerebral bleeding in COMMIT was low and similar in both groups as shown in Table 4 below
Table 4 - Number (%) of Patients with Bleeding Events in COMMIT
| Type of bleeding | clopidogrel (+ASA) (N = 22961) | Placebo (+ASA) (N = 22891) | P-value |
Major* noncerebral or cerebral bleeding** Major noncerebral Fatal Hemorrhagic stroke Fatal | 134 (0.6%) 82 (0.4%) 36 (0.2%) 55 (0.2%) 39 (0.2%) | 125 (0.5%) 73 (0.3%) 37 (0.2%) 56 (0.2%) 41 (0.2%) | 0.59 0.48 0.90 0.91 0.81 |
| Other noncerebral bleeding (non-major) | 831 (3.6%) | 721 (3.1%) | 0.005 |
| Any noncerebral bleeding | 896 (3.9%) | 777 (3.4%) | 0.004 |
* Major bleeds are cerebral bleeds or non-cerebral bleeds thought to have caused death or that required transfusion. ** The relative rate of major noncerebral or cerebral bleeding was independent of age. Event rates for clopidogrel + ASA by age were: <60 years = 0.3%, ≥60 to <70 years = 0.7%, ≥70 years 0.8%. Event rates for placebo + ASA by age were: <60 years = 0.4%, ≥60 to <70 years = 0.6%, ≥70 years 0.7%.
ACTIVE A:
In ACTIVE A, the rate of major bleeding was greater in the clopidogrel + ASA group than in the placebo + ASA group (6.7% versus 4.3%). Major bleeding was mostly of extracranial origin in both groups (5.3% in the clopidogrel + ASA group; 3.5% in the placebo + ASA group), and mainly in the gastrointestinal tract (3.5% in the clopidogrel + ASA group vs. 1.8% in the placebo + ASA group). There was an excess of intracranial bleeding in the clopidogrel + ASA treatment group compared to the placebo + ASA group (1.4% versus 0.8%, respectively). There was also a numerical excess in the rates of fatal bleeding in the clopidogrel + ASA group (see Table 5), as well as in the rate of hemorrhagic stroke (0.8% in the clopidogrel + ASA group and 0.6% in the placebo + ASA group).
Table 5 - Number (%) of patients with bleeding events in ACTIVE Ac
No. (%) with Event
Bleeding
clopidogrel
+ ASA
(N=3772)
Placebo +
ASA (N=3782)
Hazard Ratio (%)
(95% CI) p-Value
Majorab(mostly
extracranial )
251 (6.7) 162 (4.3) 1.6 (1.3 to 1.9) <0.0001
- Severeab 190 (5.0) 122 (3.2) 1.6 (1.3 to 2.0) <0.0001
- Fatal 42 (1.1) 27 (0.7) 1.6 (1.0 to 2.5) 0.0680
- ICHab 54 (1.4) 29 (0.8) 1.9 (1.2 to 2.9) 0.0056 Minord 408 (10.8) 175 (4.6) 2.4 (2.0 to 2.9) <0.0001 Anyb 1014 (26.9) 651 (17.2) 1.7 (1.5 to 1.8) <0.0001 a As adjudicated
b Includes 1 patient with an ischemic stroke adjudicated to hemorrhagic, but no bleed c Major bleeding event rates for clopidogrel + ASA by age were: <65 years = 3.3%, ≥65 to <75 years = 7.1%, ≥75 years=8.3%
c Major bleeding event rates for ASA only by age were: <65 years = 1.9%, ≥65 to <75 years = 3.9%, ≥75 years=6.0%
ICH = intracranial hemorrhage includes hemorrhagic stroke and subdural hematoma d Minor bleeding was defined as bleeding leading to a study drug discontinuation
Post-Market Adverse Drug Reactions
The following additional adverse reactions were reported in marketed use, however a causal relationship with clopidogrel has not been clearly established.
Frequencies for the following adverse reactions are not known (cannot be estimated from available data).
Blood and lymphatic system disorders:
Agranulocytosis, aplastic anemia/pancytopenia; cases of bleeding with fatal outcome (especially gastrointestinal, intracranial and retroperitoneal hemorrhage); serious cases of bleeding, mainly eye (conjunctival, ocular, retinal), musculo-skeletal, respiratory tract and skin bleeding, epistaxis, hematuria and hemorrhage of operative wound, hematoma; acquired haemophilia, thrombotic thrombocytopenic purpura (TTP). Some cases of TTP resulted in fatal outcomes (see WARNINGS AND PRECAUTIONS).
Cardiovascular disorders:
Hypotension, often related to bleeding or allergic reaction.
Gastro-intestinal disorders:
Colitis (including ulcerative or lymphocytic colitis), pancreatitis, stomatitis.
General disorders and administration site conditions:
Fever.
Hepato-biliary disorders:
Hepatitis, abnormal liver function test, acute liver failure.
Immune System disorders:
Anaphylactoid reactions, serum sickness.
Cross-reactive drug hypersensitivity among thienopyridines (such as ticlopidine, prasugrel) (see WARNINGS AND PRECAUTIONS).
Musculo-skeletal connective tissue and bone disorders:
Arthralgia, arthritis, myalgia.
Nervous System disorders:
Taste disturbances.
Psychiatric disorders:
Confusion, hallucinations.
Renal and urinary disorders:
Glomerulopathy, elevated blood creatinine.
Respiratory, thoracic and mediastinal disorders:
Bronchospasm, interstitial pneumonitis, eosinophilic pneumonia.
Skin and subcutaneous tissue disorders:
Maculopapular, erythematous or exfoliative rash, urticaria, pruritus, angioedema, bullous dermatitis (erythema multiforme), Stevens-Johnson syndrome, toxic epidermal necrolysis, drug-induced hypersensitivity syndrome, drug rash with eosinophilia and systemic symptoms (DRESS), eczema, lichen planus.
Vascular disorders:
Vasculitis.
DRUG INTERACTIONS
Overview
CYP2C19 inhibitors
Clopidogrel is metabolized to its active metabolite in part by CYP2C19. Concomitant use of drugs that inhibit the activity of this enzyme results in reduced plasma concentrations of the active metabolite of clopidogrel and a reduction in platelet inhibition. See Table 7 for drugs that inhibit CYP2C19 [see Warnings and Precautions].
Proton Pump Inhibitors (PPI): In a crossover clinical study, clopidogrel (300-mg loading dose followed by 75 mg/day) alone and with omeprazole (80 mg at the same time as clopidogrel) were administered for 5 days. As shown in Table 6 below, with concomitant dosing of omeprazole, exposure (Cmax and AUC) to the clopidogrel active metabolite and platelet inhibition were substantially reduced. Similar reductions in exposure to the clopidogrel active metabolite and platelet inhibition were observed when clopidogrel and omeprazole were administered 12 hours apart (data not shown).
There are no adequate studies of a lower dose of omeprazole or a higher dose of clopidogrel in comparison with the approved dose of clopidogrel.
A study was conducted using clopidogrel (300 mg loading dose followed by 75 mg/day) and a high dose (80 mg/day) of pantoprazole, a weak CYP2C19 inhibitor. The plasma concentrations of the clopidogrel active metabolite and the degree of platelet inhibition were less than observed with clopidogrel alone but were greater than observed when omeprazole 80 mg was co-administered with 300 mg loading dose followed by 75 mg/day of clopidogrel (Table 6).
| Table 6. Comparison of clopidogrel Active Metabolite Exposure and Platelet Inhibition with and without Proton Pump Inhibitors, Omeprazole and Pantoprazole | ||||||
| % Change from clopidogrel (300 mg/75 mg) alone | ||||||
| Cmax (ng/mL) | AUC | Platelet Inhibition† (%) | ||||
| Clopidogrel plus | Day 1 | Day 5 | Day 1 | Day 5** | Day 1 | Day 5 |
| Omeprazole* 80 mg | ↓46% | ↓42% | ↓45% | ↓40% | ↓39% | ↓21% |
| Pantoprazole 80 mg | ↓24% | ↓28% | ↓20% | ↓14% | ↓15% | ↓11% |
| †Inhibition of platelet aggregation with 5 mcM ADP *Similar results seen when clopidogrel and omeprazole were administered 12 hours apart. **AUC at Day 5 is AUC0-24 | ||||||
Some nonrandomized observational studies have shown that the combination of clopidogrel and PPI was associated with a higher incidence of adverse cardiovascular events, but sub-studies of randomized clinical trials showed no significant association. It is recommended to avoid use of strong or moderate CYP2C19 inhibitors with clopidogrel.
Anticoagulant drugs
In view of the possible increased risk of bleeding, anticoagulant drugs should be used with caution as tolerance and safety of simultaneous administration with ACCEL-CLOPIDOGREL has not been established. Risk factors should be assessed for individual patients before using ACCEL-CLOPIDOGREL.
Warfarin (CYP2C9 Substrates): At high concentrations in vitro, clopidogrel has been shown to inhibit CYP2C9. In patients receiving long-term warfarin therapy, the administration of clopidogrel 75 mg/day did not modify the pharmacokinetics of S-warfarin (a CYP2C9 substrate) or the INR; however coadministration of ACCEL-CLOPIDOGREL with warfarin increases the risk of bleeding because of independent effects on hemostasis.
Other concomitant therapy
Clinically significant adverse interactions were not detected in clinical trials with clopidogrel where patients received a variety of concomitant medications including ASA, diuretics, beta-blocking agents, angiotensin converting enzyme (ACE) inhibitors, calcium channel blockers, lipid-lowering agents, coronary vasodilators, antidiabetic agents (including insulin),
thrombolytics, unfractionated and/or LMW heparin, glycoprotein IIb/IIIa inhibitors, antiepileptic agents, and hormone replacement therapy (however, see Table 6 regarding ASA and glycoprotein IIb/IIIa inhibitors). A review of the clinical trial data indicates that there is no evidence of an interaction between clopidogrel and atorvastatin. In CAPRIE, patients on HMG CoA reductase inhibitors and clopidogrel experienced a higher incidence of bleeding events (primarily epistaxis). Patients on HMG CoA reductase inhibitors and ASA experienced a higher incidence of intracranial hemorrhage. There is no known pathophysiological or pharmacological explanation for this observation.
It is unlikely that clopidogrel may interfere with the metabolism of drugs such as phenytoin and tolbutamide and the NSAIDs, which are metabolised by cytochrome P450 2C9. Data from the CAPRIE study indicate that phenytoin and tolbutamide can be safely co-administered with clopidogrel.
No clinically significant pharmacodynamic interactions were observed when clopidogrel was coadministered in clinical studies to investigate drug interaction with atenolol, nifedipine, or both atenolol and nifedipine. The pharmacodynamic activity of clopidogrel was slightly enhanced by the coadministration of phenobarbital, however this was not considered to be clinically significant. Pharmacodynamic activity of clopidogrel was not significantly influenced by the coadministration of estrogen.
Drug-Drug Interactions
The drugs listed in this Table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 7 - Established or Potential Drug-Drug Interactions
| Agent | Ref | Effect | Clinical comment |
| Inhibitors of CYP2C19 (e.g. omeprazole) | CT | Reduced drug levels of the active metabolite of clopidogrel | Since clopidogrel is metabolized to its active metabolite partly by CYP2C19, use of drugs that inhibit the activity of this enzyme would be expected to result in reduced drug levels of the active metabolite of clopidogrel. The clinical relevance of this interaction is uncertain. The use of strong or moderate CYP2C19 inhibitors should be discouraged in patients taking clopidogrel. If a proton pump inhibitor is to be used concomitantly with clopidogrel, consider using one with less CYP2C19 inhibitory activity, such as pantoprazole. Inhibitors of CYP2C19 include but are not limited to omeprazole, esomeprazole, lansoprazole, cimetidine, ticlopidine, fluvoxamine, fluoxetine, moclobemide, felbamate, chloramphenicol, ketoconazole. |
| Selective Serotonin Reuptake Inhibitors (SSRIs) | CS | Affect platelet activation and increase the risk of bleeding. Also see above, effect on CYP2C19. | The concomitant administration of SSRIs with clopidogrel should be undertaken with caution. |
| ASA | CT | Potentiated effect of ASA on collagen-induced platelet aggregation | ASA (2 X 500 mg once) did not modify clopidogrel-mediated inhibition of ADP-induced platelet aggregation. Potential increased risk of gastrointestinal bleeding with concomitant administration of ASA. Clopidogrel (75 mg) and ASA (75-325 mg) have been administered together for up to 1 year. As a pharmacodynamic interaction between clopidogrel and ASA is possible, concomitant use should be undertaken with cautions. In patients with recent TIA or stroke who are at high risk of recurrent ischemic events, the combination of ASA and clopidogrel has not been shown to be more effective than clopidogrel alone, but the combination has been shown to increase major bleeding. |
| Atenolol, nifedipine, | CT | No effect | No clinically significant pharmacodynamic interactions observed, with atenolol, nifedipine or both atenolol and nifedipine. |
| Cimetidine | CT | No effect | Pharmacodynamic activity of clopidogrel not changed with coadminsitration. |
Digoxin, Theophylline, Antacids | CT | No effect | There was no modification of the pharmacokinetics of digoxin or theophylline with the coadministration of clopidogrel at steady state. Antacids did not modify the extent of clopidogrel absorption. |
| Estrogens | CT | No effect | Pharmacodynamic activity of clopidogrel not significantly influenced by coadministration. |
| Glycoprotein IIb/IIIa inhibitors | T | As a pharmacodynamic interaction is possible, concomitant use should be undertaken with caution. |
Table 7 - Established or Potential Drug-Drug Interactions
| Agent | Ref | Effect | Clinical comment |
Injectable Anticoagulants (Heparin) | CT | No effect | Clopidogrel at steady state did not modify effect of heparin on coagulation in healthy volunteers. Coadministration of heparin had no effect on platelet aggregation inhibition induced by clopidogrel. As a pharmacodynamic interaction between clopidogrel and heparin is possible, concomitant use should be undertaken with cautions. |
| NSAIDS | T | ↑ occult gastrointestinal blood loss (with naproxen coadministration) | Potential increased risk of gastrointestinal bleeding with concomitant administration of NSAIDS. NSAIDS and clopidogrel should be coadministered with cautions. |
Oral Anticoagulants (Warfarin) | T | Because of the increased risk of bleeding, the concomitant administration of warfarin with clopidogrel should be undertaken with caution. (See Warnings and Precautions). | |
| Phenobarbital | CT | Slight ↑ pharmacodynamic activity of clopidogrel. | Increase not considered clinically significant. |
| Thrombolytics | CS | The safety of the concomitant administration of clopidogrel, rt-PA and heparin was assessed in patients with recent myocardial infarction. Based on historical data, the incidence of clinically significant bleeding was similar to that observed when rt-PA and heparin are co-administered with acetylsalicylic acid. |
Legend: CS = Case Study; CT = Clinical Trial; T = Theoretical
Food or Herbal Product Interactions
There is no interaction of clopidogrel with food since administration of clopidogrel with meals did not significantly modify the bioavailability of clopidogrel. Interactions with herbal products have not been established.
Drug-Laboratory Interactions
None known.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
MI, Stroke or Established Peripheral Arterial Disease
The recommended dose of ACCEL-CLOPIDOGREL is 75 mg once daily long term with or without food.
Acute Coronary Syndrome
For patients with non-ST-segment elevation acute coronary syndrome (unstable angina/non Q-wave MI), ACCEL-CLOPIDOGREL should be initiated with a 300 mg loading dose and
continued long term at 75 mg once a day with ASA (80 mg-325 mg daily). (see CLINICAL TRIALS).
For patients with ST-segment elevation acute myocardial infarction, the recommended dose of ACCEL-CLOPIDOGREL is 75 mg once daily, administered in combination with ASA, with or without thrombolytics. ACCEL-CLOPIDOGREL may be initiated with or without a loading dose (300 mg was used in CLARITY; see CLINICAL TRIALS).
No dosage adjustment is necessary for elderly patients or patients with renal impairment (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations and Conditions).
Atrial Fibrillation
For patients with atrial fibrillation who have at least one risk factor for vascular events , who have a low risk of bleeding, and who are unsuitable for anticoagulation therapy, the recommended dose of ACCEL-CLOPIDOGREL is 75 mg once daily, administered in combination with ASA (75-100 mg daily) (see CLINICAL TRIALS).
Pharmacogenetics
CYP2C19 poor metaboliser status is associated with diminished antiplatelet response to clopidogrel. Although a higher dose regimen in poor metaboliser healthy subjects increases antiplatelet response, an appropriate dose regimen for this patient population has not been established in clinical outcome trials (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics, Pharmacogenetics).
Missed Dose
If a dose of ACCEL-CLOPIDOGREL is missed, it should be taken as soon as possible. However, if it is close to the time of the next dose, disregard the missed dose and return to the regular dosing schedule. Do not double doses.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Overdose following clopidogrel administration may lead to prolonged bleeding time and subsequent bleeding complications. Appropriate therapy should be considered if bleeding is observed or suspected.
A single oral dose of clopidogrel at 1500 or 2000 mg/kg was lethal to mice and rats, and at 3000 mg/kg to baboons.
Treatment:
No antidote to the pharmacological activity of clopidogrel has been found. Platelet transfusion may be used to reverse the pharmacological effects of ACCEL-CLOPIDOGREL when quick reversal is required.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The role of platelets in the pathophysiology of atherosclerotic disease and atherothrombotic events has been established. Long-term prophylactic use of antiplatelet drugs has shown consistent benefit in the prevention of ischemic stroke, myocardial infarction, unstable angina, peripheral arterial disease, need for vascular bypass or angioplasty, and vascular death in patients at increased risk of such outcomes, including those with established atherosclerosis or a history of atherothrombosis. ACCEL-CLOPIDOGREL (clopidogrel bisulfate) is a specific inhibitor of adenosine-diphosphate (ADP)-induced platelet aggregation.
Pharmacodynamics
Clopidogrel is a prodrug, one of whose metabolites is an inhibitor of platelet aggregation. Clopidogrel must be metabolised by CYP450 enzymes to produce the active metabolite that inhibits platelet aggregation. The active metabolite of clopidogrel selectively inhibits the binding of adenosine diphosphate (ADP) to its platelet P2Y12 receptor and the subsequent ADP-mediated activation of the glycoprotein GPIIb/IIIa complex, thereby inhibiting platelet aggregation. Platelet aggregation induced by agonists other than ADP is also inhibited by blocking the amplification of platelet activation by released ADP. Because the active metabolite is formed by CYP450 enzymes, some of which are polymorphic or subject to inhibition by other drugs, not all patients will have adequate platelet inhibition.
Clopidogrel does not inhibit phosphodiesterase activity. Acetylsalicylic acid (ASA) inhibits the cyclooxygenase enzyme pathway preventing the production of prostaglandin and thus, the synthesis of thromboxane A2 which induces platelet aggregation. Clopidogrel acts on the ADP receptor and ASA acts on a separate receptor thereby inhibiting different pathways of platelet activation and aggregation. Therefore, there is potential for synergy between the two agents.
Clopidogrel acts by modifying irreversibly the platelet ADP receptor. Consequently, platelets exposed to clopidogrel are affected for the remainder of their lifespan (approximately 7-10 days) and recovery of normal platelet function occurs at a rate consistent with platelet turnover. Single administration is not sufficient to reach a desired therapeutic effect. Statistically significant and dose-dependent inhibition of platelet aggregation was noted 2 hours after single oral doses of clopidogrel. Repeated doses of 75 mg per day produced inhibition of ADP-induced platelet aggregation from the first day. Steady state was reached between Day 3 and Day 7. At steady state, with a dose of 75 mg per day, the average inhibition level observed was between 40% and 60%. The aggregation level and bleeding time gradually returned to baseline values within 5-7 days after treatment was discontinued. The precise correlation between inhibition of platelet aggregation, prolongation of bleeding time and prevention of atherothrombotic events has not been established. The effect of a loading dose has been clinically evaluated in the CURE study (Clopidogrel in Unstable Angina to Prevent Recurrent Ischemic Events). The benefits of clopidogrel with concomitant ASA were apparent within 24 hours after randomization in the CURE trial.
Pharmacokinetics
The main pharmacokinetic parameters for clopidogrel are presented in the table below.
| Cmax | t1/2 (h) | AUC 0-∞ | |
| Single Dose mean | 2.2 – 2.5 ng/mL | 6 h | 2.7 ng.h/L |
Absorption:
After single and repeated oral doses of 75 mg/day, clopidogrel is rapidly absorbed. Mean peak plasma levels of unchanged clopidogrel (approximately 2.2-2.5 ng/mL after a single 75-mg oral dose) occurred approximately 45 minutes after dosing.
Absorption is at least 50%, based on urinary excretion of clopidogrel metabolites.
Administration of clopidogrel with meals did not significantly modify the bioavailability of clopidogrel as assessed by the pharmacokinetics of the main circulating metabolite.
Distribution: Clopidogrel and the main circulating (inactive) metabolite bind reversibly in vitro to human plasma proteins (98% and 94%, respectively). The binding is non saturable in vitro up to a concentration of 100 μg/mL.
Metabolism: Clopidogrel is extensively metabolized by the liver. In vitro and in vivo, clopidogrel is metabolised according to two main metabolic pathways: one mediated by esterases and leading to hydrolysis into its inactive carboxylic acid derivative (85% of circulating metabolites), and one mediated by multiple cytochromes P450. Clopidogrel is first metabolised to a 2-oxo-clopidogrel intermediate metabolite. Subsequent metabolism of the 2-oxo-clopidogrel intermediate metabolite results in formation of the active metabolite, a thiol derivative of clopidogrel. In vitro, this metabolic pathway is mediated by CYP3A4,CYP2C19, CYP1A2 and CYP2B6. The active thiol metabolite which has been isolated in vitro, binds rapidly and irreversibly to platelet receptors, thus inhibiting platelet aggregation.
The Cmax of the active metabolite is twice as high following a single 300-mg clopidogrel loading dose as it is after four days of 75-mg maintenance dose. Cmax occurs approximately 30 to 60 minutes after dosing.
Excretion: Following an oral dose of 14C-labeled clopidogrel in humans, approximately 50% was excreted in the urine and approximately 46% in the feces in the 5 days after dosing. After a single, oral dose of 75 mg, clopidogrel has a half-life of approximately 6 hours. The elimination half-life of the main circulating (inactive) metabolite was 8 hours after single and repeated administration. Covalent binding to platelets accounted for 2% of the radiolabel with a half-life of 11 days.
Pharmacogenetics
CYP2C19 is involved in the formation of both the active metabolite and the 2-oxo-clopidogrel intermediate metabolite. Clopidogrel active metabolite pharmacokinetics and antiplatelet effects, as measured by ex vivo platelet aggregation assays, differ according to CYP2C19 genotype. Genetic variants of other CYP450 enzymes may also affect the formation of clopidogrel’s active metabolite.
The CYP2C19*1 allele corresponds to fully functional metabolism while the CYP2C19*2 and CYP2C19*3 alleles are nonfunctional. The CYP2C19*2 and CYP2C19*3 alleles account for the majority of reduced function alleles in white (85%) and Asian (99%) poor metabolisers. Other alleles associated with absent or reduced metabolism are less frequent and include, but are not limited to, CYP2C19*4, *5, *6, *7, and *8. A patient with poor metaboliser status will possess two loss-of-function alleles as defined above. Published frequencies for the poor CYP2C19 metaboliser genotypes are approximately 2% for whites, 4% for blacks and 14% for Chinese.
A crossover study in 40 healthy subjects, 10 each in the four CYP2C19 metaboliser groups (ultrarapid, extensive, intermediate and poor), evaluated pharmacokinetic and antiplatelet responses using 300 mg followed by 75 mg/day and 600 mg followed by 150 mg/day, each for a total of 5 days (steady state). Decreased active metabolite exposure and diminished inhibition of platelet aggregation were observed in the poor metabolizers as compared to the other groups. When poor metabolizers received the 600 mg/150 mg regimen, active metabolite exposure and antiplatelet response were greater than with the 300 mg/75 mg regimen (see Table 8). An appropriate dose regimen for this patient population has not been established in clinical outcome trials.
Table 8 Active Metabolite Pharmacokinetics and Antiplatelet Responses by CYP2C19 Metaboliser Status (healthy subjects)
| Dose | Ultrarapid (n=10) | Extensive (n=10) | Intermediate (n=10) | Poor (n=10) | |
| AUClast (ng.h/mL) | 300 mg (Day 1) | 33 (11) | 39 (24) | 31 (14) | 14 (6) |
| 600 mg (Day 1) | 56(22) | 70 (46) | 56 (27) | 23 (7) | |
| 75 mg (Day 5) | 11 (5) | 12 (6) | 9.9 (4) | 3.2 (1) | |
| 150 mg (Day 5) | 18 (8) | 19 (8) | 16 (7) | 7 (2) | |
| IPA (%)* | 300 mg (24 h) | 40 (21) | 39 (28) | 37 (21) | 24 (26) |
| 600 mg (24 h) | 51 (28) | 49 (23) | 56 (22) | 32 (25) | |
| 75 mg (Day 5) | 56 (13) | 58 (19) | 60 (18) | 37 (23) | |
| 150 mg (Day 5) | 68 (18) | 73 (9) | 74 (14) | 61 (14) |
Values are mean (SD), * inhibition of platelet aggregation with 5μM ADP; larger value indicates greater platelet inhibition
Consistent with the above results, in a meta-analysis including 6 studies of 335 clopidogrel-treated subjects at steady state, it was shown that active metabolite exposure was decreased by 28% for intermediate metabolisers, and 72% for poor metabolisers while platelet aggregation inhibition was decreased with differences in inhibition of platelet aggregation (IPA) of 6% for intermediate metabolisers and 21% for poor metabolisers, when compared to extensive metabolisers.
The influence of CYP2C19 genotype on clinical outcomes has been evaluated in several retrospective analyses. In TRITON-TIMI 38 (n=1477) and 3 of the cohort studies (total n = 3516), carriers of a reduced function CYP2C19 allele (intermediate or poor metaboliser) had a higher rate of cardiovascular events (death, myocardial infarction, and stroke) or stent thrombosis compared to extensive metabolizers. In another retrospective analysis (CHARISMA, n = 2428) and one cohort study (n=2208), an increased event rate was observed only in poor metabolisers when compared to extensive metabolisers.
Special Populations and Conditions
Geriatrics: In elderly (≥75 years) volunteers compared to young healthy subjects, there were no differences in platelet aggregation and bleeding time (see DOSAGE AND ADMINISTRATION). No dosage adjustment is needed for the elderly.
Sex: In a small study comparing men and women (N=10 males and 10 females), less inhibition of ADP-induced platelet aggregation was observed in women. In the CAPRIE study (Clopidogrel versus ASA in Patients at Risk of Ischemic Events; for details see below), the incidence of clinical outcome events was similar in men and women.
Paediatric patients: No information available.
Renal Insufficiency: After repeat doses of 75 mg per day in subjects with moderate and severe renal impairment (creatinine clearance from 30 to 60 mL/min and from 5 to 15 mL/min, respectively), a 25% inhibition of ADP-induced platelet aggregation was observed. Although this effect was lower than that typically observed in healthy subjects, the prolongation in bleeding time was similar to healthy volunteers.
Since no differences in Cmax for both clopidogrel and the main circulating metabolite were observed, a compensatory phenomenon i.e. biliary excretion, which has been observed in animals, may explain the lower values of AUC observed in subjects with severe chronic renal failure (see DOSAGE AND ADMINISTRATION).
Ethnicity: The prevalence of CYP2C19 alleles that result in intermediate and poor CYP2C19 metabolism differs according to ethnicity (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics, Pharmacogenetics). From literature, limited data in Asian populations are available to assess the clinical implication of genotyping of this CYP on clinical outcome events.
Hepatic impairment: After repeated doses of clopidogrel 75 mg/day for 10 days in patients with Class A or B hepatic cirrhosis (mild to moderate hepatic impairment), slightly higher main active circulating metabolite of clopidogrel was observed compared to healthy subjects. However, inhibition of ADP-induced platelet aggregation and mean bleeding time prolongation was similar in the two groups.
STORAGE AND STABILITY
For blisters and bottles, store between 15°C and 30°C and protect from moisture.
SPECIAL HANDLING INSTRUCTIONS
None
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage Forms
ACCEL-CLOPIDOGREL 75 mg is available as pink, round, bevel edged, biconvex, film-coated tablets imprinted in black colour with “C75” on one side and plain on the other side.
ACCEL-CLOPIDOGREL 300 mg is available as pink, capsule shaped, biconvex, film-coated tablets that are plain on both sides.
Composition
Each 75 mg tablet contains 97.9 mg of clopidogrel bisulfate which is the molar equivalent of 75 mg of clopidogrel base. Each 300 mg tablet contains 391.5 mg of clopidogrel bisulfate which is the molar equivalent of 300 mg of clopidogrel base.
Non-medicinal ingredients: castor oil, colloidal silicon dioxide, crospovidone, hydroxypropyl cellulose, lactose monohydrate, mannitol, microcrystalline cellulose and polyethylene glycol. The pink film coating contains lactose monohydrate, hypromellose, titanium dioxide, triacetin and red iron oxide.
Packaging
ACCEL-CLOPIDOGREL 75 mg is available in HDPE bottles of 30, 100 and 500 tablets and blisters of 30s (3 x 10s). Please note that a silica gel desiccant is included in the HDPE bottles.
ACCEL-CLOPIDOGREL 300 mg is available in HDPE bottles of 500 tablets and blisters of 30s (3 x 10s). Please note that a silica gel desiccant is included in the HDPE bottles. 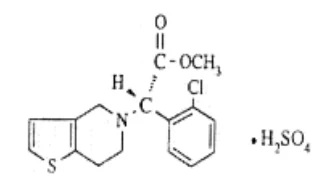
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Clopidogrel bisulfate (U.S.A.N.)
Chemical name: Methyl (S)- α-(2-chlorophenyl)-6,7-dihydrothieno[3,2-c]pyridine- 5(4H)-acetate sulfate (1:1).
Molecular formula: C16H16Cl NO2S•H2SO4
Structural formula
Molecular weight: 419.9
Physicochemical properties: Clopidogrel bisulfate is a white to off-white powder.
Solubility: Clopidogrel bisulfate is practically insoluble in water at neutral pH but freely soluble at pH 1. It also dissolves freely in methanol, sparingly in methylene chloride and is practically insoluble in ethyl ether.
Optical Rotation: About +56°.
pKa =4.55
pH and Effect on UV Absorbance:
At pH2: UV max. abs. = 271 and 278 nm
UV min. abs. = 259 and 275 nm
At pH7: UV max. abs. = 269 and 276 nm
UV min. abs. = 266 and 274 nm
At pH9: UV max. abs. = 269 and 276 nm
UV min. abs. = 266 and 274 nm
Partition co-efficient: About 3.9 at pH 7.4 in a water/octanol medium
Melting Point: About 176.8°C using differential scanning calorimetry
CLINICAL TRIALS
A two-way crossover, single dose bioequivalence study of 300 mg ACCEL-CLOPIDOGREL (clopidogrel bisulfate) tablets and 300 mg PLAVIX® (clopidogrel bisulfate) Tablets distributed by Bristol Myers Squibb, Canada Montreal was performed in 43 healthy adult, male subjects under fasting condition. The results are provided below;
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clopidogrel (1 x 300 mg tablet) From measured data Geometric Least Squares Mean Arithmetic Mean (CV %) | ||||
| Pharmacokinetic Parameter | *Test | †Reference | % Ratio of Geometric Least Squares Means | 90% Confidence Interval |
| AUCT (ng.h/mL) | 4.644 6.656 (114.34%) | 4.349 6.148 (101.76%) | 106.65 | 91.88 -124.10 |
| AUCI (ng.h/mL) | 5.222 7.292 (106.41%) | 4.857 6.686 (95.63%) | 105.54 | 92.72 -124.70 |
Cmax (ng/mL) | 2.088 3.446 (142.28%) | 1.851 2.805 (117.43%) | 112.74 | 94.29 -134.88 |
Tmax§ (h) | 0.750 (0.33, 2.33) | 1.000 (0.33, 3.00) | ||
t ½€ (h) | 5.947 (131.40%) | 5.456 (73.29%) | ||
* ACCEL-CLOPIDOGREL (clopidogrel bisulfate) 300 mg tablets (Accel Pharma Inc.) † PLAVIX® (clopidogrel bisulfate) Tablets 300 mg Distributed by Bristol Myers Squibb, Canada Montreal, QC H4S 0A4
§ Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV %) only
Study demographics and trial design
The safety and efficacy of clopidogrel in preventing atherothrombotic events has been evaluated in five large double-blind trials involving more than 88,000 patients: the CAPRIE study (Clopidogrel vs. ASA in Patients at Risk of Ischemic Events), a comparison of clopidogrel to ASA, the CURE study (Clopidogrel in Unstable Angina to Prevent Recurrent Ischemic Events), the CLARITY-TIMI 28 (Clopidogrel as Adjunctive Reperfusion Therapy – Thrombolysis in Myocardial Infarction) and the COMMIT/CCS-2 (Clopidogrel and Metoprolol in Myocardial Infarction Trial / Second Chinese Cardiac Study) and the ACTIVE A study (Atrial Fibrillation Clopidogrel Trial with Irbesartan for Prevention of Vascular Events), studies comparing clopidogrel to placebo, both given in combination with aspirin and other standard therapy.
MYOCARDIAL INFARCTION (MI), STROKE OR ESTABLISHED PERIPHERAL ARTERIAL DISEASE
CAPRIE:
The CAPRIE trial was a 19,185 patient, 304 centres, international, randomized, double-blind, parallel-group study comparing clopidogrel (75 mg daily) to ASA (325 mg daily). Patients ranged in age from 21 to 94 years (mean 62 years). The study was composed of 72.4% men and 27.6% women and included patients with established atherosclerosis or history of atherothrombosis as manifested by myocardial infarction, ischemic stroke or peripheral arterial disease. Patients received randomized treatment for up to 3 years (mean treatment period 1.6 years) and were followed to 3 years or study termination, irrespective of whether study drug had been discontinued (mean follow-up 1.9 years).
Table 9- Summary of patient demographics for CAPRIE trial in patients at risk of ischemic events
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| CAPRIE | international, randomized, double-blind, parallel-group study comparing clopidogrel to ASA | Dosage: clopidogrel (75 mg daily) or ASA (325 mg daily); Administration: oral; Duration: up to 3 years | n=19,185 clopidogrel: n=9599; ASA: n=9586) | 62 years (21-94 years) | 72.4% male 27.6% female |
Study results
The primary outcome of the trial was a composite outcome which included new ischemic stroke (fatal or non-fatal), new myocardial infarction (fatal or non-fatal), or other vascular death. Deaths not easily attributable to nonvascular causes were all classified as vascular.
As shown in the Table 10, clopidogrel was associated with a statistically significant reduction in the primary composite outcome (absolute risk reduction 0.86% and relative risk reduction 8.7%, p=0.045) and a lower incidence of IS and MI. The event curves continued to diverge over the 3-year follow-up period.
Table 10- Summary of the numbers of events of the primary outcome (composite and individual components) of the CAPRIE study (intent-to-treat analysis)
| Outcome Events of the Primary Analysis | ||||
| Patients | clopidogrel N=9599 | ASA N=9586 | p | Relative Risk Reduction (95% CI) |
| Primary Composite Outcome | 939 (9.78%) | 1020 (10.64%) | 0.045 | 8.7% (0.2, 16.4) |
| MI (fatal or not) | 275 (2.86%) | 333 (3.47%) | ||
| Other vascular death | 226 (2.35%) | 226 (2.36%) | ||
| IS (fatal or not) | 438 (4.56%) | 461 (4.81%) | ||
IS = ischemic stroke; MI = myocardial infarction
ACUTE CORONARY SYNDROME
CURE:
The CURE study included 12,562 patients with an acute coronary syndrome, defined as unstable angina or non Q-wave myocardial infarction without significant ST segment elevation and presenting within 24 hours of onset of the most recent episode of chest pain or symptoms consistent with ischemia.
Patients were required to have either ECG changes compatible with new ischemia (without significant ST segment elevation) or elevated cardiac enzymes or Troponin I or T to at least twice the upper limit of normal. Patients with contraindication to antithrombotic or antiplatelet therapy, at high risk for bleeding, severe heart failure, on oral anticoagulants, and those with recent revascularization or those having received IV glycoprotein IIb/IIIa inhibitors in the previous 3 days were excluded. During the trial, patients were allowed to receive other standard cardiovascular therapies such as heparin, glycoprotein IIb/IIIa inhibitors, lipid-lowering drugs, calcium channel blockers, nitrates, beta blockers, ACE-inhibitors, percutaneous coronary intervention (with or without stent) or CABG, as needed.
Patients were randomized to clopidogrel (300 mg loading dose followed by 75 mg/day) plus ASA (75-325 mg once daily; median 150 mg, mean 160 mg), or placebo plus ASA (75-325 mg once daily; median 150 mg, mean 160 mg). Patients were treated for 3 to 12 months (median 10.8 months; mean 9 months; 4806 patients were followed for entire 12 months). The baseline characteristics, medical history, electrocardiographic changes, and drug therapy were similar for both treatment groups.
Table 11 -Summary of patient demographics for CURE trial in patients with acute coronary syndrome
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Sex |
| CURE | international, randomized, double-blind, parallel-group study comparing clopidogrel + ASA to placebo + ASA | Dosage: clopidogrel (loading dose - 300 mg then 75 mg daily) or placebo in addition to ASA (75-325 mg daily); Administration: oral; Duration: 3-12 months | n=12,562 clopidogrel: n=6259; ASA: n=6303) | 64.2 years (52.9-75.5) | 62% male 38% female |
The number of patients experiencing the primary outcome, a composite of cardiovascular (CV) death, non-fatal myocardial infarction (MI) and stroke was 582 (9.30%) in the clopidogrel-treated group and 719 (11.41%) in the placebo-treated group; an absolute risk reduction of 2.11%, and a relative risk reduction of 20% (p= 0.00009) for the clopidogrel-treated group (see Table 12).
The number of patients experiencing the co-primary outcome (CV death, non-fatal MI, stroke or refractory ischemia) was 1035 (16.54%) in the clopidogrel-treated group and 1187 (18.83%) in the placebo-treated group; an absolute risk reduction of 2.29% and a relative risk reduction of 14% (p=0.0005) for the clopidogrel-treated group.
Events for each component of the composite outcome (CV death, non-fatal myocardial infarction, stroke, refractory ischemia) occurred less frequently with clopidogrel than in the placebo group but the differences did not reach statistical significance except for non-fatal MI. The results are summarized in Table 12.
Table 12- Incidence of the main study outcomes in the CURE study
| Outcome | clopidogrel + ASA* (N=6259) | PLACEBO + ASA* (N=6303) | Absolute Risk Reduction % | Relative Risk (95% CI) |
Primary outcome (Cardiovascular death, non-fatal MI, Stroke) | 582 (9.30%) | 719 (11.41%) | 2.11% | 0.80 (0.72, 0.90) p = 0.00009 |
Co-primary outcome (Cardiovascular death, non-fatal MI, Stroke, Refractory Ischemia) | 1035 (16.54%) | 1187 (18.83%) | 2.29% | 0.86 (0.79, 0.94) p = 0.00052 |
All Individual Outcome Events:† CV death non-fatal MI** Q-wave Non- Q-wave Stroke Refractory ischemia‡ During initial hospitalization After discharge | 318 (5.08%) 324 (5.18%) 116 (1.9%) 216 (3.5%) 75 (1.20%) 544 (8.69%) 85 (1.4%) 459 (7.6%) | 345 (5.47%) 419 (6.65%) 193 (3.1%) 242 (3.8%) 87 (1.38%) 587 (9.31%) 126 (2.0%) 461 (7.6%) | 0.39% 1.47% 1.20% 0.30% 0.18% 0.62% 0.60% 0% | 0.93 (0.79, 1.08) 0.77 (0.67, 0.89) 0.60 (0.48, 0.76) 0.89 (0.74, 1.07) 0.86 (0.63, 1.18) 0.93 (0.82, 1.04) 0.68 (0.52, 0.90) 0.99 (0.87, 1.13) |
* Other standard therapies were used as appropriate. All patients received acetylsalicylic acid (ASA) 75 - 325 mg daily (mean = 160 mg) ** Some patients had both a Q-wave and a non-Q-wave MI.
†The individual components do not represent a breakdown of the primary and co-primary outcomes, but rather the total number of subjects experiencing an event during the course of the study.
‡Only the first ischemic event was counted for each patient.
CV death: excludes clear non-CV deaths;
MI: two of three usual criteria (chest pain, ECG or enzyme/cardiac marker changes);
Stroke: neurological deficit $24 hours (CT/MRI encouraged)
Refractory ischemia (in-hospital): recurrent chest pain lasting more than 5 minutes with new ischemic ECG changes while patient on optimal medical therapy and leading to additional interventions ranging from thrombolytic therapy to coronary revascularization. Refractory ischemia (after discharge): rehospitalization lasting at least 24 hours for unstable angina with ischemic ECG changes.
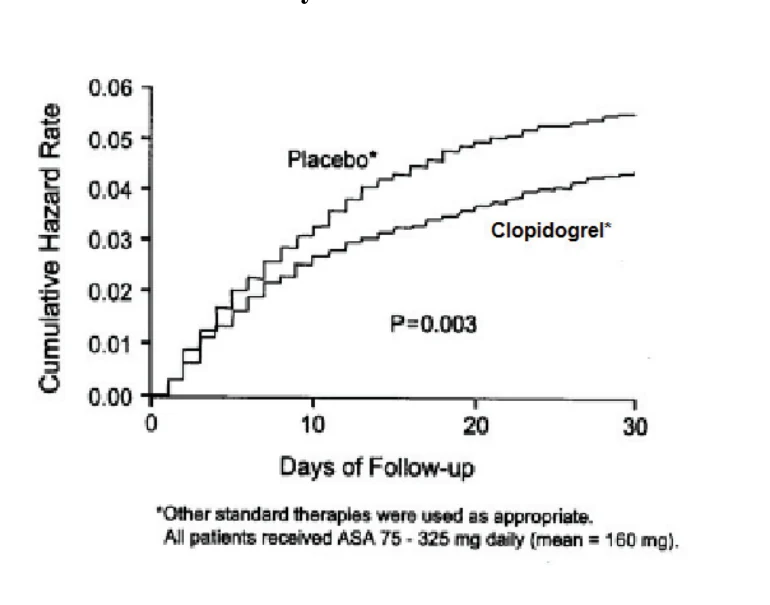
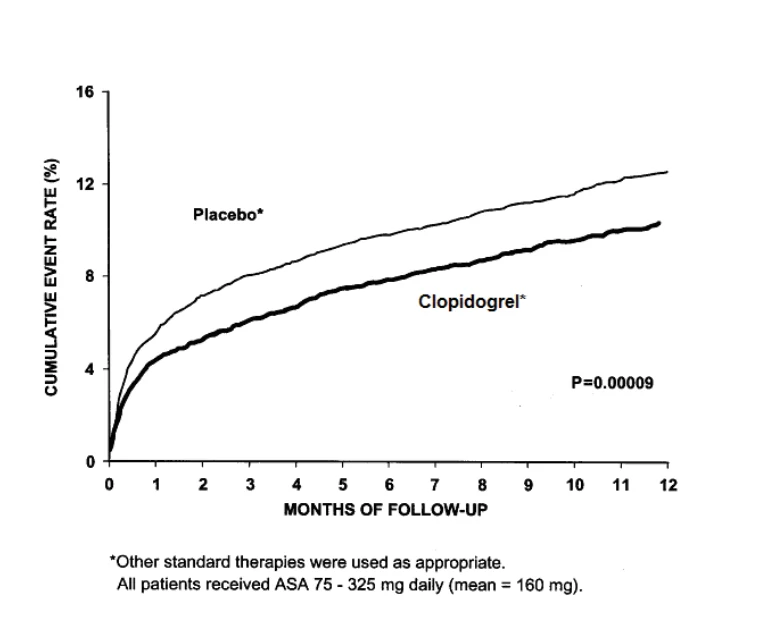
The event curves for CV death, non-fatal MI and stroke separated within the first 24 hours after initiation of therapy (Figure 1) and continued to diverge throughout the study follow-up (up to 12 months) (Figure 2). The rate of the first primary outcome was significantly lower in the clopidogrel group both within the first 30 days after randomization (relative risk, 0.79; 95 percent confidence interval, 0.67 to 0.92) and between days 30 and the end of the study (relative risk, 0.82; 95 percent confidence interval, 0.70 to 0.95).
Figure 1: Cumulative Hazard Rates for First Primary Outcome (death from cardiovascular causes, non-fatal myocardial infarction, or stroke) During the First 30 days after Randomization in the CURE Study.
No. AT RISK
Placebo 6303 6108 5998 5957
Clopidogrel 6259 6103 6035 5984
Figure 2: Cardiovascular Death, Myocardial Infarction or Stroke During 12 months follow-up in the CURE Study
No. AT RISK
Placebo 6303 5780 4664 3600 2388
Clopidogrel 6259 5866 4779 3644 2418
The risk reduction of the secondary prospectively chosen outcomes (in-hospital severe ischemia without urgent intervention, need for revascularization and heart failure) were lower in the clopidogrel group than in the placebo group and the differences observed were statistically significant.
Table 13: Secondary In-Hospital Outcomes in the CURE Study
clopidogrel + ASA* (N= 6259) | Placebo + ASA* (N= 6303) | Absolute Risk Reduction % | Relative Risk (95% CI) | |
| Severe ischemia | 176 (2.81%) | 237 (3.76%) | 1.0% | 0.74 (0.61, 0.90) |
| Revascularization procedure | 1302 (20.8%) | 1431 (22.7%) | 1.9% | 0.92 (0.69, 0.98) |
| Heart failure | 229 ( 3.7%) | 280 (4.4%) | 0.7% | 0.82 (0.69, 0.98) |
Severe ischemia: chest pain lasting more than 5 minutes with new ischemic ECG changes while patient on optimal medical therapy and leading to additional interventions ranging from thrombolytic therapy to coronary revascularization but no urgent intervention performed
* Other standard therapies were used as appropriate. All patients received ASA 75 - 325 mg daily (mean=160 mg; median 150 mg)
In general, the results obtained in populations with different characteristics, including patients with low to high risk and on other acute and long-term cardiovascular therapies were consistent with the results of the primary analyses irrespective of other treatments or interventions.
CLARITY
In patients with ST-segment elevation acute myocardial infarction, safety and efficacy of clopidogrel have been evaluated in two randomized, placebo-controlled, double-blind studies, CLARITY and COMMIT.
The randomized, double-blind, placebo-controlled CLARITY trial included 3,491 patients presenting within 12 hours of the onset of a ST elevation myocardial infarction and planned for thrombolytic therapy. Patients were randomized to receive clopidogrel (300-mg loading dose, followed by 75 mg/day) or placebo. Patients also received ASA (150 to 325 mg as a loading dose, followed by 75 to 162 mg/day), a fibrinolytic agent and, when appropriate, heparin for 48 hours. The patients were followed for 30 days.
Table 14- Summary of patient demographics for CLARITY trial in STEMI patients
| Study # | Trial Design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (range) | Gender |
CLARITY-TIMI 28 | International, randomized, double-blind, placebo- controlled study comparing clopidogrel + ASA to placebo + ASA | Dosage : clopidogrel (loading dose-300 mg then 75 mg daily) or placebo in addition to ASA (150-325 mg on first day, and 75-162 mg daily thereafter to be taken simultaneously with the study drug) Administration: oral Duration: Up to and including day of angiography or Day 8 or by hospital discharge, whichever comes first | n = 3491 clopidogrel: n= 1752 ASA: n= 1739 | 57.4 years (18-79 years) | 80.3% males 19.7% females |
STEMI = ST-elevation myocardial infarction
The primary endpoint was the occurrence of the composite of an occluded infarct-related artery (defined as TIMI Flow Grade 0 or 1) on the predischarge angiogram, or death or recurrent myocardial infarction by the time of the start of coronary angiography. For patients who did not undergo angiography, the primary endpoint was death or recurrent myocardial infarction by day 8 or by hospital discharge, if prior to Day 8.
Secondary efficacy assessments were based on the following endpoints analyzed in a hierarchical order [established for interpretation of the 3 secondary endpoints: an early electrocardiographic endpoint (degree of ST segment resolution at 180 minutes after first dose of study drug); a late angiographic endpoint (occluded IRA on predischarge angiogram); and a clinical endpoint [composite outcome of death, recurrent MI, or recurrent myocardial ischemia (severe or leading to revascularization) by the time of start of angiography or Day 8 or hospital discharge, whichever came first].
The patient population was mostly Caucasian (89.5%) and included 19.7% women and 29.2% patients ≥ 65 years. A total of 99.7% of patients received fibrinolytics (fibrin specific: 68.7%, non-fibrin specific: 31.1%, 89.5% heparin), 78.7% beta-blockers, 54.7% ACE inhibitors and 63% statins.
The number of patients who reached the primary endpoint was 262 (15.0%) in the clopidogrel-treated group and 377 (21.7%) in the placebo group, representing an absolute reduction of 6.7% and a 36 % reduction in the odds of the primary endpoint in favor of treatment with clopidogrel (95% CI: 0.53, 0.76; p < 0.001), as shown in Figure 3 below:
Figure 3: Event Rates for the Primary Composite Endpoint in the CLARITY Study
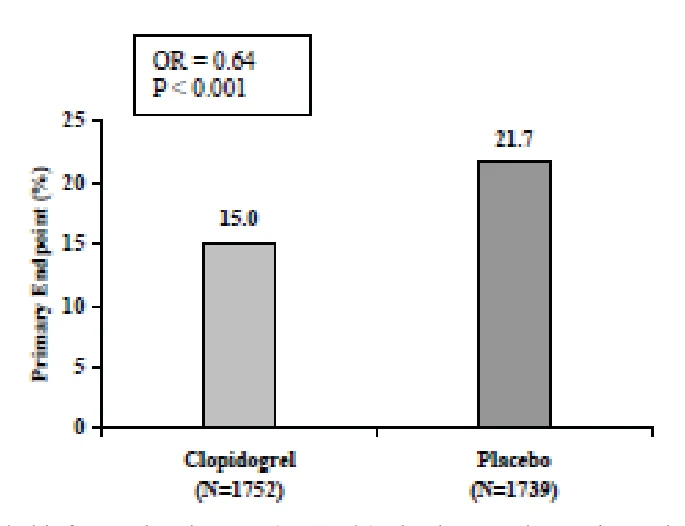
Based on odds of an occluded infarct-related artery (TFG 0/1), death or MI by angiography for clopidogrel versus placebo (OR: 0.64 [0.53 to 0.76]; p < 0.001)
The benefit of clopidogrel on the primary endpoint was consistent across all prespecified subgroups including patients’ age and gender, infarct location, and type of fibrinolytic or heparin used.
Table 15- Components of the primary endpoint: occluded IRA on the predischarge angiogram, or death or recurrent MI by the time of start of predischarge angiography, or Day 8 or hospital discharge, whichever came first (ITT population) in the CLARITY Study
| Clopidogrel 300/75 mga | Placeboa | Odds Ratio (95% CI) | p value | |
Occluded IRA N n (%) of patients reporting endpoint Death N n (%) of patients reporting endpoint Recurrent MI N n (%) of patients reporting endpoint | 1640 192 (11.7%) 1752 45 (2.6%) 1752 44 (2.5%) | 1634 301 (18.4%) 1739 38 (2.2%) 1739 62 (3.6%) | 0.59 (0.48, 0.72) 1.17 (0.75, 1.82) 0.70 (0.47, 1.04) | <0.001 0.492 0.077 |
a With background ASA and initial fibrinolytic therapy.
The secondary endpoints are listed in the table below:
Table 16- Secondary efficacy endpoint analyses (ITT population) in the CLARITY Study
| Secondary Efficacy Endpoint | Clopidogrel 300/75 mga | Placeboa | p value | Mean Difference | 95% CI |
| Adjusted mean ST segment resolution of an ECG at 180 minutes after the first dose of study drug | N = 1068 53.0 | N = 1021 55.1 | 0.223b | -2.11 | -5.50,1.28 |
| Secondary Efficacy Endpoint | Clopidogrel 300/75 mg | Placebo | p value | Odds Ratio | 95% CI |
Number (%) of patients with occluded IRA on predischarge angiogram | N = 1640 192 (11.7%) | N = 1634 301 18.4%) | <0.001b | 0.59 | 0.48,0.72 |
Number (%) of patients with death, recurrent MI, or recurrent myocardial ischemia (severe or leading to revascularization) by the time of the start of predischarge angiography c | N = 1752 145 (8.3%) | N = 1739 162 (9.3%) | 0.274b | 0.88 | 0.69,1.11 |
a: With background ASA and initial fibrinolytic therapy.
b: p-value to be interpreted following the hierarchical procedure described in the CLARITY Study c: For patients who did not undergo angiography, Day 8 or hospital discharge, whichever came first, was used.
COMMIT
The randomized, double-blind, placebo-controlled, 2x2 factorial design COMMIT trial included 45,852 patients presenting within 24 hours of the onset of the symptoms of suspected myocardial infarction with supporting ECG abnormalities (i.e., ST elevation, ST depression or left bundle-branch block). Patients were randomized to receive clopidogrel (75 mg/day) or placebo, in combination with ASA (162 mg/day), for 28 days or until hospital discharge whichever came first.
Table 17- Summary of patient demographics for COMMIT trial in STEMI patients
| Study # | Trial Design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (range) | Gender |
CCS-2/ COMMIT | International, randomized, double-blind, placebo- controlled study comparing clopidogrel + ASA to placebo + ASA, 2 by 2 factorial design | Dosage: clopidogrel (75 mg daily) or placebo in addition to ASA (162 mg daily to be taken simultaneously with the study drug) Administration: oral Duration: Maximum 4 weeks (in hospital) | n = 45 852 clopidogrel: n = 22 961 ASA: n = 22 891 | 61.3 years (15-100) | 72.2% male 27.8% female |
STEMI = ST-elevation myocardial infarction
The co-primary endpoints were death from any cause and the first occurrence of re-infarction, stroke or death.
The patient population included 27.8% women, 58.4% patients ≥ 60 years (26% patients ≥ 70 years) and 54.5% patients who received fibrinolytics. As shown in Table 18 and Figures 4 and 5 below, with clopidogrel the relative risk of death from any cause was reduced by a statistically significant 7% (p = 0.029) as was the relative risk of the combination of re-infarction, stroke or death (9%, p = 0.002).
Table 18: Outcome Events in the COMMIT Analysis
| Event | clopidogrel (+ASA) (N = 22961) | Placebo (+ASA) (N = 22891) | Odds ratio (95% CI) | p-value |
Composite endpoint: Death, MI, or Stroke* | 2121 (9.2%) | 2310 (10.1%) | 0.91 (0.86, 0.97) | 0.002 |
Death Non-fatal MI** Non-fatal Stroke** | 1726 (7.5%) 270 (1.2%) 127 (0.6%) | 1845 (8.1%) 330 (1.4%) 142 (0.6%) | 0.93 (0.87, 0.99) 0.81 (0.69, 0.95) 0.89 (0.70, 1.13) | 0.029 0.011 0.33 |
*The difference between the composite endpoint and the sum of death+non-fatal MI+non-fatal stroke indicates that 9 patients (2 clopidogrel and 7 placebo) suffered both a non-fatal stroke and a non-fatal MI. ** Non-fatal MI and non-fatal stroke exclude patients who died (of any cause).
Figure 4: Cumulative Event Rates for Death in the COMMIT Study *
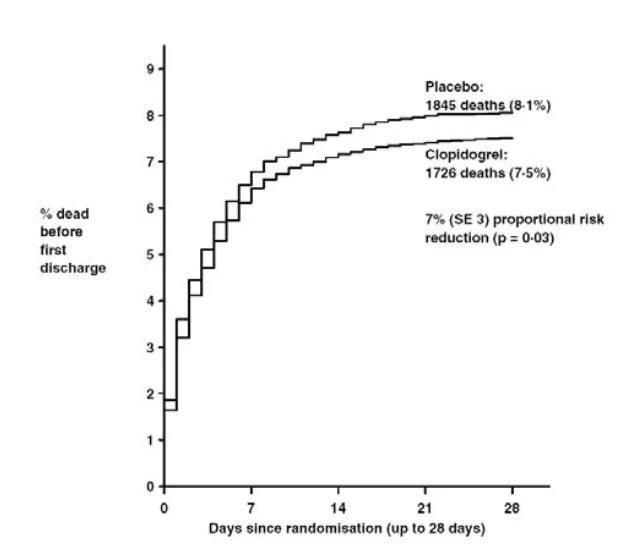
* All treated patients received ASA.
Figure 5: Cumulative Event Rates for the Combined Endpoint Re-Infarction, Stroke or
Death in the COMMIT Study *
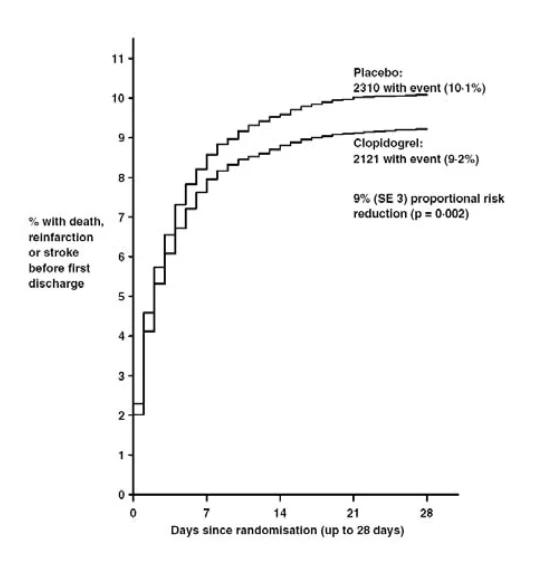
* All treated patients received ASA.
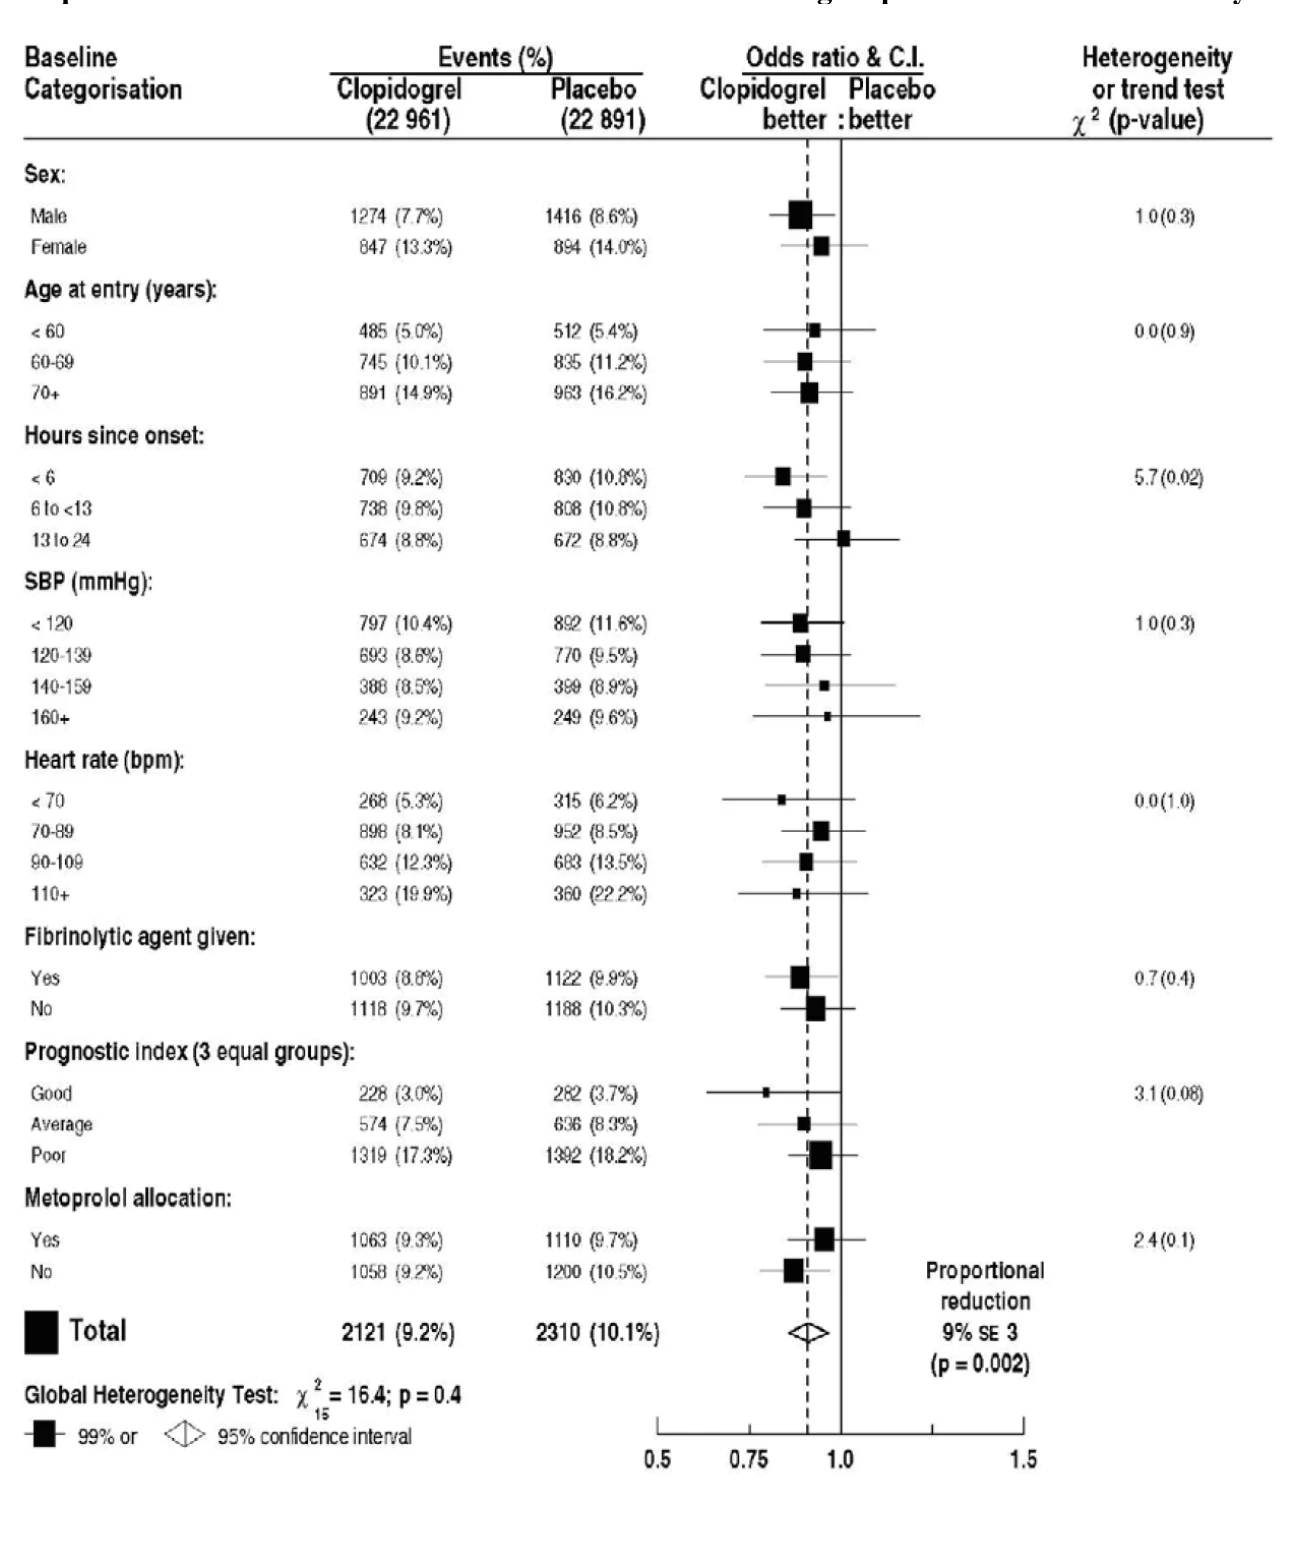
The benefit associated with clopidogrel on the combined endpoint was consistent across age, gender and with or without fibrinolytics as shown in Figure 6, and was observed as early as 24 hours.
Figure 6: Proportional Effects of Adding Clopidogrel to ASA on the Combined Primary Endpoint across Baseline and Concomitant Medication Subgroups for the COMMIT Study
ATRIAL FIBRILLATION
ACTIVE A
The ACTIVE W and ACTIVE A studies, separate trials in the ACTIVE program, included patients with atrial fibrillation (AF) who had at least one risk factor for vascular events. Based on enrollment criteria, physicians enrolled patients in ACTIVE W if they were candidates for vitamin K antagonist (VKA) therapy (such as warfarin). The ACTIVE A study included patients who could not receive VKA therapy because they were considered inappropriate for VKA therapy or unwilling to receive the treatment (see enrollment criteria below).
The ACTIVE A study (N=7,554) was a multicenter, randomized, double blind, placebo controlled study which compared clopidogrel 75 mg/day + ASA (N=3,772) to placebo + ASA (N=3,782). The recommended dose for ASA was 75 to 100 mg/day. Patients were treated for up to 5 years (mean treatment duration: 2.7 years).
Patients randomized in the ACTIVE program were those presenting with documented AF, i.e., either permanent AF or at least 2 episodes of intermittent AF in the past 6 months, and had at least one of the following risk factors: age ≥75 years; or age 55 to 74 years and either diabetes mellitus requiring drug therapy, or documented previous MI or documented coronary artery disease; treated for systemic hypertension; prior stroke, transient ischemic attack (TIA), or non-CNS systemic embolus; left ventricular dysfunction with left ventricular ejection fraction <45%; or documented peripheral vascular disease. The mean CHADS2 score was 2.0 (range 0-6).
Overall, 72.6% of patients enrolled into the ACTIVE A study were unable to take VKA. More specifically, the reasons for being enrolled in ACTIVE A instead of ACTIVE W are included in Table 19 below.
The criteria to enroll patients into ACTIVE A (rather than ACTIVE W were: patients’ unwillingness to take warfarin, patients’ inability to comply with INR monitoring, specific bleeding risk and physician’s assessment that oral vitamin K antagonist treatment was inappropriate.
Table 19: Factors influencing decision to enroll patients in ACTIVE A
Factor Groupinga
Clopidogrel
+ ASA (N=3772)
Placebo + ASA (N=3782)
All
(N=7554)
Specific Bleeding Risk 870 (23.1%) 861 (22.8%) 1731 (22.9%)
Inability to comply with INR monitoring 810 (21.5%) 831 (22.0%) 1641 (21.7%)
Physician Assessment VKA Inappropriate 1061 (28.1%) 1055 (27.9%) 2116 (28.0%)
Patient Preference Only 969 (25.7%) 995 (26.3%) 1964 (26.0%)
Factor missing 62 (1.6%) 40 (1.1%) 102 (1.4%) a Specific risk of bleeding includes any of the following: a predisposition to falls or head trauma, persistent elevation of blood pressure to more than 160/100 mmHg, previous serious bleeding while receiving oral anticoagulants (OAC), history of severe alcohol abuse, chronic renal insufficiency, documented peptic ulcer disease in the last year, thrombocytopenia, or requirement for chronic NSAID therapy. Inability to comply with INR monitoring includes no such bleeding risk. Physician Assessment VKA is inappropriate includes no such bleeding risk or INR monitoring compliance issue.
Table 20 -Summary of patient demographics for ACTIVE A trial in patients with atrial fibrillation
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Sex |
| ACTIVE A | Phase 3, randomized, double-blind, placebo-controlled superiority trial of clopidogrel plus ASA versus ASA alone | Dosage: clopidogrel (75 mg tablets once daily) in addition to ASA (75-100 mg once daily recommended) or ASA alone (75-100 mg once daily) Administration: oral Duration: Maximum 5 years | n=7,554 clopidogrel 75 mg/day + ASA: n=3772; Placebo + ASA: n=3782 | 71.0 years (25-102) | 58% male 42% female |
The patient population was mostly Caucasian (73.1%) and included 41.8% women. The mean age was 71 ± 10.2 years and 41.6% of patients were ≥75 years. A total of 23.0% of patients received antiarrhythmics, 52.1% beta-blockers, 54.6% ACE inhibitors, and 25.4% statins.
The number of patients who reached the primary endpoint (time to first occurrence of stroke, MI, non-CNS systemic embolism or vascular death) was 832 (22.1%) in the group treated with clopidogrel + ASA and 924 (24.4%) in the placebo + ASA group (see Table 21).
Table 21: Summary of frequency of adjudicated primary outcome event- first occurrence (ITT - adjudicated outcome events)
No. (%) of Events
Primary Outcome
clopidogrel
+
ASA
(N=3772)
Placebo +
ASA
(N=3782)
Relative Risk
Reduction (%)
(95% CI)
p-Value
MI/Stroke/Non-CNS systemic embolism/Vascular
death a
832 (22.06) 924 (24.43) 11.1 (2.4 to 19.1) 0.0133
MI (fatal or not) 84 (2.23) 105 (2.78)
Stroke (fatal or not) 285 (7.56) 391 (10.34)
Non-CNS systemic embolism 50 (1.33) 48 (1.27)
Vascular death 413 (10.95) 380 (10.05)
a Only the first event was counted
CNS = central nervous system; MI = myocardial infarction
The annual event rate was 6.8% and 7.6% for clopidogrel + ASA and placebo + ASA, respectively.
The benefit of clopidogrel + ASA was noted in the first few months of treatment and was maintained throughout the duration of the study up to 5 years; the rate of primary events was consistently lower in the clopidogrel + ASA group compared with the placebo + ASA group.
The reduction in the risk of major vascular events in the group treated with clopidogrel + ASA was primarily due to a large reduction in the incidence of strokes. Strokes occurred in 285 (7.6%) patients receiving clopidogrel + ASA and 391 (10.3%) patients receiving placebo + ASA. Table 22 and Figure 7 present the incidence of stroke as a secondary outcome event.
The rate of ischemic strokes (secondary outcome event) was significantly lower in the clopidogrel + ASA group than in the placebo + ASA group (6.2% vs. 9.1%; relative risk reduction, 32.4%; 95% CI, 20.2% to 42.7%) (Table 21). There was a numerical increase in the rate of hemorrhagic stroke in the placebo + ASA group compared to clopidogrel + ASA (from 22 (0.6%) to 30 (0.8%); relative risk reduction of -36.3 (risk is increased in the clopidogrel + ASA group); CI -136 to 21.4) (see Table 22).
The risk of stroke of any severity (non-disabling, disabling and fatal) was reduced with the use of clopidogrel + ASA. 69 fewer disabling or fatal strokes (modified Rankin score, 3 to 6) and 46 fewer non disabling strokes (modified Rankin score, 0 to 2) were reported with clopidogrel + ASA as compared to placebo + ASA.
There was a trend for reduction in the rates of myocardial infarction in the group treated with clopidogrel + ASA (relative risk reduction, 21.9%; 95% CI, -3% to 40.7%; p=0.08). The rates of non-CNS systemic embolism and death from vascular causes were similar between the two groups.
Table 22: Summary of frequency of secondary and other outcomes (ITT – adjudicated outcome events)*
No. (%) of Events
Outcome
clopidogrel +
ASA
(N=3772)
Placebo + ASA (N=3782)
Relative Risk Reduction (%)
(95% CI)
p-Value
Stroke (fatal or not) 296 (7.85) 408 (10.79) 28.4 (16.8 to 38.3) 0.00001 Ischemic Stroke 235 (6.23) 343 (9.07) 32.4 (20.2 to 42.7) Hemorrhagic Stroke 30 (0.80) 22 (0.58) -36.3 (-136 to 21.4) Uncertain Stroke 41 (1.09) 51 (1.35) 19.6 (-21.4 to 46.7) Total Death 825 (21.87) 841 (22.24) 1.9 (-8.0 to 10.9) 0.6958 MI (fatal or not) 90 (2.39) 115 (3.04) 21.9 (-3.0 to 40.7) 0.0789 Vascular Death 600 (15.91) 599 (15.84) -0.2 (-12.2 to 10.5) 0.9759 Non-CNS systemic embolism 54 (1.43) 56 (1.48) 3.5 (-40.3 to 33.6) 0.8521 * Patients who have had the specified outcome event but the event may not have been the first occurrence. CNS = central nervous system; MI = myocardial infarction
The annual event rate for stroke was 2.4% and 3.3% for clopidogrel + ASA and placebo + ASA, respectively.
Figure 7: Event rate over time for stroke (Adjudicated secondary outcome events)
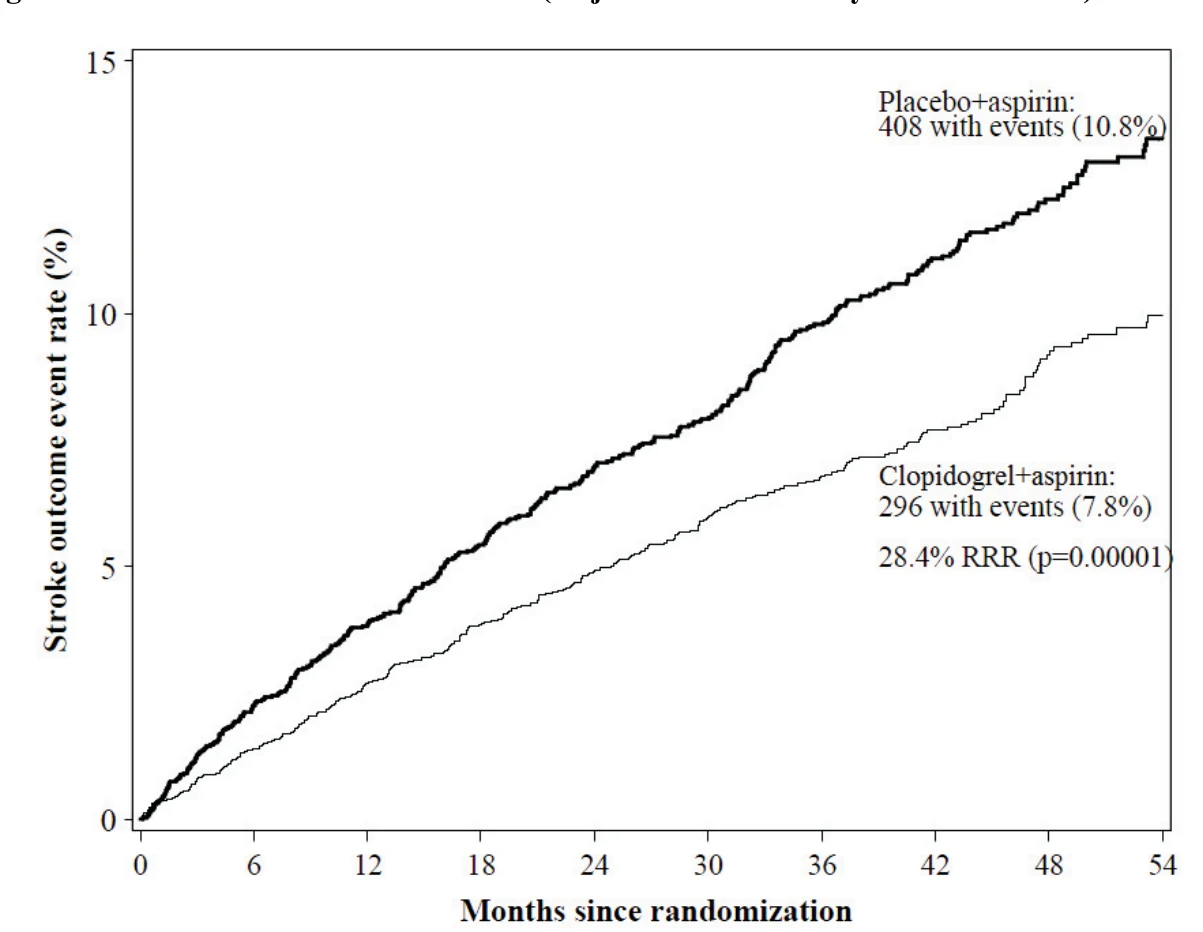
The effect of clopidogrel + ASA for the primary outcome (i.e. major vascular events) and stroke was consistent in all subgroups as shown in Figures 8 and 9.
Figure 8: Relative risks for various baseline and disease subgroups according to treatment for the primary efficacy outcome in ACTIVE A
Subgroup N Clopidogrel
+aspirin Placebo+aspirin P(Int) Clopidogrel+aspirin Better Placebo+aspirin Better
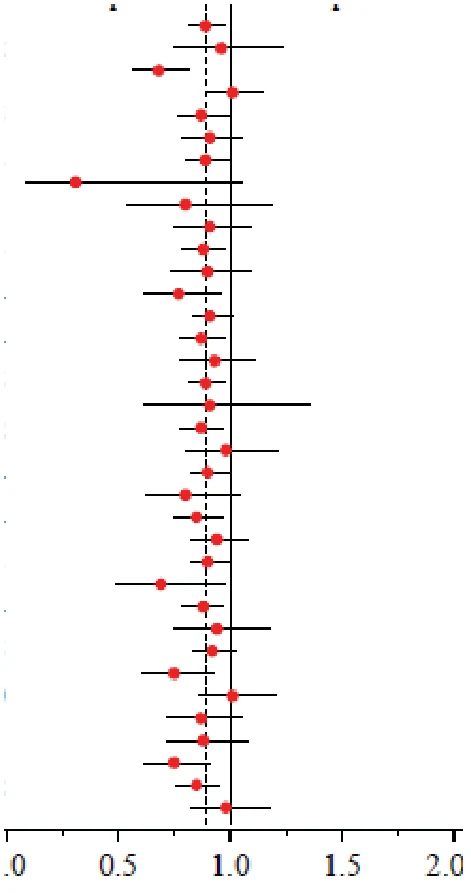
Overall 7554 6.75 7.61
Age (<65) 1866 3.7 3.87 0.2482
Age (65-74) 2549 5.04 7.39
Age (>=75) 3139 10.57 10.44
Gender (Male) 4397 6.32 7.24 0.6975
Gender (Female) 3157 7.38 8.13
Race (Caucasian) 5519 6.3 7.06 0.8763
Race (Black) 33 7.97 20.23
Race (Asian/Oriental) 367 7.05 8.75
Race (Other) 1635 8.31 9.16
Diabetes (No) 6089 6.34 7.19 0.8803
Diabetes (Yes) 1462 8.51 9.49
Hypertension (No) 1125 7.49 9.78 0.1684
Hypertension (Yes) 6427 6.62 7.25
CAD (No) 5688 6.25 7.16 0.5504
CAD (Yes) 1863 8.37 9
PAD (No) 7332 6.54 7.36 0.8515
PAD (Yes) 219 16.06 17.4
Prior MI (No) 6475 6.11 7.02 0.3202
Prior MI (Yes) 1078 11.09 11.34
Prior stroke (No) 6920 6.38 7.06 0.3944
Prior stroke (Yes) 633 11.51 14.37
Heart failure (No) 5054 5.11 6.02 0.2904
Heart failure (Yes) 2496 10.5 11.18
Prior TIA (No) 7123 6.63 7.36 0.1143
Prior TIA (Yes) 430 8.67 12.92
Previous bleeding (No) 6440 6.45 7.36 0.5574
Previous bleeding (Yes) 1113 8.58 9.08
Previous stroke/TIA (No) 6561 6.3 6.87 0.0905
Previous stroke/TIA (Yes) 992 9.99 13.43
Enrollment Grouping (Bleeding) 1731 10.77 10.63 0.1480
Enrollment Grouping (INR) 1641 7.42 8.57
Enrollment Grouping (Physician) 2116 4.99 5.67
Enrollment Grouping (Patient) 1964 4.9 6.57
AF Type (Permanent) 4814 7.84 9.21 0.1982
AF Type (Persis/Parox) 2723 4.98 5.08
HR (95% CI)
Note (post hoc factor groupings): Specific risk of bleeding includes any of the following: a predisposition to falls or head trauma, persistent elevation of blood pressure to more than 160/100 mmHg, previous serious bleeding while receiving oral anticoagulants (OAC), history of severe alcohol abuse, chronic renal insufficiency, documented peptic ulcer disease in the last year, thrombocytopenia, or requirement for chronic NSAID therapy. Inability to comply with INR monitoring includes no such bleeding risk. Physician Assessment of OAC inappropriate includes no such bleeding risk or INR monitoring compliance issue.
Figure 9: Relative risks for various baseline and disease subgroups according to treatment for the stroke outcome (ACTIVE A)
Subgroup N Clopidogrel
+aspirin
Placebo+aspirin P(Int) Clopidogrel+aspirin Better rlacebo+aspirin
Better
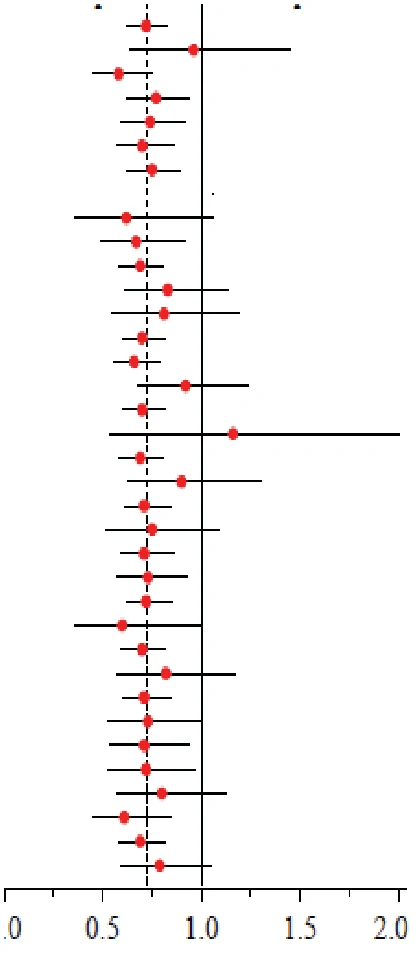
Overall 7554 2.37 3.31
Age (<65) 1866 1.34 1.4 0.9221 Age (65-74) 2549 2.08 3.61 Age (>=75) 3139 3.37 4.4 Gender (Male) 4397 1.91 2.58 0.7067 Gender (Female) 3157 3.04 4.34 Race (Caucasian) 5519 2.26 3.04 0.4299 Race (Black) 33 1.14 0 Race (Asian/Oriental) 367 3.38 5.48 Race (Other) 1635 2.54 3.8 Diabetes (No) 6089 2.19 3.2 0.2967 Diabetes (Yes) 1462 3.14 3.81 Hypertension (No) 1125 2.61 3.2 0.4761 Hypertension (Yes) 6427 2.33 3.33 CAD (No) 5688 2.26 3.42 0.0654 CAD (Yes) 1863 2.74 3 PAD (No) 7332 2.31 3.29 0.1737 PAD (Yes)* 219 4.94 4.12 Prior MI (No) 6475 2.23 3.26 0.1795 Prior MI (Yes) 1078 3.31 3.67 Prior stroke (No)
Prior stroke (Yes)
6920
633
2.14
5.36
3
7.15
0.8041
Heart failure (No) 5054 2.17 3.05 0.8686 Heart failure (Yes) 2496 2.85 3.9 Prior TIA (No) 7123 2.29 3.17 0.4277 Prior TIA (Yes) 430 3.67 6.36 Previous bleeding (No) 6440 2.25 3.23 0.4241 Previous bleeding (Yes) 1113 3.1 3.78 Previous stroke/TIA (No) 6561 2.07 2.93 0.9152 Previous stroke/TIA (Yes) 992 4.53 6.31 Enrollment Grouping (Bleeding) 1731 3.31 4.62 0.7227 Enrollment Grouping (INR) 1641 2.74 3.83 Enrollment Grouping (Physician) 2116 1.73 2.17 Enrollment Grouping (Patient) 1964 1.86 3.05 AF Type (Permanent) 4814 2.75 3.99 0.4457 AF Type (Persis/Parox) 2723 1.76 2.23
HR (95% CI)
* The upper CI for patients with PAD is 2.46. Note (post hoc factor groupings): Specific risk of bleeding includes any of the following: a predisposition to falls or head trauma, persistent elevation of blood pressure to more than 160/100 mmHg, previous serious bleeding while receiving oral anticoagulants (OAC), history of severe alcohol abuse, chronic renal insufficiency, documented peptic ulcer disease in the last year, thrombocytopenia, or requirement for chronic NSAID therapy. Inability to comply with INR monitoring includes no such bleeding risk. Physician Assessment of OAC inappropriate includes no such bleeding risk or INR monitoring compliance issue.
DETAILED PHARMACOLOGY
Pharmacodynamics:
Clopidogrel is a potent inhibitor of platelet aggregation, active in vivo against a large spectrum of inducers. Due to this antiaggregating effect, clopidogrel has a powerful antithrombotic activity in various models of thrombosis and prolongs bleeding time; it also inhibits the development of myointimal hyperplasia after injury of the vascular endothelium by preventing platelet adhesion.
The pharmacological profile of clopidogrel can be summarized as follows:
- Antiaggregating effect: after administration to various animal species, clopidogrel inhibits platelet aggregation induced by ADP and other agonists which release ADP from platelet storage. Clopidogrel is not active "in vitro". The failure to identify an active metabolite in plasma and the long lasting effect on platelets indicate that after hepatic metabolization, the active entity formed (probably a labile and highly reactive derivative) interacts rapidly with platelets and induces an irreversible modification at the level of ADP receptor.
- Hemostasis: a dose dependent prolongation of bleeding time was observed after clopidogrel treatment. This effect is related to the antiaggregating activity, as clopidogrel has no anticoagulant or fibrinolytic activity.
- Thrombosis: clopidogrel inhibits thrombus formation in a large variety of models. This is consistent with the capacity of clopidogrel to reduce aggregation induced by various agonists. The onset of the antithrombotic effect of clopidogrel and its potency closely correlate with those described for its antiaggregating activity.
- Atherogenesis: Clopidogrel reduces the development of intimal hyperplasia after injury of the endothelium. This effect is mainly due to the inhibition of platelet adhesion and of the release of platelet-derived growth factors at the site of vascular injury.
Studies to determine the general pharmacological properties of clopidogrel were carried out on major systems including: the central nervous system (mouse, rat); autonomic nervous system (dog); cardiovascular system (rat, dog); respiratory system (dog, guinea pig); gastrointestinal system (mouse, rat); and urinary system (rat). The anti-inflammatory activity (rat) was also tested.
Minor side effects appeared only at high dose levels (≥ 62.5 mg/kg) (see table 23 below). The high ratio between these doses and the antiaggregating doses active against thrombosis (ED50 ~ 1 to 5 mg/kg), indicates a wide margin of safety for clopidogrel.
Table 23: Summary of the main general pharmacodynamic effects of clopidogrel
| SYSTEM | SPECIES | DOSE (mg/kg) | EFFECTS |
| Nervous | Mouse | oral 250 | Slight analgesic effect of peripheral origin (20-30%a) |
| Mouse | oral 62.5-250 | Slight potentiation of barbiturate-induced narcosis (15-40%a) | |
| Rat | oral 125-250 | Slight EEG changes (similar to those induced by a nootropic agent) | |
| Cardiovascular | Dog | IDc 125-250 | Decrease in cardiac output (-15 to 25%b) |
| Respiratory | Dog | IDc 62.5-250 | Slight increase in respiratory frequency (5-7 cycles/min.b) |
| Guinea pig | IDc 250 | Moderate and transient antagonistic effect on serotonin-induced Bronchospasm | |
| Gastro-intestinal | Rat | oral 200 | Decrease (-36%a) in gastric emptying |
a: Modification versus mean value of control group
b: Modification versus values before administration
c: ID = intraduodenal route
Pharmacokinetics:
The pharmacokinetics of clopidogrel after single oral administration was studied in the rat and monkey. The oral absorption of clopidogrel in rats was complete while in monkeys it was estimated to be about 80%. The plasma concentration of clopidogrel was higher in female than in male rats. In the 20-400 mg/kg clopidogrel dose range, the rat plasma concentrations of clopidogrel increased proportionally with the dose administered, while in monkeys it increased more than proportionally with the dose. Following administration of 14C-labeled clopidogrel in rats, the excretion of radioactivity was mainly by feces (through the bile) while in monkeys radioactivity was roughly equally excreted in urine and feces. Distribution of 14C-labeled clopidogrel was studied in rats and radioactivity was found mainly in excretory organs and the pancreas. The transfer of radioactivity across the blood brain barrier was low. During gestation, low levels of radioactivity were found in the embryo or foetuses and placenta. There were three primary metabolic pathways of clopidogrel in rats and monkeys: (i) hydrolysis of the ester group by carboxylesterases, (ii) sulfoxidation and (iii) oxidation of the tetrahydropyridine.
TOXICOLOGY
Preclinical toxicity studies were conducted with clopidogrel bisulfate which evaluated the systemic, carcinogenic, genotoxic, reproductive, immunogenic and ancillary effects of the compound.
Acute toxicity
At very high single doses by oral administration of clopidogrel (≥1500 mg/kg in rodents, and ≥500 mg/kg in baboons), lung congestion or labored breathing, and a poor gastric tolerability (gastric erosions and/or vomiting) were reported in rats, mice and baboons. In mice, the oral LD50 value was about 2603 mg/kg in males and 2379 mg/kg in females. The intravenous LD50 value was about 160 mg/kg in males and females. In rats, the oral LD50 value was about 2420 mg/kg in males and 1910 mg/kg in females. The intravenous LD50 value was about 110 mg/kg in males and females.
Chronic toxicity
During preclinical studies in rats and baboons, the most frequently observed effects at very high doses (more than 300 times the therapeutic dose of 75 mg/day on a mg/kg basis) were acute gastritis, gastric erosions and/or vomiting. At lower doses, an increase in liver weight was observed in mice, rats and baboons associated with increases in cholesterol plasma levels in rats and baboons, and a slight hypertrophy of the smooth endoplasmic reticulum in centrilobular hepatocytes in rats. No histopathological changes were seen in mice or baboons. The liver findings were a consequence of an effect on hepatic metabolising enzymes observed at high doses, a phenomenon that is generally recognized as having no relevance to humans receiving lower therapeutic doses. After one year of treatment at doses representing between 7 and 9 times (rats) or between 10 and 23 times (baboon), the exposure seen in humans receiving the clinical dose of 75 mg/day, none of these effects were observed.
Carcinogenicity
There was no evidence of tumorigenicity when clopidogrel was administered for 78 weeks to mice and 104 weeks to rats at dosages up to 77 mg/kg/day, which afforded plasma exposures >25 times that in humans at the recommended daily dose of 75 mg/day.
Mutagenicity
Clopidogrel was not genotoxic in four in vitro tests (Ames test, DNA-repair test in rat hepatocytes, gene mutation assay in Chinese hamster fibroblasts, and chromosome aberration test in human lymphocytes). In vivo, clopidogrel had no clastogenic activity in the micronucleus test performed in mice by the oral route.
Teratogenicity and impairment of fertility
Clopidogrel was found to have no effect on the fertility of male and female rats and was not teratogenic in either rats or rabbits (at doses up to 52 times the recommended human dose on a mg/m2 basis). When given to lactating rats, clopidogrel caused a slight delay in the development of the offspring. Specific pharmacokinetic studies performed with radiolabelled clopidogrel have shown that the parent compound or its metabolites are excreted in the milk. Consequently, a direct effect (slight toxicity), or an indirect effect (low palatability) cannot be excluded.
Other studies
Clopidogrel was not toxic to bone marrow pluripotent stem cells in mice and did not cause any immunotoxic effects in rats and baboons. In the guinea pig, clopidogrel has no antigenic activity and had no phototoxic or photoallergic activity.
Clopidogrel had no promoting activity using an in vitro assay for inhibition of intercellular communication of liver cells in culture.
REFERENCES
- 1. Boneu B, Destelle G. Platelet anti-aggregating activity and tolerance of clopidogrel in atherosclerotic patients. Thromb Haemost. 1996;76: 6:939-943.
- 2. CAPRIE Steering Committee. A randomized, blinded trial of clopidogrel versus aspirin in patients at risk of ischaemic events (CAPRIE). Lancet. 1996; 348: 1329-39.
- 3. Collet JP et al. Cytochrome P450 2C19 polymorphism in young patients treated with clopidogrel after myocardial infarction: a cohort study. The Lancet 2009;373:309-317.
- 4.
COMMIT (ClOpidogrel and Metoprolol in Myocardial Infarction Trial) Collaborative
Group. COMMIT: randomized placebo-controlled trial of adding clopidogrel to aspirin in 45 852 patients with acute myocardial infarction. Lancet 2005; 366: 1607-1621.
- 5.
CURE Study Investigators. The Clopidogrel in Unstable angina to prevent Recurrent Events
(CURE) trial programme: rationale, design and baseline characteristics including meta-analysis of the effects of thienopyridines in vascular disease. Eur Heart J. 2000;21:2033-2041.
- 6. Giusti B et al. Relation of cytochrome P450 2C19 loss-of-function polymorphism to occurrence of drug-eluting coronary stent thrombosis. Am J Cardiol 2009; 103:806–811.
- 7.
Herbert J-M. Clopidogrel and antiplatelet therapy. Expert Opin. Invest. Drugs. 1994;3:
5:449-455.
- 8. Herbert J-M, Bernat A, Savi P. Hypercholesterolemia does not affect the antiplatelet activity of clopidogrel. Platelets (Edinb). 1995;6: 6:412-413.
- 9.
Mega JL et al. Cytochrome P-450 polymorphisms and response to clopidogrel. N Engl J
Med 2009; 360:354-62.
- 10. Mills DC, Puri R, Hu CJ, et al. Clopidogrel inhibits the binding of ADP analogues to the receptor mediating inhibition of platelet adenylate cyclase. Arterioscler Thromb. 1992;12: 4:430-6.
- 11. Sabatine et al. Addition of clopidogrel to aspirin and fibrinolytic therapy for myocardial infarction with ST-segment elevation. NEJM. 2005; 352: 1179-1189.
- 12.
Savi P, Heilmann E, Nurden P, et al. Clopidogrel: An antithrombotic drug acting on the
ADP-dependent activation pathway of human platelets. Clin Appl Thromb Hemost. 1996;2: 1:35-42.
- 13. Sibbing D et al. Cytochrome P450 2C19 loss-of-function polymorphism and stent thrombosis following percutaneous coronary intervention. Eur Heart J 2009: 30: 916-22.
- 14.
Simon T et al. Genetic determinants of response to clopidogrel and cardiovascular events. N
Engl J Med 2009; 360(4):363-75.
- 15. The ACTIVE Investigators. Effect of clopidogrel added to aspirin in patients with atrial fibrillation, Table 3. N Engl J Med 2009;360:2066-78
- 16. The Clopidogrel in Unstable angina to prevent Recurrent Events trial investigators. Effects of clopidogrel in addition to aspirin in patients with acute coronary syndromes without ST-segment elevation (CURE). N Engl J Med. 2001;345:494-502.
- 17. Trenk D et al. Cytochrome P450 2C19 681G>A polymorphism and high on-clopidogrel platelet reactivity associated with adverse 1-year clinical outcome of elective percutaneous coronary intervention with drug-eluting or bare-metal stents. J Am Coll Cardiol 2008; 51, 20: 1925-34.
- 18.
Product Monograph for PLAVIX (clopidogrel tablets) by sanofi-aventis Canada Inc. (control
#170659) date of revision: February 25, 2014.