


Product Monograph - Advil Plus Acetaminophen
Recent Major Label Changes
2 Contraindications 3 Serious Warnings and Precautions Box 7 Warnings and Precautions; Monitoring and Laboratory Tests – Pregnancy; Special Populations | 2025-08 |
|---|
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................2
TABLE OF CONTENTS ..............................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION ..........................................................4
1 INDICATIONS ..................................................................................................................4
1.1 Pediatrics ..................................................................................................................4
1.2 Geriatrics ..................................................................................................................4
2 CONTRAINDICATIONS .................................................................................................5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ...................................................6
4 DOSAGE AND ADMINISTRATION .............................................................................6
4.1 Dosing Considerations ...............................................................................................6
4.2 Recommended Dose and Dosage Adjustment ...........................................................7
4.3 Administration ...........................................................................................................7
4.4 Missed Dose ...............................................................................................................7
5 OVERDOSAGE .................................................................................................................7
6 DOSAGE FORMS, COMPOSITION AND PACKAGING ........................................11
7 WARNINGS AND PRECAUTIONS .............................................................................12
7.1 Special Populations ..................................................................................................18
7.1.1 Pregnant Women………………………………………………………………19
7.1.2 Breast-feeding…………………………………………………………………20
7.1.3 Pediatrics………………………………………………………………………20
7.1.4 Geriatrics………………………………………………………………………20
8 ADVERSE REACTIONS ................................................................................................20
8.1 Adverse Reaction Overview ....................................................................................20
8.2 Clinical Trial Adverse Reactions .............................................................................21
8.2.1 Clinical Trial Adverse Reactions – Pediatrics………………………..……….23
8.3 Less Common Clinical Trial Adverse Reactions .....................................................23
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...............................................................................................................23
8.5 Post-Market Adverse Reactions ...............................................................................23
9 DRUG INTERACTIONS ................................................................................................27
9.1 Serious Drug Interactions ........................................................................................27
9.2 Drug Interactions Overview .....................................................................................28
9.3 Drug-Behavioural Interactions.................................................................................28
9.4 Drug-Drug Interactions ............................................................................................28
9.5 Drug-Food Interactions ............................................................................................31
9.6 Drug-Herb Interactions ............................................................................................31
9.7 Drug-Laboratory Test Interactions ..........................................................................31
10 CLINICAL PHARMACOLOGY ...................................................................................31
10.1 Mechanism of Action .........................................................................................31
10.2 Pharmacodynamics ............................................................................................32
10.3 Pharmacokinetics ...............................................................................................33
11 STORAGE, STABILITY AND DISPOSAL .................................................................37
12 SPECIAL HANDLING INSTRUCTIONS ....................................................................37
PART II : SCIENTIFIC INFORMATION ...............................................................................38
13 PHARMACEUTICAL INFORMATION ......................................................................37
14 CLINICAL TRIALS ........................................................................................................40
14.1 Trial Design and Study Demographics ..............................................................40
14.2 Study Results .....................................................................................................43
15 MICROBIOLOGY ..........................................................................................................48
16 NON-CLINICAL TOXICOLOGY ................................................................................48
17 SUPPORTING PRODUCT MONOGRAPHS ..............................................................52
PATIENT MEDICATION INFORMATION ...........................................................................53
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Advil Plus Acetaminophen (Ibuprofen and Acetaminophen) is indicated for temporary:
- relief of migraine pain
- relief of headaches including tension headache
- relief of muscle aches and pain
- relief of joint and body pain
- relief of backache
- relief of muscle sprains and strains
- relief of aches and pain due to the common cold
- relief of pain from inflammation associated with arthritis and physical or athletic overexertion (e.g. sprains or strains)
- relief of dental pain
- relief of pre-menstrual & menstrual pain
and reduction of fever
1.1 Pediatrics
Pediatrics (< 18 years of age)): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Advil Plus Acetaminophen in pediatric patients < 18 years of age has not been established. Therefore, Health Canada has not authorized an indication for children < 18 years of age (See WARNINGS AND PRECAUTIONS).
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety and a brief discussion can be found in the appropriate sections (See WARNINGS AND PRECAUTIONS).
2 CONTRAINDICATIONS
- Active peptic ulcer, a history of recurrent ulceration or active inflammatory disease of the gastrointestinal system.
- Known or suspected hypersensitivity to acetaminophen ibuprofen or other non-steroidal anti-inflammatory drugs. Patients who are hypersensitive to acetaminophen, ibuprofen or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph. The potential for cross-reactivity between different NSAIDs must be kept in mind.
- Advil Plus Acetaminophen should not be used in patients with the complete or partial syndrome of nasal polyps, or in whom asthma, anaphylaxis, urticarial/angioedema, rhinitis or other allergic manifestations are precipitated by ASA or other nonsteroidal anti-inflammatory agents. Fatal anaphylactoid reactions have occurred in such individuals. As well, individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse effects.
- Hepatic impairment or active liver disease.
- Severely impaired or deteriorating renal function (creatinine clearance <30 mL/min). Individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs and must be monitored.
- Advil Plus Acetaminophen is not recommended for use with other NSAIDs because of the absence of any evidence demonstrating synergistic benefits and the potential for additive side effects.
- Patients should not take more than the recommended dose of acetaminophen, or take it with other products containing acetaminophen because severe or possibly fatal liver damage may occur. Alcohol may potentiate the hepatotoxic effects of acetaminophen.
- Advil Plus Acetaminophen should not be used during third trimester of pregnancy because of risk of premature closure of the ductus arteriosus, and prolonged parturition.
- Advil Plus Acetaminophen should not be used right before or after heart surgery.
- Advil Plus Acetaminophen is contraindicated in patients with systemic lupus erythematosus, as an anaphylaxis-like reaction with fever may occur, particularly when ibuprofen has been administered previously.
- Known hyperkalemia (see Warnings and Precautions - Renal - Fluid and Electrolyte Balance).
- Children and adolescents less than 18 years of age (see INDICATIONS).
3 SERIOUS WARNINGS AND PRECAUTIONS
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Do not take for fever for more than 3 days or for pain for more than 5 days unless directed by a physician. The lowest effective dose should be used for the shortest possible duration. Advil Plus Acetaminophen is not for long term use.
Serious Warnings and Precautions
- Use with caution in patients with heart failure, hypertension or other conditions predisposing to fluid retention (See WARNINGS AND PRECAUTIONS, Cardiovascular and Fluid and Electrolyte Balance; and DRUG INTERACTIONS, Drug-Drug Interactions, Ibuprofen, Antihypertensives).
- Caution in patients prone to gastrointestinal tract irritation, including those with a history of peptic ulcer (See WARNINGS AND PRECAUTIONS, Gastrointestinal DRUG INTERACTIONS, Drug-Drug Interactions, Ibuprofen, Coumarin-type anticoagulants).
- Patients at greatest risk of renal toxicity are those with impaired renal function, heart failure, liver dysfunction, those taking diuretics and the elderly (See WARNINGS AND PRECAUTIONS, Renal).
- Patients should not take more than the recommended dose of acetaminophen, or take it with other products containing acetaminophen because severe or possibly fatal liver damage may occur. Alcohol may potentiate the hepatotoxic effects of acetaminophen. (See DRUG INTERACTIONS, Drug-Drug Interactions, Acetaminophen, Acetaminophen)
- If urinary symptoms, hematuria and cystitis occur, the drug should be stopped immediately (See WARNINGS AND PRECAUTIONS, Genitourinary).
- Risk in Pregnancy: Caution should be exercised in prescribing Advil Plus Acetaminophen during the first and second trimesters of pregnancy or breastfeeding. Use of NSAIDS at approximately 20 weeks of gestation or later may cause oligohydramnios, and renal dysfunction including renal failure (See Oligohydramnios/Neonatal Renal Impairment, Pregnant Women and Breast-feeding).
- Advil Plus Acetaminophen is contraindicated for use during the third trimester because of risk of premature closure of the ductus arteriosus and uterine inertia (prolonged parturition) (see CONTRAINDICATIONS).
4.2 Recommended Dose and Dosage Adjustment
Adults of 18 years and over: Take 2 tablets every 8 hours while symptoms persist. Do not exceed 6 tablets in 24 hours, unless directed by a doctor. Do not take more than directed (see liver warning). Do not use longer than 3 days for a fever or 5 days for pain relief.
Advil Plus Acetaminophen provides up to 8 hours of pain relief.
4.3 Administration
See Recommended Dose and Dosage Adjustment.
4.4 Missed Dose
Take the missed dose as soon as you remember. If it is almost time for your next dose, wait until then to take your medicine and skip your missed dose. Do not take two doses at the same time.
5 OVERDOSAGE
IBUPROFEN
Symptoms of Overdose
The toxicity of ibuprofen overdose is dependent upon the amount of drug ingested and the time elapsed since ingestion; individual responses may vary, thus making it necessary to evaluate each case separately. Although uncommon, serious toxicity and death have been reported with ibuprofen overdosage. The most frequently reported symptoms of ibuprofen overdose include abdominal pain, nausea, vomiting, lethargy and drowsiness. Other CNS symptoms include headache, tinnitus, CNS depression and seizures. Metabolic acidosis, coma, acute renal failure and apnoea (primarily in very young pediatric patients) may rarely occur. Cardiovascular toxicity, including hypotension, bradycardia, tachycardia and atrial fibrillation, have also been reported.
Treatment of Overdose
In cases of acute overdose, the stomach should be emptied through induction of emesis (in alert patients only) or gastric lavage. Emesis is most effective if initiated within 30 minutes of ingestion. Orally administered activated charcoal may help in reducing the absorption of ibuprofen when given less than 2 hours following ingestion. There is some evidence that repeated administration of activated charcoal may bind the medication that has diffused from the circulation. Inducing diuresis may be helpful. The treatment of acute overdose is primarily supportive. Management of hypotension, acidosis and gastrointestinal bleeding may be necessary.
In pediatric patients, the estimated amount of ibuprofen ingested per body weight may be helpful to predict the potential for development of toxicity although each case must be evaluated. Ingestion of less than 100 mg/kg is unlikely to produce toxicity. Pediatric patients ingesting 100 to 200 mg/kg may be managed with induced emesis and a minimal observation time of at least four hours. Pediatric patients ingesting 200 to 400 mg/kg of ibuprofen should have immediate gastric emptying and at least four hours observation. Pediatric patients ingesting greater than 400 mg/kg require immediate medical referral, careful observation and appropriate supportive therapy. Induced emesis is not recommended in overdoses greater than 400 mg/kg because of the risk for convulsions and the potential for aspiration of gastric contents.
In adult patients, the dose reportedly ingested does not appear to be predictive of toxicity. The need for referral and follow-up must be judged by the circumstances at the time of the overdose ingestion. Symptomatic adults should be carefully evaluated, observed and supported.
Examples of Ibuprofen Overdose
A 41-year-old man with multiple medical problems, including long-term renal insufficiency, developed near-fatal acute renal failure after ingestion of a massive dose (36 g) of ibuprofen. He required dialysis for several months, at which point his renal function improved.
In children, ibuprofen overdoses less than 100 mg/kg are unlikely to produce toxicity. In adults, the dose of ibuprofen reportedly ingested does not appear to be predictive of toxicity.
With electrolyte replacement and other intensive measures, a 21-month-old child recovered within 5 days after accidental ingestion of 8 g of ibuprofen. A 2-year-old child who ingested approximately 8 g of ibuprofen was treated with activated charcoal, developed metabolic acidosis and acute renal insufficiency, and recovered within 72 hours. A 6-year-old child became comatose after ingesting 6 g of ibuprofen. He was treated with gastric lavage, charcoal, and various supportive measures and recovered within 24 hours.
ACETAMINOPHEN
Acetaminophen
In adults and adolescents (≥ 12 years of age), hepatic toxicity may occur following ingestion of greater than 7.5 to 10 grams over a period of 8 hours or less. Fatalities are infrequent (less than
3-4% of untreated cases) and have rarely been reported with overdoses of less than 15 grams. In children (<12 years of age), an acute overdosage of less than 150 mg/kg has not been associated with hepatic toxicity. Early symptoms following a potentially hepatotoxic overdose may include:
anorexia, nausea, vomiting, diaphoresis, pallor and general malaise. Clinical and laboratory evidence of hepatic toxicity may not be apparent until 48 to 72 hours post-ingestion (Temple
2005).
The following are clinical events associated with acetaminophen overdose that if seen with overdose are considered expected, including fatal events due to fulminant hepatic failure or its sequelae.
Table 2. Adverse Drug Reactions Identified with Overdose of Acetaminophen
Metabolism and Nutrition Disorders:
Anorexia
Anorexia Gastrointestinal Disorders:
Vomiting, Nausea, Abdominal discomfort
Hepatobiliary Disorders:
Hepatic necrosis, Acute hepatic failure, Jaundice, Hepatomegaly, Liver tenderness
General Disorders and Administration Site Conditions: Pallor, Hyperhidrosis, Malaise
Investigations:
Blood bilirubin increased, Hepatic enzymes increased, international normalized ratio increased, Prothrombin time prolonged, Blood phosphate increased, Blood lactate increased
The following clinical events are sequelae to acute hepatic failure and may be fatal. If these events occur in the setting of acute hepatic failure (Feldman 2006, Flomenbaum 2006) associated with acetaminophen overdose (adults and adolescents: > 12 years of age:> 7.5 gm within 8 hours; children < 12 years of age: >150 mg/kg within 8 hours), they are considered expected.
Table 3: Expected Sequelae to Acute Hepatic Failure Associated with Acetaminophen Overdose
Infections and Infestations:
Sepsis, Fungal infection, Bacterial infection
Blood and Lymphatic System Disorders:
Disseminated intravascular coagulations, Coagulopathy, Thrombocytopenia
Metabolism:
Hypoglycemia, Hypophosphatemia, Metabolic Acidosis, Lactic Acidosis
Nervous System Disorders:
Coma (with massive acetaminophen overdose or multiple drug overdose), Encephalopathy, Brain Oedema
Cardiac Disorders:
Cardiac myopathy
Vascular Disorders:
Hypotension
Respiratory, Thoracic and Mediastinal Disorders:
Respiratory Failure
Gastrointestinal Disorders:
Pancreatitis, Gastrointestinal haemorrhage
Renal and Urinary Disorders:
Acute renal failure
General Disorders and Administration Site Conditions:
Multi-organ failure
Hepatic injury is the principal toxic effect of a substantial acetaminophen overdose. The physician should be mindful that there is no early presentation that is pathognomic for the overdose. A high degree of clinical suspicion must always be maintained.
Untreated acetaminophen overdoses may produce hepatotoxicity. Acetaminophen hepatotoxicity occurs as a threshold effect and is characterized by a lack of toxicity at lower/therapeutic doses.
Acetaminophen hepatotoxicity occurs after major depletion of glutathione, an endogenous detoxifying substance. Once the threshold is exceeded, increasing acetaminophen doses may produce increasing degrees of hepatotoxicity, unless N-acetylcysteine (NAC) is administered.
The clinical course of acetaminophen overdose generally occurs in a three-phase sequential pattern. The first phase begins shortly after ingestion and lasts for 12 to 24 hours. The patient may manifest signs of gastrointestinal irritability, nausea, vomiting, anorexia, diaphoresis, pallor and general malaise. If toxicity continues, there is a latent phase of up to 48 hours. During this second phase, initial symptoms abate and the patient may feel better. However, hepatic enzymes, bilirubin, and prothrombin time or INR values will progressively rise. Right upper quadrant pain may develop as the liver becomes enlarged and tender. Most patients do not progress beyond this phase, especially if given N-acetylcysteine (NAC) treatment early in the course. Signs and symptoms of the third phase depend on the severity of hepatic damage and usually occur from three to five days following overdose ingestion. Symptoms may be limited to anorexia, nausea, general malaise, and abdominal pain in less severe cases or may progress to confusion, stupor and sequelae of hepatic necrosis including jaundice, coagulation defects, hypoglycemia, and encephalopathy, as well as renal failure and cardiomyopathy. Death, if it occurs, is generally the result of complications associated with fulminant hepatic failure. Mortality rates in patients with toxic plasma levels who do not receive antidote therapy range from 3% to 4%.
Due to the wide availability of acetaminophen, it is commonly involved in single and mixed drug overdose situations and the practitioner should screen for its presence in a patient’s serum.
Acute toxicity after single dose overdoses of acetaminophen can be anticipated when the overdose exceeds 150 mg/kg. Chronic alcohol abusers, cachectic individuals, patients with liver disease, and persons taking pharmacologic inducers of the hepatic P450 microsomal enzyme system may be at risk with lower exposures.
Specific Antidote: Any individual presenting with a possible acetaminophen overdose should be treated with N-acetylcysteine (NAC), even if the amount of acetaminophen ingested is unknown or questionable. A blood sample for determination of the plasma acetaminophen concentration should be obtained as early as possible, but no sooner than four hours following ingestion. Do not await the results of assays for plasma acetaminophen levels before initiating treatment NAC.
If the acetaminophen plasma level is found to plot above the treatment line on the acetaminophen overdose nomogram, NAC treatment should be continued for a full course of therapy. NAC is used clinically to treat acute acetaminophen overdose, and acts by interacting with the oxidative intermediate, NAPQI. NAC administered by either the i.v. or the oral route is known to be a highly effective antidote for acetaminophen poisoning. It is most effective when administered within 8 hours of a significant overdose but reports have indicated benefits to treatment initiated well beyond this time period. It is imperative to administer the antidote as early as possible in the time course of acute intoxication to reap the full benefits of the antidote's protective effects. For full prescribing information, consult the product monograph for NAC.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, COMPOSITION AND PACKAGING
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal ingredients |
|---|---|---|
| Oral | Tablet, 125 mg ibuprofen, 250 mg acetaminophen. | Carnauba wax, croscarmellose sodium, glyceryl behenate, hypromellose, iron oxides, macrogol 400, pharmaceutical ink, polydextrose, pregelatinized starch, silicon dioxide, titanium dioxide. |
Advil Plus Acetaminophen Tablets are capsule-shaped, film-coated yellow tablets with ‘Advil II’ printed in black ink on one side.
Advil Plus Acetaminophen Tablets are available in bottles in quantities of 18, 36, 72 and 144 tablets and in pouches consisting of 2 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
To minimize the potential risk for an adverse event, the lowest effective dose should be used for the shortest possible duration. Advil Plus Acetaminophen is not for long term use.
In common with other anti-inflammatory drugs, ibuprofen may mask the usual signs of infection.
Advil Plus Acetaminophen is NOT recommended for use with other NSAIDs because of the absence of any evidence demonstrating synergistic benefits and the potential for additive adverse reactions. (See Drug Interactions - Drug/Drug Interactions - Ibuprofen - Acetylsalicylic acid (ASA) or other NSAIDs)
Patients should not take more than the recommended dose of acetaminophen, or take it with other products containing acetaminophen because severe or possibly fatal liver damage may occur. Alcohol may potentiate the hepatotoxic effects of acetaminophen. (See Drug Interactions - Drug/Drug Interactions – Acetaminophen – Acetaminophen)
In case of an overdose, medical help or a poison control center should be contacted immediately. Prompt medical attention is critical, even in the absence of signs or symptoms.
Carcinogenesis and Mutagenesis
Not applicable.
Cardiovascular
Use of ibuprofen may precipitate congestive heart failure in patients with marginal cardiac function, elevated blood pressure and palpitations.
Long term continuous use may increase the risk of heart attack or stroke.
Dependence/Tolerance
Not applicable.
Ear/Nose/Throat
Patients with complete or partial syndrome of nasal polyps should not use Advil Plus Acetaminophen (See CONTRAINDICATIONS).
Endocrine and Metabolism
Not applicable.
Fluid and Electrolyte Balance
Fluid retention and edema have been observed in patients treated with ibuprofen. Therefore, as with many other nonsteroidal anti-inflammatory drugs, the possibility of precipitating congestive heart failure in elderly patients or those with compromised cardiac function should be borne in mind. Advil Plus Acetaminophen should be used with caution in patients with heart failure, hypertension or other conditions predisposing to fluid retention.
With nonsteroidal anti-inflammatory treatment there is a potential risk of hyperkalemia, particularly in patients with conditions such as diabetes mellitus or renal failure; elderly patients; or in patients receiving concomitant therapy with ß-adrenergic blockers, angiotensin converting enzyme inhibitors or some diuretics. Serum electrolytes should be monitored periodically during long-term therapy, especially in those patients who are at risk.
Gastrointestinal
Serious GI toxicity, such as peptic ulceration, perforation and gastrointestinal bleeding, sometimes severe and occasionally fatal, can occur at any time, with or without symptoms in patients treated with NSAIDs including ibuprofen.
Minor upper GI problems, such as dyspepsia, are common, usually developing early in therapy. Physicians should remain alert for ulceration and bleeding in patients treated with non-steroidal anti-inflammatory drugs, even in the absence of previous GI tract symptoms.
In patients observed in clinical trials of such agents, symptomatic upper GI ulcers, gross bleeding, or perforation appear to occur in approximately 1% of patients treated for 3-6 months and in about 2-4% of patients treated for one year. The risk continues beyond one year and possibly increases. The incidence of these complications increases with increasing dose.
Advil Plus Acetaminophen should be given under close medical supervision to patients prone to gastrointestinal tract irritation, particularly those with a history of peptic ulcer, diverticulosis or other inflammatory disease of the gastrointestinal tract such as ulcerative colitis and Crohn's disease. In these cases the physician must weigh the benefits of treatment against the possible hazards.
Physicians should inform patients about the signs and/or symptoms of serious GI toxicity and instruct them to contact a physician immediately if they experience persistent dyspepsia or other symptoms or signs suggestive of gastrointestinal ulceration or bleeding. Because serious GI tract ulceration and bleeding can occur without warning symptoms, physicians should follow chronically treated patients by checking their hemoglobin periodically and by being vigilant for the signs and symptoms of ulceration and bleeding and should inform the patients of the importance of this follow-up.
If ulceration is suspected or confirmed, or if GI bleeding occurs, Advil Plus Acetaminophen should be discontinued immediately, appropriate treatment instituted and the patient monitored closely.
No studies, to date, have identified any group of patients not at risk of developing ulceration and bleeding. The major risk factors are a prior history of serious GI events and increasing age. Possible risk factors include other factors such as Helicobacter pylori infection, excess alcohol intake, smoking, female gender and concomitant oral steroid and anticoagulant, anti-coagulants, anti-platelet agents (including ASA) or selective serotonin reuptake inhibitors (SSRI’s) have been associated with increased risk. Studies to date show that all NSAIDs can cause GI tract adverse events. Although existing data does not clearly identify differences in risk between various NSAIDs, this may be shown in the future.
There is no definitive evidence that the concomitant administration of histamine H2-receptor antagonists and/or antacids will either prevent the occurrence of gastrointestinal side effects or allow the continuation of Advil therapy when and if these adverse reactions appear.
Genitourinary
Some NSAIDs are known to cause persistent urinary symptoms (bladder pain, dysuria, urinary frequency), hematuria or cystitis. The onset of these symptoms may occur at any time after the initiation of therapy with an NSAID. Some cases have become severe on continued treatment. Should urinary symptoms occur, treatment with Advil Plus Acetaminophen must be stopped immediately to obtain recovery. This should be done before any urological investigations or treatments are carried out.
Hematologic
Drugs inhibiting prostaglandin biosynthesis do interfere with platelet function to varying degrees; therefore, patients who may be adversely affected by such an action such as those on anti-coagulants or suffering from haemophillia or platelet disorders should be carefully observed when ibuprofen is administered. Numerous studies have shown that the concomitant use of NSAIDs and anti-coagulants increases the risk of bleeding. Concurrent therapy with warfarin requires close monitoring of the international normalized ratio (INR). Even with therapeutic INR monitoring, increased bleeding may occur. (See Drug Interactions)
Blood dyscrasias (such as neutropenia, leukopenia, thrombocytopenia, aplastic anemia and agranulocytosis) associated with the use of non-steroidal anti-inflammatory drugs are rare, but could occur with severe consequences.
Hepatic/Biliary/Pancreatic
As with other nonsteroidal anti-inflammatory drugs, borderline elevations of one or more liver function tests may occur in up to 15% of patients. These abnormalities may progress, may remain essentially unchanged, or may be transient with continued therapy. A patient with symptoms and/or signs suggesting liver dysfunction, or in whom an abnormal liver test has occurred, should be evaluated for evidence of the development of more severe hepatic reaction while on therapy with this drug. Severe hepatic reactions including jaundice and cases of fatal hepatitis have been reported with nonsteroidal anti-inflammatory drugs.
Although such reactions are rare, if abnormal liver tests persist or worsen, if clinical signs and symptoms consistent with liver disease develop, or if systemic manifestations occur (e.g. eosinophilia, rash, etc.), this drug should be discontinued.
During long-term therapy, liver function tests should be monitored periodically. If there is a need to prescribe this drug in the presence of impaired liver function, it must be done under strict observation.
The frequency of acute liver injury among 625,307 people who received NSAIDs in England and Wales between 1987 and 1991, was examined. There were 311,716 patients who were prescribed ibuprofen. The incidence of acute liver injury among ibuprofen users was 1.6/100,000; this was the lowest incidence among the 8 NSAIDs studied and was significantly lower than the incidence among users of ketoprofen, piroxicam, fenbrufen, or sulindac. For NSAID users as a group, the only factors that had an independent effect on the occurrence of acute liver injury were the simultaneous use of hepatotoxic medication or the presence of rheumatoid arthritis. Based on these data, the short-term use of ibuprofen as an analgesic/antipyretic should not be of concern regarding the development of liver disease.
Slower metabolism of acetaminophen, increased activity of the cytochrome P450 enzyme system, or depleted glutathione stores are cited as theoretical risk factors for acetaminophen hepatotoxicity in patients with chronic liver disease. However, acetaminophen has been studied in both adults and children with a wide variety of liver diseases including various types of cirrhosis, hepatitis (including hepatitis C), nodular transformation, congenital hepatic fibrosis, and α1-antitrypsin deficiency. In none of these conditions is there evidence of an increased risk for hepatotoxicity at currently recommended acetaminophen doses but the studies were insufficiently powered to definitely establish the extent of risk.
Forrest et al (1979) compared acetaminophen metabolism following a single 1500 mg dose in normal subjects, patients with mild liver disease, and patients with severe liver disease. There were no significant differences in overall 24-hour urinary excretion of acetaminophen and glucuronide, sulfate, cysteine, and mercapturic acid conjugates, evidence that acetaminophen metabolism was similar to that in normal subjects. However, the elimination half-life was significantly prolonged in patients with severe liver disease.
Acetaminophen may cause hepatotoxicity in situations of intentional overdose (e.g. attempted suicide), unintentional overdose (e.g. overdosing when pain relief is not satisfactory), simultaneous use of multiple acetaminophen-containing preparations, accidental overdose or in very rare cases, after recommended doses, although causality has not been determined. The hepatotoxic reaction can be severe and life-threatening. Early symptoms following a hepatotoxic overdose may include nausea, vomiting, diaphoresis, lethargy, and general malaise. If appropriate treatment is not instituted, these may progress to upper quadrant pain, confusion, stupor, and sequelae of hepatic necrosis, such as jaundice, coagulation defects, hypoglycemia, and encephalopathy. Renal failure and cardiomyopathy may also occur. In the event of known or suspected overdosage, treatment with N-acetyl cysteine should be instituted immediately (see OVERDOSAGE, Acetaminophen), even when there are no obvious symptoms. Failure to promptly treat acetaminophen hepatotoxicity with N-acetyl cysteine can result in liver failure, leading to liver transplantation and/or death.
Immune
Patients with complete or partial syndrome of nasal polyps, rhinitis or other allergic manifestations should not use ASA or other anti-inflammatory agents. Fatal anaphylactoid reactions have occurred in such individuals even if they have taken NSAIDs in the past without any adverse effects (See Contraindications).
In occasional cases, with some NSAIDs, the symptoms of aseptic meningitis (stiff neck, severe headaches, nausea and vomiting, fever or clouding of consciousness) have been observed. Patients with autoimmune disorders (systemic lupus erythematosus, mixed connective tissue diseases, etc.) seem to be pre-disposed. Therefore, in such patients, the physician must be vigilant to the development of this complication.
Monitoring and Laboratory Tests
For Monitoring and Laboratory Tests related to the use of Advil Plus Acetaminophen see WARNINGS AND PRECAUTIONS, Fluid and Electrolyte Balance, Gastrointestinal, Hematologic, Hepatic, Renal and Special populations: Geriatrics.
Pregnancy: If Advil products are administered in the middle (approximately 20 weeks) to the end of the second trimester, it is recommended that pregnant women be closely monitored for amniotic fluid volume since these products may result in reduction of amniotic fluid volume and even oligohydramnios (see Special Populations). Advil products are contraindicated for use in the third trimester of pregnancy.
Neurologic
Some patients may experience drowsiness, dizziness, vertigo, tinnitus, hearing loss, insomnia or depression with the use of ibuprofen. If patients experience these side effects, they should exercise caution in carrying out activities that require alertness.
Ophthalmologic
Blurred and/or diminished vision has been reported with the use of ibuprofen and other non-steroidal anti-inflammatory drugs. If such symptoms develop, this drug should be discontinued and an ophthalmologic examination performed; ophthalmic examination should be carried out at periodic intervals in any patient receiving this drug for an extended period of time.
Peri-Operative Considerations
In general, NSAIDs should be discontinued prior to surgeries to decrease the risk of post-operative bleeding.
Psychiatric
See Warnings and Precautions, Neurologic.
Renal
Long term administration of nonsteroidal anti-inflammatory drugs to animals has resulted in renal papillary necrosis and other abnormal renal pathology. In humans, there have been reports of acute interstitial nephritis with hematuria, proteinuria, and occasionally nephrotic syndrome.
A second form of renal toxicity has been seen in patients with prerenal conditions leading to the reduction in renal blood flow or blood volume, where the renal prostaglandins have a supportive role in the maintenance of renal perfusion. In these patients, administration of a nonsteroidal anti-inflammatory drug may cause a dose dependent reduction in prostaglandin formation and may precipitate overt renal decompensation. Patients at greatest risk of this reaction are those with impaired renal function, heart failure, liver dysfunction, those taking diuretics, and the elderly. Discontinuation of nonsteroidal anti-inflammatory therapy is usually followed by recovery to the pre-treatment state.
Ibuprofen and its metabolites are eliminated primarily by the kidneys; therefore the drug should be used with great caution in patients with impaired renal function. In these cases, utilisation of lower doses of Advil Plus Acetaminophen should be considered and patients carefully monitored.
During long-term therapy kidney function should be monitored periodically.
Respiratory
ASA-induced asthma is an uncommon but very important indication of ASA and NSAID sensitivity. It occurs more frequently in patients with asthma who have nasal polyps.
Sensitivity/Resistance
Patients sensitive to any one of the nonsteroidal anti-inflammatory drugs may be sensitive to any of the other NSAIDs.
Sexual Function/Reproduction
Not applicable.
Skin
In rare cases, serious skin reactions such as Stevens-Johnson syndrome, toxic epidermal necrolysis, exfoliative dermatitis, DRESS (Drug Reaction with Eosinophilia and Systemic Symptoms), AGEP (Acute Generalized Exanthematous Pustulosis) and erythema multiforme have been associated with the use of NSAIDs and acetaminophen. Because the rate of these reactions is low, they have usually been noted during post-marketing surveillance in patients taking other medications also associated with the potential development of these serious skin reactions. Thus, causality is NOT clear. These reactions are potentially life threatening but may be reversible if the causative agent is discontinued and appropriate treatment instituted. Patients should be advised that if they experience skin reddening, blisters, and/or skin rash, they should discontinue this product, and contact their physician for assessment and advice, including which additional therapies to discontinue.
7.1 Special Populations
Oligohydramnios/Neonatal Renal Impairment:
Use of NSAIDs, including Advil Plus Acetaminophen, at approximately 20 weeks gestation or later in pregnancy may cause fetal renal dysfunction leading to oligohydramnios and, in some more severe cases, neonatal respiratory, musculoskeletal and renal problems (see TOXICOLOGY).
Published studies and post-marketing reports describe maternal NSAID use at approximately 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment, or failure. NSAIDs were shown to cause significant reduction in fetal urine production prior to reduction of amniotic fluid volume. There have also been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible, even after treatment discontinuation.
These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. Oligohydramnios is often, but not always, reversible with treatment discontinuation. Complications of prolonged oligohydramnios may, for example, include limb contractures and delayed lung maturation. In some post-marketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required.
If, after careful consideration of alternative treatment options for pain management, NSAID treatment is necessary anywhere from the middle (onset approximately 20 weeks) to the end of the second trimester of pregnancy, it is recommended that the use be limited to the lowest effective dose and shortest duration possible.
Consider ultrasound monitoring of fetal well-being, including of amniotic fluid volume assessment if treatment with Advil Plus Acetaminophen extends beyond 48 hours. It is recommended that NSAIDs treatment be discontinued if oligohydramnios occurs, followed by appropriate medical follow up.
Inform pregnant women not to use Advil Plus Acetaminophen and other NSAIDs from the third trimester of pregnancy because of the risk of the premature closing of the fetal ductus arteriosus (see CONTRAINDICATIONS). If treatment with Advil Plus Acetaminophen is needed for a pregnant woman anywhere from the middle (onset approximately 20 weeks gestation) to the end of the second trimester of pregnancy, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours.
7.1.1 Pregnant Women
Inhibition of prostaglandin synthesis may adversely affect pregnancy and/or embryo-fetal development. Data from epidemiological studies suggest an increased risk of miscarriage and of cardiac malformation after use of a prostaglandin synthesis inhibitor in early pregnancy.
ADVIL PLUS ACETAMINOPHEN is CONTRAINDICATED for use during the third trimester of pregnancy because of risk of premature closure of the ductus arteriosus and the potential to prolong parturition (see Toxicology).
Because of the known effects of NSAIDs on the fetal cardiovascular system, use of ibuprofen during late pregnancy should be avoided (see Oligohydramnios/Neonatal Renal Impairment).
Caution should be exercised in prescribing ADVIL PLUS ACETAMINOPHEN during the first and second trimesters of pregnancy (see Toxicology).
In animals, administration of a prostaglandin synthesis inhibitor has been shown to result in increased pre- and post-implantation loss and embryo-fetal lethality. In addition, increased incidences of various malformations, including cardiovascular, have been reported in animals given a prostaglandin synthesis inhibitor during the organogenetic period. As with other drugs known to inhibit prostaglandin synthesis, an increased incidence of dystocia and delayed parturition occurred in rats.
7.1.2 Breast-feeding
Caution should be exercised in prescribing ADVIL PLUS ACETAMINOPHEN during breast-feeding. The high protein binding and lower pH of breast milk versus plasma tend to inhibit the excretion of ibuprofen into breast milk. One study showed an ibuprofen concentration of 13 ng/mL 30 minutes after ingesting 400 mg. The milk:plasma ratio was 1:126. This translates to an infant exposure of 0.0008% of the maternal dose. It is not known to what extent, if any, ibuprofen crosses the human placenta.
Acetaminophen crosses the placenta, and is excreted in breast milk in low concentrations.
7.1.3 Pediatrics
The safety and efficacy of Advil Plus Acetaminophen in children <18 years of age have not been demonstrated.
7.1.4 Geriatrics (> 65 years of age)
Patients older than 65 years and frail or debilitated patients are most susceptible to a variety of adverse reactions from nonsteroidal anti-inflammatory drugs (NSAIDs): the incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. The chance of stomach bleeding is higher if you are: age 60 or older, have had stomach ulcers or bleeding problems, take a blood thinner or steroid drug, take with other drugs containing an NSAID like acetylsalicyclic acid (ASA), ibuprofen, naproxen, or prescription anti-inflammatory drugs, have 3 or more alcoholic drinks every day while using this product. Most reports of fatal GI events are in this population. Older patients are also at risk of lower oesophageal ulceration and bleeding.
For such patients, consideration should be given to a daily dose lower than the one usually recommended, with individual adjustment when necessary and under close supervision.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Safety and efficacy were evaluated in 7 clinical studies, including 3 pharmacokinetic (PK) studies, and 4 efficacy studies in pain and fever relief. The overall exposure in the clinical program included 1477 subjects, 715 of which received a dose of different Fixed Dose Combinations (FDCs) of ibuprofen/acetaminophen (varying amount of ibuprofen with the acetaminophen dose fixed at 500 mg). There were no Serious Adverse Events (SAEs) or deaths in these studies across any of the different fixed dose combination dose groups.
The intended FDC Ibuprofen (IBU) 250 mg/ Acetaminophen (APAP) 500 mg was well tolerated in the clinical program. The most commonly reported Treatment Emergent Adverse Events (TEAEs) (≥2%) in the FDC ibuprofen 250 mg/acetaminophen 500 mg dose group were: Nausea, Vomiting, and Dizziness.
No deaths, SAEs or severe Treatment Related Adverse Events (TRAEs) were reported in the clinical program. The safety profile of the FDC was similar to the individual monocomponents. No new safety signals were identified in any subgroup (sex, age, race and FDC dose groups).
8.2 Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
A total of 291 (19.7%) subjects who participated in the clinical program reported all causality Treatment-Emergent Adverse Events (TEAEs), most of which were mild or moderate in severity. Twenty-six (1.8%) subjects reported severe all causality Adverse Events (AE) (Table 1). A total of 26 out of 1477 (1.8%) subjects reported Treatment Related Adverse Events (TRAEs), all of which were mild or moderate in severity. No deaths, Severe Adverse Events (SAEs) or severe TRAEs were reported.
All the active treatment groups had a lower incidence of all causality Aes compared to placebo. The higher incidence of TEAEs in placebo subjects may have been due to lack of pain relief and use of opioid rescue medications in the dental pain studies, which could lead to Aes (eg, Nausea, Vomiting, and Dizziness). The incidence of TEAEs in the monocomponent groups (ibuprofen single ingredient product and acetaminophen single ingredient product) and the Fixed Dose Combination (FDC) Total treatment group (ibuprofen and acetaminophen combination product) were similar to each other and to the Total group. No new safety signals were identified.
| Table 1. Summary of Adverse Events - Number of Subjects | ||||||||||
| Table 1. Summary of Adverse Events - Number of Subjects | ||||||||||
| Number of Subjects (n, %) | ||||||||||
| Number of Subjects (n, %) | ||||||||||
| Total (N=1477) | FDC Total (N=715) | IBU (N=432) | APAP (N=330) | Placebo (N=156) | ||||||
| Total (N=1477) | FDC Total (N=715) | IBU (N=432) | APAP (N=330) | Placebo (N=156) | ||||||
| Treatment Emergent Adverse Events - All Causality | 291 (19.7) | 127 (17.8) | 72 (16.7) | 47 (14.2) | 49 (31.4) | |||||
| Serious Adverse Events - All Causality | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | |||||
| Non-Serious Treatment Emergent Adverse Events - All Causality | 291 (19.7) | 127 (17.8) | 72 (16.7) | 47 (14.2) | 49 (31.4) | |||||
| Treatment Related Adverse Events | 26 (1.8) | 13 (1.8) | 2 (0.5) | 3 (0.9) | 9 (5.8) | |||||
| Treatment Related Non-Serious Adverse Events | 26 (1.8) | 13 (1.8) | 2 (0.5) | 3 (0.9) | 9 (5.8) | |||||
| Adverse Events Leading to Discontinuation of Study Medication | 4 (0.3) | 3 (0.4) | 1 (0.2) | 0 (0.0) | 0 (0.0) | |||||
| Adverse Events Leading to Withdrawal of Subjects from Study | 4 (0.3) | 3 (0.4) | 1 (0.2) | 0 (0.0) | 0 (0.0) | |||||
| Adverse Events Caused Death | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | |||||
| Adverse Events with Severity: Severe | 26 (1.8) | 16 (2.2) | 6 (1.4) | 0 (0.0) | 4 (2.6) | |||||
| Treatment Related Adverse Events with Severity: Severe | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | |||||
FDC: Fixed Dose Combination IBU: Ibuprofen APAP: Acetaminophen | ||||||||||
The most commonly reported (≥2%) all causality TEAEs by System Organ Class (SOC) in this clinical program were Gastrointestinal disorders (220, 14.9%), Nervous system disorders (102, 6.9%), and General disorders and administration site conditions (32, 2.2%). The most commonly reported TEAEs (≥2%) in the clinical program were: Nausea, Vomiting, Dizziness, and Headache (Headache was reported at an incidence of ≥2% only in the placebo group).
The only TRAEs with an incidence of ≥2%, in the clinical program, were reported in the placebo group (Nausea and Vomiting).
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
No clinical efficacy and safety pediatric studies have been conducted for Advil Plus Acetaminophen.
8.3 Less Common Clinical Trial Adverse Reactions
In the clinical program, the only treatment-related Aes with an incidence of ≥2% were reported in the placebo group (PTs: Nausea and Vomiting). No severe TRAEs were reported in any of the other treatment groups. Only 13 subjects in the FDC Total dose group (N=715) reported 16 TRAEs with an incidence of <1.0%. These subjects were from FDC IBU 250 mg/APAP 500 mg dose group, who reported the following Aes:
Gastrointestinal disorders: Nausea (0.7%), Vomiting (0.3%), and Constipation (0.1%).
Nervous system disorders: Dizziness (0.4%), Headache (0.3%), and Somnolence (0.1%).
Skin and subcutaneous tissue disorders: Rash macular (0.1%).
General disorders and administration site conditions: Vessel puncture site bruise (0.1%).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data Clinical Trial Findings
Across the 7 studies, the vital signs data (included blood pressure, pulse rate, respiration rate, and oral temperature) were measured at baseline and at the end of study. The majority of the readings were within the normal ranges, and the changes from baseline were not considered clinically significant.
The clinical studies of Advil Plus Acetaminophen were not specifically designed to detect any abnormal laboratory values. The pharmacokinetic studies of Advil Plus Acetaminophen demonstrated that there is no potential drug interaction when the two drugs are administered together.
8.5 Post-Market Adverse Drug Reactions
Prescription Experience
IBUPROFEN
The following adverse reactions have been noted in patients treated with prescription doses (≥1200 mg/day).
Note: Reactions listed below under Causal Relationship Unknown are those which occurred under circumstances where a causal relationship could not be established. However, in these rarely reported events, the possibility of a relationship to ibuprofen cannot be excluded.
Gastrointestinal
The adverse reactions most frequently seen with prescribed ibuprofen therapy involve the gastrointestinal system.
Incidence 3 to 9%: nausea, epigastric pain, heartburn.
Incidence 1 to 3%: diarrhea, abdominal distress, nausea and vomiting, indigestion, constipation, abdominal cramps or pain, fullness of the gastrointestinal tract (bloating or flatulence).
Incidence < 1%: gastric or duodenal ulcer with bleeding and/or perforation, gastrointestinal hemorrhage, melena, hepatitis, jaundice, abnormal liver function (SGOT, serum bilirubin and alkaline phosphatase).
Allergic
Incidence less than 1%: anaphylaxis (see CONTRAINDICATIONS).
Causal relationship unknown: fever, serum sickness, lupus erythematosus.
Central Nervous System
Incidence 3 to 9%: dizziness.
Incidence 1 to 3%: headache, nervousness.
Incidence less than 1%: depression, insomnia.
Causal relationship unknown: paresthesias, hallucinations, dream abnormalities.
Aseptic meningitis and meningoencephalitis, in one case accompanied by eosinophilia in the cerebrospinal fluid, have been reported in patients who took ibuprofen intermittently and did not have any connective tissue disease.
Dermatologic
Incidence 3 to 9%: rash (including maculopapular type).
Incidence 1 to 3%: pruritus.
Incidence less than 1%: vesiculobullous eruptions, urticaria, erythema multiforme.
Causal relationship unknown: alopecia, Stevens-Johnson syndrome.
Cardiovascular
Incidence less than 1%: congestive heart failure in patients with marginal cardiac function, elevated blood pressure.
Causal relationship unknown: arrhythmias (sinus tachycardia, sinus bradycardia, palpitations).
Special Senses
Incidence 1 to 3%: tinnitus.
Incidence less than 1%: amblyopia (blurred and/or diminished vision, scotomata and/or changes in colour vision). Any patient with eye complaints during ibuprofen therapy should have an ophthalmological examination.
Causal relationship unknown: conjunctivitis, diplopia, optic neuritis.
Hematologic
Incidence less than 1%: leukopenia, and decreases in haemoglobin and hematocrit.
Causal relationship unknown: hemolytic anemia, thrombocytopenia, granulocytopenia, bleeding episodes (e.g., purpura, epistaxis, hematuria, menorrhagia).
Renal
Causal relationship unknown: decreased creatinine clearance, polyuria, azotemia.
Like other non-steroidal anti-inflammatory drugs, ibuprofen inhibits renal prostaglandin synthesis, which may decrease renal function and cause sodium retention. Renal blood flow and glomerular filtration rate decreased in patients with mild impairment of renal function who took 1200 mg/day of ibuprofen for one week. Renal papillary necrosis has been reported. A number of factors appear to increase the risk of renal toxicity (See WARNINGS AND PRECAUTIONS).
Hepatic
Incidence less than 1%: hepatitis, jaundice, abnormal liver function (SGOT, serum bilirubin, and alkaline phosphatase).
Endocrine
Causal relationship unknown: gynecomastia, hypoglycaemic reaction.
Menstrual delays of up to two weeks and dysfunctional uterine bleeding occurred in nine patients taking ibuprofen, 400 mg t.i.d., for three days before menses.
Metabolic
Incidence 1 to 3%: decreased appetite, edema, fluid retention.
Fluid retention generally responds promptly to drug discontinuation (See WARNINGS AND PRECAUTIONS).
Non-Prescription Experience: Literature (1992-1999) (at dosages ≤1200 mg/day)
One researcher conducted an extensive analysis of published data concerning the relative safety of non-prescription doses of ibuprofen and acetaminophen. Of a total of 96 randomized and blinded trials, there were 10 trials of seven days’ duration or less where the safety of both drugs was directly compared. In three of these trials, the incidence of adverse events was higher with acetaminophen; there were no reported adverse events in six trials; and one trial reported a higher incidence with ibuprofen. In this subset of 10 studies, it was reported that gastrointestinal adverse events were found to be the most common type of event reported and were predominantly dyspepsia, nausea, or vomiting. None of the GI events appeared to warrant follow-up from which the author inferred there were no serious gastrointestinal events.
It was concluded: “Although we recognize that the above mentioned data are very selective and are based on information derived from a variety of trial designs and populations, it is nonetheless instructive for indicating a relatively low incidence of severe adverse reactions with both drugs when taken at their respective non-prescription dosages.”
A double-blind, placebo-controlled study (N=1246) was conducted to prospectively evaluate the gastrointestinal tolerability, as compared to placebo, of the maximum non-prescription dose and duration (1200 mg/day for 10 consecutive days) of ibuprofen use in healthy subjects representative of a non-prescription analgesic user population.83 Gastrointestinal adverse experiences were similar in the placebo and ibuprofen groups (67 out of 413, 16% with placebo vs. 161 out of 833, 19% with ibuprofen). There was no difference between the two groups in the proportion of discontinuing due to a gastrointestinal event. Gastrointestinal adverse experiences reported by ≥1% of subjects were: dyspepsia, abdominal pain, nausea, diarrhea, flatulence, and constipation. Seventeen (1.4%) subjects had positive occult blood tests: their frequency was comparable between treatments. When used as directed to treat episodic pain, non-prescription ibuprofen at the maximum dose of 1200 mg/day for 10 days, is well-tolerated.
In two multi-trial analyses a meta analysis, and a literature review, single doses of ibuprofen had a low incidence of gastrointestinal drug reactions, comparable to that of acetaminophen and placebo. Reports from spontaneous reporting systems in the United Kingdom, France and the United States, where a prescription is not needed for ibuprofen at a daily dose up to 1200 mg, confirm the medication’s gastrointestinal safety and acceptability. A recently-completed large-scale randomized trial comparing non-prescription doses of acetylsalicylic acid, acetaminophen, and ibuprofen in 8677 adults found that the rates of significant adverse reactions were: aspirin 18.7%, ibuprofen 13.7%, and acetaminophen 14.5%. Ibuprofen was not statistically different from acetaminophen. Total gastrointestinal events (including dyspepsia) and abdominal pain were less frequent with ibuprofen (4% and 2.8%, respectively) than with acetaminophen (5.3% and 3.9%) or aspirin (7.1% and 6.8%) [all p< 0.035]. It was concluded that “The overall tolerability of ibuprofen in this large-scale study was equivalent to that of paracetamol and better than that of ASA.”
ACETAMINOPHEN
Reports of adverse reactions are rare. Although the following reactions have been reported, a causal relationship to the administration of paracetamol has been neither confirmed nor refuted: dyspepsia, nausea, allergic and hematological reactions.
Skin and subcutaneous tissue disorders – Very rare cases of serious skin reactions (including severe cutaneous reactions such as Stevens-Johnson Syndrome, Toxic Epidermal Necrolysis, and Acute Generalized Exanthematous Pustulosis) have been reported.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
Advil Plus Acetaminophen is not recommended for concomitant use with any other NSAIDs, including ASA and acetaminophen. Possible drug interactions with Advil Plus Acetaminophen include digoxin, anticoagulants, oral antidiabetic agents and insulin, antihypertensives, diuretics, methotrexate, lithium and other protein-bound drugs.
9.3 Drug-Behavioural Interactions
Severe or possibly fatal liver damage may occur if using while drinking three or more alcoholic drinks every day. Alcohol may potentiate the hepatotoxic effects of acetaminophen.
9.4 Drug-Drug Interactions
IBUPROFEN
Serious Drug Interactions
- With hepatotoxic medications (including alcohol) or hepatic enzyme inducers may increase the risk of hepatotoxicity.
- With certain anticoagulants such as warfarin, it may potentiate their effects with chronic ingestion of large doses of this product; anticoagulant dosage adjustment may be necessary.
- With acetylsalicylic acid (ASA) or other NSAIDs, may result in possible additive side effects (See CONTRAINDICATIONS).
- With anticoagulants may increase the risk of GI adverse events (e.g., ulceration and bleeding).
- With antihypertensives the benefit and risk must be weighed individually.
- With digoxin may increase serum digoxin concentration and the risk of digoxin toxicity.
- With diuretics may reduce the diuretic effect.
- With selective serotonin reuptake inhibitors (SSRIs) may increase the risk of GI adverse events (e.g., ulceration and bleeding).
- With glucocorticoids may increase the risk of GI adverse events (e.g., ulceration and bleeding).
- With lithium may elevate plasma lithium levels, reduce renal lithium clearance and increase the risk of lithium toxicity.
- With methotrexate may increase the risk of methotrexate toxicity.
Acetylsalicylic acid (ASA) or other NSAIDs
The use of Advil Plus Acetaminophen in addition to any other NSAID, including ASA, is not recommended due to the absence of any evidence demonstrating synergistic benefits and the possibility of additive side effects. Animal studies show that aspirin given with NSAIDs, including ibuprofen, yields a net decrease in anti-inflammatory activity with lowered blood levels of the non-aspirin drug. Single-dose bioavailability studies in normal volunteers have failed to show an effect of aspirin on ibuprofen blood levels. Correlative clinical studies have not been conducted.
No clinically meaningful loss of cardioprotection was observed, when patients on low dose ASA (81 mg) were administered 400 mg ibuprofen T.I.D., keeping in mind that combination NSAID therapy is associated with additive adverse reactions.
Acetylsalicylic acid (ASA) Low Dose
Ibuprofen can interfere with the anti-platelet effect of low-dose ASA (81 - 325 mg per day). Long-term daily use of ibuprofen may render ASA less effective when used for cardioprotection and stroke prevention. To minimize this interaction, regular users of ibuprofen and low-dose, immediate-release ASA should take the ibuprofen at least one hour after or 11 hours before the daily low-dose ASA. The use of delayed-release (e.g. enteric coated) ASA is not recommended when using ibuprofen regularly. Healthcare professionals should advise consumers and patients regarding the appropriate concomitant use of ibuprofen and ASA.
Antacids
A bioavailability study has shown that there was no interference with the absorption of ibuprofen when given in conjunction with an antacid containing aluminium hydroxide and magnesium hydroxide.
Antihypertensives
Combinations of ACE inhibitors, angiotensin-II antagonists, or diuretics with NSAIDs might have an increased risk for acute renal failure and hyperkalemia. Blood pressure and renal function (including electrolytes) should be monitored more closely in this situation, as occasionally there can be a substantial increase in blood pressure.
Prostaglandins are an important factor in cardiovascular homeostasis and inhibition of their synthesis by NSAIDs may interfere with circulatory control. NSAIDs may elevate blood pressure in patients receiving antihypertensive medication. Two meta analyses have observed this relationship for NSAIDs as a class and for certain NSAIDs in particular, but ibuprofen did not significantly affect blood pressure in either meta analysis. Consistent with this lack of effect, a study by Davies et al showed that ibuprofen 1600 mg/day for 14 days did not attenuate the antihypertensive effect of two β-adrenergic blockers. Houston et al. showed no effect of three weeks’ therapy with ibuprofen on the antihypertensive efficacy of verapamil, but it is not known whether this lack of interaction extends to other classes of calcium channel blockers.
When renal perfusion pressure is reduced both prostaglandins and angiotensin II are important mediators of renal autoregulation. As a class, the combination of an NSAID and angiotensin converting enzyme inhibitor theoretically may have the potential to decrease renal function. One study found a clinically significant decrease in renal function in 4 of 17 patients treated with hydrochlorothiazide and fosinopril who received ibuprofen 2400 mg/day for one month. In contrast, Minuz found no effect on the antihypertensive effect of enalapril or on plasma renin or aldosterone following two days’ treatment with ibuprofen 1200 mg/day.
The relationship of ibuprofen and antihypertensives is clearly not well defined. The benefits of concomitant medication should be analysed and compared to the potential risks before being prescribed. If ibuprofen is being recommended for long-term use, then periodic monitoring of blood pressure may be useful. Blood pressure monitoring is not necessary if ibuprofen is being recommended for short-term use as an analgesic.
Coumarin-type
Numerous studies have shown that the concomitant use of NSAIDs and anticoagulants increases the risk of GI adverse events such as ulceration and bleeding. Because prostaglandins play an important role in hemostasis, and NSAIDs affect platelet function, concurrent therapy of ibuprofen with warfarin requires close monitoring to be certain that no change in anticoagulant dosage is necessary. Several short-term controlled studies failed to show that ibuprofen significantly affected prothrombin time or a variety of other clotting factors when administered to individuals on coumarin-type anticoagulants. Nevertheless, the physician should be cautious when administering Advil Plus Acetaminophen to patients on anticoagulants.
Digoxin
Ibuprofen has been shown to increase serum digoxin concentration. Increased monitoring and dosage adjustments of digitalis glycoside may be necessary during and following concurrent ibuprofen therapy.
Diuretics
Clinical studies, as well as random observations, have shown that ibuprofen can reduce the natriuretic effect of furosemide and thiazides in some patients. This response has been attributed to inhibition of renal prostaglandin synthesis. During concomitant therapy with ibuprofen, the patient should be observed closely for signs of renal failure as well as to assure diuretic efficacy.
Glucocorticoids:
Some studies have shown that the concomitant use of NSAIDs and oral glucocorticoids increases the risk of GI adverse events such as ulceration and bleeding. This is especially the case in older (> 65 years of age) individuals.
H-2 antagonists
In studies with human volunteers, coadministration of cimetidine or ranitidine with ibuprofen had no substantive effect on ibuprofen serum concentrations.
Hypoglycaemic Agents
Ibuprofen may increase hypoglycaemic effects of oral antidiabetic agents and insulin.
Lithium
Ibuprofen produced an elevation of plasma lithium levels and a reduction in renal lithium clearance in a study of eleven normal volunteers. The mean minimum lithium concentration increased 15% and the renal clearance of lithium was decreased by 19% during this period of concomitant drug administration. This effect has been attributed to inhibition of renal prostaglandin synthesis by ibuprofen. Thus, when ibuprofen and lithium are administered concurrently, subjects should be observed carefully for signs of lithium toxicity.
Methotrexate
Ibuprofen as well as other NSAIDs has been reported to competitively inhibit methotrexate accumulation in rabbit kidney slices. This may indicate that ibuprofen could enhance the toxicity of methotrexate. Caution should be used when ibuprofen is administered concomitantly with methotrexate.
Selective Serotonin Reuptake Inhibitors (SSRIs)
Studies report an increased risk of gastrointestinal (GI) ulceration and bleeding when Ibuprofen as well as other NSAIDs are taken concomitantly with selective serotonin reuptake inhibitors (SSRIs) than when either class of drugs is taken alone (See Warnings and Precautions – Gastrointestinal).
Other Drugs
Although ibuprofen binds extensively to plasma proteins, interactions with other protein-bound drugs occur rarely. Nevertheless, caution should be observed when other drugs, also having a high affinity for protein binding sites, are used concurrently. No interactions have been reported when ibuprofen has been used in conjunction with probenecid, thyroxine, antibiotics, cyclosporine, phenytoin, corticosteroids or benzodiazepines.
ACETAMINOPHEN
Acetaminophen
Concomitant administration of this product with others containing acetaminophen, or hepatotoxic medications (including alcohol), or hepatic enzyme inducers may increase the risk of hepatotoxicity.
Anticoagulants
Chronic ingestion of large doses of acetaminophen may potentiate the effects of certain anticoagulants such as warfarin; anticoagulant dosage adjustment may be necessary.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbs have not been established.
9.7 Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Ibuprofen, like all nonsteroidal anti-inflammatory drugs (NSAIDs), is an analgesic, antipyretic, and anti-inflammatory medication.1 There is strong evidence to support the view that the main mechanism of action of ibuprofen (like other NSAIDs) is related to decreasing prostaglandin biosynthesis.
Prostaglandins are naturally-occurring fatty acid derivatives that are widely distributed in the tissues. They are believed to be a common factor in the production of pain, fever, and inflammation. Prostaglandins are believed to sensitize tissues to pain- and inflammation-producing mediators such as histamine, 5-hydroxytryptamine, and kinins. The enzyme catalysing the committed step in prostaglandin biosynthesis is prostaglandin endoperoxide synthase, also known as cyclooxygenase. There is significant evidence that the main mechanism of analgesic/antipyretic action of NSAIDs is prostaglandin biosynthesis inhibition. Other pharmacologic effects such as lysosome and plasma membrane stabilisation have been observed, but the potential relevance of these effects to ibuprofen-induced analgesia and antipyresis is unclear.
Acetaminophen has no significant anti-inflammatory activity and its mechanism(s) of action is not clear but may involve COX inhibition in the central nervous system and activation of central serotonergic pathways. In general, acetaminophen has weaker anti-inflammatory activity than NSAIDs. Both drugs have been extensively studied, and their efficacy and safety profiles in humans are well-established.
10.2 Pharmacodynamics
In studies in animals, combinations of acetaminophen and various NSAIDs have resulted in either synergistic or additive effects in tests of anti-nociceptive activity.
Miranda and co-workers conducted a study of combinations of several NSAIDs with acetaminophen in mice, measuring analgesic activity by the acetic acid abdominal constriction test (writhing test). Using an isobolographic analysis, they determined that the combination of ibuprofen and acetaminophen was synergistic.
IBUPROFEN
Animal Pharmacology
After single oral doses of 20 to 150 mg/kg of C14 labelled ibuprofen rats, the peak plasma level occurred at or before the earliest time examined (20 minutes in the 20 mg/kg group and 45 minutes in the 150 mg/kg group) and peak levels occurred with 45 minutes of dosing in nearly all tissues examined. The concentration in plasma and tissue decreased to very low levels by six hours after the 20 mg/kg dose and by 17 hours after the 150 mg/kg dose. Sixteen to 38% of the daily dose of ibuprofen was excreted in the urine.
A similar dose was given to dogs for periods of up to six months with no evidence of accumulation of the drug or its metabolites.
Inhibition of Platelet Aggregation in Animals
Like many other NSAIDs, ibuprofen inhibits platelet aggregation, as demonstrated by preventing platelet disposition in aortopulmonary arterial bypass grafts in the dog. The drug’s protective action against fatal pulmonary embolism in rabbits injected intravenously with arachidonic acid may also relate to platelet inhibition. Various prostaglandins and thromboxane A2 (TXA2), are important factors in normal platelet aggregation. Cyclooxygenase inhibition reduces TXA2 production and release, thereby reducing platelet aggregation. Ibuprofen may also reduce platelet membrane fluidity, which reduces aggregation,105 but it is not known to what extent TXA2 synthesis inhibition is involved in this effect.
Human Pharmacology
Two metabolites of ibuprofen were isolated from the urine of patients who had been treated for one month with the drug. The metabolites were identified at 2-4', (2-hydroxy-2-methylpropyl) phenylpropionic acid (metabolite A) and 2-4' (2-carboxpropyl) phenylpropionic acid (metabolite B). About 1/3 of the dose was excreted in the urine of patients as metabolite B, 1/10 as unchanged ibuprofen and 1/10 as metabolite A. The remainder of the dose could not be identified in the urine.
Effect of Ibuprofen on Platelet Aggregation, Bleeding and Clotting Times in Normal Volunteers
Platelet aggregation studies using the method of Sekhar were performed. Platelet aggregation fell significantly at a dosage of 1800 mg per day of Ibuprofen when given over a period of 28 days.
Ibuprofen was also found to influence ADP induced aggregation to a lesser extent than that influenced by collagen. Platelet aggregation induced by recalcification of citrated platelet-rich plasma (a thrombin induced reaction) was not influenced by ibuprofen treatment. Likewise, ibuprofen did not affect whole blood clotting time on recalcification or prothrombin time. Bleeding time performed two hours after the administration of ibuprofen showed a significant dose related increase.
Experimental data suggest that ibuprofen may inhibit the effect of low dose ASA (81 – 325 mg per day) on platelet aggregation when they are dosed concomitantly. In one study, when a single dose of ibuprofen 400 mg was taken within 8 hours before or within 30 minutes after immediate-release ASA dosing, a decreased effect of ASA on the formation of thromboxane or platelet aggregation occurred. However, the limitations of these data and the uncertainties regarding extrapolation of ex vivo data to the clinical situation imply that no firm conclusions can be made for regular ibuprofen use, and no clinically relevant effect is considered to be likely for occasional ibuprofen use.
10.3 Pharmacokinetics
Both drugs are well absorbed with ibuprofen being highly protein bound compared to acetaminophen. They undergo hepatic oxidative metabolism by different CYP pathways and form glucuronides and sulfates which are then excreted primarily in the urine. Acetaminophen metabolism produces a reactive intermediate, N-acetyl-p-benzoquinone imine (NAPQI), which is detoxified by conjugation with glutathione to form cysteine and mercapturic acid metabolites. No significant drug-drug interaction between ibuprofen and acetaminophen is expected when the 2 are co-administered.
Absorption: Ibuprofen is rapidly and almost completely absorbed. Peak serum concentration occurs within 1-2 hours in adults. In febrile children ages 3 months to < 12 years, the time of peak serum concentration was 1.60 and 1.54 hours for ibuprofen 5 mg/kg and 10 mg/kg, respectively. Nahata found a time to peak concentration of 1.1 and 1.2 hours for these respective doses. A similar study in febrile children by Walsonwhich used an ibuprofen suspension showed a time of peak serum concentration of 1.3 and 1.7 hours for ibuprofen 5 mg/kg and 10 mg/kg, respectively. Walson also found that mean ibuprofen plasma concentration at one hour was 21.7 ± 6.7 and 28.4± 15.2 μg/mL for 5 mg/kg and 10 mg/kg, respectively. Food decreases the rate but not the extent of absorption.
Acetaminophen is absorbed by passive diffusion, primarily in the small intestine.
Administration of a single dose of Advil Plus Acetaminophen (two tablets of ibuprofen 125 mg/acetaminophen 250 mg) tablets with a high fat, high calorie meal decreased the extent of exposure (AUCT) of ibuprofen by 15% while it had no impact on AUCT of acetaminophen, and decreased the peak concentrations (Cmax) of ibuprofen and acetaminophen by approximately 37%, as compared to the fasted condition in healthy adults. The median Tmax for ibuprofen and acetaminophen under fed conditions was delayed by approximately 1.6 and 1.9 hours, respectively, when compared to fasted. Overall, these results will have minimal clinical impact. Therefore, the Advil Plus Acetaminophen tablets can be administered without regard to food.
Distribution: The volume of distribution in adults after oral administration is 0.1-0.2 L/kg. In febrile children the volume of distribution is 0.18 and 0.22 L/kg for ibuprofen 5 mg/kg and 10 mg/kg, respectively.
At therapeutic concentrations ibuprofen is highly bound to whole human plasma and to site II of purified albumin. There is no appreciable plasma accumulation of ibuprofen or its metabolites with repeated doses.
Ibuprofen excretion in breast milk following ingestion of one 400 mg ibuprofen tablet every 6 hours for five doses was below the level (i.e., 1μg/mL) of detection. However, a later study using a more sensitive assay showed ibuprofen to be rapidly excreted in breast milk 30 minutes following oral ingestion of 400 mg of ibuprofen at a concentration of 13 ng/mL. A milk: plasma ratio of 1:126 was determined and the exposure of a suckling infant was calculated to be approximately 0.0008% of the maternal dose. It is not known whether ibuprofen crosses the placenta.
Acetaminophen is only 10-25% bound in human plasma, suggesting a negligible propensity for mutual displacement from protein binding sites that would be of any clinical consequence after co-administration.
Metabolism: Ibuprofen is a racemic mixture of R–(-) ibuprofen and S-(+) ibuprofen. R-(-) ibuprofen undergoes extensive enantiomeric conversion to S-(+) ibuprofen in humans, averaging between 53% and 65%. S-(+) ibuprofen is believed to be the pharmacologically more active enantiomer. Two major metabolites, 2-[4-(2-carboxypropyl)phenyl] propionic acid and 2-[4-(2-hydroxy-2-methylpropyl]propionic acid, have been identified in plasma and urine. The metabolites 1-hydroxyibuprofen and 3-hydroxyibuprofen have also been found in urine in very small concentrations. Cytochrome P450 (CYP) 2C9 has been identified as the most important catalyst for formation of all oxidative metabolites of R-(-) and S-(+) ibuprofen. Approximately 80% of a dose is recovered in urine, primarily as carboxymetabolites and conjugated hydroxymetabolites. Ibuprofen does not appear to induce the formation of drug metabolising enzymes in the rat.
Ibuprofen is extensively metabolized in the liver to 2-hydroxy ibuprofen and carboxy ibuprofen, which are subsequently almost fully conjugated by glucuronidation and sulfation. A small portion (10%) of an ibuprofen dose is directly conjugated. Formation of the hydroxyl and carboxy metabolites is mediated by CYP2C9, and it has been suggested that CYP2C8 may also contribute to these oxidations. The metabolites of ibuprofen have no apparent pharmacologic activity. The biotransformation pathways for ibuprofen are presented in Figure 1.
Figure 1. Biotransformation of Ibuprofen.
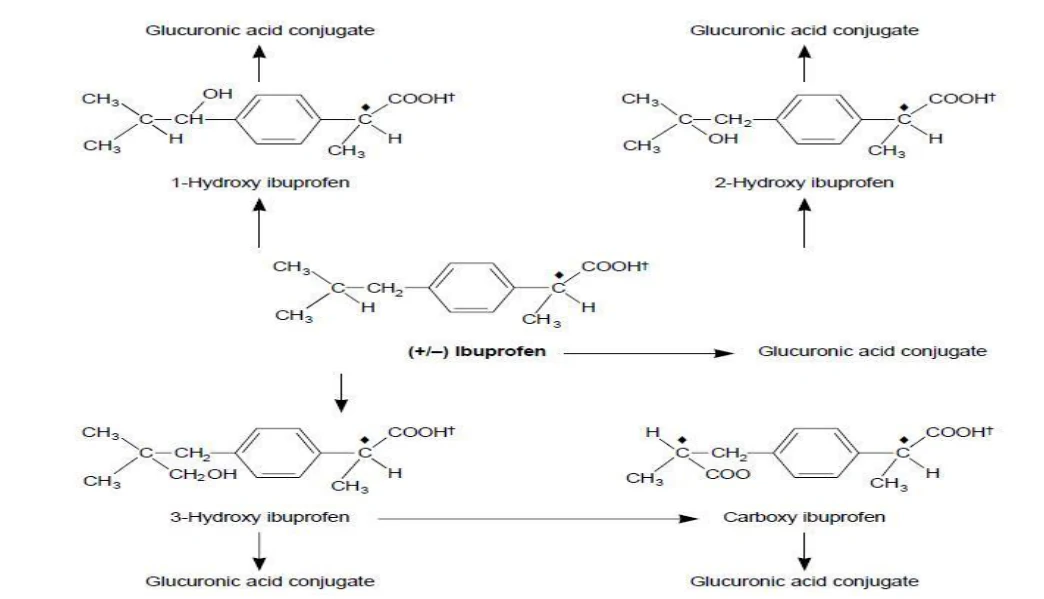
Acetaminophen is predominantly metabolized directly by glucuronidation and sulfation, with a smaller portion of the dose oxidized by cytochrome P450 (CYP). Oxidative metabolism forms a reactive intermediate, NAPQI, which is detoxified by conjugation with glutathione to form cysteine and mercapturic acid metabolites. Formation of NAPQI is mediated by the hepatic CYP2E1 isoform. Two additional minor catechol metabolites are formed, possibly by CYP2A6, and further conjugated with glucuronide or sulfate. The metabolites do not have analgesic activity. The biotransformation pathways for acetaminophen are depicted in Figure 2.
Figure 2. Biotransformation of Acetaminophen
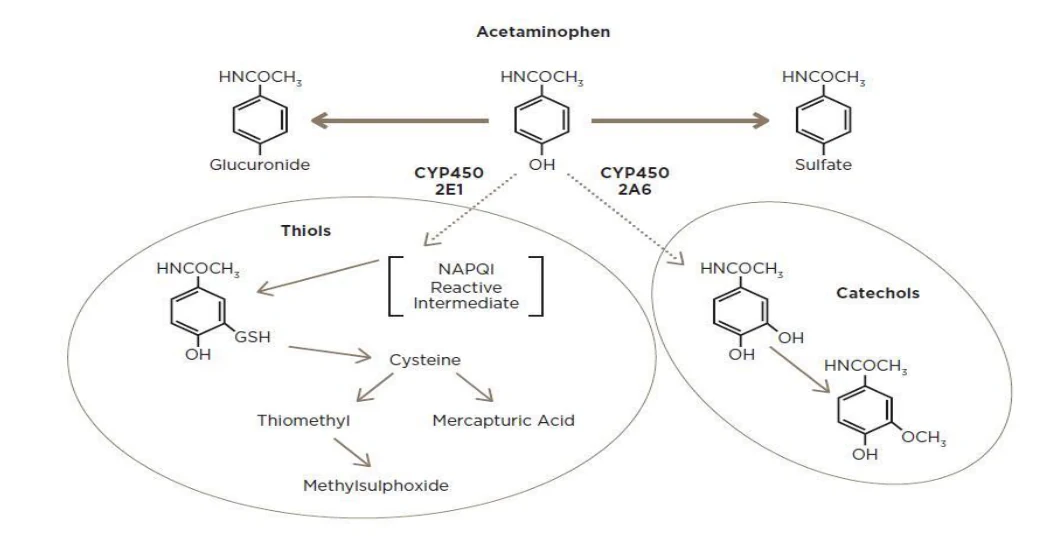
The lack of a common CYP pathway indicates a negligible possibility of competition for oxidative metabolism sites. Neither compound has been reported to induce CYPs. Both parent compounds and their oxidative metabolites undergo glucuronidation and sulfation. While the possibility exists that these compounds may compete for conjugating enzymes, the likelihood of a significant interaction is low. The predominant UDP-glucuronosyl transferase (UGT) isoform responsible for IBU glucuronidation is UGT2B7, with minor contributions by UGT1A3, UGT1A9, and UGT2B4. The isoform responsible for glucuronidation of ibuprofen oxidative metabolites has not been reported, however, the site of glucuronidation in the oxidative metabolites is the same carboxylic acid moiety that is conjugated in the parent compound (Figure 1) and it has been shown that UGT2B7 is the favored isoform for glucuronidating acids. Glucuronidation of acetaminophen is mediated primarily by UGT1A1, UGT1A6, and UGT1A9. While UGT1A9 appears to play a role in the metabolism of both ibuprofen and acetaminophen, the likelihood of a clinically significant interaction due to competition for this enzyme appears to be low as UGT1A9 plays only a minor role in ibuprofen elimination. Moreover, UGT1A9 functions as a low affinity, high capacity enzyme in the glucuronidation of both ibuprofen and acetaminophen. Collateral metabolic pathways, including sulfotransferases, available to both of these drugs and their metabolites would have the capacity, within the therapeutic dose range, to potentially accommodate substrates shunted from an inhibited site. Saturation of metabolism and elimination has not been observed with ibuprofen up to a 1200 mg oral dose, and a compensatory increase in sulfation of acetaminophen is observed when enzymes are saturated, as in the case of overdose. The maximum possible daily dose of the proposed fixed-dose combination product will be 750 mg Ibuprofen /1500 mg Acetaminophen per day, which is significantly less than the current non-prescription maximum daily doses of 1200 mg IBU and 4000 mg acetaminophen. The proposed combination dose is equivalent to 15 mg/kg IBU and 25 mg/kg APAP in a 60 kg human.
Excretion: Ibuprofen’s plasma half-life in adults is 1.5-2.0 hours. In febrile children the plasma half-life is 1.65 and 1.48 hours for ibuprofen 5 mg/kg and 10 mg/kg, respectively. Parent drug and metabolites are primarily excreted in the urine; bile and faeces are relatively minor elimination routes. Total recovery in urine is between 70% and 90% of the administered dose within 24 hours.
There is no evidence of a differential metabolism or elimination of ibuprofen in the elderly. A pharmacokinetic evaluation of ibuprofen in geriatric subjects (65 to 78 years) compared with young adult subjects (22 to 35 years) found that there was no clinically significant difference in the kinetic profiles of ibuprofen for these age groups. Furthermore, there was no statistically significant difference between the two populations in the urinary excretion pattern of the drug and its major metabolites.
The pharmacokinetics of ibuprofen have also been evaluated in children, in whom the metabolism has been shown to be similar to that reported for adults. Walson reported that for ibuprofen 10 mg/kg given to children under 12 years of age, peak plasma concentration occurred at 1.5 hours and then declined with a plasma half-life of 1.8 hours. Thus, ibuprofen appears to exhibit a similar pharmacokinetic profile in all age groups examined.
The predominant route of excretion of acetaminophen and its metabolites is in urine. Acetaminophen and its metabolites are essentially completely eliminated by renal excretion, with up to 40% - 65% and 25% - 35% of an oral dose of acetaminophen excreted as glucuronide and sulfate conjugates, respectively. Approximately 3% - 6% of a dose is excreted as catechol metabolites and their conjugates, and 5% - 12% of a dose is recovered in urine as products of NAPQI glutathione conjugation. Intact parent comprises less than 5% of the dose in urine.
11 STORAGE AND STABILITY
Advil Plus Acetaminophen should be stored in tightly-closed containers under room temperature (15-30°C) conditions.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ibuprofen
Chemical name: α-methyl-4-(2-methylpropyl)benzeneacetic acid
Other names: p-isobutylhydratropic acid
2-(4-isobutylphenyl)-propionic acid
Molecular formula and molecular mass: C13H1802; 206.28 daltons
Structural formula:
Physicochemical properties: White or almost white powder or crystals with a characteristic odour.
Solubilities: Low solubility in water (<1.0 mg/mL), soluble 1 in 1.5 of alcohol, 1 in 1 of chloroform, 1 in 2 of ether, and 1 in 1.5 of acetone. Ibuprofen is also soluble in an aqueous solution of alkali hydroxides and carbonates.
pKa and pH values: pH : 4.6 - 6.0, in a solution of 1 in 20.
pKa: 4.43
Melting Point: 75 - 77°C
Drug Substance
Proper name: Acetaminophen
Chemical name: N-acetyl-p-aminophenol
Molecular formula and molecular mass: C8H9NO2; 151.1 daltons
CH3
COOH
CH3
H3C
Structural formula:
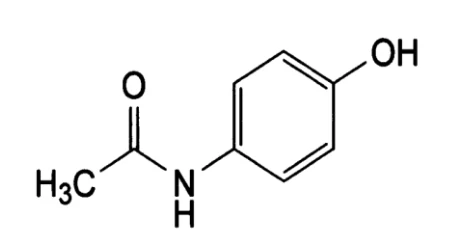
Physicochemical Properties: White, crystalline powder
Solubilities: Acetaminophen solubility in water at 25°C is essentially constant (14.95 to 15.17 mg/mL) in the biorelevant pH range of 2.0 to 7.6, which is consistent with the structure of acetaminophen as a weak acid
PH/pKa: 5.1-6.5 (pH of aqueous suspension); pKa: 9.5
Melting Point: 168-172 °C
Molecular formula and molecular mass: C8H9NO2; 151.16 daltons
14 CLINICAL TRIALS
Seven clinical trials with 1477 randomized subjects were conducted to support the development of the IBU/APAP FDC formulation. 4 studies assessed efficacy. 3 PK studies evaluated the clinical pharmacology of IBU and APAP. All 7 studies evaluated safety of the IBU/APAP FDC.
At total of 102 subjects were randomized and treated in the three phase 1 studies. A total of 394 subjects were randomized in the proof of concept (POC) dental pain efficacy study, B5061001, and a total of 691 subjects were randomized in the single dose dental pain (SDDP) and multiple dose dental pain (MDDP) pivotal efficacy studies, B5061003 and B5061004. A total of 290 subjects were randomized in the IF pivotal efficacy study B5061002.
In this section, pivotal efficacy studies conducted in support of the FDC IBU 250 mg/APAP 500 mg are summarized.
Results of the three pivotal efficacy studies indicated that the overall efficacy profile of Advil Plus Acetaminophen is superior to placebo for both analgesic and an antipyretic indications. The FDC was found to be superior as an analgesic to equivalent doses of each of the individual monocomponents.
The FDC was well tolerated in the clinical studies; the safety profile was consistent with that of each monocomponent and no new safety concerns were identified.
14.1 Trial Design and Study Demographics
Study design, objectives, demographics and treatment group sizes for the three pivotal efficacy studies are displayed in Table 2.
Table 2 Study Design and Demographics
Protocol No.
Study Design and Objective
Treatment Groups
No. of Subjects
Demographics (No. of Subjects)
Duration of Treatment
B5061002
Design: Phase 3, single-center, 8-hour, single-dose, in-patient, double-blind, randomized, placebo-controlled, full-factorial, parallel arm, safety and efficacy study in healthy male subjects.
Objective: To evaluate the safety and antipyretic efficacy of single, oral doses of FDC IBU 250 mg/APAP 500 mg tablets compared to APAP 500 mg tablets, IBU 250 mg tablets, and placebo in subjects in whom pyrexia has been induced by the IV administration of a RSE.
FDC IBU 250 mg/
APAP 500 mg
APAP 500 mg
IBU 250 mg
Placebo
290 enrolled
267 completed
Sex: 273 M/ 0 F
Mean Age (min/max):
32.2 years
(18-55 years)
Race: W/B/A/O:
213/44/6/10
Single-dose
B5061003
Design: Phase 3, 12-hour, 4-arm, single-dose, randomized, double-blind, placebo-controlled, parallel group, single-center, in-patient study of post-surgical dental pain.
Objective: To determine the analgesic efficacy and safety of a single oral dose of FDC IBU 250 mg/APAP 500 mg compared to IBU 250 mg alone, APAP 650 mg (Tylenol® Regular Strength) alone, and placebo.
FDC IBU 250 mg/ APAP 500 mg
IBU 250 mg
APAP 650 mg (Tylenol® Regular Strength)
Placebo
568 enrolled
560 completed
Sex: 233 M/ 335 F
Mean Age (min/max):
19.5 years
(18-33 years)
Race: W/B/A/O:
537/4/8/19
Single-dose
Table 2 Study Design and Demographics
Protocol No.
Study Design and Objective
Treatment Groups
No. of Subjects
Demographics (No. of Subjects)
Duration of Treatment
B5061004
Design: Phase 3, 48-hour, single-center, in-patient, multiple-dose, fixed-dosing interval, randomized, placebo-controlled, sex- and baseline pain severity-stratified, double-blind, parallel group trial of post-surgical dental pain.
Objective: To compare the analgesic efficacy and safety of FDC IBU 250 mg/APAP 500 mg every 8 hours to placebo in a 48-hour period following extraction of ≥3 third molar teeth.
FDC IBU 250 mg/ APAP 500 mg
Placebo
123 enrolled
112 completed
Sex: 56 M/ 67 F
Mean Age (min/max):
21.8 years
(18-38 years)
Race: W/B/A/O:
112/3/1/7
Multiple dose
AE = Adverse event; APAP = Acetaminophen; FDC = Fixed Dose Combination; A = Asian; B = Black; F = Female; IBU = Ibuprofen; IV = Intravenous; M = Male; O = Other; RSE = Reference Standard Endotoxin; W = White.
14.2 Study Results
A total of three pivotal clinical efficacy studies were conducted. One single-dose dental pain study was conducted to demonstrate that the FDC is superior to the monocomponents. One dose-ranging and multiple dose dental pain study was conducted to determine the efficacy of the FDC sustained efficacy with multiple doses and to confirm appropriate dosing interval. One adult induced fever study was conducted to demonstrate efficacy of the FDC compared to monocomponents and placebo.
Single Dose Dental Pain Study, B5061003
The single dose dental pain study was conducted in adult subjects with post-operative pain following extraction of at least 3 third molar teeth. The study design was a randomized, 4-arm, full-factorial, placebo- and active-controlled study, with subjects followed for 12 hours post-dosing. The FDC was IBU 250 mg /APAP 500 mg (two tablets of IBU 125 mg/APAP 250 mg). The ibuprofen (IBU) monocomponent comparator was IBU 250 mg (2 x 125 mg tablets). The acetaminophen (APAP) monocomponent comparator was 650 mg acetaminophen regular strength immediate release tablets (2 tablets of 325 mg). The primary endpoint was SPID[11]0-8 (time weighted sum of Pain Intensity Difference [PID] scores based on the 11-point Pain Severity Rating scare or from 0 hours (baseline) to 8 hours post dose.
All active treatment groups were significantly more efficacious compared to placebo. Furthermore, the FDC was significantly more efficacious than both IBU 250 mg and APAP 650 mg administered alone for the primary endpoint (SPID[11]0-8) (See Table 4).
The FDC treatment group was significantly better than IBU 250 mg and APAP 650 mg for the majority of secondary endpoints. The duration of relief for the FDC treatment group was significantly longer compared to APAP 650 mg and marginally longer compared to IBU 250 mg alone, with a median time to treatment failure of 629 minutes. Subjects in the FDC treatment group also reported “meaningful” relief significantly sooner (median: 47.9 minutes) than both active treatment groups alone.
Overall, there were no new safety concerns and all active treatments were well-tolerated.
Table 4. SPID[11]0-8 – Full Analysis Set
Placebo
N = 56
FDC IBU 250 mg/APAP 500 mg
N = 172
IBU 250 mg
N = 175
APAP 650 mg
N = 165
Root Mean Square Error
P-valuea
Mean (SD)
4.1 (19.0)
34.3 (19.6)
28.9 (20.5)
19.4 (20.0)
19.640
<0.001*
Median
0.0
37.3
30.5
16.8
Range
(-30.8, 57.8)
(-14.8, 76.8)
(-23.5, 70.5)
(-23.0, 70.3)
LSM (SE)a
4.3 (2.6)
34.4 (1.5)
28.7 (1.5)
19.6 (1.6)
Pairwise Comparisons
FDC IBU 250 mg/APAP 500 mg
vs
Placebo
FDC IBU 250 mg/APAP 500 mg
vs
IBU 250 mg
FDC IBU 250 mg/APAP 500 mg
vs
APAP 650 mg
IBU 250 mg
vs
Placebo
APAP 650 mg vs
Placebo
IBU 250 mg vs
APAP 650 mg
Trt diffb
30.08
5.66
14.76
24.42
15.32
9.10
95% CIb
(24.14, 36.02)
(1.51, 9.80)
(10.55, 18.97)
(18.50, 30.35)
(9.35, 21.29)
(4.90, 13.31)
P-valuea
<0.001 F
0.008 F
<0.001 F
<0.001 F
<0.001 F
<0.001 F
* p ≤0.05 for treatment effect.
Abbreviations: ANCOVA = analysis of covariance; APAP = acetaminophen; CI = confidence interval; Diff = difference; FDC = fixed-dose combination; IBU = ibuprofen; LSM = least square mean; mg = milligram; N = number of subjects; PID = pain intensity difference; PSR = pain severity rating; SD = standard deviation; SE = standard error; SPID[11]0-8 = time-weighted sum of PID scores based on the 11-point numerical PSR scale from 0-8 hours; Trt = treatment.
a LSM, SE and P-values from ANCOVA model with treatment, sex, baseline categorical PSR as classification variables and baseline numerical PSR as a continuous covariate.
b Trt Diff (First treatment - Second treatment) and corresponding 95% CI were calculated based on LSM from the model in a.
F: First treatment significantly better than second at 0.05 level.
Multi-Dose Dental Pain Study, B5061004
The multi-dose dental pain study was conducted in adult subjects with post-operative pain following extraction of at least 3 third molar teeth. It was a randomized, 2-arm, placebo-controlled study. Subjects were administered study medication on a fixed, 8-hour dosing schedule over a 48-hour period. The primary endpoint was SPID[11] 0-24 hours.
The FDC IBU 250 mg/APAP 500 mg (two tablets of IBU 125 mg/APAP 250 mg) was significantly more efficacious than placebo for the primary endpoint, SPID[11]0-24 (see Table 5) and the majority of secondary endpoints over a 48-hour study period. Furthermore, results showed that the FDC had a significantly longer duration of relief and a significantly faster time to onset “meaningful” relief (median: 59.2 minutes) compared to placebo.
Overall, there were no new safety concerns and the active treatment was well tolerated in this study.
Table 5. SPID[11]0-24 – Full Analysis Set
Placebo
N = 41
FDC IBU 250 mg/
APAP 500 mg
N = 82
Mean (SD)
-7.05 (54.525)
64.58 (64.554)
Median
-16.00
67.25
Range
(-71.0, 161.8)
(-44.8, 206.0)
LSM (SE)a
-8.13 (9.426)
64.76 (6.676)
FDC IBU 250 mg/APAP 500 mg vs Placebo
P-value
RMSEb
Diffc
95% CIc
P-valuea
Trt∗Sexd
Trt∗Basee
72.89
(50.075, 95.707)
<0.001∗
0.380
0.444
60.188
∗ p ≤0.05 for treatment effect or interaction effect.
Abbreviations: ANCOVA = analysis of covariance; APAP = acetaminophen; CI = confidence interval; Diff = difference; FDC = fixed-dose combination; IBU = ibuprofen; LSM = least square mean; mg = milligram; N = number of subjects; PID = pain intensity difference; PSR = pain severity rating; RMSE = root-mean square error; SD = standard deviation; SE = standard error; SPID[11]0-24 = time-weighted sum of PID scores based on the 11-point numerical PSR scale from 0 to 24 hours; Trt = treatment.
a P-values from ANCOVA model with treatment, sex, and baseline categorical PSR as classification variables, and baseline numerical PSR as a continuous covariate.
b Root-mean square error, from the ANCOVA model a.
c Trt Diff (First treatment – Second treatment) and corresponding 95% CI were calculated based on LSM from the model in a.
d P-values from ANCOVA model with treatment, sex, baseline categorical PSR, and treatment-by-gender interaction as classification variables, and baseline numerical PSR as a continuous covariate.
e P-values from ANCOVA model with treatment, sex, baseline categorical PSR, and treatment-by-baseline categorical PSR interaction as classification variables, and baseline numerical PSR as a continuous covariate.
Induced Fever Study, B5061002
The induced fever study was performed in healthy adult male volunteers. The study design was a randomized, 4-arm, full-factorial, placebo- and active-controlled study, with subjects followed for 8 hours post-dosing. The FDC was IBU 250 mg /APAP 500 mg (two tablets of IBU 125 mg/APAP 250 mg).The IBU monocomponent comparator was IBU 250 mg (2 x 125 mg tablets); the APAP monocomponent comparator was APAP 500 mg immediate release tablet. The study used an intravenous bolus Reference Standard Endotoxin (RSE; E. coli O:113) to induce fever.
The minimum oral temperature for randomization was ≥100.5°F. At any time after administration of RSE before randomization, the subject was not to be randomized if a subject developed 2 or more systemic RSE-related Aes (eg, headache, body aches, nausea, vomiting) where both were rated as severe, per the judgement of the investigator.
For the primary efficacy endpoint, WSTD0-8 hr (Weighted Sum of Temperature Differences from Baseline to 8 Hours), FDC was statistically significantly superior to placebo (p=0.002). In addition, FDC was numerically greater for fever reduction than both of the single ingredients, but did not reach statistical significance (FDC vs IBU, p=0.210; FDC vs APAP, p=0.280). This trend was observed across the majority of predefined endpoints (Figure 3).
The Induced Fever model was sufficiently sensitive to provide separation from placebo but was not sufficiently sensitive to separate between active treatments. It is hypothesized that it is theoretically possible that inducing a higher and/or longer lasting fever by administering more endotoxin may have provided for a greater separation, but would expose more participants to these higher risk conditions, leading to more adverse events and potential study discontinuations.
However, the FDC demonstrated advantages for onset of antipyresis compared to placebo and the monocomponents. For the secondary efficacy endpoint, WSTD0-2 hr, FDC was statistically significantly superior to placebo (p=0.004). However, neither IBU nor APAP were statistically significantly superior to placebo (IBU, p=0.098; APAP, p=0.054) over the same time period.
Post hoc analyses conducted to assess discrete WSTD time intervals over the early time period 0 to 120 minutes demonstrated the FDC was statistically significantly superior to IBU from 50 to 110 minutes (p=0.042), and the FDC was statistically significantly superior to both IBU and APAP from 80 to 110 minutes (p=0.045 and p=0.049, respectively) (Figure 4). Therefore, the study demonstrates that the FDC is superior to placebo for overall antipyretic efficacy.
Figure 3. Post-Treatment Temperature Over Time – Least Square Mean [Line Plot]
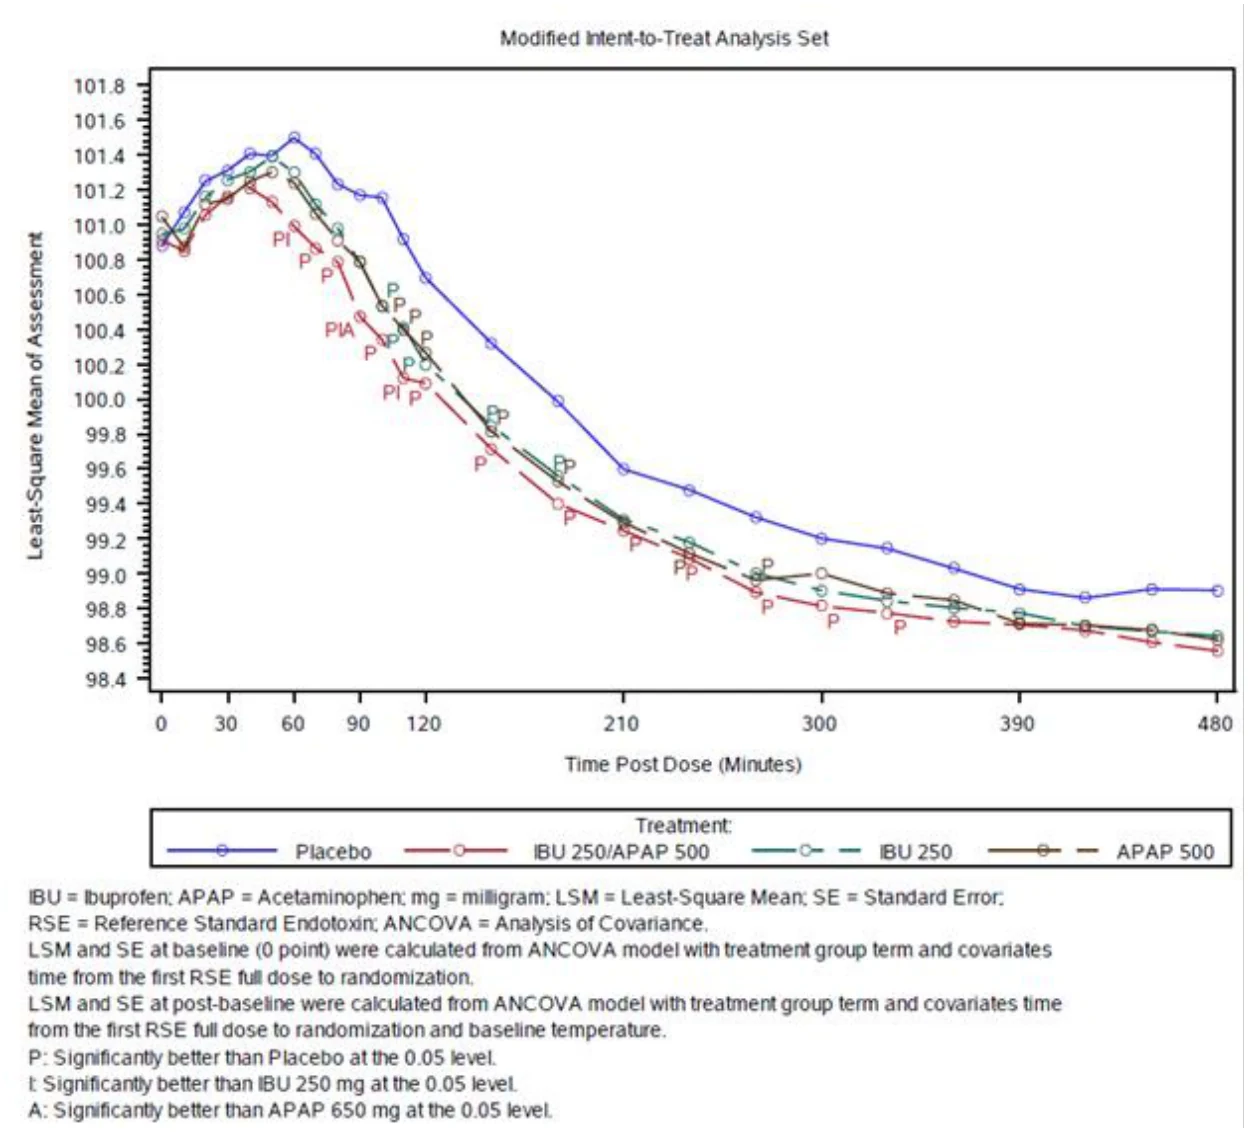
Figure 4. Time Weighted Sum of Temperature Difference for the Time Windows 50-110 and 80-110 Minutes (mITT Analysis Set)
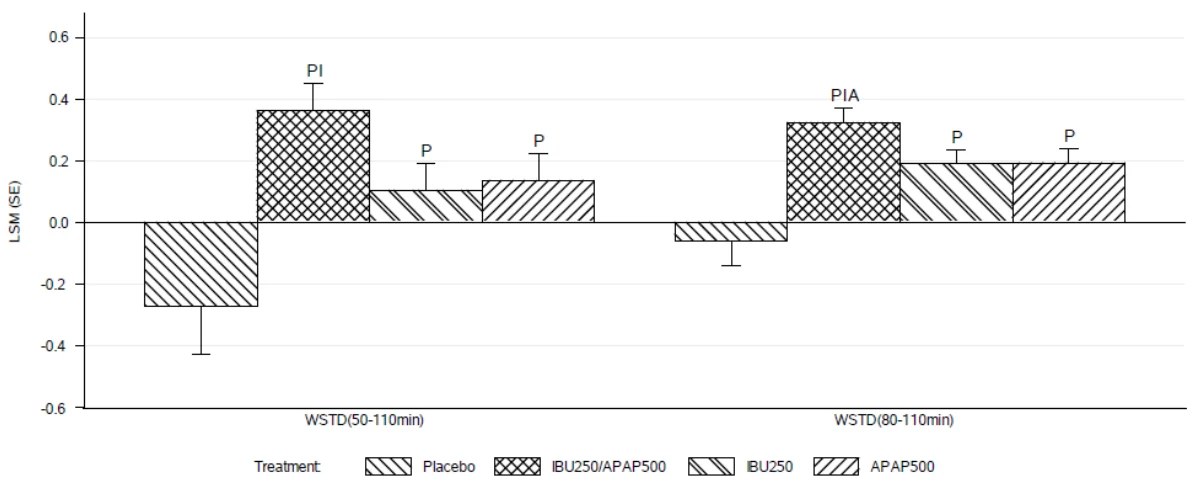
P: Significantly better than Placebo at the 0.05 level. I: Significantly better than IBU 250 mg at the 0.05 level. A: Significantly better than APAP 500 mg at the 0.05 level.
15 MICROBIOLOGY
Not applicable.
16 NON-CLINICAL TOXICOLOGY
IBUPROFEN
Single Dose Toxicity Studies
Single dose toxicity studies have been conducted using mice, rats, and dogs.
The LD50 values for ibuprofen, expressed as mg/kg of body weight are as follows:
Mouse:
Oral
800 mg/kg
Intraperitoneal
320 mg/kg
Rat:
Oral
1600 mg/kg
Subcutaneous
1300 mg/kg
Acute signs of poisoning were prostration in mice, and sedation, prostration, loss of righting reflex and laboured respiration in rats. Death occurred within 3 days from perforated gastric ulcers in mice and intestinal ulceration in rats, irrespective of the route of administration.
Following single ibuprofen doses of 125 mg/kg and above to dogs effects were observed including emesis, transient albuminuria, faecal blood loss and erosions in the gastric antrum and pylorus; no ill effects were seen with 20 or 50 mg/kg doses.
Multiple Dose Studies
The no-effect level was determined using groups of 10 male and 10 female rats which were dosed orally for 26 weeks with 180, 60, 20 or 7.5 mg/kg ibuprofen in 0.4% hydroxyethyl cellulose. The control group consisted of 20 males and 20 females which received 0.4% hydroxyethyl cellulose. Rats were weighed three times daily and blood samples were obtained in the final week of dosing. The rats were sacrificed the day after the last dose and the internal organs examined.
Rats receiving ibuprofen for 26 weeks grew normally except for males on 180 mg/kg/day, which gained significantly less weight than the controls. One male rat receiving 180 mg/kg/day died due to intestinal lesions and the death was thought to be treatment-related. Both males and females receiving 180 mg/kg/day were anaemic; leukocyte count and plasma glutamic pyruvic transaminase activities were not significantly altered. The organ to body weight ratio of males given 180 mg/kg/day was typically greater than normal. For some organs, this was because the males weighed less than the controls. Organs that were enlarged were the liver, kidney, and spleen. The same organs were also enlarged in females receiving 180 mg/kg/day, although these females were similar in body weight to the controls. In addition, the combined seminal vesicle and prostate weight was subnormal and uterine weight was increased. The thyroid gland of males receiving 180, 60, 20 mg/kg/day exhibited a slight increase in weight, which was the same for the three doses, however no such increase was observed in the females. There were no significant histological changes observed in rat tissues except for the presence of intestinal ulcers in 1 male and 3 females receiving 180 mg/kg/day.
The above experiment was adapted to establish whether the effects of ibuprofen treatment on rats were reversible when dosing ended. In this instance, rats were administered 180, 60, or 20 mg/kg/day ibuprofen for 13 weeks instead of 26 weeks, whereupon half the animals in each group were sacrificed and the remaining rats were maintained, undosed, for three weeks and then sacrificed. Haematological examinations were performed after 4, 8, and 12 weeks of treatment.
Results obtained from the dosing phase of this 13-week experiment reflected the results obtained previously, where rats were dosed for 26 weeks. Males receiving 180 mg/kg/day had enlarged kidneys, spleen, and testes; while those on lower doses had normal organ weights. Females on all three doses had enlarged kidneys, the extent of which was dose-dependent. Enlargement of the liver and ovaries was observed in females receiving 180 mg/kg/day, and of the spleen and ovaries on those on 60 mg/kg/day. None of the enlarged organs were histologically abnormal. Three weeks following withdrawal of treatment, the organ to body weight ratios had completely or almost completely returned to normal. Rats receiving 180 mg/kg/day were anaemic from week 4 of dosing and when examined after the final dose, were found to have intestinal lesions. These effects were not seen at the lower doses, thereby confirming the results of the first experiment. Since the highest dose of 180 mg/kg/day was only moderately toxic, an additional group of rats was dosed with 540 mg/kg/day. All these rats died or were killed in extremis after 4 days’ dosing. All had intestinal ulceration with peritonitis, and some also had slight renal tubular dilation.
The primary toxic effect of ibuprofen in rats is intestinal damage. Ibuprofen alters the organ to body weight ratio of certain organs, such as the liver, kidneys, gonads, and the secondary sex organs, although no histological abnormalities have occurred and the effect is reversible. The liver and kidney enlargement may be a reflection of work hypertrophy associated with the metabolism and excretion of the compound, whereas the significance of the effect on other organs is unknown. When administered in lethal doses, ibuprofen produces mild kidney lesions in addition to the intestinal damage.
Carcinogenic Potential
Thirty male and thirty female rats were given 180 mg/kg/day of ibuprofen orally for 55 weeks and 60 mg/kg/day for the next 60 weeks. The only specific pathological effect observed was intestinal ulceration. There was no evidence of tumour induction and it is concluded that ibuprofen is not carcinogenic in the rat.
Teratology Study in Rabbits
New Zealand white rabbits were given 0, 7.5, 20 and 60 mg/kg daily of ibuprofen from day 1 to day 29 of pregnancy. The mean fetal weight was unaffected; litter size was unaffected at the lower doses. Congenital malformations did occur in both treated and untreated groups with no consistent pattern except for one litter of 4 young with cyclopia. The results of this experiment indicate that ibuprofen is not teratogenic when given in toxic doses to rabbits.
Teratology Study in Rats
Newly-mated female albino rats were given ibuprofen in doses of 0, 7.5, 20, 60 and 180 mg/kg/day from day 1 to day 20 of pregnancy; ibuprofen exhibited no embryotoxic or teratogenic effects even when administered at ulcerogenic doses.
Penetration of Ibuprofen into the Rabbit and Rat Fetus
Rabbits and rats in late pregnancy were given single oral doses of 60 and 20 mg/kg respectively of C14 labelled ibuprofen. Rabbits were killed three hours after dosing and rats killed 1.5 hours after dosing when maternal and fetal blood was collected. Similar concentrations of radioactive ibuprofen were detected in both the mother and fetus indicating that the drug and its metabolites readily crossed the placental barrier into the fetal circulation.
ACETAMINOPHEN
Toxicity Studies
Acute and repeat dose studies indicated that the primary toxicity of acetaminophen was hepatotoxicity. In mice dosed for 13-weeks with acetaminophen, increased relative kidney weights and histopathological lesions in the liver (hepatocytomegaly, focal calcification, pigmentation, necrosis) occurred at doses ≥1240 mg/kg. The NOAEL was considered to be 650 mg/kg/d. The 13-week study in the rat with acetaminophen showed inflammation and hepatocytomegaly in the liver, tubular regeneration in the kidney, atrophy in the testes, ovaries and uterine horns, and lymphoid depletion in the lymph node and thymus at 1250 and 2500 mg/kg. The NOAEL was considered to be 620 mg/kg.
Genotoxicity
Acetaminophen was negative in the bacterial reverse mutation assay, genotoxic in the sister chromatid assay and in vitro chromosomal aberration assay at high concentrations, and negative in the Pig-a and Pig-a assay using reticulocytes (PIGRET) assays at doses up to 2000 mg/kg.
Carcinogenicity
Acetaminophen was not carcinogenic in rodent bioassays.
Teratology
Acetaminophen administration to both mice and rats had an effect on fertility. In continuous breeding studies in mice, there was a decrease in the number of litters per pair of mated animals at a dose of 1430 mg/kg/d. In male rats, a dose of 500 mg/kg/d impaired mating behavior as well as fertility that was associated with effects on sperm parameters.
Studies in which acetaminophen was administered to pregnant mice and rats did not reveal overt teratogenicity, although an effect on the reproductive development of the offspring was indicated. In a study in mice, a dose of 150 mg/kg/d administered during organogenesis resulted in reduced anogenital distance in female offspring at 150 mg/kg/d, and reduced follicle numbers at 50 and 150 mg/kg/d. Mating of these F1 females to untreated males resulted in an associated decrease in fertility. In F1 adult male mice that had been exposed to acetaminophen at a dose of 1430 mg/kg/d both in utero and subsequently during lactation, post-weaning and adulthood, an effect on sperm morphology occurred without an effect on fertility (mating). In a study in pregnant mice, behavioral testing of the offspring exposed in utero at a dose of 150 mg/kg/d did not reveal any effects. In a study in pregnant rats, acetaminophen administered during organogenesis did not affect the incidence of resorptions or impact fetal length or weight at doses up to 250 mg/kg/d. In another study in rats, administration of acetaminophen during late gestation at doses up to 350 mg/kg/d had no effects on litter sizes, number of live fetuses, resorptions and implantations, or on fetal sex ratios. Examination of male fetuses revealed a decrease in anogenital distance at all doses in the study (≥150 mg/kg/d). F1 adult rat females that had been exposed in utero during late gestation at a dose of 350 mg/kg/d had reduced ovarian size and a reduction in the number of pups per litter following mating.
IBUPROFEN AND ACETAMINOPHEN
Combination Toxicity
Nonclinical combination studies of ibuprofen and acetaminophen were limited to 2 studies to assess the GI toxicity. In a 14-day combination rat study, 100 mg/kg of either drug produced analgesia. The GI toxicity of ibuprofen was enhanced with the combination of ibuprofen and acetaminophen. Acetaminophen alone in this study did not cause GI toxicity.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Product Monograph: Advil Tablets, Advil Caplets, Advil Gel Caplets, Advil Extra Strength Caplets, Advil Muscle and Joint, Advil 12 Hour; Date of Revision: October 23, 2019
- 2. Product Monograph: Extra Strength Tylenol® Nighttime; Date of Revision: December 8, 2017