


Product Monograph - Aerius Dual Action 24 Hour
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| oral | modified release tablet / 5 mg desloratadine & 240 mg pseudoephedrine sulfate | For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING section. |
INDICATIONS AND CLINICAL USE
AERIUS® DUAL ACTION 24 HOUR (desloratadine/pseudoephedrine sulfate) is indicated for:
- Fast, long-acting and effective relief from multiple nasal and non-nasal symptoms associated with seasonal allergic rhinitis including nasal discharge/rhinorrhea, sinus pressure, sneezing, nasal congestion/stuffiness and itchy nose; swollen, burning, teary/watery, itchy and red eyes; itchy ears, throat, and palate; and allergic cough when these are also accompanied by nasal and sinus congestion.
AERIUS DUAL ACTION 24 HOUR is not recommended for use in pregnant or lactating women.
AERIUS DUAL ACTION 24 HOUR is not recommended for use in patients with severe hepatic or renal impairment.
AERIUS DUAL ACTION 24 HOUR should be administered when the antihistaminic, anti-allergic and anti-inflammatory properties of desloratadine and the nasal and sinus decongestant activity of pseudoephedrine are desired.
Geriatrics (≥ 65 years of age):
AERIUS DUAL ACTION 24 HOUR should be used with caution in patients 65 years of age and above.
Pediatrics (<12 years of age):
AERIUS DUAL ACTION 24 HOUR is not recommended for use in children below the age of 12 years due to lack of data on safety and efficacy.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
- Patients who are hypersensitive to adrenergic agents or to loratadine.
Due to its pseudoephedrine content, it is also contraindicated in patients:
- who are receiving irreversible monoamine oxidase (MAO) inhibitor therapy or during the 2 weeks following the stopping of such treatment (see DRUG INTERACTIONS)
- with narrow-angle glaucoma
- with urinary retention
- with cardiovascular diseases such as severe coronary artery disease, tachyarrhythmia and severe hypertension
- with hyperthyroidism
- with a history of haemorrhagic stroke or with risk factors which could increase the risk of haemorrhagic stroke.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
AERIUS DUAL ACTION 24 HOUR is not recommended for use in patients with severe hepatic or renal impairment.
General
Do not exceed the recommended dosage and the duration of treatment.
Do not use concurrently with other over-the counter antihistamines and decongestants.
Cardiovascular and Central Nervous System Effects (CNS)
The pseudoephedrine sulfate contained in AERIUS DUAL ACTION 24 HOUR Modified Release Tablets, like other sympathomimetic amines, can produce cardiovascular and central nervous system (CNS) effects in some patients such as insomnia, dizziness, weakness, tremor, or arrhythmias. In addition, central nervous system stimulation with convulsions or cardiovascular collapse with accompanying hypotension has been reported. Therefore, AERIUS DUAL ACTION 24 HOUR Modified Release Tablets should be used with caution in patients with cardiovascular disorders, and should not be used in patients with severe hypertension, tachycardia, palpitations or severe coronary artery disease.
Dependence/Tolerance
As with other CNS stimulants, pseudoephedrine sulfate carries the risk of abuse. Increased doses may ultimately produce toxicity. Continuous use can lead to tolerance and an increased risk of overdosing. Depression may follow rapid withdrawal.
Endocrine and Metabolism
Use with caution in patients with diabetes mellitus.
Gastrointestinal
Use with caution in patients with stenosing peptic ulcer and pyloroduodenal obstruction.
Genitourinary
Use with caution in patients with hypertrophy of the prostate or bladder neck obstruction.
Hepatic/Biliary/Pancreatic
The safety and efficacy of AERIUS DUAL ACTION 24 HOUR has not been established in patients with impaired hepatic function, and there are insufficient data to give adequate dose recommendations. The combination product is not recommended for use in patients with impaired hepatic function (See ACTION AND CLINICAL PHARMACOLOGY).
In a desloratadine single-dose (7.5 mg) pharmacokinetic study, subjects with mild to severe hepatic dysfunction had mean AUC and Cmax values up to 2.4 times higher than healthy subjects. Desloratadine 5mg was administered for 10 days to subjects with normal hepatic function or moderate dysfunction. Subjects with hepatic dysfunction could experience a 3-fold increase in exposure (AUC) to desloratadine. These findings are not considered to be clinically relevant.
Neurologic
Treatment should be discontinued in case of nausea or any other neurologic sign (such as headache or increased headache).
Ophthalmologic
Use with caution in patients with glaucoma and increased intraocular pressure.
Peri-Operative Considerations
If surgery is scheduled, discontinue treatment 24 hours before anaesthesia.
Renal
The safety and efficacy of AERIUS DUAL ACTION 24 HOUR has not been established in patients with impaired renal function, and there are insufficient data to give adequate dose recommendations. The combination product is not recommended for use in patients with impaired renal function (see ACTION AND CLINICAL PHARMACOLOGY).
In a desloratadine single-dose (7.5 mg) pharmacokinetic study, subjects (n=25) with varying degrees of renal insufficiency (mild, moderate, severe and hemodialysis) had 1.2 to 2.5 fold increases in desloratadine median AUC with minimal change in 3-hydroxy desloratadine concentrations. However, these findings are not considered to be clinically relevant.
Hypersensitivity Reactions
Hypersensitivity reactions including rash, pruritus, urticaria, edema, dyspnea, and anaphylaxis have been reported after administration of desloratadine a component of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets. If such a reaction occurs, therapy with AERIUS DUAL ACTION 24 HOUR Modified Release Tablets should be stopped and alternative treatment should be considered.
Special Populations
Pregnant Women: The safe use of AERIUS DUAL ACTION 24 HOUR during pregnancy has not been established. The use of pseudoephedrine decreases maternal blood flow. The use of AERIUS DUAL ACTION 24 HOUR is not recommended for pregnant women.
Nursing Women: Desloratadine and pseudoephedrine are both excreted in breast milk, therefore the use of AERIUS DUAL ACTION 24 HOUR is not recommended for women who are breast-feeding.
Pediatrics§ (< 12 years of age): AERIUS DUAL ACTION 24 HOUR is not recommended for use in children below the age of 12 years due to lack of data on safety and efficacy.
Geriatrics§ (≥ 65 years of age): The number of patients 65 years of age and above treated with AERIUS DUAL ACTION 24 HOUR were too limited to make any clinically relevant judgement regarding efficacy or safety of this drug product in this age group. Patients of 65 years or older are more likely to experience adverse reactions from sympathomimetic medicinal products. Therefore the combination product should be used with caution in patients above 65 years of age (See ACTION AND CLINICAL PHARMACOLOGY).
§CNS stimulations with convulsions or cardiovascular collapse with accompanying hypotension may be produced by sympathomimetic amines. These effects may be more likely to occur in children or elderly patients.
Athletes: Athletes should be informed that treatment with pseudoephedrine could lead to positive doping tests.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Very rare cases of hypersensitivity reactions including anaphylaxis and rash have been reported during the marketing of desloratadine. In addition, cases of tachycardia, palpitations, psychomotor hyperactivity, seizures, elevations of liver enzymes, hepatitis and increased bilirubin have been reported very rarely.
As with other sympathomimetic amines, central nervous system stimulation, muscular weakness, tightness in the chest and syncope may also be encountered with the use of pseudoephedrine sulfate.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
A total of 2852 subjects (12 to 78 years of age), of which 708 patients received AERIUS DUAL ACTION 24 HOUR daily for up to 15 days. The percentage of patients receiving AERIUS DUAL ACTION 24 HOUR who discontinued from the study because of an adverse event was 3.4%. Adverse events that were reported by ≥ 1% of patients receiving AERIUS DUAL ACTION 24 HOUR, are shown in Table 1.
| Table 1 - Incidence of Adverse Events Reported by ≥ 1% of Patients Receiving AERIUS DUAL ACTION 24 HOUR Modified Release Tablets (Pooled data from Studies P01875/P01884) | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Body System/Organ Class | DL 5.0 mg / PSE 240 mg QD (n = 708) n (%) | DL, 5mg QD (n = 712) n (%) | PSE, 240mg QD (n = 719) n (%) | ||||||
| Autonomic Nervous System | 63 (8.9) | 21 (2.9) | 84 (11.7) | ||||||
| dry mouth | 59 (8.3) | 17 (2.4) | 77 (10.7) | ||||||
| Central and Peripheral Nervous System | 34 (4.8) | 16 (2.2) | 31 (4.3) | ||||||
| dizziness | 14 (2.0) | 6 (0.8) | 13 (1.8) | ||||||
| psychomotor hyperactivity | 17 (2.4) | 2 (0.3) | 16 (2.2) | ||||||
| Gastrointestinal | 66 (9.3) | 32 (4.5) | 62 (8.6) | ||||||
| abdominal pain | 12 (1.7) | 8 (1.1) | 6 (0.8) | ||||||
| anorexia | 12 (1.7) | 2 (0.3) | 12 (1.7) | ||||||
| constipation | 12 (1.7) | 0 (0) | 9 (1.3) | ||||||
| diarrhea | 4 (0.6) | 5 (0.7) | 9 (1.3) | ||||||
| dyspepsia | 11 (1.6) | 7 (1.0) | 7 (1.0) | ||||||
| nausea | 12 (1.7) | 7 (1.0) | 18 (2.5) | ||||||
| General Disorders | 71 (10.0) | 68 (9.6) | 74 (10.3) | ||||||
| fatigue | 18 (2.5) | 19 (2.7) | 14 (1.9) | ||||||
| headache | 45 (6.4) | 37 (5.2) | 47 (6.5) | ||||||
| Heart Rate and Rhythm Disorders | 13 (1.8) | 6 (0.8) | 15 (2.1) | ||||||
| palpitation | 7 (1.0) | 4 (0.6) | 1 (0.1) | ||||||
| tachycardia | 5 (0.7) | 1 (0.1) | 14 (1.9) | ||||||
| Musculoskeletal | 16 (2.3) | 18 (2.5) | 17 (2.4) | ||||||
| myalgia | 8 (1.1) | 13 (1.8) | 12 (1.7) | ||||||
| Psychiatric | 79 (11.2) | 28 (3.9) | 86 (12.0) | ||||||
| insomnia | 35 (4.9) | 5 (0.7) | 54 (7.5) | ||||||
| irritability | 8 (1.1) | 4 (0.6) | 3 (0.4) | ||||||
| nervousness | 16 (2.3) | 5 (0.7) | 9 (1.3) | ||||||
| somnolence | 24 (3.4) | 12 (1.7) | 18 (2.5) | ||||||
| Resistance Mechanism Disorder | 11 (1.6) | 13 (1.8) | 16 (2.2) | ||||||
| Infection viral | 10 (1.4) | 11 (1.5) | 10 (1.4) | ||||||
| Table 1 - Incidence of Adverse Events Reported by ≥ 1% of Patients Receiving AERIUS DUAL ACTION 24 HOUR Modified Release Tablets (Pooled data from Studies P01875/P01884) |
|---|
| Body System/Organ Class | DL 5.0 mg / PSE 240 mg QD (n = 708) n (%) | DL, 5mg QD (n = 712) n (%) | PSE, 240mg QD (n = 719) n (%) |
|---|---|---|---|
| Respiratory | 50 (7.1) | 43 (6.0) | 54 (7.5) |
| epistaxis | 6 (0.8) | 7 (1.0) | 2 (0.3) |
| pharyngitis | 18 (2.5) | 11 (1.5) | 20 (2.8) |
| throat dry | 3 (0.4) | 2 (0.3) | 9 (1.3) |
| upper respiratory tract infection | 8 (1.1) | 11 (1.5) | 12 (1.7) |
DL = desloratadine; PSE = pseudoephedrine sulfate
There were no relevant differences in adverse reactions for subgroups of patients as defined by gender, age, or race.
In all clinical studies conducted, AERIUS DUAL ACTION 24 HOUR was safe and well tolerated. In Phase-3 studies, the overall incidence of adverse events was similar in AERIUS DUAL ACTION 24 HOUR and pseudoephedrine treatment groups, but was lower in the desloratadine group. The most common treatment-emergent adverse events of AERIUS DUAL ACTION 24 HOUR were dry mouth, headache followed by insomnia.
Less Common Clinical Trial Adverse Drug Reactions (< 1%) with AERIUS DUAL ACTION 24 HOUR
Autonomic Nervous System Disorders: autonomic system disorders, hypertension aggravated, saliva altered, saliva increased, sweating increased
Blood and Lymphatic System Disorders: blood neutrophil count decreased, white blood cell count decreased
Cardiovascular Disorder: ECG abnormal, hypertension, QTc/QT prolongation
Central and Peripheral Nervous System Disorders: confusion, migraine aggravated, paresthesia, sensory disturbance, tremor, vertigo
Gastrointestinal System Disorders: flatulence, gastritis, gastroenteritis, gastroesophageal reflux, gingival pain, loose stools, stomatitis ulcerative, tongue discoloration, vomiting,
General Disorder: asthenia, back pain, chest pain, fever, aggravated headache, injury accidental, malaise, post- procedure pain
Hearing and Vestibular Disorders: earache, tinnitus
Heart rate and Rhythm Disorders: AV block
Liver and Biliary System Disorders: SGTP increased
Metabolism and Nutritional Disorders: thirst
Musculo-Skeletal System Disorders: arthralgia, arthritis, muscle sprain, musculo-skeletal pain
Psychiatric Disorders: agitation, anxiety, concentration impaired, mental status altered, paroniria, sleep disorder, teeth-grinding
Reproductive Disorders: dysmenorrhea, intermenstrual bleeding, vaginal hemorrhage, vaginitis
Resistance Mechanism Disorder: moniliasis genital
Respiratory System Disorders: asthma aggravated, cough non-productive, coughing, dyspnea, nasal burning, pneumonia lobar, rhinitis, rhinorrhea, sinus congestion, sinusitis, wheezing
Skin and Appendages Disorders: acne, dermatitis, dry skin, insect bite, laceration skin, pruritus, rash
Special Senses Other, Disorders: taste perversion
Urinary System Disorders: dysuria, hematuria, micturition frequency, polyuria, urinary tract infection
Vascular (Extracardiac) Disorders: migraine
Vision Disorders: conjunctivitis, eyes dry, vision blurred
Abnormal Hematologic and Clinical Chemistry Findings
None to report.
Post-Market Adverse Drug Reactions
Very rare cases of hypersensitivity reactions (including anaphylaxis and rash), tachycardia, palpitations, psychomotor hyperactivity, seizures, elevation of liver enzymes, hepatitis and increased bilirubin have been reported during the marketing of desloratadine.
DRUG INTERACTIONS
Overview
Concomitant administration of sympathomimetics and reversible MAO inhibitors are not recommended. Caution should be exercised in patients being treated with other sympathomimetics, including decongestants, anorexogenics or amphetamine-type psychostimulants, antihypertensive agents, tricyclic antidepressants and other antihistamines. Caution should be exercised in patients receiving digitalis.
Antacids increase the rate of pseudoephedrine sulfate absorption, kaolin decreases it.
Drug-Drug Interactions
Interaction studies with AERIUS DUAL ACTION 24 HOUR and other medicinal products have not been conducted, however no clinically relevant interactions were observed in clinical trials with desloratadine in which azithromycin, erythromycin, ketoconazole, fluoxetine or cimetidine were co-administered.
Table 2 - Established or Potential Drug-Drug Interactions
| Ref | Effect | |
| Reversible and irreversible MAO inhibitor(s) | Theoretical | May cause risk of vasoconstriction and increased blood pressure. |
| sympathomimetic medicines | Theoretical | May result in critical hypertension reactions. |
| Bromocriptine, cabergoline, lisuride, pergolide | Theoretical | Risk of vasoconstriction and increase in blood pressure |
| Dihydroergotamine, ergotamine, methylergometrine | Theoretical | Risk of vasoconstriction and increase in blood pressure |
| Vasoconstrictors used as nasal decongestant | Theoretical | Risk of vasoconstriction |
Drug-Food Interactions
Food had no significant effect on the bioavailability (Cmax and AUC) of desloratadine and pseudoephedrine.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
The administration of AERIUS DUAL ACTION 24 HOUR should be discontinued at least 48 hours before skin tests since antihistamines may prevent or reduce otherwise positive reactions to dermal reactivity index.
Athletes should be informed that treatment with pseudoephedrine could lead to positive doping tests.
Drug-Lifestyle Interactions
The interaction with AERIUS DUAL ACTION 24 HOUR and alcohol has not been established, however in a clinical pharmacology trial, desloratadine taken concomitantly with alcohol did not potentiate the performance impairing effects of alcohol.
No studies on the effects on the ability to drive and use machines have been performed with AERIUS DUAL ACTION 24 HOUR. However, in clinical trials that assessed the driving ability, no impairment occurred in patients receiving desloratadine. However, patients should be informed that very rarely some people experience drowsiness, which may affect their ability to drive or use machines.
It is not expected that pseudoephedrine sulfate impairs psychomotor performance.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The duration of the treatment should be kept as short as possible and should not be continued after the symptoms have disappeared. It is advisable to limit treatment to about 14 days, as during chronic administration the activity of pseudoephedrine diminishes with time.
Recommended Dose and Dosage Adjustment
Adults and children 12 years of age and over: The recommended dose of AERIUS DUAL ACTION 24 HOUR is one tablet once daily.
After improvement of the congestive condition of the mucosae of the upper airway, treatment may be maintained with desloratadine alone, if necessary.
Administration
The tablet may be taken with a full glass of water but must be swallowed whole (without crushing, breaking or chewing it). The tablet may be taken with or without a meal.
OVERDOSAGE
Symptoms of overdose are mostly of a sympathomimetic nature. Symptoms may vary from CNS depression (sedation, apnoea, diminished mental alertness, cyanosis, coma, cardiovascular collapse) to CNS stimulation (insomnia, hallucination, tremors, convulsions) with possible fatal outcome. Other symptoms may include: headache, anxiety, micturition difficulty, muscle weakness and tenseness, euphoria, excitement, respiratory failure, cardiac arrhythmias, tachycardia, palpitations, thirst, perspiration, nausea, vomiting, precordial pain, dizziness, tinnitus, ataxia, blurred vision and hypertension or hypotension. CNS stimulation is particularly likely in children, as are atropine-like symptoms (dry mouth, fixed and dilated pupils, flushing, hyperthermia, and gastrointestinal symptoms). Some patients may present a toxic psychosis with delusions and hallucinations.
Treatment: In the event of overdose, consider standard measures to remove any unabsorbed drug. Symptomatic and supportive treatment is recommended. Adsorption of active substance remaining in the stomach may be attempted by administration of active charcoal suspended in water. Perform gastric lavage with physiologic saline solution, particularly in children. In adults, tap water can be used. Remove as much as possible of the amount administered before the next instillation. Desloratadine is not removed by haemodialysis and it is not known if it is eliminated by peritoneal dialysis. After emergency treatment, continue to monitor the patient medically.
AERIUS (desloratadine) administered at a dose of 45 mg daily (nine times the clinical dose) for ten days showed no statistically or clinically relevant prolongation of the QTc interval. The mean changes in QTc were 0.3 msec and 4.3 msec for placebo and desloratadine, respectively (p=0.09; Lower confidence interval (LCI) = -0.6; Upper confidence interval (UCI) = 8.7).
Treatment of the pseudoephedrine overdosage is symptomatic and supportive. Stimulants (analeptics) must not be used. Hypertension can be controlled with an alpha-blocking agent and tachycardia with a beta-blocking agent. Short acting barbituates, diazepam or paraldehyde may be administered to control seizures. Hyperpyrexia, especially in children, may require treatment with tepid water sponge baths or hypothermia blanket. Apnoea is treated with respiratory assistance.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Desloratadine is a non-sedating long acting antihistamine with selective peripheral histamine H1-receptor antagonist activity, which has demonstrated antiallergic, antihistaminic and anti-inflammatory activity.
Pseudoephedrine sulfate is the synthetic salt of one of the naturally occurring dextrorotatory diastereomer of ephedrine and classified as an indirect sympathomimetic amine. It provides a nasal decongestant effect after oral administration due to its vasoconstrictive action and produces a gradual but sustained decongestant effect, facilitating shrinkage of congested mucosa in upper respiratory areas.
Pharmacodynamics
After oral administration, desloratadine selectively blocks peripheral histamine H1-receptors as the drug is effectively excluded from entry into the central nervous system. Receptor binding data indicate that at a concentration of 2-3 ng/mL, desloratadine shows significant interaction with the human histamine H1 receptor. Desloratadine inhibited histamine release from human mast cells in vitro.
Pseudoephedrine sulfate is a sympathomimetic agent with mostly α-adrenergic activity. It has an indirect sympathomimetic effect due primarily to the release of adrenergic mediators from the post-ganglionic nerve endings. Oral administration of pseudoephedrine at the recommended dose can cause other sympathomimetic effects, such as increased blood pressure, tachycardia or manifestations of central nervous system excitation.
Pharmacokinetics
Absorption: A bioequivalence study that compared AERIUS DUAL ACTION 24 HOUR Modified release Tablets to the monotherapy (desloratadine 5 mg, and pseudoephedrine 240 mg) showed that AERIUS DUAL ACTION 24 HOUR Modified Release Tablets was not bioequivalent to the monotherapy (desloratadine 5 mg tablet). The systemic exposure to desloratadine and 3-hydroxydesloratadine was 15-20% lower from AERIUS DUAL ACTION 24 HOUR Modified Release Tablets than those from desloratadine 5 mg tablet. Clinical trials were therefore necessary to support efficacy of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets (see Clinical Trials section).
In a single dose pharmacokinetic study with AERIUS DUAL ACTION 24 HOUR, the mean time to maximum plasma concentrations (Tmax) for desloratadine occurred at approximately 6-7 hours post dose and mean peak plasma concentrations (Cmax) and area under the concentration-time curve (AUC) of approximately 1.79 ng/ml and 61.1 ng•hr/ml, respectively, were observed.
For pseudoephedrine, the mean Tmax occurred at 8-9 hours post dose and mean peak plasma concentrations (Cmax and AUC) of approximately 328 ng/ml and 6438 ng•hr/ml, respectively, were observed. Food and grapefruit juice had no effect on the bioavailability (Cmax and AUC) of desloratadine or pseudoephedrine.
Following oral administrations of AERIUS DUAL ACTION 24 HOUR Modified Release once daily for 14 days in normal healthy volunteers, steady-state conditions were reached on day 12 for desloratadine and day 10 for pseudoephedrine. For desloratadine, mean steady state peak plasma concentrations (Cmax) and area under the concentration-time curve (AUC 0-24 h) of approximately 2.44 ng/mL and 34.8 ng•hr/mL were observed, respectively. For pseudoephedrine, mean steady state peak plasma concentrations (Cmax) and AUC (0-24 h) of 523 ng/mL and 8795 ng•hr/mL were observed.
Distribution: Desloratadine and 3-hydroxydesloratadine are approximately 82% to 87% and 85% to 89% bound to plasma proteins, respectively. Protein binding of desloratadine and 3-hydroxydesloratadine was unaltered in subjects with impaired renal function.
Metabolism: Desloratadine is extensively metabolized. The results of metabolic profiling indicated that hydroxylation of desloratadine to 3-hydroxy desloratadine (3-OH desloratadine) followed by its subsequent glucuronidation was the major pathway of metabolism of desloratadine. The enzyme responsible for the metabolism of desloratadine has not been identified yet, and therefore some interactions with other drugs cannot be fully excluded. In-vivo studies with specific inhibitors of CYP3A4 and CYP2D6 have shown that these enzymes are not important in the metabolism of desloratadine. Desloratadine does not inhibit CYP3A4 and CYP2D6 and is neither a substrate nor an inhibitor of p-glycoprotein.
Data from clinical pharmacology studies indicate that a subset of the general adult and pediatric patient population has a decreased ability to form 3-hydroxydesloratadine. In pharmacokinetic and clinical trials in subjects between 2 and 70 years of age, 6 % of the subjects were poor metabolizers of desloratadine and reached a higher desloratadine concentration (poor metabolizer defined as a subject with an AUC ratio of 3-hydroxydesloratadine to desloratadine less than 0.1, or a subject with a desloratadine half-life exceeding 50 hours). In this data, no difference in prevalence of poor metabolizers was noted across age groups, but the frequency was higher in Blacks (18%) compared to Caucasians (2%) or Hispanics (2%). Ninety pediatric and 440 adult subjects were phenotyped for the polymorphism in clinical pharmacology studies. The incidence of the trait was approximately 8.6% in adults and 15.6% in pediatric subjects. The desloratadine exposure (AUC) associated with the poor metabolizer phenotype has been well characterized (~4 times that of normal metabolizers) in single dose studies and is similar in pediatric and adult subjects at various doses. Median (range) AUC in pediatric normal and poor metabolizers was 31.9 (14-74) ng•hr/mL and 116 (72-210) ng•hr/mL, respectively. The corresponding values for adult normal and poor metabolizers were 33.5 (8.7-99) ng•hr/mL and 139 (82-393) ng•hr/mL, respectively. In adults characterized as poor metabolizers, desloratadine exposure (AUC) after multiple doses has been demonstrated to be about six fold higher than that of normal metabolizers. The desloratadine exposure after multiple doses has not been documented for children. The safety profile of adult and pediatric poor metabolizers of desloratadine was not different from that of the general population.
Following administration of desloratadine 5mg for 28 days, the approximate two-fold degree of accumulation of desloratadine and 3-OH desloratadine is consistent with the half-life of DL and its active metabolite and a once daily dosing frequency. This accumulation is not clinically meaningful. The pharmacokinetics of desloratadine and 3-OH desloratadine do not change after daily dosing for 7 consecutive days.
There is no evidence of clinically relevant drug accumulation following once daily dosing of AERIUS (5 mg to 20 mg) for 14 days.
Excretion A human mass balance study documented a recovery of approximately 87% of the 14C-desloratadine dose, which was equally distributed in urine and feces as metabolic products.
The mean elimination half-life of pseudoephedrine is dependent on urinary pH. The elimination half-life is approximately 3-6 or 9-16 hours when the urinary pH is 5 or 8, respectively. The active substance and its metabolite are excreted in urine; 55-75% of the administered dose is excreted unchanged.
Special Populations and Conditions
Pediatrics: AERIUS DUAL ACTION 24 HOUR Modified Release Tablets are not an appropriate dosage form for use in pediatric patients below 12 years of age.
Geriatrics: The number of patients (n=10) 65 years of age and above treated with AERIUS DUAL ACTION 24 HOUR Modified Release Tablets was too limited to make any clinically relevant judgment regarding the efficacy or safety of this drug product in this age group.
Following multiple-dose administration of AERIUS® (desloratadine) Tablets, the mean Cmax and AUC values for desloratadine were 20% greater than in younger subjects (< 65 years old). The oral total body clearance (CL/F) when normalized for body weight was similar between the two age groups. The mean plasma elimination half-life of desloratadine was 33.7 hr in subjects ≥ 65 years old. The pharmacokinetics for 3-hydroxydesloratadine appeared unchanged in older versus younger subjects. These age-related differences are unlikely to be clinically relevant and no dosage adjustment is recommended in elderly subjects.
Gender: No clinically significant gender-related differences were observed in the pharmacokinetic parameters of desloratadine, 3-hydroxydesloratadine or pseudoephedrine following administration of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets. Female subjects treated for 14 days with AERIUS® Tablets had 10% and 3% higher desloratadine Cmax and AUC values, respectively, compared with male subjects. The 3-hydroxydesloratadine Cmax and AUC values were also increased by 45% and 48%, respectively, in females compared with males. However, these apparent differences are not considered clinically relevant and therefore no dosage adjustment is recommended.
Race: No studies have been conducted to evaluate the effect of race on the pharmacokinetics of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets. Following 14 days of treatment with AERIUS® Tablets, the Cmax and AUC values for desloratadine were 18% and 32% higher, respectively in Blacks compared with Caucasians. For 3-hydroxydesloratadine there was a corresponding 10% reduction in Cmax and AUC values in Blacks compared to Caucasians. These differences are not considered to be clinically relevant and therefore no dose adjustment is recommended.
Hepatic Insufficiency: No studies with AERIUS DUAL ACTION 24 HOUR Modified Release Tablets or pseudoephedrine were conducted in patients with hepatic impairment.
Following a single oral dose of desloratadine, pharmacokinetics were characterized in patients with mild (n=4), moderate (n=4) and severe (n=4) hepatic impairment as defined by the Child-Pugh classification of hepatic impairment and 8 subjects with normal hepatic function. Patients with hepatic impairment, regardless of severity, had approximately a 2.4-fold increase in AUC as compared with normal subjects. The apparent oral clearance of desloratadine in subjects with mild, moderate, and severe hepatic impairment was 37%, 36%, and 28% of that in normal subjects, respectively. An increase in the mean elimination half-life of desloratadine in patients with hepatic impairment was observed. For 3-hydroxydesloratadine, the mean Cmax and AUC values for subjects with hepatic impairment combined were not statistically significantly different from subjects with normal hepatic function.
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets is not recommended in patients with severe hepatic impairment (see WARNINGS AND PRECAUTIONS).
Renal Insufficiency: No studies with AERIUS DUAL ACTION 24 HOUR Modified Release Tablets were conducted in patients with renal impairment.
Following a single dose of desloratadine 7.5 mg pharmacokinetics were characterized in patients with mild (n=7; creatinine clearance 51-69 mL/min/1.73m2), moderate (n=6; creatinine clearance 34-43 mL/min/1.73m2) and severe (n=6; creatinine clearance 5-29 mL/min/1.73m2) renal impairment or hemodialysis dependent (n=6) patients. In subjects with mild and moderate impairment, median Cmax and AUC values increased by approximately 1.2 and 1.9-fold, respectively, relative to subjects with normal renal function. In patients with severe renal impairment or who were hemodialysis dependent, Cmax and AUC values increased by approximately 1.7- and 2.5-fold, respectively. Minimal changes in 3-hydroxydesloratadine concentrations were observed. Desloratadine and 3-hydroxydesloratadine were poorly removed by hemodialysis. Plasma protein binding of desloratadine and 3-hydroxydesloratadine was unaltered by renal impairment.
Pseudoephedrine is primarily excreted unchanged in the urine as unchanged drug with the remainder apparently being metabolized in the liver. Therefore, pseudoephedrine may accumulate in patients with renal impairment.
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets is not recommended in patients with severe renal impairment (see WARNINGS AND PRECAUTIONS).
STORAGE AND STABILITY
Temperature and Moisture
- Store between 15 and 25°C.
- Protect from excessive moisture and heat
- Protect from light (keep in outer carton).
Others
Keep in a safe place out of the reach of children.
SPECIAL HANDLING INSTRUCTIONS
Keep blister package in the outer carton.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage Form
Modified release tablet for oral administration.
Composition
Light blue oval tablet with “D24” branded in Black ink on one side.
Medicinal Ingredients: 5.0 mg desloratadine in the immediate release coating and 240 mg pseudoephedrine sulfate, USP in an extended release core.
Non medicinal ingredients (in alphabetical order): Ammonium hydroxide; Dibasic Calcium Phosphate Dihydrate, Edetate Disodium, Ethylcellulose, FD&C Blue No. 2 Lake, Hypromellose, Iron oxide black, Isopropyl alcohol, Magnesium Stearate, N-butyl alcohol, Polyacrylate, Polyethylene Glycol 8000, Povidone, Propylene glycol, Shellac, Silicon Dioxide, Simethicone, Talc, Titanium Dioxide.
Packaging:
AERIUS DUAL ACTION 24 HOUR is supplied in unit dose blisters comprised of laminate blister film and foil lidding. The blister is packaged in a folding carton.
Available in packs of 5 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance (1 of 2)
Proper name: desloratadine
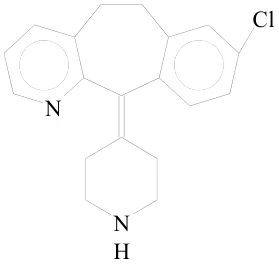
Chemical name: 8-chloro-6, 11-dihydro-11-(4-piperidinylidene)-5H-benzo-[5,6] cyclohepta [1, 2-b]pyridine
Molecular formula: C19H19CIN2
Molecular mass: 310.8
Structural formula:
Physicochemical properties:
Physical Form: white to off-white powder
Solubility: ethanol >100 mg/mL (freely soluble)
methylene chloride >100 mg/mL (freely soluble)
methanol >100 mg/mL (freely soluble)
octanol >100 mg/mL (freely soluble)
0.1N HCl 39.7 mg/mL (soluble)
DMSO 24.5 mg/mL (soluble)
water 0.1mg/mL (very slightly soluble)
pH 7.4 phosphate buffer 1.5 mg/mL (slightly soluble)
0.1N NaOH <0.1 mg/mL (practically insoluble)
pKa Values: pyridine functional group 4.2
piperidine functional group 9.7
Partition Coefficient: log KO/W
n-octanol/0.1N HCl -2.27
n-octanol/pH 3 buffer -1.44
n-octanol/pH 6 buffer 0.342
n-octanol/pH 7 buffer 1.02
n-octanol/pH 8 buffer 0.944
Melting Point: Form I 156.0 to 157.5°C
Drug Substance (2 of 2)
Proper name: pseudoephedrine sulfate
Chemical name: benzenemethanol, α- [1-(methylamino) ethyl]-, S-(R*, R*)]-, sulfate (2:1) (salt)
Molecular formula: (C10H15NO)2 • H2SO4
Molecular mass: 428.54
Structural formula:
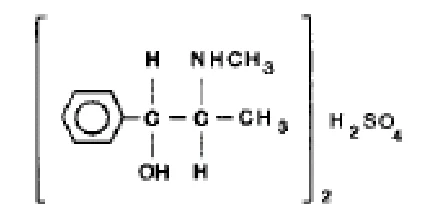
Physicochemical properties: Pseudoephedrine sulfate is a colourless hygroscopic crystal or white, hygroscopic crystalline powder, practically odourless, with a bitter taste. It is very soluble in alcohol and sparingly soluble in ether.
CLINICAL TRIALS
Study demographics and trial design
The clinical efficacy and safety of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets was evaluated in two 2-week, multicenter, randomized parallel-group clinical trials involving 2852 patients 12 to 78 years of age with seasonal allergic rhinitis, 708 of whom received AERIUS DUAL ACTION 24 HOUR Modified Release Tablets. In the two trials patients were randomized to receive AERIUS DUAL ACTION 24 HOUR Modified Release Tablets, once daily, AERIUS Tablets 5 mg once daily, and sustained-release pseudoephedrine tablet 240 mg once daily for two weeks. Primary efficacy variable was twice-daily reflective patient scoring of four nasal symptoms (rhinorrhea, nasal stuffiness/congestion, nasal itching, and sneezing) and four non-nasal symptoms (itching/burning eyes, tearing/watering eyes, redness of eyes, and itching of ears/palate) on a four-point scale (0=none, 1=mild, 2=moderate, and 3=severe).
In both trials, the antihistaminic efficacy and of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets, as measured by total symptom score excluding nasal congestion, was significantly greater than pseudoephedrine alone over the 2-week treatment period (p≤0.015); and the decongestant efficacy of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets, as measured by nasal stuffiness/congestion, was significantly greater than desloratadine alone over the 2-week treatment period p≤0.001). Clinical trial summary is presented in Table 3. Primary efficacy variable results are shown in Tables 4 to 7.
Table 3 - Summary of Efficacy and Safety Studies using AERIUS DUAL ACTION 24 HOUR in patients with Seasonal Allergic Rhinitis (SAR)
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| P01875 | Subjects received AERIUS DUAL ACTION 24 HOUR QD, DL 5.0 mg QD or PSE 240 mg QD orally for 15 days. | 1495 | 12 - 78 | 527 Males 968 Females | |
| P01884 | Subjects received AERIUS DUAL ACTION 24 HOUR QD, DL 5.0 mg QD or PSE 240 mg QD orally for 15 days. | 1357 | 11 - 78 | 516 Males 841 Females |
Study results
Table 4 - Primary Endpoint Results of study P01875: Changes in Symptoms in a 2-week Clinical Trial in Patients with Seasonal Allergic Rhinitis
| Treatment Group (n) | Mean Baseline* | Mean Change (% change) from Baseline** | AERIUS DUAL ACTION 24 HOUR comparison to components (p-value) |
| Total Symptom Score (Excluding Nasal Congestion) | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 15.01 | -6.09 (-38.8) | - |
Desloratadine Tablet 5 mg QD (369) | 14.71 | -5.10 (-33.5) | P = 0.001 |
Pseudoephedrine Tablet 240 mg QD (377) | 15.08 | -5.08 (-32.4) | P = 0.001 |
| Nasal Stuffiness/Congestion | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 2.57 | -0.90 (-33.4) | - |
Desloratadine Tablet 5 mg QD (369) | 2.55 | -0.74 (-28.0) | P = 0.001 |
Pseudoephedrine Tablet 240 mg QD (377) | 2.56 | -0.78 (-28.6) | P = 0.009 |
*To qualify at Baseline, the sum of the twice daily diary reflective scores for the three days prior to Baseline and the morning of the Baseline visit were to total ≥42 for total nasal symptom score (sum of 4 nasal symptoms of rhinorrhea, nasal stuffiness/congestion, nasal itching and sneezing) and a total of ≥35 for total non-nasal symptoms score (sum of 4 non-nasal symptoms of itching/burning eyes, tearing/watering eyes, redness of eyes, and itching of ears/palate), and a score of ≥14 for each of the individual symptoms of nasal stuffiness/congestion and rhinorrhea. Each symptom was scored on a 4-point severity scale (0=none, 1=mild, 2=moderate, 3=severe).
**Mean reduction in score averaged over the 2-week treatment period.
Table 5 - Primary Endpoint Results of study P01875: Changes in Individual Nasal Symptoms in a 2-week Clinical Trial in Patients with Seasonal Allergic Rhinitis
| Treatment Group (n) | Mean Baseline* | Mean Change (% change) from Baseline** | AERIUS DUAL ACTION 24 HOUR comparison to components (p-value) |
|---|---|---|---|
| Rhinorrhea | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 2.53 | -0.85 (-31.9) | - |
Desloratadine Tablet 5 mg QD (369) | 2.51 | -0.74 (-28.5) | P = 0.030 |
Pseudoephedrine Tablet 240 mg QD (372) | 2.53 | -0.70 (-26.2) | P = 0.002 |
| Nasal Itching | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 2.24 | -0.90 (-38.5) | - |
Desloratadine Tablet 5 mg QD (369) | 2.21 | -0.75 (-31.7) | P = 0.003 |
Pseudoephedrine Tablet 240 mg QD (372) | 2.27 | -0.75 (-30.2) | P = 0.002 |
| Sneezing | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 2.05 | -0.94 (-43.7) | - |
Desloratadine Tablet 5 mg QD (369) | 1.96 | -0.76 (-36.8) | P <0.001 |
Pseudoephedrine Tablet 240 mg QD (372) | 2.04 | -0.73 (-33.1) | P <0.001 |
| Itching/Burning Eyes | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 2.24 | -0.93 (-39.0) | - |
Desloratadine Tablet 5 mg QD (369) | 2.20 | -0.76 (-33.0) | P = 0.002 |
Pseudoephedrine Tablet 240 mg QD (372) | 2.22 | -0.79 (-33.1) | P = 0.006 |
| Treatment Group (n) | Mean Baseline* | Mean Change (% change) from Baseline** | AERIUS DUAL ACTION 24 HOUR comparison to components (p-value) |
|---|---|---|---|
| Tearing/Watery Eyes | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 2.08 | -0.88 (-39.6) | - |
Desloratadine Tablet 5 mg QD (369) | 2.03 | -0.76 (-35.5) | P = 0.031 |
Pseudoephedrine Tablet 240 mg QD (372) | 2.09 | -0.77 (-33.8) | P = 0.038 |
| Redness of Eyes | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 1.96 | -0.80 (-38.8) | - |
Desloratadine Tablet 5 mg QD (369) | 1.92 | -0.66 (-33.3) | P = 0.006 |
Pseudoephedrine Tablet 240 mg QD (372) | 1.95 | -0.70 (-34.4) | P = 0.053 |
| Itching of Ears/Palate | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (372) | 1.92 | -0.79 (-40.0) | - |
Desloratadine Tablet 5 mg QD (369) | 1.88 | -0.66 (-33.4) | P = 0.014 |
Pseudoephedrine Tablet 240 mg QD (372) | 1.99 | -0.66 (-31.9) | P = 0.011 |
*To qualify at Baseline, the sum of the twice daily diary reflective scores for the three days prior to Baseline and the morning of the Baseline visit were to total ≥42 for total nasal symptom score (sum of 4 nasal symptoms of rhinorrhea, nasal stuffiness/congestion, nasal itching and sneezing) and a total of ≥35 for total non-nasal symptoms score (sum of 4 non-nasal symptoms of itching/burning eyes, tearing/watering eyes, redness of eyes, and itching of ears/palate), and a score of ≥14 for each of the individual symptoms of nasal stuffiness/congestion and rhinorrhea. Each symptom was scored on a 4-point severity scale (0=none, 1=mild, 2=moderate, 3=severe).
**Mean reduction in score averaged over the 2-week treatment period.
Table 6 - Primary Endpoint Results of study P01884: Changes in Symptoms in a 2-week Clinical Trial in Patients with Seasonal Allergic Rhinitis
| Treatment Group (n) | Mean Baseline | Mean Change (% change) from Baseline** | AERIUS DUAL ACTION 24 HOUR comparison to components (p-value) |
| Total Symptom Score (Excluding Nasal Congestion) | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 14.84 | -5.71 (-37.4) | - |
Desloratadine Tablet 5 mg QD (337) | 15.06 | -4.78 (-30.8) | P = 0.003 |
Pseudoephedrine Tablet 240 mg QD (337) | 15.03 | -4.95 (-32.0) | P = 0.015 |
| Nasal Stuffiness/Congestion | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 2.56 | -0.85 (-32.3) | - |
Desloratadine Tablet 5 mg QD (337) | 2.57 | -0.65 (-24.8) | P < 0.0015 |
Pseudoephedrine Tablet 240 mg QD (337) | 2.54 | -0.70 (-27.1) | P = 0.002 |
*To qualify at Baseline, the sum of the twice daily diary reflective scores for the three days prior to Baseline and the morning of the Baseline visit were to total ≥42 for total nasal symptom score (sum of 4 nasal symptoms of rhinorrhea, nasal stuffiness/congestion, nasal itching and sneezing) and a total of ≥35 for total non-nasal symptoms score (sum of 4 non-nasal symptoms of itching/burning eyes, tearing/watering eyes, redness of eyes, and itching of ears/palate), and a score of ≥14 for each of the individual symptoms of nasal stuffiness/congestion and rhinorrhea. Each symptom was scored on a 4-point severity scale (0=none, 1=mild, 2=moderate, 3=severe).
**Mean reduction in score averaged over the 2-week treatment period.
Table 7 - Primary Endpoint Results of study P01884: Changes in Individual Nasal Symptoms in a 2-week Clinical Trial in Patients with Seasonal Allergic Rhinitis
| Treatment Group (n) | Mean Baseline* | Mean Change (% change) from Baseline** | AERIUS DUAL ACTION 24 HOUR comparison to components (p-value) |
|---|---|---|---|
| Rhinorrhea | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 2.50 | -0.79 (-30.4) | - |
Desloratadine Tablet 5 mg QD (337) | 2.48 | -0.67 (-26.4) | P = 0.017 |
Pseudoephedrine Tablet 240 mg QD (337) | 2.51 | -0.66 (-25.3) | P = 0.009 |
| Nasal Itching | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 2.26 | -0.90 (-38.9) | - |
Desloratadine Tablet 5 mg QD (337) | 2.24 | -0.70 (-29.7) | P <0.001 |
Pseudoephedrine Tablet 240 mg QD (337) | 2.25 | -0.74 (-31.7) | P = 0.002 |
| Sneezing | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 1.97 | -0.87 (-43.4) | - |
Desloratadine Tablet 5 mg QD (337) | 2.06 | -0.71 (-33.1) | P = 0.002 |
Pseudoephedrine Tablet 240 mg QD (337) | 2.05 | -0.76 (-36.5) | P = 0.032 |
| Itching/Burning Eyes | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 2.20 | -0.86 (-37.5) | - |
Desloratadine Tablet 5 mg QD (337) | 2.26 | -0.74 (-30.4) | P = 0.025 |
Pseudoephedrine Tablet 240 mg QD (337) | 2.23 | -0.75 (-31.9) | P = 0.033 |
| Treatment Group (n) | Mean Baseline* | Mean Change (% change) from Baseline** | AERIUS DUAL ACTION 24 HOUR comparison to components (p-value) |
|---|---|---|---|
| Tearing/Watery Eyes | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 2.00 | -0.79 (-37.4) | - |
Desloratadine Tablet 5 mg QD (337) | 2.08 | -0.70 (-31.6) | P = 0.122 |
Pseudoephedrine Tablet 240 mg QD (337) | 2.04 | -0.72 (-33.7) | P = 0.213 |
| Redness of Eyes | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 1.94 | -0.73 (-35.8) | - |
Desloratadine Tablet 5 mg QD (337) | 1.99 | -0.63 (-30.2) | P = 0.049 |
Pseudoephedrine Tablet 240 mg QD (337) | 1.96 | -0.67 (-33.7) | P = 0.242 |
| Itching of Ears/Palate | |||
AERIUS DUAL ACTION 24 HOUR Modified Release Tablets QD (333) | 1.96 | -0.77 (-39.5) | - |
Desloratadine Tablet 5 mg QD (337) | 1.93 | -0.62 (-32.1) | P = 0.005 |
Pseudoephedrine Tablet 240 mg QD (337) | 1.99 | -0.65 (-30.7) | P = 0.028 |
*To qualify at Baseline, the sum of the twice daily diary reflective scores for the three days prior to Baseline and the morning of the Baseline visit were to total ≥42 for total nasal symptom score (sum of 4 nasal symptoms of rhinorrhea, nasal stuffiness/congestion, nasal itching and sneezing) and a total of ≥35 for total non-nasal symptoms score (sum of 4 non-nasal symptoms of itching/burning eyes, tearing/watering eyes, redness of eyes, and itching of ears/palate), and a score of ≥14 for each of the individual symptoms of nasal stuffiness/congestion and rhinorrhea. Each symptom was scored on a 4-point severity scale (0=none, 1=mild, 2=moderate, 3=severe).
**Mean reduction in score averaged over the 2-week treatment period.
AERIUS DUAL ACTION 24 HOUR significantly relieved rhinorrhea, nasal stuffiness/congestion, nasal itching and sneezing, itching/burning eyes, tearing/watering eyes, redness of the eyes, and itching of the ears or palate to a greater extent than either component alone. Desloratadine and Pseudoephedrine each improved nasal stuffiness/congestion to a similar degree (no statistically significant difference). Additionally, rhinitis symptoms were reduced as early as after the first day’s dosing and the effects of the dose were maintained over the 24-hour dosing period.
There were no significant differences in the efficacy of AERIUS DUAL ACTION 24 HOUR Modified Release Tablets across subgroups of patients defined by gender, age, or race.
DETAILED PHARMACOLOGY
Pre clinical studies of desloratadine in combination with pseudoephedrine sulfate have not been conducted. However, non-clinical data with desloratadine reveal no special hazard for humans based on conventional studies of safety pharmacology, repeated-dose toxicity, genotoxicity and toxicity to reproduction. The lack of carcinogenic potential was demonstrated in studies conducted with desloratadine and loratadine.
Preclinical Pharmacology
In addition to antihistaminic activity, desloratadine has demonstrated antiallergic and anti-inflammatory activity in a number of in vitro (mainly conducted on cells of human origin) and in vivo studies. These studies have shown that desloratadine inhibits the broad cascade of events that initiate and propagate allergic inflammation, including:
- the release of proinflammatory cytokines including IL-4, IL-6, IL-8 and IL-13,
- the release of important proinflammatory chemokines such as RANTES (Regulated upon Activation, Normal T-cell Expressed and Secreted),
- superoxide anion production by activated polymorphonuclear neutrophils,
- eosinophil adhesion and chemotaxis,
- the expression of the adhesion molecules such as P-selectin,
- IgE-dependent release of histamine, prostaglandin (PGD2) and leukotriene (LTC4)
- the acute allergic bronchoconstrictor response and allergic cough.
Desloratadine exhibits excellent receptor specificity for histamine H1-receptors. This selectivity together with a limited entry to the CNS accounts for the little or no sedation liability observed in clinical studies. Although antimuscarinic activity is significant from in vitro studies, this activity does not seem to be relevant in vivo where anticholinergic effects are only seen at very high doses, well in excess of the antihistamine dose.
Results of a radiolabeled tissue distribution study in rats and a radioligand H1-receptor binding study in guinea pigs showed that desloratadine does not readily cross the blood brain barrier.
Reports of serious cardiac arrhythmias with the use of some antihistamines prompted a careful and extensive evaluation of the cardiovascular safety of desloratadine. Years of clinical experience with loratadine, and indirectly with desloratadine, indicates that desloratadine has not been associated with ventricular arrhythmias. Studies with desloratadine in rats, guinea pigs and monkeys, at multiples of the clinical dose, have confirmed there is no effect on important components of the ECG such as PR interval, QRS interval or QTc interval. Further studies on cardiac K+ channels, including the important HERG channel, have shown no effect at 1 micromolar desloratadine concentration, which is well in excess of therapeutic plasma levels.
Pharmacokinetics
In laboratory animals and humans, desloratadine was extensively absorbed (> 90%) following oral administration. In laboratory animals, accurate exposure estimates to desloratadine were only obtained at low doses since duration (0-24 hr) of plasma sampling did not allow for an accurate determination of AUC (0-∞). In rats and monkeys, CL/F values for desloratadine decreased with duration of dosing; however in humans, single dose and multiple dose CL/F values were the same. The cause for the changes in CL/F in rats and monkeys is unknown. In all species, exposure to desloratadine was greater following desloratadine administration than following an equal dose (mg/kg or mg) of loratadine.
The low amounts of desloratadine recovered in urine and feces indicate that, in laboratory animals and humans (normal metabolizers), desloratadine is metabolically cleared from plasma.
In vivo and in vitro metabolic profiles for desloratadine, loratadine and their metabolites were obtained in laboratory animals and humans. The metabolic pathways for desloratadine were the same within each species following 14C-desloratadine and 14C-loratadine administration. The primary pathways for desloratadine metabolism involved hydroxylation at either the 3-, 5-, or 6-positions. All desloratadine metabolites identified in human plasma and excreta following desloratadine and loratadine administration were also observed in profiles from at least one of the preclinical species.
The major (>5%) human metabolites of desloratadine were present in all species (mouse, rat, rabbit, monkey) after exposure to desloratadine and loratadine. In laboratory animals, hydroxylation was primarily at the 5- and 6-position while in humans hydroxylation occurred primarily at the 3-position.
Human Pharmacodynamics
Wheal and Flare: Desloratadine 5mg was significantly better than placebo, as measured by a reduction in histamine-induced wheal and flare areas for all days tested (1, 7, 14, 21, 28). There was no evidence of tachyphylaxis over the 28-day dosing period.
Effects on QTc: In clinical trials for AERIUS DUAL ACTION 24 HOUR Modified Release Tablets, ECGs were recorded at baseline and endpoint within 1 to 3 hours after the last dose. The majority of ECGs were normal at both baseline and endpoint. No clinically meaningful changes were observed following treatment with AERIUS DUAL ACTION 24 HOUR Modified Release Tablets for any ECG parameter, including the QTc interval. An increase in the ventricular rate of 7.1 and 6.4 bpm was observed in the AERIUS DUAL ACTION 24 HOUR Modified Release Tablets and pseudoephedrine groups, respectively, compared to an increase of 3.2 bpm in patients receiving desloratadine alone.
Cardiovascular Pharmacodynamics: To confirm the cardiovascular safety of AERIUS (desloratadine), a study to evaluate the electrocardiographic effects of desloratadine in subjects (n=24) treated with 45 mg desloratadine (nine times the clinical dose) once daily for 10 days was conducted. The primary endpoint of this study was the difference between Baseline (Day -1) maximum ventricular rate, PR, QRS, QT and QTc intervals and the corresponding Day 10 maximum ECG parameters. At 9-fold the proposed clinical dose, there was no statistically or clinically relevant prolongation of the QTc interval. The mean changes in QTc were 0.3 msec and 4.3 msec for placebo and desloratadine, respectively (p=0.09; Lower confidence interval (LCI) = -0.6; Upper confidence interval (UCI) = 8.7). It should be noted that in a separate rising, multiple dose study in which up to 20 mg of AERIUS was administered daily for 14 days, no statistically or clinically relevant cardiovascular effects were observed.
Psychomotor Pharmacodynamics: Drowsiness and somnolence, which affect psychomotor performance, have been reported with first generation antihistamines. The co-administration of alcohol with such products has resulted in further impairment of psychomotor performance.
In the previously mentioned clinical study, which utilized a 45 mg dose of AERIUS, there were no reports of somnolence. In a separate randomized, single-dose, double-blind, placebo-controlled, 4-way crossover study, 25 healthy volunteers were treated with desloratadine 7.5 mg/juice, desloratadine 7.5 mg/alcohol in juice, placebo tablet/alcohol in juice and placebo tablet/juice. No significant differences were found in the psychomotor test results between desloratadine and placebo groups, whether given alone or with alcohol. In a study with AERIUS (desloratadine) no effects on the ability to drive and use machines have been observed. In a separate study in normal volunteers administered a single dose of 5mg of desloratadine, no effects on standard measures of flight performance were observed.
Human Pharmacokinetics
Protein Binding: The in vitro protein binding of desloratadine to human plasma protein was determined by ultrafiltration and ranges between 82.8% to 87.2% over the concentration range of 5 to 400 ng/mL. For this degree of protein binding (free fraction 13%), interactions involving displacement are not known to be clinically important.
Effect of Food: In a single dose crossover trial using AERIUS DUAL ACTION 24 HOUR, there was no significant effect of food on the disposition of DL or PSE.
In another study, grapefruit juice had no effect on the disposition of desloratadine.
Drug-Drug Interactions: No drug interaction studies have been conducted with AERIUS DUAL ACTION 24 HOUR. Two randomized, two-way crossover, third-party blind, multiple dose (10 days), placebo-controlled studies characterized the effect of CYP3A4 inhibitors ketoconazole (N=24) and erythromycin (N=24) on the pharmacokinetics and cardiovascular safety of AERIUS (desloratadine 5 mg).
A third study (N=90) with similar design, except comparing parallel groups, investigated the effect of azithromycin, an azilide antibiotic that also inhibits CYP3A4, on the pharmacokinetics and cardiovascular pharmacodynamics of AERIUS (desloratadine 5 mg).
Two additional randomized, multiple dose, parallel group studies investigated the effect of cimetidine (N=36) and fluoxetine (N=54) on the pharmacokinetics and cardiovascular pharmacodynamics of AERIUS (desloratadine 5 mg).
Ketoconazole co-administered with desloratadine increased Cmax and AUC values for desloratadine by 29% and 21%, respectively, and 3-hydroxy desloratadine Cmax and AUC values by 77% and 110%, respectively. Erythromycin increased Cmax and AUC values for desloratadine by 24% and 14%, respectively. The increases were 43% and 40%, respectively, for 3-hydroxy desloratadine. Azithromycin co-administered with desloratadine increased the Cmax and AUC values for desloratadine by 15% and 5%, respectively. The increases were 15% and 4%, respectively, for 3-hydroxy desloratadine. Throughout these studies, there was no evidence of change in the safety profile of desloratadine, therefore the increases in plasma concentrations are not considered to be clinically relevant. Ketoconazole induced a small increase in the plasma desloratadine concentrations compared with those reported for loratadine. These data suggest that desloratadine has a reduced potential for interacting with inhibitors of CYP3A4. The similarity of the erythromycin concentrations from this study to previous studies suggests that desloratadine is unlikely to inhibit the metabolism of substrates of CYP3A4, which comprise at least 50% of drugs currently marketed. Fluoxetine co-administered with desloratadine resulted in no change in the AUC of desloratadine and an increase of 15% in the Cmax of desloratadine. The Cmax and AUC for 3-hydroxy desloratadine were increased by 17% and 13% respectively. Cimetidine co-administered with desloratadine increased Cmax and AUC values by 12% and 19% respectively and the Cmax and AUC of 3-hydroxy desloratadine were reduced by 11.2% and 2.8% respectively.
Serial ECG measurements showed no statistically significant or clinically relevant changes in QTc intervals. Mean changes in QTc were 5.4 msec and 2.3 msec for ketoconazole/desloratadine and desloratadine/placebo, respectively (p=0.14; LCI = -7.3; UCI= 11). Mean changes in QTc were 9.8 msec and 7.8 msec for erythromycin/desloratadine and desloratadine/placebo, respectively (p=0.53; LCI = -8.4; UCI = 4.5). Mean changes in QTc were -4.2 msec and -6.3 msec for desloratadine/Azithromycin and desloratadine/placebo, respectively (p = 0.61).
MICROBIOLOGY
Not applicable.
TOXICOLOGY
Non-clinical toxicology studies of desloratadine in combination with pseudoephedrine sulfate have not been conducted. Since animals and humans are exposed to desloratadine through metabolism of loratadine, studies conducted with loratadine/pseudoephedrine also support the nonclinical drug safety profile of desloratadine/pseudoephedrine.
Loratadine/Pseudoephedrine Acute toxicity
In acute and single-dose studies, loratadine/ pseudoephedrine sulfate tablets exhibited a low order of toxicity. Acute oral LD50 values ranged from approximately 600 mg/kg in mice to about 2000 mg/kg in rats. Cynomolgus monkeys tolerated single doses up to 240 mg/kg.
Loratadine/pseudoephedrine sulfate tablets were no more toxic than either their individual components, and observed effects were generally related to the pseudoephedrine component.
Loratadine/Pseudoephedrine Repeat dose toxicity
Loratadine/pseudoephedrine sulfate tablets were administered orally for 3 months to rats and monkeys. Loratadine/pseudoephedrine tablets were well tolerated in rats at doses up to 200 mg/kg/day, which is 40 times the proposed maximum clinical dose. In monkeys, daily doses up to 50 mg/kg/day were also well tolerated. Severe toxicity was observed in monkeys at a dose of 125 mg/kg/day and was attributed to the effects of the pseudoephedrine component.
Desloratadine - Acute Toxicity
The acute oral (gavage) and intraperitoneal toxicity of desloratadine was evaluated in six week old Sprague-Dawley rats and CD-1 mice. Estimated oral and intraperitoneal LD50 values in both rats and mice were significant multiples of a human dose of 5.0 mg desloratadine/day. Oral LD50 values were 3530 and ≥ 5490 times the daily human dose in mice and rats respectively. Intraperitoneal LD50 values were ≥ 460 and ≥ 680 times a daily human dose in mice and rats, respectively.
In an oral (gavage) rising-dose tolerance study in young adult cynomolgus monkeys, emesis was observed at doses ≥ 23.5 and ≥ 93.75 mg/kg in males and females, respectively. Emesis occurred approximately 15 minutes after and/or up to three hours post dose. The maximum dose that did not produce emesis in male monkeys (11.75 mg/kg) still represents an 118-fold multiple of the human dose (0.10 mg desloratadine/kg/day), and an 92-fold monkey-to-human systemic exposure multiple compared to an arithmetic mean Cmax value of 4.0 ng/mL in humans following a 5.0 mg/day dose of desloratadine.
Desloratadine - Repeated-Dose Toxicity
Two-week, one-month and three-month desloratadine studies were conducted in rats at doses of up to 240 mg/kg for an initial pilot two-week study, up to 8 mg/kg for the second two-week study and up to 120 mg/kg for one- and three-months. Desloratadine systemic exposure at 60 mg/kg is similar to that achieved with a 120 mg/kg dose of loratadine. The no-effect level for the three-month study was ≥ 3 mg/kg (low-dose) but less than 30 mg/kg. Mortality was observed in the 30, 60 and 120 mg/kg dose groups and in the comparative control (120 mg loratadine/kg) dose group in the three-month study. Fecal changes were observed and were considered related to the anticholinergic effect of this class of compounds. Clinical pathology changes occurred at desloratadine doses ≥ 30 mg/kg (systemic exposure multiple of at least 458 times). The findings associated with target organs/tissues consisted mainly of vacuolation corresponding to phospholipidosis. Phospholipidosis is a common finding of amphiphilic compounds like desloratadine and loratadine. Centrilobular hepatocyte hypertrophy occurred at desloratadine doses of ≥ 30 mg/kg and at 120 mg/kg of loratadine. There was no evidence of phospholipidosis at the 3 mg/kg dose.
Renal tubular cell necrosis and/or renal tubular dilatation were observed at desloratadine doses ≥ 60 mg/kg (systemic exposure multiple of at least 605 times) or at a loratadine dose of 120 mg/kg (desloratadine systemic exposure multiple of at least 663 times).
Renal tubular casts were seen in males given either 60 mg/kg of desloratadine or 120 mg/kg of loratadine. Myofiber degeneration, muscle fibrosis and/or mononuclear infiltrates in muscle occurred at desloratadine doses of ≥ 60 mg/kg and at 120 mg/kg of loratadine. Luminal cellular debris was seen in the seminiferous tubules of the testes at a desloratadine dose of 60 mg/kg and at 120 mg/kg dose of loratadine.
Hypospermatogenesis occurred in the testes of one or more males given 120 mg loratadine/kg or desloratadine doses ≥ 30 mg/kg. Luminal cellular debris was present in the epididymides of the loratadine-dosed males and in the desloratadine-dosed males at doses ≥ 30 mg/kg. Oligospermia was also seen in the epididymides of one male given 30 mg/kg of desloratadine, in one male given 60 mg/kg of desloratadine, and in some males given 120 mg/kg of desloratadine or loratadine. However, there were no testicular changes observed in the one-month study at doses up to 120 mg/kg. Furthermore, these testicular-related changes were consistent with those previously observed with loratadine at doses as low as 2 mg loratadine/kg in rats but with a loratadine no effect dose of 1 mg loratadine/kg for similar findings after one year of dosing. This effect on rat testes has been reported with other antihistamines. With loratadine and desloratadine, this effect is only observed in rats. In the three-month study, granulosa cell necrosis was seen in the ovaries of many females given 120 mg/kg of desloratadine and in some females given 120 mg/kg of loratadine. Uterine immaturity occurred in some females given 60 mg/kg of desloratadine and in many females given 120 mg/kg of desloratadine or loratadine.
A seven-day, a two-week, two one-month and a three-month study were conducted in monkeys with desloratadine. Desloratadine doses of up to 12 mg/kg (systemic exposure multiple of at least 182 times) were well tolerated for up to three-months of dosing and was the no-effect dose in the one-month studies. 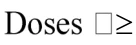 ≥ 36 mg/kg (systemic exposure multiple of at least 842 times) in the repeat one-month study caused emesis.
In the three-month study, the high dose of 18 mg/kg of desloratadine was increased to 24 mg/kg and the loratadine dose was increased from 22 mg/kg to 72 mg/kg on Day 36. Clinical signs, including few or no feces, extended abdomen, hunched posture and/or lethargy, at the 18/24 mg/kg of desloratadine (systemic exposure multiple of at least 953 times) and 22/72 mg/kg of loratadine (desloratadine systemic exposure multiple of at least 1147 times) doses were attributed to the anticholinergic effects of this class of compounds. Decreases in serum cholesterol and alkaline phosphatase were noted in the 18/24 mg/kg desloratadine group and in the 22/72 mg/kg loratadine group. Evaluation of histopathologic findings from the desloratadine 18/24 mg/kg dose group suggests that this dose produces phospholipidosis similar to that produced by the 22/72 mg/kg loratadine dose. There was no evidence of phospholipidosis following desloratadine doses of 6 mg/kg. There were no testicular changes observed in monkeys dosed for three months at doses up to 18/24 mg desloratadine/kg or 22/72 mg loratadine/kg. In this three-month study, the only effects observed at the 12 mg/kg dose of desloratadine were vacuolation in the salivary glands and lungs. A dose of 6 mg/kg (systemic exposure multiple 204 times) was the no-effect dose.
The toxicity studies demonstrate adequate exposure multiples at the no-effect levels and ensure an acceptable safety profile for desloratadine.
Teratogenicity, Mutagenicity and Carcinogenicity
Since animals and humans are exposed to desloratadine through metabolism of loratadine, carcinogenicity studies conducted with desloratadine and loratadine/pseudoephedrine assessed the teratogenic, mutagenic and carcinogenic risk of desloratadine/pseudoephedrine.
Loradatadine carcinogencity
Studies in mice and rats demonstrated that carcinogenicity findings were not considered relevant to humans taking recommended therapeutic doses of either loratadine or desloratadine. The carcinogenic potential of desloratadine was assessed using a loratadine study in rats and a desloratadine study in mice. In a 2-year study in rats, loratadine was administered in the diet at doses up to 25 mg/kg/day (estimated desloratadine and desloratadine metabolite exposures were approximately 30 times the AUC in humans at the recommended daily oral dose). A significantly higher incidence of hepatocellular tumors (combined adenomas and carcinomas) was observed in males given 10 mg/kg/day of loratadine and in males and females given 25 mg/kg/day of loratadine. The estimated desloratadine and desloratadine metabolite exposures in rats given 10 mg/kg of loratadine were approximately 7 times the AUC in humans at the recommended daily oral dose.
Desloratadine carcinogenicity
In a 2-year dietary study in mice, males and females given up to 16 mg/kg/day and 32 mg/kg/day desloratadine, respectively, did not show significant increases in the incidence of any tumors. The estimated desloratadine and metabolite exposures in mice at these doses were 12 and 27 times, respectively, the AUC in humans at the recommended daily oral dose.
Desloratadine mutagenicity
In mutagenicity studies with desloratadine, there was no evidence of mutagenic potential in a reverse point mutation assay (Salmonella/E. coli mammalian microsome bacterial mutagenicity assay) or in two assays for chromosomal aberrations (human peripheral blood lymphocyte clastogenicity assay and mouse bone marrow micronucleus assay).
Desloratadine genotoxicity
In genotoxicity studies with desloratadine, there was no evidence of genotoxic potential in a reverse mutation assay (Salmonella/E. coli mammalian microsome bacterial mutagenicity assay) or in two assays for chromosomal aberrations (human peripheral blood lymphocyte clastogenicity assay and mouse bone marrow micronucleus assay). There was no effect on female fertility in rats at doses up to 24 mg/kg/day (estimated desloratadine and desloratadine metabolite exposures were approximately 130 times the AUC in humans at the recommended daily oral dose.)
Likewise, pseudoephedrine sulfate is not considered to be carcinogenic, mutagenic or teratogenic.
Desloratadine Reproductive Toxicology
Desloratadine was not teratogenic in animal studies. There was no effect on female fertility at doses up to 24 mg/kg/day which produced systemic exposure levels in female rats which were at least 506 times those in humans given the highest recommended clinical dose of desloratadine. In a separate study, decreased fertility in male rats was shown by lower female conception rates associated with decreases in sperm numbers and motility and histopathologic testicular changes, which occurred at an oral dose of desloratadine of 12 mg/kg (systemic exposure approximately 175 times higher than in humans given the maximum recommended dose of desloratadine). Although there was no overall effect on mean sperm motility or concentration, a few rats given desloratadine at a dose of 3 mg/kg/day appeared to have testicular findings consistent with those observed previously with loratadine, which had a no effect dose of 1 mg/kg/day for similar findings after one year of administration. There was no effect on fertility at 3 mg/kg/day, which produced plasma levels (AUC) in rats that were 34 times higher than in humans receiving the maximum clinical dose of desloratadine. This effect on rat testes has been reported with other antihistamines but as with desloratadine and loratadine, this effect is not observed in other laboratory animal species and appears to be unique to the rat.
Loratadine/pseudoephedrine teratogencity
Loratadine/pseudoephedrine sulfate tablets were not teratogenic when administered orally to rats and rabbits during the period of organogenesis. The course of pregnancy of embryo/fetal viability of rats was not affected at doses up to 150 mg/kg/day (30 times the proposed clinical dose). Loratadine/pseudoephedrine sulfate tablets did not directly affect the embryo/fetal viability or offspring development of rabbits at doses up to 120 mg/kg/day.
REFERENCES
- 1. Data on File: Efficacy and safety of two formulations of SCH 483 5/240 mg compared to desloratadine 5 mg and pseudoephedrine 240 mg QD sustained release in the treatment of subjects with seasonal allergic rhinitis (study report for Protocol No. P01875). Kenilworth (NJ): Schering-Plough Research Institute; 2001 Dec.
- 2. Data on File: Efficacy and safety of two formulations of SCH 483 5/240 mg compared to desloratadine 5 mg and pseudoephedrine 240 mg QD sustained release in the treatment of subjects with seasonal allergic rhinitis (study report for Protocol No. P01884). Kenilworth (NJ): Schering-Plough Research Institute; 2000 Jun.
- 3. AERIUS®, AERIUS® SYRUP, and AERIUS KIDS® Product Monograph; October 14, 2010: Schering-Plough Canada Inc.
- 4. CLARITIN® ALLERGY + SINUS EXTRA STRENGTH Product Monograph; December 13, 2004: Schering Canada Inc.
- 5. AERIUS® DUAL ACTION 12 HOUR™ Product Monograph; June 03, 2009: Schering-Plough Canada Inc.
- 6. Torkildsen G. L, Gomesw P., Welchw D, Gopalanz G and Srinivasanz S. Evaluation of desloratadine on conjunctival allergen challenge-induced ocular symptoms. Clinical and Experimental Allergy, 1-8; 2009.